


Product Monograph - AA-Atenidone
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 01/2023 |
|---|---|
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 08/2024 |
| 7 WARNINGS AND PRECAUTIONS | 08/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women | 05/2023 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.2 Breast-feeding | 05/2023 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics | 08/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.5 Ethnic Origin | 08/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics ................................................................................................................. 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.4 Administration ......................................................................................................... 6
4.5 Missed Dose ............................................................................................................ 6
5 OVERDOSAGE ............................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 7
7 WARNINGS AND PRECAUTIONS ................................................................................... 8
7.1 Special Populations................................................................................................ 14
7.1.1 Pregnant Women ............................................................................................... 14
7.1.2 Breast-feeding ................................................................................................... 15
7.1.3 Pediatrics ........................................................................................................... 15
7.1.4 Geriatrics ........................................................................................................... 15
7.1.5 Ethnic Origin ...................................................................................................... 16
8 ADVERSE REACTIONS ................................................................................................. 16
8.1 Adverse Reaction Overview ................................................................................... 16
8.2 Clinical Trial Adverse Reactions ............................................................................. 18
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 18
8.5 Post-Market Adverse Reactions ............................................................................ 19
9 DRUG INTERACTIONS ................................................................................................. 20
9.3 Drug-Behavioural Interactions ............................................................................... 20
9.4 Drug-Drug Interactions .......................................................................................... 20
9.5 Drug-Food Interactions .......................................................................................... 27
9.6 Drug-Herb Interactions .......................................................................................... 27
9.7 Drug-Laboratory Test Interactions ......................................................................... 27
10 CLINICAL PHARMACOLOGY ........................................................................................ 27
10.1 Mechanism of Action ......................................................................................... 27
10.2 Pharmacodynamics ............................................................................................ 28
10.3 Pharmacokinetics ............................................................................................... 29
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 31
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 31
PART II: SCIENTIFIC INFORMATION ........................................................................................ 32
13 PHARMACEUTICAL INFORMATION ............................................................................. 32
14 CLINICAL TRIALS ......................................................................................................... 33
14.2 Comparative Bioavailability Studies ................................................................... 33
15 MICROBIOLOGY ......................................................................................................... 35
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 35
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 39
PATIENT MEDICATION INFORMATION ................................................................................... 40
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
AA-ATENIDONE (atenolol and chlorthalidone tablets) is indicated for:
- Treatment of hypertension for patients for whom combination therapy with atenolol and chlorthalidone is required.
This fixed combination is not indicated for initial therapy of hypertension. See 4.2 Recommended Dose and Dosage Adjustment.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of AA-ATENIDONE in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 7.1.3 Pediatrics.
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. See 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
AA-ATENIDONE (atenolol and chlorthalidone) is contraindicated in patients:
- Who are hypersensitivity to atenolol, chlorthalidone or to other sulfonamide-derivatives or to any ingredient in the formulation, including any non-medical ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- With sinus bradycardia, or bradycardia of other origin
- With second and third degree A-V block
- With of sick sinus syndrome
- With right ventricular failure secondary to pulmonary hypertension
- With uncontrolled heart failure
- With cardiogenic shock
- With hypotension
- With severe peripheral arterial disorders
- With anesthesia with agents that produce myocardial depression
- With pheochromocytoma, in the absence of alpha-blockade
- With metabolic acidosis
- Patients with anuria, severe renal failure (creatinine clearance lower than 30 mL/min), severe hepatic failure, refractory hypokalemia or conditions involving enhanced potassium loss, hyponatremia, hypercalcemia, hyperuricemia (history of gout or uric acid calculi), untreated Addison’s Disease and concomitant lithium therapy.
- Pregnancy. See 7.1.1 Pregnant Women
- Breastfeeding. See 7.1.2 Breastfeeding
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Abrupt Cessation of Therapy with AA-ATENIDONE Patients with angina should be warned against abrupt discontinuation of AA-ATENIDONE. There have been reports of severe exacerbation of angina and of myocardial infarction or ventricular arrhythmias occurring in patients with angina pectoris, following abrupt discontinuation of beta-blocker therapy. The last two complications may occur with or without preceding exacerbation of angina pectoris. Therefore, when discontinuation of AA-ATENIDONE is planned in patients with angina pectoris, the drug should be stopped and immediately replaced with atenolol and a diuretic given separately, so that the dose of atenolol may be gradually reduced over a period of about two weeks while the dose of diuretic is maintained. The same frequency of administration of both drugs should be maintained. The patients should be carefully observed and advised to limit physical activity to a minimum. In situations of greater urgency, AA-ATENIDONE should be discontinued stepwise over a shorter time and under closer observation. If angina markedly worsens or acute coronary insufficiency develops, it is recommended that treatment with AA-ATENIDONE be reinstituted promptly, at least temporarily. |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Dosage must be determined for individual patients by titration of each component separately. Where the fixed combination in AA-ATENIDONE (atenolol/chlorthalidone) supplies the dosage so determined, the combination product may be used for maintenance therapy.
- For further adjustment of dosage, however, it is best to use the individual drugs again. The treatment of hypertension is not static, but must be re-evaluated as conditions in each patient warrant.
4.2 Recommended Dose and Dosage Adjustment
One AA-ATENIDONE tablet once daily can be used to administer up to 100 mg of atenolol and
25 mg of chlorthalidone.
If further lowering of the blood pressure is required, another antihypertensive agent may be added to the regimen.
In patients with renal impairment, the dose of the components should be carefully individualized. Recommendations for dosage adjustments for atenolol and chlorthalidone in renal disease are found in the Atenolol prescribing information and Chlorthalidone prescribing information.
If dosage adjustment is necessary during maintenance therapy, it is advisable to use the individual drugs.
Pediatrics
Health Canada has not authorized an indication for pediatric use. See 7.1.3 Pediatrics.
4.4 Administration
AA-ATENIDONE tablets should be taken whole with a glass of water at the same time each day.
4.5 Missed Dose
If the patient misses a dose, inform the patient to skip the missed dose and take the next dose at the regular dosing schedule. Do not double dose.
5 OVERDOSAGE
Limited information is available with regard to overdosage with AA-ATENIDONE in humans.
Atenolol: Overdosage with atenolol has been reported with patients surviving acute doses as high as 5 g. One death was reported in a man who may have taken as much as 10 g acutely.
The predominant symptoms reported following atenolol overdosage are lethargy, disorder of respiratory drive, wheezing, sinus pause, and bradycardia. Additionally, common effects associated with overdosage of any beta-adrenergic blocking agent are congestive heart failure, hypotension, bronchospasm, and/or hypoglycemia.
Treatment should be symptomatic and supportive and directed to the removal of any unabsorbed drug by induced emesis, or administration of activated charcoal. Atenolol can be removed from the general circulation by hemodialysis. Further consideration should be given to dehydration, electrolyte imbalance and hypotension by established procedures.
Other treatment modalities should be employed at the physician’s discretion and may include:
BRADYCARDIA: Atropine 1 to 2 mg intravenously. If there is no response to vagal blockade, give isoproterenol cautiously. In refractory cases, a transvenous cardiac pacemaker may be indicated. Glucagon in a 10 mg intravenous bolus has been reported to be useful. If required, this may be repeated or followed by an intravenous infusion of glucagon 1 to 10 mg/h depending on response. If no response to glucagon occurs or if glucagon is unavailable, a beta- adrenoceptor stimulant such as dobutamine 2.5 to 10 mcg/kg/minute by intravenous infusion or isoproterenol 10 to 25 mcg given as an infusion at a rate not exceeding 5 mcg/minute may be given, although larger doses may be required.
HEART BLOCK: (second or third degree) lsoproterenol, transvenous pacemaker.
CONGESTIVE HEART FAILURE: Digitalize the patient and administer a diuretic.
Glucagon has been reported to be useful.
HYPOTENSION: Vasopressors such as dopamine or norepinephrine.
Monitor blood pressure continuously.
BRONCHOSPASM: A beta2-stimulant such as isoproterenol or terbutaline and/or intravenous aminophylline.
HYPOGLYCEMIA: Intravenous glucose.
ELECTROLYTE DISTURBANCE: Monitor electrolyte levels and renal function.
Institute measures to maintain hydration and electrolytes.
Based on the severity of symptoms, management may require intensive support care and facilities for applying cardiac and respiratory support.
Chlorthalidone: Symptoms of chlorthalidone overdose include nausea, weakness, dizziness, somnolence, hypovolemia, hypotension and electrolyte disturbances associated with cardiac arrhythmias and muscle spasm.
Treatment: There is no specific antidote. To reduce absorption, induce vomiting or gastric lavage and administer activated charcoal. Intravenous dextrose-saline and potassium chloride may be given, if necessary, with due caution.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
AA-ATENIDONE 50/25 tablets: white, round, biconvex tablets. Scored and engraved “50” over “25” on one side and engraved “APO” on the other. Available in bottles of 100 tablets.
AA-ATENIDONE 100/25 tablets: white, round, biconvex tablets. Scored and engraved “100” over “25” on one side and engraved “APO” on the other. Available in bottles of 100 tablets.
7 WARNINGS AND PRECAUTIONS
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity.
Cardiovascular
A cautious dosage schedule of chlorthalidone should be adopted in patients with severe coronary arteriosclerosis.
Concomitant administration of chlorthalidone and digitalis requires caution. Electrolytes and digitalis levels should be monitored closely. Adjustment of digitalis/chlorthalidone dosing or provision of supplemental potassium may be required. Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digitalis toxicity, which may lead to fatal arrhythmic events.
Cardiac Failure
Special caution should be exercised when administering AA-ATENIDONE (atenolol and chlorthalidone) to patients with a history of heart failure. Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure and inhibition with beta blockade always carries the potential hazard of further depressing myocardial contractility and precipitating cardiac failure. Atenolol acts selectively without abolishing the inotropic action of digitalis on the heart muscle. However, the positive inotropic action of digitalis may be reduced by the negative inotropic effect of atenolol when the two drugs are used concomitantly. The effects of beta-blockers and digitalis are additive in depressing A-V conduction. In patients without a history of cardiac failure, continued depression of the myocardium with beta-
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet 50/25 contains 50 mg atenolol and 25 mg chlorthalidone, 100/25 contains 100 mg atenolol and 25 mg chlorthalidone | Colloidal silicon dioxide, crospovidone, magnesium stearate, microcrystalline cellulose. |
blocking agents over a period of time can, in some cases, lead to cardiac failure. Therefore, at the first sign or symptom of impending cardiac failure, patients should be fully digitalised and/or given additional diuretic and the response observed closely. If cardiac failure continues, despite adequate digitalisation, AA-ATENIDONE should be immediately withdrawn and diuretic therapy maintained (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
First Degree Heart Block
Due to atenolol’s negative effect on A-V conduction time, AA-ATENIDONE should be used with caution in patients with first degree block.
Peripheral Arterial Circulatory Disorders
The atenolol component of AA-ATENIDONE may aggravate less severe peripheral arterial circulatory disorders. See 2 CONTRAINDICATIONS.
Prinzmetal’s Angina
Atenolol may increase the number and duration of angina attacks in patients with Prinzmetal’s angina due to unopposed alpha-receptor mediated coronary artery vasoconstriction. AA-ATENIDONE therefore, should only be used in these patients with the utmost care.
Sinus Bradycardia
Severe sinus bradycardia may occur with the use of atenolol from unopposed vagal activity remaining after blockade of beta1-adrenergic receptors; in such cases, the dosage should be reduced.
Driving and Operating Machinery
Occupational hazards: Because dizziness and impaired patient reaction time are possible side effects of chlorthalidone, especially at the start of therapy, patients should be warned about the possible hazards of operating machines or driving motor vehicles.
Endocrine and Metabolism
Thyrotoxicosis: In patients with thyrotoxicosis, possible deleterious effects from long-term use of atenolol have not been adequately appraised. Beta blockade may mask the clinical signs of continuing hyperthyroidism or its complications and give a false impression of improvement. Therefore, abrupt withdrawal of atenolol may be followed by an exacerbation of the symptoms of hyperthyroidism, including thyroid storm. Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Diabetes and Patients Subject to Hypoglycemia: AA-ATENIDONE should be administered with caution to patients subject to spontaneous hypoglycemia, or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic receptor blocking agents may mask the premonitory signs (e.g., tachycardia) and symptoms of acute hypoglycemia. Insulin requirements in diabetic patients may be increased, decreased, or unchanged by chlorthalidone. Diabetes mellitus which has been latent may become manifest during chlorthalidone administration. Chlorthalidone should not be used as a first-line drug for long-term treatment in patients with overt diabetes mellitus, chlorthalidone may impair glucose tolerance. Increases in serum glucose may occur. Close monitoring of glycemia is recommended in the initial phase of therapy and in prolonged therapy, tests for glucosuria should be carried out at regular intervals.
AA-ATENIDONE should be used with caution in patients with spontaneous hypoglycemia, or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic blockers may mask the premonitory signs (e.g., tachycardia) and symptoms of acute hypoglycemia. See 2 CONTRAINDICATIONS.
Hyperuricemia: Hyperuricemia may occur or acute gout may be precipitated in certain patients receiving chlorthalidone. Chlorthalidone may raise the serum uric acid level, but attacks of gout (in predisposed patients) are rarely observed during chronic treatment. In cases where prolonged and significant elevation of blood uric acid concentrations is considered potentially deleterious, concomitant use of a uricosuric agent is effective in reversing hyperuricemia without loss of diuretic and/or antihypertensive activity.
Hypercholesterolemia: Small and partially reversible increases in plasma concentrations of total cholesterol, triglycerides, or low-density lipoprotein cholesterol were reported in patients during long-term treatment with thiazides and thiazide-like diuretics. The clinical relevance of these findings is equivocal. Chlorthalidone should not be used as a first-line drug for long-term treatment in patients with hypercholesterolemia. If chlorthalidone must be used, serum lipids should be regularly monitored. If there is a rise in lipid levels, withdrawal of chlorthalidone should be considered.
Pathological changes in the parathyroid glands, with hypercalcemia and hypophosphatemia, have been observed in a few patients on prolonged thiazide therapy. The common complications of hyperparathyroidism such as renal lithiasis, bone resorption, and peptic ulceration have not been seen. Discontinue thiazides and their analogues before carrying out tests for parathyroid function.
Hepatic/Biliary/Pancreatic
Impaired Hepatic Function: In patients with impaired hepatic function or progressive liver disease, caution should be exercised since even minor alterations in fluid and electrolyte balance or of serum ammonia may precipitate hepatic coma. Hepatic encephalopathy, manifested by tremors, confusion and coma, has been reported in association with diuretic therapy, including chlorthalidone.
Immune
Systemic Lupus Erythmatosus: The possibility of exacerbation or activation of systemic lupus erythematosus has been reported with thiazide diuretics, which are structurally related to chlorthalidone. However, systemic lupus erythematosus has not been reported following chlorthalidone administration.
Anaphylaxis - Epinephrine and Beta-Blockers: There may be increased difficulty in treating an allergic type reaction in patients on beta-blockers. In these patients, the reaction may be more severe due to pharmacological effects of beta- blockers and problems with fluid changes. Epinephrine should be administered with caution since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other, these doses can be associated with excessive alpha adrenergic stimulation with consequent hypertension, reflex bradycardia and heart block and possible potentiation of brochospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids and the use of beta agonists including parenteral salbutamol or isoproterenol to overcome bronchospasm, and norepinephrine to overcome hypotension.
Monitoring and Laboratory Tests
Fluid status and Serum Electrolytes: Patients receiving chlorthalidone and their analogues should be carefully observed for clinical signs of fluid and electrolyte imbalance. As chlorthalidone is a diuretic, an inappropriately high dose can cause severe volume depletion. Serum sodium, potassium, chloride, and calcium levels should be checked periodically to detect possible electrolyte disturbances. Warning signs or symptoms of fluid and electrolyte imbalance include dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, cardiac arrhythmias or corresponding ECG changes and gastrointestinal disturbances such as nausea and vomiting.
Close monitoring of fluid status and serum electrolytes is indicated particularly in older patients, in patients receiving digitalis preparations for cardiac failure, those taking an abnormal (low in potassium) diet in patients suffering from gastrointestinal complaints, vomiting excessively or receiving parenteral fluids, patients with ascites due to liver cirrhosis, and in patients with edema due to nephrotic syndrome. For the latter condition, chlorthalidone should be used only under close control in normokalemic patients with no signs of volume depletion or severe hypoalbuminemia.
Hypokalemia may develop, especially with brisk diuresis, when severe cirrhosis is present, or during concomitant use of corticosteroids or ACTH. Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g., increased ventricular irritability). Hypokalemia may be avoided or treated by use of potassium supplements, potassium-sparing agents or foods with a high potassium content.
As with thiazide diuretics, kaluresis induced by chlorthalidone is dose dependent, and there is inter-individual variability in magnitude. With chlorthalidone dosing at 25 mg/day, serum potassium concentration decreases an average of 0.5 mmol/L. If chronic treatment with chlorthalidone is contemplated, serum potassium concentrations should be determined initially, and then 3 to 4 weeks later. If, thereafter, potassium balance is not disturbed further, concentrations should be assessed every 4 to 6 months. Conditions that may alter potassium balance (especially in the presence of brisk diuresis) include: vomiting, diarrhea, malnutrition, change in renal function (e.g., nephrosis), liver cirrhosis, hyperaldosteronism, or concomitant use of corticosteroids or ACTH.
Titrated co-administration of an oral potassium salt (e.g., KCl) may be considered in patients: receiving digitalis; exhibiting signs of coronary heart disease (unless they are also receiving an ACE inhibitor); on high doses of a beta-adrenergic agonist; whose plasma potassium concentrations are less than 3.0 mmol/L. Combined treatment consisting of chlorthalidone and a potassium salt or a potassium-sparing diuretic must be avoided in patients also receiving ACE inhibitors. See 9.4 Drug-Drug Interactions, ACE Inhibitors.
If oral potassium preparations are not tolerated, chlorthalidone may be combined with a potassium-sparing diuretic (e.g., triamterene).
Excessively strict low-salt diets should be avoided. Hyponatremia, accompanied by neurological symptoms (nausea, debility, progressive disorientation, apathy), has been observed in isolated cases.
Should hypochloremic alkalosis or hyponatremia occur, consider appropriate therapy. Water restriction rather than actual salt replacement may be considered appropriate treatment of any chloride deficit except in rare instances when hyponatremia is life threatening, then appropriate salt replacement is the therapy of choice.
Magnesium levels: Patients receiving relatively high doses of thiazides or their analogues may develop hypomagnesemia accompanied by such signs and symptoms as nervousness, muscle spasm, and cardiac arrhythmias.
Any chloride deficit during chlorthalidone therapy is generally mild and usually does not require specific treatment except under extraordinary circumstances (as in liver disease or renal disease). Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction rather than administration of salt except in rare instances when the hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Because calcium excretion is decreased by chlorthalidone, AA-ATENIDONE should be discontinued before carrying out tests for parathyroid function. Pathologic changes in the parathyroid glands, with hypercalcemia and hypophosphatemia, have been observed in a few patients on prolonged thiazide therapy; however, the common complications of hyperparathyroidism such as renal lithiasis, bone resorption and peptic ulceration have not been seen.
Serum glucose levels may increase with chronic use.
Thiazides may decrease protein bound iodine levels without signs of thyroid disturbance.
Neurologic
A cautions dosage schedule of chlorthalidone should be adopted in patients with severe cerebral arteriosclerosis.
Ophthalmologic
Choroidal effusion, acute myopia and secondary angle-closure glaucoma related to chlorthalidone: Chlorthalidone, a thiazide-like diuretic, can cause an idiosyncratic reaction, resulting in choroidal effusion, acute transient myopia and acute angle-closure glaucoma.
Symptoms include acute onset of decreased visual acuity, blurred vision or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue “AA-ATENIDONE” as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulphonamide or penicillin allergy.
Peri-Operative Considerations
Elective or Emergency Surgery: It is not advisable to withdraw beta-adrenoceptor blocking drugs prior to surgery in the majority of patients. However, care should be taken when using AA-ATENIDONE with anaesthetic agents such as those which may depress the myocardium. Vagal dominance, if it occurs, may be corrected with atropine (1 to 2 mg i.v.).
Some patients receiving beta-adrenergic blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported.
In emergency surgery, since atenolol is a competitive inhibitor of beta-adrenergic receptor agonists, its effects may be reversed, if necessary, by sufficient doses of such agonists as isoproterenol or norepinephrine.
Post-Sympathectomy Patients: Treatment with thiazide diuretics should be initiated cautiously in postsympathectomy patients since the antihypertensive effects may be enhanced.
Renal
Impaired Renal Function: AA-ATENIDONE should be used with caution since chlorthalidone may precipitate or increase azotemia. Because of the possibility of progression of renal damage, periodic determination of the BUN and serum creatinine are indicated. Should there be an elevation of either parameter, treatment should be discontinued. Like thiazides, chlorthalidone may lose its diuretic efficacy when glomerular filtration rate drops below 30 mL/min, a point at which treatment with loop diuretics may be more appropriate. Cumulative effects may develop since both components of AA-ATENIDONE are excreted by the kidney. If progressive renal impairment becomes evident, AA-ATENIDONE should be discontinued. See 2 CONTRAINDICATIONS.
Respiratory
Bronchospastic Disorders: Patients with bronchospastic diseases should, in general, not receive beta-blockers. Due to the relative beta1-selectivity of atenolol, atenolol may be used with caution in patients with bronchospastic disease who do not respond to, or cannot tolerate, other antihypertensive treatment. Since beta1-selectivity is not absolute, a beta2-stimulating agent should be administered concomitantly, the lowest possible dose of atenolol should be used. Despite these precautions, the respiratory status of some patients may worsen, and, in such cases, AA-ATENIDONE (atenolol/chlorthalidone) should be withdrawn.
Sensitivity/Resistance
Hypersensitivity Reactions: In patients receiving chlorthalidone, sensitivity reactions may occur with or without a history of allergy or bronchial asthma.
Skin
Oculomucocutaneous Syndrome: Various skin rashes and conjunctival xerosis have been reported with beta blockers, including atenolol. A severe syndrome (oculomucocutaneous syndrome) whose signs include conjunctivitis sicca and psoriasiform rashes, otitis, and sclerosing serositis has occurred with the chronic use of one beta-adrenergic blocking agent (practolol). This syndrome has not been observed with atenolol or any other such agent. However, physicians should be alert to the possibility of such reactions and should discontinue treatment with AA-ATENIDONE in the event that they occur.
Photosensitivity: During treatment with chlortalidone, long-term sun exposure is not recommended, as there is a risk of occurrence of photosensitivity symptoms.
7.1 Special Populations
7.1.1 Pregnant Women
Use of AA-ATENIDONE is contraindicated during pregnancy.
Atenolol can cause fetal harm when administered to a pregnant woman. Atenolol crosses the placental barrier and appears in the cord blood.
No randomised controlled studies have been performed on the use of atenolol in the first trimester and the possibility of fetal injury cannot be excluded. Administration of atenolol, starting in the second trimester of pregnancy, has been associated with the birth of infants that are small for gestational age. In general, β-blockers reduce placental perfusion, which has been associated with growth retardation, intrauterine death, abortion and early labour.
Studies in humans have shown that transplacental passage of atenolol does occur in pregnant women, with fetal drug serum levels equal to those of the mother. In a limited number of patients who were given atenolol during the last trimester of pregnancy, low birth weight, neonatal hypoglycemia, bradycardia in the fetus/newborn, and placental insufficiency were observed.
Neonates born to mothers who are receiving atenolol at parturition or breast-feeding may be at risk for hypoglycemia and bradycardia. Atenolol should not be given during pregnancy or to a woman who is breast-feeding unless its use is essential. (See 7 WARNINGS AND PRECAUTIONS, 7.1.2 Breast- feeding). Atenolol should be used in pregnancy only if the potential benefit justifies the potential risk to the fetus.
Atenolol has been shown to produce a dose-related increase in embryo/fetal resorptions in rats at doses equal to or greater than 50 mg/kg/day or 25 or more times the maximum recommended human dose.
Chlorthalidone, like other diuretics, can cause placental hypoperfusion. Since they do not prevent or alter the course of EPH (edema, proteinuria, hypertension)-gestosis (pre-eclampsia), these drugs must not be used to treat hypertension in pregnant women. Chlorthalidone crosses the placental barrier and appear in cord blood. Levels in fetal whole blood were about 15% of those found in the maternal blood of mothers receiving 50 mg chlorthalidone daily pre- and postpartum. Concentration in amniotic fluid is approximately 4% of maternal blood levels. The use of chlorthalidone during pregnancy may cause fetal or neonatal jaundice, thrombocytopenia and, possibly, other adverse reactions, which have occurred in the adult. See 2 CONTRAINDICATIONS; 10.3 Pharmacokinetics, Special Populations and Conditions, Pregnancy and 10.3 Pharmacokinetics, Special Populations and Conditions, Breast-feeding.
7.1.2 Breast-feeding
AA-ATENIDONE is contraindicated in lactating women.
There is a significant accumulation of atenolol in breast milk.
Neonates born to mothers who are receiving atenolol and are breast-feeding may be at risk for hypoglycemia and bradycardia. If the use of atenolol is considered essential, then mothers should stop nursing.
Thiazide-like diuretics, like chlorthalidone, are excreted in human milk. Because many drugs are excreted in human milk and because of their potential for affecting the nursing infant adversely, use in lactating mothers is contraindicated. A decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother. See 2 CONTRAINDICATIONS and 10.3 Pharmacokinetics, Special Populations and Conditions, Breast-feeding.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The safety of use of AA-ATENIDONE in children has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Clinical studies of atenolol did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic renal, or cardiac function, and concomitant diseases or other drug therapy.
Evidence from chlorthalidone clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness.
7.1.5 Ethnic Origin
Atenolol appears to be effective and well-tolerated in most ethnic populations, although the response may be less in black patients than in Caucasians.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse reactions that have been reported with the individual components are listed below:
The most serious adverse reactions encountered with atenolol are congestive heart failure, A-V block and bronchospasm. Bronchospasm may occur in patients with bronchial asthma or a history of asthmatic complaints. The most common adverse reactions reported in clinical trials with atenolol in 2500 patients are bradycardia (3%), dizziness (3%), vertigo (2%), fatigue (3%), diarrhea (2%) and nausea (3%).
Serious adverse reactions reported with chlorthalidone include cardiac arrhythmia, dyspnea, aplastic anemia and agranulocytosis. Most frequent adverse reactions (≥10%) include hypokalemia, hyperuricemia, and hyperlipidemia.
Chlorthalidone:
The following adverse reactions have been reported:
Blood and lymphatic system disorders:
Rare: Leukopenia, thrombocytopenia and eosinophilia.
Not known: Agranulocytosis, aplastic anemia.
Eye disorders:
Rare: disturbance of vision.
Not known: Choroidal effusion, acute myopia and acute angle-closure glaucoma (Cases of choroidal effusion with visual field defect have been reported after the use of thiazide and thiazide-like diuretics), xanthopsia.
Gastrointestinal disorders:
Common: minor gastrointestinal distress.
Rare: mild nausea, vomiting, diarrhea, constipation, gastric pain.
Very rare: Pancreatitis.
Not known: Gastric irritation, cramping.
General disorders and administration site conditions:
Not known: Weakness.
Hepatobiliary disorders:
Rare: intrahepatic cholestasis or jaundice.
Immune system disorders:
Very rare: Necrotizing angiitis (vasculitis) (cutaneous vasculitis).
Not known: Lyell’s syndrome (toxic epidermal necrolysis).
Investigations:
Common: decrease reaction time.
Metabolism and nutrition disorders:
Common: Anorexia, hypomagnesemia, hyperglycemia, hyponatremia and loss of appetite.
Uncommon: gout.
Rare: hypercalcemia, worsening of diabetic metabolic state.
Very rare: hypochloremic alkalosis.
Not known: Hypokalemia.
Musculoskeletal and connective tissue disorders:
Not known: Muscle spasm.
Nervous system disorders:
Common: Dizziness, slow mentation.
Rare: Paresthesias, headache.
Not known: Vertigo, restlessness
Renal and urinary disorders:
Rare: Glycosuria, allergic interstitial nephritis.
Reproductive system and breast disorders:
Common: Impotence.
Respiratory, thoracic and mediastinal disorders:
Rare: idiosyncratic pulmonary edema (respiratory disorders)
Skin and subcutaneous tissue disorders:
Common: urticaria, and other forms of skin rash.
Rare: Photosensitivity.
Not known: Purpura.
Vascular disorders:
Common: postural hypotension, which may be aggravated by alcohol, anesthetics or sedatives.
Very rare: vasculitis
Potential adverse reactions
The following adverse reactions have occurred with other beta-blockers but have not been reported with atenolol:
Blood and lymphatic system disorders: Agranulocytosis.
Cardiac disorders: Pulmonary edema, cardiac enlargement, and sinus arrest.
Eye disorders: Blurred vision, burning, and grittiness.
Gastrointestinal disorders: Mesenteric arterial thrombosis and ischemic colitis.
Nervous system disorders: Short term memory loss.
Psychiatric disorders: Aggressiveness, anxiety, emotional lability with slightly clouded sensorium.
Respiratory, thoracic, and mediastinal disorders: Laryngospasm, status asthmaticus, and fever combined with aching and sore throat.
Skin and subcutaneous tissue disorders: Exfoliative dermatitis.
Vascular disorders: Hot flushes.
8.2 Clinical Trial Adverse Reactions
No information is available.
8.3 Less Common Clinical Trial Adverse Reactions
Atenolol:
Adverse reactions, occurring with an incidence of less than 1%, grouped by system, are as follows:
Blood and lymphatic system disorders: Thrombocytopenia
Cardiac disorders: Heart failure deterioration (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular) Heart block, Palpitations, Chest pain, Lightheadedness
Eye disorders: Visual disturbances, Ichy and/or dry eyes.
Gastrointestinal disorders: Abdominal discomfort, Indigestion, Constipation.
General disorders and administration site conditions: Edema, Tiredness, Flushes, General body aches, Decreased exercise tolerance.
Investigations: Lengthening of P-R interval.
Metabolism and nutrition disorders: Anorexia.
Musculoskeletal and connective tissue disorders: Leg pain.
Nervous System disorders: Faintness, Ataxia, Drowsiness, Vivid dreams, Paresthesia, Headache, Tinnitus
Psychiatric disorders: Lethargy, Nervousness, Depression, Insomnia, Mood changes, Psychoses and hallucinations
Reproductive system and breast disorders: Impotence, Decreased libido.
Respiratory, thoracic, and mediastinal disorders: Dyspnea, Wheeziness, Cough, Bronchospasm, Epistaxis.
Skin and subcutaneous tissue disorders: Skin rash, Psoriasiform skin reactions, Exacerbation of psoriasis, Alopecia, Sweating, Purpura
Vascular disorders: Postural hypotension which may be associated with syncope, Raynaud’s phenomenon, Intermittent claudication, or worsening of pre-existing intermittent claudication, cold extremities.
8.5 Post-Market Adverse Reactions
During post-marketing experience with atenolol, cold extremeties, gastrointestinal disturbances and fatigue were commonly reported.
In a long-term, well-controlled trial of 1627 elderly patients with systolic hypertension, the incidence of dry mouth was significantly higher in patients taking atenolol (12.2%).
The following have been reported in temporal relationship to the use of the drug:
Blood and lymphatic system disorders: Thrombocytopenia.
Eye disorders: Choroidal effusion, acute myopia, acute angle-closure glaucoma (frequency unknown).
Investigations: Elevated liver enzymes and/or bilirubin.
Nervous system disorders: Headache, confusion.
Psychiatric disorders: Nightmares, impotence.
Reproductive system and breast disorders: Peyronie’s disease.
Skin and subcutaneous tissue disorders: Psoriasiform rash or exacerbation of psoriasis, purpura, reversible alopecia.
The following adverse reactions have occurred with other beta-blockers but have not been reported with atenolol:
Allergic: Laryngospasm, status asthmaticus and fever combined with aching and sore throat
Cardiovascular: Pulmonary edema, cardiac enlargement, hot flushes and sinus arrest
Central Nervous System: Aggressiveness, anxiety, short term memory loss, and emotional lability with slightly clouded sensorium
Dermatological: Exfoliative dermatitis
Gastrointestinal: Mesenteric arterial thrombosis and ischemic colitis
Hematological: Agranulocytosis
Ophthalmological: Blurred vision, burning, and grittiness
Rare cases of hepatic toxicity including intrahepatic cholestasis have been reported. Atenolol, like other beta blockers, has been associated with the development of antinuclear antibodies (ANA) and lupus syndrome.
9 DRUG INTERACTIONS
9.3 Drug-Behavioural Interactions
Consuming alcohol may modify the effect of this product. Limit alcohol consumption during treatment.
Patients should also be cautioned that taking alcohol can increase the chance of dizziness and cause the blood pressure to fall even more.
Orthostatic hypotension may occur when taking CHLORTHALIDONE and may be aggravated by alcohol, anesthetics or sedatives
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions for Atenolol
| Proper/Common name | Effect | Clinical comment |
| Alcohol, Barbiturates or Narcotics | ↑Orthostatic hypotension | Orthostatic hypotension may occur and may be potentiated by alcohol, barbiturates or narcotics. Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Proper/Common name | Effect | Clinical comment |
| Anaesthetic Agents | ↑Hypotensive potential | Anaesthetics can produce a hypotensive state with associated reflex tachycardia. Since beta blockade will inhibit reflex tachycardia, the hypotensive potential of anaesthetic agents is increased with concomitant use of AA-ATENIDONE, thus the anaesthetist should be informed and the choice of anaesthetic should be an agent with as little negative inotropic activity as possible. See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Peri-Operative Considerations. |
| Antiarrhythmic Agents | ↑Atrial-conduction time | Class I anti-arrhythmic drugs (e.g., disopyramide) and amiodarone may have potentiating effect on atrial-conduction time and induce negative inotropic effect. Caution is warranted. |
| Antihypertensive Peripheral Vasodilator | ↓Blood pressure | The combination of AA-ATENIDONE with an antihypertensive peripheral vasodilator produces a greater fall in blood pressure than either drug alone. The same degree of blood pressure control can be achieved by lower than usual doses of each drug. Therefore, when using such concomitant therapy, careful monitoring of the doses is required until the patient is stabilized. |
| Proper/Common name | Effect | Clinical comment |
| Calcium Channel Blockers | ↑Severe hypotension, bradycardia and cardiac failure | Combined use of beta-blockers and calcium channel blockers with negative inotropic effects can lead to prolongation of S-A and A-V conduction, particularly in patients with impaired ventricular function, conduction abnormalities, or diminished cardiac output. This may result in severe hypotension, bradycardia and cardiac failure. Concomitant therapy with dihydropyridines, e.g., nifedipine, may increase the risk of hypotension, and cardiac failure may occur in patients with latent cardiac insufficiency. On rare occasions the concomitant administration of intravenous beta adrenergic blocking agents with intravenous verapamil has resulted in serious adverse effects, especially in patients with severe cardiomyopathy, congestive heart failure or recent myocardial infarction. Caution is warranted. |
| Clonidine | ↑Hypertension | Beta-blockers may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. If the two drugs are co-administered, the beta-blocker should be withdrawn several days before discontinuing clonidine. If replacing clonidine by beta-blocker therapy, the introduction of beta-blockers should be delayed for several days after clonidine administration has stopped. (See prescribing information for clonidine) |
| Digitalis Glycosides | ↑Bradycardia | Digitalis glycosides may potentiate the bradycardia of beta1 blockade. Caution is warranted. |
| Fingolimod | ↑Bradycardic effects | Concomitant use of fingolimod with beta blockers may potentiate bradycardic effects and is not recommended. Where such co-administration is considered necessary, appropriate monitoring at treatment initiation, i.e. at least overnight monitoring, is recommended. |
| Proper/Common name | Effect | Clinical comment |
| Lithium | ↓Renal clearance ↑Lithium toxicity. | Lithium generally should not be given with diuretics because they reduce its renal clearance and add a high risk of lithium toxicity. The Prescribing Information for lithium preparations should be read before use of such preparations with AA-ATENIDONE. |
| Non-Steroidal Anti-Inflammatory Agents | ↓Antihypertensive effects | The concomitant use of non-steroidal anti-inflammatory agents may blunt the antihypertensive effects of beta-blockers. Caution is warranted. |
| Norepinephrine | ↓Norepinephrine | Thiazides may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude the therapeutic effectiveness of the pressor agent in therapy. |
| Reserpine or Guanethidine | ↓Sympathetic activity | Patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, should be closely monitored because the added beta-adrenergic blocking action of atenolol may produce an excessive reduction of sympathetic activity. AA-ATENIDONE should not be combined with other drugs containing beta blockers. |
Table 3 - Established or Potential Drug-Drug Interactions for Chlorthalidone
| Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| ACE inhibitors | T | The antihypertensive effect of ACE inhibitors is potentiated in the presence of agents that increase plasma renin activity (diuretics). | A cautious dosage schedule should therefore be adopted when an ACE inhibitor is added to a diuretic agent. |
| Alcohol, barbiturates and narcotics | C | Potentiation of orthostatic hypotension may occur | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Allopurinol | T | Co-administration of thiazide diuretics may increase the incidence of hypersensitivity reactions to allopurinol. | Dosage adjustment of allopurinol may be required. |
| Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Amantadine | T | Co-administration of thiazide diuretics may increase the risk of adverse effects from amantadine. | |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics. | Monitor serum potassium level. |
| Anticholinergics (e.g., atropine, biperiden) | T | The bioavailability of thiazide-type diuretics may be increased by anticholinergic agents, apparently due to a decrease in gastrointestinal motility and rate of gastric emptying. | Dose adjustment of thiazide may be required. |
| Antihypertensive Agents | T | Diuretics potentiate the action of antihypertensive agents (e.g., methyldopa, beta-blockers, vasodilators, calcium antagonists, ACE inhibitors). | Careful monitoring of the doses is required until the patient is stabilized. |
| Antineoplastic Agents (e.g., cyclophosphamide, methotrexate) | T, C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance the myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Bile acid sequestrants, e.g., Cholestyramine and colestipol resins | T | Absorption of thiazide diuretics is decreased by cholestyramine because Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and |
| Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| absorption by 43- 85%., A decrease in pharmacological effect may be expected. | increase dose of thiazide, if necessary. | ||
| Calcium or Vitamin D supplements | T, C | Concomitant use of thiazide diuretics may decrease urinary excretion of calcium, and coadministration of Vitamin D may potentiate the increase in serum calcium. Concomitant use of thiazide-type diuretics may cause hypercalcemia by increasing tubular calcium reabsorption. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements, and signs of hypercalcemia. Dose reduction and/or withdrawal of calcium and/or Vitamin D supplements may be necessary. |
| Corticosteroids and Adrenocorticotropic hormone (ACTH) | T | The hypokalemic effects of diuretic may be increased by corticosteroids, ACTH and amphotericin. | Monitor serum potassium, and adjust medications, as required. |
| Curare Derivatives and Ganglionic Blocking Agents | T | Thiazides may increase responsiveness to curare derivatives and ganglionic blocking agents. | |
| Cyclosporin | T | Concomitant treatment with diuretics may increase the risk of hyperuricemia and gout-type complications. | |
| Diazoxide | T | Thiazide diuretics may enhance the hyperglycemic effect of diazoxide. | |
| Digitalis | CT, T | Thiazide-induced electrolyte disturbances, i.e. | Concomitant administration of chlorthalidone and digitalis |
| Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| hypokalemia, hypomagnesemia, increase the risk of digitalis-induced toxicity, which may lead to fatal arrhythmic events. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular. | requires caution. Monitor electrolytes and digitalis levels closely. Supplement potassium or adjust doses of digitalis or chlorthalidone, as required. | ||
| Insulin and Oral Antidiabetic Agents | CT T | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. It may be necessary to adjust the dosage of insulin or oral antidiabetic agents in response to changes in glucose tolerance that chlorthalidone may produce. See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism. |
| Lithium | T | Diuretics enhance the cardiotoxic (manifested in ECG changes) and neurotoxic (manifested by ataxia, confusion, and mental disorientation) effects of lithium and these drugs should not be administered concurrently. | In those rare instances when these drugs must be given together, patients should be observed closely for signs and symptoms of lithium toxicity. Close monitoring of serum electrolytes and lithium concentrations and maintenance of adequate fluid, potassium and sodium intake are also necessary. |
| NSAIDs | CT | Concomitant administration of | If combination use is necessary, monitor renal |
| Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| certain NSAIDs (e.g., indomethacin) may weaken the diuretic and antihypertensive activity of thiazides, and there have been isolated reports of a deterioration of renal function in predisposed patients. | function, serum potassium, and blood pressure closely. Dose adjustments may be required. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
AA-ATENIDONE (atenolol/chlorthalidone) combines the antihypertensive activity of two agents, a beta-adrenergic receptor blocking agent (atenolol) and a diuretic (chlorthalidone).
Atenolol is a beta1-selective, beta adrenergic blocking agent, devoid of membrane stabilizing or intrinsic sympathomimetic (partial agonist) activities. It is a racemic mixture and the beta1 properties reside in the S(-) enantiomer. Beta1-selectivity decreases with increasing dose.
The mechanism of the antihypertensive effect of atenolol has not been established. Among the factors that may be involved are:
- a) competitive ability to antagonize catecholamine-induced tachycardia at the beta receptor sites in the heart, thus decreasing cardiac output.
- b) inhibition of renin release by the kidneys.
- c) inhibition of the vasomotor centres.
The mechanism of the anti-anginal effect is also uncertain. An important factor may be the reduction of myocardial oxygen requirements by blocking catecholamine-induced increases in heart rate, systolic blood pressure, and the velocity and extent of myocardial contraction.
Chlorthalidone inhibits reabsorption of sodium and chloride in the distal renal tubule thus promoting water loss. The higher urine volume increases potassium loss. Little information is available on the absorption of the drug. Its long elimination half-life and clinical experience place it as a long-acting thiazide derivative. This may not be important clinically because the biological effects of thiazides particularly as antihypertensives may be prolonged compared to their elimination rate. The longer acting agents appear to cause increased potassium loss. Although a mild diuretic, its combination with loop diuretics is particularly potent because the latter presents much more sodium chloride to the distal tubule.
The blood pressure lowering effects are initially due to volume reduction but the persisting effect includes other undetermined mechanisms that reduce peripheral resistance. A high salt intake reverses its antihypertensive effect.
The combination of atenolol with thiazide-like diuretics has been shown to be compatible and generally more effective than either drug used alone as an antihypertensive agent.
10.2 Pharmacodynamics
Atenolol:
In man atenolol reduces both isoproterenol- and exercise-induced increases in heart rate over the dose range of 50 to 200 mg. At an oral dose of 100 mg the beta1 blocking effects persist for at least 24 hours; the reduction in exercise-induced heart rate increase being about 32% and 13%, 2 and 24 hours after dosing, respectively. The logarithm of the plasma atenolol level correlates with the degree of beta1 blockade but not with the antihypertensive effect.
Chlorthalidone:
Chlorthalidone is a benzothiadiazine (thiazide)-related diuretic with a long duration of action.
Thiazide and thiazide-like diuretics act primarily on the distal renal tubule (early convoluted part), inhibiting NaCl¯ reabsorption (by antagonising the Na+Cl¯ cotransporter) and promoting Ca++ reabsorption (by an unknown mechanism). The enhanced delivery of Na+ and water to the cortical collection tubule and/or the increased flow rate leads to increased secretion and excretion of K+ and H+.
In persons with normal renal function, diuresis is induced after the administration of 12.5 mg chlorthalidone. The resulting increase in urinary excretion of sodium and chloride and the less prominent increase in urinary potassium are dose dependent and occur both in normal and in oedematous patients. The diuretic effect sets in after 2 to 3 hours, reaches its maximum after 4 to 24 hours and may persist for 2 to 3 days.
Thiazide-induced diuresis initially leads to decreases in plasma volume, cardiac output, and systemic blood pressure. The renin-angiotensin-aldosterone system may possibly become activated.
In hypertensive individuals, chlorthalidone gently reduces blood pressure. On continued administration the hypotensive effect is maintained, probably due to the fall in peripheral resistance; cardiac output returns to pretreatment values, plasma volume remains somewhat reduced and plasma renin activity may be elevated.
In renal diabetes insipidus, chlorthalidone paradoxically reduces polyuria. The mechanism of action has not been elucidated.
10.3 Pharmacokinetics
Absorption
Atenolol: Approximately 40 to 50% of an oral dose of atenolol is absorbed from the gastrointestinal tract, the remainder being excreted unchanged in the feces.
Chlorthalidone: Approximately 60% of an oral dose of chlorthalidone is absorbed from the gastrointestinal tract and excreted unchanged in the urine.
Distribution
Atenolol: Peak plasma concentrations occur 2 to 4 hours after dosing and are subject to a 4 times variability. The plasma levels are proportional to dose over the range 50 to 400 mg and 6 to 16% of atenolol is bound to plasma proteins. The mean peak plasma concentrations of atenolol were approximately 300 and 700 nanogram/mL following 50 and 100 mg, respectively. The plasma half-life is approximately 6 to 7 hours. Atenolol is extensively distributed to extravascular tissues, but only a small amount is found in the central nervous system.
Following intravenous administration, peak plasma levels were reached within 5 minutes. Declines from peak plasma levels are rapid (5- to 10-fold) during the first 7 hours; thereafter, plasma levels decay with a half-life similar to that of orally administered drug.
Atenolol is excreted in human breast milk and crosses the placental barrier - the maternal to cord blood ratio being about unity.
Chlorthalidone: Following a single dose, the peak blood concentration of chlorthalidone occurs after approximately 12 hours and decreases thereafter according to first-order kinetics; the disposition half-life is approximately 50 hours. Approximately 75% of chlorthalidone is bound in plasma.
Metabolism
Atenolol: There is no significant hepatic metabolism of atenolol in man and more than 90% of the absorbed dose reaches the systemic circulation unaltered. Small quantities of a hydroxy metabolite and a glucuronide are produced but neither has major pharmacological activity. As a consequence no accumulation occurs in patients with liver disease and no dosage adjustment is required.
Chlorthalidone: Metabolism and hepatic excretion into bile constitute a minor pathway of elimination. Within 120 hours, about 70% of the dose is excreted in the urine and in the faeces, mainly in unchanged form.
Elimination
Atenolol: Approximately 47 and 53% of the oral dose is eliminated in the urine and feces, respectively. Recovery is complete after 72 hours.
Atenolol is primarily eliminated by the kidney, predominantly by glomerular filtration. The normal elimination half-life may increase in severe renal impairment, but no significant accumulation occurs in patients who have creatinine clearance greater than 35 mL/min. The oral dose should be reduced in patients with a creatinine clearance less than 35 mL/min.
Over 85% of an intravenous dose is excreted in urine within 24 hours.
Chlorthalidone: The major portion of an absorbed dose of chlorthalidone from whole blood and plasma is excreted by the kidneys with an elimination half-life averaging 50 hours. The elimination half-life is unaltered after chronic administration. The major part of an absorbed dose of chlorthalidone is excreted by the kidneys, with a mean renal clearance of 60 mL/min. Metabolism and hepatic excretion into the bile constitute a minor way of elimination. Within 120 hours, about 70% of the dose is excreted in the urine and in the feces, mainly in an unchanged form.
Special Populations and Conditions
- Pediatrics: The safety of use of atenolol in children has not been established; therefore, AA-ATENIDONE is not recommended in the pediatric age group.
- Geriatrics: Clinical studies of atenolol and chlorthalidone tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between elderly and younger patients. See 7.1.4 Geriatrics.
- Sex: There is no available information related to differences in sex.
- Pregnancy: Atenolol and chlorthalidone tablets are contraindicated during pregnancy and breastfeeding. See 7.1.1 Pregnant Women and 7.1.2 Breast-feeding.
- Breast-feeding: Atenolol and chlorthalidone tablets are contraindicated during pregnancy and breastfeeding. Chlorthalidone crosses the placental barrier and passes into the breast milk. in mothers treated with 50 mg chlorthalidone daily before and after delivery, chlorthalidone levels in foetal whole blood are about 15% of those found in maternal blood. See 7.1.2 Breast-feeding.
- Genetic Polymorphism: There is no available information related to differences in genetic polymorphism.
- Ethnic Origin: Atenolol appears to be effective and well-tolerated in most ethnic populations, although the response may be less in black patients than in Caucasians.
- Hepatic Insufficiency: Chlorthalidone should be used with caution in patients with impaired hepatic function of progressive liver disease since minor alterations of fluid and electrolyte balance may precipitate hepatic coma. See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic.
Renal Insufficiency: When renal function is impaired, clearance of atenolol is closely related to the glomerular filtration rate. However, significant accumulation does not
- 2. See 7 WARNINGS AND PRECAUTIONS, Renal.
Renal dysfunction does not alter the pharmacokinetics of chlorthalidone, the rate limiting factor in the elimination of the drug from blood or plasma being most probably the affinity of the drug to the carbonic anhydrase of erythrocytes. No dosage adjustment is needed in patients with impaired renal function. Chlorthalidone may precipitate azotemia. Cumulative effects of the drug may develop in patients with impaired renal function.
- Obesity: There is no available information related to differences due to obesity.
11 STORAGE, STABILITY AND DISPOSAL
AA-ATENIDONE tablets should be protected from light and moisture. Store at room temperature (15°C to 30°C).
AA-ATENIDONE should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended.
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substances
Atenolol:
Proper name: Atenolol
Chemical name: 4-[2’-hydroxy-3’-[(1 -methyl-ethyl) amino]propoxy]- benzeneacetamide
Molecular formula and molecular mass: C14H22N2O3, 266.34 g/mol
Structural formula:
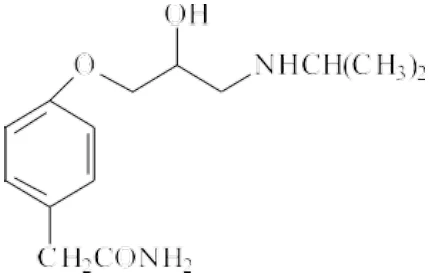
Physicochemical properties: White or almost white crystalline powder. A relatively polar hydrophilic compound with a water solubility of 26.5 mg/mL at 37°C and a log partition coefficient (octanol/water) of 0.23; freely soluble in 1 N HCI (300 mg/mL at 25°C) and less soluble in chloroform (3 mg/mL at 25°C). The melting point for atenolol is 152.0°C to 155.0°C.
Chlorthalidone:
Proper name: Chlorthalidone
Chemical Name: 2-chloro-5-( 1 -hydroxy-3-oxo- 1 -isoindolinyl) benzenesulphonamide
Molecular formula and molecular mass: C14H11ClN2O4S; 338.76 g/mol
Structural formula:
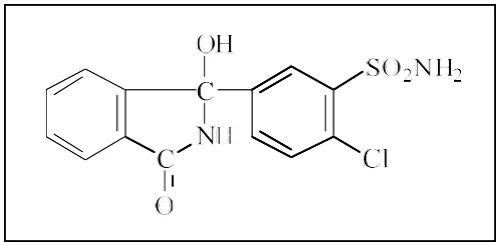
Physicochemical properties: White to yellowish-white powder. Water solubility of 0.27 mg/mL at 37°C.
14 CLINICAL TRIALS
14.2 Comparative Bioavailability Studies
50/25 mg Tablets
A comparative bioavailability study was performed on healthy human volunteers under fasting conditions. The rate and extent of absorption of atenolol and chlorthalidone was measured and compared following a double oral 50 mg/25 mg dose of AA-ATENIDONE (Atenolol and chlorthalidone Tablets) or TENORETIC® tablets.
The results from measured data are summarized as follows:
Table 4 - Summary Table of the Comparative Bioavailability Data Atenolol and Chlorthalidone Tablets (Dose: 2 x 50/25 mg) From Measured Data – Under Fasting Conditions Based on Atenolol
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
|---|---|---|---|
| AA-Atenidone | Tenorectic®ϒ | ||
AUCT (ng.h/mL) | 4494 4822 (38) | 4632 4775 (24) | 97.1 |
AUCI (ng.h/mL) | 4794 5092 (36) | 4939 5069 (22) | 97.2 |
CMAX (ng/mL) | 532 578 (39) | 581 600 (26) | 91.4 |
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
|---|---|---|---|
| AA-Atenidone | Tenorectic®ϒ | ||
| TMAX* (h) | 2.96 (63) | 2.83 (35) | - |
| T1/2* (h) | 7.45 (28) | 7.61 (25) | - |
* Arithmetic means (CV%) ** Based on the least square estimate. ϒ Tenorectic® is manufactured by Zeneca Pharma (currently AstraZeneca) and was purchased in Canada.) | |||
Table 5 - Summary Table of the Comparative Bioavailability Data Atenolol and Chlorthalidone Tablets (Dose: 2 x 50/25 mg) From Measured Data – Under Fasting Conditions Based on Chlorthalidone
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
|---|---|---|---|
| AA-Atenidone | Tenorectic®ϒ | ||
AUCT (ng.h/mL) | 118198 122323 (25) | 122054 124330 (20) | 100.9 |
AUCI (ng.h/mL) | 204088 213693 (31) | 219908 228253 (27) | 104.4 |
CMAX (ng/mL) | 2501 2599 (27) | 2574 2626 (21) | 98.1 |
| TMAX* (h) | 12.5 (51) | 10.9 (39) | - |
| T1/2* (h) | 52.4 (27) | 60.9 (33) | - |
* Arithmetic means (CV%) ** Based on the least square estimate. ϒTenorectic® is manufactured by Zeneca Pharma (currently AstraZeneca) and was purchased in Canada.) | |||
100/25 mg tablets
A comparative bioavailability study was performed on healthy human volunteers under fasting conditions. The rate and extent of absorption of atenolol and chlorthalidone was measured and compared following a single oral 100 mg/25 mg dose of AA-ATENIDONE (atenolol/chlorthalidone) or TENORETIC® tablets.
The results from measured data are summarized as follows:
Table 6 - Summary Table of the Comparative Bioavailability Data
Atenolol and Chlorthalidone Tablets (Dose: 1 x 100/25 mg) From Measured Data – Under Fasting Conditions Based on Atenolol
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** |
|---|---|---|
| AA-Atenidone | Tenoretic®ϒ | |
AUCT (ng.h/mL) | 5149 5391 (31) | |
5224 5391 (25) | 98.6 | |
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
|---|---|---|---|
| AA-Atenidone | Tenoretic®ϒ | ||
AUCI (ng.h/mL) | 5540 5753 (29) | 5601 5750 (23) | 98.9 |
CMAX (ng/mL) | 580 610 (30) | 594 621 (29) | 97.7 |
| TMAX* (h) | 3.06 (29) | 2.97 (45) | - |
| T½* (h) | 8.17 (27) | 7.88 (20) | - |
* Arithmetic means (CV%) ** Based on the least square estimate. ϒ Tenorectic® is manufactured by Zeneca Pharma (currently AstraZeneca) and was purchased in Canada.) | |||
Table 7 - Summary Table of the Comparative Bioavailability Data Atenolol and Chlorthalidone Tablets (Dose: 1 x 100/25 mg) From Measured Data - Under Fasting Conditions Based on Chlorthalidone
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
|---|---|---|---|
| AA-Atenidone | Tenoretic®ϒ | ||
AUC72 (ng.h/mL) | 77270 78025 (14) | 76427 77292 (15) | 100.9 |
AUCI (ng.h/mL) | 128123 131344 (23) | 119788 122703 (23) | 104.4 |
CMAX (ng/mL) | 1533 1554 (17) | 1562 1575 (13) | 98.1 |
| TMAX* (h) | 12.1 (42) | 11.6 (35) | - |
| T½* (h) | 52.7 (26) | 47.8 (26) | - |
* Arithmetic means (CV%) ** Based on the least square estimate. ϒ Tenorectic® is manufactured by Zeneca Pharma (currently AstraZeneca) and was purchased in Canada.) | |||
15 MICROBIOLOGY
No microbiological information is available for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
In rats, atenolol administered in combination with chlorthalidone does not interfere with the diuretic action of chlorthalidone or with beta-blocking activity of atenolol.
Acute Toxicity:
Table 8 - Summary Table of Chlorthalidone and Atenolol Alone and In combination Acute Toxicity Study Data
| Species | Sex | Route | LD50 mg/kg Chlorthalidone | LD50 mg/kg Atenolol | LD50 mg atenolol/kg Fixed Combination* | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Mouse | M&F | Oral | >2,500 | >3,125 | |||||||||||
| M&F | i.p. | 525 | 655 | ||||||||||||
| Rat | M&F | Oral | >10,000 | >5,000 | >5,000 | ||||||||||
| M | i.p. | 6,520 | 268 | 122 | |||||||||||
| F | i.p. | 3,025 | 268 | 233 | |||||||||||
*The fixed combination contained at 4:1 ratio of atenolol to chlorthalidone.
Six-Month Oral Administration Study in Rats: Atenolol and chlorthalidone alone and in combination were administered by gavage, to groups of 20 male and 20 female CD rats, once a day, 7 days a week for 6 months. Doses per group were 0, atenolol 10, chlorthalidone 2.5, and combination atenolol/chlorthalidone 10/2.5 mg/kg/day.
Results: Increased urine volume for combination treated rats; slight decrease in growth rate for rats treated with atenolol or chlorthalidone alone.
Rats treated with 75, 150 and 300 mg/kg/day atenolol orally for 6 months showed reduction in heart rate. High and intermediate dose showed decreased blood pressure. Spleen and heart weights increased. Chronic myocarditis was seen in all groups including 3 controls. Three high dose and 2 mid-dose animals were killed in moribund state.
Six Month Oral Administration Study in Dogs: Atenolol and chlorthalidone alone and in combination were administered as tablets in gelatine capsules to groups of 32 female and 32 male beagle dogs, once daily, 7 days a week for 6 months. Same doses as used in the rat study.
Results: Atenolol caused a reduction in heart rate and blood pressure in dogs receiving atenolol alone or in combination. Chlorthalidone alone or in combination was associated with a decrease in serum potassium levels. In dogs dosed with the combination a lower mean prostate weight was observed.
Chronic Toxicity Studies
Chronic toxicity studies were conducted using atenolol only. No 12 month studies have been conducted for chlorthalidone alone or in combination with atenolol.
Chronic studies performed in animals have revealed the occurrence of vacuolation of epithelial cells of Brunner’s glands in the duodenum of both male and female dogs at all tested dose levels of atenolol (starting at 15 mg/kg/day or 7.5 times the maximum recommended human dose) and an increased incidence of atrial degeneration of hearts of male rats at 300 but not 150 mg atenolol/kg/day (150 and 75 times the maximum recommended human dose, respectively).
Table 9 - Summary Table of Atenolol Chronic Toxicity Study Data
| Species | Strain | Sex | Dose mg/kg/day | Route | Duration (mo) | Effects | ||
|---|---|---|---|---|---|---|---|---|
| M | F | |||||||
| Dog | Beagle | 20 | 20 | 0, 50, 100, 200 | oral | 12 | Decreased heart rate. Prolongation of PR interval on ECG. Vacuolation of epithelial cells of duodenal Brunner’s glands: 5/10 low dose, 2/10 mid dose, 7/10 high dose. One high dose female died. | |
| Dog | Beagle | 15 | 15 | 0, 15 | oral | 12 | Vacuolation of epithelium 200 of Brunner’s glands 9/10 high dose; 1/10 low dose. | |
Carcinogenicity
Carcinogenicity studies have not been carried out with the combination or chlorthalidone alone.
Atenolol was administered to 3 groups of 65 male and 65 female CR7B1/1OJ mice at dietary levels of 0,150 and 300 mg/kg/day for 18 months followed by the control diet for an additional three months. A fourth group received 2-AAF (positive control) and a fifth was the negative control group. Retardation in weight gain was observed. There was no statistically significant difference in mortality, number of tumor bearers, number of tumors in each animal or the total number of tumors in treated and negative control animals.
Two studies were conducted in Alderley Park Strain I rats. One study employed doses of 150 and 300 mg/kg/day for 18 months followed by the control diet for an additional 6 months, while the second study used doses of 75, 150 and 300 mg/kg/day for 24 months. Results from the two studies showed no significant difference in mortality for treated and control groups. No apparent carcinogenic potential was observed.
Mutagenic Potential:
Atenolol was negative in the mouse dominant lethal test, the Chinese hamster in vivo cytogenetic test and the Salmonella Amery back mutation test (Ames test), with or without metabolic activation.
Reproductive and Developmental Toxicology
Table 10 - Summary Table of Atenolol and Chlorthalidone Combination Reproductive and Developmental Toxicity Study Data
| Species | Free combination dosage | Period of administration | Signs of toxicity |
|---|---|---|---|
| Rats | up to 300 mg/kg/day (4:1 atenolol:CHT) | days 6-15 of pregnancy | nervousness, decreased weight gain, decreased food consumption, two deaths (at high dose level only). |
| Rabbits | up to 25 mg/kg/day (4:1 atenolol:CHT) | days 6-18 of pregnancy | no observed malformations |
| Rabbits | up to 200 mg/kg/day (4:1 atenolol:CHT) | days 6-18 of pregnancy | slight decrease in weight gain; dose-related increase in the numbers of embryonic resorptions. |
Atenolol
Atenolol associated malformations were not observed when atenolol was administered at oral doses of up to 200 mg/kg/day, days 6 to 15 of gestation in rats or at doses of up to 25 mg/kg/day, days 6 to 18 of gestation in rabbits. Dose levels of 50 or more mg/kg/day were, however, associated with an increased incidence of resorptions in rats. Although a similar effect was not seen in rabbits, it should be noted that the compound was not evaluated in rabbits at doses above 25 mg/kg/day. Atenolol, administered at doses of up to 200 mg/kg/day, for 11 weeks prior to mating in males or 2 weeks prior to mating in females, did not adversely affect fertility of male or female rats. Growth or survival of offspring were not affected when pregnant females were exposed at 200 mg/kg/day from day 15 of gestation to day 21 post partum.
Chlorthalidone
Administration of various doses of chlorthalidone to pregnant mice, rats, hamsters and rabbits did not affect litter size, fetal body weight or the number of resorptions. Chlorthalidone had no effect on fertility in rats. Reproduction studies have been performed in the rat and the rabbit at doses up to 420 times the human dose and have revealed no evidence of harm to the fetus due to chlorthalidone.
Special toxicology:
Chronic studies performed in animals have revealed the occurrence of vacuolation of epithelial cells of Brunner's glands in the duodenum of both male and female dogs at all tested dose levels of atenolol (starting at 15 mg/kg/day or 7.5 times the maximum recommended human dose) and an increased incidence of atrial degeneration of hearts of male rats at 300 but not 150 mg atenolol/kg/day (150 and 75 times the maximum recommended human dose, respectively).
Effects on the Cardiovascular System
In anesthetized cats, atenolol infusion reduces the chronotropic response to isoproterenol and right cardiac sympathetic nerve stimulation.
In anesthetized dogs, atenolol 0.03 mg/kg i.v. depresses the heart rate by 22%, cardiac contractile force by 16% and diastolic blood pressure by 11%.
Studies in rats showed that atenolol was devoid of intrinsic sympathomimetic activity.
Atenolol in concentrations up to 10 mg/mL had no local anesthetic effect on the isolated sciatic nerve of the frog.
Atenolol (5 to 20 mg/kg i.v.) was without effect on the ventricular tachycardia produced by toxic levels of ouabain in anesthetized dogs. Atenolol (0.2 mg/kg i.v.) protected coronary ligated dogs from the arrhythmogenic activity of adrenaline on the fourth day after ligation (when the cardiac rhythm was predominantly sinus).
Chlorthalidone:
Chlorthalidone has been shown to reduce mean diastolic blood pressure in the genetically hypertensive rat and has an effect on norepinephrine vasoconstriction in animal studies.
Hypertension studies with chlorthalidone 12.5 to 100 mg once daily have shown that the dose- response curve is very flat for all doses above 25 mg. Adequate 24-hour reduction in blood pressure was obtained with the 25 mg dose.
In vivo and in vitro studies in rats have shown that chlorthalidone produces an increased excretion of water, sodium, chloride and to a lesser extent, potassium and bicarbonate.
Chlorthalidone has been reported to produce hyperglycemia in the rat following single large doses of the drug.
Chlorthalidone has no effect on renal circulation or glomerular filtration rate.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. TENORETIC® 50/25 mg and 100/25 mg Tablets. submission control 190685, Product Monograph, AstraZeneca Canada Inc. (JUL 12, 2016)
- 2. APO-CHLORTHALIDONE Tablets, 50 mg, submission control 272147, Product Monograph, Apotex Inc. (MAR 14, 2023)
- 3. APO-ATENOL Tablets, 50 mg and 100 mg, submission control 249096, Product Monograph, Apotex Inc. (MAR 17, 2021)
- 4. EDARBYCLOR®, Tablets 40 mg/12.5 mg, 80 mg/12.5 mg and 40 mg/25 mg, submission control: 246568, Product Monograph, Bausch Health, Canada Inc. (JUL 21, 2021)
- 5. TENORMIN Tablets, 50 mg and 100 mg, submission control 270737, Product Monograph, Searchlight Pharma Inc. (MAY 31, 2023)