


Product Monograph - AA-Diltiaz
RECENT MAJOR LABEL CHANGES
None at the time of the most recent authorization
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics ................................................................................................................... 4
1.2 Geriatrics ................................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration ........................................................................................................... 6
4.5 Missed Dose .............................................................................................................. 6
5 OVERDOSAGE ............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 7
7 WARNINGS AND PRECAUTIONS .................................................................................. 8
7.1 Special Populations ................................................................................................. 10
7.1.1 Pregnant Women .................................................................................................... 10
7.1.2 Breast-feeding ......................................................................................................... 11
7.1.3 Pediatrics ................................................................................................................. 11
7.1.4 Geriatrics ................................................................................................................. 11
8 ADVERSE REACTIONS ................................................................................................ 11
8.1 Adverse Reaction Overview .................................................................................... 11
8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 12
8.5 Post-Market Adverse Reactions .............................................................................. 13
9 DRUG INTERACTIONS ................................................................................................ 14
9.1 Serious Drug Interactions ........................................................................................ 14
9.2 Drug Interactions Overview .................................................................................... 14
9.3 Drug-Behavioural Interactions ................................................................................ 15
9.4 Drug-Drug Interactions ............................................................................................ 15
9.5 Drug-Food Interactions ........................................................................................... 23
9.6 Drug-Herb Interactions ........................................................................................... 23
9.7 Drug-Laboratory Test Interactions .......................................................................... 24
10 CLINICAL PHARMACOLOGY ....................................................................................... 24
10.1 Mechanism of Action .............................................................................................. 24
10.2 Pharmacodynamics ................................................................................................. 24
10.3 Pharmacokinetics .................................................................................................... 25
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 26
PART II: SCIENTIFIC INFORMATION ....................................................................................... 27
13 PHARMACEUTICAL INFORMATION ............................................................................ 27
14 CLINICAL TRIALS ........................................................................................................ 27
14.2 Comparative Bioavailability Studies ........................................................................ 27
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 29
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 34
PATIENT MEDICATION INFORMATION .................................................................................. 35
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
AA-DILTIAZ (diltiazem hydrochloride) is indicated for:
Angina
- AA-DILTIAZ (diltiazem hydrochloride) tablets may be used in the management of angina resulting from coronary artery spasm.
- AA-DILTIAZ tablets are indicated for the management of chronic stable angina (effort-associated angina) without evidence of vasospasm in patients who remain symptomatic despite adequate doses of beta-blockers and/or organic nitrates or who cannot tolerate those agents. AA-DILTIAZ tablets may be tried in combination with beta-blockers in chronic stable angina in patients with normal ventricular function. When such concomitant therapy is introduced, patients must be monitored closely (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
- AA-DILTIAZ tablets may be useful in unstable angina when spasm of the coronary vessels is definitely a contributing factor (e.g., ST segment elevation). In the absence of objective evidence of a spastic component, nitrates or nitrates plus a beta-blocker are at present the treatment of choice. If, in the view of a cardiologist, the addition of diltiazem to this regimen is considered necessary and safe, then the use of AA-DILTIAZ tablets might be considered. Generally, the patient should be hospitalized and treatment initiated under the supervision of a cardiologist.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of AA-DILTIAZ in pediatric patients has not been established. Therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): Pharmacokinetics of diltiazem in elderly patients has not been fully elucidated. Preliminary results in elderly patients (over 65 years old) suggest that a lower dosage might be required in this age group (see 7 WARNINGS AND PRECAUTIONS).
2 CONTRAINDICATIONS
Diltiazem Hydrochloride is contraindicated:
In patients with sick sinus syndrome except in the presence of a functioning ventricular
- pacemaker.
- In patients with second or third-degree AV block.
- In patients with known hypersensitivity to diltiazem or to any of the excipients.
- In patients with hypotension (less than 90 mm Hg systolic).
- In patients with severe bradycardia (below 40 beats per minute).
- In myocardial infarction patients, who have left ventricular failure manifested by pulmonary congestion.
- In pregnancy and in women of childbearing potential.
- Breast-feeding
- With concomitant use of dantrolene infusion.
- With concomitant use of ivabradine.
- With concomitant use of lomitapide mesylate as it may result in increased concentrations of lomitapide mesylate due to CYP3A4 inhibition (see 9.4 Drug-Drug Interactions).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Geriatrics (see 4.2 Recommended Dose and Dose Adjustment and 7.1.4 Geriatrics).
- Renal disease (see 4.2 Recommended Dose and Dose Adjustment and 7 WARNINGS AND PRECAUTIONS).
- Hepatic disease (see 4.2 Recommended Dose and Dose Adjustment and 7 WARNINGS AND PRECAUTIONS).
- Rule out pregnancy (see 2 CONTRAINDICATIONS and 7.1.1 Pregnant Women).
- Concomitant therapy with drugs metabolized by the CYP450 system (see 9.1 Serious Drug Interactions, 9.2 Drug Interactions Overview, and 9.4 Drug-Drug Interactions).
4.2 Recommended Dose and Dosage Adjustment
Angina
Chronic Stable Angina or Vasospastic Angina
Dosage must be adjusted to each patient's needs. Starting with 30 mg 4 times daily, before meals and at bedtime, dosage may be increased gradually to 240 mg a day (given in 3 to 4 equally divided doses) at one to two day intervals, until optimum response is obtained. Limited clinical experience in rare resistant cases suggests that dosage of up to 360 mg a day in 3 to 4 equally divided doses may be tried under careful supervision.
In patients with vasospastic angina, the last dose of the day may be given at bedtime to help minimize angina pain which in such patients frequently occurs in early morning.
Unstable Angina Pectoris
Dosage of AA-DILTIAZ tablets should be carefully titrated in the Intensive Care Unit, up to 360 mg/day given in 3 to 4 equally divided doses. The titration should be done as rapidly as possible with consideration of concomitant therapy (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular and 9.4 Drug-Drug Interactions).
Dosage in Elderly patients
Pharmacokinetics of diltiazem in elderly patients has not been fully elucidated. Preliminary results in elderly patients (over 65 years old) suggest that a lower dosage might be required in this age group (see 7.1.4 Geriatrics).
There are few available data concerning dosage requirements in patients with impaired renal or hepatic function. If diltiazem must be used in these patients, the dosage should be carefully and gradually adjusted depending on patient tolerance and response (see 7 WARNINGS AND PRECAUTIONS, Renal).
4.4 Administration
AA-DILTIAZ tablets should not be chewed or crushed.
4.5 Missed Dose
If a dose of this medication has been missed, it should be taken as soon as possible. However, if it is almost time for the next dose, skip the missed dose and go back to the regular dosing schedule.
5 OVERDOSAGE
There have been reports of diltiazem overdose in amounts ranging from <1 g to 18 g. In cases with a fatal outcome, the majority involved multiple drug ingestion.
Events observed following diltiazem overdose included sinus bradycardia with or without isorhythmic dissociation, pronounced hypotension possibly leading to collapse, and acute kidney injury, sinus arrest, heart block, atrioventricular conduction disturbance, cardiac arrest, and cardiac failure.
The effectiveness of intravenous calcium administration to reverse the pharmacological effects of diltiazem overdose has been inconsistent. In a few reported cases, overdose with calcium channel blockers associated with hypotension and bradycardia that was initially refractory to atropine became more responsive to atropine after the patients received intravenous calcium. In some cases, intravenous calcium has been administered (1 g calcium chloride or 3 g calcium gluconate) over 5 minutes and repeated every 10 to 20 minutes, as necessary. Calcium gluconate has also been administrated as a continuous infusion at a rate of 2 g per hour for 10 hours. Infusions of calcium for 24 hours or more may be required. Patients should be monitored for signs of hypercalcemia.
In the event of overdosage or exaggerated response, appropriate supportive measures should be employed in addition to gastric lavage. Limited data suggest that plasmapheresis or charcoal hemoperfusion may hasten diltiazem elimination. The following measures may be considered:
Bradycardia: Administer atropine. If there is no response to vagal blockade, administer isoproterenol cautiously.
High Degree AV Block: Treat as for bradycardia above. Fixed high degree AV block should be treated with cardiac pacing.
Cardiac Failure: Administer inotropic agents (isoproterenol, dopamine or dobutamine) and diuretics.
Hypotension: Administer fluids and vasopressors (e.g., dopamine or noradrenaline).
Actual treatment and dosage should depend on the severity of the clinical situation.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
AA-DILTIAZ Tablets
AA-DILTIAZ 30 mg are round, biconvex, light green, film-coated tablets, plain one side, identified "APO" over "D30" on the other side. Available in bottles of 100.
AA-DILTIAZ 60 mg are round, biconvex, yellow, scored, film-coated tablets, plain one side, identified "APO" over "D60" on the other side. Available in bottles of 100.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet, 30 mg, 60 mg of diltiazem hydrochloride | Carnauba wax, colloidal silicon dioxide, D&C yellow #10, FD&C blue #1 (30 mg tablet only), FD&C yellow #6 (60 mg tablet only), hydroxypropyl methylcellulose, lactose, magnesium stearate, polyethylene glycol and titanium dioxide. |
7 WARNINGS AND PRECAUTIONS
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity.
Cardiovascular
Cardiac Conduction
Diltiazem prolongs AV node refractory periods without significantly prolonging sinus node recovery time, except in patients with sick sinus syndrome. This effect may rarely result in abnormally slow heart rates (particularly in patients with sick sinus syndrome) or second or third-degree AV block (6 of 1208 patients or 0.5%).
Concomitant use of diltiazem with agents known to affect cardiac conduction (such as beta-blockers, digitalis or amiodarone) may result in additive effects on cardiac conduction (see 9.4 Drug-Drug Interactions).
Prior to general anesthesia, the anesthetist must be informed of ongoing diltiazem treatment. Depression of cardiac contractility, conductivity, and automaticity, as well as the vascular dilatation associated with anesthetics may be potentiated by calcium channel blockers (see 9.4 Drug-Drug Interactions).
Congestive Heart Failure
Because diltiazem has a negative inotropic effect in vitro and it affects cardiac conduction, the drug should only be used with caution and under careful medical supervision in patients with congestive cardiac failure (see 2 CONTRAINDICATIONS).
Use with Beta-blockers
The combination of diltiazem and beta-blockers warrants caution since in some patients additive effects on heart rate, AV conduction, blood pressure or left ventricular function have been observed. Close medical supervision is recommended.
Generally, diltiazem should not be given to patients with impaired left ventricular function while they receive beta-blockers. However, in exceptional cases when, in the opinion of the physician, concomitant use is considered essential, such use should be instituted gradually in a hospital setting.
Diltiazem gives no protection against the dangers of abrupt beta-blocker withdrawal and such withdrawal should be done by the gradual reduction of the dose of beta-blocker.
Hypotension
Since diltiazem lowers peripheral vascular resistance, decreases in blood pressure may occasionally result in symptomatic hypotension. In patients with angina or arrhythmias using antihypertensive drugs, the additional hypotensive effect of diltiazem should be taken into consideration.
Patients with Myocardial Infarction
Use of immediate release diltiazem at 240 mg per day started 3 to 15 days after a myocardial infarction was associated with an increase in cardiac events in patients with pulmonary congestion, and no overall effect on mortality.
Endocrine and Metabolism
Patients with Diabetes
Careful monitoring is necessary to detect new onset of diabetes or in patients with diabetes mellitus (type 1 or type 2) due to an increase in blood glucose.
Gastrointestinal
Diltiazem has an inhibitory effect on intestinal motility. Therefore, it should be used with caution in patients at risk of developing an intestinal obstruction.
Hepatic/Biliary/Pancreatic
Acute Hepatic Injury
In rare instances, significant elevations in alkaline phosphatase, CPK, LDH, SGOT, SGPT and symptoms consistent with acute hepatic injury have been observed. These reactions have been reversible upon discontinuation of drug therapy. Although a causal relationship to diltiazem has not been established in all cases, a drug induced hypersensitivity reaction is suspected (see 8.3 Less Common Clinical Trial Adverse Reactions). As with any drug given over prolonged periods, laboratory parameters should be monitored at regular intervals.
Impaired Hepatic Function
Diltiazem should be used with caution in patients with hepatic impairment. Because diltiazem is extensively metabolized by the liver, the monitoring of laboratory parameters of hepatic function is recommended, and cautious dosage titration are recommended in patients with impaired hepatic function (see 8.3 Less Common Clinical Trial Adverse Reactions).
Psychiatric
Calcium channel blocking agents, such as diltiazem, may be associated with mood changes, including depression (see 9.4 Drug-Drug Interactions and 8.3 Less Common Clinical Trial Adverse Reactions).
Renal
Acute Kidney Injury
Cases of acute renal failure have been reported in patients using diltiazem at therapeutic dosages. Patients at greater risk appear to have reduced left ventricular function, severe bradycardia, or severe hypotension.
Impaired Renal Function
Diltiazem should be used with caution in patients with renal impairment. Because diltiazem is excreted by the kidney, the monitoring of laboratory parameters of renal function is recommended, and cautious dosage titration are recommended in patients with impaired renal function. (see 8 3 Less Common Clinical Trial Adverse Reactions).
Respiratory
The use of diltiazem may induce bronchospasm, including asthma aggravation, especially in patients with pre-existing bronchial hyper-activity. Cases have been reported after dose increase. Patients should be monitored for signs and symptoms of respiratory impairment during diltiazem therapy.
Skin
Dermatological events (see 8.3 Less Common Clinical Trial Adverse Reactions) may be transient and may disappear despite continued use of diltiazem. However, skin eruptions progressing to erythema multiforme and /or exfoliative dermatitis have also been infrequently reported. Should a dermatologic reaction persist, the drug should be discontinued.
7.1 Special Populations
7.1.1 Pregnant Women
AA-DILTIAZ is contraindicated in pregnancy and in women of child-bearing potential. Fetal malformations and adverse effects on pregnancy have been reported in animals. In repeated dose studies a high incidence of vertebral column malformations was present in the offspring of mice receiving more than 50 mg/kg of diltiazem HCL orally.
In the offspring of mice receiving a single oral dose of 50 or 100 mg/kg on day 12 of gestation, the incidence of cleft palate and malformed extremities was significantly higher. Vertebral malformations were most prevalent when they received the drug on day 9. In rats, a significantly higher fetal death rate was present when 200 and 400 mg/kg were given orally on days 9 to 14 of gestation. Single oral dose studies in rats resulted in a significant incidence of skeletal malformations in the offspring of the group receiving 400 mg/kg on day 11. In rabbits, all pregnant dams receiving 70 mg/kg orally from day 6 to 18 of gestation aborted; at 35 mg/kg, a significant increase in skeletal malformations was recorded in the offspring (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1.2 Breast-feeding
Diltiazem has been reported to be excreted in human milk. One report with oral diltiazem suggests that concentrations in breast milk may approximate serum levels. Since diltiazem safety in newborns has not been established, it should not be given to breast-feeding mothers.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of AA-DILTIAZ in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Administration of diltiazem to elderly patients (over or equal to 65 years of age) requires caution. The incidence of adverse reactions is approximately 13% higher in this group. Those adverse reactions which occur more frequently include peripheral edema, bradycardia, palpitation, dizziness, rash, and polyuria. Therefore, particular care in titration is advisable (see 4.2 Recommended Dose and Dosage Adjustment).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
DILTIAZEM TABLETS
(See also OVERALL DILTIAZEM SAFETY PROFILE.)
A safety evaluation was carried out in controlled clinical trials with 1208 North American angina patients, some of whom were severely ill and were receiving multiple concomitant therapy. Adverse effects were reported in 19.6% of patients and required discontinuation of treatment in 7.2%.
The most common occurrences and their frequency are: nausea (2.7%), swelling/edema (2.4%), arrhythmia (AV block, bradycardia, tachycardia, sinus arrest) (2.0%) headache (2.0%), rash (1.8%) and asthenia (1.1 %).
OVERALL DILTIAZEM SAFETY PROFILE
In clinical trials of diltiazem tablets, diltiazem SR (sustained release) capsules and diltiazem CD (control delivery) capsules involving over 3300 patients, the most common adverse reactions were headache (4.6%), edema (4.6%), dizziness (3.5%), asthenia (2.7%), first-degree AV block (2.4%), bradycardia (1.7%), flushing (1.5%), nausea (1.4%), rash (1.2%), and dyspepsia (1.0%).
8.3 Less Common Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
DILTIAZEM TABLETS
The following events were reported in less than 1.0% of cases:
Cardiac disorders: Angina, bradycardia, congestive heart failure, palpitations, syncope. A patient with Prinzmetal's angina experiencing episodes of vasospastic angina developed periods of transient asymptomatic asystole approximately 5 hours after receiving a single 60 mg dose of diltiazem.
Ear and labyrinth disorders: Tinnitus.
Eye disorders: Amblyopia, eye irritation.
Gastrointestinal disorders: Constipation, diarrhea, dysgeusia, dyspepsia, vomiting.
General disorders and administration site conditions: Thirst, weakness.
Investigations: Weight increase.
In rare instances, mild to moderate transient elevations of alkaline phosphatase, SGOT, SGPT, LDH and CPK, have been noted during diltiazem therapy.
Metabolism and nutritional disorders: Anorexia, hyperglycemia.
Musculoskeletal and connective tissue disorders: Osteoarticular pain.
Nervous system disorders: Amnesia, confusion, dizziness, drowsiness, gait abnormality, paresthesia, personality change, tremor.
Psychiatric Disorders: Depression, hallucinations, insomnia, nervousness.
Renal and urinary disorders: Nocturia, polyuria.
Reproductive system and breast disorders: Decreased sexual performance.
Respiratory, thoracic, and mediastinal disorders: Dyspnea, epistaxis.
Skin and subcutaneous tissue disorders: Petechiae, photosensitivity, pruritus, urticaria.
Vascular disorders: Flushing, hypotension.
Rarely, reports of extremely elevated liver enzymes, cholestasis, hyperbilirubinemia, jaundice, epigastric pain, anorexia, nausea, vomiting, stool discoloration, dark urine and weight loss have been reported. The symptoms and laboratory test abnormalities have been reversible upon drug discontinuation. See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic.
Two incidents of marked hyperglycemia, hyperkalemia, bradycardia, asthenia, hypotension and gastrointestinal disturbances have been reported in diabetic patients receiving diltiazem, glyburide and a beta-blocker along with several other medications. Drugs were discontinued and supportive measures were administered which resulted in the patients fully recovering within a few days.
8.5 Post-Market Adverse Reactions
Adverse reactions reported during post marketing experience are derived from spontaneous reports and therefore, the frequency of these adverse reactions is not known.
Blood and lymphatic system disorders: Thrombocytopenia, hemolytic anemia, increased bleeding time, leukopenia.
Nervous system and psychiatric disorders: Mood changes including depression, extrapyramidal symptoms.
Cardiac disorders: Sinoatrial block, congestive heart failure, sinus arrest, cardiac arrest (asystole).
Respiratory, thoracic, and mediastinal disorders: Bronchospasm (including asthma aggravation).
Gastrointestinal disorders: Gingival hyperplasia.
Metabolism and nutrition disorders: Hyperglycaemia, diabetes (new onset), worsening of existing diabetes (type 1 or type 2).
Skin and subcutaneous tissue disorders: Photosensitivity (including lichenoid keratosis at sun exposed skin areas), angioneurotic oedema, erythema multiforme (including Stevens-Johnson syndrome, toxic epidermal necrolysis), sweating, exfoliative dermatitis (see 7 WARNINGS AND PRECAUTIONS, Skin), acute generalized exanthematous pustulosis, occasionally desquamative erythema with or without fever, allergic reactions, alopecia, purpura.
Vascular disorders: A number of well-documented cases of generalized rash, some characterized as leukocytoclastic vasculitis.
Hepatobiliary disorders: Hepatitis.
Renal disorders: Acute Kidney injury/failure.
Reproductive system and breast disorders: Gynecomastia.
Eye disorders: Detached retina, retinopathy.
Musculoskeletal and connective tissue disorders: Myopathy.
Isolated cases of angioedema have been reported. Angioedema may be accompanied by breathing difficulty. In addition, events such as myocardial infarction have been observed which are not readily distinguishable from the natural history of the disease in these patients. However, a definitive cause and effect relationship between these events and diltiazem therapy is yet to be established.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
- concomitant use of dantrolene infusion. See 9.4 Drug-Drug Interactions, Dantrolene (infusion).
- concomitant use of ivabradine. See 9.4 Drug-Drug Interactions, Moderate CYP3A4 inhibitors (ivabradine).
- concomitant use of lomitapide mesylate.
- Concomitant use of Direct Oral Anticoagulants (DOACs; e.g. apixaban, rivaroxaban, dabigatran, see 9.4 Drug-Drug Interactions)
9.2 Drug Interactions Overview
Cytochrome P450 System
As with all drugs, care should be exercised when treating patients with multiple medications. Diltiazem undergoes biotransformation mainly by the CYP3A4 isoenzyme of the cytochrome P450 system and is a substrate of the P-glycoprotein (P-gp). Diltiazem has also been shown to be an inhibitor of CYP3A4 (moderate) and P-gp.
Co-administration of diltiazem with other drugs which follow the same route of biotransformation or are inhibitors or inducers of these enzymes may result in altered bioavailability of diltiazem or these drugs. Dosages of similarly metabolized drugs, particularly those of low therapeutic ratio, and especially in patients with renal and/or hepatic impairment, may require adjustment when starting or stopping concomitantly administered diltiazem to maintain optimum therapeutic blood levels.
9.3 Drug-Behavioural Interactions
Alcohol
Alcohol can exhibit hypotensive effects. Co-administration with antihypertensive agents including diltiazem may result in additive effects on blood pressure and orthostasis. Patients should be advised that alcohol may potentiate the hypotensive effects of diltiazem, especially during the initiation of therapy and following a dosage increase. Caution should be exercised when rising from a sitting or recumbent position, and patients should notify their physician if they experience dizziness, light-headedness, syncope, orthostasis, or tachycardia.
9.4 Drug-Drug Interactions
AA-DILITAZ is contraindicated with co-administration of lomitapide mesylate as it may increased concentrations of lomitapide mesylate due to inhibition of CYP3A4 (see 9 DRUG INTERACTIONS). Co-administration of diltiazem with other drugs which follow the same route of biotransformation or are inhibitors or inducers of these enzymes may result in altered bioavailability of diltiazem or these drugs. Dosages of similarly metabolized drugs, particularly those of low therapeutic ratio, and especially in patients with renal and/or hepatic impairment, may require adjustment when starting or stopping concomitantly administered diltiazem to maintain optimum therapeutic blood levels.
Table 2 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Acetylsalicylic acid or antiplatelet drugs | T | ↑ bleeding | Because of the increased risk of bleeding due to potential or |
| such as ticagrelor, cilostazol, clopidogrel, dipyridamole, ticlopidine | observed additive effect on platelet aggregation combined with vasodilation or prevention of the normal vasoconstrictive response to bleeding, the concomitant administration of acetylsalicylic acid or antiplatelet drugs such as ticagrelor, cilostazol and clopidogrel with diltiazem should be undertaken with caution. Besides, a drug interaction is also plausible with dipyridamole and ticlopidine. Dosage adjustment and safety monitoring may be necessary when coadministration cannot be avoided. | ||
| Alpha-antagonists | T | ↑ antihypertensive | Concomitant treatment with α-antagonists may produce or aggravate hypotension. The combination of diltiazem with an α-antagonist should be considered only with the strict monitoring of blood pressure. |
| Amiodarone, digoxin | CT | ↑ bradycardia | Severe conduction system abnormalities including heart block of varying degree, sinus arrest and a low cardiac output state of life threatening severity have been reported following concomitant use of diltiazem and amiodarone. These drugs may also have additive effects on cardiac conduction and contractility. Increased risk of bradycardia is seen with amiodarone. Caution is required when these are combined with diltiazem, particularly in elderly subjects and when high doses are used. |
| Anaesthetics | T | ↑ depression of cardiac contractility, conductivity, and automaticity | The depression of cardiac contractility, conductivity, and automaticity as well as the vascular dilation associated with anesthetics may be potentiated by calcium channel blockers. When used concomitantly, anesthetics and calcium channel blockers should be titrated carefully. |
| Anti-H2 agents (Cimetidine, ranitidine) | CT | ↑ diltiazem exposure | A study in six healthy volunteers has shown a significant increase in peak diltiazem plasma levels Cmax (58%) and area-under-the-curve AUC (53%) after a 1-week course of cimetidine at 1200 mg per day and a single dose of oral diltiazem 60 mg. Ranitidine produced smaller, nonsignificant increases. Patients currently receiving diltiazem therapy should be carefully monitored for a change in pharmacological effect when initiating and discontinuing therapy with cimetidine. An adjustment in the diltiazem dose may be warranted. |
| Benzodiazepines (midazolam, triazolam) | CT | ↑ benzodiazepines plasma concentration | Diltiazem significantly increases peak plasma levels and the elimination half-life of triazolam and midazolam. Special care (close medical supervision and/or dose adjustment) should be taken when prescribing short-acting benzodiazepines metabolized by CYP3A4 in patients using diltiazem. |
| Beta-Blockers | T, CT | Arrhythmic effect ↑ propranolol | The concomitant administration of diltiazem with beta-adrenergic blocking drugs |
| exposure | warrants caution because of rhythm disturbances occurrence, and requires close medical supervision and ECG monitoring, particularly at the beginning of treatment. Such an association may have an additive effect on heart rate, on sino-atrial and AV conduction or on blood pressure (e.g., pronounced bradycardia, sinus arrest, and heart failure) (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular). Appropriate dosage adjustments may be necessary. A study in five normal subjects showed that diltiazem increased propranolol bioavailability by 50%. An increased risk of depression has been reported when diltiazem is co-administered with beta-blockers (see 8.3 Less Common Clinical Trial Adverse Reactions). | ||
| Carbamazepine | CT | ↑ Carbamazepine serum level | Concomitant administration of diltiazem with carbamazepine has been reported to result in elevated serum levels of carbamazepine (40% to 72% increase), resulting in toxicity in some cases. Patients receiving these drugs concurrently should be monitored for a potential drug interaction and dose adjustment of carbamazepine and/or diltiazem may be necessary. |
| Corticosteroids (methylprednisolone) | T | ↑ P-gp plasma concentration | Inhibition of methylprednisolone metabolism (CYP3A4) and inhibition of P- |
| glycoprotein by diltiazem. Therefore, patients should be monitored when initiating methylprednisolone treatment and a dose adjustment may be necessary. | |||
| Cyclosporine | CT | ↑ cyclosporine concentration in specific population | Concomitant administration of diltiazem and cyclosporine has resulted in an increase in cyclosporine concentrations. A pharmacokinetic interaction between diltiazem and cyclosporine has been observed during studies involving renal and cardiac transplant patients. In renal and cardiac transplant recipients, a reduction of cyclosporine dose ranging from 15% to 48% was necessary to maintain cyclosporine trough concentrations similar to those seen prior to the addition of diltiazem. If these agents are to be administered concurrently, cyclosporine concentrations should be monitored, especially when diltiazem therapy is initiated, adjusted, or discontinued. Downward titration of the cyclosporine dose may be necessary. The effect of cyclosporine on diltiazem plasma concentrations has not been evaluated. |
| Dantrolene (infusion) | CT | Ventricular fibrillation effect in animals observed | Lethal ventricular fibrillation is regularly observed in animals when intravenous verapamil and dantrolene are administered concomitantly. The combination of calcium-channel antagonist and dantrolene is therefore |
| potentially dangerous (see 2 CONTRAINDICATIONS). | |||
| Digitalis | CT | ↑ digoxin serum level | Diltiazem and digitalis glycosides may have an additive effect in prolonging AV conduction. In clinical trials, concurrent administration of diltiazem and digoxin has resulted in increases in serum digoxin levels with prolongation of AV conduction. This increase may result from a decrease in renal clearance of digoxin. Patients on concomitant therapy, especially those with renal impairment, should be carefully monitored. The dose of digoxin may need downward adjustment. |
| Direct Oral Anticoagulants (DOACs; e.g. apixaban, rivaroxaban, dabigatran) | CT | ↑ DOAC plasma concentration In a pharmacokinetic study, coadministration of apixaban with diltiazem led to a 1.4 and 1.3-fold increase in mean apixaban AUC and Cmax, respectively. | Coadministration of diltiazem and DOACs increases the risk of bleeding due to pharmacokinetic interaction via P-gp and CYP3A4. Literature evidence has shown increased risk of bleeding leading to hospitalization and even death in atrial fibrillation patients receiving diltiazem and apixaban, rivaroxaban or dabigatran. Concomitant treatment with diltiazem and DOACs in patients should be used with caution. Close clinical surveillance (looking for signs of bleeding or anemia) is recommended throughout the treatment period, especially in patients with renal impairment. |
| Inducers of CYP3A4 (e.g., avasimibe, carbamazepine, | T | ↓ diltiazem plasma concentration | Diltiazem should be used with caution together with CYP3A4 inducers and dose adjustment |
| phenytoin, rifampin) | may be necessary to maintain efficacy. Hence, monitoring of therapy is required. | ||
| Ivabradine | C | ↑ AUC ivabradine (2- 3-fold). Additional heart rate lowering | Concomitant use with ivabradine is contraindicated due to the additional heart rate lowering effect of diltiazem to ivabradine (see 2 CONTRAINDICATIONS) |
| Lithium | T | ↑ Lithium neurotoxicity | Risk of increased in lithium-induced neurotoxicity. |
| Lomitapide Mesylate | T | ↑ AUC lomitapide mesylate (4-10- fold) | Co-administration of lomitapide mesylate with diltiazem is contraindicated (see 2 CONTRAINDICATIONS) |
| Other antiarrhythmic agents | T | ↑ antiarrhythmic effect | Since diltiazem has antiarrhythmic properties, its concomitant prescription with other antiarrhythmic agents is not recommended (additive risk of increased cardiac adverse effects). This combination should only be used under close clinical and ECG monitoring. |
| Phenytoin | C | ↑ phenytoin plasma concentration | When co-administered with phenytoin, diltiazem may increase phenytoin serum concentration, in some cases, two to three-fold, as reported in spontaneous case reports. Signs and symptoms of phenytoin toxicity include nystagmus, ataxia, dysarthria, tremor, hyperreflexia, somnolence, drowsiness, lethargy, slurred speech, blurred vision, nausea and vomiting. Caution should be exercised when diltiazem and phenytoin are co-administered. It is recommended that the phenytoin serum concentration be monitored. |
| Rifampicin | CT | ↓ diltiazem plasma concentration | Administration of diltiazem with rifampicin markedly reduced plasma diltiazem concentrations and the therapeutic effect of diltiazem. Patients should be carefully monitored when initiating or discontinuing rifampicin therapy. |
| Short and Long Acting Nitrates | T | ↑ vasodilating effect | Increased hypotensive effects and faintness (additive vasodilating effects) are observed when nitrates are co-administered with Calcium Channels Inhibitors. In patients treated with calcium antagonists, the prescription of nitrate derivatives should only be carried out gradually at increasing doses due to increased hypotensive effects. |
Statins (lovastatin, pravastatin) | CT | ↑ lovastatin exposure No effect on pravastatin. | In a ten-subject study, coadministration of diltiazem with lovastatin resulted in a 3-4 times increase in mean lovastatin AUC and Cmax versus lovastatin alone; no change in pravastatin AUC and Cmax was observed during diltiazem coadministration. Diltiazem plasma levels were not significantly affected by lovastatin or pravastatin. |
| Strong inhibitors of CYP3A4 (e.g., ketoconazole, itraconazole, ritonavir, clarithromycin) | T | ↑ diltiazem plasma concentration | Strong CYP3A4 inhibitors may significantly increase the plasma concentrations of diltiazem. Diltiazem should therefore be used with caution together with these agents and monitoring of therapy is required. Appropriate dosage adjustment of diltiazem may be necessary. |
| Theophylline | T | ↑ anti- | Increased antihypertensive |
| hypertensive | effects. | ||
| X-Ray Contrast Media | T | ↑ hypotension ↑ bradycardia ↑ heart conduction disorder | Cardiovascular effects of an intravenous bolus of an X-ray contrast media, such as hypotension, bradycardia, and heart conduction disorders, may be increased in patients treated with diltiazem. Special caution is required in patients receiving concomitantly diltiazem and X-ray contrast media. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Calcium Antagonists (verapamil, nifedipine)
Limited clinical experience suggests that in certain severe conditions not responding adequately to verapamil or to nifedipine, using diltiazem in conjunction with either of these drugs may be beneficial.
9.5 Drug-Food Interactions
Grapefruit Juice
Grapefruit Juice may increase the plasma concentrations of orally administered diltiazem in some patients. The proposed mechanism is inhibition of CYP450 3A4-mediated first-pass metabolism in the gut wall by certain compounds present in grapefruit.
Patients who regularly consume grapefruit or grapefruit juice should be monitored for increased adverse effects of diltiazem such as headache, irregular heartbeat, edema, unexplained weight gain, and chest pain. Grapefruit and grapefruit juice should be avoided if an interaction is suspected.
Multivitamins with minerals
Calcium-containing products may decrease the effectiveness of calcium channel blockers by saturating calcium channels with calcium. Calcium chloride has been used to manage acute severe verapamil toxicity. Monitoring of the effectiveness of calcium channel blocker therapy is advised during co-administration with calcium products.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The therapeutic effect of this group of drugs is believed to be related to their specific cellular action of selectively inhibiting transmembrane influx of calcium ions into cardiac muscle and vascular smooth muscle. The contractile processes of these tissues are dependent upon the movement of extracellular calcium into the cells through specific ion channels. Diltiazem blocks transmembrane influx of calcium through the slow channel without affecting to any significant degree the transmembrane influx of sodium through the fast channel. This results in a reduction of free calcium ions available within cells of the above tissues. Diltiazem does not alter total serum calcium.
Angina
The precise mechanism by which diltiazem relieves angina has not been fully determined but it is believed to be brought about largely by its vasodilator action.
In angina due to coronary spasm, diltiazem increases myocardial oxygen delivery by dilating both large and small coronary arteries and by inhibiting coronary spasm at drug levels which cause little negative inotropic effect. The resultant increases in coronary blood flow are accompanied by dose dependent decreases in systemic blood pressure and decreases in peripheral resistance.
In angina of effort, it appears that the action of diltiazem is related to the reduction of myocardial oxygen demand. This is probably caused by a decrease in blood pressure brought about by the reduction of peripheral resistance and of heart rate.
Hypertension
The antihypertensive effect of diltiazem is believed to be brought about largely by its vasodilatory action on peripheral blood vessels with resultant decrease in peripheral vascular resistance.
10.2 Pharmacodynamics
Diltiazem produces antihypertensive effects both in the supine and standing positions. Resting heart rate is usually slightly reduced. During dynamic exercise, increases in diastolic pressure are inhibited while maximum achievable systolic pressure is usually unaffected. Heart rate at maximum exercise is reduced.
Studies to date, primarily in patients with normal ventricular function, have shown that cardiac output, ejection fraction and left ventricular end-diastolic pressure have not been affected.
Chronic therapy with diltiazem produces no change, or a decrease, in circulating plasma catecholamines. However, no increased activity of the renin-angiotensin-aldosterone axis has been observed. Diltiazem inhibits the renal and peripheral effects of angiotensin II.
In man intravenous diltiazem in doses of 20 mg prolongs AH conduction time and AV node functional and effective refractory periods by approximately 20%. Chronic oral administration of diltiazem in doses up to 540 mg per day has resulted in small increases in PR interval. Second degree and third-degree AV block have been observed (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular). In patients with sick sinus syndrome, diltiazem significantly prolongs sinus cycle length (up to 50% in some cases).
10.3 Pharmacokinetics
Diltiazem is considered to be a moderate inhibitor of CYP3A4, increasing the exposure of oral midazolam, a selective substrate of CYP3A4, by 3.8-fold. In an in vitro study, diltiazem was both a substrate and inhibitor of the efflux transporter, P-glycoprotein (P-gP). Co-administration of diltiazem with the P-gp probe substrate, digoxin, increased plasma concentrations and exposure of digoxin by approximately 20% and 40%, respectively.
Single oral doses of 30 to 120 mg of diltiazem hydrochloride immediate release tablets result in detectable plasma levels within 30 to 60 minutes and peak plasma levels 2 to 4 hours after drug administration. There is a departure from linearity of accumulation of diltiazem when diltiazem hydrochloride tablets are administered to steady state in normal subjects. A 240 mg daily dose (60 mg QID) gave plasma levels 2.3 times higher than a 120 mg daily dose (30 mg QID) and a 360 mg daily dose (90 mg QID) had levels 1.7 times higher than the 240 mg daily dose.
A study which compared patients with normal hepatic function to liver cirrhosis patients noted an increase in half-life and a 69% increase in bioavailability in the hepatically impaired patients. A single dose study in patients with severely impaired renal function showed no difference in the half-life of diltiazem as compared to patients with normal renal function (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
Absorption
Diltiazem is well absorbed from the gastrointestinal tract and is subject to an extensive first-pass effect giving absolute bioavailability (compared to intravenous dosing) of about 40%.
Distribution
Therapeutic blood levels appear to be in the 50 to 200 ng/mL range and the plasma elimination half-life (beta-phase) following single or multiple drug administration is approximately 3.5 to 6.0 hours. In vitro human serum binding studies revealed that 70 to 80% of diltiazem is bound to plasma proteins.
Metabolism
Diltiazem undergoes extensive hepatic metabolism in which only 2 to 4% of the drug appears unchanged in the urine and 6 to 7% appears as metabolites. The metabolic pathways of diltiazem include N- and O-demethylation (via cytochrome P450), deacetylation (via plasma and tissue esterases), in addition to conjugation (via sulfation and glucuronidation). In vitro studies have demonstrated that CYP 3A4 is the principal CYP isoenzyme involved in N-demethylation. The major metabolite, desacetyl diltiazem, is present in the plasma at levels 10 to 20% of the parent drug and is 25 to 50% as potent as diltiazem in terms of coronary vasodilation.
Elimination
Diltiazem undergoes extensive hepatic metabolism in which only 2 to 4% of the drug appears unchanged in the urine and 6 to 7% appears as metabolites. The apparent elimination half-life after single or multiple dosing is 5 to 8 hours.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature 15°C - 30°C.
AA-DILTIAZ should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance:
Proper name: Diltiazem Hydrochloride
Chemical name: 1 ,5-benzothiazepin-4(5H)-one,3-(acetyloxy)-5-[2-(dimethylamino) ethyl]-2,3-dihydro-2-(4-methoxyphenyl)-, monohydrochloride, (+)-cis
Molecular formula and molecular mass: C22H26N2O4S·HCl and 450.98 g/mol
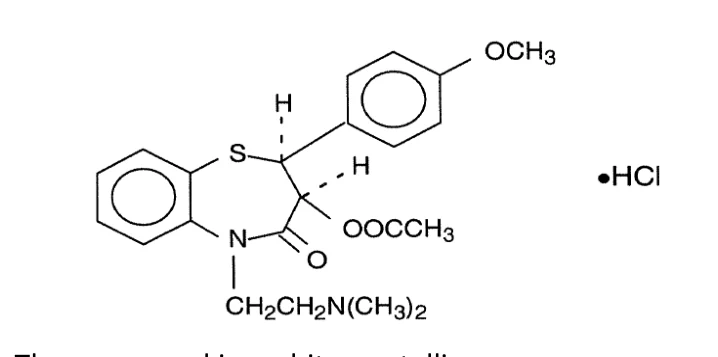
Structural formula:
Physicochemical properties: The compound is a white crystalline substance or powder having a bitter taste or odour. Diltiazem is considered freely soluble in water, methanol or chloroform, slightly soluble in absolute ethanol and barely soluble in benzene.
14 CLINICAL TRIALS
14.2 Comparative Bioavailability Studies
AA-DILTIAZ vs. Cardizem
A single dose, two-way crossover, single dose (60 mg dose as 1 x 60 mg), comparative oral bioavailability study of AA-DILTIAZ (AA Pharma Inc.) and Cardizem® (Nordic Laboratories, Inc.) was conducted in healthy, male volunteers under fasting conditions. Comparative bioavailability data from 27 volunteers that were included in the statistical analysis are presented in the following table:
Diltiazem (1 x 60 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 95% Confidence Interval |
AUCT (ng·h/mL) | 474.3 474.7(25) | 463.9 463.6 (21) | 102.2 | 95.0 – 109.4 |
CMAX (ng/mL) | 132.5 132.4 (33) | 130.6 130.7 (24) | 101.4 | 89.0 – 113.8 |
Tmax3 (h) | 3.50 (2.50 - 5.00) | 3.00 (2.50 - 4.00) | ||
T½ 4 (h) | 1.97 (27) | 2.41 (39) | ||
1 AA-DILTIAZ (diltiazem hydrochloride) tablets, 60 mg (AA Pharma Inc.)
2 Cardizem® (diltiazem hydrochloride) tablets, 60 mg (Nordic Laboratories, Inc.)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%)
A two-way, multiple dose (1 x 60 mg administered three times daily for 6 days, followed by a final dose administered on the 7th day), steady-state crossover comparative oral bioavailability study of AA-DILTIAZ (AA Pharma Inc.) and Cardizem® (Nordic Laboratories, Inc.) was conducted in healthy, male volunteers under fasting conditions. Comparative bioavailability data from 27 volunteers that were included in the statistical analysis are presented in the following table:
Diltiazem (1 x 60 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 95% Confidence Interval |
AUC0-15 (ng·h/mL) | 1046.5 1047.6 (20) | 1046.0 1042.7 (23) | 100.0 | 93.9 – 106.1 |
CMAX (ng/mL) | 239.8 239.5 (21) | 241.6 240.8 (22) | 99.3 | 93.2 – 105.3 |
Tmax3 (h) | 3.00 (0.50 - 4.00) | 3.00 (0.00 - 4.00) | ||
T½ 4 (h) | 1.6 (31) | 1.48 (19) | ||
1 AA-DILTIAZ (diltiazem hydrochloride) tablets, 60 mg (AA Pharma Inc.)
2 Cardizem® (diltiazem hydrochloride) tablets, 60 mg (Nordic Laboratories, Inc.)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%)
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Table 3: Acute Toxicity
| Route | Animal | Sex | LD50(mg/kg) | LD50 95% Confidence Limits (mg/kg) | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Oral | mice | M&F | 415 – 700 | (343 – 736) | |||||||
| rats | M&F | 560 – 810 | (505 – 1004) | ||||||||
| s.c | mice | M&F | 260 – 550 | (220 – 672) | |||||||
| i.p. | mice | M&F | 187 | (165 – 211) | |||||||
| rats | M&F | 211 | (155 – 287) | ||||||||
| i.v. | mice | M&F | 58 – 61 | (52 – 69) | |||||||
| rats | M&F | 38 – 39 | (34 – 44) | ||||||||
Toxic effects appeared rapidly, and toxicity included reduction of spontaneous activity, ptosis, piloerection, ataxia, loss of muscle tone, and loss of righting reflex. Gross autopsy of animals that died as well as the survivors revealed no abnormalities.
Tolerance was evaluated in rabbits and dogs. Dogs received oral doses of 12.5, 25, 50 or 100 mg/kg. Ataxia, disorientation, decreased activity, diuresis, and mydriasis were noted at 25 mg/kg. In addition, heavy sedation and emesis were seen at 50 mg/kg. At 100 mg/kg, convulsions occurred, and one of the two animals died. Rabbits received 100, 200, 300 and 400 mg/kg. The major symptoms were decreased activity, increased respiration, salivation and opisthotonos. One of the two rabbits died at 300 mg/kg and the two rabbits in the 400 mg/kg group died.
Subacute Toxicity
In rats, oral doses of 10, 20, 50, 100, 250 or 500 mg/kg/day of diltiazem were administered for 28 or 30 days. The relative liver weights of animals receiving 250 mg/kg/day, and 500 mg/kg/day were increased. Microscopic examination revealed drug related degeneration of hepatic and renal cells in the highest dose group.
When the drug was given to rats intraperitoneally at 25 mg/kg/day for 30 days, hepatic and renal cell degeneration was seen. Macular hyaloid degeneration of the heart also was seen in 50% of the rats in this study.
Thirty-day subacute studies in dogs revealed hepatic and renal cell degeneration when diltiazem was given at doses of 25 mg/kg/day orally and 5 mg/kg/day intravenously. Two dogs out of 5 receiving 50 mg/kg/day orally, died.
Carcinogenicity
In mice, diltiazem was administered at doses of 5, 15 or 30 mg/kg/day for a period of 21 months in females. Because of a lower survival, males were terminated at 20 months. Gross and histopathological examination failed to reveal any treatment related increase in the incidence of either neoplastic or other toxic lesions.
Rats received 6.25, 25 or 100 mg/kg/day of diltiazem for 24 months. An additional group received 200 mg/kg for 12 months. Treatment was terminated at 23 months in females receiving 100 mg/kg because of the low survival. Females had increased weight gain at 100 and 200 mg/kg; food consumption was increased among both sexes at these dose levels. Organ weight data revealed a significant increase in liver weight for rats of both sexes given 200 mg/kg. Microscopic evaluation revealed some evidence of dose dependent hepatic cytoplasmic vacuolization in rats treated with doses of 100 and 200 mg/kg/day and killed at 12 months. At 24 months, there were similar findings in control and treated animals. There was no increase in the incidence of neoplastic or other toxic lesions in rats treated with diltiazem.
Diltiazem was administered orally to dogs for 12 months at doses of 5, 10, 20 mg/kg/day. A dose related suppression of body weight gain became noticeable after 6 months.
Mutagenicity
No mutagenic changes were observed in the recombination test and two Ames reverse mutagenicity assays.
Reproductive and Developmental Toxicology
Table 4: Results in mice
| Route | Doses (mg/kg) | Time of administration during gestation | Findings in the offspring |
|---|---|---|---|
| Route | Doses (mg/kg) | Time of administration during gestation | Findings in the offspring |
| Oral | 10, 25, 50, 100, 200, 400 | Day 7 to day 12 | High incidence of vertebral column malformations when more than 50 mg/kg was administered. |
| Oral | Single doses of 12.5, 25, 50, 100, 200 | One of days 7 to 14 | Cleft palate and malformation of extremities or trunk were significantly higher when 50 or 100 mg/kg was administered on day 12. Vertebral malformations were most prevalent when 50 or 100 mg/kg was administered on day 9. |
| intra-peritoneal | 0.2, 3.1, 6.3, 12.5, 25 | Day 7 to day 12 | Fetal mortality greatly increased when 12.5 mg/kg or more was administered. No teratogenic effect was demonstrated. |
| intra-peritoneal | Single doses of 3.1, 6.3, 12.5, 25, 50 | One of days 5 to 16 | Brachydactyly and hematoma in the extremities when 50 mg/kg was administered on day 13. Vertebral column malformations from the thoracic to coccygeal level and malformations of the ribs were observed when a dose of 25 mg/kg or greater was administered on day 9. |
| Oral | 10, 50, 100, 200, 400 | Day 9 to 14 | No teratogenic effect. High fetal death rate when 200 & 400 mg/kg was administered. |
| Oral | 10, 30, 100 | Day 6 to 15 | No teratogenic effect. |
| Oral | Single doses of 300, 400, 600 | On one of days 9 to 14 | Significant incidence of skeletal malformations involving vertebrae & sternebrae when 400 mg/kg was administered on day 11. General edema, short or absent tail was observed when 600 mg/kg was administered on day 12. |
| intra-peritoneal | 0.2, 2.0, 20, 40, 80 | Day 9 to 14 | Brachydactyly & hematoma in the front paw and tail and a high fetal mortality rate were observed when 80 mg/kg was administered. |
| intra-peritoneal | 80 | Day 9 to 11 | Vertebral anomalies. |
| intra-peritoneal | 80 | Day 12 to 14 | Brachydactyly, hematoma of the front paw and tail deformities and high fetal mortality rate. |
| intra-peritoneal | Single dose of 80 | One of days 9 to 14 | Fetal mortality increased on day 11 reached 100% on day 12 and decreased thereafter. Limb and tail deformities were induced when 80 mg/kg was administered on day 13 & 14. Vertebral column deformities were induced when 80 mg/kg was administered on day 11. |
| Single dose of 40 | One of days 11 to 14 | No teratogenic effect. | |
| Oral | 17.5, 35, 70 | Day 6 to 18 | Significant increase in skeletal malformations occurred when 35 mg/kg was administered. All pregnant dams aborted between days 21 and 25 of gestation when 70 mg/kg was administered. |
| intra-peritoneal | 6.3, 12.5, 25 | Day 7 to 16 | Fetal mortality greatly increased at 12.5 mg/kg and reached 100% at 25 mg/kg. Skeletal defects and external malformations were induced when 12.5 mg/kg was administered. Their incidence was not statistically significant due to the low number of surviving fetuses. |
In fertility studies, female rats received doses of 12.5, 25, 50 and 100 mg/kg p.o. In the 100 mg/kg group, there was a reduction in the number showing a positive mating. However, the overall pregnancy rates and the average pre-coital time were comparable.
In peri- and post-natal studies, rats received diltiazem in doses of 10, 30 or 100 mg/kg/day from day 14 of gestation through day 21 postpartum. Diltiazem was associated with a reduction in early individual weights and survival rates of the pups. At 100 mg/kg/day, dystocia was evident. Retinal and tongue malformations were more frequent in the offspring of the 30 and
100 mg/kg/day group.
In Vitro Observations
Initial experimental work revealed that diltiazem was a coronary and peripheral vasodilator. Subsequent work substantiated that diltiazem's smooth muscle relaxant effect, as well as negative inotropic effect, resulted from the drug's ability to block excitation-contraction coupling by inhibiting slow calcium channel conduction. In a muscle bath study with isolated human coronary artery segments obtained at the time of cardiac transplantation, diltiazem produced nearly complete relaxation of potassium-contracted segments.
Studies in various experimental models have confirmed the negative inotropic effect of diltiazem. At low doses (1.1 x 10⁻⁷M) diltiazem caused a reduction in contractile force of guinea pig papillary muscle with no demonstrable effect on the action potential. However, at higher concentrations (1.1 x 10⁻⁵M) both a decrease in contractile tension and a lowering of maximum dp/dt were seen.
Studies done in isolated perfused rat hearts showed that diltiazem (10-6M) decreases contractility without affecting action potential duration or resting membrane potential. In several experimental models it has been shown that the concentration of diltiazem required to produce smooth muscle relaxation and vasodilation is significantly less than the concentration required to produce a negative inotropic effect.
In Vivo Observations
Pharmacodynamics
Experiments in both open and closed chest dog models indicate that diltiazem increases coronary blood flow and reduces coronary vascular resistance. Intravenous diltiazem (100 mcg/kg) increased coronary blood flow by 90%, with a predominant effect on large coronary arteries and collaterals. Increase in coronary blood flow has also been shown following diltiazem administration in both the epicardial and subendocardial regions in ischemic and non- ischemic models. There was also a dose-related decrease in mean aortic pressure and systemic vascular resistance with an increase in stroke volume and cardiac output. No significant change was noted in determinants of LV function such as LVEDP or LV dP/dT. The reduction in blood pressure that is seen with diltiazem is due to a direct vasodilatory effect on the blood vessels and is not mediated by sympathetic alpha receptor blockade, beta receptor stimulation, or ganglionic blockade. Diltiazem has been shown to inhibit the pressor responses induced by norepinephrine and angiotensin II.
In animal studies, the negative inotropic effect of diltiazem appears to be offset by its ability to decrease afterload and induce a mild reflex adrenergic response.
Pharmacokinetics
The effect of diltiazem on the pharmacokinetics of phenytoin was investigated in rats. Animals were given 20 mg/kg i.p. phenytoin alone or phenytoin together with 5 mg/kg i.p. diltiazem and the plasma samples were collected at different time intervals. The study showed that diltiazem significantly (p<0.05) increased phenytoin AUC (4-fold), Cmax (2-fold), and elimination half-life (t½: from 1.1h to 2.0h), in the rat.
17 SUPPORTING PRODUCT MONOGRAPHS
1 CARDIZEM® CD (Diltiazem Hydrochloride Controlled Delivery Capsules, 120 mg, 180 mg, 240 mg and 300 mg), submission control 291522, Product Monograph, Bausch Health, Canada Inc. (MAR 25, 2025)