


Product Monograph - AG-Citalopram Tablets (Angita Pharma, 10 mg, 20 mg, 40 mg)
Recent Major Label Changes
| 3 Serious Warnings and Precautions Box | 12/2025 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ……………………………………………………………………………………………….2
Table of Contents ................................................................................................................ 2
Part 1: Healthcare Professional Information ......................................................................... 5
1 Indications ............................................................................................................... 5
1.1 Pediatrics ................................................................................................................. 5
1.2 Geriatrics .................................................................................................................. 5
2 Contraindications ..................................................................................................... 5
3 Serious Warnings and Precautions Box ..................................................................... 6
4 Dosage and Administration ...................................................................................... 6
4.1 Dosing Considerations ............................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ........................................................ 7
4.2.1. Discontinuing Treatment ......................................................................................... 8
4.4 Administration ......................................................................................................... 9
4.5 Missed Dose ............................................................................................................. 9
5 Overdose.................................................................................................................. 9
6 Dosage Forms, Strengths, Composition and Packaging ............................................. 11
7 Warnings and Precautions ....................................................................................... 11
General ............................................................................................................................. 11
Carcinogenesis and Genotoxicity ..................................................................................... 11
Cardiovascular .................................................................................................................. 12
Driving and Operating Machinery.................................................................................... 12
Endocrine and Metabolism .............................................................................................. 13
Hematologic ..................................................................................................................... 13
Hepatic/Biliary/Pancreatic ............................................................................................... 13
Musculoskeletal ............................................................................................................... 14
Neurologic ........................................................................................................................ 14
Ophthalmologic................................................................................................................ 15
Psychiatric ........................................................................................................................ 15
Renal ………………………………………………………………………………………………………………………….17
Reproductive Health ........................................................................................................ 17
7.1 Special Populations ................................................................................................ 18
7.1.1 Pregnancy .............................................................................................................. 18
7.1.2 Breastfeeding ......................................................................................................... 19
7.1.3 Pediatrics ............................................................................................................... 19
7.1.4 Geriatrics ................................................................................................................ 19
8 Adverse Reactions ................................................................................................... 20
8.1 Adverse Reaction Overview ................................................................................... 20
8.2 Clinical Trial Adverse Reactions ............................................................................. 20
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ......................................................... 25
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 25
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics .................................. 25
8.5 Post-Market Adverse Reactions ............................................................................ 25
9 Drug Interactions ..................................................................................................... 27
9.1 Serious Drug Interactions ...................................................................................... 27
9.2 Drug Interactions Overview ................................................................................... 27
9.3 Drug-Behaviour Interactions ................................................................................. 30
9.4 Drug-Drug Interactions .......................................................................................... 30
9.5 Drug-Food Interactions .......................................................................................... 33
9.6 Drug-Herb Interactions .......................................................................................... 34
9.7 Drug-Laboratory Test Interactions ........................................................................ 34
10 Clinical Pharmacology .............................................................................................. 34
10.1 Mechanism of Action ............................................................................................. 34
10.2 Pharmacodynamics ................................................................................................ 34
10.3 Pharmacokinetics ................................................................................................... 34
11 Storage, Stability, and Disposal ................................................................................ 36
Part 2: Scientific Information .............................................................................................. 37
13 Pharmaceutical Information .................................................................................... 37
14 Clinical Trials ........................................................................................................... 38
14.1 Clinical Trials by Indication .................................................................................... 38
Symptomatic Relief of Depressive Illness ........................................................................ 38
14.2 Comparative Bioavailability Studies ...................................................................... 40
16 Non-Clinical Toxicology ............................................................................................ 41
17 Supporting Product Monographs ............................................................................. 45
Patient Medication Information .......................................................................................... 46
Part 1: Healthcare Professional Information
1 Indications
AG-Citalopram Tablets (citalopram tablets) is indicated for:
- the symptomatic relief of depressive illness in adults
The relapse rate was significantly lower in citalopram tablets treated patients than in placebo-treated patients in two placebo-controlled studies that were conducted over a 24-week period in patients who responded to 6 or 8 weeks of acute treatment with citalopram tablets (see 14.1 Clinical Trials by Indication). Nevertheless, the physician who elects to use AG-Citalopram Tablets for extended periods should periodically re-evaluate the long-term usefulness of the drug for the individual patient.
1.1 Pediatrics
Pediatrics (<18 years of age): AG-Citalopram Tablets is not indicated for use in patients below the age of 18 (see 7 Warnings and Precautions, Psychiatric, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety and effectiveness (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics and 7.1.4 Geriatrics).
2 Contraindications
- AG-Citalopram Tablets is contraindicated in patients who are hypersensitive to citalopram hydrobromide or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
Monoamine Oxidase Inhibitors
Cases of serious reactions have been reported in patients receiving selective serotonin reuptake inhibitors (SSRIs) in combination with a monoamine oxidase inhibitor (MAOI) or the reversible MAOI (RIMA), moclobemide, and in patients who have recently discontinued an SSRI and have been started on a MAOI (see 9.2 Drug Interactions Overview, Monoamine Oxidase Inhibitors). With the co-administration of an SSRI with MAOI, there have been reports of serious, sometimes fatal reactions including hyperthermia, rigidity, myoclonus, autonomic instability with possible fluctuations of vital signs, and mental status changes, including extreme agitation progressing to delirium and coma. Some cases presented with features resembling serotonin syndrome.
Therefore, citalopram should not be used in combination with a MAOI or within 14 days of discontinuing treatment with a MAOI, (including linezolid, an antibiotic which is a reversible non-selective MAO inhibitor and methylene blue, which is a MAOI). Similarly, at least 14 days should elapse after discontinuing citalopram treatment before starting a MAOI.
Pimozide
Citalopram should not be used in combination with the antipsychotic drug pimozide, as results from a controlled study indicate that concomitant use is associated with an increased risk of QTc prolongation compared to pimozide alone. This apparent pharmacodynamic interaction occurred in the absence of a clinically significant pharmacokinetic interaction; the mechanism is unknown (see 9.2 Drug Interactions Overview, Drugs That Prolong the QT Interval).
QT Prolongation
AG-Citalopram Tablets is contraindicated in patients with known QT interval prolongation or with congenital long QT syndrome. (see 7 Warnings and Precautions, QT Prolongation and Torsades de Pointes; 8.5 Post-Market Adverse Reactions; 9.2 Drug Interactions Overview, Drugs That Prolong the QT Interval; 4 Dosage and Administration; 5 Overdose).
3 Serious Warnings and Precautions Box
|
|---|
4 Dosage and Administration
4.1 Dosing Considerations
- Pediatrics: AG-Citalopram Tablets is not indicated for use in children under 18 years of age. See 7 Warnings and Precautions, Psychiatric, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
- Pregnant Women: AG-Citalopram Tablets should not be used during pregnancy unless the benefits markedly outweigh the risks, particularly during the third trimester as there are implications for neonatal health. See 7.1.1 Pregnancy.
- Elderly - Use lower doses. Advise elderly patients of increased risk of falls. Elderly women are at increased risk of hyponatraemia, SIADH. See 7.1.4 Geriatrics
Reduced dosing: Use lower initial (10 mg) and maximum (20 mg) daily doses for:
- elderly patients,
- patients with mild to moderate hepatic impairment,
- CYP2C19 poor metabolizers, or those taking cimetidine, omeprazole or other CYP2C19 inhibitors, due to the risk of QT interval prolongation.
Proceed with caution in patients with:
- severe hepatic impairment,
- severe renal impairment.
- a pre-existing slow heart rate.
Interactions (See 9. Drug Interactions)
- Do not co-administer with Monoamine Oxidase Inhibitors (contraindicated). Allow at least 14 days to elapse when switching to or from a MAOI.
- Do not co-administer with pimozide (contraindicated), or escitalopram.
Avoid or use caution if patient is concomitantly using:
- other CNS medications,
- other serotonergic agents,
- drugs that prolong QT interval,
- drugs that affect platelet function, or
- drugs that cause hyponatraemia, or
- alcohol.
- Reduce dosage gradually. Do not abruptly discontinue medication. Taper gradually when reducing dose or ending SSRI treatment, and monitor for discontinuation symptoms.
4.2 Recommended Dose and Dosage Adjustment
Adults (<65 years of age)
AG-Citalopram Tablets should be administered once daily, in the morning or evening, with or without food:
- Usual adult dose: 20 mg/day, orally.
- Titration: Dose increases should usually occur at least a week apart.
- Maximum dose: 40 mg/day (if needed, and tolerated), due to the risk of QT prolongation.
- Use lowest effective dose and reassess periodically.
Maintenance Treatment
Evaluation of citalopram tablets in two placebo-controlled studies has shown that its antidepressant efficacy was maintained for periods of up to 24 weeks, following 6 or 8 weeks of initial treatment (total of 32 weeks) (see 14.1 Clinical Trials by Indication). In the flexible dose study, the great majority of patients were receiving 20 or 40 mg/day doses both at 12 and 24 weeks. During maintenance therapy, the dosage should be kept at the lowest effective level and patients should be periodically reassessed to determine the need for continued treatment.
Switching Patients To or From a MAOI
At least 14 days should elapse between discontinuation of a MAOI and initiation of therapy with AG-Citalopram Tablets. Similarly, at least 14 days should be allowed after stopping AG-Citalopram Tablets before starting a MAOI (see 2 Contraindications, Monoamine Oxidase Inhibitors).
4.2.1. Discontinuing Treatment
Discontinuation Symptoms
Adverse events are common when a SSRI dose is reduced or treatment is discontinued, particularly if discontinuation is abrupt. Dizziness, sensory disturbances (including paraesthesia, e.g. electric shock sensations), sleep disturbances (including insomnia and intense dreams), agitation or anxiety, nausea and/or vomiting, tremor and headache are the most commonly reported reactions. See a more complete list under 8.2 Clinical Trial Adverse Reactions, Adverse Reactions following Discontinuation of Treatment (or Dose Reduction).
Discontinuation symptoms usually occur within the first few days after stopping treatment, but there have been very rare reports of such symptoms in patients who have inadvertently missed a dose.
The risk of symptoms may be dependent on several factors, including the duration and dose of therapy as well as the rate of dose reduction.
Generally, discontinuation symptoms are mild to moderate and usually resolve within 2 weeks. However, in some patients they may be severe in intensity and may be prolonged (2-3 months or more).
Discontinuation of Treatment with Citalopram
Treatment with SSRIs including citalopram should NOT be discontinued abruptly, due to the risk of discontinuation symptoms.
Whenever possible, AG-Citalopram Tablets treatment should be discontinued gradually over a period of several weeks or months.
Patients should be monitored for discontinuation. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, dose titration should be managed on the basis of the patient’s clinical response (See 8.2 Clinical Trial Adverse Reactions, Adverse Reactions following Discontinuation of Treatment (or Dose Reduction)
Special Populations
Pediatrics (<18 years of age):
Health Canada has not authorized an indication for pediatric use.
Geriatrics (≥65 years of age):
A longer half-life and decreased clearance have been demonstrated in the elderly, therefore lower doses and a lower maximum dose should be considered. It may be desirable to start at 10 mg daily and titrate upwards as needed and tolerated. A single oral dose of 20 mg/day is the recommended dose for most elderly patients. Some patients may respond to a 10 mg/day dose (see
7.1.4 Geriatrics). The dose may be titrated to a maximum of 20 mg/day if needed and tolerated. As with other SSRIs, caution should be exercised in treating elderly female patients who may be more susceptible to adverse events such as hyponatremia and SIADH (syndrome of inappropriate antidiuretic hormone secretion). See 7 Warnings and Precautions, Diabetic patients, Hyponatraemia. See also 10.3 Pharmacokinetics, Geriatrics.
Hepatic Impairment
Dosages should be restricted to the lower end of the dose range in patients with mild to moderate hepatic insufficiency. Accordingly, an initial single oral dose of 10 mg daily is recommended. Subsequently, the dose may be increased based on the patient’s response and clinical judgement. Patients with reduced hepatic function should receive dosages of no more than 20 mg/day (see 7 Warnings and Precautions, Hepatic Impairment). Citalopram should be used with additional caution in patients with severe hepatic impairment.
Renal Impairment
No dosage adjustment is necessary for patients with mild to moderate renal impairment. Since there is no information available on the pharmacokinetic or pharmacodynamic effects of citalopram tablets in patients with severe renal impairment, AG-Citalopram Tablets should be used with caution in these patients.
CYP2C19 Poor Metabolisers
An initial dose of 10 mg daily during the first two weeks of treatment is recommended for patients who are known to be poor metabolisers of CYP2C19. The dose may be increased to a maximum of 20 mg daily depending on individual patient response (see 10.3 Pharmacokinetics, Metabolism). AG-Citalopram Tablets 20 mg/day is also the maximum recommended dose for patients taking concomitant CYP2C19 inhibitors (e.g. cimetidine) because of the risk of QT prolongation.
4.4 Administration
AG-Citalopram Tablets should be administered once daily, in the morning or evening, with or without food.
4.5 Missed Dose
In the event that a dose is missed, the patient should skip the missed dose and should take the next dose when it is due.
5 Overdose
In clinical trials with racemic citalopram, there were no reports of fatal citalopram overdoses of up to 2000 mg. All patients recovered. Events of torsade de pointes have been reported during overdose with citalopram tablets during post-market use (see 2 Contraindications; 7 Warnings and Precautions, QT Prolongation and Torsades de Pointes; 8.5 Post Market Adverse Reactions; 9.2 Drug Interactions Overview, Drugs That Prolong the QT Interval; 4 Dosage and Administration). When specified, these overdoses were in the range of 800-1000 mg.
Comprehensive clinical data on citalopram overdose are limited and many cases involve concomitant overdoses of other drugs and/or alcohol. Fatal cases of citalopram overdose have been reported with citalopram alone; however, the majority of fatal cases have involved overdose with concomitant medications. Post-marketing reports of drug overdoses involving citalopram have included fatalities with citalopram alone as well as non-fatal overdoses of up to 5200 mg.
Although most patients recovered without sequelae, 3 fatalities with known overdoses of racemic citalopram alone have been reported in the literature (doses of 2800 mg, 2880 mg, and 3920 mg).
Fatal cases of serotonin syndrome have been reported in patients who took overdoses of moclobemide and citalopram tablets (see 7 Warnings and Precautions: Neurologic).
Serotonin Toxicity/Neuroleptic Malignant Syndrome (NMS). The plasma concentrations of moclobemide were between 16 and 90 mg/L (therapeutic range: 1 to 3 mg/L) and those of citalopram tablets between 0.3 and 1.7 mg/L (therapeutic concentration: 0.3 mg/L). This indicates that a relatively low dose of citalopram tablets, given with an overdose of moclobemide represents a serious risk for the patient.
The following symptoms have been seen in reported overdose of citalopram: agitation, atrial and ventricular arrhythmia, bradycardia, bundle branch block, cardiac arrest, confusion, convulsion, coma, cyanosis, dizziness, ECG changes, hyperventilation, hypotension, hypertension, loss of consciousness, mydriasis, nausea, QRS prolongation, QT prolongation, rhabdomyolysis, seizure, serotonin syndrome, somnolence, stupor, sweating, tachycardia, torsade de pointes, tremor, and vomiting.
Management of Overdose
Establish and maintain an airway to ensure adequate ventilation and oxygenation. Gastric lavage and use of activated charcoal should be considered. Gastric lavage should be carried out as soon as possible after oral ingestion. Cardiac and vital sign monitoring are recommended, along with general symptomatic and supportive measures. There are no specific antidotes for AG-Citalopram Tablets.
ECG monitoring is advisable in case of overdose.
Due to the large volume of distribution of citalopram tablets, forced diuresis, dialysis, hemoperfusion and exchange transfusion are unlikely to be of benefit.
In managing overdosage, the possibility of multiple drug involvement must be considered.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral |
| Croscarmellose sodium, crospovidone, glycerol, hypromellose, lactose monohydrate, macrogol 4000, magnesium stearate, maize starch, microcrystalline cellulose and titanium dioxide |
Description
AG-Citalopram Tablets is available as white to off white film-coated tablets:
10 mg: Each white to off white colored, oval shaped, scored, film coated tablets, imprinted “C” on one side and “10” on the other side. Available in bottles of 100 tablets.
20 mg: Each white to off white colored, oval shaped, scored, film coated tablets, imprinted on scored side with “N” on the left side and “C” on the right side, and imprinted on the non-scored side with “20”. Available in blister packs of 30 tablets (3x10 tablets) and in bottles of 100 and 500 tablets.
40 mg: Each white to off white colored, oval shaped, scored, film coated tablets, imprinted on scored side with “N” on the left side and “C” on the right side, and imprinted on the non-scored side with “40”. Available in blister packs of 30 tablets (3x10 tablets) and in bottles of 100 tablets.
7 Warnings and Precautions
See 3 Serious Warnings and Precautions Box.
General
Discontinuation of Treatment with Citalopram
Treatment with SSRIs, including citalopram, should NOT be discontinued abruptly, due to the risk of discontinuation symptoms (see 4.2.1 Discontinuing Treatment).
Carcinogenesis and Genotoxicity
For animal data, see 16 Non-Clinical Toxicology, Carcinogenicity and Genotoxicity.
Cardiovascular
Patients with Cardiac Disease
Citalopram has not been systematically evaluated in patients with a recent history of myocardial infarction or unstable heart disease. Patients with these diagnoses were generally excluded from clinical trials during the drug’s premarketing assessment.
In clinical trials, citalopram tablets caused small but statistically significant decreases in heart rate (see 8.2 Clinical Trial Adverse Reactions, Decreased Heart Rate). Consequently, caution should be observed when citalopram is initiated in patients with pre-existing slow heart rate.
QT Prolongation and Torsades de Pointes
Citalopram tablets can cause a dose-dependent increase in the QT interval (see 2 Contraindications, QT Prolongation; 8.5 Post-Market Adverse Reactions; 9.2 Drug Interactions Overview, Drugs That Prolong the QT Interval; 4 Dosage and Administration; 5. Overdose).
Events of torsade de pointes, ventricular fibrillation, cardiac arrest, and sudden death have been reported during post-marketing use of citalopram tablets. Torsade de pointes is a polymorphic ventricular tachyarrhythmia. Generally, the risk of torsade de pointes increases with the magnitude of QT/QTc prolongation produced by the drug. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
A randomized, double-blind, placebo- and positive-controlled, crossover study was performed in healthy subjects (N=119) to examine the effects of citalopram 20 mg/day and 60 mg/day on ECG intervals (individually corrected QTcNi interval) when administered according to an escalating multiple dose regimen (9 days at 20 mg/day, 4 days at 40 mg/day, 9 days at 60 mg/day). The maximum mean (upper bound of the 95% one-sided confidence interval) differences from placebo were 8.5 (10.8) and 18.5 (21.0) msec for 20 mg and 60 mg citalopram, respectively. The effects of the 40 mg/day dose were not studied, but are predicted to be approximately 13 msec (estimate value on QTcNI).
- AG-Citalopram Tablets should not be dosed above 40 mg/day.
- In patients who are CYP2C19 poor metabolizers or patients taking concomitant cimetidine or other CYP2C19 inhibitor, AG-Citalopram Tablets should not be dosed over 20 mg/day.
- Hypokalemia and hypomagnesemia should be corrected prior to initiation of treatment and periodically monitored.
- ECG monitoring is recommended in patients with risk factors for torsades de pointes, such as congestive heart failure, recent myocardial infarction, bradyarrhythmias, or patients on concomitant medications that prolong the QT interval or in patients with altered metabolism. e.g., liver impairment.
Driving and Operating Machinery
In studies in normal volunteers, citalopram tablets in doses of 40 mg/day did not impair cognitive function or psychomotor performance. However, psychotropic medications may impair judgement, thinking or motor skills. Consequently, patients should be cautioned against driving a car or operating hazardous machinery until they are reasonably certain that AG-Citalopram Tablets does not affect them adversely.
Endocrine and Metabolism
Diabetic Patients
Citalopram tablets have not been systematically evaluated in diabetic patients since diabetes constituted an exclusion criterion. Although 13 patients did receive insulin during the studies, this number is too small to determine whether citalopram tablets affect the response to insulin. Rare events of hypoglycemia were reported. Treatment with an SSRI in patients with diabetes may alter glycaemic control (hypoglycaemia and hyperglycaemia). AG-Citalopram Tablets should be used with caution in diabetic patients on insulin or other antidiabetic drugs.
Hematologic
Abnormal Bleeding
SSRIs and serotonin norepinephrine reuptake inhibitors (SNRIs), including AG-Citalopram Tablets, may increase the risk of bleeding events by causing abnormal platelet aggregation. Concomitant use of acetylsalicylic acid (ASA), nonsteroidal anti-inflammatory drugs (NSAIDs), warfarin and other anticoagulants may add to the risk. Case reports and epidemiological studies (case-control and cohort design) have demonstrated an association between use of drugs that interfere with serotonin reuptake and the occurrence of gastrointestinal bleeding. Bleeding events related to SSRIs and SNRIs use have ranged from ecchymoses, hematomas, epistaxis, and petechiae to life-threatening haemorrhages.
SSRIs/SNRIs, including AG-Citalopram Tablets, may increase the risk of postpartum haemorrhage (see 7.1.1 Pregnancy, Complications following late third trimester exposure to SSRIs).
Patients should be cautioned about the risk of bleeding associated with the concomitant use of AG-Citalopram Tablets and NSAIDs, ASA, or other drugs that affect coagulation (see 9.2 Drug Interactions Overview, Drugs Affecting Platelet Function (e.g., NSAIDs, ASA and other anticoagulants)). Caution is advised in patients with a history of bleeding disorder or predisposing conditions (e.g., thrombocytopenia).
Hepatic/Biliary/Pancreatic
Hepatic Impairment
In subjects with hepatic impairment, citalopram tablets clearance was significantly decreased and plasma concentrations, as well as elimination half-life significantly increased (see
10.3 Pharmacokinetics, Hepatic Insufficiency). Consequently, the use of AG-Citalopram Tablets in hepatically impaired patients should be approached with caution and a lower maximum dosage is recommended (see 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment).
Musculoskeletal
Bone Fracture Risk
Epidemiological studies show an increased risk of bone fractures following exposure to some antidepressants, including SSRIs/ SNRIs. The risks appear to be greater at the initial stages of treatment, but significant increased risks were also observed at later stages of treatment. The possibility of fracture should be considered in the care of patients treated with AG-Citalopram Tablets. Elderly patients and patients with important risk factors for bone fractures should be advised of possible adverse events which increase the risk of falls, such as dizziness and orthostatic hypotension, especially at the early stages of treatment but also soon after withdrawal.
Preliminary data from observational studies show association of SSRIs/SNRIs and low bone mineral density in older men and women. Until further information becomes available, a possible effect on bone mineral density with long term treatment with SSRIs/SNRIs, including AG-Citalopram Tablets, cannot be excluded, and may be a potential concern for patients with osteoporosis or major risk factors for bone fractures.
Neurologic
Seizures
Citalopram tablets have not been systematically evaluated in patients with a seizure disorder. These patients were excluded from clinical studies during the premarketing testing of citalopram tablets. In clinical trials, seizures occurred in 0.25% of patients treated with citalopram tablets and in 0.23% patients treated with placebo. Like other antidepressants, AG-Citalopram Tablets should be used with caution in patients with a history of seizure disorder. The drug should be discontinued in any patient who develops seizures.
Serotonin Toxicity/Neuroleptic Malignant Syndrome (NMS)
Serotonin toxicity, also known as serotonin syndrome, has been reported with citalopram tablets, particularly during combined use with other serotonergic drugs (see 9.4 Drug-Drug Interactions).
Serotonin toxicity is characterized by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature > 38°C and ocular clonus or inducible clonus
Neuroleptic malignant syndrome has also been rarely reported with citalopram tablets, particularly during combined use with neuroleptic/antipsychotic drugs. The clinical manifestations of neuroleptic malignant syndrome often overlap with those of serotonin toxicity, including hyperthermia, hypertonia, altered mental status, and autonomic instability. In contrast to serotonin toxicity, patients with neuroleptic malignant syndrome may present with “lead pipe” muscle rigidity as well as hyporeflexia.
The concomitant use of AG-Citalopram Tablets with monoamine oxidase inhibitors, including linezolid and methylthioninium chloride (methylene blue), is contraindicated (see 2 Contraindications, Monoamine Oxidase Inhibitors). AG-Citalopram Tablets should be used with caution in patients receiving other serotonergic drugs or antipsychotics/neuroleptics. If concomitant treatment with AG-Citalopram Tablets and other serotonergic drugs and/or antipsychotics/neuroleptics is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). Serotonin toxicity and neuroleptic malignant syndrome may result in potentially life-threatening conditions. If serotonin toxicity or neuroleptic malignant syndrome is suspected, discontinuation of AG-Citalopram Tablets should be considered.
Ophthalmologic
Angle-Closure Glaucoma
As with other antidepressants, AG-Citalopram Tablets can cause mydriasis, which may trigger an angle-closure attack in a patient with anatomically narrow ocular angles. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Psychiatric
POTENTIAL ASSOCIATION WITH BEHAVIORAL AND EMOTIONAL CHANGES, INCLUDING SELF-HARM:
- Pediatrics: Placebo-Controlled Clinical Trial Data
Recent analyses of placebo-controlled clinical trial safety databases from SSRIs and other newer anti-depressants suggest that use of these drugs in patients under the age of 18 may be associated with behavioral and emotional changes, including an increased risk of suicidal ideation and behavior over that of placebo.
The small denominators in the clinical trial database, as well as the variability in placebo rates preclude reliable conclusions on the relative safety profiles among these drugs.
- Adults and Pediatrics: Additional data
There are clinical trial and post marketing reports with SSRIs and other newer anti-depressants, in both pediatrics and adults, of severe agitation-type adverse events coupled with self-harm and harm to others. The agitation-type events include: akathisia, agitation, disinhibition, emotional lability, hostility, aggression and depersonalization. In some cases, the events occurred within several weeks of starting treatment.
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behavior is advised in patients of all ages. This includes monitoring for agitation-type emotional and behavioral changes.
An FDA meta-analysis of placebo-controlled clinical trials of antidepressant drugs in adult patients aged 18 to 24 years with psychiatric disorders showed an increased risk of suicidal behaviours with antidepressants compared to placebo.
Suicide
Depression is associated with an increased risk of suicidal thoughts, self-harm and suicide (suicide-related events). This risk persists until significant remission occurs. As improvement may not occur during the first few weeks or more of treatment, patients should be closely monitored until such improvement occurs. It is general clinical experience that the risk of suicide may increase in the early stages of recovery. Therefore, high risk patients should be closely supervised throughout therapy with AG-Citalopram Tablets and consideration should be given to the possible need for hospitalization. In order to minimize the opportunity for overdosage, prescription for AG-Citalopram Tablets should be written for the smallest quantity of drug consistent with good patient management.
Other psychiatric conditions for which citalopram is prescribed can also be associated with an increased risk of suicide-related events. In addition, these conditions may be co-morbid with major depressive disorder. The same precautions observed when treating patients with major depressive disorder should therefore be observed when treating patients with other psychiatric disorders.
Patients with a history of suicide-related events, or those exhibiting a significant degree of suicidal ideation prior to commencement of treatment, are at greater risk of suicidal thoughts or suicide attempts and should receive careful monitoring during treatment. In addition, there is a possibility of an increased risk of suicidal behaviour in young adults.
Patients (and caregivers of patients) should be alerted about the need to monitor for the emergence of such events and to seek medical advice immediately if these symptoms present.
(See 7 Warnings and Precautions, Psychiatric, Potential Association with Behavioral and Emotional Changes, Including Self-Harm).
Activation of Mania/Hypomania
In placebo-controlled trials with citalopram tablets, some of which included patients with bipolar disorder, mania/hypomania was reported in 0.1% of 1027 patients treated with citalopram tablets versus none of the 426 patients treated with placebo. Activation of mania/hypomania has also been reported in a small proportion of patients with major affective disorders treated with other marketed antidepressants. If a patient enters a manic phase, AG-Citalopram Tablets should be discontinued.
As with all drugs effective in the treatment of depression, AG-Citalopram Tablets should be used with caution in patients with a history of mania. A major depressive episode may be the initial presentation of bipolar disorder. Patients with bipolar disorder may be at an increased risk of experiencing manic episodes when treated with antidepressants alone. Therefore, the decision to initiate symptomatic treatment of depression should only be made after patients have been adequately assessed to determine if they are at risk for bipolar disorder.
Electroconvulsive Therapy (ECT)
The safety and efficacy of the concurrent use of citalopram tablets and ECT have not been studied and therefore, caution is advisable.
Renal
Hyponatraemia
Hyponatraemia and SIADH (syndrome of inappropriate antidiuretic hormone secretion) have been reported as a rare adverse event with use of citalopram tablets, as with other SSRIs. The majority of these occurrences have been in elderly individuals, some in patients taking diuretics or who were otherwise volume-depleted. Elderly female patients in particular seem to be a group at risk.
Renal Impairment
No dosage adjustment is needed in patients with mild to moderate renal impairment. Since, no information is available on the pharmacokinetic or pharmacodynamic effects of citalopram tablets in patients with severely reduced renal function (creatinine clearance < 30 mL/min), AG-Citalopram Tablets should be used with caution in these patients.
Reproductive Health
- Fertility
Male Fertility
Animal data have shown that citalopram may affect sperm quality (see 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicology, Fertility). Human case reports with some SSRIs have shown that an effect on sperm quality is reversible. Impact on human fertility has not been observed.
- Function
Selective serotonin reuptake inhibitors (SSRIs) may cause symptoms of sexual dysfunction. Patients should be informed that there have been reports of long-lasting sexual dysfunction where the symptoms have continued despite discontinuation of SSRIs. See 8.2 Clinical Trial Adverse Reactions, Male and Female Sexual Dysfunction with SSRIs.
- Teratogenic Risk
See 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicology.
7.1 Special Populations
7.1.1 Pregnancy
The safety of citalopram tablets during pregnancy has not been established. Therefore, AG-Citalopram Tablets should not be used during pregnancy, unless, in the opinion of the physician, the expected benefits to the patient markedly outweigh the possible risk to the fetus (see 16 Non-Clinical Toxicology, Reproductive and Development Toxicology).
Complications following late third trimester exposure to SSRIs:
Post-marketing reports indicate that some neonates exposed to SSRIs such as citalopram tablets and other antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and other newer anti-depressants, or, possibly, a drug discontinuation syndrome. It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome (see 7 Warnings and Precautions, Neurologic, Serotonin Toxicity/Neuroleptic Malignant Syndrome (NMS)).
When treating a pregnant woman with AG-Citalopram Tablets during the third trimester, the physician should carefully consider the potential risks and benefits of treatment.
Risk of PPHN and exposure to SSRIs (including citalopram tablets):
Epidemiological studies on persistent pulmonary hypertension of the newborn (PPHN) have shown that the use of SSRIs (including citalopram) in pregnancy, particularly use in late pregnancy, was associated with an increased risk of PPHN. PPHN occurs in 1-2 per 1,000 live births in the general population and is associated with substantial neonatal morbidity and mortality. In a retrospective case-control study of 377 women whose infants were born with PPHN and 836 women whose infants were born healthy, the risk for developing PPHN was approximately six-fold higher for infants exposed to SSRIs after the 20th week of gestation compared to infants who had not been exposed to antidepressants during pregnancy (Odds Ratio 6.1, 95% CI 2.2-16.8). A study using data from the Swedish Medical Birth Register for 831,324 infants born in 1997-2005 found an increased risk of PPHN of approximately 2-fold associated with patient-reported maternal use of SSRIs in the first trimester of pregnancy (Risk Ratio 2.4, 95% CI 1.2-4.3), and an increased risk of PPHN of approximately 4-fold associated with a combination of patient-reported maternal use of SSRIs in the first trimester and an antenatal SSRI prescription in later pregnancy (Risk Ratio 3.6, 95% CI 1.2-8.3).
Observational data indicate an increased risk (less than 2-fold) of postpartum haemorrhage following SSRI/SNRI exposure within the month prior to birth (see 7 Warnings and Precautions, Abnormal Bleeding).
Citalopram Treatment during Pregnancy - Effects on Newborns
In animal reproduction studies, citalopram has been shown to have adverse effects on embryo/fetal and postnatal development, including teratogenic effects, when administered at doses greater than human therapeutic doses (see 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicology). There are no adequate and well-controlled studies in pregnant women; therefore, citalopram should be used during pregnancy only if the potential benefit to the patient justifies the potential risk to the fetus.
7.1.2 Breastfeeding
The safety of citalopram tablets during lactation has not been established. Citalopram hydrobromide is excreted in human milk. AG-Citalopram Tablets should not be administered to nursing mothers unless, in the opinion of the treating physician, the expected benefits to the patient markedly outweigh the possible risks to the child; in which case the infant should be closely monitored.
7.1.3 Pediatrics
Pediatrics (<18 years of age): AG-Citalopram Tablets is not indicated for use in patients below the age of 18 years (see 7 Warnings and Precautions, Psychiatric, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Elderly patients should be administered lower doses and a lower maximum dose (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics). In premarketing clinical trials, 800 elderly patients (≥65 years of age) have been treated with citalopram tablets. Of these patients 298 were ≥75 years old. In a pharmacokinetic study (N=11, age 73 to 90 years), clearance was substantially decreased and half-life prolonged. In a multiple-dose pharmacokinetic study, the area under the curve (AUC) and half-life of S-citalopram were increased by approximately 50% at steady-state in elderly subjects as compared to young subjects. (See 10.3 Pharmacokinetics, Geriatrics). In a 6- week placebo-controlled study, approximately equal numbers of patients received citalopram tablets at 20 or 30 mg per day, as the final dose. In about 5% of patients, the final dose was 10 mg per day (see
14.1 Clinical Trials by Indication).
8 Adverse Reactions
8.1 Adverse Reaction Overview
During the premarketing clinical development, 3652 patients received citalopram tablets for the treatment of depression. Of these patients, 66% were females and 34% were males. The mean age of the patients was 50 years, with 70% being <60 years old (30% <40 years old, 40% 40 to 59 years old) and 30% being ≥60 years old. Adverse events observed with citalopram tablets are in general mild and transient. They usually attenuate during the first one or two weeks of treatment.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse Findings Observed in Short-term, Placebo-controlled Trials
Adverse Reactions Leading to Discontinuation of Treatment
From the short-term (4 to 6 weeks) placebo-controlled, Phase III clinical trials, 15.9% (163/1027) of the citalopram tablets-treated patients discontinued treatment due to an adverse event. The discontinuation rate in the placebo-treated patients was 7.7% (33/426).
The events associated with discontinuation of citalopram tablets in 1% or more of patients at a rate of at least twice that of placebo, were as follows: nausea (4.1% vs. 0.0%), insomnia (2.4% vs. 1.2%), somnolence (2.4% vs. 1.2%), dizziness (2.3% vs. 0.7%), vomiting (1.3% vs. 0.0%), agitation (1.2% vs. 0.0%), asthenia (1.1% vs. 0.5%), and dry mouth (1.1% vs. 0.2%).
Incidence of Adverse Events in Placebo-controlled Studies
Table 2 enumerates the incidence of treatment emergent adverse events that occurred in 1027 depressed patients who received citalopram tablets at doses ranging from 10 to 80 mg/day in placebo-controlled trials of up to 6 weeks in duration. Events included are those occurring in 2% or more of patients treated with citalopram tablets, and for which the incidence in patients treated with citalopram tablets was greater than the incidence in placebo-treated patients. Reported adverse events were classified using the standard World Health Organization (WHO)-based dictionary terminology.
The prescriber should be aware that these figures cannot be used to predict the incidence of adverse events in the course of usual medical practice where patient characteristics and other factors differ from those which prevailed in the clinical trials. Similarly, the cited frequencies cannot be compared with figures obtained from other clinical investigations involving different treatments, uses, and investigators. The cited figures, however, do provide the prescribing physician with some basis for estimating the relative contribution of drug and non-drug factors to the adverse event incidence rate in the population studied.
Table 2 - Treatment-emergent adverse events* incidence in placebo-controlled clinical trials
| System organ class /preferred term | Percentage of Patients Reporting | ||||||
|---|---|---|---|---|---|---|---|
| Citalopram (N = 1027) | Placebo (N = 426) | ||||||
Gastrointestinal disorders Nausea1 Dry mouth1 Diarrhea Dyspepsia Vomiting Abdominal pain | 20.6 19.4 8.1 4.3 3.9 3.1 | 13.4 12.2 5.4 3.5 2.6 2.1 | |||||
| General disorders and administration site conditions | |||||||
Fatigue Fever1 | 5.2 2.4 | 3.1 0.2 | |||||
Infections and Infestations Upper respiratory tract infection Rhinitis Pharyngitis Sinusitis1 | 5.1 4.9 3.4 2.4 | 4.7 3.3 2.8 0.2 | |||||
Metabolism and nutrition disorders Anorexia1 | 4.2 | 1.6 | |||||
Nervous System disorders Tremor | 8.4 | 6.3 | |||||
| Psychiatric disorders | |||||||
Somnolence1 Nervousness Anxiety Agitation1 Libido decreased1 | 17.3 3.6 3.3 2.4 2.2 | 9.9 3.5 2.1 0.7 0.2 | |||||
Renal and urinary disorders Micturition disorder | 2.3 | 2.1 | |||||
| Reproductive system and breast disorders | |||||||
| Ejaculation disorder1 | 6.2 | 1.1 | |||||
Impotence3 Dysmenorrhea2 (<50 years) | 3.2 2.7 | 0.6 1.6 | |||||
Respiratory, Thoracic and Mediastinal Disorders Yawning | 2.1 | 0 | |||||
| Skin and subcutaneous tissue disorders | |||||||
| Sweating increased | 10.5 | 8.0 | |||||
*Events included are those occurring in 2% or more of patients treated with citalopram tablets, and for which the incidence in patients treated with citalopram tablets was greater than the incidence in placebo-treated patients.
1Statistically significantly higher incidence in the citalopram group (p <0.05).
2Denominator used was for females only (N=623 for citalopram tablets; N=245 for placebo).
3Denominator used was for males only (N=404 for citalopram tablets; N=181 for placebo).
The following events had a higher incidence in the placebo group compared to the citalopram group: asthenia, back pain, headache, dizziness, constipation, palpitation, insomnia, abnormal vision.
Most Frequent Adverse Events
Adverse events that occurred in citalopram tablets-treated patients in the course of the short-term, placebo-controlled trials with an incidence greater than, or equal to, 10% were: nausea, dry mouth, somnolence, and increased sweating (Table 2).
Dose Dependency of Adverse Events
The potential relationship between the dose of citalopram tablets and the incidence of an adverse event was examined in a fixed dose short-term, placebo-controlled study in which patients received citalopram tablets at doses of 10, 20, 40 or 60 mg per day. The incidence of diarrhea, dry mouth, fatigue, insomnia, increased sweating, nausea and somnolence was dose-related.
Male and Female Sexual Dysfunction with SSRIs
While sexual dysfunction is often part of depression and other psychiatric disorders, there is increasing evidence that treatment with SSRIs may induce sexual side effects. Furthermore, there have been reports of long-lasting sexual dysfunction where these symptoms have continued despite discontinuation of SSRIs. This is a difficult area to study because patients may not spontaneously report symptoms of this nature, and therefore, it is thought that sexual side effects with SSRIs may be underestimated.
In placebo-controlled, short-term clinical trials, the reported incidence of decreased libido, ejaculation disorders (primarily ejaculation delay and ejaculation failure), and impotence in male depressed patients receiving citalopram tablets (N=404) was 3.7%, 6.2%, and 3.2%, respectively. In female depressed patients receiving citalopram tablets (N=623), the reported incidence of decreased libido and anorgasmia was 1.3% and 1.1%, respectively. The reported incidence of each of these adverse events was ≤1% among male and female depressed patients receiving placebo.
Weight Changes
Patients treated with citalopram tablets in controlled trials experienced a weight loss of about 0.5 kg compared to no change for placebo patients.
Decreased Heart Rate
Retrospective analyses of electrocardiograms in citalopram tablets-treated (N=779 <60 years and N=313 ≥60 years) and placebo-treated (N=74 <60 years and N=43 ≥60 years) patients indicated that citalopram tablets decreases heart rate. In patients <60 years old, the mean decrease was approximately 5 bpm, while in patients ≥60 years old, mean decreases ranged between 5 to 10 bpm. Following the initial drop, heart rate remained decreased but stable over prolonged periods of time (up to one year in over 100 younger and over 50 elderly patients). The effect was reversible within approximately a week after stopping treatment.
In the 6-week, fixed dose, dose-response study, the mean decreases in heart rate ranged between 2-6 bpm in the 20-60 mg/day dose range, but the effect did not seem to be dose-related and was independent of gender. In placebo-treated patients heart rates remained unaffected. The differences in heart rates between citalopram tablets and placebo-treated patients were statistically significant. ECG parameters, including QT interval, remained unaffected.
Adverse Reactions following Discontinuation of Treatment (or Dose Reduction)
There have been reports of adverse reactions upon the discontinuation of citalopram tablets (particularly when abrupt), including but not limited to the following: dizziness, abnormal dreams, sensory disturbances (including paresthesias and electric shock sensations), agitation or anxiety, emotional indifference, impaired concentration, headache, migraine, tremor, nausea and/or vomiting, sleep disturbances (including insomnia and intense dreams), confusion, diarrhoea, palpitations, irritability, visual disturbances and sweating or other symptoms which may be of clinical significance.
Generally, these events are mild to moderate and are self-limiting, however, in some patients they may be severe and/or prolonged. Symptoms associated with discontinuation have been reported for other selective serotonin reuptake inhibitors.
Additional Adverse Events Observed During the Premarketing Evaluation of Citalopram Tablets
The events listed below include all adverse events that were reported in the overall development program of citalopram tablets (N=3652). All reported events are included except those already listed in Table 2 and those events which occurred in only one patient. It is important to emphasize that, although the events reported occurred during treatment with citalopram tablets, they were not necessarily caused by it. The events are enumerated using the following criteria:
- frequent: adverse events that occurred on one or more occasions in at least 1/100 patients
- infrequent: adverse events that occurred in less than 1/100 patients but at least in 1/1000 patients
- rare: adverse events that occurred in fewer than 1/1000 patients.
General Disorders and Administration Site Conditions: Frequent: influenza-like symptoms, non-pathological trauma, pain. Infrequent: chest pain, edema, hot flushes, malaise, rigors. Rare: peripheral edema, sudden death.
Cardiac Disorders: Frequent: postural hypotension, tachycardia. Infrequent: angina pectoris, arrhythmia, bradycardia, cardiac failure, cerebrovascular disorders, edema dependent, extrasystoles, flushing, hypertension, hypotension, myocardial infarction, myocardial ischemia, peripheral ischemia. Rare: aggravated hypertension, bundle branch block, cardiac arrest, coronary artery disorder, ECG abnormal, heart disorder, phlebitis, supraventricular extrasystoles.
Nervous System Disorders: Frequent: migraine, paraesthesia. Infrequent: abnormal gait, ataxia, convulsions, dysphonia, dystonia, extrapyramidal disorder, hyperkinesia, hypertonia, hypoesthesia, hypokinesia, involuntary muscle contractions, leg cramps, neuralgia, speech disorder, syncope, taste perversion, vertigo. Rare: abnormal coordination, convulsions grand mal, hyperesthesia, ptosis, sensory disturbance, stupor.
Ear and Labyrinth disorders: Infrequent: earache, tinnitus.
Endocrine Disorders: Rare: goiter, gynecomastia, hypothyroidism.
Eye Disorders: Frequent: abnormal accommodation. Infrequent: conjunctivitis, eye pain, mydriasis. Rare: eye abnormality, keratitis, photophobia.
Gastrointestinal Disorders: Frequent: flatulence. Infrequent: colitis, dental abscess, dysphagia, eructation, gastritis, gastroenteritis, gastrointestinal disorder (not specified), hemorrhoids, increased saliva, teeth-grinding, toothache. Rare: appendicitis, esophagitis, gastric ulcer, gastroesophageal reflux, gingivitis, stomatitis, tooth disorder, ulcerative stomatitis.
Immune System Disorders: Infrequent: allergic reaction, allergy
Injury, poisoning and procedural complications: Rare: traumatic injury.
Blood and Lymphatic System Disorders: Infrequent: anemia, epistaxis, leukocytosis, purpura. Rare: coagulation disorder, gingival bleeding, granulocytopenia, hematoma, leukopenia, lymphadenopathy, lymphocytosis, pulmonary embolism.
Hepatobiliary Disorders: Infrequent: cholecystitis, cholelithiasis, increased gamma-GT, increased ALT. Rare: bilirubinemia, increased AST, jaundice.
Metabolism and Nutrition Disorders: Frequent: appetite decreased, weight decrease, weight increase. Infrequent: alcohol intolerance, leg edema, xerophthalmia. Rare: dehydration, edema, hypoglycemia, hypokalemia, increased alkaline phosphatase, obesity, thirst.
Musculoskeletal and Connective Tissue Disorders: Infrequent: arthralgia, arthritis, arthrosis, dystonia, leg pain, muscle weakness, myalgia. Rare: bone disorder, bursitis, osteoporosis, rheumatoid arthritis, tendon disorder.
Neoplasms Benign, Malignant and Unspecified (incl cysts and polyps): Rare: breast neoplasm malignant female.
Psychiatric Disorders: Frequent: abnormal dreaming, aggravated depression, amnesia, apathy, confusion, depression, impaired concentration, increased appetite, sleep disorder, suicide attempt. Infrequent: abnormal thinking, aggressive reaction, delusion, depersonalization, drug abuse, drug dependence, emotional lability, euphoria, hallucination, increased libido, manic reaction, neurosis, paranoid reaction, paroniria, psychosis, psychotic depression. Rare: catatonic reaction, hysteria, personality disorder.
Reproductive System and Breast Disorders: Frequent: Abnormal orgasm Infrequent: amenorrhea, breast pain, lactation nonpuerperal, menorrhagia, menstrual disorder, penis disorder, premenstrual syndrome, prostatic disorder, salpingitis, testis disorder, unintended pregnancy, vaginal dryness, vaginitis. Rare: breast enlargement, vaginal hemorrhage.
Infections and Infestations: Infrequent: abscess, fungal infection, herpes simplex infection, otitis media, viral infection. Rare: bacterial infection, moniliasis, sepsis.
Respiratory, Thoracic and Mediastinal System Disorders: Infrequent: bronchitis, coughing, dyspnea, pneumonia. Rare: asthma, bronchospasm, increased sputum, laryngitis, pneumonitis, respiratory disorder.
Skin and Subcutaneous Tissue Disorders: Frequent: pruritus, rash. Infrequent: acne, alopecia, dermatitis, dry skin, eczema, photosensitivity reaction, psoriasis, rash erythematous, rash maculo-papular, skin discoloration, urticaria. Rare: cellulitis, decreased sweating, hypertrichosis, melanosis, pruritus ani.
Renal and Urinary Disorders: Frequent: polyuria. Infrequent: abnormal urine, cystitis, hematuria, micturition frequency, urinary incontinence, urinary retention, urinary tract infection. Rare: dysuria, facial edema, oliguria, renal calculus, renal pain.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Not applicable.
8.3 Less Common Clinical Trial Adverse Reactions
See 8.2 Clinical Trial Adverse Reactions, Additional Adverse Events Observed During the Premarketing Evaluation of Citalopram Tablets
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
Not applicable.
8.5 Post-Market Adverse Reactions
The following adverse events have been identified during post-approval use of citalopram tablets. These events are reported voluntarily from a population of uncertain size, and it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Table 3 – Spontaneous Adverse Events
| System Organ Class | Adverse Event |
|---|---|
| Blood and Lymphatic System Disorders | Eosinophilia, Hemolytic anemia, Pancytopenia, Thrombocytopenia, |
| Cardiac Disorders | Torsade de pointes, Ventricular arrhythmia, Cardiac arrest, Cardio-respiratory arrest, Electrocardiogram QT interval prolonged, Long QT syndrome, Ventricular fibrillation, Ventricular tachycardia, Sudden death |
| Endocrine Disorders | Hyperprolactinemia*, Inappropriate ADH secretion |
| Eye Disorders | Visual disturbance |
| General Disorders and Administration Site Conditions | Fatigue, Condition aggravated, Pyrexia |
| Gastrointestinal Disorders | Gastrointestinal haemorrhage (including rectal haemorrhage), Pancreatitis, Constipation |
| Hepatobiliary Disorders | Hepatitis, Liver function test abnormal |
| Immune System Disorders | Anaphylactic reaction, Hypersensitivity, |
| Investigations | Decreased drug level, Decreased prothrombin time, Increased drug level, Increased prothrombin time |
| Metabolism and Nutrition Disorders | Hyponatraemia, Hypokalaemia |
| Musculoskeletal and Connective Tissue Disorders | Rhabdomyolysis |
| Nervous System Disorders | Akathisia, Choreoathetosis, Dyskinesia, Extrapyramidal disorder, Movement disorder, Myoclonus, Neuroleptic malignant syndrome, Neuropathy, Nystagmus, Serotonin syndrome, Syncope, Dizziness, Disturbance in attention, Taste disturbance |
| Pregnancy, Puerperium and Perinatal Conditions | Spontaneous abortion/fetal death |
| Psychiatric Disorders | Abnormal orgasm (female), Bruxism, Confusional state, Delirium, Hypomania, Panic attack, Restlessness, Withdrawal syndrome, Abnormal dreams |
| Renal and Urinary Disorders | Acute renal failure |
| Reproductive System and Breast Disorders | Galactorrhoea Female: menometrorrhagia, postpartum haemorrhage* Male: Priapism |
| Skin and Subcutaneous Tissue Disorders | Angioedemas, Ecchymosis, Epidermal necrolysis, Erythema multiforme, Stevens-Johnson syndrome, Photosensitivity |
| Vascular Disorders | Orthostatic hypotension, Vasodilatation |
* This event has been reported for the therapeutic class of SSRIs/SNRIs.
9 Drug Interactions
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
Alcohol
Although citalopram tablets did not potentiate the cognitive and psychomotor effects of alcohol in volunteers, the concomitant use of alcohol and AG-Citalopram Tablets should be avoided.
Cimetidine
AG-Citalopram Tablets should not be dosed above 20 mg/day in patients receiving cimetidine.
Central Nervous System (CNS) drugs
Drug interactions have not been specifically studied between citalopram and other centrally acting drugs. Given the primary CNS effects of citalopram, caution should be used as with other SSRIs when citalopram is taken in combination with other centrally acting drugs.
Cytochrome P450 Isozymes
Using in vitro models of human liver microsomes, the biotransformation of citalopram to its demethyl metabolites was shown to depend on both CYP2C19 and CYP3A4, with a small contribution from CYP2D6. Studies have also indicated that citalopram is a weak inhibitor of CYP2D6 and CYP2C19 and a weak or negligible inhibitor of CYP3A4, CYP1A2, CYP2C9 and CYP2E1. Although citalopram has a low potential for clinically significant drug interactions, caution is recommended, when citalopram is co-administered with drugs that are mainly metabolized by CYP2D6, and that have a narrow therapeutic index.
One in vitro study using human liver microsomes has shown that ketoconazole and omeprazole reduced the rate of formation of the demethylcitalopram metabolite of citalopram to 45-60% and 75-85% of control, respectively. As data are not available from multi-dose pharmacokinetic studies, the possibility that the clearance of citalopram will be decreased when AG-Citalopram Tablets is administered with a potent inhibitor of CYP3A4 (e.g., ketoconazole, itraconazole, fluconazole or erythromycin), or a potent inhibitor of CYP2C19 (e.g., omeprazole, esomeprazole, fluvoxamine, lansoprazole, ticlopidine), should be considered.
AG-Citalopram Tablets 20 mg/day is the maximum recommended dose for patients taking concomitant CYP2C19 inhibitors because of the risk of QT prolongation.
In addition, a single-dose study of escitalopram co-administered with a multiple-dose regimen of cimetidine, a non-specific CYP inhibitor, led to significant changes in most of the pharmacokinetic parameters of escitalopram. The overall metabolic pathways for escitalopram and citalopram are qualitatively similar and the interaction potential for escitalopram is expected to closely resemble that of citalopram. Thus, this allows for extrapolation to previous studies with escitalopram.
Various scientific publications have acknowledged that the main components in grapefruit juice may act as a CYP3A4 inhibitor. Citalopram is also metabolized by other isoenzymes not affected by grapefruit juice, namely CYP2C19 and CYP2D6.
Drugs Affecting Platelet Function (e.g., NSAIDs, ASA and other anticoagulants)
Serotonin release by platelets plays an important role in hemostasis. Epidemiological studies of the case-control and cohort design that have demonstrated an association between use of psychotropic drugs that interfere with serotonin reuptake and the occurrence of upper gastrointestinal bleeding have also shown that concurrent use of an NSAID, ASA or other anticoagulants may potentiate the risk of bleeding.
Altered anticoagulant effects, including increased bleeding, have been reported when SSRIs and SNRIs are co-administered with warfarin. Patients receiving warfarin therapy should be carefully monitored when AG-Citalopram Tablets is initiated or discontinued (see 7 Warnings and Precautions, Abnormal Bleeding).
Drugs That Prolong the QT Interval
ECG monitoring is recommended if AG-Citalopram Tablets is administered with concomitant medications that have demonstrated prolongation of the QT interval (see 2 Contraindications, QT Prolongation; 7 Warnings and Precautions, QT Prolongation and Torsades de Pointes; 8.5 Post-Market Adverse Reactions; 9.2 Drug Interactions Overview, Cimetidine and Cytochrome P450 Isozymes; 4 Dosage and administration).
Drugs known to prolong the QT/QTc Interval:
The concomitant use of citalopram with another drug known to prolong the QT/QTc interval should be carefully considered to determine that the therapeutic benefit outweighs the potential risk. Drugs that have been associated with QT/QTc interval prolongation and/or torsade de pointes include, but are not limited to, the examples in the following list. Chemical/pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QT/QTc prolongation and/or torsade de pointes:
- class IA antiarrhythmics (e.g., procainamide, disopyramide);
- class III antiarrhythmics (e.g., amiodarone, sotalol, ibutilide);
- class IC antiarrhythmics (e.g., propafenone);
- antipsychotics (e.g., chlorpromazine, pimozide, haloperidol, droperidol, ziprasidone);
- antidepressants (e.g., fluoxetine, venlafaxine, tricyclic/tetracyclic antidepressants e.g., amitriptyline, imipramine, maprotiline);
- opioids (e.g., methadone);
- macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, telithromycin, tacrolimus);
- quinolone antibiotics (e.g., moxifloxacin, levofloxacin, ciprofloxacin);
- antimalarials (e.g., quinine, chloroquine);
- azole antifungals (e.g., ketoconazole, fluconazole, voriconazole);
- domperidone; 5-hydroxytryptamine (5-HT)3 receptor antagonists (e.g., ondansetron);
- tyrosine kinase inhibitors (e.g., sunitinib, nilotinib, lapatinib);
- histone deacetylase inhibitors (e.g., vorinostat);
- beta-2 adrenoceptor agonists (e.g., salmeterol, formoterol).
The use of citalopram should be carefully considered with drugs that can disrupt electrolyte levels (see 7 Warnings and Precautions, Hyponatraemia), including, but not limited to, the following:
- loop, thiazide, and related diuretics;
- laxatives and enemas;
- amphotericin B;
- high dose corticosteroids.
Monoamine Oxidase Inhibitors
In patients receiving SSRIs in combination with a monoamine oxidase inhibitor (MAOI), there have been reports of serious, sometimes fatal, reactions including hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, and mental status changes, including extreme agitation progressing to delirium and coma. These reactions have also been reported in patients who have recently discontinued SSRI treatment and have been started on a MAOI. Some cases presented with features resembling serotonin syndrome or neuroleptic malignant syndrome. AG-Citalopram Tablets should not be used in combination with a MAOI, (including linezolid, an antibiotic which is a reversible non-selective MAO inhibitor and methylene blue, which is a MAOIs) or within 14 days of discontinuing treatment with a MAOI. Similarly, at least 14 days should elapse after discontinuing AG-Citalopram Tablets treatment before starting a MAOI (see 2 Contraindications, Monoamine Oxidase Inhibitors).
Serotonergic Drugs
Based on the mechanism of action of citalopram and the potential for serotonin syndrome, caution is advised when AG-Citalopram Tablets is coadministered with other drugs or agents that may affect the serotonergic neurotransmitter systems, such as tryptophan, triptans, serotonin reuptake inhibitors, lithium, St. John's Wort, dextromethorphan, opioids (including methadone, buprenorphine and tramadol, fentanyl and its analogues, tapentadol, meperidine and pentazocine) (see 7 Warnings and Precautions, Neurologic, Serotonin Toxicity/Neuroleptic Malignant Syndrome (NMS)). Concomitant use of AG-Citalopram Tablets and MAO inhibitors (including linezolid and methylene blue), is contraindicated (see 2 Contraindications, Monoamine Oxidase Inhibitors).
Triptans (5HT1 agonists)
Cases of life-threatening serotonin syndrome have been reported during combined use of selective serotonin reuptake inhibitors (SSRIs)/serotonin norepinephrine reuptake inhibitors (SNRIs) and triptans. If concomitant treatment with AG-Citalopram Tablets and a triptan is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 7 Warnings and Precautions, Neurologic, Serotonin Toxicity/Neuroleptic Malignant Syndrome (NMS)).
Escitalopram
AG-Citalopram Tablets is a racemic mixture of R-citalopram and S-citalopram, the later being the active isomer. As escitalopram, is the active isomer of racemic citalopram (AG-Citalopram Tablets), the two drugs should not be taken together.
Other Drugs
No pharmacodynamic interactions have been noted in clinical trials where citalopram tablets have been given concomitantly with benzodiazepines (anxiolytics/hypnotics), analgesics (NSAIDs, non-NSAIDs), antihistamines, antihypertensives or other cardiovascular drugs. Pharmacokinetic interactions between citalopram and these drugs were not specifically studied.
9.3 Drug-Behaviour Interactions
See 7 Warnings and Precautions, Psychiatric, Potential Association with Behavioural and Emotional Changes, Including Self-Harm.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction.
Where studies are described in this section, they were carried out in young, healthy, mostly male volunteers. In addition, some of the studies, namely interactions with metoprolol, warfarin, digoxin, imipramine, and levomepromazine, utilized only single doses of these drugs, although citalopram tablets were given repeatedly to attain steady state. Thus, data are not available in patients who would be receiving these drugs on an ongoing basis at therapeutic doses.
Table 4 - Established or Potential Drug-Drug Interactions
| Non-proprietary name (s) of the drug product (s) | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| pimozide | CT | In a double-blind crossover study in healthy young adults, a single dose of the anti-psychotic drug, pimozide 2 mg co-administered with citalopram tablets 40 mg given once daily for 11 days was associated with a mean increase in QTc values at Tmax of approximately 12 msec compared to pimozide when given with placebo. This apparent pharmacodynamic interaction occurred in the absence of a clinically significant pharmacokinetic interaction; the mechanism is unknown. | Concomitant use of AG-Citalopram Tablets and pimozide is contraindicated (see 2 CONTRAINDICATIONS, Pimozide). |
| Ritonavir (Substrate for CYP3A4) | CT | Combined administration of a single dose of ritonavir (600 mg), a CYP3A4 substrate and a potent inhibitor of CYP3A4, and escitalopram (20 mg) did not affect the pharmacokinetics of either ritonavir or escitalopram. | |
| theophylline | CT | Co-administration of citalopram tablets (40 mg/day for 21 days) with the CYP1A2 substrate theophylline (single dose of 300 mg) did not affect the pharmacokinetics of theophylline. | |
| triazolam | CT | Combined administration of citalopram tablets (titrated to 40 mg/day for 28 days) and the CYP3A4 substrate triazolam (single dose of 0.25 mg) did not significantly affect the pharmacokinetics of either drug. | |
| warfarin | CT | Administration of citalopram tablets (40 mg/day for 21 days), did not affect either the pharmacokinetics or the pharmacodynamics (prothrombin time) of a single, 25 mg dose of warfarin, a CYP3A4 and CYP2C9 substrate. | |
| Non-proprietary name (s) of the drug product (s) | Source of evidence | Effect | Clinical comment |
| cimetidine | CT | Citalopram tablets 40 mg/day were administered for 29 days. During the last 8 days of treatment, cimetidine (400 mg bid) was added to the treatment regimen. In the presence of cimetidine, a potent inhibitor of hepatic cytochrome P450 enzymes (CYP2D6, 3A4 and 1A2 inhibitor), the Cmax and AUC of citalopram tablets was increased by 39% and 41%, respectively. | Caution should be exercised at the upper end of the dose range of AG-Citalopram Tablets when it is used concomitantly with high doses of cimetidine. AG-Citalopram Tablets 20 mg/day is the maximum recommended dose when taken with cimetidine. |
| escitalopram | T | Escitalopram is the active isomer of racemic citalopram (AG-Citalopram Tablets) | The two drugs should not be taken together. |
| digoxin | CT | Administration of citalopram tablets (40 mg/day for 21 days) did not affect the pharmacokinetics of digoxin (single dose of 1 mg), although the serum levels of citalopram tablets were slightly lower in the presence of digoxin. | |
| imipramine / desipramine | CT | Coadministration of citalopram tablets (40 mg/day for 10 days) and the tricyclic antidepressant, imipramine (single dose of 100 mg), did not affect the pharmacokinetics of either drug. However, in the presence of citalopram tablets, the concentration of desipramine, the metabolite of imipramine, increased by approximately 50% and its half-life was prolonged. The results indicate that citalopram tablets do not interfere with the demethylation of imipramine to desipramine but do inhibit the metabolism of desipramine to its 2- hydroxy metabolite. Both imipramine and desipramine are substrate for CYP2D6. | The clinical significance of this finding is unknown. Concomitant treatment with AG-Citalopram Tablets and imipramine/desipramine should be undertaken with caution. |
| Non-proprietary name (s) of the drug product (s) | Source of evidence | Effect | Clinical comment |
| carbamazepine | CT | Carbamazepine, titrated to 400 mg/day, was given for 21 days alone and then in combination with citalopram tablets (40 mg/day) for an additional 14 days. Citalopram tablets did not affect the plasma levels of either carbamazepine, a CYP3A4 substrate, or its metabolite, carbamazepine-epoxide. | Since carbamazepine is a microsomal enzyme inducer, the possibility that carbamazepine may increase the clearance of AG-Citalopram Tablets should be considered if the two drugs are given concomitantly. |
| Non-proprietary name (s) of the drug product (s) | Source of evidence | Effect | Clinical comment |
| ketoconazole | CT | Combined administration of citalopram tablets (40 mg single dose) and the potent CYP3A4 inhibitor ketoconazole (200 mg single dose) decreased the Cmax of ketoconazole by 21% and did not affect the pharmacokinetics of citalopram tablets. | |
| levomepromazine | CT | Coadministration of citalopram tablets (40 mg/day for 10 days) and levomepromazine (single dose of 50 mg), a CYP2D6 inhibitor, did not affect the pharmacokinetics of either drug. | |
| lithium | CT | Coadministration of citalopram tablets (40 mg/day for 10 days) and lithium (30 mmol/day for 5 days), did not affect the pharmacokinetics of either drug. | Since lithium may increase serotonergic neurotransmission, concomitant treatment with these two drugs should be undertaken with caution. |
| metoprolol | CT | Coadministration of citalopram tablets (40 mg/day for 22 days) and the β-adrenergic blocking agent metoprolol (single dose of 150 mg), resulted in a twofold increase in the plasma levels of metoprolol. However, the effect of metoprolol, a CYP2D6 substrate, on blood pressure and heart rate was not affected. | |
| omeprazole | CT | CYP2C19 inhibitor | Co-administration of omeprazole (30 mg once daily for 6 days), a CYP2C19 inhibitor, with escitalopram (single dose of 20 mg on Day 5) resulted in an increase in escitalopram AUC and Cmax of approximately 50% and 10%, respectively. AG-Citalopram Tablets 20 mg/day is the maximum recommended dose for patients taking concomitant CYP2C19 inhibitors because of the risk of QT prolongation. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Although there is a theoretical possibility of pharmacokinetic drug product interactions resulting from co-administration of citalopram with grapefruit juice, the onset of an interaction is considered unlikely (see 9.2 Drug Interactions Overview, Cytochrome P450 Isozymes).
9.6 Drug-Herb Interactions
St. John’s Wort: In common with other SSRIs, pharmacodynamic interactions between citalopram and the herbal remedy St. John’s Wort may occur and may result in undesirable effects.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Citalopram is a highly selective and potent serotonin (5-hydroxytryptamine, 5-HT) reuptake inhibitor with minimal effects on the neuronal reuptake of norepinephrine (NE) and dopamine (DA). The ability of citalopram to potentiate serotonergic activity in the central nervous system via inhibition of the neuronal reuptake of serotonin is thought to be responsible for its antidepressant action. Tolerance to the inhibition of serotonin reuptake is not induced by long-term (14 days) treatment of rats with citalopram.
Citalopram is a racemic mixture with the S (+) enantiomer mediating the pharmacological effects. The R (-) enantiomer contributes little to the activity of citalopram.
10.2 Pharmacodynamics
Citalopram has no or very low affinity for a series of receptors including serotonin 5-HT1A, 5-HT2, dopamine D1 and D2, α1-, α2-, β-adrenergic, histamine H1, muscarinic cholinergic, benzodiazepine, gamma aminobutyric acid (GABA) and opioid receptors.
Citalopram like other SSRIs may increase plasma prolactin, an effect secondary to the prolactin stimulating role of serotonin (see 8.5 Post-Market Adverse Reactions).
10.3 Pharmacokinetics
Table 5 – Summary of Citalopram pharmacokinetic parameters in Healthy Male Volunteers
Cmax (nmoL/L) | Tmax (hr) | t½ (h) | AUC0-∞ (nmol/L*hr) | CL (L/min) | Vdβ (L/kg) | |
|---|---|---|---|---|---|---|
| Mean | 122 | 4 | 37 | 5118 | 0.33 | 12.3 |
Absorption
Following the administration of a single oral dose of citalopram (40 mg) to healthy male volunteers, peak blood levels occurred at about 4 hours (range 1 to 6 hours). The absolute bioavailability of citalopram was about 80% (range 52 to 93%) relative to an intravenous dose. Absorption was not affected by food.
Distribution
After intravenous infusion in healthy male volunteers, the apparent volume of distribution (Vd)β was about 12 L/kg (range 9-17 L/kg), indicating a pronounced tissue distribution; Vdβ oral was about 17 L/kg (range 14-21 L/kg). The binding of citalopram and its demethylated metabolites to human plasma proteins is about 80%.
The single- and multiple-dose pharmacokinetics of citalopram are linear and dose-proportional in a dose range of 10 to 60 mg/day. Steady-state plasma levels are achieved in patients in 1-2 weeks. At a daily dose of 40 mg, the average plasma concentration is about 83 ng/mL (n=114) with a range from 30 to 200 ng/mL. Citalopram does not accumulate during long-term treatment. A clear relationship between citalopram plasma levels and therapeutic response or side effects has not been established.
Metabolism
Citalopram is metabolized in the liver to demethylcitalopram (DCT), didemethylcitalopram (DDCT), citalopram-N-oxide, and a deaminated propionic acid derivative. In vitro studies show that DCT, DDCT and citalopram-N-oxide also inhibit the neuronal reuptake of serotonin but are less selective and less potent than the parent compound and are of minor clinical importance. Unchanged citalopram is the predominant compound in plasma.
In vitro studies indicated that the biotransformation of citalopram to its demethyl metabolites depends on both CYP2C19 and CYP3A4, with a small contribution from CYP2D6. An initial dose of 10 mg is recommended for known poor metabolisers of CYP2C19 (see 4.2 Recommended Dose and Dosage Adjustment, CYP2C19 Poor Metabolisers).
Elimination
The elimination half-life of citalopram (t2β) is approximately 37 hours (range: 30 - 42 hours) which allows recommendation of once-daily dosing. The systemic citalopram plasma clearance (ClS) is 0.33 L/min. Citalopram is eliminated primarily via the liver (85%) and the remainder via the kidneys; approximately 12% (range 6-21%) of the daily dose is excreted in urine as unchanged citalopram.
Special populations and conditions
- Pediatrics: AG-Citalopram Tablets is not indicated for use in patients below the age of 18 (see 1.1 Pediatrics).
- Geriatrics: Elderly patients (4 males and 7 females aged 73 - 90 years), received a 20 mg/day dose of citalopram for 3-4 weeks. In the elderly, steady state plasma levels were elevated (106 ng/mL), half-life prolonged (1.5 - 3.75 days) and clearance decreased (0.08 - 0.3 L/min). Elevation of citalopram plasma levels occurred at an earlier age in females than in males. In this population, lower doses and a lower maximum dose of citalopram are recommended (see 7.1.4 Geriatrics and 4.2 Recommended Dose and Dosage Adjustment, Geriatrics).
- Hepatic Insufficiency: The pharmacokinetics of citalopram were compared in patients with reduced hepatic function (3 female and 6 male patients aged 41 - 60 years) to those seen in 12 healthy male volunteers (aged 21 - 43 years). In patients with reduced hepatic function the half-life of citalopram was approximately doubled (83 hours vs. 37 hours), steady state citalopram concentrations increased by 61% and oral clearance decreased by 37%. Consequently, the use of citalopram in patients with reduced hepatic function should be approached with caution and lower maximal doses should be prescribed (see 7 Warnings and Precautions, Hepatic Impairment and 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment).
- Renal Insufficiency: In patients with mild to moderate reduction of the renal function (4 female and 3 male patients aged 30-55 years), citalopram was being eliminated more slowly than in 12 healthy male volunteers (aged 21-43 years); half-lives being 49 hours vs. 37 hours. However, mild to moderate renal impairment had no major influence on the kinetics of citalopram. At present, no information is available for chronic treatment of patients with severely reduced renal function (creatinine clearance <20 mL/min).
11 Storage, Stability, and Disposal
AG-Citalopram Tablets should be stored in a dry place at room temperature between 15-30oC.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Citalopram hydrobromide
Chemical name: (RS)-1-[3-(Dimethylamino) propyl]-1-(p-fluorophenyl)-5-phthalancarbonitrile, monohydrobromide
Molecular formula and molecular mass: C20H22BrFN2O
405.30 g/mol
Structural formula:
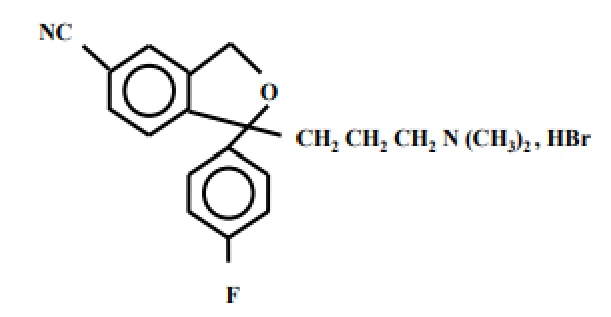
Physicochemical properties:
Description: white to off-white, crystalline material having no more than a slight odour.
Melting Point: 185°-188°C
pH: 5.5-6.5 (0.5% w/v in water)
pKa: 9.5 (microtitration)
Solubility: water (sparingly soluble) ethanol (soluble) chloroform (freely soluble)
diethylether (very slightly soluble)
Partition Coefficient: log P (octanol/phosphate buffer pH 7.4) - 1.57
14 Clinical Trials
14.1 Clinical Trials by Indication
Symptomatic Relief of Depressive Illness
Table 6 – Summary of Patient Demographics for Clinical Trials in the treatment of depression
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Age (range) | Sex |
|---|---|---|---|---|---|
| 91206 | Double-blind, placebo controlled, fixed-dose multicentre study in outpatients with moderate to severe depression | 10, 20, 40, or 60 mg/day or placebo Oral 6 weeks | 129 to 131 per group | 18-65 years | Male/ Female |
| 85A | Double-blind, Placebo controlled flexible-dose, randomized, parallel group (2 arms) study | initial dose: 20 mg/day, could be titrated to the maximal tolerated dose or a maximum dose of 80 mg/day Oral 4-weeks | 83 to 87 per group | 18-65 years | Male or post- menopausal or surgically sterilized Female |
| 89303 | Double-blind, placebo controlled fixed-dose, randomized, parallel group (3-arms) study | 20 or 40 mg/day, or placebo Oral 6-weeks | 64 to 70 per group | 19-72 years | Male/ Female |
| 89306 | Double-blind, Placebo controlled fixed-dose randomized study | 20 or 40 mg/day or placebo Oral 6-weeks | 88 to 97 per group | 17-76 years | Male/ Female |
| 86141 | Double-blind, Placebo controlled, flexible-dose, randomized parallel group (2 arms) study | 10-30mg or placebo Oral 6-weeks | Citalopram tablets n=98 Placebo n=51 | ≥65 years | Male/ Female |
The efficacy of citalopram tablets in the treatment of depression was established in five placebo-controlled studies in patients who met the Diagnostic and Statistical Manual of Mental Disorders (DSM-III or DSM-III-R criteria) for major depression. Response to treatment was evaluated by the Hamilton Depression Rating Scale (HAMD) and/or the Montgomery Åsberg Depression Rating Scale (MADRS), as well as the Clinical Global Impression (CGI) Severity Scale.
On the HAMD and MADRS, total scores, selected single items, and percentage of responders (defined as patients whose HAMD/MADRS total score decreased by at least 50% versus baseline) were assessed.
In a 6-week fixed-dose, dose-response study (Study #91206), patients received citalopram tablets, at doses of 10, 20, 40, or 60 mg/day or placebo (n=129 to 131 per group). The 40 and 60 mg/day doses were titrated, with patients reaching these designated doses within 4 and 8 days, respectively. The study showed that the 40 and 60 mg/day doses were significantly more effective than placebo, although the 60 mg/day dose was not more effective than the 40 mg/day dose. The lower doses did not show statistically significant superiority over placebo, except on the MADRS; on this scale the percent of ‘responders’ was significantly higher in all the citalopram tablets-treated groups than in the placebo-treated group.
The second study was a 4-week flexible-dose study (Study #85A) in which 85% of the depressed patients met the criteria for melancholia. At entry, 89 and 91 patients were randomized to the citalopram tablets and placebo groups, respectively. This was the only study in which more male than female patients participated (64% vs. 36%). The initial dose of citalopram tablets, 20 mg/day, could be titrated to the maximal tolerated dose or a maximum dose of 80 mg/day. Patients treated with citalopram tablets showed significantly greater improvement than patients treated with placebo. At week 4, the average daily dose was 63 mg, with 52% of patients receiving the 80 mg/day dose.
In a 6-week fixed-dose study (Study #89303), patients received citalopram tablets, 20 or 40 mg/day, or placebo (n=64 to 70 per group). Patients treated with citalopram tablets, 40 mg/day, showed significantly greater improvement than placebo-treated patients. The difference between the lower dose of citalopram tablets and placebo was not significant.
In another 6-week fixed-dose study (Study #89306), patients received citalopram tablets, 20 or 40 mg/day or placebo (n=88 to 97 per group). Although citalopram tablets-treated patients improved to a somewhat greater degree than the placebo-treated patients, the differences between drug and control groups did not reach statistical significance due to a high placebo response, i.e., substantial improvement in the placebo group.
A 6-week, flexible-dose study was conducted in elderly (Study #86141), depressed patients (the mean age of male and female patients was 75 and 77 years, respectively) to determine the antidepressant effect and safety of citalopram tablets in this subpopulation. The number of patients who received citalopram tablets and placebo was 98 and 51, respectively. The study allowed patients to enter with lower baseline HAMD scores than are usually acceptable (≥18 in clinical trials). However, only a small percentage of patients had HAMD scores of less than 18 at entry. The dose of citalopram tablets was titrated from a starting dose of 10 mg/day to a maximum dose of 30 mg/day. Patients treated with citalopram tablets showed significantly greater improvement than patients treated with placebo. The final dose of citalopram tablets was 10, 20 and 30 mg/day in 5%, 51% and 44% of patients, respectively.
The effectiveness of citalopram tablets in preventing relapse was assessed in two long-term studies. Depressed patients who responded to citalopram tablets during an initial 6 or 8 weeks of acute treatment (fixed doses of 20 or 40 mg/day in one study and flexible doses of 20-60 mg/day in the second study) were randomized to continue on citalopram tablets or receive placebo. The number of patients who received citalopram tablets and placebo was 257 and 116, respectively. In both studies, patients who continued on citalopram tablets experienced significantly lower relapse rates over the subsequent 6 months compared to those receiving placebo. In the fixed-dose study, the relapse rates were similar at the 20 and 40 mg/day doses, namely 10% and 12%, respectively. Of the placebo-treated patients, 31% experienced relapse. In the flexible-dose study, the relapse rates were 14% and 24% in the citalopram tablets and placebo-treated patients, respectively. While the majority of patients (76%) were maintained on 20 or 40 mg/day of citalopram tablets during most of the study, some patients received 60 mg/day (not a recommended dose), while a few patients were maintained on less than 20 mg/day.
14.2 Comparative Bioavailability Studies
An open-labeled, randomized, two-treatment, two-period, two-sequence, single-dose, crossover comparative bioavailability study of PrAG-Citalopram Tablets 40 mg tablets (Angita Pharma Inc.) and CelexaTM 40 mg tablets (Forest Pharmaceuticals Inc, subsidiary of Forest Laboratories, Inc) was conducted in healthy, adult subjects under fasting conditions. Comparative bioavailability data from 23 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Citalopram (1 x 40 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72h (ng.h/mL) | ||||
1727.64 1772.95 (24.15) | 1665.00 1728.47 (28.51) | 103.7 | 97.6 - 110.2 | |
AUCI (ng.h/mL) | 2763.89 2911.29 (33.31) | 2655.65 2646.76 (47.48) | 104.1 | 97.4 - 111.2 |
Cmax (ng/mL) | 54.16 55.69 (24.72) | 53.82 55.59 (27.53) | 100.6 | 94.0- 107.8 |
Tmax3 (h) | 4.50 (2.50-16.00) | 4.25 (2.00-5.50) | ||
T½4 (h) | 51.11 (31.85) | 58.54 (39.65) | ||
1 AG-Citalopram Tablets (citalopram as citalopram hydrobromide) tablets, 40 mg (Angita Pharma Inc.).
2 Celexa (citalopram as citalopram hydrobromide) tablets, 40 mg (Forest Pharmaceuticals Inc, subsidiary of Forest Laboratories, Inc.)
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV%) only
16 Non-Clinical Toxicology
General Toxicology
Acute Toxicity
The LD50 values of citalopram ranged between 900-1700 mg/kg after oral administration and 38-74 mg/kg after intravenous administration. However, some mortality was also seen in the 400-600 mg/kg dose range, indicating a very flat dose-response curve regarding mortality.
Signs of toxicity were sedation and tremor, while convulsions occurred at doses close to or above the LD50 values.
Table 7 - LD50 Values in the Mouse and Rat (mg/kg body weight)
| Species | Sex | Route of Administration | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| i.v. | p.o. | i.p. | s.c. | i.m. | ||||||||||||
| Mouse | Male | 72 ± 9 | 1140 ± 190 | 220 ± 9 | 534 ± 71 | >400 | ||||||||||
| Female | 74 ± 10 | 900 ± 120 | 207 ± 20 | - | - | |||||||||||
| Rat | Male | 40 ± 4 | 1710 ± 292 | 157 ± 27 | 1950 ± 364 | >400 | ||||||||||
| Female | 38 ± 7 | 1426 ± 554 | 133 ± 17 | - | - | |||||||||||
A number of single dose toxicity studies have been carried out in dogs to investigate the potential cardiovascular toxicity of citalopram. In these studies, cardiotoxicity was not observed, but tonic-clonic convulsions were seen after oral administration of 20-40 mg/kg, as well as after slow intravenous infusion of 20-24 mg/kg. The critical plasma concentration for convulsions was about 1950 ng/mL.
Cardiovascular Effects
Citalopram blocked heterologous HERG-mediated currents in transfected Chinese hamster ovary cells with an IC50 of 4 mcM.
In conscious dogs, single oral doses of 5 mg/kg of citalopram caused pronounced fluctuation of the blood pressure and heart rate. A 10 mg/kg dose caused tachycardia and elevated blood pressure. The ECG was unchanged.
In anaesthetized cats, single oral doses of 35 mg/kg decreased the following parameters: mean arterial blood pressure, left ventricular end diastolic pressure, contractility, cardiac performance, stroke volume, and cardiac output. Peripheral resistance was increased. ECG abnormalities included alterations in conduction, changes in rhythm and T-wave inversion in 2 of 6 cats.
Convulsions, Arrhythmia and Death in Dogs
Toxicity studies in dogs revealed that citalopram administration led to fatal ventricular arrhythmias. Consequently, studies were undertaken to elucidate the mechanism of this effect and to determine its relevance to humans.
The studies have shown that, in dogs:
- i.v. infusion of citalopram, at a dose of 20 mg/kg, led to convulsions. The blood levels of citalopram were 1950 ng/mL at this dose. In the presence of diazepam, also infused intravenously, higher doses of citalopram could be infused, namely up to 70 mg/kg (6800 ng/mL). Convulsions and death also occurred when plasma citalopram levels exceeded 1950 ng/mL after oral administration.
- Intravenous infusion of the didemethyl metabolite of citalopram caused QT prolongation in a dose range of 5 to 22 mg/kg. The blood levels of the metabolite were 300 ng/mL at the 5 mg/kg dose. The QT prolongation was dose-dependent.
- When citalopram, 20 mg/kg, and didemethylcitalopram, 5 mg/kg, were infused concomitantly (in the presence of diazepam in order to prevent convulsions), 5 out of 9 dogs died due to ventricular fibrillation. At these doses, the plasma levels of citalopram and didemethylcitalopram were 1950 ng/mL and 300 ng/mL, respectively.
As shown in the table below, there is a substantial difference in the plasma levels of citalopram and its metabolite in dogs and in humans at the recommended therapeutic doses.
| Treatment | Dog ventricular fibrillation | Patients at steady state after a 40 mg/day dose of citalopram |
|---|---|---|
citalopram, 20 mg/kg plus didemethylcitalopram, 5 mg/kg | 1950 ng mL 300 ng/mL | 83 ng/mL 5.2 ng/mL |
Long-term Toxicity
Toxicological studies, including daily dosing for periods up to 26 weeks in mice and 52 weeks in rats and dogs, have been carried out. Plasma drug monitoring in the long-term safety studies documented that animals have been exposed to average citalopram levels of up to about 1200 ng/mL (dogs and rats) and 2900 ng/mL (mice), as well as substantial levels of demethylcitalopram [up to about 1800 ng/mL (rats), 600 ng/mL (dogs), 1150 ng/mL (mice)] and didemethylcitalopram [up to about 650 ng/mL (rats), 600 ng/mL (dogs), 300 ng/mL (mice)]. Apart from behavioral and functional characteristics of exaggerated 5 -HT stimulation (e.g., hyperactivity, tremor, tail rigidity, mydriasis, reduced food consumption, and reduced body weight gain), two treatment-related findings have been demonstrated in rodents, namely fatty infiltration of the liver and lipidosis (vacuolization of lymphocytes). Both of the findings were reversible. In addition, retinal degeneration and testicular atrophy were also observed in rats.
Toxicokinetics
Plasma levels were determined in several long-term toxicity studies. The table below summarizes the results seen in some of these studies.
| Species | Study | Dose mg/kg | CTa ng/mL | DCTb ng/mL | DDCTc ng/mL | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Ratd | 12-month tox po (diet) | 32 | male 330 female 334 | 474 391 | 246 204 | ||||||||
| 60 | male 690 female 826 | 989 862 | 497 290 | ||||||||||
| 120 | male 1163 female 1286 | 1947 1655 | 758 577 | ||||||||||
| Doge | 12-month tox po (in capsules) | 1 | 19 | 22 | 95 | ||||||||
| 3 | 350 | 170 | 314 | ||||||||||
| 8 | 1218 | 586 | 574 | ||||||||||
| Man | multiple dose po 6 weeks | 0.3 | 39 | 13 | 3.7 | ||||||||
| 0.6 | 83 | 28 | 5.2 | ||||||||||
| 0.9 | 121 | 41 | 6.3 | ||||||||||
a: citalopram; b: demethylcitalopram; c: didemethylcitalopram; d: average value at Week 52;
e: 2 hours postdose - Week 52 (1 and 3 mg/kg dose groups), Week 57 (8 mg/kg dose group).
The data indicate that the plasma levels of citalopram, as well as those of the demethylated metabolites, are considerably higher in animals than in man. The approximate 0.9 mg/kg dose in man corresponds a dose of 60 mg/day, and the 0.6 mg/kg dose corresponds to the highest clinical dose currently recommended (40 mg/day). The plasma levels of the parent drug, seen in rats and dogs at the highest doses, are approximately 10 times higher in animals than in man, while the levels of the didemethyl metabolites are almost 100 fold higher. In the rat, a NOEL (no observable effect level) could not be established in this study; at the low dose minimal vacuolization of hepatocytes with fatty infiltration, and foam cell accumulation in lungs were noted. The changes were reversible. In dogs, the NOEL was 3 mg/kg.
Hepatic Fatty Infiltration in Rodents
Fatty infiltration in the liver was first observed in a 3-month gavage study in rats given
8-32 mg/kg/day of citalopram. This administration resulted in dose-related hepatic fatty infiltration in all male rats but not in female rats at any of the doses. The fatty infiltration in male rats was also observed in a 4-week study, however, only at considerably higher doses
(>160 mg/kg). In female rats only minimal fatty infiltration was seen at a 200 mg/kg/day dose.
Lipidosis (phospholipids) in Rodents
Phospholipidosis, which has been seen in rodents, is an abnormal accumulation of phospholipids in phagocytic cells and cells which catabolize biomembranes, such as pulmonary alveolar macrophages and circulating leucocytes (especially lymphocytes).
Phospholipidosis developed in rats receiving citalopram at daily doses of 120 mg/kg and slight vacuolization of peripheral lymphocytes was observed in mice at daily doses of 100 mg/kg, in the 52-week and 26-week studies, respectively. Both conditions were reversible within 3-4 weeks.
Retinal Degeneration/Atrophy in Rats
In the rat carcinogenicity study, a slight, dose-related increase in lens opacity was seen, affecting males only. In addition, increased incidence/severity of retinal degeneration/atrophy was seen in the high-dose group (80 mg/kg/day). The incidence was higher in females, however, more female than male rats survived the study. It was concluded by an independent pathologist that the retinal changes were most likely related to drug-induced pupillary dilatation (mydriasis) which increased the risk of retinal damage in the already light-sensitive albino rat.
Testicular Atrophy in Rats
In the 52-week rat toxicity study, testicular atrophy was seen at the 60 and 120 mg/kg/day doses of citalopram.
Genotoxicity: Citalopram did not have mutagenic activity in most of the in vitro tests (Ames Salmonella assay; chromosome aberration assay in cultured human lymphocytes; gene mutation assay in cultured mouse lymphoma L5178Y) and in vivo tests (micronucleus test; unscheduled DNA synthesis). However, citalopram was mutagenic in some in vitro studies (Ames Salmonella assay and Chinese hamster lung cell assay).
Carcinogenicity: Citalopram did not show any carcinogenic potential in mice at daily doses of 40-240 mg/kg (1.5 years) and in rats at 8-80 mg/kg (2 years). There was an increased incidence of small intestine carcinoma in rats treated with 8 and 24 mg/kg/day of citalopram but not in rats treated with an 80 mg/kg/day dose.
Reproductive and developmental toxicology: Citalopram did not affect the reproductive performance of rats at dosages up to 16 mg/kg/day (males) and 32 mg/kg/day (females).
In the teratology studies in rats, effects were observed in the conceptuses at dosages that were toxic to the dams. Minimal developmental toxicity was evident at 32 mg/kg/day: manifested as low incidences of resorptions, slightly reduced fetal and pup weights, and small reversible delays in ossification and postnatal development.
In rabbits, dosages of 4.8 mg/kg/day and above were toxic to the dams, and 16 mg/kg/day and above caused deaths. There were no effects on embryo-fetal development at the highest dose that could be assessed (16 mg/kg/day).
In a rat embryo/fetal development study, oral administration of citalopram (32, 56, or 112 mg/kg/day) to pregnant animals during the period of organogenesis resulted in decreased embryo/fetal growth and survival and an increased incidence of fetal abnormalities (including cardiovascular and skeletal defects) at the high dose, which is approximately 27 times the maximum recommended human dose (MRHD) of 40 mg/day on a body surface area (mg/m2) basis. This dose was also associated with maternal toxicity (clinical signs, decreased body weight gain). The developmental, no-effect dose of 56 mg/kg/day is approximately 9 times the MRHD on a mg/m2 basis. In a second embryo/fetal developmental study in rats conducted at similar dose levels, no increase in fetal abnormalities were observed.
In a rabbit study, no adverse effects on embryo/fetal development were observed at doses of up to 16 mg/kg/day, or approximately 5 times the MRHD on a mg/m2 basis. Thus, teratogenic effects were observed at a maternally toxic dose in one embryo-foetal developmental study in the rats, but were not confirmed in a second rat study or in the rabbit.
When female rats were treated with citalopram (4.8, 12.8, or 32 mg/kg/day) from late gestation through weaning, increased offspring mortality during the first 4 days after birth and persistent offspring growth retardation were observed at the highest dose, which is approximately 5 times the MRHD on an mg/m2 basis. The no-effect dose of 12.8 mg/kg/day is approximately 2 times the MRHD on an mg/m2 basis. Similar effects on offspring mortality and growth were seen when dams were treated throughout gestation and early lactation at doses ≥ 24 mg/kg/day, approximately 4 times the MRHD on an mg/m2 basis. A no-effect dose was not determined in that study.
Fertility
Animal data have shown that citalopram induces a reduction of fertility index and pregnancy index, reduction in number in implantation and abnormal sperm at exposure well in excess of human exposure.
17 Supporting Product Monographs
- 1. CELEXA (Tablets, 10 mg, 20 mg and 40 mg citalopram hydrobromide (as base)), control 299602, product monograph, Lundbeck Canada Inc. (2025-12-01)