


Product Monograph - AJ-Vinorelbine
Indications and Clinical Use
AJ-VINORELBINE (vinorelbine injection USP) is indicated in the treatment of advanced non-small cell lung cancer (NSCLC), as a single agent or in combination.
AJ-VINORELBINE is also indicated for the treatment of patients with metastatic breast cancer who have failed standard first-line chemotherapy for metastatic disease. In addition, AJ-VINORELBINE is indicated for the treatment of patients with metastatic breast cancer who have relapsed within 6 months of anthracycline-based adjuvant therapy.
Contraindications
AJ-VINORELBINE is contraindicated in patients with known hypersensitivity to vinorelbine tartrate. As with other vinca alkaloids, AJ-VINORELBINE is contraindicated in patients who have drug-induced severe granulocytopenia or severe thrombocytopenia.
Warnings
AJ-VINORELBINE (vinorelbine injection USP) is a cytotoxic drug and should be used only by physicians experienced with cancer chemotherapeutic drugs. Blood counts should be taken prior to the next dose. Discontinue or reduce the dosage upon evidence of abnormal depression of the bone marrow.
AJ-VINORELBINE is for intravenous use only. Vinorelbine tartrate is a moderate vesicant and can produce phlebitis or extravasation injury. Inadequate flushing of the vein after peripheral administration may increase the risk of phlebitis.
It is extremely important that the needle be properly positioned in the vein before this product is injected.
If leakage into surrounding tissue should occur during intravenous administration of AJ-VINORELBINE, it may cause severe irritation. The injection should be discontinued immediately, and any remaining portion of the dose should then be introduced into another vein.
A low incidence of death (1 %) due to neutropenic sepsis has been reported (see ADVERSE
REACTIONS). Bone marrow toxicity, specifically granulocytopenia, is dose-limiting. Complete blood counts with differentials should be performed and results reviewed prior to each dose of AJ-
VINORELBINE. AJ-VINORELBINE should not be administered to patients with granulocyte counts
<1000 cells/mm3. Patients developing severe granulocytopenia should be monitored carefully for evidence of infection and/or fever (See DOSAGE AND ADMINISTRATION).
Pregnancy
There are no studies in pregnant women. Vinorelbine has been shown to be embryotoxic and/or fetotoxic in animals (see TOXICOLOGY). AJ-VINORELBINE should not be used in pregnancy.
Nursing Mothers
It is not known whether the drug is excreted in human milk. Because many drugs are excreted in human milk and because of its potential for serious adverse reactions in nursing infants, it is recommended that nursing be discontinued in women who are receiving therapy with AJ-VINORELBINE.
Use in Children
Safety and effectiveness in children have not been established.
Precautions
General
In all instances where the use of AJ-VINORELBINE is considered for chemotherapy, the physician must evaluate the need and usefulness of the drug against the risk of adverse events. Most drug-related adverse reactions are reversible. If severe adverse events occur, the drug should be reduced in dosage or discontinued and appropriate corrective measures should be taken based on the clinical judgment of the physician. Reinstitution of therapy with AJ-VINORELBINE should be carried out with caution and alertness as to possible recurrence of toxicity.
AJ-VINORELBINE should be used with extreme caution in patients whose bone marrow reserve may have been compromised by prior irradiation or chemotherapy, or whose marrow function is recovering from previous chemotherapy.
Administration of AJ-VINORELBINE to patients with prior radiation therapy may result in radiation recall reactions (see ADVERSE REACTIONS and Drug Interactions).
Patients with a prior history or pre-existing neuropathy, regardless of etiology, should be monitored for new or worsening signs and symptoms of neuropathy while receiving AJ-VINORELBINE.
Acute shortness of breath and severe bronchospasm have been reported infrequently following the administration of vinorelbine tartrate and of other vinca alkaloids. These events have been encountered most commonly when the vinca alkaloid was used in combination with mitomycin and may require aggressive treatment, particularly when there is pre-existing pulmonary dysfunction. Bronchodilators, steroids and/or oxygen have produced symptomatic relief.
Care must be exercised to avoid contamination of the eye with AJ-VINORELBINE. Accidental exposure should be treated immediately with a large volume of irrigation solution (water or sodium chloride).
Use in the Elderly
Of the total number of patients in North American clinical studies of intravenous vinorelbine tartrate, approximately one-third were 65 years of age or greater. No overall differences in effectiveness or safety were observed between these patients and younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
Use in Pregnancy
See Warnings.
Patients with Special Diseases and Conditions
Hematologic
Since dose-limiting clinical toxicity is the result of depression of the white blood cell count, it is imperative that complete blood counts with differentials be obtained prior to each dose of AJ-
VINORELBINE (See ADVERSE REACTIONS, Hematologic).
Hepatic
There is no evidence that the toxicity of vinorelbine tartrate is enhanced in patients with elevated liver enzymes; no data are available for patients with severe baseline cholestasis. However, pharmacologic evidence suggests that the liver plays an important role in the metabolism of vinorelbine tartrate.
Although there are no data available from patients with severe liver disease, caution should be exercised when administering AJ-VINORELBINE to patients with severe hepatic injury or impairment.
Drug Interaction
Acute pulmonary reactions have been reported with vinorelbine tartrate and other vinca alkaloids used in conjunction with mitomycin (see PRECAUTIONS, General). AJ-VINORELBINE should be administered with caution in combination with mitomycin. Although the pharmacokinetics of vinorelbine are not influenced by the concurrent administration of cisplatin, the incidence of toxicities, specifically granulocytopenia, high frequency hearing loss and tinnitus, with the combination of vinorelbine tartrate and cisplatin are higher than with single-agent vinorelbine tartrate.
Patients who receive AJ-VINORELBINE and paclitaxel, either concomitantly or sequentially, should be monitored for signs and symptoms of neuropathy. Administration of AJ-VINORELBINE to patients with prior or concomitant radiation therapy may result in radiosensitizing effects.
Information for Patients
Patients should be informed that AJ-VINORELBINE is a vesicant and can produce phlebitis or extravasation injury, and that the major acute toxicities of AJ-VINORELBINE are related to bone marrow toxicity, specifically granulocytopenia with increased susceptibility to infection, and neuropathy. They should also be advised to report fever or chills immediately. AJ-VINORELBINE should not be used in pregnancy unless the physician feels the potential benefit justifies the risk of potential harm to the fetus.
Adverse Reactions
Reporting Suspected Side Effects
You can report any suspected adverse reactions associated with the use of health products to the Canada Vigilance Program by one of the following 3 ways:
- Report online at www.healthcanada.gc.ca/medeffect
- Call toll-free at 1-866-234-2345
Complete a Canada Vigilance Reporting Form and:
- Fax toll-free to 1-866-678-6789, or
Mail to:
Canada Vigilance Program
Health Canada
Postal Locator 0701E
Ottawa, Ontario
K1A 0K9
Postage paid labels, Canada Vigilance Reporting Form and the adverse reaction reporting guidelines are available on the MedEffectTM Canada Web site at
www.healthcanada.gc.ca/medeffect.
NOTE: Should you require information related to the management of side effects, contact your health professional. The Canada Vigilance Program does not provide medical advice.
Data in the following tables are based on the experience of 365 patients (143 patients with NSCLC; 222 patients with advanced breast cancer) for whom a complete safety database was available and who were treated with vinorelbine tartrate as a single agent in three North American trials (one NSCLC trial and
two advanced breast cancer trials). Patients treated for breast cancer were allowed to have received adjuvant chemotherapy in both trials, and in one, up to two prior regimens for advanced disease. The dosing schedule was 30 mg/m2 intravenous vinorelbine tartrate on a weekly basis.
Table 1
Hematologic Adverse Events and Clinical Chemistry Elevations in 365 Patients Receiving Single-
Agent Vinorelbine Tartrate that are Possibly Attributable to the Study Medicationa,b
| Hematology | ABC (%) | NSCLC (%) | ||||||
Granulocytopenia <2,000 cells/mm3 <500 cells/mm3 Leukopenia <4,000 cells/mm3 <1,000 cells/mm3 Thrombocytopenia <100,000 cells/mm3 <50,000 cells/mm3 Anemia <11 g/dL <8 g/dL Hospitalization due to granulocytopenic complications | 96 41 99 16 6 <1 87 14 9 | 80 28 81 12 4 1 77 1 8 | ||||||
| Clinical Chemistry Elevations | % Incidence All Grades | % Incidence Grade 3 | % Incidence Grade 4 | |||||
| ABC | NSCLC | ABC | NSCLC | ABC | NSCLC | |||
Total Bilirubin NSCLC: n=137 ABC: n=214 | 14 | 9 | 4 | 3 | 3 | 2 | ||
SGOT NSCLC: n=133 ABC: n=213 | 74 | 54 | 7 | 2 | <1 | 1 | ||
ABC = Advanced Breast Cancer NSCLC = Non-Small Cell Lung Cancer a Grade based on modified criteria of the National Cancer Institute
b
Patients with NSCLC had not received prior chemotherapy. The majority of patients with advanced breast cancer had received prior chemotherapy.
Table 2
Summary of Adverse Events Occurring in ≥5% of 365 Patients Receiving Single-Agent Vinorelbine
Tartrate that are Possibly Attributable to the Study Medicationa,b
| Adverse Event | % Incidence All Grades | % Incidence Grade 3 | % Incidence Grade 4 | |||
| ABC n = 122 | NSCLC n = 143 | ABC n = 122 | NSCLC n = 143 | ABC n = 122 | NSCLC n = 143 | |
General Injection site reaction Asthenia Pain Pain injection site Fever Pain Abdomen Pain Chest Phlebitis | 21 41 16 18 19 12 8 5 | 38 25 15 13 10 6 5 10 | 1 8 3 3 1 1 1 0 | 5 5 2 1 0 1 2 1 | 0 0 0 0 0 0 0 0 | 0 0 0 0 1 0 0 0 |
Digestive System Nausea Constipation Anorexia Stomatitis Vomiting Diarrhea | 50 38 19 16 23 20 | 33 28 16 15 14 13 | 3 3 <1 0 2 <1 | 1 2 2 0 1 1 | 0 0 0 0 0 0 | 0 0 0 0 0 0 |
| Musculoskeletal System Myasthenia | 9 | 5 | 2 | 1 | <1 | 0 |
Nervous System Paresthesia Hypesthesia | 20 11 | 11 10 | 0 <1 | 1 0 | 0 <1 | 0 0 |
| Respiratory System Dyspnea | 9 | 3 | 1 | 2 | 1 | 0 |
Skin and Appendages Alopecia Rash | 12 5 | 12 5 | 0 0 | 1 0 | 0 0 | 0 0 |
ABC = Advanced Breast Cancer NSCLC = Non-Small Cell Lung Cancer a Grade based on modified criteria of the National Cancer Institute
b
Patients with NSCLC had not received prior chemotherapy. The majority of patients with advanced breast cancer had received prior chemotherapy.
Hematologic
Granulocytopenia was the major dose-limiting toxicity with vinorelbine tartrate; it was generally reversible and not cumulative over time. Granulocyte nadirs occurred 7 to 10 days after the dose and usually recovered within the following 7 to 14 days. Granulocytopenia resulted in hospitalizations for fever and/or sepsis in 8% of NSCLC and 9% of breast cancer patients. Septic deaths occurred in approximately 1 % of patients.
Grade 3 or 4 anemia occurred in 1 % of lung cancer and 14% of breast cancer patients. Blood products were administered to 18% of patients who received vinorelbine tartrate. The incidence of Grade 3 and 4 thrombocytopenia was less than 1%,
Neurologic
Mild to moderate peripheral neuropathy manifested by paresthesia and hypesthesia were the most frequently reported neurologic toxicities (10% to 20%, see Table 2). Loss of deep tendon reflexes occurred in less than 5% of patients. The development of severe peripheral neuropathy was unusual.
Dermatologic
Alopecia was reported in only 12% of patients and was usually mild.
Vinorelbine tartrate is a moderate vesicant. Injection site reactions, including erythema, pain at injection site, and vein discoloration occurred in approximately one-third of all patients; 2% were severe, Chemical phlebitis along the vein proximal to the site of injection was reported.
Gastrointestinal
Mild or moderate nausea occurred in 32% of NSCLC and 47% of breast cancer patients treated with vinorelbine tartrate. Severe nausea was infrequent (1 % and 3% in NSCLC and breast cancer patients respectively). Prophylactic administration of antiemetics was not routine in patients treated with single-agent vinorelbine tartrate. Constipation occurred in approximately 28% of NSCLC and 38% of breast cancer patients, with paralytic ileus occurring in less than 2% of patients. Vomiting, diarrhea, anorexia, and stomatitis were usually mild or moderate and occurred in less than 20% of patients.
Hepatic
Transient elevations of liver enzymes were reported without clinical symptoms.
Cardiovascular
Chest pain was reported in 5% of NSCLC and 8% of breast cancer patients. Most reports of chest pain were in patients who had either a history of cardiovascular disease or tumor within the chest. There have been rare reports of myocardial infarction; however, these have not been shown definitely attributable to vinorelbine tartrate.
Pulmonary
Shortness of breath was reported in 3% of NSCLC and 9% of breast cancer patients; and was severe in
2% of each patient population. Interstitial pulmonary changes have been documented in a few patients.
Other
Asthenia occurred in approximately 25% of patients with NSCLC and 41 % of patients with breast cancer. It was usually mild or moderate but tended to increase with cumulative dosing.
Other toxicities that have been reported in ≤5% of patients include jaw pain, myalgia, arthralgia, headache, dysphagia, and rash. Hemorrhagic cystitis and the syndrome of inappropriate ADH secretion were each reported in <1 % of patients. The treatment of these entities is mainly symptomatic. The treatment of hemorrhagic cystitis is i.v. fluids for forced diuresis and/or irrigation of bladder. For the treatment of SIADH, please refer to the major textbooks of medicine.
Observed During Clinical Practice:
In a randomized study in NSCLC patients, 206 patients received treatment with vinorelbine tartrate plus cisplatin and 206 patients received single-agent vinorelbine tartrate. The incidence of severe nausea and vomiting was 30% for vinorelbine tartrate/cisplatin compared to <2% for single-agent vinorelbine tartrate.
Cisplatin did not appear to increase the incidence of neurotoxicity observed with single-agent vinorelbine tartrate. However, myelosuppression, specifically Grade 3 and 4 granulocytopenia, was greater with the combination of vinorelbine tartrate/cisplatin (79%) than with single-agent vinorelbine tartrate (53%). The incidence of fever and infection may be increased with the combination.
In addition to adverse events reported from clinical trials, the following events have been identified during post marketing use of vinorelbine tartrate.
Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. These events have been chosen for inclusion due to combination of their seriousness, frequency of reporting, or potential causal connection to vinorelbine tartrate or a combination of these factors.
Body as a Whole: Systemic allergic reactions reported as anaphylaxis, pruritis, urticaria and angioedema, flushing and radiation recall events such as dermatitis and esophagitis (see PRECAUTIONS) have been reported.
Hematologic: Thromboembolic events including pulmonary embolus and deep venous thrombosis have been reported primarily in seriously ill and debilitated patients with known predisposing risk factors for these events.
Neurologic: Peripheral neurotoxicities such as, but not limited to, muscle weakness and disturbance of gait have been observed in patients with and without prior symptoms. Vestibular and auditory deficits have been observed with vinorelbine tartrate, usually when used in combination with cisplatin. There may be increased potential for neurotoxicity in patients with pre-existing neuropathy, regardless of etiology, who receive vinorelbine tartrate. Patients who receive vinorelbine tartrate and paclitaxel, either concomitantly or sequentially, should be monitored for signs and symptoms of neuropathy (see
PRECAUTIONS).
Skin: Injection site reactions, including localised rash and urticaria, blister formation and skin sloughing have been observed in clinical practice. Some of these reactions may be delayed in appearance.
Gastrointestinal: Dysphagia and mucositis have been reported.
Cardiovascular: Hypertension, hypotension, vasodilation, tachycardia, and pulmonary edema have been reported.
Pulmonary: Pneumonia has been reported.
Vinorelbine can produce acute and subacute pulmonary reactions. The acute reaction usually resembles an allergic event and may respond to bronchodilators. Subacute pulmonary reactions occur shortly after drug administration and may be characterized by cough, dyspnea, hypoxemia, and interstitial infiltration.
Subacute pulmonary reactions may respond to corticosteroid therapy.
Musculoskeletal: Headache has been reported with and without other musculoskeletal aches and pains.
Other: Pain in tumour-containing tissue, back pain and abdominal pain have been reported. Electrolyte abnormalities including hyponatremia, consistent with the syndrome of inappropriate ADH secretion, have been reported in seriously ill and debilitated patients.
Combination Use: Patients with prior exposure to paclitaxel and who have demonstrated neuropathy should be monitored closely for new or worsening neuropathy. Patients who have experienced neuropathy with previous drug regimens should be monitored for symptoms of neuropathy while receiving AJ-
VINORELBINE. AJ-VINORELBINE may result in radiosensitizing effects with prior or concomitant radiation therapy (see PRECAUTIONS).
Symptoms and Treatment of Overdosage
For management of a suspected drug overdose, contact your regional Poison Control Centre.
The primary anticipated complications of overdosage would consist of bone marrow suppression and peripheral neurotoxicity.
There is no known antidote for vinorelbine tartrate overdosage. Overdoses involving quantities up to ten times the recommended dose (30 mg/m2) have been reported. The toxicities described were consistent with those listed in the Adverse Reactions section including paralytic ileus, stomatitis, and esophagitis.
Bone marrow aplasia, sepsis, and paresis have also been reported. Fatalities have occurred following overdose of vinorelbine tartrate. If overdosage occurs, general supportive measures together with appropriate blood transfusions, growth factors and antibiotics should be instituted as deemed necessary by the physician.
Dosage and Administration
This preparation is for intravenous administration only. It should be administered by individuals experienced in the administration of cancer chemotherapeutic drugs.
Dosage
The usual initial dose of AJ-VINORELBINE is 30 mg/m2 administered weekly. The recommended method of administration is an intravenous injection over 6 to 10 minutes. In controlled trials, single-agent vinorelbine tartrate was given weekly until progression or dose-limiting toxicity.
No dose adjustments are required for renal insufficiency. If moderate or severe neurotoxicity develops,
AJ-VINORELBINE should be discontinued. The dosage should be adjusted according to hematologic toxicity or hepatic insufficiency.
Dose Modifications for Hematologic Toxicity: Granulocyte counts should be: ≥1000 cells/mm3 prior to the administration of AJ-VINORELBINE. In the referenced North American trial, in which hematologic adverse events were observed, the following dose adjustment scheme was employed and should be followed in patients receiving AJ-VINORELBINE.
TABLE 3
Dose Adjustments Based on Granulocyte Counts
| Granulocytes (cells/mm3) on days of Treatment | Dose of AJ-VINORELBINE (mg/m2) |
| ≥ 1500 | 30 |
| 1000 to 1499 | 15 |
| < 1000 | Do not administer. Repeat granulocyte count in 1 week. If granulocyte count is <1000 cells/mm3 for >3 weeks, discontinue VINORELBINE INJECTION. |
Note: For patients who, during treatment with AJ-VINORELBINE, have experienced fever and/or sepsis while granulocytopenic or required a delay in dosing of up to 3 weeks due to granulocytopenia, the dose of AJ- VINORELBINE should be: 22.5 mg/m2 for granulocytes ≥ 1500 cells/m3 11.25 mg/m2 for granulocytes 1000 to 1499 cells/m3 | |
AJ-VINORELBINE should be administered with caution to patients with hepatic insufficiency. In patients who develop hyperbilirubinemia during treatment with AJ-VINORELBINE, the dose should be adjusted for total bilirubin.
Administration Precautions
AJ-VINORELBINE must be administered intravenously. It is extremely important that the intravenous needle or catheter be properly positioned before any AJ-VINORELBINE is injected. Leakage into surrounding tissue during intravenous administration of AJ-VINORELBINE may cause considerable irritation, local tissue necrosis and/or thrombophlebitis. If extravasation occurs, the injection should be discontinued immediately, and any remaining portion of the dose should then be introduced into another vein. The application of moderate heat to the area of leakage in the form of warm compress applied for 15 to 20 minutes at least four times per day for the first 24 to 48 hours in addition to rest and elevation of the affected site for 48 -72 hours has been reported to help disperse drug and minimize discomfort associated with the extravasation of other vinca alkaloids.
As with other toxic compounds, caution should be exercised in handling and preparing the solution of AJ-
VINORELBINE. Skin reactions may occur with accidental exposure. The use of gloves is recommended.
If the solution of AJ-VINORELBINE contacts the skin or mucosa, immediately wash the skin or mucosa thoroughly with soap and water. Severe irritation of the eye has been reported with accidental
contamination of the eye with another vinca alkaloid. If this happens with AJ-VINORELBINE, the eye should be washed with water immediately and thoroughly.
Preparation for Administration: AJ-VINORELBINE must be diluted in either a syringe or I.V. bag using one of the recommended solutions. The diluted AJ-VINORELBINE should be administered over 6 to 10 minutes into the side port of a free-flowing I.V. followed by flushing with at least 75 to 125 mL of one of the solutions. For diluents that may be used, see PHARMACEUTICAL INFORMATION,
Reconstituted Solutions.
Syringe: The calculated dose of AJ-VINORELBINE should be diluted to a concentration between 1.5 and 3.0 mg/mL.
I.V. Bag: The calculated dose of AJ-VINORELBINE should be diluted to a concentration between 0.5 and 2.0 mg/mL.
Pharmaceutical Information
Drug Substance
Proper Name: vinorelbine tartrate
Chemical Name: 3',4'-didehydro-4'-deoxy-C'norvincaleukoblastine- di-L-tartrate
Structural Formula:
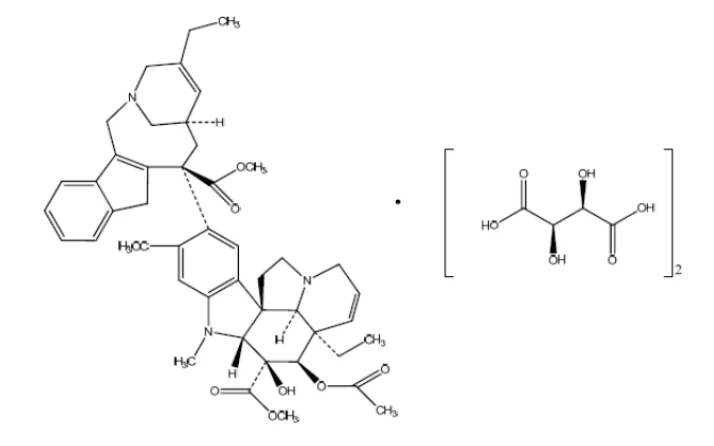
Molecular Formula: C45H54N4O8•2C4H6O6
Molecular Weight: 1079.11 g/mol
Description: Vinorelbine tartrate is a white to yellow or light brown amorphous powder, have a melting point of 210°C with decomposition. It is soluble in water, in ethanol and methanol, and practically insoluble in hexane.
Composition
AJ-VINORELBINE consists of an aqueous solution of vinorelbine tartrate, equivalent to 10 mg vinorelbine base per millilitre of solution. No other preservatives or other additives are present. AJ-
VINORELBINE is a clear colorless to pale yellow solution in Water for Injection.
Stability and Storage Recommendations
Store AJ-VINORELBINE vials under refrigeration (2° to 8°C) in the original package to protect from light. This product should not be frozen.
AJ-VINORELBINE is initially clear and colourless to pale yellow, but may develop a slightly darker yellow to light amber colour in time. This does not indicate a change which should preclude its use.
Parenteral drug products should be visually inspected for particulate matter and discoloration prior to administration whenever solution and container permit. If particulate matter is seen, AJ-VINORELBINE should not be administered.
Reconstituted Solutions
Syringe: AJ-VINORELBINE diluted to a concentration between 1.5 and 3.0 mg/mL may be used for up to 24 hours when stored in polypropylene syringes at 5° to 30°C. The following solutions may be used for dilution:
5% Dextrose Injection, USP
0.9% Sodium Chloride Injection, USP
I.V. Bag: AJ-VINORELBINE diluted to a concentration between 0.5 and 2.0 mg/mL may be used for up to 24 hours when stored in polyvinylchloride bags at 5° to 30°C. The following solutions may be used for dilution:
5% Dextrose Injection, USP
0.9% Sodium Chloride Injection, USP
0.45% Sodium Chloride Injection, USP
5% Dextrose and 0.45% Sodium Chloride Injection, USP
Ringer's Injection, USP
Lactated Ringer's Injection, USP
As with all the parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, discoloration and leakage prior to administration, whenever solution and container permit. Any unused portion should be discarded.
Special Instructions
Since vinorelbine tartrate is a cytostatic agent, established procedures specific to the handling and use of such agents must be followed.
Availability of Dosage Forms
AJ-VINORELBINE is supplied in clear flint glass vials as a solution of 10 mg/mL vinorelbine base in 1 mL and 5 mL single-dose vials.
Pharmacology
Pharmacodynamics
Antitumour Activity: In vitro: Vinorelbine tartrate was a potent inhibitor of tumour cell growth with broad spectrum activity comparable to vincristine (VCR) and vinblastine (VLB). Vinorelbine was shown to participate in both multi-level drug resistance (MDR) and non-MDR forms of resistance. In combination studies, an additive effect was noted when cells were exposed sequentially to vinorelbine and then to cisplatin, while synergy was observed with a simultaneous combination of vinorelbine and paclitaxel.
In vivo: Vinorelbine tartrate demonstrated antitumour activity in both murine and human tumour xenograft models that have been previously shown to be sensitive to either VLB or VCR. Vinorelbine was active by the intraperitoneal (IP), oral (PO) and intravenous (IV) routes on several administration schedules against IP, IV and subcutaneous (SC) implants of various murine tumours. Vinorelbine when administered IV, was also active against SC implants of lung, mammary and stomach human tumour xenografts in nude mice. Vinorelbine plus either etoposide or cisplatin provided a significant advantage in increased life span (lLS) over that of comparably dosed single agents.
Antitubulin Activity: In vitro: In cultured mouse embryos, vinorelbine tartrate was active against all classes of mitotic microtubules (the antitumour target), while it was least active against axonal microtubules (the neurotoxic target). At pharmacologic concentrations in cell-free systems, vinorelbine was much less effective than VLB or VCR at inducing spiralization of microtubules (a potential toxicity endpoint). Vinorelbine, VLB and VCR were equipotent in inhibiting assembly regardless of isotubulins or microtubule associated proteins (MAPS).
Cell Cycle Arrest: At physiologic concentrations, vinorelbine tartrate was similar to other vinca alkaloids in its effect on tumour cell cycle kinetics, producing mitotic arrest (block in M phase without altering G2 phase) and polyploidy. Polyploid cells are usually non-viable and this probably plays a role in the mechanism of antitumour activity.
Neuropharmacological Effect in Mice and Rats:
Neuropharmacologically, vinorelbine tartrate presented the same hypothermic and acute neurotoxicity profile expected of the vinca alkaloids. Mice treated intravenously with vinorelbine experienced only slight hypothermia, which, although statistically significant, was within standard pharmacological limits.
No characteristic signs that typically accompany hypothermia (e.g., ptosis, piloerection, or tremors) were noted in the vinorelbine tartrate-treated animals. Vinorelbine produced neurotoxic effects in rats after acute IV administration, similiar to those that occurred with VCR. However, unlike VCR, vinorelbine did not produce limb paralysis. And, although mortalities occurred after both IV vinorelbine and VCR administration, a 10-fold greater dose of vinorelbine than VCR was required to produce the same effect.
Cardiovascular/Respiratory Effect in Dogs: Cardiovascular and respiratory studies of IV vinorelbine tartrate in anesthetized dogs indicate that vinorelbine (along with two other vinca alkaloids studied) has no effect on hemodynamics, respiratory function, or the incidence of cardiac arrhythmias.
Gastrointestinal Effects in Mice and Rats: Possible gastrointestinal (GI) effects of vinorelbine tartrate were explored using models of GI transit, GI tolerance, and gastric secretion. In mice, IV treatment with vinorelbine had no effect on the GI transit time in a standard charcoal meal test. In mice and rats, IV vinorelbine showed excellent GI tolerance, with no evidence of ulcers or bleeding in the esophagus, stomach or intestine. Vinorelbine was found to inhibit gastric secretion after IV administration in rats.
This effect, however, occurred at one half the LD50 dose.
Urinary System Effects in Rats: Studies with vinorelbine tartrate on renal function indicate a moderate diuretic effect in rats after IV administration. Additionally, a pronounced increase in electrolyte elimination occurred. And, although there was evidence of hemolyzed blood in the urine after high IV doses of vinorelbine, examination of the kidneys and bladder revealed no histologic changes.
Hemobiologic Effects in Rats: Hemobiologic studies with vinorelbine tartrate showed a platelet antiaggregating property in vitro, but only at the very high concentration of 1.0 mM, which at minimum is
1000-fold the therapeutic plasma concentration.
Pharmacokinetics
In vitro studies have shown that vinorelbine is rapidly and highly distributed into cells. Studies of vinorelbine binding to human blood constituents revealed high binding to platelets and lymphocytes. The free fraction was ~0.11 in pooled human plasma over a concentration range of 234 to 1169 ng/mL. The binding to plasma constituents in cancer patients ranged from 79.6% to 91.2%. Vinorelbine binding was not altered in the presence of cisplatin, 5-fluorouracil, or doxorubicin.
Absorption and Disposition: In all animal species studied (mouse, rat, dog, monkey), vinorelbine tartrate plasma concentration declined in a multiexponential manner with an initial rapid decay followed by a slower terminal phase. Half-life values, after intravenous administration, were 7.3 hours in the mouse and 9.5 hours in the rat. Half-lives were considerably longer in the dog (ranging from 13 to 42 hours after various oral doses) and the monkey (16.6 to 35.5 hours after various oral and intravenous doses). Plasma clearances, estimated after intravenous administration in the rat and monkey, were 2 L/h/kg and 0.54
L/h/kg, respectively. Vinorelbine was shown to be rapidly absorbed after oral administration in all species studied with Tmax values ranging from 1 to 2 hours after administration. The bioavailability of radioactivity in the mouse was 25% following a radiolabelled dose, while absorption of radioactivity was essentially complete after oral administration to the monkey. Absolute bioavailability in the rat, determined using immunoassay methodology, was found to be 16%.
Tissue Distribution: In tissue distribution studies of radiolabelled vinorelbine tartrate, radioactivity was widely distributed throughout the animals studied (mouse, rat, and monkey) with the highest amounts of radioactivity typically found in organs of elimination such as liver and kidneys. Minimal amounts of radioactivity were found in the heart and brain tissue.
Elimination and Metabolism: Vinorelbine tartrate was primarily eliminated in the feces in all species studied (mouse, rat and monkey). Typically, 50% to 80% of an administered dose was recovered, regardless of the route of administration. A small percentage of the dose was excreted in the urine (1% to
19%, usually < 10%) and the majority of the amount excreted was recovered as unchanged drug.
Evidence for substantial metabolism exists, and excretion via the bile appears to be a significant pathway for metabolites and parent drug. Three metabolites were isolated from perfused rat liver preparations, but not in sufficient quantity for identification. In vivo isolation and identification of metabolites was hindered because of the low quantities of metabolites present in animals administered non-toxic doses and the inadequate sensitivity of analytical methodology.
Clinical Trials
Advanced Non-Small Cell Lung Cancer (NSCLC)
Data from two controlled clinical studies (612 + 211 patients), as well as additional data from more than
100 patients enrolled in two uncontrolled clinical trials, support the use of vinorelbine tartrate in patients with advanced non-small cell lung cancer (NSCLC). One randomized, three-arm trial in 612 Stage III or
IV NSCLC patients compared treatment with single-agent vinorelbine tartrate (30 mg/m2/week), vinorelbine tartrate (30 mg/m2/week) plus cisplatin (120 mg/m2 days 1 and 29, then every six weeks), and vindesine (3 mg/m2/week for 7 weeks, then every other week) plus cisplatin (120 mg/m2 days 1 and 29, then every 6 weeks). Vinorelbine tartrate, as a single agent, was well-tolerated and resulted in a median survival of 31 weeks and a response rate of 14%. The combination of Vinorelbine tartrate plus cisplatin produced a median survival of 40 weeks and a response rate of 28%. The results achieved with
Vinorelbine tartrate as a single agent were comparable to those seen with vindesine plus cisplatin (median survival 32 weeks and response rate of 19%), but significantly less severe nausea, vomiting, and neurotoxicity were observed in patients treated with single-agent vinorelbine tartrate. In the subgroup of patients with Stage IV disease, vinorelbine tartrate plus cisplatin produced longer survival than vindesine plus cisplatin (36 weeks vs 27 weeks).
The results with single-agent vinorelbine tartrate noted in the above trial were confirmed in a second randomized, two-arm study (211 patients) which compared treatment with single-agent vinorelbine tartrate (30 mg/m2 weekly) to a control drug, 5-fluorouracil (5FU) (425 mg/m2 IV bolus) plus leucovorin
(LV) (20 mg/m2 IV bolus) administered five consecutive days every four weeks. Compared to 5 FU/LV, vinorelbine tartrate improved survival. The median survival for patients treated with vinorelbine tartrate was 30 weeks versus 22 weeks for 5FU/LV. The median survival for similar patients given best supportive care is reported to range from 9 to 21 weeks. The one year survival rates were, 24% (±4%
S.E.) for vinorelbine tartrate and 16% (±S% S.E.) for 5FU/LV, using the Kaplan-Meier product-limit estimates. The response rates for vinorelbine tartrate and 5FU/LV were 14% and 5%, respectively.
In an uncontrolled study in 78 patients with inoperable NSCLC treated with single-agent vinorelbine tartrate (30 mg/m2/week), the median survival was 33 weeks. The response rate was 33%. A Phase I/II dose-ranging study of vinorelbine tartrate (20, 25, or 30 mg/m2/week) plus cisplatin (120 mg/m2 days 1 and 29, then every 6 weeks) in 32 patients with NSCLC demonstrated a median survival of 44 weeks.
There were no responses at the lowest dose level; the response rate was 33% in the 21 patients treated at the two highest dose levels.
Advanced Breast Cancer
Data from one randomized, controlled clinical study (179 patients) and three uncontrolled studies (302 patients) support the effectiveness of vinorelbine tartrate in patients with advanced breast cancer. The randomized, controlled trial compared vinorelbine tartrate (30 mg/m2/week) to intravenous melphalan (25 mg/m2/every 4 weeks) in patients who had progressed on one or two prior chemotherapy regimens for advanced disease, with one regimen containing an anthracycline. Patients who relapsed during or within 6 months of treatment with an anthracycline-containing adjuvant chemotherapy regimen were also eligible.
Melphalan was chosen as a Phase II comparator because of the lack of a commonly accepted standard treatment in this patient population. Treatment with vinorelbine tartrate resulted in significantly longer time to disease progression, time to treatment failure, and survival compared to melphalan. Median time to disease progression was 12 weeks for the vinorelbine tartrate patients and 8 weeks for the melphalan arm (p<O.001). Median time to treatment failure was 11 weeks and 8 weeks respectively, for the vinorelbine tartrate and melphalan groups (p<0.001). The median survival was 35 weeks for the group receiving vinorelbine tartrate and 31 weeks for the melphalan arm (p=0.03). The 1-year survival rates were 36% and 22% respectively, for the vinorelbine tartrate and melphalan groups. Although the proportion of patients who responded to vinorelbine tartrate (16%) was greater than those responding to melphalan (9%), the difference was not significant (p=0.42). However, when objective responses and stabilization were combined, the difference approached significance in favor of vinorelbine tartrate (47% vs 28%, p=0.06). Disease-related symptoms improved or remained stable compared to baseline in the majority of patients in both groups.
An uncontrolled study conducted in the U.S. was designed to determine the safety and efficacy of vinorelbine tartrate (30 mg/m2/week) used as first-line or second-line therapy in the treatment of patients with advanced breast cancer. Patients were not previously treated with an anthracycline containing regimen. The overall response rate was 35% for 60 first-line patients and 32% for 47 second-line patients.
There were 9 (15%) complete responses and 12 (20%) partial responses among the first-line patients. The median duration of response was 34 weeks for both first- and second line patients. There were 3 (6%)
complete responses and 12 (26%) partial responses among second-line patients. The estimated median duration of complete response for first- and second-line patients combined exceeds 1 year.
A total of 195 patients were treated with single-agent vinorelbine tartrate (30 mg/m2/week) in two
European Phase II clinical trials. The patients in both trials had no previous cytotoxic therapy for
advanced breast cancer. In one trial, the objective response rate was 41 % in 145 evaluable patients. In the other trial, an objective response rate of 50% was observed in 50 evaluable patients.
Toxicology
Animals
Acute Toxicity
Rodents: Single-dose lethality values calculated from the results of mouse and rat studies are listed below. The combined male/female value is given, as no sex differences were apparent.
TABLE 4
Acute Toxicity Vinorelbine
| Species/Strain | Route | LD10 (mg/kg) | LD50 (mg/kg) | LD90 (mg/kg) |
| Mouse/CD-1 | IV | 21.9 | 36.1 | 59.3 |
| Mouse/OF1 | IV | 30.4 | 36.6 | 43.8 |
| Rat/Sprague-Dawley | IV | 10.1 | 11.2 | 12.4 |
| Rat/Sprague-Dawley | IV | 11.2 | 14.1 | 17.6 |
| Mouse/CD-1 | Oral | 56.4 | 82.8 | 121.5 |
| Rat/Sprague-Dawley | Oral | 23.6 | 30.0 | 38.1 |
| Mouse/CD-1 | IP | 16.6 | 24.5 | 39.3 |
| Mouse/OF1 | IP | 22.7 | 35.5 | 55.5 |
| Rat/Sprague-Dawley | IP | 6.0 | 10.1 | 17.1 |
| Rat/Sprague-Dawley | IP | 2.6 | 6.2 | 14.7 |
Ataxia, convulsions and respiratory difficulty were noted almost immediately after dosing in animals treated intravenously at the highest doses. Deaths occurred as early as 15 minutes postdose. Clinical signs seen in animals treated by all three routes included lethargy and piloerection in mice and rats and diarrhea, chromodacryorrhea, edema of the muzzle, and prostration in rats. Swollen abdomens and evidence of peritonitis were noted in some animals treated by the intraperitoneal route. Deaths occurred from day 1 to as late as 16 and 29 days postdose in mice and rats respectively.
Lethality studies using daily doses for 5 days were conducted in mice (IV) and rats (oral). The 5-day cumulative mg/kg values calculated were as follows:
TABLE 5 Lethality Studies
| Species/Strain | Route | LD10 (mg/kg) | LD50 (mg/kg) | LD90 (mg/kg) |
| Mouse/OF1 | IV | 31.6 | 39.8 | 49.9 |
| Rat/Sprague-Dawley | Oral | - | 14 | - |
Mortality occurred from day 6 to 23 in mice and day 4 to 21 in rats, with clinical signs first noted on days
5 or 6. Piloerection, muzzle or facial edema, and subdued behavior were seen in both species. In addition, skin paleness was noted in mice and diarrhea, chromorhinorrhea, and vaginal bleeding were seen in rats.
Thus single and cumulative intravenous 5-dose LD50S in mice were essentially the same (36 and
40 mg/kg) and the cumulative oral 5-dose LD50 in rats was the same as the intravenous single dose LD50 in rats (14 and 14.1 mg/kg).
Beagle dogs: The beagle dog was the most susceptible of any species tested in single dose studies. An oral dose of 2.0 mg/kg and an intravenous dose of 1.0 mg/kg were lethal. Toxic effects included leukopenia, enteritis, elevated liver enzymes with or without histopathological evidence of hepatic necrosis or biliary hyperplasia, bone marrow hypoplasia and lymphoid depletion of spleen/lymph nodes.
The lowest dose where one or more toxic effects were recorded was 0.5 mg/kg (oral and IV).
Monkeys: Acute toxic effects in rhesus and cynomolgus monkeys were observed after oral doses of 36 mg/kg (only dose tested) and 20 mg/kg (lowest dose) respectively and were similar to those seen in beagle dogs.
Vinorelbine Injection – Product Monograph Page 26 of 30
TABLE 6 Subchronic/Chronic Toxicity
| Species/Strain | No. per Group | Route | Dose (mg/kg) | Frequency | Duration | Drug-Related Findings (Lowest Dose where Effect Noted) |
| Rat/ Sprague-Dawleya | 5M, 5F | IV | 1.0, 2.0, 5.0 | 1 x wk | 9 wk | 1.0 Decreased WBC/RBC, elevated liver enzymes, infections, injection site irritation 2.0 Decreased body weight 5.0 Mortality |
| Dog/Beagle | 2M, 2F | IV | 0.25, 0.50, 0.75 | 1 x wk | 13 wk | 0.25 Injection site irritation 0.50 Decreased WBC, thymic involution, injection site irritation 0.75 Mortality, decreased RBC, increased hepatic enzymes, decreased body weight, infections |
| Monkey/ Rhesus | 1M, 1F 1M, 1F 1M, 1F 1M, 1F | IV IV IV IV | 0.75, 1.0, 1.50, 2.0 1.0 0.20-0.80 escalating doseb 2.0-4.0 cyclicc | 1 x wk 2 x wk 5 x wk, off 2 wks (1 cycle) 1 x wk | 29-39 wk 5 wk 15 cycles 4 wk | 0.75 Decreased WBC/RBC, injection site irritation 1.50 Enteritis, decreased body weight 2.00 Bone marrow hypoplasia Decreased WBC/RBC, decreased body weight, thymic involution Mortality, decreased WBC/RBC, thymic involution and bone marrow hypoplasia following completion of the dosage regimen Mortality, enteritis, decreased WBC/RBC, decreased body weight, bone marrow hypoplasia |
| Rat/ Sprague-Dawleya | 6M, 0F 6M, 0F | Oral Oral | 5.0, 10.0 15.0, 20.0 | 2 x wk 1 x wk | 4 wk 4 wk | 5.0 Decreased RBC 10.0 Mortality, decreased WBC, increased hepatic enzymes, decreased body weight, infections 15.0 Mortality, decreased RBC, increased hepatic enzymes, decreased body weight, infections 20.0 Decreased WBC |
| Rat/ Sprague-Dawleya | 10M, 10F 10M, 10F | Oral Oral | 1.0, 2.0, 4.0 7.0, 14.0 | daily 1 x wk | 42 days 6 wk | 2.0 Increased hepatic enzymes 4.0 Mortality, decreased WBC/RBC, reduced body weight, thymic involution, bone marrow hypoplasia 7.0 Decreased WBC/RBC4 14.0 Mortality, increased hepatic enzymes, reduced body weight, thymic involution, bone marrow hypoplasia |
| Monkey/Rhesus | 1M, 1F | Oral | 4.0-70.0 escalatinge | 1 x wk | 13 wk | Enteritis, decreased WBC/RBC, increased hepatic enzymes, thymic involution, bone marrow hypoplasia |
| Monkey/Rhesus | 2M or 2F | Oral | 4.0, 10.0 | 1 x wk | 13 wk | 4.0 decreased WBC, increased hepatic enzymes |
a – as noted in previous studies, affected rats showed signs of piloerection, decreased activity and muzzle swelling b – 0.20 mg/kg (3 cycles), 0.40 mg/kg (6 cycles), 0.60 mg/kg (3 cycles), 0.80 mg/kg (3 cycles) c
- 4.0 mg/kg for 3 weeks followed by 2.0 mg/kg for 1 week (3.0 mg/kg for 4 weeks after washout in 1 animal) d – splenic extramedullary hematopoiesis – 7 mg/kg once weekly dose only
e – 4.0 mg/kg escalating to 6.0, 8.0, 10.0, 12.0, 14.0, 20.0, 30.0, 40.0, 50.0, 70.0, 70.0 (weeks 2-13)
Vinorelbine Injection – Product Monograph Page 27 of 30
Mutagenicity
Vinorelbine tartrate was shown to be mutagenic in a mouse micronucleus assay and an in vivo cytogenetics study in which bone marrow cells from treated Chinese hamsters were examined. The effect seen, polyploidy, is one that the Ames and mouse lymphoma mutagenesis assays do not detect and these assays were negative or equivocal with vinorelbine tartrate.
Reproduction and Teratology
Reproduction: No deleterious effects on maternal or fetal parameters were seen in an intravenous rat fertility/reproduction study in which males were treated once weekly for 9 weeks and females once weekly for 4 weeks with a dose of 1.5 mg/kg vinorelbine tartrate.
Teratology: Vinorelbine tartrate was found to be embryotoxic when given to mice once during gestation at 1 to 5 mg/kg intravenously but not at 0.5 mg/kg.
Other Studies
The in vitro hemolysis and protein flocculation test with human blood revealed a 10 mg/mL solution of vinorelbine tartrate to be unlikely to exert any hemolytic or protein flocculation problems when used clinically.
An acute study of 17 deacetyl vinorelbine sulfate (a vinorelbine tartrate degradation product) resulted in a
LD50 of 23.0 mg/kg. Clinical signs of toxicity included subdued behaviour, prostration, piloerection and clonic convulsions. In a mouse micronucleus mutagenicity study, 17 deacetyl vinorelbine produced an increase in the incidence in micronuclei in mice sampled 24 or 48 hours postdose. Bromo-12-vinorelbine sulfate (a vinorelbine tartrate process impurity) was negative in the same assay.
Vinorelbine Injection – Product Monograph Page 28 of 30
TABLE 7 Teratology
| Species | No./Group | Route | Dose (mg/kg) and Frequency | Drug-Related Findings |
| Mouse | 10F | IV | 0.5, 1.0, 3.0, 5.0 One dose on day 9 of gestation | Embryotoxicity at doses 1.0-5.0 mg/kg. Fetotoxicity (delayed ossification) at 1.0 mg/kg. |
| Rat | 2F | IV | 0.10, 0.26, 0.70 Every 3 days for 2 weeks and then through mating and until gestation day 7 | Decreased weight gain and enlarged spleens in dams receiving 0.70 mg/kg. External and/or visceral abnormalities were observed in 4 fetuses at the 0.10 mg/kg dose level. Skeletal abnormalities were observed in all dose groups. |
| Rat | 35F | IV | 0.10, 0.22, 0.50 Dosed on gestational days 7, 10, 13 and 16 | A low incidence of skeletal abnormalities were observed in F1 fetuses in the 0.50 mg/kg dose group. |
| Rat | 25F | IV | 0.10, 0.32, 1.00 Dosed every 3 days starting at day 17 of gestation and continuing until day 21 of lactation | Decreased weight gain was observed in female neonates during suckling and male neonates up to 7 weeks of age at the 1.00 mg/kg dose only. No other deleterious effects observed. |
| Rabbit | 6F | IV | 0.10, 0.25, 0.50, 0.75 Dosed on gestation days 6, 12 and 18 | Decreased mean fetal weight and increased number of small foetuses, increased incidence of blood in fetal cochleas and discoloration of fetal lens observed in the 0.75 mg/kg dose group. |
| Rabbit | 6F | IV | 0.10, 0.25, 0.50, 0.75 Dosed on gestation days 6, 9, 12, 15, and 18 | Reduced fetal weight was observed in the 0.25 and 0.50 mg/kg dose groups. Embryotoxicity was observed at doses of 0.50 and 0.75 mg/kg. Vinorelbine tartrate was maternally lethal at 0.75 mg/kg when given for 5 but not 3 days. No terata was seen at any dose level. |
| Rabbit | 15F | IV | 0.22, 0.40, 0.70 Dosed on gestation days 6, 9, 12, 15, 18. 0.7 Dosed on gestation days 7, 10, 13, 16 0.70 Dosed on gestation days 8, 11, 14, 17 | Vinorelbine tartrate was severely maternally toxic at the 0.70 mg/kg dose level and resulted in maternal clinical signs, reduced body weight and food intake, abortions, and deaths with an increased incidence of external and visceral anomalies in the few live foetuses remaining. |
Vinorelbine Injection – Product Monograph Page 29 of 30
References or Selected Bibliography
Safe Handling of Cytotoxic Agents
- 1. Recommendations for the safe handling of parenteral antineoplastic drugs. Washington, DC: Division of Safety, National Institutes of Health, 1983. US Dept of Health and Human Services, Public Health Service publication NIH 83-2621.
- 2.
AMA Council on Scientific Affairs. Guidelines for handling parenteral antineoplastics. JAMA 1985;
253: 1590-1592.
- 3. National Study Commission on Cytotoxic Exposure. Recommendations for handling cytotoxic agents, 1987. Available from Louis P. Jeffrey, Chairman, National Study Commission on Cytotoxic Exposure, Massachusetts College of Pharmacy and Allied Health Sciences, 179 Longwood Avenue, Boston, Massachusetts, 02115.
- 4. Clinical Oncological Society of Australia. Guidelines and recommendations for safe handling of antineoplastic agents. Med J Australia 1983; 1 :426-428.
- 5.
Jones RB, Frank R, Mass T. Safe handling of chemotherapeutic agents: a report from the Mount Sinai
Medical Center. CA-A Cancer J for Clin 1983; 33:258-263.
- 6. American Society of Hospital Pharmacists. ASHP technical assistance bulletin on handling cytotoxic and hazardous drugs. Am J Hosp Pharm 1990; 47:1033-1049.
- 7.
Yodaiken RE, Bennet D. OSHA work-practice guidelines for personnel dealing with cytotoxic
(antineoplastic) drugs. Am J Hosp Pharm 1986; 43:1193-1204.
Select Papers
- 8. Berthaud P, Le Chevalier T, Ruffie P, et al. Phase I-II study of vinorelbine (Navelbine®) plus cisplatin in advanced non-small cell lung cancer. Eur J Cancer 1992; 28A(11):1863-1865.
- 9. Binet S, Fellous A, Lataste H, et al. In situ analysis of the action of Navelbine® on various types of microtubules using immunofluorescence. Semin Onco11989; 16(2, SuppI4):5-8.
- 10.
Cortes-Funes H, Mathe G, eds. Drugs Supplement. Vol 44, Suppl4. Auckland, Adis International,
1992; 1-69.
- 11. Depierre A, Lemarie E, Dabouis G, et al. A phase II study of Navelbine (vinorelbine) in the treatment of non-small-cell lung cancer. Am J Clin Oncol 1991; 14(2):115-119.
- 12. Depierre A, Lemarie E, Dabouis G, et al. Efficacy of Navelbine® (NVB) in non-small-cell lung cancer (NSCLC). Semin Onco11989; 16(2, SuppI4):26- 29.
- 13. Fellous A, Ohayon R, Vacassin T, et al. Biochemical effects of Navelbine® on tubulin and associated proteins. Semin Onco11989; 16(2, SuppI4):9-14.
- 14.
Krikorian A, Rahmani R, Bromet M, et al. Pharmacokinetics and metabolism of Navelbine®. Semin
Onco11989; 16(2, SuppI4):21-25.
- 15.
Pierre Fabre Oncologie (eds.) Navelbine® (vinorelbine) update and new trends. Paris: John Libbey
Eurotext, 1991; chap. 15-22, pp.141-194.
Vinorelbine Injection – Product Monograph Page 30 of 30
- 16. Le Chevalier T, Brisgand D, Douillard JY, et al. Randomized study of vinorelbine and cisplatin versus vindesine and cisplatin versus vinorelbine alone in advanced non-small-cell lung cancer: Results of a European multicenter trial including 612 patients. J Clin Onco11994; 12(2):360-367.
- 17.
Marty M, Extra JM, Espie M, et al. Advances in vinca-alkaloids: Navelbine®. Nouv Rev Fr
Hematol1989; 31:77-84.
- 18.
Yokoyama A, Furusa K, Niitani H, et al. Multi-institutional phase II study of Navelbine (vinorelbine)
in non-small cell lung cancer, abstract No. 95. Proceedings of ASCO, March 1992; 11 :287.
- 19.
Canobbio L, Boccardo F, Pastorino G, et al. Phase II Study of Navelbine® in Advanced Breast
Cancer, Semin Onco11989; 16(2, SuppI4):33-36.
- 20. Fumoleau P, Delgado FM, Delozier T, et al. Phase II Trial of Weekly intravenous vinorelbine in first-line advanced breast cancer chemotherapy. J Clin Onco11993; 11(7):1245-1252.
- 21. Gasparini G, Caffo 0, Barni S, et al. Vinorelbine is an active anti proliferative agent in pretreated advanced breast cancer patients: A Phase II study. J Clin Onco11994; 12(10):2094-2101.
- 22. Jones S, Winer E, Vogel C, et al. A multicentre randomized trial of IV Navelbine® vs IV Alkeran® in patients with anthracycline-refractory advanced breast cancer (ABC). Proceedings of ASCO, March 1994; 103:22.
- 23.
Lluch A, Garcia C, Casado A. Phase II trial with Navelbine (NVB) in advanced breast cancer (ABC)
previously untreated. Proceedings of ASCO, March 1992; 11:72.
- 24. Marty M, Extra JM, Dieras W, et al. A review of the antitumor activity of vinorelbine in breast cancer. Drugs 1992; 44(Suppl 4):29-35.
- 25.
Navelbine® (Vinorelbine Tartrate Injection Vials) – Product Monograph. 2005. Pierre Fabre Pharma
Canada Inc., St-Bruno-de-Montarville, QC.
- 26. Romero A, Rabinovich MG, Vallejo CT, et al. Vinorelbine as first-line chemotherapy for metastatic breast carcinoma. J Clin Oncol 1994; 12(2):336-341.
- 27. Spielmann M, Dorval T, Turpin F, et al. Phase II trial of vinorelbine/doxorubicin as first-line therapy of advanced breast cancer. J Clin Onco11994; 12(9):1764-1770.
- 28. Tresca P, Fumoleau P, Roche H, et al. Vinorelbine, a new active drug in breast carcinoma: Results of an ARTAC phase II trial. Br Canc Res Treat 1990; 16(2): 161.
- 29. Vogel C, Bertsch L, Hohneker J. Navelbine®: A promising new drug with a favorable toxicity profile for breast and non-small cell lung cancer (NSCLC). Cancer Investig 1993; 12(SuppI1):17-18.
- 30. Weber B, Vogel C, Jones S, et al. A U.S. multicenter phase II trial of Navelbine in advanced breast cancer. Proc ASCO 1993; 12:61.
- 31.
ONS Clinical Practice Committee. Cancer Chemotherapy Guidelines. Recommendations for the
Management of vesicant extravastion, hypersensitivity, and anaphylaxis. Pittsburg, Pa: Oncology Nursing Society; 1992:1-4.