


Product Monograph - Apo-Cetirizine (Apotex, 20 mg)
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics ................................................................................................................... 4
2 CONTRAINDICATIONS .................................................................................................. 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 4
4.1 Dosing Considerations .............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration .......................................................................................................... 5
4.5 Missed Dose .............................................................................................................. 5
5 OVERDOSAGE .............................................................................................................. 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................... 6
7 WARNINGS AND PRECAUTIONS ................................................................................... 6
7.1 Special Populations ................................................................................................... 7
7.1.1 Pregnant Women ...................................................................................................... 7
7.1.2 Breast-feeding .......................................................................................................... 8
7.1.3 Pediatrics .................................................................................................................. 8
7.1.4 Geriatrics ................................................................................................................... 8
8 ADVERSE REACTIONS ................................................................................................... 8
8.1 Adverse Reaction Overview ...................................................................................... 8
8.2 Clinical Trial Adverse Reactions ................................................................................ 9
8.3 Less Common Clinical Trial Adverse Reactions (<1%) ............................................ 11
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ................................................................................................... 11
8.5 Post-Market Adverse Reactions ............................................................................. 11
9 DRUG INTERACTIONS ................................................................................................. 11
9.2 Drug Interactions Overview .................................................................................... 11
9.3 Drug-Behavioural Interactions ............................................................................... 12
9.4 Drug-Drug Interactions ........................................................................................... 12
9.5 Drug-Food Interactions ........................................................................................... 12
9.6 Drug-Herb Interactions ........................................................................................... 12
9.7 Drug-Laboratory Test Interactions ......................................................................... 12
10 CLINICAL PHARMACOLOGY ........................................................................................ 12
10.1 Mechanism of Action .............................................................................................. 13
10.2 Pharmacodynamics ................................................................................................. 13
10.3 Pharmacokinetics.................................................................................................... 17
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 18
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 18
PART II: SCIENTIFIC INFORMATION ..................................................................................... 19
13 PHARMACEUTICAL INFORMATION ............................................................................. 19
14 CLINICAL TRIALS ......................................................................................................... 19
14.1 Clinical Trials by Indication ..................................................................................... 19
14.2 Comparative Bioavailability Studies ....................................................................... 21
15 MICROBIOLOGY ......................................................................................................... 22
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 22
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 24
PATIENT MEDICATION INFORMATION ................................................................................ 25
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Adults and children 12 years of age and over: APO-CETIRIZINE (cetirizine hydrochloride, 20 mg tablets) is indicated:
- for the fast relief of nasal and non-nasal symptoms associated with seasonal and perennial allergic rhinitis (i.e. sneezing, rhinorrhea, post-nasal discharge, nasal congestion/stuffiness, tearing and redness of the eyes, itchy nose/throat) and chronic idiopathic urticaria (e.g. pruritus and hives).
1.1 Pediatrics
Pediatrics - Children <12 years of age: Cetirizine hydrochloride (20 mg tablets) is not recommended in children less than 12 years of age, as safety and efficacy have not been established in this age group.
1.2 Geriatrics
Geriatrics: Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness and a brief discussion can be found in the appropriate sections (see 7.1.4 Geriatrics). Cetirizine hydrochloride 20 mg tablets are not recommended in patients 65 years and older. The recommended starting dose is 5 mg once daily.
2 CONTRAINDICATIONS
APO-CETIRIZINE (cetirizine hydrochloride tablets) is contraindicated in those patients with a known hypersensitivity to it, to its parent compound, hydroxyzine, or to piperazine derivatives, in patients who are hypersensitive to any other ingredient in the formulation, or in patients with severe renal impairment (less than 10 mL/min creatinine clearance).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The recommended initial dose of cetirizine hydrochloride is 5 or 10 mg per day, depending on symptom severity. APO-CETIRIZINE 20 mg tablets are recommended only if lower doses (non-prescription) of cetirizine hydrochloride do not provide sufficient response for patients 12 years of age and older.
4.2 Recommended Dose and Dosage Adjustment
Adults and Children 12 Years of Age and Over
The recommended dose is one 20 mg tablet once daily, with or without food. The maximum recommended daily dose is 20 mg.
Geriatrics (≥ 65 Years of age)
APO-CETIRIZINE 20 mg tablets are not recommended in patients 65 years and older. The recommended starting dose is 5 mg once daily.
Patients with hepatic impairment
APO-CETIRIZINE 20 mg tablets are not recommended in patients with moderate or severe hepatic impairment. The recommended starting dose is 5 mg once daily.
Patients with renal impairment
APO-CETIRIZINE 20 mg tablets are not recommended for patients with moderate renal impairment. In patients with moderate renal impairment, the recommended starting dose is 5 mg once daily.
APO-CETIRIZINE is contraindicated in patients with severe renal impairment (less than 10 mL/min creatinine clearance).
Pediatrics (< 12 years of age)
APO-CETIRIZINE 20 mg tablets should not be administered to children under 12 years of age. It is recommended to use an appropriate pediatric formulation of cetirizine.
4.4 Administration
See 4.2 Recommended Dose and Dosage Adjustment above.
4.5 Missed Dose
If you missed a dose of this medication, you do not need to make up the missed dose. Skip the missed dose and continue with your next scheduled dose. Do not take two doses at the same time. Do not exceed the maximum daily dose.
5 OVERDOSAGE
Overdose has been reported with cetirizine hydrochloride. Symptoms observed after an overdose of cetirizine are mainly associated with CNS effects or with symptoms that could suggest an anticholinergic effect. Adverse events reported after an intake of at least 5 times the recommended daily dose are: confusion, diarrhea, dizziness, fatigue, headache, malaise, mydriasis, pruritus, restlessness, sedation, somnolence, stupor, tachycardia, hypertension, tremor, and urinary retention. Hyperactivity and severe lethargy have been seen in children. If an acute overdose occurs, evacuation of the stomach should be considered during the first few hours after this overdose. Treatment should be symptomatic and supportive taking into account any concomitantly ingested medications. There is no known specific antidote to cetirizine hydrochloride. Cetirizine hydrochloride is not effectively removed by dialysis, and dialysis will be ineffective unless a dialyzable agent has been concomitantly ingested. The minimal lethal oral dose in rodents is at least 590 times the maximum clinically studied dose.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Film-coated tablet 20 mg | Carnauba wax, cornstarch, hydroxypropyl methylcellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polydextrose, polyethylene glycol, titanium dioxide |
Description
APO-CETIRIZINE (Cetirizine hydrochloride tablets) Film-coated Scored Tablet: 20 mg of cetirizine hydrochloride. The 20 mg tablets are only available by prescription.
APO-CETIRIZINE 20 mg tablets are white to off-white, rectangle-shaped, biconvex coated tablets; engraved “20” scored “MG” on one side, and “APO” on the other side. Available in bottles of 100 tablets.
7 WARNINGS AND PRECAUTIONS
General
Severe skin reactions such as acute generalized exanthematous pustulosis (AGEP) have been reported very rarely with cetirizine-containing products. This acute pustular eruption may exhibit an early or delayed onset with numerous small, mostly non-follicular pustules arising on a widespread edematous erythema mainly localized on the skin folds, trunk, and upper extremities, which may be accompanied by fever. Patients should be carefully monitored.
If symptoms persist or worsen, or if new symptoms occur, the patient should discontinue use and consult a physician.
Hepatic Impairment
Occasional instances of liver function test (transaminase) elevations have occurred during cetirizine hydrochloride therapy. This incidence was 1.6% in the short-term trials and 4.4% in the 6 month trials. These liver enzyme elevations, mainly ALT, were generally reversible. There was no evidence of jaundice or hepatitis, and the clinical significance is presently unknown. Consequently, APO-CETIRIZINE should be used with caution in patients with pre-existing liver disease. In patients with moderate or severe hepatic impairment, a starting dose of 5 mg is recommended.
Activities Requiring Mental Alertness
Studies using objective measurements have shown no effect of cetirizine hydrochloride at a dose of 10 mg on cognitive function, motor performance or sleep latency in healthy volunteers. However, in clinical trials the appearance of some CNS effects, particularly somnolence, have been observed. If drowsiness occurs, patients should be advised not to drive or operate machinery. Patients should be advised to avoid concurrent use of APO-CETIRIZINE with sedating substances, including alcohol, because additional reductions in alertness and additional impairment of CNS performance may occur. (See 9 DRUG INTERACTIONS).
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Until such data become available, APO-CETIRIZINE should not be used during pregnancy, unless advised otherwise by a physician.
No teratogenic effects were caused by oral doses as high as 60, 188 and 133 times the maximum clinically studied human dose in mice, rats and rabbits, respectively. No effects on reproduction and fertility were observed at doses as high as 40 and 10 times the maximum recommended human dose in male and female mice, respectively. An oral dose 60 times the maximum clinically studied human dose in female mice did not affect parturition or lactation. Although the animal studies are not indicative of any adverse effects during pregnancy at clinically relevant doses, such studies are not always predictive of a human response.
Cetirizine is a major human metabolite of hydroxyzine (50 mg hydroxyzine = 20 mg cetirizine). Thus, the long-term experience with hydroxyzine also provides an indication of the safety of cetirizine in pregnancy. During 30 years of clinical use, hydroxyzine has not been associated with an increase of any human congenital malformation above the expected background incidence. Thus, human exposure to cetirizine has occurred for more than 30 years without any indication that it or its parent compound, hydroxyzine, is a human teratogen. The effect of hydroxyzine on human pregnancies have been studied in a large epidemiology study (the Collaborative Perinatal Project). The study did not report any increase in human congenital malformation as a consequence of the use of hydroxyzine.
7.1.2 Breast-feeding
Use of APO-CETIRIZINE in nursing mothers is not recommended, unless directed otherwise by a physician. Studies in beagle dogs indicate that approximately 3% of the dose is excreted in milk. The extent of excretion in human milk is unknown.
7.1.3 Pediatrics
Cetirizine hydrochloride tablets 20 mg should not be administered to children below 12 years of age (see 4 DOSAGE AND ADMINISTRATION). It is recommended to use an appropriate pediatric formulation of cetirizine.
7.1.4 Geriatrics
Cetirizine hydrochloride was well tolerated by patients aged 65 and over. Clearance of cetirizine hydrochloride is reduced in proportion to creatinine clearance. In patients whose creatinine clearance is reduced (i.e., those with moderate renal impairment), a starting dose of 5 mg/day is recommended (see 10.3 Pharmacokinetics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
In clinical development programs (domestic and international), cetirizine hydrochloride has been evaluated in more than 6000 treated patients at daily doses ranging from 5 to 20 mg. The most common adverse reactions were headache and somnolence (see paragraph below). The incidence of headache associated with cetirizine hydrochloride was not different from placebo. The incidence of somnolence associated with cetirizine hydrochloride was dose related and predominantly mild to moderate.
Most adverse reactions reported during cetirizine hydrochloride therapy in clinical trials were mild to moderate. The incidence of discontinuation due to adverse reactions in patients receiving cetirizine hydrochloride was not significantly different from placebo (1.0% vs 0.6%, respectively, in placebo-controlled trials). There was no difference by gender or by body weight with regard to the incidence of adverse reactions.
Occasional instances of transient, reversible hepatic transaminase elevations have occurred during cetirizine hydrochloride tablets, without evidence of jaundice, hepatitis or other clinical findings.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse events which were reported at an incidence of greater than 2% and greater than placebo in clinical trials with the 20 mg tablet (one to four weeks duration) are listed in Table 1.
Table 1
ADVERSE REACTIONS REPORTED IN PLACEBO-CONTROLLED UNITED STATES CETIRIZINE HYDROCHLORIDE TRIALS (TOTAL DAILY DOSE 20 mg) AT RATES OF ≥ 2% AND GREATER THAN PLACEBO (Percent Incidence)
| Adverse Experience | Cetirizine Hydrochloride 20 mg Tablets (N=272) | Placebo (N=671) | Difference of Percentage |
| Somnolence | 23.9 | 7.7 | 16.2 |
| Dry Mouth | 7.7 | 1.5 | 6.2 |
| Fatigue | 7.0 | 2.4 | 4.6 |
The following events were observed infrequently (equal to or less than 2%), in 3982 patients who received cetirizine hydrochloride tablets in worldwide trials, including an open study of 6 months duration; a causal relationship with cetirizine hydrochloride tablets administration has not been established.
Application Site: application site reaction, injection site inflammation
Autonomic Nervous System: anorexia, urinary retention, flushing, saliva increased
Cardiovascular: palpitation, tachycardia, hypertension, arrhythmia, cardiac failure
Central and Peripheral Nervous Systems: fatigue, dizziness, insomnia, nervousness paresthesia, confusion, hyperkinesia, hypertonia, migraine, tremor, vertigo, leg cramps, ataxia, dysphonia, coordination abnormal, hyperesthesia, hypoesthesia, myelitis, paralysis, ptosis, speech disorder, twitching, visual field defect
Endocrine: thyroid disorder
Gastrointestinal: nausea, pharyngitis, appetite increased, dyspepsia, abdominal pain, diarrhea, flatulence, constipation, vomiting, stomatitis ulcerative, tongue disorder, tooth caries aggravated, stomatitis, tongue discoloration, tongue edema, gastritis, hemorrhage rectum, hemorrhoids, melena, hepatic function abnormal
Genitourinary: polyuria, urinary tract infection, cystitis, dysuria, hematuria, urine abnormal
Hearing and vestibular: earache, tinnitus, deafness, ototoxicity
Metabolic/Nutritional: thirst, edema, dehydration, diabetes mellitus
Musculoskeletal: myalgia, arthralgia, bone disorder, arthrosis, tendon disorder, arthritis, muscle weakness
Psychiatric: depression, emotional lability, concentration impaired, anxiety, depersonalization, paroniria, thinking abnormal, agitation, amnesia, libido decreased, euphoria
Resistance Mechanism: healing impaired, herpes simplex, infection, infection fungal, infection viral
Respiratory System: epistaxis, rhinitis, coughing, respiratory disorder, bronchospasm, dyspnea, upper respiratory tract infection, hyperventilation, sinusitis, sputum increased, bronchitis, pneumonia
Reproductive: dysmenorrhea, menstrual disorder, breast pain female, intermenstrual bleeding, leukorrhea, menorrhagia, pregnancy unintended, vaginitis, testes disorder
Reticuloendothelial: lymphadenopathy
Skin: pruritus, rash, skin disorder, skin dry, urticaria, acne, dermatitis, rash erythematous, sweating increased, alopecia, angioedema, furunculosis, bullous eruption, eczema, hyperkeratosis, hypertrichosis, photosensitivity reaction, photosensitivity toxic reaction, rash maculopapular, seborrhea, purpura
Special Senses: taste perversion, taste loss, parosmia
Vision: eye abnormality, vision abnormal, eye pain, conjunctivitis, xerophthalmia, glaucoma, ocular hemorrhage
Body as a Whole: weight increase, back pain, malaise, pain, chest pain, fever, asthenia, edema generalized, edema periorbital, edema peripheral, rigors, edema legs, face edema, hot flushes, abdomen enlarged, allergic reaction, nasal polyp
8.3 Less Common Clinical Trial Adverse Reactions (<1%)
Weight gain was reported as an adverse event in 0.4% of cetirizine patients in placebo controlled trials. In an open study of 6 months duration, the mean weight gain was 2.8% after 20 weeks, with no further increase at 26 weeks.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Occasional instances of transient, reversible hepatic transaminase elevations have occurred during cetirizine therapy.
8.5 Post-Market Adverse Reactions
Additional adverse drug reactions identified during post-marketing experience with cetirizine include: blurred vision, eye swelling, feeling abnormal, enuresis, hepatic function abnormal (increased transaminases, alkaline phosphatase, alanine aminotransferase, aspartate aminotransferase, γ-glutamyl transferase and bilirubin), erectile dysfunction, hallucination, dysgeusia, dyskinesia, dystonia, memory impairment, tremor, arthralgia, urinary retention, fixed drug eruption, pruritus, pruritus upon withdrawal and weight increased.
In post-marketing experience the following additional rare, but potential severe adverse events have been reported: hemolytic anemia, thrombocytopenia, orofacial dyskinesia, severe hypotension, anaphylaxis, hepatitis [including Drug-induced liver injury (DILI) and other types of non-infectious hepatitis], glomerulonephritis, stillbirth, cholestasis and acute generalized exanthematous pustulosis. In addition, isolated cases of the following adverse drug reactions have been reported: convulsions, syncope, aggression, and hypersensitivity.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Interaction studies with cetirizine hydrochloride and alcohol or diazepam indicate that at therapeutic doses, cetirizine hydrochloride does not increase alcohol-induced or diazepam-induced impairment of motor and mental performance.
The drug should not be used with sedating substances such as alcohol and some other medications, including anti-anxiety medications, sleep aids, antihistamines, antidepressants, muscle relaxants or prescription analgesics due to possible interactions.
9.3 Drug-Behavioural Interactions
Interactions with lifestyle have not been established.
9.4 Drug-Drug Interactions
No clinically significant drug interactions have been found with theophylline, pseudoephedrine, cimetidine, erythromycin and ketoconazole. Epidemiologic data suggests that there also would not be interaction with other macrolide antibiotics or imidazole antifungals. In clinical trials, cetirizine hydrochloride has been safely administered with beta-agonists, non-steroidal anti-inflammatory drugs, oral contraceptives, narcotic analgesics, corticosteroids, H2-antagonists, cephalosporins, penicillins, thyroid hormones and thiazide diuretics. If drowsiness occurs, concurrent use of APO-CETIRIZINE with sedating substances should be avoided because additional reductions in alertness and additional impairment of CNS performance may occur. (See 7 WARNINGS AND PRECAUTIONS, Activities Requiring Mental Alertness).
Based on (1) its relatively low level of metabolic elimination, (2) no effect on corrected QT intervals at plasma concentrations three times the maximal therapeutic levels, and (3) no apparent interactions with ketoconazole or erythromycin, cetirizine is unlikely to have clinically significant interactions with other macrolides such as clarithromycin or other imidazole antifungals such as itraconazole in patients with normal renal and hepatic function. Although no data with these other drugs are available at the present time, there is no epidemiological evidence (the safety database comprised 6,490 patients evaluated in U.S. and Canadian studies) of interactions between macrolide antibiotics and/or imidazole antifungals taken orally, and cetirizine/hydroxyzine. The epidemiologic data do not suggest an increase of adverse events, cardiac or non-cardiac, in patients treated with cetirizine and concomitant macrolide or imidazole antifungal medication.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Cetirizine hydrochloride, an active human metabolite of hydroxyzine, is a histamine H1 receptor antagonist anti-allergic compound; its principal effects are mediated via selective inhibition of peripheral H1 receptors. Cetirizine hydrochloride is distinguished from other histamine H1 receptor antagonists by the presence of a carboxylic acid function. This difference may be partly responsible for the selectivity of cetirizine hydrochloride seen in pharmacologic models and its distinctive pharmacokinetic properties in humans.
10.2 Pharmacodynamics
The antihistaminic activity of cetirizine hydrochloride has been well documented in a variety of animal and human models. In vivo animal models have shown negligible anticholinergic or antiserotonergic activity. In vitro receptor binding studies have detected no measurable affinity for other than H1 receptors. Autoradiographic studies have shown negligible penetration into the brain. Systemically administered cetirizine does not significantly occupy cerebral H1 receptors. Several studies involving objective and subjective tests in healthy volunteers have demonstrated that cetirizine hydrochloride at doses up to 10 mg did not significantly differ from placebo with respect to CNS impairment, daytime drowsiness, reaction times, mental alertness, task performance, objective CNS depression and various other tests of cognitive function.
Cetirizine hydrochloride does not exacerbate asthma and is effective in a variety of histamine mediated disorders. In adults, oral doses of 5 to 20 mg in humans strongly inhibit the skin wheal and flare response caused by the intradermal injection of histamine. The onset of activity occurs within 20 (50% of subjects) to 60 (95% of subjects) minutes and persists for at least 24 hours following a single dose. The effects of intradermal injection of various other mediators or histamine releasers as well as components of the allergy cascade, including allergic inflammatory response to cutaneous antigen challenge are also inhibited.
Studies in normal volunteers show that cetirizine hydrochloride at doses of 5 to 20 mg strongly inhibits the skin wheal and flare caused by the intradermal injection of histamine. The onset of activity corresponds with the occurrence of maximal plasma levels, and significant blockade persists for at least 24 hours after a single dose. The effects of intradermal injection of various other mediators or histamine releasers are also inhibited by cetirizine hydrochloride tablets, as is cold-induced urticaria.
In mildly asthmatic subjects, cetirizine hydrochloride at 5 to 20 mg is highly effective in blocking bronchoconstriction due to nebulized histamine, with virtually total blockade after a 20 mg dose; a modest reduction of resting bronchial tone is also seen.
Studies in normal subjects using objective assessments of psychomotor performances showed that cetirizine hydrochloride at doses up to 20 mg did not produce significant changes in the Multiple Sleep Latency test, a measure of daytime drowsiness, in comparison with placebo. However, hydroxyzine 25 mg caused a statistically significant decrease in time to sleep onset. When the Flicker Fusion Threshold was used to measure mental alertness, cetirizine hydrochloride did not produce significant change but hydroxyzine significantly reduced the mental alertness. In this study, cetirizine hydrochloride 10 and 20 mg and hydroxyzine 25 mg had equipotent antihistaminic activity as determined by the suppression of skin wheal response to histamine.
Several combined placebo and positive control studies in normal subjects using a multiple crossover design with objective and subjective assessments of CNS and performance impairment showed that cetirizine hydrochloride 10 mg did not differ from placebo. Positive controls i.e. sedating antihistamines, e.g. diphenhydramine, hydroxyzine, triprolidine, were included in these trials to verify that the tests were able to detect impairment. Objective tests included: Multiple Sleep Latency Test (EEG monitoring), Critical Flicker-Fusion (CFF), Choice Reaction Time (CRT), Continuous Tracking Test (CTT), word testing, simulated driving tests and assembly line tests (SALT), actual road-driving tests. Subjective tests included: Visual Analog Scale (VAS) reporting, Stanford Sleepiness Scale (SSS) by the subject as well subjective assessments by driving instructors.
Due to the association of torsades and QT prolongation with newer antihistamines, and the metabolic/pharmacokinetic interaction of antihistamines with erythromycin and ketoconazole, three studies were performed to evaluate the pharmacokinetic effects and ECG effects of cetirizine, and the possible interactions of cetirizine with ketoconazole and erythromycin. These studies show that cetirizine, alone or in combination with erythromycin or ketoconazole, does not cause clinically significant QTc prolongation. Furthermore, no effects on the pharmacokinetics of erythromycin or ketoconazole and no effects of these two compounds on the pharmacokinetics of cetirizine were seen.
Protocol 90CK16-0497: There were no statistically significant differences among the treatments in mean QTc prior to daily dosing, indicating that multiple dosing with cetirizine at both the maximal clinically studied daily dose (20 mg) or three times the maximal clinically studied dose (60 mg once daily) has no effect on QTc relative to a placebo effect. Furthermore, cetirizine did not have any statistically significant effect on QT (uncorrected) or on heart rate as measured by RR interval. This finding was consistent over all dose days as indicated by no statistically significant treatment-by-day interaction for each of the three parameters. This suggests that, within the first 7 days of treatment, cetirizine produces neither an early transient effect nor a late-appearing cumulative effect. Also, there were no significant differences with respect to the mean changes in QTc, QT, and RR from pre-dosing to 1, 2, 4, and 6 hours after dosing indicating that a dose of cetirizine has no acute effect on QT interval or heart rate relative to placebo at any of the post-dose hours for up to 7 days of treatment. The plasma cetirizine concentration-time profiles were dose proportional.
Four subjects (19.1%) during cetirizine hydrochloride 20 mg treatment and 6 subjects (28.6%) during cetirizine hydrochloride 60 mg experienced at least one 10% prolongation of QTc as compared to 6 subjects (28.6%) on placebo. These incidence rates were not significantly different. The largest prolongations observed were 15.6%, 19.0%, and 15.4% over baseline for placebo, cetirizine hydrochloride 20 mg, and cetirizine hydrochloride 60 mg, respectively.
Protocol 92KC16-0604: The objectives of this study were to determine whether cetirizine, in the presence of erythromycin, induces a prolongation of the QT interval and to determine whether there are pharmacokinetic interactions between cetirizine and erythromycin in young, healthy males. This was a randomized, multiple dose, open (the cardiologist was blinded), two-way crossover study with a washout period. The two treatment regimens administered in the study were the following:
Regimen 1
Day 1:
Days 2 to 6:
Days 7 to 16:
placebo o.d.
20 mg cetirizine o.d.
500 mg erythromycin q8h and
20 mg cetirizine o.d.
Regimen 2
Day 1:
Days 2 to 6:
Days 7 to 16:
placebo o.d.
500 mg erythromycin q8h
500 mg erythromycin q8h and 20 mg cetirizine o.d.
The mean change from baseline Hodges QTc after 5 days of dosing with cetirizine alone and erythromycin alone was -5, 10 msec and 3.01 msec, respectively. After an additional 10 days of dosing with combination treatment, the mean change from baseline was -3.71 msec for combination treatment following cetirizine alone and -0.39 msec for combination treatment following erythromycin alone. Using these mean changes, the drug interaction effect was estimated to be 0.03 msec, which is not statistically significantly different from zero. This result indicates that any possible effect on changes in Hodges QTc attributable to either drug alone is not altered by the presence of the other, and that the effect on Hodges QTc of combination dosing is the sum of the individual effects. The estimated effect of cetirizine is -5.08 msec which is a statistically significant reduction from baseline. The estimated erythromycin effect of 3.03 msec was not statistically significant. These results indicate that cetirizine did not induce a mean prolongation of Hodges QTc, and since the effect of combination dosing was just the sum of each component (estimated to be -2.05), there was no significant mean prolongation associated with combination treatment.
No subject experienced a 10% prolongation of Hodges QTc over baseline during cetirizine alone treatment. Eight subjects experienced at least 1 prolongation of 10% or greater. Two subjects (13.3%) had a 10% or greater increase during treatment with erythromycin alone,
2 subjects (14.3%) during combination treatment following cetirizine and 4 subjects (26.7%) had an occurrence during combination treatment following erythromycin. The maximum prolongation in any subject in the study was 17.8% which occurred during erythromycin treatment alone. There was no significant pharmacokinetic interaction between cetirizine and erythromycin when administered concomitantly in therapeutic dosages and regimens.
Protocol 92CK16-0603: The objectives of this study were to determine whether cetirizine, in the presence of ketoconazole, induces a prolongation of the QT interval and to determine whether there are pharmacokinetic interactions between cetirizine and ketoconazole in young, healthy males. This was a randomized, multiple dose, open (the cardiologist was blinded), two-way crossover study. The two treatment regimens administered in the study were the following:
Regimen 1
Day 1:
placebo o.d.
Days 2 to 6:
400 mg ketoconazole o.d.
Days 7 to 16:
400 mg ketoconazole o.d. and
20 mg cetirizine o.d.
Regimen 2
Day 1:
placebo o.d.
Days 2 to 6:
placebo o.d.
Days 7 to 16:
20 mg cetirizine o.d.
There was no statistically significant drug interaction effect on the change in Hodges QTc from baseline. This indicates that the effect of the combination on changes in Hodges QTc is equal to the sum of the individual component effects. The effects of each drug alone on change in Hodges QTc from baseline were statistically significant, with a mean increase from baseline of 8.16 msec and 8.32 msec for cetirizine and ketoconazole, respectively. Based on these findings, the effect of combination treatment on changes in Hodges QTc is estimated to be 16.48 msec.
No subject experienced a 10% or greater QTc prolongation during the 5 days placebo treatment. Two subjects (13.3%) experienced an increase in QTc of 10% or greater during the 10 day cetirizine treatment, 1 subject (6.3%) during the 5 day ketoconazole treatment and 5 subjects (31.3%) had an occurrence during combination treatment (2 in study phase 1 and 3 in study phase II). The maximum prolongation in any subject in the study was 14.3%, which occurred during combination treatment. Cetirizine did not significantly affect ketoconazole plasma pharmacokinetics.
Using Bazett’s formula for QTc, 3 subjects had a total of 12 occurrences of a QTc >440 msec. There was 1 occurrence on placebo, 4 on cetirizine treatment and 7 on combined treatment. These occurrences of QTc >440 msec were episodic and not sustained.
The results of the study of protocol 90CK16-0497 demonstrate that cetirizine alone in multiple doses up to 60 mg (three times the maximum recommended dose of 20 mg) does not cause a prolongation of the QTc. Cetirizine did not increase mean QTc nor increase the percentage of patients who had 10% increases or greater in post-dose QTc. The pharmacokinetics of cetirizine were linear over the dose range and no dose related increase in QTc was seen. The results of study protocols 92CK16-0603 and 0604 demonstrate there was no significant interaction of cetirizine with either ketoconazole or erythromycin on QTc. Cetirizine given at the maximum recommended dose of 20 mg daily did not prolong the QTc when given in combination with either ketoconazole 400 mg o.d. or erythromycin 500 mg q8h for 10 days. Moreover, cetirizine did not significantly alter the pharmacokinetics of either ketoconazole or erythromycin nor were the pharmacokinetics of cetirizine altered by either ketoconazole or erythromycin.
With regard to QTc effect of cetirizine hydrochloride alone in the interaction studies, a small clinically insignificant decrease was seen in the erythromycin-cetirizine interaction study, and a small clinically insignificant increase in QTc was seen in the cetirizine-ketoconazole study. However, this small increase may be the result of other factors. For example, in the study of protocol 0497, a small increase in QTc was seen with placebo. In order to facilitate a comparison of the data in the 20 to 60 mg cetirizine hydrochloride study (protocol 90CK16-0497) with that in the two interaction studies, an analysis was done using the Hodges QTc formula and statistical models similar to the interaction study analyses. Based on this analysis, QTc increases of 5.4 msec, 3.0 msec and 7.3 msec for placebo, 20 mg and 60 mg cetirizine, respectively, were observed at the end of the 7 day treatment period. A shortened RR interval was found in all treatment groups, including placebo. The increase associated with placebo treatment indicates that other factors may affect QTc such as deconditioning during confinement, which is essentially a time effect.
10.3 Pharmacokinetics
TABLE 2 - TYPICAL PHARMACOKINETIC PARAMETERS OF CETIRIZINE IN ADULTS
| Cmax (ng/mL) | Tmax (hr) | t1/2 (h) | AUC (ng.hr/mL) | Urinary Recovery (%) | |
|---|---|---|---|---|---|
| Adults 10 mg Single dose mean | 300 | 1.1 | 8.0 | 2871 | 60 |
Absorption
In adults, cetirizine hydrochloride is rapidly absorbed after oral administration. Peak plasma levels after a 10 mg dose are approximately 300 ng/mL and occur at about 1 hour. Co-administration of cetirizine hydrochloride with food does not affect bioavailability as measured by AUC but absorption is delayed by about 1 hour, with 23% lower Cmax.
While a high-fat meal does not impact the extent of absorption of cetirizine from the orally disintegrating tablet (ODT) as measured by AUCT, absorption is delayed by approximately 3 hours and Cmax is reduced by approximately 37% when the ODT is administered with a high-fat meal relative to the ODT administered under fasted conditions.
Distribution:
Plasma protein binding is 93% in the concentration range observed in clinical studies. The apparent volume of distribution is 0.45 L/kg, suggestive of significant extravascular distribution.
Metabolism:
In adults, cetirizine hydrochloride is less extensively metabolized than other antihistamines and approximately 60% of an administered dose is excreted unchanged in 24 hours. High bioavailability is associated with generally low inter-subject variation in blood levels. It is attributable primarily to low first-pass metabolism. Only one metabolite has been identified in humans - the product of oxidative dealkylation of the terminal carboxymethyl group. The antihistaminic activity of this metabolite is negligible.
Elimination
The plasma elimination half-life is approximately 8 to 9 hours and does not change with multiple dosing. Pharmacokinetics are dose independent and plasma levels are proportional to the dose administered over the clinically studied range of 5 to 20 mg.
Special Populations and Conditions
- Geriatrics: The clearance of cetirizine hydrochloride is reduced in elderly patients, but only in proportion to the decrease in creatinine clearance. Thus, in 16 patients with a mean age of 77 years, half-life increased to 12 hours. Cetirizine hydrochloride blood levels were monitored in a clinical trial of 59 patients aged 60 to 82, who received 10 mg daily for 3 weeks and no undue accumulation of cetirizine hydrochloride was found.
- Hepatic Insufficiency / Renal Insufficiency: In patients with mild to moderate hepatic and renal impairment, total body clearance of cetirizine hydrochloride is reduced and AUC and half-life increased by about 2 to 3 fold. Clearance is reduced in proportion to the decline in creatinine clearance. Plasma levels are unaffected by hemodialysis. The plasma elimination half-life in dialysis patients is approximately 20 hours and the plasma AUC is increased by about threefold.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature, 15°C to 30°C.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not Applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Cetirizine Hydrochloride (USP)
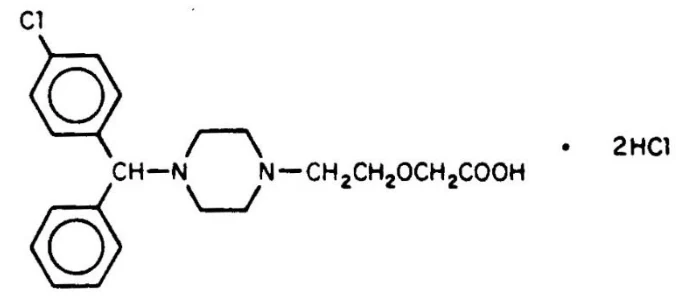
Chemical name: (RS)-2(2-(4-[4-chlorophenyl)phenylmethyl]-1-piperazinyl)ethoxy) acetic acid, dihydrochloride
(±)-[2-[4-(4-chlorophenyl)phenylmethyl]-1-piperazinyl]ethoxy]acetic acid, dihydrochloride.
Molecular formula and molecular mass: C21H25ClN2O3·2HCl, 461.82 g/mol
Structural formula:
Physicochemical properties:
- Cetirizine hydrochloride is a white or practically white powder. It is freely soluble in water and practically insoluble in chloroform and acetone.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Randomized, multi-centre, double-blind, placebo-controlled clinical trials have demonstrated the effectiveness of cetirizine hydrochloride in relieving the symptoms associated with seasonal allergic rhinitis, perennial allergic rhinitis and chronic idiopathic urticaria. The clinical trials have shown only weak anticholinergic effects. There is no evidence that tolerance to the antihistaminic or anti-allergy effects of cetirizine hydrochloride develops or that it has any abuse potential or dependency liability.
In adults, objective and subjective tests in healthy volunteers, have demonstrated that cetirizine hydrochloride at doses up to 10 mg did not significantly differ from placebo with respect to CNS impairment, daytime drowsiness, reaction times, mental alertness, task performance, objective CNS depression and various other tests of cognitive function.
Three well-controlled clinical trials assessed the effects of cetirizine hydrochloride (10 mg) on nasal congestion as an individual symptom score when it was part of the constellation of symptoms associated with allergic rhinitis (as assessed in adults with SAR). Cetirizine proved to be significantly more effective than placebo in improving nasal congestion.
Improvement in quality of life (QOL) with cetirizine hydrochloride (10 mg) in patients with allergic rhinitis has been demonstrated in a number of published studies (2 to 6 weeks duration) using a variety of validated QOL measurement tools (see Table 3). Improvement in the following QOL domains were observed: physical, social and work activities, vitality and social functioning, practical problems, symptom distress (nasal, eye), sleep problems, and emotional difficulties.
TABLE 3
RANDOMIZED, PARALLEL, DOUBLE-BLIND, PLACEBO-CONTROLLED CLINICAL STUDIES DEMONSTRATING IMPROVEMENT IN QUALITY OF LIFE DOMAINS FOLLOWING REGULAR CETIRIZINE HYDROCHLORIDE 10 mg (p.o.) USE ( 2 TO 6 WEEKS)
| Study | Study Description | Result |
| Study | Study Description | Result |
| Bousquet J. et al (1996) | Objective to determine effect of cetirizine HCl 10 mg on QOL in patients with allergic rhinitis. Duration of study: 6 weeks. Total of 122 subjects completed cetirizine arm versus 126 subjects in placebo arm. Validated QOL measurement tool used: SF-36* | Quality of life and nasal symptoms were measured after 1 and 6 weeks of treatment using SF-36 questionnaire. After 6 weeks, percentage of days without rhinitis or only mild rhinitis was significantly greater in the cetirizine group compared with the placebo group. Cetirizine improved all nine QOL dimensions (from p = 0.01 to p<0.0001) after 1 and 6 weeks of cetirizine treatment. |
| Burtin B. et al (2000) | Investigate extent to which cetirizine HCl 10 mg continues to improve QOL after long-term treatment (6 weeks) versus shorter-term treatment (1 week). Validated QOL measurement tool used: SF-36*. Note: This is an additional analysis of the study published by Bousquet et al (1996). | Further 5 week course of therapy maintains QOL improvements seen after 1 week. |
| Murray JJ. et al (2002) | Evaluate the health-related quality of life effects, safety and efficacy of cetirizine HCl 10 mg in treatment of seasonal allergic rhinitis. Patients completing the 2-week treatment period included 413 in the cetirizine group and 396 in the placebo group. Validated QOL measurement tool used: RQLQ† | QOL scores were measured following 2 weeks of treatment. The cetirizine-treated patient group experienced greater (p<0.001) improvement in overall RQLQ and individual domain scores, compared to the placebo patient group. |
| Noonan MJ. et al (2003) | Test the effect of cetirizine HCl 10 mg once daily on the health-related QOL (HRQL) of adult patients 18-65 years of age with allergic rhinitis. Study duration: 2 weeks. 196 subjects completed the cetirizine study arm; 183 completed the placebo study arm. Validated QOL measurement tool used: RQLQ† | The cetirizine-treated patient group reported greater improvement in overall HRQL (p<0.001) and in each of the seven domains of RQLQ after two weeks (p<0.05 to p<0.001) versus the placebo patient group. |
- SF-36: Medical Outcome Short-Form Health Survey
† RQLQ: Rhinoconjunctivitis Quality of Life Questionnaire
14.2 Comparative Bioavailability Studies
A randomized, two-way, single dose, crossover comparative bioavailability study of APO-CETIRIZINE 20 mg Tablets (Apotex Inc.) and REACTINE® 20 mg Tablets (McNeil Consumer Healthcare, division of Johnson & Johnson Inc.) was conducted on healthy adult Asian male subjects under fasting conditions. Comparative bioavailability data from 21 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Cetirizine (1 x 20 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCt (ng·h/mL) | 6218.03 6306.65 (16.86) | 6337.46 6410.72 (16.16) | 98.1 | 95.8 − 100.5 |
AUCinf (ng·h/mL) | 6594.65 6721.67 (19.75) | 6726.66 6832.82 (18.85) | 98.0 | 95.5 − 100.7 |
Cmax (ng/mL) | 737.69 744.71 (16.08) | 741.01 746.65 (14.94) | 99.6 | 93.8 − 105.6 |
Tmax3 (h) | 0.83 (0.50-1.676) | 1.00 (0.50-1.67) | ||
Thalf4 (h) | 8.96 (21.05) | 9.01 (19.78) | ||
1 APO-CETIRIZINE (as cetirizine hydrochloride ) tablets, 20 mg (Apotex Inc.). 2 REACTINE®(as cetirizine hydrochloride) tablets, 20 mg (McNeil Consumer Healthcare, division of Johnson & Johnson Inc.) were purchased in Canada. 3 Expressed as the median (range) only. 4 Expressed as arithmetic means (CV%) only. | ||||
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute and chronic toxicity studies of cetirizine have been performed in rodents, dogs, and monkeys using oral and intravenous administration of the drug. Significant safety margins, calculated based on rodent hepatotoxicity, ranged from 20 to greater than 370 times the expected maximum clinical dose (EMCD) of 20 mg depending on species, route of administration, and duration of treatment. Toxicity-related liver findings were not evident in dogs receiving cetirizine hydrochloride orally for 1 month at doses up to 338 times the EMCD or for 6 months and 1 year respectively at doses up to 188 and 150 times the EMCD, nor were liver-related changes observed in cynomolgus monkeys receiving cetirizine hydrochloride for 1 month and 1 year respectively at doses up to 375 and 112.5 times the EMCD.
Carcinogenicity:
Dietary administration of cetirizine hydrochloride to mice (52/sex/level) at dose levels of 1, 4, or 16 mg/kg/day for 104 weeks, produced no evidence of a carcinogenic potential at doses 40 times the maximum clinically studied human daily dose (20 mg).
Dietary administration of cetirizine hydrochloride to rats (50/sex/level) at dose levels of 3, 8, or 20 mg/kg/day for 104 weeks produced no evidence of a carcinogenic potential at doses 50 times higher than the maximum clinically studied human daily dose.
Non-neoplastic treatment-related microscopic findings consisted of a tendency towards an increased incidence of centrilobular vacuolation and fat deposition in the liver in male rats at 8 and 20 mg/kg, and of a slight, not dose- related, increased incidence of ulceration of the non-glandular stomach in female rats.
Genotoxicity:
The mutagenic potential of cetirizine hydrochloride was assessed in in vitro non-mammalian cell systems as well as in in vitro and in vivo mammalian cell systems. Cetirizine hydrochloride was not mutagenic.
Reproductive and Developmental Toxicology:
Cetirizine hydrochloride was administered by oral gavage at dose levels of 0, 4, 16 and 64 mg/kg/day to groups of 20 male and 40 female COBS CD-1 mice, in a reproduction and fertility study. There were no effects on male and female fertility or reproductive performance, or on pup development through 2 generations at oral doses up to 16 mg/kg, 40 times the EMCD of 20 mg.
Cetirizine hydrochloride was administered by oral gavage at dose levels of 6, 24, and 96 mg/kg/day to groups of 30 time-mated COBS CD-1 female mice from day 6 to day 15 of gestation. Cetirizine hydrochloride at dose levels up to 96 mg/kg/day from gestation days 6 through 15 was not embryo-feto- toxic nor teratogenic.
Cetirizine hydrochloride, administered by oral gavage at dose levels of 8, 25, 75 and 225 mg/kg/day to mated Sprague Dawley female rats (25 to 26 animals/level) from day 6 to day 15 of gestation, was not teratogenic. The no-effect level for maternal toxicity was 25 mg/kg, and the no-effect level for embryo-feto-toxicity, although not clearly established, was approximately 8 mg/kg. At 8 mg/kg, the incidence of reduced ossification of parietal, interparietal, and hyoid cranial bones was slightly higher than control incidence, but, considered to be within normal variability.
Cetirizine hydrochloride, administered by oral gavage at dose levels of 15, 45, and 135 mg/kg/day to mated New Zealand White female rabbits (16/level at 15 and 45 mg/kg; 18/level at 135 mg/kg; 17 in the control group) from day 6 to day 18 of gestation was not teratogenic. The no-effect level for maternal toxicity and embryo-feto-toxicity was 15 mg/kg, 37.5 times the EMCD. At 15 mg/kg, maternal body weight gain was slightly decreased during the post-treatment period.
Re-analysis of the data demonstrated that no adverse effects on embryo-fetal viability, body weight or morphology were produced by maternally toxic dosages in development toxicity (Segment II) studies in the rat (225 mg/kg/day, 563 times the maximum clinically studied human dose), rabbit (135 mg/kg/day, 338 times the maximum clinically studied human dose) and mouse (96 mg/kg/day, 240 times the maximum clinically study human dose.)
Cetirizine hydrochloride was administered by oral gavage to groups of 32 time-mated COBS CD-1 female mice at dose levels of 0, 6, 24 or 96 mg/kg/day from day 15 of gestation and continued up to sacrifice of the dams on, or shortly after, day 21 post-partum (weaning). Cetirizine hydrochloride, at dose levels of 6 and 24 mg/kg/day, up to 60 times the EMCD, from day 15 of gestation to weaning of pups, did not produce any adverse effect on perinatal conditions or progeny development. At 96 mg/kg, cetirizine hydrochloride treatment was associated with slight maternal effects and lower mean pup weights after birth, at 4 to 21 days of lactation.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. REACTINE® 20 mg Tablet (cetirizine hydrochloride tablets, 20 mg), submission control 286899, Product Monograph, McNeil Consumer Healthcare division of Johnson & Johnson Inc. (OCT 11, 2024)