


Product Monograph - Aredia 90mg
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| I.V. infusion | sterile lyophilized powder:
|
|
INDICATIONS AND CLINICAL USE
- Tumour-induced hypercalcaemia following adequate saline rehydration
Prior to treatment with AREDIA® (pamidronate disodium), renal excretion of excess calcium should be promoted by restoring and maintaining adequate fluid balance and urine output.
- Conditions associated with increased osteoclast activity: predominantly lytic bone metastases and multiple myeloma
- Symptomatic Paget’s disease of bone
CONTRAINDICATIONS
AREDIA® is contraindicated in:
- patients with known or suspected hypersensitivity to AREDIA® (pamidronate disodium), to any of its excipients (see DOSAGE FORMS, COMPOSITION AND PACKAGING), or to other bisphosphonates
- pregnancy
- breast-feeding women
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
General
AREDIA® (pamidronate disodium) MUST NEVER BE GIVEN AS A BOLUS INJECTION SINCE SEVERE LOCAL REACTIONS AND THROMBOPHLEBITIS MAY RESULT FROM HIGH LOCAL CONCENTRATIONS.
AREDIA® SHOULD ALWAYS BE DILUTED AND ADMINISTERED AS A SLOW INTRAVENOUS INFUSION (see DOSAGE AND ADMINISTRATION). REGARDLESS OF THE VOLUME OF SOLUTION IN WHICH AREDIA® IS DILUTED, SLOW INTRAVENOUS INFUSION IS ABSOLUTELY NECESSARY FOR SAFETY.
AREDIA® should not be given together with other bisphosphonates to treat hypercalcaemia since the combined effects of these agents are unknown.
AREDIA® should not be mixed with calcium-containing intravenous infusions.
Patients must be assessed prior to and during administration of AREDIA® to assure that they are appropriately hydrated. This is especially important for patients receiving diuretic therapy.
It is essential in the initial treatment of tumour-induced hypercalcaemia that intravenous rehydration be instituted to restore urine output. Patients should be hydrated adequately throughout treatment but over hydration must be avoided.
Cardiovascular
In patients with cardiac disease, especially in the elderly, additional saline overload may precipitate cardiac failure (left ventricular failure or congestive heart failure). Therefore, overhydration should be avoided especially in patients at risk of cardiac failure. Fever (influenza-like symptoms) may also contribute to this deterioration.
Atrial fibrillation: When the effects of zoledronic acid (4 mg) and pamidronate (90 mg) were compared in one clinical trial, the number of atrial fibrillation adverse events was higher in the pamidronate group (12/556, 2.2%) than in the zoledronic acid group (3/563, 0.5%). Previously, it has been observed in a clinical trial investigating patients with postmenopausal osteoporosis, that zoledronic acid treated patients (5 mg) had an increased rate of atrial fibrillation serious adverse events compared to placebo (1.3% compared to 0.6%). The mechanism of this increased incidence of atrial fibrillation in isolated studies with some bisphosphonates, including AREDIA®, is unknown.
Effects on ability to drive or use machines
Somnolence and/or dizziness may occur following AREDIA® infusion, in which case the patient should not drive, operate potentially dangerous machinery or engage in other activities that may be hazardous because of decreased alertness.
Endocrine and Metabolism
Paget’s disease
Pre-existing hypocalcaemia must be treated by adequate intake of calcium and Vitamin D before initiating AREDIA®. Other disturbances of mineral metabolism (e.g., parathyroidectomy resulting in partial or complete hypoparathyroidism) must also be effectively managed. It is recommended that patients with Paget’s disease of bone have their serum calcium levels assessed before and during treatment with AREDIA® (e.g., as part of their annual examination). All patients should be counselled regarding the importance of calcium and vitamin D supplementation in maintaining serum calcium levels and on the symptoms of hypocalcaemia.
Lytic bone metastases or multiple myeloma
In the absence of hypercalcaemia, patients who are at risk of calcium or vitamin D deficiency, should be given oral calcium and Vitamin D supplementation in order to minimize the risk of hypocalcaemia. In the event that hypercalcaemia develops, calcium and Vitamin D supplements should be discontinued immediately.
Hematologic
In clinical trials for patients with multiple myeloma and metastatic breast cancer, patients treated with AREDIA® had a higher number of anaemia, leukopenia and thrombocytopenia adverse events than placebo-treated patients. Therefore, patients with pre-existing anaemia, leukopenia, or thrombocytopenia should have regular haematology assessments.
Hepatic/Biliary/Pancreatic
There are no clinical data available in patients with severe hepatic impairment. Therefore, caution should be exercised when AREDIA® is given to these patients (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics).
Musculoskeletal Pain
In post-marketing experience, severe and occasionally incapacitating bone, joint, and/or muscle pain has been reported in patients taking bisphosphonates, including AREDIA®. The time to onset of symptoms varied from one day to several months after starting the drug. Most patients had relief of symptoms after stopping treatment. A subset of patients had recurrence of symptoms when re-challenged with the same drug or another bisphosphonate.
Ophthalmologic
Ocular disturbances (conjunctivitis, uveitis, episcleritis and orbital inflammation) have been reported with bisphosphonate therapy, including AREDIA®. Patients with ocular events other than uncomplicated conjunctivitis should be referred to an ophthalmologist for evaluation. Treatment with AREDIA® may need to be discontinued.
Osteonecrosis of the jaw
Osteonecrosis of the jaw (ONJ) has been reported in patients treated with bisphosphonates, including AREDIA®. The majority of reports have occurred in cancer patients treated with bisphosphonates; however, some cases have been reported in patients receiving bisphosphonates for Paget's disease. Although no causal relationship has been established, there is an association between bisphosphonate use and the development of ONJ. Post-marketing experience suggests a greater frequency of reports of ONJ based on tumour type (advanced breast cancer, multiple myeloma) and dental status (dental extractions, periodontal disease and local trauma including poorly fitting dentures); these are associated with a greater risk of developing ONJ. Patients with cancer also receive other treatments that may play a role in the development of ONJ, such as chemotherapy and glucocorticosteroids. Many patients had signs of local infection including osteomyelitis.
Presentation of ONJ may include altered local sensation (hyperaesthesia or numbness), maxillofacial pain, “toothaches”, denture sore spots, loose teeth, exposed bone in the oral cavity, impaired healing, recurrent or persistent soft tissue infection in the oral cavity and marked oral odour. The onset can be from months to years after commencing bisphosphonate therapy. Patients should maintain good oral hygiene; it is recommended that advance cancer patients be encouraged to have an oral examination of both hard and soft tissues, with preventive dentistry prior to treatment with bisphosphonates, and that such assessments continue at regularly scheduled intervals after bisphosphonate therapy is initiated. While on bisphosphonate treatment, patients should avoid invasive dental procedures if possible. Biopsies are not recommended unless metastasis to the jaw is suspected. For patients who develop ONJ while on bisphosphonate therapy, dental surgery may exacerbate the condition. For patients requiring dental procedures, there is no data available to suggest whether discontinuation of bisphosphonate treatment reduces the risk of ONJ. Clinical judgment of the treating physician should guide the management plan of each patient based on individual benefit/risk assessment.
Atypical fractures of the femur
Atypical subtrochanteric and diaphyseal femoral fractures have been reported with bisphosphonate therapy, primarily in patients receiving long-term treatment for osteoporosis. Reports of atypical femoral fracture have also been received in patients treated with AREDIA®. These transverse or short oblique fractures can occur anywhere along the femur from just below the lesser trochanter to just above the supracondylar flare. These fractures occur after minimal or no trauma and some patients experience thigh or groin pain, often associated with imaging features of stress fractures, weeks to months before presenting with a completed femoral fracture. Fractures are often bilateral; therefore the contralateral femur should be examined in AREDIA®-treated patients, who have sustained a femoral shaft fracture. Poor healing of these fractures has also been reported. Discontinuation of AREDIA® therapy in patients suspected to have an atypical femur fracture should be considered pending evaluation of the patient, based on an individual benefit risk assessment.
During AREDIA® treatment patients should be advised to report any thigh, hip or groin pain and any patient presenting with such symptoms should be evaluated for an incomplete femur fracture.
Renal
Bisphosphonates, including AREDIA®, have been associated with renal toxicity manifested as deterioration of renal function and potential renal failure. Renal deterioration, progression to renal failure and dialysis (some with fatal outcome) have been reported very rarely in patients after the initial dose or a single dose of AREDIA®. Deterioration of renal function (including renal failure) has also been reported following long-term treatment with AREDIA® in patients with multiple myeloma.
Due to the risk of clinically significant deterioration in renal function which may progress to renal failure, single doses of AREDIA® should not exceed 90 mg and the recommended infusion time should be observed (see DOSAGE AND ADMINISTRATION).
Special Populations
Pregnant Women:
There are no adequate studies that support the use of AREDIA® in pregnant women. It has been shown that AREDIA® can cross the placenta in rats and has produced marked maternal and embryo/foetal adverse effects in rats and rabbits (see TOXICOLOGY - Reproductive Toxicity). Therefore, AREDIA® may pose a risk to the foetus/new-born child and should not be used during pregnancy (see CONTRAINDICATIONS).
Bisphosphonates are incorporated into the bone matrix, from where they are gradually released over periods of weeks to years. The extent of bisphosphonate incorporation into adult bone, and hence, the amount available for release back into the systemic circulation, is directly related to the total dose and duration of bisphosphonate use. Although there are very limited data on foetal risk in humans, bisphosphonates do cause foetal harm in animals, and animal data suggest that uptake of bisphosphonates into foetal bone is greater than into maternal bone. Therefore, there is a theoretical risk of foetal harm (e.g., skeletal and other abnormalities) if a woman becomes pregnant after completing a course of bisphosphonate therapy. The impact of variables such as time between cessation of bisphosphonate therapy to conception, the particular bisphosphonate used, and the route of administration (intravenous versus oral) on this risk has not been established.
Nursing Women:
There are no adequate studies that support the use of AREDIA® in lactating women. A study in lactating rats has shown that pamidronate passes into the milk. Mothers treated with AREDIA® should therefore not breast feed their infants (see CONTRAINDICATIONS).
Women of child-bearing potential:
Women of child-bearing potential must use highly effective contraception during treatment.
Fertility:
There are no data available.
Paediatrics:
There are no adequate studies that support the use of AREDIA® in children. AREDIA® is not recommended for use in children.
Renal Impairment:
AREDIA® is excreted intact primarily via the kidney (see ACTION AND CLINICAL PHARMACOLCONTRAINDIOGY - Pharmacokinetics), thus the risk of adverse reactions may be greater in patients with impaired renal function. Single doses of AREDIA® should not exceed 90 mg and the recommended infusion time should be observed (see DOSAGE AND ADMINISTRATION).
As with other i.v. bisphophonates renal monitoring is recommended, for instance, measurement of serum creatinine prior to each dose of AREDIA®. Experience with AREDIA® in patients with severe renal impairment (serum creatinine >440 μmol/L in TIH patients; >180 μmol/L in multiple myeloma patients) is limited. If clinical judgment determines that the potential benefits outweigh the risk in such cases, AREDIA® should be used cautiously and renal function carefully monitored. Patients treated with AREDIA® for bone metastases or multiple myeloma should have their dose withheld if renal function has deteriorated (see DOSAGE AND ADMINISTRATION - Renal Impairment).
Monitoring and Laboratory Tests
Patients should have standard serum creatinine and clinical renal function parameters periodically evaluated. Patients receiving frequent AREDIA® infusions over a prolonged period of time, and those with pre-existing renal disease or a predisposition to renal impairment (e.g., patients with multiple myeloma and/or tumour-induced hypercalcaemia) should have evaluations of standard laboratory and clinical parameters of renal function prior to each dose of AREDIA®. Fluid balance (urine output, daily weights) should also be followed carefully. If there is deterioration of renal function during AREDIA® therapy, the infusion must be stopped (see WARNINGS AND PRECAUTIONS).
AREDIA® is excreted intact primarily via the kidney, thus the risk of renal adverse reactions may be greater in patients with impaired renal function.
Patients with anaemia, leukopenia or thrombocytopenia should have regular haematology assessments.
Serum electrolytes, calcium, phosphate and magnesium should be monitored following initiation of therapy with AREDIA®. Occasional cases of mild, transient hypocalcaemia, usually asymptomatic, have been reported. Symptomatic hypocalcaemia occurs rarely and can be reversed with calcium gluconate. Patients who have undergone thyroid surgery may be particularly susceptible to develop hypocalcaemia due to relative hypoparathyroidism.
In tumour-induced hypercalcaemia, either ionized calcium or total serum calcium corrected (adjusted) for albumin should be monitored during treatment with AREDIA®. Serum calcium levels in patients who have hypercalcaemia of malignancy may not reflect the severity of hypercalcaemia, since hypoalbuminaemia is commonly present. Corrected serum calcium values should be calculated using established algorithms, such as:
| cCa = tCa + (0.02 x [40 - ALB]) |
where:
cCa = adjusted calcium concentration (mmol/L)
tCa = measured total calcium concentration (mmol/L)
ALB = measured albumin concentration (g/L)
Although mild hypercalcaemia may be asymptomatic, moderate to severe hypercalcaemia is usually associated with a variety of signs and symptoms, and can be life-threatening if not promptly recognized and treated. Individuals at risk and their caregivers should be made aware that signs and symptoms of hypercalcaemia include: lethargy, fatigue, confusion, loss of appetite, nausea and vomiting, constipation, excessive thirst and urination. Measures such as maintaining mobility and ensuring adequate hydration could diminish the symptoms of hypercalcaemia. However, when symptoms of hypercalcaemia are detected, it is important to seek medical assistance promptly.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Adverse reactions with AREDIA® (pamidronate disodium) are usually mild and transient. The most common adverse reactions are influenza-like symptoms and mild fever (an increase in body temperature of >1°C, which may last up to 48 hours). Fever usually resolves spontaneously and does not require treatment. Acute "influenza-like" reactions usually occur only with the first AREDIA® infusion. The tables below show the incidence of the more commonly observed adverse effects overall and by indication.
Clinical Trial Adverse Drug Reactions
Adverse drug reactions from clinical trials are listed according to system organ classes in MedDRA. Within each system organ class, the adverse drug reactions are ranked by frequency, with the most frequent reactions first. Within each frequency grouping, adverse drug reactions are presented in order of decreasing seriousness. In addition, the corresponding frequency category using the following convention (CIOMS III) is also provided for each adverse drug reaction: very common (≥1/10); common (≥1/100, <1/10); uncommon (≥1/1,000, <1/100); rare (≥1/10,000, <1/1,000); very rare (<1/10,000), including isolated reports.
Infections and infestations
Very Rare: reactivation of Herpes simplex and Herpes zoster
Blood and lymphatic system disorders
Common: anaemia, thrombocytopenia, lymphocytopenia, granulocytopenia
One case of acute lymphoblastic leukemia has been reported in a patient with Paget's disease. The causal relationship to the treatment or the underlying disease is unknown.
Immune system disorders
Uncommon: allergic reactions including anaphylactoid reactions, bronchospasm, dyspnea,
Quincke’s (angioneurotic) oedema.
Very Rare: anaphylactic shock
Metabolism and nutrition disorders
Very Common: hypocalcaemia, hypophosphatemia
Common: hypokalemia, hypomagnesemia, increase in serum creatinine
Uncommon: abnormal liver function tests, increase in serum urea
Very Rare: hyperkalemia, hypernatremia
Nervous system disorders
Common: symptomatic hypocalcaemia (tetany, paresthesia), headache, insomnia, somnolence
Uncommon: seizures, lethargy, agitation, dizziness
Very Rare: confusion, visual hallucinations
Eye disorders
Common: conjunctivitis
Uncommon: uveitis (iritis, iridocyclitis)
Very Rare: scleritis, episcleritis, xanthopsia
Cardiac disorders
Common: Atrial fibrillation
Very Rare: left ventricular failure (dyspnea, pulmonary edema), congestive heart failure (edema) due to fluid overload
Vascular disorders
Common: hypertension
Uncommon: hypotension
Gastrointestinal disorders
Common: nausea, vomiting, anorexia, abdominal pain, diarrhea, constipation, gastritis
Uncommon: dyspepsia
Skin and subcutaneous disorders
Common: rash
Uncommon: pruritus
Musculoskeletal and connective tissue disorders
Common: transient bone pain, arthralgia, myalgia, generalized pain
Uncommon: osteonecrosis of the jaw (ONJ), muscle cramps
Renal and urinary disorders
Uncommon: acute renal failure
Rare: focal segmental glomerulosclerosis including the collapsing variant, nephrotic syndrome
Very Rare: haematuria, deterioration of pre-existing renal disease
General disorders and administration site conditions
Very common: fever and influenza-like symptoms sometimes accompanied by malaise, rigor, fatigue and flushes
Common: reactions at the infusion site: pain, redness, swelling, induration, phlebitis, thrombophlebitis)
Tumour-Induced Hypercalcaemia and Paget’s Disease
Adverse events considered to be related to AREDIA® occurring in ≥1% patients in the specified indication:
Adverse events
| Tumour-induced hypercalcaemia | Paget’s disease | |
|---|---|---|
| no. of patients | n=910 | n=395 |
| (%) | (%) | |
| Fever | 6.9 | 8.9 |
| Headache | 0.0 | 4.8 |
| Hypocalcaemia | 3.2 | 0.8 |
| Influenza-like symptoms | 0.0 | 11.9 |
| Infusion site reaction | 1.7 | 1.8 |
| Malaise | 0.0 | 5.8 |
| Myalgia | 0.0 | 2.0 |
| Nausea | 0.9 | 2.0 |
| Pain (bone) | 0.0 | 8.9 |
| Pain (unspecified) | 0.0 | 7.9 |
| Rigors | 0.0 | 2.8 |
Bisphosphonates, including AREDIA®, have been associated with renal toxicity manifested as deterioration of renal function and potential renal failure (see WARNINGS AND PRECAUTIONS). Since many patients with tumour-induced hypercalcaemia have compromised renal function prior to receiving antihypercalcaemia therapy (see WARNINGS AND PRECAUTIONS), it is difficult to estimate the role of individual bisphosphonates in subsequent changes in renal function. Deterioration of renal function (elevation of serum creatinine of >20% above baseline) which could not be readily explained in terms of pre-existing renal disease, prior nephrotoxic chemotherapies or compromised intravascular volume status has been noted in 7 cases of 404 patients treated with AREDIA® where these data have been reported. As with other i.v. bisphosphonates, renal monitoring is recommended (see WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests).
Bone Metastases and Multiple Myeloma
The most commonly reported adverse events regardless of relationship to therapy are shown in the table below.
Deterioration of renal function (including renal failure) has been associated with bisphosphonates including AREDIA®. Renal monitoring is recommended (see WARNINGS
AND PRECAUTIONS - Monitoring and Laboratory Tests).
| Commonly Reported Adverse Events in Three Controlled Trials (regardless of causality) | ||
|---|---|---|
| Bone metastases and multiple myeloma patients | ||
| Adverse Event | AREDIA® 90 mg | Placebo |
| n=572 | n=573 | |
| General | ||
| Asthenia | 16.4 | 15.4 |
| Fatigue | 30.4 | 35.5 |
| Fever | 35.5 | 30.5 |
| Metastases | 14.0 | 13.6 |
| Digestive System | ||
| Anorexia | 20.8 | 18.0 |
| Constipation | 27.6 | 30.9 |
| Diarrhea | 24.3 | 26.2 |
| Dyspepsia | 13.6 | 12.4 |
| Nausea | 48.4 | 46.4 |
| Pain Abdominal | 17.3 | 14.0 |
| Vomiting | 30.9 | 28.1 |
| Hemic and Lymphatic System | ||
| Anemia | 35.1 | 32.6 |
| Granulocytopenia | 16.8 | 17.3 |
| Thrombocytopenia | 11.0 | 13.1 |
| Musculoskeletal System | ||
| Myalgias | 22.6 | 16.9 |
| Skeletal Pain | 59.4 | 69.1 |
| CNS | ||
| Headache | 24.0 | 19.7 |
| Insomnia | 18.2 | 17.3 |
| Respiratory System | ||
| Coughing | 21.2 | 18.8 |
| Dyspnea | 23.3 | 18.7 |
| Upper Respiratory Infection | 19.8 | 20.9 |
| Urogenital System | ||
| Urinary Tract Infection | 14.5 | 10.8 |
Post-Market Adverse Drug Reactions
The following adverse reactions have been reported in post-marketing use:
General: reactivation of Herpes simplex and Herpes zoster, influenza-like symptoms;
Musculoskeletal and connective tissue disorders: severe and occasionally incapacitating bone, joint, and/or muscle pain, osteonecrosis of the jaw (ONJ), atypical subtrochanteric and diaphyseal femoral fractures;
CNS: confusion and visual hallucinations, sometimes in the presence of electrolyte imbalance;
Skin: rash, pruritus;
Eye disorders: conjunctivitis, scleritis, orbital inflammation;
Renal and urinary disorders: renal tubular disorders (RTD), tubulointerstitial nephritis, glomerulonephropathies;
Respiratory, thoracic and mediastinal disorders: adult respiratory distress syndrome (ARDS), interstitial lung disease (ILD);
Laboratory abnormalities: hyperkalaemia, hypernatremia, haematuria. Instances of allergic manifestations have been reported, including hypotension, dyspnea, or angioedema, and anaphylactic shock.
Description of Selected Adverse Drug Reactions
Atrial fibrillation: When the effects of zoledronic acid (4 mg) and pamidronate (90 mg) were compared in one clinical trial, the number of atrial fibrillation adverse events was higher in the pamidronate group (12/556, 2.2%) than in the zoledronic acid group (3/563, 0.5%). Previously, it has been observed in a clinical trial investigating patients with postmenopausal osteoporosis, that zoledronic acid treated patients (5 mg) had an increased rate of atrial fibrillation serious adverse events compared to placebo (1.3% compared to 0.6%).The mechanism of this increased incidence of atrial fibrillation in isolated studies with some bisphosphonates, including AREDIA®, is unknown.
Osteonecrosis of the jaw: Cases of osteonecrosis of the jaw (ONJ) are uncommon, although data suggest a higher number of reported cases in certain cancers, such as advanced breast cancer and multiple myeloma. Some cases have been reported in patients receiving pamidronate for Paget's disease. The majority of reported cases of ONJ are associated with invasive dental procedures (such as tooth extraction or dental surgery and local trauma including poorly fitting dentures) or periodontal disease. Many patients had signs of local infection, including osteomyelitis.
DRUG INTERACTIONS
Drug interaction studies with AREDIA® in humans have not been conducted. Since hepatic and metabolic clearance of AREDIA® are minor, AREDIA® displays little potential for drug-drug interactions at either the metabolic or protein binding level (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacokinetics and DETAILED PHARMACOLOGY – Animal Pharmacology).
Caution is warranted when AREDIA® is used with other potentially nephrotoxic drugs.
In multiple myeloma patients, the risk of renal deterioration may be increased when AREDIA® is used in combination with thalidomide.
AREDIA® should not be used in combination with other bisphosphonates.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Dosing recommendations differ for tumour-induced hypercalcaemia, lytic bone metastases and multiple myeloma, and Paget’s disease. For patients suffering from TIH and multiple myeloma, see the TIH dosage guidelines.
AREDIA® (pamidronate disodium) must never be given as a bolus injection (see WARNINGS AND PRECAUTIONS). AREDIA® should be administered in a compatible calcium-free intravenous solution (e.g., sterile normal saline or dextrose 5% in water). AREDIA® should be infused slowly.
To minimize local reactions the cannula should be carefully inserted in a relatively large vein.
The infusion rate should never exceed 60 mg/h (1 mg/min) and the concentration of AREDIA® in the infusion solution should not exceed 90 mg/250 mL. A dose of 90 mg should normally be administered as a 2-hour infusion in 250 mL infusion solution. However, in patients with multiple myeloma and in patients with tumour-induced hypercalcaemia it is recommended not to exceed 90 mg in 500 mL over 4 hours (i.e., an infusion rate of 22.5 mg/h).
Renal Impairment
AREDIA® should not be administered to patients with severe renal impairment (creatinine clearance <30 mL/min) unless in cases of life-threatening tumour-induced hypercalcaemia where the benefit outweighs the potential risk.
As with other i.v. bisphosphonates, renal monitoring is recommended, for instance, measurement of serum creatinine prior to each dose of AREDIA®. In patients receiving AREDIA® for bone metastases or multiple myeloma who show evidence of deterioration in renal function, AREDIA® treatment should be withheld until renal function returns to within 10% of the baseline value. This recommendation is based on a clinical study, in which renal deterioration was defined as follows:
For patients with normal baseline creatinine, increase of 0.5 mg/dL.
For patients with abnormal baseline creatinine, increase of 1.0 mg/dL.
A pharmacokinetic study conducted in patients with cancer and normal or impaired renal function indicates that the dose adjustment is not necessary in mild (creatinine clearance 61 to 90 mL/min) to moderate renal impairment (creatinine clearance 30 to 60 mL/min). In such patients, the infusion rate should not exceed 90 mg/4h (approximately 20 to 22 mg/h).
Hepatic Impairment
A pharmacokinetic study indicates that no dose adjustment is necessary in patients with mild to moderate abnormal hepatic function (see DETAILED PHARMACOLOGY - Hepatic impairment). AREDIA® has not been studied in patients with severe hepatic impairment (see WARNINGS AND PRECAUTIONS). Therefore, caution should be exercised when AREDIA® is given to patients with severe hepatic impairment.
Recommended Dose and Dosage Adjustment
Dosing Guidelines for Tumour-Induced Hypercalcaemia
Patients must be adequately rehydrated prior to and during administration of AREDIA®.
In tumour-induced hypercalcaemia, either ionized calcium or total serum calcium corrected (adjusted) for albumin should be monitored during treatment with AREDIA®. Serum calcium levels in patients who have hypercalcaemia of malignancy may not reflect the severity of hypercalcaemia, since hypoalbuminaemia is commonly present. Corrected serum calcium values should be calculated using established algorithms, such as:
| cCa = tCa + (0.02 x [40 - ALB]) |
where:
cCa = adjusted calcium concentration (mmol/L)
tCa = measured total calcium concentration (mmol/L)
ALB = measured albumin concentration (g/L)
Although mild hypercalcaemia may be asymptomatic, moderate to severe hypercalcaemia usually associated with a variety of signs and symptoms, and can be life-threatening if not promptly recognized and treated. Individuals at risk and their caregivers should be made aware that signs and symptoms of hypercalcaemia include: lethargy, fatigue, confusion, loss of appetite, nausea and vomiting, constipation, excessive thirst and urination. Measures such as maintaining mobility and ensuring adequate hydration could diminish the symptoms of hypercalcaemia. However, when symptoms of hypercalcaemia are detected, it is important to seek medical assistance promptly.
The recommended total dose of AREDIA® for a treatment course depends upon initial plasma calcium levels. Doses should be adapted to the degree of severity of hypercalcaemia to ensure normalization of plasma calcium and to optimize the duration of response. A dose of 90 mg should be administered in 500 mL of infusion solution. The infusion rate should not exceed
22.5 mg/hour.
The total dose for a treatment course may be given as a single infusion, or in multiple infusions spread over 2 to 4 consecutive days. The maximum dose of AREDIA® per treatment course is 90 mg whether for initial or repeat treatment courses. Higher doses have not been associated with increased clinical effect.
The following table presents dosing guidelines for AREDIA® derived from clinical data on uncorrected calcium values. These dose ranges also apply for calcium corrected for serum protein.
| Tumour-induced Hypercalcaemia | ||||
| Initial Serum Calcium | Total Dose | Concentration of | Maximum Infusion Rate | |
| (mmol/L) | (mg %) | (mg) | Infusate (mg/mL) | (mg/h) |
| Up to 3.0 | Up to 12.0 | 30 | 30 mg/ 125 mL | 22.5 mg/h |
| 3.0 - 3.5 | 12.0 - 14.0 | 30 or 60§ | 30 mg/ 125 mL 60 mg/ 250 mL | 22.5 mg/h 22.5 mg/h |
| 3.5- 4.0 | 14.0 - 16.0 | 60§ or 90 | 60 mg/ 250 mL 90 mg/ 500 mL | 22.5 mg/h 22.5 mg/h |
| >4.0 | >16.0 | 90 | 90 mg/ 500 mL | 22.5 mg/h |
§Two vials of 30 mg each may be used
Decreases in serum calcium levels are generally observed within 24 to 48 hours after drug administration, with maximum lowering occurring by 3 to 7 days. If hypercalcaemia recurs, or if plasma calcium does not decrease within 2 days, repeat infusions of AREDIA® may be given, according to the dosing guidelines. The limited clinical experience available to date has suggested the possibility that AREDIA® may produce a weaker therapeutic response with repeat treatment in patients with advanced cancer.
Dosing Guidelines for Bone Metastases and Multiple Myeloma
The recommended dose of AREDIA® for the treatment of predominantly lytic bone metastases and multiple myeloma is 90 mg administered as a single infusion every 4 weeks. In patients with bone metastases who receive chemotherapy at 3-weekly intervals, AREDIA® 90 mg may also be given every 3 weeks. A dose of 90 mg should normally be administered as a 2-hour infusion in 250 mL of infusion solution. However, in patients with multiple myeloma it is recommended not to exceed 90 mg in 500 mL over 4 hours.
Radiotherapy is the treatment of choice for patients with solitary lesions in weight bearing bones.
| Bone Metastases | ||
| Disease State | Dosing Schedule | Concentration of Infusate |
| (mg/mL) | ||
| Bone metastases | 90 mg/2 hours every 3*- 4 weeks | 90 mg/250 mL |
| Multiple myeloma | 90 mg/4 hours every 4 weeks | 90 mg/500 mL |
* for patients receiving chemotherapy every 3 weeks
Dosing Guidelines for Paget’s Disease of Bone
The recommended total dose of AREDIA® for a treatment course is 180 to 210 mg. This may be administered as 6 doses of 30 mg once a week (total dose 180 mg). Alternatively, 3 doses of 60 mg may be administered every second week, but treatment should be initiated with a 30 mg dose (total dose 210 mg) as influenza-like reactions are common only with the first infusion. Each dose of 30 mg or 60 mg should be diluted in at least 250 mL or 500 mL, respectively, of normal saline or D5W. An infusion rate of 15 mg per hour is recommended. This regimen, omitting the initial dose, can be repeated after 6 months until remission of disease is achieved, and when relapse occurs (see table below).
| Paget’s Disease | |||
|---|---|---|---|
| Recommended total dose/treatment course: 180-210 mg | |||
| Regimen | Dosing Schedule | Concentration of Infusate | Infusion Rate |
| (mg/mL) | (mg/h) | ||
Regimen 1 Total dose 180 mg | 30 mg once weekly for 6 weeks | 30 mg in ≥250-500 mL | 15 mg/h |
| Regimen 2 | Infusions administered every 2 weeks. | 30/60 mg§ in ≥250-500 mL | 15 mg/h |
| Total dose 210 mg | Initial dose (week 1) = 30 mg; Subsequent doses (weeks 3, 5 & 7) = 60 mg | ||
Re-treatment Regimen Total dose 180 mg | 60 mg every 2 weeks for a total of 3 infusions. | 60 mg§ in 500 mL | 15 mg/h |
§Two vials of 30 mg each may be used
Administration
Reconstitution:
Each vial of sterile lyophilized powder should be reconstituted with Sterile Water for Injection prior to dilution as given in the following table:
| RECONSTITUTION TABLE | |||
| Vial size | Volume of diluent to be added to the vial | Approximate available volume | Nominal concentration |
| 30 mg/10 mL vial | 10 mL | 10 mL | 3 mg/mL |
| 90 mg/10 mL vial | 10 mL | 10 mL | 9 mg/mL |
Dilution of Reconstituted Solution for I.V. Infusion:
Reconstituted solutions that have been prepared with Sterile Water for Injection should be further diluted with either 0.9% w/v sodium chloride or 5% w/v glucose solution prior to intravenous infusion administration. The reconstituted solution is chemically and physically stable for 24 hours at room temperature. However, from a microbiological point of view, it is preferable to use the product immediately after aseptic reconstitution and dilution.
If not used immediately, the duration and conditions of storage prior to use are the care provider’s responsibility. The total time between reconstitution, dilution and end of administration must not exceed 24 hours.
All parenteral products should be visually inspected for particulate matter and discoloration prior to administration. Any solution found to have particulate matter or discoloration should be discarded.
Incompatibilities
Pamidronate forms complexes with divalent cations. For this reason, AREDIA® reconstituted solution must not be mixed with calcium or other divalent cation-containing intravenous solutions such as Ringer’s solution. AREDIA® reconstituted solution should be diluted with 0.9% w/v sodium chloride solution of 5% w/v glucose solution. Studies with containers and infusion sets/devices for infusion made of glass, polyethylene and polyvinylchloride have been shown to be compatible with diluted AREDIA® solution.
OVERDOSAGE
Patients who have received doses higher than those recommended should be carefully monitored. Clinically significant hypocalcaemia with paresthesia, tetany and hypotension, may be reversed by an infusion of calcium gluconate. Acute hypocalcaemia is not expected to occur with AREDIA® (pamidronate disodium) since plasma calcium levels fall progressively for several days after treatment.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
AREDIA® (pamidronate disodium) belongs to a class of bisphosphonates (previously termed diphosphonate), which inhibit bone resorption. The therapeutic activity of AREDIA® is attributable to its potent anti-osteoclastic activity on bone. In animal studies, at therapeutic doses, pamidronate disodium inhibits bone resorption apparently without inhibiting bone formation and mineralization.
The predominant means by which AREDIA® reduces bone turnover both in vitro and in vivo appears to be through the local, direct antiresorptive effect of bone-bound bisphosphonate. Pamidronate disodium binds to calcium phosphate (hydroxyapatite) crystals and directly inhibits the formation and dissolution of this bone mineral component in vitro. In vitro studies indicate that pamidronate disodium is a potent inhibitor of osteoclastic bone resorption. Pamidronate disodium also suppresses the migration of osteoclast precursors onto the bone and their subsequent transformation into the mature resorbing osteoclast.
Tumour-induced hypercalcaemia
In tumour-induced hypercalcaemia, AREDIA® normalizes plasma calcium between 3 and 7 days following the initiation of treatment irrespective of the type of malignancy or presence of detectable metastases. This effect is dependent on initial calcium levels.
AREDIA® improves symptoms associated with hypercalcaemia, e.g. anorexia, nausea, vomiting and diminished mental status.
The kidneys play a prominent role in calcium homeostasis. In addition to skeletal osteolysis, renal dysfunction contributes to the pathogenesis of tumour-induced hypercalcaemia. When diagnosed, most hypercalcemic patients are significantly dehydrated. Elevated plasma calcium antagonizes antidiuretic hormone-induced renal concentration, and thus results in polyuria and excessive fluid loss. Hydration status is further compromised by reduced fluid intake due to nausea, vomiting and diminished mental status. Furthermore, dehydration often leads to a fall in glomerular filtration rate (GFR).
Before AREDIA® therapy is initiated, patients should be adequately rehydrated with isotonic saline (0.9%) (see WARNINGS AND PRECAUTIONS, General). Normalization of plasma calcium levels by AREDIA® in adequately hydrated patients may also normalize plasma parathyroid hormone (PTH) which is suppressed by hypercalcaemia.
The duration of normocalcaemia following AREDIA® treatment varies in patients with tumour-induced hypercalcaemia because of early mortality, and the heterogeneity of diseases and cancer therapies. In general, recurrences tend to occur preferentially after treatment with lower doses: at doses of 30 mg or less, plasma calcium levels tend to increase after approximately 1 week, while at high doses (total treatment doses of 45 to 90 mg) plasma calcium levels remained normal for at least 2 weeks and up to several months. One study has shown a clear relationship between recurrence rates and AREDIA® dose: in patients treated with single i.v. infusions of 30, 45, 60 and 90 mg AREDIA®, recurrence rates were lower for the higher dose group 9 months after initial treatment. In patients in whom the underlying disease is well controlled by cancer therapy, the duration of response tends to be more prolonged.
Clinical experience with AREDIA® in relapsed tumour-induced hypercalcaemia is limited. In general, with re-treatment, the response is similar to that with the first AREDIA® treatment, unless the cancer has progressed significantly. Therefore, AREDIA® treatment appears effective for recurrent hypercalcaemia at doses established for the initial treatment course (see DOSAGE AND ADMINISTRATION). The mechanisms underlying possible decreased effects of repeat treatment with AREDIA® in advanced cancer are unknown.
In severe forms of hypercalcaemia the dose of AREDIA® may be increased, or eventually, a combination drug therapy should be considered (see WARNINGS AND PRECAUTIONS).
Bone metastases and multiple myeloma
Lytic bone metastases in cancer patients are caused by increased osteoclast activity. Metastatic tumour cells secrete paracrine factors which stimulate neighbouring osteoclasts to resorb bone. By inhibiting osteoclast function, bisphosphonates interrupt the cascade of events which lead to tumour-induced osteolysis. Lytic bone destruction causes significant complications and associated morbidity.
Clinical trials in patients with predominantly lytic bone metastases or multiple myeloma showed that AREDIA® prevented or delayed skeletal-related events, (SREs: hypercalcaemia, pathologic fractures, radiation therapy to bone, orthopedic surgery, spinal cord compression) and decreased bone pain. When used in combination with standard anticancer treatment, AREDIA® led to a delay in progression of bone metastases. In addition, osteolytic bone metastases which have proved refractory to cytotoxic and hormonal therapy may show radiological evidence of disease stabilization or sclerosis.
A significant reduction in bone pain was also demonstrated, which in some patients led to decreased analgesic intake and increased mobility. Greater deteriorations in ECOG performance status and Spitzer quality of life scores were seen in the placebo patients compared to AREDIA®-treated patients.
Paget’s disease
Paget's disease of bone, which is characterized by local areas of increased bone resorption and formation with qualitative changes in remodelling, responds well to treatment with AREDIA®. Repeated infusions of pamidronate disodium do not lead to reduced efficacy. In addition, patients resistant to etidronate and calcitonin respond well to AREDIA® infusions. In long-term follow-up to clinical trials, bone fracture rate does not appear to be increased following treatment with pamidronate disodium relative to the normally occurring rate in patients with Paget's disease.
Clinical and biochemical remission of Paget's disease has been demonstrated by bone scintigraphy, by decreases in urinary hydroxyproline and serum alkaline phosphatase, and by symptomatic improvement. Bone scans show that AREDIA® reduces the number of bones and the percent of the skeleton affected and that bone scintigraphy significantly improves. Bone biopsies consistently show histological and histomorphometric improvement indicating the reversal of the disease process. Symptoms improve even in those with severe disease.
Pharmacokinetics
General characteristics: Pamidronate has a strong affinity for calcified tissues and total elimination is not observed within the time frame of experimental studies.
Absorption: Pamidronate sodium is given by intravenous infusion. By definition, absorption is complete by the end of the infusion.
Distribution: Plasma concentrations of pamidronate rise rapidly after infusion is started and fall rapidly when the infusion is stopped. The apparent plasma half-life is about 0.8 hours. Apparent steady state is therefore achieved with infusions of more than about 2 to 3 hours’ duration. When infused i.v. at 60 mg over 1 hour, the peak plasma concentration is about 10 nmol/mL and the apparent total plasma clearance is about 180 mL/min.
Pamidronate disodium binding to human serum proteins is relatively low (about 54%) but increases to approximately 5 mmol when exogenous 95% calcium is added to human plasma.
Biotransformation/Metabolism: Hepatic and metabolic clearances of AREDIA® are minor.
Elimination: Urinary elimination is biphasic (t½α = 1.6 h; t½β = 27.2 h). The apparent renal clearance is about 54 mL/min, and there is a tendency for renal clearance to correlate with creatinine clearance.
After an i.v. infusion, about 20 to 55% of the dose is recovered in the urine within 72 hours as unchanged pamidronate, the majority being excreted within the first 24 hours. Pamidronate does not appear to be metabolized, and the remaining fraction of the dose is retained in the body (within the time frame of the studies). The percentage of the dose retained is independent of both the dose (range 15 to 180 mg) and the infusion rate (range 1.25 to 60 mg/h).
Retention is similar after each dose of pamidronate disodium. Thus, accumulation in bone is not capacity limited and is dependent solely on the cumulative dose.
Special Populations and Conditions
Hepatic Impairment:
The pharmacokinetics of pamidronate were studied in male cancer patients at risk for bone metastases with normal hepatic function (n=6) and mild to moderate hepatic dysfunction (n=9). Each patient received a single 90 mg dose of AREDIA® infused over 4 hours. Although there was a statistically significant difference in the pharmacokinetics between patients with normal and impaired hepatic function, the difference was not considered clinically relevant. Patients with hepatic impairment exhibited higher mean area under the curve (AUC, 39.7%) and maximum concentration (Cmax, 28.6%) values. Nevertheless, pamidronate was still rapidly cleared from the plasma. Drug levels were not detectable in patients by 12 to 36 hours after drug infusion. Because AREDIA® is administered on a monthly basis, drug accumulation is not expected. No changes in AREDIA® dosing regimen are recommended for patients with mild to moderate abnormal hepatic function (see DOSAGE AND ADMINISTRATION).
Renal Impairment:
A pharmacokinetic study conducted in patients with cancer showed no differences in plasma AUC of pamidronate between patients with normal function and patients with mild to moderate renal impairment. In patients with severe renal impairment (creatinine clearance <30 mL/min), the AUC of pamidronate was approximately 3 times higher than in patients with normal renal function (creatinine clearance >90 mL/min) (see DOSAGE AND ADMINISTRATION).
Geriatrics
No data are available in this population.
Paediatrics
No data are available in this population.
STORAGE AND STABILITY
Protect vials from heat (i.e., store below 30°C).
AREDIA® must be kept out of the reach and sight of children and pets.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Availability of Dosage Forms
PrAREDIA® 30 mg (pamidronate disodium) vials for injection:
Each vial of white to practically white lyophilisate contains pamidronate disodium (30 mg). Available in cartons of 1 vial.
PrAREDIA® 90 mg (pamidronate disodium) vials for injection:
Each vial of white to practically white lyophilisate contains pamidronate disodium (90 mg). Available in cartons of 1 vial.
Composition
AREDIA® 30 mg/vial for injection:
Each vial of sterile lyophilized powder contains anhydrous pamidronate disodium (30 mg) and mannitol (470 mg). Phosphoric acid is employed to adjust the pH to 6.3.
AREDIA® 90 mg/vial for injection:
Each vial of sterile lyophilized powder contains anhydrous pamidronate disodium (90 mg) and mannitol (375 mg). Phosphoric acid is employed to adjust the pH to 6.3.
These preparations contain NO preservatives.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Pamidronate disodium |
| Chemical name: | Disodium-3-amino-1-hydroxypropylidene-1,1-bisphosphonate |
| Molecular formula: | C3H9NO7P2Na2 • 5H2O |
| Molecular mass: | 369.1 |
| Structural formula: | C OH PO3HNa PO3HNa CH2CH2 H2N • 5H2O |
| Physicochemical properties: | Description: Colourless, crystalline powder Solubility: Soluble in water or 2N sodium hydroxide, poorly soluble in 0.1N hydrochloric acid and 0.1N acetic acid and insoluble in organic solvents pH: The pH of a 1% solution in water is approximately 8.2. |
CLINICAL TRIALS
The potent inhibitory effect of pamidronate disodium on bone resorption has been demonstrated in clinical studies which have shown pamidronate disodium to be highly effective in the treatment of malignant hypercalcaemia, bone metastases and Paget's disease of the bone.
Tumour-induced Hypercalcaemia
Pamidronate disodium lowered plasma calcium between 3 to 7 days following the initiation of treatment irrespective of the tumour type or presence of detectable bone metastases. In controlled clinical trials, pamidronate disodium was infused at up to 15 mg per hour for doses up to 60 mg whereas 90 mg was infused over 24 hours.
Normalization of plasma calcium levels was accompanied by a decrease in urinary calcium levels to normal, and in some cases, to below normal levels. Since it has been reported that calcium absorption from the kidney and gut are not increased by pamidronate disodium administration, the decreases in urinary calcium observed can be regarded as solely reflecting inhibition of bone resorption rather than effects on the kidney and gut.
Normalization of plasma calcium, including transient hypocalcaemia, is dependent on the initial levels of plasma calcium and the dose of pamidronate disodium selected. Severe hypercalcaemia (plasma calcium >4.0 mmol/L) required higher doses of pamidronate disodium for normalization than moderate hypercalcaemia. However, treatment of moderate hypercalcaemia with high doses of pamidronate disodium (60 to 90 mg) can lead to transient hypocalcaemia. A single infusion of 90 mg is indicated only for cases of severe hypercalcaemia.
Several changes in biochemical parameters occur secondary to the normalization of plasma calcium which reflect the antiresorptive activity of pamidronate disodium. Parathyroid hormone levels, which are usually suppressed in hypercalcaemia of malignancy, typically recover after treatment with pamidronate disodium. This is considered to be a physiological response to lowering of blood calcium levels. Previously suppressed parathyroid hormone levels have not been observed to increase above the upper limits of normal.
Urinary calcium/creatinine and urinary hydroxyproline/creatinine ratios decrease and usually return to within or below normal after treatment with pamidronate disodium. These changes occur within the first week after treatment, as do decreases in serum calcium levels, and are consistent with the antiresorptive pharmacologic action of pamidronate disodium.
The decrease in urinary phosphate excretion despite a rise in glomerular filtration rate after pamidronate disodium administration suggests a positive phosphorus balance. This effect may be related to increased phosphate uptake into bone since the lowering of phosphate excretion occurred after reductions in plasma calcium, plasma phosphate and urinary hydroxyproline. Phosphate levels usually returned to normal within 7-10 days. The ratio of plasma phosphate to the renal phosphate threshold (TmPO4/GFR) is also decreased with pamidronate disodium treatment, probably reflecting a rise in PTH secretion due to the sharp fall in plasma calcium.
Pamidronate disodium had no consistent effects on plasma magnesium levels, thus confirming the absence of effect of pamidronate disodium on magnesium metabolism.
Bone metastases and multiple myeloma
Three large Phase III trials, one in multiple myeloma and two in breast cancer (one versus standard chemotherapy and one versus hormonal therapy) showed that 90 mg AREDIA® (pamidronate disodium) infused every 3-4 weeks significantly decreased the skeletal morbidity rate (number of SREs/year) in all patient groups (see below for a more detailed description of the results). Skeletal-related events (SREs) were defined as episodes of pathologic fractures, radiation therapy to bone, surgery to bone, and spinal cord compression. Radiation to bone was also significantly lower in all AREDIA® groups. The proportion of patients experiencing an SRE was significantly smaller, and the time to first SRE was significantly longer in AREDIA®-treated multiple myeloma and breast cancer + chemotherapy patients. The same trend was seen in the hormonally-treated breast cancer patients. Fewer AREDIA®-treated multiple myeloma patients suffered vertebral pathologic fractures.
Multiple Myeloma
In a double-blind, randomized, placebo-controlled trial, 392 patients with advanced multiple myeloma were enrolled to receive AREDIA® or placebo in addition to their underlying antimyeloma therapy to determine the effect of AREDIA® on the occurrence of skeletal-related events (SREs). SREs were defined as episodes of pathologic fractures, radiation therapy to bone, surgery to bone, and spinal cord compression. Patients received either 90 mg of AREDIA® or placebo as a monthly 4-hour intravenous infusion for 9 months. Of the 392 patients, 377 were evaluable for efficacy (196 AREDIA®, 181 placebo). The proportion of patients developing any SRE was significantly smaller in the AREDIA® group (24% vs. 41%, p<0.001), and the mean skeletal morbidity rate (#SRE/year) was significantly smaller for AREDIA® patients than for placebo patients (mean: 1.1 vs. 2.1, p<0.02). The times to the first SRE occurrence, pathologic fracture, and radiation to bone were significantly longer in the AREDIA® group (p=0.001, 0.006, and 0.046, respectively). Moreover, fewer AREDIA® patients suffered any pathologic fracture (17% vs. 30%, p=0.004) or needed radiation to bone (14% vs. 22%, p=0.049).
In addition, decreases in pain scores from baseline occurred at the last measurement for those AREDIA® patients with pain at baseline (p=0.026) but not in the placebo group. At the last measurement, a worsening from baseline was observed in the placebo group for the Spitzer quality of life variable p<0.001) and ECOG performance status (p<0.011) while there was no significant deterioration from baseline in these parameters observed in AREDIA®-treated patients.
After 21 months, the proportion of patients experiencing any skeletal event remained significantly smaller in the AREDIA® group than the placebo group (p=0.015). In addition, the mean skeletal morbidity rate (#SRE/year) was 1.3 vs. 2.2 for AREDIA® patients vs. placebo patients (p=0.008), and time to first SRE was significantly longer in the AREDIA® group compared to placebo (p=0.016). Fewer AREDIA® patients suffered vertebral pathologic fractures (16% vs. 27%, p=0.005). Survival of all patients was not different between treatment groups.
Bone Metastases
Two double-blind, randomized, placebo-controlled trials compared the safety and efficacy of 90 mg of AREDIA® infused over two hours every three to four weeks for 24 months to that of placebo in preventing SREs in breast cancer patients with osteolytic bone metastases who had at least two lytic metastases, one of which was at least 1 cm in diameter. In one trial patients were receiving hormonal therapy and in the second patients were being treated with chemotherapy, at trial entry.
Breast Cancer Patients Receiving Hormonal Therapy:
372 patients receiving hormonal therapy were randomized to received either 90 mg of AREDIA® (182) or placebo (190) each given as a two-hour infusion at intervals of three to four weeks for 24 months. The proportion of patients developing an SRE was smaller in the AREDIA® treatment group than in the placebo treatment group throughout the trial (3, 6, 9, 12, 15, 18, 21 and 24 months). At the end of the 24 monthly cycles of the trial, the proportion of patients having an SRE (+HCM) was significantly lower for AREDIA® patients than for placebo patients
(56% vs. 67% p=0.027) and the mean skeletal morbidity rate (#SRE/year) was significantly smaller for AREDIA® patients than for placebo patients (mean: 2.4 vs. 3.8, p=0.008). The median time to the first SRE (+HCM) and for radiation to bone significantly greater for AREDIA® patients compared to placebo patients (p=0.049 and 0.016, respectively).
Bone lesion partial response, assessed radiologically, was 30% for the AREDIA® group and 24% for the placebo group (p=0.202). In addition, pain and analgesic scores increased significantly less (p=0.007, and p<0.001, respectively) from baseline in the AREDIA® group than in the placebo group at last measurement.
Breast Cancer Patients Receiving Chemotherapy:
382 patients receiving chemotherapy were randomized to receive either 90 mg of AREDIA® (n=185) or placebo (n=197) each given as a two-hour infusion at intervals of three to four weeks for 24 months. The proportion of patients developing any SRE was significantly lower on AREDIA® than on placebo at 15 months, 18 months, 21 months and 24 months. At the end of the 24 monthly cycles of the trial, the proportion of patients having any SRE (+HCM) was significantly lower for AREDIA® patients than for placebo patients (50% vs. 70% p<0.001) and the mean skeletal morbidity rate (#SRE/year) was significantly smaller for AREDIA® patients than for placebo patients (mean: 2.6 vs. 4.3, p<0.001). The times to the first SRE occurrence, any pathologic fracture, non-vertebral pathologic fracture, and radiation to bone was statistically significantly shorter for placebo compared to AREDIA® patients (p<0.001, 0.009, 0.001 and 0.001, respectively).
Bone lesion complete and partial response, assessed radiologically, was significantly higher in AREDIA® vs. placebo breast cancer patients receiving chemotherapy (34% vs. 19%, p=0.002). In addition, pain and analgesic scores increased significantly less (p=0.050 and p=0.009, respectively) from baseline in the AREDIA® group than in the placebo group at last measurement. In both treatment groups, the ECOG performance status worsened from baseline to endpoint, but the worsening was significantly (p=0.002) larger in the placebo group than in the AREDIA® group.
Paget's Disease:
A clear dose response was demonstrated in a randomized, double-blind clinical trial in which patients received a single dose of pamidronate disodium (N=64). A single infusion of pamidronate disodium 15 mg was not effective; 90 mg was most effective. A 50% fall from baseline was achieved in both ALP (alkaline phosphatase) and OHP:Cr (hydroxyproline:creatinine ratio) in >20% of patients with both 45 and 90 mg pamidronate disodium (p<0.05).
In a multiple-dose infusion study, pamidronate disodium was infused i.v. at 15 mg/2 hours daily for 5 consecutive days (N=12). ALP normalized in 4 patients. Five patients required re-treatment within 6 months and 6 patients after 6 months.
In an open clinical trial, patients were stratified according to initial ALP. Those with ALP <500 (Group A; N=65) or >500 I.U./L (Group B; N=11) were administered 180-195 mg or 360-375 mg pamidronate disodium, respectively, as 30 mg weekly infusions. In Group A, ALP normalized in 80% and OHP:Cr in 88% patients. In addition, bone scan results significantly improved. The duration of remission was 543 and 388 days, respectively. In Group B, ALP and OHP:Cr were reduced 80% and 73%, respectively. These patients had particularly severe disease and only 25% remitted on the basis of OHP:Cr and the median duration of remission was relatively short (52 days). In both groups there were subjective clinical improvements in over 50% patients.
In a larger, open clinical trial of similar design, patients were also stratified according to initial ALP. However, those with ALP <500 (Group A; N=159) or >500 I.U./L (Group B; N=52) were administered 210 mg or 390 mg pamidronate disodium, respectively, as infusions of 30 mg initially then 60 mg every 2 weeks. In Group A, ALP normalized in 81% and OHP:Cr in 93% patients. In addition, bone scan results significantly improved (scintigraphic index, % of skeleton affected and number of bones affected). The median duration of remission was 780 and 494 days, respectively. In Group B, results were similar to those achieved in the previous study. Symptom evaluation demonstrated improvement in 50-60% patients.
DETAILED PHARMACOLOGY
Animal Pharmacology
Subcutaneous administration of pamidronate disodium to rats reduced urinary hydroxyproline excretion within 2 to 8 days starting at 0.16 µmol/kg/day and reaching a maximum at 16 µmol/kg/day. At higher doses (>40 µmol/kg/day) pamidronate disodium inhibited bone mineralization as assessed by the molar ratio of calcium to hydroxyproline in metaphyseal bone. Doses below this level reduced bone alkaline phosphatase activity, hydroxyproline synthesis and calcium content. These changes in bone apposition parameters required at least 23 days exposure for a maximal effect, compared to 8 days for effects on bone resorption. Thus, pamidronate disodium inhibits bone resorption in rats at doses several-fold lower than those that affect bone growth and mineralization.
Low doses of pamidronate disodium increased both elastic and ultimate bone strength in the rat, whereas high doses (>14 mg/kg/day I.P.) produced opposite effects. The latter doses were far above those required to completely suppress calcium mobilization in rats.
In dogs, long-term intermittent treatment with pamidronate disodium retains structural integrity in cortical and vertebral bone. Intermittent oral pamidronate disodium treatment for 12 weeks caused no changes in the mechanical properties of cortical femoral bone but trabecular bone showed a significant increase in compressive stiffness and torsional strength.
In mice, S.C. administration of 16 µmol/kg (4.5 mg/kg) pamidronate disodium for 7 days increased tibial growth plate width without concomitant effects on longitudinal growth.
The intermittent administration of pamidronate disodium to animals was also effective in inhibiting bone resorption. In 10-week old pigs, administration of 1.6 µg/kg/day pamidronate disodium for 5 out of 21 days produced a significant inhibition of bone resorption that was equivalent to that produced with a continuous 60-day dosing regimen. In mice, once weekly treatment for 1 year augmented diaphyseal wall thickness and the number of persisting trabeculae. This effect was mainly achieved by a suppression of endosteal bone resorption, which occurs during the retrogressive phase of C57BL/Silberberg mice aged more than
4 months. Bones of treated mice also demonstrated a higher femoral calcium content and ash weight, and increased resistance to fracture stress in comparison to untreated controls.
As a result of hormonal regulation, pamidronate disodium does not significantly affect serum calcium in normal, healthy animals. Under various experimental conditions however, changes in serum calcium values will reflect the effects of pamidronate disodium on bone metabolism. In thyroid-parathyroidectomized rats, the 1,25(OH)2 vitamin D3-stimulated mobilization of calcium from bone was inhibited by pamidronate disodium at daily doses of 0.02-0.6 mg/kg S.C. Similarly, pamidronate disodium reduced hypercalcaemia of malignancy in rats bearing Walker 256 carcinosarcoma tumours. Mice bearing 5T2 myelomas had fewer skeletal lesions if treated with pamidronate disodium, although the myeloma itself was unaffected by pamidronate disodium treatment.
Twenty-four hours after single intravenous administration of 10 mg/kg to growing rats, approximately 50% of the dose is retained in bone, 0.1% in blood, 1.1% in spleen and 30% in liver. Pamidronate disodium is also stored in tracheal cartilage of rats. The percent uptake into the liver increases with dose, ranging from 3.0% at 0.01 mg/kg, to 30% at 10 mg/kg doses. Levels accumulated in liver at 10 mg/kg gradually decline during the 2 weeks after administration, with redistribution and uptake into bone, or elimination by the kidneys over 24-48 hours.
Pamidronate disodium does not undergo significant metabolism in the rat: at 10 mg/kg i.v., approximately 20% of the dose is excreted unchanged in the urine by 24 hours. Bile accounts for less than 0.1% of the administered dose. The biological half-life of pamidronate disodium in rats has been estimated to be approximately 300 days.
A preferential uptake and prolonged storage of 14C-pamidronate disodium in bone is also observed in dogs following single intravenous administration. Radioactivity is detectable in blood only up to 72 hours.
Human Pharmacology
Pamidronate disodium is a second-generation bisphosphonate. These agents are synthetic analogues of pyrophosphate and specifically inhibit bone resorption. First generation compounds such as 1-hydroxyethylidene-1, 1-biphosphonic acid (HEBP or etidronate disodium) block resorption but may also inhibit bone mineralization. Pamidronate disodium, a second generation bisphosphonate, inhibits bone resorption at doses that do not appear to affect the mineralization of newly-formed osteoid tissue and thus constitutes a rational treatment for pathological bone resorption. The predominant mode of action appears to be a local, direct effect; bisphosphonates complex tightly to, and inhibit the formation and dissolution of, hydroxyapatite crystals.
TOXICOLOGY
Acute Toxicity
In acute toxicity studies, pamidronate disodium was better tolerated when administered as a short-term i.v. infusion or i.p. than as a bolus i.v. dose, presumably because of lower plasma concentrations. In mice, the i.v. bolus and I.P. LD50 of pamidronate disodium were 20.3 mg/kg and 40 mg/kg respectively; in rats 80 mg/kg and 65 mg/kg, and in rabbits, 18.5 mg/kg and 190 mg/kg. In dogs, the LD50 was >10 mg/kg for a bolus i.v. dose and >40 mg/kg when administered as an i.v. infusion.
Subacute and Chronic Toxicity
Pamidronate disodium has been administered to mice, rats, rabbits and dogs for 3 months by intermittent i.v. infusion or a bolus i.v. dose. Repeat dose animal studies demonstrate that intermittent administration of pamidronate disodium by i.v. infusion is better tolerated than the bolus i.v. route. Dose- and regimen-dependent nephropathy occurred in all species except the mouse. These studies indicate that adverse effects with pamidronate disodium correlate strongly with peak plasma concentration. It should therefore be administered intermittently by slow infusion; daily intravenous administration, especially as a bolus, should be avoided.
The no-toxic effect level for rats and dogs administered 2, 6 or 20 mg/kg by i.v. infusion for 1 hour weekly for 3 months was 2 mg/kg for both species. In all dose groups in the dog, but only at the highest dose in the rat, pharmacological effects were evident as non-reversible, dose-related increase in primary spongy bone formation with a widened metaphyses, increased calcification and impaired remodelling with no impairment of mineralization. This was accompanied by reduced AP and serum phosphate. The major target organ for toxic effects was the kidney, but following high i.v. doses, especially those administered as a bolus, inflammation/degeneration was also observed in the stomach and the lung, and to a lesser extent in the spleen, liver and heart.
Reproductive Toxicity
Pamidronate crosses the placenta barrier readily and accumulates primarily in the foetal bones in rats. Reproductive toxicological studies conducted in rats and rabbits by peroral or intravenous administration at dose levels comparable to human therapeutic dose revealed that pamidronate causes the following adverse events and developmental abnormalities: reduced fertility in both sexes and the first generation of the offspring, distress and prolongation of parturition process with fatal outcome, marked increases in resorption, pre- and post-implantation losses, reduced number of viable pups born, delayed skeletal maturation and ossification, shortening of long bones and visceral and external abnormality (dilated and kinked ureters, displaced testis, shortened body, curved or hooked joints, mal-rotated hind limbs, subcutaneous haemorrhage and oedema, etc.).
A study in lactating rats has shown that pamidronate passes into the milk.
Carcinogenesis and Mutagenesis
Mutagenic potential was assessed by three different methods both in vitro (Ames test, point mutation test, and a cytogenetic test) and in vivo (nucleus anomaly test, sister chromatid exchange study and a micronucleus test). There was no evidence of mutagenic potential in vivo. In vitro tests were also negative apart from a slight increase in the number of chromosome aberrations in Chinese hamster ovary cells at the highest concentration only (2500 µg/mL).
Carcinogenic potential was assessed in both mice and rats treated with pamidronate disodium ≤40 mg/kg/day and ≤75 mg/kg/day, respectively, by gavage for 2 years. These studies repeated earlier studies completed in the 1970's, in which pamidronate disodium ≤1000 mg/kg was added to the food supply. From these studies, pamidronate disodium does not appear to have carcinogenic potential.
The only unexpected finding in these repeat carcinogenicity studies was hydrocephaly observed in the mouse study. This event occurred at all dose levels, and was probably caused by changes in cranial bones as a result of the pharmacological activity of the compound in the young, growing animals. It is not thought to be of relevance in adult patients in whom bone growth is complete.
In mice receiving pamidronate disodium ≤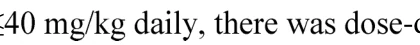 -dependent reduction in the incidence of neoplasms, which was attributed to pamidronate disodium-related decreases in food consumption; mice fed a restricted diet have been shown to develop fewer tumours than those fed ad libitum. In this study, the incidence of liver tumours was reduced relative to control animals. In female mice fed with pamidronate disodium 879 mg/kg/day in the diet, the incidence of benign hepatomas was increased relative to control animals.
In both rat carcinogenicity studies, the incidence of neoplastic lesions was within the range observed with historical controls, apart from a slight increase in intestinal leiomyomas observed in females in one study only. Intestinal leiomyomas occur spontaneously in 0.44% Wistar rats (range 0-2%) used as controls in carcinogenicity studies. The mean incidence of these tumours in female Wistar rats administered 1000 mg/kg/day in the diet was 1.2% (range 0-3.7%). As no intestinal leiomyomas were observed in female rats in the other rat study, it is unlikely that these benign, non-fatal tumours are of biological or clinical significance.
REFERENCES
- 1. BERENSON JR, LICHTENSTEIN A, PORTER L, DIMOPOULOS M, BORDONI R et al. Efficacy of pamidronate in reducing skeletal events in patients with advanced multiple myeloma. NEJM 1996; 334: 488-493
- 2. BODY JJ, MAGRITTE A, SERA J, SCULIER JP, and BORKOWSKI A. Aminohydroxypropylidene bisphosphonate (APD) treatment for tumor-associated hypercalcemia: A randomized comparison between a 3-day treatment and single 24-hour infusions. J Bone Miner Res 1989; 4 (6): 923-928
- 3. BODY JJ, BORKOWSKI A, CLEEREN A, and BIJVOET OLM. Treatment of malignancy-associated hypercalcemia with intravenous aminohydroxypropylidene diphosphonate. J Clin Oncol 1986; 4 (8): 1177-1183
- 4. BODY JJ, POT M, BORKOWSKI A, SCULIER JP, and KLASTERSKY J. Dose/response study of aminohydroxypropylidene bisphosphonate in tumor-associated hypercalcemia. Am J Med 1987; 82: 957-963
- 5. BOONEKAMP PM, van der WEE-PALS LJA, van WIJK-VAN LENNEP MML, THESING CW, and BIJVOET OLM. Two modes of action of bisphosphonates on osteoclastic resorption of mineralized matrix. Bone Miner 1986; 1: 27-39
- 6. CAL JC, and DALEY-YATES PT. Disposition and nephrotoxicity of 3-amino-1-hydroxypropylidene-1-1-bisphosphonate (APD) in rats and mice. Toxicology 1990; 65: 179-197
- 7. COLEMAN RE, and PUROHIT OP. Osteoclast inhibition for the treatment of bone metastases. Cancer Treatment Reviews 1993; 19:79-103
- 8. COLEMAN RE, and RUBENS RD. 3(amino-1,1-hydroxypropylidene) bisphosphonate (APD) for hypercalcemia of breast cancer. Br J Cancer 1987; 56: 465-469
- 9. COLEMAN RE, WOLL PJ, SCRIVENER W, RUBENS RD. Treatment of bone metastases from breast cancer with (3-amino-1-hydroxypropylidene)-1,1-bisphosphonate (APD). Br J Cancer 1988;58:621-625
- 10. DALEY-YATES PT, DODWELL DJ, PONGCHAIDECHA M, COLEMAN RE and HOWELL A. The clearance and bioavailability of pamidronate in patients with breast cancer and bone metastases. Calcif Tissue Int 1991;49:433-435
- 11. FITTON A, and McTAVISH D. Pamidronate. A review of its pharmacological properties and therapeutic efficacy in resorptive bone disease. Drugs 1991; 41: 289-318
- 12. FLANAGAN AM, and CHAMBERS TJ. Inhibition of bone resorption by bisphosphonate; interactions between bisphosphonates, osteoclasts, and bone. Calcif Tissue Int 1991; 49:407-415
- 13.
FOLAY-NOLAN D, DALY MJ, WILLIAMS D, WASTI A, and MARTIN M.
- Pamidronate associated hallucinations. Ann Rheum Dis 1992; 51: 927-928
- 14. FRAUNFELDER FW, FRAUNFELDER FT, and JENSVOLD B. Scleritis and Other Ocular Side Effects Associated With Pamidronate Disodium. Am J Ophthalmol 2003; 135 (2): 219 - 222
- 15. GRAEPEL P, BENTLEY P, FRITZ H, MIYAMOTO M, and SLATER SR. Reproduction toxicity studies with pamidronate. Arzneim Forsch / Drug Res 1992; 42: 654-667
- 16. HARINCK HIJ, BIJVOET OLM, PLANTINGH AST, BODY JJ, ELTE JWF, SLEEBOOM HP, WILDIERS J, and NEIJT JP. Role of bone and kidney in tumor-induced hypercalcemia and its treatment with bisphosphonate and sodium chloride. Am J Med 1987; 82: 1133-1142
- 17. HARINCK HIJ, PAPAPOULOS SE, BLANKSMA HJ, MOOLENAAR AJ, VERMEIJ P, and BIJVOET OLM. Paget's disease of bone: early and late responses to three different modes of treatment with aminohydroxypropylidene bisphosphonate (APD). Br Med J 1987; 295: 1301-1305
- 18. HOSKING DJ, COWLEY A, and BUCKNALL CA. Rehydration in the treatment of severe hypercalcemia. Q J Med 1981; 200: 473-481
- 19. HUGHES DE, MIAN M, GUILLARD-CUMMING DF, and RUSSELL RGG. The cellular mechanism of action of bisphosphonates. Drugs Exptl Clin Res 1991; 17: 109-114
- 20. KELLIHAN MJ, and MANGINO PD. Pamidronate. Ann of Pharmacother 1992; 26: 1262-1269
- 21. LEYVRAZ S, HESS U, FLESCH G, BAUER J, SAUFFE S, FORD JM, and BURCKHARDT P. Pharmacokinetics of pamidronate in patients with bone metastases. J Natl Cancer Inst 1992;84:788-792
- 22. LOWIK CWGM, VAN DER PLUIJM G, VAN DER WEE-PALS LJA, BLOYS VAN TRESLONG-DE GROOT H, and BIJVOET OLM. Migration and phenotypic transformation of osteoclast precursors into mature osteoclasts: The effect of bisphosphonate. J Bone Miner Res 1988; 3 (2): 185-192
- 23. MASUD T, and FRANCIS RM. Adverse effects of drugs for bone disease. Adv Drug React Bull 1992; (155): 583-586
- 24. MORTON AR, CANTRILL JA, CRAIG AE, HOWELL A, DAVIES M, and ANDERSON DC. Single dose versus daily intravenous aminohydroxypropylidene biphosphonate (APD) for the hypercalcemia of malignancy. Br Med J 1988; 296: 811-814
- 25.
MORTON AR, CANTRILL JA, PILLAI GV, MCMAHON A, ANDERSON DC, and HOWELL A. Sclerosis of lytic bone metastases after disodium aminohydroxypropylidene
- bisphosphonate (APD) in patients with breast carcinoma. Br Med J 1988; 297: 772-773
- 26. PUROHIT OP, ANTHONY C, RADSTONE CR, OWEN J and COLEMAN RE. High-dose intravenous pamidronate for metastatic bone pain. Br J Cancer 1994; 70: 554-558
- 27. RALSTON SH, GALLAGHER SJ, PATEL U, DRYBURGH FJ, FRASER WD, COWAN RA, and BOYLE IT. Comparison of three intravenous bisphosphonates in cancer-associated hypercalcemia. Lancet 1989; II (8673): 1180-1182
- 28. RALSTON SH, GALLACHER SJ, PATEL U, CAMPBELL J, and BOYLE IT. Cancer-associated hypercalcemia: Morbidity and mortality. Clinical experience in 126 treated patients. Ann Intern Med 1990; 112 (7): 499-504
- 29. RITCH PS. Treatment of cancer-related hypercalcemia. Semin Oncol 1990; 17 (2 Suppl 5): 26-33
- 30. RYAN PJ, and SAMPATH R. Idiopathic orbital inflammation following intravenous pamidronate. Rheumatology 2001; 40: 956-957
- 31. SATO M, GRASSER W, ENDO N, AKINS R, SIMMONS H, THOMPSON DD, GOLUB E, and RODAN GA. Bisphosphonate action; Alendronate localization in rat bone and effects on osteoclast ultrastructure. J Clin Invest 1991; 88: 2095-2105
- 32. SAWYER N, NEWSTEAD C, DRUMMOND A, NEWLAND A, and CUNNINGHAM J. One-shot high-dose pamidronate disodium (APD): effective, simple treatment for hypercalcemia in haematological malignancy. Clin Lab Haematol 1989; 11: 179-184
- 33. SERIS ES. Perspectives: a practical guide to the use of pamidronate in the treatment of Paget's disease. J Bone Mineral Res 1994; 9 (3):303-304
- 34. SHAHINIAN VB, KUO YF, FREEMAN JL, and GOODWIN JS. Risk of Fracture after androgen deprivation for prostate cancer. N Engl J Med. 2005 Jan 13;352(2):154-64
- 35. SHINODA H, ADAMEK G, FELIX R, FLEISCH H, SCHENK R, and HAGAN P. Structure-activity relationships of various bisphosphonates. Calcif Tissue Int 1983; 35: 87-99
- 36. SILVERMAN P, and DISTELHORST CW. Metabolic emergencies in clinical oncology. Semin Oncol 1989; 16 (6): 504-515
- 37. THIEBAUD D, JAEGER PH, JACQUET AF, and BURCKHARDT P. Dose response in the treatment of malignant hypercalcemia by a single infusion of the bisphosphonate AHPrBP (APD). J Clin Oncol 1988; 6 (5): 762-768
- 38. THURLIMANN B, MORANT R, JUNGI WF, and RADZIWILL A. Pamidronate for pain control in patients with malignant osteolytic bone disease: a prospective dose-effect study. Supportive Care Cancer 1992; 2: 61-65
- 39. WINGEN F, and SCHMAHL D. Pharmacokinetics of the osteotropic diphosphonate 3-amino-1-hydroxypropane-1,1-diphosphonic acid in mammals. Arzneimittelforschung 1987; 37 (II) (9): 1037-1042
- 40. YATES AJP, MURRAY RML, JERUMS GJ, and MARTIN TJ. A comparison of single and multiple intravenous infusions of 3-amino-1-hydroxypropylidene-1,1-bisphosphonate (APD) in the treatment of hypercalcemia of malignancy. Aust N Z J Med 1987; 17: 387-391
- 41. VALENTIN-OPRAN A, CHARHON SA, MEUNIER PJ, EDOUARD CM, ARLOT ME. Quantitative histology of myeloma-induced bone changes. Br J Haematol 1982; 52:601-10