


Product Monograph - Boostrix
RECENT MAJOR LABEL CHANGES
| Section | Date |
|---|---|
| 1 INDICATIONS | AUG 2021 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | AUG 2021 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women | AUG 2021 |
| 7 WARNINGS AND PRECAUTIONS, Guillain-Barré Syndrome | SEP 2022 |
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | APR 2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
8 INDICATIONS ............................................................................................................... 4
9 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 4
4.1 Dosing Considerations ............................................................................................ 4
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.4 Administration ........................................................................................................ 6
5 OVERDOSAGE .............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 7
7.1 Special Populations................................................................................................. 8
7.1.1 Pregnant Women ............................................................................................. 8
7.1.2 Breast-feeding .................................................................................................. 9
8 ADVERSE REACTIONS .................................................................................................. 9
8.2 Clinical Trial Adverse Reactions .............................................................................. 9
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 11
8.5 Post-Market Adverse Reactions ........................................................................... 12
9 DRUG INTERACTIONS ................................................................................................ 13
9.3 Drug-Behavioural Interactions .............................................................................. 13
9.4 Drug-Drug Interactions ......................................................................................... 13
9.5 Drug-Food Interactions ......................................................................................... 13
9.6 Drug-Herb Interactions ......................................................................................... 13
9.7 Drug-Laboratory Test Interactions ........................................................................ 13
10 CLINICAL PHARMACOLOGY ....................................................................................... 13
10.1 Mechanism of Action ...................................................................................... 13
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 14
PART II: SCIENTIFIC INFORMATION ....................................................................................... 15
13 PHARMACEUTICAL INFORMATION ............................................................................ 15
14 CLINICAL TRIALS ........................................................................................................ 15
14.1 Clinical Trials by Indication ............................................................................. 15
Booster vaccination against diphtheria, tetanus and pertussis ...................................... 15
Passive protection against pertussis in infants (less than 3 months of age) born to mothers vaccinated during pregnancy ........................................................................... 21
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 22
PATIENT MEDICATION INFORMATION .................................................................................. 23
PART I: HEALTH PROFESSIONAL INFORMATION
8 INDICATIONS
BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) is indicated for:
- Booster vaccination against diphtheria, tetanus and pertussis of individuals from the age of four years onwards.
- Passive protection against pertussis in early infancy following maternal immunisation during pregnancy (see 4 DOSAGE AND ADMINISTRATION, 7 WARNINGS AND PRECAUTIONS, and 14 CLINICAL TRIALS).
BOOSTRIX is not intended for primary immunization.
9 CONTRAINDICATIONS
- BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) is contraindicated in individuals who are hypersensitive to any component of the vaccine or individuals having shown signs of hypersensitivity after previous administration of diphtheria, tetanus, or pertussis vaccines (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING)
- BOOSTRIX is contraindicated if the individual has experienced an encephalopathy of unknown etiology, occurring within 7 days following previous vaccination with pertussis containing vaccine. In these circumstances, adult-type combined diphtheria tetanus vaccine should be used.
- BOOSTRIX should not be administered to individuals who have experienced transient thrombocytopenia or neurological complications following an earlier immunization against diphtheria and/or tetanus.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Tetanus Prophylaxis in Wound Management
Table 1 summarizes the recommended use of immunizing agents in wound management. It is important to ascertain the number of doses of toxoid previously given and the interval since the last dose. When a tetanus booster dose is required, the combined preparation of tetanus and diphtheria toxoid formulated for adults (Td) is preferred. Appropriate cleansing and debridement of wounds is imperative, and use of antibiotics may be considered.
Some individuals with humoral immune deficiency, including those with HIV infection, may not respond adequately to tetanus toxoid. Therefore, tetanus immune globulin (TIG) should be used in addition to tetanus toxoid if a wound occurs that is not clean, regardless of the time elapsed since the last booster.
Table 1 - Guide to Tetanus Prophylaxis in Wound Management
| History of Tetanus Immunization | Clean, minor wounds | All other wounds | ||||||
|---|---|---|---|---|---|---|---|---|
| Td or Tdap* | Tig** | Td or Tdap* | Tig | |||||
| Uncertain of < 3 doses of an immunization series† | Yes | No | Yes | Yes | ||||
| ≥ 3 doses received in an immunization series† | No‡ | No | No§ | No¶ | ||||
*Adult type combined tetanus and diphtheria toxoids or a combined preparation of diphtheria, tetanus and acellular pertussis. If the individual is < 7 years old a tetanus toxoid-containing vaccine is given as part of the routine childhood immunization.
**Tetanus immune globulin, given at a separate site from Td (or Tdap).
† The immunization series for tetanus is described in the text (Schedule and Dosage).
‡Yes, if > 10 years since last booster.
§Yes, if > 5 years since last booster. More frequent boosters not required and can be associated with increased adverse events. The bivalent toxoid, Td, is not considered to be significantly more reactogenic than T alone and is recommended for use in this circumstance. The individual should be informed that Td (or Tdap) has never been given.
¶Yes, if individuals are known to have a significant humoral immune deficiency state (e.g. HIV, agammaglobulinemia) since immune response to tetanus toxoid may be suboptimal.
4.2 Recommended Dose and Dosage Adjustment
A single 0.5 mL dose of the vaccine is recommended.
Repeat vaccination against diphtheria and tetanus should be performed at intervals as per official recommendations (generally 10 years). It is not necessary to recommence primary vaccination, should the officially recommended interbooster interval be exceeded.
If BOOSTRIX is administered to a pregnant woman, it should ideally be done during the third trimester of pregnancy or according to recommendations from the National Advisory Committee on Immunization (NACI).
BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) should not be mixed with other vaccines in the same syringe.
BOOSTRIX is for deep muscular injection.
4.4 Administration
Pre-filled syringe Instructions
Hold the syringe by the barrel, not by the plunger. Unscrew the syringe cap by twisting it anticlockwise. | |
|---|---|
To attach the needle, connect the hub to the Luer Lock Adaptor and rotate a quarter turn clockwise until you feel it lock. Do not pull the syringe plunger out of the barrel. If it happens, do not administer the vaccine. |
Prior to vaccination, the vaccine should be well shaken in order to obtain a homogeneous turbid white suspension and visually inspected for any foreign particulate matter and/or variation of physical aspect prior to administration. In the event of either being observed, do not administer the vaccine, and any unused vaccine or waste material should be disposed of in accordance with local requirements.
5 OVERDOSAGE
Cases of overdose have been reported during post-marketing surveillance. Adverse events following overdosage, when reported, were similar to those reported with normal vaccine administration.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
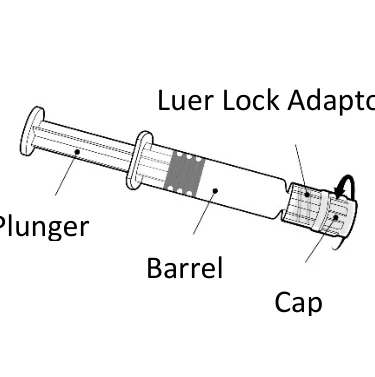 Plunger Barrel Cap Luer Lock Adaptor | |
|---|---|
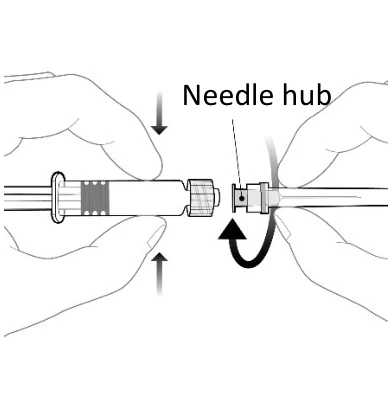 Needle hub |
Table 2 Administration Route, Dosage Form, Strength, Non-medicinal Ingredients
Packaging
BOOSTRIX is available in prefilled syringes (type I glass) with a plunger stopper (butyl rubber) and with a rubber tip cap (in packages of 10).
Description
BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) is presented as a turbid white suspension in a single dose prefilled syringe. Upon storage, a white deposit and clear supernatant can be observed. This is a normal finding.
BOOSTRIX meets the World Health Organization requirements for manufacture of biological substances and for diphtheria and tetanus vaccines.
7 WARNINGS AND PRECAUTIONS
General
It is good clinical practice that immunization should be preceded by a review of the medical history (especially with regards to previous immunization and possible occurrence of undesirable events).
As with any other vaccine, BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) may not protect 100% of individuals receiving the vaccine.
BOOSTRIX should under no circumstances be administered intravenously.
As with other vaccines, the administration of BOOSTRIX should be postponed in individuals suffering from acute severe febrile illness. The presence of a minor infection is not a contraindication.
If any of the following events occur in temporal relation to administration of whole-cell DTP or acellular DTP vaccine, the decision to give subsequent doses of vaccine containing the pertussis component should be carefully considered. There may be circumstances, such as high incidence of pertussis, in which the potential benefits outweigh possible risks, particularly since these events have not been proven to cause permanent sequelae.
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Intramuscular | Suspension for injection/ not less than 2.5 limit of flocculation (‘Lf’) or 2 IU (‘International Units') of diphtheria toxoid; 8 mcg of pertussis toxoid; 8 mcg of filamentous hemagglutinin; 2.5 mcg of pertactin (69 kDa outer membrane protein); and, not less than 5 Lf (20 IU) of tetanus toxoid. | 0.5 mg aluminum (as aluminum salts), sodium chloride, water for injection. |
- Temperature of ≥ 40.0oC within 48 hours of vaccination, not due to another identifiable cause.
- Collapse or shock like state (hypotonic hyporesponsive episode) within 48 hours of vaccination.
- Persistent, inconsolable crying lasting ≥ 3 hours, occurring within 48 hours of vaccination.
- Convulsions with or without fever, occurring within 3 days of vaccination.
Syncope (fainting) can occur following, or even before, any vaccination as a psychogenic response to the needle injection. It is important that procedures are in place to avoid injury from faints.
Guillain-Barré Syndrome
A review by the National Academy of Medicine found evidence for a causal relationship between receipt of tetanus toxoid and both Guillain-Barré Syndrome (GBS) and brachial neuritis. If GBS occurred within 6 weeks of receipt of prior vaccine containing tetanus toxoid, the decision to give BOOSTRIX or any vaccine containing tetanus toxoid should be based on careful consideration of the potential benefits and possible risks.
Hematologic
BOOSTRIX should be administered with caution to individuals with thrombocytopenia or a bleeding disorder since bleeding may occur following an intramuscular administration to these individuals. Firm pressure should be applied to the injection site (without rubbing) for at least 2 minutes.
Immune
HIV infection is not considered as a contraindication for diphtheria, tetanus and pertussis vaccination. The expected immunological response may not be obtained after vaccination.
Neurologic
In children with progressive neurological disorders, including infantile spasms, uncontrolled epilepsy or progressive encephalopathy, it is better to defer pertussis (Pa or Pw) immunization until the condition is corrected or stable. However, the decision to give pertussis vaccine must be made on an individual basis after careful consideration of the risks and benefits.
A history or a family history of convulsions and a family history of an adverse event following DTP vaccination do not constitute contraindications.
Sensitivity/Resistance
As with other injectable vaccines, appropriate medication (e.g. Epinephrine 1:1000) should be readily available for immediate use in case of anaphylaxis or anaphylactoid reactions following administration of the vaccine. For this reason, the vaccinee should remain under medical supervision for 30 minutes after immunization.
7.1 Special Populations
7.1.1 Pregnant Women
Safety data from a randomized controlled clinical trial (341 pregnancy outcomes) and from a published prospective observational study where BOOSTRIX was administered to pregnant women during the third trimester (793 pregnancy outcomes), as well as data from post-marketing surveillance where pregnant women were exposed to BOOSTRIX in the second or third trimester have shown no vaccine related adverse effect on pregnancy or on the health of the fetus/newborn child.
Human data from prospective clinical studies on the use of BOOSTRIX during the first and second trimester of pregnancy are not available. Animal studies with BOOSTRIX do not indicate direct or indirect harmful effects with respect to fertility, pregnancy, embryonal/fetal development, parturition or post-natal development (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
The safety of BOOSTRIX when administered to breast-feeding women has not been evaluated.
It is unknown whether BOOSTRIX is excreted in human breast milk.
BOOSTRIX should only be used during breast-feeding when the possible advantages outweigh the potential risks.
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
A total of 1,243 vaccinees have received a dose of BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) in clinical studies of which 1,032 were over 10 years of age.
During controlled clinical studies, diary cards were used to monitor signs and symptoms in all vaccinees following administration of a dose of BOOSTRIX. Table 3 below summarizes data from two pivotal studies for solicited local and general symptoms reported during a 15 day follow up period after vaccination. Onset of the majority of local and general symptoms occurred within 48 hours of vaccination. All symptoms resolved without sequelae. A causal relationship between these events and vaccination has not necessarily been established.
Table 3 - Summary data from 2 pivotal studies for solicited local and general symptoms reported during a 15 day follow up period vaccination
| Solicited Symptoms | Incidence (%) | |||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
BOOSTRIX administered to adolescent subjects aged 10-17 years | Adolescent comparator group who received separate Td and aP (ap) vaccines | BOOSTRIX administered to adult subjects aged 18 years | Adult comparator group who received separate Td and aP (ap) vaccines | |||||||||||||||||||
BOOSTRIX N=448 | Td N=60 | aP N =59 | BOOSTRIX N =438 | Td* N=54 | aP* N=55 | |||||||||||||||||
| Local reactions | ||||||||||||||||||||||
| Pain (All) | 79.0 | 83.3 | 67.8 | 72.6 | 85.2 | 56.4 | ||||||||||||||||
| (Grade 3) | 3.8 | 10.0 | 8.5 | 0.7 | 0 | 3.65 | ||||||||||||||||
| Redness (All) | 33.0 | 53.3 | 15.3 | 32 | 38.9 | 20.0 | ||||||||||||||||
| (≥ 50 mm) | 5.8 | 16.7 | 0 | 2.5 | 7.4 | 0 | ||||||||||||||||
| Swelling (All) | 35.0 | 46.7 | 15.3 | 20.8 | 29.6 | 10.9 | ||||||||||||||||
| (≥ 50 mm) | 7.8 | 10.0 | 1.7 | 2.5 | 5.6 | 0 | ||||||||||||||||
| General Symptoms | ||||||||||||||||||||||
| Fever (≥ 37.5oC) | 8.9 | 8.3 | 5.1 | 18.5 | 33.3 | 12.7 | ||||||||||||||||
| Fever (≥ 39.1oC) | 0.4 | 0 | 0 | 0.2 | 0 | 0 | ||||||||||||||||
| Malaise | 27.7 | 26.7 | 20.3 | 19.2 | 20.4 | 14.5 | ||||||||||||||||
| Fatigue | 56.2 | 50.0 | 40.7 | 27.2 | 25.9 | 23.6 | ||||||||||||||||
| Vomiting | 4.0 | 5.0 | 3.4 | 3.4 | 3.7 | 5.5 | ||||||||||||||||
| Headache | 51.3 | 51.7 | 35.6 | 37.0 | 44.4 | 47.3 | ||||||||||||||||
| Dizziness | 20.5 | 26.7 | 13.6 | 10.0 | 3.7 | 9.1 | ||||||||||||||||
Td – Tetanus + diphtheria toxoid
aP – acellular pertussis * These data are from the first vaccination of either of these comparator vaccine.
Clinical Studies in Children, Adolescents and Adults
Children from 4 to 9 years of age
The safety profile in Table 4 is based on data from clinical trials where BOOSTRIX was administered to 839 children (from 4 to 9 years of age).
Table 4 Children from 4 to 9 years of age
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Very common: ≥1/10 | injection site reactions (including pain, redness and swelling), fatigue | General and administration site conditions |
| irritability | Psychiatric disorders | |
| somnolence | Nervous system disorders |
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Common: ≥1/100 and <1/10 | fever ≥ 37.5°C (including fever > 39°C) | General and administration site conditions |
| anorexia | Metabolism and nutrition disorders | |
| headache | Nervous system disorders | |
| diarrhoea, vomiting, gastrointestinal disorders | Gastrointestinal disorders |
Adults, adolescents, and children, from the age of 10 years onwards
The safety profile in Table 5 is based on data from clinical trials where BOOSTRIX was administered to 1,931 adults, adolescents and children (above 10 years of age).
Table 5 Adults, adolescents, and children, from the age of 10 years onwards
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Very common: ≥1/10 | injection site reactions (including pain, redness and swelling), fatigue, malaise | General and administration site conditions |
| headache | Nervous system disorders | |
Common: ≥1/100 and <1/10 | fever > 37.5oC, injection site reactions (such as injection site mass and injection site abscess sterile) | General and administration site conditions |
| dizziness | Nervous system disorders | |
| nausea, gastrointestinal disorders | Gastrointestinal disorders |
8.3 Less Common Clinical Trial Adverse Reactions
Children from 4 to 9 years of age
The safety profile in Table 6 is based on data from clinical trials where BOOSTRIX was administered to 839 children (from 4 to 9 years of age).
Table 6 Children from 4 to 9 years of age
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Uncommon: ≥1/1,000 and <1/100 | other injection site reactions (such induration), pain | General and administration site conditions |
| upper respiratory tract infections | Infections and infestations | |
| disturbances in attention | Nervous system disorders | |
| conjunctivitis | Eye disorders |
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
| rash | Skin and subcutaneous tissue disorders |
Adults, adolescents, and children, from the age of 10 years onwards
The safety profile in Table 7 is based on data from clinical trials where BOOSTRIX was administered to 1,931 adults, adolescents and children (above 10 years of age).
Table 7 Adults, adolescents, and children, from the age of 10 years onwards
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Uncommon: ≥1/1,000 and <1/100 | fever > 39°C, influenza like illness, pain | General and administration site conditions |
| upper respiratory tract infections, pharyngitis | Infections and infestations | |
| lymphadenopathy | Blood and lymphatic system disorders | |
| syncope | Nervous system disorders | |
| cough | Respiratory, thoracic and mediastinal disorders | |
| diarrhoea, vomiting | Gastrointestinal disorders | |
| hyperhidrosis, pruritus, rash | Skin and subcutaneous tissue disorders | |
| arthralgia, myalgia, joint stiffness, musculoskeletal stiffness | Musculoskeletal and connective tissue disorders |
8.5 Post-Market Adverse Reactions
Table 8 Post-Market Adverse Reactions
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Rare: ≥1/10,000 and <1/1,000 | extensive swelling of the vaccinated limb, asthenia | General and administration site conditions |
| angioedema | Blood and lymphatic system disorders | |
| convulsions (with or without fever) | Nervous system disorders | |
| urticaria | Skin and subcutaneous tissue disorders |
| Frequency | Adverse Event | System/Organ Class |
|---|---|---|
Very rare: <1/10,000 | allergic reactions, including anaphylactic and anaphylactoid reactions | Immune system disorders |
Data on 146 subjects suggest a small increase in local reactogenicity (pain, redness, swelling) with repeated vaccination according to a 0, 1, 6 months schedule in adults (> 40 years of age).
9 DRUG INTERACTIONS
9.3 Drug-Behavioural Interactions
The vaccine is unlikely to produce an effect on the ability to drive and use machines.
9.4 Drug-Drug Interactions
The drugs listed in this section are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Concomitant use with other inactivated vaccines or with immunoglobulin has not been studied. It is unlikely the coadministration will result in interference with the immune responses. When considered necessary, BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) can be administered simultaneously with other vaccines or immunoglobulin, at a different injection site.
As with other vaccines, individuals receiving immunosuppressive therapy or individuals with immunodeficiency may not achieve an adequate response.
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Diphtheria
Diphtheria is a serious communicable disease, primarily a localized and generalized intoxication caused by diphtheria toxin, an extracellular protein metabolite of toxigenic strains of Corynebacterium diphtheriae. The disease occurs most frequently in unimmunized or partially immunized individuals. The incidence of diphtheria in Canada has decreased from 9,000 cases reported in 1924 to extremely low levels. Only one or two cases have been reported annually in recent years. The case fatality rate remains 5 to 10%, with the highest death rates in the very young and elderly. If immunization levels are allowed to fall and adults do not receive booster doses, disease re-emergence may appear as demonstrated in the Commonwealth of Independent States (former Soviet Union), where tens of thousands of cases with substantial mortality have been reported. Protection against disease is due to the development of neutralizing antibodies to the diphtheria toxin. Following adequate immunization with diphtheria toxoid, it is generally accepted that protection persists for at least 10 years. Serum antitoxin levels of at least 0.01 antitoxin units per mL are generally regarded as protective. This significantly reduces both the risk of developing diphtheria and the severity of clinical illness. Immunization with diphtheria toxoid does not, however, eliminate carriage of C. diphtheriae in the pharynx or nose or on the skin.
Tetanus
Tetanus is an intoxication manifested primarily by neuromuscular dysfunction caused by a potent exotoxin released by Clostridium tetani. Immunization is highly effective, provides long lasting protection and is recommended for the entire population. Only 1 to 7 with an average of 5 cases of tetanus are reported annually in Canada while no deaths have been recorded since 1995. The disease continues to occur almost exclusively among persons who are unvaccinated or inadequately vaccinated or whole vaccination histories are unknown or uncertain.
Spores of C. tetani are ubiquitous. Naturally acquired immunity to tetanus toxin does not occur. Thus, universal primary immunization and timed booster doses to maintain adequate tetanus antitoxin levels are necessary to protect all age groups. Protection against disease is due to the development of neutralizing antibodies to the tetanus toxin. Tetanus toxoid is a highly effective antigen and a completed primary series generally induces serum antitoxin levels of at least 0.01 antitoxin units per mL, a level which has been reported to be protective. It is generally accepted that protection persists for at least 10 years. To maintain immunity to tetanus following completion of primary immunization, booster doses administered as Td are recommended at 10 yearly intervals.
Pertussis
Pertussis (whooping cough) is a disease of the respiratory tract caused by Bordetella pertussis. Pertussis is highly communicable and can affect individuals of any age; however, severity is greatest among young infants.
Although there is no established serologic correlate of protection against pertussis, majority of pregnant women were found to have undetectable anti-pertussis toxin levels. Newborn infants therefore remain susceptible until their first vaccination at two months of age. Immunization in pregnancy provides newborn infants benefits from the transfer of the maternal antibodies.
Antigenic components of B. pertussis believed to contribute to protective immunity include: pertussis toxin; filamentous hemagglutinin; and pertactin (69kDa). Although the role of these antigens in providing protective immunity in humans is not well understood, clinical trials which evaluated candidate acellular DTP vaccines manufactured by GlaxoSmithKline supported the efficacy of three component INFANRIX (DTaP). Recently published data suggests a higher importance of the PT and pertactin (69kDa) components in providing protection against pertussis.
11 STORAGE, STABILITY AND DISPOSAL
BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) must be stored at 2 to
8oC. Do not use beyond the expiry date printed on the label and packaging.
Protect from light.
Stability data indicate that the vaccine is stable at temperatures up to 37°C for 7 days. These data are intended to guide healthcare professionals in case of temporary temperature excursion only.
DO NOT FREEZE; discard if vaccine has been frozen.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine for booster vaccination
Product Characteristics:
BOOSTRIX (combined diphtheria, tetanus, acellular pertussis (adsorbed) vaccine) contains combined diphtheria and tetanus toxoids, and three purified pertussis antigens [pertussis toxoid (PT), filamentous hemagglutinin (FHA) and pertactin (69 kDalton outer membrane protein)], adsorbed onto aluminum salts. The final vaccine is formulated in saline.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Booster vaccination against diphtheria, tetanus and pertussis
A summary of the pivotal and follow-up trials of BOOSTRIX in vaccinees of different ages is presented in Table 9.
Table 9 - Summary of studies (Total cohort)
| Study ID | Trial Design, Study Duration | Study and control vaccines | Number of subjects enrolled | Gender %Male Median Age (range) | |||
|---|---|---|---|---|---|---|---|
| One month after vaccination with BOOSTRIX (see Table 10) | |||||||
| APV-118 | Single blind, randomised | dTpa (BOOSTRIX) DTPa (INFANRIX) Td (TD-PUR) + Pa (PACMERIEUX) / pa (GSK) | 211 107 103 | 47.9% 5 years (4-6) | |||
| dTpa-001 | Single blind, randomised | dTpa (BOOSTRIX) pa (GSK) + Td (LEDERJECT) one month later Td (TD-PUR) + Pa (GSK) one month later | 46 46 46 | 53.6% 13 years (11-17) | |||
| Study ID | Trial Design, Study Duration | Study and control vaccines | Number of subjects enrolled | Gender %Male Median Age (range) | |||||
|---|---|---|---|---|---|---|---|---|---|
| dTpa-002 | Single blind, randomised | dTpa (BOOSTRIX) pa (GSK) + Td (LEDERJECT) one month later Td (LEDERJECT) + pa (GSK) one month later | 440 55 55 | 40.9% 39 years (19-70) | |||||
| dTpa-003 | Blinded, randomised, single centre, phase III | dTpa (BOOSTRIX) pa (GSK) Td (TD-RIX) | 99 100 100 | 49.2% 30 years (18-73) | |||||
| dTpa-004 | Single blind, randomised | dTpa (BOOSTRIX) lot A dTpa (BOOSTRIX) lot B dTpa (BOOSTRIX) lot C Td (LEDERJECT)+ pa (GSK) | 150 150 150 60 | 45.3% 11 years (10-13) | |||||
| Persistence up to 5-6 years after vaccination of children with BOOSTRIX (see Table 10) | |||||||||
| APV-124 | Open | No vaccine administered dTpa (BOOSTRIX) DTPa (INFANRIX) Td (TD-PUR) + Pa (PACMERIEUX) / pa (GSK) | 125 67 56 | 48.1% 5 years (4-6) | |||||
| dTap 0.3-004 | Double-blind, randomized, multicentre, phase III | dTpa (BOOSTRIX) DTPa (INFANRIX) Td (TD-PUR) + Pa (PACMERIEUX) / pa (GSK) Subjects received a dose of dTpa but with a different formulation and so data not shown. | 83 195 42 | 51.1% 11 years (10-12) | |||||
| Persistence up to 10 years after vaccination of adolescents with BOOSTRIX (see Table 11) and second booster dose with BOOSTRIX (see Table 12) | |||||||||
| dTpa-017 | Open | No vaccine administered dTpa (BOOSTRIX) (pooled groups**) Td (LEDERJECT)+ pa (GSK) | 269 30 | 46.6% 14 years (13-15) | |||||
| dTpa-030 | Open | No vaccine administered dTpa (BOOSTRIX) (pooled groups**) Td (LEDERJECT)+ pa (GSK) | 267 36 | 43.3% 16 years (15-17) | |||||
| dTpa-040 | Open, non-randomised, single-centre, phase IV | dTpa (BOOSTRIX) (pooled groups**) Td (LEDERJECT)+ pa (GSK) All subjects received a dose of BOOSTRIX | 75 7 | 12.2% 21.0 years (21-22) | |||||
| Study ID | Trial Design, Study Duration | Study and control vaccines | Number of subjects enrolled | Gender %Male Median Age (range) | ||||
|---|---|---|---|---|---|---|---|---|
| Persistence up to 10 years after vaccination of adults with BOOSTRIX (see Table 11) and second booster dose with BOOSTRIX (see Table 12) | ||||||||
| dTpa-021 | Open | No vaccine administered dTpa (BOOSTRIX) pa (GSK) + Td (LEDERJECT) one month later Td (LEDERJECT) + pa (GSK) one month later | 310 40 37 | 28.7% (age not evaluate d) | ||||
| dTpa-027 | Open | No vaccine administered dTpa (BOOSTRIX) pa (GSK) + Td (LEDERJECT) one month later Td (LEDERJECT) + pa (GSK) one month later | 240 34 30 | 27.6% 46 years (25-74) | ||||
| dTpa-039 | Open, non-randomised, single-centre, phase IV | dTpa (BOOSTRIX) Pooled pa + Td groups *** All subjects received a dose of BOOSTRIX | 164 39 | 31.4% 52.0 years (29-74) | ||||
| Vaccination of subjects ≥ 40 years of age with BOOSTRIX or BOOSTRIX-POLIO | ||||||||
| dTpa-034 | Double blind, randomised, multicentre, phase III | 3 doses dTpa (BOOSTRIX) at month 0, 1 and 6 1 dose dTpa-IPV at month 0 and 2 doses of Td (TEDIVAX) at month 1 and 6 3 doses of Td (TEDIVAX) at month 0, 1 and 6 | 155 152 153 | 41.3% 57.0 years (40-85) | ||||
* 3 consistency lots of dTpa-IPV
** 3 consistency lots of dTpa from study dTpa-004
*** Pooling of subjects from the two groups, group pa (GSK) + Td (LEDERJECT) one month later and group Td (LEDERJECT) + pa (GSK) one month later
In clinical studies APV-118, dTpa-001, dTpa-002, dTpa-003, and dTpa-004, the immune response to the diphtheria, tetanus, and acellular pertussis components was evaluated. The results are presented in Table 10. Approximately one month following booster vaccination with BOOSTRIX, the following seroprotection/seropositivity rates were observed.
Table 10 - Percent Seroprotection / Seropositivity one month following vaccination with BOOSTRIX
| Antigen | Seroprotection / Seropositivity | Adults and adolescents from the age of 10 years onwards, at least 1690 subjects (% vaccinees) | Children from 4 to 9 years of age, at least 415 subjects (% vaccinees) |
|---|---|---|---|
| Diphtheria | ≥ 0.1 IU/ml* | 97.2% | 99.8% |
| Tetanus | ≥ 0.1 IU/ml* | 99.0% | 100.0% |
Pertussis: -Pertussis toxoid -Filamentous haemagglutinin -Pertactin | ≥ 5 EL.U/ml ≥ 5 EL.U/ml ≥ 5 EL.U/ml | 97.8% 99.9% 99.4% | 99.0% 100.0% 99.8% |
*cut-off accepted as indicative of protection
Results of the comparative studies with commercial dT vaccines containing the same antigen content indicates that the degree and duration of protection with BOOSTRIX would not be different from those obtained with these vaccines.
In clinical studies APV-124, dTap 0.3-004, dTpa-017, dTpa-030, dTpa-040, dTpa-021, dTpa-027 and dTpa-039, the persistence of immune response was evaluated. Three to 3.5 years, 5 to 6 years and 10 years following vaccination with BOOSTRIX, the following persistence of responses were observed in Table 11.
Table 11 - Persistence of Responses Observed 3 to 3.5, 5 to 6 and 10 years Following Vaccination with BOOSTRIX
| Antigen | Res-ponse(1) | Adults and adolescents 10 years and older Percentage of vaccinees demonstrating response (CI) | Children 4 years and older(2) Percentage of vaccinees demonstrating response (CI) | ||||
|---|---|---|---|---|---|---|---|
| 3-3.5 years persistence | 5 years persistence | 10 years persistence | 3-3.5 years persistence | 5 to 6 years persistence | |||
| Adult(3) | Adolescent (3) | Adult(3) | Adolescent(3) | Adult(3) | Adolescent (3) | ||
| N = 309 | N = 261 | N = 232 | N = 250 | N = 158 | N = 74 | N = 118 | N = 68 |
| Diph-theria | |||||||
| ≥ 0.1 IU/ml | |||||||
| 71.2% | 91.6% | 84.1% | 86.8% | 64.6% | 82.4% | 97.5 % | 94.2 % |
| (65.8-76.2) | (87.6-94.7) | (78.7-88.5) | (82.0-90.7) | (56.6-72.0) | (71.8-90.3) | (93.0-99.5) | (85.8-98.4) |
| ≥ 0.016 IU/ml(4) | |||||||
| 97.4% | 100% | 94.4% | 99.2% | 89.9% | 98.6% | 100 % | Not |
| (95.6-99.2) | (98.2-100) | (90.6-97.0) | (96.9-99.9) | (84.1-94.1) | (92.7-100) | (97.0-100) | determined |
| Tetanus | |||||||
| ≥ 0.1 IU/ml | |||||||
| 94.8% | 100% | 96.2% | 100% | 95.0% | 97.3% | 98.4 % | 98.5 % |
| (91.8-97.0) | (98.6-100) | (93.0-98.3) | (98.6-100) | (90.4-97.8) | (90.6-99.7) | (94.2-99.8) | (92.1-100) |
| Pertussis | |||||||
| Per-tussis | |||||||
| ≥ 5 EL.U/ml | |||||||
| 90.6% | 81.6% | 89.5% | 76.8% | 85.6% | 61.3% | 58.7% | 51.5% |
| toxoid | |||||||
| (86.8-93.6) | (76.4-86.1) | (84.9-93.1) | (71.1-81.9) | (79.2-90.7) | (49.4-72.4) | (49.4-67.6) | (39.0-63.8) |
| Antigen | Res-ponse(1) | Adults and adolescents 10 years and older Percentage of vaccinees demonstrating response (CI) | Children 4 years and older(2) Percentage of vaccinees demonstrating response (CI) | ||||
|---|---|---|---|---|---|---|---|
| 3-3.5 years persistence | 5 years persistence | 10 years persistence | 3-3.5 years persistence | 5 to 6 years persistence | |||
| Adult(3) | Adolescent (3) | Adult(3) | Adolescent(3) | Adult(3) | Adolescent (3) | ||
| N = 309 | N = 261 | N = 232 | N = 250 | N = 158 | N = 74 | N = 118 | N = 68 |
| Filamen-tous | |||||||
| ≥ 5 EL.U/ml | |||||||
| 100% | 100% | 100% | 100% | 99.4% | 100% | 100% | 100% |
| Haem-agglut-inin | |||||||
| (98.8-100) | (98.6-100) | (98.5-100) | (98.6-100) | (96.6-100) | (95.2-100) | (96.9-100) | (94.8-100) |
| Pert-actin | |||||||
| ≥ 5 EL.U/ml | |||||||
| 94.8% | 99.2% | 95.0% | 98.1% | 95.0% | 96.0% | 99.2% | 100% |
| (91.7-97.0) | (97.3-99.9) | (91.4-97.4) | (95.5-99.4) | (90.3-97.8) | (88.8-99.2) | (95.5-100) | (94.9-100) |
(1)Response: Where, at the specified time point, a concentration of antibodies against diphtheria and tetanus ≥ 0.1 IU/ml was considered as seroprotection and a concentration of antibodies against pertussis ≥ 5EL.U/ml was considered as seropositivity.
(2)This reflects the age at which children were vaccinated with BOOSTRIX
(3)The terms ‘adult’ and ‘adolescent’ reflect the ages at which subjects received their first vaccination with BOOSTRIX.
(4)Percentage of subjects with antibody concentrations associated with protection against disease (≥ 0.1 IU/ml by ELISA assay or ≥ 0.016 IU/ml by an in-vitro Vero-cell neutralisation assay).
N = the minimum number of subjects with available data for each antigen; CI = Confidence Interval (95%)
In clinical studies dTpa-040 and dTpa-039, the immunogenicity of BOOSTRIX, administered 10 years after a previous booster dose with reduced-antigen content diphtheria, tetanus and acellular pertussis vaccine(s) was evaluated. One month post vaccination, > 99 % of subjects were seroprotected against diphtheria and tetanus and seropositive against pertussis (see Table 12).
Table 12 - Immunogenicity of a second booster dose of BOOSTRIX administered 10 years after the first dose in either adolescents or adults
| Antigen | Response(1) | Adolescents(2) | Adults(3) | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Number of subjects (N) | % vaccinees demonstrating response (CI) | Number of subjects (N) | % vaccinees demonstrating response (CI) | |||||||||||
| Diphtheria(4) | ≥ 0.1 IU/mL | 73 | 100% (95.1-100) | 152 | 99.3% (96.4-100) | |||||||||
| Tetanus (5) | ≥ 0.1 IU/mL | 73 | 100% (95.1-100) | 153 | 100% (97.6-100) | |||||||||
| Pertussis | ||||||||||||||
Pertussis toxoid | ≥ 5 EL.U/mL | 73 | 100% (95.1-100) | 152 | 100% (97.6-100) | |||||||||
Filamentous haemagglutinin | ≥ 5 EL.U/mL | 73 | 100% (95.1-100) | 152 | 100% (97.6-100) | |||||||||
| Pertactin | ≥ 5 EL.U/mL | 73 | 100% | 153 | 100% | |||||||||
| (95.1-100) | (97.6-100) |
(1) Response: Where, one month after the second booster dose, a concentration of antibodies against diphtheria and tetanus ≥ 0.1 IU/mL was considered as seroprotection, a concentration of antibodies against pertussis ≥ 5 EL.U/mL was considered as seropositivity.
(2) The term ‘adolescent’ reflects the age at which subjects received their first booster dose (10-13 years) where subjects received a second booster dose 10 years later at 21-22 years of age.
(3) The term ‘adult’ reflects the age at which subjects received their first booster dose (19-70 years) where subjects received a second booster dose 10 years later at 29-74 years of age.
(4) To demonstrate that the second booster dose elicits seroprotective antibody concentrations in at least 80% of subjects against diphtheria, the lower limit of the 95% confidence interval for concentrations ≥ 0.1 IU/ml must be above 80%.
(5) To demonstrate that the second booster dose elicits seroprotective antibody concentrations in at least 90% of subjects against tetanus, the lower limit of the 95% confidence interval for concentrations ≥ 0.1 IU/ml must be above 90%.
N = number of subjects with available results
CI = Confidence Interval (95%)
In clinical study dTpa-034, after administration of one dose of BOOSTRIX to 139 adults ≥ 40 years of age that had not received any diphtheria and tetanus containing vaccine in the past 20 years, at least 98.5% of adults were seropositive for all three pertussis antigens and 81.5% and 93.4% were seroprotected against diphtheria and tetanus respectively. After administration of two additional doses one and six months after the first dose, the seropositivity rate was 100% for all three pertussis antigens and the seroprotection rates for diphtheria and tetanus reached 99.3% and 100% respectively.
Pertussis
One month post vaccination, the overall response rate for each of the three individual pertussis antigens (pertussis toxoid, filamentous hemagglutinin, pertactin) was between 92.1 – 100%, 95.0 – 99.8% and 97.9 – 100%, respectively.
The pertussis antigens contained in BOOSTRIX are an integral part of the pediatric acellular pertussis combination vaccine (INFANRIX), for which efficacy after primary vaccination has been demonstrated in a household contact efficacy study. The antibody titres to all 3 pertussis components following vaccination with BOOSTRIX are higher than those observed during the household contact efficacy trial. Based on these comparisons, BOOSTRIX provides protection against pertussis, however the degree and duration of protection afforded by the vaccine are undetermined.
Protective efficacy of pertussis
There is currently no correlate of protection defined for pertussis; however, the protective efficacy of GlaxoSmithKline DTPa (INFANRIX) vaccine against WHO defined typical pertussis (≥ 21 days of paroxysmal cough with laboratory confirmation) was demonstrated in the following 3 dose primary studies:
A prospective blinded household contact study performed in Germany (3, 4, 5 months schedule). Based on data collected from secondary contacts in households where there was an index case with typical pertussis, the protective efficacy of the vaccine was 88.7%. Protection against laboratory confirmed mild disease, defined as 14 days or more of cough of any type was 73 and 67% when defined as 7 days or more of cough of any type.
An NIH sponsored efficacy study performed in Italy (2, 4, 6 months schedule). The vaccine efficacy was found to be 84%. When the definition of pertussis was expanded to include clinically milder cases with respect to type and duration of cough, the efficacy of INFANRIX was calculated to be 71% against > 7 days of any cough and 73% against > 14 days of any cough. In a follow up of the same cohort, the efficacy was confirmed up to 5 years after completion of primary vaccination without administration of a booster dose of pertussis.
As infants cannot begin their pertussis vaccination course until they are at least 6 weeks old and three doses of vaccine need to be given, vaccination does not confer complete protection until infants have received all 3 doses. Several studies have shown that adults are a significant source of pertussis in the first week of life. It could be expected that immunization of immediate close contacts of newborn infants, such as parents, grandparents and healthcare workers, would reduce exposure of pertussis to infants not yet adequately protected through immunization. Booster immunization with BOOSTRIX, an acellular pertussis vaccine with reduced antigen content of diphtheria toxoids and pertussis, has demonstrated that the vaccine was immunogenic and well tolerated in clinical studies in which adolescents and adults have received BOOSTRIX.
Passive protection against pertussis in infants (less than 3 months of age) born to mothers vaccinated during pregnancy
In a randomized, cross-over, placebo-controlled study (DTPA-047), higher pertussis antibody concentrations were demonstrated at delivery in the cord blood of infants born to mothers vaccinated with BOOSTRIX (N=291) versus placebo (N=292) after 27 weeks of pregnancy. The concentrations of antibodies against the pertussis antigens PT, FHA and PRN were respectively 8, 16 and 21 times higher in the cord blood of infants born to vaccinated mothers versus controls.
Immunogenicity in infants and toddlers born to mothers vaccinated during pregnancy
In two follow-up studies (DTPA-048, -049), more than 500 infants and toddlers. born to mothers vaccinated with BOOSTRIX or placebo after 27 weeks of pregnancy, received primary and booster vaccination of INFANRIX hexa and Prevnar* 13..Antibody response to diphtheria, tetanus, hepatitis B, inactivated polio virus, Haemophilus influenzae type b or pneumococcal antigens were comparable between infants/toddlers born to vaccinated mothers and infants/toddlers born to unvaccinated mothers. Lower concentrations of antibodies against all pertussis antigens (PT, FHA and PRN) were observed post primary vaccination and against PT and FHA antigens post booster vaccination in infants/toddlers born to vaccinated mothers compared to infants/toddlers born to unvaccinated mothers. However, 92.1% to 98.1% of infants and toddlers born to vaccinated mothers showed a booster response (post-booster antibody concentration ≥2 times the pre-booster antibody concentration) against these pertussis antigens.
*Trademark owned by Wyeth LLC
Effectiveness in the protection against pertussis disease in infants born to women vaccinated during pregnancy:
BOOSTRIX or BOOSTRIX-POLIO vaccine effectiveness (VE) was evaluated in three published observational studies, in UK, Spain and Australia (Amirthalingam G et al, 2016 Clin Infect Dis. 63(suppl_4):S236-S243; Bellido-Blasco J et al, 2017 Euro Surveill. 22(22); Saul N et al, 2018 Vaccine 36(14):1887-1892). The vaccine was used during the third trimester of pregnancy for passive protection of infants below 3 months of age against pertussis disease.
Across the three studies, VE against pertussis disease for infants below 3 months of age born to mothers vaccinated during the third trimester of pregnancy with BOOSTRIX or BOOSTRIX-POLIO ranged between 69% to 90.9%.
If maternal vaccination occurs within two weeks before delivery, VE in the infant may be lower than these figures.
16 NON-CLINICAL TOXICOLOGY
Nonclinical data obtained with BOOSTRIX reveal no specific hazard for humans based on conventional studies of female fertility and embryo-fetal development in rats and rabbits, and also parturition and postnatal toxicity in rats (up to the end of the lactation period).