


Product Monograph - Carboplatin Injection (Auro Pharma)
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions, Neurologic | 07/2022 |
| 8 Adverse Reactions, 8.5 Post-Market Adverse Reactions | 07/2022 |
| 7 Warnings and Precautions, Cardiovascular | 02/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ........................................................................................................................ 4
1.1 Pediatrics ............................................................................................................................. 4
1.2 Geriatrics ............................................................................................................................. 4
2 CONTRAINDICATIONS ........................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ...................................................................... 4
4 DOSAGE AND ADMINISTRATION ........................................................................................... 5
4.1 Dosing Considerations .......................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................... 5
4.3 Reconstitution ...................................................................................................................... 6
4.4 Administration ...................................................................................................................... 6
4.5 Missed Dose .......................................................................................................................... 6
5 OVERDOSAGE ....................................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................................... 6
7 WARNINGS AND PRECAUTIONS ............................................................................................ 7
7.1 Special Populations ............................................................................................................ 11
7.1.1 Pregnant Women............................................................................................................ 11
7.1.2 Breast-feeding ................................................................................................................ 11
7.1.3 Pediatrics ........................................................................................................................ 11
7.1.4 Geriatrics ........................................................................................................................ 11
8 ADVERSE REACTIONS .......................................................................................................... 11
8.1 Adverse Reaction Overview ............................................................................................... 11
8.5 Post-Market Adverse Reactions ......................................................................................... 13
9 DRUG INTERACTIONS .......................................................................................................... 13
9.4 Drug-Drug Interactions ...................................................................................................... 13
9.5 Drug-Food Interactions ...................................................................................................... 14
9.6 Drug-Herb Interactions ...................................................................................................... 14
9.7 Drug-Laboratory Test Interactions ..................................................................................... 14
10 CLINICAL PHARMACOLOGY ............................................................................................... 14
10.1 Mechanism of Action ....................................................................................................... 14
10.3 Pharmacokinetics ............................................................................................................ 14
11 STORAGE, STABILITY AND DISPOSAL ................................................................................. 15
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................... 15
PART II: SCIENTIFIC INFORMATION ........................................................................................ 17
13 PHARMACEUTICAL INFORMATION .................................................................................... 17
14 CLINICAL TRIALS ................................................................................................................ 17
15 MICROBIOLOGY ................................................................................................................ 17
16 NON-CLINICAL TOXICOLOGY.............................................................................................. 17
17 SUPPORTING PRODUCT MONGORAPHS............................................................................ 19
PATIENT MEDICATION INFORMATION ................................................................................... 20
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Carboplatin Injection is indicated for the treatment of ovarian cancer of epithelial origin in first line therapy, and in second line therapy after other treatments have failed.
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics: Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
- Severe myelosuppression.
- Pre-existing severe renal impairment. Dosage adjustment may allow use in the presence of mild renal impairment (see 4 DOSAGE AND ADMINISTRATION).
- History of severe allergic reactions to carboplatin, other platinum-containing compounds, or to any ingredients in the formulation, including any non-medicinal ingredients, or component of the container (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING). Patients allergic to mannitol may be given Carboplatin Injection.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- Carboplatin Injection is a highly toxic drug with a narrow therapeutic index and a therapeutic effect is unlikely to occur without some evidence of toxicity.
- Serious and fatal infections following administration of live or live-attenuated vaccines in patients treated with carboplatin (see 7 WARNINGS AND PRECAUTIONS)
- Hypersensitivity reactions, sometimes fatal, have been reported and may occur within minutes of Carboplatin Injection administration (see 8 ADVERSE REACTIONS)
- Bone marrow suppression is dose related and may be severe, resulting in infection and/or bleeding. Anemia may be cumulative and may require transfusion support. Vomiting is another frequent drug-related side effect (see 7 WARNINGS AND PRECAUTIONS).
- Fatal veno-occlusive disease (see 7 WARNINGS AND PRECAUTIONS)
- Fatal hemolytic anemia (see 7 WARNINGS AND PRECAUTIONS)
- Fatal hemolytic-uremic syndrome (see 7 WARNINGS AND PRECAUTIONS)
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Carboplatin Injection should only be administered to patients under the supervision of a qualified physician who is experienced in the use of chemotherapeutic agents.
- Dosage reduction or discontinuation may be necessary in the case of severe alteration of renal function tests.
- Patients presenting with impaired renal function requires adequate dosage adjustments and frequent monitoring of both hematological nadirs and renal function.
- Peripheral blood counts and renal function should be monitored closely.
- Audiograms should be performed prior to initiating therapy and during treatment or when auditory symptoms occur.
4.2 Recommended Dose and Dosage Adjustment
Adult Dosage
The recommended dose of carboplatin in previously untreated adults with normal renal function is 400 mg/m2 given as a single intravenous infusion over 15 to 60 minutes. Therapy should not be repeated until four weeks after the previous carboplatin course.
Initial dosage should be reduced 20 to 25% in patients with risk factors such as previous myelosuppressive therapy and poor performance status. Initial and subsequent dose reduction may be required in elderly patients, depending upon their physical status.
Determination of hematologic nadir by weekly blood counts during initial courses is recommended for future dosage adjustment and scheduling of carboplatin.
Dosage in Patients with Impaired Renal Function
Hematological nadir and renal function should be closely monitored.
A suggested dosage schedule based on creatinine clearance is:
| CREATININE CLEARANCE | DOSE OF CARBOPLATIN |
|---|---|
> 40 mL/min. 20 - 39 mL/min. 0 - 19 mL/min. | 400 mg/m2 250 mg/m2 150 mg/m2 |
Pediatric dosage
Specific dosage recommendations cannot be made due to insufficient use in pediatrics (<18 years of age); therefore, Health Canada has not authorized an indication for pediatric use.
4.3 Reconstitution
Parenteral Products:
Dilution for Intravenous Infusion
Vials of Carboplatin Injection may be further diluted with 5% dextrose injection or 0.9% sodium chloride injection to give solutions containing approximately 0.3, 0.5 and 2.0 mg/mL carboplatin.
Diluted solutions of Carboplatin Injection are stable for 24 hours in glass or plastic containers, in light and dark storage conditions. Discard unused portion after 24 hours.
Dilutions prepared as directed with 5% dextrose injection or 0.9% sodium chloride injection are stable for 48 hours under refrigeration from the time of initial dilution, after which time the unused portion should be discarded.
4.4 Administration
- Carboplatin Injection should be prepared for administration by professionals who have been trained in the safe use of cytotoxic drugs.
- The personnel carrying out these procedures should be adequately protected with clothing, gloves, masks and eye protection.
4.5 Missed Dose
For a missed dose of Carboplatin Injection, the physician will decide when the patient should receive the next one.
5 OVERDOSAGE
No cases of overdosage of carboplatin are known. Should it occur, the patient may need to be sustained through complications relating to myelosuppression, renal and hepatic impairment. Death may follow.
Signs and symptoms of overdosage should be managed with supportive measures including hemodialysis. From reports in which doses up to 1600 mg/m2 were used, patients were said to feel extremely unwell and developed diarrhea and alopecia. Use of higher than recommended doses of carboplatin has been associated with loss of vision, especially in patients with impaired renal function (see 8 ADVERSE REACTIONS).
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous Infusion | Solution 10 mg/mL carboplatin | Mannitol and Sterile water for injection. Contains no preservatives. |
Carboplatin Injection, 10 mg / mL is supplied as a sterile aqueous solution for intravenous use, available in clear glass vials of 5 mL, 15 mL, 45 mL and 60 mL, each wrapped in a clear shrink sleeve. Each single-use vial is individually packaged in a carton. Carboplatin Injection is preservative-free and the vial stopper is not made with natural rubber latex.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Carboplatin Injection should only be administered to patients under the supervision of a qualified physician who is experienced in the use of chemotherapeutic agents. Diagnostic and treatment facilities should be readily available for appropriate management of therapy and possible complications.
Blood counts as well as renal and hepatic function tests must be done regularly. Discontinue the drug if abnormal depression of bone marrow or abnormal renal or hepatic function is seen.
Carcinogenesis and Mutagenesis
Acute promyelocytic leukaemia (APL) and myelodysplastic syndrome (MDS)/acute myeloid leukemia (AML) have been reported years after therapy with carboplatin and other antineoplastic treatments.
Carboplatin is mutagenic in in vitro tests (see 16 NON-CLINICAL TOXICOLOGY).
Cardiovascular
There have been reports of hypersensitivity reactions which progressed to Kounis syndrome (defined as acute allergic mediated coronary arteriospasm, including stent thrombosis, both of which can result in myocardial infarction, see 8.1 Adverse Reaction Overview - Cardiac Disorders). The clinical manifestations of this syndrome are associated with subclinical, clinical, acute or chronic allergic reactions accompanied by cardiac symptomatology. Kounis syndrome can develop in patients with and without cardiac risk factors and may be presented with a combination of cardiac and/or allergic symptoms (such as cutaneous rash, urticaria, asthma, etc.) and should be promptly investigated and appropriate treatment should be initiated.
Ear/Nose/Throat
Carboplatin may produce cumulative ototoxicity. Audiograms should be performed prior to initiating therapy and during treatment or when auditory symptoms occur. Clinically important deterioration of auditive function may require dosage modifications or discontinuation of therapy. The risk of ototoxicity may be increased by concomitant administration of other ototoxic drugs (e.g., aminoglycosides and cisplatin).
Delayed onset hearing loss has been reported in pediatric patients. Ototoxicity may be more pronounced in younger children. Long-term audiometric follow-up in the pediatric population is recommended.
Endocrine and Metabolism
Patients at high risk of Tumour Lysis Syndrome (TLS) such as patients with high proliferative rate, high tumor burden and high sensitivity to cytotoxic agents should be monitored closely and appropriate precaution taken.
Gastrointestinal
Carboplatin induces emesis. The incidence and severity of emesis may be reduced by pretreatment with antiemetics.
Hematologic
Myelosuppression as a result of carboplatin treatment is closely related to the renal clearance of the drug. Therefore, in patients who have abnormal renal function or who are receiving concomitant therapy with nephrotoxic drugs, myelosuppression especially thrombocytopenia, may be more severe and prolonged. Treatment of severe hematologic toxicity may consist of supportive care, anti-infective agents for complicating infections, transfusions of blood products, autologous bone marrow rescue, peripheral stem cell transplantation and hematopoietic agents (colony-stimulating factors).
Hemolytic anemia, with the presence of serologic, drug-induced antibodies, has been reported in patients treated with carboplatin. This event can be fatal. In case of unexplained hemolysis the specialized serologic testing and treatment discontinuation should be considered.
The occurrence, severity and protraction of toxicity are likely to be greater in patients who have received extensive prior treatment for their disease, have poor performance status and who are more than 65 years of age.
Hepatic/Biliary/Pancreatic
Cases of veno-occlusive disease, including hepatic veno-occlusive disease (sinusoidal obstructive syndrome) have been reported. Some of them were fatal. Patients should be monitored for signs and symptoms of vascular occlusion and thromboembolism.
Immune
Patients with a history of allergic reaction to platinum compounds should be monitored for allergic symptoms. In case of an anaphylactic-like reaction to carboplatin, the infusion should be immediately discontinued and appropriate symptomatic treatment initiated.
Administration of live or live-attenuated vaccines in patients immunocompromised by chemotherapeutic agents including carboplatin, may result in serious or fatal infections. Vaccination with a live vaccine should be avoided in patients receiving carboplatin. Killed or inactivated vaccines may be administered; however, the response to such vaccines may be diminished.
Monitoring and Laboratory Tests
Renal function parameters should be assessed prior to, during and after therapy. Peripheral blood counts (including platelets, white blood cells and hemoglobin) should be followed during and after therapy. Combination therapy with other myelosuppressive drugs may require modification of dosage and/or frequency of administration in order to minimize additive effects. Supportive transfusional therapy may be required in patients who suffer severe myelosuppression.
Carboplatin courses should not be repeated more frequently than monthly in most circumstances, in order to ensure that the nadir in blood counts has occurred and that there has been recovery to a satisfactory level.
Peripheral blood counts and renal function should be monitored closely. Blood counts should be performed prior to commencement of carboplatin therapy and weekly to assess hematologic nadir for subsequent dose adjustments. Lowest levels in white cells and platelets are seen between days 14 and 28, and days 14 and 21 respectively after initial therapy. A greater reduction in platelets is seen in patients who have received extensive myelosuppressive chemotherapy than in untreated patients. White blood cell counts less than 2000 cells/mm3 or platelets less than 50 000 cells/mm3 may necessitate postponement of carboplatin therapy until bone marrow recovery is evident, usually within 5 to 6 weeks.
Audiograms should be performed prior to initiating therapy and during treatment or when auditory symptoms occur.
Patients should be monitored for signs and symptoms of vascular occlusion and thromboembolism.
Neurologic
Cases of encephalopathy have been reported in patients who have received extensive prior treatment for their disease. Patients should be observed for altered mental state and other neurological signs and symptoms.
Post-market cases of posterior reversible encephalopathy syndrome (PRES, also known as RPLS, reversible posterior leukoencephalopathy syndrome) have been reported in patients receiving carboplatin in combination chemotherapy. Signs and symptoms of PRES could be headache, altered mental functioning, seizures, abnormal vision from blurriness to blindness, hypertension (see 8.5 Post- Market Adverse Reactions). Diagnosis of PRES is based upon confirmation by brain imaging.
Neurotoxicity, such as parasthesias and decreased deep tendon reflexes, and ototoxicity are more likely to be seen in patients who have received cisplatin previously. Routine neurologic examination is advisable during carboplatin therapy, particularly in patients previously treated with cisplatin and in patients over 65 years of age.
Renal
Hemolytic-uremic syndrome (HUS) is a potentially life-threatening side effect. Carboplatin should be discontinued at the first sign of any evidence of microangiopathic hemolytic anaemia, such as rapidly falling haemoglobin with concomitant thrombocytopenia, elevation of serum bilirubin, serum creatinine, blood urea nitrogen, or lactate dehydrogenase (LDH). Renal failure may not be reversible with discontinuation of therapy and dialysis may be required.
Dosage reduction or discontinuation may be necessary in the case of severe alteration of renal function tests. Renal toxicity is not usually dose-limiting. Pre-treatment and post-treatment hydration is not necessary. However, about 25% of patients show decreases in creatinine clearance below 60 mL/min. and, less frequently, rises in serum creatinine and blood urea nitrogen may be seen in patients who have previously experienced nephrotoxicity as a result of cisplatin therapy.
The optimal use of carboplatin in patients presenting with impaired renal function requires adequate dosage adjustments and frequent monitoring of both hematological nadirs and renal function.
Reproductive Health: Female and Male Potential
Women of childbearing potential should be advised to avoid becoming pregnant while receiving carboplatin and to use effective contraception during treatment with carboplatin and for at least 7 months after the last dose (see 7.1.1 Pregnant Women).
Men with female partners of childbearing potential should be advised to use effective contraception during treatment with carboplatin and for at least 4 months after the last dose.
- Fertility
Gonadal suppression resulting in amenorrhea or azoospermia may occur in patients receiving antineoplastic therapy. These effects appear to be related to dose and length of therapy and may be irreversible. Prediction of the degree of testicular or ovarian functional impairment is complicated by the common use of combinations of several antineoplastics, which makes it difficult to assess the effects of individual agents.
Male and female fertility may be impacted by treatment with carboplatin (see 16 NON-CLINICAL TOXICOLOGY). Both men and women should seek advice for fertility preservation before treatment with carboplatin.
7.1 Special Populations
7.1.1 Pregnant Women
Carboplatin produces embryotoxicity and teratogenicity in rats. Safe use of carboplatin in human pregnancy has not been established and its use in pregnancy is not recommended.
If the drug is administered during pregnancy or if the patient becomes pregnant while receiving carboplatin, the patient should be informed of the potential hazard to the fetus. Women of childbearing potential are advised to avoid becoming pregnant while on carboplatin therapy.
7.1.2 Breast-feeding
Carboplatin and its active metabolites have been identified in human milk of treated mothers. Because of the potential for serious adverse reactions in infants, breast-feeding should be discontinued during therapy and for 1 month following last dose of treatment or treatment should be discontinued, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Sufficient use of carboplatin in pediatrics (<18 years of age) has not occurred to allow specific dosage recommendations to be made; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
For patients aged 65 and over, dosage adjustment, initially or subsequently, may be necessary, depending on the patient's physical status.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Myelosuppression is the dose-limiting toxicity of carboplatin injection. It is usually reversible and is not cumulative when carboplatin is used as a single agent and at the recommended dosage regimens. Adverse reactions which have been observed include:
Allergic reactions and immune system disorders: In less than 2% of patients, reactions similar to those seen after cisplatin have been observed: erythematous rash, fever, pruritus, hypotension and bronchospasm. However, no cross-reactivity between cisplatin and carboplatin was observed. Hypersensitivity reactions, sometimes fatal, may occur within a few minutes after intravenous administration of carboplatin.
Cardiac disorders: Isolated cases of cardiovascular incidents (cardiac insufficiency, embolism) as well as isolated cases of cerebrovascular accidents have been reported and were fatal in less than 1% of patients. Kounis syndrome has also been reported.
Gastrointestinal system: Nausea and vomiting 53%, nausea only 25%, diarrhea 6%, constipation 3%. Nausea and vomiting usually occur 6 to 12 hours after administration of carboplatin and disappear within 24 hours. It is readily controlled (or may be prevented) by antiemetic medication. Other gastrointestinal effects, such as abdominal pain (sometimes fatal) and stomatitis have been reported.
General disorders and administration site conditions: Alopecia 2%, influenza-like syndrome 1%, reaction at injection site < 1%. Mucosal inflammation has been reported. Asthenia has also been reported, sometimes fatal.
Hematologic system: Leucopenia 55%, thrombocytopenia 32%, anemia 59%, bleeding 6%. Hemolytic anemia (sometimes fatal), with the presence of serologic, drug-induced antibodies, has been reported in patients treated with carboplatin (see 7 WARNINGS AND PRECAUTIONS). Transfusional support has been required in about one-fifth of patients. Neutropenia has also been reported, sometimes fatal. Hemolytic uremic syndrome (HUS) has also been reported.
Hepatic system: Increases in alkaline phosphatase 36%, SGOT 15%, SGPT 16%, total bilirubin 4%. Increases in liver enzymes have been transient in the majority of cases.
Musculoskeletal and connective tissue disorders: Myalgia/arthralgia has been reported, sometimes fatal.
Neoplasms benign, malignant and unspecified: There have been rare reports of acute myelogenous leukemias and myelodysplastic syndromes, sometimes fatal, arising in patients who have been treated with carboplatin, mostly when given in combination with other potentially leukemogenic agents.
Neurological system: Peripheral neuropathy 6%, dysgeusia <1%. Paresthesias present prior to treatment, especially if caused by cisplatin, may persist or worsen during carboplatin therapy (see 7 WARNINGS AND PRECAUTIONS). Encephalopathy has also been reported (see 7 WARNINGS AND PRECAUTIONS).
Renal and urinary disorders: Decrease in creatinine clearance 25%, increases in uric acid 25%, blood urea nitrogen 16% and serum creatinine 7%.
Serum electrolytes: Decreases in serum magnesium 37%, potassium 16% and calcium 5%. These changes have not caused clinical symptoms. Hyponatremia has also been reported, sometimes fatal.
Skin and subcutaneous tissue disorders: Exfoliative dermatitis may rarely occur. Urticaria has also been reported, sometimes fatal, in association with carboplatin. Stevens-Johnson Syndrome (SJS), toxic epidermal necrolysis (TEN), and erythema multiforme (EM) have also been reported.
Special Senses: Subclinical decrease in hearing acuity as determined by audiogram in the high frequency (4000 to 8000 Hz) range 15%, clinical ototoxicity usually manifested as tinnitus 1%. In patients who developed hearing loss as a result of cisplatin therapy, the impairment may persist or worsen. Visual abnormalities, such as transient sight loss (which can be complete for light and colors) or other disturbances may occur in patients treated with carboplatin. Improvement and/or total recovery of vision usually occurs within weeks after the drug is discontinued. Cortical blindness has been reported in patients with impaired renal function receiving high-dose carboplatin.
Vascular: Cases of veno-occlusive disease, including hepatic veno-occlusive disease have been reported. Some of them were fatal (see 7 WARNINGS AND PRECAUTIONS).
8.5 Post-Market Adverse Reactions
Post-market cases of posterior reversible encephalopathy syndrome (PRES, also known as RPLS, reversible posterior leukoencephalopathy syndrome) have been reported infrequently in patients receiving carboplatin in combination chemotherapy (see 7 WARNINGS AND PRECAUTIONS).
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
Concomitant administration of carboplatin and aminoglycosides results in an increased risk of nephrotoxicity and/or ototoxicity, and the drugs should be used concurrently with caution. The use of other nephrotoxic drugs results in a potentiation of renal effects by carboplatin.
Combination therapy with other myelosuppressive drugs may necessitate changes in the dose or frequency of administration of carboplatin in order to minimize additive myelosuppressive effects.
A decrease in phenytoin serum levels has been observed with concurrent administration of carboplatin and phenytoin/fosphenytoin. This may lead to exacerbation of seizures.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Carboplatin is a synthetic analogue of cisplatin. Like cisplatin, carboplatin interferes with DNA intrastrand and interstrand crosslinks in cells exposed to the drug. DNA reactivity has been correlated with cytotoxicity.
In vitro, carboplatin has demonstrated slight cytotoxic activity against C26 colorectal, M109 lung, RCA colorectal and to a lesser degree against B16-F10 melanoma, Moser colorectal and KB nasopharyngeal cell lines. When carboplatin was tested against human and hamster pancreatic adenocarcinoma cell lines, it was found to be active against COLO 357, WD Pa Ca and PD Pa Ca. It was also active against Novikoff hepatoma cells. Carboplatin has shown activity, upon prolonged exposure, against a cisplatin- sensitive human ovarian cancer cell line (NCI-H2780).
No clinical trial data on which the original indication was authorized, however, In vivo, carboplatin demonstrated antitumour activity against the following tumours: B16 melanoma, C26 colon carcinoma, C38 colon carcinoma, M5076 reticulum cell sarcoma, Lewis lung carcinoma, L1210/CDDP, P388 murine leukemia, P388 murine leukemia/CDDP, ADJ/PC6A plasmacytoma, Yoshida ascites sarcoma, CD8F, mammary and Xeno mammary MX1.
10.3 Pharmacokinetics
Following administration of carboplatin in man, linear relationships exist between dose and plasma concentrations of total and free ultrafilterable platinum.
The area under the plasma concentration versus time curve for total platinum also shows a linear relationship with the dose.
Repeated dosing during four consecutive days did not produce an accumulation of platinum in plasma.
Distribution:
Carboplatin is not bound to plasma proteins. However, 87% of the platinum from carboplatin becomes irreversibly bound to plasma proteins within 24 hours following administration.
Elimination
Carboplatin is excreted primarily in the urine with recovery of approximately 70% of the administered platinum within 24 hours. Following administration of carboplatin, half-lives of free ultrafilterable platinum and carboplatin in man were approximately 6 hours and 1.5 hours, respectively. Plasma bound platinum from carboplatin is slowly eliminated with a minimum half-life of 5 days.
Excretion of carboplatin is by glomerular filtration. Patients with poor renal function have a higher area under curve (AUC) for total platinum and a reduction in dosage is recommended (see 4 DOSAGE AND ADMINISTRATION).
11 STORAGE, STABILITY AND DISPOSAL
Carboplatin Injection should be stored between 15 and 25°C, protected from light and freezing.
The product is available in a clear glass vial that is packaged in a clear shrink sleeve to protect from breakage. It is recommended that the vial remains in the carton until time of use.
The Carboplatin Injection vial should be inspected for damage and visible signs of leaks before use. If there are signs of breakage or leakage from the vial, do not use. Incinerate the unopened package.
Parenteral drug products should be inspected visually for clarity, particulate matter, precipitation, and discolouration prior to administration, whenever possible. Vials with visible particulate matter should not be used.
12 SPECIAL HANDLING INSTRUCTIONS
Carboplatin Injection should be prepared for administration by professionals who have been trained in the safe use of cytotoxic drugs.
Needles, syringes, catheters or intravenous administration sets that contain aluminum parts which may come in contact with carboplatin should not be used for preparation or administration of Carboplatin Injection. Carboplatin may interact with aluminum to form a black precipitate.
The personnel carrying out these procedures should be adequately protected with clothing, gloves, masks and eye protection.
Personnel regularly involved in the preparation and handling of carboplatin should have bi-annual blood examinations.
In the event of contact with the skin or eyes, the affected area should be washed with copious amounts of water or normal saline.
A bland cream may be used to treat the transient stinging of skin. Medical advice should be sought if the eyes are affected.
In the event of spillage, personnel wearing protective clothing should sponge up the spilled material. The area should be rinsed twice with water, and all solutions, and contaminated clothing and sponges put into a plastic bag and sealed. The bag should be disposed of as below.
Syringes, containers, absorbent materials, solution and any other material which has come into contact with carboplatin should be placed in a thick plastic bag or other impervious container and incinerated at 1000°C. Tightly sealed containers may explode.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Carboplatin |
|---|---|
| Chemical name: |
|
| Molecular formula and molecular mass: | C6H12N2O4Pt and 371.27 g/mol. |
| Structural formula: | 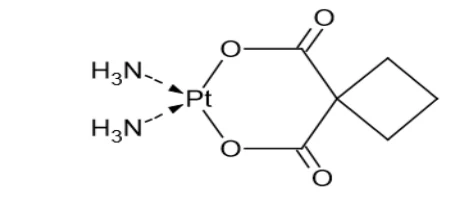 |
| Physicochemical properties: | Colorless microcrystalline solid. Sparingly soluble in water, very slightly soluble in acetone and in alcohol (96%). The pH of a 1.0% w/v solution of carboplatin in water is 5.5 to 7.5. |
14 CLINICAL TRIALS
The clinical trial data on which the original indication was authorized is not available.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute and Subacute Toxicity
The LD10, LD50 and LD90 were determined in rodents (Table 1).
Table 1. Toxicity of Carboplatin in Rats and Mice
| Lethality | Mice, CDF1 (M&F) | Rats, F344 (M) | Rats, Sprague- Dawley (M&F) | ||||
| Single Dose | 5 Daily Doses | Single Dose | Single Dose | ||||
| mg/kg | (mg/m2) | mg/kg | (mg/m2/da y) | mg/kg | (mg/m2) | mg/kg | (mg/m2) | |
LD10 LD50 LD90 | 122.9 149.5 181.7 | (369) (448) (545) | 37.7 46.3 56.9 | (113) (139) (171) | 52.5 60.9 70.9 | (313) (365) (425) | 83.6 102.0 124.8 | (502) (613) (749) |
The toxicity studies in mice showed carboplatin to have a narrow margin of safety, as is common with many cancer therapeutic agents. Carboplatin exerted its toxic effect mainly on the rapidly dividing, quickly turned over cells in the immune, digestive, hematopoietic, and reproductive systems (in order of frequency). Mucous membrane necrosis of the colon correlated with clinical signs of gastrointestinal distress, which included anorexia, adipsia, loss of body weight, and bloody diarrhea. Hematopoietic hyperplasia of the bone marrow was reflected in the hematological changes of decreased reticulocyte and possibly lymphocyte counts. At doses up to 200 mg/kg/day intravenously as a single dose and as five consecutive daily doses, the clinical signs observed were reversible, as were most of the hematologic changes and pathologic lesions at the end of 29 (single-dose study) and 33 days (five daily dose study).
Single doses of carboplatin to rats within the intravenous dose range of 40 to 80 mg/kg increased BUN values slightly on day 10, but, unlike cisplatin, produced no other indications of renal toxicity. The drug produced reductions in hematocrit and WBC counts with pronounced anemia, dose-related neutropenia and marked elevations of myeloid:erythroid (M:E) ratio. Unlike cisplatin, carboplatin produced no gastrointestinal toxicity or destruction of lymphocytes.
The lowest single intravenous dose of carboplatin causing emesis in dogs was 624 mg/m2 (31.2 mg/kg). Both the leukocyte and platelet counts were constantly decreased in dogs given carboplatin at doses equivalent to one-half the lowest emetic dose. These hematologic changes were corroborated by the mild to marked hypocellularity of the bone marrows taken from these dogs. Carboplatin caused renal lesions at doses equivalent to 75% of its lowest emetic dose. Female dogs showed a mild decrease in hematocrit, hemoglobin and erythrocytes, an apparently sex-linked response.
Dogs given five daily intravenous doses up to 12.0 mg/kg/day of carboplatin showed emesis, anorexia and diarrhea or loose feces, and leucopenia at 1.5 mg/kg/day. At 3.0 mg/kg/day, reticulopenia, thrombocytopenia, and mild decreases in hematocrit, hemoglobin and erythrocytes were also observed. At 6.0 and 12 mg/kg/day, additional diarrhea, blood, bile or mucous in the feces, anorexia and loss of body weight, moderate periportal hepatocellular vacuolization and mild to moderate renal tubular necrosis occurred. Gastrointestinal lesions included degeneration of crypt epithelial cells, lymphoid depletion of Payer's patches and to lesser extent ulceration and mucosal erosion. Bone marrow hypocellularity and elevated M:E ratios were observed. Centrilobular congestion, marked ovarian atrophy, and significant increases in BUN and SGPT were seen in females.
17 SUPPORTING PRODUCT MONGORAPHS
1 PrCARBOPLATIN INJECTION BP (Carboplatin Injection), Sterile solution, 10 mg / mL, (50 mg, 150 mg, 450 mg, 600 mg of carboplatin per vial), Submission Control Number: 274117, Product Monograph, Pfizer Canada ULC. (AUG 23, 2023).