


Product Monograph - Cefazolin in Dextrose Injection, USP
Recent Major Label Changes
None at time of the most recent authorization
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................................ 2
Table of Contents ................................................................................................................................. 2
Part 1: Healthcare Professional Information ......................................................................................... 4
- 1.
Indications ................................................................................................................................... 4
1.1. Pediatrics ................................................................................................................................. 4
1.2. Geriatrics ................................................................................................................................. 5
- 2. Contraindications ......................................................................................................................... 5
- 4.
Dosage and Administration .......................................................................................................... 5
4.1. Dosing Considerations ............................................................................................................. 5
4.2. Recommended Dose and Dosage Adjustment........................................................................ 5
4.4. Administration ......................................................................................................................... 7
- 5. Overdosage .................................................................................................................................. 8
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................................. 8
- 7.
Warnings and Precautions ............................................................................................................ 8
General ................................................................................................................................................. 8
Gastrointestinal .................................................................................................................................... 9
Immune ................................................................................................................................................. 9
Monitoring and Laboratory Tests ......................................................................................................... 9
Overgrowth of Non-Susceptible Organisms ......................................................................................... 9
Renal ..................................................................................................................................................... 9
Sensitivity/Resistance ......................................................................................................................... 10
Skin ...................................................................................................................................................... 10
7.1. Special Populations ............................................................................................................... 10
7.1.1. Pregnancy ..................................................................................................................... 10
7.1.2. Breastfeeding ............................................................................................................... 10
7.1.3. Pediatrics ...................................................................................................................... 10
- 8. Adverse Reactions ...................................................................................................................... 10
- 9.
Drug Interactions ........................................................................................................................ 11
9.4. Drug-Drug Interactions .......................................................................................................... 11
9.7. Drug-Laboratory Test Interactions ........................................................................................ 11
- 10.
Clinical Pharmacology ................................................................................................................ 11
10.1. Mechanism of Action ............................................................................................................ 11
10.3. Pharmacokinetics .................................................................................................................. 11
- 11. Storage, Stability and Disposal ................................................................................................... 12
- 12. Special Handling Instructions ...................................................................................................... 12
Part 2: Scientific Information ............................................................................................................. 13
- 13. Pharmaceutical Information ....................................................................................................... 13
- 14. Clinical Trials .............................................................................................................................. 14
- 15. Microbiology .............................................................................................................................. 14
- 16. Non-Clinical Toxicology ............................................................................................................... 15
- 17. Supporting Product Monographs ................................................................................................ 16
Patient Medication Information ......................................................................................................... 17
Part 1: Healthcare Professional Information
1. Indications
CEFAZOLIN IN DEXTROSE INJECTION, USP (cefazolin sodium) is indicated in the treatment of the following infections when caused by susceptible strains of the listed organisms:
Respiratory Tract Infections caused by Streptococcus pneumoniae, Klebsiella pneumoniae, Hemophilus influenzae, Staphylococcus aureus (penicillin-sensitive and penicillin- resistant) and group A beta-haemolytic streptococci.
Urinary Tract Infections caused by Escherichia coli, Proteus mirabilis, Klebsiella pneumoniae and some strains of enterobacter, and enterococci. See note below.
Skin and Soft Tissue Infections caused by Staphylococcus aureus (penicillin- sensitive and penicillin- resistant), group A beta-haemolytic streptococci and other strains of streptococci.
Bone and Joint Infections caused by Staphylococcus aureus.
Septicemia caused by Streptococcus pneumoniae, Staphylococcus aureus (penicillin-sensitive and penicillin resistant), Proteus Mirabilis, Escherichia coli and Klebsiella pneumoniae. See note below.
Endocarditis caused by Staphylococcus aureus (penicillin-sensitive and penicillin-resistant) and group A beta haemolytic streptococci.
Determine susceptibility of the causative organism to cefazolin sodium, by performing appropriate culture and susceptibility studies should be performed. (See 15 Microbiology for disc susceptibility tests and dilution techniques).
Note: Most strains of Enterococci, indole positive Proteus (P. vulgaris), Enterobacter cloacae, Morganella morganii, Providencia rettgeri and methicillin-resistant Staphylococci are resistant. Serratia, Pseudomonas, and Acinetobacter calcoaceticus (formerly Mima and Herellea species) are almost uniformly resistant to cefazolin. (See 15 Microbiology).
Perioperative Prophylaxis: In patients undergoing potentially contaminated surgical procedures, and in patients in whom infection would pose a serious risk (e.g., during open-heart surgery and prosthetic arthroplasty), the preoperative, intraoperative and postoperative administration of CEFAZOLIN IN DEXTROSE INJECTION, USP may reduce the incidence of certain post-operative infections.
Identification of the causative organisms should be made by culture should signs of infection occur, so that appropriate therapy may be instituted.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of CEFAZOLIN IN DEXTROSE INJECTION, USP and other antibacterial drugs, CEFAZOLIN IN DEXTROSE INJECTION, USP should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.1. Pediatrics
Pediatrics (< 1 month): The safety and efficacy of cefazolin sodium in prematures and infants under one month of age has not been established (see 4.2 Recommended Dose and Dosage Adjustment, Pediatric Use).
1.2. Geriatrics
Geriatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2. Contraindications
CEFAZOLIN IN DEXTROSE INJECTION, USP is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container, or to the cephalosporin group of antibiotics. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
4. Dosage and Administration
4.1. Dosing Considerations
CEFAZOLIN IN DEXTROSE INJECTION, USP in GALAXY Container (PL 2040 Plastic) is a premixed solution intended only for intravenous infusion. Administer CEFAZOLIN IN DEXTROSE INJECTION, USP intravenously over approximately 30 minutes.
4.2. Recommended Dose and Dosage Adjustment
Adults:
Adult Dosage Guide
| Type of Infection | Dose | Frequency |
|---|---|---|
Mild infections caused by susceptible Gram-positive cocci | 250 mg to 500 mg | Every 8 hours |
| Moderate to severe infections | 500 mg to 1 g | Every 6 to 8 hours |
Cefazolin sodium has been administered in dosages of 6 g per day in serious infections such as endocarditis.
Treatment should be continued for at least 10 days in beta-haemolytic streptococcal infections to minimize possible complications associated with the disease.
Dosage in Patients with Reduced Renal Function:
After an initial loading dose appropriate to the severity of the infection, the following reduced dosage schedule is recommended:
Dosage Guide for Patients with Renal Impairment
| Creatinine Clearance (mL/s) | Serum Creatinine (mMol/L) | Dosage |
|---|---|---|
| ≤0.91 | ≥140 | 250 mg to 1 g every 6-12 hours |
| 0.58-0.9 | 141-273 | 250 mg to 1 g every 8-12 hours |
| 0.18-0.57 | 274-406 | 125 mg to 500 mg every 12 hours |
| ≤0.17 | ≥407 | 125 mg to 500 mg every 18 hours |
Perioperative Prophylactic Use:
The recommended dosage regimen to prevent postoperative infection in contaminated or potentially contaminated surgery is:
- a. One gram intravenously administered ½ hour to 1 hour prior to the start of surgery so that at the time of the initial surgical incision adequate antibiotic levels are present in the serum and tissues.
- b. For lengthy operative procedures (e.g., 2 hours or more) 0.5-1.0 g administered intravenously during surgery. (Administration should be modified according to the duration of the operative procedure and the time of greatest exposure to infective organisms.)
- c. Postoperatively, 0.5-1.0 gram intravenously every 6 to 8 hours for 24 hours postoperatively. The prophylactic administration of CEFAZOLIN IN DEXTROSE INJECTION, USP maybe continued for 3 to 5 days following the completion of surgery in which the occurrence of infection may be particularly devastating (e.g., open-heart surgery and prosthetic arthroplasty).
Pediatric Use:
A total daily dosage of 25 to 50 mg per kg (approximately 10 to 20 mg per pound) of body weight, divided into three or four equal doses, is effective for most mild to moderately severe infections in children.
For severe infections total daily dosage maybe increased to 100 mg per kg (45 mg per pound) of body weight. The use of cefazolin sodium in prematures and in infants under one month is not recommended since the safety for use in these patients has not been established (see 1.1 Pediatrics).
Pediatric Dosage Guide – 25 mg/kg/day
| Weight | 25 mg/kg/day Divided Into 3 Doses | 25 mg/kg/day Divided into 4 doses | |||
|---|---|---|---|---|---|
| lb | kg | Approximate Single Dose mg/q8h | Volume Needed of 20 mg/mL Solution | Approximate Single Dose mg/q6h | Volume Needed of 20 mg/mL Solution |
| 10 | 4.5 | 40 mg | 2 mL | 30 mg | 1.5 mL |
| 20 | 9 | 75 mg | 3.75 mL | 55 mg | 2.75 mL |
| 30 | 13.6 | 115 mg | 5.75 mL | 85 mg | 4.25 mL |
| 40 | 18.1 | 150 mg | 7.5 mL | 115 mg | 5.75 mL |
| 50 | 22.7 | 190 mg | 9.5 mL | 140 mg | 7 mL |
Pediatric Dosage Guide-50 mg/kg/day
| Weight | 50 mg/kg/day Divided Into 3 Doses | 50 mg/kg/day Divided into 4 doses | |||
|---|---|---|---|---|---|
| lb | kg | Approximate Single Dose mg/q8h | Volume Needed of 20 mg/mL Solution | Approximate Single Dose mg/q6h | Volume Needed of 20 mg/mL Solution |
| 10 | 4.5 | 75 mg | 3.75 mL | 55 mg | 2.75 mL |
| 20 | 9 | 150 mg | 7.5 mL | 110 mg | 5.5 mL |
| 30 | 13.6 | 225 mg | 11.25 mL | 170 mg | 8.5 mL |
| 40 | 18.1 | 300 mg | 15 mL | 225 mg | 11.25 mL |
| 50 | 22.7 | 375 mg | 18.75 mL | 285 mg | 14.25 mL |
Treatment with 60 percent of the normal daily dose may be administered in divided doses every 12 hours to children with mild to moderate renal impairment (Ccr 0.67-1.17 mL/s). Children with moderate to severe renal impairment (Ccr 0.33- 0.87 mL/s) should be given 25 percent of the normal daily dose in equally divided doses every 12 hours, and children with severe renal impairment (Ccr 0.08-0.33 mL/s) should receive 10 percent of the normal daily dose every 24 hours.
All dosage recommendations apply after an initial loading dose.
4.4. Administration
Directions For Use of Cefazolin In Dextrose Injection, USP In Galaxy Container (PL2040 Plastic)
CEFAZOLIN IN DEXTROSE INJECTION, USP in GALAXY Container (PL 2040 Plastic) is to be administered either as a continuous or intermittent infusion using sterile equipment. Administer CEFAZOLIN IN DEXTROSE INJECTION, USP intravenously over approximately 30 minutes.
Thawing of Plastic Container
Thaw frozen container at room temperature (25°C) or under refrigeration (5°C). (DO NOT FORCE THAW BY IMMERSION IN WATER BATHS OR BY MICROWAVE IRRADIATION.)
Check for minute leaks by squeezing container firmly. If leaks are detected, discard solution as sterility may be impaired.
Do not add supplementary medication.
The container should be visually inspected. Visually inspect the container. If the outlet port protector is damaged, detached, or not present, discard container as solution path sterility may be impaired.
Components of the solution may precipitate in the frozen state and will dissolve upon reaching room temperature with little or no agitation. Potency is not affected. Agitate after solution has reached room temperature. If after visual inspection the solution remains cloudy or if an insoluble precipitate is noted or if any seals or outlet ports are not intact, the container should be discarded.
The thawed solution is stable for 30 days under refrigeration (5°C) and 48 hours at 25°C. Do not refreeze thawed antibiotics.
CAUTION: Do not use plastic containers in series connections. Such use could result in air embolism due to residual air being drawn from the primary container before administration of the fluid from the secondary container is complete.
Preparation for administration
- 1. Suspend container from eyelet support.
- 2. Remove protector from outlet port at bottom of container
- 3. Attach administration set. Refer to complete directions accompanying set.
5. Overdosage
There is a lack of experience with acute CEFAZOLIN IN DEXTROSE INJECTION, USP overdosage. Supportive therapy should be instituted according to symptoms in cases of suspected overdosage.
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
CEFAZOLIN IN DEXTROSE INJECTION, USP is supplied as a frozen, premixed, iso-osmotic, sterile, nonpyrogenic solution available in single dose Galaxy containers in two pack sizes: 50 mL bags in cartons of 24 bags each. 100 mL bags in cartons of 12 bags each.
7. Warnings and Precautions
General
In beta-haemolytic streptococcal infections, treatment should be continued for at least 10 days, to minimize possible complications associated with the disease.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Intravenous | solution, 20 mg / mL | Dextrose hydrous, water for injection, sodium hydroxide / hydrochloric acid (for pH adjustment) |
Gastrointestinal
In patients with a history of lower gastrointestinal disease, particularly colitis, CEFAZOLIN IN DEXTROSE INJECTION, USP should be prescribed with caution.
Immune
CEFAZOLIN IN DEXTROSE INJECTION, USP should be used with caution in penicillin-allergic patients. There is clinical evidence of partial cross-allergenicity of the penicillins and the cephalosporins. There are instances of patients who have had reactions to both penicillins and cephalosporins (including fatal anaphylaxis after parenteral use). Clinical and laboratory evidence of partial cross-allergenicity of the two drug classes exists.
CEFAZOLIN IN DEXTROSE INJECTION, USP should be administered cautiously and then only when absolutely necessary to any patient who has demonstrated allergy, particularly to drugs. Immediate emergency treatment with epinephrine is indicated for serious anaphylactoid reactions. As indicated, oxygen, intravenous steroids, and airway management, including intubation, should also be employed.
Monitoring and Laboratory Tests
ClinitestR tablets solution, but not enzyme-based tests such as ClinistixR and Tes-TapeR, may falsely indicate glucose in the urine of patients on cefazolin.
As with other dextrose-containing solutions, CEFAZOLIN IN DEXTROSE INJECTION, USP should be prescribed with caution in patients with overt or known subclinical diabetes mellitus or carbohydrate intolerance for any reason.
Positive direct and indirect Coombs’ tests have been reported during treatment with cefazolin. These may also occur in neonates whose mothers received cephalosporins before delivery. The clinical significance of this effect has not been established.
Overgrowth of Non-Susceptible Organisms
The overgrowth of non-susceptible organisms may result from the prolonged use of CEFAZOLIN IN DEXTROSE INJECTION, USP. It is essential that the patient be carefully observed.
Renal
Caution should be exercised in treating patients with pre-existing renal damage although cefazolin sodium has not shown evidence of nephrotoxicity.
Patients with low urinary output due to impaired renal function should be administered reduced daily dosages of CEFAZOLIN IN DEXTROSE INJECTION, USP (See 4.2 Recommended Dose and Dosage Adjustment, Dosage in Patients with Reduced Renal Function). Blood levels of cefazolin in dialysis patients remain fairly high and should be monitored.
Probenecid may decrease renal tubular secretion of cefazolin sodium when used concurrently with cefazolin sodium, resulting in increased and prolonged cefazolin blood levels (see 9.4 Drug-Drug Interactions).
Seizures may occur with the administration of CEFAZOLIN IN DEXTROSE INJECTION, USP, particularly in patients with renal impairment when the dosage is not reduced appropriately. Discontinue CEFAZOLIN IN DEXTROSE INJECTION, USP if seizures occur or make appropriate dosage adjustments in patients with renal impairment. Anticonvulsant therapy should be continued in patients with known seizure disorders.
Sensitivity/Resistance
Development of Drug Resistant Bacteria
Prescribing CEFAZOLIN IN DEXTROSE INJECTION, USP in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug- resistant bacteria.
Skin
Severe Cutaneous Adverse Reactions
Severe cutaneous adverse reactions (SCAR) such as acute generalized exanthematous pustulosis (AGEP), drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN) have been reported in association with beta-lactam treatment, When SCAR is suspected, CEFAZOLIN IN DEXTROSE INJECTION, USP should be discontinued and appropriate therapy and/or measures should be taken.
7.1. Special Populations
7.1.1. Pregnancy
The safety of the use of cefazolin sodium during pregnancy has not been established.
7.1.2. Breastfeeding
Very low concentrations of cefazolin are found in the milk of nursing mothers. CEFAZOLIN IN DEXTROSE INJECTION, USP should be administered with caution to a nursing woman.
7.1.3. Pediatrics
The safety of the use of cefazolin sodium in prematures and infants under one month of age has not been established (see 4.2 Recommended Dose and Dosage Adjustment, Pediatric Use).
8. Adverse Reactions
The following adverse reactions have been reported:
Gastrointestinal: Diarrhea, oral candidiasis (oral thrush), vomiting, nausea, stomach cramps, anorexia. During antibiotic treatment symptoms of pseudo membranous colitis can appear. There have been rare reports of nausea and vomiting. There have been reports of pseudo membranous colitis with the use of cephalosporins. It is therefore important to consider its diagnosis in patients who develop diarrhea in association with antibiotic use.
Haematologic: Cases of impaired blood coagulation have been reported during cefazolin treatment. Patients with risk factors causing vitamin K deficiency or affecting other clotting mechanisms (parenteral alimentation, dietary deficiencies, reduced hepatic and renal function) may be at increased risk of bleeding during cefazolin treatment. Monitoring of patients and vitamin K supplementation should be considered as indicated.
Blood clotting disturbances including prolongation of the prothrombin time, increased INR and bleeding. Neutropenia, anemia, leukopenia, thrombocythemia, positive direct and indirect antiglobulin (Coombs’) tests.
Hepatobiliary and Renal: Without clinical evidence of renal or hepatic impairment transient increases in AST (SGOT), ALT (SGPT), BUN and alkaline phosphatase levels have been observed. Transient hepatitis and cholestatic jaundice have been reported rarely, as with some penicillins and some other cephalosporins.
Immune system disorders: Allergic reactions occur infrequently and include: anaphylaxis, eosinophilia, itching, drug fever, skin rash.
Local Reactions: Phlebitis at the site of injection has occurred rarely. Some induration has been reported.
Other: Vulvar pruritus, genital moniliasis, vaginitis and anal pruritus.
9. Drug Interactions
9.4. Drug-Drug Interactions
The renal tubular secretion of cefazolin sodium may be decreased when probenecid is used concurrently, resulting in increased and prolonged cefazolin sodium blood levels.
9.7. Drug-Laboratory Test Interactions
ClinitestR tablets solution, but not enzyme-based tests such as ClinistixR and Tes-TapeR, may falsely indicate glucose in the urine of patients on cefazolin.
Positive direct and indirect Coombs’ tests have been reported during treatment with cefazolin. These may also occur in neonates whose mothers received cephalosporins before delivery. The clinical significance of this effect has not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
CEFAZOLIN is a cephalosporin antibiotic for parenteral administration. Cefazolin exerts its bactericidal effect by inhibiting bacterial cell wall synthesis.
10.3. Pharmacokinetics
The blood levels of cefazolin listed on the following table were determined following intravenous administration.
Serum Concentration (mg/mL) Following Administration:
(Time After Intravenous Injection in Minutes)
| 5 | 15 | 30 | 60 | 120 | 240 | |
|---|---|---|---|---|---|---|
| Cefazolin 1g | 188.4 | 135.8 | 106.8 | 73.7 | 45.6 | 16.5 |
The serum half-life is approximately 1.8 hours following intravenous administration.
The mean peak serum levels of cefazolin in hospitalized patients are approximately equivalent to those seen in normal volunteers.
Healthy volunteers received a continuous intravenous infusion of 3.5 mg/kg for 1 hour (approximately 250 mg) and 1.5 mg/kg hourly for the next two hours (approximately 100 mg). A steady serum level of 28 mg/mL was attained at the third hour.
Cefazolin levels in synovial fluid and serum are similar four hours after drug administration. Levels in cord blood are equivalent to 40% of those found in maternal blood.
In patients without obstructive biliary disease, serum levels of cefazolin can be up to five times lower than bile levels of cefazolin. However, bile levels of cefazolin are considerably lower than serum levels in patients with obstructive biliary disease.
Cefazolin is excreted unchanged in the urine. Approximately 60% of the drug is excreted in the first six hours, and this increases to 70%-80% within 24 hours.
11. Storage, Stability and Disposal
Store frozen bags in a freezer capable of maintaining a temperature of -20°C.
Thaw frozen container at room temperature (25⁰C) or under refrigeration (5⁰C). (DO NOT FORCE THAW BY IMMERSION IN WATER BATHS OR BY MICROWAVE IRRADIATION.)
The thawed solution is stable for 30 days under refrigeration (5°C) and 48 hours at 25°C. Do not refreeze thawed antibiotics.
12. Special Handling Instructions
Not Applicable
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance:
Proper Name: cefazolin sodium
Chemical Name: 5-Thia-1-azabicyclo[4.2.0]oct-2-ene-2-carboxylic acid, 3-[[(5-methyl 1,3,4-thiadiazol-2-yl)thio]methyl]-8-oxo-7-[[(1H-tetrazol-1-yl)acetyl]amino]-, monosodium salt (6R-trans)
Monosodium (6R,7R)-3-[[(5-methyl-1,3,4-thiadiazol-2-yl) thio]methyl]-8-oxo-7-[2-(1H-tetrazol-1-yl)acetamido]- 5-thia-1-azabicyclo[4.2.0]oct-2-ene-2-carboxylate
Structural Formula:
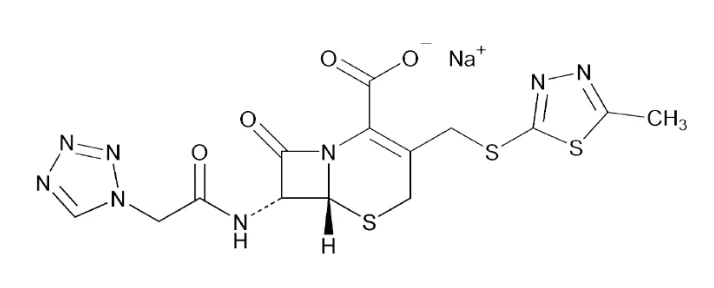
Molecular Formula: C14H13N8NaO4S3
Molecular Weight: 476.49 g / mol
Description: Cefazolin sodium: is a white or almost white powder, very hygroscopic. Cefazolin sodium meets the requirement of the current USP monograph for Cefazolin sodium, USP.
Composition
CEFAZOLIN IN DEXTROSE INJECTION, USP is a frozen, premixed, iso-osmotic, sterile, nonpyrogenic solution available in a single dose Galaxy container in two pack sizes:
| Pack Size | Composition |
|---|---|
| 50 mL | Cefazolin sodium equivalent to 1000 mg of Cefazolin, USP Dextrose, USP* (2 g as dextrose hydrous) Water for Injection, USP Sodium hydroxide / Hydrochloric acid (for pH adjustment) |
| 100 mL | Cefazolin sodium equivalent to 2000 mg of Cefazolin, USP Dextrose, USP* (4 g as dextrose hydrous) Water for Injection, USP Sodium hydroxide / Hydrochloric acid (for pH adjustment) |
* Dextrose, USP has been added to adjust osmolality
The solution is intended for intravenous use after thawing to room temperature.
The GALAXY container (PL 2040 Plastic) is fabricated from a specially designed multilayer plastic (PL 2040). Solutions are in contact with the polyethylene layer of this container and can leach out certain chemical components of the plastic in very small amounts within the expiration period. However, the suitability of the plastic has been confirmed in tests in animals according to the USP biological tests for plastic containers, as well as by tissue culture toxicity studies.
14. Clinical Trials
Clinical trial information is not available.
15. Microbiology
Cefazolin Activity Against Clinical Isolates
| No. of Strains | Cumulative Percentage Susceptible to Strains Indicated Concentration (µg/mL) | ||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| <0.05 | <0.1 - 0.78 | 1.56 - 3.13 | 6.25 - 12.5 | 25 – 50 | 100 | ||||||||||||||||||
| S. aureus | 700 | 0.14 | 59.1 | 90.6 – 92.4* | 97.3 | 99.7 | 99.9 | ||||||||||||||||
| S. pyogenes | 5 | 80+ | 100 | ||||||||||||||||||||
| S. faecalis | 2 | 50 | 100 | ||||||||||||||||||||
| S. pneumoniae | 6 | 100+ | |||||||||||||||||||||
| E. coli | 484 | 8.7 | 67.9 | 92.1 | 95.9 | 97.7 | |||||||||||||||||
| P. mirabilis | 30 | 50 | 86.7 | 90 | 90 | ||||||||||||||||||
| K. pneumoniae | 138 | 2.9 | 53.6 | 73.2 | 91.3 | 93.5 | |||||||||||||||||
| Enterobacter | 31 | 6.5 | 29.0 | 64.5 | 77.4 | ||||||||||||||||||
| H. influenzae | 30 | 13.3 | 70.0 | 100 | |||||||||||||||||||
| N. gonorrhoeae | 13 | 38.5 | 100 | ||||||||||||||||||||
| Shigella spp. | 2 | 50 | 50 | 100 | |||||||||||||||||||
| Salmonella spp. | 8 | 100 | |||||||||||||||||||||
| Staphylococci (coagulase - negative) | 295 | 66 | 82 | 90 | 93 | 100 | |||||||||||||||||
* Reported as 3.13-6.25 µ.g/mL
+ Reported as ≤ 0.1 µ.g /mL
Disc Susceptibility Tests:
The following criteria should be used to interpret tests using a standardized 30 µg cephalosporin- class disc:
Zones of 18 mm or greater indicate that the tested organisms are susceptible and are likely to respond to therapy. Zones of 15 to 17 mm indicate organisms of intermediate susceptibility which may be susceptible if high dosage is used or if the infection is confined to tissues and fluids (e.g., urine) in which high antibiotic levels are attained. Zones of 14 mm or less are produced by resistant organisms.
The cephalothin disc should not be used for testing susceptibility to other cephalosporins.
Dilution Techniques:
If the minimal inhibitory concentration (MIC) for cefazolin is not more than 16 mg/mL, then a bacterial isolate may be considered susceptible. If the MIC is equal to or greater than 64 mg/mL, organisms are considered to be resistant.
The ranges of MIC for the control strains were:
E. coli ATCC 25922 1.0-4.0 mg/mL
S. aureus ATCC 25923 0.25-1.0 mg/mL
16. Non-Clinical Toxicology
General Toxicology
Acute Toxicity:
Parenteral and oral cefazolin demonstrated low toxicity in rodents, canines and rabbits tested in acute toxicity studies.
| Species | Route of Administration | LD50 LD (g/kg) |
|---|---|---|
| Mice | intravenous | ≥3.9 |
| intraperitoneal | ≥4 | |
| subcutaneous | 7.6 | |
| oral | >11 | |
| Rats | intravenous | ≥3 |
| intraperitoneal | 7.4 | |
| subcutaneous | >10 | |
| oral | >11 | |
| Rabbits | intravenous | >2 |
| Dogs | intravenous | >2 |
Subacute and Chronic Toxicity:
Rats and dogs were studied in subacute and chronic parenteral toxicity of cefazolin. Rats were treated for 3 and 6 months subcutaneously and for one month intraperitoneally. The highest doses ranged from 2000 mg/kg per day in the 6 month study to 4000 mg/kg per day in the 1 and 3 month studies. Anemia was the only significant abnormality attributable to s.c. drug administration. In all experiments there was a definite dose-related depression of SGPT levels. Leukocytosis and hypererythropoiesis accompanied the anemia, which was probably related to hemorrhaging at the injection site.
The lowering of the SGPT was dependent upon both the dose and the duration of treatment. This was not statistically significant at the low doses and was reversible upon withdrawal of the drug. Equivalent chronic studies in dogs produced similar results: at the higher doses there was a fall in SGPT and frank anemia resulted from high subcutaneous doses. Dogs treated intravenously did not develop the anemia indicating that it was probably associated with hemorrhaging at the site of injection.
Reproductive and Developmental Toxicology
Rabbits and mice were administered cefazolin in doses of 240 mg/kg/day and 2400 mg/kg/day. No teratologic effects were observed. No adverse effects on mating, fertility, gestation, delivery and lactation were observed in rats administered 2000 mg/kg per day. Baby rats whose mothers were injected with 1200 mg/kg/day of cefazolin prior to delivery and throughout lactation were observed and there was no effect on the birth, or peri- and postnatal development.
Special Toxicology
Nephrotoxicity:
The nephrotoxicity of cefazolin was studied following intravenous injections of rabbits and subcutaneous injections of mice and rats. The mean nephrotoxic intravenous dose in rabbits was between 300 and 400 mg/kg/day. No evidence of renal damage was produced when cefazolin was injected subcutaneously into mice at a dose of 8 g/kg/day for up to 3 days and into rats at a dose of 4 g/kg/day for up to 7 days.
17. Supporting Product Monographs
- 1. CEFAZOLIN FOR INJECTION powder for solution, 500 mg, 1 g and 10 g, control 297943, product monograph, Teva Canada Limited. (2025-12-29)