


Product Monograph - Ciloxan
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Ophthalmic (topical) | Solution/ 0.3% w/v ciprofloxacin (as ciprofloxacin hydrochloride) | Benzalkonium chloride as preservative. Sodium acetate, acetic acid, mannitol, edetate disodium, hydrochloric acid and/or sodium hydroxide (to adjust pH), purified water |
Ointment/ 0.3% w/w ciprofloxacin (as ciprofloxacin hydrochloride) | White petrolatum, mineral oil | |
INDICATIONS AND CLINICAL USE
CILOXAN® (ciprofloxacin ophthalmic solution) is indicated for the treatment of the following infections of the eye and its adnexae when caused by susceptible strains of the designated bacteria.
Corneal Ulcers: Pseudomonas aeruginosa, Staphylococcus aureus,
Staphylococcus epidermidis, Streptococcus pneumoniae.
Conjunctivitis: Staphylococcus aureus, Staphylococcus epidermidis,
Streptococcus (Viridans group), Streptococcus pneumoniae, Haemophilus influenzae.
CILOXAN® (ciprofloxacin ophthalmic ointment) is indicated for the treatment of the following infections of the eye and its adnexae when caused by susceptible strains of the designated bacteria.
Corneal Ulcers: Pseudomonas aeruginosa, Staphylococcus aureus,
Staphylococcus epidermidis.
Conjunctivitis: Staphylococcus aureus, Staphylococcus epidermidis,
Streptococcus (Viridans group), Streptococcus pneumoniae, Haemophilus influenzae.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of CILOXAN and other antibacterial drugs, CILOXAN should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria.
Pediatrics (< 1 year of age): The safety and efficacy of CILOXAN in children less than one year of age have not been demonstrated.
CONTRAINDICATIONS
CILOXAN is contraindicated in patients with:
- Hypersensitivity to ciprofloxacin or to any ingredient in the formulation or component of the container. For a complete listing, see Dosage Forms, Composition and Packaging section.
- Hypersensitivity to other quinolones, including nalidixic acid.
WARNINGS AND PRECAUTIONS
NOT FOR INJECTION INTO THE EYE.
FOR TOPICAL OCULAR USE ONLY.
General
Whenever clinical judgement dictates, the patient should be examined with the aid of magnification, such as slit lamp biomicroscopy and, where appropriate, fluorescein staining.
Serious and occasionally fatal hypersensitivity (anaphylactic) reactions, some following the first dose, have been reported in patients receiving therapy with quinolones by systemic administration. Some reactions were accompanied by cardiovascular collapse, loss of consciousness, tingling, pharyngeal or facial edema, dyspnea, urticaria, and itching. Only a few patients had a history of hypersensitivity reactions. Anaphylactic reactions may require epinephrine and other emergency measures. Ciprofloxacin should be discontinued at the first sign of hypersensitivity or allergy and the patient monitored until the risk of anaphylaxis is no longer present.
Severe hypersensitivity reactions characterized by rash, fever, eosinophilia, jaundice, and hepatic necrosis with fatal outcome have been reported rarely (less than one per million prescriptions) in patients receiving systemically administered ciprofloxacin along with other drugs. One report exists of anaphylaxis in a patient treated with topical ciprofloxacin concomitantly with several other antibiotics and medications. The possibility that these reactions were related to ciprofloxacin cannot be excluded. Ciprofloxacin should be discontinued at the first appearance of a skin rash or any other sign of hypersensitivity reaction.
Tendon inflammation and rupture may occur with systemic fluoroquinolone therapy including ciprofloxacin, particularly in elderly patients and in those treated concurrently with corticosteroids. Therefore treatment with CILOXAN should be discontinued at the first sign of tendon inflammation.
Driving and Using Machinery:
Temporary blurred vision or other visual disturbances may affect the ability to drive or use machines. If blurred vision occurs upon administration, the patient must wait until vision clears before driving or using machinery.
Susceptibility/ Resistance
Development of Drug Resistant Bacteria:
Prescribing CILOXAN in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Potential for Microbial Overgrowth:
As with other antibacterial preparations, prolonged use of CILOXAN may result in overgrowth of non-susceptible organisms, including fungi. If superinfection occurs, discontinue use and institute alternative therapy.
Ophthalmologic
In clinical studies of patients with bacterial corneal ulcer, a white crystalline precipitate located in the superficial portion of the corneal defect was observed in 29 (18.8%) out of 154 patients administered CILOXAN solution and in 32 (12.6%) of 253 patients administered CILOXAN ointment. The onset of the precipitate was within 24 hours to 7 days (solution) and 13 days (ointment) after starting therapy. In 16 patients administered CILOXAN solution, resolution of the precipitate was seen in 1 to 8 days (seven within the first 24-72 hours). In four patients, resolution was noted in 10-13 days. In one patient, the precipitate was immediately irrigated out upon its appearance. In six patients, exact resolution days were unavailable; however, at follow-up examinations 18-44 days after onset of the event, complete resolution of the precipitate was noted. In two patients, outcome information was unavailable. The presence of the white precipitate did not preclude continued use of CILOXAN solution or ointment, nor did it adversely affect the clinical course of the ulcer or visual outcome. A literature report exists of a single case of ciprofloxacin-associated dense precipitate apparently interfering with re-epithelialization.
Contact lens wear is not recommended during treatment of an ocular infection. Therefore, patients should be advised not to wear contact lenses during treatment with CILOXAN.
CILOXAN solution contains the preservative benzalkonium chloride, which may cause eye irritation and is known to bind to and discolour soft contact lenses. Avoid contact of CILOXAN* ophthalmic solution with soft contact lenses. In case patients are allowed to wear contact lenses, they must be instructed to remove contact lenses prior to application of CILOXAN solution and wait at least 15 minutes before re-insertion.
Ophthalmic dosage regimens involving both solution and ointment formulations of ciprofloxacin 0.3% have not been studied. A controlled study of the efficacy and safety of ciprofloxacin ointment versus ciprofloxacin solution 0.3% has not been conducted.
In patients with large (> 4mm) and/or deep stromal ulcers, the clinical success rate was lower for both ciprofloxacin and standard (fortified antibiotics) therapy.
Sexual Function/Reproduction
Studies have not been performed in humans to evaluate the effect of topical administration of ciprofloxacin on fertility. Reproduction studies of systemic ciprofloxacin exposure have been performed in rats and mice at doses up to 6 times the usual daily human dose and have revealed no evidence of impaired fertility.
Special Populations
Pregnant Women: There are no adequate and well controlled studies of CILOXAN in pregnant women. CILOXAN should be used in pregnant women only if in the physician’s opinion, the benefit clearly outweighs any potential unknown risks.
Reproduction studies of systemic ciprofloxacin exposure have been performed in rats and mice at doses up to 6 times the usual daily human dose and have revealed no evidence of harm to the fetus due to ciprofloxacin. In rabbits, as with most antimicrobial agents, ciprofloxacin (30 and 100 mg/kg orally) produced gastrointestinal disturbances resulting in maternal weight loss and an increased incidence of abortion. No teratogenicity was observed at either dose. After intravenous administration in rabbits, at doses up to 20 mg/kg, no maternal toxicity was produced and no embryotoxicity or teratogenicity was observed.
Nursing Women: It is not known whether topically applied CILOXAN is excreted in human milk; however, it is known that orally administered ciprofloxacin is excreted in the milk of lactating rats and that other drugs of this class are excreted in human milk. For this reason, and because of the potential for serious adverse reactions from ciprofloxacin in nursing infants, a decision should be made to discontinue nursing or to discontinue the drug, taking into consideration the importance of the drug to the mother.
Pediatrics (< 1 years of age): The safety and efficacy of CILOXAN solution or ointment in children less than one year of age have not been demonstrated.
Pediatrics (≥ 1 years of age): CILOXAN solution has been used to treat conjunctivitis in 123 children between the ages of one and twelve years and CILOXAN ointment has been used in 182 children between the ages of one and twelve years. No serious adverse event was reported in these patients.
Ciprofloxacin and quinolone-related drugs have been shown to cause arthropathy in immature animals of most species tested following oral administration. Topical ocular administration of ciprofloxacin to immature animals (Beagle dogs) did not cause arthropathy or demonstrate any articular lesions, and there is no evidence that the ophthalmic dosage form has any effect on the weight bearing joints.
In 634 children treated orally with ciprofloxacin, clinical and radiologic monitoring did not reveal any skeletal toxicity felt to be quinolone-related. However, there are a small number of reports of arthralgia in children, associated with oral ciprofloxacin therapy. This arthralgia has been shown to be reversible on discontinuation of the systemic medication.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
During clinical studies, treatment related adverse events to CILOXAN solution and ointment were mild, infrequent in occurrence and non-serious in nature, and did not lead to premature discontinuation of therapy.
CILOXAN Solution
The most frequently reported adverse events that were considered related or possibly related to CILOXAN solution were: transient discomfort, i.e., stinging, burning, irritation (8.6%), noticeable taste (4.5%), foreign body sensation (1.8%), and itching (1.2%). Treatment-related or possibly related medical events occurring between 0.5 and 1% incidence were: lid margin crusting, crystals/ scales, erythema/redness, dryness, discharge, corneal staining, keratopathy/keratitis, hyperemia/congestion and tearing.
In clinical trials in which 154 patients were treated for bacterial corneal ulcers, the most frequently reported adverse event related or possibly related to therapy was a white crystalline precipitate seen in 29 (18.8%) patients. The precipitate required no adjunctive therapy and resolved spontaneously with continued ciprofloxacin use.
Other rarely reported events related or possibly related to CILOXAN solution included: ocular congestion, photophobia, pain, vision decrease, chemosis, corneal infiltrate, inflammation, blurred vision, corneal toxicity, allergy, intolerance, lid edema, heavy sensation, swelling, conjunctival reaction, numbing sensation, conjunctivitis, punctate epithelial erosion, worsened infiltrate, and headache.
CILOXAN Ointment
The most commonly reported drug adverse reactions in patients with conjunctivitis treated with CILOXAN ointment were discomfort (1.3%), pruritus (1.3%), and hyperemia (1.3%), and in patients with corneal ulcers were: white precipitate (12.6%), discomfort (2.0%), and blurred vision (1.2%).
Other reactions associated with CILOXAN ointment occurring in less than 1.0% of patients included: pruritus, eye pain, tearing, photophobia, allergic reactions, dry eye, decreased visual acuity, lid erythema, corneal staining, keratoconjunctivitis, keratopathy, corneal lesion, epitheliopathy, ocular edema, irritation, foreign body sensation, nausea, dermatitis and metallic taste.
Post-Market Adverse Drug Reactions
The following additional adverse reactions were seen with CILOXAN solution or ointment in subsequent clinical trials:
Ear and labyrinth disorders: ear pain;
Eye disorders: asthenopia, conjunctival edema, corneal epithelium defect, diplopia, eyelid exfoliation, hordeolum, hypoesthesia eye, punctate keratitis, vital dye staining cornea present;
Gastrointestinal disorders: abdominal pain, diarrhea;
Nervous system disorders: dizziness;
Respiratory, thoracic and mediastinal disorders: paranasal sinus hypersecretion, rhinitis.
The following additional adverse reactions were seen with CILOXAN solution or ointment via spontaneous reporting. Reliable estimates of the frequencies of spontaneous reactions cannot be determined because they are reported voluntarily from a population of uncertain size:
Musculoskeletal and connective tissue disorders: tendon disorder.
DRUG INTERACTIONS
Specific drug interaction studies have not been conducted with CILOXAN solution or ointment. However, the systemic administration of some quinolones has been shown to elevate plasma concentrations of theophylline, interfere with the metabolism of caffeine, enhance the effects of the oral anticoagulant, warfarin and its derivatives, and has been associated with transient elevations in serum creatinine in patients receiving cyclosporin concomitantly.
DOSAGE AND ADMINISTRATION
Recommended Dose
Solution:
Conjunctivitis (Adults and Children 1 year and older):
Instill one or two drops of CILOXAN solution into the conjunctival sac(s) every two hours while awake for two days and then two drops every four hours while awake for 5 days.
Corneal Ulcer (Adults and Children 12 years and older):
Instill two drops of CILOXAN solution into the affected eye(s) every 15 minutes for the first six hours and then two drops into the affected eye(s) every 30 minutes for the remainder of the first day. On the second day, instill two drops in the affected eye(s) hourly. On the third through the fourteenth day, place two drops in the affected eye(s) every four hours. If corneal reepithelialization has not occurred after 14 days, the continuation of the dosing regimen is at the discretion of the attending physician.
Ointment:
Conjunctivitis (Adults and Children 1 year and older): Apply a 1/2" ribbon of CILOXAN ointment into the conjunctival sac(s) three times a day on the first two days and then apply a 1/2" ribbon two times a day for the next five days.
Corneal Ulcer (Adults and Children 12 years and older):
Apply a 1/2" ribbon of CILOXAN ointment into the conjunctival sac(s) every 1-2 hours around the clock on the first two days, then apply a 1/2" ribbon every 4 hours for up to 12 days. If corneal reepithelialization has not occurred after 12 days, the continuation of the dosing regimen is at the discretion of the attending physician.
Missed Dose:
If a dose is missed, treatment should be continued as soon as possible. However if it is almost time for the next dose, the missed dose should be skipped. Do not use a double dose to make up for the one missed.
Administration
Solution and ointment:
Patients should be advised to avoid contamination of the dispensing tip.
OVERDOSAGE
A topical overdosage of CILOXAN is considered to be a remote possibility. Discontinue medication when heavy or protracted use is suspected. A topical overdosage may be flushed from the eye(s) with warm tap water. Accidental ingestion of the content of one bottle (10 mL size) or tube (3.5 g size) would result in ingestion of up to 30 mg ciprofloxacin or 10.5 mg ciprofloxacin, respectively.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The bactericidal action of ciprofloxacin results from inhibition of the enzyme, DNA gyrase, which is required for the synthesis of bacterial DNA.
Pharmacokinetics:
Topically applied ciprofloxacin ophthalmic solution is absorbed systemically with ciprofloxacin plasma concentrations approaching steady state at the end of dosing each day. Ciprofloxacin plasma concentrations following a routine ophthalmic treatment regimen were in the range of nonquantifiable to 4.7 ng/mL with the majority of levels falling between 1.5 to 2.5 ng/mL. Maximum serum concentration following a single oral administration of a 250 mg ciprofloxacin tablet is about 1200 ng/mL.
STORAGE AND STABILITY
Store in the carton at room temperature (2oC – 30oC). Keep out of reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each mL of CILOXAN Solution contains:
Medicinal ingredient: Ciprofloxacin hydrochloride 3.5 mg equivalent to 3 mg base.
Preservative: Benzalkonium chloride 0.006% w/v.
Non-medicinal ingredients: Sodium acetate, acetic acid, mannitol, edetate disodium, hydrochloric acid and/or sodium hydroxide (to adjust pH) and purified water.
CILOXAN solution is available in 5 mL and 10 mL plastic DROP-TAINER® dispensers.
Each gram of CILOXAN Ointment contains:
Medicinal ingredient: Ciprofloxacin Hydrochloride 3.5 mg equivalent to 3 mg base.
Non-medicinal ingredients: White petrolatum, mineral oil.
CILOXAN ointment is available in 3.5 g metal ophthalmic ointment tubes.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance:
Proper name: Ciprofloxacin Hydrochloride
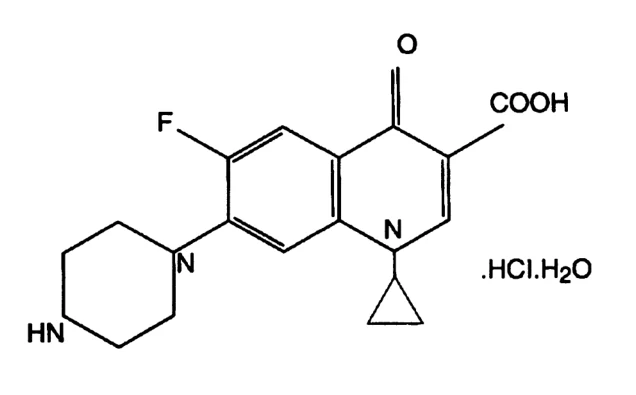
Chemical Name: 1 cyclopropyl-6-fluoro-1,4-dihydro-4-oxo-7-(1-piperazinyl)-3-quinolinecarboxylic acid, hydrochloride monohydrate.
Molecular formula and molecular mass: C17H18FN303.HCl.H20; 385.8
Structural Formula:
Physicochemical properties: Ciprofloxacin is a faintly yellowish to light yellow crystalline substance. Ciprofloxacin is readily water soluble and the pH of a 2.5% solution is about 4.
DETAILED PHARMACOLOGY
Animal Pharmacology:
After topical application of ciprofloxacin 0.3%, (1 drop every 30 minutes for a total of 6 doses), the concentration of ciprofloxacin achieved in the aqueous humor of rabbits when the corneal epithelium was intact, was 4.8 µg/mL and when debrided was 12.9 µg/mL.
Human Pharmacology:
Topically applied CILOXAN® is absorbed systemically with ciprofloxacin plasma concentrations approaching steady state at the end of dosing each day. Ciprofloxacin plasma concentrations following a routine ophthalmic treatment regimen were in the range of non-quantifiable to 4.7 ng/mL with the majority of levels falling between 1.5 to 2.5 ng/mL. Maximum serum concentration following a single oral administration of a 250 mg ciprofloxacin tablet is about 1200 ng/mL.
Dose response studies and pharmacokinetic studies were not performed with CILOXAN ointment.
MICROBIOLOGY
Ciprofloxacin has in vitro activity against both gram-positive and gram-negative organisms. The bactericidal action of ciprofloxacin results from interference of the enzyme, DNA gyrase, needed for the synthesis of bacterial DNA. The in vitro activity of ciprofloxacin against various strains of microorganisms is listed in Table 1.
The minimum bactericidal concentration (MBC) generally does not exceed the minimum inhibitory concentration (MIC) by more than a factor of 2. Resistance to ciprofloxacin in vitro develops slowly (multiple-step mutation). Rapid one-step development of resistance has not been observed.
Cross-resistance with other quinolones has been observed. However, organisms resistant to antimicrobial agents having other mechanisms of action (e.g. beta-lactam and aminoglycoside antibiotics) may be sensitive to ciprofloxacin. Conversely, organisms resistant to ciprofloxacin might be sensitive to antimicrobial agents having other mechanisms of action.
Table 1: MIC90S for Potential Ocular Pathogens
| No. of Strains | MIC90 (µg/mL) | MIC range (µg/mL) | ||
| ||||
| Staphylococcus aureus | 397 | 0.5 | 0.25 - 4.0 | |
| Staphylococcus aureus (methicillin-susceptible) | 287 | 0.5 | 0.5 | |
| Staphylococcus aureus (methicillin-resistant) | 339 | 0.25 | 0.25 - 4.0 | |
| S. epidermidis | 136 | 0.25 | 0.25 – 2.0 | |
| Staphylococcus, other coagulase-negative | 432 | 0.25 | 0.25 -1.0 | |
| Streptococcus pneumonia | 331 | 1.0 | 1.0 -2.0 | |
| S. pyogenes | 215 | 0.25 | 0.25 - 2.0 | |
| Streptococcus, Viridans group | 87 | 2.0 | 2.0 – 4.0 | |
| Enterococcus spp | 580 | 0.06 | 0.06 – 8.0 | |
| Corynebacterium spp including JKs | 52 | 0.5 | 0.5 – 1.0 | |
| ||||
| Neisseria gonorrhoeae | 335 | 0.004 | 0.002 – 0.06 | |
| N. meningitidis | 215 | 0.06 | 0.008 – 0.06 | |
| Haemophilus influenzae | 717 | 0.06 | 0.00 – 0.003 | |
| Moraxella (Branhamella) catarrhalis | 246 | 0.06 | 0.015 – 0.5 | |
| Acinetobacter spp | 279 | 1.0 | 0.5 – 2.0 | |
| Pseudomonas aeruginosa | 801 | 1.0 | 0.012 – 1.0 | |
| P. aeruginosa (gentamicin-resistant) | 11 | 4.0 | 4.0 | |
| Escherichia coli | 634 | 0.25 | 0.004 – 0.25 | |
| Klebsiella pneumoniae | 376 | 0.125 | 0.015 – 0.5 | |
| Proteus mirabilis | 464 | 0.125 | 0.015 – 0.25 | |
| Serratia marcescens | 238 | 1.0 | 0.125 | |
| ||||
| Bacteroides spp | 365 | 16.0 | 0.015 – 32.0 | |
| Clostridium spp (excluding C. difficile) | 156 | 8.0 | 0.5 – 32.0 | |
| Peptostreptococcus spp | 30 | 4.0 | 2.0 – 4.0 | |
| 68 | 2.0 | 1.0 – 2.0 | |
TOXICOLOGY
Ciprofloxacin has been shown to cause arthropathy in immature animals of most species tested following oral administration. However, in a one-month topical ocular study, 0.3% or 0.75% Ciprofloxacin Hydrochloride Ophthalmic Solution administered four times per day to immature Beagle dogs did not demonstrate any articular lesions. Based on ocular toxicology studies performed in rabbits, the ocular effects produced by an exaggerated topical ocular exposure to 0.3%, 0.75% or 1.5% Ciprofloxacin Hydrochloride Ophthalmic Solution or Ointment were minimal and transient in nature, confined to the conjunctiva, and generally comparable to those effects observed in the untreated control and vehicle control groups. In a sub-chronic, one-month topical ocular irritation study, 0.3% to 1.5% Ciprofloxacin Hydrochloride Ophthalmic Solution or Ointment did not demonstrate a cumulative ocular irritation potential and did not demonstrate any apparent systemic or ocular toxicity in rabbits.
The cataractogenic potential of oral ciprofloxacin in rats was evaluated. The results indicate that ciprofloxacin was not co-cataractogenic. An intravenous study of ciprofloxacin at levels up to 20 mg/kg over a six month period in Rhesus monkeys indicated that there were no signs of changes in lens transparency due to the administration of ciprofloxacin.
Mutagenicity
Eight in vitro mutagenicity tests have been conducted with ciprofloxacin and the test results are listed below:
Salmonella/Microsome Test (Negative)
E. coli DNA Repair Assay (Negative)
Mouse Lymphoma Cell Forward Mutation Assay (Positive)
Chinese Hamster V79 Cell HGPRT Test (Negative)
Syrian Hamster Embryo Cell Transformation Assay (Negative)
Saccharomyces cerevisiae Point Mutation Assay (Negative)
Saccharomyces cerevisiae Mitotic Crossover and Gene Conversion Assay (Negative)
Rat Hepatocyte DNA Repair Assay (Positive)
Thus 2 of the 8 tests were positive but results of the following 3 in vivo test systems gave negative results:
Rat Hepatocyte DNA Repair Assay
Micronucleus Test (Mice)
Dominant Lethal Test (Mice)
Carcinogenicity
Long-term carcinogenicity studies in mice and rats have been completed. After oral dosing for up to 2 years, there is no evidence that ciprofloxacin had any carcinogenic or tumorigenic effects in these species.
REFERENCES
- 1. Bioliterature, Inc. Ciprofloxacin product information monograph – compendium of preclinical and clinical data. Marcel Dekker, Inc., New York. 1988.
- 2. Kanellopoulos AJ, Miller F, Wittpen JR. Deposition of topical ciprofloxacin to prevent re-epithelization of a corneal defect. Am J Ophthalmol 1994; 117:258-259.
- 3. Leibowitz HM. Antibacterial effectiveness of ciprofloxacin 0.3% ophthalmic solution in the treatment of bacterial conjunctivitis. Am J Ophthalmol 1991; 112:29S-33S.
- 4. Leiibowitz HM. Clinical evaluation of ciprofloxacin 0.3% ophthalmic solution for the treatment of bacterial keratitis. Am J Ophthalmol 1991; 112:34S-47S.
- 5. Lorian V. Antibiotics in laboratory medicine. 3rd Ed. Williams and Wilkins, Baltimore. 1991.
- 6. O’Brien TP, Sawusch MR, Dick JD, Gottsch JD. Topical ciprofloxacin treatment of Pseudomonas keratitis in rabbits. Arch Ophthalmol 1988, 106:1444.
- 7. Reidy JJ, Hobden JA, Hill JM, Forman K and O’Callaghan RJ. The efficacy of topical ciprofloxacin and norfloxacin in the treatment of experimental Pseudomonas keratitis. Cornea 1991; 10:25.
- 8. Schaad UB, Stoupis C, Wedgwood J, Tschaeppeler H, Vock P. Clinical, radiologic and magnetic resonance monitoring for skeletal toxicity in pediatric patients with cystic fibrosis receiving a three month course of ciprofloxacin. Pediatr Infect Dis J 1991; 10:723-729.
- 9. Smith BR. National co-operative study of ciprofloxacin susceptibility in the United States. Curr Ther Res 1990; 47:962-970.
- 10. Wolfson JS and DC Hooper. Quinolone antimicrobial agents. American Society for Microbiology, Washington, DC. 1989.