Product Monograph - Colistimethate for Injection U.S.P.
ACTION AND CLINICAL PHARMACOLOGY
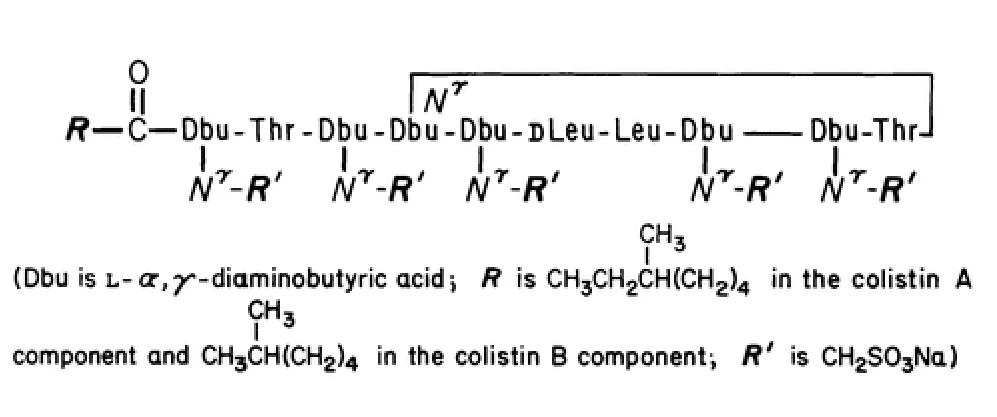
Colistimethate for Injection USP is the pentasodium salt of the penta (methanesulfonic acid) derivative of colistin. Colistin is a basic polypeptide antibiotic substance produced by the growth of Bacillus polymyxa var. colistinus.
Colistin derivatives appear to alter the permeability of the bacterial cytoplasmic membrane, causing leakage of intracellular nucleosides. The drugs are bactericidal in action.
IM administration of sodium colistimethate with activity equivalent to that of 150 mg of colistin produces peak serum levels of approximately 5 to 7.5 μg/mL within 2 hours. Peak serum levels after IV administration occur within 10 minutes and are higher but decline more rapidly than those achieved after IM administration. The serum half-life is approximately 1.5 hours following IV and 2.75 to 3 hours following IM administration. Blood levels appear to decline more rapidly in children than in adults.
Hydrolysis of sodium colistimethate is required for antibacterial activity. Sodium colistimethate and its metabolites are excreted primarily by the kidneys; urine levels of the active antibiotic are considerably higher than serum levels. In 24 hours, approximately 66% after IM administration and 75% after IV administration is excreted.
INDICATIONS AND CLINICAL USE
Colistimethate for Injection USP is indicated for the treatment of acute or chronic infections due to sensitive strains of certain gram-negative bacilli. Particularly indicated when the infection is caused by sensitive strains of P. aeruginosa. This antibiotic is not indicated for infections due to proteus or neisseria. Sodium colistimethate has proven clinically effective in treatment of infections due to the following gram-negative organisms: A. aerogenes, E. coli, K. pneumoniae and P. aeruginosa.
Pending results of appropriate bacteriologic cultures and sensitivity tests, sodium colistimethate may be used to initiate therapy in serious infections that are suspected to be due to gram-negative organisms.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Colistimethate for Injection USP and other antibacterial drugs, Colistimethate for Injection USP should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
Colistimethate for Injection USP is contraindicated in patients with a history of sensitivity to the drug.
PRECAUTIONS
Maximum daily dose of Colistimethate for Injection USP should not exceed 5 mg/kg/day with normal renal function.
Occupational Hazards: Transient neurological disturbances may occur. These include circumoral paresthesias or numbness, tingling or formication of the extremities, generalized pruritus, vertigo, dizziness, and slurring of speech. For these reasons, patients should be warned not to drive vehicles or use hazardous machinery while on therapy.
Reduction of dosage may alleviate symptoms. Therapy need not be discontinued, but such patients should be observed with particular care. Overdosage can result in renal insufficiency, muscle weakness and apnea.
Pregnancy: The safety of sodium colistimethate during human pregnancy has not been established.
Since sodium colistimethate is eliminated mainly by renal excretion, it should be used with caution when the possibility of impaired renal function exists. The decline in renal function with advanced age should be considered.
When actual renal impairment is present, sodium colistimethate may be used, but the greatest caution should be exercised and the dosage should be reduced in proportion to the extent of the impairment. Administration of amounts of sodium colistimethate in excess of renal excretory capacity will lead to high serum levels and can result in further impairment of renal function, initiating a cycle which, if not recognized, can lead to acute renal insufficiency, renal shutdown and further concentration of the antibiotic to toxic levels in the body. At this point, interference of nerve transmission at neuromuscular junctions may occur and result in muscle weakness and apnea.
Easily recognized signs indicating the development of impaired renal function are diminishing urine output, rising BUN and serum creatinine. If present, therapy with sodium colistimethate should be discontinued immediately.
If a life-threatening situation exists, therapy may be reinstated at a lower dosage after blood levels have fallen.
Certain other antibiotics (kanamycin, streptomycin, dihydrostreptomycin, polymyxin, neomycin) have also been reported to interfere with the nerve transmission at the neuromuscular junction and thus should not be given concomitantly with sodium colistimethate except with the greatest caution. The antibiotics with a gram positive antimicrobial spectrum, e.g. penicillin, tetracycline, sodium cephalothin, have not been reported to interfere with nerve transmission and, accordingly, would not be expected to potentiate this activity of sodium colistimethate.
Other drugs, including curariform muscle relaxants (ether, tubocurarine, succinylcholine, gallamine, decamethonium and sodium citrate), potentiate the neuromuscular blocking effect and should be used with extreme caution in patients being treated with sodium colistimethate.
If apnea occurs it may be treated with assisted respiration, oxygen, and calcium chloride injections.
Susceptibility/Resistance: Prescribing Colistimethate for Injection USP in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
ADVERSE REACTIONS
Respiratory arrest has been reported following IM administration of sodium colistimethate. Impaired renal function increases the possibility of apnea and neuromuscular blockade following administration of sodium colistimethate. This has generally been due to failure to follow recommended guidelines, usually overdosage, failure to reduce dose commensurate with degree of renal impairment, and/or concomitant use of other antibiotics or drugs with neuromuscular blocking potential.
A decrease in urine output or increase in BUN or serum creatinine can be interpreted as signs of nephrotoxicity, which is probably a dose dependent effect of sodium colistimethate. These manifestations of nephrotoxicity are reversible following discontinuation of the antibiotic.
Increases of BUN have been reported for patients receiving sodium colistimethate at dose levels of 1.6 - 5 mg/kg per day. The BUN values returned to normal following cessation of sodium colistimethate administration.
Paraesthesia, tingling of the extremities or tingling of the tongue and generalized itching or urticaria have been reported by patients who received sodium colistimethate by IM or IV injection. In addition, the following adverse reactions have been reported for sodium colistimethate: drug fever and gastrointestinal upset, vertigo, and slurring of speech. The subjective symptoms reported by the adult may not be manifest in infants or young children, thus requiring close attention to renal function.
OVERDOSE
| For management of a suspected drug overdose, please contact your regional Poison Control Centre. |
Symptoms: Dizziness, ataxia, speech disturbances, generalized muscular weakness, apnea and elevated BUN.
Treatment: Usual medical regimen for treatment of oliguria or anuria. Consider dialysis, particularly if a massive overdosage is discovered shortly after administration.
DOSAGE AND ADMINISTRATION
For IV or IM use: Average dose is 2.5 mg/kg/day given in 2 to 4 divided doses. In the presence of bacteremia, septicemia or other serious infections, greater than average doses may be required. Maximal dose of 5 mg/kg/day should not be exceeded in patients with normal renal function.
Vial Composition
Each Colistimethate for Injection USP vial contains: colistin base activity (as sodium colistimethate) 150 mg which forms a clear, aqueous solution when reconstituted with 2.0 mL of Sterile Water for Injection USP. Each mL of reconstituted sterile solution contains: sodium colistimethate equivalent to 75 mg colistin base.
Stability and Storage Recommendations
Store Colistimethate for Injection USP in powder form at controlled room temperature (15°C-30°C).
After reconstitution, Colistimethate for Injection USP solution should be stored refrigerated (2 ° C-8 ° C) or at room temperature (15 ° C-30 ° C) and used within 7 days.
Any infusion solution containing colistimethate sodium should be freshly prepared and used for no longer than 24 hours.
AVAILABILITY OF DOSAGE FORMS
Colistimethate for Injection USP vials are available in the dosage strength equivalent to 150 mg colistin base activity per vial.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Colistimethate Sodium
Chemical Name: Colistimethate Sodium
Empirical Formula: C58H105N16O28Na5S5 (colistin A component)
Molecular Weight: 1749.82 g/mol (colistin A component)
Structural Formula: