


Product Monograph - Depakene (BGP Pharma, Solution)
Recent Major Label Changes
| 3 Serious Warnings and Precautions Box, Male patients of reproductive potential | 2024-06 |
|---|---|
| 4.1 Dosing Considerations, Male patients of reproductive potential | 2024-06 |
| 7 Warnings and Precautions, Pregnancy Prevention Program | 2026-05 |
| 7 Warnings and Precautions, Endocrine and Metabolism: Weight gain | 2025-10 |
| 7 Warnings and Precautions, Reproductive Health: Teratogenic risk | 2024-06, 2025-10 |
| 7 Warnings and Precautions, Skin: Severe Cutaneous Adverse Reactions; and Angioedema | 2025-10 |
| 7 Warnings and Precautions, 7.1.1 Pregnancy, Female children/Women of childbearing potential/Pregnancy | 2024-06, 2026-05 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................. 2
Table of Contents ................................................................................................................. 2
Part 1: Healthcare Professional Information ......................................................................... 5
- 1.
Indications ..................................................................................................................... 5
1.1. Pediatrics ................................................................................................................ 5
1.2. Geriatrics ................................................................................................................. 5
- 2. Contraindications .......................................................................................................... 5
- 3. Serious Warnings and Precautions Box .......................................................................... 6
- 4.
Dosage and Administration ........................................................................................... 7
4.1. Dosing Considerations ............................................................................................ 7
4.2. Recommended Dose and Dosage Adjustment ........................................................ 8
4.4. Administration ........................................................................................................ 9
4.5. Missed Dose ............................................................................................................ 9
- 5. Overdose ....................................................................................................................... 9
- 6. Dosage Forms, Strengths, Composition, and Packaging ............................................... 10
- 7.
Warnings and Precautions ........................................................................................... 11
General ............................................................................................................................. 14
Carcinogenesis and Genotoxicity ...................................................................................... 14
Driving and Operating Machinery ..................................................................................... 14
Endocrine and Metabolism ............................................................................................... 15
Hematologic ..................................................................................................................... 17
Hepatic/Biliary/Pancreatic ................................................................................................ 18
Monitoring and Laboratory Tests ..................................................................................... 20
Musculoskeletal ................................................................................................................ 21
Neurologic ........................................................................................................................ 21
Psychiatric ......................................................................................................................... 22
Renal ………………………………………………………………………………………………………………………….23
Reproductive Health ......................................................................................................... 23
Skin ………………………………………………………………………………………………………………………….24
7.1. Special Populations ............................................................................................... 25
7.1.1. Pregnancy .................................................................................................... 25
7.1.2. Breastfeeding .............................................................................................. 31
7.1.3. Pediatrics ..................................................................................................... 31
7.1.4. Geriatrics ..................................................................................................... 31
- 8.
Adverse Reactions ....................................................................................................... 32
8.1. Adverse Reaction Overview .................................................................................. 32
8.2. Clinical Trial Adverse Reactions ............................................................................. 32
8.5. Post-Market Adverse Reactions ............................................................................ 35
- 9.
Drug Interactions ......................................................................................................... 36
9.1. Serious Drug Interactions ...................................................................................... 36
9.2. Drug Interactions Overview .................................................................................. 37
9.3. Drug-Behaviour Interactions ................................................................................. 37
9.4. Drug-Drug Interactions ......................................................................................... 37
9.5. Drug-Food Interactions ......................................................................................... 49
9.6. Drug-Herb Interactions ......................................................................................... 49
9.7. Drug-Laboratory Test Interactions ........................................................................ 49
- 10.
Clinical Pharmacology .................................................................................................. 49
10.1. Mechanism of Action ............................................................................................ 49
10.2. Pharmacodynamics ............................................................................................... 50
10.3. Pharmacokinetics .................................................................................................. 50
- 11. Storage, Stability, and Disposal ................................................................................... 51
Part 2: Scientific Information .............................................................................................. 52
- 13. Pharmaceutical Information ........................................................................................ 52
- 14.
Clinical Trials ............................................................................................................... 52
14.1. Clinical Trials by Indication .................................................................................... 52
- 16. Non-Clinical Toxicology ............................................................................................... 52
Patient Medication Information ......................................................................................... 57
Part 1: Healthcare Professional Information
1. Indications
DEPAKENE (valproic acid oral solution) is indicated for:
- use as sole or adjunctive therapy in the treatment of simple or complex absence seizures, including petit mal, and is useful in primary generalized seizures with tonic-clonic manifestations.
- use adjunctively in patients with multiple seizure types which include either absence or tonic-clonic seizures.
In accordance with the International Classification of Seizures, simple absence is defined as a very brief clouding of the sensorium or loss of consciousness (lasting usually 2 to 15 seconds), accompanied by certain generalized epileptic discharges without other detectable clinical signs. Complex absence is the term used when other signs are also present.
See 2 Contraindications and 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity for statement regarding serious or fatal hepatic dysfunction.
1.1. Pediatrics
Pediatrics (< 18 years of age): When DEPAKENE is used in children under the age of 2 years, it should be used with extreme caution and as a sole agent. Above the age of 2 years, experience in epilepsy has indicated that the incidence of fatal hepatotoxicity decreases considerably in progressively older patient groups (see 2 Contraindications; 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity; 7.1.3 Pediatrics).
1.2. Geriatrics
Geriatrics (≥ 65 years of age): The safety and efficacy of DEPAKENE in patients 65 years of age and over with epilepsy have not been established. Caution should be exercised in dose selection for geriatric patients, recognizing the more frequent hepatic and renal dysfunctions, and limited experience with DEPAKENE in this population (see 7.1.4 Geriatrics, 4.1 Dosing Considerations, Dosing in Elderly Patients and 10.3 Pharmacokinetics, Special populations and conditions, Geriatrics).
2. Contraindications
DEPAKENE is contraindicated in:
- Patients with known hypersensitivity to the drug (see 7 Skin, 8.2 Clinical Trial Adverse Reactions and 8.5 Post-Market Adverse Reactions), any ingredient in the formulation or component of the container. For a complete listing of ingredients, see 6 Dosage Forms, Strengths, Composition, and Packaging.
- Pregnant patients unless there is no suitable alternative treatment (see 3 Serious Warnings and Precautions Box, Female children/Women of childbearing potential/Pregnancy (Teratogenicity) and 7 Pregnancy Prevention Program, and 7.1.1 Pregnancy).
- Women of childbearing potential, unless the conditions of the Pregnancy Prevention Program are fulfilled (see 7 Pregnancy Prevention Program, and 7.1.1 Pregnancy).
- Patients with hepatic disease or significant hepatic dysfunction (see 3 Serious Warnings and Precautions Box, Hepatotoxicity and 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity).
- Patients known to have mitochondrial disorders caused by mutations in mitochondrial DNA polymerase γ (POLG; e.g., Alpers-Huttenlocher Syndrome) and children under two years of age who are suspected of having a POLG-related disorder (see 3 Serious Warnings and Precautions Box, Patients with Mitochondrial Disease and 7 Hepatic/Biliary/Pancreatic).
- Patients with known urea cycle disorders (see 7 Endocrine and Metabolism, Urea Cycle Disorders and Risk of Hyperammonemia).
- Patients with known systemic primary carnitine deficiency with uncorrected hypocarnitinemia (see 7 Endocrine and Metabolism, Patients at Risk of Hypocarnitinemia).
- Patients with known porphyria.
3. Serious Warnings and Precautions Box
- Female children/Women of childbearing potential/Pregnancy (Teratogenicity): DEPAKENE is contraindicated as treatment for epilepsy during pregnancy unless there is no suitable alternative treatment (see 2 Contraindications). DEPAKENE can cause fetal harm. Because of its high teratogenic potential and risk of developmental disorders in infants exposed in utero, DEPAKENE should not be used in female children or in women of childbearing potential unless alternative treatments are ineffective or not tolerated and unless the conditions of the Pregnancy Prevention Program are fulfilled. In women planning to become pregnant, all efforts should be made to switch to appropriate alternative treatment prior to conception (see 7 Pregnancy Prevention Program, and 7.1.1 Pregnancy: Female children/Women of childbearing potential/Pregnancy; and Risk in the neonate).
- Male patients of reproductive potential: A retrospective observational study indicated an increased risk of neurodevelopmental disorders (NDDs) in children born to men treated with valproate in the 3 months prior to conception, compared to those treated with lamotrigine or levetiracetam. Male patients should be advised of precautions that should be taken to mitigate the potential risk of fetal harm from paternal exposure to valproate prior to conception (see 7 Reproductive Health, Teratogenic risk).
- Hepatotoxicity: Hepatic failure resulting in fatalities has occurred in patients receiving DEPAKENE. These incidences usually occurred during the first 6 months of treatment with DEPAKENE. Caution should be observed when administering DEPAKENE to patients with a prior history of hepatic disease. Patients on multiple anticonvulsants, children, those with congenital metabolic disorders including mitochondrial disorders such as carnitine deficiency, urea cycle disorders, and polymerase γ (POLG) mutations (see 7 Hepatic/Biliary/Pancreatic: Serious or Fatal Hepatotoxicity), those with severe seizure disorders accompanied by mental retardation, and those with organic brain disease may be at particular risk. Experience has indicated that children under the age of 2 years are at a considerably increased risk of developing fatal hepatotoxicity, especially those on multiple anticonvulsants (see 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity and 8.1 Adverse Reaction Overview, Pediatric Population).
- Patients with Mitochondrial Disease: There is an increased risk of valproate-induced acute liver failure and resultant deaths in patients with hereditary neurometabolic syndromes caused by DNA mutations of the mitochondrial DNA Polymerase γ (POLG) gene (e.g., Alpers Huttenlocher Syndrome). DEPAKENE is contraindicated in patients known to have mitochondrial disorders caused by POLG mutations and children under two years of age who are clinically suspected of having a mitochondrial disorder (see 2 Contraindications). In patients over two years of age who are clinically suspected of having a hereditary mitochondrial disease, DEPAKENE should only be used after other anticonvulsants have failed. This older group of patients should be closely monitored during treatment with DEPAKENE for the development of acute liver injury with regular clinical assessments and serum liver testing. POLG mutation screening should be performed in accordance with current clinical practice (see 7 Hepatic/Biliary/Pancreatic, Patients with Mitochondrial Disease).
- Pancreatitis: Cases of life-threatening pancreatitis have been reported in both children and adults receiving DEPAKENE. Some of the cases have been described as hemorrhagic with a rapid progression from initial symptoms to death. Patients and guardians should be warned that abdominal pain, nausea, vomiting and/or anorexia can be symptoms of pancreatitis that require prompt medical attention. If pancreatitis is diagnosed, DEPAKENE should ordinarily be discontinued. Alternative treatment for the underlying medical condition should be initiated as clinically indicated. Some cases have occurred shortly after initial use as well as after several years of use (see 7 Hepatic/Biliary/Pancreatic, Pancreatitis).
4. Dosage and Administration
4.1. Dosing Considerations
Patients receiving combined antiepileptic therapy require careful monitoring when another agent is started, stopped or when the dose is altered (see 9 Drug Interactions).
As the dosage of DEPAKENE is titrated upward, blood concentrations of phenobarbital, and/or phenytoin may be affected (see 9 Drug Interactions).
Antiepileptic drugs (AEDs) should not be abruptly discontinued in patients in whom the drug is administered to prevent major seizures because of the strong possibility of precipitating status epilepticus with attendant hypoxia and threat to life.
Any changes in dosage and administration, or the addition or discontinuance of concomitant drugs, should ordinarily be accompanied by close monitoring of clinical status and valproate plasma concentrations (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels).
When changing therapy involving drugs known to induce hepatic microsomal enzymes (e.g., carbamazepine) or other drugs with valproate interactions, (see 9 Drug Interactions), it is advisable to monitor serum valproate concentrations.
Female children, women of childbearing potential and pregnant women with epilepsy
Valproic Acid treatment must be initiated and supervised by a specialist experienced in the management of epilepsy. Valproate should not be used in female children and women of childbearing potential unless other treatments are ineffective or not tolerated (see 2 Contraindications, 7 Pregnancy Prevention Program, and 7.1.1 Pregnancy).
Valproate is prescribed and dispensed according to the Valproate Pregnancy Prevention Program (see 7 Pregnancy Prevention Program).
In the exceptional circumstance when valproate is the only treatment option during pregnancy in epileptic women, valproic acid should preferably be prescribed as monotherapy and at the lowest effective dose, if possible as a prolonged release formulation. During pregnancy, the daily dose of immediate release formulations should be divided into at least two single doses.
Available data show an increased risk of major congenital malformations and neurodevelopmental disorders in the children of mothers treated during pregnancy with either valproate monotherapy or valproate polytherapy, compared to the population not exposed to valproate.
Male patients of reproductive potential
See 3 Serious Warnings and Precautions Box, Male patients of reproductive potential and 7 Reproductive Health, Teratogenic risk.
Male patients should be informed about the need for regular (at least annual) review of treatment by a specialist experienced in the management of epilepsy. The specialist should at least annually review whether valproate is the most suitable treatment for the patient. During this review, the specialist should ensure the male patient has acknowledged the risk and understood the precautions needed with valproate use (Annual Risk Acknowledgement Form).
Dosing in Elderly Patients:
Due to a decrease in unbound clearance of valproate and possibly a greater sensitivity to somnolence in the elderly, the starting dose should be reduced. Dosage should be increased more slowly and with regular monitoring for fluid and nutritional intake, dehydration, somnolence, urinary tract infection, and other adverse events. Dose reductions or discontinuation of DEPAKENE should be considered in patients with decreased food or fluid intake and in patients with excessive somnolence. The ultimate therapeutic dose should be achieved on the basis of clinical response (see 7.1.4 Geriatrics).
Dose-Related Adverse Events:
The frequency of adverse events (particularly elevated liver enzymes and thrombocytopenia) may be dose related. The probability of thrombocytopenia appears to increase significantly at total valproate concentration of ≥ 110 mcg/mL [females] or ≥ 135 mcg/mL [males] (see 7 Hematologic, Dose-related Adverse Events: Thrombocytopenia). Therefore, the benefit of improved therapeutic effect with higher doses should be weighed against the possibility of a greater incidence of adverse effects.
4.2. Recommended Dose and Dosage Adjustment
DEPAKENE is administered orally. The recommended initial dosage is 15 mg/kg/day, increasing at one-week intervals by 5 to 10 mg/kg/day until seizures are controlled or side effects preclude further increases.
The maximum recommended dosage is 60 mg/kg/day. When the total daily dose exceeds 250 mg, it should be given in a divided regimen (Table 1).
Table 1 - Initial Doses by Weight (based on 15 mg/kg/day)
| Weight | Total Daily Dose (mg) | Teaspoonful of Oral Solution | |||
| kg | lb | Dose 1 | Dose 2 | Dose 3 | |
| 10 to 24.9 | 22 to 54.9 | 250 | 0 | 0 | 1 |
| 25 to 39.9 | 55 to 87.9 | 500 | 1 | 0 | 1 |
| 40 to 59.9 | 88 to 131.9 | 750 | 1 | 1 | 1 |
| 60 to 74.9 | 132 to 164.9 | 1,000 | 1 | 1 | 2 |
| 75 to 89.9 | 165 to 197.9 | 1,250 | 2 | 1 | 2 |
Therapeutic Blood Levels:
A good correlation has not been established between daily dose, total serum valproate concentration and therapeutic effect. However, therapeutic valproate serum concentrations for most patients with epilepsy will range from 50 to 100 mcg/mL (350 to 700 micromole/L). Some patients may be controlled with lower or higher serum concentrations (see 7 Pregnancy Prevention Program, Contraception, 7 General, Interaction with Carbapenem Antibiotics, 7 Monitoring and Laboratory Tests, and 7 Reproductive Health, Estrogen-containing products).
Conversion from DEPAKENE to EPIVAL:
EPIVAL (divalproex sodium) enteric-coated tablets dissociate to the valproate ion in the gastrointestinal tract. EPIVAL tablets are uniformly and reliably absorbed, however, because of the enteric coating, absorption is delayed by an hour when compared to DEPAKENE.
In patients previously receiving DEPAKENE therapy, EPIVAL should be initiated at the same daily dosing schedule. After the patient is stabilized on EPIVAL, a dosing schedule of two or three times a day may be chosen in selected patients. Changes in the dosing of EPIVAL or concomitant medications should be accompanied by increased monitoring of plasma concentrations of valproate and other medications, as well as the patient’s clinical status.
4.4. Administration
DEPAKENE may be taken with or without food.
Patients who experience gastrointestinal irritation may benefit from administration of the drug with food or by a progressive increase of the dose from an initial low level. Co-administration of DEPAKENE with food should cause no clinical problems in the management of patients with epilepsy.
4.5. Missed Dose
The patient should not abruptly stop taking their medication because of the risk of increasing their seizures.
If the patient misses a dose, they should not try to make up for it by doubling up on their next dose. They should take their next regularly scheduled dose and try not to miss any more doses.
5. Overdose
Overdosage with DEPAKENE may result in somnolence, muscular hypotonia, hyporeflexia, miosis, impaired respiratory function, hypotension, metabolic acidosis, heart block, deep coma and circulatory collapse/shock. Cases of intracranial hypertension related to cerebral oedema have been reported. Fatalities have been reported; however, patients have recovered from valproate levels as high as 2,120 mcg/mL.
The presence of sodium content in the valproate formulations may lead to hypernatremia when taken in overdose.
In a reported case of overdosage with DEPAKENE after ingesting 36 g in combination with phenobarbital and phenytoin, the patient presented in deep coma. An electroencephalogram (EEG) recorded diffuse slowing, compatible with the state of consciousness. The patient made an uneventful recovery.
In overdose situations, the fraction of drug not bound to protein is high and hemodialysis or tandem hemodialysis plus hemoperfusion may result in significant removal of drug. The benefit of gastric lavage or emesis will vary with the time since ingestion. As valproic acid is absorbed very rapidly, gastric lavage may be of limited value. General supportive measures should be applied with particular attention to the prevention of hypovolemia and the maintenance of adequate urinary output.
In case of valproate overdose resulting in hyperammonemia, carnitine may be given through IV route to attempt to normalize ammonia levels.
Naloxone has been reported to reverse the CNS depressant effects of DEPAKENE overdosage. Because naloxone could theoretically also reverse the antiepileptic effects of DEPAKENE, it should be used with caution.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 2 – Dosage Forms, Strengths, Composition, and Packaging
* hydrochloric acid and sodium hydroxide are used for pH adjustment.
** methylparaben and propylparaben may cause allergic reactions (possibly delayed).
*** DEPAKENE oral solution contains 3 g of sucrose per 5 mL dose (see 7 Endocrine and Metabolism, Sucrose or Fructose Intolerance).
DEPAKENE (valproic acid) oral solution is a red-coloured liquid containing the equivalent of 250 mg valproic acid, as the sodium salt, per 5 mL (50 mg/mL) supplied in 240 mL bottles.
| Route of Administration | Dosage Form/ Strength/ Composition | Non-Medicinal Ingredients |
| oral | oral solution / 250 mg/5 mL | artificial cherry flavor, FD&C Red No. 40, glycerin, hydrochloric acid*, methylparaben**, propylparaben**, purified water, sodium hydroxide*, sorbitol, sucrose***, vanillin. |
7. Warnings and Precautions
Pregnancy Prevention Program:
Valproate has a high teratogenic potential and children exposed in utero to valproate have a high risk for major congenital malformations and neurodevelopmental disorders (see 7.1.1 Pregnancy).
DEPAKENE is contraindicated in the treatment of epilepsy during pregnancy unless no other suitable alternative can be found (see 2 Contraindications) and, in women of childbearing potential unless the conditions of the pregnancy prevention program are fulfilled.
Information on the Pregnancy Prevention Program including educational resources, as well as to report suspected embryo-fetal exposure to valproate, can be found at the following website: www.depakene.ca.
Conditions of Pregnancy Prevention Program
The prescriber must ensure that:
- individual circumstances are evaluated in each case and discussed with the patient. This is to guarantee the patient’s engagement and understanding of the therapeutic options together with the risks and the measures needed to mitigate the risks.
- the potential for pregnancy is assessed for all female patients.
- the patient understands and acknowledges the risks of major congenital malformations and neurodevelopmental disorders including the magnitude of these risks for children exposed to valproate in utero.
- the patient understands and acknowledges the risk of notably low birthweight for the gestational age (< 10th percentile) for children exposed to valproate in utero (see 7.1.1 Pregnancy, SGA (Small for Gestational Age) from in utero exposure).
- the patient understands the need to undergo pregnancy testing prior to initiation of treatment and during treatment with valproate as deemed necessary by the patient or treating physician. It is recommended that testing be done following a missed period, the failure of the selected method of contraception or as needed.
- the patient is counselled regarding contraception, and that the patient is capable of complying with the need to use effective and reliable contraception (see 7 Pregnancy Prevention Program, Contraception), without interruption during the entire duration of treatment with valproate.
- the patient understands the need for regular (at least annual) review of treatment by a specialist experienced in the management of epilepsy.
- the patient understands the need to consult her physician as soon as she is planning pregnancy to ensure timely discussion and switching to alternative treatment options prior to conception, and before contraception is discontinued.
- the patient understands the need to urgently consult her physician if she becomes pregnant.
- the patient has received the patient guide.
- the patient has acknowledged that she has understood the risks associated with valproate use and necessary precautions to be taken during treatment (Annual Risk Acknowledgement Form).
These conditions also apply to women who are not currently sexually active unless the prescriber considers that there are compelling and convincing reasons to indicate that there is no risk of pregnancy.
Pharmacist or other health care professional must ensure that:
- the patient card is provided with every valproate dispensing and that the patients understand its content.
- the patient is advised not to stop valproate treatment and to immediately contact a specialist in case of planned or suspected pregnancy.
Female Children
- The prescriber must ensure that parents/caregivers of female children understand the need to contact the specialist once the female child receiving valproate treatment experiences menarche.
- The prescriber must ensure that parents/caregivers of female children who have experienced menarche are provided with comprehensive information about the risks of major congenital malformations and neurodevelopmental disorders including the magnitude of these risks for children exposed to valproate in utero. The prescriber must also inform them about the risk of SGA (Small for Gestational Age) from in utero exposure. (See 7.1.1 Pregnancy).
- In patients who have experienced menarche, the prescribing specialist must reassess the need for continuing valproate therapy annually and consider alternative treatment options. If valproate is the only suitable treatment, the patient must use at least one effective and reliable method of contraception (preferably a user-independent form) or two complementary forms of contraception. Patient must also meet all other conditions of the Pregnancy Prevention Program. Every effort should be made by the specialist to switch the female children to alternative treatment before they reach adulthood.
Pregnancy Test
Pregnancy must be excluded before the start of treatment with valproate. Treatment must not be initiated in women of childbearing potential without a negative plasma pregnancy test result, confirmed by a health care provider, to rule out unintended use in pregnancy.
Contraception
Women of childbearing potential who are prescribed valproate must use at least one form of effective and reliable contraception (preferably a user-independent form) or two complementary forms of contraception without interruption during the entire duration of treatment. These patients must be provided with comprehensive information on pregnancy prevention and should be referred for contraceptive advice if they are not using effective contraception. Individual circumstances should be evaluated in each case, when choosing the contraception method involving the patient in the discussion, to guarantee her engagement and compliance with the chosen measures. Even if she has amenorrhea she must follow all the advice on effective and reliable contraception. At least 1 of these forms of contraception must be a primary form, which include tubal ligation, partner's vasectomy, intrauterine devices, birth control pills, and topical/injectable/insertable hormonal birth control products. Secondary or barrier forms of contraception include diaphragms, latex condoms, and cervical caps. A diaphragm and cervical cap must each be used with a spermicide.
Estrogen-containing hormonal contraceptives may result in decreased serum valproate levels and potentially lower valproate efficacy. Patients taking DEPAKENE should be advised not to start or stop such products without consulting their physician. Prescribers should monitor valproate serum levels and clinical response when initiating or discontinuing estrogen-containing products (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels; 7 Reproductive Health, Estrogen-containing products; 7.1.1 Pregnancy, Female children/Women of childbearing potential/Pregnancy; and 9.4 Drug-Drug Interactions, Table 3).
Annual Treatment Reviews by a Specialist
The specialist should, at least annually, review whether valproate is the most suitable treatment option for the patient. The specialist should discuss the Annual Risk Acknowledgement Form, at initiation of treatment and during each annual review and ensure that the patient has understood its content.
Pregnancy Planning
If a woman is planning to become pregnant, a specialist experienced in the management of epilepsy, must reassess valproate therapy and consider alternative treatment options. Every effort should be made to switch to appropriate alternative treatment prior to conception, and before contraception is discontinued (see 7.1.1 Pregnancy). If switching is not possible, the woman should receive further counselling regarding valproate risks for the unborn child to support her informed decision making regarding family planning.
In Case of Pregnancy
If a woman receiving valproate treatment becomes pregnant, she must be immediately referred to a specialist to re-evaluate treatment with valproate and consider alternative options. Patients with a valproate exposed pregnancy and their partners should be referred to a specialist experienced in pre-natal medicine for evaluation and counselling regarding the exposed pregnancy (see 7.1.1 Pregnancy).
Where available, prenatal diagnostic testing to detect neural tube and other defects, should be offered to pregnant women receiving DEPAKENE treatment.
Educational Materials
In order to assist healthcare professionals and patients in avoiding exposure to valproate during pregnancy, the Marketing Authorization Holder has provided educational materials to reinforce related warnings and provide guidance regarding use of valproate in women of childbearing potential and details of the Pregnancy Prevention Program. A patient guide and patient card should be provided to all women of childbearing potential receiving valproate treatment.
Educational materials are also available for healthcare professionals and male patients regarding use in males patients of reproductive potential.
A Risk Acknowledgement Form must be used at the time of treatment initiation and during each annual review of valproate treatment by the specialist, and when a woman is planning a pregnancy or has become pregnant. Specialist should reassess benefits and risks of valproate treatment and determine if the patient should continue to receive valproate therapy.
General
Antiepileptic drugs (AEDs), including DEPAKENE should be withdrawn gradually to minimize the potential for seizures or increased seizure frequency (see 4.2 Recommended Dose and Dosage Adjustment).
Interaction with Carbapenem Antibiotics
Carbapenem antibiotics (ertapenem, imipenem, meropenem, doripenem) can reduce serum valproic acid concentrations to sub-therapeutic levels. This can result in loss of seizure control in epileptic patients or loss of efficacy in non-epileptics. In some cases of co-administration in epileptic patients, breakthrough seizures have occurred. Increasing valproic acid dose may not be sufficient to overcome this interaction. If co-administration is essential, serum valproic acid concentrations should be monitored daily after initiating carbapenem therapy. Alternative antibacterial or anticonvulsant therapy should be considered if serum valproic acid concentrations drop significantly or seizure control deteriorates (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels; 9.4 Drug-Drug Interactions, Table 3).
Effects of Valproate on HIV and CMV Viruses Replication
There are in vitro studies that suggest valproate stimulates the replication of the HIV (Human Immunodeficiency Virus) and CMV (Cytomegalovirus) viruses under certain experimental conditions. The clinical relevance of these in vitro data is unknown. Additionally, the relevance of these in vitro findings is uncertain for patients receiving maximally suppressive antiretroviral therapy. Nevertheless, these data should be borne in mind when interpreting the results from regular monitoring of the viral load in HIV infected patients receiving valproate or when following CMV infected patients clinically.
Carcinogenesis and Genotoxicity
Long-term animal toxicity studies indicate that valproic acid is a weak carcinogen or promoter in rats and mice (see 16 Carcinogenicity; and Genotoxicity). The significance of these findings for humans is not known.
Driving and Operating Machinery
DEPAKENE may produce central nervous system (CNS) depression, especially when combined with other CNS depressants, including but not limited to alcohol, other antiepileptic medications, and antipsychotics (see 9.4 Drug-Drug Interactions, Table 3).
Patients should be cautioned not to engage in hazardous occupations, such as driving a car, operating dangerous machinery or engaging in activities that require alertness or physical coordination until it is known that they do not become drowsy from the drug.
Endocrine and Metabolism
Urea Cycle Disorders and Risk of Hyperammonemia
DEPAKENE is contraindicated in patients with known urea cycle disorders. Hyperammonemic encephalopathy, sometimes fatal, has been reported following initiation of DEPAKENE in patients with urea cycle disorders, a group of uncommon genetic abnormalities, particularly ornithine transcarbamylase deficiency. Prior to initiation of DEPAKENE, evaluation for urea cycle disorders (UCD) should be considered in the following patients:
- those with a history of unexplained encephalopathy or coma, encephalopathy associated with protein load, pregnancy-related or postpartum encephalopathy, unexplained mental retardation, or history of elevated plasma ammonia or glutamine;
- those with signs and symptoms of UCD, for example, cyclical vomiting and lethargy, episodic extreme irritability, ataxia, low blood urea nitrogen (BUN), protein avoidance;
- those with a family history of UCD or a family history of unexplained infant deaths (particularly males);
- those with other signs or symptoms of UCD. Patients receiving DEPAKENE who develop symptoms of unexplained hyperammonemic encephalopathy should receive prompt treatment (including discontinuation of DEPAKENE) and be evaluated for underlying urea cycle disorders (see 2 Contraindications and 7 Endocrine and Metabolism: Hyperammonemia; Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin; Patients at Risk of Hypocarnitinemia; and Hepatic/Biliary/Pancreatic: Serious or Fatal Hepatotoxicity).
Hyperammonemia
Hyperammonemia has been reported in association with DEPAKENE and may be present despite normal liver function tests. In patients who develop unexplained lethargy and vomiting or changes in mental status, hyperammonemic encephalopathy should be considered as a possible cause and serum ammonia level should be measured. Hyperammonemia should also be considered in patients with hypothermia (see 7 Endocrine and Metabolism: Hypothermia). If serum ammonia is increased, DEPAKENE should be discontinued. Appropriate interventions for treatment of hyperammonemia should be initiated, and such patients should undergo investigation for underlying urea cycle disorders (see 2 Contraindications and 7 Endocrine and Metabolism: Urea Cycle Disorders and Risk of Hyperammonemia; and Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin) or other metabolic disorders (see 7 Endocrine and Metabolism: Patients at Risk of Hypocarnitinemia; and Hepatic/Biliary/Pancreatic: Serious or Fatal Hepatotoxicity).
Asymptomatic elevations of serum ammonia are more common and, when present, require close monitoring of serum ammonia levels. If the elevation persists, discontinuation of DEPAKENE should be considered.
Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin
Concomitant administration of topiramate, acetazolamide, phenobarbital or phenytoin and DEPAKENE has been associated with hyperammonemia with or without encephalopathy in patients who have tolerated either drug alone. Clinical symptoms of hyperammonemic encephalopathy often include acute alterations in level of consciousness and/or cognitive function with lethargy or vomiting. Hypothermia can also be a manifestation of hyperammonemia (see 7 Endocrine and Metabolism, Hypothermia). In most cases, symptoms and signs abated with discontinuation of either drug.
It is not known if topiramate, acetazolamide, phenobarbital or phenytoin monotherapy is associated with hyperammonemia.
Patients with inborn errors of metabolism or reduced hepatic mitochondrial activity may be at an increased risk for hyperammonemia with or without encephalopathy. Although not studied, an interaction of topiramate, acetazolamide, phenobarbital or phenytoin and DEPAKENE may exacerbate existing defects or unmask deficiencies in susceptible persons (see 2 Contraindications and 7 Endocrine and Metabolism: Urea Cycle Disorders and Risk of Hyperammonemia; and Hyperammonemia).
Hypothermia
Hypothermia, defined as an unintentional drop in core body temperature to < 35°C (95°F), has been reported in association with DEPAKENE both in conjunction with and in the absence of hyperammonemia. This adverse reaction can also occur in patients using concomitant topiramate with DEPAKENE after starting topiramate treatment or after increasing the daily dose of topiramate (see 7 Endocrine and Metabolism: Hyperammonemia; and Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin; and 9.4 Drug-Drug Interactions, Table 3). Hypothermia may be manifested by a variety of clinical abnormalities including, lethargy, confusion, coma and significant alterations in other major organ systems such as the cardiovascular and respiratory systems. Clinical management and assessment should include examination of blood ammonia levels. Consideration should be given to stopping DEPAKENE in patients who develop hypothermia (see 7 Endocrine and Metabolism: Hyperammonemia; and Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin).
Patients at Risk of Hypocarnitinemia
Valproate administration may trigger occurrence or worsening of hypocarnitinemia that can result in hyperammonemia (that may lead to hyperammonemic encephalopathy). Other symptoms such as liver toxicity, hypoketotic hypoglycaemia, myopathy including cardiomyopathy, rhabdomyolysis, and Fanconi syndrome have been observed with use of valproate, mainly in patients with risk factors for hypocarnitinemia or pre-existing hypocarnitinemia. Valproate may decrease carnitine blood and tissue levels and therefore impair mitochondrial metabolism including the mitochondrial urea cycle. There may be a higher risk for symptomatic hypocarnitinemia with valproate treatment for pediatric patients, patients with metabolic disorders including mitochondrial disorders related to carnitine (see 7 Endocrine and Metabolism: Urea Cycle Disorders and Risk of Hyperammonemia; and Hepatic/Biliary/Pancreatic: Patients with Mitochondrial Disease), impaired carnitine nutritional intake, or concomitantly using pivalate-conjugated medicines or other antiepileptics (see 9 Drug Interactions).
Patients should be warned to report immediately any signs of hyperammonemia such as ataxia, impaired consciousness or vomiting for further investigation (see 7 Endocrine and Metabolism: Hyperammonemia). Carnitine supplementation may be considered when symptoms of hypocarnitinemia are observed.
Valproate is contraindicated in patients with known systemic primary carnitine deficiency with uncorrected hypocarnitinemia. Patients with known systemic primary carnitine deficiency and corrected for hypocarnitinemia should be treated with valproate only if there is no suitable therapeutic alternative. In these patients, close monitoring for recurrence of hypocarnitinemia should be implemented.
Patients with an underlying carnitine palmitoyltransferase (CPT) type II deficiency should be warned of the greater risk of rhabdomyolysis when taking valproate. Carnitine supplementation may be considered in these patients (see 5 Overdose, 7 Musculoskeletal, and 8 Adverse Reactions).
Sucrose or Fructose Intolerance
DEPAKENE oral solution contains sucrose, which may be harmful to the teeth. Patients with rare hereditary problems of fructose intolerance, glucose-galactose malabsorption or sucrase-isomaltase insufficiency should not take this medicine.
When prescribing to diabetic patients, the sucrose content should be taken into account (see 6 Dosage Forms, Strengths, Composition, and Packaging).
DEPAKENE oral solution contains sorbitol. Patients with rare hereditary problems of fructose intolerance should not take this medicine.
Weight gain
Patients should be warned of the risk of weight gain at the initiation of therapy (see 8 Adverse Reactions) and appropriate strategies should be adopted to minimize the risk.
Hematologic
Valproate can adversely effect several hematologic parameters and monitoring is recommended (see 7 Monitoring and Laboratory Tests; 8.2 Clinical Trial Adverse Reactions; 8.5 Post-Market Adverse Reactions).
Thrombocytopenia
There have been reported post-marketing cases of coagulation abnormalities in patients of all ages receiving valproate therapy. These include thrombocytopenia, hypofibrinogenemia, and/or decrease in other coagulation factors, which can lead to bleeding and other complications, especially in the cases of decrease in factors VII, VIII and XIII. These abnormalities may not necessarily be dose-dependent. Some of the hemorrhage manifestations may include mucosal bleeding (e.g., menorrhagia, epistaxis, hematuria, melena), easy-bruising, soft-tissue hematoma, hemarthrosis, and intracranial hemorrhage. Caution should be taken in patients taking valproate and anticoagulants and in cases of injury or surgery to avoid life-threatening or fatal bleeding. Coagulation abnormalities that develop in pregnant woman may result in hemorrhagic complications in the neonate (see 7.1.1 Pregnancy, Coagulation Abnormalities and Risk in the Neonate).
Because of reports of thrombocytopenia and inhibition of the second phase of platelet aggregation, and abnormal coagulation parameters (e.g., low fibrinogen), platelet counts and coagulation tests are recommended before initiating therapy and at periodic intervals. It is recommended that patients receiving DEPAKENE be monitored for platelet count and coagulation parameters prior to planned surgery (see 7 Monitoring and Laboratory Tests). Clinical evidence of hemorrhage, bruising or a disorder of hemostasis/coagulation is an indication for reduction of DEPAKENE dosage or withdrawal of therapy (see 7 Hematologic, Dose-related Adverse Events: Thrombocytopenia).
Dose-related Adverse Events: Thrombocytopenia
The frequency of adverse effects thrombocytopenia (particularly elevated liver enzymes and thrombocytopenia) may be dose-related. In a clinical trial of EPIVAL (divalproex sodium) as monotherapy in patients with epilepsy, 34/126 patients (27%) receiving approximately 50 mg/kg/day on average, had at least one value of platelets ≤ 75 x 109/L. Approximately half of these patients had treatment discontinued with return of platelet counts to normal. In the remaining patients, platelet counts normalized with continued treatment. In this study, the probability of thrombocytopenia appeared to increase significantly at total valproate concentrations of ≥ 110 mcg/mL (females) or ≥ 135 mcg/mL (males).
In addition, the findings from a crossover clinical trial conducted with EPIVAL ER (divalproex sodium extended-release tablets), in 44 epilepsy patients, indicate that the frequency of treatment-emergent mild thrombocytopenia (platelet count between 100 to150 x 109/L) was significantly higher after 12 weeks of treatment with EPIVAL ER than after 12 weeks of treatment with EPIVAL (7 versus 3 low counts, respectively).
The therapeutic benefit which may accompany the higher doses should therefore be weighed against the possibility of a greater incidence of adverse events.
Hepatic/Biliary/Pancreatic
Serious or Fatal Hepatotoxicity
Hepatic failure resulting in fatalities has occurred in patients receiving DEPAKENE and its derivatives. These events usually have occurred during the first 6 months of treatment with DEPAKENE. Caution should be observed when administering DEPAKENE to patients with a prior history of hepatic disease. Patients on multiple anticonvulsants, children, those with congenital metabolic disorders including mitochondrial disorders such as carnitine deficiency, urea cycle disorders, POLG mutations (see 2 Contraindications; 3 Serious Warnings and Precautions Box; 7 Endocrine and Metabolism: Urea Cycle Disorders and Risk of Hyperammonemia, Patients at Risk of Hypocarnitinemia and, Hepatic/Biliary/Pancreatic: Patients with Mitochondrial Disease), those with severe seizure disorders accompanied by mental retardation, and those with organic brain disease may be at particular risk.
Experience has indicated that children under the age of 2 years are at a considerably increased risk of developing fatal hepatotoxicity, especially those on multiple anticonvulsants, those with congenital metabolic disorders, those with severe seizure disorders accompanied by mental retardation, and those with organic brain disease. The risk in this age group decreased considerably in patients receiving DEPAKENE as monotherapy. Similarly, patients aged
3 to 10 years were at somewhat greater risk if they received multiple anticonvulsants than those who received only DEPAKENE. Above the age of 2 years, experience in epilepsy has indicated that the incidence of fatal hepatotoxicity decreases considerably in progressively older patients. No deaths have been reported in patients over 10 years of age who received DEPAKENE alone.
If DEPAKENE is to be used in children 2 years old or younger, it should be used with extreme caution and as a sole agent. In this patient population, concomitant use of salicylates and DEPAKENE should be avoided due to the risk of liver toxicity. The benefits of therapy should be weighed against the risk (see 7.1.3 Pediatrics).
Serious or fatal hepatotoxicity may be preceded by non-specific symptoms such as loss of seizure control, malaise, weakness, lethargy, facial edema, anorexia, and vomiting. Patients should be monitored closely for appearance of these symptoms. Patients and parents should be instructed to report such symptoms. Because of the non-specific nature of some of the early signs, hepatotoxicity should be suspected in patients who become unwell, other than through obvious cause, while taking DEPAKENE.
Liver function tests should be performed prior to therapy and at frequent intervals thereafter especially during the first 6 months of therapy, especially in patients at risk as described above (see 7 Monitoring and Laboratory Tests; 9.4 Drug-Drug Interactions, Table 3). However, physicians should not rely totally on serum biochemistry since these tests may not be abnormal in all instances, but should also consider the results of careful interim medical history and physical examination.
In high-risk patients, it might also be useful to monitor serum fibrinogen and albumin for decreases in concentration and serum ammonia for increases in concentration. If changes occur, DEPAKENE should be discontinued. Dosage should be titrated to and maintained at the lowest dose consistent with optimal seizure control.
The drug should be discontinued immediately in the presence of significant hepatic dysfunction, suspected or apparent. In some cases, hepatic dysfunction has progressed in spite of discontinuation of drug. The frequency of adverse effects (particularly elevated liver enzymes and thrombocytopenia) may increase with increasing dose. The therapeutic benefit which may accompany the higher doses should therefore be weighed against the possibility of a greater incidence of adverse effects (see 2 Contraindications).
Patients with Mitochondrial Disease
Valproate induced acute liver failure and liver-related deaths have been reported in patients with hereditary neurometabolic syndromes caused by mutations in the gene for mitochondrial DNA polymerase γ (POLG) (e.g., Alpers-Huttenlocher Syndrome) at a higher rate than those without these syndromes (see 2 Contraindications).
POLG-related disorders should be suspected in patients with a family history or suggestive symptoms of a POLG-related disorder, including but not limited to unexplained encephalopathy, refractory epilepsy (focal, myoclonic), status epilepticus at presentation, developmental delays, psychomotor regression, axonal sensorimotor neuropathy, myopathy cerebellar ataxia, opthalmoplegia, or complicated migraine with occipital aura. POLG mutation testing should be performed in accordance with current clinical practice for the diagnostic evaluation of such disorders. The A467T and W748S mutations are present in approximately 2/3 of patients with autosomal recessive POLG-related disorders.
In patients over two years of age who are clinically suspected of having a hereditary mitochondrial disease, DEPAKENE should only be used after other anticonvulsants have failed. This older group of patients should be closely monitored during treatment with DEPAKENE for the development of acute liver injury with regular clinical assessments and liver function test monitoring.
In the presence of significant hepatic dysfunction, suspected or apparent, DEPAKENE should be discontinued and alternative therapy initiated. In some cases, hepatic dysfunction has progressed in spite of discontinuation of the drug (see 2 Contraindications; 3 Serious Warnings and Precautions Box; and 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity).
Pancreatitis
Cases of life-threatening pancreatitis have been reported in both children and adults receiving DEPAKENE. Some of the cases have been described as hemorrhagic with a rapid progression from initial symptoms to death. Some cases have occurred shortly after initial use as well as after several years of use. The rate based upon the reported cases exceeds that expected in the general population and there have been cases in which pancreatitis recurred after rechallenge with DEPAKENE. In clinical trials, there were 2 cases of pancreatitis without alternative etiology in 2,416 patients, representing 1,044 patient-years experience. Patients and guardians should be warned that abdominal pain, nausea, vomiting, and/or anorexia can be symptoms of pancreatitis that require prompt medical evaluation. If pancreatitis is diagnosed, DEPAKENE should ordinarily be discontinued. Alternative treatment for the underlying medical condition should be initiated as clinically indicated.
Monitoring and Laboratory Tests
Pregnancy test
Treatment must not be initiated in women of childbearing potential without a negative plasma pregnancy test result, confirmed by a health care provider, to exclude unintended use in pregnancy (see 2 Contraindications; 3 Serious Warnings and Precautions Box, Female children/Women of childbearing potential/Pregnancy (Teratogenicity); 7 Pregnancy Prevention Program; 7.1.1 Pregnancy).
Liver function
Evaluate liver function prior to initiation of treatment and at frequent intervals during the first 6 months of treatment, especially in patients at risk (see 3 Serious Warnings and Precautions Box, Hepatotoxicity; 7 Hepatic/Biliary/Pancreatic).
Blood tests (e.g., complete blood count including platelet count, coagulation parameters)
Valproate treatment is associated with hematologic adverse effects (see 7 Hematologic; 8.2 Clinical Trial Adverse Reactions). Evaluate hematologic parameters prior to initiation of treatment, at periodic intervals during treatment, before surgery, in cases of spontaneous bruising or bleeding and, during pregnancy (see 7 Hematologic; 7.1.1 Pregnancy, Coagulation Abnormalities).
POLG mutation testing
Consider POLG mutation testing prior to initiation of treatment with valproate in accordance with current clinical practice for patients with a family history or symptoms suggestive of a POLG-related disorder (see 2 Contraindications; 3 Serious Warnings and Precautions Box, Patients with Mitochondrial Disease; and 7 Hepatic/Biliary/Pancreatic, Patients with Mitochondrial Disease).
Monitoring Valproate Concentrations
See 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels.
Since DEPAKENE may interact with concurrently administered drugs which are capable of enzyme induction, periodic plasma concentration determinations of valproate and concomitant drugs are recommended during the early course of therapy and whenever enzyme-inducing drugs are introduced or withdrawn (see 9 Drug Interactions).
Protein binding of valproate is reduced in the elderly, in patients with renal impairment, and in the presence of other drugs (e.g., acetylsalicylic acid). Accordingly, measurements of plasma levels of valproate may be misleading in these patients, as actual drug exposure may be higher than measured values (see 7.1.4 Geriatrics; 7 Hepatic/Biliary/Pancreatic; Endocrine and Metabolism, Hyperammonemia; Hematologic, Thrombocytopenia; and 9.4 Drug-Drug Interactions, Table 3).
Musculoskeletal
- Rhabdomyolysis
Rare cases of rhabdomyolysis, independent of neuroleptic malignant syndrome, have been reported to occur in patients treated with DEPAKENE (see 8.2 Clinical Trial Adverse Reactions). Cases have included renal failure and fatalities.
Patients should be carefully monitored for muscle pain, tenderness or weakness, particularly if accompanied by malaise or fever or tea-coloured urine. Blood creatine phosphokinase (CPK) levels should be assessed in patients experiencing these symptoms and DEPAKENE therapy should be discontinued if markedly elevated CPK levels are measured or if the patient develops signs and symptoms indicative of rhabdomyolysis.
Caution should be exercised in prescribing DEPAKENE to patients with predisposing/risk factors, including: prior history of muscular disorders such as CPT II deficiency (carnitine palmitoyltransferase type II) (see 7 Endocrine and Metabolism: Patients at Risk of Hypocarnitinemia); uncontrolled hypothyroidism; hepatic or renal impairment; and concomitant medications that are known to be associated with rhabdomyolysis (e.g., statins, antipsychotics, diuretics, some antidepressants).
Neurologic
Brain Atrophy
There have been post-marketing reports of reversible and irreversible cerebral and cerebellar atrophy with neurological symptoms, in children, adults, and the elderly, receiving valproate therapy. A temporal relationship between valproate therapy and the development of cerebral atrophy and associated signs and symptoms was also demonstrated. In some cases, symptoms disappeared after valproate discontinuation but patients recovered with permanent sequelae (see 8.2 Clinical Trial Adverse Reactions). The motor and cognitive functions of patients on valproate should be routinely monitored and drug should be discontinued in the presence of suspected or apparent signs of brain atrophy.
Neurological Problems in Children after in utero Exposure to Valproate
Reports of cerebral atrophy with various forms of neurological problems including cognitive developmental delays, psychomotor impairment and decreased IQ scores have been reported in children who were exposed in utero to valproate products (see 7.1.1 Pregnancy: Female children/Women of childbearing potential/Pregnancy; and Risk in the Neonate).
Aggravated convulsions
As with other antiepileptic drugs, some patients may experience a worsening of convulsion frequency and severity, or the onset of new types of convulsions with valproate. Post-marketing reports of serious aggravated seizures have been reported for valproic acid including status epilepticus and death. In case of aggravated convulsions, patients should be advised to consult their physician immediately.
Psychiatric
Suicidal Behaviour and Ideation
Suicidal ideation and behaviour have been reported in patients treated with antiepileptic agents in several indications.
All patients treated with antiepileptic drugs (AEDs), irrespective of indication, should be monitored for signs of suicidal ideation and behaviour and appropriate treatment should be considered. Patients (and caregivers of patients) should be advised to seek medical advice should signs of suicidal ideation or behaviour emerge.
An FDA meta-analysis of randomized placebo controlled trials, in which AEDs were used for various indications, has shown a small increased risk of suicidal ideation and behaviour in patients treated with these drugs. The mechanism of this risk is not known.
There were 43,892 patients treated in the placebo controlled clinical trials that were included in the meta-analysis. Approximately 75% of patients in these clinical trials were treated for indications other than epilepsy and, for the majority of non-epilepsy indications the treatment (AED or placebo) was administered as monotherapy. Patients with epilepsy represented approximately 25% of the total number of patients treated in the placebo controlled clinical trials and, for the majority of epilepsy patients, treatment (AED or placebo) was administered as adjunct to other antiepileptic agents (i.e., patients in both treatment arms were being treated with one or more AED). Therefore, the small increased risk of suicidal ideation and behaviour reported from the meta-analysis (0.43% for patients on AEDs compared to 0.24% for patients on placebo) is based largely on patients that received monotherapy treatment (AED or placebo) for non-epilepsy indications. The study design does not allow an estimation of the risk of suicidal ideation and behaviour for patients with epilepsy that are taking AEDs, due both to this population being the minority in the study, and the drug-placebo comparison in this population being confounded by the presence of adjunct AED treatment in both arms.
Behavioural Disorders
There have been post-marketing reports of behavioural disorders, including aggression, agitation, abnormal behaviour, psychomotor hyperactivity, disturbance in attention, and learning disorders. Although patients of all ages were affected, including the elderly, a large number of cases were reported in children (see 8.1 Adverse Reaction Overview, Pediatric Population). There was no clear trend with respect to valproate dose. In some cases, patients improved or recovered following valproate discontinuation. Attention deficit hyperactivity disorder (ADHD), Autism spectrum disorders and developmental delay have been reported from in utero exposure (see 7.1.1 Pregnancy).
Renal
Renal Impairment
Renal impairment is associated with an increase in the unbound fraction of valproate. In several studies, the unbound fraction of valproate in plasma from renally impaired patients was approximately double that for subjects with normal renal function. Accordingly, monitoring of total concentrations in patients with renal impairment may be misleading since free concentrations may be substantially elevated whereas total concentrations may appear to be normal. Hemodialysis in renally impaired patients may remove up to 20% of the circulating valproate.
Reproductive Health
Fertility
Amenorrhea, polycystic ovaries and increased testosterone levels have been reported in women using valproate.
The effect of DEPAKENE on the development of the testis in humans is unknown (see 16 Reproductive and developmental toxicology, Fertility for results in animal studies). Valproate administration has been associated with reduced semen quality in humans and thus may impair fertility in men (see 8.5 Post-Market Adverse Reactions). Discontinuation or dose reduction of valproate may be associated with the improvement of impaired male fertility markers and could be linked with successful conception, as observed in some case reports.
Teratogenic risk
- In utero exposure to valproate
See 2 Contraindications; 3 Serious Warnings and Precautions Box, Female children/Women of childbearing potential/Pregnancy (Teratogenicity); 7 Pregnancy Prevention Program; 7 Reproductive Health, Fertility; 7.1.1. Pregnancy; 16 Reproductive and developmental toxicology.
- Risk to children of fathers treated with valproate
A retrospective observational study on electronic medical records in 3 European Nordic countries indicates an increased risk of neuro-developmental disorders (NDDs) in children (from 0 to 11 years old) born to men treated with valproate in the 3 months prior to conception, compared to those treated with lamotrigine or levetiracetam.
The adjusted cumulative risk of NDDs ranged between 4.0% to 5.6% in the valproate group versus between 2.3% to 3.2% in the composite lamotrigine/levetiracetam monotherapy group. The pooled adjusted hazard ratio (HR) for NDDs overall obtained from the meta-analysis of the datasets was 1.50 (95% CI: 1.09-2.07). Due to study limitations, it is not possible to determine which of the studied NDD subtypes (autism spectrum disorder, intellectual disability, communication disorder, attention deficit/hyperactivity disorder, movement disorders) contributes to the overall increased risk of NDDs.
Despite study limitations, by way of precautions, the prescriber should inform the male patients of this potential risk. The prescribers should discuss with the patient, the need for effective contraception, including for the female partner, while using valproate and for 3 months after stopping the treatment. The risk to children born to men stopping valproate at least 3 months prior to conception (i.e., allowing a new spermatogenesis without valproate exposure) is not known.
The male patient should be advised:
- not to donate sperm during treatment and for 3 months after stopping the treatment;
- of the need to consult his doctor to discuss alternative treatment options, as soon as he is planning to father a child, and before discontinuing contraception;
- that he and his female partner should contact their doctor for counseling in case of pregnancy if he used valproate within 3 months prior to conception.
The male patient should also be informed about the need for regular (at least annual) review of treatment by a specialist experienced in the management of epilepsy. The specialist should at least annually review whether valproate is the most suitable treatment for the patient. During this review, the specialist should ensure the male patient has acknowledged the risk and understood the precautions needed with valproate use (Annual Risk Acknowledgement Form).
Educational materials are available for healthcare professionals and male patients. A patient guide and a patient card should be provided to all men of reproductive potential using valproate.
- Estrogen-containing products
Valproate does not reduce the efficacy of hormonal contraceptives.
However, estrogen-containing products, including estrogen-containing hormonal contraceptives, may increase the clearance of valproate, which may result in decreased serum concentration of valproate and potentially decreased valproate efficacy. Patients taking DEPAKENE should be advised not to start or stop estrogen-containing products (including oral contraceptives) without consulting their physician. Prescribers should monitor clinical response (seizure control) when initiating, or discontinuing estrogen-containing products. Consider monitoring of valproate serum levels (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels; 9.4 Drug-Drug Interactions, Table 3).
Skin
- Severe Cutaneous Adverse Reactions
Serious and sometimes fatal Severe Cutaneous Adverse Reactions (SCARs) including Stevens-Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN), Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), and erythema multiforme (EM) have been reported with valproate treatment (see 8.2 Clinical Trial Adverse Reactions).
Patients should be informed about the signs and symptoms of serious skin manifestations and monitored closely. Valproate should be discontinued at the first sign of a rash, unless the rash is clearly not drug related. If a rash occurs, the patient should be evaluated for signs and symptoms of DRESS (see 7 Skin, Drug Reaction with Eosinophilia and Systemic Symptoms). If signs or symptoms suggestive of SCARs are observed, prompt assessment is needed and treatment must be discontinued if diagnosis of SCARs is confirmed.
- Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)
Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), also known as multi-organ hypersensitivity reactions, has been reported rarely in close temporal association to the initiation of DEPAKENE therapy in adult and pediatric patients (median time to detection 21 days; range 1 to 40). Although there have been a limited number of reports, many of these cases resulted in hospitalization and in a few cases death has been reported. Signs and symptoms of this disorder were diverse; however, patients typically, although not exclusively, presented with fever and rash associated with other organ system involvement. Other associated manifestations may include lymphadenopathy, hepatitis, liver function test abnormalities, hematological abnormalities (e.g., eosinophilia, thrombocytopenia, neutropenia), pruritus, nephritis, oliguria, hepato-renal syndrome, arthralgia, and asthenia. Because the disorder is variable in its expression, other organ system symptoms and signs, not noted here may occur. If this reaction is suspected, DEPAKENE should be discontinued and an alternative treatment started. Although the existence of cross sensitivity with other drugs that produce this syndrome is unclear, the experience amongst drugs associated with multi-organ hypersensitivity would indicate this to be a possibility.
- Serious Skin Reactions during concomitant use of lamotrigine
Serious skin reactions (such as Stevens-Johnson syndrome and Toxic Epidermal Necrolysis) have been reported with concomitant lamotrigine and DEPAKENE administration. Valproate reduces the plasma clearance and prolongs the elimination half-life of lamotrigine (see 9.4 Drug-Drug Interactions, Table 3, Lamotrigine), which may increase the risk of serious skin reactions. The dose of lamotrigine should be reduced when co-administered with DEPAKENE. See the lamotrigine Product Monograph for details on lamotrigine dosage adjustments with concomitant DEPAKENE administration.
- Angioedema
Angioedema has been reported in patients treated with valproate in the post-marketing setting. Valproate should be discontinued immediately if symptoms of angioedema such as facial, perioral, or upper airway swelling occur. Valproate should be discontinued permanently if a clear alternative etiology for the reaction cannot be established (see 2 Contraindications; 8.5 Post-Market Adverse Reactions).
7.1. Special Populations
7.1.1. Pregnancy
Female children/Women of childbearing potential/Pregnancy:
DEPAKENE can cause fetal harm when administered to pregnant women.
DEPAKENE use during pregnancy, as adjunctive therapy or as monotherapy, is associated with an increased risk of severe birth defects such as neural tube defects (e.g., spina-bifida), craniofacial defects, cleft palate, cardiovascular malformations (e.g., atrial septal defect), hypospadias, and neurodevelopmental disorders, compared to the population not exposed to valproate. In some cases, fatal outcomes have been reported (see 7.1.1 Pregnancy, Birth Defects from in utero exposure; Risk of Neurological Problems from in utero exposure). Tests to detect neural tube and other defects using current accepted procedures should be considered a part of routine prenatal care in pregnant women receiving DEPAKENE (see 7.1.1 Pregnancy, Pregnant Women).
Treatment of epilepsy
- Valproate is contraindicated during pregnancy, unless there is no suitable alternative treatment.
- Valproate is contraindicated in women of childbearing potential, unless alternative treatments are ineffective or not tolerated and unless the conditions of the pregnancy prevention programme are fulfilled. Women of childbearing potential must use at least one effective and reliable method of contraception (preferably a user-independent form) or two complementary forms of contraception during treatment with DEPAKENE (see 2 Contraindications; 7 Pregnancy Prevention Program).
The benefit and risk should be carefully re-assessed, at least annually, at puberty, and urgently when a woman of childbearing potential plans a pregnancy or becomes pregnant. Since some of the congenital malformations occur in the first trimester of pregnancy before many women know that they are pregnant, all women of childbearing potential should be informed of the potential hazard to the fetus from exposure to DEPAKENE.
Pregnancy Registry
Pregnant patients taking DEPAKENE should be encouraged to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves. Information on the registry can also be found at the following website: http://www.aedpregnancyregistry.org/.
Pregnancy Prevention Program
See 7 Pregnancy Prevention Program.
Further information on the Pregnancy Prevention Program including educational resources, as well as to report suspected embryo-fetal exposure to valproate, can be found at the following website: www.depakene.ca.
If a woman is planning a pregnancy:
A specialist experienced in the management of epilepsy, must reassess valproate therapy and consider alternative treatment options. Every effort should be made to switch to appropriate alternative treatment prior to conception, and before contraception is discontinued (see 7 Pregnancy Prevention Program; 7.1.1. Pregnancy: Female children/Women of childbearing potential/Pregnancy; and Risk in the Neonate). If switching is not possible, the woman should receive further counselling regarding the valproate risks for the unborn child to support her informed decision making regarding family planning.
Pregnant Women
Valproate as treatment for epilepsy is contraindicated in pregnancy unless there is no suitable alternative treatment (see 2 Contraindications and 7 Pregnancy Prevention Program).
If a woman using valproate becomes pregnant, she must be immediately referred to a specialist to consider alternative treatment options.
During pregnancy, maternal tonic-clonic seizures and status epilepticus with hypoxia may carry a particular risk of death for mother and the unborn child. If, despite the known risks of valproate in pregnancy and after careful consideration of alternative treatment, in exceptional circumstances, a pregnant woman must receive valproate for epilepsy, it is recommended to:
- Use the lowest effective dose and divide the daily dose of valproate into several small doses to be taken throughout the day (see 4.1 Dosing Considerations; 4.2 Recommended Dose and Dosage Adjustment);
- Consider the use of a prolonged release formulation of DEPAKENE, which may be preferable to immediate-release formulations in order to avoid high peak plasma concentrations.
All patients with a valproate exposed pregnancy and their partners should be referred to a specialist experienced in pre-natal medicine for evaluation and counselling. Specialized prenatal monitoring should take place to detect possible occurrence of neural tube defects or other malformations. Folate supplementation (5 mg daily) before the pregnancy may decrease the risk of neural tube defects which may occur in all pregnancies. However, available evidence does not suggest that folate can prevent birth defects or malformations due to valproate exposure.
Risk in the neonate
Cases of hemorrhagic syndrome have been reported very rarely in neonates whose mothers have taken valproate during pregnancy. This hemorrhagic syndrome is related to thrombocytopenia, hypofibrinogenemia and/or to a decrease in other coagulation factors (see 7.1.1 Pregnancy, Coagulation Abnormalities).
Afibrinogenemia has also been reported and can be fatal. However, this syndrome must be distinguished from the decrease of vitamin-K factors induced by phenobarbital and other enzymes. Therefore, in neonates, platelet count, plasma levels of fibrinogen, coagulation tests and coagulation factors should be investigated.
Cases of hypoglycemia have been reported in neonates whose mothers have taken valproate during the third trimester of pregnancy.
Cases of hypothyroidism have been reported in neonates whose mothers have taken valproate during pregnancy.
Withdrawal syndrome (symptoms include: agitation, irritability, hyperexcitability, jitteriness, hyperkinesia, tonicity disorders, tremor, convulsions and feeding disorders) may occur, in the days following birth, in neonates whose mothers have taken valproate during the last trimester of pregnancy.
Birth Defects from in utero exposure
Summary
- Studies in human females have demonstrated placental transfer of valproate.
- Valproate can cause fetal harm when administered to pregnant women;
- Maternal valproate use can cause neural tube defects (e.g., spina-bifida) and other structural abnormalities (e.g., craniofacial defects, cardiovascular malformations such as atrial septal defect, hypospadias, limb malformations such as club foot and polydactyly);
- The rate of congenital malformations among babies born to mothers using valproate monotherapy is about four times higher than the rate among babies born to epileptic mothers using other anti-epileptic monotherapies.
- The risk of major congenital malformations in children after in utero exposure to anti-epileptic polytherapy including valproate is higher than that of anti-epileptic drug polytherapy not including valproate.
- This risk is dose-dependent in valproate monotherapy, and available data suggest it is valproate dose-dependent in polytherapy. However, a threshold dose below which no risk exists cannot be established.
Data
Data described below were gained almost exclusively from women who received valproate to treat epilepsy. Data from Pregnancy Registries indicate an increased risk of congenital anomalies in infants exposed to DEPAKENE monotherapy during the first trimester of pregnancy as compared to other antiepileptic drugs. Based on Pregnancy Registry data and the United States Centers for Disease Control (CDC), the estimated risk of valproate-exposed women having children with spina-bifida, oral clefts, neural tube defects, and hypospadias is approximately 1 to 2% as compared to the risk of spina-bifida in the general population which is about 0.06 to 0.07%.
In a study using NAAED Pregnancy Registry data, 16 cases of major malformations following prenatal valproate exposure were reported among offspring of 149 enrolled women who used valproate during pregnancy. Three of the 16 cases were neural tube defects; the remaining cases included craniofacial defects, cardiovascular malformations and malformations of varying severity involving other body systems. The NAAED Pregnancy Registry has reported a major malformation rate of 10.7% in the offspring of women exposed to valproate monotherapy during pregnancy (average daily dose: 1000 mg; range: 500 – 2000 mg/day) as compared to major malformation rate of 2.9% among 1,048 epileptic women who received any other antiepileptic drug monotherapy during pregnancy. These data show a four-fold increased risk for any major malformation following valproate exposure in utero compared to the risk following exposure in utero to any other antiepileptic drug monotherapy.
Data derived from a meta-analysis (including registries and cohort studies) has shown that 10.93% of children of epileptic women exposed to valproate monotherapy during pregnancy suffer from major congenital malformations (95% CI 8.91-13.13). This is greater than the risk of major malformations in the general population (about 2-3%).
Available data show an increased incidence of minor and major malformations. The most common types of malformations include neural tube defects, facial dysmorphism, cleft lip and palate, craniostenosis, cardiac, renal and urogenital defects, limb defects (including bilateral aplasia of the radius), and multiple anomalies involving various body systems.
In utero exposure to valproate may result in eye malformations (including colobomas and microphthalmos) that have been observed in conjunction with other congenital malformations. These eye malformations may affect vision. In most cases, valproate was taken as monotherapy during the whole pregnancy and not a specific trimester.
In utero exposure to various therapeutic doses of valproate, during any trimester of pregnancy, can also result in hearing impairment or deafness due to ear and/or nose malformations (secondary effect) and/or to direct toxicity on the hearing function. All cases to date were reported as serious and included both unilateral and bilateral deafness or hearing impairment. When outcomes were reported, the majority of the cases remained unresolved. In 58% of the cases, the age of diagnosis of hearing impairment or deafness was within the first 4 weeks following birth. Monitoring of signs and symptoms of ototoxicity is recommended.
Risk of Neurological Problems from in utero Exposure
- Cerebral Atrophy:
Exposure in utero to valproate products has been associated with cerebral atrophy with varying degrees/manifestations of neurological compromise, including developmental delays and psychomotor impairment (see 7 Neurologic, Brain Atrophy and 8.5 Post-Market Adverse Reactions).
- Neurodevelopmental Disorders
Available data show that exposure to valproate in utero can have adverse effects on mental and physical development of the exposed children. Whether a child’s in utero exposure to valproate is as monotherapy, or as polytherapy with other anti-epileptic drugs, the risks of neurodevelopmental disorders are significantly greater than for children in the general population or those born to untreated epileptic mothers. The risks seem to be dose-dependent but a threshold dose below which no risk exists, cannot be established. The exact gestational period for risk of these effects is uncertain and it is possible that the risk exists throughout the entire pregnancy.
Studies in preschool children exposed to valproate monotherapy in utero show that up to 30-40% experience delays in their early development such as talking and walking later, lower intellectual abilities, poor language skills (speaking and understanding) and memory problems.
- Decreased IQ
Valproate can cause decreased Intelligence Quotient (IQ) scores in children following in utero exposure. Although it is not known exactly when during pregnancy cognitive effects in valproate-exposed children occur, there is a risk that it may occur early in pregnancy.
IQ measured in school aged children (age 6) with a history of valproate exposure in utero was on average 7-10 points lower than those children exposed to other antiepileptics. There is evidence in children exposed to valproate that the risk of intellectual impairment may be independent of maternal IQ. There are limited data on long term outcomes.
- Autism and/or Autism Spectrum Disorders
A population-based study was conducted in Denmark based on various national patient registries including the Danish Medical Birth Register. This study showed that children exposed to valproate in utero are at increased risk of autism spectrum disorders (approximately 3-fold) and childhood autism (approximately 5-fold) compared to the children of unexposed epileptic women in the same study.
- Attention Deficit Hyperactivity Disorder (ADHD)
Another population-based study in Denmark was also conducted based on various national patient registries including the Danish Medical Birth Register. This study showed that children exposed to valproate in utero are at increased risk of developing ADHD compared to the children of unexposed epileptic women in the same study. Data show that 8.4% of the children exposed to valproate in utero were diagnosed with ADHD compared to 3.2% of unexposed children in the same study.
Although available studies have some limitations, the weight of the evidence supports a causal association between valproate exposure in utero and subsequent adverse effects on neurodevelopment, including increases in the occurrence of autism spectrum disorders.
- SGA (Small for Gestational Age) from in utero exposure
In utero exposure to valproate can lead to babies being born SGA (small for gestational age, defined as birth weight below the 10th percentile corrected for gestational age, stratified by gender).
Epidemiological studies have reported a decrease in mean birth weight, and higher risk of being born with a low birth weight (<2500 grams) or small for gestational age (SGA) for children exposed to valproate in utero in comparison to unexposed or lamotrigine-exposed children. This aligns with preclinical data demonstrating a dose-related fetal weight decrease in animals exposed to valproate in utero, compared to unexposed animals (see 16 Reproductive and developmental toxicology, Development). Available human data do not allow for a conclusion regarding potential effect of dose.
Coagulation Abnormalities
Pregnant women taking DEPAKENE may develop coagulation abnormalities, which may result in hemorrhagic complications in the neonate including death (see 7 Hematologic, Thrombocytopenia; 7.1.1 Pregnancy, Risk in the Neonate). If DEPAKENE is used in pregnancy, the coagulation parameters should be monitored carefully (see 7 Monitoring and Laboratory Tests).
Hepatic Failure
Hepatic failure, resulting in the death of a newborn and of an infant has been reported following the use of valproate during pregnancy.
Hypoglycemia
Serious post-marketing reports of hypoglycemia have been received for neonates whose mothers received DEPAKENE treatment during pregnancy. In most cases, DEPAKENE was the only reported antiepileptic drug (AED). Most of these neonates also displayed other congenital anomalies including hypospadias, complex facial dysmorphism, limb anomalies, severe cardiac anomalies, etc. Therefore, if a decision has been made to use DEPAKENE during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be made aware of the potential hazard to the fetus.
Thyroid Gland Abnormalities
Cases of hypothyroidism have been reported in neonates whose mothers have taken valproate during pregnancy. There have also been reported cases of increased serum thyroid stimulating hormone or decreased serum thyroxine levels in children receiving valproate therapy. In addition, there have been reported cases of hypothyroidism and hyperthyroidism in adults and children receiving valproate monotherapy.
7.1.2. Breastfeeding
DEPAKENE is secreted in breast milk. Concentrations in breast milk have been reported to be 1 to 10% of maternal serum concentrations. Women should not breastfeed during DEPAKENE treatment and for one month after discontinuation of the drug. Based on literature and clinical experience, hematological disorders have been shown in breastfed newborns/infants of treated women.
7.1.3. Pediatrics
Experience has indicated that children under the age of 2 years are at a considerably increased risk of developing fatal hepatotoxicity, especially those on multiple anticonvulsants, those with congenital metabolic disorders, those with severe seizure disorders accompanied by mental retardation, and those with organic brain disease. When DEPAKENE is used in patients 2 years of age or younger, it should be used with extreme caution and as a sole agent, and the concomitant use of salicylates should be avoided due to the risk of liver toxicity. The benefits of therapy should be weighed against the risks. See 2 Contraindications; and 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity.
Above the age of 2 years, experience in epilepsy has indicated that the incidence of fatal hepatotoxicity decreases considerably in progressively older patient groups.
In patients over two years of age who are clinically suspected of having a hereditary mitochondrial disease, DEPAKENE should only be used after other anticonvulsants have failed. (see 7 Hepatic/Biliary/Pancreatic, Patients with Mitochondrial Disease).
Younger children, especially those receiving enzyme-inducing drugs, will require larger maintenance doses to attain targeted total and unbound valproate concentrations. The variability in free fraction limits the clinical usefulness of monitoring total serum valproate concentrations. Interpretation of valproate concentrations in children should include consideration of factors that affect hepatic metabolism and protein binding.
7.1.4. Geriatrics
Alterations in the kinetics of unbound valproate in the elderly (≥ 65 years of age) indicate that the initial dosage should be reduced in this population (see 4.1 Dosing considerations and 10.3 Pharmacokinetics, Geriatrics).
The safety and efficacy of DEPAKENE in elderly patients with epilepsy have not been evaluated in clinical trials. Caution should thus be exercised in dose selection for an elderly patient, recognizing the more frequent hepatic and renal dysfunctions, and limited experience with DEPAKENE in this population.
A study of elderly patients revealed valproate-related somnolence and discontinuation of DEPAKENE for this adverse event (see 7.1.4 Geriatrics, Somnolence in the Elderly). The starting dose should be reduced in elderly patients, and dosage reductions or discontinuation should be considered in patients with excessive somnolence (see 4.1 Dosing Considerations; 10.3 Pharmacokinetics, Geriatrics).
Somnolence in the elderly
In a group of elderly patients (mean age 83 years old, n = 172), DEPAKENE doses were increased by 125 mg/day to a target dose of 20 mg/kg/day. Compared to placebo a significantly higher number of valproate-treated patients had somnolence, and although not statistically significant, a higher number of valproate-treated patients experienced dehydration. Discontinuations for somnolence were also significantly higher in valproate-treated patients compared to placebo. In approximately one-half of the patients with somnolence, there was also associated reduced nutritional intake and weight loss. In elderly patients, dosage should be increased more slowly and with regular monitoring for fluid intake, dehydration, somnolence, urinary tract infection and other adverse events. Dose reductions or discontinuation of DEPAKENE should be considered in patients with decreased food or fluid intake and in patients with excessive somnolence (see 4.1 Dosing Considerations).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The most commonly reported adverse reactions are nausea, vomiting and indigestion. Since DEPAKENE has usually been used with other antiepileptics, it is not possible in most cases to determine whether the adverse reactions listed in 8.2 Clinical Trial Adverse Reactions are due to DEPAKENE alone or to the combination of drugs.
Pediatric Population
The safety profile of valproate in the pediatric population is comparable to adults, but some adverse reactions are more severe or principally observed in the pediatric population. For example, there is a particular risk of severe liver damage in infants and young children especially under the age of 3 years. These risks appear to decrease with increasing age; young children are also at a higher risk of severe pancreatitis, which may result in fatalities (see 3 Serious Warnings and Precautions Box, Hepatotoxicity, 7 Hepatic/Biliary/Pancreatic: Serious or Fatal Hepatotoxicity; and Pancreatitis). Psychiatric disorders such as aggression, agitation, disturbance in attention, abnormal behavior, psychomotor hyperactivity and learning disorder are principally observed in the pediatric population (see 7 Psychiatric, Behavioural Disorders).
8.2. Clinical Trial Adverse Reactions
Adverse events that have been reported with DEPAKENE from epilepsy trials, spontaneous reports, and other sources are listed below by system organ class.
Blood and Lymphatic System Disorders:
Thrombocytopenia and inhibition of the secondary phase of platelet aggregation may be reflected in altered bleeding time, petechiae, bruising, hematoma formation, epistaxis, and hemorrhage (see 7 Hematologic, Thrombocytopenia).
Relative lymphocytosis, macrocytosis and hypofibrinogenemia have been noted. Leukopenia and eosinophilia have also been reported. Anemia, including macrocytic with or without folate deficiency, aplastic anemia, pancytopenia, bone marrow suppression, agranulocytosis and acute intermittent porphyria have been reported (see 7 Monitoring and Laboratory Tests; 8.2 Clinical Trial Adverse Reactions, Neoplasms Benign, Malignant and Unspecified [including cysts and polyps]).
Cardiac Disorders:
Bradycardia
Ear and Labyrinth Disorders:
Hearing loss, either reversible or irreversible, has been reported; however, a cause and effect relationship has not been established. Ear pain has also been reported.
Eye Disorders:
Diplopia
Gastrointestinal Disorders:
Nausea, vomiting and indigestion are the most commonly reported side effects at the initiation of therapy. These effects are usually transient and rarely require discontinuation of therapy. Diarrhea, abdominal cramps, constipation, gingival disorder (mainly gingival hyperplasia) and parotid gland swelling have also been reported.
There have been reports of acute pancreatitis, including rare fatal cases, occurring in association with DEPAKENE therapy (see 3 Serious Warnings and Precautions Box, Pancreatitis; 7 Hepatic/Biliary/Pancreatic, Pancreatitis).
General Disorders and Administration Site Conditions:
Edema of the extremities, fever and hypothermia
Hepatobiliary Disorders:
Liver injury
Minor elevations of transaminases [e.g., serum glutamic-oxaloacetic transaminase (SGOT) and serum glutamic-pyruvic transaminase (SGPT)] and lactate dehydrogenase (LDH) are frequent and appear to be dose-related. Occasionally, laboratory tests also show increases in serum bilirubin and abnormal changes in other liver function tests. These results may reflect potentially serious hepatotoxicity (see 3 Serious Warnings and Precautions Box, Hepatotoxicity; 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity).
Immune System Disorder:
Allergic reaction, anaphylaxis
Infections and Infestations:
Pneumonia, otitis media and urinary tract infection
Investigations:
Abnormal thyroid function tests (including both hyperthyroidism and hypothyroidism) (see 7.1.1 Pregnancy, Thyroid Gland Abnormalities and 9.7 Drug-Laboratory Test Interactions).
Metabolism and Nutrition Disorders:
Hyperammonemia (see 7 Endocrine and Metabolism: Hyperammonemia; Urea Cycle Disorders and Risk of Hyperammonemia; and Patients at Risk of Hypocarnitinemia), hypocarnitinemia (see 2 Contraindications and 7 Endocrine and Metabolism: Patients at Risk of Hypocarnitinemia), hyponatremia, biotin deficiency/biotinidase deficiency and inappropriate antidiuretic hormone (ADH)
secretion. There have been rare reports of Fanconi syndrome (proximal renal tubular dysfunction) occurring primarily in children. Hyperglycinemia has been reported and associated with a fatal outcome in patient with pre-existing non-ketotic hyperglycinemia.
Anorexia with some weight loss and increased appetite with some weight gain have also been reported. Obesity has been reported in post-marketing experience.
Musculoskeletal and Connective Tissue Disorders:
Weakness, rhabdomyolysis and bone pain have been reported (see 7 Musculoskeletal).
Reports have been received of decreased bone mass, potentially leading to osteoporosis and osteopenia, during long-term therapy with some anticonvulsant medications, including DEPAKENE. Some studies have indicated that supplemental calcium and vitamin D may be of benefit to patients who are on chronic DEPAKENE therapy.
A lupus erythematosus-like syndrome has been reported rarely.
Neoplasms Benign, Malignant and Unspecified (including cysts and polyps):
Myelodysplastic syndrome in both adults and children (all children were on valproate monotherapy). In some cases in adults and/or children, myelodysplastic syndrome was reversible upon valproate discontinuation (see 7 Hematologic).
Nervous System Disorders:
Sedative effects have been noted in patients receiving DEPAKENE alone but occur most often in patients on combination therapy. Sedation usually disappears upon reduction of other anti-epileptic medication.
Hallucination, ataxia, headache, nystagmus, asterixis, "spots before the eyes", tremor (may be dose-related), confusion, dysarthria, dizziness, hypesthesia, vertigo, incoordination, memory impairment, cognitive disorder, and extrapyramidal disorders including parkinsonism have been reported with the use of valproate. Rare cases of coma have been reported in patients receiving DEPAKENE alone or in conjunction with phenobarbital.
Encephalopathy, with or without fever or hyperammonemia, has been reported without evidence of hepatic dysfunction or inappropriate valproate plasma levels. Most patients recovered, with noted improvement of symptoms, upon discontinuation of the drug.
Aggravated convulsions (increase in number of seizures or appearance of new seizure type or worsening of seizures) have been reported in patients with epilepsy treated with valproate monotherapy (see 7 Neurologic).
Psychiatric Disorders:
Emotional upset, depression, psychosis, aggression, psychomotor hyperactivity, hostility, agitation, disturbance in attention, abnormal behaviour, learning disorder and behavioural deterioration.
(see 7 Psychiatric).
Renal and Urinary Disorders:
Enuresis, urinary incontinence, acute renal failure and tubulointerstitial nephritis.
Reproductive System and Breast Disorders:
There have been reports of irregular menses, secondary amenorrhea, breast enlargement and galactorrhea in patients receiving DEPAKENE. Hyperandrogenism (hirsutism, virilism, acne, male pattern alopecia, and/or androgen increased).
There have been rare spontaneous reports of polycystic ovary disease. A cause and effect relationship has not been established.
Respiratory, Thoracic and Mediastinal Disorders:
Increased cough, pleural effusion
Skin and Subcutaneous Tissue Disorders:
Transient and/or dose related alopecia (hair loss), hair disorders (such as hair texture abnormal, hair colour changes, hair growth abnormal), have been observed.
Skin rash, DRESS (Drug Rash with Eosinophilia and Systemic Symptoms), photosensitivity, generalized pruritus, erythema multiforme, Stevens-Johnson syndrome, and petechiae have been reported rarely (see 7 Skin).
Rare cases of Toxic Epidermal Necrolysis (TEN) have been reported (see 7 Skin) including a fatal case of a 6 month old infant taking DEPAKENE and several other concomitant medications. An additional case of Toxic Epidermal Necrolysis resulting in death was reported in a 35 year old patient with AIDS taking several concomitant medications and with a history of multiple cutaneous drug reactions.
Serious skin reactions have been reported with concomitant administration of lamotrigine and DEPAKENE (see 7 Skin; 9.4 Drug-Drug Interactions, Table 3).
Cutaneous vasculitis has also been reported.
8.5. Post-Market Adverse Reactions
Adverse Events in Elderly Patients:
In elderly patients (above 65 years of age), there were more frequent reports of accidental injury, infection, pain, and to a lesser degree, somnolence and tremor, when compared to patients 18 to 65 years of age. Somnolence and tremor tended to be associated with the discontinuation of DEPAKENE.
Reproductive Findings
There have been very rare reports of testicular atrophy, decreased semen volume, male hypogonadism, decreased blood testosterone and/or increased blood prolactin levels in patients treated with valproate products. There are insufficient data to determine the exact effect of valproate therapy on testicular development in humans (see 7 Reproductive Health, Fertility; 16 Reproductive and developmental toxicology, Fertility).
There have been post-marketing reports of aspermia, azoospermia, decreased sperm count, decreased spermatozoa motility, abnormal spermatozoa morphology and ultimately, infertility in male patients who received sodium valproate products (effects may be improved by dose reduction or discontinuation) (see 7 Reproductive Health, Fertility; 16 Non-Clinical Toxicology, Fertility).
Hematologic
Cases of acquired Pelger-Huët anomaly have been reported in adults and children, mostly in the context of myelodysplastic syndrome but also in patients who did not develop myelodysplastic syndrome. In some cases acquired Pelger-Huët anomaly was reversible following valproate dose reduction or discontinuation (see 7 Hematologic; 8.2 Clinical Trial Adverse Reactions, Neoplasms Benign, Malignant and Unspecified (including cysts and polyps)).
Neurologic
There have been post-marketing reports of reversible and irreversible cerebral and cerebellar atrophy associated with the use of valproate products. In some cases the patients recovered with permanent sequelae (see 7 Neurologic, Brain Atrophy). Cerebral atrophy seen in children exposed to valproate in utero led to various forms of neurological events, including developmental delays and psychomotor impairment. Congenital malformations and developmental disorders have also been reported. See 7.1.1 Pregnancy: Female children/Women of childbearing potential/Pregnancy, Birth Defects; and Risk of Neurological Problems from in utero Exposure.
Skin
See 7 Skin and 8.2 Clinical Trial Adverse Reactions.
Other cutaneous adverse reactions reported with valproate during post-marketing experience:
- angioedema
- hyperpigmentation including skin, mucosal, nail and nail bed discoloration or hyperpigmentation
- nail and nail bed disorders
9. Drug Interactions
9.1. Serious Drug Interactions
- Rare cases of coma have been reported in patients receiving DEPAKENE alone or in conjunction with phenobarbital (see 9.4 Drug-Drug Interactions, Table 3).
- Serious skin reactions (such as Stevens-Johnson syndrome and Toxic Epidermal Necrolysis) have been reported with concomitant lamotrigine and DEPAKENE administration (see 9.4 Drug-Drug Interactions, Table 3).
9.2. Drug Interactions Overview
Patients receiving combined antiepileptic therapy require careful monitoring when another agent is started, stopped or when the dose is altered.
DEPAKENE has been found to be a weak inhibitor of some P450 isozymes, epoxide hydrase, and glucuronyl transferases.
Drugs that affect the level of expression of hepatic enzymes, particularly those that elevate levels of glucuronyl transferases (such as ritonavir; see Table 3 below), may increase the clearance of valproate. For example, phenytoin, carbamazepine, and phenobarbital (or primidone) can double the clearance of valproate. Thus, for patients on DEPAKENE monotherapy the half-life of valproate will generally be longer and concentration higher than in patients receiving polytherapy with antiepileptic drugs.
In contrast, drugs that are inhibitors of cytochrome P450 isozymes, such as antidepressants, may be expected to have little effect on valproate clearance because cytochrome P450 microsomal mediated oxidation is a relatively minor secondary metabolic pathway compared to glucuronidation and beta-oxidation.
The concomitant administration of DEPAKENE with other drugs that exhibit extensive protein binding (e.g., acetylsalicylic acid, carbamazepine, dicumarol, warfarin, tolbutamide, phenytoin, and clozapine) may result in alteration of serum drug levels.
Since DEPAKENE may interact with concurrently administered drugs which are capable of enzyme induction, periodic plasma concentration determinations of valproate and concomitant drugs are recommended during the early course of therapy and whenever enzyme-inducing drugs are introduced or withdrawn (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels).
9.3. Drug-Behaviour Interactions
The use of valproate with alcohol or other CNS drugs with overlapping undesirable effects such as sedation or somnolence, should be avoided (see 9.4 Drug-Drug Interactions, Table 3; 7 Driving and Operating Machinery).
9.4. Drug-Drug Interactions
Table 3 provides information about the potential influence of several commonly prescribed medications on DEPAKENE pharmacokinetics as well as the potential influence of DEPAKENE on the pharmacokinetics (PK) and pharmacodynamics (PD) of several commonly prescribed medications. The list is not exhaustive nor could it be, since new interactions are continuously being reported. The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated). Please note that drugs may be listed under specific name, family or pharmacologic class. Reading the entire section is recommended.
Risk of liver damage
The concomitant use of salicylates should be avoided in children under 3 years of age due to the risk of liver toxicity (see 3 Serious Warnings and Precautions Box, Hepatotoxicity, 7
Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity, and 8.1 Adverse Reaction Overview, Pediatric Population).
Concomitant use of valproate and multiple anticonvulsant therapy increases the risk of liver damage, especially in young children (see 3 Serious Warnings and Precautions Box, Hepatotoxicity, 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity, and 8.1 Adverse Reaction Overview, Pediatric Population).
Concomitant administration of valproate and cannabidiol has been associated with an increased risk of ALT and/or AST elevation (see Table 3, Cannabidiol (CBD); 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity; 7 Monitoring and Laboratory Tests).
Table 3 - Established or Potential Drug-Drug Interactions
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |||||
| Acetaminophen | CT | ↔ acetaminophen | DEPAKENE had no effect on any of the pharmacokinetic parameters of acetaminophen when it was concurrently administered to three epileptic patients. | |||||
| Acetazolamide | C | Effect on drug concentrations unknown | Concomitant administration of valproate and acetazolamide has been associated with encephalopathy and/or hyperammonemia. Patients treated concomitantly with these two drugs should be carefully monitored for signs and symptoms of hyperammonemic encephalopathy (see 7 Endocrine and Metabolism). | |||||
| Acetylsalicylic Acid | CT | ↑ valproate | A study involving the co-administration of acetylsalicylic acid at antipyretic doses (11 to 16 mg/kg) with DEPAKENE to pediatric patients (n = 6) revealed a decrease in protein binding and inhibition of valproate metabolism. Valproate free fraction was increased 4-fold in the presence of acetylsalicylic acid compared to DEPAKENE alone. The beta-oxidation pathway consisting of 2-E-valproic acid, 3-OH-valproic acid, and 3-keto valproic acid was decreased from 25% of total metabolites excreted on DEPAKENE alone to 8.3% in the presence of acetylsalicylic acid. Caution should be exercised when DEPAKENE is co-administered with drugs affecting coagulation, [e.g., acetylsalicylic acid and warfarin] (see 7 Hematologic, Thrombocytopenia; 7 Monitoring and Laboratory Tests; 8.2 Clinical Trial Adverse Reactions). | |||||
| Alcohol | T | PD effect | DEPAKENE may potentiate the CNS depressant action of alcohol. Alcohol intake is not recommended during treatment with DEPAKENE (see 7 Driving and Operating Machinery; 9.3 Drug-Behavior Interactions). | |||||
| Amitriptyline / Nortriptyline | CT | In general: ↓ amitriptyline ↓ nortriptyline Rarely: ↑ amitriptyline ↑ nortriptyline | Administration of a single oral 50 mg dose of amitriptyline to 15 healthy volunteers (10 males and 5 females) who received DEPAKENE (500 mg twice daily) resulted in a 21% decrease in plasma clearance of amitriptyline and a 34% decrease in the net clearance of nortriptyline. Rare post-marketing reports of concurrent use of DEPAKENE and amitriptyline resulting in an increased amitriptyline and nortriptyline levels have been received. Concurrent use of DEPAKENE and amitriptyline has rarely been associated with toxicity. Monitoring of amitriptyline levels should be considered for patients taking DEPAKENE concomitantly with amitriptyline. Consideration should be given to lowering the dose of amitriptyline/nortriptyline in the presence of DEPAKENE. | |||||
Antacids Alumina and magnesium trisilicate oral suspension is not currently marketed in Canada. | CT | ↔ valproate | A study involving the co-administration of DEPAKENE 500 mg with 160 milliequivalent doses of commonly administered antacids (62 ml of aluminum and magnesium hydroxide oral suspension, 97 ml of alumina and magnesium trisilicate oral suspension, or 42 ml of calcium carbonate oral suspension) did not reveal any effect on the extent of absorption of DEPAKENE. | |||||
| Other - Antipsychotics, Monoamine Oxidase Inhibitors (MAOIs) and Tricyclic Antidepressants | T | PD effect Effect on drug concentrations unknown | In addition to enhancing CNS depression when used concurrently with DEPAKENE, antipsychotics, tricyclic antidepressants and MAOIs may lower the seizure threshold. Dosage adjustments for DEPAKENE may be necessary to control seizures. | |||||
Antiretroviral agents
| C | ↓ valproate | Effect of antiretroviral agents on valproate Protease inhibitors such as lopinavir and ritonavir decrease valproate plasma level when co-administered with valproate. | |||||
| CT | ↑ zidovudine | Reduction of therapeutic effect of valproate was observed in a patient with bipolar disorder with the initiation of HIV treatment with lopinavir/ritonavir, zidovudine, and lamivudine. Effect of valproate on zidovudine In 6 patients who were seropositive for HIV, the clearance of zidovudine (100 mg every 8 hours) was decreased by 38% after administration of valproate (250 or 500 mg every 8 hours); the half-life of zidovudine was unaffected. | |||||
| Benzodiazepines | CT | ↑ lorazepam ↑ diazepam | DEPAKENE may decrease oxidative liver metabolism of some benzodiazepines, resulting in increased benzodiazepine serum concentrations. (see Table 3. Diazepam and Lorazepam). | |||||
| Cannabidiol (CBD) | CT | ↑ Alanine Transaminase (ALT) | Cannabidiol at doses 10 to 25 mg/kg and valproate led to ALT increases greater than 3 times the upper limit of normal in 19% of the patients. Exercise appropriate liver monitoring and consider dose reduction or discontinuation in case of significant anomalies of liver parameters (see 7 Hepatic/Biliary/Pancreatic). | |||||
| Carbamazepine / carbamazepine-10,11-epoxide | CT | ↓ valproate ↓ CBZ ↑ CBZ-E | Effect of carbamazepine on valproate Concomitant use of CBZ with DEPAKENE may decrease serum concentrations and the half-life of valproate due to increased metabolism induced by hepatic microsomal enzyme activity. Effect of valproate on carbamazepine and carbamazepine-10,11-epoxide Serum levels of carbamazepine (CBZ) decreased 17% while that of carbamazepine-10,11-epoxide (CBZ-E) increased by 45% upon co-administration of DEPAKENE and CBZ to epileptic patients. Monitoring of valproate and carbamazepine serum concentrations is recommended when either medication is added to or withdrawn from an existing regimen (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). Changes in the serum concentration of the CBZ-E metabolite of CBZ will not be detected by routine serum CBZ assay. | |||||
| Carbapenem Antibiotics | C | ↓ valproate | Carbapenem antibiotics (ertapenem, imipenem, meropenem, doripenem) can reduce serum | |||||
| valproic acid concentrations to sub-therapeutic levels. This can result in loss of seizure control in epileptic patients or loss of efficacy in non-epileptics. In some cases of co-administration in epileptic patients, breakthrough seizures have occurred. Increasing valproic acid dose may not be sufficient to overcome this interaction. If co-administration is essential, serum valproic acid concentrations should be monitored daily (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). Alternative antibacterial or anticonvulsant therapy should be considered if serum valproic acid concentrations drop significantly or seizure control deteriorates (see 7 General, Interaction with Carbapenem Antibiotics). | ||||||||
| Chlorpromazine | CT | ↑ valproate | A study involving the administration of 100 to 300 mg/day of chlorpromazine to schizophrenic patients already receiving DEPAKENE (200 mg twice daily) revealed a 15% increase in trough plasma levels of valproate. This increase is not considered clinically important. | |||||
| Cholestyramine | C, CT | ↓ valproate | Co-administration of cholestyramine may lead to a decrease in valproate plasma concentration when co-administered. | |||||
| Cimetidine or Erythromycin | T | ↑ valproate | Cimetidine and/or erythromycin may decrease the clearance and increase the half-life of DEPAKENE by altering its metabolism. In patients receiving DEPAKENE, serum valproic acid levels should be monitored when treatment with cimetidine is instituted, increased, decreased, or discontinued. The DEPAKENE dose should be adjusted accordingly (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). | |||||
| Clonazepam | T | No PK interaction | The concomitant use of DEPAKENE and clonazepam may induce absence status in patients with a history of absence type seizures. | |||||
| Clozapine | C CT T | No interaction | Concomitant treatment of valproate and clozapine may increase the risk of neutropenia and clozapine-induced myocarditis. If concomitant use of valproate with clozapine is necessary, careful monitoring for both events is required. | |||||
| Concomitant use of valproic acid with clozapine may alter the plasma levels of clozapine. Rare but serious reports of seizures, including onset of seizures in non-epileptic patients, and isolated cases of delirium where clozapine was co-administered with valproic acid have been reported. | ||||||||
| Diazepam | CT | ↑ diazepam | Valproate displaces diazepam from its plasma albumin binding sites and inhibits its metabolism. Co-administration of DEPAKENE (1,500 mg daily) increased the free fraction of diazepam (10 mg) by 90% in healthy volunteers (n = 6). Plasma clearance and volume of distribution for free diazepam were reduced by 25% and 20%, respectively, in the presence of valproate. The elimination half-life of diazepam remained unchanged upon addition of valproate. | |||||
| Estrogen-containing products | C CT T | ↓ valproate | Effect of estrogen-containing products on valproate Estrogen-containing products, including estrogen-containing hormonal contraceptives, may increase the clearance of valproate, which may decrease valproate serum concentration and potentially decrease valproate efficacy. Based on limited data from literature, an approximate 20% increase in valproate clearance has been reported in some patients that were concomitantly treated with valproate and estrogen-containing products. Inter-individual variability has been noted. There are insufficient data to establish a robust PK-PD relationship resulting from this PK interaction. Prescribers should monitor clinical response (seizure control), when adding, or discontinuing estrogen-containing products. Consider monitoring valproate plasma levels (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). Effect of valproate on estrogen-containing products Valproate usually has no enzyme inducing effect; as a consequence, valproate does not reduce efficacy of estroprogestative agents in women receiving hormonal contraception. | |||||
| Ethosuximide | CT | ↑ ethosuximide | Valproate inhibits the metabolism of | |||||
| ethosuximide. Administration of a single ethosuximide dose of 500 mg with DEPAKENE (800 to 1,600 mg/day) to healthy volunteers (n = 6) was accompanied by a 25% increase in elimination half-life of ethosuximide and a 15% decrease in its total clearance as compared to ethosuximide alone. Patients receiving DEPAKENE and ethosuximide, especially along with other anticonvulsants, should be monitored for alterations in serum concentrations of both drugs (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). | ||||||||
| Felbamate | CT | ↑ valproate | A study involving the co-administration of 1,200 mg/day of felbamate with DEPAKENE to patients with epilepsy (n = 10) revealed an increase in mean valproate peak concentration by 35% (from 86 to 115 mcg/mL) compared to DEPAKENE alone. Increasing the felbamate dose to 2,400 mg/day increased the mean valproate peak concentration to 133 mcg/mL (another 16% increase). A decrease in DEPAKENE dosage may be necessary when felbamate therapy is initiated. Lower doses of DEPAKENE may be necessary when used concomitantly with felbamate. | |||||
| Haloperidol | CT | ↔ valproate | A study involving the administration of 6 to 10 mg/day of haloperidol to schizophrenic patients already receiving DEPAKENE (200 mg twice daily) revealed no significant changes in valproate trough plasma levels. | |||||
| Lamotrigine | CT | ↑ lamotrigine | Effect of valproate on lamotrigine: Serious skin reactions (such as Stevens-Johnson syndrome and Toxic Epidermal Necrolysis) have been reported with concomitant lamotrigine and DEPAKENE administration. The dose of lamotrigine should be reduced when co-administered with DEPAKENE (see 7 Skin). | |||||
| CT, T | The effects of DEPAKENE on lamotrigine were investigated in 6 healthy male subjects. Each subject received a single oral dose of lamotrigine alone and with DEPAKENE 200 mg every 8 hours for 6 doses starting 1 hour before the lamotrigine dose was given. DEPAKENE administration reduced the total clearance of lamotrigine by 21% and increased the plasma elimination half-life from 37.4 hours to 48.3 hours (p < 0.005). Renal clearance of lamotrigine was unchanged. In a steady-state study involving 10 healthy volunteers, the elimination half-life of lamotrigine increased from 26 to 70 hours with DEPAKENE co-administration (a 165% increase). In a study involving 16 epileptic patients, DEPAKENE doubled the elimination half-life of lamotrigine. In an open-labelled study, patients receiving enzyme inducing AEDs (e.g., carbamazepine, phenytoin, phenobarbital, or primidone) demonstrated a mean lamotrigine plasma elimination half-life of 14 hours while the elimination half-life was 30 hours in patients taking DEPAKENE plus an enzyme inducing antiepileptic agent. The latter value is similar to the lamotrigine half-life during monotherapy indicating that valproic acid may counteract the effect of the enzyme inducer. If DEPAKENE is discontinued in a patient receiving lamotrigine and an enzyme inducing antiepileptic, serum lamotrigine concentrations may decrease. Patients receiving combined antiepileptic therapy require careful monitoring when another agent is started, stopped or when the dose is altered. Effect of lamotrigine on valproate: Literature studies provide inconsistent results (decrease, stable or small increase in valproate concentrations). | |||||||
| Lithium | CT | ↔ lithium | Effect of lithium on valproate In a double-blind placebo-controlled multiple dose crossover study in 16 healthy male volunteers, the AUC and Cmax of valproate increased 11 to 12% and Tmax was reduced. These changes were statistically significant but are not likely to have clinical importance. | |||||
Effect of valproate on lithium Co-administration of DEPAKENE (500 mg twice daily) and lithium carbonate (300 mg three times daily) to normal male volunteers (n = 16) had no effect on the steady-state kinetics of lithium. | ||||||||
| Lorazepam | CT | ↑ lorazepam | Concomitant administration of DEPAKENE (500 mg twice daily) and lorazepam (1 mg twice daily) in healthy male volunteers (n = 9) was accompanied by a 17% decrease in the plasma clearance of lorazepam. This decrease is not considered clinically important. | |||||
| Mefloquine | C | ↓ valproate | Concomitant administration of mefloquine and DEPAKENE can decrease plasma valproate concentrations. This may lead to increased frequency of seizures. The DEPAKENE dose may need to be adjusted. | |||||
Metamizole Not currently marketed in Canada for human use | C, T | ↓ valproate | Metamizole may decrease valproate serum levels when co-administered, which may result in potentially decreased valproate clinical efficacy. Prescribers should monitor clinical response (seizure control) and consider monitoring valproate serum levels and dose adjustment, as appropriate (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). | |||||
| Methotrexate | C | ↓ valproate | Some case reports describe a significant decrease in valproate serum levels after methotrexate administration, with occurrence of seizures. Prescribers should monitor clinical response (seizure control) and consider monitoring valproate serum levels as appropriate (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). | |||||
| Nimodipine | CT | ↑ nimodipine | Concomitant use of nimodipine with valproic acid may increase nimodipine plasma concentration by 50%. | |||||
| Olanzapine | CT | ↓ olanzapine | Valproic acid may decrease the olanzapine plasma concentration. Administration of a single 5 mg dose of olanzapine to 10 healthy, non-epileptic volunteers with Depakote ER® (divalproex sodium extended-release tablets) 1000 mg QD did not affect olanzapine Cmax or elimination half-life. However, olanzapine AUC was 35% lower in the presence of Depakote ER® | |||||
| (divalproex sodium extended-release tablets). The clinical significance of these observations is unknown. | ||||||||
| Oral contraceptive Steroids | CT | No PK interaction | Administration of a single-dose of ethinyloestradiol (50 mcg)/levonorgestrel (250 mcg) to 6 women on DEPAKENE (200 mg twice daily) therapy for 2 months did not reveal any pharmacokinetic interaction. DEPAKENE is not a significant enzyme inducer and would not be expected to decrease concentrations of steroid hormones (see 7 Reproductive Health, Estrogen-containing products). However, clinical data about the interaction of DEPAKENE with oral contraceptives are minimal. | |||||
| Phenobarbital | CT C | ↓ valproate ↑ phenobarbital | Effect of phenobarbital on valproate Phenobarbital increases the metabolism of valproic acid and hence, increases valproic acid metabolite levels. Patients treated with this drug should be carefully monitored for signs and symptoms of hyperammonemia (see 7 Endocrine and Metabolism, Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin). Effect of valproate on phenobarbital Valproate was found to inhibit the metabolism of phenobarbital. Co-administration of DEPAKENE (250 mg twice daily for 14 days) with phenobarbital to healthy subjects (n = 6) resulted in a 50% increase in half-life and a 30% decrease in plasma clearance of phenobarbital (60 mg single-dose). The fraction of phenobarbital dose excreted unchanged increased by 50% in the presence of valproate. There is evidence for severe CNS depression, with or without significant elevations of barbiturate or valproate serum concentrations. All patients receiving concomitant barbiturate therapy should be closely monitored for neurological toxicity. Serum barbiturate concentrations should be obtained, if possible, | |||||
| and the barbiturate dosage decreased, if appropriate. | ||||||||
| Phenytoin | CT C | ↓ valproate ↑ phenytoin | Effect of phenytoin on valproate Phenytoin increases the metabolism of valproic acid and hence, increases valproic acid metabolite levels. Patients treated with this drug should be carefully monitored for signs and symptoms of hyperammonemia (see 7 Endocrine and Metabolism, Hyperammonemia and Encephalopathy Associated with Concomitant use of Topiramate, Acetazolamide, Phenobarbital or Phenytoin). Effect of valproate on phenytoin Valproate displaces phenytoin from its plasma albumin binding sites and inhibits its hepatic metabolism. Co-administration of DEPAKENE (400 mg three times daily) with phenytoin (250 mg) in healthy volunteers (n = 7) was associated with a 60% increase in the free fraction of phenytoin. Total plasma clearance and apparent volume of distribution of phenytoin increased 30% in the presence of valproate. Both the clearance and apparent volume of distribution of free phenytoin were reduced by 25%. In patients with epilepsy, there have been reports of breakthrough seizures occurring with the combination of DEPAKENE and phenytoin. The dosage of phenytoin should be adjusted as required by the clinical situation. | |||||
| Pivalate-conjugated medicines | C, CT, T | ↓ carnitine | Concomitant administration of valproate and pivalate-conjugated medicines that decrease carnitine levels (such as adefovir dipivoxil) may trigger occurrence of hypocarnitinemia (see 7 Endocrine and Metabolism: Patients at Risk of Hypocarnitinemia). Concomitant administration of these medicines with valproate is not recommended. Patients in whom co-administration cannot be avoided should be carefully monitored for signs and symptoms of hypocarnitinemia. | |||||
| Primidone | T | ↑ phenobarbital | Primidone is metabolized into a barbiturate (phenobarbital), and therefore, may also be involved in a similar or identical interaction with DEPAKENE as phenobarbital. | |||||
| Propofol | C, CT | ↑ propofol | Valproic acid may inhibit the metabolism of propofol, thus increasing propofol exposure. Reduce the dose of propofol when co-administering with valproate and monitor patients closely for signs of increased sedation or cardiorespiratory depression. | |||||
| Quetiapine | C, T | Effect on drug concentrations unknown | Co-administration of valproate and quetiapine may increase the risk of neutropenia/leucopenia. | |||||
| Rifampin | CT | ↓ valproate | A study involving the administration of a single dose of DEPAKENE (7 mg/kg) 36 hours after 5 nights of daily dosing with rifampin (600 mg) revealed a 40% increase in the oral clearance of valproate. DEPAKENE dosage adjustment may be necessary when it is co-administered with rifampin (see 4.2 Recommended Dose and Dosage Adjustment, Therapeutic Blood Levels). | |||||
| Rufinamide | C, CT | ↑ rufinamide | Valproic acid may lead to an increase in plasma levels of rufinamide that is dependent on concentration of valproic acid. Caution should be exercised, particularly in children, as this effect is larger in the pediatric population. | |||||
| Selective Serotonin Re-Uptake Inhibitors (SSRIs) | C | ↑ valproate | Some evidence suggests that SSRIs inhibit the metabolism of DEPAKENE, resulting in higher than expected levels of valproate. | |||||
| Tolbutamide | T | ↑ tolbutamide | From in vitro experiments, the unbound fraction of tolbutamide was increased from 20 to 50% when added to plasma samples taken from patients treated with DEPAKENE. The clinical relevance of this displacement is unknown. | |||||
| Topiramate | CT | Effect unknown | Hyperammonemia and hypothermia Concomitant administration of valproate and topiramate has been associated with encephalopathy and/or hyperammonemia. Concomitant administration of topiramate with DEPAKENE has also been associated with | |||||
hypothermia in patients who have tolerated either drug alone. Patients treated with these two drugs should be carefully monitored for signs and symptoms of hyperammonemic encephalopathy (see also 2 Contraindications, patients with known urea cycle disorders and 7 Endocrine and Metabolism). Blood ammonia levels should be measured in patients with reported onset of hypothermia (see 7 Endocrine and Metabolism, Hypothermia). | ||||||||
| Warfarin | T | Effect unknown | In an in vitro study, valproate increased the unbound fraction of warfarin by up to 32.6%. The therapeutic relevance of this is unknown. Caution is recommended when DEPAKENE is administered with drugs affecting coagulation and coagulation tests should be monitored if DEPAKENE is instituted in patients taking anticoagulants (see 7 Hematologic and Monitoring and Laboratory Tests). | |||||
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical; ↔ = No effect / No significant changes
9.5. Drug-Food Interactions
Co-administration of DEPAKENE with food should cause no clinical problems in the management of patients with epilepsy (see 4.4 Administration).
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
DEPAKENE is partially eliminated in the urine as a ketone-containing metabolite which may lead to a false interpretation of the urine ketone test.
There have been reports of altered thyroid function tests associated with DEPAKENE; the clinical significance of these is unknown (see 7.1.1 Pregnancy, Thyroid Gland Abnormalities).
10. Clinical Pharmacology
10.1. Mechanism of Action
DEPAKENE has anticonvulsant properties. Although its mechanism of action has not yet been established, it has been suggested that its activity is related to increased brain levels of gamma-aminobutyric acid (GABA). The effect on the neuronal membrane is unknown.
10.2. Pharmacodynamics
A good correlation has not been established between daily dose, serum level and therapeutic effect of DEPAKENE. In epilepsy, the therapeutic plasma concentrations range is believed to be from 50 to 100 mcg/mL (350 to 700 micromole/L) of total valproate. Occasional patients may be controlled with serum levels lower or higher than this range (see 4 Dosage and Administration).
10.3. Pharmacokinetics
Absorption
Valproic acid is rapidly absorbed after oral administration. Peak serum levels occur approximately 1 to 4 hours after a single oral dose. A slight delay in absorption occurs when the drug is administered with meals but this does not affect the total absorption.
Distribution
Valproic acid is rapidly distributed throughout the body and the drug is strongly bound (90%) to human plasma proteins. Increases in dose may result in decreases in the extent of protein binding and variable changes in valproic acid clearance and elimination.
Protein Binding
The plasma protein binding of valproate is concentration dependent and the free fraction increases from approximately 10% at 40 mcg/mL to 18.5% at 130 mcg/mL. Protein binding of valproate is reduced in the elderly, in patients with chronic hepatic diseases, in patients with renal impairment, in hyperlipidemic patients, and in the presence of other drugs (e.g., acetylsalicylic acid). Conversely, valproate may displace certain protein-bound drugs (e.g., phenytoin, carbamazepine, warfarin, and tolbutamide). See 9 Drug Interactions for more detailed information on the pharmacokinetic interactions of valproate with other drugs.
CNS Distribution
Valproate concentrations in cerebrospinal fluid (CSF) approximate unbound concentrations in plasma (ranging from 7 to 25% of total concentration).
Metabolism
Valproate is metabolized almost entirely by the liver. In adult patients on monotherapy, 30 to 50% of an administered dose appears in urine as a glucuronide conjugate. Mitochondrial (beta)-oxidation is the other major metabolic pathway, typically accounting for over 40% of the dose. Usually, less than 15 to 20% of the dose is eliminated by other oxidative mechanisms. Less than 3% of an administered dose is excreted unchanged in urine.
Due to the saturable plasma protein binding, the relationship between dose and total valproate concentration is nonlinear; concentration does not increase proportionally with the dose, but rather increases to a lesser extent. The kinetics of unbound drug are linear.
Elimination
Mean plasma clearance and volume of distribution for total valproate are 0.56 L/hr/1.73 m2 and 11 L/1.73 m2, respectively. Mean plasma clearance and volume of distribution for free valproate are 4.6 L/hr/1.73 m2 and 92 L/1.73 m2, respectively. These estimates cited apply primarily to patients who are not taking drugs that affect hepatic metabolizing enzyme systems. For example, patients taking enzyme-inducing AEDs (carbamazepine, phenytoin, and phenobarbital) will clear valproate more rapidly. Because of these changes in valproic acid clearance, monitoring of valproate and concomitant drug concentrations should be intensified whenever enzyme-inducing drugs are introduced or withdrawn.
Elimination of valproic acid and its metabolites occurs principally in the urine, with minor amounts in the feces and expired air. Very little unmetabolized parent drug is excreted in the urine.
The serum half-life (t½) of valproic acid is typically in the range of 6 to 16 hours. Half-lives in the lower part of the above range are usually found in patients taking other AEDs capable of enzyme induction.
Special populations and conditions:
- Neonates/Infants: Within the first 2 months of life, infants have a markedly decreased ability to eliminate valproate compared to children and adults. This is a result of reduced clearance (perhaps due to delay in development of glucuronosyltransferase and other enzyme systems involved in valproate elimination) as well as increased volume of distribution (in part due to decreased plasma protein binding). For example, in one study, the half-life in neonates under 10 days ranged from 10 to 67 hours, compared to a range of 7 to 13 hours in children greater than 2 months.
- Pediatrics: Patients between 3 months and 10 years have 50% higher clearances expressed on weight (i.e., L/min/kg) than do adults. Over the age of 10 years, children have pharmacokinetic parameters that approximate those of adults.
- Geriatrics: The capacity of elderly patients (age range: 68 to 89 years) to eliminate valproate has been shown to be reduced compared to younger adults (age range: 22 to 26 years). Intrinsic clearance is reduced by 39%; the free fraction is increased by 44% (see 4.1 Dosing Considerations; 7.1.4 Geriatrics).
- Sex: There are no differences in unbound clearance (adjusted for body surface area) between males and females (4.8 ± 0.17 and 4.7 ± 0.07 L/hr per 1.73 m2, respectively).
- Genetic Polymorphism: No data available on genetic polymorphism.
- Ethnic Origin: The effects of race on the kinetics of valproate have not been studied.
- Hepatic Insufficiency: See 2 Contraindications and 7 Hepatic/Biliary/Pancreatic, Serious or Fatal Hepatotoxicity for statements regarding hepatic dysfunction and associated fatalities.
- Renal Insufficiency: See 7 Renal, Renal Impairment.
- Storage, Stability, and Disposal
Store DEPAKENE oral solution between 15 and 30°C.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance:
Non-proprietary name of the drug substance(s): valproic acid
Chemical name: 2-propylpentanoic acid or dipropylacetic acid
Molecular formula and molecular mass: C8H16O2 144.21
Structural formula:
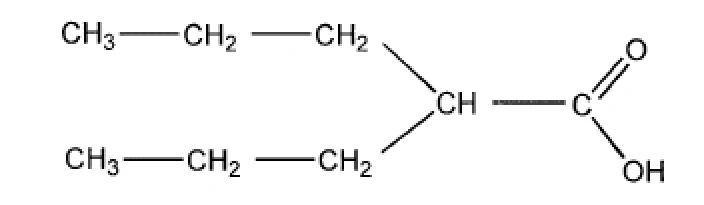
Physicochemical properties: Valproic acid is a clear colorless to faint brown viscous liquid having a characteristic odor. The bulk drug substance displays solubility characteristics consistent with aliphatic carboxylic acids having limited solubility in water. The compound is freely soluble in dilute base and slightly soluble in dilute aqueous mineral acids.
14. Clinical Trials
14.1. Clinical Trials by Indication
The clinical trial data on which the original indication was authorized is not available.
16. Non-Clinical Toxicology
Safety Pharmacology:
Valproic acid has been shown to be effective against several types of chemically and electrically induced convulsions in a variety of animal species. These included maximal electroshock, low frequency electroshock, CO2 withdrawal, pentylene tetrazole, cobalt, bemegride, bicuculline and 1-glutamate. Many forms of photic and auditory induced seizures are also effectively blocked by valproic acid.
In animal studies, valproic acid at doses of 175 mg/kg or less had no effect on locomotor activity and conditioned responses to positive reinforcement.
Doses greater than 175 mg/kg inhibited spontaneous and conditioned behaviour in mice and rats and interfered with coordination of hind limbs in rats. Suppression of spontaneous and evoked brain potentials was also demonstrated at these higher dose levels.
Valproic acid at doses of 175 mg/kg or less had little or no effect on the autonomic nervous system, cardiovascular system, respiration, body temperature, inflammatory responses, smooth muscle contraction or renal activity. Intravenous doses of 22, 43 and 86 mg/kg in animals caused very transient decreases followed by compensatory increases in blood pressure.
Sodium valproate injectable caused decreased activity, ataxia, dyspnea, prostration and death in rats and mice acutely exposed to dosages exceeding 200 mg/kg.
General toxicology
The initial animal testing was done with sodium valproate, whereas most of the recent research has been with valproic acid. The conversion factor is such that 100 mg of the sodium salt is equivalent to 87 mg of the acid. References to dosage are in terms of valproic acid activity.
Acute Toxicity
Acute toxicity has been determined in several animal species using oral, intravenous, intraperitoneal and subcutaneous routes. The oral median lethal dose in adult rats and dogs was about 1 to 2 g/kg. Toxicity was similar for both sexes; however, it tended to be greater in newborn and 14-day old rats and in young adult rats. The signs of toxicity were those of central nervous system depression. Specific organ damage was limited to cellular debris in reticuloendothelial tissue and slight fatty degeneration of the liver.
Large oral doses (more than 500 mg/kg) produced irritation of the gastrointestinal tract of rats.
In adult male mice, the oral medial lethal dose of divalproex sodium was 1.66 g/kg (equal to approximately 1.54 g/kg valproic acid).
Pulverized divalproex sodium enteric-coated tablets (equivalent to 250 mg valproic acid), suspended in 0.2% methylcellulose, were administered orally to mice and rats of both sexes (10/sex/species/group) in dosages ranging from 1.74 to 4.07 g/kg. The oral median lethal dose (LD50) ranged from 2.06 to 2.71 g/kg. No consistent sex-related or species-related differences were observed.
Signs of central nervous system depression, such as decreased activity, ataxia, and sleep, were observed. At necropsy, discolouration and/or thickening of the glandular mucosa were observed in only 2 female rats treated with 2.71 g/kg that died acutely.
When mature rats and dogs were administered up to 240 mg/kg/day or 120 mg/kg/day, respectively, for at least four consecutive weeks, no significant toxicologic effects were reported. However, significant reductions in testicular weights and total white cell counts in rats given 240 mg/kg/day were considered as evidence of subtle toxicity from sodium valproate injectable. Therefore, 90 mg/kg/day in rats and 120 mg/kg/day in dogs were considered the highest non-toxic doses.
The acute intravenous toxicity of sodium valproate injectable formulation containing the equivalent of 100 mg valproic acid/mL was evaluated in both sexes of mice and rats. Groups of mice and rats (five/sex/species/group) were treated at dosages ranging from 0.5 to 9.0 mL/kg (50 to 900 mg valproate/kg). No overt signs of toxicity were present in rats and mice given 0.5 mL/kg (50 mg valproate/kg). LD50 values for the test solution in mice and rats (data combined for both sexes) were 7.3 and 7.0 mL/mg (730 and 700 mg valproate/kg), respectively.
Subacute and Chronic Toxicity
Subacute and chronic toxicity studies consisted of 1, 3, 6 and 18 months studies in rats and 3, 6 and 12 months studies in dogs. Pathologic changes included suppression of the hematopoietic system, depletion of lymphocytes from lymphoid tissues and the loss of germinal epithelial cells from seminiferous tubules. Reduced spermatogenesis and testicular atrophy occurred in dogs at doses greater than 90 mg/kg/day and in rats at doses greater than 350 mg/kg/day. In rats, the first indication of toxicity at 350 mg/kg/day was decreased food consumption and growth.
Genotoxicity
Valproate was not mutagenic in bacteria (Ames test), or mouse lymphoma L5178Y cells at thymidine kinase locus (mouse lymphoma assay), and did not induce DNA repair activity in primary culture of rat hepatocytes. After oral administration, valproate did not induce either chromosome aberrations in rat bone marrow, or dominant lethal effects in mice.
In literature, after intraperitoneal exposure to valproate, increased incidences of DNA and chromosome damage (DNA strand-breaks, chromosomal aberrations or micronuclei) have been reported in rodents. However, the clinical significance of the results obtained with the intraperitoneal route of administration is unknown.
Statistically significant higher incidences of sister-chromatid exchange (SCE) have been observed in epileptic children exposed to valproate as compared to healthy children or epileptic children not exposed to valproate. However, contradictory results were reported in another study conducted in a mixed population of adults and children who showed similar SCE frequencies in treated or untreated epileptic patients. The clinical significance of an increase in SCE frequency is not known.
Carcinogenicity
Two hundred rats were given valproic acid in the diet for 107 weeks. Mean doses consumed in the treatment period were: 81 mg/kg/day (males) and 85 mg/kg/day (females), in the low dose group; 161 mg/kg/day (males) and 172 mg/kg/day (females) in the high dose group (approximately 10 to 50% of the maximum human daily dose on a mg/m2 basis). Control animals received corn oil in the diet. The chief finding in the study was an increased incidence of skin fibrosarcomas in treated males of the high-dose group. There were 2 such neoplasms in the low dose group, 5 in the high dose group and none in control males. Fibrosarcomas in rats are relatively infrequent, usually occurring in less than 3% of animals.
Valproic acid was also administered in the diet to female mice for nearly 19 months at doses of 81 and 163 mg/kg/day and to male mice for nearly 23 months at doses of 80 and 159 mg/kg/day. A significant dose related trend occurred in male mice in the incidence of bronchoalveolar adenomas, and when the data were adjusted for the times of death, the incidence in the high dose group was significantly increased.
Depending on the method of statistical analysis, the incidence of hepatocellular carcinomas and/or adenomas also showed significant or almost significant increases for the corresponding observations. The results of these two studies indicate that valproic acid is a weak carcinogen or promoter in rats and mice. The significance of these findings for humans is unknown at present.
Subcutaneous fibrosarcomas were observed in male rats and hepatocellular carcinomas and bronchiolo-alveolar adenomas were observed in male mice at incidences slightly higher than concurrent study controls but comparable to those in registries of historical controls.
Reproductive and developmental toxicology
- Development
Teratogenic effects, including increased frequencies of malformations of multiple organ systems, intrauterine growth retardation and death, have been demonstrated in mice, rats, rabbits and monkeys following prenatal exposure to valproate. Doses greater than 65 mg/kg/day given to rats, mice and rabbits produced an increased incidence of skeletal abnormalities of the ribs, vertebrae and palate. Animal studies show that in utero exposure to valproate results in morphological and functional alterations of the auditory system in rats and mice.
Neural tube closure defects have been seen in mice exposed to maternal plasma valproate concentrations exceeding 230 mcg/mL (2.3 times the upper limit of the human therapeutic range for epilepsy) during susceptible periods of embryonic development.
Studies in rats have shown placental transfer of the drug. Administration of an oral dose of 200 mg/kg/day or greater (50% of the maximum human daily dose or greater on a mg/m2 basis) to pregnant rats during organogenesis produced malformations (skeletal, cardiac and urogenital) and growth retardation in the offspring. These doses resulted in peak maternal plasma valproate levels of approximately 340 mcg/mL or greater (3.4 times the upper limit of the human therapeutic range for epilepsy or greater). Embryolethality was observed at doses of 350 mg/kg/day. There was a dose related delay in onset of parturition. Post-natal growth and survival of the progeny were adversely affected, particularly when drug administration spanned the entire gestation and early lactation period. Survival among pups born to the high dose females was very poor but was improved when pups were transferred to control dams shortly after birth. Behavioural deficits have been reported in the offspring of rats given a dose of 200 mg/kg/day throughout most of pregnancy.
Doses greater than 150 mg/kg/day given to pregnant rabbits produced fetal resorptions and (primarily) soft-tissue abnormalities in the offspring. At an oral dose of 350 mg/kg/day (approximately 2 times the maximum human daily dose on a mg/m2 basis) embryolethality and skeletal and visceral malformations were observed in rabbits exposed during organogenesis.
Skeletal malformations, growth retardation, and death were observed in rhesus monkeys following administration of an oral dose of 200 mg/kg/day (equal to the maximum human daily dose on a mg/m2 basis) during organogenesis. This dose resulted in peak maternal plasma valproate levels of approximately 280 mcg/mL (2.8 times the upper limit of the human therapeutic range for epilepsy).
In mice, rats, and rabbits, in utero exposure to valproate induced a dose-related decrease in fetal weight, intra-uterine growth restriction and reduction in crown rump length compared to unexposed animals.
In published literature, behavioral abnormalities have been reported in first generation offspring of mice and rats after in utero exposure to clinically relevant doses/exposures of valproate. In mice, behavioral changes have also been observed in the 2nd and 3rd generations, albeit less pronounced in the 3rd generation, following an acute in utero exposure of the first generation from dams dosed with valproate at 300 mg/kg (i.p.) or 500 mg/kg (s.c.) valproate on GD 10 or 10.5, respectively. The relevance of these findings for humans is unknown.
Fertility
Chronic toxicity studies in adult rats and dogs demonstrated reduced spermatogenesis and testicular atrophy at oral doses of valproic acid of 400 mg/kg/day or greater in rats (approximately equivalent to or greater than the maximum human daily dose on a mg/m2 basis) and 150 mg/kg/day or greater in dogs (approximately 1.4 times the maximum human daily dose or greater on a mg/m2 basis). Segment I fertility studies in rats have shown that oral doses up to 350 mg/kg/day (approximately equal to the maximum human daily dose on a mg/m2 basis) for 60 days have no effect on fertility.
In juvenile rats, a decrease in testes weight was only observed at doses exceeding the maximum tolerated dose (from 240 mg/kg/day by intraperitoneal or intravenous route) and with no associated histopathological changes. No effects on the male reproductive organs were noted at tolerated doses (up to 90 mg/kg/day). There are insufficient data to determine the effect of valproate on testicular development in humans (see 8.5 Post-Market Adverse Reactions, Reproductive Findings).