


Product Monograph - Digoxin Injection C.S.D.
RECENT MAJOR LABEL CHANGES
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics (<10 years of age) ................................................................................ 4
1.2 Geriatrics (>70 years of age) ................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ......................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .................................................... 5
4.4 Administration ................................................................................................... 10
4.5 Missed Dose ....................................................................................................... 11
5 OVERDOSAGE ........................................................................................................... 11
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................... 12
7 WARNINGS AND PRECAUTIONS ................................................................................ 13
7.1 Special Populations ............................................................................................ 16
7.1.1 Pregnant Women ................................................................................................... 16
7.1.2 Breast-feeding ........................................................................................................ 16
7.1.3 Pediatrics (<10 years of age) .................................................................................. 16
7.1.4 Geriatrics (>70 years of age) .................................................................................. 16
8 ADVERSE REACTIONS................................................................................................ 17
8.1 Adverse Reaction Overview ............................................................................... 17
8.2 Clinical Trial Adverse Reactions ......................................................................... 18
8.3 Less Common Clinical Trial Adverse Reactions (<1%) ........................................ 20
8.5 Post-Market Adverse Reactions ......................................................................... 20
9 DRUG INTERACTIONS ............................................................................................... 20
9.2 Drug Interactions Overview ............................................................................... 20
9.3 Drug-Behavioural Interactions ........................................................................... 21
9.4 Drug-Drug Interactions ...................................................................................... 21
9.5 Drug-Food Interactions ...................................................................................... 28
9.6 Drug-Herb Interactions ...................................................................................... 28
9.7 Drug-Laboratory Test Interactions..................................................................... 28
10 CLINICAL PHARMACOLOGY ....................................................................................... 28
10.1 Mechanism of Action ......................................................................................... 28
10.2 Pharmacodynamics ............................................................................................ 29
10.3 Pharmacokinetics ............................................................................................... 30
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 31
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 31
PART II: SCIENTIFIC INFORMATION ...................................................................................... 32
13 PHARMACEUTICAL INFORMATION ........................................................................... 32
14 CLINICAL TRIALS ....................................................................................................... 33
14.1 Trial Design and Study Demographics ............................................................... 33
14.2 Study results ....................................................................................................... 34
15 MICROBIOLOGY ....................................................................................................... 36
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 36
PATIENT MEDICATION INFORMATION ................................................................................. 37
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
DIGOXIN INJECTION C.S.D. (Digoxin Injection) is indicated for:
Congestive Heart Failure: Digoxin Injection is indicated for the treatment of mild to moderate heart failure. Digoxin Injection increases left ventricular ejection fraction and improves heart failure symptoms as evidenced by exercise capacity and heart failure-related hospitalizations and emergency care, while having no effect on mortality. Where possible, Digoxin Injection should be used with a diuretic and angiotensin-converting enzyme inhibitor, but an optimal order for starting these three drugs cannot be specified.
Digoxin is usually continued after failure is controlled unless some known precipitating factor is corrected. Studies have shown that withdrawal of digoxin may worsen functional status, exercise capacity, and the left ventricular ejection fraction in patients with heart failure. In patients in whom digoxin may be difficult to regulate, or in whom the risk of toxicity may be great (e.g. patients with unstable renal function or whose potassium levels tend to fluctuate) a cautious withdrawal of digoxin may be considered. If digoxin is discontinued, the patient should be regularly monitored for clinical evidence of recurrent heart failure.
- Atrial Fibrillation: Digoxin Injection is indicated for the control of ventricular response rate in patients with chronic atrial fibrillation.
1.1 Pediatrics (<10 years of age)
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Digoxin Injection in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use. Digitalization in infants and children must be individualized (see 4 DOSAGE AND ADMINISTRATION).
1.2 Geriatrics (>70 years of age)
Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 4 DOSAGE AND ADMINISTRATION and 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics.).
2 CONTRAINDICATIONS
- Digitalis glycosides are contraindicated in ventricular fibrillation.
In a given patient, an untoward effect requiring permanent discontinuation of other
- digitalis preparations usually constitutes a contraindication to digoxin.
- DIGOXIN INJECTION is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING. Allergy to digoxin, though rare, does occur. It may not extend to all such preparations, and another digitalis glycoside may be tried with caution.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
General
Recommended dosages of digoxin may require considerable modification because of individual sensitivity of the patient to the drug, the presence of associated conditions, or the use of concurrent medications.
In selecting the dose of digoxin, several factors must be considered:
- 1. The body weight of the patient. Doses should be calculated based upon (i.e. ideal) body weight.
- 2. The patient’s renal function, preferably evaluated on the basis of estimated creatinine clearance.
- 3. The patient’s age. Infants and children require different doses of digoxin than adults. Also, advanced age may be indicative of diminished renal function even in patients with normal serum creatinine concentration (i.e. below 1.5 mg/dL).
- 4. Concomitant disease states, concurrent medication or other factors likely to alter the pharmacokinetic or pharmacodynamic profile of digoxin (see 7 WARNINGS AND PRECAUTIONS).
- 5. To minimize toxic side effects, the lowest effective dose should be used as the maintenance dose.
4.2 Recommended Dose and Dosage Adjustment
Serum Digoxin Concentrations
In general, the dose of digoxin used should be determined on clinical grounds. However, measurement of serum digoxin concentrations can be helpful to the clinician in determining the adequacy of digoxin therapy and in assigning certain probabilities to the likelihood of digoxin intoxication. About two-thirds of adults considered adequately digitalized (without evidence of toxicity) have serum digoxin concentrations ranging from 0.8 to 2.0 ng/mL. However, digoxin may produce clinical benefits even at serum concentrations below this range. About two-thirds of adult patients with clinical toxicity have serum digoxin concentrations greater than 2.0 ng/mL. However, since one-third of patients with clinical toxicity have concentrations less than 2.0 ng/mL, values below 2.0 ng/mL do not rule out the possibility that a certain sign or symptom is related to digoxin therapy. Rarely, there are patients who are unable to tolerate digoxin at serum concentrations below 0.8 ng/mL. Consequently, the serum concentration of digoxin should always be interpreted in the overall clinical context, and an isolated measurement should not be used alone as the basis for increasing or decreasing the dose of the drug.
To allow adequate time for equilibration of digoxin between serum and tissue, sampling of serum concentrations should be done just before the next scheduled dose of the drug. If this is not possible, sampling should be done at least 6 to 8 hours after the last dose, regardless of the route of administration or the formulation used. On a once-daily dosing schedule, the concentration of digoxin will be 10% to 25% lower when sampled at 24 versus 8 hours, depending upon the patient's renal function. On a twice-daily dosing schedule, there will be only minor differences in serum digoxin concentrations whether sampling is done at 8 or 12 hours after a dose.
If a discrepancy exists between the reported serum concentration and the observed clinical response, the clinician should consider the following possibilities:
- 1. Analytical problems in the assay procedure.
- 2. Inappropriate serum sampling time.
- 3. Administration of a digitalis glycoside other than digoxin.
- 4. Conditions (described in 7 WARNINGS and PRECAUTIONS) causing an alteration in the sensitivity of the patient to digoxin.
- 5. Serum digoxin concentration may decrease acutely during periods of exercise without any associated change in clinical efficacy due to increased binding of digoxin to skeletal muscle.
Heart Failure
Adults: Digitalization may be accomplished by either of two general approaches that vary in dosage and frequency of administration, but reach the same endpoint in terms of total amount of digoxin accumulated in the body.
- 1. Rapid digitalization may be achieved by administering a loading dose based upon projected peak body digoxin stores, then calculating the maintenance dose as a percentage of the loading dose.
- 2. More gradual digitalization may be obtained by beginning an appropriate maintenance dose, thus allowing digoxin body stores to accumulate slowly. Steady-state serum digoxin concentrations will be achieved in approximately 5 half-lives of the drug for the individual patient. Depending upon the patient’s renal function, this will take between 1 and 3 weeks.
Maintenance Dosing: The doses of digoxin used in controlled trials in patients with heart failure have ranged from 125 to 500 mcg (0.125 to 0.5 mg) in these studies, the digoxin dose has been generally titrated according to the patient’s age, lean body weight, and renal function. Therapy is generally initiated at a dose of 250 mcg (0.25 mg) once daily in patients under age of 70 with good renal function, at a dose of 125 mcg (0.125 mg) once daily in patients over age 70 or with impaired renal function, and at a dose of 62.5 mcg (0.0625 mg) in patients with marked renal impairment. Dose may be increased every 2 weeks according to clinical response.
In a subset of approximately 1800 patients enrolled in the DIG trial (wherein dosing was based on an algorithm similar to that in Table 3) the mean (± SD) serum digoxin concentrations at 1 month and 12 months were 1.01 ± 0.47 ng/ mL and 0.97 ± 0.43 ng/ mL, respectively.
The maintenance dose should be based upon the percentage of the peak body stores lost each day through elimination. The following formula has had a wide clinical use:
Maintenance dose = Peak body stores (i.e. Loading Dose) x % Daily Loss
100
Where % Daily Loss = 14 Ccr/5
(Ccr is creatinine clearance, corrected to 70 kg body weight or 1.73 m2 body surface area.)
Rapid Digitalization with a Loading Dose: Peak body digoxin stores of 8 to 12 mcg/kg should provide therapeutic effect with minimum risk of toxicity in most patients with heart failure and normal sinus rhythm. Because of altered digoxin distribution and elimination, projected peak body stores for patients with renal insufficiency should be conservative (i.e. 6 to 10 mcg/kg) (see 7 WARNINGS AND PRECAUTIONS).
The loading dose should be administered in several portions, with roughly half the total given as the first dose. Additional fractions of this planned total dose may be given at 6 to 8 hour intervals, with careful assessment of clinical response before each additional dose.
If the patient’s clinical response necessitates a change from the calculated dose of digoxin, then calculation of the maintenance dose should be based upon the amount actually given.
A single initial dose of 500 to 750 mcg (0.5 to 0.75 mg) of digoxin tablets usually produces a detectable effect in 0.5 to 2 hours that becomes maximal in 2 to 6 hours. Additional doses of 125 to 375 mcg (0.125 to 0.375 mg) may be given cautiously at 6 to 8 hour intervals until clinical evidence of an adequate effect is noted. The usual amount of digoxin tablet that a 70 kg patient requires to achieve 8 to 12 mcg/kg peak body stores is 750 to 1250 mcg (0.75 to 1.25 mg).
Digoxin injection is frequently used to achieve rapid digitalization, with conversion to digoxin tablet for maintenance therapy. If patients are switched from intravenous to oral digoxin formulations, allowances must be made for differences in bioavailability when calculating maintenance dosages.
Table 1: Usual Daily Maintenance Dose Requirements of Digoxin (mcg) for
Estimated Peak Body Stores of 10 mcg/kg
| Body Weight (kg) | Number of Days Before Steady State Achieved** | ||||||||||||||||
Corrected Ccr (mL/min per 70 kg)* | kg | 50 | 60 | 70 | 80 | 90 | 100 | ||||||||||
| 0 | 62.5*** | 125 | 125 | 125 | 187.5 | 187.5 | 22 | ||||||||||
| 10 | 125 | 125 | 125 | 187.5 | 187.5 | 187.5 | 19 | ||||||||||
| 20 | 125 | 125 | 187.5 | 187.5 | 187.5 | 250 | 16 | ||||||||||
| 30 | 125 | 187.5 | 187.5 | 187.5 | 250 | 250 | 14 | ||||||||||
| 40 | 125 | 187.5 | 187.5 | 250 | 250 | 250 | 13 | ||||||||||
| 50 | 187.5 | 187.5 | 250 | 250 | 250 | 250 | 12 | ||||||||||
| 60 | 187.5 | 187.5 | 250 | 250 | 250 | 375 | 11 | ||||||||||
| 70 | 187.5 | 250 | 250 | 250 | 250 | 375 | 10 | ||||||||||
| 80 | 187.5 | 250 | 250 | 250 | 375 | 375 | 9 | ||||||||||
| 90 | 187.5 | 250 | 250 | 250 | 375 | 500 | 8 | ||||||||||
| 100 | 250 | 250 | 250 | 375 | 375 | 500 | 7 | ||||||||||
*Ccr is creatinine clearance, corrected to 70 kg body weight or 1.73 m2 body surface area. For adults, if only serum creatinine concentrations (Scr) are available, a Ccr (corrected to 70 kg body weight) may be estimated in men as (140 - Age)/Scr. For women, this result should be multiplied by 0.85. Note: This equation cannot be used for estimating creatinine clearance in infants or children.
** If no loading dose administered.
*** 62.5 mcg = 0.0625 mg
Example: Based on Table 1, a patient in heart failure with an estimated lean body weight of 70 kg and Ccr of 60 mL/min, should be given 250 mcg (0.25 mg) daily of digoxin usually taken after the morning meal. If no loading dose is administered, steady-state serum concentration in this patient should be anticipated at approximately 11 days.
Geriatrics (>70 years of age): Given the higher incidence of concomitant illness (renal, hepatic and cardiovascular) and concomitant medication in the elderly, TOLOXIN should be used with caution in this population. See 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.4 Geriatrics.
Pediatrics (<10 years of age): In general, divided daily dosing is recommended for infants and young children (under age 10). In the newborn period, renal clearance of digoxin is diminished and suitable dosage adjustments must be observed. This is especially pronounced in the premature infant. Beyond the immediate newborn period, children generally require proportionally larger doses than adults on the basis of body weight or body surface area. Children over 10 years of age require adult dosages in proportion to their body weight. Some researchers have suggested that infants and young children tolerate slightly higher serum concentrations than do adults.
Additional Information for Digoxin Injection
Rapid Digitalization with a Loading Dose: A digoxin injection can be used to achieve rapid digitalization, with conversion to an oral formulation of digoxin for maintenance therapy. If patients are switched from intravenous to oral digoxin formulations, allowances must be made for differences in bioavailability when calculating maintenance dosages (see Table 2).
Peak digoxin body stores of 8 to 12 mcg/kg should provide therapeutic effect with minimum risk of toxicity in most patients with heart failure and normal sinus rhythm. Because of altered digoxin distribution and elimination, projected peak body stores for patients with renal insufficiency should be conservative (i.e. 6 to 10 mcg/kg (see 7 WARNINGS AND PRECAUTIONS)).
Digitalizing and daily maintenance doses for each age group are given in Table 2 and should provide therapeutic effect with minimum risk of toxicity in most patients with heart failure and normal sinus rhythm. These recommendations assume the presence of normal renal function.
The loading dose should be administered in several portions, with roughly half the total given as the first dose. Additional fractions of this planned total dose may be given at 6- to 8-hour intervals, with careful assessment of clinical response before each additional dose. If the patients’ clinical response necessitates a change from the calculated loading dose of digoxin, then calculation of the maintenance dose should be based upon the amount actually given.
| Table 2: Usual Digitalizing and Maintenance Dosages for Digoxin Oral Solution in Children with Normal Renal Function Based on Lean Body Weight | |||
| Age | Oral Digitalizing* Dose (mcg/kg) | IV Digitializing Dose (mcg/kg) | Daily Maintenance Dose† (mcg/kg) |
| Premature | 20 to 30 | 15 to 25 | 20% to 30% of oral [or IV] digitalizing dose ‡ |
| Full-Term | 25 to 35 | 20 to 30 | 25% to 35% of oral [or IV] digitalizing dose ‡ |
| 1 to 24 Months | 35 to 60 | 30 to 50 | |
| 2 to 5 Years | 30 to 40 | 25 to 35 | |
| 5 to 10 Years | 20 to 35 | 15 to 30 | |
| Over 10 Years | 10 to 15 | 8 to 12 | |
| * IV digitalizing doses are 80% of oral digitalizing doses. | |||
| † Divided daily dosing is recommended for children under 10 years of age. | |||
| ‡ Projected or actual digitalizing dose providing clinical response. | |||
In children with renal disease, digoxin must be carefully titrated based upon clinical response.
Gradual Digitalization with a Maintenance Dose
More gradual digitalization can also be accomplished by beginning an appropriate maintenance dose. The range of percentages provided in Table 2 can be used in calculating this dose for patients with normal renal function.
It cannot be overemphasized that both the adult and pediatric dosage guidelines provided are based upon average patient response and substantial individual variation can be expected. Accordingly, ultimate dosage selection must be based upon clinical assessment of the patient.
Artial Fibrillation
Adults and Children: Peak digoxin body stores larger than 8-12 mcg/kg required for most patients with heart failure and normal sinus rhythm have been used in control of ventricular rate in patients with atrial fibrillation. Doses of digoxin used for the treatment of chronic atrial fibrillation should be titrated to the minimum dose that achieves the desired ventricular rate control without causing undesirable side effects. Data are not available to establish the appropriate resting or exercise target rates that should be achieved.
Dosage Adjustment When Changing Preparations: The difference in bioavailability between intravenous digoxin and oral solution or tablet formulations must be considered when changing from one dosage to another.
It has been shown that differences in formulations of digoxin, despite an identical content of active ingredients, may be associated with differences in fractional gastrointestinal absorption. Consequently, differences in bioavailability between different formulations of digoxin tablets must be considered when changing from one brand to another. In switching to another digoxin product, particular emphasis needs to be placed on clinical monitoring of patients and monitoring of serum digoxin levels and potassium levels. Small changes in serum levels of digoxin may lead to inadequate digitalization or to toxicity. Inadequate digitalization, may result in appearance of symptoms of atrial fibrillation such as tachycardia, palpitation, and dyspnea. Toxic levels of digoxin may produce loss of appetite, nausea, vomiting, drowsiness, bradycardia, and visual disturbances. These effects are particularly important in elderly and pediatric patients and in those with coexisting diseases or receiving concurrent medication.
4.4 Administration
Digoxin Injection is given as an intravenous injection by a doctor or nurse. Digoxin is usually given in injectable form to stabilize the condition. It may take several weeks to several months for digoxin to improve the heart function.
A lower dose may be required in the elderly, in children, or in patients with kidney problems.
4.5 Missed Dose
If a dose is missed, patients are advised to take the dose as soon as remembered if within 12 hours of scheduled dose and not take if remembered later. Patients are advised not to double doses and to consult their doctor if a dose is missed for 2 days or more.
5 OVERDOSAGE
Adults
Digoxin should be temporarily discontinued until the adverse reaction resolves.
Every effort should also be made to correct factors that may contribute to the adverse reaction (such as electrolyte disturbances or concurrent medications). Once the adverse reaction has resolved, therapy with digoxin may be reinstituted, following a careful reassessment of dose.
Withdrawal of digoxin may be all that is required to treat the adverse reaction. However, when the primary manifestation of digoxin overdosage is a cardiac arrhythmia, additional therapy may be needed.
If the rhythm disturbance is a symptomatic bradyarrhythmia or heart block, consideration should be given to the reversal of toxicity with Digoxin Immune Fab (Ovine) (see Massive Digitalis Overdosage subsection), the use of atropine, or the insertion of a temporary cardiac pacemaker. However, asymptomatic bradycardia or heart block related to digoxin may require only temporary withdrawal of the drug and cardiac monitoring of the patient.
If the rhythm disturbance is a ventricular arrhythmia, consideration should be given to the correction of electrolyte disorders, particularly if hypokalemia (see Administration of Potassium subsection) or hypomagnesemia is present. Digoxin Immune Fab (Ovine) is a specific antidote for digoxin and may be used to reverse potentially life-threatening ventricular arrhythmias due to digoxin overdosage.
Administration of Potassium
Every effort should be made to maintain the serum potassium concentration between 4.0 and 5.5 mmol/L. Potassium is usually administered orally, but when correction of the arrhythmia is urgent and the serum potassium concentration is low, potassium may be administered cautiously by the intravenous route. The electrocardiogram should be monitored for any evidence of potassium toxicity (e.g. peaking of T waves) and to observe the effect on the arrhythmia. Potassium salts may be dangerous in patients who manifest bradycardia or heart block due to digoxin (unless primarily related to supraventricular tachycardia) and in the setting of massive digitalis overdosage (see Massive Digitalis Overdosage subsection).
Massive Digitalis Overdosage: Manifestations of life-threatening toxicity include severe ventricular tachycardia or ventricular fibrillation, or progressive bradyarrhythmias or heart block. The administration of more than 10 mg of digoxin in a previously healthy adult, or more than 4 mg in a previously healthy child or a steady-state serum concentration greater than 10 ng/mL, often results in cardiac arrest.
Digoxin Immune Fab (Ovine) should be used to reverse the toxic effect of a massive overdose. The decision to administer Digoxin Immune Fab (Ovine) to a patient who has ingested a massive dose of digoxin but who has not yet manifested life-threatening toxicity should depend on the likelihood that the life-threatening toxicity will occur.
Patients with massive digitalis ingestion should receive large doses of activated charcoal to prevent absorption and bind digoxin in the gut during enteroenteric recirculation. Emesis or gastric lavage may be indicated especially if ingestion has occurred within 30 minutes of the patient’s presentation at the hospital. Emesis should not be induced in patients who are obtunded. If a patient presents more than 2 hours after ingestion or already has toxic manifestations, it may be unsafe to induce vomiting or attempt passage of a gastric tube, because such maneuvers may induce an acute vagal episode that can worsen digitalis-related arrhythmias.
Severe digitalis intoxication can cause a massive shift of potassium from inside to outside the cell, leading to life-threatening hyperkalemia. The administration of potassium supplements in the setting of massive intoxication may be hazardous and should be avoided. Hyperkalemia caused by massive digitalis toxicity is best treated with Digoxin Immune Fab (Ovine); initial treatment with glucose and insulin may also be required if hyperkalemia itself is acutely life-threatening.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form/ Strength | Clinically Relevant Nonmedicinal Ingredients |
| Intravenous or intramuscular | liquid 0.5 mg / 2mL | ethyl alcohol 10 %, propylene glycol 40 %, citric acid 0.08%, sodium phosphate 0.3 % and water for injection. |
Digoxin Injection C.S.D. 0.5 mg / 2mL
Each mL of clear, colourless liquid contains: digoxin 0.25 mg, ethyl alcohol 10 %, propylene glycol 40 %, citric acid 0.08%, sodium phosphate 0.3 % and water for injection.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
Digoxin Injection C.S.D. 0.5 mg / 2 mL is available as 2 mL ampoules, boxes of 10.
7 WARNINGS AND PRECAUTIONS
General
Digitalis alone or with other drugs has been used in the treatment of obesity. This use of digoxin or other digitalis glycosides is unwarranted. Moreover, since they may cause potentially fatal arrhythmias or other adverse effects, the use of these drugs solely for the treatment of obesity is dangerous.
Anorexia, nausea, vomiting and arrhythmias may accompany heart failure or may be indications of digitalis intoxication. Clinical evaluation of the cause of the symptoms should be attempted before further digitalis administration. In such circumstances determination of the serum digoxin concentration may be an aid in deciding whether or not digitalis toxicity is likely to be present. If the possibility of digitalis intoxication cannot be excluded, cardiac glycosides should be temporarily withheld, if permitted by the clinical situation.
Patients with renal insufficiency require smaller than usual maintenance doses of Digoxin Injection (see 4 DOSAGE AND ADMINISTRATION).
Heart failure accompanying acute glomerulonephritis requires extreme care in digitalization. Relatively low loading and maintenance doses and concomitant use of antihypertensive drugs may be necessary and careful monitoring is essential. Digoxin Injection should be discontinued as soon as possible, especially if a therapeutic trial does not result in improvement. Patients with severe carditis, such as carditis associated with rheumatic fever or viral myocarditis, are especially sensitive to digoxin-induced disturbances of rhythm.
Newborn infants display considerable variability in their tolerance to digoxin. Premature and immature infants are particularly sensitive and dosage must not only be reduced but must be individualized according to their degree of maturity. Impaired renal function must also be carefully taken into consideration.
Dosage of digoxin must be carefully titrated and differences in the bioavailability of parenteral preparations, oral solution and tablets taken into account when changing patients from one preparation to another.
Carcinogenesis and Mutagenesis
There have been no long-term studies performed in animals to evaluate carcinogenic potential, nor have studies been conducted to assess the mutagenic potential of digoxin or its potential to affect fertility.
Cardiovascular
Use During Electrical Cardioversion
Reduction of digoxin dosage may be desirable prior to electrical cardioversion to avoid induction of ventricular arrhythmias, but the physician must consider the consequences of rapid increase in ventricular response to atrial fibrillation if digoxin is withheld 1 to 2 days prior to cardioversion. If there is a suspicion that digitalis toxicity exists, elective cardioversion should be delayed. If it is not prudent to delay cardioversion, the energy level selected should be minimal at first and carefully increased in an attempt to avoid precipitating ventricular arrhythmias.
Sinus Node Disease and AV Block
Incomplete AV block, especially in patients with Stokes-Adams attacks, may progress to advanced or complete heart block if digoxin is given. Heart failure in these patients can usually be controlled by other measures and by increasing the heart rate. If digitalization is essential, electrical pacing of the ventricles may be indicated. In some patients with sinus node disease (i.e. Sick Sinus Syndrome), digoxin may worsen sinus bradycardia or sinoatrial block. Digoxin is not indicated for the treatment of sinus tachycardia unless it is associated with heart failure.
Accessory AV Pathway (Wolff-Parkinson-White Syndrome)
In patients with Wolff-Parkinson-White Syndrome and atrial fibrillation, digoxin can enhance transmission of impulses through the accessory pathway. This effect may result in extremely rapid ventricular rates and even ventricular fibrillation.
Use in Patients with Preserved Left Ventricular Systolic Function
Digoxin may worsen the outflow obstruction in patients with idiopathic hypertrophic subaortic stenosis (IHSS). Unless cardiac failure is severe, it is doubtful whether digoxin should be employed. Patients with chronic constrictive pericarditis may fail to respond to digoxin. In addition, slowing of the heart rate by digoxin in some patients may further decrease cardiac output. Patients with heart failure from amyloid heart disease or constrictive cardiomyopathies respond poorly to treatment with digoxin. Patients with severe carditis, such as carditis associated with rheumatic fever or viral myocarditis, are especially sensitive to digoxin-induced disturbances of rhythm.
Use in Patients with Acute Myocardial Infarction
Digoxin should be used with caution in patients with acute myocardial infarction. The use of inotropic drugs in some patients in this setting may result in undesirable increases in myocardial oxygen demand and ischemia.
Multifocal Atrial Tachycardia
Digoxin should not be used for the treatment of multifocal atrial tachycardia.
Dependence/Tolerance
No drug dependence has been reported with the use of digoxin.
Endocrine and Metabolism
In Patients with Electrolyte Disorders
In patients with hypokalemia, toxicity may occur despite serum digoxin concentrations within the normal range, because potassium depletion sensitizes the myocardium to digoxin. Therefore, it is desirable to maintain normal serum potassium levels in patients being treated with digoxin. Hypokalemia may result from diuretic, amphotericin B or corticosteroid therapy, and from peritoneal or hemodialysis or mechanical suction of gastrointestinal secretions. It may also accompany malnutrition, diarrhea, prolonged vomiting, old age, long-standing heart failure, long-standing wasting diseases and treatment with ion-exchange resins or carbenoxolone. In general, rapid changes in serum potassium or other electrolytes should be avoided, and IV treatment with potassium should be reserved for special circumstances as described below (see 5 OVERDOSAGE).
Calcium, particularly when administered rapidly by the intravenous route, may produce serious arrhythmias in digitalized patients. Hypercalcemia from any cause predisposes the patient to digitalis toxicity. On the other hand, hypocalcemia can nullify the effects of digoxin in man; thus digoxin may be ineffective until serum calcium is restored to normal. These interactions are elated to the fact that calcium affects contractility and excitability of the heart in a manner similar to digoxin.
Hypomagnesemia may predispose to digitalis toxicity. If low magnesium levels are detected in a patient on digoxin, replacement therapy should be instituted.
Use in Thyroid Disorders and Hypermetabolic States
In hypothyroidism, the digoxin requirements are reduced. Digoxin responses in patients with compensated thyroid disease are normal. Heart failure and/or atrial arrhythmias resulting from hypermetabolic or hyperdynamic states (e.g., hyperthyroidism, hypoxia, or arteriovenous shunt) are best treated by addressing the underlying condition. Atrial arrhythmias associated with hypermetabolic states are particularly resistant to digoxin treatment. Care must be taken to avoid toxicity if digoxin is used.
Monitoring and Laboratory Tests
Patients receiving Digoxin Injection should have their serum electrolytes and renal function (BUN and/or serum creatinine) assessed periodically; the frequency of assessments will depend on the clinical setting. For discussion of serum digoxin concentrations, (see 4 DOSAGE AND ADMINISTRATION).
The use of therapeutic doses of digoxin may cause prolongation of the PR interval and depression of the ST segment on the electrocardiogram. Digoxin may produce false positive ST-T changes on the electrocardiogram during exercise testing. These electrophysiologic effects reflect an expected effect of the drug and are not indicative of toxicity.
Renal
In Patients with Renal Disease
Patients with renal insufficiency require smaller than usual maintenance doses of digoxin (see 4 DOSAGE AND ADMINISTRATION) .
If the patient has been given digoxin during the previous week or any other less rapidly excreted drug of the digitalis group during the previous 2 weeks, the dose of digoxin must be reduced accordingly. Digoxin toxicity develops more frequently and lasts longer in patients with renal impairment because of the decreased excretion of digoxin. Therefore, it should be anticipated that dosage requirements will be decreased in patients with moderate to severe renal disease (see 4 DOSAGE AND ADMINISTRATION) . Because of impaired renal function and excretion in elderly patients, they frequently require lower than recommended doses. Because of the prolonged half-life, a longer period of time is required to achieve an initial or new steady-state concentration in patients with renal impairment than in patients with normal renal function.
7.1 Special Populations
7.1.1 Pregnant Women
Teratogenic Effects: Animal reproduction studies have not been conducted with digoxin. It is also not known whether digoxin can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity, although there have been no reports of teratogenic effects following the use of digoxin in pregnancy since its availability in 1929. Digoxin should be given to pregnant women only if clearly needed.
7.1.2 Breast-feeding
Studies have shown that digoxin concentrations in the mother’s serum and milk are similar. However, the estimated daily dose to a nursing infant will be far below the usual infant maintenance dose. Therefore, this amount should have no pharmacologic effect upon the infant. Nevertheless, caution should be exercised when digoxin is administered to a nursing woman.
7.1.3 Pediatrics (<10 years of age)
Digitalis glycosides are a major cause of poisoning in children. The tolerance of newborn infants to digitalis glycosides is variable, since their renal clearance of the medication is reduced. Premature and immature infants are especially sensitive. Dosage of digoxin should be reduced and individualized according to the infant’s degree of maturity, since renal clearance increases as the infant matures. Children older than 1 month of age generally require proportionally larger doses than adults on the basis of body weight or body surface area.
7.1.4 Geriatrics (>70 years of age)
Although appropriate studies on the relationship of age to the effects of digitalis glycosides have not been performed in the geriatric population, the majority of experience with digoxin is in this population. This drug is known to be substantially excreted by the kidneys, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients may be more likely to have age-related renal function impairment, which may significantly increase the elimination half-life of digoxin, care should be taken in dose selection, which should be based on renal function, and it may be useful to monitor renal function (see 4 DOSAGE AND ADMINISTRATION). Additionally, elderly patients may have a decreased volume of distribution of digitalis due to decreased muscle mass. These factors may contribute to digitalis toxicity in elderly patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
In general, the adverse reactions of digoxin are dose-dependent and occur at doses higher than those needed to achieve a therapeutic effect. Hence, adverse reactions are less common when digoxin is used within the recommended dose range or therapeutic serum concentration range and when there is careful attention to concurrent medications and conditions.
Because some patients may be particularly susceptible to side effects with digoxin, the dosage of the drug should always be selected carefully and adjusted as the clinical condition of the patient warrants. In the past, when high doses of digoxin were used and little attention was paid to clinical status or concurrent medications, adverse reactions to digoxin were more frequent and severe. Cardiac adverse reactions accounted for about one-half, gastrointestinal disturbances for about one-fourth, and CNS and other toxicity for about one-fourth of these adverse reactions. However, available evidence suggests that the incidence and severity of digoxin toxicity has decreased substantially in recent years. In recent controlled clinical trials, in patients with predominantly mild to moderate heart failure, the incidence of adverse experiences was comparable in patients taking digoxin and in those taking placebo. In a large mortality trial, the incidence of hospitalization for suspected digoxin toxicity was 2% in patients taking digoxin compared to 0.9% in patients taking placebo. In this trial, the most common manifestations of digoxin toxicity included gastrointestinal and cardiac disturbances; CNS manifestations were less common.
Adults
Cardiac:
Unifocal or multiform ventricular premature contractions, especially in bigeminal or trigeminal patterns, are the most common arrhythmias associated with digoxin toxicity in adults with heart disease. Persistent bigeminy at rest but not on exercise when the sinus rate increases has traditionally been acceptable in the management of some arrhythmias. Ventricular tachycardia and ventricular fibrillation may result from digitalis toxicity. Atrioventricular (AV) dissociation, accelerated junctional (nodal) rhythm and atrial tachycardia with block are also common arrhythmias caused by digoxin overdosage. Excessive slowing of the pulse is a clinical sign of digoxin overdosage. AV block (Wenckebach) of increasing degree may proceed to complete heart block (including asystole).
Note: The electrocardiogram is fundamental in determining the presence and nature of these cardiac disturbances.
Digoxin may also induce other changes in the ECG (e.g. PR prolongation, ST depression), which represent digoxin effect and may or may not be associated with digitalis toxicity. Cardiac toxicity can also occur at therapeutic doses in patients who have conditions which may alter their sensitivity to digoxin (see 7 WARNINGS AND PRECAUTIONS).
Gastrointestinal:
Anorexia, nausea, vomiting, and less commonly, diarrhea are common early symptoms of overdosage. However, uncontrolled heart failure may also produce such symptoms. Rarely, the use of digoxin has been associated with abdominal pain.
It is inadvisable to rely on nausea as an early warning of excessive digoxin as arrhythmias may occur first.
Central Nervous System:
Visual disturbances (blurred or yellow vision), headache, weakness, apathy, psychosis, and mental disturbances (such as anxiety, depression, delerium, and hallucination) can occur.
Other:
Gynecomastia is occasionally observed following prolonged use of digoxin. Thrombocytopenia and maculopapular rash and other skin reactions have been rarely observed.
Pediatrics
Toxicity differs from the adult in a number of respects. Anorexia, nausea, vomiting, diarrhea and CNS disturbances may be present but are rare as initial symptoms in infants. Cardiac arrhythmias are more reliable signs of toxicity. Digoxin in children may produce any arrhythmia. The most commonly encountered are conduction disturbances or supraventricular tachyarrhythmias, such as atrial tachycardia with or without block and junctional (nodal) tachycardia. Ventricular arrhythmias are less common. Sinus bradycardia may also be a sign of impending digoxin intoxication, especially in infants, even in the absence of first-degree heart block. Any arrhythmia or alteration in cardiac conduction that develops in a child taking digoxin should initially be assumed to be a consequence of digoxin intoxication, until further evaluation proves otherwise.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials, therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Table 4 summarizes the incidence of those adverse experiences listed above for patients treated with digoxin tablets or placebo from two randomized, double-blind, placebo-controlled withdrawal trials. Patients in these trials were also receiving diuretics with or without angiotensin-converting enzyme inhibitors. These patients had been stable on digoxin, and were randomized to digoxin or placebo. The results shown in Table 4 reflect the experience in patients following dosage titration with the use of serum digoxin concentrations and careful follow-up. These adverse experiences are consistent with results from a large, placebo-controlled mortality trial (DIG trial) wherein over half the patients were not receiving digoxin prior to enrollment.
| Table 4: Adverse Experiences in Two Parallel, Double-Blind, Placebo-Controlled Withdrawal Trials with Digoxin Tablets (Number of Patients Reporting) | |||||
| Adverse Experience | Digoxin (n=123) (%) | Placebo Patients (n=125) (%) | |||
| Cardiovascular | |||||
| Palpitation | 1 (0.8) | 4 (3.2) | |||
| Ventricular extrasystole | 1 (0.8) | 1 (0.8) | |||
| Tachycardia | 2 (1.6) | 1 (0.8) | |||
| Heart arrest | 1 (0.8) | 1 (0.8) | |||
| Gastrointestinal | |||||
| Anorexia | 1 (0.8) | 4 (3.2) | |||
| Nausea | 4 (3.3) | 2 (1.6) | |||
| Vomiting | 2 (1.6) | 1 (0.8) | |||
| Diarrhea | 4 (3.3) | 1 (0.8) | |||
| Abdominal pain | 0 | 6 (4.8) | |||
| CNS | |||||
| Headache | 4 (3.3) | 4 (3.2) | |||
| Dizziness | 6 (4.9) | 5 (4.0) | |||
| Mental disturbances | 5 (4.1) | 1 (0.8) | |||
| Other | |||||
| Rash | 2 (1.6) | 1 (0.8) | |||
| Death | 4 (3.3) | 3 (2.4) | |||
8.3 Less Common Clinical Trial Adverse Reactions (<1%)
Gastrointestinal: Rarely, the use of digoxin has been associated with abdominal pain, intestinal ischemia, and hemorrhagic necrosis of the intestines.
Other: Thrombocytopenia and maculopapular rash and other skin reactions have been rarely observed.
8.5 Post-Market Adverse Reactions
Adverse reactions to digoxin are usually dose dependent and occur at dosages higher than those needed to achieve a therapeutic effect.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Digitalis glycosides have a narrow therapeutic range and changes in digoxin pharmacokinetics and/or pharmacodynamics caused by a digoxin-drug interaction can result in toxicity or underdigitalization. The presence of or a change in an underlying disease state also can cause changes in digoxin pharmacokinetics and/or pharmacodynamics and may complicate or contribute to a digoxin-drug interaction. Because a risk of digoxin toxicity exists, and the clinical significance of an interaction may be variable and not necessarily predictable, it is important that the addition or withdrawal of a drug to or from a therapeutic regimen that includes digoxin be carefully evaluated in the context of the patient and the clinical situation.
Potassium-depleting corticosteroids and diuretics may be major contributing factors to digitalis toxicity. Calcium, particularly if administered rapidly by the intravenous route, may produce serious arrhythmias in digitalized patients. Quinidine, verapamil, amiodarone, propafenone, indomethacin, itraconazole, alprazolam, and spironolactone raise the serum digoxin concentration due to a reduction in clearance and/or in volume of distribution of the drug, cause a rise in serum digoxin concentration, with the implication that digitalis intoxication may result. This rise appears to be proportional to the dose.
Certain antibiotics [erythromycin and clarithromycin (and possibly other macrolide antibiotics) and tetracycline] may increase digoxin absorption in patients who inactivate digoxin by bacterial metabolism in the lower intestine, so that digitalis intoxication may result. Recent studies have shown that specific colonic bacteria in the lower gastrointestinal tract convert digoxin to cardioinactive reduction products, thereby reducing its bioavailability. Although inactivation of these bacteria by antibiotics is rapid, the serum digoxin concentration will rise at a rate consistent with the elimination half-life of digoxin. The magnitude of rise in serum digoxin concentrations relates to the extent of bacterial inactivation, and may be as much as 2 fold in some cases.
Propantheline and diphenoxylate, by decreasing gut motility, may increase digoxin absorption. Antacids, kaolin-pectin, sulfasalazine, neomycin, cholestyramine, phenytoin, St. John’s Wort (Hypericum perforatum) and certain anticancer drugs may interfere with intestinal digoxin absorption, resulting in unexpectedly low serum concentrations. Thyroid administration to a digitalized hypothyroid patient may increase the dose requirement of digoxin. Concomitant use of digoxin and sympathomimetics increases the risk of cardiac arrhythmias because both enhance ectopic pacemaker activity. Succinylcholine may cause a sudden extrusion of potassium from muscle cells and may thereby cause arrhythmias in digitalized patients. Although α-adrenergic blockers or calcium channel blockers and digoxin may be useful in combination to control atrial fibrillation, their additive effects on AV node conduction can result in complete heart block.
Due to the considerable variability of these interactions, digoxin dosage should be carefully individualized when patients receive co-administered medications. Furthermore, caution should be exercised when combining digoxin with any drug that may cause a significant deterioration in renal function, since a decline in glomerular filtration or tubular secretion may impair the excretion of digoxin.
9.3 Drug-Behavioural Interactions
Serum digoxin concentration may decrease acutely during periods of exercise without any associated change in clinical efficacy due to increased binding of digoxin to skeletal muscle.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 5: Established or Potential Drug-Drug Interactions with Digoxin
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Albuterol | USP DI 2004 | Concurrent use may decrease serum digoxin concentrations, possibly by redistributing digoxin to other tissues. Albuterol may also decrease serum potassium concentrations, which may increase the risk of digoxin toxicity. |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Alprazolam | USP DI 2004 | Concurrent use may increase serum digoxin concentrations, possibly by decreasing the renal clearance of digoxin; although one small study performed in healthy volunteers concluded that alprazolam had no significant effect on digoxin clearance, contradictory evidence has been reported in patients [primarily elderly patients] receiving long-term digoxin therapy. | |
| Amiodarone | USP DI 2004 | Increases in serum digoxin concentrations by as much as 100% have been reported with concurrent use. Although it is thought that amiodarone decreases renal and/or nonrenal clearance and/or the volume of distribution of digoxin, other contributing factors, such as amiodarone-induced displacement of digoxin from tissue binding sites, also may be involved. Amiodarone has a long elimination half-life [15 to 65 days or longer] and digoxin toxicity may not appear until several weeks after the addition of amiodarone or may persist long after discontinuation of amiodarone | |
| Antacids or antidiarrheal adsorbents (e.g. kaolin and pectin) or sulfasalazine | USP DI 2004 | Concurrent use may decrease digoxin bioavailability by decreasing digoxin absorption. | In the case of antidiarrheal adsorbents and sulfasalazine, the digoxin dose may be administered 8 hours before the interacting medication. |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Antibiotics, oral, especially macrolide antibiotics, such as: clarithromycin or erythromycin or tetracycline | USP DI 2004 | Concurrent use of some oral antibiotics may increase serum digoxin concentrations in patients who inactivate digoxin in the lower intestine by bacterial metabolism; in these individuals, altering the bowel flora with certain antibiotics may diminish digoxin conversion to inactive metabolites, resulting in increased serum digoxin concentration; the increase in serum digoxin concentration has been as much as twofold in some cases and correlates with the extent of bacterial inactivation. Although there are limited data, this interaction has been reported with oral use of clarithromycin, erythromycin, and tetracycline | |
| Anticancer medications (such as bleomycin, cyclophospha-mide, cytarabine, doxorubicin, procarbazine, and vincristine) or radiation therapy | USP DI 2004 | Concurrent use may decrease digoxin bioavailability by decreasing digoxin absorption; the reduced absorption that occurs during concurrent use with anticancer medications or radiation therapy may be due to temporary damage to the gastrointestinal mucosa and may continue for several days after treatment. However, digitoxin absorption does not appear to be affected by anticancer agents. | In the case of concurrent use of anticancer medications, a dosage form with greater bioavailability, such as the capsule or solution, may help to minimize decreased bioavailability. |
| Atorvastatin | USP DI 2004 | Concurrent use may increase digoxin serum concentrations; steady-state serum concentration increases of approximately 20% have been reported. | |
| Beta-adrenergic blocking agents including atenolol, carvedilol, metoprolol and propranolol | USP DI 2004 | Concurrent use with these agents may have additive effects on slowing atrioventricular [AV] nodal conduction; concurrent use with carvedilol in patients with hypertension increased the steady-state area under the plasma concentration–time curve [AUC] and trough concentrations of digoxin by 14% and 16%, respectively. | Plasma digoxin concentrations should be monitored when digoxin is co-administered with beta-adrenergic blocking agents. |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Bran fiber, dietary | USP DI 2004 | It is uncertain whether concurrent administration of dietary bran fiber decreases digoxin bioavailability. In one small study, there was presumed to be a decrease in digoxin absorption when concurrent administration of digoxin with 5 grams of fiber resulted in a decrease in urinary excretion of digoxin. Another small study found no change in steady-state serum digoxin concentrations when digoxin was administered 15 to 30 minutes before administration of 11 grams of bran [as a bran muffin], with a second bran muffin administered several hours later. | |
| Bupropion | Clinical Trial | Bupropion (extended-release, 150 mg) administered ~24 hours before digoxin, decreases digoxin AUC0-24h by 40% and increases digoxin renal clearance by 80% in healthy volunteers. | Serum digoxin concentrations should be monitored and dosages adjusted accordingly. |
| Calcium channel blocking agents, especially bepridil or diltiazem or nifedipine or verapamil | USP DI 2004 | Concurrent use with calcium channel blocking agents may have additive effects on AV nodal conduction, which could result in complete heart block; concurrent use also may increase serum digoxin concentrations by reducing digoxin renal clearance, possibly as a result of inhibition of active tubular secretion of digoxin; verapamil may increase serum digoxin concentrations by 30 to 200%; bepridil may increase serum digoxin concentrations by approximately 34%; some studies have reported no interaction with diltiazem while others have reported increases in serum digoxin concentrations of 20 to 60%; contradictory evidence of an interaction also exists for nifedipine, although serum digoxin increases of 15 to 50% have been reported; increases in serum digitoxin concentrations also have been reported with concurrent use of diltiazem and verapamil, although increases were less pronounced than with digoxin use and may be due to a reduction in extrarenal digitoxin clearance. | Serum digitalis concentrations and electrocardiogra m [ECG] should be monitored and dosages should be adjusted accordingly. |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Cholestyramine or colestipol | USP DI 2004 | Colestipol and cholestyramine may delay and reduce the absorption of digoxin. | Digoxin dose may be administered 8 hours before the interacting medication to minimize the interference with digoxin absorption. |
| Cyclosporine | USP DI 2004 | Concurrent use has resulted in increases in serum digoxin concentrations, possibly as a result of decreased apparent volume of distribution and/or plasma clearance of digoxin. | |
| Diphenoxylate or propantheline | USP DI 2004 | Concurrent use may increase digoxin bioavailability; diphenoxylate and propantheline increase digoxin absorption by decreasing intestinal motility. | |
| Diuretics, potassium-depleting (such as bumetanide, ethacrynic acid, furosemide, indapamide, mannitol, or thiazides) or hypokalemia-causing medications | USP DI 2004 | Decreases in serum potassium concentrations that can occur with these medications may increase the risk of digitalis toxicity. | Frequent serum potassium concentration determinations are recommended when these medications are concurrently administered with digoxin. |
| Flecainide | USP DI 2004 | Concurrent use has increased serum digoxin concentrations, on average, by 24%; it also has been speculated that concurrent use may cause a slight additive increase in the PR interval | |
Hepatic enzyme inducers, such as: barbiturates or phenytoin or rifampin | USP DI 2004 | Concurrent use may increase the metabolism of digitoxin; serum digitoxin concentrations have been reported to decrease by 50% in patients who received 180 mg of phenobarbital per day for 12 weeks; decreases in serum digoxin concentrations also have been reported with concurrent use of rifampin, although the mechanism for this interaction is not completely understood. | Serum digitalis concentrations should be monitored and dosages adjusted accordingly. |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Indomethacin | USP DI 2004 | Concurrent use may increase digoxin serum concentrations, possibly by inhibiting the renal elimination of digoxin; two small studies that evaluated the interaction in healthy adult patients did not find a clinically significant interaction. Another small study found a significant increase [about 40% on average] in serum digoxin concentrations in adult heart failure patients treated with digoxin on a long-term basis. A small study in premature infants treated conventionally with indomethacin for patent ductus arteriosus [PDA] found an increase in serum digoxin concentrations of approximately 50% with concurrent use. | |
| Itraconazole | USP DI 2004 | Concurrent use may increase serum digoxin concentrations, possibly by decreasing renal elimination of digoxin; serum digoxin concentration increases of approximately 50% have been reported | |
| Metoclopramide | USP DI 2004 | Concurrent use of metoclopramide may decrease digoxin absorption by increasing gastrointestinal motility; serum digoxin concentrations as determined by AUC have been reported to decrease by about 24%. | |
| Neomycin, oral | USP DI 2004 | Concurrent use decreases the rate and extent of absorption of digoxin. In a study in healthy volunteers, the extent of absorption of digoxin was decreased by as much as 51% after single doses of digoxin and neomycin. The absorption of digoxin also was decreased when the antibiotic was given 3 or 6 hours before the digoxin dose. The mechanism of this interaction has not been established. | It is recommended that digoxin be administered at least 8 hours before neomycin |
| Omeprazole | USP DI 2004 | Concurrent use with digoxin may increase digoxin absorption, possibly by altering gastric acidity; on average, Cmax and AUC values have been reported to be about 10% higher with concurrent use. |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Propafenone | USP DI 2004 | Concurrent use of propafenone with digoxin results in an increase in serum digoxin concentrations ranging from 35 to 85%, which appears to be unrelated to digoxin renal clearance but may be related to a decrease in the volume of distribution and nonrenal clearance of digoxin. | Careful monitoring of digoxin concentrations and dosage reduction of digoxin are recommended when propafenone is initiated, |
| Quinidine or quinine | USP DI 2004 | Concurrent use with quinidine has resulted in increased digoxin plasma concentrations, possibly due to an initial displacement of digoxin from quinidine binding sites, and a reduction in the renal and nonrenal clearance and volume of distribution of digoxin; the extent of the interaction is proportional to plasma quinidine concentrations and, on average, concurrent use results in 100% increases in serum digoxin concentrations, although increases of over 300% have been reported; concurrent use of quinidine with digitoxin has resulted in increases in serum digitoxin concentrations of 30 to 67%, the smaller increases possibly resulting from impairment of extrarenal clearance of digitoxin by quinidine; increases in serum digoxin concentrations also have been reported with concurrent use of quinine. | Serum digitalis concentrations should be monitored and dosage adjusted as indicated. |
| Spironolactone | USP DI 2004 | Concurrent use with digoxin may increase serum digoxin concentrations, possibly by decreasing digoxin renal and nonrenal clearance and/or digoxin volume of distribution; it has been estimated that digoxin plasma concentrations may increase by one third with concurrent use | |
| Succinylcholine | USP DI 2004 | Concurrent use may cause a sudden release of potassium from muscle cells, increasing the risk of arrhythmias in digitalized patients | |
| Sucralfate | USP DI 2004 | Sucralfate was reported to reduce digoxin plasma concentrations by about 19%, presumably by reducing the bioavailability of digoxin. | Sucralfate should not be taken within 2 hours of digoxin |
| Interacting Drugs | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Sympathomi-metics | USP DI 2004 | Concurrent use may increase the risk of cardiac arrhythmias. | |
| Thyroid hormones | USP DI 2004 | Patients with thyroid disease may have an altered sensitivity to digitalis: hyperthyroid patients may have a reduced response to digitalis and hypothyroid patients may have an increased risk of digitalis toxicity. | Increase in digitalis dose may be required with the use of thyroid hormones in a hypothyroid patient. |
Legend: USP DI 2004 = United States Pharmacopeia Drug Information 2004
9.5 Drug-Food Interactions
The amount of digoxin absorbed from an oral digoxin dose may be reduced when taken with meals high in bran fiber. See 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Error! Reference source not found., Bran fiber, dietary.
9.6 Drug-Herb Interactions
St. John’s Wort (Hypericum perforatum) may interfere with intestinal digoxin absorption, resulting in unexpectedly low serum concentrations. Patients are advised to consult with their doctors before taking herbal products.
9.7 Drug-Laboratory Test Interactions
The use of therapeutic doses of digoxin may cause prolongation of the PR interval and depression of the ST segment on the electrocardiogram. Digoxin may produce false positive ST-T changes on the electrocardiogram during exercise testing. These electrophysiologic effects reflect an expected effect of the drug and are not indicative of toxicity.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The influence of digitalis glycosides on the myocardium is dose related, and involves both direct action on cardiac muscle and the specialized conduction system, and indirect actions on cardiovascular system mediated by the autonomic nervous system. The indirect actions mediated by the autonomic nervous system involve a vagomimetic action, which is responsible for the effects of digitalis on the sinoatrial (SA) and atrioventricular (AV) nodes; and also a baroreceptor sensitization which results in increased carotid sinus nerve activity and enhanced sympathetic withdrawal for any given increment in mean arterial pressure. The pharmacologic consequences of these direct and indirect effects are: an increase in the force and velocity of myocardial systolic contraction (positive inotropic action); a slowing of heart rate (negative chronotropic effect); and decreased conduction velocity through the AV node. In higher doses, digitalis increases sympathetic outflow from the CNS to both cardiac and peripheral sympathetic nerves. This increase in sympathetic activity may be an important factor in digitalis cardiac toxicity. Most of the extracardiac manifestations of digitalis toxicity are also mediated by the CNS.
10.2 Pharmacodynamics
Digoxin produces hemodynamic improvement in patients with heart failure. Short and long-term therapy with the drug increases cardiac output and lowers pulmonary artery pressure, pulmonary capillary wedge pressure, and systemic vascular resistance. These hemodynamic effects are accompanied by an increase in the left ventricular ejection fraction and a decrease in end-systolic and end-diastolic dimensions.
Inhibition of Sodium-Potassium – ATPase
Digoxin inhibits sodium-potassium ATPase, an enzyme that regulates the quantity of sodium and potassium inside cells. Inhibition of the enzyme leads to an increase in the intracellular concentration of sodium and thus (by stimulation of sodium-calcium exchange) an increase in the intracellular concentration of calcium.
Positive Inotropic Effect
Both sodium and calcium ions enter cardiac muscle cells during each cycle of depolarization, contraction, and repolarization. The greater the amount of activating calcium, the greater the force of the contraction.
Electrophysiological Actions
Atrial and ventricular muscle and specialized cardiac pacemaker and conduction fibers exhibit differing responses and sensitivities to cardiac glycosides that are a summation of the direct effects of these drugs on cardiac cells and their indirect, neurally mediated effects. At therapeutic, nontoxic serum or plasma concentrations (1 to 2 ng/mL), digoxin decreases automaticity and increases maximal diastolic resting membrane potential predominantly in atrioventricular (AV) nodal tissues, due to an increase in vagal tone and a decrease in sympathetic nervous system activity. There also is a prolongation of the effective refractory period and a decrease in conduction velocity in AV nodal tissue. At higher concentrations, this may cause sinus bradycardia or arrest and/or prolongation of AV conduction or heart block.
Chronic Atrial Fibrillation
In patients with chronic atrial fibrillation, digoxin slows rapid ventricular response rate in a linear dose-response fashion from 0.25 to 0.75 mg/day. Digoxin should not be used for the treatment of multifocal atrial tachycardia.
10.3 Pharmacokinetics
Distribution:
Clinical evidence indicates that the early high serum concentrations do not reflect the concentration of digoxin at its site of action, but that with chronic use, the steady-state post-distribution serum levels are in equilibrium with tissue levels and correlate with pharmacologic effects. In individual patients, these post-distribution serum concentrations are linearly related to maintenance dosage and may be useful in evaluating therapeutic and toxic effects.
Digoxin is concentrated in tissues and therefore has a large apparent volume of distribution. Digoxin crosses both the blood-brain barrier and the placenta. At delivery, serum digoxin concentration in the newborn is similar to the serum level in the mother. Approximately 20 to 25% of plasma digoxin is bound to protein. Serum digoxin concentrations are not significantly altered by large changes in fat tissue weight, so that its distribution space correlates best with lean (ideal) body weight, not total body weight.
Metabolism:
Metabolism occurs partially in the stomach, but also may occur in the liver and, although only about 16% of a dose of digoxin is metabolized, several metabolites of digoxin and their metabolic pathways have been identified. The bis-digitoxoside and mono-digitoxoside metabolites are considered to be cardioactive. Other metabolites, such as digoxigenin, are considered to be less cardioactive than digoxin. In some patients (estimated to be approximately 10% of patients taking digoxin), other cardioinactive metabolites, such as dihydrodigoxin and dihydrodigoxigenin, may result from the metabolism of digoxin by intestinal bacteria. In these individuals, as much as 40% or more of the oral dose of digoxin may be converted to these inactive reduction products. The metabolism of digoxin is not dependent upon the cytochrome P-450 system.
Elimination:
Elimination of digoxin follows first-order kinetics (that is, the quantity of digoxin eliminated at any time is proportional to the total body content). Following IV administration to normal subjects, 50 to 70% of a digoxin dose is excreted unchanged in the urine. Renal excretion of digoxin is proportional to glomerular filtration rate and is largely independent of urine flow. In subjects with normal renal function, digoxin has a half-life of 1.5 to 2 days.
Special Populations and Conditions
Pediatrics: The tolerance of newborn infants to digitalis glycosides is variable, since their renal clearance of the medication is reduced. Premature and immature infants are especially sensitive. Dosage should be reduced and individualized according to the infant's degree of maturity, since renal clearance increases as the infant matures. Children older than l month of age generally require proportionally larger doses than adults on the basis of body weight or body surface area (see 4 DOSAGE AND
- ADMINISTRATION).
- Geriatrics: Elderly patients may be more likely to have age-related renal function impairment, which may significantly increase the elimination half-life of digoxin. Additionally, elderly patients may have a decreased volume of distribution of digitalis due to decreased muscle mass. These factors may contribute to digitalis toxicity in elderly patients.
- Sex: Digoxin is primarily removed from the body by renal elimination. Although the digoxin clearance in women is about 10-15% lower than in men, the effect of gender on the pharmacokinetics of digoxin is not expected to be clinically significant when initiating and monitoring digoxin therapy in patients.
- Genetic Polymorphism: The effect of genetic polymorphism on the pharmacokinetics of digoxin was not studied.
- Ethnic Origin: Race differences in digoxin pharmacokinetics have not been formally studied. Because digoxin is primarily eliminated as unchanged drug via the kidney and because there are no important differences in creatinine clearance among races, pharmacokinetic differences due to race are not expected.
- Hepatic Insufficiency: Plasma digoxin concentration profiles in patients with acute hepatitis generally fell within the range of profiles in a group of healthy subjects.
Renal Insufficiency: The clearance of digoxin can be primarily correlated with renal function as indicated by creatinine clearance. In children with renal disease, digoxin must be carefully titrated based on clinical response.
The half-life of digoxin in anuric patients is prolonged to 4 to 6 days. Digoxin is not effectively removed from the body by dialysis, exchange transfusion or during cardiopulmonary bypass because most of the drug is in the tissue rather than circulating in the blood.
11 STORAGE, STABILITY AND DISPOSAL
Store between 15 and 30°C. Protect from light. Protect from freezing.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Digoxin
Chemical Name: 3β-[(O-2, 6-dideoxy-β-D-ribo-hexopyranosyl-(1-4)-O-2,6-dideoxy-β-D-ribo-hexopyranosyl-(1-4)-2,6-dideoxy-β-D-ribo-hexopyranosyl)oxy]-12β,14-dihydroxy-5β-card-20(22)-enolide
Molecular Formula and Molecular Mass: C41H64O14 ; MW=780.95
Structural Formula:
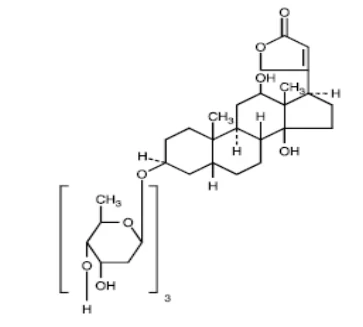
Physicochemical Properties: Digoxin exists as odorless white crystals that melt with decomposition above 230°C. The drug is practically insoluble in water and in ether; slightly soluble in diluted (50%) alcohol and in chloroform; and freely soluble in pyridine.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 6 Summary of Patient Demographics for Controlled Clinical Trials for Digoxin in Congestive Heart Failure
| Study # | Study Design | Dosage, Route of administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex |
Digitalis Investigation Group (DIG Trial) | Randomized, double-blind, placebo-controlled | Daily dose: 0.125 - 0.500 mg tablets (median dose 0.25 mg) Study duration: Range from 28 to 58 months (mean duration 37 months) | Total: 7788 patients At randomization, 67% were NYHA class I or II, 71% had heart failure of ischemic etiology, 44% had been receiving digoxin, and most were receiving concomitant ACE inhibitor (94%) and diuretic (82%). Main trial: (left ventricular ejection fractions of 0.45 or less): Digoxin- 3397 patients Placebo- 3403 patients Ancillary trial: (left ventricular ejection fractions greater than 0.45): Digoxin- 492 patients Placebo- 496 patients | Digoxin Mean age: 63.4 Range: 63.4 ± 11.0 Placebo Mean age: 63.5 Range: 63.5 ± 10.8 | Digoxin Males and Females (22.2%) Placebo Males and Females (22.5%) |
GHBA 436 (PROVED Trial) | Double-blind, placebo-controlled, parallel, multicenter study | Daily dose: 0.125, 0.25, 0.375, or 0.5 mg tablets with diuretic Study duration: Minimum of 12 weeks | Total: 88 patients Digoxin- 42 patients Placebo- 46 patients | Digoxin Mean age: 63.7 Range: 25.0-89.0 Placebo Mean age: 63.7 Range: 40.0-82.0 | Digoxin Males: 38 Females: 4 Placebo Males: 37 Females: 9 |
GHBA 437 (RADIANCE Trial) | Randomized, double-blind, placebo-controlled, parallel, multicenter study | Daily dose: 0.125, 0.25, 0.375, or 0.5 mg tablets with angiotensin converting enzyme inhibitor and diuretic Study duration: 12 weeks | Total: 178 patients with NYHA class II or III heart failure previously treated with digoxin, a diuretic, and an ACE inhibitor Digoxin- 85 patients Placebo- 93 patients | Digoxin Mean age: 61.4 Range: 34.0-84.0 Placebo Mean age: 59.2 Range: 24.0-82.0 | Digoxin Males: 60 Females: 25 Placebo Males: 76 Females: 17 |
The Digitalis Investigation Group (DIG) main trial was a multicenter, randomized, double-blind, placebo-controlled mortality study of 6801 patients with heart failure and left ventricular ejection fraction ≤0.45. At randomization, 67% were NYHA class I or II, 71% had heart failure of ischemic etiology, 44% had been receiving digoxin, and most were receiving concomitant ACE inhibitor (94%) and diuretic (82%). Patients were randomized to placebo or digoxin, the dose of which was adjusted for the patient's age, sex, lean body weight, and serum creatinine (see 4 DOSAGE AND ADMINISTRATION), and followed for up to 58 months (median 37 months). The median daily dose prescribed was 0.25 mg.
Two 12-week, double-blind, placebo-controlled studies enrolled 178 (RADIANCE trial) and 88 (PROVED trial) patients with NYHA class II or III heart failure previously treated with digoxin, a diuretic, and an ACE inhibitor (RADIANCE only) and randomized them to placebo or treatment with digoxin.
14.2 Study results
Table 7 - Results of Controlled Clinical Trials for Digoxin in Congestive Heart Failure
| Primary Endpoints | Associated Value and Statistical Significance for Drug and Placebo at Specific Dosages |
| DIG Trial | |
Primary outcome: mortality. Secondary outcomes were mortality from cardiovascular causes, death from worsening heart failure, hospitalization for worsening heart failure, and hospitalization for other causes, in particular suspected digoxin toxicity. | There were 1181 deaths (34.8%) in the digoxin group and 1194 deaths (35.1%) in the placebo group. There was a trend toward a decrease in the risk of death attributed to worsening heart failure (risk ratio, 0.88, 95% confidence interval, 0.77 to 1.01; P=0.06). There were 6% fewer hospitalizations overall in the digoxin group than in the placebo group, and fewer patients were hospitalized for worsening heart failure (26.8% vs 34.7%; risk ratio, 0.72; 95% confidence interval, 0.66 to 0.79; P<0.001). |
| GHBA 436 (PROVED Trial) | |
| Primary objectives were to evaluate the effects of the withdrawal of digoxin on: (1) exercise tolerance, and (2) the rate of withdrawal from the trial due to worsening of CHF in patients with NYHA Class II-III CHF who were in normal sinus rhythm and receiving concomitant therapy with diuretics. | Patients withdrawn from digoxin therapy showed worsened maximal exercise capacity (median change in exercise time -96 s) compared with that of patients who continued to receive digoxin (change in exercise time +4.5 s) (p=0.003). Patients withdrawn from digoxin therapy showed an increased incidence of treatment failures (p=0.039) (39%, digoxin withdrawal group vs 19%, digoxin maintenance group) and a decreased time to treatment failure (p=0.037). In addition, patients who continued to receive digoxin had a lower body weight (p=0.044) and heart rate (p=0.003) and a higher left ventricular ejection fraction (p=0.016). |
| GHBA-437 (RADIANCE Trial) | |
Primary objectives were to evaluate the effects of the withdrawal digoxin on exercise tolerance and on the rate of withdrawal from the trial due to worsening of CHF in patients with NYHA Class II-III CHF who were in normal sinus rhythm receiving concomitant therapy with diuretics and an ACE inhibitor. Endpoint was the last measurement obtained during the double-blind digoxin withdrawal period for each patient. | Worsening heart failure necessitating withdrawal from the study developed in 23 patients switched to placebo, but in only 4 patients who continued to receive digoxin (P<0.001). The relative risk of worsening heart failure in the placebo group as compared with the digoxin group was 5.9 (95 percent confidence interval, 2.1 to 17.2). All measures of functional capacity deteriorated in the patients receiving placebo as compared with those continuing to receive digoxin (P=0.033 for maximal exercise tolerance, P=0.01 for submaximal exercise endurance, and P=0.019 for New York Heart Association class). In addition, the patients switched from digoxin to placebo had lower quality of life scores (P=0.04), decreased ejection fractions (P=0.001), and increases in heart rate (P=0.001) and body weight (P<0.001). |
DIG Trial
Overall all cause mortality was 35% with no difference between groups (95% confidence limits for relative risk of 0.91 to 1.07). Digoxin was associated with a 25% reduction in the number of hospitalizations for heart failure, a 28% reduction in the risk of a patient having at least one hospitalization for heart failure, and a 6.5% reduction in total hospitalizations (for any cause).
Use of digoxin was associated with a trend to increase time to all cause death or hospitalization. The trend was evident in subgroups of patients with mild heart failure as well as more severe disease, as shown in Table 8. Although the effect on all cause death or hospitalization was not statistically significant, much of the apparent benefit derived from effects on mortality and hospitalization attributed to heart failure. In situations where there is no statistically significant benefit of treatment evident from a trial’s primary endpoint, results pertaining to secondary endpoint should be interpreted cautiously.
Table 8 Subgroup Analyses of Mortality and Hospitalization During the First Two Years Following Randomization in the DIG Trial with Digoxin.
Risk of All-Cause Mortality or All-Cause Hospitalization* | Risk of HF-Related Mortality or HF-Related Hospitalization* | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n | Placebo | Digoxin | Relative risk† | Placebo | Digoxin | Relative risk† | |||||||||
| All patients (EF ≤0.45) | 6801 | 604 | 593 | 0.94 (0.88-1.00) | 294 | 217 | 0.69 (0.63-0.76) | ||||||||
| NYHA I/II | 4571 | 549 | 541 | 0.96 (0.89-1.04) | 242 | 178 | 0.70 (0.62-0.80) | ||||||||
| EF 0.25-0.45 | 4543 | 568 | 571 | 0.99 (0.91-1.07) | 244 | 190 | 0.74 (0.66-0.84) | ||||||||
| CTR ≤0.55 | 4455 | 561 | 563 | 0.98 (0.91-1.06) | 239 | 180 | 0.71 (0.63-0.81) | ||||||||
Risk of All-Cause Mortality or All-Cause Hospitalization* | Risk of HF-Related Mortality or HF-Related Hospitalization* |
|---|
| n | Placebo | Digoxin | Relative risk† | Placebo | Digoxin | Relative risk† | |
|---|---|---|---|---|---|---|---|
| NYHA III/IV | 2224 | 719 | 696 | 0.88 (0.80-0.97) | 402 | 295 | 0.65 (0.57-0.75) |
| EF <0.25 | 2258 | 677 | 637 | 0.84 (0.76-0.93) | 394 | 270 | 0.61 (0.53-0.71) |
| CTR >0.55 | 2346 | 687 | 650 | 0.85 (0.77-0.94) | 398 | 287 | 0.65 (0.57-0.75) |
| EF >0.45‡ | 987 | 571 | 585 | 1.04 (0.88-1.23) | 179 | 136 | 0.72 (0.53-0.99) |
* Number of patients with an event during the first 2 years per 1000 randomized patients.
† Relative risk (95% confidence interval).
‡ DIG Ancillary Study.
PROVED and RADIANCE Trials
Both trials demonstrated better preservation of exercise capacity in patients randomized to digoxin. Continued treatment with digoxin reduced the risk of developing worsening heart failure, as evidenced by heart failure-related hospitalizations and emergency care and the need for concomitant heart failure therapy. The larger RADIANCE study also showed treatment-related benefits in NYHA class and patients' global assessment. In the smaller PROVED trial, these trended in favor of a treatment benefit.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
There have been no long-term studies performed in animals to evaluate carcinogenic potential, nor have studies been conducted to assess the mutagenic potential of digoxin or its potential to affect fertility.