


Product Monograph - Dom-Moclobemide Tablets 150mg
ACTIONS AND CLINICAL PHARMACOLOGY
Moclobemide is a short-acting, Reversible Inhibitor of Monoamine oxidase type A (RIMA). It is a benzamide derivative which inhibits the deamination of serotonin, noradrenaline and dopamine. This action leads to increased concentrations of these neurotransmitters, which may account for the antidepressant activity of moclobemide.
Monoamine oxidases are currently subclassified into two types, A and B, which differ in their substrate specificity. Moclobemide preferentially inhibits MAO-A; at a 300 mg dose, the inhibition of MAO-A is approximately 80%, while that of MAO-B is approximately 20 - 30%. The estimated MAO-A inhibition is short-lasting (maximum 24 hours) and reversible.
PHARMACOKINETICS
Comparative Bioavailability Data
A comparative bioavailability study of moclobemide tablets 150 mg and 300 mg tablets was performed. Pharmacokinetic and bioavailability data were measured in 42 volunteers in the fed and fasting state. The results can be summarized as follows:
Moclobemide (1 x 150 mg, fed state) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval 90% |
AUCT‡ (ng.h/mL) | 2607.9 3048.5 (59.2) | 2634.7 3050.4 (57.3) | 99 | 95-103 |
AUCI (ng.h/mL) | 2682.0 3168.5 (62.9) | 2703.8 3150.2 (59.5) | 99 | 95-103 |
Cmax (ng/mL) | 794.9 871.7 (43.0) | 824.5 905.9 (43.6) | 96 | |
Tmax§ (h) | 1.74 (41.3) | 1.61 (38.1) | ||
T1/2el§ (h) | 1.86 (35.4) | 1.76 (29.1) | ||
* Dom-MOCLOBEMIDE 150 mg tablet (Dominion Pharmacal)
† MANERIX® 150 mg tablet (Roche Canada Inc).
§ Expressed as either the arithmetic mean (CV%) only.
Moclobemide (1 x 150 mg, fasting state) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval 90% |
AUCT‡ (ng.h/mL) | 2958.5 3368.6 (56.4) | 3147.6 3613.6 (58.5) | 94 | 90 - 98 |
AUCI (ng.h/mL) | 3050.6 3538.4 (64.0) | 3243.2 3801.8 (66.6) | 94 | 91 - 98 |
Cmax (ng/mL) | 1027.5 1078.9 (33.6) | 10954.4 1172 (38.0) | 94 | |
Tmax§ (h) | 1.10 (38.0) | 0.99 (35.0) | ||
T1/2el§ (h) | 1.98 (44.7) | 2.03 (43.9) | ||
* Dom-MOCLOBEMIDE 150 mg tablet (Dominion Pharmacal)
† MANERIX® 150 mg tablet (Roche Canada Inc).
§ Expressed as either the arithmetic mean (CV%) only.
Moclobemide (1 x 300 mg, fasting state) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval 90% |
AUCT‡ (ng.h/mL) | 10084.4 10931.0 (39.4) | 9607.8 10463.3 (41.7) | 105 | 101 - 109 |
AUCI (ng.h/mL) | 10503.0 11549.2 (43.9) | 10000.8 11065.9 (46.8) | 105 | 101 - 109 |
Cmax (ng/mL) | 2941.2 3111.4 (31.5) | 2703.9 2797.4 (25.3) | 109 | |
Tmax§ (h) | 1.0 (34.7) | 1.3 (52.2) | ||
T1/2el§ (h) | 2.36 (33.4) | 2.35 (34.7) | ||
* Dom-MOCLOBEMIDE 300 mg tablet (Dominion Pharmacal)
† MANERIX® 300 mg tablet (Roche Canada Inc).
§ Expressed as either the arithmetic mean (CV%) only.
Moclobemide (1 x 300 mg, fed state) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval 90% |
AUCT‡ (ng.h/mL) | 7956.8 8592.7 | 7521.4 8163.8 (45.5) | 106 | 103 - 109 |
AUCI (ng.h/mL) | 8315.2 9218.6 (54.5) | 7834.0 8699.0 (54.4) | 106 | 103 - 109 |
Cmax (ng/mL) | 2078.5 2150.1 (26.2) | 1863.8 1933.8 (28.8) | 112 | |
Tmax§ (h) | 1.65 (45.8) | 1.60 (42.4) | ||
T1/2el§ (h) | 2.30 (38.8) | 2.23 (38.0) | ||
* Dom-MOCLOBEMIDE 300 mg tablet (Dominion Pharmacal)
† MANERIX® 300 mg tablet (Roche Canada Inc).
§ Expressed as either the arithmetic mean (CV%) only.
Volunteers
General: Following oral administration, moclobemide is 98% absorbed from the gastrointestinal tract. Due to hepatic first pass effect, absolute bioavailability is approximately 55% after single doses, but 90% after multiple doses. The apparent volume of distribution is approximately 1.2 L/kg, indicating extensive tissue distribution.
Moclobemide is extensively metabolized, largely via oxidative reactions on the morpholine moiety of the molecule. While 95% of the administered dose is excreted in the urine, less than 1% of this is in the unchanged form. Active metabolites recovered in vitro or in animal experiments are present only at very low concentrations in the systemic circulation in man. Moclobemide is 50% bound to plasma proteins, mainly to albumin. The presence of food reduces the rate, but not the extent of moclobemide absorption.
Single Dose: Following the administration of a 100 mg single oral dose of moclobemide to healthy subjects, peak plasma concentrations ranged from 488 ng/mL to 1,450 ng/mL (mean Cmax: 849 ng/mL) and were reached in 0.5 to 3.5 hours (mean Tmax: 49 min). The elimination half-life is 1.5 hours. Up to 200 mg, the pharmacokinetics of moclobemide are linear. At higher doses, non-linear pharmacokinetics are observed. In a dose range of 400 mg to 1,200 mg, maximum plasma concentrations increased and clearance decreased in a non dose-proportional manner. With increasing doses, the elimination half-life also becomes prolonged.
Multiple Doses: During the second week of a 100 mg t.i.d. dosing regimen in healthy subjects, the steady-state trough concentrations of moclobemide ranged between 114 ng/mL and 517 ng/mL. An increase in the dose to 150 mg t.i.d. resulted in a greater than proportional increase in moclobemide steady-state trough concentrations, namely to concentrations ranging between 346 ng/mL and 1,828 ng/mL.
Patients
Hepatic Impairment, Single Dose: In patients with liver cirrhosis, the administration of a single 100 mg dose of moclobemide resulted in approximately a three-fold increase in peak plasma concentrations (Cmax: 1,607 ng/mL), and elimination half-life (t1/2β: 4.0 hr), while clearance decreased about four-fold (CI 337 mL/min).
Renal Impairment, Single Dose: In patients with renal insufficiency, the administration of a single 100 mg dose of moclobemide did not appreciably alter the pharmacokinetics of the drug, except for an increase in absorption time.
Elderly Patients, Single and Multiple Dose: Following a 100 mg t.i.d. dosing regimen in elderly subjects (65 to 77 years old), Cmax and AUC values were somewhat higher than in young subjects (21 to 34 years old), namely 1,498 versus 950 ng/mL and 5,571 versus 3,102 ng●h/mL, respectively. Clearance in the elderly was reduced (19.7 versus 32.3 L/h).
Slow Metabolisers: Because moclobemide is partly metabolized by polymorphic isozymes (CYP2C19 and CYP2D6), blood levels of the drug can be affected in patients with genetically or drug-induced poor metabolism. Approximately 2% of the Caucasian population and 15% of the Asian population can be genetically phenotyped as slow metabolisers with respect to oxidative hepatic metabolism. It was found that the area under the curve (AUC) measurement in slow metaboliser subjects was approximately 1.5 times greater than in extensive metaboliser subjects for the same dose of moclobemide. This increase is within the normal range of variation (up to two-fold) typically seen in patients.
INDICATIONS AND CLINICAL USE
Adults
Dom-MOCLOBEMIDE is indicated for the symptomatic relief of depressive illness.
Pediatrics < 18 years of age:
The safety and efficacy of moclobemide has not been established in the pediatric population, therefore its use is not recommended.
CONTRAINDICATIONS
Dom-MOCLOBEMIDE (moclobemide) is contraindicated in the following circumstances:
- In patients with a known hypersensitivity to Dom-MOCLOBEMIDE or any component of the product. As with any other exogenous compound, the possibility of hypersensitivity reaction should be considered in susceptible patients.
- In patients in an acute confusional state.
- Concomitantly with tricyclic/tetracyclic antidepressants (see DRUG INTERACTIONS, Other Antidepressants).
- In combination with selective serotonin reuptake inhibitors (SSRIs), serotonin norepinephrine reuptake inhibitors (SNRIs) or conventional monoamine oxidase inhibitors (MAO-Is) (see DRUG INTERACTIONS, Other Antidepressants).
- In combination with selegiline (see DRUG INTERACTIONS).
- In combination with meperidine. Although there is limited experience with the concomitant use of moclobemide and narcotics, death has occurred in patients receiving a conventional MAO inhibitor and meperidine (pethidine) given concomitantly.
- Concomitantly with thioridazine (see PRECAUTIONS and DRUG INTERACTIONS).
- Concomitantly with dextromethorphan (contained in many proprietary cough medicines).
- In combination with Bupropion
- In combination with Triptans
- In combination with Tramadol
WARNINGS
Potential Association with the Occurrence of Behavioural and Emotional Changes, Including Self-Harm
It is unknown whether increased risk of suicidal ideation and behaviour is associated with the use of older antidepressants (e.g. moclobemide) in pediatric patients and/or adults. However, recent analyses of placebo-controlled clinical trial safety databases from SSRIs and other newer antidepressants suggest that use of these drugs may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo. Thus, rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages given any antidepressant drug. This includes monitoring for emotional and behavioural changes.
PRECAUTIONS
General
In patients with thyrotoxicosis or pheochromocytoma, conventional MAO-inhibitors may precipitate a hypertensive reaction. Because there are no data available on the use of moclobemide in such patients, caution is advised when prescribing Dom-MOCLOBEMIDE to these subjects.
Occupational Hazards
Patients should be cautioned against driving an automobile or performing hazardous tasks until they are certain of the effect that Dom-MOCLOBEMIDE has on them.
Use in Pregnancy
Safety of use in pregnancy has not been established. Therefore, Dom-MOCLOBEMIDE is not recommended in women who may be pregnant, unless, in the opinion of the physician, the expected benefits to the patient markedly outweigh the possible risk to the fetus.
Nursing Mothers
Clinical data suggest that small quantities of moclobemide are excreted in human milk. Therefore, Dom-MOCLOBEMIDE is not recommended in nursing mothers unless the anticipated benefits outweigh the potential harm to the infant.
Angle-Closure Glaucoma
As with other antidepressants, Dom-MOCLOBEMIDE can cause mydriasis, which may trigger an angle-closure attack in a patient with anatomically narrow ocular angles. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Hepatic Dysfunction
In patients with severe liver dysfunction, the daily dose of Dom-MOCLOBEMIDE should be substantially reduced to one-third or one-half of the standard dose (see ACTIONS AND CLINICAL PHARMACOLOGY-PHARMACOKINETICS).
Renal Dysfunction
Single dose pharmacokinetic data suggest that no dosage adjustment may be required in patients with impaired renal function (see ACTIONS AND CLINICAL PHARMACOLOGY - PHARMACOKINETICS). However, multiple dose studies with moclobemide have not been performed in patients with renal dysfunction, therefore, Dom-MOCLOBEMIDE should be used with caution in this patient population. In normal volunteers, the absolute bioavailability almost doubles following multiple dosing as compared to a single dose.
Thioridazine
A study to evaluate the potential of moclobemide to inhibit the cytochrome enzyme P4502D6 (P4502D6) concluded that moclobemide can affect the pharmakokinetics of drugs (such as thioradazine) that are mainly metabolized by P4502D6. Thioridazine administration results in a dose-dependent prolongation of the QTc interval, which may cause serious ventricular arrhythmias including torsades de pointes-type arrhythmias and sudden death. This risk is expected to increase with moclobemide -induced inhibition of thioridazine metabolism (see CONTRAINDICATIONS and DRUG INTERACTIONS).
DRUG INTERACTIONS
Selegiline
Studies revealed that the combination of moclobemide and selegiline had a supra-additive effect to the tyramine sensitivity. The tyramine sensitive factor was increased with an individual variability. It was expected that the effect of oral tyramine might potentiate this effect to an even greater extent. It was therefore concluded that food containing tyramine should be omitted. Under daily conditions an absolute omission of food with tyramine is almost impossible. Based on the individual variability of the increase in sensitivity it is also not possible to recommend a specific amount which would be still well tolerated. Therefore the combination of moclobemide and selegiline is contraindicated.
Linezolid
Linezolid is a reversible, non-selective inhibitor of MAO and its use is contraindicated in combination with Dom-MOCLOBEMIDE.
Cimetidine
Cimetidine doubles the AUC (area under the plasma concentration-time curve) of moclobemide and is expected to approximately double moclobemide steady-state concentrations.
In patients receiving moclobemide concomitantly with cimetidine, a 50% reduction in the dosage of moclobemide may be necessary.
Triptans
Triptans are potent serotonin receptor agonists indicated for the treatment of migraine. In general, triptans are metabolized by monoamine oxidases (MAOs) and various cytochrome P450 enzymes. Concomitant use of Dom-MOCLOBEMIDE with a triptan can lead to potentially harmful exposure to the triptan or its active metabolite. Due to these characteristics, the concomitant use of triptans with Dom-MOCLOBEMIDE is contraindicated (See CONTRAINDICATIONS).
Trimipramine and Maprotiline
The concomitant use of Dom-MOCLOBEMIDE with Trimipramine and Maprotiline can result in an increase of their plasma concentrations. As Trimipramine and Maprotiline are non-selective monoamine reuptake inhibitors, their plasma concentration elevation may increase monoamine concentration to a level that can lead to severe adverse events (e.g. serotonin syndrome). Therefore, combination of Trimipramine/Maprotiline and Dom-MOCLOBEMIDE is contraindicated.
Tyramine
During studies conducted at the maximum recommended moclobemide dose of 600 mg/day, the mean dose of tyramine required to produce a 30 mm Hg increase in systolic blood pressure was 148 + 50 mg (76 – 200 mg) when moclobemide was administered immediately after tyramine. The threshold dose of tyramine was reduced to 84 + 23 mg (54 – 112 mg) when the sequence of administration was reversed so that moclobemide was administered one hour before tyramine. These findings indicate that the potentiation of tyramine may be minimized by administering moclobemide after, instead of prior to, a tyramine-enriched meal. There is limited experience in patients who took moclobemide before meals. Most clinical trial protocols specified that the drug be taken immediately after meals. Therefore, patients should be instructed to take Dom-MOCLOBEMIDE immediately after meals.
Treatment with moclobemide does not necessitate special dietary restrictions. In clinical studies it was demonstrated that up to 100 mg tyramine can be safely ingested during treatment with moclobemide 600 mg/day when moclobemide was given after meals. This amount of tyramine, 100 mg, corresponds to 1,000 g to 2,000 g mild or 200 g strong cheese, or to 70 g Marmite yeast extract.
As a safety measure, patients should be urged to report immediately the abrupt occurrence of any of the following symptoms; occipital headache, palpitations, neck stiffness, tachycardia or bradycardia or other atypical or unusual symptoms not previously experienced.
Other Antidepressants
Concomitant Use: Clinical interaction studies between moclobemide and a tricyclic antidepressant (clomipramine) resulted in severe adverse reactions (see CONTRAINDICATIONS). Data involving other tricyclic/tetracyclic antidepressants are limited. Therefore, the concomitant use of Dom-MOCLOBEMIDE and tricyclic/tetracyclic antidepressants is contraindicated.
Clinical data are not available on the concomitant use of moclobemide and selective serotonin reuptake inhibitors (SSRI), serotonin-norepinephrine reuptake inhibitors (SNRIs) or conventional monoamine oxidase inhibitors (MAO-Is). Therefore, until clinical data become available, Dom-MOCLOBEMIDE should not be administered in combination with these agents.
Sequential Use: Treatment with a tricyclic antidepressant may be initiated following the discontinuation of Dom-MOCLOBEMIDE with a short washout period of no less than two days.
When switching patients from serotonergic antidepressants to a conventional MAO-inhibitor, it is standard practice to allow for a washout period equivalent to at least 4-5 half-lives of the previously administered drug or any active metabolites. This recommendation also applies to Dom-MOCLOBEMIDE.
Fluoxetine
An exception is fluoxetine; at least five weeks should elapse between its discontinuation and initiation of treatment with Dom-MOCLOBEMIDE.
Drugs metabolised by CYP2C19
Care should be taken with concomitant use of drugs that are metabolised by CYP2C19 as moclobemide is an inhibitor of this enzyme. The plasma concentration of these drugs (e.g. proton pump inhibitors (PPIs), some antiepileptic or other CYP2C19 substrates) may be increased when concomitantly used with moclobemide. In CYP2C19 extensive metabolisers, the use of the PPI omeprazole resulted in a twofold AUC increase of moclobemide. Similarly, moclobemide inhibits the metabolism of omeprazole in CYP2C19 extensive metabolisers resulting in a doubling of the omeprazole exposure.
Buspirone
To date, there is no experience regarding the co-administration of moclobemide and buspirone. Therefore, patients should be carefully monitored should concomitant administration be implemented.
Antipsychotics
In depressed patients with schizophrenic or schizoaffective disorder, psychotic symptoms may be exacerbated during treatment with Dom-MOCLOBEMIDE. There is little experience regarding the concomitant use of moclobemide and antipsychotic drugs. Therefore, patients should be carefully monitored should concomitant treatment be undertaken.
Thioridazine
A study to evaluate the potential of moclobemide to inhibit the cytochrome enzyme P4502D6 (P4502D6) concluded that moclobemide can affect the pharmakokinetics of drugs (such as thioradazine) that are mainly metabolized by P4502D6. Thioridazine administration results in a dose-dependent prolongation of the QTc interval, which may cause serious ventricular arrhythmias including torsades de pointes-type arrhythmias and sudden death. This risk is expected to increase with moclobemide-induced inhibition of thioridazine metabolism (see CONTRAINDICATIONS).
Alcohol
Excessive alcohol consumption should be avoided. Alcohol interaction studies were performed at blood alcohol concentrations of 0.05%. However, no studies were conducted at blood alcohol concentrations recognized as legally intoxicating.
Anesthetic Agents
While specific data on the use of moclobemide in patients undergoing anesthesia are not available, based on its reversible action and short elimination half-life (see ACTIONS AND CLINICAL PHARMACOLOGY), Dom-MOCLOBEMIDE should be discontinued no less than two days before the administration of anesthetic agents, especially spinal or local anesthetic agents that contain epinephrine.
In animals, moclobemide has been shown to potentiate the effects of opiates. The combination of moclobemide and meperidine (pethidine) is not recommended (see CONTRAINDICATIONS). Other opioid analgesics should be used with extreme caution, if at all, and a dosage adjustment may be necessary for these drugs.
Sympathomimetics
Following multiple oral doses of moclobemide (total dose: 600 mg/day), a phenylephrine -induced increase in systolic blood pressure was potentiated (1.6 times) after intravenous administration. Patients should be advised to avoid the concomitant use of sympathomimetic amines (e.g., amphetamine and ephedrine like compounds contained in many proprietary cold, hay fever or weight-reducing preparations), until further studies have been conducted.
Dextromethorphan
Dom-MOCLOBEMIDE should not be co-administered with dextromethorphan as isolated cases of severe central nervous system adverse reactions have been reported after co-administration (See CONTRAINDICATIONS).
Antihypertensive Agents
Clinical trials with moclobemide have shown inconsistent effects on the blood pressure of hypertensive patients. Therefore, careful monitoring is recommended during initial treatment.
ADVERSE REACTIONS
The following table lists the adverse events reported during clinical trials in which 1,922 patients were treated with 50-600 mg/day moclobemide for depressive illness. Limited experience in 60 patients treated with 601-750 mg/day of moclobemide suggests that the incidence of adverse reactions may increase at higher doses.
| Clinical Adverse Events > 1% | |||
|---|---|---|---|
| Organ System | Adverse Event | % | |
| Moclobemide (n=1922) | Placebo (n=271) | ||
| Central Nervous System | headache, pressure in head | 8.0 | 11.1 |
| insomnia, sleep disturbances | 7.3 | 4.8 | |
| dizziness | 5.1 | 8.1 | |
| tremour | 5.0 | 3.0 | |
| increased agitation | 4.5 | 2.6 | |
| restlessness, nervousness | 4.1 | 2.6 | |
| sleepiness, somnolence | 3.7 | 5.5 | |
| tiredness, sedation | 3.0 | 4.1 | |
| increased anxiety, acute anxiety state | 2.8 | 2.2 | |
| weakness or faintness | 1.2 | 1.8 | |
| Gastrointestinal | nausea constipation gastrointestinal pain epigastric discomfort sickness diarrhea abdominal fullness, abdominal pain vomiting | 5.2 3.9 2.3 1.9 1.8 1.6 1.6 | 4.8 3.3 2.6 1.1 1.1 1.5 0.4 |
| Cardiovascular | tachycardia, palpitations | 3.8 | 3.3 |
| hypotension | 3.0 | 0.4 | |
| orthostatic, reactive hypotension | 2.3 | 3.3 | |
| Clinical Adverse Events > 1% | |||
|---|---|---|---|
| Anticholinergic | dry mouth | 9.2 | 10.7 |
| Miscellaneous | sweating | 2.4 | 2.2 |
| blurred vision | 1.8 | 1.1 | |
| increase/loss of appetite | 1.3 | 1.8 | |
Other clinical adverse events with an incidence of < 1% in clinical studies, or reported in post- marketing surveillance, are as follows:
Psychiatric: Difficulties falling asleep, nightmares/dreams, hallucinations, memory disturbances, confusion, disorientation, delusions, increased depression, excitation/irritability, hypomanic symptoms, aggressive behaviour, apathy, tension.
Cases of suicidal ideation and suicidal behaviours have been reported during antidepressant therapy or early after treatment discontinuation (see WARNINGS).
Central and Peripheral Nervous System: Migraine, extrapyramidal effects, tinnitus, paresthesia, dysarthria.
Gastrointestinal: Heartburn, gastritis, meteorism, indigestion.
Cardiovascular: Hypertension, bradycardia, extrasystoles, angina/chest pain, phlebitic symptoms, flushing.
Dermatological/Mucocutaneous: Exanthema/rash, allergic skin reaction, itching, gingivitis, stomatitis, dry skin, conjunctivitis, pruritus, urticaria.
Genito-Urinary: Disturbances of micturition (dysuria, polyuria, tenesmus) metrorrhagia, prolonged menstruation.
Miscellaneous: General malaise, skeletal/muscular pain, altered taste sensations, hot flushes/cold sensation, photopsia, dyspnea, visual disturbances.
Laboratory Abnormalities
Laboratory examinations were performed in a total of 1,401 patients during clinical trials with moclobemide. Reductions were observed in leucocyte, SGOT and SGPT values, however, these reductions were attributed to raised baseline values returning to normal, and were not considered clinically relevant. No other laboratory abnormalities were noted during clinical trials.
In post-market surveillance, there appeared to be a low incidence of raised liver enzymes, without associated clinical sequelae.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Symptoms
Signs and symptoms of overdosage with moclobemide include nausea, vomiting, drowsiness, disorientation, slurred speech, amnesia, reduced reflexes, agitation, hypertension and convulsions. One patient remained stuporous for 36 hours following an overdose with 1,550 mg moclobemide. All abnormal laboratory values and vital signs returned to within normal range one to five days after overdosage. No organ toxicity was reported.
Treatment
The treatment of overdosage should consist of general supportive measures. Gastric lavage or induction of emesis, activated charcoal and fluid control may be of benefit.
As with other antidepressants, mixed overdoses of moclobemide with other drugs (e.g. agents active on the CNS), could be life-threatening. Serotonergic syndrome and death have been reported after combined overdose of moclobemide and other antidepressants. Therefore, such patients should be closely monitored so that appropriate care and treatment may be given.
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
DOSAGE AND ADMINISTRATION
Note: Dom-MOCLOBEMIDE (moclobemide) should always be taken after meals (see DRUG INTERACTIONS).
Usual Adult Dosage
The administration of Dom-MOCLOBEMIDE should be initiated at 300 mg daily dose (in two divided doses), and increased gradually to a maximum of 600 mg/day if needed, noting carefully the clinical response and any evidence of intolerance. Individual patient response may allow for a reduction of the daily dose. As with other antidepressants, it should be kept in mind that there may be a lag time in therapeutic response. There is no evidence that increasing the dosage rapidly shortens this latent period and may, in fact, increase the incidence of side-effects. Furthermore, because bioavailability of moclobemide has been shown to increase over the first week of dosing (see PHARMACOKINETICS), the initial daily dose of 300 mg should not be increased until after this first week of therapy.
Liver Dysfunction
When hepatic metabolism is severely impaired by hepatic disease or inhibited by a drug that affects microsomal mixed function oxidase activity (e.g. cimetidine), the daily dose of Dom-MOCLOBEMIDE should be reduced to one-third or one-half of the standard dose.
Renal Dysfunction
Single dose pharmacokinetic data suggest that no dosage adjustment may be required in patients with impaired renal function. However, multiple dose studies with moclobemide have not been performed in patients with renal dysfunction, therefore, Dom-MOCLOBEMIDE should be used with caution in this patient population. In normal volunteers, the absolute bioavailability almost doubles following multiple dosing as compared to a single dose.
Elderly
No dosage adjustments are necessary in elderly patients.
Cimetidine
Cimetidine doubles the AUC (area under the plasma concentration-time curve) of moclobemide and is expected to approximately double moclobemide steady-state concentrations (see DRUG INTERACTIONS).
In patients receiving Dom-MOCLOBEMIDE concomitantly with cimetidine, a 50% reduction in the dosage of Dom-MOCLOBEMIDE may be necessary.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Moclobemide
Chemical Name: p-chloro-N-(2-morpholinoethyl)benzamide
Structural Formula:
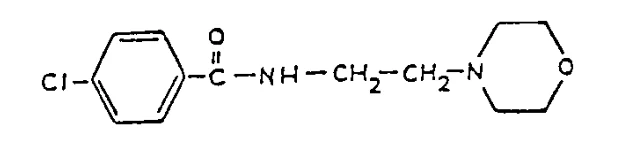
Molecular Formula: C13H17ClN2O2
Molecular Weight: 268.74 g/mol
Description: Moclobemide is an almost white crystalline powder with a faint odour.
Solubility: It is slightly soluble in water.
pH and pK values: pka is approximately 6.2.
Partition Coefficient: The partition coefficient in pH 7.4 octanol/buffer solution at 22°C is approximately 40.
Melting Point: The melting point is approximately 138°C.
Stability and Storage Recommendations
Store between 15°C and 30°C.
AVAILABILITY OF DOSAGE FORMS
Tablets
150 mg: Each yellow, coated, oval, biconvex tablet with a white core, scored on one side and debossed “P” logo and “150” on the other contains 150 mg of moclobemide, and the following non medicinal ingredients: Corn Starch, Hydroxypropyl Methylcellulose, Lactose, Magnesium Stearate, Povidone, Sodium Starch Glycolate, Synthetic Yellow Iron Oxide, Titanium Dioxide, Triacetin. Available in HDPE bottles of 100 tablets.
300 mg: Each white coated, oval, biconvex tablet with a white core, scored on one side and debossed “P” logo and “300” on the other contains 300 mg of moclobemide, and the following non medicinal ingredients: Corn Starch, Hydroxypropyl Cellulose, Hydroxypropyl Methylcellulose, Lactose, Magnesium Stearate, Polyethylene Glycol, Povidone, Sodium Starch Glycolate, Titanium Dioxide. Available in HDPE bottles of 100 tablets.
PHARMACOLOGY
ANIMAL
Pharmacodynamics
In vitro, Ex vivo: Liver and brain tissue homogenates were incubated with moclobemide and tested with the MAO substrates serotonin (5-HT) and phenylethylamine (PEA) in order to characterize moclobemide as an inhibitor of MAO-A or MAO-B, respectively (Table 1).
Table 1: In vitro and ex vivo MAO Inhibition in Liver and Brain Tissue Homogenates
| Man | Rat | |||||||||||
| Homogenate | 5-HT | PEA | 5-HT | PEA | ||||||||
Liver Brain (In vitro, IC50, mcmol/L) | 12 11 | >1,000 >1,000 | 4 8 | 220 70 | ||||||||
Brain (Ex vivo, ED50, mcmol/kg p.o.) | 10 | 98 | ||||||||||
Liver Brain (Ex vivo, ED50, mcmol/kg i.p.) | 0.5-0.9 5.0-7.5 | 9-12 110- ≥200 | ||||||||||
In in vitro rat brain models, moclobemide had no effect on the synaptosomal uptake of serotonin, dopamine and norepinephrine.
In vivo: After the administration of a 50 mg/kg oral dose of moclobemide to rats, slight elevations in cerebral norepinephrine, dopamine and serotonin concentrations, lasting 16 hours, were observed. Values had returned to control levels by 24 hours after administration. Concentrations of the monoamine metabolites were reduced maximally by two and seven hours after administration but had returned to control levels by 24 hours (Figure 1).
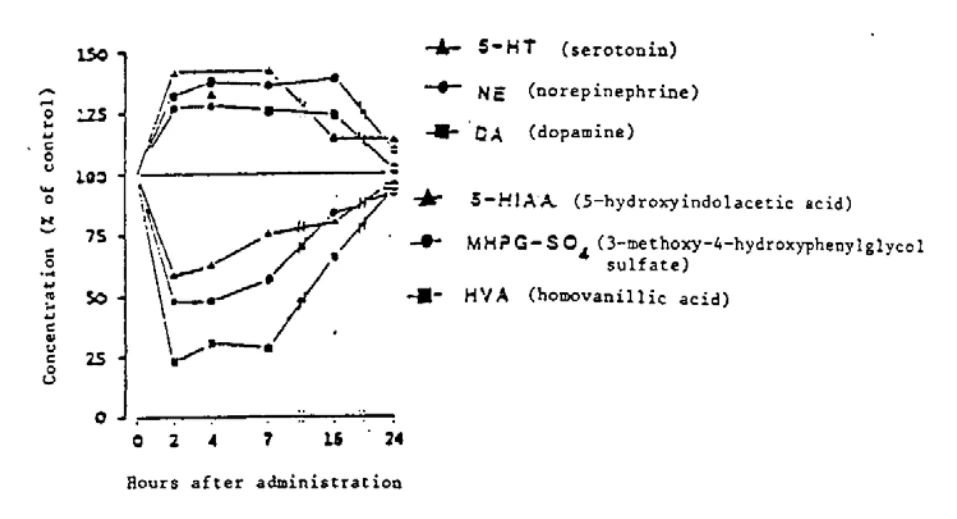
Figure 1: Changes in activities of brain monoamines and their metabolites with time after oral administration of 50 mg/kg moclobemide in rat. Points represent percentages of controls (saline) and are means of five single values.
Moclobemide was also active in animal models considered predictive for antidepressant activity:
(1) It reversed monoamine releaser-induced sedation and ptosis in mice with a duration of action of less than 16 hours (ED50 = 30 mg/kg i.p.)
(2) In cats, moclobemide dose-dependently suppressed REM sleep (ED50 = 18.6 mg/kg i.p.) without disturbing the sleep-wakefulness cycle (10-30 mg/kg i.p.), and
(3) In the behavioural despair test in mice, moclobemide decreased the immobility score (ED120= 43 mg/kg). In addition, moclobemide potentiated the 5-hydroxytryptophan-induced behavioural triad (head twitching, tremour and abduction) in mice (ED50 = 1.0 mg/kg i.p.).
Drug Interactions
A 100 mg/kg p.o. single dose of moclobemide potentiated the effects of single dose meperidine, morphine and dextropropoxyphene in groups of 10 mice. Following repeated dosing with analgesics, no significant potentiation was observed. In groups of 6 rats, there was no acute interaction between moclobemide and hydroflumethiazide, but sodium excretion was increased following the repeated administration of 100 mg/kg p.o. moclobemide. Moclobemide (100 mg/kg p.o.) potentiated the anti-inflammatory action of ibuprofen in groups of 5 rats. A possible antagonism was found with ouabain (mice) and prazosin (rats). An antagonism with furosemide was observed (rats).
Pharmacokinetics
The pharmacokinetic profile of moclobemide was determined in rats and dogs. Following oral administration, moclobemide was rapidly absorbed, reaching peak concentrations within 10 minutes in rats and 0.5-1 hour in dogs. A hepatic first-pass effect reduced absolute bioavailability to 10-20% and 67% in rats and dogs, respectively. In dogs, maximum plasma concentrations increased proportionately with increasing doses (5-100 mg/kg) and declined with a terminal half-life of approximately 1-2 hours. Distribution and metabolism were extensive in both species; only 1-3% of the dose was recovered in urine as intact drug. The major route of elimination after metabolism was via the kidneys. Approximately 66-90% of the administered dose was recovered in the urine, primarily within the first 24 hours. The main urinary metabolites in rat were the N-oxide metabolite (13%), p-chlorohippuric acid (11%) and the secondary amine (8%). In dogs, p-chlorohippuric acid, the secondary amine and the N-oxide accounted for 36%, 22% and 7% of the dose, respectively. The protein binding of moclobemide in plasma from dogs ranged from 27% to 44%.
TOXICOLOGY
Acute Toxicity
LD50 (moclobemide)
| Species | Strain | Route | LD50 (mg/kg) | Observation Period | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Mice | Fü SPF | oral i.p. | 1,141 572 | 24h + 10 days | |||||||
| Charles River CFI | oral i.p. s.c. | 730-800 450-530 940->1,000 | 14 days | ||||||||
| Rats | Fü SPF | oral i.p. | 4,138-4,444 678 | 24h + 10 days 10 days | |||||||
| Charles River CD | oral i.p. | 1,300 530 | 14 days | ||||||||
| Rabbits | New Zealand White | oral | 800 | 14 days | |||||||
Most frequently observed signs and symptoms were decreased motor activity, muscle relaxation, respiratory depression, loss of righting reflex, ataxia, sedation, hypnosis, salivation, tonic-clonic convulsions, tremours, and corneal opacity.
Subacute Toxicity
In an oral pyramiding dose toxicity study, moclobemide was dispersed in starch, encapsulated and administered to four dogs (two/sex) at doses of 0 (starch capsule) 3, 10, 30, 100, 300 and 1,000 mg/kg.
The dogs were essentially asymptomatic following doses of 3, 10, 30 and 100 mg/kg. After the 300 mg/kg dose, three dogs exhibited emesis. There was a slight 34% reduction in food consumption in female dogs and the platelet count of all dogs was slightly elevated (24%). Following the administration of the 1,000 mg/kg dose, all four dogs exhibited emesis, excessive salivation, decreased motor activity and half-shut eyes. Three dogs had tremours and two of four dogs were dazed, ataxic and displayed jerking movements of the head. One dog was disoriented and exhibited lacrimation. Food consumption was markedly reduced (92%) in male dogs but only slightly decreased (42%) in female dogs; food consumption returned to pretreatment levels one day after dosing. The platelet count was slightly elevated one (20%) and seven (22%) days after the final dose.
Long-term Toxicity
Long-term toxicology studies have been conducted in rats and dogs:
| Species | Route of Admin. | Maximum Dose (mg/kg) | Treatment Duration |
|---|---|---|---|
| Rats | I.V. p.o. | 50 300 | 4 weeks 14 weeks |
| Species | Route of Admin. | Maximum Dose (mg/kg) | Treatment Duration |
|---|---|---|---|
p.o. p.o | 270 250 | 26 weeks 18 months | |
| Dogs | I.V. p.o p.o. p.o | 50 200 100 125 | 4 weeks 12 weeks 26 weeks 12 months |
Rats
- 1.
Four-Week I.V.
Moclobemide (25 mg/mL) was administered intravenously for four weeks to rats (12/sex/group) at doses of 0 (saline control), 10, 20 or 50 mg/kg/day.
The 50 mg/kg/day dose produced tonic-clonic convulsions immediately after injection (males only), followed by slight sedation lasting approximately 30 minutes (males and females) and one male death. A moderate dose-dependent reduction in body weight gain (15% at the highest dose) was seen in male rats.
- 2.
Fourteen-Week Oral
Moclobemide was administered as a dietary admixture for fourteen weeks to rats (6/sex/group) at doses of 0 (controls), 30, 100 or 300 mg/kg/day.
Food consumption and body weight gain were reduced in a dose-dependent manner; at the highest dose, weight gains of 15-60 g were noted compared to increases of 101-229 g in the control group. Immediate moderate to large weight gains occurred at the end of the 14-week treatment period.
The slight increases in GOT, GPT, alkaline phosphatase and blood sugar observed in all treated groups relative to controls were considered not to be drug-related. Administration of 100 or 300 mg/kg/day dose of moclobemide was associated with a slight transient depression of total serum protein in male rats. A small delay in bromsulphalein elimination was observed in week 12 in two female rats receiving the 100 mg/kg/day dose.
- 3.
Twenty-Six Week Oral
Moclobemide was administered as a dietary admixture for 26 weeks to rats (20/sex/group) at doses of 0 (controls), 30, 90 or 270 mg/kg/day.
Slight piloerection was periodically observed in high-dose animals from day 30 onward. Bodyweight gains were reduced in a dose-related manner; at the highest dose, male and female bodyweights were 61% and 71% of controls, respectively.
Increases in hemoglobin and mean cell hemoglobin concentration (MCHC) were evident in treated animals of both sexes after 6 weeks of treatment. In most cases these increases, which ranged from 2-16% above control values, were statistically significant. Similar increases (2-11%) were seen in high dose animals of both sexes after 13 and 24 weeks of treatment. All treated females showed increases in GOT after 2 and 6 weeks that were statistically significantly different from controls in most cases. A similar pattern was evident in middle and high dose females after 13 weeks. These increases ranged from 14-41% above control values. After 24 weeks, GOT values in treated females were within normal range.
Macroscopic examination at necropsy revealed a slightly increased incidence of gastrointestinal reddening in treated animals, particularly in males. Small spleens were occasionally noted, predominantly in high-dose females. The majority of absolute organ weights showed statistically significant reductions in treated animals associated with the reduced bodyweight gain. Treatment related increases in relative organ weights were observed in lungs (7-24%), kidneys (4-12%), thyroids (14-43%; males only) and gonads (0-56%).
- 4.
18-Month Oral
Moclobemide was administered as a dietary admixture for 18 months to rats (20/sex/group) at doses of 0 (controls), 10, 50 or 250 mg/kg/day.
Body weight development was dose dependently retarded in both sexes. Blood chemistry examinations showed a slight tendency to minimally increased alkaline phosphatase and GPT values in rats treated with 250 mg/kg/day moclobemide.
In male rats receiving 250 mg/kg/day moclobemide, relative heart and liver weights (adjusted to a body weight of 100 g) were reduced by 8.3% and 12.8%, respectively, compared to controls. In females of the same dosage group, adjusted relative ovary and brain weights were decreased 16.8% and 32.1%, respectively, compared to controls.
Dogs
- 1.
Four-Week I.V.
Moclobemide (25 mg/mL) was administered intravenously for four weeks to dogs (3/sex/group) at doses of 0 (saline control), 12.5, 25 or 50 mg/kg/day.
During the first days of the experiment, animals treated with 25 mg/kg/day moclobemide became slightly sedated shortly after drug administration. Moderate to marked sedation, lasting one to two hours after injection, was noted in the 50 mg/kg/day dosage group throughout the study. CNS-related head-shaking was also observed at this dose.
- 2.
Twelve-Week Oral
Moclobemide capsules were administered for twelve weeks to dogs (4 males and 2 females/group) at doses of 0 (empty capsule), 20, 60 or 200 mg/kg/day.
Dogs administered 60 mg/kg/day moclobemide had a 5% weight loss during the first weeks of the study. Ten to fifteen percent reductions in RBC counts, hematocrit and hemoglobin occurred in some of the dogs in this group. Biochemically, only plasma cholesterol values were affected, decreasing slightly in some of the dogs.
At the 200 mg/kg/day dosage, dogs showed immediate, severe weight losses amounting to approximately 10% per week for the first two weeks. After six weeks of moclobemide administration, body weights of five of the six animals in this group were decreased to 60 to 70% of their starting weights. Moclobemide administration was stopped, and three dogs were sacrificed due to cachexia. In the three remaining dogs, immediate and rapid weight gains were observed following treatment discontinuation. In one week, the body weights of these animals were increased to 25% above their weights at six weeks.
Reductions of approximately 25% in RBC counts, hematocrit and hemoglobin concentrations were observed after six weeks of the 200 mg/kg/day moclobemide dose. Slight increases in GOT and GPT, a reduction in plasma cholesterol concentrations; a slowing of the heart rate and lengthening of the QT interval; very low heart weights in two dogs, and slight atrophy of the myocardial fibers were also observed at this dose. After three weeks without moclobemide, these changes showed marked improvement.
- 3.
Twenty-Six Week Oral
Moclobemide capsules were administered for twenty-six weeks to dogs (4/sex/group) at doses of 0 (empty capsule), 10, 30 or 100 mg/kg/day.
Dogs administered 100 mg/kg/day moclobemide began to lose weight from week six, and body weights remained virtually constant until study termination. However, moclobemide had no effect on the consumption of food and water.
Moderate dose-related decreases in hemoglobin concentration, RBC count, and PCV were noted at week six. These decreases were statistically significant in dogs administered 100 mg/kg/day moclobemide. This effect was less marked during the remainder of the study, but decreases were also statistically significant in females in the high-dose group at weeks 13, 18 and 24. A dose-related reduction in plasma cholesterol concentrations was observed in female dogs; decreases in this parameter were statistically significant at the high dose throughout the study, at 30 mg/kg/day after weeks 13 and 18, and at the low dose after 13 weeks.
At the high-dose, absolute uterus weights decreased, and absolute liver weights increased in males. Relative liver weights were increased at 30 and 100 mg/kg/day; relative thyroid and adrenal weights were increased at the high dose, and relative lung weights were increased at all three moclobemide doses. Decreased relative uterus weights were seen in the high-dose group.
Microscopic examination of tissue sections revealed the following:
- a) Anestrus, characterized by an absence of normal reproductive-cycle changes in the uteri, ovaries and mammary glands of all female dogs administered 100 mg/kg/day moclobemide.
- b) Minimal hepatic fibrosis, indicative of low-grade liver injury, occurring in three males and three females in the high-dose group, and in one of four females given 30 mg/kg/day moclobemide.
- c) A minimal increase in the incidence and severity of thymic regression in male dogs in the high-dose group.
- 4.
Twelve-Month Oral
Moclobemide capsules were administered for 12 months to dogs (5/sex/group) at doses of 0
(empty capsule), 5, 20 or 100/125 mg/kg/day. As a result of good tolerance, the dose in group four was increased from 100 mg/kg/day to 125 mg/kg/day after six months. One dog of each sex from each dosage group continued to be examined for an additional six weeks after drug administration ended (recovery period).
At the highest dose, a moderate 10-20% reduction in RBC counts, hemoglobin and PCV was observed in females after 9 and 12 months of moclobemide administration. These values remained within the lower limit of the physiological range during the study and returned to normal during the recovery period. Mean triglyceride values were minimally increased in males and decreased in females. Cholesterol levels were minimally to moderately decreased (20-40%) in both sexes at most examinations. Alkaline phosphatase showed a tendency to higher values in males. Triglyceride, cholesterol and alkaline phosphatase values returned to normal during the recovery period.
At the highest dose, liver and adrenal weights were increased. Histological examination of the liver revealed a slight increase in hemosiderin deposits relative to other groups, especially in females. Minimal fibrosis was observed in five dogs and an additional case occurred in one animal administered 5 mg/kg/day.
Mutagenicity
Ames Test: In the Ames test, with and without metabolic activation, moclobemide concentrations of 0.02-20 mg/plate were not mutagenic for Salmonella typhimurium strains TA 1535, TA 1537, TA 1538, TA 98 and TA 100.
Micronucleus Test (Mouse Bone Marrow): Moclobemide did not induce chromosomal breakage or mitotic non-disjunctions in mouse bone marrow after a single dose of 800 mg/kg by gavage.
Hamster V-79/HGPRT Assay: Moclobemide concentrations of 1.0 - 4.0 mg/mL (without metabolic activation) or 2.0 - 3.4 mg/mL (with metabolic activation) did not induce forward mutations at the HGPRT locus in Chinese Hamster V79 cells.
Induction of Chromosomal Abberations (Human Lymphocytes): Moclobemide concentrations of 200-600 mg/mL (without metabolic activation) or 600-4,000 mg/mL (with metabolic activation) did not induce chromosomal damage in human peripheral lymphocytes.
Unscheduled DNA Synthesis (Rat Hepatocytes): Moclobemide did not induce DNA damage resulting in unscheduled DNA synthesis, in freshly isolated rat hepatocytes at 0.1 - 2.0 mg/mL, or in cultured human fibroblasts at 0.4 - 1.2 mg/mL.
Carcinogenicity
- 1.
Eighty Week Oral - Mice
An 80 week oral (dietary admixture) carcinogenicity study with moclobemide was conducted in mice (50/sex/group) at doses of 0 (control-1), 0 (control-2), 10, 50 or 250 mg/kg/day.
Body weight development was similar for both male and female mice at moclobemide doses of 10 and 50 mg/kg/day. At 250 mg/kg/day, body weights were reduced by 10% relative to the other groups. Relative kidney weights in the highest dose group were increased approximately 15% compared to control animals.
Neoplastic lesions were observed in the lungs, hemolymphoreticular system, liver, ovaries and pituitary gland in both the control and treatment groups. The incidences of lesions which occurred more frequently in treated animals than in controls are summarized below:
Lungs Bronchioalveolar Tumours (Females) (Males) | Hemolymphoreticular System Malignant Lymphomas (Males) | Liver Adenomas (Males) | ||||||
|---|---|---|---|---|---|---|---|---|
| Control-1 | 33% | 52% | 4% | 4% | ||||
| 10 | 36% | 46% | 10% | 14% | ||||
| 50 | 40% | 52% | 8% | 14% | ||||
| 250 | 57% | 38% | 4% | 16% | ||||
| Control-2 | 42% | 36% | 2% | 12% | ||||
The dose-related increase in pulmonary tumours observed in females did not reach statistical significance. The neoplastic lesions noted in this study were considered to reflect the spectrum of spontaneous neoplasms usually observed in mice of this strain and age.
- 2.
Two Year Oral - Rats
A two-year oral (dietary admixture) carcinogenicity study was conducted in rats (50/sex/group) at moclobemide doses of 0 (control -1), 0 (control-2), 9, 45 or 225 mg/kg/day.
Thirty-seven males and 60 females died prematurely. In both sexes, survival was greater at 45 and 225 mg/kg/day moclobemide than at 0 and 9 mg/kg/day. The negative dose-related trend was significant for males and for both sexes combined.
A total of 136 rats, 71 males and 65 females, had foci or hyperplasia. The clearest effect of treatment was for hepatocellular hyperplasia. Of the 23 cases reported, one occurred in the combined control groups, none was seen at 9 mg/kg, 7 occurred at 45 mg/kg and 15 at 225 mg/kg. The dose-related trend was similar and highly significant in each sex individually. The increases reached statistical significance at a moclobemide dose of 225 mg/kg for males and females individually and at 45 mg/kg for both sexes combined.
An increased incidence of alveolar foam cell aggregates was noted in the lungs of male rats at the 45 and 225 mg/kg/day doses and in females at the 9, 45 and 225 mg/kg/day doses. In addition, an increased incidence of small clusters of greenish-brown pigmented alveolar macrophages was diagnosed in the males receiving 225 mg/kg/day. Microscopic examination revealed no qualitative morphological differences between the alveolar macrophages of treated and control rats. The number and size of type II pneumocytes, however, were increased in treated rats compared to controls.
Reproduction and Teratology
- 1.
Fertility and General Reproductive Performance
A fertility and reproductive performance study was conducted in rats at oral (gavage) doses of 15, 40 or 100 mg/kg/day. Thirty-six males were treated 70 days prior to and during mating and 36 females for 14 days prior to mating until the 22nd day of lactation.
Nervousness and salivation were observed in both sexes. No treatment-related parental mortality occurred. The median weight gain of parental males in the 100 mg/kg dose group was significantly reduced throughout the first three weeks of treatment. A slight decrease in median body weight at weaning was observed in dams in the 40 mg/kg dose group. The body weights of females in the 100 mg/kg dose group were decreased throughout most of the treatment period.
Mating success, gestation length, and pregnancy outcome were not influenced by treatment in any group. A slight decrease in the median number of corpora lutea per pregnant female in the two upper dose groups was considered not to be drug-related.
Embryonic and fetal resorption rates were comparable to controls in all dose groups. In the highest dose group, the number of pups born alive was slightly decreased. Median body weights of the F-1 pups were comparable to controls in all dose groups during the lactation period.
The survivability of the F-1 pups was slightly to moderately reduced in the 40 and 100 mg/kg dose group, respectively. The examination of pups which died during the lactation period and of pups in the necropsy sub-groups revealed no abnormality considered to be drug-related.
When the rats from the F-2 generation were mated, the number of implantations, resorptions, and pups born were comparable to controls in all dose groups. At lactation days 1 and 4, a delay in pup weight development and a reduction in survivability were observed in the 100 mg/kg group.
The tests for physical and functional development as well as those for learning and memory revealed no statistically significant findings.
- 2.
Embryotoxicity and Teratology - Rats (Oral)
A teratology study was performed in 40 mated female rats at oral (gavage) doses of 25, 70 or 200 mg/kg/day from day 7 to day 16 of gestation inclusively. Another group of 40 rats received only the vehicle and served as control animals. On the 21st day of gestation, the rats in each dosage group were allocated to either a necropsy or a rearing subgroup.
During the treatment period, maternal weight gain was slightly retarded in the 25 and 70 mg/kg/day groups and moderately reduced in the 200 mg/kg group; by day 17 of gestation, dam weight gains in the low and mid-dose groups were approximately 72-85% of control values. In the high-dose group, dam weight gains were approximately 44% of control values. The reproductive process was not impaired in any of the dosage groups.
In the rearing experiment, there was no indication of a postnatal effect caused by drug administration at 25 or 70 mg/kg/day. At the 200 mg/kg/day dose, the survivability of the pups during the lactation period was reduced slightly to 85%.
The examination of skeletal abnormalities revealed no findings deviating from the norm except an increased number of incised vertebral bodies and poorly ossified sternebrae in the higher dosage groups. These findings indicate a slight retardation of ossification. An examination of soft tissue revealed no malformations in the groups given drug at 25 and 200 mg/kg/day. In the mid-dose group, two fetuses had an enlarged renal pelvis, one fetus had an enlargement of the right lateral cerebral ventricle, and one fetus had exencephaly and spina bifada. Due to their infrequent occurrence, these malformations are considered to be of a spontaneous nature.
- 3.
Embryotoxicity and Teratology - Rabbits (Oral)
A teratology study was performed in 20 mated female rabbits at oral (gavage) doses of 15, 40 or 100 mg/kg/day from day 7 to day 19 of gestation, inclusively. Another group of 20 rabbits received vehicle only and served as controls. The dams were sacrificed on day 30 of gestation and examined for drug effects on fertility and fetal gross abnormalities.
A dose-related retardation of maternal weight gain was observed during the treatment period; by day 20 of gestation, dam weight gains were 85%, 68% and 51% of control values in the low, mid and high dose groups, respectively.
The reproductive process (mean number of corpora lutea and implantations) was not impaired in any of the dosage groups). In the 15 mg/kg/day group, the resorption rate was significantly higher than in controls (33.6% of implantations versus 12.6% of implantations). As the number of resorptions in the higher dosage groups was significantly lower than in the 15 mg/kg group, and within the control range, this finding may not be drug-related. In the 100 mg/kg group, three dams aborted a total of 19 fetuses, two of the dams had severe diarrhea before aborting. One dam in each of the 15 mg/kg and the 40 mg/kg groups aborted.
Detailed examinations of the fetuses for skeletal abnormalities revealed that one fetus in the 40 mg/kg group had a missing medulla oblongata; omphalocele occurred in one fetus in the 15 mg/kg group and in one fetus in the 40 mg/kg group; and in the 40 mg/kg group, four fetuses in one litter had a thick, flatulent abdomen; one fetus had a protruding tongue. Due to their infrequent occurrence at low dosages only, these malformations are considered to be of a spontaneous nature.
- 4.
Perinatal and Postnatal - Rats (oral)
A perinatal and postnatal study was performed in 24 mated female rats/group at oral (gavage) doses of 30, 70 or 150 mg/kg/day from day 16 of gestation up to the end of the lactation period (day 23). Another group of 24 rats received the vehicle only and served as control.
Alopecia and mild transient diarrhea were observed in single animals of all treatment groups including controls, and were therefore regarded as not treatment related. Weight development was slightly delayed in dams in the 150 mg/kg dose group throughout the entire treatment period. No drug-related maternal death was observed. Reproductive parameters were not affected by treatment, with the exception of a slight nonsignificant increase in the resorption rate of dams in the 150 mg/kg dose group.
The median weight development of the F-1 pups during the lactation period was slightly delayed in all dose groups. A slight decrease in pup survivability was observed in the highest dose group. No treatment related gross external or visceral abnormalities were observed in living or dead pups. Tests of the physical and functional development of the F-1 generation revealed no statistically significant findings in any dose group.
BIBLIOGRAPHY
Drug Interactions
- 1. Dingemanse J. An update of recent moclobemide interaction data. Int Clin Psychopharmacol 1993;7: 167-180.
- 2. Dingemanse J, Kneer J, Wallnoefer A et al. Pharmacokinetic pharmacodynamic interactions between two selective Monoamine oxidase inhibitors: moclobemide and selegiline.Clinical Neuropharmacology 1996;19, No.5:399-414.
3 Korn A, Wagner B, Moritz E, et al. Tyramine pressure sensitivity in healthy subjects during combined treatment with moclobemide and selegiline. Eur J Clin Pharmacol 1996;49: 273-278.
Pharmacodynamics
- 1. Amrein R, et al. Interactions of moclobemide with concomitantly administered medication: evidence from pharmacological and clinical studies. Psychopharmacology 1992; 106:S24-31.
- 2. Gasic S, et al. Cardiocirculatory effect of moclobemide (Ro 11-1163), a new reversible, short-acting MAO-inhibitor with preferential type A inhibition, in healthy volunteers and depressive patients. Eur J Clin Pharmacol 1983; 25: 173-7.
- 3. Korn A, et al. Influence of moclobemide (Ro 11-1163) on the peripheral adrenergic system: interaction with tyramine and tricyclic antidepressants. In: Tipton KF, et al, eds. Monoamine oxidase and disease: prospects for therapy with reversible inhibitors. London: Academic Press. 1984: 487-95.
- 4. Korn A, et al. Tyramine pressor effect in man: studies with moclobemide, a novel, reversible monoamine oxidase inhibitor. J Neural Transm 1988; (suppl 26): 57-71.
- 5. Mueller T, Gieschke R, Ziegler WH. Blood pressure response to tyramine-enriched meal before and during MAO-inhibition in man: influence of dosage regimen. J Neural Transm 1988; (suppl 26): 105-14.
Pharmacokinetics
- 1. Geschke R, Koerner J, Eggers H. Determination of the new monoamine oxidase inhibitor moclobemide and three of its metabolites in biological fluids by high-performance liquid chromatography. J Chromatogr 1987; 420:111-20.
- 2. Raaflaub J, Haefelfinger P, Trautmann KH. Single dose pharmacokinetics of the MAO-inhibitor moclobemide in man. Arzneimittelforsch 1984; 34:80-2.
- 3. Schoerlin MP, et al. Disposition kinetics of moclobemide, a monoamine oxidase-A enzyme inhibitor: single and multiple dosing in normal subjects. Clin Pharmacol Ther 1987; 42:395-404.
- 4. Schoerlin MP, et al. Effect of food intake on the relative bioavailability of moclobemide (Ro 11-1163). J Neural Transm 1988; (suppl 26): 115-21.
- 5. Schoerlin MP, et al. The influence of renal insufficiency on the absorption and disposition of the monoamine oxidase-A inhibitor moclobemide. In: Aiache JM, et al, eds. Clinical Pharmacokinetics Vol 3. Freiburg (no publisher), 1987: 342-8.
- 6. Weisel FA, Raaflaub J, Kettler R. Pharmacokinetics of oral moclobemide in healthy human subjects and effects on MAO-activity in platelets and excretion of urine monoamine metabolites. Eur J Clin Pharmacol 1985; 28:89-95.
Clinical Use
- 1. Casacchia M, et al. A placebo-controlled study of the antidepressant activity of moclobemide, a new MAO-A inhibitor. Pharmacopsychiatry 1984; 17:122-5.
- 2. Heinze G, Sanchez A. Overdose with moclobemide. J Clin Psychiatry 1986; 47:438.
- 3. Larsen JK, Holm P, Mikkelsen PL. Moclobemide and clomipramine in the treatment of depression: a randomized clinical trial. Acta Psychiatr Scand 1984; 70:254-60.
- 4. Norman TR, et al. A controlled study of a specific MAO-A reversible inhibitor (Ro 11-1163) and amitriptyline in depressive illness. J Affect Disord 1985; 8:29-35.
- 5. Stefanis CN, Alevizos BH, Papadimitriou GN. Controlled clinical study of moclobemide, (Ro 11-1163), a new MAO inhibitor, and desipramine in depressive patients. In: Tipton KF, et al, eds. Monoamine oxidase and disease: prospects for therapy with reversible inhibitors. London: Academic Press, 1984: 377-92.
Other
- 1. MANERIX ® Product Monograph, Valeant Canada Lp, dated November 18, 2015, Control no. 187463.