


Product Monograph - Galantamine ER (Pro Doc)
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS | 02/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics ....................................................................................................................... 4
1.2 Geriatrics ....................................................................................................................... 4
2 CONTRAINDICATIONS ...................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ...................................................................................... 4
4.1 Dosing Considerations .................................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ............................................................. 5
4.4 Administration .............................................................................................................. 6
4.5 Missed Dose .................................................................................................................. 6
5 OVERDOSAGE .................................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................................... 8
7 WARNINGS AND PRECAUTIONS ....................................................................................... 9
7.1 Special Populations ..................................................................................................... 12
7.1.1 Pregnant Women ........................................................................................................ 12
7.1.2 Breast-feeding ............................................................................................................. 12
7.1.3 Pediatrics ..................................................................................................................... 12
7.1.4 Geriatrics ..................................................................................................................... 12
8 ADVERSE REACTIONS ..................................................................................................... 13
8.1 Adverse Reaction Overview ........................................................................................ 13
8.2 Clinical Trial Adverse Reactions .................................................................................. 15
8.3 Less Common Clinical Trial Adverse Reactions ........................................................... 19
8.5 Post-Market Adverse Reactions .................................................................................. 20
9 DRUG INTERACTIONS ..................................................................................................... 21
9.2 Drug Interactions Overview ........................................................................................ 21
9.4 Drug-Drug Interactions ............................................................................................... 22
9.5 Drug-Food Interactions ............................................................................................... 23
9.6 Drug-Herb Interactions ............................................................................................... 23
9.7 Drug-Laboratory Test Interactions .............................................................................. 23
10 CLINICAL PHARMACOLOGY ............................................................................................ 23
10.1 Mechanism of Action .................................................................................................. 23
10.2 Pharmacodynamics ..................................................................................................... 24
10.3 Pharmacokinetics ........................................................................................................ 24
11 STORAGE, STABILITY AND DISPOSAL .............................................................................. 28
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................ 28
PART II: SCIENTIFIC INFORMATION ...................................................................................... 29
13 PHARMACEUTICAL INFORMATION ................................................................................. 29
14 CLINICAL TRIALS ............................................................................................................. 30
14.1 Trial Design and Study Demographics ........................................................................ 30
14.2 Study Results ............................................................................................................... 31
14.3 Comparative Bioavailability Studies ........................................................................... 38
15 MICROBIOLOGY ............................................................................................................. 39
16 NON-CLINICAL TOXICOLOGY........................................................................................... 39
17 SUPPORTING PRODUCT MONOGRAPHS ......................................................................... 57
PATIENT MEDICATION INFORMATION ................................................................................. 58
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
GALANTAMINE ER (galantamine hydrobromide extended release capsules) is indicated for the symptomatic treatment of patients with mild to moderate dementia of the Alzheimer’s type.
Galantamine has not been studied in controlled clinical trials for longer than 6 months.
GALANTAMINE ER should only be prescribed by (or following consultation with) clinicians who are experienced in the diagnosis and management of Alzheimer’s disease.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available in children. Therefore, the use of GALANTAMINE ER is not recommended in children under 18 years of age.
1.2 Geriatrics
Geriatrics ( ≥ 85 years of age): There is limited safety information for galantamine in this patient population (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
GALANTAMINE ER is contraindicated in patients with known hypersensitivity to galantamine hydrobromide, other tertiary alkaloid derivatives or to any excipients used in the formulation. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
GALANTAMINE ER is not indicated for use in patients with mild cognitive impairment (see 7.1.4 Geriatrics, Patients with Mild Cognitive Impairment [MCI]).
GALANTAMINE ER should only be prescribed by (or following consultation with) clinicians who are experienced in the diagnosis and management of Alzheimer’s disease.
4.1 Dosing Considerations
- Concomitant Treatment: In patients treated with potent CYP2D6 or CYP3A4 inhibitors, dose reductions can be considered (see 9 DRUG INTERACTIONS).
- Special Populations: Dosage adjustments may be required for elderly patients ( ≥ 85 years old) with low body weight (especially females) (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, 7.1.4 Geriatrics), and patients with hepatic and/or renal impairment (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, Renal).
Missed Dose: The missed dose should be taken at the next scheduled dose. Doses should
- not be doubled. If therapy has been interrupted for several days or longer, the patient should be restarted at the lowest dose and the dose escalated to the current dose (see 4.5 Missed Dose).
4.2 Recommended Dose and Dosage Adjustment
The dosage of galantamine (as galantamine IR) shown to be effective in controlled clinical trials is 16-32 mg/day. As the dose of 32 mg/day is less well tolerated than lower doses and does not provide increased effectiveness, the recommended dose range is 16-24 mg/day. The dose of 24 mg/day did not provide a statistically significant greater clinical benefit than 16 mg/day. It is possible, however, that a daily dose of 24 mg of galantamine might provide additional benefit for some patients.
The recommended starting dose is 8 mg once daily for 4 weeks. The dose should be increased to the initial maintenance dose of 16 mg once daily after 4 weeks. If this initial maintenance dose is well tolerated, a further increase to 24 mg once daily may be considered only after a minimum of 4 weeks at 16 mg once daily.
The abrupt withdrawal of galantamine in those patients who had been receiving doses in the effective range was not associated with an increased frequency of adverse events in comparison with those continuing to receive the same doses of that drug. The beneficial effects of galantamine are lost, however, when the drug is discontinued.
Pediatrics
Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics).
Geriatrics
Dose escalation for elderly patients ( ≥ 85 years old) with low body weight (especially females) or serious comorbid diseases should be undertaken with particular caution (see 7.1.4 Geriatrics).
Hepatic Impairment
There is limited information on the pharmacokinetics of galantamine in hepatically impaired patients (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Impairment). It is therefore recommended that dose escalation with GALANTAMINE ER in Alzheimer’s disease patients with hepatic impairment be undertaken with caution and under conditions of close monitoring for adverse effects.
Galantamine plasma concentrations may be increased in patients with moderate to severe hepatic impairment. In patients with moderately impaired hepatic function (Child-Pugh score of 7–9), based on pharmacokinetic modelling, dosing with GALANTAMINE ER extended release capsules should begin with 8 mg every other day in the morning, preferably with food, for at least 1 week. Then the dosage should be increased to 8 mg once daily for at least 4 weeks. In these patients, daily doses should not exceed a total of 16 mg once daily. Since no data are available on the use of galantamine in patients with severe hepatic impairment (Child-Pugh score of 10–15), GALANTAMINE ER is not recommended for this population (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Renal Impairment
There is limited information on the pharmacokinetics of galantamine in renally impaired patients (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment). It is therefore recommended that dose escalation with GALANTAMINE ER in Alzheimer’s disease patients with renal impairment (creatinine clearance of 9 to 60 mL/min) be undertaken with caution and under conditions of close monitoring for adverse effects.
For patients with renal impairment (creatinine clearance of 9 to 60 mL/min), dose escalation should proceed cautiously, and the maintenance dose should generally not exceed 16 mg once daily. Since no data are available on the use of galantamine in patients with a creatinine clearance less than 9 mL/min, GALANTAMINE ER is not recommended for this population (see 7 WARNINGS AND PRECAUTIONS, Renal).
In a population of cognitively-impaired individuals, safe use of this and all other medications may require supervision.
4.4 Administration
GALANTAMINE ER should be administered once daily in the morning, preferably with food. Patients and caregivers should be advised to ensure adequate fluid intake during treatment.
4.5 Missed Dose
The missed dose should be taken at the next scheduled dose. Doses should not be doubled. If therapy has been interrupted for several days or longer, the patient should be restarted at the lowest dose and the dose escalated to the current dose.
5 OVERDOSAGE
Symptoms
Overdosage with cholinesterase inhibitors can result in cholinergic crisis characterized by severe nausea, vomiting, gastro-intestinal cramping, salivation, lacrimation, urination, defecation, sweating, bradycardia, hypotension, respiratory depression, collapse and convulsions. Increasing muscle weakness together with tracheal hypersecretion and bronchospasm, may lead to vital airway compromise.
There have been post-marketing reports of torsade de pointes, QT prolongation, bradycardia, ventricular tachycardia and brief loss of consciousness in association with inadvertent overdoses of galantamine. In one case where the dose was known, eight 4 mg tablets (32 mg total) were ingested on a single day.
Two additional cases of accidental ingestion of 32 mg (nausea, vomiting, and dry mouth; nausea, vomiting, and substernal chest pain) and one of 40 mg (vomiting), resulted in brief hospitalizations for observation with full recovery. One patient, who was prescribed 24 mg/day and had a history of hallucinations over the previous two years, mistakenly received 24 mg twice daily for 34 days and developed hallucinations requiring hospitalization. Another patient, who was prescribed 16 mg/day, inadvertently ingested 160 mg and experienced sweating, vomiting, bradycardia, and near-syncope one hour later, which necessitated hospital treatment. His symptoms resolved within 24 hours.
Treatment
Galantamine has a plasma half-life of approximately 7–8 hours. It is recommended that, in case of asymptomatic overdose, no further dose of GALANTAMINE ER should be administered and the patient should be monitored.
As in any case of overdose, general supportive measures should be utilized. Signs and symptoms of significant overdosing of galantamine are predicted to be similar to those of overdosing of other cholinomimetics. These effects generally involve the central nervous system, the parasympathetic nervous system, and the neuromuscular junction. In addition to muscle weakness or fasciculations, some or all of the following signs of cholinergic crisis may develop: severe nausea, vomiting, gastrointestinal cramping, salivation, lacrimation, urination, defecation, sweating, bradycardia, hypotension, respiratory depression, collapse and convulsions. Increasing muscle weakness is a possibility and may result in death if respiratory muscles are involved.
Tertiary anticholinergics such as atropine may be used as an antidote for galantamine overdosage. Intravenous atropine sulphate titrated to effect is recommended at an initial dose of 0.5 to 1.0 mg intravenously (IV) with subsequent doses based upon clinical response.
Atypical responses in blood pressure and heart rate have been reported with other cholinomimetics when co-administered with quaternary anticholinergics. It is not known whether galantamine and/or its metabolites can be removed by dialysis (hemodialysis, peritoneal dialysis, or hemofiltration). Dose-related signs of toxicity in animals included hypoactivity, tremors, clonic convulsions, salivation, lacrimation, chromodacryorrhea, mucoid feces, and dyspnea.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Extended release capsule / 8 mg, 16 mg, 24 mg galantamine base | Colloidal Silicon Dioxide, Eudragit, Gelatin, Microcrystalline Cellulose, Titanium Dioxide, and Triethyl Citrate. 16 mg capsule also contains Red Iron Oxide. 24 mg capsule also contains Red Iron Oxide and Yellow Iron Oxide. |
Dosage Forms
Extended release capsules
8 mg: Each white opaque capsule imprinted with "GT8" contains 8 mg galantamine as galantamine hydrobromide, and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Eudragit, Gelatin, Microcrystalline Cellulose, Triethyl Citrate and Titanium Dioxide.
16 mg: Each pink opaque capsule imprinted with "GT16" contains 16 mg galantamine as galantamine hydrobromide, and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Eudragit, Gelatin, Microcrystalline Cellulose, Red Iron Oxide, Triethyl Citrate and Titanium Dioxide.
24 mg: Each caramel opaque capsule imprinted with "GT24" contains 24 mg galantamine as galantamine hydrobromide, and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Eudragit, Gelatin, Microcrystalline Cellulose, Red Iron Oxide, Triethyl Citrate, Titanium Dioxide and Yellow Iron Oxide.
Imprinting ink for capsules has the following non-medicinal ingredients: Ammonium Hydroxide, Iron Oxide Black, Propylene Glycol and Shellac Glaze.
Packaging
GALANTAMINE ER is available in bottles of 30 and 100 capsules.
7 WARNINGS AND PRECAUTIONS
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity and Mutagenicity for discussion on animal data.
Cardiovascular
Because of their pharmacological action, cholinesterase inhibitors have vagotonic effects on the sinoatrial and atrioventricular nodes, leading to bradycardia and all types of atrioventricular node block (see 8 ADVERSE REACTIONS). These actions may be particularly important to patients with “sick sinus syndrome” or other supraventricular cardiac conduction disorders, or to patients taking other drugs concomitantly which significantly slow heart rate. In clinical trials, patients with serious cardiovascular disease were excluded. Caution should be exercised in treating patients with active coronary artery disease or congestive heart failure. It is recommended that GALANTAMINE ER not be used in patients with cardiac conduction abnormalities (except for right bundle branch block) including “sick sinus syndrome” and those with unexplained syncopal episodes.
In randomized controlled trials, bradycardia was reported at 2-3% for galantamine doses up to 24 mg/day compared with < 1% for placebo, but was rarely severe and rarely led to treatment discontinuation. No increased incidence of heart block was observed at the recommended doses. Patients treated with galantamine up to 24 mg/day at the recommended dosing schedule showed a dose-related increase in risk of syncope (placebo, 0.7% [2/286]; 4 mg twice a day (b.i.d.), 0.4% [3/692]; 8 mg b.i.d., 1.3% [7/552]; 12 mg b.i.d., 2.2% [6/273]).
A 6-week cardiovascular safety clinical trial (GAL-USA-16; n=139) was performed to investigate the effect of galantamine at doses up to 32 mg/day. This dosing regimen was: 8 mg/day in Week 1, 16 mg/day in Week 2, 24 mg/day in Weeks 3 and 4, and 32 mg/day in Weeks 5 and 6. Heart block/pauses greater than two seconds were more common in galantamine-treated patients than in placebo-treated patients. It should be noted that a forced one-week dose escalation was used in this study, which is not recommended. Whether these cardiac effects are attenuated by slower titration rates is not known. Particular caution is warranted during titration where the majority of pauses occurred in the above study.
Driving and Operating Machinery
GALANTAMINE ER may cause adverse reactions (such as dizziness and somnolence), which could affect the ability to drive or use machines, especially during the first weeks after initiation of treatment (see 8 ADVERSE REACTIONS).
Endocrine and Metabolism
Weight Monitoring
Cholinesterase inhibitors as well as Alzheimer’s disease can be associated with significant weight loss. In controlled clinical trials, the use of galantamine was associated with weight loss. Weight decrease occurred early during treatment and was related to dose. Weight loss of ≥ 7% occurred more frequently in patients treated with galantamine and in female patients than in patients receiving placebo. Where weight loss may be of clinical concern, body weight should be monitored.
Gastrointestinal
Through their primary action, cholinesterase inhibitors may be expected to increase gastric acid secretion due to increased cholinergic activity. Therefore, patients should be monitored closely for symptoms of active or occult gastrointestinal bleeding, especially those with an increased risk for developing ulcers, e.g., those with a history of ulcer disease or patients using concurrent nonsteroidal anti-inflammatory drugs (NSAIDs). In controlled clinical studies with galantamine, patients with symptomatic peptic ulceration were excluded. Clinical studies of galantamine have shown no increase, relative to placebo, in the incidence of either peptic ulcer disease or gastrointestinal bleeding (see 8 ADVERSE REACTIONS).
Galantamine, as a predictable consequence of its pharmacological properties, has been shown to produce nausea, vomiting and diarrhea, anorexia and weight loss. These effects appeared more frequently at higher doses (see 8 ADVERSE REACTIONS), with nausea and vomiting being more prevalent in women and patients with lower body weight and correspondingly higher plasma drug concentrations. Females are more sensitive to the cholinergic adverse effects associated with cholinesterase inhibitors and in general are more likely to experience nausea and vomiting than are males. In most cases, these effects were of mild to moderate intensity and transient and have resolved during continued galantamine treatment or upon treatment discontinuation.
Genitourinary
Although not observed in clinical trials of galantamine, cholinomimetics may cause bladder outflow obstruction.
Hepatic/Biliary/Pancreatic
There is limited information on the pharmacokinetics of galantamine in hepatically impaired patients (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Impairment). It is therefore recommended that dose escalation with GALANTAMINE ER in Alzheimer’s disease patients with hepatic impairment be undertaken with caution and under conditions of close monitoring for adverse effects (see 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment). Since no data are available on the use of galantamine in patients with severe hepatic impairment (Child-Pugh score of 10–15), GALANTAMINE ER is not recommended for this population.
Neurologic
Galantamine has not been studied in patients with moderately severe or severe Alzheimer’s disease, non-Alzheimer dementias or individuals with Parkinsonian features. The efficacy and safety of GALANTAMINE ER in these patient populations is unknown.
Seizures
In placebo-controlled trials with galantamine, cases of seizure were reported; there was no increase in incidence compared with placebo. Convulsions have been reported with galantamine (see 8 ADVERSE REACTIONS). Seizure activity may also be a manifestation of Alzheimer’s disease. The risk/benefit of GALANTAMINE ER treatment for patients with a history of seizure disorder must therefore be carefully evaluated.
Tremor and Other Extrapyramidal Symptoms
Like other cholinomimetics, there have been post-marketing reports of extrapyramidal disorders related to an increase in cholinergic tone that may also worsen symptoms of pre- existing extrapyramidal disorders (see 8.5 Post-Market Adverse Reactions).
Peri-Operative Considerations
Anesthesia
Galantamine, as a cholinesterase inhibitor, is likely to exaggerate succinylcholine -type muscle relaxation during anesthesia.
Renal
There is limited information on the pharmacokinetics of galantamine in renally impaired patients (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment). It is therefore recommended that dose escalation with GALANTAMINE ER in Alzheimer’s disease patients with renal impairment (creatinine clearance of 9 to 60 mL/min) be undertaken with caution and under conditions of close monitoring for adverse effects (see 4.2 Recommended Dose and Dosage Adjustment, Renal Impairment). Since no data are available on the use of galantamine in patients with a creatinine clearance of less than 9 mL/min, GALANTAMINE ER is not recommended for this population.
Respiratory
Like other cholinomimetic drugs, GALANTAMINE ER should be prescribed with care for patients with a history of asthma or obstructive pulmonary disease.
Skin
Serious skin reactions (Stevens-Johnson syndrome and acute generalized exanthematous pustulosis), and other less serious skin reactions (e.g., erythema multiforme), have been reported in patients receiving galantamine (see 8.5 Post-Market Adverse Reactions). Patients or caregivers should be instructed to inform their health care provider of any skin reactions that occur during treatment with GALANTAMINE ER. It is recommended that treatment should be discontinued at the first appearance of skin rash.
7.1 Special Populations
7.1.1 Pregnant Women
The safety of galantamine in pregnant women has not been established. GALANTAMINE ER should not be used in women of childbearing potential unless, in the opinion of the physician, the potential benefit to the patient justifies the potential risk to the fetus.
In a teratology study in which rats were dosed from Day 14 (females) or Day 60 (males) prior to mating through the period of organogenesis, a slightly increased incidence of skeletal variations was observed at doses of 8 mg/kg/day (3 times the MRHD on a mg/m2 basis) and
16 mg/kg/day. In a study in which pregnant rats were dosed from the beginning of organogenesis through day 21 post-partum, pup weights were decreased at 8 and
16 mg/kg/day, but no adverse effects on other postnatal developmental parameters were seen. The doses causing the above effects in rats produced slight maternal toxicity. No major malformations were caused in rats given up to 16 mg/kg/day. No drug-related teratogenic effects were observed in rabbits given up to 40 mg/kg/day (32 times the MRHD on a mg/m2 basis) during the period of organogenesis.
7.1.2 Breast-feeding
It is unknown if galantamine is excreted in human breast milk and therefore GALANTAMINE ER should not be used in nursing mothers.
7.1.3 Pediatrics
Pediatrics: The safety and effectiveness of galantamine in any illness occurring in pediatric patients have not been established.
7.1.4 Geriatrics
Geriatrics ( ≥ 85 years of age): In controlled clinical studies, the number of patients aged 85 years or over who received galantamine hydrobromide tablets at therapeutic doses of 16 or 24 mg/day was 123. Of these patients, 70 received the maximum recommended dose of 24 mg/day. There is limited safety information for galantamine in this patient population.
Since cholinomimetics, as well as Alzheimer’s disease, can be associated with significant weight loss, caution is advised regarding the use of GALANTAMINE ER in elderly patients with low body weight, especially in those ≥ 85 years old.
Use in Elderly Patients with Serious Comorbid Disease
There is limited information on the safety of galantamine treatment in patients with mild to moderate Alzheimer’s disease and serious/significant comorbidity. The use of GALANTAMINE ER in Alzheimer’s disease patients with chronic illnesses common among the geriatric population, should be considered only after careful risk/benefit assessment and include close monitoring for adverse events. Dose escalation in this patient population should proceed with caution.
Patients with Mild Cognitive Impairment (MCI)
Mortality in Investigational Trials in MCI
Two randomized, double-blind, placebo-controlled efficacy and safety studies of two years’ duration were completed in non-demented subjects with MCI. Individuals with MCI demonstrate isolated memory impairment greater than expected for their age and education, but do not meet current diagnostic criteria for Alzheimer's disease. In these trials, galantamine hydrobromide tablets were not shown to be effective in patients with MCI. In the double -blind portion of these two trials, a total of 13 deaths in subjects on galantamine hydrobromide tablets (n=1,026) were recorded and 1 death in subjects on placebo (n=1,022); the reason for this difference is currently unknown. This difference in mortality has not been observed in galantamine studies in Alzheimer’s disease. Approximately half of the galantamine deaths appeared to have resulted from various vascular causes (myocardial infarction, stroke, and sudden death); other deaths appeared to have resulted from infection, suicide and cancer.
There is no evidence of an increased risk of mortality when galantamine is used in patients with mild to moderate Alzheimer’s disease.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
A total of 2,287 patients with mild to moderate Alzheimer’s disease were treated with galantamine hydrobromide tablets in Phase III controlled clinical studies using either a 1-week or 4-week dose-escalation period, and 761 patients received galantamine hydrobromide tablets 24 mg/day, the maximum recommended maintenance dose. The number of patients who completed the studies was 1,686 (72%). The mean duration of treatment for all galantamine groups was 130 days (range 1-214 days).
Adverse Events Leading to Discontinuation
Overall, 19% (441/2,287) of patients treated with galantamine hydrobromide tablets discontinued from Phase III controlled clinical trials due to adverse events compared to 8% (98/1,159) in the placebo group. For patients treated with galantamine hydrobromide tablets, the rate of discontinuation due to adverse events was 14% for males and 22% for females.
In the 4-week dose-escalation fixed-dose study (GAL-USA-10), 8% (55/692) of patients treated with galantamine hydrobromide tablets withdrew due to adverse events compared to 7% (20/286) in the placebo group. During the dose-escalation phase of this study the incidence of discontinuations due to adverse events was 4% for placebo, 5% for galantamine 16 mg/day and 6% for galantamine 24 mg/day. During the maintenance phase, 4% of patients who received placebo, 3% of patients who received galantamine 16 mg/day and 4% of patients who received galantamine 24 mg/day withdrew from this study due to adverse events.
Table 1 shows the most frequent adverse events leading to discontinuation for study GAL-USA- 10, in which the recommended 4-week dose-escalation schedule was used.
Table 1: Most Frequent Adverse Events Leading to Discontinuation in a Placebo-Controlled, Double-Blind Trial with a 4-Week Dose-Escalation Schedule (GAL-USA-10)
| Adverse Events | Recommended 4-week dose escalation | ||
Placebo n = 286 % | 16 mg/day n = 279 % | 24 mg/day n = 273 % | |
| Nausea | < 1 | 2 | 4 |
| Vomiting | 0 | 1 | 3 |
| Anorexia | < 1 | 1 | < 1 |
| Dizziness | < 1 | 2 | 1 |
| Syncope | 0 | 0 | 1 |
Most Frequent Adverse Clinical Events Seen in Association with the Use of Galantamine Hydrobromide Tablets
The most frequent adverse events, defined as those occurring at a frequency of at least 5% and at least twice the rate of placebo in study GAL-USA-10, in which the recommended 4-week dose-escalation schedule was used are shown in Table 2.
These events were primarily gastrointestinal and tended to occur at a lower rate with 16 mg/day, the initial recommended maintenance dose. Administration of galantamine hydrobromide tablets with food, the use of anti-emetic medication and ensuring adequate fluid intake may reduce the impact of these events.
Table 2: Most Frequent Adverse Events in a Randomized Placebo-Controlled Clinical Trial with a 4-Week Dose Increment During Dose-Escalation and Maintenance Phases (GAL-USA-10)
| Week 1–12† | Week 13–21 |
Adverse Events
Placebo n=286 % | 16 mg/day n=279 % | 24 mg/day n=273 % | Placebo n=259 % | 16 mg/day n=243 % | 24 mg/day n=241 % | |||||||
| Nausea | 5 | 11 | 13 | <1 | 4 | 6 | ||||||
| Vomiting | <1 | 5 | 6 | <1 | 2 | 6 | ||||||
| Diarrhea | 5 | 9 | 4 | 2 | 5 | 2 | ||||||
| Anorexia | 2 | 5 | 5 | 1 | 2 | 5 | ||||||
| † Dose escalation occurred with 4 weeks per dose increment | ||||||||||||
The majority of these adverse events occurred during the dose-escalation period. Nausea and vomiting, the most frequent adverse events, occurred more frequently at higher doses, lasted 5-7 days in most cases, and the majority of patients had one episode. The incidence of weight loss in this study was, during dose escalation (Weeks 1-12): placebo, 1%; 16 mg/day, 3%; 24 mg/day, 2%; and during the maintenance phase (Weeks 13-21): placebo, < 1%; 16 mg/day, 3%; 24 mg/day, 3%.
Dose-escalation should be cautious and maintenance dosing should remain flexible and be adjusted according to individual needs.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse Events Reported in Clinical Trials with Galantamine Hydrobromide Tablets
The reported adverse events in trials of galantamine hydrobromide tablets reflect experience gained under closely monitored conditions in a highly selected patient population. In actual practice or in other clinical trials, these frequency estimates may not apply, as the conditions of use, reporting behaviour and the types of patients treated may differ.
Table 3 lists the most common adverse events (adverse events occurring with an incidence of 2% with galantamine tablet treatment and in which the incidence was greater than with placebo treatment) for four placebo-controlled trials for patients treated with 16 or 24 mg/day of galantamine tablets. The combined values presented in Table 3 were derived from trials using a 1-week or the recommended 4-week dose-escalation period.
Table 3: Adverse Events Reported in at Least 2% of Patients with Alzheimer’s Disease Administered Galantamine Hydrobromide Tablets and at a Frequency Greater than with Placebo (Combined 1- and 4-Week Dose-Escalation Data)
| Body System/Adverse Events | Placebo (n=801) % | Galantamine Tablets† (n=1,040) % |
|---|---|---|
Body as a whole - general disorders Fatigue | 3 | 5 |
| Syncope | 1 | 2 |
Central and peripheral nervous system disorders Dizziness | 6 | 9 |
| Headache | 5 | 8 |
| Tremor | 2 | 3 |
Gastrointestinal system disorders Nausea | 9 | 24 |
| Vomiting | 4 | 13 |
| Body System/Adverse Events | Placebo (n=801) % | Galantamine Tablets† (n=1,040) % |
|---|---|---|
| Diarrhea | 7 | 9 |
| Abdominal pain | 4 | 5 |
| Dyspepsia | 2 | 5 |
Heart rate and rhythm disorders Bradycardia | 1 | 2 |
Metabolic and nutritional disorders Anorexia Weight decrease | 3 2 | 9 7 |
Psychiatric disorders Depression | 5 | 7 |
| Insomnia | 4 | 5 |
| Somnolence | 3 | 4 |
Red blood cell disorders Anemia | 2 | 3 |
Respiratory system disorders Rhinitis | 3 | 4 |
Urinary system disorders Urinary tract infection | 7 | 8 |
| Hematuria | 2 | 3 |
| † Adverse events in patients treated with 16 or 24 mg/day of galantamine in three placebo-controlled trials with a 1-week dose-escalation period and a 26-week fixed-dose galantamine treatment, and one placebo--controlled trial with the recommended 4-week dose-escalation period and a 21-week fixed-dose galantamine treatment are included. | ||
No clinically relevant abnormalities in laboratory values were observed. In a cardiovascular safety clinical trial (GAL-USA-16), pauses greater than two seconds were more common in galantamine-treated patients than in placebo-treated patients during the dose-escalation period (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Adverse Events Reported in Clinical Trials with Galantamine Hydrobromide Extended Release Capsules
Adverse reactions in clinical trials of once-daily treatment with galantamine hydrobromide extended release capsules were similar to those seen with galantamine hydrobromide tablets (see Table 4).
Table 4: Adverse Events Reported in at Least 2% of Patients with Alzheimer’s Disease Administered Galantamine Hydrobromide Tablets or Galantamine Hydrobromide Extended-Release Capsules and at a Frequency Greater than Placebo
System Organ Class Preferred Term | Placebo (n=320) % | Galantamine Tablets (n=326) % | Galantamine Extended-Release Capsules (n=319) % |
|---|---|---|---|
Body as a whole – general disorders Injury | 6 | 4 | 8 |
| Edema peripheral | 3 | 2 | 4 |
| Fatigue | 1 | 4 | 4 |
| Syncope | 1 | 1 | 2 |
| Fever | 1 | 2 | 1 |
| Leg pain | 1 | 2 | < 1 |
Central & peripheral nervous system disorders Dizziness | 4 | 7 | 10 |
| Headache | 6 | 6 | 8 |
| Tremor | 0 | 1 | 2 |
Gastrointestinal system disorders Nausea | 5 | 14 | 17 |
| Vomiting | 2 | 9 | 7 |
| Abdominal pain | 2 | 3 | 2 |
| Dyspepsia | 2 | 3 | 2 |
Heart rate and rhythm disorders Bradycardia | 2 | 2 | 3 |
Metabolic and nutritional disorders Anorexia | 3 | 7 | 6 |
Weight decrease Hyperglycemia | 1 1 | 5 2 | 4 2 |
Musculoskeletal system disorders Arthralgia | 2 | 2 | 3 |
| Skeletal pain | 1 | 3 | 2 |
| Arthritis | 1 | 1 | 2 |
| Myalgia | 1 | 1 | 2 |
| Psychiatric disorders | |||
| Depression | 3 | 5 | 6 |
| Anxiety | 3 | 1 | 4 |
| Somnolence | 2 | 2 | 3 |
| Depression aggravated | 1 | 2 | 2 |
| Aggressive reaction | 1 | 2 | 2 |
| Nervousness | 1 | 2 | 1 |
System Organ Class Preferred Term | Placebo (n=320) % | Galantamine Tablets (n=326) % | Galantamine Extended-Release Capsules (n=319) % |
|---|---|---|---|
Respiratory system disorders Rhinitis | 3 | 4 | 4 |
| Pneumonia | 1 | 2 | 2 |
Secondary terms Abrasion nosa | 1 | 1 | 2 |
Skin and appendages disorders Rash | 1 | < 1 | 3 |
Urinary system disorders Hematuria | 1 | 1 | 2 |
| Micturition frequency | 1 | 2 | 1 |
Vision disorders Cataract | 1 | 1 | 2 |
a not otherwise specified
Other galantamine Clinical Trial Adverse Drug Reactions
Additional adverse drug reactions that do not appear in Table 4, and that occurred in at least 2% of patients with Alzheimer’s disease administered galantamine and at a frequency greater than placebo, are listed below by system organ class:
Injury, Poisoning and Procedural Complications: fall, laceration
Adverse Events Observed During the GAL-INT-6 Study
A randomized, double-blind, placebo-controlled clinical trial (GAL-INT-6) was conducted in a study population consisting of two different types of dementia patients: patients with vascular dementia (VaD) and patients with Alzheimer’s disease and concomitant cerebrovascular disease (AD+CVD).
The frequencies of certain cardiovascular-related adverse events, including syncope, hypertension, arrhythmia and bundle branch block were increased in patients treated with galantamine compared to placebo. The increase was due primarily to events that occurred in the subgroup of Alzheimer’s patients with concomitant cerebrovascular disease. Patients with Alzheimer’s disease and concomitant cerebrovascular disease who were treated with galantamine experienced syncope (3%), hypertension (4%), arrhythmia (3%) and bundle branch block (2%), but these events were not reported in the placebo group.
In the vascular dementia subgroup syncope was reported for 2% of patients treated with galantamine and 2% of patients treated with placebo; hypertension was reported for 5% of patients treated with galantamine and 2% of patients treated with placebo. Arrhythmia and bundle branch block adverse events were not reported in the vascular dementia subgroup.
In the entire study population the most common treatment-emergent adverse events (nausea, dizziness, vomiting, abdominal pain, diarrhea, fatigue and upper respiratory tract infection) were consistent with what has been observed in previous studies of galantamine hydrobromide tablets involving Alzheimer’s disease patients (see 8 ADVERSE REACTIONS).
8.3 Less Common Clinical Trial Adverse Reactions
Galantamine hydrobromide tablets have been administered to 3,055 patients with Alzheimer’s disease during clinical trials worldwide.
A total of 2,357 patients received galantamine in placebo-controlled trials and 761 patients with Alzheimer’s disease received galantamine 24 mg/day, the maximum recommended maintenance dose. About 1,000 patients received galantamine for at least one year and approximately 200 patients received galantamine for two years. To establish the rate of adverse events, data from all patients for any dose of galantamine hydrobromide tablets in 8 placebo- controlled trials and 6 open-label extension trials were pooled. The methodology to gather and codify these adverse events was standardized across trials, using WHO terminology. All events occurring in approximately 0.1% of patients are included, except for those already listed elsewhere in labelling, WHO terms too general to be informative, or relatively minor events.
Events are classified by body system and listed using the following definitions: frequent adverse events - those occurring in at least 1/100 patients; infrequent adverse events - those occurring in 1/100 to 1/1,000 patients; rare - those occurring in 1/1,000 to 1/10,000 patients; very rare - those occurring in fewer than 1/10,000 patients. These adverse events are not necessarily related to galantamine tablet treatment and in most cases, were observed at a similar frequency in placebo-treated patients in the controlled studies.
Body as a Whole – General Disorders: Frequent: chest pain, asthenia, fever, malaise.
Cardiovascular System Disorders: Frequent: hypertension; Infrequent: postural hypotension, hypotension, dependent edema, cardiac failure, myocardial ischemia or infarction, flushing, supraventricular extrasystoles.
Central and Peripheral Nervous System Disorders: Frequent: lethargy; Infrequent: vertigo, hypertonia, convulsions, involuntary muscle contractions, paresthesia, ataxia, hypokinesia, hyperkinesia, apraxia, aphasia, leg cramps, tinnitus, transient ischemic attack or cerebrovascular accident, dysgeusia, hypersomnia.
Eye Disorders: Infrequent: vision blurred.
Gastrointestinal System Disorders: Frequent: flatulence, abdominal discomfort, abdominal pain, upper stomach discomfort; Infrequent: gastritis, melena, dysphagia, rectal hemorrhage, dry mouth, saliva increased, diverticulitis, gastroenteritis, hiccup, retching; Rare: esophageal perforation.
Heart Rate and Rhythm Disorders: Infrequent: AV block, palpitation, atrial arrhythmias including atrial fibrillation and supraventricular tachycardia, QTc prolonged, bundle branch block, T-wave inversion, ventricular tachycardia; Rare: severe bradycardia.
Hepatobiliary: There have been reports of hepatic-related adverse reactions including elevated liver enzymes and hepatitis, from both open-label studies of galantamine (duration up to 4 years) and post-marketing experience (see 8.5 Post-Market Adverse Reactions).
Metabolic and Nutritional Disorders: Frequent: decreased appetite; Infrequent: hyperglycemia, alkaline phosphatase increased, NPN increased.
Musculoskeletal System Disorders: Frequent: muscle spasms; Infrequent: muscular weakness.
Platelet, Bleeding and Clotting Disorders: Infrequent: purpura, epistaxis, thrombocytopenia.
Psychiatric Disorders: Infrequent: apathy, paroniria, paranoid reaction, libido increased, delirium; Rare: suicidal ideation, suicide attempt.
Skin and Appendages Disorders: Frequent: hyperhidrosis.
Urinary System Disorders: Frequent: incontinence; Infrequent: hematuria, micturition frequency, cystitis, urinary retention, nocturia, renal calculi.
8.5 Post-Market Adverse Reactions
Other adverse events from post-approval controlled and uncontrolled clinical trials and post- marketing experience observed in patients treated with galantamine hydrobromide tablets include:
Body as a Whole – General Disorders: dehydration (including rare, severe cases leading to renal insufficiency and renal failure).
Cardiac Disorders: atrioventricular block complete.
Central and Peripheral Nervous System Disorders: behavioural disturbances (including agitation, aggression, hallucination, hallucination visual, hallucination auditory) and extrapyramidal disorders (including, but not limited to, pleurothotonus, parkinsonism, tremor, dyskinesia, cogwheel rigidity, postural abnormal).
Gastrointestinal: upper and lower GI bleeding.
Hepatobiliary: elevated liver enzymes, hepatitis.
Immune System Disorders: hypersensitivity.
Metabolic and Nutritional Disorders: hypokalemia.
Skin and subcutaneous tissue disorders: Stevens-Johnson syndrome, acute generalized exanthematous pustulosis, erythema multiforme.
Some of these adverse events may be attributable to cholinomimetic properties of galantamine or in some cases may represent manifestations or exacerbations of the underlying disease processes common in the elderly population.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Multiple metabolic pathways and renal excretion are involved in the elimination of galantamine so no single pathway appears predominant. Based on in vitro studies, CYP2D6 and CYP3A4 were the major enzymes involved in the metabolism of galantamine. CYP2D6 was involved in the formation of O-desmethyl-galantamine, whereas CYP3A4 mediated the formation of galantamine-N-oxide.
Use with Inhibitors of CYP2D6 or CYP3A4
During treatment with potent inhibitors of CYP2D6 or CYP3A4 patients may experience an increased incidence of cholinergic side effects, predominantly nausea and vomiting. Under these circumstances, based on tolerability, a reduction of the galantamine maintenance dose can be considered (see 4.1 Dosing Considerations).
Use with Anticholinergics
Because of their mechanism of action, cholinesterase inhibitors have the potential to interfere with the activity of anticholinergic medications.
Use with Cholinomimetics and Other Cholinesterase Inhibitors
A synergistic effect may be expected when cholinesterase inhibitors are given concurrently with succinylcholine, similar neuromuscular blocking agents or cholinergic agonists such as bethanechol.
Use with Other Psychoactive Drugs
Few patients in the clinical trials received neuroleptics, antidepressants or anticonvulsants, thus, there is limited information concerning the interaction of galantamine with these drugs.
9.4 Drug-Drug Interactions
Effect of Other Drugs on the Metabolism of Galantamine
Pharmacokinetic studies to assess the potential of galantamine for interaction with cimetidine, ranitidine, ketoconazole, erythromycin, paroxetine, warfarin and digoxin were limited to short- term, mostly single-dose studies in young healthy volunteers. Similar studies in elderly patients were not done.
In vitro
CYP3A4 and CYP2D6 are the major enzymes involved in the metabolism of galantamine. CYP3A4 mediates the formation of galantamine-N-oxide, whereas CYP2D6 is involved in the formation of O-desmethyl-galantamine. Because galantamine is also glucuronidated and excreted unchanged in urine, no single pathway appears predominant.
In vivo
Cimetidine and Ranitidine: Galantamine was administered as a single dose of 4 mg on Day 2 of a three-day treatment with either cimetidine (800 mg daily; n = 6 males and 6 females) or ranitidine (300 mg daily; n=6 males and 6 females). Cimetidine increased the bioavailability of galantamine by approximately 16%. Ranitidine had no effect on the pharmacokinetics of galantamine.
Ketoconazole: Ketoconazole, a strong inhibitor of CYP3A4 and an inhibitor of CYP2D6, at a dose of 200 mg b.i.d. for 4 days, increased the AUC of galantamine by 30% when subjects were treated with galantamine 4 mg b.i.d. for 8 days (n=8 males and 8 females).
Erythromycin: Erythromycin, a moderate inhibitor of CYP3A4 at a dose of 500 mg q.i.d. for 4 days increased the AUC of galantamine by 10% when subjects received galantamine 4 mg b.i.d. for 6 days (n=8 males and 8 females).
Paroxetine: Paroxetine, a strong inhibitor of CYP2D6, increased the AUC of galantamine tablets 4 mg b.i.d., 8 mg b.i.d. and 12 mg b.i.d. by 40%, 45% and 48 %, respectively, in 16 healthy volunteers (8 males and 8 females) who received galantamine together with 20 mg/day paroxetine.
Memantine: In a multiple dose pharmacokinetic study in healthy volunteers (n=15, age range 21-55 years), concurrent administration of memantine at a dose of 10 mg b.i.d. did not affect the pharmacokinetic profile of galantamine (16 mg daily) at steady state.
The safety of co-administering memantine and galantamine in patients with Alzheimer’s disease has not been studied in clinical trials.
Effect of Galantamine on the Metabolism of Other Drugs
In vitro
Galantamine did not inhibit the metabolic pathways catalyzed by CYP1A2, CYP2A6, CYP3A4,
CYP4A, CYP2C, CYP2D6 or CYP2E1. This indicates that the inhibitory potential of galantamine towards the major forms of cytochrome P450 is very low.
In vivo
Warfarin: Galantamine at 12 mg b.i.d. had no effect on the pharmacokinetics of R- and S- warfarin (25 mg single dose) or on the prothrombin time (n=16 males). The protein binding of warfarin was unaffected by galantamine.
Digoxin: Galantamine at 12 mg b.i.d. had no effect on the steady-state pharmacokinetics of digoxin (0.375 mg once daily) when they were co-administered. In this study, however, one healthy subject was hospitalized for second- and third-degree heart block and bradycardia
(n=8 males and 8 females).
Nicotinic Receptor Modulation
Single in vitro applications of galantamine dose-dependently modulate the effect on nicotinic receptors, having a positive allosteric (sensitizing) effect at concentrations below 0.28 mcg/mL (1 mcM) and an inhibitory effect at higher concentrations. Chronic in vitro or in vivo studies on nicotinic receptor modulation have not been conducted.
It is unknown whether galantamine has an effect on the pharmacodynamic action of other drugs that act on cholinergic nicotinic receptors (see 10 CLINICAL PHARMACOLOGY).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Although the etiology of cognitive impairment in Alzheimer’s disease is not fully understood, it has been reported that acetylcholine-producing neurons degenerate in the brains of patients with Alzheimer’s disease. The degree of this cholinergic loss has been correlated with degree of cognitive impairment and density of amyloid plaques (a neuropathological hallmark of Alzheimer’s disease).
Galantamine, a tertiary alkaloid, is a competitive and reversible cholinesterase inhibitor. While the precise mechanism of galantamine’s action is unknown, it is postulated to exert its therapeutic effect by enhancing cholinergic function. This is accomplished by increasing the concentration of acetylcholine through reversible cholinesterase inhibition. It has also been postulated, based on in vitro data, that galantamine enhances the action of acetylcholine through binding to an allosteric site on the nicotinic receptors. The clinical relevance to humans of these in vitro findings is unknown.
If these mechanisms are correct, galantamine’s effect may lessen as the disease process advances and fewer cholinergic neurons remain functionally intact. There is no evidence that galantamine alters the course of the underlying dementing process.
10.2 Pharmacodynamics
Galantamine is a selective, reversible and competitive cholinesterase inhibitor. The predominant pharmacological mechanism of action is the inhibition of acetylcholinesterase. It has been established in in vitro studies, that galantamine has a selectivity for acetylcholinesterase over butyrylcholinesterase.
Overall, the pharmacological effects of galantamine on overt behaviour, and on the gastrointestinal, urinary, cardiovascular, respiratory and central nervous systems can be explained by its anticholinesterase activity.
Single applications of galantamine dose-dependently modulate the effect on nicotinic receptors, having a positive allosteric(sensitizing) effect at concentrations below 0.28 mcg/mL (1 mcM) and an inhibitory effect at higher concentrations. Chronic in vitro or in vivo studies on nicotinic receptor modulation have not been conducted.
Because of its structure, the potential effect of galantamine on opioid receptors has been investigated. Evidence regarding interaction of galantamine with these receptors is inconsistent. Functional tests related to neurotransmitters and neuromodulators revealed that any observed effect is likely to be either a direct or an indirect consequence of the property of galantamine to potentiate cholinergic neurotransmission at sites where acetylcholine is actively released by nerve impulses.
10.3 Pharmacokinetics
The summary of related pharmacokinetic parameters in healthy subjects is presented in Table 5.
Table 5: Pharmacokinetic Parameters of Galantamine after Single or Multiple Dose Administration
Cmax (ng/mL) | Tmax (h) | Css,av (ng/mL) | Cmin (ng/mL) | AUC† (ng.h/mL) | T1/2 (h) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Single dose, 12 healthy males | |||||||||||||||||
| 8 mg, solution p.o. | 42.6 ± 13.1 | 1.2 ± 0.6 | - | - | 427 ±102 | 7.3 ± 1.7 | |||||||||||
| 8 mg, 1 hr IV infusion | - | - | - | - | 482 ±112 | 7.4 ± 1.7 | |||||||||||
| Food effect, single dose, 24 healthy elderly | |||||||||||||||||
| Fasted, 8 mg p.o. | 57.5 ± 15.8 | 1.1 ± 0.5 | - | - | 562 ±180 | 9.7 ± 3.1 | |||||||||||
| Non-fasted, 8 mg p.o. | 42.5 ± 7.5 | 2.6 ±1.4 | - | - | 543 ±176 | 9.7 ± 3.3 | |||||||||||
| Multiple oral dose, 27 healthy males | |||||||||||||||||
| 12 mg b.i.d. tablet | 89.4 ± 18.3 | 1.0 ± 0.6 | 51.9 ± 12.2 | 30.7 ± 10.3 | 623 ± 147 | - | |||||||||||
| 12 mg b.i.d. solution | 87.6 ± 20.5 | 1.1 ± 0.5 | 50.5 ± 13.0 | 29.8 ± 10.2 | 606 ± 156 | - | |||||||||||
| Dose-proportionality, multiple oral dose, 18 healthy subjects | |||||||||||||||||
| 4 mg b.i.d. tablet | 30.7 ± 6.2 | 1.9 ± 0.8 | 17.7 ± 4.6 | 10.6 ± 4.0 | 212 ± 56 | - | |||||||||||
| 8 mg b.i.d. tablet | 63.8 ± 14.2 | 1.7 ± 0.8 | 36.6 ± 9.8 | 20.6 ± 6.8 | 439 ± 117 | - | |||||||||||
| 12 mg b.i.d. tablet | 97.4 ± 31.4 | 1.9 ± 1.1 | 53.1 ± 12.7 | 29.1 ± 9.3 | 637 ± 152 | - | |||||||||||
| 16 mg b.i.d. tablet | 137 ± 36 | 1.7 ± 0.9 | 76.5 ± 20.3 | 41.5 ± 14.2 | 918 ± 244 | 7.9 ± 0.8 | |||||||||||
† AUC = AUC∞ after single dose and AUC = AUCτ after multiple dose
Absorption:
After oral intake of a single 8 mg galantamine solution in 12 healthy males, absorption is rapid, with a peak plasma concentration (Cmax) of 43 ± 13 ng/mL, which is reached after 1.2 hours (Tmax), and a mean AUC∞ of 427 ± 102 ng.h/mL.
The absolute oral bioavailability of galantamine is 88.5%. Bioavailability of the tablet was the same as the bioavailability of an oral solution in 27 healthy males. Food did not affect the AUC of galantamine but Cmax decreased by 25% and Tmax was delayed by 1.5 hours after repeated oral dosing of 12 mg galantamine b.i.d. in 24 healthy elderly subjects.
The maximum inhibition of cholinesterase activity of about 40% was achieved about one hour after a single oral dose of 8 mg galantamine in healthy male subjects.
In a steady-state bioavailability study, galantamine hydrobromide extended release capsules, 24 mg once daily, were shown to be bioequivalent to the 12 mg twice-daily galantamine hydrobromide tablets with respect to AUC24h and Cmin. The Cmax value of the 24 mg once-daily extended release capsule, which is reached after 4.4 hours, was about 24% lower than that of the 12 mg twice-daily tablet. Food had no effect on the steady-state bioavailability of the 24 mg extended release capsules. In a dose-proportionality study of galantamine extended release capsules in healthy elderly and young subjects, steady-state plasma concentrations were achieved within 6 days at all doses (8 mg, 16 mg, and 24 mg) in both age groups. Steady-
state pharmacokinetics were dose-proportional within the studied dose range of 8 mg to 24 mg in both age groups.
Distribution:
Galantamine is a low-clearance drug (plasma clearance of approximately 300 mL/min) with a moderate volume of distribution (average Vdss of 175 L) after a one-hour IV infusion of 8 mg galantamine in 12 healthy males.
The plasma protein binding of galantamine is 18% at therapeutically relevant concentrations. In whole blood, galantamine is mainly distributed to blood cells (52.7%) and plasma water (39.0%), whereas the fraction of galantamine bound to plasma proteins is only 8.4%. The blood- to-plasma concentration ratio of galantamine is 1.2.
Metabolism:
Galantamine is metabolized by hepatic cytochrome P450 enzymes, glucuronidated and excreted unchanged in the urine. In vitro studies indicate that cytochrome CYP2D6 and CYP3A4 are the major cytochrome P450 isoenzymes involved in the metabolism of galantamine, and inhibitors of both pathways increase oral bioavailability of galantamine modestly (see 9.4 Drug- Drug Interactions). O-demethylation, mediated by CYP2D6 is greater in extensive metabolizers of CYP2D6 than in poor metabolizers. In plasma from both poor and extensive metabolizers, however, unchanged galantamine and its glucuronide accounted for most of the sample radioactivity.
Elimination:
The elimination of galantamine is bi-phasic, with a terminal half-life in the order of 7-8 hours in young healthy subjects (n = 4 males). Two studies in healthy elderly subjects indicated that the terminal half-life of galantamine is 8.5 hours (n = 13 males and 16 females) and 9.7 hours (n = 10 males and 14 females) after administering a single oral dose of 10 mg galantamine. Up to 8 hours post-dose, unchanged galantamine accounted for 39-77% of the total radioactivity in the plasma, and galantamine glucuronide accounted for 14-24%. Seven days after a single oral dose of 4 mg 3H-galantamine, 93-99% of the radioactivity had been recovered, with about 95% in urine and about 5% in feces. Total urinary recovery of unchanged galantamine accounted for, on average, 32% of the dose, and that of galantamine glucuronide for another 12% on average.
After IV and oral administration, about 20% of the dose was excreted as unchanged galantamine in the urine in 24 hours, with a renal clearance of about 65 mL/min, which represents 20–25% of the total plasma clearance of about 300 mL/min.
Pharmacokinetics – Nonclinical Studies
The plasma kinetics and tissue distribution of galantamine after single oral administration were studied in rats. After a 2.5 mg/kg oral dose, maximal plasma and brain levels of unchanged galantamine in male rats were approximately 211 ng/mL and 348 ng/g, respectively. In female rats, maximal plasma and brain levels were approximately 348 ng/mL and 491 ng/g, respectively. These studies showed that the brain to plasma Cmax ratio of unchanged galantamine is in the range of 1.4 to 1.6. Tissue concentrations of galantamine declined at a similar rate to corresponding plasma levels. There was no undue retention or accumulation in any tissues.
Special Populations and Conditions
Patients with Alzheimer’s disease: Data from clinical trials in patients indicate that there is a difference in total clearance after oral administration between patients with Alzheimer’s disease and healthy subjects (13.2 L/h versus 19.4 L/h) based on pooled population analysis. Therefore, the plasma concentrations of galantamine in elderly patients (median age 75) with Alzheimer’s disease are 30-40% higher than in healthy young subjects (median age 28).
Sex: No specific pharmacokinetic study was performed to investigate the sex differences. A population pharmacokinetic analysis (n = 539 males and 550 females) suggests that galantamine clearance is about 20% lower in females than in males, which is explained by lower body weight in females.
Race: Pharmacokinetic differences due to race have not been identified in a population pharmacokinetic analysis (n = 1,029 White, 24 Black, 13 Asian and 23 other).
Hepatic Impairment: Following a single 4 mg dose of galantamine, the pharmacokinetics of galantamine in subjects with mild hepatic impairment (n = 8; Child-Pugh score of 5-6) were similar to those in healthy subjects. In patients with moderate hepatic impairment (n = 8; Child-Pugh score of 7-9), AUC and half-life of galantamine were increased by about 30% compared to normal subjects (see 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment and 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Renal Impairment: In patients with renal insufficiency, elimination of galantamine decreases with decreasing creatinine clearance. Following a single 8 mg dose of galantamine, AUC increased by 37% and 67% in moderately (n = 8; creatinine clearance of 30 to
60 mL/min/1.73 m2) and severely (n = 9; creatinine clearance of 5 to 29 mL/min/1.73 m2) renal- impaired patients compared to normal volunteers (n = 8) (see 4.2 Recommended Dose and Dosage Adjustment, Renal Impairment; and 7 WARNINGS AND PRECAUTIONS, Renal).
CYP2D6 Poor Metabolizers: Approximately 7% of the normal population has a genetic variation that leads to reduced levels of activity of the CYP2D6 isozyme. Such individuals have been referred to as poor metabolizers. After a single oral dose of 4 mg or 8 mg galantamine, CYP2D6 poor metabolizers demonstrated a similar Cmax and about 35% AUC∞ increase of unchanged galantamine compared to extensive metabolizers.
A total of 356 patients with Alzheimer’s disease enrolled in two Phase III studies were genotyped with respect to CYP2D6 (n = 210 hetero-extensive metabolizers, 126 homo-extensive metabolizers, and 20 poor metabolizers). Population pharmacokinetic analysis indicated that there was a 25% decrease in median clearance in poor metabolizers compared to extensive metabolizers. Dosage adjustment is not necessary in patients identified as poor metabolizers as the dose of drug is individually titrated to tolerability due to observed inter-patient variability.
11 STORAGE, STABILITY AND DISPOSAL
GALANTAMINE ER extended release capsules should be stored between 15°C and 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Galantamine Hydrobromide
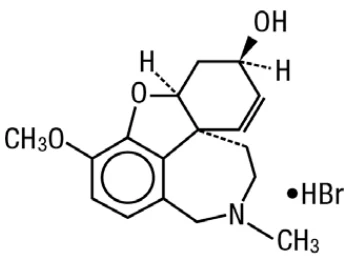
Chemical name: (4aS,6R,8aS)-4a,5,9,10,11,12-hexahydro-3-methoxy-11-methyl-6H-benzofuro[3a,3,2-ef][2]benzazepin-6-ol hydrobromide
Molecular formula and molecular mass: C17H21NO3·HBr, 368.27 g/mol
Structural formula:
Physicochemical properties:
Description: Galantamine hydrobromide is a white to almost white powder.
Solubility: It is freely soluble in water (pH = 5.2), 0.1 N hydrochloric acid (pH = 1.0) and 0.1 N sodium hydroxide (pH = 8.3).
Ionization Constant: pKa = 8.2 (azepine moiety)
Partition Coefficient: log P = 1.09, between n-octanol and an aqueous buffer solution at pH = 12.0
Melting Point: 257.3°C
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Efficacy data for galantamine hydrobromide tablets in the symptomatic treatment of patients with Alzheimer’s disease were derived from 4 randomized, double-blind, placebo-controlled clinical trials in patients with probable Alzheimer’s disease [diagnosed by NINCDS-ADRDA criteria, with Mini-Mental State Examination Scores that were ≥ 10 and ≤24]. Doses studied were 8-32 mg/day given as twice daily doses. In 3 of the 4 studies, patients were started on a low dose of 8 mg, then titrated weekly by 8 mg/day to 24 or 32 mg as assigned (GAL-USA-1,
GAL-INT-1, GAL-INT-2). In the fourth study (U.S. 4-week Dose-Escalation Fixed-Dose Study, GAL- USA-10) dose escalation of 8 mg/day occurred over 4-week intervals. The mean age of patients participating in the 4 trials of galantamine hydrobromide tablets was 75 years with a range of 41 to 100. Approximately 62% of patients were women and 38% were men. The racial distribution was White 94%, Black 3% and other races 3%. Two other studies examined a three times daily dosing regimen; these also showed or suggested benefit but did not suggest an advantage over twice daily dosing.
The data shown in section 14.2 Study Results were obtained from the Intent-To-Treat population (ITT analysis, i.e. all patients who were randomized to treatment, regardless of whether or not they were able to complete the study. For patients unable to complete the study, their last observation while on treatment was carried forward and used at endpoint).
U.S. Twenty-One-Week Fixed-Dose Study (GAL-USA-10)
In a study of twenty-one weeks’ duration, 978 patients were randomized to doses of 8, 16, or 24 mg of galantamine per day, or to placebo, each given in 2 divided doses. Treatment was initiated at 8 mg/day for all patients randomized to galantamine, and increased by 8 mg/day every 4 weeks. Therefore, the maximum dose-escalation phase was 8 weeks and the minimum maintenance phase was 13 weeks (in patients randomized to 24 mg/day of galantamine).
U.S. Twenty-Six-Week Fixed-Dose Study (GAL-USA-1)
In a study of 26 weeks’ duration, 636 patients were randomized to either a dose of 24 mg or 32 mg of galantamine per day, or to placebo, each given in two divided doses. The 26-week study was divided into a 3-week dose-escalation phase and a 23-week maintenance phase.
Study Outcome Measures: In GAL-USA-10 and GAL-USA-1, the primary efficacy of galantamine hydrobromide tablets was evaluated using a dual outcome assessment strategy as measured by the Alzheimer’s disease Assessment Scale (ADAS-cog) and the Clinician’s Interview Based Impression of Change (CIBIC-plus).
The ability of galantamine hydrobromide tablets to improve cognitive performance was assessed with the cognitive sub-scale of the Alzheimer’s disease Assessment Scale (ADAS-cog), a multi-item instrument that has been extensively validated in longitudinal cohorts of Alzheimer’s disease patients. The ADAS-cog examines selected aspects of cognitive performance including elements of memory, orientation, attention, reasoning, language , and praxis.
The patients recruited as participants in GAL-USA-10 and GAL-USA-1 had mean scores on the ADAS-cog of approximately 27 units, with a range from 5 to 69. Experience gained in longitudinal studies of ambulatory patients with mild to moderate Alzheimer’s disease suggests that they gain 6 to 12 units a year on the ADAS-cog. Lesser degrees of change, however, are seen in patients with very mild or very advanced disease because the ADAS-cog is not uniformly sensitive to change over the course of the disease. The annualized rate of decline in the placebo patients participating in galantamine trials was approximately 4.5 units per year.
The ability of galantamine hydrobromide tablets to produce an overall clinical effect was assessed using a Clinician’s Interview Based Impression of Change that required the use of caregiver information, the CIBIC-plus. The CIBIC-plus used in the trials was a semi-structured instrument based on a comprehensive evaluation at baseline and subsequent time -points of 4 major areas of patient function: general, cognitive, behavioural and activities of daily living.
Clinical trials for investigational drugs have used a variety of CIBIC formats, each different in terms of depth and structure. As such, results from a CIBIC-plus reflect clinical experience from the trial or trials in which it was used and cannot be compared directly with the results of CIBIC- plus evaluations from other clinical trials.
Among the secondary measures of efficacy, the Alzheimer’s disease Cooperative Study, Activities of Daily Living Inventory (ADCS/ADL) was used. The ADCS/ADL is a caregiver-rated evaluation, which yields a compound score derived from a categorical scale of 23 items concerning participation in activities of daily living.
Extended Release Capsules (Study GAL-INT-10)
The efficacy of galantamine hydrobromide extended release capsules was studied in a randomized, double-blind, placebo-controlled trial using a 4-week dose escalation, flexible dosing regimen of 16 or 24 mg/day for a treatment duration of 6 months. Galantamine hydrobromide immediate release tablets served as an active control arm in this study. Primary efficacy endpoints in this study were ADAS-cog/11 and CIBIC-plus.
14.2 Study Results
U.S. Twenty-One-Week Fixed-Dose Study (GAL-USA-10)
Effects on the ADAS-cog
Figure 1 illustrates the time course for the change from baseline in ADAS-cog scores for all four dose groups over the 21 weeks of the study. At 21 weeks of treatment, the mean differences in the ADAS-cog change scores for the galantamine-treated patients compared to the patients on placebo were 0.8, 2.9 and 2.9 units for the 8, 16 and 24 mg/day treatments, respectively. The 16 mg/day and 24 mg/day treatments were statistically significantly superior to placebo and to
the 8 mg/day treatment. There was no statistically significant difference between the 16 mg/day and 24 mg/day dose groups.
Figure 1: Time-course of the Changes from Baseline in ADAS-cog Score (ITT Population)
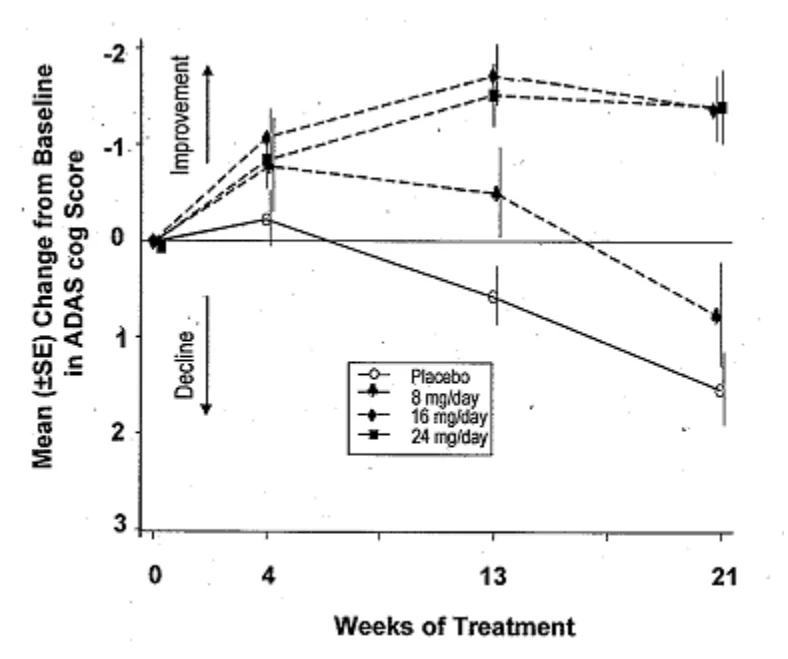
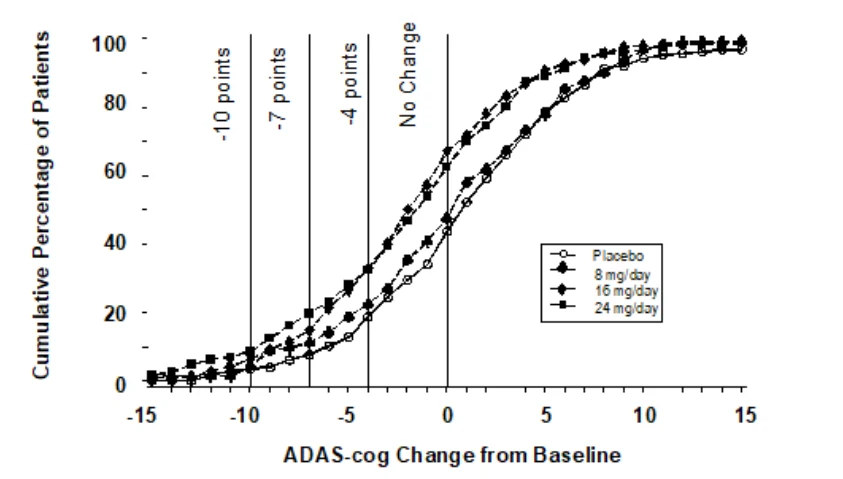
Figure 2 illustrates the cumulative percentages of patients from each of the four treatment groups who had attained at least the measure of improvement in ADAS-cog score shown on the X-axis. Three change scores (10-point, 7-point and 4-point reductions) and no change in score from baseline have been identified for illustrative purposes, and the percent of patients in each group achieving that result is shown in the inset table.
The curves demonstrate that both patients assigned to galantamine hydrobromide tablets and placebo have a wide range of responses, but that the galantamine hydrobromide groups are more likely to show the greater improvements.
Figure 2: Cumulative Percentage of Patients with Specified Changes from Baseline in ADAS-cog Scores (ITT Population)
| Change in ADAS-cog | ||||
| Treatment | -10 | -7 | -4 | 0 |
| Placebo | 3.7% | 7.8% | 19.0% | 43.9% |
| 8 mg/day | 4.5% | 11.4% | 22.7% | 47.7% |
| 16 mg/day | 6.4% | 15.0% | 33.1% | 67.3% |
| 24 mg/day | 8.8% | 19.8% | 32.4% | 62.6% |
Effects on the CIBIC-plus
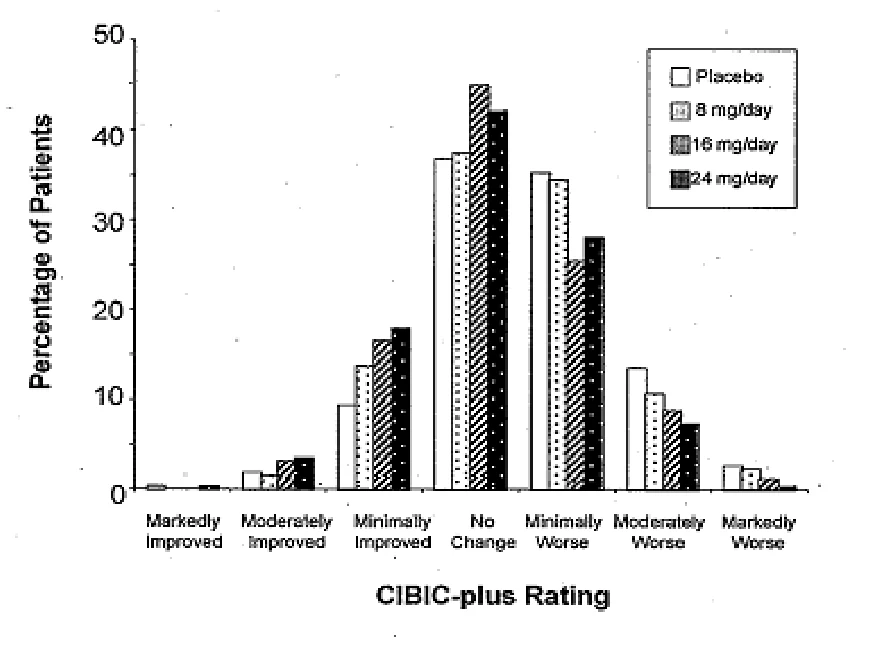
Figure 3 is a histogram of the percentage distribution of CIBIC-plus scores attained by patients assigned to each of the four treatment groups. The galantamine-placebo differences for these groups of patients in the mean rating were 0.10, 0.32 and 0.38 units for the 8, 16 and 24 mg/day treatments, respectively. The 16 mg/day and 24 mg/day treatments were statistically significantly superior to placebo. The differences vs. the 8 mg/day treatment for the 16 and 24 mg/day treatments were 0.22 and 0.28, respectively. There were no statistically significant differences between the 16 mg/day and 24 mg/day dose groups.
Figure 3: Distribution of CIBIC-plus Ratings at Week 21 (ITT Population)
Effects on ADCS/ADL Inventory
The Alzheimer’s disease Cooperative Study, Activities of Daily Living Inventory was used as a secondary efficacy measure. At baseline, mean ADCS/ADL scores (mean ± SE) were for the placebo group: 52.3 ± 0.89 units; for the 16 mg/day group: 51.6 ± 0.93 units; for the 24 mg/day group: 51.9 ± 0.98 units. At Week 21, the placebo group declined an average of 3.9 ± 0.55 units, and the 16 mg/day and 24 mg/day groups deteriorated minimally at 1.0 ± 0.51 units and
1.6 ± 0.56 units, respectively. The difference between the placebo group and the galantamine treatment groups (16 mg/day or 24 mg/day) was statistically significant.
U.S. Twenty-Six-Week Fixed-Dose Study (GAL-USA-1)
Effects on the ADAS-cog
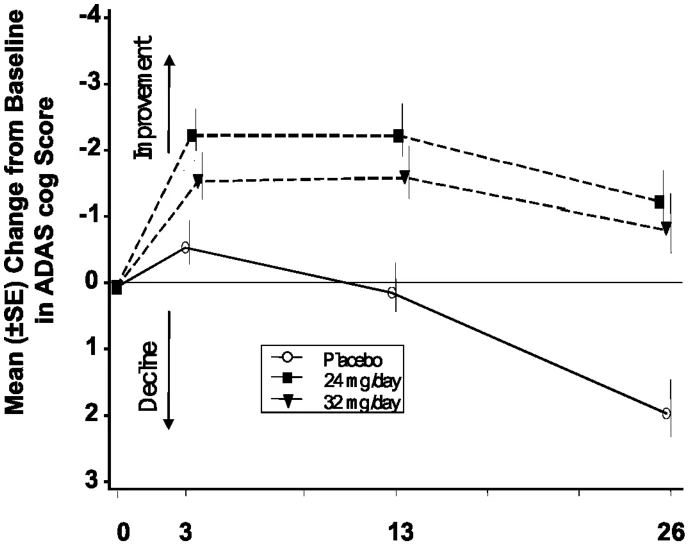
Figure 4 illustrates the time course for the change from baseline in ADAS-cog score for all three dose groups over the 26 weeks of the study. At 26 weeks of treatment, the mean difference in the ADAS-cog change scores for the galantamine-treated patients compared to the patients on placebo were 3.2 and 2.8 units for the 24 mg/day and 32 mg/day treatments, respectively. Both treatments were statistically significantly superior to placebo, but were not statistically significantly different from each other.
Figure 4: Time-course of the Changes from Baseline in ADAS-cog Score (ITT Population)
Weeks of Treatment
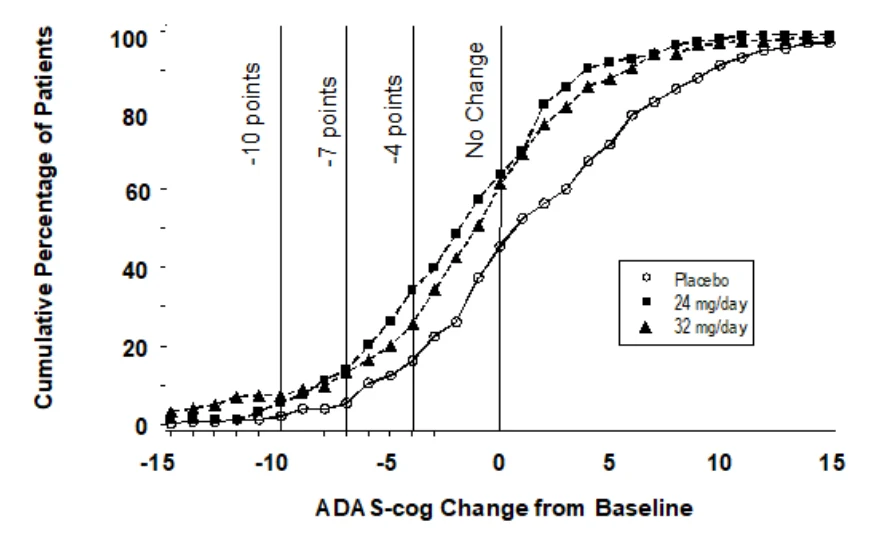
Figure 5 illustrates the cumulative percentages of patients from each of the three treatment groups who had attained at least the measure of improvement in ADAS-cog score shown on the X-axis. Three change scores (10-point, 7-point and 4-point reductions) and no change in score from baseline have been identified for illustrative purposes, and the percent of patients in each group achieving that result is shown in the inset table.
The curves demonstrate that both patients assigned to galantamine hydrobromide tablets and placebo have a wide range of responses, but that the galantamine groups are more likely to show the greater improvements. Curve for an effective treatment would be shifted to the left of the curve for placebo, while an ineffective or deleterious treatment would be superimposed upon, or shifted to the right of the curve for placebo, respectively.
Figure 5: Cumulative Percentage of Patients with Specified Changes from Baseline in ADAS-cog Scores (ITT Population)
| Change in ADAS-cog | ||||
| Treatment | -10 | -7 | -4 | 0 |
| Placebo | 2.3% | 5.6% | 16.4% | 45.5% |
| 24 mg/day | 5.8% | 14.0% | 34.3% | 63.8% |
| 32 mg/day | 7.7% | 13.4% | 25.8% | 61.2% |
Effects on the CIBIC-plus
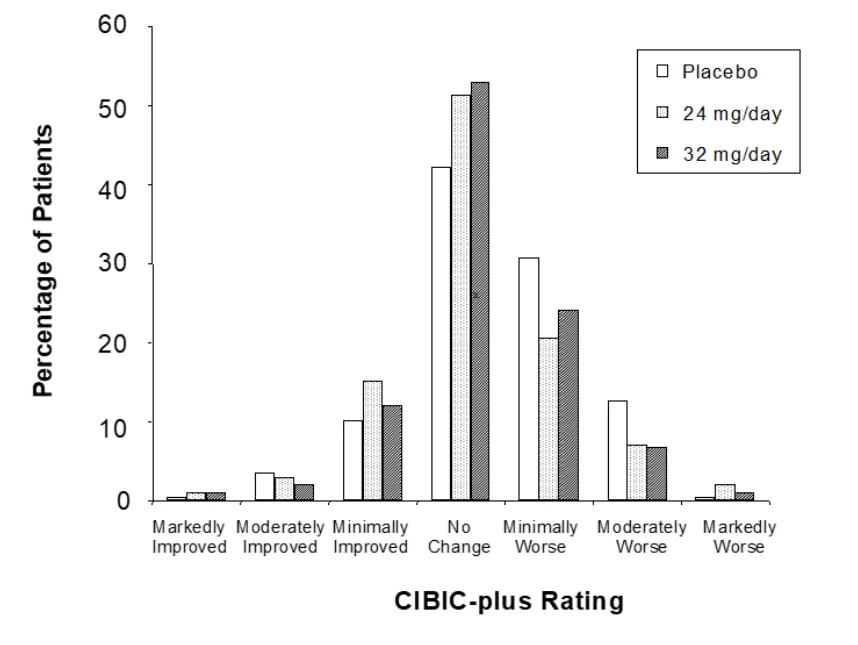
Figure 6 is a histogram of the percentage distribution of CIBIC-plus scores attained by patients assigned to each of the three treatment groups. The mean galantamine -placebo differences for these groups of patients in the mean rating were 0.22 and 0.17 units for 24 and 32 mg/day of galantamine, respectively. The mean ratings for both groups were statistically significantly superior to placebo, but were not significantly different from each other.
Figure 6: Distribution of CIBIC-plus Ratings Week 26 (ITT Population)
Age, gender and race
Patient’s age, gender or race did not predict outcome of treatment.
Extended Release Capsules (Study GAL-INT-10)
At Month 6, galantamine hydrobromide extended release capsules showed a statistically significant improvement over placebo for ADAS-cog/11 but not for CIBIC-Plus. Galantamine hydrobromide extended release capsules were statistically significantly better than placebo on the Alzheimer’s disease Cooperative Study-Activities of Daily Living scale (ADCS-ADL), a secondary efficacy endpoint. Similar efficacy results were obtained for the galantamine hydrobromide immediate release treatment arm of this study.
14.3 Comparative Bioavailability Studies
A blinded, randomized, balanced, two-sequence, two-treatment, two-period, crossover, single dose, bioequivalence study of GALANTAMINE ER capsules (galantamine hydrobromide) 8 mg of Pro Doc Ltée, with PrREMINYL ER® capsules (galantamine hydrobromide) 8 mg of Janssen-Ortho Inc., Toronto, Canada, in normal, healthy, adult, male human subjects under fasting conditions (n=18).
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Galantamine (1 x 8 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-t (ng.h/mL) | 387.0 (396.23 - 21.89%) | 407.2 (414.58 -18.78%) | 95.04 | 89.89 – 100.48 |
Cmax (ng/mL) | 20.8 (20.97 - 13.23%) | 21.8 (21.97 - 11.02%) | 95.26 | 90.47 – 100.31 |
AUC0-inf (ng.h/mL) | 430.6 (443.85 - 24.86%) | 456.0 (467.35 - 22.48%) | 94.45 | 89.63 – 99.51 |
Tmax§ (h) | 4.50 (1.00 - 10.00) | 4.50 (4.00 - 10.00) | ||
*GALANTAMINE ER 8 mg Capsules (Pro Doc Ltée)
† REMINYL ER® 8 mg Capsules (Janssen-Ortho Inc.), were purchased in Canada.
§ Expressed as the median (range) only.
A blinded, randomized, balanced, two-sequence, two-treatment, two-period, crossover, single dose, bioequivalence study of GALANTAMINE ER capsules (galantamine hydrobromide) 8 mg of Pro Doc Ltée, with PrREMINYL ER® capsules (galantamine hydrobromide) 8 mg of Janssen-Ortho Inc., Toronto, Canada, in normal, healthy, adult, male human subjects under fed conditions (n=18).
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Galantamine (1 x 8 mg) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-t (ng.h/mL) | 370.4 373.55 (13.37%) | 410.6 413.74 (12.45%) | 90.19 | 87.24 – 93.25 |
Cmax (ng/mL) | 22.2 22.37 (12.99%) | 26.9 27.08 (11.48%) | 82.49 | 78.97 – 86.18 |
AUC0-inf (ng.h/mL) | 403.5 407.43 (14.16%) | 433.5 437.20 (13.16%) | 93.08 | 89.55 – 96.75 |
Tmax§ (h) | 4.50 (3.5 - 10.00) | 6.25 (4.5 - 10.00) | ||
*GALANTAMINE ER 8 mg Capsules (Pro Doc Ltée)
† REMINYL ER® 8 mg Capsules (Janssen-Ortho Inc), were purchased in Canada.
§ Expressed as the median (range) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
The potential toxicity of galantamine has been evaluated in acute, sub-chronic, chronic, carcinogenicity, mutagenicity, and reproduction studies.
Acute (Single Dose) Toxicity
The acute toxicity of galantamine was studied following oral and intravenous administration to adult mice, rats and dogs. A summary of the acute toxicity studies is presented in Table 6.
Oral single doses with galantamine up to 36 mg/kg (mice), 40 mg/kg (rats) and 8 mg/kg (dogs) were given to laboratory animals. Mortality was noted in mice at 36 mg/kg and in rats from 36 mg/kg onwards. All dogs survived the study.
Intravenous single escalation doses up to 10 mg/kg in rats and dogs did not lead to mortality. In both oral and intravenous studies, clinical effects mainly involved the gastrointestinal and central nervous systems.
Additional studies were conducted to compare the acute toxicity of batches of different sources and that of norgalantamine, the major impurity. The comparative single-dose studies indicate that there is no relevant difference in the acute toxicity profile between both galantamine batches, while norgalantamine showed a similar, but less pronounced, toxicity profile.
Table 6: Acute (Single-Dose) Toxicity Studies with Galantamine
Species/ Strain | Route of Administration | # Animals/ Group | Dosesa (mg/kg/day) | LD50 (mg/kg) | Summary of Toxic Signs |
|---|---|---|---|---|---|
| Mouse | oral (gavage) | 2 or 5/sex/grp | 1.6, 4, 12, 36 | 15 < LD50 < 45 | 4 mg/kg = hypoactivity was observed. 12 mg/kg = additional signs of tremors, salivation, perineal staining and lacrimation. 36 mg/kg = surviving M of grp, exhibited tremors and the F showed similar signs to those observed at 12 mg/kg; 4/5 M and F died within 30 minutes post dosing. Prior to death most animals exhibited tremors, salivation and clonic convulsions. No mortality occurred up to 12 mg/kg. The majority of signs were considered exaggerated pharmacologic responses. |
| Mouse | oral (gavage) oral (gavage) | 2/sex/grp 5/sex/grp | 4, 8, 12, 16, 20, 25b 20, 20, 28c | not determined | 16 mg/kg gal (0.8%) = 1M death. Up to 20 mg/kg all remaining mice survived. At all dose levels: piloerection, hypoactivity, a hunched posture, tremors, excessive salivation and a white periorbital secretion were seen. All mice receiving up to 20 mg/kg of gal (2.0%) survived treatment. At all dose levels: piloerection, a hunched posture, hypoactivity, tremors and excessive salivation (noted in M) were seen. All mice receiving up to 20 mg/kg of norgal survived. In all M receiving 8 mg/kg or greater: piloerection, a hunched posture, hypoactivity, tremors and excessive salivation were seen. One F receiving 12 mg/kg: hunched posture. 20 mg/kg gal (0.8% & 2.0%) = death (1/5) F and 1M & 1F, respectively. Tremors were noted in those 3 animals prior to |
Species/ Strain | Route of Administration | # Animals/ Group | Dosesa (mg/kg/day) | LD50 (mg/kg) | Summary of Toxic Signs | |
|---|---|---|---|---|---|---|
| death. Gal (0.8% & 2.0%) resulted in tremors, hypoactivity and fur staining, which lasted up to 4 (0.8%) or 24 hrs (2.0%) after dosing in the surviving mice. All mice with norgalantamine survived the study. Tremors and hypoactivity were seen in animals when treated with norgal. Four hours after dosing, all animals appeared clinically normal. | ||||||
| Mouse | IV (bolus) single IV (bolus) | 2/sex/grp 5/sex/grp | 1.6, 3.2, 4.8, 6.4, 8 4.8, 4.8, 12c | not determined | 1-week study: 6.4 mg/kg gal (0.8%) = two M deaths. 8 mg/kg gal (0.8%) = all mice died. 6.4 mg/kg gal (2.0%) = one M death. 8 mg/kg gal (2.0%) = one M death. Gal (0.8%) (clinical) = tremors and/or hypoactivity in F from 3.2 mg/kg onwards and in M from 4.8 mg/kg onwards. Gal (2.0%) = tremors and hypoactivity in most F receiving 3.2 mg/kg or greater. The majority of M receiving 4.8 mg/kg or greater were observed with tremors, hypoactivity, laboured respiration. Norgalantamine up to 8 mg/kg did not lead to mortality or any clinical signs of toxicity. 2-week study: Tremors, hypoactivity. | |
| Rat | oral (gavage) | 5/sex/grp | 0.4, 1.6, 8, 40 | 50 | Up to 8 mg/kg, all rats survived. 40 mg/kg = 1/5 (M & F) died within 5 hours after dosing; severe clinical signs of tremor, salivation, clonic convulsions, dyspnea, chromodacryorrhea, perineal staining, reduced amount of feces or stained furs up to Day 4. 8 mg/kg = tremors, perineal staining and mucoid feces on day of dosing. | |
| Rat | oral (gavage) | 2 or 5/sex/grp | 1.6, 4, 12, 36 | > 45 | All rats, except one F of the 36 mg/kg dosage grp, survived the study. 4 and 12 mg/kg = tremors in females within 1 hr after dosing. 36 mg/kg = tremors, chromodacryorrhea, lacrimation, salivation, perineal staining and soft or mucoid feces on day of dosing in both sexes. Perineal staining persisted through Day 1. | |
Species/ Strain | Route of Administration | # Animals/ Group | Dosesa (mg/kg/day) | LD50 (mg/kg) | Summary of Toxic Signs |
|---|---|---|---|---|---|
| Rat | oral (gavage) oral (gavage) | 2/sex/grp 5/sex/grp | 4, 8, 12, 16, 20b 24, 24, 32c | not determined | Up to 20 mg/kg gal (0.8% & 2.0%) all rats survived. Gal 0.8% at all dose levels and gal 2.0% at 12 mg/kg or greater: tremors and hypoactivity were seen. All rats receiving up to 20 mg/kg of norgal remained clinically unremarkable. 24 mg/kg gal (0.8%) = tremors. 24 mg/kg gal (2.0%) = tremors, hypoactivity and fur staining. 32 mg/kg (norgal) = tremors, hypoactivity, fur staining. Animals without fur staining were back to normal 4 hours after dosing, and those with fur staining 24 hours after dosing. |
| Rat | IV (bolus) IV (bolus) | 2/sex/grp 5/sex/grp | 3.2, 8, 12, 20, 32b,d 3.2, 3.2, 9.6c | not determined | 4.8 mg/kg (0.8%) = 1M death. 6.4 mg/kg (0.8%) = 2M + 1F deaths. 8 mg/kg (0.8%) = 2M + 2F deaths. All M receiving 4.8 mg/kg or greater, and F receiving 6.4 displayed tremors, hypoactivity and piloerection. 3.2 mg/kg (2.0%) = 1M death. 8 mg/kg (2.0%) = 2M + 2F deaths. Surviving M receiving 3.2 mg/kg was hypoactive after dosing. 12 mg/kg (norgal) = 1 death. 20 mg/kg (norgal) = 2M deaths. 32 mg/kg (norgal) = 1M + 2F deaths. Tremors were noted prior to death. Rats receiving 12 mg/kg or greater: hypoactivity, piloerection, excessive salivation and laboured respiration were seen. 3.2 mg/kg gal (0.8 and 2.0%) = tremors and hypoactivity which disappeared 2 hours after dosing. 9.6 mg/kg (norgal) = death of 1 M, tremors and hypoactivity. |
Species/ Strain | Route of Administration | # Animals/ Group | Dosesa (mg/kg/day) | LD50 (mg/kg) | Summary of Toxic Signs |
|---|---|---|---|---|---|
| Rat | IV (bolus) | 1 or 2/sex/grp | 2.5, 3.75, 5, 10 | not determined | 3.75 mg/kg tremors (M and F). 5 mg/kg = tremors; death (2M). 10 mg/kg = 1M/1F died within 2 minutes after dosing. |
| Rat | IV (inf. 20 min) | 6M + 6F | 2.5, 5, 10 | not determined | 2.5 and 5 mg/kg = slight tremors during infusion period 10 mg/kg = slight sedations and moderate tremors (M and F) |
| Rat | IV (inf. 1 hr) | 15M + 15F | 1.25-5; 2.5-10 | not determined | 10 mg/kg = tremors |
| Dog | oral (capsules) | 3M + 3F | 0.8, 4, 8 | not determined | 4 mg/kg = moderate fecal changes (mucoid and/or soft feces) and salivation 8 mg/kg = emesis with apparent compound, soft mucoid feces and body tremors |
| Dog | IV (inf. 15 min) | 1M + 1F | 2.5-5 | not determined | 2.5 mg/kg = slight to moderate tremors 5 mg/kg = severe tremors, respiratory difficulties, coughing and immediate expulsion of soft feces, ↑ systolic blood pressure |
| Dog | IV (inf. 1 hr) | 4M + 4F | 0.63-5, 2.5-10 | not determined | 2.5 mg/kg = slight salivation in 1/4 dogs. 5 mg/kg = slight to moderate tremors, slightly ↑ systolic blood pressure; occasional dyspnea. 10 mg/kg = moderate to severe tremors accompanied by dyspnea and salivation in most dogs; immediate expulsion of soft feces in 1 dog and vomiting in another dog. Hematocrit and hemoglobin as well as systolic and diastolic blood pressure were slightly ↑. |
- a. Galantamine base equivalents.
- b. Dose-range-finding study.
- c. Doses are listed as galantamine (0.8% impurities), galantamine (2% impurities) and norgalantamine, respectively.
- d. As a result of unexpected mortality at 8 mg/kg, the original doses for galantamine (0.8%) and galantamine (2.0%) were amended to 1.6, 3.2, 6.4 and 8 mg/kg and 0.8, 1.6, 2.4, 3.2 and 8 mg/kg, respectively.
Sub-Chronic (Repeated-Dose) Toxicity
Subchronic (1-month) and chronic (6- to 12-month) studies were performed in rats and dogs. In the two species, the dose of 1.6 mg/kg was considered non-toxic in the 6- to 12-month studies. Most of the effects observed were related to an exaggerated pharmacological action of galantamine and were general manifestations of cholinergic stimulation.
An overview of the repeated dose toxicity studies is given in Table 7.
Table 7: Sub-Chronic (Repeated-Dose) Toxicity Studies with Galantamine
Species, Age No./Sex/Grp | Route, Dosea (mg/kg/day), Duration | Results |
|---|---|---|
Rat 4 wks. old 10/sex/grp | oral (gavage) 0, 0.8, 4→12, 8 28 days | All animals survived the study. There were no adverse clinical effects nor any effects on body weight and food consumption. Hematology, serum and urine analysis revealed comparable findings between groups. No macroscopic or histological changes were observed at any dose. It has to be noted that the results of this study are not in line with all other repeated dose toxicity studies which revealed clinical signs related to cholinergic stimulation. |
Rat 8 wks. old 5/sex/grp | oral (gavage) 0, 4, 8, 16, 24 4 wks. | All animals survived the study. Treatment related clinical signs occurred at all doses and were predominantly indicative of effects on the central nervous system. They included twitching, fasciculations, frequent urination and salivation (M) at all doses. > 8 mg/kg = lacrimation; salivation. > 16 mg/kg = tremors. 24 mg/kg = spasms (F) and hypoactivity; salivation. Most of the effects were considered to be the result of an exaggerated pharmacological response. Other clinical signs (fecal changes, chromorhinorrhea, chromodacryorrhea, wet perineal staining, wet ventral surface and hunched posture) were considered to be slight to marked in nature. No galantamine-related effects were noted on laboratory parameters. Gross and histopathology revealed no adverse effects. |
Rat 8 wks. old 5/sex/grp | oral (gavage) 0, 28, 32, 36 4 wks. | No mortality occurred during the study. Water consumption, hematology, serum and urine analysis revealed no adverse effects. No macroscopic or histological changes related to galantamine were present at any dosage. Tremors were noted in all treated animals. After two weeks of dosing, fasciculations occurred in all treated animals and continued throughout the dosing period. Due to the nature of the compound, the CNS effects were considered to be the result of an exaggerated pharmacological response. > 32 mg/kg (M) = slight ↓ in food consumption. Slight ↓ in body weight and weight gain at all doses. |
Rat 6 wks. old 15/sex/grp | oral (gavage) 0, 1.6, 8, 16, 32 6 months | After 6 months of dosing, galantamine was well tolerated up to 32 mg/kg. No treatment-related mortality occurred during the initial 6 months of the study. 1.6 mg/kg = no adverse effects, except for a slight ↓ in serum calcium in M and slight ↓ in potassium and globulin in F. 8 mg/kg = clinical signs typical of cholinesterase inhibition occurred (abnormal behaviour, chromodacryorrhea, |
Species, Age No./Sex/Grp | Route, Dosea (mg/kg/day), Duration | Results | ||
|---|---|---|---|---|
chromorhinorrhea, lacrimation, perineal staining, salivation, tremors, twitching and polyuria) generally appeared within 2 hours after dosing. No ocular changes were seen. Body weight gain was slightly ↓ in F only. Hematology and urine analysis revealed no effects. Some serum parameters showed changes: albumin in M and glucose in F were ↑ and calcium, globulin and potassium were ↓ in both M and F. The weights of the salivary glands were ↑, which was histologically identified as acinar cell hypertrophy in the mandibular salivary gland in F. These effects were also present at 16 and 32 mg/kg, but more pronounced and in both sexes. Lacrimation, as well as a ↓ in serum phosphorus, were present in M at 16 mg/kg and in M and F at 32 mg/kg. | ||||
Rat 6 wks. old 15/sex/grp and 10/sex/grp further studied for 14 days | oral (gavage) 0, 1.6, 8, 16, 32 12 months | After 12 months of dosing, results were very similar to those observed after 6 months. Toxicity was further evidenced by ↑ mortality, especially in F at 32 mg/kg. There were no specific test-article-related morphologic lesions in these animals. > 8 mg/kg = slight ↓in white blood cells and lymphocytes. 8, 16 and 32 mg/kg = histological changes in lungs (↑ presence of foamy macrophages). Most changes were at least partially reversible after a four-week recovery period. The acinar hypertrophy of the salivary glands, occurring in both sexes at the 6- and 12-month interval was no longer evident following the recovery period. | ||
Dog 15-19 wks. old 3M + 3 F 1M + 1F | oral (capsule) phase 1: 1.6 ➔12.8 phase 2: 4 ➔12 MTD and 14 days | No clinical effects were observed in M and F dosed up to 8 mg/kg in phase 1. During phase 2, administration of 4.8 and 3.2 mg/kg was associated with shaking, coughing and isolated incidences of vomiting, noted in both the M and F dog. 9.6 mg/kg repeat administration (phase 2) = abnormal behaviour and impaired balance in M on the first two days of dose administration only. Vasodilatation, coughing and shaking noted in both animals throughout phase 2; in addition, isolated incidences of vomiting were also noted in the F dog. Similar clinical signs were noted at this dose level when administered during phase 1 (Days 12 and 15). | ||
Species, Age No./Sex/Grp | Route, Dosea (mg/kg/day), Duration | Results | ||
|---|---|---|---|---|
| 12.8 mg/kg phase 1 (Day 11 only) = vasodilatation, shaking, coughing and abnormal behaviour, the F was noted to have general pallor and laboured respiration. Minimal to slight myodegeneration in the muscle wall of the urinary bladder and the duodenum of phase 1 animals, and in the urinary bladder and the stomach of phase 2 animals was noted. | ||||
Dog 18-24 wks. old 3/sex/grp | oral (capsule) 0, 0.8, 3.2, 9.6 4 wks. | All animals survived the study. No treatment-related effects were noted on body weight, food consumption, ophthalmologic observations, hematology, serum analysis, urinalysis, organ weights or gross pathology. 0.8 mg/kg = slight vasodilatation in both sexes, on the first day of dosing only. 3.2 mg/kg = vasodilatation, shaking, lip licking, vomiting and coughing in M and F dogs. Loose/liquid feces and sporadic abnormal behaviour were seen in F; severity and frequency of these clinical signs ↓ during the first two weeks of treatment, except for coughing, which was still present after 2 weeks 9.6 mg/kg = same clinical reactions as noted in animals receiving 3.2 mg/kg; greater persistence for the duration of treatment but the severity ↓ over the treatment period. More severe clinical signs, such as impaired balance, abnormal behaviour, excessive salivation and laboured breathing, were noted on the first few days of dose administration. Panting was observed in M dogs from day 9 onwards. Histological examination revealed myodegeneration in the muscle wall of the urinary bladder in M and F receiving 3.2 and 9.6 mg/kg. One male receiving 9.6 mg/kg was found to have chronic inflammation in the muscle wall of the stomach. The severity of the clinical signs noted on the first day of dosing in dogs receiving 9.6 mg/kg excluded the use of a higher dose in subsequent longer-term toxicity studies. | ||
Dog 7-8 months 1 or 2/sex/grp | oral (capsule) 0, 0.8, 4, 8 4 wks. | All animals survived the dosing period. No effects on body weight, food consumption, auditory and eye examination, ECG, blood-, serum- and urine-variables were observed. Treatment-related changes were limited to clinical signs indicative of central nervous system effects, as a result of an exaggerated pharmacological response, and gastrointestinal effects. 0.8 mg/kg = no toxic- effect dose. 4 mg/kg = salivation in both sexes, hyperpnea in F and mucoid and/or soft feces as well as emesis in one or both sexes. 8 mg/kg = same effects as in the previous (4 mg/kg) group; ataxia, diarrhea, hyperactivity and tremors seen in both sexes whereas emesis (with apparent compound | ||
Species, Age No./Sex/Grp | Route, Dosea (mg/kg/day), Duration | Results | ||
|---|---|---|---|---|
| and/or food), bloody feces and hyperpnea were noted in M. Histological examination revealed no galantamine-related effects, except in 1 M dog dosed at 8 mg/kg, which manifested mild focal atrophy of the urinary bladder muscularis characterized by a small area of shrunken muscle fibers. | ||||
Dog 7-9 months 4/sex/grp | oral (capsule) 0, 1.6, 4, 8 6 months and 12 months | After 6 months: No treatment-related mortality present. All doses = clinical signs consistent with the exaggerated pharmacological action of galantamine noted (cholinergic stimulation, including ataxia, fasciculations, hyperactivity, lacrimation, salivation, tremors, urinary incontinence and gastrointestinal tract disturbances such as emesis and fecal changes). No effects were observed on ECG, heart rate, haematology or urinalysis at any dose. 1.6 mg/kg = no toxic effects. 4 mg/kg = ↓in serum calcium and phosphorus in F. 8 mg/kg = transient ↓in body weight gain in M, ↓serum calcium and phosphorus levels in M and F dogs and a slightly ↓ liver weight in F. Histological examination revealed focal degeneration of the urinary bladder smooth muscle. After 12 months: Similar effects to those obtained after 6 months of dosing. Gross and histological examination additionally revealed evidence of uterine pseudopregnancy and endometrial hyperplasia, associated with an ↑ in the number of ovarian corpora lutea. 4 mg/kg = ↑ uterine weight in one female. 8 mg/kg = ↑ uterine weight in two females. All effects, except for those on the F reproductive tract, were reversible after one month of recovery. | ||
- a) Galantamine in base-mg base equivalents/kg body weight.
MTD: Maximum Tolerated Dose.
Carcinogenicity
In a 24-month oral carcinogenicity study in rats, a slight increase in endometrial adenocarcinomas was observed at 10 mg/kg/day (4 times the Maximum Recommended Human Dose [MRHD] on a mg/m2 basis or 6 times on an exposure [AUC] basis) and 30 mg/kg/day (12 times the MRHD on a mg/m2 basis or 19 times on an AUC basis). No increase in neoplastic changes was observed in females at 2.5 mg/kg/day (equivalent to the MRHD on a mg/m2 basis or 2 times on an AUC basis) or in males up to the highest dose tested of 30 mg/kg/day (12 times the MRHD on a mg/m2 and AUC basis.)
Galantamine was not carcinogenic in a 6-month oral carcinogenicity study in transgenic (P 53- deficient) mice up to 20 mg/kg/day, or in a 24-month oral carcinogenicity study in male and female mice up to 10 mg/kg/day (2 times the MRHD on a mg/m2 basis and equivalent on an AUC basis).
Mutagenicity
Galantamine was investigated for its potential to induce point and/or gene mutations and chromosome aberrations in in vitro and in vivo tests systems. In addition, mutagenicity studies were conducted with norgalantamine, the major impurity. The results of the mutagenicity studies indicate that galantamine as well as norgalantamine have no mutagenic potential.
Galantamine produced no evidence of genotoxic potential when evaluated in the in vitro Ames
S. typhimurium or E. coli reverse mutation assay, in vitro mouse lymphoma assay, in vivo micronucleus test in mice, or in vitro chromosome aberration assay in Chinese hamster ovary cells.
The results of these studies are presented in detail in Table 8
Table 8: Mutagenicity Studies with Galantamine
Species/Dose (mg/kg/day)/ Route | Parameters Evaluated | Results/Observations |
|---|---|---|
S. typhimurium / 8, 40, 200, 1,000, 5,000 mcg/plate in vitro | Bacterial reverse mutation assay Ames (in the presence and absence of S-9) (Ames test) | No biologically relevant increase in revertant colonies was observed, indicating galantamine was not mutagenic in the Ames test in Salmonella typhimurium. |
S. typhimurium / 40, 120, 400, 1,200, 4,000 mcg/plate in vitro | Bacterial reverse mutation assay Ames (in the presence and absence of S-9) (Ames test) | Both in the presence and in the absence of a rat liver S-9 microsomal fraction, galantamine was not mutagenic in the Ames assay. |
E. Coli / 6.4, 32, 160, 960 and 4,000 mcg/plate in vitro | Ames plate incorporation method in presence and absence of S-9. | No biologically relevant ↑ in revertant colonies, both in the presence and the absence of a rat liver metabolic activation system (S9), was observed up to the highest tested concentrations of 4,000 mcg/plate. Galantamine is not considered to be mutagenic under these test conditions. |
Mouse lymphoma cells 200, 400, 1,250 and 4,000 mcg/mL in vitro | Mammalian cell gene mutation test (in the presence and the absence of S-9 metabolic activations system). | Galantamine did not induce an ↑ in mutations at the thymidine kinase (TK)-locus; galantamine did not show mutagenic activity in the presence or absence of S-9 under conditions of this test. |
Chinese hamster ovary cells -S9: 80, 400, 800 +S9: 400, 800, 4,000 in vitro | Chromosome aberration tests in presence and absence of S-9. | No ↑ in chromosome aberrations, when evaluated at concentrations up to 4,000 mcg/mL in the presence and up to 800 mcg/mL in the absence of a metabolic activation system. |
Mouse 6.4, 10, 16 mg/kg in vivo oral (gavage) | Oral mouse micronucleus test; polychromatic erythrocytes (PCE), micronucleated PCE, normochromated erythrocytes (NCE) and micronucleated NCE chromosome aberrations. | No ↑ in micronucleated polychromatic erythrocytes was noted, indicating that galantamine was not clastogenic under the test conditions. |
Species/Dose (mg/kg/day)/ Route | Parameters Evaluated | Results/Observations |
|---|---|---|
S. typhimurium / E. coli 8, 40, 200, 1,000, 5,000 mcg/plate in vitro | Ames reverse mutation study. | No mutagenic potential of norgalantamine was demonstrated both in the presence and absence of S-9. |
Chinese hamster ovary cells 50, 250, 500, 2,500, 5,000 mcg/mL in vitro | Chromosome aberration tests in the presence and absence of S-9. | Norgalantamine showed no clastogenicity under the test conditions. |
Mouse 20, 32, 50 mg/kg oral (gavage) | Oral norgalantamine mouse micronucleus test; polychromatic erythrocytes (PCE), micronucleated PCE, normochromated erythrocytes (NCE) and micronucleated NCE chromosome aberrations. | There was no ↑ in micronuclei in the dosed groups, indicating that norgalantamine was not clastogenic under the conditions of this test. |
Reproduction and Teratology
No impairment of fertility was seen in rats given up to 16 mg/kg/day (7 times the Maximum Recommended Human Dose [MRHD] on a mg/m2 basis) for 14 days prior to mating in females and for 60 days prior to mating in males.
In a teratology study in which rats were dosed from Day 14 (females) or Day 60 (males) prior to mating through the period of organogenesis, a slightly increased incidence of skeletal variations was observed at doses of 8 mg/kg/day (3 times the MRHD on a mg/m2 basis) and
16 mg/kg/day. In a study in which pregnant rats were dosed from the beginning of organogenesis through Day 21 postpartum, pup weights were decreased at 8 and 16 mg/kg/day, but no adverse effects on other postnatal developmental parameters were seen. The doses causing the above effects in rats produced slight maternal toxicity. No major malformations were caused in rats given up to 16 mg/kg/day. No drug-related teratogenic effects were observed in rabbits given up to 40 mg/kg/day (32 times the MRHD on a mg/m2 basis) during the period of organogenesis.
A summary of the reproductive studies is presented in Table 9.
Table 9: Reproduction Studies with Galantamine
Species/Dose (mg/kg/day)/ Route/No. Sex | Parameters Evaluated | Results/Observations |
|---|---|---|
| Fertility and Development | ||
Rat 0, 2, 8, 16, 32 oral (gavage) control: 6M + 6F; 84: 6M + 12 F | Maternal: clinical signs, mortality, body weight, food consumption, estrous cycle monitoring, mating, parturition monitoring, necropsy. Litter: litter size, malformations, clinical signs and mortality, body weight, necropsy. | 32 mg/kg = M and F prematurely sacrificed after 10 days of dosing due to severe adverse clinical effects including tremors, hypoactivity, salivation and piloerection, ↓ body weight gain and food consumption, and the death of one M. 2 mg/kg = no toxic-effect dose. 8 and 16 mg/kg = adverse clinical signs including tremors, post-dose salivation, abnormal breathing and piloerection in both M and F; ↓ body weight gain and food consumption; reduced number of pups per litter; ↑ time taken to mate at 16 mg/kg; possible effect on fertility (2/6 F not pregnant) could not be excluded at this dosage. No apparent effects on the pups from either of these groups. |
Rat 0, 2, 8, 16 oral (gavage) 100 M + 100 F | Clinical signs, mortality, body weight, food consumption, estrous cycle monitoring, mating, parturition monitoring, necropsy. | 2 mg/kg = no parental toxicity nor any adverse effects on the litter. 8 mg/kg = parental toxicity evidenced by periodic tremors, which lasted from 30 minutes up to 4 hrs after dosing, and ↓ body weight gain and food consumption in M and F; no effects on the number of estrous cycles, fertility, pregnancy or sperm motility, morphology or concentration; ↑ incidence of litters with fetuses observed with minor skeletal deviations (abnormal sternebrae). 16 mg/kg = periodic post-dose tremors throughout the dosing period, which lasted from 30 minutes onwards up to 4 hrs, and occasional salivation in both sexes; noisy breathing in M; ↓ body weights, body weight gain and food consumption; slight reduction in the number of the pre-mating estrous cycles; cohabitation-mating interval not adversely affected; no adverse effects on fertility or copulation indices; sperm analysis revealed no effects; number of corpora lutea, implantations and live fetuses, and the fetal weight were comparable between groups; slightly ↑ incidence of minor skeletal deviations (abnormal sternebrae and rudimentary 14th ribs). No major abnormalities were noted at any dose. In general, there was |
Species/Dose (mg/kg/day)/ Route/No. Sex | Parameters Evaluated | Results/Observations |
|---|---|---|
| no effect upon mating performance or fertility at any dose. No teratogenic effects were observed. | ||
| Developmental and Pre/Postnatal Developmental Toxicity | ||
Rabbit 1: 2→32; 2: 24 oral (gavage) 3F/3F | Mortality and clinical signs and MTD, body weight, food consumption, necropsy. | Phase 1: No mortality occurred during this phase. No adverse effects present at 2, 4 and 8 mg/kg. No clinical abnormalities except for absent, reduced or liquid feces noted in one F at 32 mg/kg. 16 and 32 mg/kg = slight ↓ in body weight and food consumption (recovery in both body weight and food consumption observed during the two-day periods of withdrawal from treatment). Phase 2: No mortality of clinical observations were seen during this phase of the study. A slight body weight loss as well as ↓ food consumption was noted from the start of dosing until Day 5. No abnormalities were noted for any rabbit at necropsy. |
Rabbit 4, 12, 24, 32 oral (gavage) 20 F (4 groups) | Maternal: mortality and clinical signs, body weight, food consumption, necropsy, pregnancy status, number of corpora lutea, number and distribution of implantation sites. Fetal: external abnormalities, body weight, gender. | Study 1: No mortality (except 1F, which aborted on day 20 of pregnancy). 2F at 12 and 24 mg/kg and 1F at 32 mg/kg = reduced, loose or liquid feces. No effects on body weight gain, food consumption, necropsy, pregnancy parameters, fetal sex and no fetal abnormalities were observed at any dosage groups. Study 2: No test-article-related mortality. 2F at 48 mg/kg = tremors. 1F of each group = reduced fecal output. 40 and 48 mg/kg = ↓ body weight gain and food consumption. No galantamine-related abnormalities were noted at necropsy at any dosage. |
Rabbit 4, 12, 28, 40 oral (gavage) 20 F (4 groups) | Maternal: clinical signs, body weight, food consumption, necropsy, pregnancy status, number of corpora lutea, number | No mortalities (except 1F in the group treated at 40 mg/kg was prematurely sacrificed due to the abnormal clinical signs on the first day of dosing [trembling, noisy and rapid breathing, convulsions and constricted pupils]). This rabbit was replaced by another F. 4 and 12 mg/kg = no adverse effects. |
Species/Dose (mg/kg/day)/ Route/No. Sex | Parameters Evaluated | Results/Observations |
|---|---|---|
and distribution of implantation sites, live fetuses. Fetal: external/visceral and skeletal abnormalities, body weight, gender. | 28 mg/kg = maternal toxicity evidenced by tremors from Day 1 until Day 6 of the treatment period. 40 mg/kg = all F were aggressive, had excessive feed-stamping and tremors; body weight loss and ↓ food consumption. 28 mg/kg = body weight loss and ↓ food consumption. There was no effect of galantamine on the pregnancy parameters and there were no abnormalities seen at maternal necropsy. At none of the doses were there any effects on the fetuses (fetal sex ratio, fetal weight and fetal necropsy). No teratogenic effects were observed. | |
Rat 2, 8, 16 oral (gavage) 25 F (3 groups) | Maternal: clinical signs, body weight, food consumption, necropsy, parturition observations, litter size. F1 generation during lactation: body weight, gender, clinical signs and malformations, necropsy on culled pups, development during lactation. F1 generation post-weaning: clinical observations, body weight, ophthalmoscopy, auditory function, E-maze learning test, sexual development observations, reproductive capacity, necropsy. F2 females: pregnancy status, number of corpora lutea, number and distribution of implantation sites. | No test-article-related mortality. 2 mg/kg = no adverse effects on dams or their litters. 8 mg/kg = maternal toxicity characterized by decreased body weight gain and food consumption. 16 mg/kg = tremors, post-dose salivation, reduced body weight and decreased food consumption. 8 and 16 mg/kg = pup weights reduced. Galantamine had no effects on post-weaning development, mating performance and fertility of the F1 animals. |
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrPAT-galantamine ER, (extended release capsules, 8 mg, 16 mg, 24 mg,) submission control number 248978, Product Monograph, Janssen Inc., June 28, 2021.
- 2. Pr REMINYL ER, (extended release capsules, 8 mg, 16 mg, 24 mg) submission control number 200217, Product Monograph, Janssen Inc., January 11, 2017.