


Product Monograph - GD-Ziprasidone
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Oral | Capsules 20, 40, 60, and 80 mg | Lactose monohydrate, magnesium stearate, pregelatinized starch, and gelatin capsules. |
INDICATIONS AND CLINICAL USE
Schizophrenia
GD-Ziprasidone (ziprasidone hydrochloride) is indicated for the treatment of schizophrenia and related psychotic disorders. The prescriber should consider the finding of ziprasidone’s greater capacity to prolong the QT/QTc interval compared to other antipsychotic drugs (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS).
The efficacy of ziprasidone was established in short-term (4- and 6-week) controlled trials of schizophrenic inpatients (see Part II: CLINICAL TRIALS).
Ziprasidone has been shown to be effective in maintaining clinical improvement during long-term therapy (1-year). The physician who elects to use GD-Ziprasidone for extended periods should periodically re-evaluate the long-term usefulness of the drug for the individual patient.
Bipolar Disorder
GD-Ziprasidone (ziprasidone hydrochloride) is indicated for the treatment of acute manic or mixed episodes associated with bipolar disorder. The prescriber should consider the finding of ziprasidone’s greater capacity to prolong the QT/QTc interval compared to other antipsychotic drugs (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS).
The efficacy of ziprasidone in acute mania was established in 2 placebo-controlled, double-blind, 3-week studies which compared ziprasidone with placebo and 1 double-blind, 12-week (3-week placebo-controlled, active comparator acute phase and 9-week active comparator phase) study which compared ziprasidone to haloperidol and placebo, in patients meeting DSM-IV criteria for Bipolar I Disorder (see Part II: CLINICAL TRIALS).
The effectiveness of ziprasidone for longer-term use and for prophylactic use in mania has not been systematically evaluated in controlled clinical trials. Therefore, physicians who elect to use ziprasidone for extended periods should periodically re-evaluate the long-term risks and benefits of the drug for the individual patient.
Geriatrics (>65 years of age): GD-Ziprasidone is not indicated in elderly patients with dementia (see WARNINGS AND PRECAUTIONS, Serious Warnings and Precaution Box and ACTION AND CLINICAL PHARMACOLOGY, Special Populations). Caution should be used when treating geriatric patients with GD-Ziprasidone. See ACTION AND CLINICAL PHARMACOLOGY, Special Populations), and DOSAGE AND ADMINISTRATION sections.
Pediatrics (<18 years of age): The safety and efficacy of GD-Ziprasidone in children under the age of 18 years have not been established and its use is not recommended in this population (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
CONTRAINDICATIONS
QT Prolongation: Because of ziprasidone’s dose-related prolongation of the QT interval and the known association of fatal arrhythmias with QT prolongation by some other drugs, ziprasidone is contraindicated in patients with:
- known history of QT prolongation (including congenital long QT syndrome);
- recent acute myocardial infarction; or
- uncompensated heart failure (see WARNINGS AND PRECAUTIONS).
Pharmacokinetic/pharmacodynamic studies between ziprasidone and other drugs that prolong the QT interval have not been performed. An additive effect of ziprasidone and other drugs that prolong the QT interval cannot be excluded. Therefore, ziprasidone should not be given with dofetilide, sotalol, quinidine, other Class Ia and III anti-arrhythmias, mesoridazine, thioridazine, chlorpromazine, droperidol, pimozide, sparfloxacin, gatifloxacin, moxifloxacin, halofantrine, mefloquine, pentamidine, arsenic trioxide, levomethadyl acetate, dolasetron mesylate, probucol or tacrolimus. Ziprasidone is also contraindicated with drugs that have demonstrated QT prolongation as one of their pharmacodynamic effects and have this effect described in their respective Product Monograph as a contraindication or a warning (see WARNINGS AND PRECAUTIONS).
- Patients who are hypersensitive to ziprasidone or to any ingredient in the formulation or component of the container. For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
Increased Mortality in Elderly Patients with Dementia
Elderly patients with dementia treated with atypical antipsychotic drugs are at an increased risk of death compared to placebo. Analyses of 13 placebo-controlled trials with various antipsychotics (modal duration of 10 weeks) in these patients showed a mean 1.6-fold increase in the death rate in the drug-treated patients. Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature (see WARNINGS AND PRECAUTIONS, Special Populations, Use in Geriatric Patients with Dementia).
QT Prolongation (see also CONTRAINDICATIONS):
GD-Ziprasidone (ziprasidone hydrochloride) is associated with moderate QT/QTC interval prolongation, as described in the subsections below.
Recommendations regarding Risk Factors for QT prolongation
Many drugs that cause QT/QTc prolongation are suspected to increase the risk of a rare, potentially fatal polymorphic ventricular tachyarrhythmia known as torsades de pointes. Generally, the risk of torsades de pointes increases with magnitude of the QT/QTc prolongation produced by the drug.
Torsades may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope or seizures. If sustained, torsades de pointes can progress to ventricular fibrillation and sudden cardiac death.
As per Health Canada’s QT/QTc Guidelines, in the general population, certain circumstances may increase the risk of the occurrence of torsades de pointes in association with the use of drugs that prolong the QT/QTc interval, including (1) bradycardia; (2) electrolyte disturbances (e.g., hypokalemia, hypomagnesemia, or hypocalcemia); (3) concomitant use of other drugs that prolong the QT/QTc interval; (4) presence of congenital prolongation of the QT interval; (5) family history of sudden cardiac death at <50 years; (6) personal history of cardiac disease or arrhythmias; (7) acute neurological events, e.g., stroke; (8) being female or 65 years of age or older; (9) nutritional deficits e.g., eating disorders; (10) diabetes mellitus. Therefore:
- Ziprasidone should not be used in combination with other drugs that are known to prolong the QT/QTc interval (see CONTRAINDICATIONS). Additionally, clinicians should be alert to the identification of other drugs that have been consistently observed to prolong the QT/QTc interval. Such drugs should not be prescribed with ziprasidone.
- Ziprasidone should also not be used in patients with congenital long QT syndrome, or in patients with a history of cardiac arrhythmias, with recent acute myocardial infarction, or with uncompensated heart failure (see CONTRAINDICATIONS).
- If patients with stable cardiac disease are treated, an ECG review should be considered before treatment is started.
- Persistently prolonged QT/QTc intervals may also increase the risk of further prolongation and arrhythmia, but it is not clear that routine screening ECG measures are effective in detecting such patients. Rather, if cardiac symptoms, such as palpitations, vertigo, syncope or seizures occur then the possibility of a malignant cardiac arrhythmia should be considered and a cardiac evaluation including an ECG should be performed. If the QTc interval for a patient is >500 msec, then it is recommended that the treatment be stopped.
- It is recommended that patients being considered for ziprasidone treatment who are at risk for significant electrolyte disturbances (e.g., diuretic therapy, protracted diarrhea or vomiting, water intoxication, eating disorder, and alcoholism), have baseline serum potassium and magnesium measurements performed and levels corrected if necessary. Hypokalemia (and/or hypomagnesemia) may increase the risk of QT prolongation and arrhythmia. It is essential to periodically monitor serum electrolytes in patients for whom diuretic therapy is introduced during ziprasidone treatment.
- Patients receiving treatment with drugs that prolong the QT/QTc interval should be counselled appropriately, regarding risk factors, symptoms suggestive of arrhythmia and risk management strategies.
Description of Data:
- 1) Studies Specifically Designed to Assess QT Prolongation
- a) Comparative study (128-054): Six antipsychotics
A study directly comparing the QT/QTc prolonging effect of ziprasidone with several other drugs effective in the treatment of schizophrenia was conducted in patient volunteers (n=28-35 per drug). In the first phase of the trial, ECGs were obtained at the time of maximum plasma concentration when the drug was administered alone. In the second phase of the trial, ECGs were obtained at the time of maximum plasma concentration while the drug was co-administered with an inhibitor of the CYP450 metabolism of the drug.
In the first phase of the study, the mean change in QTc from baseline was calculated for each drug, using a sample-based correction that makes adjustments for the effect of heart rate on the QT interval. The mean increase in QTc from baseline for ziprasidone (baseline correction) at 160 mg/day was 15.9 msec, which was approximately 9 to 14 msec greater than for four of the comparator drugs (haloperidol at 15 mg/day [7.1 msec], quetiapine at 750 mg/day [5.7 msec], risperidone at 16 mg/day [3.6 msec], and olanzapine at 20 mg /day [1.7 msec], but was approximately 14 msec less than the prolongation observed for thioridazine at 300 mg/day [30.1 msec].
In the second phase of the study, the effect of ziprasidone on QTc length (16.6 msec) was not augmented by the presence of a metabolic inhibitor (ketoconazole 200 mg BID). The mean increase for the other comparator drugs was haloperidol [13.3 msec], quetiapine [8.0 msec], olanzapine [3.0 msec], and risperidone [2.6 msec], compared to thioridazine [29.6 msec].
- b) QT Effects at 2x maximum recommended ziprasidone dose
A study examining the effect of 3 doses of orally administered ziprasidone (including twice the recommended clinical dose, n=29) and haloperidol (the highest dose level was comparably high, n=30) on the QTc interval was conducted in clinically stable patients with schizophrenia and schizoaffective disorder. The study comprised 4 consecutive periods, including drug tapering (phase 1), wash out (phase 2), drug therapy (phase 3) followed by the study drug wash out and initiation of outpatient drug therapy (phase 4). Serial baseline electrocardiograms (ECGs) were collected under controlled conditions on the last day (day 0) of period 2 at times matched to those collected during study drug administration (phase 3) at the time of estimated peak drug exposure. At each steady-state dose level, three ECGs and a pharmacokinetic sample were collected at the predicted time of peak exposure to administered drug (Tmax). One of the three ECGs was collected at Tmax and the other two were collected one hour on either side of Tmax.
The mean increase in QTc from baseline for ziprasidone at 40 mg/day was 4.5 msec, and at 160 mg/day was 19.5 msec (comparable to the study described above). A further increase in dose to 320 mg/day (twice the maximum recommended clinical dose) led to an increase in QTc of 22.5 msec, which was only 3 msec more than after 160 mg/day in this study, suggesting a plateau. In comparison, there was no mean QTc increase apparent at the lowest haloperidol dose (2.5 mg/day). At the 2 higher doses of haloperidol, (15 and 30 mg/day), mean QTc increases ranged from 6.6 to 7.2 msec. No subject in either treatment group experienced a QTc interval >450 msec or an increase from baseline of >75 msec.
- 2) Data from Non-QT specific ziprasidone studies
In placebo-controlled trials, ziprasidone increased the QTc interval compared to placebo by approximately 10 msec at the highest recommended daily dose of 160 mg, which was the basis for subsequent QT-specific studies. The clinical trial data for ziprasidone did not reveal an excess risk of mortality for ziprasidone compared to other antipsychotic drugs or placebo.
Electrocardiogram readings revealing QTc intervals exceeding the potentially clinically relevant threshold of 500 msec in clinical trials with ziprasidone occurred in: 2/3266 (0.06%) patients receiving ziprasidone and 1/538 (0.19%) patients receiving placebo. One patient had a history of prolonged QTc and a screening measurement of 489 msec; QTc was 503 msec during ziprasidone treatment. The other patient, who was receiving ziprasidone for more than 6.5 years without interruption, had a QTc of 503 msec at week 189, and 435 msec 19 weeks later, while maintained on the same oral dose of ziprasidone. There were confounding factors that contributed to the occurrence of these cases.
- 3) Post-Marketing Data (see also ADVERSE EVENTS, Post-Marketing)
Torsades de Pointes
There have been rare post-marketing reports of torsades de pointes (in the presence of multiple confounding factors) (see ADVERSE REACTIONS; Post-Market Adverse Drug Reactions). Torsades de pointes have not been observed in association with the use of ziprasidone at recommended doses in clinical trials, but experience is too limited to rule out increased risk.
Analysis of Post-Marketing Data
In view of the clinical trial data demonstrating a moderate QT prolongation effect of ziprasidone, a review of 5-year, post-marketing spontaneous data from the FDA AERS database was conducted using a set of heart-related search terms.
Small elevations in spontaneous reporting rates were observed for ziprasidone compared with two other atypical antipsychotics, for both fatal cases, and "all" cases (i.e., fatal plus non-fatal).
Accumulated case reports should not be used as a basis for determining the incidence of a reaction or estimating risk for a particular product, as neither the total number of reactions occurring, nor the number of patients exposed to the health product is known. Because of the multiple factors that influence reporting, quantitative comparisons of health product safety cannot be made from the data. Comparison of reporting rates cannot be employed to confirm or refute a hypothesis, due to well-known, inherent limitations with spontaneous reporting of adverse events.
General
Body Temperature Regulation
Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing ziprasidone for patients who will be experiencing conditions which may contribute to an elevation in core body temperature, e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity, or being subject to dehydration.
Carcinogenesis and Mutagenesis
For animal data, see Part II: TOXICOLOGY.
Cardiovascular
See also CONTRAINDICATIONS; and WARNINGS AND PRECAUTIONS, QT Prolongation.
Orthostatic Hypotension
Ziprasidone may induce orthostatic hypotension associated with dizziness, tachycardia and, in some patients, syncope, especially during the initial dose-titration period, probably reflecting its α1-adrenergic antagonist properties. Syncope was reported in 0.6% (22/3834) of the patients treated with ziprasidone.
Ziprasidone should be used with particular caution in patients with known cardiovascular disease (history of myocardial infarction or ischemic heart disease, heart failure or conduction abnormalities), cerebrovascular disease or conditions which would predispose patients to hypotension (dehydration, hypovolemia and treatment with antihypertensive medications). Patients with a history of clinically significant cardiac disorders were excluded from the trials.
Dependence/Tolerance
GD-Ziprasidone has not been systematically studied, in animals or humans, for its potential for abuse, tolerance or physical dependence. While clinical trials did not reveal any tendency for drug-seeking behaviour, these observations were not systematic and it is not possible to predict on the basis of this limited experience the extent to which ziprasidone will be misused, diverted and/or abused once marketed. Consequently, patients should be evaluated carefully for a history of drug abuse, and such patients should be observed closely for signs of GD-Ziprasidone misuse or abuse (e.g., development of tolerance, increases in dose, drug-seeking behaviour).
Endocrine and Metabolism
Hyperglycemia
As with some other antipsychotics, hyperglycemia, exacerbation of pre-existing diabetes, and diabetic coma have been reported very rarely during the use of ziprasidone. However, no causal relationship with ziprasidone has been established (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions). Diabetic ketoacidosis (DKA) has occurred in patients with no reported history of hyperglycemia. Patients should have baseline and periodic monitoring of blood glucose and body weight.
Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia and the increasing incidence of diabetes mellitus in the general population. Given these confounders, and that there is no data in drug-naïve patients, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies, which did not include ziprasidone, suggest an increased risk of treatment-emergent hyperglycemia-related adverse events in patients treated with the atypical antipsychotics. Because ziprasidone was not marketed at the time these studies were performed, it is not known if ziprasidone is associated with this increased risk. Precise risk estimates for hyperglycemia-related adverse events in patients treated with atypical antipsychotics are not available.
Any patient treated with atypical antipsychotics should be monitored for symptoms of hyperglycemia, including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients required continuation of anti-diabetic treatment despite discontinuation of the suspect drug. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control.
Hyperprolactinemia
As with other drugs that antagonize dopamine D2 receptors and/or serotonin 5-HT2 receptors, GD-Ziprasidone may elevate prolactin levels in humans. Elevations associated with GD-Ziprasidone treatment are generally mild and may decline during administration.
Increased prolactin levels were also observed in animal studies with this compound, and were associated with an increase in mammary gland neoplasia in mice; a similar effect was not observed in rats (see TOXICOLOGY, Carcinogenicity).
Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin-dependent in vitro, GD-Ziprasidone should only be administered to patients with previously detected breast cancer if the benefits outweigh the potential risks.
Although disturbances such as galactorrhea, amenorrhea, gynecomastia, and impotence have been reported with prolactin-elevating compounds, the clinical significance of elevated serum prolactin levels is unknown for most patients. Long-standing hyperprolactinemia when associated with hypogonadism may lead to decreased bone mineral density in both female and male subjects. Caution should be exercised when considering ziprasidone treatment in patients with pituitary tumors. Neither clinical studies nor epidemiological studies conducted to date have shown an association between chronic administration of this class of drugs and tumorigenesis in humans. The available evidence is considered too limited to be conclusive at this time.
Gastrointestinal
Patients should be advised of the risk of severe constipation during GD-Ziprasidone treatment, and that they should tell their doctor if constipation occurs or worsens, as they may need laxatives (see ADVERSE REACTIONS, Post Market Adverse Drug Reactions).
Genitourinary
Priapism
Rare cases of priapism have been reported with antipsychotic use, such as ziprasidone. This adverse reaction, as with other psychotropic drugs, did not appear to be dose-dependent and did not correlate with duration of treatment. The likely mechanism of action of priapism is a relative decrease in sympathetic tone. Severe priapism may require surgical intervention.
Hematologic
Venous Thromboembolism
Venous thromboembolism (VTE), including fatal pulmonary embolism, has been reported with antipsychotic drugs, including GD-Ziprasidone, in case reports and/or observational studies. When prescribing GD-Ziprasidone, all possible risk factors for VTE should be identified before and during treatment with GD-Ziprasidone and preventive measures undertaken.
Hemic and Lymphatic System
Neutropenia, granulocytopenia, and agranulocytosis have been reported during antipsychotic use (see ADVERSE REACTIONS, Post Market Adverse Drug Reactions). Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting GD-Ziprasidone and then periodically throughout treatment.
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) and history of drug induced leukopenia/neutropenia. Patients with a pre-existing low WBC or a history of drug induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and GD-Ziprasidone should be discontinued at the first sign of decline in WBC, in the absence of other causative factors.
Patients with neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Patients with severe neutropenia (absolute neutrophil count <1 x 10⁹/L) should discontinue GD-Ziprasidone and have their WBC followed until recovery.
Hepatic
See WARNINGS AND PRECAUTIONS, Special Populations, Hepatic Impairment.
Neurologic
Neuroleptic Malignant Syndrome (NMS)
A potentially fatal symptom complex sometimes referred to as NMS has been reported in association with the administration of antipsychotic drugs, including ziprasidone.
Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatinine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure.
In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.), and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology.
The management of NMS should include: 1) immediate discontinuation of antipsychotic drugs including GD-Ziprasidone and other drugs not essential to concurrent therapy; 2) intensive symptomatic treatment and medical monitoring; and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment regimens for uncomplicated NMS.
If a patient requires antipsychotic drug treatment after recovery from NMS, the potential reintroduction of drug therapy should be carefully considered. The patient should be carefully monitored, since recurrences of NMS have been reported.
Tardive Dyskinesia (TD)
A syndrome consisting of potentially irreversible, involuntary and disabling dyskinetic movements may develop in patients treated with antipsychotic drugs. Although the prevalence of the tardive dyskinesia syndrome appears to be highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the tardive dyskinesia syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown.
The risk of developing tardive dyskinesia, and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses.
There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment itself however may suppress (or partially suppress) the signs and symptoms of the tardive dyskinesia syndrome and thereby may possibly mask the underlying process. The effect that symptomatic suppression has upon the long-term course of the tardive dyskinesia syndrome is unknown.
Given these considerations, GD-Ziprasidone should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who 1) suffer from a chronic illness that is known to respond to antipsychotic drugs, and 2) for whom alternative, equally effective but potentially less harmful treatments are not available or appropriate. In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically.
If signs and symptoms of tardive dyskinesia appear in a patient on GD-Ziprasidone, drug discontinuation should be considered. However, some patients may require treatment with GD-Ziprasidone despite the presence of the tardive dyskinesia syndrome.
Potential Effect on Cognitive and Motor Performance
Falls
Antipsychotic drugs (which includes ziprasidone) may cause somnolence, postural hypotension, and motor and sensory instability, which could lead to falls and, consequently, fractures or other injuries. For patients with diseases, conditions, or medications that could exacerbate these effects, a fall risk assessment should be completed when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.
Somnolence was a commonly reported adverse event in patients treated with ziprasidone. In the 4- and 6-week placebo-controlled trials in patients with schizophrenia, somnolence was reported in 14% of patients on ziprasidone compared to 7% of patients on placebo (see ADVERSE REACTIONS). Since ziprasidone has the potential to impair judgment, thinking, or motor skills, patients should be cautioned about performing activities requiring mental alertness, such as operating a motor vehicle (including automobiles) or operating hazardous machinery, until they are reasonably certain that ziprasidone therapy does not affect them adversely.
Seizures
During clinical trials, seizures occurred in 0.4% of patients treated with ziprasidone. There were confounding factors that may have contributed to the occurrence of seizures in many of these cases. Nevertheless, as with other antipsychotic drugs, ziprasidone should be used cautiously in patients with a history of seizures or with conditions that potentially lower the seizure threshold, e.g., Alzheimer’s dementia. Conditions that lower the seizure threshold may be more prevalent in a population of 65 years or older.
Serotonin Syndrome
Serotonin syndrome is a rare and potentially life-threatening event in which signs and symptoms include high fever, seizures, arrhythmias, and unconsciousness observed in patients taking multiple serotonergic agents or who have had considerable exposure to a single serotonin-augmenting drug. In isolated cases, there have been reports of serotonin syndrome temporally associated with the therapeutic use of ziprasidone in combination with other serotonergic medicinal products such as SSRIs (see ADVERSE REACTIONS, Post Market Adverse Drug Reactions). The features of serotonin syndrome can include confusion, agitation, fever, sweating, ataxia, hyperreflexia, myoclonus and diarrhea,hyperthermia, rigidity, and autonomic instability with possible rapid fluctuations of vital signs and symptoms can progress to delirium and coma. Management of serotonin syndrome includes withdrawal of the offending medication and supportive care for mild cases; hospitalization is required for moderate to severe cases.
Psychiatric
Suicide
The possibility of a suicide attempt is inherent in psychotic illness; thus, close supervision and appropriate clinical management of high-risk patients should accompany drug therapy.
Prescriptions for GD-Ziprasidone should be written for the smallest quantity of capsules consistent with good patient management, in order to reduce the risk of overdose.
Renal
Dose adjustments are not required for patients with renal impairment (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency).
Skin
Severe Cutaneous Adverse Reactions
Drug reaction with eosinophilia and systemic symptoms (DRESS) has been reported with ziprasidone exposure. DRESS consists of a combination of three or more of the following: cutaneous reaction (such as rash or exfoliative dermatitis), eosinophilia, fever, lymphadenopathy and one or more systemic complications such as hepatitis, nephritis, pneumonitis, myocarditis, and pericarditis.
Other severe cutaneous adverse reactions, such as Stevens-Johnson syndrome, have been reported with ziprasidone exposure (see ADVERSE REACTIONS, Post Market Adverse Drug Reactions).
Severe cutaneous adverse reactions are sometimes fatal. Discontinue ziprasidone if severe cutaneous adverse reactions occur.
Rash
In pre-marketing trials with ziprasidone, about 5% of patients developed rash (173/3834) and/or urticaria (12/3834), with discontinuation in about one-sixth of these cases. The occurrence of rash was related to dose of ziprasidone, although the finding might also be explained by the longer exposure time in the higher dose patients. Several patients with rash had signs and symptoms of associated systemic illness, e.g., elevated white blood cells (WBC). Most patients improved promptly with adjunctive treatment with antihistamines or steroids and/or upon discontinuation of ziprasidone, and all patients experiencing these events were reported to recover completely. Upon appearance of rash for which an alternative etiology cannot be identified, ziprasidone should be discontinued.
Special Populations
Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Women of childbearing potential receiving ziprasidone should therefore be counselled on the need to use an effective method of contraception during treatment with GD-Ziprasidone.
Patients should be advised to notify their physician if they become pregnant or intend to become pregnant. GD-Ziprasidone should not be used during pregnancy unless the expected benefits to the mother markedly outweigh the potential risks to the fetus.
Fertility: There are no adequate and well-controlled studies in women and men exposed to ziprasidone.
Teratogenic effects
In animal studies, ziprasidone demonstrated developmental toxicity, including possible teratogenic effects at doses similar to human therapeutic doses. When ziprasidone was administered to pregnant rabbits during the period of organogenesis, an increased incidence of fetal structural abnormalities (ventricular septal defects and other cardiovascular malformations and kidney alterations) was observed at a dose of 30 mg/kg/day (3 times the maximum recommended human dose (MRHD) of 200 mg/day on a mg/m2 basis). There was no evidence to suggest that these developmental effects were secondary to maternal toxicity. The developmental no-effect dose was 10 mg/kg/day (equivalent to the MRHD on an mg/m2 basis).
In rats, embryofetal toxicity (decreased fetal weights, delayed skeletal ossification) was observed following administration of 10 to 160 mg/kg/day (0.5 to 8 times the MRHD on a mg/m2 basis) during organogenesis or throughout gestation, but there was no evidence of teratogenicity. Doses of 40 and 160 mg/kg/day (2 and 8 times the MRHD on a mg/m2 basis) were associated with maternal toxicity. The developmental no-effect dose was 5 mg/kg/day (0.2 times the MRHD on a mg/m2 basis).
There was an increase in the number of pups born dead and a decrease in postnatal survival through the first 4 days of lactation among the offspring of female rats treated during gestation and lactation with doses of 10 mg/kg/day (0.5 times the MRHD on a mg/m2 basis) or greater. Offspring developmental delays and neurobehavioral functional impairment were observed at doses of 5 mg/kg/day (0.2 times the MRHD on a mg/m2 basis) or greater. A no-effect level was not established for these effects.
Non teratogenic effects
Neonates exposed to antipsychotic drugs (including ziprasidone) during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
GD-Ziprasidone should not be used during pregnancy unless the expected benefits to the mother markedly outweigh the potential risks to the fetus.
Labor and Delivery
The effect of GD-Ziprasidone on labor and delivery in humans is not known.
Nursing Women
There are no adequate and well-controlled studies in lactating women. Limited data indicate that ziprasidone is excreted into breast milk at very low levels. It is recommended that women taking GD-Ziprasidone should not breast-feed.
Pediatrics (< 18 years of age)
The safety and efficacy of GD-Ziprasidone in children under the age of 18 years have not been established and its use is not recommended.
Weight gain has been observed with atypical antipsychotic use in pediatric and adolescent patient populations. Independent of any drug-specific effects, weight gain can be associated with adverse changes in other metabolic parameters (e.g., glucose and lipid metabolism).
Abnormal childhood weight and metabolic status can have adverse effects on cardiovascular outcomes in adulthood. Weight gain and adverse effects on other metabolic parameters associated with atypical antipsychotics can be more frequent or more severe in pediatric and adolescent patients than in the adult patients.
The following adverse events in the two studies in pediatrics are of note because they are not typical of the adult population treated with ziprasidone: abnormally decreased bicarbonate values; elevations in testosterone, elevations in insulin, total neutrophils, monocytes and ALT; fatigue; abdominal pain, insomnia; restlessness. There are also adverse events of note due to a greater incidence rate compared to adults, or a greater differential over placebo: blurred vision; extrapyramidal symptoms (aggregated); sedation/somnolence; nausea; vomiting; and elevations in serum prolactin (See ADVERSE REACTIONS, Adverse Drug Reactions in Pediatrics).
The long-term safety, including cardiometabolic effects and effects on growth, maturation and behavioural development in patients under 18 years of age has not been systematically evaluated.
The ziprasidone pediatric study in schizophrenia was terminated by Pfizer due to lack of efficacy (Placebo-controlled study A1281134, and open-label extension 1135).
Geriatrics (> 65 years of age)
The number of patients 65 years or older with schizophrenia or related disorders, exposed to ziprasidone during clinical trials was limited (n=109). In general, there was no indication of any different tolerability of ziprasidone or for reduced clearance of ziprasidone in the elderly compared to younger adults. Nevertheless, geriatric patients generally have decreased cardiac, hepatic and renal function, and more frequent use of concomitant medication. The presence of multiple factors that might increase the pharmacodynamic response to ziprasidone, or cause poorer tolerance or orthostasis, should lead to consideration of a lower starting dose, slower titration, and careful monitoring during the initial dosing period for elderly patients.
Use in Geriatric Patients with Dementia
Overall Mortality
Elderly patients with dementia treated with atypical antipsychotic drugs have an increased mortality compared to placebo in a meta-analysis of 13 controlled trials of various atypical antipsychotic drugs. GD-Ziprasidone is not indicated in elderly patients with dementia (e.g., dementia related psychosis) (see WARNINGS AND PRECAUTIONS, Serious Warnings and Precautions).
Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use. Aspiration pneumonia is a common cause of morbidity and mortality in elderly patients, in particular those with advanced Alzheimer’s dementia. Ziprasidone and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia.
Cerebrovascular Adverse Events (CVAEs), including Stroke in Elderly Patients with Dementia
In placebo-controlled trials with some atypical antipsychotics, there was a higher incidence of cerebrovascular adverse events (cerebrovascular accidents and transient ischemic attacks) including fatalities compared to placebo-treated subjects. GD-Ziprasidone is not indicated for the treatment of patients with dementia (e.g., dementia-related psychosis). (see WARNINGS AND PRECAUTIONS, Serious Warnings and Precautions).
Use in Patients with Concomitant Illness
Ziprasidone has not been evaluated or used to any appreciable extent in patients with a recent history of myocardial infarction or unstable heart disease. Patients with these diagnoses were excluded from pre-marketing clinical studies. Because of the risks of QT/QTc prolongation and orthostatic hypotension with ziprasidone, caution should be observed in cardiac patients (see CONTRAINDICATIONS, as well as WARNINGS AND PRECAUTIONS, QT Prolongation and Cardiovascular, Orthostatic Hypotension).
Hepatic Impairment
In patients with hepatic insufficiency, lower doses should be considered (see DOSAGE AND ADMINISTRATION, Hepatic Impairment and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Hepatic Insufficiency).
Renal Impairment
Dose adjustments are not required for patients with renal impairment (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency).
Lactose
GD-Ziprasidone capsules contain lactose. This should be considered when prescribing to patients with rare hereditary problems of galactose intolerance, lactase deficiency or glucose-galactose malabsorption.
Monitoring and Laboratory Tests
Patients being considered for ziprasidone treatment that are at risk of significant electrolyte disturbances should have baseline serum potassium and magnesium measurements. Low serum potassium and magnesium should be repleted before proceeding with treatment. Patients who are started on diuretics during ziprasidone therapy need periodic monitoring of serum potassium and magnesium. Ziprasidone should be discontinued in patients who are found to have persistent QTc measurements >500 msec (see WARNINGS AND PRECAUTIONS, QT Prolongation).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The stated frequencies of adverse events represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event of the type listed. An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse Events Observed in Short-Term, Placebo-Controlled Trials
The following findings are based on a pool of two 6-week, and two 4-week placebo-controlled trials for schizophrenia and a pool of three 3-week flexible dose trials for bipolar mania in which ziprasidone was administered in doses ranging from 10 to 200 mg/day.
Schizophrenia
Adverse Events Associated with Discontinuation of Treatment in Short-Term, Placebo-Controlled Trials
A total of 4.1% (29/702) of patients treated with ziprasidone (ziprasidone hydrochloride) in short-term, placebo-controlled studies discontinued treatment due to an adverse event, compared with 2.2% (6/273) on placebo and 8.2% (7/85) on the active control drug. The most common event associated with dropout was rash, including 7 dropouts for rash among ziprasidone patients (1%) compared to no placebo patients (see WARNINGS AND PRECAUTIONS, SKIN, Rash).
Adverse Events Occurring at an Incidence of 1% or more in Short-Term, Placebo-Controlled Trials (up to 6 weeks)
Table 1 enumerates the incidence, rounded to the nearest percent, of treatment-emergent adverse events that occurred during acute therapy (up to 6 weeks) in predominantly schizophrenic patients, including only those events that occurred in 1% or more of patients treated with ziprasidone and for which the incidence in patients treated with ziprasidone was greater than the incidence in placebo-treated patients.
Table 1. Treatment-Emergent Adverse Event Incidence in Short-Term Placebo-Controlled Trials – Schizophrenia
| Body System | Percentage of patients reporting | |
|---|---|---|
| Ziprasidone (n = 702) | Placebo (n = 273) | |
| Body as a Whole | ||
| Asthenia | 5 | 3 |
| Accidental Injury | 4 | 2 |
| Chest Pain | 3 | 2 |
| Cardiovascular | ||
| Tachycardia | 2 | 1 |
| Postural Hypotension | 1 | 0 |
| Digestive | ||
| Nausea | 10 | 7 |
| Constipation | 9 | 8 |
| Dyspepsia | 8 | 7 |
| Diarrhea | 5 | 4 |
| Dry Mouth | 4 | 2 |
| Anorexia | 2 | 1 |
| Musculoskeletal | ||
| Myalgia | 1 | 0 |
| Nervous | ||
| Extrapyramidal Symptoms* | 14 | 8 |
| Somnolence | 14 | 7 |
| Akathisia | 8 | 7 |
| Dizziness** | 8 | 6 |
| Respiratory | ||
| Respiratory Tract Infection | 8 | 3 |
| Rhinitis | 4 | 2 |
| Cough Increased | 3 | 1 |
| Skin and Appendages | ||
| Rash | 4 | 3 |
| Fungal Dermatitis | 2 | 1 |
| Special Senses | ||
| Abnormal Vision | 3 | 2 |
* Extrapyramidal Symptoms includes the following adverse event terms: extrapyramidal syndrome, hypertonia, dystonia, dyskinesia, hypokinesia, tremor, paralysis and twitching. None of these adverse events occurred individually at an incidence greater than 5% in schizophrenia trials.
** Dizziness includes the adverse event terms dizziness and lightheadedness
Explorations for interactions on the basis of gender did not reveal any clinically meaningful differences in the adverse event occurrence on the basis of this demographic factor.
Commonly Observed Adverse Events in Short-Term, Placebo-Controlled Trials
In the schizophrenia studies, the most commonly observed adverse events associated with the use of ziprasidone (incidence of 5% or greater) and observed at a rate on ziprasidone at least twice that of placebo were somnolence (14%), extrapyramidal symptoms (14%), and respiratory tract infection (8%).
Dose Dependency of Adverse Events in Short-Term, Placebo-Controlled Trials
An analysis for dose response in the schizophrenia 4-study pool revealed an apparent relation of adverse event to dose for the following events: asthenia, postural hypotension, anorexia, dry mouth, increased salivation, arthralgia, anxiety, dizziness, dystonia, hypertonia, somnolence, tremor, rhinitis, rash, and abnormal vision.
Extrapyramidal Symptoms (EPS) - Schizophrenia
The incidence of reported EPS for ziprasidone-treated patients in the short-term, placebo-controlled trials was 14% vs. 8% for placebo. Medications to treat EPS and movement disorders were allowed; but if clinically meaningful movement disorder side effects were observed by the clinician or volunteered by the subject, or if a clinically meaningful movement disorder, present at screening, increased in severity or required the administration of anticholinergics or propanolol, these symptoms and their severity were recorded as adverse event. Objectively collected data from those trials on the Simpson Angus Rating Scale (for EPS) and the Barnes Akathisia Scale (for akathisia) did not generally show a difference between ziprasidone and placebo.
Table 2. Treatment-Emergent Extrapyramidal Symptoms Assessed by Adverse Events Incidence in Short-Term, Schizophrenia Placebo-Controlled Trials
| Percentage of Subjects Reporting Event | ||||||
| Extrapyramidal Symptoms | Ziprasidone N=702 | Placebo N=273 | ||||
| Dystonic events1 | 4.0% | 2.2% | ||||
| Parkinsonism events2 | 10.7% | 5.1% | ||||
| Akathisia events3 | 8.4% | 7.0% | ||||
| Dyskinetic events4 | 1.9% | 2.9% | ||||
| Residual events5 | 0.3% | 0.4% | ||||
| Any extrapyramidal event | 21.7% | 15% | ||||
1Patients with the following COSTART terms were counted in this category: dystonia, oculogyric crisis
2Patients with the following COSTART terms were counted in this category: abnormal gait, akinesia, cogwheel rigidity, extrapyramidal syndrome, hypokinesia, muscular hypertonia, tremor
3Patients with the following COSTART terms were counted in this category: akathisia
4Patients with the following COSTART terms were counted in this category: dyskinesia, paralysis, tardive dyskinesia
5Patients with the following COSTART terms were counted in this category: twitching
Dystonia
Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs. An elevated risk of acute dystonia is observed in males and younger age groups.
Vital Sign Changes
Ziprasidone is associated with orthostatic hypotension (see WARNINGS AND PRECAUTIONS, Cardiovascular, Orthostatic Hypotension).
ECG Changes
Ziprasidone is associated with an increase in the QTc interval (see WARNINGS AND PRECAUTIONS, QT Prolongation). In schizophrenia trials, ziprasidone was associated with a mean increase in heart rate of 1.4 beats per minute compared to a 0.2 beats per minute decrease among placebo patients.
Weight Gain
The proportions of patients meeting a weight gain criterion of >7% of body weight were compared in a pool of four 4- and 6-week placebo-controlled schizophrenia clinical trials, revealing a statistically significantly greater incidence of weight gain for ziprasidone (10%) compared to placebo (4%). A median weight gain of 0.5 kg was observed in ziprasidone patients compared to no median weight change in placebo patients. In this set of clinical trials, weight gain was reported as an adverse event in 0.4% of ziprasidone and 0.4% of placebo patients.
During long-term therapy with ziprasidone, a categorization of patients at baseline on the basis of body mass index (BMI) revealed the greatest mean weight gain and highest incidence of clinically significant weight gain (>7% of body weight) in patients with low BMI (<23) compared to normal (23-27) or overweight patients (>27). There was a mean weight gain of 1.4 kg for those patients with a “low” baseline BMI, no mean change for patients with a “normal” BMI, and a 1.3 kg mean weight loss for patients who entered the program with a “high” BMI.
Less Common Clinical Trial Adverse Events (<1%) – Schizophrenia
Other Adverse Events Observed During the Pre-marketing Evaluation of Oral Ziprasidone
All reported treatment-emergent events are included except those already listed in Table 1 or in other sections. It is important to emphasize that, although the events reported occurred during treatment with ziprasidone capsules, they were not necessarily caused by the therapy.
The adverse events are categorized by body system and listed in order of decreasing frequency according to the following definitions: frequent adverse events are those occurring in at least 1/100 patients (only those not already listed in the tabulated results from placebo-controlled trials appear in this listing); infrequent adverse events are those occurring in 1/100 to 1/1000 patients; rare events are those occurring in fewer than 1/1000 patients.
Body As a Whole – Frequent: abdominal pain, flu syndrome, fever, accidental fall, face edema, chills, photosensitivity reaction, flank pain, hypothermia, motor vehicle accident; Rare: feeling hot.
Cardiovascular System – Frequent: hypertension; Infrequent: bradycardia, angina pectoris, atrial fibrillation; Rare: first degree AV block, bundle branch block, phlebitis, pulmonary embolus, cardiomegaly, cerebral infarct, cerebrovascular accident, deep thrombophlebitis, myocarditis, thrombophlebitis.
Digestive System – Frequent: vomiting; Infrequent: rectal hemorrhage, dysphagia, tongue edema; Rare: gum hemorrhage, jaundice, fecal impaction, gamma glutamyl transpeptidase increased, hematemesis, cholestatic jaundice, hepatitis, hepatomegaly, leukoplakia of mouth, fatty liver deposit, melena.
Endocrine – Rare: hypothyroidism, hyperthyroidism, thyroiditis.
Hemic and Lymphatic System – Infrequent: anemia, ecchymosis, leukocytosis, leukopenia, eosinophilia, lymphadenopathy; Rare: thrombocytopenia, hypochromic anemia, lymphocytosis, monocytosis, basophilia, lymphedema, polycythemia, thrombocythemia.
Metabolic and Nutritional Disorders – Infrequent: thirst, transaminase increased, peripheral edema, hyperglycemia, creatine phosphokinase increased, alkaline phosphatase increased, hypercholesteremia, dehydration, lactic dehydrogenase increased, albuminuria, hypokalemia; Rare: BUN increased, creatinine increased, hyperlipemia, hypocholesteremia, hyperkalemia, hypochloremia, hypoglycemia, hyponatremia, hypoproteinemia, glucose tolerance decreased, gout, hyperchloremia, hyperuricemia, hypocalcemia, hypoglycemic reaction, hypomagnesemia, ketosis, respiratory alkalosis.
Musculoskeletal System – Infrequent: tenosynovitis; Rare: myopathy.
Nervous System – Frequent: agitation, tremor, dyskinesia, hostility, paresthesia, confusion, vertigo, hypokinesia, hyperkinesia, abnormal gait, oculogyric crisis, hypesthesia, ataxia, amnesia, cogwheel rigidity, delirium, hypotonia, akinesia, dysarthria, withdrawal syndrome, buccoglossal syndrome, choreoathetosis, diplopia, incoordination, neuropathy; Rare: myoclonus, nystagmus, torticollis, circumoral paresthesia, opisthotonos, reflexes increased, trismus.
Respiratory System – Frequent: dyspnea; Infrequent: pneumonia, epistaxis; Rare: hemoptysis, laryngismus.
Skin and Appendages – Infrequent: maculopapular rash, urticaria, alopecia, eczema, exfoliative dermatitis, contact dermatitis, vesiculobullous rash. Drug reaction with eosinophilia and systemic symptoms (DRESS).
Special Senses – Infrequent: conjunctivitis, dry eyes, tinnitus, blepharitis, cataract, photophobia; Rare: eye hemorrhage, visual field defect, keratitis, keratoconjunctivitis.
Urogenital System – Infrequent: impotence, abnormal ejaculation, amenorrhea, hematuria, menorrhagia, female lactation, polyuria, urinary retention, metrorrhagia, male sexual dysfunction, anorgasmia, glycosuria; Rare: gynecomastia, vaginal hemorrhage, nocturia, oliguria, female sexual dysfunction, uterine hemorrhage.
Bipolar Mania
Adverse Events Associated with Discontinuation of Treatment in Short-Term, Placebo-Controlled Trials
For ziprasidone-treated subjects in short-term, placebo controlled studies 5.5% (25/457) discontinued treatment due to adverse events, compared with 3.1% (7/224) on placebo. The most common events associated with dropout (> 0.5%) in the ziprasidone-treated patients were events affecting the nervous system (17/457; 3.7%), the digestive system (5/457; 1.1%), and body as a whole (4/457; 0.9%).
Adverse Events Occurring at an Incidence of 2% or more in Short-Term, Placebo-Controlled Bipolar Trials
Table 3 enumerates the incidence of treatment-emergent adverse events that occurred during therapy in bipolar patients, including only those events that occurred in 2% or more of patients treated with ziprasidone and for which the incidence in patients treated with ziprasidone was greater than the incidence in placebo-treated patients.
Commonly Observed Adverse Events in Short-Term, Placebo-Controlled Trials
In bipolar mania clinical trials, the most common adverse events associated with the use of ziprasidone (incidence of 5% or greater) and observed at a rate on ziprasidone at least twice that of placebo were somnolence, akathisia, dizziness, dystonia, and extrapyramidal syndrome.
| Table 3. Treatment-Emergent, Adverse Event Incidence in Short-Term (up to 3 weeks), Placebo-Controlled Trials - Bipolar Mania | ||||||
|---|---|---|---|---|---|---|
| Body System and COSTART Preferred Term | Ziprasidone (n=457) | Placebo (n=224) | ||||
| Body as a whole | ||||||
| Headache | 67 (14.7%) | 31 (13.8%) | ||||
| Asthenia | 21 (4.6%) | 3 (1.3%) | ||||
| Pain | 15 (3.3%) | 5 (2.2%) | ||||
| Accidental Injury | 14 (3.1%) | 3 (1.3%) | ||||
| Cardiovascular | ||||||
| Hypertension | 10 (2.2%) | 3 (1.3%) | ||||
| Digestive | ||||||
| Nausea | 32 (7.0%) | 13 (5.8%) | ||||
| Dyspepsia | 30 (6.6%) | 11 (4.9%) | ||||
| Constipation | 25 (5.5%) | 11 (4.9%) | ||||
| Diarrhea | 17 (3.7%) | 7 (3.1%) | ||||
| Vomiting | 17 (3.7%) | 5 (2.2%) | ||||
| Tooth Disorder | 17 (3.7%) | 5 (2.2%) | ||||
| Dry mouth | 16 (3.5%) | 6 (2.7%) | ||||
| Increased salivation | 12 (2.6%) | 1 (0.4%) | ||||
| Nervous | ||||||
| Somnolence | 104 (22.8%) | 19 (8.5%) | ||||
| Extrapyramidal Syndrome | 62 (13.6%) | 11 (4.9%) | ||||
| Akathisia | 59 (12.9%) | 10 (4.5%) | ||||
| Dizziness | 49 (10.7%) | 9 (4.0%) | ||||
| Dystonia | 32 (7.0%) | 3 (1.3%) | ||||
| Tremor | 23 (5.0%) | 6 (2.7%) | ||||
| Hypertonia | 22 (4.8%) | 3 (1.3%) | ||||
| Agitation | 19 (4.2%) | 9 (4.0%) | ||||
| Anxiety | 17 (3.7%) | 6 (2.7%) | ||||
| Dyskinesia | 11 (2.4%) | 1 (0.4%) | ||||
| Respiratory | ||||||
| Pharyngitis | 10 (2.2%) | 1 (0.4%) | ||||
| Skin and Appendages | ||||||
| Pruritus | 15 (3.3%) | 5 (2.2%) | ||||
| Special senses | ||||||
| Abnormal vision | 18 (3.9%) | 4 (1.8%) | ||||
ECG Changes
Ziprasidone is associated with an increase in the QTc interval (see WARNINGS AND PRECAUTIONS, QT Prolongation).
Extrapyramidal Symptoms (EPS) – Bipolar Mania
The incidence of reported extrapyramidal syndrome and other EPS-related adverse events in the short-term, placebo-controlled trials was greater for ziprasidone-treated patients. Medications to treat EPS and movement disorders were allowed; but if clinically meaningful movement disorder side effects were observed by the clinician or volunteered by the subject, or if a clinically meaningful movement disorder present at screening increased in severity or required the administration of anticholinergics or propanolol, these symptoms and their severity were recorded as adverse events. EPS-related adverse events in all studies were usually mild, dose-related and reversible upon dose reduction and/or administration of antiparkinsonian medication. Objectively collected data from those trials on the Simpson Angus Rating Scale (for EPS) and the Barnes Akathisia Scale (for akathisia) did not generally show a difference between ziprasidone and placebo.
Table 4. Treatment-Emergent Extrapyramidal Symptoms Assessed by Adverse Events Incidence in Short-Term, Bipolar Mania Placebo-Controlled Trials
| Percentage of Subjects Reporting Event | |||||
| Extrapyramidal Symptoms | Ziprasidone N=457 | Placebo N=224 | |||
| Dystonic events1 | 8.3% | 1.8% | |||
| Parkinsonism events2 | 23.6% | 8.9% | |||
| Akathisia events3 | 13.1% | 4.5% | |||
| Dyskinetic events4 | 3.9% | 0.9% | |||
| Residual events5 | 0.4% | 0.9% | |||
| Any extrapyramidal event | 40.3% | 15.6% | |||
1Patients with the following COSTART terms were counted in this category: dystonia, myoclonus, oculogyric crisis, torticollis, trismus.
2Patients with the following COSTART terms were counted in this category: abnormal gait, extrapyramidal syndrome, hypertonia, hypokinesia, muscular hypertonia, tremor
3Patients with the following COSTART terms were counted in this category: akathisia, hyperkinesia
4Patients with the following COSTART terms were counted in this category: dyskinesia, paralysis, tardive dyskinesia
5Patients with the following COSTART terms were counted in this category: twitching
Less Common Clinical Trial Adverse Events (<1%) – Bipolar Disorder
All reported treatment-emergent events are included except those already listed in Table 3 or in other sections. It is important to emphasize that, although the events reported occurred during treatment with ziprasidone capsules, they were not necessarily caused by the therapy.
The adverse events are categorized by body system and listed in order of decreasing frequency according to the following definitions: frequent adverse events are those occurring in at least 1/100 patients (only those not already listed in the tabulated results from placebo-controlled trials appear in this listing); infrequent adverse events are those occurring in 1/100 to 1/1000 patients; rare events are those occurring in fewer than 1/1000 patients.
Body As A Whole - Frequent: abdominal pain, back pain, neck pain; Infrequent: chest pain, infection, abscess, face edema, fever, flu syndrome, hot flushes, allergic reaction, cellulitis, chest pain substernal, chills infection bacterial, lab test abnormal, suicidal ideation.
Cardiovascular System - Infrequent: hypotension, tachycardia, palpitation, bundle branch block, migraine, bradycardia, hemorrhage, pallor, postural hypotension, QT interval prolonged, syncope.
Digestive System - Frequent: gastritis, flatulence, tongue edema, dysphagia, anorexia; Infrequent: increased appetite, gastroenteritis, duodenitis, fecal impaction, gingivitis, gum hemorrhage, mouth ulceration, periodontitis, stomach ulcer.
Hemic and Lymphatic System - Infrequent: bruise, leukopenia.
Metabolic and Nutritional Disorders - Infrequent: edema, peripheral edema, thirst, hypocalcemia, respiratory alkalosis, SGPT increased, weight gain, weight loss.
Musculoskeletal System - Frequent: myalgia; Infrequent: arthralgia, joint disorder, leg cramps, myasthenia, bone pain, arthrosis, bone fracture accidental, myopathy, painful swelling.
Nervous System - Frequent: Insomnia, paralysis, depression, speech disorder, abnormal dreams, abnormal gait, hypesthesia, oculogyric crisis; Infrequent: manic reaction, muscular hypertonia, thinking abnormal, hypokinesia, withdrawal syndrome, bipolar affective disorder – manic, grand mal convulsion, nervousness, twitching, vertigo, amnesia, apathy, ataxia, bipolar affective disorder – depressive, confusion, delusions, depersonalization, hallucinations, hyperkinesia, manic depressive reaction, paresthesia, personality disorder, sleep disorder, torticollis, trismus.
Respiratory System - Frequent: respiratory tract infection, dyspnea, rhinitis, cough increased, respiratory disorder; Infrequent: asthma, sinusitis, bronchitis, hiccup, hypoxia.
Skin And Appendages - Frequent: rash, fungal dermatitis. Infrequent: sweating, acne, maculopapular rash, dry skin, urticaria, alopecia, dermatitis, exfoliative dermatitis, herpes simplex, skin disorder.
Special Senses - Frequent: ear pain; Infrequent:photophobia, conjunctivitis, tinnitus, ear disorder, otitis media, dry eyes, otitis externa.
Urogenital System - Frequent: vaginitis, dysmenorrhea; Infrequent: urinary frequency, polyuria, urinary tract infection, dyspareunia, female lactation, mastitis female, uterine spasm, dysuria, penile erection, urinary incontinence, anorgasmia, breast pain.
Adverse Events in Pediatrics (<18 years of age)
The safety and efficacy of GD-Ziprasidone in children under the age of 18 years have not been established and its use is not recommended (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
All of the adverse events described above for adults with bipolar disorder and schizophrenia should be considered in the case of children and adolescents taking GD-Ziprasidone. Additional adverse events of note from each of the two studies in the pediatric population, are summarized in the following tables. The listed events are those that are either i) worse in children than in adults (greater frequency rates compared to studies in adults of the same disorder, or greater difference from placebo rates, or greater severity), or ii) identified only in pediatric populations, and for which drug rates are greater than placebo.
Table 5 Adverse Events during short-term (4 weeks) treatment of children and adolescents with Bipolar Disorder (ages 10 -17 years), that were identified as worse in children compared to adults or unique to children, and greater than placebo.
| Body System and MedDRA term | Percentage of Subjects With Adverse events | |||||||
|---|---|---|---|---|---|---|---|---|
| Ziprasidone (n=149) | Placebo (n=88) | |||||||
| Eye Disorders | ||||||||
| Vision blurred | 6% | 1% | ||||||
| Gastrointestinal Disorder | ||||||||
| Nausea | 14% | 7% | ||||||
| Vomiting | 8% | 1% | ||||||
| Abdominal pain a | 13% | 7% | ||||||
| General Disorders | ||||||||
| Fatigue | 15% | 7% | ||||||
| Investigations | ||||||||
| Prolactin increased b | 11% 6 % (male) 17 % (female) | 1% 3% (male) 0 % (female) | ||||||
| Insulin increased c | 6% | 0% | ||||||
| Total neutrophils (Abs) increased d | 4% | 0% | ||||||
| Increased ALTe | 2 % | 0% | ||||||
| Increased Testosterone (females)f | 17% | 3% | ||||||
| Nervous system disorders | ||||||||
| Extrapyramidal Symptoms g | 30% | 7% | ||||||
| Sedation, Somnolence | 56% | 14% | ||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||
| Upper respiratory tract infection | 5% | 0% | ||||||
| Psychiatric Disorders | ||||||||
| Body System and MedDRA term | Percentage of Subjects With Adverse events |
|---|
| Ziprasidone (n=149) | Placebo (n=88) | |
|---|---|---|
| Insomnia | 9% | 3% |
| Restlessness | 5% | 1% |
Includes data up to 6 days after last dose of study drug.
Subjects were counted only once per treatment in each row.
Medical Dictionary for Regulatory Activities (v14.0) coding applied
a Abdominal pain includes the following adverse reaction terms: abdominal discomfort, abdominal pain, abdominal pain upper, abdominal pain lower b Prolactin levels: >19.47 μg/L males (>1.1 ULN=17.7 μg/L); >32.12 μg/L females (>1.1 ULN=29.2 μg/L) at any time. Two subjects had an increased prolactin level greater than 60 μg/L (females, on ziprasidone, 64 ug/L and 101 ug/L).For the term prolactin, “n’ for ziprasidone = 114 and for placebo = 71
c Insulin levels: >32.4 UU/ml (>1.2 ULN=27 UU/ml) at any time. The maximum value observed was 56 UU/ml. For the term insulin, “n’ for ziprasidone = 88, and for placebo = 54
d Total neutrophils (abs) levels: > 9360 per μL (>1.2 ULN=7800 per μL ) at any time. Values ranged up to 15600 per μL For the term total neutrophils (abs), “n’ for ziprasidone = 107 and for placebo = 74
e ALT levels >3 X ULN = 30 U/L males and 20 U/L females. For the term ALT, “n” for ziprasidone = 132, and for placebo = 84.
f Testosterone: >1.2 X ULN = 40 ng/dL and >1.2 X baseline in subjects with abnormal baseline (ie, 4 of 8 females in the ziprasidone group and 1 or 1 female in the placebo group). Increased Testosterone (females), “n” for ziprasidone = 46, and for placebo = 29.
g “Extrapyramidal symptoms” includes the following adverse reaction terms: akathesia, musculoskeletal stiffness, tremor, extrapyramidal disorder, dystonia, drooling, dyskinesia, muscle twitching, tic, muscle spasms, cogwheel rigidity, gait disturbance, torticollis.
Table 6. Adverse Events during short-term (6 weeks) treatment of children and adolescents with Schizophrenia (ages 13 -17 years), that were identified as worse in children compared to adults or unique to children, and greater than placebo.
| Body System and MedDRA term | Percentage of Subjects With Adverse events | |||||||
|---|---|---|---|---|---|---|---|---|
| Ziprasidone (n=193) | Placebo (n=90) | |||||||
| Gastrointestinal Disorder | ||||||||
| Nausea | 10% | 2% | ||||||
| Vomiting | 6% | 3% | ||||||
| General Disorders | ||||||||
| Fatigue | 9% | 4% | ||||||
| Investigations | ||||||||
| Prolactin increased a | 20% 24% (male) 14% (female) | 5% 8 % (male) 0% (female) | ||||||
| Bicarbonate decreased b | 17% | 6% | ||||||
| Monocytes increased c | 7% | 2% | ||||||
| Nervous system disorders | ||||||||
| Body System and MedDRA term | Percentage of Subjects With Adverse events |
|---|
| Ziprasidone (n=193) | Placebo (n=90) | |
|---|---|---|
| Extrapyramidal Symptoms d | 25% | 7% |
| Sedation, Somnolence | 24% | 7% |
| Dizziness | 9% | 1% |
Includes data up to 6 days after last dose of study drug.
Subjects were counted only once per treatment in each row.
Medical Dictionary for Regulatory Activities (v14.0) coding applied
a Prolactin levels: >19.47 μg/L males (>1.1 ULN=17.7 μg/L); >32.12 μg/L females (>1.1 ULN=29.2 μg/L) at any time. One subject had an increased prolactin level greater than 60 μg/L (female, on ziprasidone, 98.3 ug/L). For the term prolactin increased, “n’ for ziprasidone = 50 and for placebo = 20 b Bicarbonate levels: < 19.8 mEq/L (<0.9 LLN= 22 per μL ) at any time. Lowest observed ziprasidone value was 15 mEq/L. For the term bicarbonate decreased, “n’ for Z ziprasidone = 95 and for placebo = 49
c Monocyte levels: > 11% (>1.2 ULN=9-10%) at any time. Highest observed ziprasidone value was 17%. For the term monocytes increased, “n’ for ziprasidone = 172 and for placebo = 84
d “Extrapyramidal symptoms” includes the following adverse reaction terms: gait disturbance, muscle rigidity, muscle spasms, muscle twitching, torticollis, musculoskeletal stiffness, akathisia, drooling, dyskinesia, dystonia, extrapyramidal disorder, hypokinesia, parkinsonian rest tremor, tremor, masked facies.
Weight Gain in Children and Adolescents:
In one 4-week, placebo-controlled trial in child and adolescent patients (10-17 years of age) with bipolar disorder, the mean increase in body weight was 0.7 kg in the ziprasidone group and 0.8 kg in the placebo group. Of ziprasidone treated patients, 6.9 % gained ≥ 7% of their bodyweight, compared to 3.7% of placebo-treated patients.
In the open-label study that enrolled patients from the above bipolar trial, 41% of patients (67/169) completed 26 weeks of therapy with ziprasidone. After 26 weeks of treatment, the mean increase in body weight was 3.9 kg, and 30% of the patients gained ≥ 7% of their body weight in completers, not adjusted for normal growth. In order to adjust for normal growth over 26 weeks, an increase of at least 0.5 standard deviation from baseline in BMI Z-score was used as a measure of a clinically significant change; 16% of patients on ziprasidone met this criterion after 26 weeks of treatment.
In one 6-week, placebo-controlled trial in adolescent patients (13-17 years of age) with schizophrenia, the mean change in body weight was -0.1 kg in the ziprasidone group and 0.0 kg in the placebo group. Of ziprasidone treated patients 4 % gained > 7% of their bodyweight, compared to 0% of placebo-treated patients.
In the open-label study that enrolled patients from the above schizophrenia trial, 34% of patients (76/221) completed 26 weeks of therapy with ziprasidone, and 13 % of the patients gained ≥ 7% of their body weight, not adjusted for normal growth After 26 weeks of treatment, the mean increase in body weight was 1.7 kg. In order to adjust for normal growth over 26 weeks an increase of at least 0.5 standard deviation from baseline in BMI Z-score was used as a measure of a clinically significant change; 8% of patients on ziprasidone met this criterion after 26 weeks of treatment.
Extrapyramidal Symptoms (EPS) in Children and Adolescent Population:
The pediatric EPS data are from one short-term placebo controlled, monotherapy study in each of bipolar patient population (4 week duration; 10-17 years of age) and schizophrenic population (6 week duration; 13-17 years of age). Across the two placebo-controlled studies, the incidences of adverse events potentially related to EPS showed a greater differential between ziprasidone and placebo compared to trials of adults with these indications (Incidence of EPS on ziprasidone was 30% and 25% for bipolar and schizophrenia respectively, compared to 7% for placebo in both studies). The identified events included akathisia, drooling, dyskinesia, dystonia, gait disturbance, extrapyramidal disorder, muscle spasms/twitching, musculoskeletal stiffness, tremor, and torticollis.
Bipolar Open-label Data: In the 26-week open label extension study, a total of 18% (29 /162)experienced EPS during that period. All reported EPS events were of mild or moderate severity. Of the subjects experiencing EPS 21 % (6/29) had dose reductions, and 7% (2/29) were discontinued from drug. In the pediatric bipolar patient population, EPS events of note in addition to those mentioned above include: tic, cogwheel rigidity, restless legs syndrome, and dysarthria.
Schizophrenia Open-label Data: In the 26-week, open label extension study that enrolled subjects from the placebo-controlled schizophrenia trial, a total of 15% (34/221) experienced EPS during that period. Of these, 8% (3 /34) experienced an EPS event as severe. Of the subjects experiencing EPS 30% (10 /34) had dose reductions, and none were discontinued from drug. In the schizophrenia patient population, EPS events of note in addition to the aggregated events listed above include: tardive dyskinesia, restless legs syndrome, masked facies and oculogyric crisis.
While the majority of extrapyramidal adverse events resolved within the duration of each study period, there were cases in which the events remained unresolved at the end of both the controlled and open-label trials.
QTc Prolongation Effects
Ziprasidone was associated with a mild to moderate dose-related prolongation of the QT interval in the pediatric bipolar and schizophrenia clinical trials. There are insufficient data to determine whether this population is more vulnerable than adults to QT prolongation effects from ziprasidone.
Laboratory Abnormalities
The laboratory abnormalities observed during the double-blind phase of the two pediatric studies are presented in Tables 5 and 6 (bipolar mania and schizophrenia respectively). Of note in the open-label phases, an ALT value of 763 U/L was observed in a patient , along with akathesia and fatigue, and an elevated AST value. No follow-up information is available. Decreased bicarbonate was reported at 32% (44/136) in the open-label bipolar study, and 23% (47/ 201) in the open-label schizophrenia study. Increased prolactin was reported at 7% (10/134) and 20% (17 /86) respectively. One subject in the open-label schizophrenia study had an adverse event of increased prolactin of moderate severity.
Suicide-Related Events:
In the ziprasidone pediatric studies, periodic searches were conducted of the adverse event database of each study to identify all possibly suicide-related adverse events (PSRAEs). These were reviewed by a blinded independent panel of experts and classified according to the C-CASA suicidality classification system (Columbia Classification Algorithm for Suicide Assessment) The incidence rates below exclude events classified as overdose due to dosing error.
In one 4-week, placebo-controlled trial in child and adolescent patients (10-17 years of age) with bipolar disorder, the incidence of PSRAEs was 5.4% (8/149) for ziprasidone and 5.9% (5/88) for placebo. In the 26-week, open-label study that enrolled patients from the above trial (N=162), the incidence of PSRAEs was 9.3% (15/162).
In one 6-week, placebo-controlled trial in adolescent patients (13-17 years of age) with schizophrenia, the incidence of PSRAEs was 2.3% (5/193) for ziprasidone and 2.2% (2/90) for placebo. In the 26-week, open-label study that enrolled patients from the above trial (N=221). The incidence of PSRAEs was 4.1% (9/221).There was one completed suicide (a 17 year old female with a diagnosis of schizophrenia, disorganized type, receiving 160 mg ziprasidone).
The safety and efficacy of GD-Ziprasidone in children under the age of 18 years have not been established and its use is not recommended.
Post-Market Adverse Drug Reactions
Adverse event reports not listed above that have been received from spontaneous post-marketing reports for ziprasidone since market introduction are shown below (no causal relationship with ziprasidone has been established).
Cardiac Disorders: Tachycardia, torsades de pointes (in the presence of multiple confounding factors - see WARNINGS AND PRECAUTIONS, QT Prolongation);
Gastrointestinal Disorders: Dysphagia, swollen tongue, severe constipation (see WARNINGS AND PRECAUTIONS, Gastrointestinal).
Hemic and Lymphatic System - neutropenia, granulocytopenia and agranulocytosis.
Immune System Disorders: Allergic reaction;
Metabolic and Nutritional Disorders: diabetic coma, lipids abnormal
Nervous System Disorders: Facial droop, neuroleptic malignant syndrome, serotonin syndrome (alone or in combination with serotonergic medicinal products), tardive dyskinesia;
Psychiatric Disorders: Insomnia, mania/hypomania;
Renal and Urinary Disorders: Enuresis, urinary incontinence;
Reproductive System and Breast Disorders: Galactorrhea, priapism;
Skin and subcutaneous Tissue Disorders: Angioedema, rash; Stevens Johnson Syndrome, Drug reaction with eosinophilia and systemic symptoms (DRESS);
Vascular Disorders: Postural hypotension, syncope.
Sleep-related Disorders: Atypical antipsychotic drugs, including ziprasidone, have been reported with cases of sleep apnoea, with or without concomitant weight gain. In patients who have a history of or are at risk for sleep apnoea, GD-Ziprasidone should be prescribed with caution.
Risks of somnambulism (sleep walking) and sleep-related eating disorder have been reported with the use of atypical antipsychotics including ziprasidone.
DRUG INTERACTIONS
Overview
Drug-drug interactions can be pharmacodynamic (combined pharmacologic effects) or pharmacokinetic (alteration of plasma levels). The risks of using ziprasidone in combination with other drugs have been evaluated as described below. Based upon the pharmacodynamic and pharmacokinetic profile of ziprasidone, possible interactions could be anticipated:
Pharmacodynamic Interactions
- 1. Ziprasidone should not be used with any drug that prolongs the QT interval (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
- 2. Given the primary CNS effects of ziprasidone, caution should be used when it is taken in combination with other centrally acting drugs.
- 3. Because of its potential for inducing hypotension, ziprasidone may enhance the effects of certain antihypertensive agents.
- 4. Ziprasidone may antagonize the effects of levodopa and dopamine agonists.
Pharmacokinetic Interactions
Drug-Drug Interactions
Effect of Other Drugs on Ziprasidone
Ketoconazole
Ketoconazole, a potent inhibitor of CYP3A4, at a dose of 400 mg per day for 5 days, increased the AUC and Cmax of ziprasidone (80 mg BID) by approximately 35-40%. The serum concentration of S-methyl-dihydroziprasidone, at the expected Tmax of ziprasidone, was increased by 55% during ketoconazole treatment. No additional QTc prolongation was observed. Other potent inhibitors of CYP3A4 would be expected to have similar effects.
Coadministration of potent CYP3A4 inhibitors has the potential of increasing ziprasidone serum concentrations. The clinical importance of this potential has not been clearly defined.
Carbamazepine
Carbamazepine is an inducer of CYP3A4; administration of 200 mg BID for 25 days resulted in a decrease of approximately 36% in the AUC of ziprasidone (20 mg BID). This effect may be greater when higher doses of carbamazapine are administered.
Valproate, Lamotrigine
Ziprasidone has not been studied for drug interaction with valproate or lamotrigine.
Cimetidine
Cimetidine at a dose of 800 mg QD for 2 days did not affect pharmacokinetics of ziprasidone (single 40 mg dose).
Antacids
The coadministration of 30 mL of MAALOX® with ziprasidone (single 40 mg dose) did not affect the pharmacokinetics of ziprasidone.
Benztropine, Propranolol, or Lorazepam
Population pharmacokinetic analysis of schizophrenic patients enrolled in controlled clinical trials has not revealed evidence of clinically significant pharmacokinetic interaction with benztropine, propranolol, or lorazepam.
Effect of ziprasidone on Other Drugs
Summary re: Potential for Effect on Cytochrome P450
In vitro studies revealed little potential for ziprasidone to interfere with the metabolism of drugs cleared primarily by CYP1A2, CYP2C9, CYP2C19, CYP2D6 and CYP3A4. Consistent with these in vitro results, studies in normal healthy volunteers showed that ziprasidone did not alter the metabolism of dextromethorphan, a CYP2D6 model substrate, nor of ethinyl estradiol, a CYP3A4 substrate. Thus, ziprasidone is unlikely to cause clinically important drug interactions mediated by these enzymes (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Protein Binding
The in vitro plasma protein binding of ziprasidone was not altered by warfarin or propranolol, two highly protein-bound drugs, nor did ziprasidone alter the binding of these drugs in human plasma. Thus, the potential for drug interactions with ziprasidone due to displacement appears to be minimal.
Dextromethorphan
Consistent with in vitro results, a study in normal healthy volunteers showed that ziprasidone did not alter the metabolism of dextromethorphan, a CYP2D6 model substrate, to its major metabolite, dextrorphan. There was no statistically significant change in the urinary dextromethorphan/dextrorphan ratio.
Oral Contraceptives
Ziprasidone, at a dose of 20 mg BID, did not affect the pharmacokinetics of concomitantly administered oral contraceptives, ethinylestradiol (0.03 mg), a CYP3A4 substrate, or levonorgestrel (0.15 mg) progesterone components.
Lithium
Ziprasidone, at a dose of 40 mg BID, administered concomitantly with lithium at a dose of 450 mg BID for 7 days did not affect the steady-state level or renal clearance of lithium.
As ziprasidone and lithium are associated with cardiac conduction changes, the combination may pose a risk for pharmacodynamic interaction, including arrhythmias.
CNS Drugs/Alcohol - Given the primary CNS effects of ziprasidone, caution should be used when it is taken in combination with other centrally acting drugs, including alcohol.
Drug-Food Interactions
The absorption of ziprasidone is increased up to two-fold in the presence of food.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
Smoking
Based on in vitro studies utilizing human liver enzymes, ziprasidone is a substrate for CYP1A2, however, the contribution of this pathway is minor. Consistent with these in vitro results, population pharmacokinetic evaluation has not revealed any significant differences in ziprasidone pharmacokinetics between smokers and nonsmokers.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The absorption of ziprasidone is increased up to two-fold in the presence of a meal. Ziprasidone (ziprasidone hydrochloride) should be administered with a meal. See also: WARNINGS and PRECAUTIONS, QT Prolongation, Recommendations regarding Risk Factors for QTc Prolongation.
Recommended Dose and Dosage Adjustment
Schizophrenia
Initial Treatment
GD-Ziprasidone may be administered at an initial daily dose of 40 mg BID with a meal. However, individual patients may benefit from an initial dose of 20 mg BID. Daily dosage may subsequently be adjusted on the basis of clinical status up to 80 mg BID. Dosage adjustments, if indicated, should generally occur at intervals of not less than 2 days, since steady-state is achieved within 1 to 3 days.
Efficacy in schizophrenia was studied in a dose range of 20 to 100 mg BID in short-term, placebo-controlled clinical trials. There were trends toward dose response within the range of 20 to 80 mg BID, but results were not consistent. An increase to a dose greater than 80 mg BID is not generally recommended. The safety of doses above 100 mg BID has not been systematically evaluated in clinical trials.
Maintenance Treatment
It is recommended that responding patients with schizophrenia be continued on GD-Ziprasidone at the lowest dose needed to maintain remission. The efficacy of ziprasidone 20, 40, or 80 mg BID in maintenance treatment has been established over a 12-month treatment period.
Patients should be periodically reassessed to determine the need for maintenance treatment. While there is no body of evidence available to answer the question of how long the patient should be treated with GD-Ziprasidone, the effectiveness of maintenance treatment is well established for many other antipsychotic drugs.
Bipolar Disorder
Bipolar Mania
Initial Treatment
Oral ziprasidone should be administered at an initial daily dose of 40 mg BID with a meal. The dose should then be increased to 60 mg or 80 mg BID on the second day of treatment and subsequently adjusted on the basis of toleration and efficacy within the range 40-80 mg BID. In the flexible-dose clinical trials, the mean daily dose administered was approximately 120 mg.
Maintenance Treatment
There is no body of evidence available from controlled trials to guide a clinician in the longer-term management of a patient who improves during treatment of mania with ziprasidone. While it is generally agreed that pharmacological treatment beyond an acute response in mania is desirable, both for maintenance of the initial response and for prevention of new manic episodes, there are no systematically obtained data to support the use of ziprasidone in such longer-term treatment (i.e., beyond 3 weeks).
Dosage in Special Populations
Dosage adjustments are generally not required on the basis of age, gender, race, or renal impairment.
Geriatrics (>65 years old)
Given the greater sensitivity of this population, a lower starting dose, slower titration, and careful monitoring during the initial dosing period may be considered for elderly patients when clinical factors warrant (see WARNINGS AND PRECAUTIONS-Special Populations, Geriatrics).
GD-Ziprasidone is not indicated for treatment of elderly patients with dementia (see WARNINGS AND PRECAUTIONS - Serious Warnings and Precautions).
Hepatic Impairment
Lower doses should be considered for hepatic insufficiency, considering that <1% of ziprasidone is cleared renally, and there is a lack of experience with ziprasidone in patients with severe hepatic impairment.
Missed Dose
The missed dose should be taken at the next scheduled dose. Doses should not be doubled.
OVERDOSAGE
Symptoms
In premarketing trials, accidental or intentional overdosage of ziprasidone was documented in 10 patients. All of these patients survived without sequelae. In the patient taking the largest confirmed amount, 3240 mg, the only symptoms reported were minimal sedation, slurring of speech, and transitory hypertension (200/95).
In post-marketing use, the most common adverse events reported in association with ziprasidone overdose generally included extrapyramidal symptoms, somnolence, tremor, and anxiety. Hypertension, hypotension, diarrhea, tachycardia, and prolongation of the QTc and QRS intervals have also been reported.
Treatment
There is no specific antidote to ziprasidone, and it is not dialyzable. The possibility of multiple drug involvement should be considered.
In case of acute overdosage, establish and maintain an airway and ensure adequate oxygenation and ventilation. Intravenous access should be established and gastric lavage (after intubation, if patient is unconscious) and administration of activated charcoal together with a laxative should be considered. The possibility of obtundation, seizure, or dystonic reaction of the head and neck following overdose may create a risk of aspiration with induced emesis.
Cardiovascular monitoring should commence immediately and should include continuous electrocardiographic monitoring to detect possible arrhythmias. If antiarrhythmic therapy is administered, disopyramide, procainamide, and quinidine carry a theoretical hazard of additive QT-prolonging effects that might be additive to those of ziprasidone.
Hypotension and circulatory collapse should be treated with appropriate measures such as intravenous fluids. If sympathomimetic agents are used for vascular support, epinephrine and dopamine should not be used, since beta stimulation combined with α1-antagonism associated with ziprasidone may worsen hypotension. Similarly, it is reasonable to expect that the alpha-adrenergic-blocking properties of bretylium might be additive to those of ziprasidone, resulting in problematic hypotension.
In cases of severe extrapyramidal symptoms, anticholinergic medication should be administered.
Close medical supervision and monitoring should continue until the patient recovers.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
GD-Ziprasidone (ziprasidone hydrochloride) is an atypical antipsychotic agent for oral administration.
Mechanism of Action
The mechanism of action of ziprasidone, as with other drugs having efficacy in schizophrenia, is unknown. However, it has been proposed that the efficacy of this drug in schizophrenia is mediated through a combination of dopamine type 2 (D2) and serotonin type 2 (5HT2) antagonism.
Antagonism at receptors other than dopamine and 5HT2 with similar receptor affinities may explain some of the other therapeutic and side effects of ziprasidone. Antagonism of histamine H1 receptors may explain the somnolence observed with ziprasidone. Antagonism of α1-adrenergic receptors may explain the orthostatic hypotension observed with ziprasidone.
Pharmacodynamics
Ziprasidone exhibited high in vitro binding affinity for the dopamine D2 and D3, the serotonin 5-HT2A, 5-HT2C, 5-HT1A, 5-HT1D, and α1-adrenergic receptors (Ki = 4.8, 7.2, 0.4, 1.3, 3.4, 2, and 10 nM, respectively), and moderate affinity for the histamine H1 receptor (Ki=47 nM). Ziprasidone functioned as an antagonist at the D2, 5-HT2A, and 5-HT1D receptors, and as an agonist at the 5-HT1A receptor.
Ziprasidone inhibited synaptic reuptake of serotonin and norepinephrine. No appreciable affinity was exhibited for other receptor/binding sites tested, including the cholinergic muscarinic receptor (IC50 >1 µM).
Pharmacokinetics
Overview
The multiple-dose pharmacokinetics of ziprasidone are dose-proportional within the proposed clinical dose range, and ziprasidone accumulation is predictable with multiple dosing. Steady–state is attained within 1-3 days when dosing as recommended. The mean terminal phase half-life after multiple dosing in normal volunteers and schizophrenic patients is between 6 and 10 hours, with a range of individual values from 3 to 18 hours.
Ziprasidone’s activity is primarily due to the parent drug. Ziprasidone is extensively metabolized after oral administration with only a small amount excreted in the urine (<1%) or feces (<4%) as unchanged drug. Ziprasidone is unlikely to interfere with the metabolism of drugs metabolized by cytochrome P450 enzymes.
Absorption
Following oral administration of multiple doses of ziprasidone with food, peak serum concentrations typically occur 6 to 8 hours post-dose. The absolute bioavailability of a 20 mg dose under fed conditions is approximately 60%. The absorption of ziprasidone is increased up to two-fold in the presence of food.
Distribution
Ziprasidone has a mean apparent volume of distribution of 1.5 L/kg. Twice daily dosing generally leads to attainment of steady state within 1–3 days.
Ziprasidone is greater than 99% bound to plasma proteins, binding primarily to albumin and α1-acid glycoprotein. The in vitro plasma protein binding of ziprasidone was not altered by warfarin or propranolol, two highly protein-bound drugs, nor did ziprasidone alter the binding of these drugs in human plasma. Thus, the potential for drug interactions with ziprasidone due to displacement is minimal.
Metabolism
Ziprasidone is extensively metabolized after oral administration with only a small amount excreted as unchanged drug in the urine (<1%) or feces (<4%). Unchanged ziprasidone represents about 44% of total drug-related material in serum.
Ziprasidone is primarily cleared via three metabolic routes (one route begins with reduction, the other two with oxidation) to yield four major circulating metabolites: S-methyldihydroziprasidone, via reduction then methylation, and benzisothiazolepiperazine (BITP) sulphoxide, BITP-sulphone, and ziprasidone sulphoxide via oxidation routes.
Based on in vivo abundance of excretory metabolites, approximately two-thirds of ziprasidone metabolic clearance is mediated via reduction and methylation to generate S-methyldihydroziprasidone, while cytochrome P450-catalyzed oxidation mediates less than one third of ziprasidone clearance.
In vitro studies using human liver subcellular fractions indicate that the metabolite S-methyldihydroziprasidone is generated in two steps: the reduction reaction is mediated by aldehyde oxidase and potentially also by glutathione, while the subsequent methylation is mediated by thiol methyltransferase. There are no known clinically relevant inhibitors or inducers of aldehyde oxidase. In vitro studies using human liver microsomes and recombinant enzymes indicate that CYP3A4 is the major CYP contributing to the two routes of oxidative metabolism of ziprasidone. CYP1A2 may contribute to a much lesser extent.
Excretion
The mean terminal phase half-life after multiple dosing in normal volunteers and schizophrenic patients is between 6 and 10 hours, with a range of individual values from 3 to 18 hours. Approximately 20% of ziprasidone dose is excreted in the urine, with approximately 66% being eliminated in the feces. S-methyldihydroziprasidone is mainly eliminated by biliary excretion and CYP3A4 metabolism. The sulphoxide is eliminated through renal excretion and by secondary metabolism catalyzed by CYP3A4.
Special Populations and Conditions
Pediatrics
Safety and efficacy of GD-Ziprasidone in children have not been established.
Age and Gender
In a multiple-dose (8 days of treatment) study involving n=32 subjects, there was no difference in the pharmacokinetics of ziprasidone between men and women or between elderly (>65 years) and young (18 to 45 years) subjects. Additionally, population pharmacokinetic evaluation of patients in controlled trials has revealed no evidence of clinically significant age or gender-related differences in the pharmacokinetics of ziprasidone. Dosage modifications for age or gender are, therefore, not recommended.
Race
No specific pharmacokinetic study was conducted to investigate the effects of race. Population pharmacokinetic evaluation has revealed no evidence of clinically significant race-related differences in the pharmacokinetics of ziprasidone. Dosage modifications for race are, therefore, not recommended.
Hepatic Insufficiency
As ziprasidone is cleared substantially by the liver, the presence of hepatic impairment would be expected to increase the AUC of ziprasidone; a multiple-dose study at the lowest therapeutic dose of 20 mg BID for 5 days in subjects with clinically significant (Childs-Pugh Class A and B) cirrhosis (n=13) revealed an increase in AUC0-12 of 19% and 34% respectively, compared to a matched control group (n=13). A half-life of 7.1 hours was observed in subjects with cirrhosis compared to 4.8 hours in the control group. The effect of liver impairment on the serum concentrations of the metabolites is unknown.
Renal Insufficiency
Because ziprasidone is highly metabolized with less than 1% of the drug excreted unchanged, renal impairment alone is unlikely to have a major impact on the pharmacokinetics of ziprasidone. The pharmacokinetic characteristics of ziprasidone following 8 days of treatment with 20 mg BID were similar among subjects with varying degrees of renal impairment (n=27), and subjects with normal renal function (n=9), indicating that dosage adjustment based upon the degree of renal impairment is not required. Ziprasidone is not removed by hemodialysis.
STORAGE AND STABILITY
Store at controlled room temperature between 15-30ºC.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Opaque hard gelatin capsules contain ziprasidone hydrochloride, monohydrate equivalent to 20, 40, 60 and 80 mg of ziprasidone. The non-medicinal ingredients include: lactose monohydrate, pregelatinized starch, magnesium stearate.
All capsule strengths (20 mg, 40 mg, 60 mg and 80 mg) are available in 6 blister cards of 10 capsules each (60 capsules per carton). 20 mg capsules are supplied as size #4 blue/white hard gelatin capsules, imprinted in black with “Pfizer” and “ZDX 20". 40 mg capsules are supplied as size #4 blue/blue hard gelatin capsules, imprinted in black with “Pfizer” and “ZDX 40". 60 mg capsules are supplied as size #3 white/white hard gelatin capsules, imprinted in black with “Pfizer” and “ZDX 60". 80 mg capsules are supplied as size #2 blue/white hard gelatin capsules, imprinted in black with “Pfizer” and “ZDX 80".
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ziprasidone hydrochloride, monohydrate (U.S.A.N.)
Ziprasidone (I.N.N.)
Chemical name: 5-[2-[4-(1,2-benzisothiazol-3-yl)-1-piperazinyl]ethyl]-6-chloro-1,3-dihydro-2H-indol-2-one, monohydrochloride, monohydrate
Molecular formula: C21H21Cl N4 OS·HCl·H2O
Molecular mass: 467.42
Structural formula:
Physicochemical properties:
Description: White/slightly pink powder slightly soluble in dimethylsulfoxide and methanol, very slightly soluble in water, and practically insoluble in acetone, methylene chloride, hexane, isopropanol, 0.01 N hydrochloric acid and 0.1 N sodium hydroxide.
pKa: Apparent pKa = 6.68; (determination performed in DMSO: H20, 4:1, v/v).
Melting Point: decomposition at 318ºC by DSC.
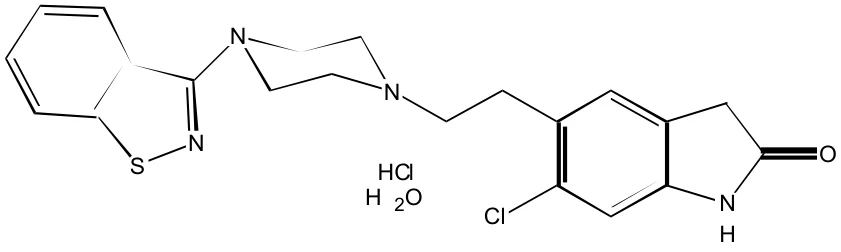
CLINICAL TRIALS
Schizophrenia Trials
The efficacy of oral ziprasidone (ziprasidone hydrochloride) in the treatment of schizophrenia was established in 4 short-term (4- to 6-week) and 1 long-term (52-week) placebo-controlled trials of psychotic inpatients who met DSM-III-R criteria for schizophrenia. Each study included 2-3 fixed doses of ziprasidone as well as placebo. Four (4) of the 5 trials were able to distinguish ziprasidone from placebo; 1 short-term study did not. Although a single fixed-dose haloperidol arm was included as a comparative treatment in 1 of the 3 short-term trials, this single study was inadequate to provide a reliable and valid comparison of ziprasidone and haloperidol.
Several instruments were used for assessing psychiatric signs and symptoms in these studies, among them the Brief Psychiatric Rating Scale (BPRS) and the Positive and Negative Syndrome Scale (PANSS), both multi-item inventories of psychopathology traditionally used to evaluate the effects of drug treatment in psychosis. The BPRS psychosis cluster (conceptual disorganization, hallucinatory behaviour, suspiciousness, and unusual thought content) is considered a particularly useful subset for assessing actively psychotic schizophrenic patients. A second traditional assessment, the Clinical Global Impression (CGI), reflects the impression of a skilled observer, fully familiar with the manifestations of schizophrenia, about the overall clinical state of the patient. In addition, the Scale for the Assessment of Negative Symptoms (SANS) was employed in some clinical trials.
The results of the trials are as follows:
- 1. In a 4-week, placebo-controlled trial (n=139) comparing 2 fixed doses of ziprasidone (20 and 60 mg BID) with placebo, only the 60 mg BID dose was superior to placebo, on the BPRS total score and the CGI-S score. This higher dose group was not superior to placebo on the BPRS psychosis cluster or on the SANS.
- 2. In a 6-week, placebo-controlled trial (n=302) comparing 2 fixed dose of ziprasidone (40 and 80 mg BID) with placebo, both dose groups were superior to placebo on the BPRS total score, the BPRS psychosis cluster score, the CGI severity score, and the PANSS total and negative subscale scores. Although the 80 mg BID dose group has a numerically greater effect than 40 mg BID dose group, the difference was not statistically significant.
- 3. In a 6-week, placebo-controlled trial (n=419) comparing 3 fixed doses of ziprasidone (20, 60 and 100 mg BID) with placebo, all three dose groups were superior to placebo on the PANSS total score, the BPRS total score, the BPRS psychosis cluster, and the CGI-S. Only the 100 mg BID dose group was superior to placebo on the PANSS negative subscale score. There was no clear evidence for a dose-response relationship within the 20 mg BID and 100 mg BID dose range.
- 4. In a 4-week, placebo-controlled trial (n=200) comparing 3 fixed doses of ziprasidone (5, 20 and 40 mg BID), none of the dose groups was statistically superior to placebo on any outcome of interest.
- 5. A double-blind, randomized, parallel-group study was conducted in n=294 symptomatically stable inpatients with DSM-III-R diagnosis of chronic schizophrenia, who had been hospitalized for a period of not less than 2 months at study entry. Patients were randomized to 1 of 3 fixed doses of ziprasidone (20, 40, or 80 mg BID) or placebo and followed for 52 weeks. Patients were observed for “impending psychotic relapse”, defined as 2 consecutive study visit assessments showing a score of >6 (much worse or very much worse) on the CGI-improvement scale, and/or a score of >6 (moderately severe) on the hostility or uncooperativeness items of the PANSS. Ziprasidone was significantly superior to placebo in both time to relapse and rate of relapse, with no significant difference between the different dose groups.
There were insufficient data to examine population subsets based on age and race. Examination of population subsets based on gender did not reveal any differential responsiveness.
An analysis of the effect of ziprasidone on patients with clinically significant depressive symptoms (Montgomery-Asberg Depression Rating Scale, MADRS) >14 was conducted in 2 multicentre, placebo-controlled studies in acute schizophrenia. A statistically significant improvement versus placebo (p<0.05) in the MADRS was observed in patients receiving ziprasidone 60 mg twice daily (n=32) in one study and 80 mg twice daily (n=56) in another study. The validity of this scale in patients with schizophrenia however is not established.
Bipolar Disorder Trials
Bipolar Mania
The short-term efficacy of oral ziprasidone in treatment of manic or mixed episodes associated with bipolar disorder, with or without psychotic features was established in 3 studies. The doses used in these studies reflect those approved for the treatment of schizophrenia.
Primary rating instruments used for assessing manic symptoms in these trials were: (1) the Mania Rating Scale (MRS), which is derived from the Schedule for Affective Disorders and Schizophrenia-Change Version (SADS-CB) with items grouped as the Manic Syndrome subscale (elevated mood, less need for sleep, excessive energy, excessive activity, grandiosity), the Behavior and Ideation subscale (irritability, motor hyperactivity, accelerated speech, racing thoughts, poor judgment) and impaired insight; and (2) the Clinical Global Impression – Severity of Illness Scale (CGI-S), which was used to assess the clinical significance of treatment response.
The results of the trials are as follows:
In a 3-week, double-blind, placebo-controlled, randomized trial (n=210) the dose of ziprasidone was 40 mg BID on Day 1 and 80 mg BID on Day 2. Titration within the range of 40-80 mg BID (in 20 mg BID increments) was permitted for the duration of the study. Ziprasidone was significantly more effective than placebo in reduction of MRS total score and the CGI-S score. The ziprasidone group demonstrated statistically significant improvement by Day 2 (SADS-CB-derived MRS) or Day 4 (CGI-S) of double-blind treatment. The mean daily dose of ziprasidone in this study was 132 mg.
In a 3-week, double-blind, placebo-controlled flexible dosing study (n=205, ziprasidone was initiated at 40 mg BID and could be adjusted by a maximum of 40 mg/day starting on Day 2, within the range of 40 to 80 mg BID. Ziprasidone was significantly superior to placebo in reduction of the SADS-CB derived MRS total score. Statistically significant improvement was apparent at the earliest timepoint assessed (Day 2) and was maintained from Day 7 to endpoint (Day 21 or early discontinuation). The mean daily dose of ziprasidone during this study was 112 mg.
A 3-week placebo-controlled and active comparator acute treatment plus a 9-week active comparator phase, double-blind, double-dummy, randomized trial, compared ziprasidone (n=444) to placebo in the treatment of mania at Week 3 and evaluated maintenance of effect for ziprasidone (40-80mg BID) and haloperidol (4-15 mg BID) at Week 12. Ziprasidone was superior to placebo in analyses of mean change from baseline to Week 3 on the MRS. The effect of ziprasidone was significant as early as Day 2. The responder rate (at least 50% decrease in MRS from baseline) at week 3 was significantly higher in the ziprasidone group (36.9%) compared to the placebo group. The mean daily dose of drug for all days of treatment was 121 mg.
DETAILED PHARMACOLOGY
ANIMAL
Pharmacodynamics
Ziprasidone exhibits potent effects in preclinical assays predictive of antipsychotic activity. While the compound was found to be a dopamine antagonist in vitro and in vivo, its most potent action is antagonism of serotonin 5-HT2A receptors, where its affinity was an order of magnitude greater than that observed for dopamine D2 receptor sites. In vivo, ziprasidone antagonized 5-HT2A receptor agonist-induced head twitch with six-fold higher potency than was required to block d-amphetamine-induced hyperactivity, a measure of central D2 receptor antagonism which is predictive of antipsychotic efficacy. Ziprasidone also had high affinity for the 5-HT1A (agonist), 5-HT1D (antagonist), and 5-HT2C (antagonist) serotonin receptor subtypes, and blocked the neuronal reuptake of norepinephrine and serotonin with moderate affinity. Ziprasidone was found to enhance the release of dopamine in rat prefrontal cortex.
The potential for antipsychotic efficacy without severe motor side effects is supported by the relatively weak potency of ziprasidone to produce catalepsy in animals, contrasted with its potent antagonism of conditioned avoidance responding and dopamine receptor agonist-induced locomotor activation and stereotypy.
In addition to the animal studies of antipsychotic efficacy and mechanism of action, a general pharmacological evaluation of ziprasidone was conducted to obtain a more extensive characterization of its actions on various organ systems in vitro and in vivo. In general, ziprasidone was well tolerated in animals at doses that produced effective dopamine receptor antagonism in the brain. Cardiovascular changes in dog were limited to mild increases in heart rate after oral doses of ziprasidone that achieved 2- to 4-fold higher plasma levels than the plasma Cmax associated with the maximum recommended human dose.
Respiratory function, as judged by blood gas measurements, gastrointestinal motility and renal function (24-hour), were not perturbed by effective dopamine receptor antagonist doses of ziprasidone. Like other D2 receptor antagonists, ziprasidone did not appear to act as a potent inhibitor of gastric acid secretion in pylorus ligated rats. In vitro, ziprasidone antagonized both α1-adrenoceptor and histamine H1 receptor-induced contractions in isolated guinea pig aorta and ileum, respectively. These effects occurred at concentrations at least 8-fold higher than ziprasidone’s Ki for antagonizing D2 receptors in vitro. Ziprasidone had no effects on isolated uterine smooth muscle in rat or on histamine-induced chronotropic activity in guinea pig atrial strips.
Pharmacokinetics
Oral bioavailability was generally less than 40% in mice, rats and dogs, and 60% in humans. The low oral bioavailability in animals was due to incomplete absorption of the dose as indicated by the >50% recovery of the dose in feces as unchanged drug in mice, rats and dogs administered a radiolabeled dose.
There was a 2.5- to 10-fold difference in the half-life observed in mice and rats as compared to that observed in dogs and man. This difference in half-life between rodents and non-rodent species was due to the larger volume of distribution observed in the dogs, and the lower clearance observed in both dogs and humans. In rats and dogs administered multiple doses of ziprasidone, drug exposure at the end of the study was similar to drug exposure at the start of study. Thus, there was no evidence of accumulation and/or metabolic autoinduction after multiple dosing of ziprasidone.
The serum protein binding of ziprasidone is >99% in humans, Long-Evans rats, Sprague-Dawley rats, New Zealand White rabbits and beagle dogs, and greater than 95% in CD-1 mice. In the reproductive toxicity studies in rats and rabbits administered ziprasidone, placental transfer of drug was observed. Studies in pigmented and non-pigmented rats demonstrated that the fractional retention of drug-related material in the eye was due to melanin binding (reversible).
All the metabolites observed in the excreta collected from humans were also observed in the excreta collected from mice, rats and dogs, the species in which the safety studies were conducted. In dogs, rats, mice, and humans, the percentage of circulating radioactivity identified as metabolites was approximately 83%, 50%, 81% and 54%, respectively. Ziprasidone-sulfoxide and -sulfone were the major metabolites in serum collected from all species including humans.
HUMAN
Pharmacodynamics
In normal volunteer PET studies, serum concentrations between 20 and 40 ng/mL are associated with greater than 65% D2 receptor occupancy and greater than 80% 5-HT2 receptor occupancy.
As with other drugs that antagonize D2 receptors, ziprasidone elevates prolactin levels with acute administration. In normal male volunteers, ziprasidone concentrations correlate with increasing prolactin levels. At steady-state, the magnitude of the response was decreased compared with single dose administration, and returned to baseline levels within 12 hours of dosing.
Prolactin elevations observed in both sexes are transient and minimal. These elevations are not generally sustained during chronic administration.
Pharmacokinetics
Following the administration of multiple doses of ziprasidone under fed conditions, peak serum concentrations typically occur 6 to 8 hours post-dose with steady-state attained within 1 to 3 days. Ziprasidone displays linear kinetics over the clinical dose range. Its half-life ranges from 2.9 to 18.0 hours (5th to 95th percentile; mean of 6.6 hours), and apparent systemic clearance ranges from 3.4 to 13.9 mL/min/kg (5th to 95th percentile; mean 7.5 mL/min/kg). The absolute bioavailability of a 20 mg dose under fed conditions is approximately 60%. The absorption of single oral doses of ziprasidone is increased by 100% in the presence of food. Serum concentrations and half-life do not significantly vary between individuals on the basis of gender, age, renal or hepatic status. Ziprasidone has a volume of distribution of approximately 1.5 L/kg. It is greater than 99% bound to plasma proteins, binding primarily to albumin and α1-acid glycoprotein.
Metabolism and Elimination
Following a single oral dose of 14C/3H-labeled ziprasidone, only a small amount (<1%) was excreted unchanged in the urine. Approximately 20% of the dose is excreted in the urine, with approximately 66% being eliminated in the feces. Unchanged ziprasidone represents about 44% of total drug-related material in serum.
Based on in vivo abundance of excreted metabolites, approximately two-thirds of ziprasidone is metabolized via reduction by aldehyde oxidase. There are no known clinically relevant inhibitors or inducers of aldehyde oxidase. Less than one-third of ziprasidone metabolic clearance is mediated by cytochrome P450 catalyzed oxidation.
In vitro studies using human liver microsomes and recombinant enzymes indicate that CYP3A4 is the major CYP contributing to the oxidative metabolism of ziprasidone. CYP1A2 may contribute to a much lesser extent.
Effect on Cytochrome P450
In vitro studies utilizing human liver microsomes showed that ziprasidone has little potential to inhibit CYP1A2, CYP2C9, CYP2C19, CYP2D6 and CYP3A4. Thus, ziprasidone is unlikely to cause clinically important drug interactions mediated by these enzymes. Consistent with these in vitro results, studies in normal healthy volunteers showed that ziprasidone did not alter the metabolism of dextromethorphan, a CYP2D6 model substrate, to its major metabolite, dextrorphan, and did not alter the pharmacokinetics of ethinyl estradiol, a CYP3A4 substrate.
TOXICOLOGY
Acute Toxicity - Mice and rats
SPECIES (# of animals) | SEX | ROUTE | LD50 base/mg/kg (95% C.I.) | Range of Lethal Doses base/mg/kg | |
| No Deaths | All Dead | ||||
Albino Mice (3) | M | Oral | >2 000 | 500* | ND |
Albino Mice (3) | F | Oral | >2 000 | 2 000 | ND |
S-D Rats (3) | M | Oral | >2 000 | 2 000 | ND |
S-D Rats (3) | F | Oral | >2 000 | 2 000 | ND |
Albino Mice (3) | M | IP | 500-1 000 | 500 | 1 000 |
S-D Rats (3) | M | IP | >2 000 | 2 000 | ND |
* The death of one of 3 animals dosed at 2000 mg/kg was probably the result of injury from fighting and not compound-related. IP = Intraperitoneal ND = Not determined | |||||
Description of findings
CP-88,059-1 has a low order of acute toxicity in mice and rats when given either orally or intraperitoneally. No definitive target organs of toxicity were identified, however, clinical signs indicative of CNS effects were produced (especially sedation). Clinical signs included decreased activity and respiration, ptosis and ataxia. Generally within one hour of dosing, the animals became weak, assumed a stationary, prone position, and were barely able to move. Their respiration often became shallow, and several animals were prostrate or nearly prostrate.
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
|---|---|---|---|---|---|
| Chronic Toxicity | |||||
| CD-1 Mice | Oral (diet) | 0 10 40 40 100 100 200 200 400 | 10M 10F 10M 10F 10M 10F 10M 10F 10M 10F | 15 days day 1-15 day 15-37/40 day 1-15 day 15-37/40 day 1-15 day 15-37/40 day 1-15 day 15-37/40 | Dose-related decreased activity, body weight loss and decreased body weight gain, and a commensurate decrease in food consumption were observed. These effects were minimal at the 10 and 40 mg/kg doses, and at all doses the mice appeared to become tolerant to the effects on activity and body weight over time, and also when the dose was escalated. At an initial dose of 200 mg/kg, marked effects on body weight and clinical signs were noted (as well as limited mortality in a separate metabolism group). By the end of the study, this same group of mice receiving 400 mg/kg exhibited mildly decreased activity, and mean body weights were 12.8 or 3.5% below controls for males and females, respectively. Plasma drug concentrations were below or near the lower limit of detection (50 ng/mL) at doses of 10 or 40 mg/kg and increased proportionally with dose at 100, 200 or 400 mg/kg. Plasma AUC(0-24 hr) were approximately 2-fold higher in female than in male mice. |
| CD-1 Mice | Oral (diet) | 0 40 40 100 40 100 200 | 15M 15F 15M 15F 15M 15F 15M 15F | day 1-103 day 1-103 day 1-15 day 15-103 day 1-15 day 15-29 day 29-103 | No lethality was observed. Clinical signs were limited to mildly decreased activity and a slightly slow response to stimuli. Body weight gain inhibition was observed in the high dose male mice compared to controls. Serum 5'NT levels were elevated in drug-treated females compared to controls. Histopathologically, thymic lymphocytolysis in high and intermediate dose mice of both sexes, and atrophy of the adrenal cortical X-zone in females at all doses were observed. A low incidence of diffuse fatty change of the liver raises the possibility that CP-88,059-1 is slightly hepatotoxic. All CP-88,059-1 treated animals were exposed to drug in a dose-dependent manner. The maximum recommended dose level for the mouse carcinogenicity study is 200 mg/kg/day. By starting at 50 mg/kg/day, and increasing to 100, and finally to 200 mg/kg/day the initial decrement in body weight should be attenuated. |
| CD-1 Mice | Oral (diet) | 0 50 100 200 | 15M 15F 15M 15F 15M 15F 15M 15F | 29 days | Treatment-related signs included decreased activity in all treated animals (with a dose-related incidence and severity), and dehydration in 6/15 high dose females. This latter finding resulted in the mortality of three of the animals. Decreases in body weight occurred in the high dose group and intermediate dose males following the first week of compound administration. These changes were related to slightly lower food consumption in these groups. Dose-related increases in mean serum prolactin concentrations of female CD-1 mice were observed. There was no compound-related effect on serum prolactin concentrations of male CD-1 mice. |
| Long-Evans Rats | Oral (gavage) | 0 5 25 75 | 3M 3F 3M 3F 3M 3F 3M 3F | 2 weeks (15 days) | Weight gain was reduced in intermediate and high dose animals. Food consumption was reduced in high dose males only. Clinical signs observed in all drug-treated animals included sedation, decreased motor activity and ptosis. No other drug-related findings were detected. |
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
|---|
| Chronic Toxicity | |||||||
|---|---|---|---|---|---|---|---|
| S-D Rats | I.V. | .05 .1 .2 | 10M 10F 10M 10F 10M 10F | 2 weeks | No evidence of pharmacologic activity or target organ toxicity was observed. NOAEL = 0.2 mg/kg/day. | ||
| Long-Evans Rats | Oral (gavage) | 0 10 40 160 | 10M 10F 10M 10F 10M 10F 10M 10F | 1 month (36-39 days) | Effects consistent with the pharmacology of the compound were observed (transient sedation to sternal recumbency) in all drug-treated groups, and were associated with decreased food consumption and body weight gain in male groups. NOAEL = 160 mg/kg/day. | ||
| S-D Rats | Oral (gavage) | 0 10 40 200 | 15M 15F 15M 15F 15M 15F 15M 15F | 6 months | Decreased motor activity occurred at all dose levels in both sexes but was more pronounced in the intermediate and high dose groups. Dose-related decreases in body weight gain were observed mostly in males. Several high dose males exhibited aggressive behaviour upon handling. Stress related or secondary changes such as adrenal hypertrophy were observed at the intermediate and high dose groups. NOAEL = 10 mg/kg/day | ||
| Fischer Rats 344 | Oral (diet) | 0 10 40 40 100 200 0 100 40 | 10M 10F 10M 10F 10M 10F 10M 10F 10M 10F | day 1-22 day 1-15 day 15-22 day 1-15 day 15-22 day 1-3 day 3-8 day 8-22 day 1-3 | Dose-related effects were observed on activity and body weight, even at the low dose of 10 mg/kg (low dose male mean body weight was 9% less than that of controls after 2 weeks of dosing). Doses above 100 mg/kg were clearly not tolerated. Plasma concentrations were disproportionally lower than expected and sometimes below the lower limit of quantification (50 ng/mL) after 9 days at 10 mg/kg. After 9 days at 40 and 100 mg/kg, the mean plasma AUC (0-24 hr) increased proportionally with dose and mean values were 9.706 and 23.513 ng·hr/mL, respectively. | ||
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
|---|
| Chronic Toxicity | ||||||
|---|---|---|---|---|---|---|
| Long-Evans Rats | Oral (diet) | 0 5 1 5 10 5 10 20 | 15M 15F 15M 15F 15M 15F 15M 15F | day 1-95 day 1-95 day 1-15 day 15-29 day 29-95 day 1-15 day 15-36 day 36-95 | No lethality was observed. Clinical signs were limited to sporadic incidences of mildly decreased activity, ptosis and chromodacryorrhea. Body weight gain inhibition was observed in the intermediate and high dose rats compared to controls. Mean body weight gains for the intermediate dose groups were 84 and 90% for the males and females, respectively, and mean body weight gains for the high dose animals were 81 and 86% for the males and females, respectively, when compared to and expressed as the percentage of control body weight gain. No drug-related ophthalmology or clinical pathology changes were observed. All CP-88,059-1 treated animals were exposed to drug in a dose proportional manner. There were no drug-related histopathological changes observed in the tissues examined. High dose males had slightly increased relative liver weights and slightly decreased absolute testicular weights compared to controls. Neither of these alterations in organ weights was accompanied by discernible gross or histological organ alterations. The maximum tolerated dose was 10 mg/kg/day. | |
| Beagle Dogs | Oral (gavage) | 0 2 5 10 20 | 1M 1F 1M 1F 1M 1F 1M 1F 1M 1F | 2 weeks (14 days) | Clinical signs observed in all drug-treated animals included sedation, decreased motor activity, splayed hind limbs, intermittent tremors, ptosis and shallow breathing. | |
| Beagle Dogs | I.V. | 0 .05 .1 .2 | 2M 2F 2M 2F 2M 2F 2M 2F | 2 weeks (15 days) | Numerous clinical signs observed in all drug-treated groups were consistent with the pharmacologic profile of the compound. These included tremors, pawing, increased and/or decreased activity, circling, aggressive behaviour, cage biting, head pressing and ptosis (last two observations not noted in low dose animals). Other findings, salivation, emesis, panting and vocalization occurred secondarily to these drug-related clinical signs. One high dose female had scattered, swollen, vacuolated hepatocytes in the liver (seen also in some treated and control animals but less prominently), and a slight elevation in serum alkaline phosphatase concentration. Those are minor changes and do not appear to be linked and are of questionable significance. NOAEL = 0.2 mg/kg/day | |
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
|---|
| Chronic Toxicity | |||||
|---|---|---|---|---|---|
| Beagle Dogs | Oral (gavage) | 0 10 20 (10 BID) 40 (20 BID) | 3M 3F 3M 3F 3M 3F 3M 3F | 1 month (36 days) | Drug plasma concentrations indicated the BID regimen increased exposure to drug over that observed after SID administration. Sedation at all dose levels and miosis in two high dose dogs were observed. These effects are consistent with the pharmacology of the compound. Drug-induced elevations in serum transaminase (ALT or AST) activities occurred in one intermediate and four high dose dogs, and decreased erythroid parameters were recorded for one high dose dog. NOAEL = 10 mg/kg/day. |
| Beagle Dogs | Oral (gavage) | 0 5 10 (5 BID) 40 (20 BID) | 4M 4F 4M 4F 4M 4F 4M 4F | 6 months | Target organ toxicity in the form of intrahepatic cholestatis was observed in all animals receiving the 40 mg/kg (20 BID) high dose. The cholestatis was of mild to moderate severity and correlated with the progressive increase in hepatic enzymes (ALT and Alk Ph). A dose-related inhibition of weight gain and/or weight loss occurred in intermediate and high dose male animals. Numerous clinical signs consistent with the pharmacologic profile of the compound were observed in all drug-treated groups. [Those included: sedation, tremors, head pressing, pawing, increased activity, pacing/circling, aggressive behaviour, limb extension/unusual postures, cage biting, muscle fasciculations, prolapse of the nictitating membrane, miosis and mammary gland development in females.] NOAEL = 5 mg/kg/day. |
| Beagle Dogs | Oral (gavage) | 0 5 10 (5 BID) 20 (10 BID) | 4M 4F 4M 4F 4M 4F 4M 4F | 12 months | All treatment-related effects were consistent with the pharmacologic properties of the compound, and included sedation, tremors, face pressing, pawing, cage biting, limb lifting/unusual positives postures, increased activity, aggressive behaviour, prolapse of the nictitating membrane and mammary gland development (intermediate dose females). Significant weight loss occurred in high dose males. There were no treatment-related effects noted in clinical pathology or histopathology parameters. Plasma drug concentrations exhibited a wide animal-to-animal variation within a given treatment group. Also, a difference in exposure was noted between male and female animals at the high and intermediate dose levels. NOAEL = 10 mg/kg/day. |
| TEST ORGANISM | MAJOR FINDINGS |
| Mutagenicity | |
Ames Test Salmonella typhimurium Strains. TA 1537 Gene Mutation Mouse Lymphoma L5178Y (in vitro). Chromosomal Mutation Mouse Bone Marrow (in vivo) Human Lymphocytes (in vitro). | The results of a comprehensive battery of in vivo and in vitro genetic toxicology studies were generally negative, the exception being a slight increase in mutation frequency in Salmonella typhimurium TA 1537, but only at or near insoluble levels. Such results were not considered to represent a genotoxic hazard by CP-88,059 due to the small response which lacked a true dose-relationship (positive only at the highest level tested), a reduction to non-significant levels by microsomal enzymes, a lack of mutagenic activity in urine from drug-treated mice, findings that gene mutation assays in mammalian cells in vitro were negative, and there was no indication of chromosomal mutation induction in mammalian cells either in vivo or in vitro. |
Carcinogenicity
Mice
CP-88,059-1 was administered in the diet of CD-1 mice (50/sex/dose) at an initial dose of 50 mg/kg for the three treated groups. Two groups of 50/sex control mice received unsupplemented feed. On Day 15, the mid and high doses were increased to 100 mg/kg, and on Day 29 the high dose was increased to 200 mg/kg. The final dose levels were therefore 50, 100 and 200 mg/kg. It was concluded, at the end of this 24-month study, that treatment at the mid and high doses produced a statistically significant reduction both in body weight gain during the growth phase of the animals and in body weight in mice at the end of the study compared to controls. This was associated with a reduction in food and water consumption. Histopathological findings were limited to females and consisted of a dose-related increase in the incidence of hyperplasia and neoplasia in the pituitary gland (shown immunohistochemically to be prolactin-producing) and secondary changes in the mammary gland, ovaries and uterus. These findings were seen at 50 to 200 mg/kg/day, corresponding to systemic exposure about 1-4 times greater than that in humans; a no-effect dose level for these effects was not established.
Proliferative changes in the pituitary and mammary glands are not unexpected findings in rodents following treatment with this class of compounds, and are associated with increased prolactin concentrations.
Rats
CP-88,059-1 was administered in the diet of Long-Evans rats (50/sex/level) for 2 years at dose levels of 2, 6 and 12 mg/kg/day. All groups (low, intermediate and high) began at 2 mg/kg/day, and after 2 weeks the intermediate and high dose groups were raised to 6 mg/kg/day. After another two weeks, the high dose level group was increased to 12 mg/kg/day. Two identical control groups (50/sex/group) received non-medicated diet.
At dose levels up to 12 mg/kg/day, causing body weight decrements of approximately 10 to 20% relative to controls, ziprasidone showed no oncogenic potential in the rat.
Reproduction and Teratology
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS | |||
|---|---|---|---|---|---|---|---|---|
| Fertility and Reproduction | ||||||||
| Sprague- Dawley Rats | Oral (gavage) | 0 10 40 160 | 20M 20F 10M 10F 10M 10F 20M 20F | M: 4 wks prior to mating F: 2 wks prior to mating through gestation and post partum 10 days | Sedation noted for all treatment groups. Food intake and body weights were decreased in a dose-related manner in male rats in all treated groups. Other signs included rough hair coat in males at 160 mg/kg and chromodacryorrhea in animals from both the 40 and 160 mg/kg dose groups. Fertility was decreased in mating groups containing female rats treated with 160 mg/kg. The number of pups per litter was decreased at 160 mg/kg/day, while the proportion of pups born alive were decreased in litters from animals treated with 160 mg/kg. Survival of pups to postnatal day 4 decreased in all treated litters compared to control litters, particularly in the high dose group. The sedation observed in the dams after dosing was likely responsible for the decreased pup survival in the 160 mg/kg dose group. | |||
| Sprague- Dawley Rats | Oral (gavage) | 0 5 10 40 | 20M 40F 20M 40F 20M 40F 20M 40F | M: 10 wks prior to mating F: 2 wks prior to mating; through gestation and lactation | Sedation occurred at all dose levels but fertility was unaffected. Post-natal functional development testing indicated a slight delay in development that would be predicted based on the deficits in the body weights of the pups. From the findings in this Segment I, Fertility and Reproduction Study with CP-88,059-1, the No Observed Adverse Effect Level (NOAEL) for fertility, defined as successful copulation and pregnancy, is 40 mg/kg, the highest dose tested. The NOAEL for reproduction and fetal/neonatal outcome is 5 mg/kg based on decreased gestational body weight gain at the 10 and 40 mg/kg dose levels, altered estrous cycles, decreased number of implantation sites, and number of viable pups at birth in litters from F0 dams at 40 mg/kg and decreased fetal body weights in the F1 offspring at the 10 and 40 mg/kg dose level. For all adult animals who were directly treated, the NOAEL is 5 mg/kg based on non-reproductive parameters. | |||
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS | ||
|---|---|---|---|---|---|---|---|
| Teratology | |||||||
| S-D Rats | Oral (gavage) | 0 10 30 60 | 20F 20F 20F 20F | 12 days gestation (day 6 - 17) | Clinical signs included ptosis and prostration at 40 and 160 mg/kg. Reductions in the maternal weight gain in all treated groups and body weight losses at 160 mg/kg were also recorded. Fetal weights were reduced at 40 and 160 mg/kg, and delays in the ossification (5th metacarpus, and the sacral and caudal vertebrae) were found at 160 mg/kg. Reproductive parameters were not affected. The findings support the conclusion that CP-88,059 is not teratogenic in rats. NOAEL = 10 mg/kg for dams and fetuses. | ||
| New-Zealand White Rabbits | Oral (gavage) | 0 10 30 60 | 20F 20F 20F 20F | 13 days gestation (day 6 - 18) | Administration of the compound to female rabbits during organogenesis induced abortions at 30 and 60 mg/kg, two deaths at 60 mg/kg, a reduction of food intake and a loss in body weight during the treatment period, at 30 and 60 mg/kg. Lower fetal weights and coelosomy were recorded at 60 mg/kg. Reproductive parameters were unaffected. NOAEL = 10 mg/kg for dams. NOAEL = 30 mg/kg for fetuses. | ||
| New-Zealand White Rabbits | Oral (gavage) | 0 10 30 | 24F 20F 24F | 13 days gestation (day 6 - 18) | All animals survived the dosing period with the exception of one high dose animal that died as a result of a dosing accident on gestation day 13 and one high dose animal who was found to be moribund on gestation day 22. The does and the fetuses were exposed to CP-88,059 associated radioactivity. There were no significant changes in maternal body weights or food consumption parameters. Mean fetal body weights, placental weights, and skeletal ossification and development were unaffected by treatment. Two fetuses in one litter in the control group were found with spina bifida. Three fetuses in three litters in the high dose group were noted to have a ventricular septal defect. This is not considered to be treatment-related. The findings indicate that CP-88,059 is not teratogenic in rabbits. | ||
| New-Zealand White Rabbits | Oral (gavage) | 0 30 | 30F 29F | 13 days gestation (day 6 - 18) | All animals survived the dosing period, except one high dose animal which was found moribund and sacrificed on gestational day 27. The only clinical sign noted was occasional loose or soft stool in 6/29 animals of the 30 mg/kg group. Mean maternal body weight gain and food consumption, indications of maternal toxicity, were significantly decreased during part or all of the treatment period. Reproductive parameters, mean fetal body weights and placental weights were unaffected by treatment. Visceral examination of the fetuses showed one fetus in each of the control and 30 mg/kg dose groups with a ventricular septal defect. The findings support the conclusion that CP-88,059 is not teratogenic in rabbits and confirm the previously noted NOAEL for fetuses to be 30 mg/kg. | ||
| SPECIES | ROUTE | DOSE BASE mg/kg/day | ANIMAL PER DOSE LEVEL | DURATION | FINDINGS |
|---|
| Teratology | |||||
|---|---|---|---|---|---|
| S-D Rats | Oral (gavage) | 0 5 10 40 | 23F 23F 23F 23F | 13 days gestation (day 6 - 18) through lactation day 21 | None of the dams died as a consequence of treatment. Mild to moderate sedation occurred at all dose levels, but did not interfere with food consumption, parturition, lactation or adequate maternal care of offspring. Mean body weight was significantly lower for the 40 mg/kg dams throughout gestation and lactation. Food consumption was not affected for any treated group. The NOAEL for maternal effects is 10 mg/kg based on body weight inhibitions seen at 40 mg/kg. The NOAEL for postnatal development and behaviour of offspring is 5 mg/kg based on body weight inhibitions at 10 and 40 mg/kg, increased number of pups born dead and reduced number of pups alive on post natal day 4, delays in eye opening and air righting, and increased motor activity in females at 40 mg/kg. |
Other Studies
Antigenicity Study in Guinea Pigs
CP-88,059-1 does not induce either a systemic anaphylaxis reaction or passive cutaneous anaphylaxis reaction in guinea pigs.
Dermal Toxicity and Ocular Irritation in Rabbits
CP-88,059 is not a Class B Poison or a harmful substance upon either oral or dermal exposure. It is not considered a corrosive material, and it is not an ocular irritant.
Oral Toxicity (Rats), Dermal Toxicity (Rabbits) and Ocular Irritation (Rabbits)
CP-88,059 is not a Class B Poison or a harmful substance upon either oral or dermal exposure. It is not considered a corrosive material, and it is not an ocular irritant.
Acute Phototoxicity (BALB/c Mice)
Ziprasidone did not produce a phototoxic reaction in BALB/c mice as evidenced by the lack of erythema, visible edema, and a statistically significant increase in ear thickness.
REFERENCES
- 1. Addington D.; Pantelis, C.; Dineen, M., et al, Efficacy and tolerability of ziprasidone versus risperidone in patients with acute exacerbation of schizophrenia or schizoaffective disorder: an 8-week, double-blind, multicenter trial. The Journal of clinical psychiatry 2004; 65 (12): 1624-33.
- 2. Arato M.; O'Connor, R.; Meltzer, H.Y.; ZEUS Study Group. A 1-year, double-blind, placebo-controlled trial of ziprasidone 40, 80 and 160 mg/day in chronic schizophrenia: the Ziprasidone Extended Use in Schizophrenia ZEUS study. International Clinical Psychopharmacology 2002; 17 (5): 207-15.
- 3. Apseloff G, Mullet D, Wilner KD, et al. The effects of ziprasidone on steady-state lithium levels and renal clearance of lithium. Br J Clin Pharmacol 2000;49(suppl 1):61s-4s.
- 4. Bench CJ, Lammertsma AA, Dolan RJ, et al. Dose dependent occupancy of central dopamine D2 receptors by the novel neuroleptic CP-88,059-01: a study using positron emission tomography and 11C-raclopride. Psychopharmacol 1993;112:308-314.
- 5. Canadian Psychiatric Association Working Group. Clinical Practice Guidelines Treatment of Schizophrenia Can J Psychiatry, 2005 (50, Supp 1).
- 6. Carnahan RM, Lund BC, Perry PJ. Ziprasidone, a new atypical antipsychotic drug. Pharmacotherapy 2001;21(6):717-730.
- 7. Consensus Development Conference on Antipsychotic Drugs and Obesity and Diabetes. Diabetes Care 2004; 27(2): 596-601.
- 8. Daniel DG, Copeland LF. Ziprasidone: comprehensive overview and clinical use of a novel antipsychotic. Exp Opin Invest Drugs 2000;9(4):819-828.
- 9. Daniel DG, Zimbroff DL, Potkin SG, et al. Ziprasidone 80 mg/day and 160 mg/day in the acute exacerbation of schizophrenia and schizoaffective disorder: a 6-week placebo-controlled trial. Neuropsychopharmacology 1999;20(5):491-505.
- 10. Davis R, Markham A. Ziprasidone. CNS Drugs 1997; 8(2):153-159.
- 11. Endicott J, Spitzer R. A diagnostic interview: the schedule for affective disorders and schizophrenia. Arch Gen Psychiatry 1978; 35:837-44.
- 12. Expert Canadian consensus suggestions on the rational, clinical use of ziprasidone in the treatment of schizophrenia and related psychotic disorders. [Ziprasidone in the treatment of schizophrenia and related psychotic disorders] Neuropsychiatric Disease and Treatment 2005; 1(2): 89-108.
- 13. Feltus MSK, Gardner DM. Second generation antipsychotics for schizophrenia. Can J Clin Pharmacol 1999; 6(4):187-195.
- 14. Goff DC, Posever T, Herz L, et al. An exploratory haloperidol-controlled dose-finding study of ziprasidone in hospitalized patients with schizophrenia or schizoaffective disorder. J Clin Psychopharmacol 1998;18(4):296-304.
- 15. Hamelin BA, Allard S, Laplante L, et al. The effect of timing of a standard meal on the pharmacokinetics and pharmacodynamics of the novel atypical antipsychotic agent ziprasidone. Pharmacotherapy 1998;18(1):9-15.
- 16. Harrigan EP, Miceli JJ, Anziano R, et al. A randomized evaluation of the effects of six antipsychotic agents on QTc, in the absence and presence of metabolic inhibition. J Clin Psychopharmacol 2005;24(1):62-9.
- 17. Harvey P.; Siu, C.; Romano, S. Randomized, controlled, double-blind, multicenter comparison of the cognitive effects of ziprasidone versus olanzapine in acutely ill inpatients with schizophrenia or schizoaffective disorder. Psychopharmacology 2004; 172 (3): 324-32.
- 18. Hirsch S.; Kissling, W.; Bäuml, J. et al. A 28-week comparison of ziprasidone and haloperidol in outpatients with stable schizophrenia. The Journal of clinical psychiatry 2002; 63 (6): 516-23.
- 19. Howard HR, Lowe JA III, Seeger TF, et al. 3-Benzisothiazolylpiperazine derivatives as potential atypical antipsychotic agents. J Med Chem 1996;39(1):143-8.
- 20. Howard HR, Prakash C, Seeger TF. Ziprasidone hydrochloride: Antipsychotic, dopamine D2 antagonist, 5-HT2 antagonist. Drugs Future 1994;19(6):560-3.
- 21. Howard HR, Prakash C, Seeger TF. Ziprasidone hydrochloride: Antipsychotic, dopamine antagonist, 5-HT2 antagonist. Drugs Future 1996;21(6):681-2.
- 22. Howard HR, Prakash C, Seeger TF. Ziprasidone hydrochloride: Antipsychotic, dopamine antagonist, 5-HT2 antagonist. Drugs Future 1998;23(6):690
- 23. Keck P, Buffenstein A, Ferguson J, et al. Ziprasidone 40 and 120 mg/day in the acute exacerbation of schizophrenia and schizoaffective disorder: a 4-week placebo-controlled trial. Psychopharmacology 1998;140:173-184.
- 24. Keck PE Jr et al. Ziprasidone in the treatment of acute bipolar mania: a three-week, placebo-controlled, double-blind, randomized trial Am J Psychiatry. 2003;160(4):741-8.
- 25. Keck PE, McElroy SL, Arnold LM. Ziprasidone: a new atypical antipsychotic. Expert Opin Pharmacother 2001;2(6):1033-42.
- 26. Keck PE, Reeves KR, Harrigan EP and the Ziprasidone Study Group. Ziprasidone in the short-term treatment of patients with schizoaffective disorder: results from two double-blind, placebo-controlled, multicenter studies. J Clin Psychopharmacol 2001;21:27-35.
- 27. Mamo D, Kapur, S.; Shammi, C.M. et al. A PET study of dopamine D2 and serotonin 5-HT2 receptor occupancy in patients with schizophrenia treated with therapeutic doses of ziprasidone. The American journal of psychiatry 2004; 161 (5): 818-25.
- 28. Miceli JJ, Anziano RJ, Robarge L, et al. The effect of carbamazepine on the steady-state pharmacokinetics of ziprasidone in healthy volunteers. Br J Clin Pharmacol 2000a; 49 (suppl 1): 65s-70s.
- 29. Potkin S et al. Ziprasidone in acute bipolar mania : A 21-day randomized, double-blind, placebo-controlled replication trial. J Clin Psychopharmacol. 2005;25(4):301-10.
- 30. Prakash C, Kamel A, Anderson W, et al. Metabolism and excretion of the novel antipsychotic drug ziprasidone in rats after oral administration of a mixture of 14C- and 3H-labeled ziprasidone. Drug Metab Dispos 1997;25(1):206-218.
- 31. Prakash C, Kamel A, Gummerus J, et al. Metabolism and excretion of a new antipsychotic drug, ziprasidone, in humans. Drug Metab Dispos 1997;25(7):863-72.
- 32. Prakash C. Characterization of the novel benzisothiazole ring-cleaved products of the antipsychotic drug ziprasidone. Drug Metab Dispos 1997;25(7):897-901.
- 33. Seeger TF, Seymour PA, Schmidt AW, et al. Ziprasidone (CP-88,059): a new antipsychotic with combined dopamine and serotonin receptor antagonist activity. J Pharmacol Exp Ther 1995;275(1):101-113.
- 34. Smith AW, Lebel LA, Howard HR, et al. Ziprasidone: a novel antipsychotic agent with a unique receptor binding profile. Eur J Pharmacol 2001;425:197-201.
- 35. Sprouse JS, Reynolds LS, Braselton JP, et al. Comparison of the novel antipsychotic ziprasidone with clozapine and olanzapine: inhibition of dorsal raphe cell firing and the role of 5-HT1A receptor activation. Neuropsychopharmacology 1999;21:622-31.
- 36. Tamminga CA, Lahti AC. The new generation of antipsychotic drugs. Int Clin Psychopharmacol 1996;11(Suppl 2):73-6.
- 37. The pharmacokinetics of ziprasidone. In: Br J Clin Pharmacol 2000;49(Suppl 1):1S-76S.
- 38. Treatment recommendations for patients with schizophrenia [APA Guidelines] Am J Psychiatry 2004;161(2): 1-56.
- 39. Vieta, Eduard et al. Ziprasidone in the treatment of acute mania: a 12-week, placebo-controlled, haloperidol-referenced study. J. of Phsychopharmacology 24(4) (2010) 547-558
- 40. Woo Vincent et al Canadian Diabetes position paper: Antipsychotic medications and associated risks of weight gain and diabetes. Canadian Journal of Diabetes 2005:29(2):111-12.
- 41. Zorn SH, Seeger TF, Seymour PA, et al. Ziprasidone (CP-88,059) preclinical pharmacology review. JPN J Neurophychopharmacol 1995;17(10):701-7.
- 42.
Gandelman, Kuan, et al. The Impact of Calories and Fat Content of Meals on Oral
Ziprasidone Absorption: A Randomized, Open-Label, Crossover Trial. J.Clin Psychiatry
2009’ 70(1):58-62