


Product Monograph - Hydralazine Hydrochloride Injection, USP (Auro Pharma)
RECENT MAJOR LABEL CHANGES
None at the time of the most recent authorization.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ...................................................................................................................... 4
1.1 Pediatrics .......................................................................................................................... 4
1.2 Geriatrics .......................................................................................................................... 4
2 CONTRAINDICATIONS ......................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................... 4
4 DOSAGE AND ADMINISTRATION ........................................................................................ 4
4.1 Dosing Considerations ...................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................. 5
4.3 Reconstitution .................................................................................................................. 5
4.4 Administration ................................................................................................................. 5
5 OVERDOSAGE ..................................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................................ 6
7 WARNINGS AND PRECAUTIONS .......................................................................................... 7
7.1 Special Populations ....................................................................................................... 10
7.1.1 Pregnant Women ................................................................................................. 10
7.1.2 Breast-feeding ...................................................................................................... 10
7.1.3 Pediatrics .............................................................................................................. 11
7.1.4 Geriatrics .............................................................................................................. 11
8 ADVERSE REACTIONS ........................................................................................................ 11
8.1 Adverse Reaction Overview ........................................................................................... 11
8.2 Clinical Trial Adverse Reactions ...................................................................................... 11
8.3 Less Common Clinical Trial Adverse Reactions ............................................................... 11
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...................................................................................................................................... 11
8.5 Post-market adverse reactions ....................................................................................... 11
9 DRUG INTERACTIONS ....................................................................................................... 13
9.1 Drug Interactions Overview ............................................................................................ 13
9.2 Drug-Behavioural Interactions ....................................................................................... 13
9.3 Drug-Drug Interactions ................................................................................................... 13
9.4 Drug-Food Interactions .................................................................................................. 14
9.5 Drug-Herb Interactions .................................................................................................. 14
9.6 Drug-Laboratory Test Interactions ................................................................................. 14
10 CLINICAL PHARMACOLOGY ............................................................................................. 14
10.1 Mechanism of Action ................................................................................................... 14
10.2 Pharmacokinetics ......................................................................................................... 15
11 STORAGE, STABILITY AND DISPOSAL ............................................................................... 16
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................ 16
PART II: SCIENTIFIC INFORMATION ...................................................................................... 17
13 PHARMACEUTICAL INFORMATION ................................................................................. 17
14 CLINICAL TRIALS .............................................................................................................. 17
15 MICROBIOLOGY .............................................................................................................. 17
16 NON-CLINICAL TOXICOLOGY ........................................................................................... 17
17 SUPPORTING PRODUCT MONOGRAPHS ......................................................................... 19
PATIENT MEDICATION INFORMATION ................................................................................ 20
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Hydralazine Hydrochloride Injection, USP (hydralazine hydrochloride injection) is indicated for the emergency treatment of severe essential hypertension when the drug cannot be given orally or when there is an urgent need to lower blood pressure (e.g. toxemia of pregnancy or pre-eclampsia).
1.1 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatric patients or patients with marked renal damage may require a lower dosage.
2 CONTRAINDICATIONS
- Hypersensitivity to hydralazine or dihydrazine, or to any of the excipients.
- Idiopathic systemic lupus erythematosus (SLE) and related diseases.
- Severe tachycardia and heart failure with a high cardiac output (e.g., in thyrotoxicosis).
- Myocardial insufficiency due to mechanical obstruction (e.g., in the presence of aortic or mitral stenosis or constrictive pericarditis).
- Isolated right-ventricular heart failure due to pulmonary hypertension (cor pulmonale).
- Acute dissecting aneurysm of the aorta.
- Coronary artery disease.
- Porphyria
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The dose of Hydralazine Hydrochloride Injection, USP (hydralazine hydrochloride injection) must always be individualized and adjusted according to the patient's blood pressure response.
- Patients should be hospitalized. The parenteral administration of Hydralazine Hydrochloride Injection, USP should always be carried out cautiously and under strict medical supervision.
- Blood pressure and heart rate should be checked frequently (i.e., every 5 minutes). Blood pressure levels may begin to fall within a few minutes after injection, with an average maximal decrease occurring in 10 to 80 minutes. In cases where there has been increased intracranial pressure, lowering the blood pressure may increase cerebral ischemia. A satisfactory response can be defined as a decrease in diastolic blood pressure to 90 to 100 mmHg.
4.2 Recommended Dose and Dosage Adjustment
The initial dose is 5 to 10 mg, administered by slow intravenous injection in order to avoid precipitous decreases in mean arterial pressure with a critical reduction in cerebral or utero-placental perfusion. Geriatric patients or patients with marked renal damage may require a lower dosage. In hypertensive crises other than pre-eclampsia/eclampsia, usual doses of 20 - 40 mg have been used, repeated as necessary. If it is necessary to repeat the injection, this should be done after an interval of 20 to 30 minutes, throughout which blood pressure and heart rate should be monitored.
Most patients can be transferred to an oral anti-hypertensive within 24 to 48 hours.
4.3 Reconstitution
Parenteral Products: The injection solution should be used immediately after the vial is opened. It should not be added to infusion solutions. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
4.4 Administration
Patients should be hospitalized. The parenteral administration of Hydralazine Hydrochloride Injection, USP should always be carried out cautiously and under strict medical supervision.
Blood pressure and heart rate should be checked frequently (i.e., every 5 minutes). Blood pressure levels may begin to fall within a few minutes after injection, with an average maximal decrease occurring in 10 to 80 minutes. In cases where there has been increased intracranial pressure, lowering the blood pressure may increase cerebral ischemia. A satisfactory response can be defined as a decrease in diastolic blood pressure to 90 to 100 mmHg.
Direct Injection
Administer the solution by slow intravenous injection. For ease of administration the solution may be further diluted with physiological saline.
5 OVERDOSAGE
Signs and Symptoms of Overdosage
Symptoms include hypotension, tachycardia, accompanied by headache, generalized skin flushing, sweating, nausea and dizziness. Also possible are myocardial ischemia with angina pectoris, and cardiac arrhythmia. Further signs may include impairment of consciousness, headache and vomiting, as well as possible tremor, convulsions, oliguria, hypothermia, profound shock and coma.
Treatment for Overdosage
There is no known specific antidote. Supportive measures including intravenous fluids are also indicated. If hypotension is present, an attempt should be made to raise the blood pressure without increasing the tachycardia. Adrenaline should not be used to correct the hypotension, since it enhances the cardiac-accelerating effects of hydralazine.
Support of the cardiovascular system is of primary importance. Shock should be treated with plasma expanders. If possible, vasopressors should not be given, but if a vasopressor is required, care should be taken not to precipitate or aggravate cardiac arrhythmia. The ECG should be monitored while the vasopressors are being administered. Tachycardia responds to beta blockers. Digitalization may be necessary, and renal function should be monitored and supported as required. The use of dopamine to elevate systolic blood pressure to 90 mmHg may be considered in an emergency.
No experience has been reported with extracorporeal or peritoneal dialysis.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Intravenous | Solution, 20 mg/mL hydralazine hydrochloride | hydrochloric acid, methyl paraben, propyl paraben, propylene glycol, sodium hydroxide, water for injection |
1 mL clear glass vials containing clear to pale yellow sterile solution, available in cartons of 10 vials.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Cardiovascular
The overall “hyperdynamic” state of the circulation induced by hydralazine may accentuate certain clinical conditions. Hydralazine can cause anginal attacks and ECG changes indicative of myocardial ischemia. Myocardial stimulation may provoke or aggravate angina pectoris, congestive heart failure or myocardial infarction.
Patients with suspected or confirmed coronary artery disease should therefore be given Hydralazine Hydrochloride Injection, USP only under beta-blocker cover or in combination with other suitable sympatholytic agents. It is important that the beta-blocker medication should be commenced a few days before the start of treatment with Hydralazine Hydrochloride Injection, USP.
Patients who have survived a myocardial infarction should not receive hydralazine hydrochloride until post-infarction stabilization has been achieved. Hydralazine Hydrochloride Injection, USP should not be used in heart failure.
Postural hypotension may result from hydralazine hydrochloride, but is less common than with ganglionic blocking agents. The drug should be used with caution in patients with cerebral vascular disease since abrupt decreases in blood pressure should be avoided in these patients.
Cerebrovascular disease
Like all potent antihypertensives, Hydralazine Hydrochloride Injection, USP should be used with caution in patients suffering from cerebrovascular disease, since it can increase ischemia.
Hydralazine hydrochloride may provoke in a few patients a clinical picture simulating systemic lupus erythematosus (SLE) including glomerulonephritis. In its mild form this syndrome is reminiscent of rheumatoid arthritis (arthralgia, sometimes associated with fever and skin rash). When fully developed a syndrome resembling disseminated lupus erythematosus occurs.
Should this SLE-like syndrome develop, treatment should be discontinued immediately. Symptoms and signs usually regress when the drug is discontinued but residua have been detected many years later. Long-term treatment with adrenocorticosteroids may be necessary.
The frequency of these untoward effects increases with dosage and duration of exposure to the drug and is higher in slow than in fast acetylators. When treated with the same dosage, slow acetylators have higher serum concentrations than fast acetylators. The lowest effective dosage should therefore be used for maintenance therapy. Rapid acetylators, often respond inadequately even to doses of 100 mg daily. In these patients, the dosage can be raised with only a slightly increased risk of a SLE-like syndrome. If 100 mg daily fails to elicit an adequate clinical effect, the patient's acetylator status should be evaluated.
Slow acetylators and women run a greater risk of developing this SLE-like syndrome. In such cases dosage should be kept below 100 mg daily and the patients carefully monitored for clinical signs and symptoms suggestive of this syndrome.
Complete blood counts, examination of lupus erythematosus cell preparations, antinuclear antibody titer determinations and urine analysis are indicated before and periodically (e.g. every 6 months) during prolonged therapy with hydralazine even though the patient is asymptomatic. Microhaematuria and/or proteinuria, in particular together with positive titres of anti-nuclear factors (ANF), may be initial signs of immune-complex glomerulonephritis associated with the SLE-like syndrome. A positive ANF titre requires that the physician carefully weighs the implications of the test results against the benefits of continued therapy with Hydralazine Hydrochloride Injection, USP. If overt clinical signs and symptoms develop, the medicine should be withdrawn at once. A complete blood count and ANF titre determination is indicated before and periodically during prolonged therapy with Hydralazine Hydrochloride Injection, USP even if the patient is asymptomatic.
These tests are also indicated if the patient develops arthralgia, fever, chest pain, continued malaise or other unexplained signs or symptoms. If the results of these tests are abnormal, treatment should be discontinued.
Antinuclear antibodies may be found in the blood of as many as 50 percent of patients receiving hydralazine who remain asymptomatic. A positive antinuclear antibody titer requires that the physician carefully weigh the implications of the test results against the benefits to be derived from antihypertensive therapy with hydralazine hydrochloride.
Driving and Operating Machinery
A pronounced lowering of the blood pressure may adversely affect the patient's reactions (e.g. as in driving or operating machinery).
Hematologic
Blood dyscrasias consisting of reduction in hemoglobin and red cell count, leukopenia, agranulocytosis and purpura have been reported. Periodic blood counts are advised during therapy. If such abnormalities develop, therapy should be discontinued.
Hepatic/Biliary/Pancreatic
In patients with hepatic dysfunction, serum levels of hydralazine increased as compared to those in patients with normal hepatic function, therefore the dose or the dosing interval should be adjusted according to the clinical response, in order to avoid accumulation of the "apparent" active substance.
Neurologic
Peripheral neuritis, evidenced by paresthesias, numbness and tingling in the extremities has been observed. Published evidence suggests an antipyridoxine effect and the addition of pyridoxine to the regimen or medicine withdrawal if symptoms develop.
Peri-Operative Considerations
When undergoing surgery, patients treated with Hydralazine may show a fall in blood pressure, in which case one should not use adrenaline to correct the hypotension, since it enhances the cardiac-accelerating effects of hydralazine hydrochloride.
Renal
In hypertensive patients with normal kidneys who are treated with hydralazine hydrochloride, there is evidence of increased renal blood flow and a maintenance of glomerular filtration rate. In some instances, improved renal function has been noted where control values were below normal prior to hydralazine hydrochloride administration. However, as with any antihypertensive agent, hydralazine hydrochloride should be used with caution in patients with advanced renal damage.
In patients with renal impairment (creatinine clearance < 30 mL/min or serum creatinine > 2.5 mg/100 mL or 221 µmol/L), serum levels of hydralazine increased as compared to those in patients with normal renal function, therefore the dose or the interval between doses should be adjusted according to the clinical response, in order to avoid accumulation of the "apparent" active substance.
Reproductive Health: Female and Male Potential
Fertility
No data exists on effects of the drug on fertility.
Function
No data exists on effects of the drug on sexual function.
- Teratogenic Risk
Usage in Pregnancy (Category C: Drugs which, owing to their pharmacological effects, have caused or may be suspected of causing harmful effects on human fetus or neonate without causing malformations). These effects may be reversible.
Hydralazine is known to cross the placenta following intravenous administration and has been associated with fetal distress and fetal cardiac arrhythmia in the last trimester of pregnancy. Teratogenic effects observed in humans included the cleft palate and malformations of facial and cranial bones. In view of the possible teratogenic potential in humans, use of Hydralazine Hydrochloride Injection, USP in pregnancy before the third trimester should be avoided. The medicine should only be given in the third trimester if the expected benefit justifies the potential risk to the fetus.
Animal experiments have shown hydralazine is teratogenic in mice at oral doses equal to or greater than 20 mg/kg/day; a "no effect" dose has not been clearly established. Hydralazine was teratogenic in rabbits where oral doses equal to and greater than 75 mg/kg/day caused phalangeal defects. Hydralazine was not teratogenic in rats at oral doses up to 180 mg/kg/day. Embryo-lethality was observed in mice at doses equal to or greater than 20 mg/kg/day.
Hydralazine was, however, not embryolethal in rats and rabbits at oral doses up to 180 and 60 mg/kg/day, respectively. Delayed ossification was observed in mice and rats at maternotoxic doses greater than 20 and 60 mg/kg/day, respectively, and reduced fetal weight was seen in mice at doses greater than 20 mg/kg/day.
Respiratory
Treatment with Hydralazine Hydrochloride Injection, USP may induce systemic vasculitis, including ANCA (anti-neutrophil cytoplasm antibody)-positive vasculitis, leading to pulmonary renal syndrome which is a combination of diffuse alveolar haemorrhage and rapidly aggressive glomerulonephritis.
Patients may present with severe respiratory and/or renal failure and require treatment in an intensive care unit. The syndrome is characterised by a fulminant course if left untreated and may sometimes be fatal.
Skin
Skin rash and febrile reactions occur rarely, in which case the medicine should be withdrawn.
7.1 Special Populations
7.1.1 Pregnant Women
Usage in Pregnancy (Category C: Drugs which, owing to their pharmacological effects, have caused or may be suspected of causing harmful effects on human fetus or neonate without causing malformations. These effects may be reversible.
7.1.2 Breast-feeding
Hydralazine passes into breast milk. Alternatives to hydralazine should be considered in nursing mothers.
7.1.3 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
The elderly may be more sensitive to the hypotensive effects. In addition, the risk of hydralazine-induced hypothermia may be increased in elderly patients. Concurrent hepatic and renal insufficiency should be taken into account.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common adverse reactions are tachycardia, palpitation, anginal symptoms, flushing, headache, dizziness, nasal congestion and gastrointestinal disturbances. These are more frequent at the start of treatment, especially if the dosage is raised rapidly. However, such reactions generally subside in the further course of treatment or following a reduction of dosage. Isolated cases of peripheral neuritis, polyneuritis and paraesthesia have also been reported.
The most severe reactions are neuropathy, blood dyscrasias, and an acute rheumatoid state resulting in a syndrome resembling disseminated lupus erythematosus (see 7 Warnings and Precautions).
8.2 Clinical Trial Adverse Reactions
This information is not available for this drug.
8.3 Less Common Clinical Trial Adverse Reactions
This information is not available for this drug.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
This information is not available for this drug product.
8.5 Post-market adverse reactions
Cardiovascular System
Tachycardia, palpitations, flushing, hypotension, anginal symptoms, edema, heart failure, paradoxical pressor responses.
Central and Peripheral Nervous System
Headache, dizziness, peripheral neuritis evidenced by paresthesia numbness and tingling, tremor.
Musculo-Skeletal System
Arthralgia, joint swelling, myalgia, muscle cramps.
Skin and Appendages
Rash.
Urogenital System
Proteinuria, increased plasma creatinine, hematuria sometimes in association with glomerulonephritis, acute renal failure, urinary retention, difficulty in micturition
Gastrointestinal Tract
Gastrointestinal disturbances, diarrhea, constipation, nausea, vomiting, jaundice, liver enlargement, abnormal liver function sometimes in association with hepatitis, paralytic ileus.
Blood
Anemia, leukopenia, neutropenia, thrombocytopenia with or without purpura, hemolytic anemia, leucocytosis, lymphadenopathy, pancytopenia, splenomegaly, agranulocytosis, antinuclear antibodies.
Psychiatric reactions
Agitation, anorexia, anxiety, depression, hallucinations, disorientation, sleep disturbances
Sense Organs
Increased lacrimation, conjunctivitis, nasal congestion, blurred vision.
Hypersensitivity Reactions
Systematic lupus erythematosus like syndrome (sometimes resulting in a fatal outcome; see 7 WARNINGS AND PRECAUTIONS), chills, eosinophilia, hypersensitivity reactions such as pruritus, urticaria, vasculitis, hepatitis.
Respiratory Tract
Dyspnea, pleural pain.
Miscellaneous
Rare: Fever, weight decrease, malaise, exophthalmos, decreased libido, pancreatitis; hyperuricemia, hyperglycemia and hypokalemia.
9 DRUG INTERACTIONS
9.1 Drug Interactions Overview
Concomitant treatment with other vasodilators, calcium antagonists, ACE inhibitors, diuretics, antihypertensives, anaesthetics, tricyclic antidepressants and major tranquilizers, nitrates or drugs exerting central depressant actions (including alcohol), may potentiate the hypotensive effect of hydralazine hydrochloride.
9.2 Drug-Behavioural Interactions
Interactions between the drug and behavioural risks such as alcohol consumption, sexual activity, and smoking have not been studied.
9.3 Drug-Drug Interactions
The drugs listed in Table 3 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction.
Table 3 Established or Potential Drug-Drug interactions with hydralazine hydrochloride
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
Beta blockers (e.g. acebutolol, atenolol, metaprolol, propranolol) | T | Concurrent administration of hydralazine hydrochloride with beta blockers subject to a strong first pass effect (e.g. propanolol) may increase their bioavailability. | Download adjustment of these drugs may be required when they are given concomitantly with hydralazine hydrochloride. |
Diazoxide (Anti-hypertensive) | T | Administration of hydralazine hydrochloride shortly before or after diazoxide may lead to marked hypotension | Patients should be continuously observed for several hours for any excessive fall in blood pressure |
Other antihypertensives (vasodilators, calcium antagonists, ACE inhibitors, diuretics), anaesthetics, tricyclic antidepressants, major tranquillisers, nitrates or drugs exerting central depressant actions (including alcohol) | T | There is potential for the hypotensive effect of hydralazine to be antagonised. | Patients should be continuously observed for several hours for any excessive fall in blood pressure. |
|---|---|---|---|
| Epinephrine | T | Hydralazine hydrochloride may reduce the pressor responses to epinephrine | Caution is warranted |
MAO inhibitors (e.g. moclobemide, phenelzine, procarbazine, tranylcypromine) | T | MAO inhibitors should be used with caution in patients receiving hydralazine | |
NSAIDS (e.g. celecoxib, diclofenac, ibuprofen, indomethacin, naproxen) | T | There is potential for the hypotensive effect of hydralazine to be antagonised. | Patients should be continuously observed for several hours for any excessive fall in blood pressure. |
| Oestrogens | T | There is potential for the hypotensive effect of hydralazine to be antagonised. | Patients should be continuously observed for several hours for any excessive fall in blood pressure. |
T = Theoretical
9.4 Drug-Food Interactions
Interactions with food have not been established.
9.5 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.6 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Although the precise mechanism of action of hydralazine hydrochloride injection is not fully understood, the major effects are on the cardiovascular system. Hydralazine apparently lowers blood pressure by exerting a peripheral vasodilating effect through a direct relaxation of vascular smooth muscle. Hydralazine, by altering cellular calcium metabolism, interferes with the calcium movements within the vascular smooth muscle that are responsible for initiating or maintaining the contractile state.
The peripheral vasodilating effect of hydralazine results in decreased arterial blood pressure (diastolic more than systolic); decreased peripheral vascular resistance; and an increased heart rate, stroke volume, and cardiac output. The vasodilating effect is much greater on arterioles than on veins and vascular resistance decreases more in the coronary, cerebral, splanchnic and renal circulations than in skin and muscle.
Hydralazine usually increases renin activity in plasma, presumably as a result of increased secretion of renin by the renal juxtaglomerular cells in response to reflex sympathetic discharge. This increase in renin activity leads to the production of angiotensin II, which then causes stimulation of aldosterone and consequent sodium reabsorption and fluid retention.
Sodium retention and excessive sympathetic stimulation of the heart caused by hydralazine may be precluded by co-administration of a thiazide diuretic and a beta-blocker. Beta- adrenergic blocking drugs and hydralazine hydrochloride are complementary in their pharmacologic effects, a beta-adrenergic blocking agent minimizes hydralazine-induced increases in cardiac rate and output, and hydralazine prevents the reflex increase in peripheral resistance induced by beta- blockers.
Hydralazine hydrochloride acts directly on peripheral arterioles, where it has a relaxing effect on the smooth muscle of the vessel wall, with a resultant decrease in arteriolar resistance, decreasing arterial blood pressure, diastolic often more than systolic.
Hydralazine exerts no direct actions on the heart. When the drug decreases arterial pressure and thereby activating the baroreceptors, cardiovascular reflexes result in increased sympathetic discharge. Since hydralazine hydrochloride does not increase venous capacitance or depress cardiac function, sympathetic stimulation increases heart rate, left ventricular velocity, stroke volume and cardiac output.
10.2 Pharmacokinetics
Distribution:
After intravenous administration of hydralazine hydrochloride no first-pass effect occurs; acetylator status therefore has no influence on the plasma levels. In the plasma only small amounts of the free drug can be traced, the bulk circulating in conjugated form, i.e. mainly as pyruvic acid hydrazone. Only the so-called “apparent” hydralazine, i.e. the sum of the free and conjugated hydralazine, can be measured reliably.
Hydralazine becomes bound to plasma proteins (chiefly albumin) to the extent of 88 -90%. It is rapidly distributed in the body and displays a specific affinity for muscle tissue in the arterial walls. It crosses the placental barrier and also passes into breast milk.
Metabolism:
The pattern of the metabolites depends on the subject's acetylator and presumably hydroxylator status. Urinary excretion of NAc-HPZ (N-acetyl-hydrazine-phthalazinone), the main metabolite from the acetylation pathway, may be used to determine acetylator phenotype. The plasma half-life generally ranges from 2 to 3 hours, but in rapid acetylators it is shorter, averaging 45 minutes. In patients with impaired renal function, the plasma half-life is prolonged to up to 16 hours at a creatinine clearance of < 20 mL/min.
Elimination:
Hydralazine and its metabolites are rapidly excreted by the kidney. The bulk of the hydralazine excreted is in the form of acetylated and hydroxylated metabolites, some of which are conjugated with glucuronic acid; 2 - 14% is excreted as "apparent" hydralazine. Renal elimination may be impaired in patients of advanced age.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15°C to 30°C, protect from heat and light.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions applicable to this drug.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Hydralazine Hydrochloride USP |
|---|---|
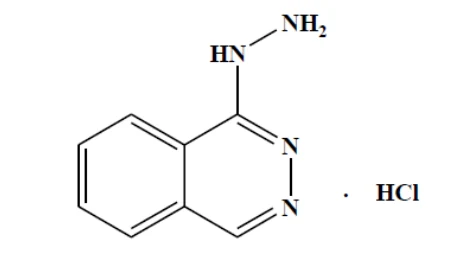
| Chemical name: | 1-HYDRAZINOPHTHALAZINE MONOHYDROCHLORIDE. |
| Molecular formula and molecular mass: | C8H8N4 · HCl, 196.64 g / mol |
| Structural formula: | |
| Pharmaceutical standard: | USP |
| Product Characteristics: | |
| Description: | White to off-white powder. |
| Melting Point: | Melts about 275°C,with decomposition |
| Solubility: | Soluble in water, practically insoluble in alcohol and in ether. |
| pH (Dissolve 0.5 g in 25 ml of carbon dioxide-free water): | Between 3.5 and 4.2 |
14 CLINICAL TRIALS
Clinical trial data is not available for this drug.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
 |
Rats: The acute toxicity of hydralazine, as determined intravenously in female white rats is comparatively low: the LD50 is 34 mg/kg.
Dogs: Single doses of 20 mg/kg intravenously and 200 mg/kg orally were tolerated. The test animals manifested tachycardia, depression, and emesis. Vomiting occurred at doses of 8 and 16 mg/kg and central nervous system stimulation at 32 and 64 mg/kg.
Sub-acute Toxicity
Dogs: Hydralazine in oral doses of 30 mg/kg given 5 days per week for 3 months was well tolerated.
Long-term Toxicity
Mice: Doses of 7.4 mg/day to males and 5.4 mg/day to females administered orally throughout the lifespan resulted in increased incidence of lung tumours (classified as adenomas and adenocarcinomas).
Dogs: Hydralazine was given in oral doses of 1, 3 and 10 mg/kg per day for 6 months. Heinz bodies were detected in the erythrocytes of the high dosage group. Other changes observed included: reversible elevations and depressions of the ST-segment; dose¬-related tachycardia; dose-related conjunctivitis and in one animal conjunctivitis sicca with pannus formation; in one intermediate dose animal, a small area of subendocardial fibrosis was observed histologically.
Teratogenicity
Mice: Doses of 20, 60, 120 and 150 mg/kg were used. Somnolence and dyspnea, as well as death, at the highest doses indicate that maximum tolerated doses had been exceeded. A dose-related increase in the incidence of cleft palate, agnathia, and hypognathia was observed. Rats: Doses of 20, 60 and 180 mg/kg were used. Maximum tolerated doses were again exceeded, but teratogenic manifestations were not observed, although there was a delay in ossification characterized by unossified calcanei, sternebrae and phalangeal nuclei.
Rabbits: Doses of 10, 30 and 60 mg/kg were used. At the high dose level, some somnolence, as well as one apparent drug-related death, indicated that doses were in the maximum tolerated range.
In the 60 mg/kg dose group one out of 84 fetuses showed mandibular aplasia (agnathia inferior). This malformation is considered to be of spontaneous origin, however, a drug related effect cannot be entirely discounted.
Hydralazine was teratogenic in rabbits where oral doses equal to and greater than 75 mg/kg/day caused phalangeal defects.
Genotoxicity:
Hydralazine induces gene mutations, chromosomal aberrations and DNA damage in mammalian cells in vitro, as well as gene mutations in bacteria, yeast and Drosophila. The potential for similar effects in vivo has not been adequately reported.
Mice: In a lifetime study in Swiss albino mice, there was a statistically significant increase in the incidence of lung tumours (adenomas and adenocarcinomas) of both male and female mice given hydralazine hydrochloride continuously in their drinking water at a dosage of about 50- 200 mg/kg/day; a “no effect” dose has not been established.
Rat: In a 2-year carcinogenicity study of Sprague-Dawley albino rats given hydralazine hydrochloride by gavage at dose levels of 15, 30 and 60 mg/kg/day showed increases in the incidences of hepatic neoplasms in both sexes and of Leydig cell tumours in males. Benign interstitial (Leydig) cell tumours of the testes were also significantly increased in male rats from the high-dose group. The tumours observed are common in aged rats and the increased incidence was not observed until 18 months of treatment.
Mutagenicity:
Hydralazine was shown to be mutagenic in bacterial systems (Gene Mutation and DNA Repair) and in one of two rat and one rabbit hepatocyte in-vitro DNA repair studies. In the latter study the effect was evident in cells from slow acetylator rabbits but not from fast acetylators.
Additional in-vivo and in-vitro studies using lymphoma cells, germinal cells, and fibroblasts from mice, bone marrow cells from Chinese hamsters and fibroblasts from human cell lines did not demonstrate any mutagenic potential for hydralazine.
Hydralazine hydrochloride in chronic toxicity studies has been shown to increase the incidence of some tumours in aging rodents. A mutagenic potential was observed in some but not all mutagenicity tests. The extent to which these findings indicate a risk to man is uncertain. While long-term clinical observations have not suggested that human cancer is associated with hydralazine use, epidemiologic studies have so far been insufficient to arrive at any conclusion.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrAPRESOLINE® Solution, 20 mg / mL, submission control 263009, Product Monograph, SteriMax Inc. (September 13, 2022).