


Product Monograph - Imodium Complete
RECENT MAJOR LABEL CHANGES
| Section 6: Dosage Forms, Strengths, Composition and Packaging – Addition of 40-count blister packs and removal of 42-count bottles | 07/2020 |
|---|---|
| Section 5: Overdosage – addition of drug withdrawal syndrome | 12/2021 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.4 Administration ......................................................................................................... 5
5 OVERDOSAGE ............................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 7
7 WARNINGS AND PRECAUTIONS ................................................................................. 7
7.1 Special Populations .................................................................................................. 8
7.1.1 Pregnant Women ............................................................................................... 8
7.1.2 Breast-feeding .................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................ 9
8 ADVERSE REACTIONS................................................................................................. 9
8.1 Adverse Reaction Overview ..................................................................................... 9
8.2 Clinical Trial Adverse Reactions ............................................................................. 10
8.5 Post-Market Adverse Reactions ............................................................................. 11
9 DRUG INTERACTIONS .............................................................................................. 12
9.4 Drug-Drug Interactions .......................................................................................... 12
9.5 Drug-Food Interactions .......................................................................................... 12
9.6 Drug-Herb Interactions .......................................................................................... 12
9.7 Drug-Laboratory Test Interactions......................................................................... 12
10 CLINICAL PHARMACOLOGY ...................................................................................... 12
10.1 Mechanism of Action ....................................................................................... 12
10.2 Pharmacodynamics .......................................................................................... 13
10.3 Pharmacokinetics ............................................................................................. 14
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 15
PART II: SCIENTIFIC INFORMATION ..................................................................................... 16
13 PHARMACEUTICAL INFORMATION .......................................................................... 16
14 CLINICAL TRIALS ...................................................................................................... 17
14.1 Trial Design and Study Demographics ............................................................. 17
14.2 Study Results .................................................................................................... 17
14.3 Comparative Bioavailability Studies ................................................................ 17
15 MICROBIOLOGY ...................................................................................................... 18
16 NON-CLINICAL TOXICOLOGY .................................................................................... 18
PATIENT MEDICATION INFORMATION ................................................................................ 22
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
IMODIUM® Complete (Loperamide Hydrochloride and Simethicone) is indicated:
- as an adjunct to rehydration therapy for the symptomatic control of acute, nonspecific diarrhea associated with gas-related abdominal discomfort, such as distention, bloating, flatulence, abdominal pain and cramping.
Treatment of diarrhea with IMODIUM® Complete is only symptomatic. Whenever an underlying etiology can be determined, specific treatment should be given when appropriate (or when indicated).
1.1 Pediatrics
Pediatrics (<12 years of age): The use of Loperamide hydrochloride/Simethicone is not recommended for children under 12 years of age except on the advice of a physician.
Loperamide hydrochloride/Simethicone should not be given to children under 6 years of age without medical prescription and supervision.
Loperamide hydrochloride/Simethicone is contraindicated for use in children under 2 years of age.
1.2 Geriatrics
No dose adjustments are required for the elderly.
2 CONTRAINDICATIONS
- Loperamide hydrochloride/Simethicone is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging section of the product monograph.
- Loperamide hydrochloride/Simethicone is contraindicated for use in children under 2 years of age.
- Loperamide hydrochloride/Simethicone is contraindicated in those in whom constipation must be avoided.
- Loperamide hydrochloride/Simethicone should not be used in the case of acute dysentery that is characterized by blood in stools and elevated temperature. Fluid and electrolyte depletion may occur in patients who have diarrhea. The use of Loperamide hydrochloride/Simethicone does not preclude the administration of appropriate fluid and electrolyte therapy.
- Loperamide hydrochloride/Simethicone should not be used in patients with bacterial enterocolitis caused by invasive organisms including Salmonella, Shigella, and Campylobacter.
- Loperamide hydrochloride/Simethicone must not be used in patients with acute ulcerative colitis or pseudomembranous colitis associated with broad-spectrum antibiotics. In such patients, agents which inhibit intestinal motility or delay intestinal transit time have increased the possible risk of significant sequelae including ileus, megacolon and toxic megacolon. Loperamide hydrochloride/Simethicone therapy should be discontinued promptly if abdominal distention occurs or if untoward symptoms develop. In general, Loperamide hydrochloride/Simethicone should not be used when the inhibition of peristalsis is to be avoided.
- IMODIUM® Complete should not be used in patients who have difficulty swallowing.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- IMODIUM® Complete should be used with special caution in children under 12 years of age because of greater variability of response and possible difficulty of swallowing.
- Hepatic Impairment: Although no pharmacokinetic data are available in patients with hepatic impairment, IMODIUM® Complete should be used with caution in such patients because of reduced first pass metabolism. (see Warnings and Precautions).
4.2 Recommended Dose and Dosage Adjustment
Adults and children 12 years of age and older: Swallow 2 IMODIUM® Complete after the first loose bowel movement and one caplet after each subsequent loose bowel movement, up to a maximum of 4 caplets a day for no more than 2 days.
Children 6-11 years of age: IMODIUM® Complete is not recommended for children under 12 years of age except on the advice of a physician. The proposed dose that may be used: Swallow 1 IMODIUM® Complete Caplet after the first loose bowel movement and ½ caplet after each subsequent loose bowel movement, up to a maximum 3 caplets (for ages 9- 11 years) or maximum 2 caplets (for ages 6-8 years) per day, for no longer than 2 days.
Geriatrics (> 65 years of age): No dose adjustments are required for the elderly.
Renal Impairment: No dosage adjustment necessary in renal impairment.
4.4 Administration
IMODIUM® Complete should be taken by mouth and can be taken at any time of day. The caplets should be taken with a full (250 mL) glass of water.
Drink plenty of clear fluids to help prevent dehydration which may accompany diarrhea.
Take only on an empty stomach (1 hour before or 2 hours after a meal).
5 OVERDOSAGE
Symptoms:
In case of overdosage (including relative overdosage due to hepatic dysfunction), central nervous system depression (stupor, coordination, abnormality, somnolence, miosis, muscular hypertonia, respiratory depression), urinary retention and paralytic ileus may occur. Children may be more sensitive to CNS effects than adults.
In clinical trials with loperamide hydrochloride, an adult who took three 20 mg doses within a 24-hour period was nauseated after the second dose and vomited after the third dose. In studies designed to examine the potential for side effects, intentional ingestion of up to 60 mg of loperamide hydrochloride in a single dose to healthy subjects resulted in no significant adverse effects.
In individuals who have intentionally ingested overdoses (reported in doses from 40 mg up to 792 mg per day) of loperamide HCl, QT interval and QRS complex prolongation, and/or serious ventricular arrhythmias, including Torsade de Pointes, have been observed (see Warnings and Precautions). Fatal cases have also been reported. Abuse, misuse and/or overdose with excessively large doses of loperamide may unmask Brugada syndrome. Brugada syndrome is an inherited cardiac electrophysiology disorder that results in an alteration of the transmembrane ion currents involved in the cardiac action potential. Patients with Brugada syndrome typically do not have structural heart disease but have a higher risk of syncope and cardiac death. Upon cessation, cases of drug withdrawal syndrome have been observed in individuals abusing, misusing, or intentionally overdosing with excessively large doses of loperamide.
Treatment:
Clinical trials have demonstrated that slurry of activated charcoal administered promptly after ingestion of loperamide hydrochloride can reduce the amount of drug which is absorbed into the systemic circulation by as much as nine fold. Slurry of 100 gms of activated charcoal should be administered orally as soon as fluids can be retained.
In cases of overdose, ECG monitoring for QT interval prolongation should be initiated.
If CNS symptoms of overdose occur, naloxone can be given as an antidote. Since the duration of action of loperamide is longer than that of naloxone (1 to 3 hours), repeated treatment with naloxone might be indicated. Therefore, the patient should be monitored closely for at least 48 hours in order to detect possible CNS depression.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
IMODIUM® Complete (white caplet with a vanilla odour, debossed with “IMO” on one side and scored and debossed with “2" and “125" on the other side) each contain 2 mg of loperamide hydrochloride and 125 mg of simethicone and are packaged in blister packs of 20 caplets and 40 caplets.
7 WARNINGS AND PRECAUTIONS
General
If clinical improvement is not observed within 48 hours, the administration of Loperamide hydrochloride/Simethicone should be discontinued and patients should be advised to consult their physician.
In case of accidental ingestion of Loperamide hydrochloride/Simethicone by children, see OVERDOSE section.
The use of higher than the recommended doses for control of the diarrhea may lead to abnormal heart rhythms and serious cardiac events leading to death.
Tiredness, dizziness, or drowsiness may occur in the setting of diarrheal symptoms treated with loperamide. Therefore, it is advisable to use caution when driving a car or operating machinery.
Abuse and misuse, as an opioid substitute, have been described in individuals with opioid addiction.
Dependence/Tolerance
Physical dependence to loperamide hydrochloride in humans has not been observed at the recommended dosage. Upon cessation, cases of drug withdrawal syndrome have been observed in individuals abusing, misusing, or intentionally overdosing with excessively large doses of loperamide (see OVERDOSAGE section). Studies in morphine-dependent monkeys demonstrated that loperamide hydrochloride at doses above those recommended for humans prevented signs of morphine withdrawal. However, in humans, the naloxone challenge pupil test, which when positive indicates opiate-like effects was negative, when performed after a
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Caplets / Loperamide Hydrochloride, 2 mg & Simethicone, 125 mg | acesulfame potassium, croscarmellose sodium, dibasic calcium phosphate, flavour, maltodextrin, microcrystalline cellulose, propylene glycol, stearic acid |
single high dose, or after more than two years of therapeutic use of loperamide hydrochloride. There is no evidence of any dependence potential for simethicone.
Hepatic/Biliary/Pancreatic
Patients with hepatic dysfunction should be monitored for signs of central nervous system (CNS) toxicity due to the extensive first pass metabolism of loperamide in the liver. IMODIUM® Complete must be used with caution in patients with hepatic impairment as it may result in a relative overdose leading to CNS toxicity.
Immune
HIV-infected patients treated with Loperamide hydrochloride/Simethicone for diarrhea should have therapy stopped at the earliest signs of abdominal distension. There have been isolated reports of obstipation with an increased risk for toxic megacolon in AIDS HIV-infected patients with infectious colitis from both viral and bacterial pathogens treated with loperamide hydrochloride.
Neurologic
Loperamide hydrochloride/Simethicone should be used with special caution in young children and those with compromised blood brain barrier (eg, meningitis) because of the greater variability of response in these groups. Dehydration, particularly in young children, may further influence the variability of response to Loperamide hydrochloride/Simethicone.
Renal
Since the majority of loperamide is metabolized, and metabolites or the unchanged drug is excreted in the feces, dose adjustments in patients with a kidney disorder are not required.
7.1 Special Populations
7.1.1 Pregnant Women
Safe use of Loperamide hydrochloride/Simethicone during pregnancy has not been established. Reproduction studies performed with loperamide hydrochloride in the rat and the rabbit revealed no evidence of impaired fertility or harm to the fetus at dosage levels up to 30-fold the therapeutic dose for man. Therefore, Loperamide hydrochloride / Simethicone should be used in pregnant women only when, in the opinion of the physician, the potential benefits outweigh the potential risks.
Although there are no indications that loperamide or simethicone possess teratogenic or embryotoxic properties, the anticipated therapeutic benefits should be weighed against potential hazards before Loperamide hydrochloride/Simethicone is given during pregnancy, especially during the first trimester.
7.1.2 Breast-feeding
Small amounts of loperamide may appear in human breast milk. Therefore, Loperamide hydrochloride/Simethicone is not recommended during breast-feeding.
7.1.3 Pediatrics
Pediatrics (<12 years of age):
The use of Loperamide hydrochloride/Simethicone is not recommended for children under 12 years of age except on the advice of a physician. See DOSAGE AND ADMINISTRATION.
Loperamide hydrochloride/Simethicone should be used with special caution in young children because of the greater variability of response in these groups. Dehydration, particularly in young children, may further influence the variability of response to Loperamide hydrochloride/Simethicone.
In patients with (severe) diarrhea, especially in children, fluid and electrolyte depletion may occur. In such cases administration of appropriate fluid and electrolyte replacement should be considered.
Loperamide hydrochloride/Simethicone should not be given to children under 6 years of age without medical prescription and supervision.
Loperamide hydrochloride/Simethicone is contraindicated for use in children under 2 years of age.
8 ADVERSE REACTIONS
The standard for defining frequency terms will be based on the Council for International Organizations of Medical Science (CIOMS) convention. Specifically:
Very common (>1/10) Common (>1/100, <1/10) Uncommon (>1/ 1,000, <1/100) Rare (>1/10,000, <1/1,000) Very rare (<1/10,000), including isolated reports
8.1 Adverse Reaction Overview
With use of loperamide hydrochloride, occasional hypersensitivity reactions have been reported, such as skin rash and urticaria, and extremely rare cases of anaphylactic reaction (including anaphylactic shock) and bullous eruption including Toxic Epidermal Necrolysis. In the majority of these cases, the patients were on other medications which may have caused or contributed to the events.
The adverse effects reported in adults during clinical trials with Loperamide hydrochloride/Simethicone Chewable Tablets were generally of a minor and self-limiting nature and infrequent: nausea, altered taste (<2%); headache, chills, dry mouth, cough, skin rash (<1%); constipation (<1%) and/or abdominal distension have also been reported. In some very rare cases, particularly in which the treatment information had not been respected, these latter effects have been associated with ileus (including paralytic ileus). Urinary retention has been reported rarely.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying andapproximating rates of adverse drug reactions in real-world use.
Common Adverse Events in Patients with Acute Diarrhea: The following adverse events with an incidence of 1.0% or greater or classified as “common”, which were more frequently reported in patients on loperamide/simethicone than on placebo, are presented in the table below:
| Table 1 - Listing of Common Adverse Events in patients with acute diarrhea with an Incidence of 1.0% or greater as measured in Clinical Trials. | |||||||||
Loperamide 2 mg + Simethicone 125 mg n= 462 (%) | Loperamide 2 mg n= 456 (%) | Simethicone 125 mg n= 462 (%) | Placebo n= 456 (%) | ||||||
Gastrointestinal disorders Nausea Nervous System disorders Dysgeusia | 1.7 1.9 | 0.4 4.2 | 0.4 0.0 | 0.4 0.2 | |||||
The adverse event with an incidence of 1.0% or greater or classified as “common”, which was more frequently reported in patients on placebo than on loperamide/simethicone, was: dizziness.
8.5 Post-Market Adverse Reactions
Loperamide/Simethicone is a combination product containing loperamide hydrochloride. Therefore, adverse experiences considered significant for loperamide hydrochloride will also be included in this section due to the theoretical expectation of a similar adverse event profile even in the absence of actual reports for Loperamide/Simethicone.
Adverse events which may be causally related to the administration of Loperamide/Simethicone that have come to light as a result of reports received in relation to administration of the marketed product are provided in this section. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Immune System Disorders: Allergic reactions and in some cases severe hypersensitivity reactions including anaphylactic reaction, anaphylactic shock and anaphylactoid reactions have been reported for loperamide hydrochloride.
Nervous System Disorders: Dizziness, loss of consciousness, coordination abnormality, hypertonia, stupor and depressed level of consciousness have been reported for loperamide hydrochloride.
Eye Disorders: Miosis has been reported for loperamide hydrochloride.
Gastrointestinal Disorders: Abdominal pain/abdominal pain upper, nausea, constipation, flatulence, vomiting and dyspepsia.
Abdominal distension, ileus (including paralytic ileus) and megacolon including toxic megacolon have been reported for loperamide hydrochloride (see PRECAUTIONS).
Renal and Urinary Disorders: Urinary retention has been reported for loperamide hydrochloride
Psychiatric System Disorders: Drowsiness
Skin and Subcutaneous Tissue Disorders: Rash, urticaria and pruritus.
Angioedema, and bullous eruptions including Stevens-Johnson syndrome, erythema multiforme, and toxic epidermal necrolysis have been reported for loperamide hydrochloride.
Special Senses: Dysgeusia
A number of the adverse events reported during the clinical investigations and post-marketing experience with loperamide are frequent symptoms of the underlying diarrheal syndrome (abdominal pain/discomfort, nausea, vomiting, dry mouth, tiredness, drowsiness, dizziness, constipation, and flatulence). These symptoms are often difficult to distinguish from undesirable drug effects.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
Non-clinical data have shown that loperamide is a P-glycoprotein substrate. Concomitant administration of loperamide (16 mg single dose) with quinidine, or ritonavir, which are both P-glycoprotein inhibitors, resulted in a 2 to 3-fold increase in loperamide plasma levels. The clinical relevance of this pharmacokinetic interaction with P-glycoprotein inhibitors, when loperamide is given at recommended dosages, is unknown.
The concomitant administration of loperamide (4 mg single dose) and itraconazole, an inhibitor of CYP3A4 and P glycoprotein, resulted in a 3 to 4 fold increase in loperamide plasma concentrations. In the same study a CYP2C8 inhibitor, gemfibrozil, increased loperamide by approximately 2 fold. The combination of itraconazole and gemfibrozil resulted in a 4 fold increase in peak plasma levels of loperamide and a 13 fold increase in total plasma exposure. These increases were not associated with central nervous system (CNS) effects as measured by psychomotor tests (i.e., subjective drowsiness and the Digit Symbol Substitution Test).
The concomitant administration of loperamide (16 mg single dose) and ketoconazole, an inhibitor of CYP3A4 and P-glycoprotein, resulted in a 5 fold increase in loperamide plasma concentrations. This increase was not associated with increased pharmacodynamic effects as measured by pupillometry.
Concomitant treatment with oral desmopressin resulted in a 3 fold increase of desmopressin plasma concentrations, presumably due to slower gastrointestinal motility.
It is expected that drugs with similar pharmacological properties may potentiate loperamide’s effect and that drugs that accelerate gastrointestinal transit may decrease its effect.
Since simethicone is not absorbed from the gastrointestinal tract, no relevant interactions between simethicone and other drugs are expected.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Diarrhea may be defined as a failure or imbalance of one or a combination of activities in the gut which include secretion, absorption and motility. Loperamide hydrochloride has been shown to act on all of these functions via cholinergic, non-cholinergic, opiate and non-opiate receptor-mediated mechanisms. In this way, loperamide HCl effectively reduces fecal output and frequency, improves stool consistency and relieves symptoms of abdominal cramping and fecal incontinence.
10.2 Pharmacodynamics
Loperamide binds to the opiate receptor in the gut wall. Consequently, it inhibits the release of acetylcholine and prostaglandins, thereby reducing propulsive peristalsis, increasing intestinal transit time and enhancing resorption of water and electrolytes. Loperamide does not change the physiological flora. Loperamide increases the tone of the anal sphincter, thereby reducing incontinence and urgency. Loperamide does not act centrally. Loperamide has a high affinity for the gut wall and is extensively metabolized on first-pass through the liver. Therefore, loperamide hardly reaches the systemic circulation.
Simethicone is an inert surface-active agent with anti-foaming properties which relieves symptoms associated with diarrhea, particularly flatulence, abdominal discomfort, bloating and cramping.
Animal Data: Motility in the gut is the result of cholinergic and noncholinergic biphasic stimulation of the intestinal musculature. The cholinergic mediator, acetylcholine (ACh), is responsible for the first phase of peristalsis, while prostaglandins (PG) are thought to mediate the second phase. Loperamide has been shown to inhibit release of both ACh and PG from isolated guinea pig ileum, as well as directly block the action of PG on smooth muscle preparations from rats. The net result is a reduction in the number of peristaltic waves, the fluid expelled by each wave, and overall gut motility. Loperamide produces a sustained inhibition of the peristaltic activity of the guinea pig ileum in vitro at doses as low as 0.005 mg/L. The inhibitory effects are dose-related, the activity of both the longitudinal and circular muscles being affected.
Loperamide, administered orally, blocks castor oil-induced diarrhea in rats and has an ED50 value of 0.15 mg/kg (1 hour). The antidiarrheal action is rapid, regular and long-lasting. Loperamide has also been shown to decrease secretion caused by E. coli enterotoxin both in vivo and in vitro. This is accomplished by increasing the chloride secretion into the plasma at the serosal membrane, thus effectively decreasing chloride as well as sodium and water loss at the mucosal surface. This effect on chloride secretion can be blocked with naloxone.
Unlike fentanyl, morphine, codeine and diphenoxylate, chronic administration of loperamide in doses as high as 300 times the antidiarrheal dose, does not produce physical dependence in mice or narcotic withdrawal symptoms in rats, and no preference for loperamide can be experimentally established.
Simethicone acts in the stomach and intestines by changing the surface tension of gas bubbles, enabling them to coalesce. This defoaming action relieves flatulence by dispersing and preventing the formation of mucus-surrounded gas pockets in the GI tract; thus, excess gas is freed and eliminated more easily from the stomach by belching or from the intestines by passing flatus.
10.3 Pharmacokinetics
Diarrhea is often associated with gas-related abdominal discomfort. Simethicone (poly-dimethylsiloxane) acts as a defoaming agent in the stomach and intestines, by changing the surface tension of gas bubbles, thus enabling them to coalesce and be eliminated more easily.
The combination of loperamide hydrochloride and simethicone has been shown in clinical trials to be overall more effective than either of its active components in controlling the symptoms of both diarrhea and gas-related discomfort.
Only very small amounts (0.3%) of the administered dose of loperamide are absorbed from the G.I. tract. Pharmacokinetic investigation with the loperamide HCl/simethicone combination product was based on loperamide plasma levels of 24 healthy adult volunteers following oral administration of 4 chewable tablets or four 2mg loperamide HCl capsules, each treatment containing a total of 8 mg loperamide hydrochloride. Plasma levels of unchanged loperamide remained below 1.5 ng/mL throughout the 48-hour study period. Peak loperamide levels (Cmax 0.95ng/mL) from the loperamide HCl/simethicone chewable tablets were reached at 6.6 hours following ingestion, with apparent elimination half-life of about 22 hours and an AUCinf of 26.7ng.hr/mL. For the loperamide HCl capsules the Cmax (1.36ng/mL) was reached at 4.3 hours, the apparent elimination half-life was 18.3 hours, and the AUCinf was 28.3ng.hr/mL. Thus, the absorption of loperamide from the chewable tablet combination occurs at a slower rate than from regular loperamide (IMODIUM®) capsules.
There is no evidence that simethicone is absorbed from the G.I. tract. It is thought to be physiologically inert and devoid of toxicity.
Absorption: Most ingested loperamide is absorbed from the gut, but as a result of significant first pass metabolism, systemic bioavailability is only approximately 0.3%. The simethicone component of loperamide-simethicone is not absorbed.
Distribution: Studies on distribution in rats show a high affinity for the gut wall with a preference for binding to receptors of the longitudinal muscle layer. The plasma protein binding of loperamide is 95%, mainly to albumin. Non-clinical data have shown that loperamide is a P-glycoprotein substrate.
Metabolism: Loperamide is almost completely extracted by the liver, where it is predominantly metabolized, conjugated and excreted via the bile. Oxidative N-demethylation is the main metabolic pathway for loperamide, and is mediated mainly through CYP3A4 and CYP2C8. Due to this very high first pass effect, plasma concentrations of unchanged drug remain extremely low.
Animal Data:
Tritium-labelled loperamide was administered orally to eight groups of five fasted male Wistar rats (250 ± 10 g) at a dosage of 1.25 mg/kg. Urine and feces were collected for up to 4 days. The rats were killed at different times from 1 to 96 hours after drug administration in order to examine blood, organs and tissues. In one rat, the bile was cannulated for 48 hours. The radioactive content of each sample was measured and the fractions due to loperamide, metabolites, and volatile radioactivity were determined by the inverse isotope dilution technique and lyophilization. Only 5% of the drug and its metabolites was recovered from the urine, the bulk being excreted with the feces. Drug plasma levels were low at all times. Maximum plasma levels of unchanged loperamide did not exceed 0.22% of the administered dose corresponding to about 75 mg/mL of plasma. The gastrointestinal tract contained about 85% of loperamide 1 hour after dosing. Brain levels were extremely low, never exceeding 22 ng/g brain tissue, or 0.005% of the administered dose. The existence of an enterohepatic shunt was shown, but the uptake of the drug into the general circulation was low. Differentiation between total radioactivity and nonvolatile radioactivity demonstrated that most of the residual organ radioactivity was due to tritiated water.
Elimination Excretion of the unchanged loperamide and the metabolites mainly occurs through the feces. The half-life of loperamide in man is about 11 hours with a range of 9-14 hours.
Special Populations and Conditions
- Pediatrics: No pharmacokinetic studies were performed in the pediatric population.
11 STORAGE, STABILITY AND DISPOSAL
Store at controlled room temperature (15-30°C).
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance (1 of 2)
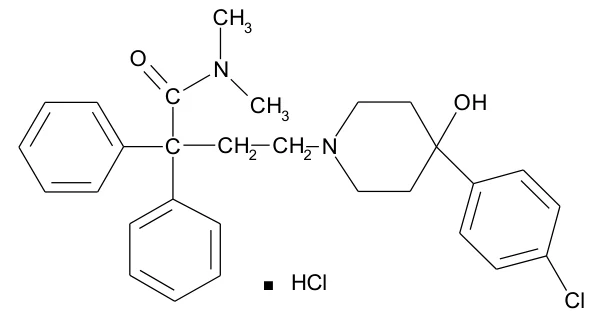
Proper name: Loperamide Hydrochloride, USP
Chemical name: 4-(4-Chlorophenyl)-4-hydroxy-N,N-dimethyl-α,α-diphenyl-1- piperidinebutyramide hydrochloride
Molecular formula and molecular mass: C29 H33 Cl N2 O2. HCl, 513.51
Structural formula:
Physicochemical properties: White to faintly yellowish, amorphous or microcrystalline powder; soluble in methanol, chloroform and ethanol, slightly soluble in water and ether; practically insoluble at physiological pH (<0.002%); melts, with decomposition, between 220 and 228°C. pKa value is 8.66.
Drug Substance (2 of 2)
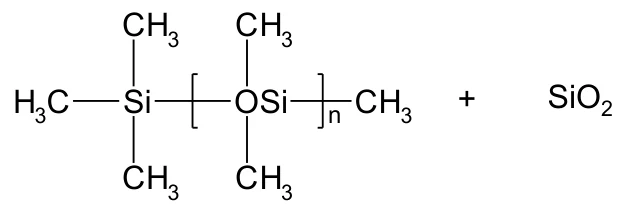
Proper name: Simethicone, USP
Chemical name: α-(Trimethylsilyl)-ω-methyl-poly[oxy(dimethylsilylene)] mixture with silicon dioxide.
Structural formula:
Physicochemical properties: Light grey, oily liquid; immiscible with water, alcohol; miscible with chloroform, ether; refractive index (nD25): 1.400-1.410; density: 0.964-0.984.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Canada Reference Product: The efficacy of Loperamide hydrochloride/Simethicone Chewable Tablets in the treatment of acute diarrhea with associated gas-related discomfort was investigated in three pivotal, randomized, double-blind, parallel-group clinical trials, in comparison with loperamide alone, simethicone alone and placebo. A total of over 350 patients received the combination product in these studies.
14.2 Study Results
Canada Reference Product: The combination product shortened the median duration of the diarrheal episodes by 75%, 71% and 42% respectively in these three studies and was significantly superior (p=0.0001) to both placebo and simethicone alone in two of them. When also compared to loperamide alone, the combination product reduced the median duration by 59% (p=0.0001) and by 30% (p=0.0586). In the same two studies, 69% to 79% of the patients who received the loperamide HCl/simethicone combination had no more unformed stools by 24 hours after initiation of therapy, compared to 8% to 30% of patients who were given placebo (p=0.0001, both studies).
In two studies, the loperamide HCl/simethicone combination was also significantly (p=0.0001) more effective than all of the other treatments in decreasing the time to complete relief of intestinal gas symptoms. Compared to simethicone alone, the combination product reduced the median duration of gas symptoms by 43% (p=0.001) and 48% (p=0.001) in these two primary studies.
14.3 Comparative Bioavailability Studies
A single dose [4 x (2 mg loperamide/125 mg simethicone)], open-label, randomized, two-treatment crossover study comparing the bioavailability of loperamide from IMODIUM® Complete and IMODIUM® Complete Chewable Tablets was conducted in 28 healthy male and female volunteers under fasting conditions. Results from the study are presented in the table below:
Table 2 - Summary of the Comparative Bioavailability Data
LOPERAMIDE 4 x (2 mg loperamide HCl/125 mg simethicone) From Measured Data Geometric Mean Arithmetic Mean (CV%) | ||||
| PARAMETER | TEST IMODIUM® Complete* | REFERENCE IMODIUM® Complete Chewable Tablets* | % RATIO OF GEOMETRIC MEANS | 90% CONFIDENCE INTERVAL |
AUCT (ng.h/ml) | 29.3 32.4 (51) | 27.4 30.0 (49) | 106.9 | 102.1 – 113.3 |
AUCI (ng.h/ml) | 33.6 37.1 (52) | 31.4 34.6 (52) | 107.0 | 102.0 – 113.0 |
CMAX (ng/ml) | 1.70 1.94 (62) | 1.58 1.74 (53) | 107.6 | 101.9 – 115.2 |
| TMAX** (h) | 5.7 (14) | 5.9 (16) | ||
| T½** (h) | 16.3 (27) | 16.2 (20) | ||
*Manufactured by McNeil Consumer Healthcare
** Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Toxicity studies on loperamide of up to 12 months in the dog and 18 months in the rat have not shown any toxic effect other than some reduction in body weight gain and food consumption at daily doses of up to 5mg/kg/day {30 times the Maximum Human Use Level (MHUL)} and 40mg/kg/day (240 times MHUL) respectively. The No Toxic Effect Levels (NTEL) in these studies were 1.25mg/kg/day (8 times MHUL) and 10mg/kg/day (60 times MHUL) in dogs and rats respectively. Results of in vivo and in vitro studies carried out indicated that loperamide is not genotoxic. There was no carcinogenic potential. In reproduction studies, very high doses of loperamide (40 mg/kg/day-240 times MHUL) impaired fertility and fetal survival in association with maternal toxicity in rats. Lower doses had no effects on maternal or fetal health and did not affect peri- and post-natal development.
Pre-clinical effects were observed only at exposures considered sufficiently in excess of the maximum human exposure, indicating little relevance to clinical use.
Simethicone is a member of the class of linear polydimethylsilicones, which have been in wide general and medicinal use for many years and are regarded as biologically inert and not exhibiting toxic properties. Simethicone has not been the subject of specific animal toxicity studies.
The low toxicity of simethicone has been generally recognized in over four decades of widespread use. In a 13-week feeding study in rats, fed a diet containing up to 0.2% silicone, histologic examination of the tissues of 50 sacrificed animals (tissues included heart, lungs, liver, spleen, stomach, intestines, kidneys, thymus, thyroid and adrenals) did not reveal any gross or microscopic abnormalities attributable to treatment.
Loperamide Hydrochloride – Acute: The acute toxicity of loperamide hydrochloride (7-day mortality) has been assessed in several species by various routes. The following values were obtained:
| Species | Routes of Administration | LD50 (mg/kg) |
| Mouse | p.o. s.c. i.p. | 105 75 28 |
| Adult rat | p.o. i.v. | 185 5.1 |
| Young male rat | p.o. | 135 |
| Young female rat | p.o. | 261 |
| Guinea pig | p.o. | 41.5 |
| Dog | p.o. i.v. | >40 2.8 |
The therapeutic ratio (LD50/ED50 "8 hour" castor oil test) for loperamide hydrochloride when given orally to rats is 1:125. This compares to diphenoxylate, morphine and codeine which have therapeutic ratios of 1:55, 1:13 and 1:5.5, respectively. As well, the oral safety margin is wider than the intravenous.
Loperamide Hydrochloride – Subacute (Rats): Wistar rats (10 males and 10 females per dose group) were given loperamide hydrochloride in their diet at 40, 10 and 2.5 mg/100 g of food seven days a week for 15 weeks. Control animals received diet only. No drug-induced mortality was observed. Health, behaviour and appearance were normal in all groups, except that the 40 mg/100 g food-dosed animals showed a swollen abdomen during the first four weeks. No effects could be evidenced on hemograms, serum analyses and urinalyses except a decrease of creatinine in the dosed animals. Weight gain and food consumption were lower in the 40 mg/100 g food-dosed animals. At this 40 mg/100 g food dose, some minor macroscopic and microscopic changes are probably related to reduced food consumption.
Loperamide Hydrochloride – Chronic (Rats): Wistar rats (30 males and 30 females per dose group) were given loperamide hydrochloride in their diet at 40, 10 and 2.5 mg/100 g of food seven days a week, while control animals received diet only. Interim sacrifices of 20 animals per dose group were carried out at 6, 12 and 18 months on study. No drug-induced mortality was observed. Health, behaviour and appearance were normal in all groups throughout the entire experimental period. Weight gain and food consumption were lower in the 40 mg/100 g food-dosed animals especially during the initial 3 months of dosing. As for the subacute toxicity study, no effects could be evidenced on hemograms, serum analyses and urinalyses, except a decrease of creatinine in 10 and 40 mg/100 g food-dosed animals and dose-related hyperemia of the vascular system of the intestine and mesenterium, but no other dose- or drug-related changes.
Loperamide Hydrochloride – Chronic (Dogs):
Beagle dogs (3 males and 3 females per dose group) were given loperamide hydrochloride in gelatine capsules at 5.0, 1.25 and 0.31 mg/kg six days a week for 12 months. Some depression was seen during the first week of drug administration at 1.25 and 5 mg/kg. Behaviour and appearance were normal during the rest of the experiment, except that haemorrhagic stools were seen from time to time at 5 mg/kg and soft stools at 0.31 and 1.25 mg/kg, especially during the first 6 weeks of drug administration. EquGross pathologic and histologic examinations failed to reveal any dose or drug-related changes.
Reproductive and Developmental Toxicology:
Fertility and General Reproductive Performance in Rats:
Adult Wistar rats (2 groups per dose level) were given loperamide hydrochloride in their diet at 40, 10 and 2.5 mg/100 g of food as follows:
| Group A | 20 males - drug given 60 days premating 20 females - no drug |
| Group B | 20 males - no drug 20 females - drug 14 days premating plus throughout gestation |
Loperamide hydrochloride has no effect on male fertility when administered orally to males for at least 60 days prior to mating at doses of 40, 10 and 2.5 mg/100 g food, or approximately 40, 10 and 2.5 mg/kg. No pregnancies occurred among the females dosed at 40 mg/100 g food for at least 14 days prior to mating and during the complete period of gestation. No data on offspring are available for this group. In the other groups, there was no difference in the number of implantations per dam, litter size, percentage of live, dead and resorbed fetuses; distribution of live, dead and resorbed fetuses in the left and right uterine horns; and body weight of live young. There was no evidence of teratogenicity.
Peri- and Post-natal Studies in Rats:
Mature female Wistar rats (20 animals per dose group) were given loperamide hydrochloride in their diet at 40, 10 and 2.5 mg/100 g of food from day 16 of pregnancy throughout a three-week lactation period. Control animals received diet only. Food consumption and body weight gain were affected in the 40 mg/100 g food-dosed females, resulting in a decrease of fetal weight gain and survival rate. There was no difference between the control group and the 2.5, 10 and 40 mg/100 g food-dosed groups in pregnancy rate, duration of gestation, litter size, percentage of live and stillborn fetuses. There were no abnormalities in any young.
Teratology (Rats): Pregnant primiparous female Wistar rats (20 animals per dose group) were given loperamide hydrochloride in their diet at 40, 10 and 2.5 mg/100 g of food from day 6 through day 15 of pregnancy. On day 22, fetuses were delivered by caesarean section. At 40 mg/100 g food, only 1 female out of 20 became pregnant, thus confirming the results of the fertility study in rats. There was no significant difference between the control group and the 2.5 and 10 mg/100 g food-dosed groups in pregnancy rate; number of implantations per dam; litter size, percentage of live, dead and resorbed fetuses; distribution of live, dead and resorbed fetuses in the left and right uterine horns; and body weight of live young. No macroscopic, visceral, or skeletal malformations were seen.
Teratology (Rabbits): Primiparous female New Zealand white rabbits, fertilized by artificial insemination (15-20 animals per dose group) were given loperamide hydrochloride by gavage at 40, 20 and 5 mg/kg from day 6 through 18 postinsemination. Control animals received an equivalent volume of isotonic saline vehicle. Animals were sacrificed on day 28. No differences in pregnancy rate could be noted. The mortality rate was higher in the 40 mg/kg dosed rabbits and was mainly due to enteritis. There was no difference in pregnancy rate between dosed and controlled. The average weight gain and litter size of treated females was affected, and the average weight at delivery was lower in the young of the 40 mg/kg dosed females. There was little or no difference in the percentage of live, dead and resorbed fetuses. No macroscopic visceral or skeletal abnormalities were seen except in 1 fetus with bifurcated ribs of the control group and 1 fetus with cyclopia of the 40 mg/kg dosed group.
It is not believed that this case of cyclopia is drug-related as cases of cyclopia and agnathia have been encountered in control fetuses of earlier experiments with the same New Zealand rabbit strain.