


Product Monograph - Jamp Acitretin
RECENT MAJOR LABEL CHANGES
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 01/2026 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Psychiatric | 01/2026 |
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
- 1
INDICATIONS ............................................................................................................... 4
- 1.1 Pediatrics (< 18 years of age) ................................................................................ 4
- 1.2 Geriatrics (≥ 65 years of age) .................................................................................. 4
- 2 CONTRAINDICATIONS .................................................................................................. 4
- 3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 6
- 4
DOSAGE AND ADMINISTRATION.................................................................................. 6
- 4.1 Dosing Considerations .......................................................................................... 6
- 4.2 Recommended Dose and Dosage Adjustment ...................................................... 7
- 4.4 Administration ...................................................................................................... 7
- 4.5 Missed Dose .......................................................................................................... 7
- 5 OVERDOSAGE .............................................................................................................. 7
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION, AND PACKAGING ................................ 8
- 7
WARNINGS AND PRECAUTIONS ................................................................................... 8
- 7.1 Special Populations ............................................................................................. 15
- 7.1.1 Pregnancy ....................................................................................................... 15
- 7.1.2 Breast-feeding ................................................................................................. 15
- 7.1.3 Pediatrics ........................................................................................................ 16
- 7.1.4 Geriatrics (≥ 65 years of age) ............................................................................ 16
- 8
ADVERSE REACTIONS ................................................................................................. 16
- 8.1 Adverse Reaction Overview ................................................................................ 16
- 8.2 Clinical Trial Adverse Reactions........................................................................... 16
- 8.3 Less Common Clinical Trial Adverse Reactions (< 1.0%) ...................................... 18
- 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 19
- 8.5 Post-Market Adverse Reactions .......................................................................... 21
- 9
DRUG INTERACTIONS ................................................................................................ 22
- 9.1 Serious Drug Interactions .................................................................................... 22
- 9.2 Drug Interactions Overview ................................................................................ 22
- 9.3 Drug-Behavioural Interactions ............................................................................ 22
- 9.4 Drug-Drug Interactions ....................................................................................... 23
- 9.5 Drug-Food Interactions ....................................................................................... 23
- 9.6 Drug-Herb Interactions ....................................................................................... 23
- 9.7 Drug-Laboratory Test Interactions ...................................................................... 24
- 10
CLINICAL PHARMACOLOGY ........................................................................................ 24
- 10.1 Mechanism of Action .......................................................................................... 24
- 10.2 Pharmacodynamics ............................................................................................. 24
- 10.3 Pharmacokinetics ................................................................................................ 24
- 11 STORAGE, STABILITY, AND DISPOSAL......................................................................... 26
- 12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 27
PART II: SCIENTIFIC INFORMATION ....................................................................................... 28
- 13 PHARMACEUTICAL INFORMATION ............................................................................ 28
- 14
CLINICAL TRIALS ........................................................................................................ 28
14.1 Clinical Trial by Indication…………………………………………………………………….………….28
- 14.2 Comparative Bioavailability Studies…………………………………………………………………28
- 15 MICROBIOLOGY ......................................................................................................... 30
- 16 NON-CLINICAL TOXICOLOGY ...................................................................................... 30
- 17 SUPPORTING PRODUCT MONOGRAPHS…………………………………………………………………..41
PATIENT MEDICATION INFORMATION .................................................................................. 42
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JAMP Acitretin (acitretin capsules) is indicated for:
- Severe psoriasis (includes erythrodermic and pustular types)
- Other disorders of keratinization
Severe psoriasis is a condition that involves more than 10% of body surface area or is physically, occupationally or psychologically disabling.
Because of significant adverse effects associated with its use, JAMP Acitretin should be reserved for patients with the diseases listed above when these are unresponsive to or intolerant of standard treatment. JAMP Acitretin should only be prescribed by physicians knowledgeable and experienced in the use of systemic retinoids and who understand the risk of teratogenicity associated with JAMP Acitretin treatment (see 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX,
7 WARNINGS AND PRECAUTIONS, 7.1.1. Pregnancy, 7.1.2 Breast-feeding). It is recommended that renewal prescriptions of JAMP Acitretin be limited to a one-month supply in order to ensure patients return for regular follow-up appointments.
Most patients experience a relapse after discontinuing treatment. Subsequent courses, when clinically indicated, have produced similar therapeutic results.
1.1 Pediatrics (< 18 years of age)
The use of JAMP Acitretin in children is not recommended (see 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics).
1.2 Geriatrics (≥ 65 years of age)
The effects of aging might be expected to increase some risks associated with acitretin treatment (see
7 WARNINGS AND PRECAUTIONS, 7.1.4. Geriatrics).
2 CONTRAINDICATIONS
JAMP Acitretin is contraindicated in pregnancy. JAMP Acitretin is highly teratogenic and must not be used by females who are pregnant or intend to become pregnant.
JAMP Acitretin is also contraindicated in females of childbearing potential unless strict contraception is practiced 4 weeks before, during and for at least 3 years after treatment cessation. JAMP Acitretin must not be used by females who may not use reliable contraception while undergoing treatment and for at least 3 years following discontinuation of treatment. Retinoids are known to cause a very high percentage of severe birth defects as a result of in utero exposure. Potentially any exposed fetus can be affected. There are no accurate means of determining whether an exposed fetus has been affected. The risk of giving birth to a deformed child is exceptionally high if acitretin is taken before or during pregnancy or within 3 years after the last dose, independent of previous treatment duration. Thereafter, the patient and physician should assess the risks and desirability of discontinuing effective contraception, based on the most current information available. All of the conditions in WARNINGS AND PRECAUTIONS must be met before prescribing JAMP Acitretin to any female of childbearing potential. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnancy.
Clinical evidence has shown that concurrent ingestion of acitretin and ethanol has been associated with the formation of etretinate, which has a significantly longer elimination half-life than acitretin.
Because the longer elimination half-life of etretinate would increase the duration of teratogenic potential for female patients, ethanol must not be ingested by female patients either during treatment with JAMP Acitretin or for 2 months after treatment cessation.
If pregnancy does occur during JAMP Acitretin treatment, JAMP Acitretin treatment must be stopped immediately and the physician and patient must discuss the desirability of continuing the pregnancy.
JAMP Acitretin should only be prescribed by physicians knowledgeable in the use of systemic retinoid treatment. See 1 INDICATIONS.
JAMP Acitretin is also contraindicated in the following conditions:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
- Patients with hypersensitivity to other retinoids or to Vitamin A or its metabolites.
- Breast Feeding/Nursing Mothers: Clinical data indicates that acitretin is excreted in human milk. Therefore, nursing mothers should not receive JAMP Acitretin because of the potential for serious adverse reactions in nursing infants. Females should not breastfeed for at least 3 years following discontinuation of JAMP Acitretin.
Consumption of alcohol (in drinks, food, or medicines):
- In females of childbearing potential during treatment with JAMP Acitretin: Alcohol must not be ingested during treatment and for two months after cessation of treatment. Clinical evidence has shown that etretinate, the prodrug of acitretin, can be formed with concurrent ingestion of acitretin and alcohol. Measurable levels of etretinate have been detected in plasma samples of patients administered acitretin capsules. Etretinate is highly teratogenic and has a longer half-life (approximately 120 days) than acitretin. The length of time necessary to wait after termination of JAMP Acitretin treatment to ensure that no etretinate will be detectable in the blood has not been determined. Etretinate has a long elimination phase. When etretinate has been used as primary treatment, etretinate has been found in the blood of some patients up to 2.9 years after discontinuation of treatment.
- Male patients are advised to avoid alcohol or limit consumption during treatment and for 2 months after cessation of treatment.
- It is not known whether substances other than ethanol are associated with transesterification of acitretin to etretinate. See 9.4. DRUG-DRUG INTERACTIONS.
- Patients with severely impaired hepatic or renal function.
- Patients with chronic abnormally elevated blood lipid values.
- Patients taking tetracyclines. Since both acitretin and tetracycline can cause increased intracranial pressure, their combined use is contraindicated. See 9.4. DRUG-DRUG INTERACTIONS.
- Patients taking methotrexate. An increased risk of hepatitis has been reported to result from combined use of methotrexate and etretinate. Consequently, the combination of methotrexate with acitretin is also contraindicated. See 9.4. DRUG-DRUG INTERACTIONS.
- Hypervitaminosis A. Concomitant administration of acitretin and vitamin A or other retinoids is contraindicated due to increased risk of hypervitaminosis A. See 9.4. DRUG-DRUG INTERACTIONS.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Pregnancy Prevention:
JAMP Acitretin should only be prescribed by physicians knowledgeable in the use of systemic retinoids. See 1 INDICATIONS.
Full patient information about the teratogenic risk and the strict pregnancy prevention measures should be given by the physician to all patients, male and female. In addition, when prescribing this drug to female patients of childbearing potential, physicians must use the JAMP Acitretin Pregnancy Prevention Program. The Pregnancy Prevention Program includes two educational booklets: A General Guidelines booklet for all patients (male and female) and a Pregnancy Prevention Program booklet that contains information for females of childbearing potential including mandatory effective contraception and specified pregnancy tests. The information must be reviewed by all patients (male and female) during the initial screening period prior to commencing JAMP Acitretin and guided by the prescribing physician. The Pregnancy Prevention
Program’s Physician Checklist must be completed by the physician when screening any female of childbearing potential. Additionally, the Pregnancy Prevention Program booklet includes Patient Self-Evaluation questions and answers to enhance understanding of teratogenic risk. All patients (male and female) must read and understand and sign the Pregnancy Prevention Program’s Informed Consent Form. See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Reproductive Health, 7.1.1 Pregnancy and 7.1.2 Breast-feeding. The Pregnancy Prevention Program materials are available at www.jampinfo.com.
Hepatic: Cases of jaundice with elevated serum bilirubin and transaminases, toxic hepatitis and acute reversible hepatic injury have occurred in patients taking acitretin capsules in clinical trials. Cases of hepatitis and hepatic-related deaths have occurred in patients taking etretinate (acitretin is the active metabolite). Hepatic function should be checked before starting treatment with JAMP Acitretin and monitored during treatment. See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and Monitoring and Laboratory Tests.
Neurologic: There have been rare reports of pseudotumor cerebri (benign intracranial hypertension) (See 7 WARNINGS AND PRECAUTIONS, Neurologic).
Psychiatric: Treatment with systemic retinoids can cause mood changes including irritability, aggression, depression, psychotic disorder, suicidal ideation/self-harm and suicide (see
7 WARNINGS AND PRECAUTIONS, Psychiatric).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
JAMP Acitretin should only be prescribed by qualified physicians experienced in the use of systemic retinoids who understand the risk of teratogenicity associated with acitretin capsules treatment. When prescribing this drug, physicians must use the JAMP Acitretin Pregnancy Prevention Program. Full patient information about the teratogenic risk and the strict pregnancy prevention measures should be given by the physician to all patients, male and female. See 2 CONTRAINDICATIONS and 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
There is intersubject variation in the pharmacokinetics, clinical efficacy, and incidence of side effects with acitretin capsules. Individualization of dosage is required to achieve maximum therapeutic response while minimizing side effects.
4.2 Recommended Dose and Dosage Adjustment
The capsules should preferably be taken once daily with a meal or following a meal. The following serves a guideline:
Initial Treatment
JAMP Acitretin treatment should be initiated at 25 mg per day, given as a single dose with the main meal. If by four weeks the response is unsatisfactory, and in the absence of toxicity, the daily dose may be gradually increased to a maximum of 75 mg per day. The dose may be reduced if necessary to minimize side effects.
Maintenance Treatment
Psoriasis: Maintenance doses of 25 mg to 50 mg per day may be given after initial response to treatment. The maintenance dose should be based on clinical efficacy and tolerability. It may be necessary in some cases to increase the dose to a maximum of 75 mg per day.
In general, treatment should be terminated when lesions have resolved sufficiently. Relapses may be treated as outlined for initial treatment.
Other Keratinization Disorders: Maintenance doses of 10 mg to a maximum of 50 mg per day may be given for disorders of keratinization.
4.4 Administration
JAMP Acitretin capsules should preferably be taken once daily with a meal or following a meal.
4.5 Missed Dose
A missed dose should be taken as soon as the patient remembers. However, if it is almost time for the next dose, the patient should skip the missed dose and continue with the regular dosing schedule.
Doses should not be doubled up on the following day.
5 OVERDOSAGE
To date, there has been no experience with acute overdose of acitretin capsules. In the event of acute overdosage, acitretin must be withdrawn at once. Evacuation of the stomach should be considered during the first few hours after overdose. Signs and symptoms of overdosage with acitretin capsules are identical to acute vitamin A toxicity, i.e., severe headache, nausea or vomiting, drowsiness, irritability, and pruritus. Specific treatment is unnecessary because of the low acute toxicity of the preparation. Elevated intracranial pressure has been reported with both acute and chronic vitamin A overdoses as well as in patients treated with therapeutic doses of acitretin capsules. Patients with a JAMP Acitretin overdose should be monitored closely for signs of increased intracranial pressure. If overdosage occurs in patients already receiving therapeutic doses of JAMP Acitretin, the drug must be discontinued immediately.
All female patients of childbearing potential who have taken an overdose of JAMP Acitretin must:
- Have a pregnancy test at the time of the overdose.
- Use an effective form of contraception for at least 3 years duration after the overdose.
If the pregnancy test is positive, the patient should be fully counselled on the serious risk to the fetus from exposure to JAMP Acitretin and the physician and patient should discuss the desirability of continuing the pregnancy. See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7 WARNINGS AND PRECAUTIONS, Reproductive Health, Teratogenic Risk.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION, AND PACKAGING
Table 1 - Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | 10 mg, 25 mg | Non-medicinal ingredients: Colloidal silicon dioxide, lactose monohydrate, magnesium stearate, maltodextrin, sodium ascorbate, sodium lauryl sulfate. Capsule shell contains: Gelatin, iron oxide black, iron oxide red, iron oxide yellow, sodium lauryl sulfate, titanium dioxide. Printing ink: Iron oxide black, potassium hydroxide, propylene glycol, shellac, strong ammonia solution. |
JAMP Acitretin 10 mg: Hard gelatin capsule containing 10 mg acitretin.
Opaque brown, colored cap imprinted with ‘ACI’ in black lettering, and opaque white, colored body imprinted with ‘10’ in black lettering, size ‘4’ hard gelatin capsules filled with yellow or greenish yellow granular powder.
JAMP Acitretin 25 mg: Hard gelatin capsule containing 25 mg acitretin.
Opaque brown, colored cap imprinted with ‘ACI’ in black lettering and, opaque yellow, colored body imprinted with ‘25’ in black lettering, size ‘1’ hard gelatin capsules filled with yellow or greenish yellow granular powder.
JAMP Acitretin capsules 10 and 25 mg are available in units of 30 capsules contained in a "push-through blister" package.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
- Transient Worsening:
Patients should be advised that a transient worsening of their psoriasis may occur during the initial JAMP Acitretin treatment period and usually does not require dose adjustment.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X
(1-844-764-7669).
It should be emphasized that, at the present time, not all the consequences of life-long administration of acitretin are known.
- Blood Donation:
Females of childbearing potential must not receive blood from patients being treated with JAMP Acitretin. Therefore, donation of blood by a patient (Male or Female), being treated with JAMP Acitretin is prohibited during treatment and for 3 years after completion of treatment with JAMP Acitretin due to the risk of females of childbearing potential receiving blood from patients being treated with JAMP Acitretin.
Cardiovascular
Serum cholesterol and serum triglycerides (fasting values) should be performed before starting treatment with JAMP Acitretin and again at intervals of 4 weeks until the lipid response to the drug is established, which is usually within four to eight weeks, and thereafter every three months during treatment. Approximately 65% of patients receiving acitretin capsules during clinical trials experienced an elevation in serum triglycerides. Approximately 30% developed a decrease in high density lipoproteins (HDL). Approximately 9% experienced elevated serum cholesterol levels. These effects of acitretin capsules were reversible upon cessation of treatment.
In patients with diabetes, alcoholism, obesity, cardiovascular risk factors or a lipid metabolism disorder undergoing treatment with acitretin, more frequent checks of serum values for lipids and/or glycaemia may be necessary.
Patients with an increased tendency to develop hypertriglyceridemia include those with diabetes mellitus, obesity, increased alcohol intake or a familial history of these conditions.
Hypertriglyceridemia and lowered HDL may increase a patient’s cardiovascular risk status. In addition, elevation of serum triglycerides to greater than 800 mg/dL has been associated with fatal fulminant pancreatitis. Therefore, every attempt should be made to control significant elevations of triglycerides or HDL decreases by reduction of weight or restriction of dietary fat and alcohol intake while continuing JAMP Acitretin treatment. Consumption of alcohol is contraindicated during JAMP Acitretin treatment and for two months after cessation of treatment. See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and
- 8 ADVERSE REACTIONS.
If, despite these measures, hypertriglyceridemia and low HDL levels persist, the discontinuation of JAMP Acitretin should be considered. An associated risk of atherogenesis cannot be ruled out if these conditions persist. There have been post-marketing reports of acute myocardial infarction, thromboembolism and stroke in patients treated with acitretin capsules. See 8 ADVERSE REACTIONS.
Post-marketing cases of capillary leak syndrome/retinoic acid syndrome have been reported with acitretin treatment.
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery. Decreased night vision and blurring of vision has been reported with acitretin treatment (see
- 7 WARNINGS AND PRECAUTIONS, Ophthalmologic). Patients should be advised of this potential problem and warned to be cautious when driving or operating any vehicle at night.
Ear/Nose/Throat
Impaired hearing and tinnitus have been reported in some patients treated with acitretin capsules. Patients who experience tinnitus or hearing impairment should discontinue JAMP Acitretin treatment and be referred for specialized care for further evaluation.
Endocrine and Metabolism
- Glucose Tolerance:
In diabetics or patients with risk factors/family history of diabetes, retinoids may affect glucose tolerance. Blood-sugar levels must therefore be checked more frequently than usual in the early stages of treatment. Elevated fasting blood glucose levels have been reported and new cases of diabetes have been diagnosed during acitretin capsules treatment. See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, DRUG-DRUG INTERACTIONS, Table 4- Sulfonylurea (glyburide), and 8 ADVERSE REACTIONS.
Gastrointestinal
Other retinoids have been temporally associated with inflammatory bowel disease (including regional ileitis, colitis and hemorrhage) in patients without a prior history of intestinal disorders. Therefore, it is expected that some patients taking JAMP Acitretin could develop inflammatory bowel disease. Patients experiencing abdominal pain, rectal bleeding or severe diarrhea should discontinue JAMP Acitretin immediately.
Hepatic/Biliary/Pancreatic
- Hepatotoxicity:
Hepatic function should be checked before starting treatment with JAMP Acitretin, every 4 weeks for the first 2 months after commencement, and then at least every 3 months during treatment. If abnormal results are obtained, weekly checks should be instituted. If hepatic function fails to return to normal or deteriorates further, JAMP Acitretin must be withdrawn. In such cases it is advisable to continue monitoring hepatic function for at least 3 months. Elevations of AST (SGOT), ALT (SGPT) or LDH have occurred in 20-28% of patients treated with acitretin capsules. One of the 329 patients treated in clinical trials had clinical jaundice with elevated serum bilirubin and transaminases considered possibly related to acitretin capsules treatment. Liver function test results in this patient returned to normal after acitretin capsules were discontinued.
If hepatotoxicity is suspected during treatment with JAMP Acitretin, the drug should be discontinued and the etiology further investigated.
Ten of 652 patients treated in clinical trials of etretinate, (acitretin is the active metabolite), had clinical or histologic hepatitis considered to be possibly or probably related to etretinate treatment. There have been four reports of hepatitis-related deaths worldwide; two of these patients had received etretinate for a month or less before presenting with hepatic symptoms. See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS, Monitoring and
Laboratory Tests, and 8 ADVERSE REACTIONS.
- Pancreatitis:
There have been some reports of fatal fulminant pancreatitis with acitretin capsules and other retinoids. This is sometimes associated with elevation of serum triglycerides in excess of 800 mg/dL or 9 mmol/L. See 8 ADVERSE REACTIONS. Therefore, every attempt should be made to control significant triglyceride elevation, see 7 WARNINGS AND PRECAUTIONS, Cardiovascular. JAMP Acitretin treatment should be discontinued if uncontrolled hypertriglyceridemia or if symptoms of pancreatitis occur.
Immune
Anaphylactic reactions have been very rarely reported. In individuals treated with systemic retinoids, these reactions were more serious after prior exposure to topical retinoids. Severe allergic reactions, including hypersensitivity to acitretin necessitate interruption of treatment and careful monitoring.
Monitoring and Laboratory Tests
- Pregnancy Tests:
At the start of JAMP Acitretin treatment, two pregnancy tests must be obtained from a licensed laboratory (minimum sensitivity 25 mIU/mL). The first test (with a negative result) is obtained at screening when JAMP Acitretin treatment is under consideration and the second (confirmatory) test (with a negative result) must be obtained up to 3 days before the first dose is given. During treatment, pregnancy tests should be arranged at 28 day-intervals. A negative pregnancy test not older than 3 days is mandatory before a renewal prescription is provided at monthly follow-up visits with the physician. After stopping treatment, pregnancy tests should be performed at 1-3 monthly intervals for a period of 3 years after the last dose was given. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7 WARNINGS AND PRECAUTIONS, Reproductive Health, Teratogenic Risk.
- Lipid Monitoring:
Serum cholesterol and serum triglycerides (fasting values) should be performed before starting treatment with acitretin and again at intervals of 4 weeks until the lipid response to the drug is established, which is usually within four to eight weeks and thereafter every three months during treatment. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular.
In patients with diabetes, alcoholism, obesity, cardiovascular risk factors or a lipid metabolism disorder undergoing treatment with acitretin, more frequent monitoring of serum values for lipids, and/or glycaemia and other cardiovascular indicators, e.g., blood pressure, is necessary. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular.
- Glucose Monitoring:
In diabetics or patients with risk factors/family history of diabetes, retinoids can alter glucose tolerance. Blood-sugar levels must therefore be checked more frequently than usual in the early stages of treatment. See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism.
- Signs of Depression:
If symptoms of a new depression develop or an existing depression worsens during treatment with JAMP Acitretin, the drug should be discontinued promptly and the patient referred for appropriate psychiatric assessment, treatment and counselling. See 7 WARNINGS AND PRECAUTIONS, Psychiatric.
- Hepatic function:
Hepatic function should be checked before starting treatment with JAMP Acitretin, every 4 weeks for the first 2 months after commencement, and then at least every 3 months during treatment. If abnormal results are obtained, weekly checks or drug withdrawal should be instituted. In such cases it is advisable to continue monitoring hepatic function for at least 3 months. Elevations of AST (SGOT), ALT (SGPT) or LDH have occurred in 20-28% of patients treated with acitretin capsules. See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic.
- Bone:
In adults, especially elderly, receiving treatment with JAMP Acitretin, appropriate examinations should be periodically performed in view of possible ossification abnormalities. If such disorders arise, the continuation of treatment should be discussed with the patient on the basis of a careful risk/benefit analysis.
Musculoskeletal
In clinical trials with acitretin capsules, patients were prospectively evaluated for evidence of development or change in bony abnormalities of the vertebral column following six months of treatment. Of 262 patients treated with acitretin capsules, 7% had pre-existing abnormalities of the spine which showed new changes or progression of pre-existing findings. Changes included degenerative spurs, anterior bridging of spinal vertebrae, diffuse idiopathic skeletal hyperostosis, and narrowing and destruction of cervical disc space. During the six-month period of observation, no bone changes were seen in patients who had normal pre-treatment X-rays. Other retinoids, including etretinate, have been associated with the development of extraosseous calcification and/or hyperostosis. Calcification of the ligaments of the spine, tendon insertions of the arms and legs, and intraosseous membranes of the arms and legs have been reported. Hyperostotic changes of the vertebrae, forearms, hips, acetabula, legs and calcanei have also been reported. It is not clear whether the extraosseous calcification and/or hyperostosis are progressive. Pre-treatment radiographs of the cervical, thoracic and lumbar spine may be useful when monitoring patients on long-term JAMP Acitretin treatment. Early recognition of musculoskeletal symptoms associated with JAMP Acitretin treatment may be important. There is some evidence that scintigraphic changes appear before radiographic findings. Scintigraphic changes may disappear after discontinuation of JAMP Acitretin treatment, however, radiographic changes may persist. Bone scintigraphy may be important in monitoring patients undergoing JAMP Acitretin treatment since scintigraphic changes seem to precede radiographic changes.
In adults, especially elderly, receiving long-term treatment with JAMP Acitretin, appropriate examinations should be periodically performed in view of possible ossification abnormalities. If such disorders arise, the continuation of treatment should be discussed with the patient on the basis of a careful risk/benefit analysis. See 1 INDICATIONS and 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests.
Possible related adverse events that are associated with JAMP Acitretin and other retinoid use are: Osteoporosis, osteopenia, bone fractures, delayed healing of bone fractures, myalgia, arthralgia and elevated serum creatine phosphokinase.
There have been occasional reports of bone changes in children, receiving long-term treatment with etretinate, including premature epiphyseal closure, skeletal hyperstosis, and extraosseus calcification See 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics.
Neurologic
- Benign Intracranial Hypertension (Pseudotumor Cerebri):
Acitretin capsules and other retinoids have been associated with rare cases of pseudotumor cerebri (benign intracranial hypertension). Early symptoms and signs of benign intracranial hypertension include headache, nausea and vomiting and visual disturbances and patients with such symptoms should be advised to discontinue acitretin immediately, be examined for papilledema, and be referred for neurological evaluation and care. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
As tetracyclines can also cause an increase in intracranial pressure, their combination with JAMP Acitretin should be avoided. See 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS.
Ophthalmologic
Drug-related ophthalmic effects (dry eyes, irritation of eyes, brow and lash loss, blepharitis and/or crusting of lids, photophobia, redness, recurrent styes, pannus and subepithelial corneal lesions) were noted during treatment with acitretin capsules in 29% of 252 patients who were followed with ophthalmic examinations. Patients should be advised that they may experience decreased tolerance to contact lenses during the initial treatment period.
Decreased night vision and blurring of vision have been reported by some patients. Patients should be advised of these potential problems and warned to be cautious when driving or operating any vehicle at night. 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery.
The following additional ophthalmic effects have occurred in patients taking etretinate (the prodrug of acitretin): Decreased visual acuity, minimal posterior subcapsular cataract, iritis, blot retinal hemorrhage and scotoma.
Patients receiving JAMP Acitretin treatment should be carefully monitored for visual problems and any patient experiencing visual difficulties should discontinue this drug and undergo ophthalmic evaluation.
Psychiatric
Treatment with systemic retinoids can cause mood changes including irritability, aggression and depression. Depression, psychotic disorder and/or other psychiatric symptoms such as aggressive feelings or thoughts of self-harm/suicide have been reported in patients taking systemic retinoids as well as in patients taking acitretin capsules. All patients should be screened and monitored for signs of new or worsening depressive symptoms during treatment. Before starting treatment with JAMP Acitretin, physicians should determine whether the patient may be depressed or has a history of depression including a family history of major depression. If symptoms of a new depression develop or an existing depression worsens during treatment with JAMP Acitretin, the drug should be discontinued promptly and the patient referred for appropriate psychiatric assessment, treatment, and counselling, as necessary. However, discontinuation of JAMP Acitretin may not alleviate symptoms and therefore further psychiatric or psychological evaluation may be necessary. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Reproductive Health Teratogenic Risk
Acitretin capsules are highly teratogenic. The use of systemic retinoids in humans is associated with congenital abnormalities. There is an extremely high risk that major human fetal abnormalities (e.g., craniofacial defects, cardiac and vascular or CNS malformations, skeletal and thymic defects) will occur if pregnancy occurs during treatment with JAMP Acitretin or within 3 years of cessation of treatment. Any exposed fetus can be affected. The risk of giving birth to a deformed child is exceptionally high if acitretin is taken before or during pregnancy, independent of previous treatment duration.
Major fetal abnormalities associated with retinoid administration during or before pregnancy have been reported, including meningomyelocoele, meningoencephalocoele, multiple synostosis, facial dysmorphia, anophthalmia, syndactyly, absences of terminal phalanges, malformations of hip, ankle and forearm, low set ears, high palate, decreased cranial volume and alterations of the skull and cervical vertebrae on X-ray. See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
JAMP Acitretin is contraindicated in every female of childbearing potential unless all of the following conditions apply:
- The patient has severe psoriasis or other severe disorder of keratinization which are resistant to standard therapies.
- The patient is reliable in understanding and carrying out the physician’s instructions.
- The patient is able to comply with mandatory contraceptive measures reliably and without fail.
- Before treatment with JAMP Acitretin, the patient has received from the physician and acknowledged understanding of, a detailed and careful oral and printed explanation of the precautions to be taken, the risk of very severe fetal malformation, and the possible consequences if pregnancy occurs during the course of treatment with acitretin or within 3 years of discontinuing. The JAMP Acitretin Pregnancy Prevention Program will be presented and all steps implemented. The explanation will include a line drawing, which is shown to the patient, of an infant with the characteristic deformities resulting from retinoid exposure during pregnancy.
- It is absolutely essential that every female of childbearing potential who is to undergo treatment with JAMP Acitretin uses effective contraception (2 complementary methods, (i.e., one primary and one secondary method) without interruption for at least four weeks before, during, and for 3 years after the discontinuation of treatment with acitretin). The patient should be instructed to immediately contact a doctor or pharmacist in case of suspected pregnancy.
- At the start of treatment, two negative serum or urine pregnancy tests (with a minimum sensitivity of 25 mIU/mL), from a licensed laboratory. The first test (with a negative result) is obtained at screening when JAMP Acitretin treatment is under consideration and the second (confirmatory) test (with a negative result) must be obtained up to 3 days before the first dose is given. During treatment, pregnancy tests should be arranged at 28-day intervals. A negative pregnancy test, not older than 3 days, is mandatory before a renewal prescription is provided at these visits. After stopping JAMP Acitretin treatment, pregnancy tests must be performed at 1-3 monthly intervals for a period of at least 3 years after the last dose is given. Pregnancy tests serve to reinforce to the patient the necessity of avoiding pregnancy and in the event of pregnancy, provide the physician and patient an immediate opportunity to discuss the serious risk to the fetus from this exposure to JAMP Acitretin and the desirability of continuing the pregnancy.
- Treatment should not begin until the second or third day of the next menstrual period.
- The same effective and uninterrupted contraceptive measures described above must be taken every time a course of JAMP Acitretin treatment is repeated, however long the intervening period may have been, and must be continued for 3 years after the last dose.
- Should pregnancy occur, in spite of these precautions, there is a high risk of severe malformation of the fetus (e.g. craniofacial defects, cardiac and vascular or CNS malformations, skeletal and thymic defects) and the incidence of spontaneous abortion is increased. This risk applies especially during treatment with acitretin and 2 months after treatment. For 3 years after acitretin discontinuation, the risk is lower (particularly in females who have not consumed alcohol) but cannot be entirely excluded due to possible formation of etretinate.
- The patient must avoid alcohol consumption during treatment and for 2 months after stopping treatment.
See 2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Contraception Method:
It is recommended that two reliable forms of contraception be used simultaneously unless abstinence is the chosen method. Primary contraceptive method is a combination hormonal contraceptive product or an intrauterine device and it is recommended that a secondary method of contraceptive, i.e., a condom or diaphragm (cap) is also used. Low dose progesterone-only products (minipills) are not recommended due to indications of possible interference by acitretin capsules with their contraceptive effect. See 9 DRUG-DRUG INTERACTIONS, Table 4.
Male Patients:
For male patients treated with acitretin capsules, available data, based on the level of maternal exposure from semen and seminal fluid indicate a minimal, if any, risk of teratogenic effects. Male patients should be reminded that they must not share their medication with anyone, particularly not females.
Skin
There have been very rare post-marketing reports of severe skin reactions (e.g., erythema multiforme (EM), Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN)) associated with other retinoids and these are therefore expected with JAMP Acitretin. These events may be serious and result in hospitalization, life threatening events, disfiguration, disability and/or death. JAMP Acitretin treatment should be discontinued if the patient develops any of the following reactions: rash, especially if associated with fever and/or malaise; conjunctivitis (red or inflamed eyes); blisters on legs, arms or face and/or sores in mouth, throat, nose or eyes; peeling skin or other serious skin reactions.
The effects of UV light are enhanced by retinoid treatment. Patients should avoid excessive exposure to sunlight and unsupervised use of sun lamps. Where necessary a sun-protection product with a high protection factor of at least SPF 30 should be used.
It is recommended that aggressive chemical dermabrasion, cutaneous laser treatment and wax epilation be avoided in patients on JAMP Acitretin treatment and for a sufficient period of time after the end of treatment because of the risk of hypertrophic scarring in atypical areas, epidermal stripping, dermatitis and more rarely hyper- or hypo-pigmentation in treated areas.
Concurrent administration of JAMP Acitretin with keratolytic or exfoliative anti-acne agents should be avoided as local irritation may increase. Patients should be advised to use a skin-moisturizing ointment or cream and a lip balm from the start of treatment as JAMP Acitretin is likely to cause dryness of the skin and lips.
Post-marketing cases of exfoliative dermatitis have been reported with acitretin treatment.
7.1 Special Populations
7.1.1 Pregnancy
JAMP Acitretin is contraindicated for use by pregnant females. JAMP Acitretin is also contraindicated for use by female patients of childbearing potential unless strict conditions of use are followed. See
2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX. The JAMP Acitretin Pregnancy
Prevention Program must be followed by physicians and patients.
7.1.2 Breast-feeding
JAMP Acitretin is contraindicated for use by nursing mothers. Clinical data indicate that acitretin is excreted in human milk. Therefore, nursing mothers should not receive JAMP Acitretin because of the potential for serious adverse reactions in nursing infants. Women should not breastfeed for an undetermined period of time of at least 3 years following discontinuation of JAMP Acitretin. See
2 CONTRAINDICATIONS, 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7 WARNINGS AND
PRECAUTIONS, Reproductive Health.
7.1.3 Pediatrics
The use of JAMP Acitretin in children is not recommended.
Ossification of interosseous ligaments and tendons of the extremities, skeletal hyperostosis and premature epiphyseal closure have been reported with other systemic retinoids, including etretinate of which acitretin is the active metabolite. Due to the uncertain effect of long-term acitretin capsules treatment on growth and skeletal development, JAMP Acitretin is not recommended for use in children. See 7 WARNINGS AND PRECAUTIONS, Musculoskeletal.
7.1.4 Geriatrics (≥ 65 years of age):
Clinical trials did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently than younger subjects. Geriatric patients, receiving treatment with acitretin should be examined appropriately and periodically in view of possible ossification abnormalities. See 1 INDICATIONS and 7 WARNINGS AND PRECAUTIONS, Musculoskeletal.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Undesirable effects are seen in most patients receiving acitretin. An initial worsening of psoriasis symptoms is sometimes seen at the beginning of the treatment period.
The most frequent undesirable effects observed are symptoms of hypervitaminosis A.
Hypervitaminosis A produces a wide spectrum of signs and symptoms primarily of the gastrointestinal system (e.g., dryness of the lips, which can be alleviated by application of a fatty ointment), skin and subcutaneous tissue, and musculoskeletal, hepatobiliary and nervous systems.
Table 2 below lists, grouped by frequency, the adverse reactions reported during clinical trials in which patients were treated with acitretin capsules for psoriasis.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Table 2: Adverse Events Reported during Clinical Trials in which Patients were Treated with Acitretin Capsules for Psoriasis
| System Organ Class / Preferred Term | VERY COMMON >10% | a COMMON 1-10% |
|---|---|---|
| Ear and labyrinth disorders | Cerumen impaction Ear pain Tinnitus | |
| Eye Disorders | Xerophthalmia | Blepharitisb Conjunctivitis/ Eye irritation Eye pain Photophobia Visual impairment / Vision blurred |
| General disorders and administration site conditions | Chills | Fatigue Oedema Pain Thirst |
| Gastrointestinal disorders | Cheilitis Dry mouth Lip dry | Abdominal pain Gingival bleeding Gingivitis Nausea Stomatitis Salivary hypersecretion |
| Infections and infestations | Rhinitis | Infection Paronychia |
| Metabolism and nutrition disorders | - | Decreased appetite Increased appetite |
| Musculoskeletal and connective tissue disorders | Arthralgia | Arthritis Back pain Bone Pain Exostosisc Myalgia |
| Neoplasms benign, malignant and unspecified (incl cysts and polyps) | - | Pyogenic granuloma |
| System Organ Class / Preferred Term | VERY COMMON >10% | a COMMON 1-10% |
|---|---|---|
| Nervous system disorders | Hyperaesthesia | Headache Dysgeusia Hypertonia Hypoaesthesia Paraesthesia |
| Psychiatric disorders | - | Insomnia Nervousness |
| Reproductive system and breast disorders | - | Erectile dysfunction |
| Respiratory, thoracic and mediastinal disorders | Epistaxis | |
| Skin and subcutaneous tissue disorders | Alopecia Dry skin Erythema Nail disorder Pruritus Rash erythematous Skin atrophy Skin exfoliation Sticky skin | Cold sweat Dermatitis bullous Dermatitis psoriasiform Hair texture abnormal Hyperhidrosis Photosensitivity reaction Purpura Seborrhoea Skin fissures Skin ulcer Rash |
- a Some may bear no relationship to treatment.
- b Based on review of eye examination forms by consulting ophthalmologist (N=252).
- c Incidence of 7% based on review of films by consulting radiologist (N=262).
8.3 Less Common Clinical Trial Adverse Reactions (< 1.0%) Ear and labyrinth disorders: Deafness
Eye Disorders: Cataract, Eye disordera, Corneal neovascularisationa, Corneal lesiona, Lacrimal disorder, Night blindness
Gastrointestinal disorders: Anorectal disorder, Constipation, Diarrhea, Dyspepsia, Glossitis, Melaena, Tongue ulceration, Mouth ulceration, Pancreatitis, Rectal tenesmus, Saliva altered
General disorders and administration site conditions: Chest Pain, Gait disturbance, Impaired healing, Malaise, Pyrexia
Hepatobiliary disorders: Hepatitis, Jaundice
Infections and infestations: Candidiasis, Hordeolumb, Laryngitis, Otitis externa, Pharyngitis, Sinusitis
Investigations: Bleeding time prolonged, Urine analysis abnormal
Metabolism and nutrition disorders: Alcohol intolerance
Musculoskeletal and connective tissue disorders: Bursitis, Muscle spasms, Muscular weakness, Osteoarthritis
Nervous system disorders: Ageusia, Benign intracranial hypertension, Somnolence
Psychiatric disorders: Depression
Renal and urinary disorders: Dysuria
Reproductive system and breast disorders: Balanoposthitis, Genital discharge
Respiratory, thoracic and mediastinal disorders: Cough, Dysphonia, Sputum increased
Skin and subcutaneous tissue disorders: Acne, Angioedema, Dermatitis, Eczema, Skin disorder, Skin hypertrophy, Skin mass, Skin odour abnormal
Vascular disorders: Flushing, Hot flush, Vasculitisb
- a Based on review of eye examination forms by consulting ophthalmologist (N=252).
- b Vasculitis has not been documented with acitretin but has been seen with other retinoids.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Table 3 below lists abnormal hematologic clinical chemistry findings during clinical trials in which patients were treated with acitretin capsules for psoriasis.
Table 3: Abnormal Hematologic Clinical Chemistry Findings (shown as % change) Reported during Clinical trials in which Patients were Treated with Acitretin Capsules for Psoriasis
| SYSTEM ORGAN CLASS/ LABORATORY ABNORMALITY | % CHANGE INCREASED | % CHANGE DECREASED | COMMENTS |
|---|---|---|---|
| INVESTIGATIONS: | |||
| Alanine aminotransferase | 28 | If hepatotoxicity is suspected, treatment should be discontinued (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS). | |
| Aspartate aminotransferase | 23 | ||
| Blood lactate dehydrogenase | 21 | ||
| Blood alkaline phosphatase | 16 | ||
| Gamma-glutamyltransferase | 14 | ||
| Bilirubin conjugated | 11 | ||
| Blood triglycerides | 65 | ||
| SYSTEM ORGAN CLASS/ LABORATORY ABNORMALITY | % CHANGE INCREASED | % CHANGE DECREASED | COMMENTS |
|---|---|---|---|
| Blood cholesterol | 9 | The effects on triglycerides, cholesterol and HDL were reversible upon cessation of acitretin capsules treatment. (see 7 WARNINGS AND PRECAUTIONS). | |
| High density lipoprotein | 30 | ||
| Blood bilirubin | 2 | ||
| Globulins | 2 | ||
| Blood albumin | 1 | ||
| Blood uric acid | 17 | ||
| Blood creatinine | 5 | ||
| Blood urea | 2 | ||
| Reticulocyte count | 38 | ||
| White blood cell count | 11 | 7 | |
| Eosinophil count | 8 | ||
| Monocyte count | 7 | ||
| Band neutrophil count | 4 | ||
| Basophil count | 3 | ||
| Neutrophil count | 16 | 5 | |
| Lymphocyte count | 2 | 11 | |
| Haemoglobin | 4 | 9 | |
| Platelet count | 2 | 6 | |
| Haematocrit | 3 | 5 | |
| Red blood cell count | 2 | 3 | |
| Blood phosphorus | 16 | 13 | |
| Blood potassium | 12 | 3 | |
| Blood magnesium | 12 | 12 | |
| Blood sodium | 2 | 1 | |
| Blood calcium | 4 | 2 | |
| SYSTEM ORGAN CLASS/ LABORATORY ABNORMALITY | % CHANGE INCREASED | % CHANGE DECREASED | COMMENTS |
|---|---|---|---|
| Blood chloride | 2 | 3 | |
| Blood creatine phosphokinase | 37 | Other reported laboratory abnormalities. | |
| Blood glucose | 21 | 7 | |
| Blood iron | 7 | 3 | |
| Red blood cells urine | 10 | Urinary abnormalities | |
| White blood cells urine positive | 7 | ||
| RENAL and URINARY DISORDERS: | |||
| Glycosuria | 4 | See additional urinary abnormalities under INVESTIGATIONS above. | |
| Ketonuria | 3 | ||
| Proteinuria | 2 | ||
8.5 Post-Market Adverse Reactions
The following adverse reaction has been identified during post approval use of acitretin capsules.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency or establish a causal relationship to drug exposure.
Undesirable effects reported for acitretin in post-market, either spontaneously or in clinical trials, are listed below, by System Organ Class and frequency.
Frequencies are defined as: Very common (≥ 1 / 10), Common (≥ 1/ 100 to < 1 / 10),
Uncommon (≥ 1 / 1,000 to <1/100), Rare (≥ 1 / 10,000 to < 1 /1,000), Very rare (< 1 / 10,000) and Not known (cannot be estimated from the available data).
1Cardiovascular Disorders: Unknown: Acute myocardial infarction, Thromboembolism, Stroke
Eye disorders: Very rare: ulcerative keratitis
Gastrointestinal disorders: Very common: Thirst; Common: Gastro-intestinal disorders (e.g. vomiting), Stomatitis; Not known: Dysgeusia, Rectal hemorrhage
General disorders and administration site conditions: Common: Peripheral oedema Immune system disorders: Not known: Type I Hypersensitivity (angioedema, urticaria) Infections and infestations: Not known: Vulvo-vaginitis due to Candida albicans
Investigations: Very common: Lipids abnormal (during treatment with high doses of acitretin, reversible elevation of serum triglycerides and serum cholesterol has occurred, especially in high-risk patients and during long-term treatment. An associated risk of atherogenesis cannot be ruled out if these conditions persist), Liver function test abnormal (transient, usually reversible elevation of transaminases and alkaline phosphatases)
Nervous system disorders: Uncommon: Dizziness; Rare: Neuropathy peripheral; Very rare: Benign intracranial hypertension
Psychiatric: Not known: Aggressive feelings and/or Suicidal thoughts, Psychotic disorder
Respiratory, thoracic and mediastinal disorders: Very common: Drying of and inflammation of mucous membranes (e.g. rhinitis)
Skin and subcutaneous tissue disorders: Very common: Skin exfoliation (all over the body, particularly on the palms and soles); Common: Brittle nails, Dermatitis, Paronychia, Skin fragility; Uncommon: Rhagades; Not known: Exfoliative dermatitis, Madarosis, Pyogenic granuloma,
Vascular disorders: Not known: Capillary leak syndrome/retinoic acid syndrome
1 Acitretin capsules have been associated with abnormal lipid values including hyperglyceridemia and decreased HDL and this potentially may increase the risk of the cardiovascular risk status of patients taking acitretin capsules. Although no causal relationship has been established, there are reports of patients taking acitretin capsules who have had acute myocardial infarction and thromboembolic events.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
In addition to the drug interactions indicated as serious above (see 9.1 Serious Drug Interactions), the following considerations for drug interactions may apply:
Investigations have shown acitretin capsules have no protein binding interaction with coumarin type anticoagulants (Warfarin). Concomitant administration of Phenprocoumon and acitretin capsules does not alter the hypothrombinemic effect of Phenprocoumon or the plasma disposition of acitretin capsules. Concomitant administration of acitretin capsules and Digoxin or acitretin capsules and Cimetidine does not alter the pharmacokinetics of acitretin capsules, Digoxin or Cimetidine.
9.3 Drug-Behavioural Interactions
Photosensitivity: Patients taking JAMP Acitretin should avoid excessive exposure to sunlight and unsupervised use of sun lamps. Where necessary a sun-protection product with a high protection factor of at least SPF 30 should be used. See 7 WARNINGS AND PRECAUTIONS, Skin.
Serious Drug Interactions
Vitamin A/retinoids: Concomitant administration of JAMP Acitretin and vitamin A and other systemic retinoids must be avoided due to the risk of possible additive toxic effects and increased risk of hypervitaminosis A. See 2 CONTRAINDICATIONS and 8.1 ADVERSE REACTIONS OVERVIEW.
Methotrexate: The combined administration of JAMP Acitretin and methotrexate is contraindicated because of an increased risk of hepatitis reported to result from the combination of methotrexate and etretinate. See 2 CONTRAINDICATIONS.
Tetracycline: Combined use of JAMP Acitretin and tetracyclines is contraindicated since both can cause increased intracranial pressure. See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Neurologic.
Alcohol: Clinical evidence has shown that etretinate (prodrug of acitretin) can be formed with concurrent ingestion of acitretin and alcohol. See 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions.
Driving or operating machinery: Patients should be advised of the potential problem of decreased night vision and warned to be cautious when driving or operating any vehicle at night. See
7 WARNINGS AND PRECAUTIONS, Ophthalmologic.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4: Established or Potential Drug-Drug Interactions
| Drug/Substance | Ref | Effect | Clinical comment |
|---|---|---|---|
| Vitamin A/retinoids | T/C | Additive effect/Vitamin A toxicity | Risk of possible additive toxic effects/ hypervitaminosis A (see 2 CONTRAINDICATIONS). |
| Methotrexate | C | Additive | Risk of hepatitis (see 2 CONTRAINDICATIONS). |
| Tetracycline | T/C | Additive | JAMP Acitretin and tetracycline both can cause increased intracranial pressure (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Neurologic). |
| Ethanol (alcohol in drinks, food, medicine) | T/C | 1Transesterification | Conversion of acitretin to etretinate (see 2 CONTRAINDICATIONS). |
| Low dose progesterone-only contraceptive (minipills) | C | Possible interference with contraceptive effect | Not a reliable form of contraceptive when taking JAMP Acitretin (see 7 WARNINGS AND PRECAUTIONS, Reproductive Health, Contraception Method). |
| Phenytoin | T | Partially reduces protein binding | Clinical significance is unknown. Caution to be exercised when using these drugs together. |
| Sulfonylurea (glyburide) | C | Treatment with acitretin capsules either increased insulin sensitivity directly or interacted with glyburide to do so. | Careful supervision and monitoring of diabetic patients recommended (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism). |
Legend: C = Case Study; T = Theoretical
1 It is not known whether substances other than ethanol are associated with transesterification.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
- St. John’s Wort:
Acitretin capsules use is associated with depression in some patients. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS, Psychiatric, and 8 ADVERSE REACTIONS). Female patients of childbearing potential should be prospectively cautioned not to self-medicate with the herbal supplement St. John’s Wort because a possible interaction has been suggested with hormonal contraceptives based on reports of breakthrough bleeding on oral contraceptives shortly after starting St. John's Wort. Pregnancies have been reported by users of combined hormonal contraceptives who also used some form of St. John's Wort
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Acitretin is a retinoid, an aromatic analogue of vitamin A. The mechanism of action of acitretin is unknown, however, evidence exists for a wide range of actions at various cellular and subcellular levels. These include regulation of RNA/DNA synthesis, modulation of factors which influence epidermal proliferation, modification of glycoprotein synthesis and modulation of the immune response. Whatever the exact mechanism of action, the most prominent effect of acitretin is a modulation of cellular differentiation in the epidermis which re-establishes a more normal pattern of cell growth.
10.2 Pharmacodynamics
Use of acitretin in psoriatic patients results in improvement manifested by a decrease in scale, erythema, and thickness of lesions, and decreased inflammation in the epidermis and dermis.
10.3 Pharmacokinetics Absorption
Oral absorption of acitretin was optimal (approximately double) when given with food compared to fasting conditions. The oral absorption of acitretin increased proportionally with dose. The mean absolute bioavailability of the 50 mg acitretin capsule was approximately 59%. The 10 mg and 25 mg acitretin capsule formulations had a bioavailability of 90% and 105%, respectively relative to a 25 mg oral suspension when taken with food. Following multiple doses, acitretin plasma concentrations reached steady-state conditions within two weeks and increased in a dose proportional manner. In psoriatic patients who received acitretin (10 to 50 mg/day) for eight weeks, mean steady-state trough concentrations of acitretin ranged between 6 and 25 ng/mL.
Distribution and Metabolism:
Acitretin is more than 98 % bound to plasma proteins, primarily albumin. Following oral absorption, acitretin undergoes metabolism and interconversion by simple isomerization to its 13-cis form (main metabolite). Both acitretin and its 13-cis isomer are eliminated from the body primarily by metabolism to chain-shortened breakdown products and conjugates. The steady-state plasma trough concentrations of this biologically active metabolite are 5-6-fold higher than acitretin and decline in parallel with those of the parent drug. The mean accumulation ratio for the metabolite was 0.9 and average trough concentrations (~116 ng/mL) remained constant throughout the study.
Measurable levels of etretinate, of which acitretin is the active metabolite, have been detected in plasma samples of patients administered acitretin. The use of alcohol may be a contributing factor to the presence of etretinate in these patients. In a two-way crossover study in healthy volunteers, all 10 subjects formed etretinate following the ingestion of a single 100 mg oral dose of acitretin in the presence of alcohol (1.4 g/kg ethanol over approximately 3 hours). Peak concentrations of etretinate measured in these subjects ranged from 22 ng/mL to 105 ng/mL (mean: 55 ng/mL). Etretinate has a long elimination phase. When acitretin was administered in the absence of ethanol in this study, etretinate was not measurable. However, the formation of etretinate from acitretin in the absence of ethanol cannot be excluded. When etretinate has been used as primary treatment, etretinate has been found in the blood of some patients up to 2.9 years after discontinuation of treatment. Of 240 evaluated psoriatic patients who received treatment with acitretin capsules (5-60 mg/day) with no restrictions on alcohol use, 7.5% were found to have measurable concentrations of etretinate (range:
5-62 ng/mL) and a further 27% had a trace of etretinate in the plasma which was not measurable.
Elimination
In patients administered multiple oral doses of acitretin for up to nine months, the range of elimination half-life (t1/2) values observed was 33-92 hours for acitretin (harmonic mean = 48 hours) and 28-123 hours for cis - acitretin (harmonic mean = 64 hours). The mean terminal elimination half-life for the metabolite was 75 hours (range 53-99 hours).
Special Populations and Conditions
- Geriatrics:
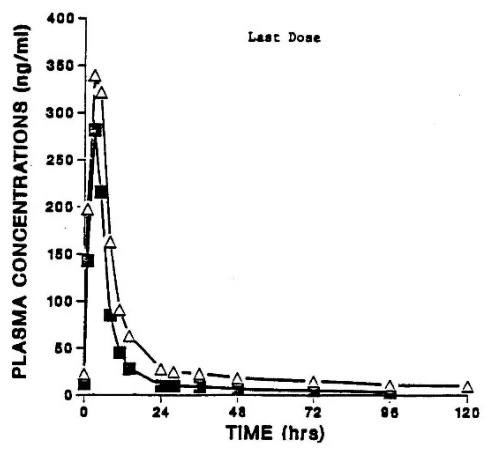
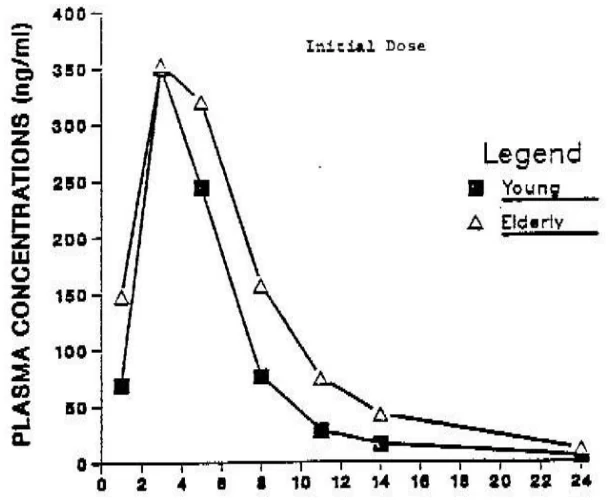
The effect of age on the pharmacokinetics of acitretin was investigated in eight elderly male subjects (64-72 years, weighing 67.2-89.0 kg) and six young healthy male subjects (24-32 years, weighing 60-89 kg) who received single and multiple oral doses of acitretin. Plasma concentrations of acitretin in the elderly subjects were 49% higher after the first and last drug dose as assessed by AUC0-24 (Figure 1). The trough plasma concentrations at steady-state for acitretin were also two-fold higher for the elderly group during multiple 25 mg oral doses. The range of terminal elimination half-lives observed for acitretin were 37-96 hours (harmonic mean = 54 hours) in elderly and 39-70 hours (harmonic mean = 53 hours) in young subjects.
Figure 1 Mean Acitretin Plasma Concentration-time Profiles After the First and Last Oral Dose of Acitretin in Young and Elderly Subjects
- Renal Insufficiency:
End Stage Renal Failure
A preliminary study was conducted in three male subjects (ages 29-63 years, weighing 56-73 kg) with end-stage renal failure and on hemodialysis, who received a single 50 mg oral dose of acitretin with food. The pharmacokinetics of acitretin appeared to be unaffected in the three subjects. Additionally, arterial and venous plasma concentrations of acitretin were virtually identical and neither drug nor metabolite was found in the dialysate samples.
Animals
In general, the absorption and disposition of acitretin in animals support the pharmacokinetics of acitretin in humans. In the dog and monkey, oral absorption of acitretin was rapid with peak plasma concentrations reached in 1-4 hours, although absorption was not dose proportional. The elimination half-life in the dog following oral administration was approximately two hours. In the rat, plasma concentrations of acitretin in males were higher than in females. Gender differences in the disposition of acitretin were also found in the dog in that the total clearance and volume of distribution in females were less than in males although the elimination half-life remained unchanged. Excretion of acitretin differed as well, with the rat excreting 80% and 2-20% in the bile and urine, respectively and the dog excreting 96% and 4% in the feces and urine, respectively.
11 STORAGE, STABILITY AND DISPOSAL
Store: 15-25°C. Protect from heat and light.
The product is sensitive to moisture, keep in original packaging.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Keep out of reach of children. The medicine should not be used after the expiry date (EXP) shown on the package. JAMP Acitretin (acitretin) is highly teratogenic. Due to the risk of fetal malformations, this medicine (capsules) must not be passed on to other people. Unused or expired products should be returned to a pharmacy for disposal.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name:
Acitretin
Chemical name:
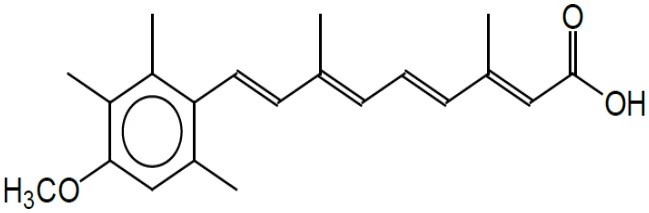
(2E,4E,6E,8E)-9-(4-methoxy-2,3,6-trimethylphenyl)-3,7- dimethylnona-2,4,6,8-tetraenoic acid
Molecular formula:
C21H26O3
Molecular mass:
326.4 g/mol
Structural formula:
Physicochemical properties:
Acitretin is a yellow to greenish-yellow crystalline powder.
Acitretin is sparingly soluble in tetrahydrofuran,
slightly soluble in acetone and ethyl alcohol and it is insoluble in Water and Cyclohexane.
pKa is 4.72 ± 0.33 in most acidic conditions at a temperature of 25°C.
The melting range is 228-230°C
14 CLINICAL TRIALS
14.1 Clinical Trial by Indication
Trial Design and Study Demographics
Study Results
No information on clinical trials is available.
14.2 Comparative Bioavailability Studies
A double-blinded, randomized, two-treatment, two-period, two-sequence, crossover, single oral dose (1 x 10 mg), comparative bioavailability study of PrJAMP Acitretin 10 mg capsules (JAMP Pharma Corporation) and PrSORIATANE® 10 mg capsules (Allergan Inc.) was conducted in 30 healthy, adult male subjects under fed conditions. A summary of comparative bioavailability data from 24 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Acitretin (1 x 10 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 655.30 679.73 (26.93) | 607.02 621.58 (21.22) | 107.1 | 101.2 - 113.4 |
AUCI (ng·h/mL) | 664.92 688.92 (26.53) | 616.00 630.37 (20.90) | 107.1 | 101.2 - 113.2 |
Cmax (ng/mL) | 81.20 84.38 (29.00) | 68.03 72.26 (34.17) | 117.6 | 103.5 - 133.5 |
Tmax3 (h) | 7.00 (2.50 - 12.00) | 5.16 (1.52 - 12.00) | ||
t1/24 (h) | 4.36 (27.79) | 4.12 (25.31) | ||
1 PrJAMP Acitretin (acitretin) capsules, 10 mg (JAMP Pharma Corporation)
2 PrSORIATANE® (acitretin) capsules, 10 mg (Allergan Inc., Canada)
3 Expressed as the median (range)
4 Expressed as the Arithmetic mean (CV%) only
A randomized, two-treatment, two-sequence, two-period, single-dose, crossover oral comparative bioavailability study of JAMP Acitretin 25 mg capsules (JAMP Pharma Corporation) and PrSORIATANE® 25 mg capsules was conducted in 30 healthy, adult, male subjects under fed conditions. A summary of the comparative bioavailability data is presented in following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
acitretin (1 x 25 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
acitretin (1 x 25 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 1702.69 1760.55 (26.35) | 1503.28 1545.80 (23.48) | 113.3 | 107.6 - 119.3 |
AUCI (ng·h/mL) | 1714.81 1772.43 (26.21) | 1513.95 1556.47 (23.42) | 113.3 | 107.6 - 119.3 |
| Cmax (ng/mL) | 195.05 205.97 (32.67) | 185.53 194.38 (30.33) | 105.1 | 95.8 - 115.4 |
| Tmax3 | 7.00 | 4.67 | ||
| (h) | (4.00 - 12.00) | (2.50 - 8.00) | ||
T 4 ½ | 4.57 | 4.55 | ||
| (h) | (26.25) | (35.73) | ||
1 JAMP Acitretin (acitretin) capsules, 25 mg (JAMP Pharma Corporation)
2 PrSORIATANE® (acitretin) capsules, 25 mg (Allergan Inc., Canada)
3 Expressed as the median (range)
4 Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Animals
In general, the absorption and disposition of acitretin in animals support the pharmacokinetics of acitretin in humans. In the dog and monkey, oral absorption of acitretin was rapid with peak plasma concentrations reached in 1-4 hours, although absorption was not dose proportional. The elimination half-life in the dog following oral administration was approximately two hours. In the rat, plasma concentrations of acitretin in males were higher than in females. Gender differences in the disposition of acitretin were also found in the dog in that the total clearance and volume of distribution in females were less than in males although the elimination half-life remained unchanged. Excretion of acitretin differed as well, with the rat excreting 80% and 2-20% in the bile and urine, respectively and the dog excreting 96% and 4% in the feces and urine, respectively.
General Toxicology:
- Single-dose Toxicity
LD50 (Acitretin)
| SPECIES | STRAIN | ROUTE | LD50 (mg/kg) | OBSERVATION PERIOD | SIGNS AND SYMPTOMS |
|---|---|---|---|---|---|
| Mouse | Fü SPF | Oral i.p. | >8,000 >250 <500 | 30 days 30 days | Decreased respiratory rate, alopecia, weight loss |
| Rat | Fü SPF | Oral i.p. | >8,000 500 | 30 days 30 days | Decreased respiratory rate, alopecia, weight loss |
| Rabbit | New Zealand White | Oral | >1,000 | 14 days | Alopecia, unkept appearance, reddening around eyes, nose, mouth and/or genital area |
| Dog | Beagle | Oral | >1,000 | 14 days | Diarrhea |
JAMP Acitretin (Acitretin Capsules) Page 32 of 50
- Repeat-dose Toxicity
| SPECIES | STRAIN SEX/#/ group | ROUTE | DOSE/ mg/kg/day | DURATION /animals/ group | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
| Rat | M/10 | i.v. (mixed micelle formulation) | 0 (control) 0.5 or 2.0 | 2 weeks | No mortality; Statistically significant dose-related increase in adrenal weight at 2.0 mg/kg/day dose (13% higher than control) |
| Dog | M/3 | i.v, (mixed micelle formulation) | 0 (control) 1.0 or 5.0 | 2 weeks | No mortality; No findings distinguished treated from control dogs |
| Primates | 1M/1F | Oral (spray dried powder formulation) | Escalating: 20 (Wk 1) 40 (Wk 2) 80 (Wk 3) 160 (Wk 4) | 4 weeks | No mortality observed. At the end of the study, the erythrocyte counts were decreased to about 15-26% of the predosing values at doses greater than 40 mg/kg/day. Reticulocyte counts were increased after one week of dosing with 20 mg/kg/day and were increased 5-10 fold over predose values when measured at the end of the second week of study, after one week of dosing with 40 mg/kg/day. |
| Rats | M/10 | Oral (wet milled beadlet preparation) | 0 (control) 5 10 20 40 80 | Preliminary Study (dose ranging): 2-4 wks | The higher doses 20, 40, 80, mg/kg/day were very poorly tolerated. Rats showed dose-related deterioration of general condition, emaciation, decreased diameter of long bones, single and multiple fractures, elevated serum alkaline phosphatase activity and serum triglyceride levels |
JAMP Acitretin (Acitretin Capsules) Page 33 of 50
| SPECIES | STRAIN SEX/#/ group | ROUTE | DOSE/ mg/kg/day | DURATION /animals/ group | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
| Rats | M/10 | Oral (spray dried powder) | 0 (control) 1 3 5 10 15 | Preliminary Study (dose ranging): 4 weeks | Marked treatment effects at doses of 10 and 15 mg/kg/day included: rough/dull hair. Occasional hyperkeratosis of the tail, loosened incisors, moderate to marked decrease in long bone diameter, focally thickened long bones, and or single and/or multiple fractures of long bones. |
| Rats | 24/sex/ group | Oral (spray dried powder) | 0 (control) 0.5 *(this group was increased to 6.0 for Wks 14-18) 1.0 3.0 | 6 months (26-week dosing period) | *As no major side effects were noted at any of the doses for the first 13 wks, the 0.5 dose group was increased to 6.0 for Wks 14-18: Female rats: presented with failure to gain weight, slight sensitivity to handling, tendency toward decreased motor activity, slight to moderate elevations in serum alkaline phosphatase (149 U/L: 96 U/L control) and elevations (25-70%) in levels of serum cholesterol, triglycerides, and high density lipoprotein. No major bone changes were observed in these female rats. Male rats: 17/24 showed effect characteristic of hypervitaminosis A, i.e., weight loss, increased sensitivity to handling, decreased motor activity, fractures, erythema, crusting of the skin, rough fur. During Wk 18: Serum phosphatase (35 %). Moderate elevations in serum triglyceride concentrations (120 mg/100 mL; 70 mg/100 mL (control). No changes in serum cholesterol of serum low or high density lipoprotein concentrations. Moderate alterations of the ossification of the epiphyseal line in long bones were noted in these rats at |
JAMP Acitretin (Acitretin Capsules) Page 34 of 50
| SPECIES | STRAIN SEX/#/ group | ROUTE | DOSE/ mg/kg/day | DURATION /animals/ group | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
necropsy at the end of the study. These groups (M/F) were placed on an unmedicated diet for one week at Wk 19 and restated on 0.5 mg/kg/day dose. The clinical changes reversed during Wks 20-26. At the end of the 26-week dosing period, 16 rats/sex/group were necropsied; the other 8 rats/sex/group were maintained without treatment for 4 wks to determine reversibility. Dosages of 0.5 and 1.0 mg/kg/day were tolerated without effects. Female rats in the 3.0 dose group presented with minimal, (4.5 %) decreases in body weight gain, and slight to moderate 25-70 % increases in plasma cholesterol, triglycerides, and low and high density lipoproteins. Male rats in the 3.0 dose group presented with slightly greater decreases in body weight gain (11%), increase in serum alkaline phosphatase (10-15%), and a slight tendency to premature ossification of the epiphyseal line. Clinical changes reversed when the 6.0 mg/kg/day dose was decreased back to 0.5 mg/kg/day (Weeks 20-26) and during the recovery period in the other groups. | |||||
| Dog | 6/sex/ Group | Oral (spray dried powder in gelatin capsules) | 0 (control) 5 15 50* | 1 year | A preliminary dose range finding study was conducted in 2 dogs (1/sex) in ascending dose fashion [10 mg/kg/day (Week 1); 20 mg/kg/day (Week 2); 30 mg/kg/day (Week 3); 40 mg/kg/day (Week 4); 60 mg/kg/day (Week 5); 100 mg/kg/day (Week 6)]. In the one-year study, male dogs treated at the high dose (50 mg/kg/day) developed severe otitis externa by 5-6 wks. Treatment was interrupted during Weeks 7-8 and for female dogs during Wks 21-22. Due to persistent recurrence of the |
JAMP Acitretin (Acitretin Capsules) Page 35 of 50
| SPECIES | STRAIN SEX/#/ group | ROUTE | DOSE/ mg/kg/day | DURATION /animals/ group | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
condition, the high dose was decreased to 30 mg/kg/day from Wk 17 for males and Wk 27 for females. At 26 weeks and at 1 year, 2/sex group were killed, necrsopsied and 2 male dogs (1 - 0/ 1- high dose) were maintained for 3 months without treatment to determine reversibility of effects. At doses of 5 and 15 mg/kg/day, mild to moderate reddening of the skin was noted and presented histopathologically as hypertrophy/hyperplasia. The cutaneous effects seen at the 50 mg/kg/day dose were severe and required a decrease to a dose of 30 mg/kg/day. Other clinical findings: A slight decrease in the number of spermatozoa in the testes of one dog at 26 weeks of treatment at the 15 mg/kg/day dose; this improved by 1 yr and reversed during the recovery period. Elevated leucocyte counts were observed in two dogs of each sex (1.38 – 2.20 x 10 10 L (treated); 9.5. x 10 9 L (control)). Increased numbers of immature unsegmented granulocytes (secondary to severe otitis externa) were seen at Week 13. A female dog developed cervical ankylosis. Prostate and testes weights were decreased by approximately 50% at the 6-month sacrifice but the decreases were less pronounced at one year. Almost all treated dogs showed some dose-related hypertrophic and/or hyperplastic alterations of the epidermis and the sebaceous and ceruminous glands. Additionally, in the high-dose dogs, moderate to marked chronic, relapsing, suppurative inflammation was seen in the external ear canal. Mild to moderate spermatogenic arrest and the appearance of multinucleated giant cells were noted in the testes of one mid- |
JAMP Acitretin (Acitretin Capsules) Page 36 of 50
| SPECIES | STRAIN SEX/#/ group | ROUTE | DOSE/ mg/kg/day | DURATION /animals/ group | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
and both high-dose males at 6 months but the severity diminished by the end of the study. All clinical findings reversed during the recovery period. | |||||
| Rat | Wistar/ 20/sex/ dose | Oral (Feed admixture) | 0 (control) 2 4 10 | 18 months | 2, 4 mg/kg/day group: Overall clinical tolerance was good. Minor symptoms were not considered treatment-related, except crust formation on the eyelids, more frequently in males in the 4 mg/kg/day group. 10 mg/kg/day groups: Definite systemic toxicity and treatment was interrupted in Weeks 27 and 28, and in Weeks 54 and 55 due to severe side effects. After 3-4 months treatment at the highest dose, 70 % (26/37) developed signs indicative of long bone fractures. At the end of the study, most of these rats had multiple bone fractures. At study-end, most of the rats in the 10 mg/kg/day group had multiple bone fractures. Severe osteoporosis and multiple fractures of the extremities, shoulder blades and/or spinal column were diagnosed in 5 male and 5 female rats. No bone fractures occurred in any other dosage group. In addition to the clinical signs related to bone fractures, crust formation on the eyelids and nose were seen in the high-dose group. No major hematologic changes were observed. A minimal reduction of erythrocytes (RBC) developed after 4 weeks in male rats administered 4 or 10 mg/kg/day. Maximal reductions in RBC occurred in Weeks 13, 26 and 39 (10% - 4 mg/kg/day; 12% - 10 mg/kg/day). An RBC decrease was observed in high-dose group females after Week 13, with a maximal reduction of 13% in Week 53. In the mid-dose group, the RBC reduction was significant only in Week 39. |
JAMP Acitretin (Acitretin Capsules) Page 37 of 50
| SPECIES | STRAIN SEX/#/ group | ROUTE | DOSE/ mg/kg/day | DURATION /animals/ group | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
Corresponding minimal reductions in hemoglobin and hematocrit and minimal to slight increases in MCV and MCH were observed in high-dose group males and females and mid-dose group males. An increased number of reticulocytes was also noted in males and females of the high-dose group; occasionally, these values slightly exceeded normal physiologic limits. A slight but dose dependent increase in kidney weight was noted in males of the 4 and 10 mg/kg/day groups but with no histomorphologic correlate. A trend to a slight increase in extramedullary hematopoiesis in the spleen of treated rats was considered to result from the slightly increased RBC count. This mostly minimal to slight change was more often seen in animals of the high-dose group. |
Carcinogenicity:
| SPECIES | STRAIN | ROUTE | DOSE mg/kg/day | DURATION | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
| Rats | Wistar (50/sex/ group) | Oral | 0 (control - 1) 0.5 1 2 0 (control - 2) | 104 - week | A total of 159 rats (83 males/76 females) died or were killed during the course of the study. The number of premature killings was slightly increased in high-dose group males due to drug-related clinical symptoms. Most animals died or were killed during the last quarter of the study. Spontaneous deaths or euthanasia were frequently related to tumours of the pituitary gland. Oral administration of 0.5 mg/kg/day acitretin was tolerated without drug-related side effects. In the mid-dose group, the incidence of slight to moderate incrustations in the periocular or nasal areas was slightly |
JAMP Acitretin (Acitretin Capsules) Page 38 of 50
| SPECIES | STRAIN | ROUTE | DOSE mg/kg/day | DURATION | OBSERVATIONS/RESULTS |
|---|---|---|---|---|---|
increased in males and females. These findings were usually noted towards the end of the study. In the high-dose group, incrustations in the periocular or nasal area and fractures of the long bones were observed from 6 months onwards. By the end of the study, most of the rats from the high-dose group had developed these symptoms. In males, stagnation of body weight gain was noted between study Weeks 72 and 77. Drug-related non-neoplastic lesions were seen in the bones of high-dose group animals. Slight to moderate osteoporosis was observed in the femurs of 6 male and 2 female rats, and in the sternum of 5 male and 2 female rats. Calluses were noted in the femurs of 20 males and 20 females, in the sterni of 6 males and 6 females, in the spinal vertebrae of 1 male, and in grossly changed forelimb bones of 13 males and 11 females. Increased erythropoiesis was noted in the spleen of 26 males and 37 females of the high-dose group, in comparison to seven males and 19 females of control group -1, and 12 males and 25 females of control group -2. This increase was considered to be secondary to repeated bone injuries and associated hemorrhages rather than a primary effect of acitretin. Neoplastic lesions, which were observed primarily in the endocrine and reproductive organs and the skin, were considered to reflect the spectrum of spontaneous findings commonly diagnosed in aged rats of this strain. |
JAMP Acitretin (acitretin capsules) Page 39 of 50
Mutagenicity:
No evidence of mutagenicity for acitretin was observed in the following assays:
Ames Mutagenicity Assay using S. typhimurium strains: TA 98, TA 100, TA 1535, and TA 1537 at concentrations up to 30 mcg/plate with and without metabolic activation by hepatic S-9; or using
S. typhimurium strains: TA 98, TA 100, TA 1535, TA 1537, TA 1538, and E. coli strain WP2 uvr at concentrations up to 5,000 mcg/plate with and without metabolic activation by hepatic S-9.
- Hamster V-79/HGPRT Assay in the cell line, V-79 derived from Chinese hamster lung cells at maximum concentrations of 1 mcg/mL without metabolic activation and 200 mcg/mL with metabolic activation by hepatic S-9.
- Unscheduled DNA synthesis in rat hepatocytes at concentrations up to 100 mcg/mL and human fibroblasts at concentrations up to 200 mcg/mL.
- Induction of Chromosomal Aberrations in Human Lymphocytes at concentrations up to 200 mcg/mL with metabolic activation by hepatic S-9.
- Mouse Micronucleus Assay at a single oral dose of 3 mg/kg
Reproductive and Developmental Toxicology:
- Fertility and General Reproductive Performance in Rats
Fertility and reproductive performance was conducted in 36 rats/sex treated with acitretin (in a rape seed oil formulation) at oral doses of 0 (vehicle control), 0.3, 1.0 and 3.0 mg/kg/day. The dosing of male rats was initiated 70 days prior to mating and continued throughout the mating period. The dosing of the female rats was initiated 14 days prior to mating and was continued throughout the mating, gestation, and lactation periods (including Day 22 of lactation). Two successive generations were also studied.
No drug-related parental mortality and no signs of parental toxicity were noted in this study. Survivability of the offspring in the 3.0 mg/kg/day high-dose group was reduced (24.6% mortality compared to 8.8% for the control group) and some of the physical and developmental tests such as hair growth, ear opening, auditory startle, pupilary contraction, and memory retention were adversely affected. There were no treatment related effects observed during the F1 progeny mating studies nor on the survivability and weight development of the F2 progeny.
No effects were observed with the two lowest doses (0.3 and 1.0 mg/kg/day).
- Embryotoxicity and Teratology
Mice
An embryotoxicity/teratogenicity study was conducted in 36 female mice given acitretin orally (as a rape seed oil formulation) at doses of 0 (vehicle control), 1, 3, and 10 mg/kg/day from Day 7 through Day 16 of gestation (mating = Day 1). The study included postnatal evaluation.
There were no signs of adverse maternal effects in any of the dose groups. Vaginal bleeding was noted in all dose groups and some of these animals died. In three mice with vaginal bleeding that survived, complete resorption of all fetuses was noted. The resorption rate for the high-dose group was increased (25.8% compared to 10.2% for the control group).
Dose-dependent teratogenic effects were observed in the mid- and high-dose (3 and 10 mg/kg/day) groups. Skeletal malformations (cervical, neural arches and long bones) and soft tissue malformations
JAMP Acitretin (acitretin capsules) Page 40 of 50
(exencephaly, cleft palate, unilateral kidney agenesis and enlarged renal pelvis) were observed.
No embryotoxicity, teratogenicity or adverse effects on postnatal development of offspring were noted in the low-dose group (1.0 mg/kg/day).
Rats
An embryotoxicity/teratogenicity study with acitretin was conducted in 36 female rats at oral doses of 0 (vehicle control), 7.5, 15 and 30 mg/kg/day. Acitretin was administered as a rape seed oil formulation from Day 7 to 16 of gestation (mating = Day 1). The study included postnatal evaluation of the pups.
No compound-related maternal toxicity or mortality was noted, nor were there drug-related adverse effects on the resorption rate, average litter size, or mean body weight of live fetuses.
Severe isolated malformations (malformed axial skeleton, exencephaly and ectopy of intestines) were noted in two fetuses in the low-dose group (7.5 mg/kg/day). As these deviations were isolated and not dose-related, they may be of a spontaneous nature. The 15 and 30 mg/kg/day, doses were considered to be teratogenic. At 15 mg/kg/day, abnormally shaped humeri were observed; the same malformation as well as malformed radii, ulnae and cleft palate were noted at 30 mg/kg/day.
No effects were noted during postnatal evaluation of offspring from the low- and mid-dose groups. At 30 mg/kg/day pup survival was reduced but the surviving pups were not considered to be adversely affected. The highest dose of acitretin which provided no evidence for teratogenicity in the rat was
7.5 mg/kg/day.
Rabbits
An embryotoxicity/teratogenicity study in rabbits (20 females/group) was conducted with acitretin (in a rape seed oil formulation) at oral doses of 0 (vehicle control), 0.2, 0.6 and 2.0 mg/kg/day. Acitretin was administered from Day 7 to Day 19 of gestation (mating = Day 1).
Maternal weight gain was not adversely affected in any of the dose groups. The dose of 0.6 mg/kg/day resulted in a low incidence of cleft palate and brain anomalies. The 2.0 mg/kg/day dose was teratogenic (open eyes, ectrodactyl, spina bifida, ectopie of abdominal viscera, and bilateral apical deficiencies of the distal phalanges of forelimbs and hind limbs) and resulted in a statistically significant resorption rate (56%). The 24-hour postnatal survival rate of kits (80%) was significantly reduced at the high dose.
No embryotoxic, teratogenic or effects on the course or outcome of the pregnancy were noted at
0.2 mg/kg/day.
Peri-/Postnatal Development in Rats
A peri-/postnatal study was conducted in rats (24 females/group) with acitretin (in a rape seed oil formulation) at oral doses of 0 (vehicle control), 0.3, 1.0 and 3.0 mg/kg/day. Acitretin was administered from Day 16 of pregnancy to Day 22 of lactation (mating = Day 1). The study included postnatal evaluation of pups for physical and functional development.
No effects were seen on maternal mortality, maternal weight gain, and median duration of gestation or resorption rate. No effects were seen on macroscopic and visceral examination of the pups. No alterations
JAMP Acitretin (acitretin capsules) Page 41 of 50
were observed in learning or memory ability or in functional development of the offspring. At 3.0 mg/kg/day, pup survival was approximately 84% compared to 94% for the control group. Incisor eruption delay was the only physical effect noted in the high-dose offspring.
In vitro Studies
Use of acitretin in psoriatic patients results in improvement manifested by a decrease in scale, erythema, and thickness of lesions, and decreased inflammation in the epidermis and dermis.
17 SUPPORTING PRODUCT MONOGRAPHS
PrSORIATANE® (Capsules, 10 mg and 25 mg), submission control 292616, Product Monograph, Allergan Inc. (APR 4, 2025)