


Product Monograph - Jamp Enalapril
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS | 07/2022 |
| 4 DOSAGE AND ADMINISTRATION | 07/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ............................................................................................................... 4
- 1.1 Pediatrics ........................................................................................................................ 4
- 1.2 Geriatrics ........................................................................................................................ 4
- 2 CONTRAINDICATIONS .................................................................................................. 5
- 3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
- 4.1 Dosing Considerations.................................................................................................... 5
- 4.2 Recommended Dose and Dosage Adjustment............................................................... 5
- 4.4 Administration ............................................................................................................... 8
- 4.5 Missed Dose ........................................................................................................................ 8
- 5 OVERDOSAGE.............................................................................................................. 8
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................... 10
- 7.1 Special Populations ...................................................................................................... 14
- 7.1.1 Pregnant Women ............................................................................................... 14
- 7.1.2 Breast-feeding .................................................................................................... 15
- 7.1.3 Pediatrics............................................................................................................ 15
- 7.1.4 Geriatrics ............................................................................................................ 15
8 ADVERSE REACTIONS ................................................................................................. 16
8.1 Adverse Reaction Overview ................................................................................. 16
- 8.2 Clinical Trial Adverse Reactions ............................................................................ 16
- 8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 19
- 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...................................................................................................... 19
- 8.5 Post-Market Adverse Reactions ........................................................................... 20
9 DRUG INTERACTIONS ................................................................................................ 22
9.2 Drug Interactions Overview ........................................................................................ 22
- 9.4 Drug-Drug Interactions ................................................................................................ 22
- 9.5 Drug-Food Interactions ............................................................................................... 25
- 9.6 Drug-Herb Interactions ................................................................................................ 26
- 9.7 Drug-Laboratory Test Interactions.............................................................................. 26
10 CLINICAL PHARMACOLOGY ........................................................................................ 26
- 10.1 Mechanism of Action ................................................................................................. 26
- 10.2 Pharmacodynamics .................................................................................................... 26
- 10.3 Pharmacokinetics ....................................................................................................... 27
- 11 STORAGE, STABILITY AND DISPOSAL ............................................................................. 28
PART II: SCIENTIFIC INFORMATION ........................................................................................ 29
- 13 PHARMACEUTICAL INFORMATION ............................................................................. 29
14 CLINICAL TRIALS ........................................................................................................ 30
- 14.1 Trial Design and Study Demographics ........................................................................... 30
- 14.2 Study Results .............................................................................................................. 31
- 14.3 Comparative Bioavailability Studies……………………………………………………………………….33
- 15 MICROBIOLOGY ........................................................................................................ 35
- 16 NON-CLINICAL TOXICOLOGY ...................................................................................... 35
- 17 SUPPORTING PRODUCT MONOGRAPHS………………………………………………………………………………47
PATIENT MEDICATION INFORMATION ................................................................................... 48
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JAMP Enalapril (enalapril maleate) is indicated for:
- essential or renovascular hypertension
- treatment of symptomatic congestive heart failure
Hypertension
JAMP Enalapril is indicated in the treatment of essential or renovascular hypertension. It is usually administered in association with other drugs, particularly thiazide diuretics.
In using JAMP Enalapril consideration should be given to the risk of angioedema (see 7 WARNINGS AND PRECAUTIONS).
Congestive Heart Failure
JAMP Enalapril is indicated in the treatment of symptomatic congestive heart failure usually in combination with diuretics and/or digitalis. In these patients, enalapril improves symptoms, increases survival, and decreases the frequency of hospitalization (see 14 CLINICAL TRIALS for details and limitations of survival trials). Treatment with JAMP Enalapril should be initiated under close medical supervision.
In clinically stable asymptomatic patients with left ventricular dysfunction (ejection fraction
≤35%), enalapril decreases the rate of development of overt heart failure and decreases the incidence of hospitalization for heart failure (see 14 CLINICAL TRIALS for details and limitations of survival trials).
1.1 Pediatrics
Pediatrics (<16 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of enalapril maleate in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use. See 4 DOSAGE AND ADMINISTRATION
1.2 Geriatrics
Geriatrics: Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 4 DOSAGE AND ADMINISTRATION).
2 CONTRAINDICATIONS
JAMP Enalapril is contraindicated in:
- Patients who are hypersensitive to these products or to any ingredient in their formulation. For a complete listing, see the 6 DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
- Patients with a history of angioneurotic edema relating to previous treatment with an angiotensin converting enzyme inhibitor.
- Patients with hereditary or idiopathic angioedema.
Combination with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or
type 2) or moderate to severe renal impairment (GFR <60 ml/min/1.73 m2) (see 7 WARNINGS AND PRECAUTIONS).
- Combination with a neprilysin inhibitor (e.g., sacubitril). Do not administer JAMP Enalapril within 36 hours of switching to or from sacubitril/valsartan, a product containing a neprilysin inhibitor (See 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The absorption of JAMP Enalapril is not affected by food.
- Dosage must be individualized.
- Special attention for dialysis patients.
The splitting of JAMP Enalapril tablets is not advised.
4.2 Recommended Dose and Dosage Adjustment
Hypertension: Initiation of therapy requires consideration of recent antihypertensive drug treatment, the extent of blood pressure elevation and salt restriction; the dosage of other antihypertensive agents being used with JAMP Enalapril may need to be adjusted.
The recommended initial dose in patients not on diuretics is 5 mg once a day. Dosage should be adjusted according to blood pressure response. The usual dosage range is 10 to 40 mg per day administered in a single dose or two divided doses.
Serious Warnings and Precautions
- When used in pregnancy, angiotensin converting enzyme (ACE) inhibitors can cause injury or even death of the developing fetus. When pregnancy is detected, JAMP Enalapril should be discontinued as soon as possible.
In some patients treated once daily, the antihypertensive effect may diminish toward the end of the dosing interval. In such patients, an increase in dosage or twice-daily administration should be considered. If blood pressure is not controlled, a diuretic may be added.
The maximum daily dose is 40 mg. Raising the dose above that level is not recommended because of the possibility of increased adverse reactions.
Symptomatic hypotension occasionally may occur following the initial dose of JAMP Enalapril and is more likely in patients who are currently being treated with a diuretic. The diuretic should, if possible, be discontinued for two to three days before beginning therapy with JAMP Enalapril to reduce the likelihood of hypotension (see 7 WARNINGS AND PRECAUTIONS).
If the diuretic cannot be discontinued, an initial dose of 2.5 mg should be used to determine whether excessive hypotension occurs.
To date there is insufficient experience with enalapril in the treatment of accelerated or malignant hypertension. JAMP Enalapril, therefore, is not recommended in such situations.
Pediatrics (<16 years of age): The usual recommended starting dose is 0.08 mg/kg (up to 5 mg) once daily. Dosage should be adjusted according to blood pressure response. Doses above 0.58 mg/kg (or in excess of 40 mg) have not been studied in pediatric patients (see 10 CLINICAL PHARMACOLOGY). JAMP Enalapril is not recommended in neonates and in pediatric patients with glomerular filtration rate <30 mL/min/1.73 m2, as no data are available.
Geriatrics (>65 years of age): The starting dose should be 2.5 mg. Some elderly patients may be more responsive to JAMP Enalapril than younger patients.
Dosing Adjustment in Renal Impairment: (See WARNINGS AND PRECAUTIONS, Anaphylactoid Reactions during Membrane Exposure)
The doses should be reduced in patients with hypertension according to the following guidelines:
Table 1. Dosing Adjustment in Renal Impairment
| Renal Status | Creatinine Clearance mL/min (mL/s) | Initial Dose mg/day |
| Normal Renal Function | >80 mL/min (>1.33 mL/s) | 5 mg |
| Mild Impairment | 30 to 80 mL/min (0.50 to 1.33 mL/s) | 5 mg |
| Moderate to Severe Impairment | ≤30 mL/min (≤0.50 mL/s) | 2.5 mg |
| Dialysis Patients | - | 2.5 mg on dialysis daysx |
x Enalaprilat is dialyzable. Dosage on nondialysis days should be adjusted depending on the blood pressure response.
Congestive Heart Failure: Enalapril maleate is generally used in conjunction with a diuretic and/or digitalis. Blood pressure and renal function should be monitored, both before and during treatment with enalapril maleate, because severe hypotension and, more rarely, consequent renal failure have been reported (see 7 WARNINGS AND PRECAUTIONS).
Initiation of therapy requires consideration of recent diuretic therapy and the possibility of severe salt/volume depletion. If possible, the dose of diuretic should be reduced before beginning treatment to reduce the likelihood of hypotension. Serum potassium also should be monitored (see 9 DRUG INTERACTIONS).
The recommended initial dose in patients with symptomatic heart failure or asymptomatic left ventricular dysfunction (ejection fraction ≤35%) is 2.5 mg once a day, to be administered under close medical supervision to determine the initial effect on blood pressure. After the initial dose, the patient should be observed for at least two hours or until the pressure has stabilized for at least another additional hour (see 7 WARNINGS AND PRECAUTIONS).
In the absence of, or after effective management of symptomatic hypotension following initiation of therapy, the dose should be increased gradually depending on the patient’s response. The usual therapeutic dosing range is 5 to 20 mg daily, given as a single dose or two divided doses.
This dose titration may be performed over a 2 to 4 weeks period, or more rapidly if indicated by the presence of residual signs and symptoms of heart failure. The dosage regimen, in patients with symptomatic heart failure, which was effective in reducing mortality and the need for hospitalization in multicentre studies ranged between 16.4 and 18.8 mg/day. The majority of patient experience in clinical studies has been with twice-daily dosage.
The maximum daily dose is 40 mg.
Dosage Adjustment in Patients with Congestive Heart Failure and Renal Impairment or Hyponatremia: In patients with heart failure who have hyponatremia (serum sodium less than 130 mEq/L) or with serum creatinine greater than 1.6 mg/dL, therapy should be initiated at 2.5 mg daily under close medical supervision (see 4 DOSAGE AND ADMINISTRATION and 9 DRUG INTERACTIONS).
The dose may be increased to 2.5 mg b.i.d. then 5 mg b.i.d. and higher as needed, usually at intervals of four days or more if at the time of dosage adjustment there is not excessive hypotension or significant deterioration of renal function.
The maximum daily dose is 40 mg.
4.4 Administration
See 4 DOSAGE AND ADMINISTRATION.
4.5 Missed Dose
Patients should be instructed that if they miss a dose of JAMP Enalapril, they should take the next dose as soon as possible. If no more than six hours have elapsed since the missed dose, the patient can take that day’s dose of medication and then return to the regularly scheduled time. The Patient should not double the dose.
5 OVERDOSAGE
Limited data are available for overdosage in humans. The most prominent features of overdosage reported to date are marked hypotension, beginning some six hours after ingestion of tablets, concomitant with blockade of the renin-angiotensin system, and stupor. Serum enalaprilat levels 100- and 200-fold higher than usually seen after therapeutic doses have been reported after ingestion of 300 mg and 440 mg of enalapril, respectively.
The recommended treatment of overdosage is intravenous infusion of normal saline solution. If ingestion is recent, induce emesis. Enalaprilat may be removed from the general circulation by hemodialysis (see 7 WARNINGS AND PRECAUTIONS).
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | Tablet* 2.5 mg, 5 mg, 10 mg, 20 mg | Anhydrous Lactose, Crospovidone, Maleic acid, Zinc stearate and Hydrogenated Castor oil. Tablets 10 mg contain Ferric oxide red and 20 mg contain Ferric oxide red, as well as Ferric oxide yellow. |
* The splitting of JAMP Enalapril tablets is not advised.
JAMP Enalapril (Enalapril Maleate) is available as uncoated tablets for oral administration.
JAMP Enalapril 2.5 mg tablets are white to off white, oval shaped, flat beveled edged, uncoated tablets debossed with ‘EN25’ on one side and score line on the other side.
JAMP Enalapril 5 mg tablets are white to off white, rounded triangle shaped, biconvex, uncoated tablets debossed with ‘EN5’ on one side and score line on the other side.
JAMP Enalapril 10 mg tablets are rust red coloured, round triangle shaped, biconvex, uncoated tablets debossed with ‘EN10’ on one side and score line on the other side.
JAMP Enalapril 20 mg tablets are peach coloured, rounded, triangle shaped, biconvex, uncoated tablets debossed with ‘EN20’ on one side and score line on the other side
JAMP Enalapril 2.5 mg tablets are available in bottles of 100 tablets.
JAMP Enalapril 5 mg, 10 mg and 20 mg tablets are available in bottles of 100 and 500 tablets.
The splitting of JAMP Enalapril tablets is not advised.
Composition
Each tablet of JAMP Enalapril is made with 2.5, 5, 10 or 20 mg of enalapril maleate respectively in the tablets, and the following non-medicinal ingredients: Anhydrous Lactose, Crospovidone, Maleic acid, Zinc stearate and Hydrogenated Castor oil.
Tablets 10 mg contain Ferric oxide red and 20 mg contain Ferric oxide red, as well as Ferric oxide yellow.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Angioedema: Angioedema of the face, extremities, lips, tongue, glottis and/or larynx has been reported rarely in patients treated with enalapril maleate. This may occur at any time during treatment and may be life threatening.
Very rarely, fatalities have been reported due to angioedema associated with laryngeal edema or tongue edema. Patients with involvement of the tongue, glottis or larynx are likely to experience airway obstruction, especially those with a history of airway surgery. However, where there is involvement of the tongue, glottis or larynx, likely to cause airway obstruction, appropriate therapy which may include subcutaneous adrenaline solution 1:1000 (0.3 mL to 0.5 mL) and/or measures to ensure a patent airway should be administered promptly when indicated.
If angioedema occurs, JAMP Enalapril should be discontinued promptly and appropriate monitoring should be instituted to ensure complete resolution of symptoms prior to dismissing the patient. Even in those instances where swelling of only the tongue is involved, without respiratory distress, patients may require prolonged observation since this may be life threatening and treatment with antihistamines and corticosteroids may not be sufficient.
In patients who experience angioedema, future administration is contraindicated (see 2 CONTRAINDICATIONS).
The incidence of angioedema during ACE inhibitor therapy has been reported to be higher in black than in non-black patients.
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see 2 CONTRAINDICATIONS).
Patients receiving coadministration of ACE inhibitor and mTOR (mammalian target of rapamycin) inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema. Caution should be used when these drugs are used concomitantly (see 9 DRUG INTERACTIONS).
Patients receiving concomitant ACE inhibitor and neprilysin inhibitor therapy may be at increased risk for angioedema (see 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS).
Patients receiving concomitant ACE inhibitor and dipeptidyl peptidase IV (DPP-IV inhibitors such as alogliptin, linagliptin, saxagliptin, and sitagliptin may be at increased risk for angioedema (see 9 DRUG INTERACTIONS). Caution should be used when these drugs are used concomitantly.
Anaphylactoid Reactions during Membrane Exposure: Anaphylactoid reactions have been reported in patients dialysed with high-flux membranes (e.g., polyacrylonitrile [PAN]) and treated concomitantly with an ACE inhibitor. Dialysis should be stopped immediately if symptoms such as nausea, abdominal cramps, burning, angioedema, shortness of breath and severe hypotension occur. Symptoms are not relieved by antihistamines. In these patients consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent.
Anaphylactoid Reactions during Desensitization: There have been isolated reports of patients experiencing sustained life-threatening anaphylactoid reactions while receiving ACE inhibitors during desensitizing treatment with hymenoptera (bees, wasp) venom. In the same patients, these reactions have been avoided when ACE inhibitors were temporarily withheld for at least 24 hours, but they have reappeared upon inadvertent re challenge.
Anaphylactoid Reactions during LDL Apheresis: Rarely, patients receiving ACE inhibitors during low-density lipoprotein (LDL)-apheresis with dextran sulfate have experienced life- threatening anaphylactoid reactions. These reactions were avoided by temporarily withholding ACE inhibitor therapy prior to each apheresis.
Cardiovascular
Hypotension: Symptomatic hypotension has occurred after administration of enalapril maleate, usually after the first or second dose or when the dose was increased. It is more likely to occur in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, or vomiting. In patients with severe congestive heart failure, with or without associated renal insufficiency, excessive hypotension has been observed and may be associated with oliguria and/or progressive azotemia, and rarely with acute renal failure and/or death.
Because of the potential fall in blood pressure in these patients, therapy should be started under very close medical supervision, usually in a hospital. Such patients should be followed closely for the first two weeks of treatment and whenever the dose of enalapril and/or diuretic is increased. Similar considerations may apply to patients with ischemic heart or cerebrovascular disease in whom an excessive fall in blood pressure could result in a myocardial infarction or cerebrovascular accident (see 8 ADVERSE REACTIONS).
If hypotension occurs, the patient should be placed in supine position and, if necessary, receive an intravenous infusion of normal saline. A transient hypotensive response is not a contraindication to further doses which usually can be given without difficulty once the blood pressure has increased after volume expansion.
Valvular Stenosis: There is concern on theoretical grounds that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Dual Blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin converting enzyme inhibitors (ACEIs), such as enalapril maleate, or of angiotensin receptor antagonists (ARBs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR <60 ml/min/1.73 m2). Therefore, the use of JAMP Enalapril, in combination with aliskiren-containing drugs is contraindicated in these patients (see 2 CONTRAINDICATIONS). Further, co-administration of ACEIs, including JAMP Enalapril, with other agents blocking the RAS, such as ARBs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia.
Ear/Nose/Throat
Cough: A dry, persistent cough, which usually disappears only after withdrawal or lowering of the dose of enalapril maleate has been reported. Such possibility should be considered as part of the differential diagnosis of the cough.
Endocrine and Metabolism
Hypoglycemia: Rare cases of hypoglycemia in diabetic patients on oral antidiabetic agents or insulin have been reported. Diabetic patients treated with oral antidiabetic agents or insulin starting an ACE inhibitor should be told to closely monitor for hypoglycemia, especially during the first month of combined use. In addition, hypoglycemia appeared to be more likely to occur during the first weeks of combined treatment and in patients with renal impairment (see 8 ADVERSE REACTIONS).
Hematologic
Neutropenia/Agranulocytosis: Agranulocytosis and bone marrow depression have been caused by angiotensin converting enzyme inhibitors. Several cases of agranulocytosis and neutropenia have been reported in which a causal relationship to enalapril cannot be excluded. Current experience with the drug shows the incidence to be rare. Periodic monitoring of white blood cell counts should be considered, especially in patients with collagen vascular disease and renal disease.
Hepatic/Biliary/Pancreatic
Patients with Impaired Liver Function: Hepatitis, jaundice (hepatocellular and/or cholestatic), elevations of liver enzymes and/or serum bilirubin have occurred during therapy with enalapril maleate in patients with or without pre-existing liver abnormalities (see 8 ADVERSE REACTIONS). In most cases the changes were reversed on discontinuation of the drug.
Should the patient receiving JAMP Enalapril experience any unexplained symptoms (see PATIENT MEDICATION INFORMATION), particularly during the first weeks or months of treatment, it is recommended that a full set of liver function tests and any other necessary investigation be carried out. Discontinuation of JAMP Enalapril should be considered when appropriate.
There are no adequate studies in patients with cirrhosis and/or liver dysfunction JAMP Enalapril should be used with particular caution in patients with pre-existing liver abnormalities. In such patients, baseline liver function tests should be obtained before administration of the drug and close monitoring of response and metabolic effects should apply.
Nitritoid Reactions – Gold: Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including enalapril (see 9 DRUG INTERACTIONS).
Peri-Operative Considerations
Surgery/Anesthesia: In patients undergoing major surgery or during anesthesia with agents that produce hypotension, enalapril blocks angiotensin II formation, secondary to compensatory renin release. If hypotension occurs and is considered to be due to this mechanism, it can be corrected by volume expansion.
Renal
Renal Impairment: As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk.
The use of ACEIs – including of JAMP Enalapril – or ARBs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR <60 ml/min/1.73 m2). (See 2 CONTRAINDICATIONS and 9 DRUG INTERACTIONS, Dual Blockade of the Renin- Angiotensin-System (RAS) with ACEIs, ARBs or aliskiren-containing drugs).
Use of JAMP Enalapril should include appropriate assessment of renal function.
Hyperkalemia: Elevated serum potassium (greater than 5.7 mEq/L) was observed in approximately one percent of hypertensive patients in clinical trials with enalapril. In most cases these were isolated values which resolved despite continued therapy. Hyperkalemia was a cause of discontinuation of therapy in 0.28% of hypertensive patients. Risk factors for the development of hyperkalemia include renal insufficiency, diabetes mellitus, and concomitant use of potassium- sparing diuretics (e.g., spironolactone, eplerenone, triamterene, or amiloride), potassium supplements, potassium-containing salt substitutes or other drugs that may increase serum potassium (e.g., trimethoprim-containing products). The use of potassium supplements, potassium-sparing diuretics, potassium-containing salt substitutes or other drugs that may increase serum potassium, particularly in patients with impaired renal function should be given only for documented hypokalemia and with caution and frequent monitoring of serum potassium since they may lead to a significant increase in serum potassium. Hyperkalemia can cause serious, sometimes fatal, arrhythmias. If concomitant use of JAMP Enalapril and any of the above-mentioned agents is deemed appropriate, they should be used with caution and with frequent monitoring of serum potassium (see 9 DRUG INTERACTIONS).
7.1 Special Populations
- 7.1.1 Pregnant Women
Pregnant Women: ACE inhibitors can cause fetal and neonatal morbidity and mortality when administered to pregnant women. When pregnancy is detected, JAMP Enalapril should be discontinued as soon as possible.
The use of ACE inhibitors during the second and third trimesters of pregnancy has been associated with fetal and neonatal injury including hypotension, neonatal skull hypoplasia, anuria, reversible or irreversible renal failure, and death. Oligohydramnios has also been reported, presumably resulting from decreased fetal renal function, associated with fetal limb contractures, craniofacial deformation, and hypoplastic lung development.
Prematurity, and patent ductus arteriosus and other structural cardiac malformations, as well as neurologic malformations, have also been reported following exposure in the first trimester of pregnancy.
Infants with a history of in utero exposure to ACE inhibitors should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit.
Enalapril has been removed from the neonatal circulation by peritoneal dialysis with some clinical benefit and may, theoretically, be removed by exchange transfusion, although there is no experience with the latter procedure.
Animal Data
Maternal and fetal toxicity occurred in some rabbits given enalapril at doses of 1 mg/kg/day or more. Saline supplementation prevented the maternal and fetal toxicity seen at doses of 3 and 10 mg/kg/day, but not at 30 mg/kg/day (50 times the maximum human dose). Enalapril was not teratogenic in rabbits.
There was no fetotoxicity or teratogenicity in rats treated with enalapril at doses up to
200 mg/kg/day (333 times the maximum human dose). Fetotoxicity expressed as a decrease in average fetal weight, occurred in rats given 1200 mg/kg/day of enalapril, but did not occur when these animals were supplemented with saline. The drug crosses the placental barrier in rats and hamsters.
7.1.2 Breast-feeding
Nursing Women: Enalapril and enalaprilat are secreted in human milk in trace amounts. Use of ACE inhibitors (JAMP Enalapril) is not recommended during breast-feeding.
7.1.3 Pediatrics
Pediatrics (<16 years of age): The safety and antihypertensive effect have been studied short- term (one month) in patients aged 6 to 16 years (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics).
JAMP Enalapril is not recommended in neonates and in children with glomerular filtration rate
<30 mL/min/1.73 m2, as no data are available.
7.1.4 Geriatrics
See 4 DOSAGE AND ADMINISTRATION.
8 ADVERSE REACTIONS
- 8.1 Adverse Reaction Overview
The most severe adverse reactions were: angioedema (0.2%), hypotension (2.3%) and renal failure (5 cases).
In hypertensive patients, hypotension occurred in 0.9% and syncope in 0.5%. In congestive heart failure patients, hypotension occurred in 4.4% and syncope in 0.8%.
The most frequent clinical adverse reactions were: headache (4.8%), dizziness (4.6%) and fatigue (2.8%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Hypertension
Adverse experiences occurring in greater than one percent of patients with hypertension treated with enalapril maleate in controlled clinical trials are shown below. In patients treated with enalapril maleate, the maximum duration of therapy was three years; in placebo treated patients the maximum duration of therapy was 12 weeks.
Table 3 Hypertension
| Enalapril maleate n = 2314 | Placebo n = 230 | |
| Body As A Whole Fatigue Orthostatic effects Asthenia | 3.0 1.2 1.1 | 2.6 0.0 0.9 |
| Digestive Diarrhea Nausea | 1.4 1.4 | 1.7 1.7 |
Nervous /Psychiatric Headache Dizziness | 5.2 4.3 | 9.1 4.3 |
Respiratory Cough | 1.3 | 0.9 |
Skin Rash | 1.4 | 0.4 |
Heart Failure
Adverse experiences occurring in greater than one percent of patients with heart failure treated with enalapril maleate are shown below. The incidences represent the experiences from both controlled and uncontrolled clinical trials (maximum duration of therapy was approximately one year). In the placebo treated patients, the incidences reported are from the controlled trial s (maximum duration of therapy is 12 weeks). The percentage of patients with severe heart failure (New York Heart Association [NYHA] Class IV) was 29 percent and 43 percent for patients treated with enalapril maleate and placebo, respectively.
Table 4 – Congestive Heart Failure
| Enalapril maleate n = 2314 | Placebo n = 230 | |
Body As A Whole Orthostatic Effects Syncope Chest Pain Fatigue Abdominal Pain Asthenia | 2.2 2.2 2.1 1.8 1.6 1.6 | 0.3 0.9 2.1 1.8 2.1 0.3 |
Cardiovascular Hypotension Orthostatic Hypotension Angina Pectoris Myocardial Infarction | 6.7 1.6 1.5 1.2 | 0.6 0.3 1.8 1.8 |
Digestive Diarrhea Nausea Vomiting | 2.1 1.3 1.3 | 1.2 0.6 0.9 |
Nervous/Psychiatric Dizziness Headache Vertigo | 7.9 1.8 1.6 | 0.6 0.9 1.2 |
| Respiratory Cough Bronchitis Dyspnea Pneumonia | 2.2 1.3 1.3 1.0 | 0.6 0.9 0.4 2.4 |
Skin Rash | 1.3 | 2.4 |
Urogenital Urinary Tract Infection | 1.3 | 2.4 |
- 8.3 Less Common Clinical Trial Adverse Reactions
Hypertension
Cardiovascular: Hypotension, chest pain, palpitations, acute myocardial infarction
Digestive: Vomiting, dysphagia, abdominal pain Hematologic: Anemia, Leukopenia Hypersensitivity: Angioedema
Musculoskeletal: Muscle cramps
Nervous System/Psychiatric: Insomnia, nervousness, somnolence, paresthesia
Respiratory: Dyspnea
Skin: Pruritus, hyperhidrosis
Special Senses: Taste disturbance
Urogenital: Renal failure, proteinuria, oliguria, impotence
Heart Failure
Cardiovascular: Palpitations
Musculoskeletal: Muscle cramps Nervous System/Psychiatric: Insomnia Skin: Pruritus
Special Senses: Taste disturbance
Urogenital: Renal failure, impotence
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Hyperkalemia: (See 7 WARNINGS AND PRECAUTIONS)
Creatinine, Blood Urea Nitrogen (BUN): Increases in serum creatinine and BUN were reported in about 20% of patients with renovascular hypertension and in about 0.2% of patients with essential hypertension treated with enalapril maleate alone.
In patients with congestive heart failure, who were also receiving diuretics and/or digitalis, increases in BUN and serum creatinine, usually reversible upon discontinuation of enalapril maleate and/or concomitant therapy, were observed in about 9.7% of patients.
Hemoglobin and Hematocrit: Decreases in hemoglobin and hematocrit (mean approximately
0.34 g% and 1.0 vol%, respectively) occurred frequently in either hypertensive or congestive heart failure patients treated with enalapril maleate but were rarely of clinical importance. In clinical trials, less than 0.1% of patients discontinued therapy due to anemia.
Hepatic: Elevations of liver enzymes and/or serum bilirubin have occurred (see WARNINGS AND PRECAUTIONS).
Clinical Trial Findings
Pediatric Patients: In a four-week placebo-controlled clinical trial, 110 hypertensive pediatric patients (6–16 years of age) received medication for 14 days including 51 patients for a four- week period. The adverse experience profile was no different from that seen in adult patients.
Post-Market Findings
Laboratory Test Findings: Hyponatremia
8.5 Post-Market Adverse Reactions Adverse Reactions Reported in Uncontrolled Trials and/or Marketing Experience:
Other serious clinical adverse experiences occurring since the drug was marketed or adverse experiences occurring in 0.5 to 1.0 percent of patients with hypertension or heart failure in clinical trials are listed below and, within each category, are in order of decreasing severity.
Body as a Whole
Anaphylactoid reactions (see 7 WARNINGS AND PRECAUTIONS).
Cardiovascular
Cardiac arrest, myocardial infarction or cerebrovascular accident, possibly secondary to excessive hypotension in high-risk patients (see WARNINGS ANDPRECAUTIONS); pulmonary embolism and infarction; pulmonary edema; angina pectoris; arrhythmia including atrial tachycardia and bradycardia; atrial fibrillation; palpitation, Raynaud’s phenomenon.
Endocrine
Syndrome of inappropriate anti diuretic hormone secretion (SIADH).
Digestive
Ileus, pancreatitis, hepatic failure, hepatitis (hepatocellular or cholestatic jaundice), liver function abnormalities (see 7 WARNINGS AND PRECAUTIONS), melena, anorexia, dyspepsia, constipation, glossitis, stomatitis, dry mouth.
Hematologic
Rare cases of neutropenia, thrombocytopenia, hemolytic anemia and bone marrow depression.
Metabolic
Rare cases of hypoglycemia in diabetic patients on oral anti diabetic agents or insulin have been reported (see 7 WARNINGS AND PRECAUTIONS).
Musculoskeletal
Muscle cramps.
Nervous System/Psychiatric
Vertigo, depression, confusion, ataxia, somnolence, insomnia, nervousness, peripheral neuropathy (e.g., paresthesia, dysesthesia), dream abnormality.
Respiratory
Bronchospasm, rhinorrhea, sore throat and hoarseness, asthma, upper respiratory infection, pulmonary infiltrates, eosinophilic pneumonitis.
Skin
Exfoliative dermatitis, toxic epidermal necrolysis, Stevens-Johnson syndrome, pemphigus, herpes zoster, erythema multiforme, urticaria, pruritus, alopecia, flushing, diaphoresis, photosensitivity.
Special Senses
Blurred vision, taste alteration, anosmia, tinnitus, conjunctivitis, dry eyes, tearing, hearing impairment.
Urogenital
Renal failure, oliguria, renal dysfunction (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION), flank pain, gynecomastia, impotence.
A symptom complex has been reported which may include some or all of the following: fever, serositis, vasculitis, myalgia/myositis, arthralgia/arthritis, a positive anti nuclear antibody (ANA), elevated erythrocyte sedimentation rate, eosinophilia and leukocytosis. Rash, photosensitivity or other dermatologic manifestations may occur. These symptoms may be reversible upon discontinuation of therapy.
In very rare cases, intestinal angioedema has been reported with angiotensin converting enzyme inhibitors including enalapril.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
See Drug-Drug Interactions table
9.4 Drug-Drug Interactions
Table 5- Established or Potential Drug-Drug Interactions
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Agents Affecting Sympathetic Activity | Beta-adrenergic blocking drugs add some further antihypertensive effect to enalapril. | Agents affecting sympathetic activity (e.g., ganglionic blocking agents or adrenergic neuron blocking agents) may be used with caution. | |
| Agents Causing Renin Release | The antihypertensive effect of JAMP Enalapril augmented by antihypertensive agents that cause renin release (e.g., diuretics). | ||
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
| Agents Increasing Serum Potassium | Since enalapril decreases aldosterone production, elevation of serum potassium may occur | Potassium-sparing diuretics such as spironolactone, eplerenone, triamterene or amiloride, potassium supplements or other drugs that may increase serum potassium (e.g., trimethoprim-containing products) should be given only for documented hypokalemia and with caution and frequent monitoring of serum potassium particularly in patients with impaired renal function since they may lead to a significant increase in serum potassium. Salt substitutes which contain potassium should also be used with caution (see 7 WARNINGS AND PRECAUTIONS). | |
| Dual Blockade of the Renin- Angiotensin System (RAS) with ACEIs, ARBs or aliskiren- containing drugs | Increased incidence of severe hypotension, renal failure, and hyperkalemia. | Dual Blockade of the Renin- Angiotensin System (RAS) with ACEIs, ARBs or aliskiren-containing drugs is contraindicated in patients with diabetes and/or renal impairment, and is generally not recommended in other patients. See 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS | |
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
| Gold | Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium auro thiomalate) and concomitant ACE inhibitor therapy including enalapril | See 7 WARNINGS AND PRECAUTIONS | |
| Hypotension – Patients on Diuretic Therapy | Patients on diuretics and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with enalapril. | The possibility of hypotensive effects with enalapril can be minimized by either discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with enalapril (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION). | |
| Lithium Salts | As with other drugs which eliminate sodium, lithium clearance may be reduced. | Therefore, the serum lithium levels should be monitored carefully if lithium salts are to be administered. | |
| Mammalian Target of Rapamycin (mTOR) Inhibitors | Patients taking concomitant mTOR inhibitor(e.g., temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema. | Caution should be used when these drugs are used concomitantly (see 7 WARNINGS and PRECAUTIONS). | |
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
| Neprilysin Inhibitors | Patients taking a concomitant neprilysin inhibitor(e.g., sacubitril) may be at increased risk for angioedema | (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS). | |
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) Including Selective Cyclooxygenase-2 Inhibitors | In some patients with compromised renal function (e.g., elderly patients or patients who are volume- depleted including those on diuretic therapy) who are being treated with NSAIDS including selective COX-2 inhibitors, the co-administration of ACE inhibitors or angiotensin II receptor antagonists may result in further deterioration of renal function. Cases of acute renal failure, usually reversible, have also been reported. | The antihypertensive effect of enalapril may be diminished with concomitant non-steroidal anti- inflammatory drug use including selective cyclooxygenase-2 inhibitors (COX-2 inhibitors). This combination should therefore be administered with caution in this patient population. | |
Dipeptidyl peptidase IV (DPP- IV) inhibitors (e.g. alogliptin, linagliptin, saxagliptin, sitagliptin) | C | Patients taking concomitant DPP-IV inhibitors may be at increased risk for angioedema | Caution should be used when using DPP-IV and ACE inhibitors concomitantly (see 7 WARNING AND PRECAUTIONS). |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
The absorption of enalapril is not influenced by the presence of food in the gastrointestinal tract.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
- 10.1 Mechanism of Action
Enalapril maleate is an ACE inhibitor which is used in the treatment of hypertension and heart failure.
Angiotensin converting enzyme (ACE) is a peptidyl dipeptidase which catalyzes the conversion of angiotensin I to the pressor substance, angiotensin II. After absorption, enalapril, a pro-drug, is hydrolyzed to enalaprilat, its active metabolite, which inhibits ACE. Inhibition of ACE results in decreased plasma angiotensin II, which leads to increased plasma renin activity (due to removal of negative feedback of renin release) and decreased aldosterone secretion. Although the latter decrease is small, it results in a small increase in serum potassium. In patients treated with enalapril maleate and a thiazide diuretic there was essentially no change in serum potassium (see WARNINGS AND PRECAUTIONS).
ACE is identical to kininase II. Thus, enalapril maleate may also block the degradation of bradykinin, a potent vaso depressor peptide. However, the role that this plays in the therapeutic effects of either drug is unknown.
While the mechanism through which enalapril maleate lowers blood pressure is believed to be primarily the suppression of the renin-angiotensin-aldosterone system, enalapril maleate also lowers blood pressure in patients with low-renin hypertension.
10.2 Pharmacodynamics
Administration of enalapril maleate to patients with hypertension results in a reduction of both supine and standing blood pressure. Abrupt withdrawal of enalapril maleate has not been associated with a rapid increase in blood pressure. In most patients studied, after oral administration of an individual dose of enalapril, the onset of antihypertensive activity is seen at one hour with peak reduction of blood pressure achieved by 4–6 hours. At recommended doses, the antihypertensive effect has been shown to be maintained for at least 24 hours. In some patients the effect may diminish towards the end of the dosing interval (see 4 DOSAGE AND ADMINISTRATION). On occasion, achievement of optimal blood pressure reduction may require several weeks of therapy.
In hemodynamic studies in patients with essential hypertension, blood pressure reduction was accompanied by a reduction in peripheral arterial resistance with an increase in cardiac output and little or no change in heart rate. Following administration of enalapril maleate, there was an increase in renal blood flow; glomerular filtration rate was usually unchanged.
When enalapril maleate is given together with thiazide-type diuretics, its blood pressure lowering effect is approximately additive.
Administration of enalapril to patients with congestive heart failure reduces afterload and preload of the heart, resulting in an increase in cardiac output, without reflex tachycardia.
When used in hypertensive, normo lipidemic patients, enalapril had no effect on plasma lipoprotein fractions.
Studies in dogs indicate that enalapril crosses the blood brain barrier poorly, if at all; enalaprilat does not enter the brain.
10.3 Pharmacokinetics
Table 6- Summary of Enalaprilat’s Pharmacokinetic Parameters in Healthy Volunteers Further to a 10 mg
Oral Dose of Enalapril
Cmax ng/mL | t½ (h)* | AUC0-∞ ng•h/mL | |
| Single dose mean | 32.3 | 11 | 423 |
*Effective half-life of accumulation
Absorption
Enalapril maleate is rapidly absorbed with peak serum concentrations of enalapril occurring within one hour. Based on urinary recovery the extent of absorption of enalapril from enalapril maleate is approximately 60%. The absorption of enalapril is not influenced by the presence of food in the gastrointestinal tract.
Metabolism:
Following absorption, enalapril is rapidly and extensively hydrolyzed to enalaprilat, a potent angiotensin converting enzyme inhibitor (which itself is poorly absorbed). Peak serum concentrations of enalaprilat occur 3 to 4 hours after an oral dose of enalapril. Except for conversion to enalaprilat, there is no evidence of significant metabolism of enalapril.
Elimination
Excretion of enalapril is primarily renal. Approximately 94% of the dose is recovered in the urine and feces as enalaprilat or enalapril. The principal components in urine are enalaprilat, accounting for about 40% of the dose, and intact enalapril.
The serum concentration profile of enalaprilat exhibits a prolonged terminal phase, apparently associated with binding to ACE. The effective half-life for accumulation of enalaprilat following multiple doses of enalapril is 11 hours.
In hypertensive children aged 2 months to 15 years the kinetics of enalapril maleate were approximately similar to adults (see 4 DOSAGE AND ADMINISTRATION).
Special Populations and Conditions
- Pediatrics: In pediatric patients the antihypertensive effect of enalapril maleate has been studied in hypertensive children aged 6–16 years (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY,10.3 PHARMACOKINETICS).
- Race: The antihypertensive effect of angiotensin converting enzyme inhibitors is generally lower in black than in non-black patients.
- Renal Insufficiency: The disposition of enalapril and enalaprilat in patients with renal insufficiency is similar to that in patients with normal renal function until the glomerular filtration rate is 30 mL/min (0.50 mL/s) or less. With renal function ≤30 mL/min (≤0.50 mL/s), peak and trough enalaprilat levels increase, time to peak concentration increases and time to steady state may be delayed. The effective half-life of enalaprilat following multiple doses of enalapril is prolonged at this level of renal insufficiency (see 4 DOSAGE AND ADMINISTRATION). Enalaprilat is dialyzable at the rate of 62 mL/min (1.03 mL/s).
11 STORAGE, STABILITY AND DISPOSAL
Store at controlled room temperature (15°C–30°C). Keep container tightly closed. Protect from moisture.
NOTE: Tablets should be discarded after 6 months of opening the bottle.
PART II: SCIENTIFIC INFORMATION
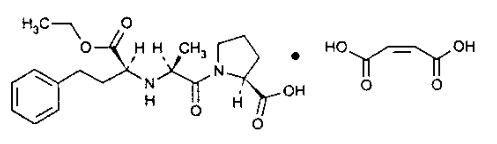
- 13 PHARMACEUTICAL INFORMATION Drug Substance
| Enalapril maleate | ||
| Proper name: | Enalapril maleate | |
| Chemical name: | L-Proline, 1-[N-[1- (ethoxycarbonyl)-3-phenylpropyl]- L-alanyl]-, (S)-, (Z)-2-butenedioate (1:1). | |
| Molecular formula: | C20 H28 N2 O5 .C4 H4 O4 | |
| Molecular mass: | 492.53 | |
| Structural formula: | ||
| Physicochemical properties: | Enalapril maleate is a white to off- white crystalline powder which melts at ≈143°C to 144°C. It is sparingly soluble in water (pH 3.4), soluble in ethanol, and freely soluble in methanol and dimethyl formamide. The pKa1 and pKa2 of the base moiety are 3.0 and 5.4 respectively. |
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 7- Summary of patient demographics for clinical trials SOLVD – Treatment study
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
SOLVD- Treatment | Multicentre, randomized, double- blind, placebo- controlled | 2.5 or 5 mg twice daily Titrated up to 10 mg twice daily up to 55 months | 2569 Placebo: 1284 Enalapril: 1285 | 60.2 years (20–80) | Male: 2065 Female: 504 |
Table 8– Summary of patient demographics for clinical trials SOLVD-Prevention study
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
SOLVD- Prevention | Multicentre, randomized, double- blind, placebo- controlled | 2.5 mg twice daily gradually increased to 10 mg twice daily Follow-up for a minimum of 46 months to a maximum of 62 months | 4228 Placebo: 2117 Enalapril: 2111 | 58.7 years (20–80) | Male: 3752 Female: 476 |
Table 9 – Summary of patient demographics for clinical trials
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| CONSENSUS | Multicentre, randomized, double-blind, | 5 mg twice daily increased to a maximum of | 253 Placebo: 126 | 70 years (36–91) | Male: 179 |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
placebo- controlled | 20 mg twice daily | Enalapril: 127 | Female: 74 |
14.2 Study Results
Table 10 - Results of study SOLVD – Treatment study
| Primary Endpoints | Associated value and statistical significance for Enalapril N (%) | Associated value and statistical significance for Placebo N (%) | p-Value |
| Overall mortality | 451 (35.1%) | 510 (39.7%) | 0.008 |
In a multicentre, placebo-controlled, double-blind study (SOLVD), 2569 patients with symptomatic heart failure (primarily New York Heart Association Class II and III and ejection fraction ≤35%), were randomized to placebo or enalapril given as an adjunct to conventional therapy. Diseases that excluded patients from enrolment in the study included severe stable angina, hemodynamically significant valvular or outflow tract obstruction, renal failure, cerebral vascular disease (e.g., significant carotid artery diseases), advanced pulmonary disease, malignancies, active myocarditis and constrictive pericarditis. The use of enalapril was associated with an 11% reduction in all-cause mortality (which corresponds to a 16% risk reduction in all-cause mortality) and a 30% reduction in hospitalization forheart failure (which corresponds to a 36% risk reduction in hospitalization for heart failure). The chief difference in mortality was in deaths due to progressive heart failure. There was no significant difference in the number of deaths classified as due to arrhythmia without worsening congestive heart failure.
Table 11– Results of SOLVD-Prevention study
| Primary Endpoints | Enalapril N (%) | Placebo N (%) | p-Value |
| Overall mortality | 306 (14.5%) | 332 (15.7%) | 0.211 |
A second multicentre trial used the SOLVD protocol for a study of asymptomatic or minimally symptomatic patients. SOLVD-Prevention patients, who had left ventricular ejection fraction
≤35% and no history of symptomatic heart failure, were randomized to placebo (n=2117) or enalapril (n=2111) and followed for up to 5 years. The majority of patients in the SOLVD-
Prevention trial had a history of ischemic heart disease. A history of myocardial infarction was present in 80% of patients, current angina pectoris in 34%, and a history of hypertension in 37%. No statistically significant mortality effect was demonstrated in this population. Enalapril - treated subjects had 32% fewer first hospitalizations for heart failure, and 32% fewer total heart failure hospitalizations. Compared to placebo, 32% fewer patients receiving enalapril developed symptoms of overt heart failure.
Hospitalizations for cardiovascular reasons were also reduced. There was an insignificant reduction in hospitalizations for any cause in the enalapril treatment group (for enalapril vs. placebo, respectively, 1166 vs. 1201 first hospitalizations, 2649 vs. 2840 total hospitalizations), although the study was not powered to look for such an effect.
The SOLVD-Prevention trial was not designed to determine whether treatment of asymptomatic patients with low ejection fraction would be superior, with respect to preventing hospitalization, to closer follow-up and use of enalapril at the earliest sign of heart failure.
However, under the conditions of follow-up in the SOLVD-Prevention trial (every four months at the study clinic; personal physician as needed), 68% of patients on placebo who were hospitalized for heart failure had no prior symptoms recorded which would have signaled initiation of treatment.
The SOLVD-Prevention trial was also not designed to show whether enalapril modified the progression of underlying heart disease.
Table 12 – Results of CONSENSUS study
| Primary Endpoints | Enalapril N (%) | Placebo N (%) | p-Value | ||||
| Overall mortality | 6 months | 33 (26.0%) | 55 (43.6%) | 0.004 | |||
| 12 months | 46 (36.2%) | 66 (52.4%) | 0.011 | ||||
| End of study | 50 (39.4%) | 68 (54.0%) | 0.003 | ||||
In another multicentre, placebo-controlled trial (CONSENSUS, see BIBLIOGRAPHY, no. 22), 253 patients with severe congestive heart failure (New York Heart Association Class IV) were randomized to placebo or enalapril given as an adjunct to conventional therapy. The use of enalapril was associated with an improvement of symptoms and a reduction in mortality from the progression of heart failure. No difference was seen in the incidence of sudden cardiac death.
14.3 Comparative Bioavailability Studies
A double blind, balanced, randomized, two-treatment, two-period, two-sequence, single dose, crossover, bioequivalence study comparing JAMP Enalapril 20 mg tablets (JAMP Pharma Corporation) to PrVASOTEC® 20 mg tablets (Merck Frosst Canada Ltd., Merck Frosst Canada Ltdée.) was conducted with 33 normal, healthy, adult, human male subjects under fasting conditions.
Enalapril (1 x 20 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng*hr/mL) | 251.70 280.39 (77.90) | 256.31 258.05 (11.85) | 98.20 | 88.66 to 108.77 |
AUCI (ng*hr/mL) | 279.39 379.10 (158.78) | 262.55 264.26 (11.56) | 106.41 | 90.87 to 124.62 |
Cmax (ng/mL) | 155.09 157.25 (17.61) | 155.78 157.85 (16.47) | 99.55 | 93.33 to 106.19 |
Tmax§ (h) | 0.95 (133.14) | 0.70 (32.54) | ||
T½§ (h) | 1.39 (147.60) | 1.33 (58.40) | ||
* JAMP Enalapril 20 mg tablets (JAMP Pharma Corporation, Canada)
† PrVasotec® 20 mg tablets (Merck Frosst Canada Inc., Merck Frosst Canada Ltée), were purchased in Canada
€ Expressed as the arithmetic mean (CV%) only
A double blind, balanced, randomized, two-treatment, two-period, two-sequence, single dose, crossover, bioequivalence study comparing JAMP Enalapril 10 mg tablets (JAMP Pharma Corporation) to PrVASOTEC® 10 mg tablets (Merck Frosst Canada Ltd., Merck Frosst Canada Ltdée.) was conducted with 35 normal, healthy, adult, human male subjects under fasting conditions.
Enalapril (1 x 10 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | Confidence Interval |
AUCT‡ (ng*hr/mL) | 140.96 143.81 (20.16) | 133.98 139.26 (28.94) | 105.21 | 99.47% to 111.27% |
AUCI (ng*hr/mL) | 145.27 148.05 (19.64) | 138.09 143.26 (28.28) | 105.20 | 99.65% to 111.06% |
Cmax (ng/mL) | 94.17 96.48 (22.64) | 88.29 91.00 (24.68) | 106.65 | 100.35% to 113.35% |
Tmax§ (h) | 0.87 (25.44) | 0.86 (29.41) | ||
T½§ (h) | 0.94 (60.81) | 0.83 (15.98) | ||
* JAMP Enalapril 10 mg tablets (JAMP Pharma Corporation, Canada)
† PrVasotec® 10 mg tablets (Merck Frosst Canada Inc., Merck Frosst Canada Ltée), were purchased in Canada
€ Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Table 13 – Mechanism of Action
| Study | Species/Strain | No. of Animals/Group | Route | Dose | Results |
|---|---|---|---|---|---|
Effect of enalapril maleate on total serum ACE in rats and dogs | Male Sprague/ Dawley rats | 12 experimental 6 placebo | P.O. | 10 mg/kg/day for 7 or 14 days | 79% increase in ACE after 7 days & 140% after 14 days |
Male beagle hounds | 3 dogs | P.O. | 10 mg/kg (free base) for 7 or 14 days | 30% increase in ACE after 7 days & 48% after 14 days | |
| 3 dogs | P.O. | 30 mg/kg/day for 3 days | 1.5-fold increase in ACE | ||
In vivo ACE inhibition in anesthetized and unanesthetized rats and dogs | Male Sprague/ Dawley rats (Blue Spruce) | 6 rats | I.V. P.O. | 3, 10, 30 mcg/kg 0.1, 0.3, 1.0 and 3.0 mg/kg | The ED50 is 14.0 mcg/kg I.V. and 0.29 mg/kg p.o. |
| Mongrel or beagle dogs (male & female) | 6 dogs per dose | I.V. | 30, 130, 430, 1430 mcg/kg | Dose related inhibition of pressor response to angiotensin. | |
ED50: Enalaprilat: 6.4 mcg/kg. Enalapril maleate: | |||||
Effect of enalaprilat on canine hind limb vasodilator response to | Anesthetized dogs male or female | 4 dogs | I.V. | 0.3– 100 mcg/kg | Local inhibition of ACE: (enalaprilat) ED50 = 4.8 (4.4 to 5.2 mcg/kg) |
| Study | Species/Strain | No. of Animals/Group | Route | Dose | Results |
bradykinin and vasoconstrictor response to angiotensins | I.V. |
Table 14 – Effects on Blood Pressure
| Study | Species/Strain | No. of Animals/Group | Route | Dose | Results |
Antihypertensive activity in sodium-deficient rats | Male Sprague/ Dawley rats | 6 rats/group and at least 8 treatment groups | P.O. | Enalapril 1 to 10 mg/kg | Enalapril produced a dose-dependent decrease in systolic BP for 3 or more hours |
| Effect on renal hypertensive rats (Grollman technique) | Male Sprague/ Dawley rats | Most groups = 6 to 8 rats/treatment group | P.O. | Enalapril 3.0 mg/kg | Enalapril produced a mean decrease in systolic pressure of ≈20 mmHg and a slight tachycardia |
| Relationship between angiotensin 1 blockade and blood pressure lowering in spontaneous hypertensive rats, renal hypertensive rats, and renal hypertensive dogs and normotensive sodium depleted dogs | Sprague/ Dawley rats normotensive dogs (mongrel) | At least 4 to 5 rats/group and at least 3 dogs per group | P.O. | Enalapril 0.1 to 3 mg/kg | Time course of blood pressure decrease did not coincide with time course for maximal inhibition of angiotensin 1 pressor response |
Table 15 – Other Effects
| Study | Species/Strain | No. of Animals/Group | Route | Dose | Results |
| Effects in acute renal failure in dogs | Mongrel dogs | 4/group | P.O. | 1.0 mg/kg b.i.d. for 3 days | No further deterioration of acute renal failure occurred |
Whole body autoradiography | Golden hamsters | Min. 16 | P.O. | 5 mg/kg | No radioactivity was found in the spinal cord or brain of either male or female hamsters |
General Toxicology: Acute Toxicity
Table 16 – LD50 Values:
| Route | Species | Sex | MSDRLa | NMB/RLb |
| Oral | Mouse | Male Female | 2 g/kg 2 g/kg | 3.5 g/kg 3.5 g/kg |
| Rat | Male Female | 2 g/kg 2 g/kg | 3.5 g/kg 3.0 g/kg | |
| Intravenous | Mouse | Male Female | - 750 mg/kg | 900 mg/kg 900 mg/kg |
| Rat | Male Female | - - | 950 mg/kg 850 mg/kg | |
| Subcutaneous | Mouse | Male Female | - - | 1150 mg/kg 1500 mg/kg |
| Rat | Male Female | - - | 1750 mg/kg 1400 mg/kg |
a Merck Sharp and Dohme Research Laboratories, West Point, PA, USA
b Nippon Merck-Banyu Co., Menuma, Japan
Signs of toxicity: ptosis, decreased activity, bradypnea, loss of righting, ataxia, dyspnea, and clonic convulsions.
Table 17 – Sub-Acute and Chronic Toxicity
| Species | Duration | No. of Animals/Group | Route | Dose mg/kg/day | Effects |
| Rat | 1-Month | 10 M + 10 F | Oral | 0, 10, 30, 90 | At all doses: Slight decrease in body weight gain. At 30 & 90 mg/kg/day: Dose-related increase in BUN in males. |
| Rat | 3- Months | 15 M + 15 F | Oral | 0, 10, 30, 90 | At all doses: Slight decrease in body weight gain and in serum sodium, slight increase in serum potassium. Small increase in kidney weight and decrease in heart weight. At 30 & 90 mg/kg/day: Dose-related increase in BUN. |
| Rat | 1-Year | 25 M + 25 F | Oral | 0, 10, 30, 90 | 6-month interim kill: Males given 90 mg/kg/day had a significantly (P≤0.05) greater kidney weight than controls. |
| Species | Duration | No. of Animals/Group | Route | Dose mg/kg/day | Effects |
1 year: Dose-related decrease in weight gain (7 to 19%) Dose-related increase in serum urea nitrogen in males given 30 and 90 mg/kg/day (values up to 52.9 and 89.2 mg/100 mL respectively). Three high dose females showed elevated serum urea nitrogen levels. Serum potassium values were increased (0.1 to 0.8 mEq/L) in male rats on the high dose. Males given 90 mg/kg/day had a significantly (P≤0.05) greater kidney weight than controls. | |||||
| Rat | 1-Month | 20 M + 20 F | Oral | 0, 90 & 90 with physiologic saline for drinking | Un supplemented: Less weight gain (8 to 19%), increase in serum urea nitrogen (up to 62.8 mg%). Supplemented: Body weight gain and serum urea nitrogen levels similar to controls. |
| Rat (sodium depleted) | 3-Weeks | 30 M + 30 F | Oral | 0, 90 | A marked potentiation in toxicity included: death, weight loss, marked increases in serum urea nitrogen, creatinine and potassium, renal tubular degeneration. |
| Species | Duration | No. of Animals/Group | Route | Dose mg/kg/day | Effects |
| Dog Beagle | 1-Month | 3 M + 3 F | Oral | 0, 10, 30, 90 (4 doses only) reduced to 60 (4 doses only) | At 30 mg: One dog showed increase in BUN and renal tubular degeneration. At high doses: 6/6: deaths (7–12 days) Increase in serum urea nitrogen, glucose, SGOT, SGPT, and potassium; decrease in serum sodium and chloride; renal tubular degeneration and increased hepatocellular fat. |
Dog Beagle | 3- Months | 3 M + 3 F | Oral | 0, 10, 30, 90 (7 doses only) | At all doses: Slight decrease in serum sodium. At 30 mg: 2/6: deaths Increase in BUN and serum glucose; renal tubular degeneration. At 90 mg: 5/6: deaths Increase in BUN, serum glucose, SGOT, SGPT, alkaline phosphatase and potassium. |
| Decrease in serum chloride; renal tubular degeneration, increased hepatocellular fat; hepatocellular necrosis. |
| Species | Duration | No. of Animals/Group | Route | Dose mg/kg/day | Effects |
Dog Beagle | 1-Year | 5 M + 5 F | Oral | 0, 3, 5, 15 | No drug-induced changes were seen. |
Dog Beagle | 15-Days | 3 M + 3 F | Oral | 0, 60 with and without saline supplementation | Un supplemented treated dogs: 3/6: deaths 4/6: increase in serum urea nitrogen 3/6: decrease in serum chloride increase in SGOT, SGPT and potassium 1/6: increase in alkaline phosphatase 1/6: hepatocellular lesions (in 1st animal which died) 5/6: renal lesions (3 moderate, 2 slight renal tubular necrosis). Saline supplemented treated dogs: 0/6: deaths 3/6: increase in serum urea nitrogen 1/6: very slight renal tubular necrosis and moderate renal tubular cell vacuolation |
| Dog Beagle | 15-Days | 3 M + 3 F | Oral | 0, 90 with and without saline supplementation | Un supplemented treated dogs: 6/6: deaths 6/6: increase in serum urea nitrogen, |
| Species | Duration | No. of Animals/Group | Route | Dose mg/kg/day | Effects |
5/6: increase in SGOT 2/6: increase in serum potassium 5/6: marked renal tubular degeneration 1/6: moderate renal tubular degeneration 6/6: slight to marked thymic atrophy 3/6: ulceration of distal esophagus 2/6: oral mucosal lesions Supplemented treated dogs: 2/6: deaths 6/6: increase in serum urea nitrogen, creatinine 3/6: increase in SGOT and SGPT 0/6: increase in potassium 2/6: moderate renal tubular degeneration 4/6: slight renal tubular degeneration 4/6: slight to moderate thymic atrophy 3/6: liverdegeneration |
Table 18 – Teratology Studies:
| Species | No. of Animals/Group | Dose mg/kg/day | Duration of Dosing | Results |
| Rat (Charles River CD) | 20 F | 0, 10, 30, 90 | Day 15 of gestation through Day 20 of lactation | At all dosage levels:
At 90 mg/kg/day:
|
| Rat (Charles River CD) | 25 F | 0, 10, 100, 200 100 + saline, 200 + saline | Days 6 through Day 17 of gestation | Decreased maternal weight gain at 100 and 200 mg/kg/day in un supplemented rats. No treatment-related effects on reproductive status or teratogenic effects in any of the groups. |
Rat (CLEA Japan Inc- JCL:SD) | 25 F | 0, 12, 120, 1200 1200 + saline | Days 6 through Day 17 of gestation | Un supplemented treated rats:
At 1200 mg/kg/day:
Supplemented treated rats:
|
| Species | No. of Animals/Group | Dose mg/kg/day | Duration of Dosing | Results |
| Rabbit (New Zealand albino) | 18 F | 0, 3, 10, 30 (with saline) | Days 6 through Day 18 of gestation | At 3 and 10 mg/kg/day:
At 30 mg/kg/day:
|
Table 19 – Fertility and Postnatal Evaluation Studies:
| Species | No. of Animals/Grou p | Dose mg/kg/day | Duration of Dosing | Results |
Rat (Charles River CD) | 15 M + 30 F | 0, 10, 30, 90 | Males 70 days prior to mating to termination of females. Females 15 days prior to mating and throughout gestation. | No effects on reproductive status were observed at any dose. Males at 30 & 90 mg/kg/day:
|
| Species | No. of Animals/Grou p | Dose mg/kg/day | Duration of Dosing | Results |
Females at 30 & 90 mg/kg/day:
Pups: Reduced body weights in F1 pups at 90 mg/kg/day on Day 1 postpartum and secondarily a delay in postnatal development. Increased incidence of deaths of F1 pups at 30 and 90 mg/kg/day during lactation. |
Mutagenicity:
Enalapril was not mutagenic in the Ames microbial mutagen test with or without metabolic activation, in the Rec-Assay, sister chromatid exchange with cultured chinese hamster cells, (up to 20 mg/mL) and the micro-nucleus test with mice.
In vitro chromosomal aberration test = enalapril was clastogenic at 10 and 20 mg/mL but not at 5 mg/mL.
Carcinogenicity:
There was no evidence of a carcinogenic effect when enalapril was administered for 106 weeks to rats (Charles River CD-1) at doses up to 90 mg/kg/day (150 times the maximum daily human dose).
Enalapril has also been administered for 94 weeks to male and female mice (Charles River CD•1) at doses up to 90 and 180 mg/kg/day, respectively (150 and 300 times the maximum daily dose for humans), and no evidence of carcinogenicity was noted.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Vasotec® (enalapril maleate), Tablets, 5 mg, 10 mg and 20 mg, submission control number 247519, Product Monograph, Organon Canada Inc. Last revised: July 21, 2021.