


Product Monograph - Jamp Frovatriptan
RECENT MAJOR LABEL CHANGES
| Section | Date |
|---|---|
| None | N/A |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed. RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
- 1.1 Pediatrics ................................................................................................................ 4
- 1.2 Geriatrics ................................................................................................................ 4
- 2 CONTRAINDICATIONS .................................................................................................. 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
- 4.1 Dosing Considerations ............................................................................................ 5
- 4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
- 4.4 Administration ........................................................................................................ 6
- 5 OVERDOSAGE .............................................................................................................. 6
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 7
7 WARNINGS AND PRECAUTIONS ................................................................................... 7
- 7.1 Special Populations ............................................................................................... 12
- 7.1.1 Pregnant Women ............................................................................................ 12
- 7.1.2 Breast-feeding ................................................................................................ 12
- 7.1.3 Pediatrics ........................................................................................................ 12
- 7.1.4 Geriatrics ........................................................................................................ 12
8 ADVERSE REACTIONS ................................................................................................. 12
- 8.1 Adverse Reaction Overview .................................................................................. 12
- 8.2 Clinical Trial Adverse Reactions ............................................................................ 13
- 8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 15
8.5 Post-Market Adverse Reactions ............................................................................ 16
9 DRUG INTERACTIONS ................................................................................................. 16
- 9.1 Serious Drug Interactions ...................................................................................... 16
- 9.2 Drug Interactions Overview .................................................................................. 16
- 9.3 Drug-Behavioral Interactions ................................................................................ 16
- 9.4 Drug-Drug Interactions ......................................................................................... 17
- 9.5 Drug-Food Interactions ......................................................................................... 18
- 9.6 Drug-Herb Interactions ......................................................................................... 18
- 9.7 Drug-Laboratory Test Interactions ........................................................................ 18
10 CLINICAL PHARMACOLOGY ........................................................................................ 18
- 10.1 Mechanism of Action ...................................................................................... 18
- 10.2 Pharmacodynamics ......................................................................................... 19
- 10.3 Pharmacokinetics ............................................................................................ 19
- 11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 20
- 12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 20
PART II: SCIENTIFIC INFORMATION ....................................................................................... 21
- 13 PHARMACEUTICAL INFORMATION ............................................................................. 21
14 CLINICAL TRIALS......................................................................................................... 21
- 14.1 Clinical Trials by Indication .............................................................................. 21
Migraine with or without aura ........................................................................................ 21
- 14.2 Comparative Bioavailability Studies ............................................................... 21
- 15 MICROBIOLOGY ......................................................................................................... 22
- 16 NON-CLINICAL TOXICOLOGY ...................................................................................... 23
- 17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 23
PATIENT MEDICATION INFORMATION .................................................................................. 25
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JAMP Frovatriptan (frovatriptan tablets) is indicated for the acute treatment of migraine attacks with or without aura in adults.
JAMP Frovatriptan is not intended for the prophylactic therapy of migraine or for the use in the management of hemiplegic, ophthalmoplegic or basilar migraine (see 2 CONTRAINDICATIONS).
The safety and effectiveness of frovatriptan tablets have not been established for cluster headache, which is present in an older, predominantly male, population.
1.1 Pediatrics
Pediatrics (< 18 years old): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 8.5 Post-Market Adverse Reactions).
1.2 Geriatrics
Geriatrics (≥ 65 years old): Because migraine occurs infrequently in the elderly, clinical experience with frovatriptan tablets is limited in such patients. Limited evidence from clinical studies and experience suggests that the use of frovatriptan tablets in the geriatric population may be associated with slight differences in safety or effectiveness (see 4.2 Recommended Dose and Dosage Adjustment; 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
2 CONTRAINDICATIONS
JAMP Frovatriptan is contraindicated:
- In patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
In patients with history, symptoms, or signs of ischemic cardiac syndromes such as angina pectoris of any type (e.g., stable angina of effort and vasospasm forms of angina such as
the Prinzmetal’s variant, all forms of myocardial infarction, and silent myocardial ischemia);
- In patients with history, symptoms, or signs of valvular heart disease or cardiac arrhythmias (especially tachycardia);
- In patients with history, symptoms, or signs of cerebrovascular syndromes (e.g., stroke and transient ischemic attack (TIA));
In patients with history, symptoms, or signs of peripheral vascular syndromes (e.g.,
ischemic bowel disease and Raynaud’s syndrome);
- In patients with other significant underlying cardiovascular diseases (e.g., atherosclerotic disease, congenital heart disease);
- In patients with severe or uncontrolled hypertension as JAMP Frovatriptan may increase blood pressure;
- In patients with hemiplegic, ophthalmoplegic or basilar migraine;
- Within 24 hours of treatment with another 5-HT1 agonist, or an ergot-type medication like dihydroergotamine;
- In patients with severe hepatic impairment (Child-Pugh grade C) as there are no data available.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- JAMP Frovatriptan is recommended only for the acute treatment of migraine attacks, and should not be used prophylactically.
- JAMP Frovatriptan should be administered with caution to patients with diseases that may alter the absorption, metabolism, or excretion of drugs (see 10.3 Pharmacokinetics).
- The safety of treating an average of more than 4 migraine attacks in a 30-day period has not been established.
- In patients with mild to moderate controlled hypertension, patients should be treated cautiously (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Effects on Blood Pressure).
- 4.2 Recommended Dose and Dosage Adjustment General
The recommended dosage of JAMP Frovatriptan is a single tablet for migraine headache with or without aura.
The total daily dose of JAMP Frovatriptan should not exceed 2 tablets (2 x 2.5 mg per day).
If the headache recurs after initial relief, a second dose may be taken between 4 and 24 hours after the first dose.
For a given attack, if a patient has no response to the first dose of JAMP Frovatriptan, the diagnosis of migraine should be reconsidered before administration of a second dose. There is no evidence that a second dose of frovatriptan is effective in patients who do not respond to a first dose of the drug for the same headache (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Cerebrovascular Events and Fatalities with 5-HT1 Agonists).
Pediatrics (< 18 years old)
Health Canada has not authorized an indication for pediatric use.
Geriatrics (≥ 65 years old)
Although some changes in the pharmacokinetics of frovatriptan tablets have been observed in geriatric patients during clinical trials, no dosage adjustment is required for this population (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics).
Hepatic impairment
No dosage adjustment is required in patients with mild to moderate hepatic impairment (see 10.3 Pharmacokinetics).
JAMP Frovatriptan is contraindicated in patients with severe hepatic impairment (Child-Pugh grade C) due to the absence of clinical data (see 2 CONTRAINDICATIONS).
Renal impairment
No dosage adjustment is required in patients with renal impairment (see 10.3 Pharmacokinetics).
4.4 Administration
It is recommended that JAMP Frovatriptan be taken orally with fluids.
Patients should be advised to read the Patient Medication Information before taking JAMP Frovatriptan.
5 OVERDOSAGE
There is no direct experience of any patient taking an overdose of frovatriptan tablets. The maximum single dose of frovatriptan given to male and female patients with migraine was 40 mg (16 times the clinical dose) and the maximum single dose given to healthy male subjects was 100 mg (40 times the clinical dose) without significant adverse events.
As with other 5-HT1 receptor agonists, there is no specific antidote for frovatriptan. The elimination half-life of frovatriptan is 26 hours. Therefore, if an overdose occurs, the patient should be monitored closely for at least 48 hours and be given any necessary symptomatic treatment.
The effects of hemo- or peritoneal dialysis on blood concentrations of frovatriptan are unknown.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet 2.5 mg frovatriptan (as frovatriptan succinate monohydrate) | lactose anhydrous, magnesium stearate, microcrystalline cellulose, Silicon dioxide, sodium starch glycollate, Opadry II white. Opadry II white includes Macrogol 3350, titanium dioxide, Hypromellose, Lactose monohydrate and triacetin. |
JAMP Frovatriptan tablets are available as round, white to off white, film-coated tablets containing 2.5 mg of frovatriptan.
JAMP Frovatriptan tablets are available in blister cards of 6 tablets, 1 blister card per carton.
7 WARNINGS AND PRECAUTIONS
General
JAMP Frovatriptan should only be used where a clear diagnosis of migraine has been established.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY.
Cardiovascular
Discomfort in the chest, neck, throat and jaw (including pain, tightness, pressure and heaviness) have been reported after treatment with frovatriptan tablets. Because 5-HT1 agonists may cause coronary vasospasm, patients who experience signs or symptoms suggestive of angina following dosing should be evaluated for the presence of CAD or a predisposition to variant angina before receiving additional doses, and should be monitored electrocardiographically if dosing is resumed and similar symptoms recur. Similarly, patients who experience other symptoms or signs suggestive of decreased arterial flow, such as ischemic bowel syndrome or Raynaud’s syndrome following JAMP Frovatriptan administration should be evaluated for atherosclerosis or predisposition to vasospasm (see 2 CONTRAINDICATIONS).
Non-Coronary Vasospastic Events: 5-HT1 agonists may cause vasospastic reactions other than coronary artery vasospasm. Extensive post-market experience has shown the use of another 5-HT1 agonist to be associated with rare occurrences of peripheral vascular ischemia and colonic ischemia with abdominal pain and bloody diarrhea.
Cardiac Events and Fatalities with 5-HT1 Agonists: Serious adverse cardiac events including acute myocardial infarction, life-threatening disturbances of cardiac rhythm and death have been reported within a few hours following the administration of 5-HT1 agonists. Considering the extent of use of 5-HT1 agonists in patients with migraine, the incidence of these events is extremely low. JAMP Frovatriptan should be discontinued if any cardiac disturbances occur.
Risk of Myocardial Ischemia and/or Infarction and other Adverse Cardiac Events: Frovatriptan tablets has been associated with transient chest and/or neck pain and tightness which may resemble angina pectoris. Following the use of other 5-HT1 agonists, in rare cases, these symptoms have been identified as being the likely result of coronary vasospasm or myocardial ischemia. Rare cases of serious coronary events or arrhythmia have occurred following use of other 5-HT1 agonists, and may therefore also occur with JAMP Frovatriptan.
Because of the potential of this class of compounds (5-HT1B/1D agonists) to cause coronary vasospasm, JAMP Frovatriptan is contraindicated in patients with documented ischemic or vasospastic coronary artery disease (see 2 CONTRAINDICATIONS). It is strongly recommended that 5-HT1 agonists (including JAMP Frovatriptan) not be given to patients in whom unrecognized coronary artery disease (CAD) is predicted by the presence of risk factors such as: hypertension, hypercholesterolemia, smoker, obesity, diabetes, strong family history of CAD, female with surgical or physiological menopause, or male over 40 years of age, unless a cardiovascular examination provides satisfactory clinical evidence that the patient is reasonably free of coronary artery and ischemic myocardial disease or other significant underlying cardiovascular disease. The sensitivity of cardiac diagnostic procedures to detect cardiovascular diseases or predisposition to coronary artery vasospasm is modest at best. If, during the cardiovascular evaluation, the patient’s medical history, electrocardiogram (ECG) or other evaluations reveal findings indicative of, or consistent with, coronary artery vasospasm, or myocardial ischemia, JAMP Frovatriptan should not be administered (see 2 CONTRAINDICATIONS).
These evaluations, however, may not identify every patient who has cardiac disease, and in very rare cases, serious cardiac events, such as myocardial infarction or coronary ischemia have occurred in patients without evidence of underlying cardiovascular disease.
For patients with risk factors predictive of CAD, who are determined to have a satisfactory cardiovascular evaluation, it is strongly recommended that administration of the first dose of JAMP Frovatriptan take place in a clinical setting, such as the physician’s office or a similarly staffed medical facility, unless the patient has previously received frovatriptan. Because cardiac ischemia can occur in the absence of clinical symptoms, consideration should be given to obtaining an ECG during the interval immediately following the first use of JAMP Frovatriptan in a patient with risk factors. However, an absence of drug-induced cardiovascular effects on the occasion of the initial dose does not preclude the possibility of such effects occurring with subsequent administrations.
If symptoms consistent with angina occur after the use of JAMP Frovatriptan, ECG evaluation should be carried out to look for ischemic changes.
It is recommended that patients who are intermittent long-term users of JAMP Frovatriptan and who have or acquire risk factors predictive of CAD as described above undergo periodic interval cardiovascular evaluation as they continue to use JAMP Frovatriptan.
The systematic approach described above is intended to reduce the likelihood that patients with unrecognized cardiovascular disease are inadvertently exposed to JAMP Frovatriptan.
Effects on Blood Pressure: Significant elevations in systemic blood pressure, including hypertensive crisis, have been reported on rare occasions in patients with and without a history of hypertension treated with other 5-HT1 agonists. In young healthy subjects, there were statistically significant increases in systolic and diastolic blood pressure only at single doses of 80 mg frovatriptan (32 times the clinical dose) and above. These increases were transient, resolved spontaneously and were not clinically significant. JAMP Frovatriptan is contraindicated in patients with severe or uncontrolled hypertension (see 2 CONTRAINDICATIONS). In patients with controlled hypertension, JAMP Frovatriptan should be administered with caution, as transient increases in blood pressure and peripheral vascular resistance have been observed in a small portion of patients.
Cardiovascular Pharmacodynamics of Another 5-HT1 Agonist: In subjects (n=10) with suspected coronary artery disease undergoing angiography, a 5-HT1 agonist at a subcutaneous dose of 1.5 mg produced an 8% increase in aortic blood pressure, an 18% increase in pulmonary artery blood pressure, and an 8% increase in systemic vascular resistance. In addition, mild chest pain or tightness was reported by four subjects. Clinically significant increases in blood pressure were experienced by three of the subjects (two of whom also had chest pain/discomfort). Diagnostic angiogram results revealed that 9 subjects had normal coronary arteries and 1 had insignificant coronary artery disease.
In an additional study with the same drug, migraine patients (n=35) free of cardiovascular disease were subjected to assessments of myocardial perfusion by positron emission tomography while receiving a subcutaneous 1.5 mg dose in the absence of a migraine attack. Reduced coronary vasodilatory reserve (~10%), increased coronary resistance (~20%), and decreased hyperaemic myocardial blood flow (~10%) were noted. The relevance of these findings to the use of the recommended oral dose of this 5-HT1 agonist is not known.
Similar studies have not been done with frovatriptan tablets. However, owing to the common pharmacodynamic actions of 5-HT1 agonists, the possibility of cardiovascular effects of the nature described above should be considered for any agent of this pharmacological class.
Dependence/Tolerance
Although the abuse potential of frovatriptan tablets has not been specifically assessed in clinical trials, no abuse of, tolerance to, withdrawal from, or drug-seeking behavior was observed in patients who received frovatriptan tablets. The 5-HT1 agonists, as a class, have not been associated with drug abuse.
Driving and Operating Machinery
Patients should be advised not to drive or operate a vehicle or potentially dangerous machinery until the effect of frovatriptan is known. JAMP Frovatriptan may cause dizziness. Exercise caution when driving or operating a vehicle or potentially dangerous machinery (see 8.2 Clinical Trial Adverse Reactions).
Hepatic/Biliary/Pancreatic
Since there is no clinical or pharmacokinetic experience with frovatriptan tablets in patients with severe hepatic impairment, it is contraindicated in this population (see 2 CONTRAINDICATIONS). JAMP Frovatriptan can be used in patients with mild to moderate hepatic impairment (see 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment and 10.3 Pharmacokinetics, Special Population and Conditions, Hepatic Insufficiency).
Immune
Hypersensitivity: Rare hypersensitivity (anaphylaxis/anaphylactoid) reactions have occurred in patients receiving 5-HT1 agonists, including frovatriptan tablets. Such reactions can be life threatening or fatal. In general, hypersensitivity reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens. Owing to the possibility of cross-reactive hypersensitivity reactions, JAMP Frovatriptan should not be used in patients having a history of hypersensitivity to chemically-related 5-HT1 receptor agonists (see 2 CONTRAINDICATIONS). In case of serious allergic/hypersensitivity reactions, frovatriptan treatment should be discontinued immediately and should never be administered again.
Monitoring and Laboratory Tests
No specific laboratory tests are recommended for monitoring patients prior to and/or after the treatment with JAMP Frovatriptan.
Neurologic
Cerebrovascular Events and Fatalities with 5-HT1 Agonists: Cerebral hemorrhage, subarachnoid hemorrhage, stroke and other cerebrovascular events have been reported in patients treated with other 5-HT1 agonists, and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the agonist having been administered in the belief that the symptoms experienced were a consequence of migraine, when they were not.
Before treating migraine headaches with JAMP Frovatriptan in patients not previously diagnosed as migraineurs, and in migraineurs who present with atypical symptoms, care should be taken to exclude other potentially serious neurological conditions. If a patient does not respond to the first dose, the opportunity should be taken to review the diagnosis before a second dose is given. It should be noted, however, that patients who suffer from migraine may have an increased risk of certain cerebrovascular events such as stroke, hemorrhage or transient ischemic attack.
Medication Overuse Headache: Overuse of acute migraine treatments has been associated with the exacerbation of headache (medication overuse headache, MOH) in susceptible patients. Withdrawal of the treatment may be necessary.
Neurological Conditions: Care should be taken to exclude other potentially serious neurologic conditions before treating headache in patients not previously diagnosed with migraine or who experience a headache that is atypical for them. There have been rare reports where patients received 5-HT1 agonists for severe headache that were subsequently shown to have been secondary to an evolving neurological lesion. For newly diagnosed patients or patients presenting with atypical symptoms, the diagnosis of migraine should be reconsidered if no response is seen after the first dose of JAMP Frovatriptan.
Seizures: Caution should be observed if JAMP Frovatriptan is to be used in patients with a history of epilepsy or structural brain lesions which lower the convulsion threshold.
Serotonin Toxicity / Serotonin Syndrome: Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported with triptans, including JAMP Frovatriptan, particularly during combined use with other serotonergic drugs ( see 9.2 Drug Interactions Overview; 9.4 Drug-Drug Interactions).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g., tachycardia, flushing) and altered mental state (e.g., anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with JAMP Frovatriptan and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Ophthalmologic
Binding to Melanin-Containing Tissues: Because there could be accumulation of frovatriptan and/or its metabolites in melanin rich tissues over time, this raises the possibility that frovatriptan could cause toxicity in these tissues after extended use. However, no effects on the retina related to treatment with frovatriptan were noted in toxicity studies. Although no systemic monitoring of ophthalmologic function was undertaken in clinical trials, and no specific recommendations for ophthalmological monitoring are made, prescribers should be aware of the possibility of long-term ophthalmologic effects (see 16 NON-CLINICAL TOXICOLOGY, Special Toxicology, Binding to Melanin Containing Tissues).
Reproductive Health: Female and Male Potential
- Fertility
Non-clinical studies on male and female rats revealed an increase in the number of females that mated on the first day of pairing compared to control animals, a prolongation of the estrous cycle and a decrease in the mean number of corpora lutea in females, thus resulting in a lower number of live fetuses per litter. This suggested a partial impairment of ovulation.
There were no other fertility-related effects (see 16 NON-CLINICAL TOXICOLOGY).
- Teratogenic Risk
Non-clinical studies on pregnant rats, at doses greater than MRHD, reported dose-related increases in incidences of both litters and total numbers of fetuses with a syndrome of related effects on a specific organ in the developing embryo in all treated groups, which is consistent with a slight delay in fetal maturation. Although not statistically significant compared to control, slightly lower fetal weights and an increased incidence of early embryonic deaths in treated rats were observed. There was no evidence of this latter effect at the lowest dose level studied. When pregnant rabbits were dosed throughout organogenesis, no effects on fetal development were observed (see 16 NON-CLINICAL TOXICOLOGY).
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled trials in pregnant women. In animal studies, frovatriptan produced developmental toxicity (embryofetal lethality, fetal abnormalities, and decreased embryofetal growth) when administered to pregnant rats at doses greater than those used clinically (see 16 NON-CLINICAL TOXICOLOGY).
JAMP Frovatriptan should be used during pregnancy only if the benefits to the mother and her fetus outweigh the risks.
7.1.2 Breast-feeding
It is not known whether frovatriptan is excreted in human milk. Frovatriptan and/or its metabolites are excreted in the milk of lactating rats with the maximum concentration being four-fold higher than that seen in plasma. Therefore, caution should be exercised when considering the administration of JAMP Frovatriptan to a nursing woman.
7.1.3 Pediatrics
Pediatrics (< 18 years old): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 8.5 Post-Market Adverse Reactions).
7.1.4 Geriatrics
Geriatrics (≥ 65 years old): Because migraine occurs infrequently in the elderly, clinical experience with frovatriptan tablets is limited in such patients.
Limited evidence from clinical studies and experience suggests that the use of frovatriptan tablets in the geriatric population is associated with differences in pharmacokinetics (see 10.3 Pharmacokinetics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Serious cardiac events, including some that have been fatal, have occurred following the use of other 5-HT1 agonists. These events are extremely rare and most have been reported in patients with risk factors predictive of CAD. Events reported have included coronary artery vasospasm, transient myocardial ischemia, myocardial infarction, ventricular tachycardia and ventricular fibrillation (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Among more than 3000 patients with migraine who participated in premarketing clinical trials of frovatriptan tablets, no deaths or serious cardiac events related to the use of frovatriptan tablets were reported.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Among 1554 patients treated with frovatriptan tablets in four placebo-controlled studies (Trials 1, 3, 4 and 5 in Table 2), only 1% (16) of the patients withdrew because of the treatment-emergent adverse events.
Table 2 lists treatment-emergent adverse events reported within 48 hours of drug administration that occurred with frovatriptan 2.5 mg at an incidence rate of ≥1% and more than 1% more often than placebo, in the first attack in the four placebo-controlled trials.
Frovatriptan tablets is generally well tolerated. The incidence of adverse events in clinical trials did not increase when up to 2 doses were used within 24 hours. The majority of adverse events were mild or moderate and transient. The incidence of adverse events in the four placebo- controlled clinical trials was not affected by gender, age or concomitant medications commonly used by migraine patients. There were insufficient data to assess the impact of race on the incidence of adverse events.
Table 2 – Treatment-Emergent Adverse Events (Incidence ≥1% and 1% Greater Than Placebo)
of Patients in Four Placebo-Controlled Migraine Trials
Frovatriptan 2.5 mg n = 1554 (%) | Frovatriptan 5 mg n=99 (%) | Placebo n = 838 (%) | |||||
|---|---|---|---|---|---|---|---|
| Cardiac disorders | |||||||
| Chest pain | 2 | 3 | 1 | ||||
| Throat tightness | 2 | 1 | 0 | ||||
| Gastrointestinal disorders | |||||||
| Mouth dry | 3 | NR | 1 | ||||
| Dyspepsia | 2 | 3 | 1 | ||||
| General disorders | |||||||
| Fatigue | 5 | 4 | 2 | ||||
| Asthenia | NR | 4 | 1 | ||||
| Hot or cold sensation* | 3 | NR | 2 | ||||
| Rigors | NR | 2 | 1 | ||||
| Dysesthesia | 1 | NR | 0 | ||||
| Musculoskeletal and connective tissue disorders | |||||||
| Skeletal pain | 3 | NR | 2 | ||||
| Nervous system disorders | |||||||
| Dizziness | 8 | NR | 5 | ||||
Frovatriptan 2.5 mg n = 1554 (%) | Frovatriptan 5 mg n=99 (%) | Placebo n = 838 (%) | |||||
|---|---|---|---|---|---|---|---|
| Headache | 4 | NR | 3 | ||||
| Paresthesia | 4 | NR | 2 | ||||
| Hypertonia | NR | 4 | 0 | ||||
| Psychiatric disorders | |||||||
| Euphoria | NR | 2 | 0 | ||||
| Respiratory, thoracic and mediastinal disorders | |||||||
| Rhinitis | NR | 3 | 1 | ||||
| Vascular disorders | |||||||
| Flushing | 4 | NR | 2 | ||||
* The term “sensation” encompasses adverse events described as pain, discomfort, pressure, constriction, numbness and tingling.
NR= No incidence rates of ≥1% and 1% greater than placebo.
Other Frequently Observed Events in Association with Frovatriptan Succinate
In the list that follows, the incidence of other reported adverse events (frequent, minimum 1/100 patients) in the four placebo-controlled trials are presented. The incidence of each adverse event is calculated as the number of patients reporting the event at least once divided by the number of patients who used frovatriptan tablets. All adverse events reported within 48 hours of drug administration in the first attack in the four placebo-controlled trials are included, except those already listed in Table 2, those too general to be informative, those not reasonably associated with the use of the drug and those which occurred at the same or a greater incidence in the placebo group. Events are further classified within system organ classes and enumerated in order of decreasing frequency.
Cardiac disorders: palpitation
Ear and labyrinth disorders: tinnitus
Eye disorders: abnormal vision
General disorders and administration site conditions: pain Gastrointestinal disorders: vomiting, abdominal pain, diarrhea Nervous system disorders: hypoesthesia
Psychiatric disorders: insomnia, anxiety
Respiratory, thoracic and mediastinal disorders: sinusitis, rhinitis
Skin and subcutaneous tissue disorders: sweating increased
Long-Term Safety
In a long-term, open-label study where patients were allowed to treat multiple migraine attacks with frovatriptan tablets for up to 1 year, 5% (26/496) patients discontinued due to treatment-
emergent adverse events.
The adverse events which occurred within 48 hours of drug administration in this long-term open-label safety study were similar to those that occurred in the placebo-controlled trials. The most frequent adverse events were: nausea, dizziness, fatigue, somnolence, headache, dyspepsia, skeletal pain, flushing and paresthesia.
8.3 Less Common Clinical Trial Adverse Reactions
In the list that follows, the incidence of infrequent (between 1/1000 and 1/100 patients) and rare (less than 1/1000 patients) reported adverse events in the four placebo-controlled trials are presented. All adverse events reported within 48 hours of drug administration in the first attack in the four placebo-controlled trials are included, except those already listed in Table 2, those too general to be informative, those not reasonably associated with the use of the drug and those which occurred at the same or a greater incidence in the placebo group. Events are further classified within system organ classes and enumerated in order of decreasing frequency.
Blood and lymphatic system disorders: Infrequent: epistaxis; Rare: purpura Cardiac disorders: Infrequent: tachycardia, abnormal ECG; Rare: bradycardia Ear and labyrinth disorders: Infrequent: ear ache, hyperacusis
Eye disorders: Infrequent: eye pain, conjunctivitis, abnormal lacrimation
Gastrointestinal disorders: Infrequent: dysphagia, flatulence, constipation, anorexia, esophagospasm, increased salivation, taste perversion; Rare: change in bowel habits, cheilitis, eructation, gastroesophageal reflux, hiccup, peptic ulcer, salivary gland pain, stomatitis, toothache
General disorders and administration site conditions: Infrequent: asthenia, rigors, fever, hot flashes, malaise; Rare: feeling of relaxation, leg pain, edema mouth
Metabolism and nutrition disorders: Infrequent: thirst and dehydration; Rare: hypocalcemia, hypoglycemia
Musculoskeletal and connective tissue disorders: Infrequent: myalgia, back pain, arthralgia, arthrosis, leg cramps, muscle weakness
Nervous system disorders: Infrequent: tremor, hyperesthesia, migraine aggravated, involuntary muscle contractions, vertigo, ataxia, abnormal gait, speech disorder; Rare: hypertonia, hypotonia, abnormal reflexes, tongue paralysis, syncope
Psychiatric disorders: Infrequent: confusion, nervousness, agitation, euphoria, impaired concentration, depression, emotional lability, amnesia, thinking abnormal, depersonalization; Rare: depression aggravated, abnormal dreaming, personality disorder
Renal and urinary disorders: Infrequent: micturition frequency, polyuria; Rare: nocturia, renal pain, abnormal urine
Respiratory, thoracic and mediastinal disorders: Infrequent: pharyngitis, dyspnea, hyperventilation, laryngitis
Skin and subcutaneous tissue disorders: Infrequent: pruritus, bullous eruption
8.5 Post-Market Adverse Reactions
Rare reports of serious cardiovascular events have been reported in association with the use of frovatriptan tablets, this includes chest tightness and tachycardia. There have also been rare reports of serious allergic type reactions, including anaphylactic reactions. The uncontrolled nature of post-marketing surveillance, however, makes it impossible to definitely determine the proportion of the reported cases that were actually caused by frovatriptan or to reliably assess causation in individual cases.
Pediatrics (< 18 years of age): Post-marketing experience with other triptans includes a limited number of reports that describe pediatric patients who have experienced clinically serious adverse events that are similar in nature to those reported rarely in adults.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
Frovatriptan is not an inhibitor of human monoamine oxidase (MAO) enzymes or cytochrome P450 (isozymes 1A2, 2C9, 2C19, 2D6, 2E1, 3A4) in vitro at concentrations up to 250 to 500-fold higher than the highest blood concentrations observed in man at a dose of 2.5 mg. No induction of drug metabolizing enzymes was observed following multiple dosing of frovatriptan to rats or on addition to human hepatocytes in vitro. Although no clinical studies have been performed, it is unlikely that frovatriptan will affect the metabolism of co- administered drugs metabolized by these mechanisms.
The pharmacokinetic profile of frovatriptan was unaffected when a single oral dose of frovatriptan 2.5 mg was administered to healthy female subjects receiving the MAO-A inhibitor, moclobemide, at an oral dose of 150 mg bid for 8 days.
9.3 Drug-Behavioral Interactions
Interactions with individual behaviour risks such as alcohol consumption, sexual activity and smoking have not been established.
Serious Drug Interactions
The following drugs or class of drugs may interact with JAMP Frovatriptan and cause serious and life- threatening adverse reactions if administered within 24 hours of each other (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions):
- Ergot-containing drugs (e.g., dihydroergotamine)
- Other 5-HT1 agonists
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 – Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Ergot-containing drugs (e.g., dihydroergotamine) | CT, T | The AUC and Cmax of frovatriptan (2 x 2.5 mg dose) were reduced by approximately 25% when co-administered with ergotamine tartrate. Possibility of additive vasospastic effects. | Due to the theoretical risk of a pharmacodynamic interaction, use of ergot- type medications and JAMP Frovatriptan within 24 hours of each other is contraindicated (see 2 CONTRAINDICATIONS). |
| Oral contraceptives | CT | Retrospective analysis of pharmacokinetic data from females across trials indicated that the mean Cmax and AUC of frovatriptan are 30% higher in those subjects taking oral contraceptives compared to those not taking oral contraceptives. The effect of frovatriptan tablets on the pharmacokinetics of oral contraceptives has not been studied. | Caution is warranted when JAMP Frovatriptan is administered in patients taking oral contraceptives. |
| Propranolol | CT | Propranolol increased the AUC of frovatriptan 2.5 mg in males by 60% and in females by 29%. The Cmax of frovatriptan was increased by 23% in males and by 16% in females in the presence of propranolol. The tmax as well as half-life of | Caution is warranted when JAMP Frovatriptan is administered in patient taking propranolol. |
| frovatriptan, though slightly longer in the females, were not affected by concomitant administration of propranolol. | |||
|---|---|---|---|
Serotonergic Drugs (SSRIs, SNRIs, other triptans) | C | Cases of life-threatening serotonin syndrome have been reported with combined use. | See 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin Syndrome / Serotonin Toxicity. |
| Other 5-HT1 agonists | T | The administration of frovatriptan succinate with other 5-HT1 agonists has not been evaluated in migraine patients. | Because their vasospastic effects may be additive, co-administration of JAMP Frovatriptan and other 5-HT1 agonists within 24 hours of each other is contraindicated (see 2 CONTRAINDICATIONS). |
Legend: AUC = Area under the curve; Cmax = maximum concentration; C = Case Study; CT = Clinical trial; T = Theoretical; Tmax = time when maximum concentration is reached
9.5 Drug-Food Interactions
No significant interaction with food is expected (see 10.3 Pharmacokinetics, Absorption).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Frovatriptan tablets is not known to interfere with commonly employed clinical laboratory tests.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Frovatriptan tablets is a 5-HT receptor agonist that binds with high affinity for 5-HT1B and 5-HT1D receptors. Frovatriptan has no significant effects on GABAA mediated channel activity and has no significant affinity for benzodiazepine binding sites.
Frovatriptan is believed to act on extracerebral, intracranial arteries and to inhibit excessive dilation of these vessels in migraine.
- 10.2 Pharmacodynamics Non-Clinical Studies
Non-clinical pharmacology studies of frovatriptan investigated its primary activity as well as general activity (i.e., safety). The primary vasoconstrictor activity was examined in several in vitro studies with human and other mammalian arteries and in the cat and dog in vivo. The safety pharmacology was examined using in vivo models that included the mouse, cat, and dog.
The primary activity studies show that frovatriptan is a potent vasoconstrictor in isolated cerebral arteries, as well as a potent, but low efficacy, vasoconstrictor in isolated coronary arteries. By virtue of its apparent partial agonist activity in human isolated coronary arteries, frovatriptan demonstrates a functional selectivity for cerebral arteries over coronary arteries. In cell-based assays in vitro, frovatriptan is a potent, full agonist at human recombinant 5-HT1B and 5-HT1D receptors and a moderately potent, partial agonist at 5-HT1F receptors. Unlike sumatriptan, frovatriptan is a moderately potent, full agonist at 5-HT7 receptors. The desmethyl metabolite of frovatriptan (SB 205555-A) exhibits affinity for 5-HT1A, 5-HT1B, 5-HT1D, 5-HT1E, 5-HT1F and 5-HT7 binding sites with pKi values approximately 0.5 units lower than those for frovatriptan, whereas the N-acetyl desmethyl metabolite (SB 210199) exhibits no significant affinity at these sites.
In terms of general pharmacological effects, frovatriptan is a consistent and potent constrictor of the carotid vascular bed in the cat and dog in vivo. It is devoid of pronounced or dose- related gross behavioral effects in the mouse. Frovatriptan attenuates carrageenan-induced thermal hyperalgesia but does not possess anti-nociceptive activity in the mouse.
10.3 Pharmacokinetics
The pharmacokinetics of frovatriptan are similar in migraine patients and healthy subjects.
Absorption
Mean maximum blood concentrations (Cmax) in patients are achieved approximately 2 - 4 hours after administration of a single oral dose of frovatriptan 2.5 mg. The absolute bioavailability of an oral dose of frovatriptan 2.5 mg in healthy subjects is about 20% in males and 30% in females. Food has no significant effect on the bioavailability of frovatriptan, but delays tmax by one hour.
Distribution
Binding of frovatriptan to serum proteins is low (approximately 15%). Reversible binding to blood cells at equilibrium is approximately 60%, resulting in a blood:plasma ratio of about 2:1 in both males and females. The mean steady state volume of distribution of frovatriptan following intravenous administration of 0.8 mg is 4.2 L/kg in males and 3.0 L/kg in females.
Metabolism
In vitro, cytochrome P450 1A2 appears to be the principal enzyme involved in the metabolism of frovatriptan. Following administration of a single dose of radiolabeled frovatriptan 2.5 mg to healthy male and female subjects, 32% of the dose was recovered in urine and 62% in feces. Radiolabeled compounds excreted in the urine were unchanged frovatriptan, hydroxylated frovatriptan, N-acetyl desmethyl frovatriptan, hydroxylated N–acetyl desmethyl frovatriptan and desmethyl frovatriptan, together with several other minor metabolites. Desmethyl frovatriptan has lower affinity for 5-HT1B/1D receptors compared to the parent compound. The N-acetyl desmethyl metabolite has no significant affinity for 5-HT receptors. The activity of the other metabolites is unknown.
Elimination
After an intravenous dose, mean clearance of frovatriptan was 220 and 130 mL/min in males and females, respectively. Renal clearance accounted for about 40% (82 mL/min) and 45% (60 mL/min) of total clearance in males and females, respectively. The mean terminal elimination half-life of frovatriptan in both males and females is approximately 26 hours.
Special Populations and Conditions
- Pediatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
- Geriatrics: Mean AUC of frovatriptan was 1.5- to 2-fold higher in healthy elderly subjects (age 65 - 77 years) compared to those in healthy younger subjects (age 21 - 37 years). There was no difference in tmax or t1/2 between the two populations.
- Sex: There was no difference in the mean terminal elimination half-life of frovatriptan in males and females. Bioavailability was higher, and systemic exposure to frovatriptan was approximately 2-fold greater, in females than males, irrespective of age.
- Race: The effect of race on the pharmacokinetics of frovatriptan has not been examined.
- Hepatic Insufficiency: There is no clinical or pharmacokinetic experience with frovatriptan tablets in patients with severe hepatic impairment (see 2 CONTRAINDICATIONS). The AUC in subjects with mild (Child-Pugh 5 - 6) to moderate (Child-Pugh 7 - 9) hepatic impairment is about twice as high as the AUC in young, healthy subjects, but within the range found among normal elderly subjects.
- Renal Insufficiency: Since less than 10% of frovatriptan tablets is excreted in urine after an oral dose, it is unlikely that the exposure to frovatriptan will be affected by renal impairment. The pharmacokinetics of frovatriptan following a single oral dose of 2.5 mg was not different in patients with renal impairment (5 males and 6 females, creatinine clearance 16 - 73 mL/min) and in subjects with normal renal function.
11 STORAGE, STABILITY AND DISPOSAL
Store between 15-30°C.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not Applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Frovatriptan as frovatriptan succinate
Chemical name: (+) 3-methylamino-6-carboxamido-1,2,3,4-tetrahydrocarbazole monosuccinate monohydrate
Molecular formula and molecular mass: C14H17N3O.C4H6O4.H2O, 379.4 g/mol Structural formula:
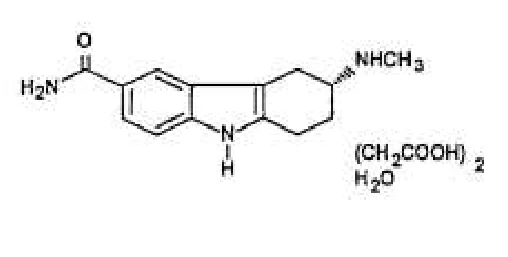
Physicochemical properties:
Solubility: frovatriptan monosuccinate monohydrate is water-soluble, i.e., its aqueous solubility is more than 100 mg/mL at pH 3 or above
Melting point: 165°- 172°C pKa: 10.38
Hygroscopy: not hygroscopic
Polymorphism: no evidence of polymorphism has been detected
14 CLINICAL TRIALS
- 14.1 Clinical Trials by Indication Migraine with or without aura
Summary of patient demographics: The efficacy of frovatriptan tablets in the acute treatment of migraine headaches was demonstrated in five randomized, double-blind, placebo-controlled, outpatient trials. Two of these were dose-finding studies in which patients were randomized to receive doses of frovatriptan ranging from 0.5-40 mg. The three studies evaluating only one dose studied 2.5 mg. In these controlled short-term studies combined, patients were predominately female (88%) and Caucasian (94%) with a mean age of 42 years (range 18-69). Patients were instructed to treat a moderate or severe headache. Headache response, defined as a reduction in headache severity from moderate or severe pain to mild or no pain, was assessed for 24 hours after dosing. The associated symptoms nausea, vomiting, photophobia and phonophobia were also assessed. Maintenance of response was assessed for up to 24 hours post-dose. In two of the trials a second dose of frovatriptan tablets was provided after the initial treatment, to treat recurrence of headache within 24 hours. Other medication, excluding other 5-HT1 agonists and ergotamine-containing compounds was permitted from 2 hours after the first dose of frovatriptan tablets. The frequency and time to use of additional medications were also recorded.
Study Results: Comparisons of drug performance based upon results obtained in different clinical trials are never reliable. Because trials are conducted at different times, with different samples of patients, by different investigators, employing different criteria and/or different interpretations of the same criteria, under different conditions (dose, dosing regimen, e tc.), quantitative estimates of treatment response and the timing of the response may be expected to vary considerably from study to study.
In all five placebo-controlled trials, the percentage of patients achieving a headache response 2 and 4 hours after treatment was significantly greater for those taking frovatriptan tablets compared with those taking placebo (Table 4).
Lower doses of frovatriptan (1 mg or 0.5 mg) were not effective at 2 hours. Higher doses (5 mg to 40 mg) of frovatriptan showed no added benefit over 2.5 mg but did cause a greater incidence of adverse events.
Table 4 – Headache Response (Mild or No Headache) in studies 1, 2, 3, 4, 5 in migraine with or without auraa
| Trial | Frovatriptan 2.5 mg | Placebo | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 2 hours | 4 hours | 2 hours | 4 hours | |||||||||
| 1 | 42%* (n=90) | 64%** (n=85) | 22% (n=91) | 38% (n=81) | ||||||||
| 2 | 38%* (n=121) | 68%** (n=117) | 25% (n=115) | 33% (n=106) | ||||||||
| 3 | 39%* (n=187) | 56%** (n=156) | 21% (n=99) | 31% (n=81) | ||||||||
| 4 | 46%** (n=672) | 65%** (n=586) | 27% (n=347) | 38% (n=305) | ||||||||
| 5 | 37%** (n=438) | 62%** (n=388) | 23% (n=225) | 32% (n=202) | ||||||||
a ITT observed data, excludes patients who had missing data or were asleep; *0.001≤ p ≤0.050, **p <
0.001 in comparison with placebo
Following the treatment of migraine with frovatriptan tablets in controlled clinical trials, there was low recurrence of migraine headaches (7%-25%). This is postulated to be due to the long half- life of frovatriptan.
In patients with migraine-associated nausea, photophobia and phonophobia at baseline there was a decreased incidence of these symptoms in frovatriptan tablets-treated patients compared to placebo.
Efficacy was unaffected by a history of aura, gender, age, or concomitant medications commonly used by migraine patients.
14.2 Comparative Bioavailability Studies
A randomized, blinded, balanced, two treatment, two period, two sequence, single dose, crossover comparative bioavailability study of JAMP Frovatriptan (frovatriptan) 2.5 mg tablets (JAMP Pharma Corporation, Canada) and PrFrova®/MD (frovatriptan) 2.5 mg tablets (Teva Canada Innovation), in 32 normal, healthy, adult, male and female human subjects under fasting conditions was conducted. The results from 31 subjects completing the study are summarized below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Frovatriptan (1 x 2.5 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test† | Reference* | % Ratio of Geometric Means | 90% Confidence Interval |
| AUC0-72 | 76.80 | 71.12 | 107.98 | 100.42 -116.10 |
| (ng.h/mL) | 85.99 (49.27) | 81.74 (56.20) | ||
| AUCI | 85.54 | 80.29 | 106.54 | 98.96 - 114.70 |
| (ng.hr/mL) | 96.14 (49.72) | 92.42 (56.24) | ||
| Cmax | 5.47 | 5.28 | 103.59 | 97.05 - 110.57 |
| (ng/mL) | 5.73 (30.81) | 5.62 (37.34) | ||
T § max (h) | 3.00 | 3.00 | ||
| (2.00 - 5.00) | (2.00 - 5.00) | |||
T € ½ (h) | 23.45 (21.25) | 23.36 (23.42) | ||
† JAMP Frovatriptan 2.5 mg tablets (JAMP Pharma Corporation)
* PrFROVA®/MD 2.5 mg frovatriptan tablets (Endo Pharmaceuticals Inc., USA; marketed by Teva Canada Innovation) was purchased in Canada.
§ Expressed as median (range) only
€ Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute and Long-Term Studies: Single dose toxicity studies in rats and mice indicate that frovatriptan has low acute oral toxicity with a lethal dose in excess of 2000 mg/kg. Toxicity studies with frovatriptan up to the maximum tolerated dose in several species give no indication of adverse effects (including mutagenic or carcinogenic effects) likely to be relevant to the proposed clinical use of frovatriptan.
In rodents, repeat dose oral studies in mice, demonstrated a no-observed-adverse-effect-level (NOAEL) of 40 mg/kg/day for 84 weeks, giving a 140- to 400-fold safety margin based upon human exposure (AUC) to frovatriptan in blood at the proposed dose of 2.5 mg (0.04 mg/kg). Repeat dose oral studies in rats, demonstrated a NOAEL of 10 mg/kg/day for 26 weeks, giving a 30- to 50-fold safety margin based upon human exposure to frovatriptan in blood at the proposed dose of 2.5 mg (0.04 mg/kg). Effects that were observed in rats included peripheral vasodilation as well as renal, adrenal and thyroid histopathological lesions. These effects, which only occurred at high doses are not considered to be relevant to man at the proposed clinical dose.
In dogs, repeat dose oral studies demonstrated no histopathological changes attributable to frovatriptan administration at blood exposures up to 130-fold higher than those anticipated in man. Dose levels were limited by the pharmacological effects of frovatriptan on the central nervous and cardiovascular systems. No evidence of any ocular toxicity has been noted in long term oral studies at blood exposures 50- to 130-fold higher than those anticipated in man.
Tachycardia, a compensatory response to peripheral vasodilatation and a consequence of the pharmacological effects of frovatriptan, was observed in dogs but is not anticipated to be a problem with the much lower dose levels used clinically.
Carcinogenicity
The carcinogenic potential of frovatriptan was evaluated in an 84-week study in mice (4, 13 and 40 mg/kg/day), a 104-week study in rats (8.5, 27 and 85 mg/kg/day), and a 26-week study in p53(+/-) transgenic mice (20, 62.5, 200, and 400 mg/kg/day). Although the maximum tolerated dose (MTD) was not achieved in the 84-week mouse study and in female rats, exposures at the highest doses studied were many fold greater than those achieved at the maximum recommended daily human dose (MRHD) of 7.5 mg. There were no increases in tumor incidence in the 84-week mouse study at doses producing 140 times the exposure achieved at the MRHD based on blood AUC comparisons. In the rat study, there was a statistically significant increase in the incidence of pituitary adenomas in males only at 85 mg/kg/day, a dose that produced 250 times the exposure achieved at the MRHD based on AUC comparisons. In the 26-week p53 (+/-) transgenic mouse study, there was an increased incidence of subcutaneous sarcomas in females dosed at 200 and 400 mg/kg/day, or 390 and 630 times the human exposure based on AUC comparisons. The incidence of sarcomas was not increased at lower doses that achieved exposure 180 and 60 times the human exposure.
These sarcomas were physically associated with subcutaneously implanted animal identification transponders. There were no other increases in tumor incidence of any type in any dose group. The relevance of these sarcomas to humans is unknown.
Genotoxicity
Frovatriptan was clastogenic in human lymphocyte cultures, in the absence of metabolic activation. In the bacterial reverse mutation assay (Ames test), frovatriptan produced an equivocal response in the absence of metabolic activation. No mutagenic or clastogenic activity were seen in an in vitro mouse lymphoma assay, an in vivo mouse bone marrow micronucleus test, or an ex vivo assay for unscheduled DNA synthesis in rat liver.
Reproductive and Developmental Toxicology
Impairment of Fertility: Male and female rats were dosed prior to and during mating, and up to implantation, at doses of 100, 500, and 1000 mg/kg/day (equivalent to approximately 130, 650 and 1300 times the MRHD on a mg/m2 basis). At all dose levels, there was an increase in the number of females that mated on the first day of pairing compared to control animals. This occurred in conjunction with a prolongation of the estrous cycle. In addition, females had a decreased mean number of corpora lutea, and consequently a lower number of live fetuses per litter, which suggested a partial impairment of ovulation. There were no other fertility - related effects.
When pregnant rats were administered frovatriptan during the period of organogenesis at oral doses of 100, 500 and 1000 mg/kg/day (equivalent to 130, 650 and 1300 times the MRHD) on a mg/m2 basis) there were dose related increases in incidences of both litters and total numbers of fetuses with dilated ureters, unilateral and bilateral pelvic cavitation, hydronephrosis, and hydroureters. A no-effect dose for renal effects was not established. This signifies a syndrome of related effects on a specific organ in the developing embryo in all treated groups, which is consistent with a slight delay in fetal maturation. This delay was also indicated by a treatment related increased incidence of incomplete ossification of the sternebrae, skull and nasal bones in all treated groups. Slightly lower fetal weights and an increased incidence of early embryonic deaths in treated rats were observed; although not statistically significant compared to control, the latter effect occurred in both the embryo-fetal developmental study and in the prenatal-postnatal developmental study. There was no evidence of this latter effect at the lowest dose level studied, 100 mg/kg/day (equivalent to 130 times the MRHD on a mg/m2 basis). When pregnant rabbits were dosed throughout organogenesis at doses up to 80 mg/kg/day (equivalent to 210 times the MRHD on a mg/m2 basis) no effects on fetal development were observed.
Special Toxicology
Binding to Melanin Containing Tissues: When pigmented rats were given a single oral dose of 5 mg/kg of radiolabelled frovatriptan, the radioactivity in the eye after 28 days was 87% of the value measured after 8 hours. This suggests that frovatriptan and/or its metabolites may bind to the melanin of the eye. Because there could be accumulation in melanin rich tissues over time, this raises the possibility that frovatriptan could cause toxicity in these tissues after extended use. However, no effects on the retina related to treatment with frovatriptan were noted in toxicity studies.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrFROVA (frovatriptan tablets; 2.5 mg), submission control 267525, Product Monograph, Endo Pharmaceuticals Inc., May 12, 2023.