


Product Monograph - Jardiance
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS | 01/2024 |
|---|---|
| 1 INDICATIONS, 1.1 Pediatrics | 01/2024 |
| 1 INDICATIONS, 1.2 Geriatrics | 01/2024 |
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 01/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations, Temporary interruption for surgery | 09/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 01/2024 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Geriatrics (≥65 years of age) | 02/2023 |
| 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Prolonged diabetic ketoacidosis | 09/2024 |
| 7 WARNINGS AND PRECAUTIONS, Genitourinary | 01/2024 |
| 7 WARNINGS AND PRECAUTIONS, Genitourinary, Necrotizing fasciitis of the perineum (Fournier’s gangrene) | 07/2025 |
| 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests | 01/2024 |
| 7 WARNINGS AND PRECAUTIONS, Peri-Operative Considerations | 09/2024 |
| 7 WARNINGS AND PRECAUTIONS, Renal | 01/2024 |
| 7 WARNING AND PRECAUTIONS, 7.1.3 Pediatrics | 01/2024 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics | 02/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES………………………………………………………….…….……………………………………….2
TABLE OF CONTENTS ............................................................................................................. 2
1 INDICATIONS .............................................................................................................. 5
1.1 Pediatrics ................................................................................................................... 5
1.2 Geriatrics ................................................................................................................... 5
2 CONTRAINDICATIONS ................................................................................................. 6
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 6
4 DOSAGE AND ADMINISTRATION ................................................................................. 6
4.1 Dosing Considerations .............................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ......................................................... 7
4.4 Administration .......................................................................................................... 8
4.5 Missed Dose .............................................................................................................. 8
5 OVERDOSAGE ............................................................................................................. 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 8
7 WARNINGS AND PRECAUTIONS .................................................................................. 9
7.1 Special Populations ................................................................................................. 13
7.1.1 Pregnant Women .............................................................................................. 13
7.1.2 Breast-feeding ................................................................................................... 14
7.1.3 Pediatrics ........................................................................................................... 14
7.1.4 Geriatrics ........................................................................................................... 14
8 ADVERSE REACTIONS................................................................................................ 14
8.1 Adverse Reaction Overview .................................................................................... 14
8.2 Clinical Trial Adverse Reactions .............................................................................. 15
8.3 Less Common Clinical Trial Adverse Reactions (<1%)a ........................................... 21
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .............................................................................................................. 22
8.5 Post-Market Adverse Reactions .............................................................................. 27
9 DRUG INTERACTIONS ............................................................................................... 27
9.2 Drug Interactions Overview .................................................................................... 27
9.3 Drug-Behavioural Interactions ................................................................................ 28
9.4 Drug-Drug Interactions ........................................................................................... 28
9.5 Drug-Food Interactions ........................................................................................... 32
9.6 Drug-Herb Interactions ........................................................................................... 32
9.7 Drug-Laboratory Test Interactions.......................................................................... 32
10 CLINICAL PHARMACOLOGY ....................................................................................... 32
10.1 Mechanism of Action ........................................................................................ 32
10.2 Pharmacodynamics ........................................................................................... 33
10.3 Pharmacokinetics .............................................................................................. 33
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 35
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 35
PART II: SCIENTIFIC INFORMATION ...................................................................................... 36
13 PHARMACEUTICAL INFORMATION ........................................................................... 36
14 CLINICAL TRIALS ....................................................................................................... 37
14.1 Clinical Trials by Indication ............................................................................... 37
Type 2 diabetes mellitus (T2DM) ..................................................................................... 37
Heart Failure ..................................................................................................................... 56
Chronic Kidney Disease .................................................................................................... 70
15 MICROBIOLOGY ....................................................................................................... 73
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 74
PATIENT MEDICATION INFORMATION ................................................................................. 76
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Type 2 diabetes mellitus (T2DM)
Monotherapy: JARDIANCE (empagliflozin) is indicated for use as an adjunct to diet and exercise to improve glycemic control in adult patients with T2DM for whom metformin is inappropriate due to contraindications or intolerance.
Add-on combination: JARDIANCE is indicated in adult patients with T2DM to improve glycemic control in combination with:
- metformin
- metformin and a sulfonylurea
- pioglitazone (alone or with metformin)
- linagliptin and metformin
- basal or prandial insulin (alone or with metformin)
when metformin alone or the existing therapy listed above, along with diet and exercise, do not provide adequate glycemic control.
Add-on combination in patients with established cardiovascular disease: JARDIANCE is indicated as an adjunct to diet, exercise and standard care therapy to reduce the incidence of cardiovascular death in patients with T2DM and established cardiovascular disease.
Important Limitations of Use: Use of JARDIANCE with insulin mix (regular or analogue mix) has not been studied. Therefore, JARDIANCE should not be used with insulin mix.
Heart Failure (HF)
JARDIANCE is indicated in adults as an adjunct to standard of care therapy for the treatment of heart failure.
Limitations of Use: JARDIANCE is not recommended for the emergency treatment of acute heart failure.
Chronic kidney disease (CKD)
JARDIANCE is indicated to reduce the risk of sustained eGFR decline, end-stage kidney disease and cardiovascular and renal death in adults with chronic kidney disease.
1.1 Pediatrics
Pediatrics (<18 years of age): Safety and efficacy of JARDIANCE have not been established in patients under 18 years of age; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (>65 years of age): JARDIANCE should be used with caution in geriatric patients with type 2 diabetes mellitus. A greater increase in risk of adverse reactions in geriatric patients with type 2 diabetes mellitus treated for glycemic control, was seen with JARDIANCE in the elderly, compared to younger patients. See 4.1 Dosing Consideration, 7.1.4 Geriatrics.
In the EMPEROR-Reduced study, a total of 2312 (62%) treated patients with HFrEF were 65 years of age and older. In the EMPEROR-Preserved study, a total of 4786 (80%) treated patients with HFpEF were 65 years of age and older. Safety and efficacy in both studies were similar for patients 65 years and younger and those older than 65.
The EMPA-KIDNEY study included 2089 (32%) patients 65 to <75 years of age, and 1518 (23%) patients 75 years of age and older. Efficacy was similar for patients younger than 65 years and those aged 65 and older. An increase in risk of adverse reactions was observed in the elderly, compared to younger patients in both study arms. JARDIANCE should be used with caution in geriatric CKD patients due to risks of volume depletion and hypotension.
2 CONTRAINDICATIONS
- JARDIANCE is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Ketoacidosis
- Clinical trial and post-market cases of ketoacidosis, a serious life-threatening condition requiring urgent hospitalization, have been reported in patients with type 2 diabetes mellitus (T2DM) treated with JARDIANCE, and other sodium-glucose co-transporter 2 (SGLT2) inhibitors. Fatal cases of ketoacidosis have been reported in patients with T2DM taking JARDIANCE. A number of these cases have been atypical with blood glucose values below 13.9 mmol/L (250 mg/dL). See 8 ADVERSE REACTIONS, Ketoacidosis.
- Cases of ketoacidosis have also been reported in patients without T2DM taking JARDIANCE.
- The risk of ketoacidosis must be considered in the event of non-specific symptoms such as nausea, vomiting, anorexia, abdominal pain, excessive thirst, difficulty breathing, confusion, unusual fatigue, or sleepiness. If these symptoms occur, regardless of blood glucose level, JARDIANCE treatment should be immediately discontinued, and patients should be assessed for ketoacidosis immediately.
- JARDIANCE should not be used for the treatment of ketoacidosis or in patients with a history of ketoacidosis.
- JARDIANCE is not indicated, and should not be used, in patients with type 1 diabetes.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- JARDIANCE may be taken at any time of the day with or without food.
- Assess renal function prior to initiation of JARDIANCE therapy and regularly thereafter. See 7 WARNINGS AND PRECAUTIONS, Renal.
- Assess volume status and, if necessary, correct volume depletion prior to initiation of JARDIANCE therapy. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular.
- Concomitant use with insulin or an insulin secretagogue (e.g., sulfonylurea): When JARDIANCE is used as add-on therapy with insulin or an insulin secretagogue, a lower dose of insulin or the insulin secretagogue may be considered to reduce the risk of hypoglycemia. See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Use with Medications Known to Cause Hypoglycemia and 8 ADVERSE REACTIONS.
- Temporary interruption for surgery: JARDIANCE treatment should be interrupted for a minimum of 3 days, when possible, prior to major surgical procedures or procedures associated with prolonged fasting. Monitor for ketoacidosis in the post-procedural period. Ensure risk factors for ketoacidosis are resolved and that the patient is clinically stable and has resumed oral intake before considering JARDIANCE treatment re-initiation. See 7 WARNINGS and PRECAUTIONS, Endocrine and Metabolism, Treatment Interruption considerations.
- Diuretics: JARDIANCE should be used with caution in patients taking diuretics, particularly loop diuretics, due to the increased risk of adverse events due to volume depletion during co-administration. See 9.4 Drug-Drug Interactions, Pharmacodynamic interactions, Diuretics.
- Patients hospitalized for acute heart failure (de novo or decompensated chronic heart failure) should be adequately stabilised and should receive heart failure therapies in accordance with clinical guidelines.
4.2 Recommended Dose and Dosage Adjustment
Type 2 diabetes mellitus (T2DM)
To improve glycemic control, the recommended starting dose of JARDIANCE is 10 mg taken orally, once daily. In patients tolerating JARDIANCE 10 mg once daily and who require additional glycemic control, and who have an eGFR ≥30 mL/min/1.73 m2, the dose can be increased to 25 mg once daily.
To reduce the incidence of cardiovascular death in patients with T2DM and established cardiovascular disease the recommended dose of JARDIANCE is 10 mg taken orally once daily.
Heart Failure (HF)
The recommended dose of JARDIANCE is 10 mg taken orally once daily.
Chronic kidney disease (CKD)
The recommended dose of JARDIANCE is 10 mg taken orally once daily.
Considerations for Special Populations
Renal Impairment: The glucose-lowering efficacy of JARDIANCE is dependent on renal function and decreases with declining renal function.
- If eGFR falls below 30 mL/min/1.73m² the recommended dose of JARDIANCE is limited to 10 mg and additional glucose lowering treatment should be considered if needed. See 7 WARNINGS AND PRECAUTIONS, Renal.
- JARDIANCE 10 mg can be used regardless of renal function. Efficacy and safety trials with JARDIANCE did not enroll adult patients with an eGFR less than 20 mL/min/1.73 m2 or on dialysis. Due to limited experience, it is not recommended to initiate treatment with JARDIANCE in patients on dialysis. See 7 WARNINGS AND PRECAUTIONS, Renal.
Hepatic Impairment: No dosage adjustment for JARDIANCE is necessary for patients with mild or moderate hepatic impairment. JARDIANCE exposure is increased in patients with severe hepatic impairment. See 10 CLINICAL PHARMACOLOGY, Hepatic insufficiency.
Experience in patients with severe hepatic impairment is limited. Therefore, JARDIANCE is not recommended for use in this population.
Pediatrics (<18 years of age): The safety and efficacy of JARDIANCE have not been established; therefore, Health Canada has not authorized an indication for use in pediatric patients.
Geriatrics (≥65 years of age): No dose adjustment for JARDIANCE is required based on age; however renal function and risk of volume depletion should be taken into account. See 7.1.4 Geriatrics.
4.4 Administration
JARDIANCE tablets should be taken whole and should not be cut or divided.
4.5 Missed Dose
If a dose is missed, it should be taken as soon as the patient remembers. A double dose of JARDIANCE should not be taken on the same day.
5 OVERDOSAGE
It is reasonable to employ usual supportive measures, e.g., remove unabsorbed material from the gastrointestinal tract, employ clinical monitoring, and institute supportive treatment as dictated by the patient’s clinical status. The removal of JARDIANCE by haemodialysis has not been studied.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
Description
JARDIANCE 10 mg film-coated tablets are pale yellow, round, biconvex and bevel-edged, debossed with “S10” on one side and the Boehringer Ingelheim company symbol on the other side.
JARDIANCE 25 mg film-coated tablets are pale yellow, oval, biconvex and debossed with “S25” on one side and the Boehringer Ingelheim logo on the other.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Film-coated tablets 10 mg, or 25 mg | Colloidal silicon dioxide, croscarmellose sodium, hydroxypropyl cellulose, hypromellose, lactose monohydrate, magnesium stearate, macrogol, microcrystalline cellulose, titanium dioxide, talc, and yellow ferric oxide. |
Packaging
PVC/aluminium unit dose blisters in cartons containing: 10 x 1 blister card (physician sample for the patients); or 10 x 3 blister cards, or 10 x 9 blister cards (commercial presentation).
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
JARDIANCE is not indicated for use in patients with type 1 diabetes and should not be used for the treatment of ketoacidosis.
Cardiovascular
Use in patients at risk for volume depletion, hypotension and/or electrolyte imbalances: JARDIANCE is not recommended for use in patients who are volume depleted.
Due to its mechanism of action, JARDIANCE causes diuresis that may be associated with decreases in blood pressure. See 10.1 Mechanism of Action.
Caution should be exercised in patients for whom an empagliflozin induced drop in blood pressure could pose a risk, such as patients with known cardiovascular disease, patients on antihypertensive therapy (particularly loop diuretics), elderly patients, patients with low systolic blood pressure, or in case of intercurrent conditions that may lead to volume depletion (such as gastrointestinal illness).
Careful monitoring of volume status is recommended. Temporary interruption of JARDIANCE should be considered for patients who develop volume depletion until the depletion is corrected. See 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests, and 8 ADVERSE REACTIONS, Volume Depletion and hypotension.
Cerebrovascular Accidents
In the EMPA-REG OUTCOME trial, JARDIANCE (empagliflozin 10 mg and 25 mg treatment groups combined) was associated with a non-significant trend for a higher risk of fatal/non-fatal stroke compared to the placebo group: HR 1.18 (95% CI 0.89, 1.56). See 14 CLINICAL TRIALS, EMPA-REG OUTCOME TRIAL, Stroke.
A causal relationship between JARDIANCE and stroke has not been established; however, caution should be observed in patients at high risk for cerebrovascular accidents.
Driving and Operating Machinery
No studies on the effects on the ability to drive and use machines have been performed. JARDIANCE may cause dizziness or light-headedness. Patients should be advised to take precautions and not drive or use machines until they know how the medicine affects them.
Endocrine and Metabolism
Ketoacidosis: Clinical trial and post-market cases of ketoacidosis, a serious life-threatening condition requiring urgent hospitalization, have been reported in patients with type 2 diabetes mellitus treated with JARDIANCE, or other SGLT2 inhibitors. In a number of reported cases, the presentation of the condition was atypical with only moderately increased blood glucose values, below 13.9 mmol/L (250 mg/dL). Fatal cases of ketoacidosis have been reported in patients with diabetes mellitus taking JARDIANCE. See 8 ADVERSE REACTIONS, Ketoacidosis.
Reports of ketoacidosis, including life-threatening and fatal cases, have also been identified in post-marketing surveillance in patients with type 1 diabetes mellitus receiving SGLT2 inhibitors, including JARDIANCE. The safety and efficacy of JARDIANCE in patients with type 1 diabetes have not been established. Limited data from clinical trials suggest that ketoacidosis occurs with common frequency when patients with type 1 diabetes are treated with SGLT2 inhibitors.
JARDIANCE is not indicated, and should not be used, in patients with type 1 diabetes. The diagnosis of type 2 diabetes mellitus should therefore be confirmed before initiating JARDIANCE.
Cases of ketoacidosis have also been reported in patients without T2DM taking JARDIANCE.
Patients treated with JARDIANCE who present with signs and symptoms consistent with severe metabolic acidosis should be assessed for ketoacidosis regardless of presenting blood glucose levels, as ketoacidosis associated with JARDIANCE may be present even if blood glucose levels are less than 13.9 mmol/L (250 mg/dL).
The risk of ketoacidosis must be considered in the event of non-specific symptoms such as nausea, vomiting, anorexia, abdominal pain, excessive thirst, difficulty breathing, confusion, unusual fatigue, or sleepiness.
If these symptoms occur, regardless of blood glucose level, JARDIANCE treatment should be immediately discontinued, patients should be assessed for ketoacidosis immediately, and prompt treatment should be instituted.
SGLT2 inhibitors have been shown to increase blood ketones in clinical trial subjects.
Before initiating JARDIANCE, consider factors in the patient history that may predispose to ketoacidosis including pancreatic insulin deficiency from any cause, caloric restriction, and alcohol abuse.
Conditions that can precipitate ketoacidosis while taking empagliflozin include patients on a very low carbohydrate diet (as the combination may further increase ketone body production), patients with conditions that lead to restricted food intake or severe dehydration, patients with increased insulin requirement due to an acute medical illness, surgery, or alcohol abuse, patients with a low beta-cell function reserve [e.g., type 2 diabetes patients with low C-peptide or latent autoimmune diabetes in adults (LADA)], pancreatic disorders suggesting insulin deficiency (e.g., type 1 diabetes, history of pancreatitis, or pancreatic surgery), insulin dose reduction (including insulin pump failure), and patients with a history of ketoacidosis. JARDIANCE should be used with caution in these patients. These patients should be monitored closely.
Caution should be taken when reducing the insulin dose in patients requiring insulin. See 4.1 Dosing Considerations, Concomitant use with insulin or an insulin secretagogue (e.g., sulfonylurea).
JARDIANCE should not be used for the treatment of ketoacidosis or in patients with a history of ketoacidosis. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Prolonged diabetic ketoacidosis
Diabetic ketoacidosis may be prolonged in some patients. In most post-marketing adverse event reports where JARDIANCE treatment was stopped at or before diagnosis, ketoacidosis lasted for 3 days or more despite JARDIANCE discontinuation and standard treatment of diabetic ketoacidosis.
Treatment Interruption considerations
Temporarily discontinue treatment with JARDIANCE in patients who are hospitalized for major surgical procedures, or will undergo scheduled surgery, and in patients who are hospitalized for serious infections or acute serious medical illnesses. Withhold JARDIANCE treatment for at least 3 days, if possible, prior to major surgery or any other procedures associated with prolonged fasting, when, based on the drug pharmacology, most of JARDIANCE would be expected to be eliminated. Monitoring for ketoacidosis is recommended in these patients even if drug treatment has been interrupted or discontinued. Ensure risk factors for ketoacidosis are resolved prior to considering JARDIANCE treatment re-initiation. See 4.1 Dosing Considerations, Temporary interruption for surgery.
Educate patients on the signs and symptoms of ketoacidosis and instruct patients to discontinue JARDIANCE and seek medical attention immediately if signs and symptoms occur.
Use with Medications Known to Cause Hypoglycemia: Insulin secretagogues and insulin are known to cause hypoglycemia. The use of JARDIANCE in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin was associated with a higher rate of hypoglycemia compared with placebo in a clinical trial. See 8.2 Clinical Trial Adverse Reactions, Description of Selected Adverse Reactions in T2DM Patients Being Treated for Glycemic Control, Hypoglycemia.
Therefore, a lower dose of the insulin secretagogue or insulin may be required to reduce the risk of hypoglycemia when used in combination with JARDIANCE. See 4.1 Dosing Considerations, Concomitant use with insulin or an insulin secretagogue (e.g., sulfonylurea).
Genitourinary
Genital mycotic infections: JARDIANCE increases the risk of genital mycotic infections, particularly for patients with a history of genital mycotic infections. See 8 ADVERSE REACTIONS, Genital mycotic infections.
Monitor and treat as appropriate.
Urinary tract infections (including urosepsis and pyelonephritis): JARDIANCE increases the risk for urinary tract infections. See 8.2 Clinical Trial Adverse Reactions, Description of Selected Adverse Reactions in T2DM Patients Being Treated for Glycemic Control, Urinary Tract Infections.
There have been post-marketing reports of serious urinary tract infections including urosepsis and pyelonephritis, some of them requiring hospitalization, in patients receiving SGLT2 inhibitors, including JARDIANCE. See 8.5 Post-Market Adverse Reactions.
Evaluate patients for signs and symptoms of urinary tract infections and treat promptly, if indicated. Temporary interruption of JARDIANCE should be considered in patients with complicated urinary tract infections.
Necrotizing fasciitis of the perineum (Fournier’s gangrene): Cases of necrotizing fasciitis of the perineum (also known as Fournier’s gangrene), a rare, but serious and life-threatening necrotizing infection requiring urgent surgical intervention, have been reported in female and male patients treated with SGLT2 inhibitors, including JARDIANCE. Serious outcomes have included hospitalization, multiple surgeries, and death. See 8.5 Post-Market Adverse Reactions.
Patients treated with JARDIANCE who present with pain or tenderness, erythema, swelling in the genital or perineal area, fever, or malaise should be evaluated for necrotizing fasciitis. If suspected, JARDIANCE should be discontinued, and prompt treatment should be instituted (including broad-spectrum antibiotics and surgical debridement if necessary).
Hematologic
Elevated hemoglobin and hematocrit: Mean hemoglobin and hematocrit increased in patients administered JARDIANCE, as did the frequency of patients with abnormally elevated values for hemoglobin/hematocrit. See 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Hematocrit.
JARDIANCE should be used with caution in patients with an elevated hematocrit.
Hepatic/Biliary/Pancreatic
Substantial elevations in hepatic transaminases have been reported in empagliflozin treated patients in clinical trials; however, a causal relationship with empagliflozin has not been established. Use of JARDIANCE is not recommended in patients with severe hepatic impairment. See 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment and 10 CLINICAL PHARMACOLOGY, Hepatic insufficiency.
Immune
Hypersensitivity reactions: JARDIANCE is contraindicated in patients with a history of hypersensitivity reaction to the active substance or to any of the excipients. See 2 CONTRAINDICATIONS.
Serious hypersensitivity reactions, including rash, angioedema and urticaria, have been observed with JARDIANCE in post-marketing reports. See 8.5 Post-Market Adverse Reactions.
If a hypersensitivity reaction occurs, discontinue JARDIANCE; treat promptly per standard of care, and monitor until signs and symptoms resolve.
Monitoring and Laboratory Tests
Blood glucose and HbA1c: Response to JARDIANCE treatment should be monitored by periodic measurements of blood glucose and HbA1c levels.
Due to its mechanism of action, patients taking JARDIANCE will test positive for glucose in their urine. See 9.7 Drug-Laboratory Test Interactions.
Renal function: Renal function should be assessed prior to initiation of JARDIANCE and regularly thereafter. See 7 WARNINGS AND PRECAUTIONS, Renal.
Monitoring of renal function is recommended prior to and following initiation of any concomitant drug which might have an impact on renal function.
Reduced intravascular volume: JARDIANCE is not recommended for use in patients who are volume depleted. Before initiating JARDIANCE, assess volume status, particularly in patients at risk, as well as in case of intercurrent conditions that may lead to fluid loss (such as a gastrointestinal illness) for patients already taking JARDIANCE. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular, and 4.1 Dosing Consideration.
In these patients, careful monitoring of volume status (e.g., physical examination, blood pressure measurements, laboratory tests, including hematocrit, serum electrolytes and renal function tests) is recommended. Temporary interruption of treatment with JARDIANCE should be considered until fluid loss is corrected.
Peri-Operative Considerations
Temporarily discontinue treatment with JARDIANCE in T2DM patients who are hospitalized for major surgical procedures or will undergo scheduled surgery. Ensure risk factors for ketoacidosis are resolved and that the patient is clinically stable and has resumed oral intake before considering JARDIANCE treatment re-initiation. Monitoring for ketoacidosis is recommended in these patients. See 7 WARNINGS and PRECAUTIONS, Endocrine and Metabolism, Treatment Interruption considerations, and 4.1 Dosing Considerations, Temporary interruption for surgery.
Renal
JARDIANCE causes intravascular volume contraction and increases serum creatinine and decreases eGFR in a dose dependent fashion. Renal function abnormalities can occur after initiating JARDIANCE. Patients with hypovolemia are more susceptible to these changes. See 8.4 Abnormal Laboratory Findings, Hematologic, Clinical Chemistry and Other Quantitative Data, Increases in serum creatinine and decreases in eGFR.
Renal function should be assessed prior to initiation of JARDIANCE and periodically thereafter.
The glucose-lowering benefit of JARDIANCE decreases with declining renal function and was not demonstrated to be statistically significant in subjects with eGFR less than 30 mL/min/1.73 m2. See 14 CLINICAL TRIALS, Use in Patients with Type 2 Diabetes and Renal Impairment.
Efficacy and safety trials with JARDIANCE did not enroll adult patients with an eGFR less than 20 mL/min/1.73 m2 or on dialysis. Once enrolled, patients were not required to discontinue therapy for worsening of eGFR to less than 20 mL/min/1.73 m2 or initiation of dialysis. Due to limited experience, it is not recommended to initiate treatment with JARDIANCE in patients on dialysis.
Safety and efficacy of JARDIANCE have not been established in CKD patients with polycystic kidney disease, or patients requiring or with a recent history (within 3 months) of intravenous immunosuppressive therapy or greater than 45 mg of prednisone or equivalent for the treatment of kidney disease. JARDIANCE is not recommended for the treatment of CKD in these patients.
There have been post-marketing reports of acute kidney injury, some requiring hospitalization and dialysis, in patients receiving SGLT2 inhibitors. Before initiating JARDIANCE, consider factors that may predispose patients to acute kidney injury including hypovolemia, chronic renal insufficiency, congestive heart failure and concomitant medications (diuretics, ACE inhibitors, ARBs, NSAIDs). Consider temporarily discontinuing JARDIANCE in any setting of reduced oral intake (such as acute illness or fasting) or fluid losses (such as gastrointestinal illness or excessive heat exposure); monitor patients for signs and symptoms of acute kidney injury. If acute kidney injury occurs, discontinue JARDIANCE promptly and institute treatment.
7.1 Special Populations
7.1.1 Pregnant Women
JARDIANCE must not be used in pregnancy. There are limited data for the use of JARDIANCE in pregnant women. When pregnancy is detected, JARDIANCE should be discontinued. Based on results from animal studies, SGLT2 inhibitors may affect renal development and maturation. See 16 NON-CLINICAL TOXICOLOGY.
7.1.2 Breast-feeding
JARDIANCE must not be used in nursing women. No data in humans are available on excretion of JARDIANCE into milk. Available animal data have shown excretion of empagliflozin in milk reaching levels up to 5 times higher than that in the maternal plasma. See 16 NON-CLINICAL TOXICOLOGY.
As functional maturation of the kidneys in humans continues in the first 2 years of life, there may be a risk to the developing kidney if JARDIANCE is used during breastfeeding.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Safety and effectiveness of JARDIANCE have not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): JARDIANCE should be used with caution in geriatric patients with type 2 diabetes. A total of 2721 (32%) patients treated with empagliflozin were 65 years and over, and 491 (6%) were 75 years and over in the pool of double-blind, controlled clinical safety and efficacy studies of JARDIANCE in patients with type 2 diabetes treated for glycemic control.
A greater increase in risk of adverse reactions related to urinary tract infections was seen with JARDIANCE in the elderly patients with type 2 diabetes treated for glycemic control, compared to younger patients, and increased in patients who were 75 years of age and older. A greater increase in risk of adverse reactions related to volume depletion was seen with JARDIANCE in patients ≥75 years of age. JARDIANCE is expected to have diminished antihyperglycemic efficacy in elderly patients as older patients are more likely to have impaired renal function. Therefore, JARDIANCE should be used with caution in this population. See 1.2 Geriatrics, 4.1 Dosing Considerations.
In the EMPEROR-Reduced study, a total of 2312 (62%) treated patients with HFrEF were 65 years of age and older. In the EMPEROR-Preserved study, a total of 4786 (80%) treated patients with HFpEF were 65 years of age and older. Safety and efficacy in both studies were similar for patients 65 years and younger and those older than 65.
The EMPA-KIDNEY study included 2089 (32%) patients 65 to <75 years of age, and 1518 (23%) patients 75 years of age and older. Efficacy was similar for patients younger than 65 years and those aged 65 and older. An increase in risk of adverse reactions was observed in the elderly, compared to younger patients in both study arms. JARDIANCE should be used with caution in geriatric CKD patients due to risks of volume depletion and hypotension.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Type 2 diabetes mellitus (T2DM)
A total of 10 004 patients with type 2 diabetes were treated with JARDIANCE in clinical studies to evaluate the safety of JARDIANCE, alone or in combination with other antidiabetic agents.
Placebo controlled double-blinded trials of 18 to 24 weeks of exposure included 2971 patients, of which 995 were treated with placebo, 999 were treated with JARDIANCE 10 mg and 977 were treated with JARDIANCE 25 mg.
In these trials, the frequency of AEs leading to discontinuation was similar by treatment groups for placebo (5.3%) and JARDIANCE 10 mg (4.8%) and 25 mg (4.9%).
The most frequent adverse drug reaction was hypoglycemia, which depended on the type of background therapy used in the respective studies. The overall incidence of adverse events with JARDIANCE and the frequency of adverse events leading to discontinuation with JARDIANCE were similar to placebo.
Heart Failure
The EMPEROR-Reduced study included 3730 patients with heart failure and reduced ejection fraction treated with empagliflozin 10 mg or placebo. The EMPEROR-Preserved study included 5985 patients with heart failure and preserved ejection fraction treated with empagliflozin 10 mg or placebo. Approximately half of the patients had type 2 diabetes mellitus.
The most frequent adverse events (≥2% of patients receiving JARDIANCE) from the EMPEROR studies pooled data occurring at a higher incidence in the JARDIANCE arm compared to the placebo arm (≥1% higher) were hypotension (empagliflozin 10 mg: 7.5%, vs. placebo: 6.3%), and urinary tract infection (empagliflozin 10 mg: 6.3%, vs. placebo: 5.2%).
No new adverse reactions were identified in the EMPEROR heart failure studies.
The EMPULSE trial studied in-hospital initiation of JARDIANCE 10 mg in patients hospitalized for acute heart failure (de novo or decompensated chronic heart failure), irrespective of ejection fraction, once stabilized.
The safety profile was consistent with the known safety of JARDIANCE in patients with heart failure.
Chronic kidney disease
The EMPA-KIDNEY study included patients with chronic kidney disease (N = 6609) treated with empagliflozin 10 mg or placebo. About 44% of the patients had type 2 diabetes mellitus.
The overall safety profile of JARDIANCE was generally consistent across the studied indications.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
JARDIANCE has been evaluated in clinical trials in patients with T2DM, in patients with heart failure (HFrEF and HFpEF) and in patients with chronic kidney disease. The overall safety profile of JARDIANCE was generally consistent across the studied indications. Ketoacidosis was observed in patients with or without T2DM.
Clinical Trials in Patients with T2DM Treated for Glycemic Control
In a pooled dataset of the five 24-week placebo-controlled clinical trials and 18-week data from the placebo-controlled study as add-on to insulin therapy, adverse events regardless of causality that occurred in ≥1% of patients receiving JARDIANCE and more commonly than in patients given placebo (excluding hypoglycemia), are shown in Table 2.
Table 2: Adverse Events Reported in ≥1% of Patients with T2DM Treated with JARDIANCE and More Frequently than in Patients Treated with Placebo
System organ class Preferred term | JARDIANCE 10 mg n = 999 N (%) | JARDIANCE 25 mg n = 977 N (%) | Placebo n = 995 N (%) |
|---|---|---|---|
System organ class Preferred term | JARDIANCE 10 mg n = 999 N (%) | JARDIANCE 25 mg n = 977 N (%) | Placebo n = 995 N (%) |
| Gastrointestinal disorders | |||
| Nausea | 23 (2.3) | 11 (1.1) | 14 (1.4) |
| Constipation | 14 (1.4) | 8 (0.8) | 12 (1.2) |
| Toothache | 10 (1.0) | 3 (0.3) | 5 (0.5) |
| Dry mouth | 3 (0.3) | 10 (1.0) | 1 (0.1) |
| General disorders and administration site conditions | |||
| Fatigue | 19 (1.9) | 6 (0.6) | 11 (1.1) |
| Thirst | 15 (1.5) | 12 (1.2) | 0 (0) |
| Infections and infestations | |||
| Urinary tract infection | 82 (8.2) | 60 (6.1) | 58 (5.8) |
| Upper respiratory tract infection | 31 (3.1) | 39 (4.0) | 38 (3.8) |
| Vaginal infection1 | 6 (1.4) | 4 (1.0) | 2 (0.4) |
| Bronchitis | 13 (1.3) | 9 (0.9) | 10 (1.0) |
| Gastroenteritis | 13 (1.3) | 10 (1.0) | 9 (0.9) |
| Sinusitis | 11 (1.1) | 9 (0.9) | 7 (0.7) |
| Vulvovaginal candidiasis1 | 5 (1.1) | 3 (0.7) | 0 (0) |
| Vulvovaginal mycotic infection1 | 4 (0.9) | 7 (1.7) | 0 (0) |
| Influenza | 9 (0.9) | 12 (1.2) | 11 (1.1) |
| Vulvitis1 | 0 (0) | 5 (1.2) | 0 (0) |
| Investigations | |||
| Weight decreased | 5 (0.5) | 14 (1.4) | 2 (0.2) |
| Metabolism and nutrition disorders | |||
| Hypoglycemia | 78 (7.8) | 79 (8.1) | 61 (6.1) |
| Dyslipidemia | 39 (3.9) | 28 (2.9) | 34 (3.4) |
| Hyperlipidemia | 8 (0.8) | 12 (1.2) | 8 (0.8) |
| Musculoskeletal and connective tissue disorders | |||
| Arthralgia | 24 (2.4) | 22 (2.3) | 22 (2.2) |
| Muscle spasms | 9 (0.9) | 10 (1.0) | 7 (0.7) |
| Renal and urinary disorders | |||
| Pollakiuria | 19 (1.9) | 15 (1.5) | 5 (0.5) |
| Polyuria | 14 (1.4) | 10 (1.0) | 1 (0.1) |
| Reproductive system and breast disorders | |||
| Balanoposthitis2 | 7 (1.3) | 1 (0.2) | 0 (0) |
| Vulvovaginal pruritus1 | 11 (2.5) | 8 (1.9) | 3 (0.6) |
| Respiratory, thoracic and mediastinal disorders | |||
| Cough | 14 (1.4) | 12 (1.2) | 11 (1.1) |
1Percentages calculated with the number of female subjects in each group as denominator: placebo (N=481), JARDIANCE 10 mg (N=443), JARDIANCE 25 mg (N=420).
2Percentages calculated with the number of male subjects in each group as denominator: placebo (N=514), JARDIANCE 10 mg (N=556), JARDIANCE 25 mg (N=557).
Table 3: Serious and/or Unexpected Adverse Event Reported at a Higher Frequency than Placebo during JARDIANCE Treatment in the EMPA-REG OUTCOME Trial
MedDRA System organ class/ Preferred term (PT) | JARDIANCE 10 mg N=2345 n (%) | JARDIANCE 25 mg N=2342 n (%) | Placebo N=2333 n (%) |
|---|---|---|---|
| Skin and subcutaneous tissue disorders | |||
| Rash | 43 (1.8) | 53 (2.3) | 34 (1.5) |
| Musculoskeletal and connective tissue disorders | |||
| Osteoporosisa | 25 (1.1) | 16 (0.7) | 13(0.6) |
| Infections and infestations | |||
| Urosepsis | 6 (0.3) | 11 (0.5) | 3 (0.1) |
| Pyelonephritis | 3 (0.1) | 10 (0.4) | 4 (0.2) |
| Neoplasms benign, malignant and unspecified (including cysts and polyps) | |||
| Pancreatic neoplasm malignanta,b | 6 (0.3) | 6 (0.3) | 2 (0.1) |
| Hepatobiliary disorders | |||
| Hepatomegaly | 5 (0.2) | 4 (0.2) | 2 (0.1) |
| Vascular disorders | |||
| Deep vein thrombosis | 3 (0.1) | 10 (0.4) | 5 (0.2) |
| Metabolism and nutrition disorders | |||
| Diabetic ketoacidosisa | 3 (0.1) | 1 (0.04) | 1 (0.04) |
| |||
Description of Selected Adverse Reactions in T2DM Patients Being Treated for Glycemic Control
Hypoglycemia: The frequency of hypoglycemia depended on the type of background therapy used in each study (see Table 4). The incidence of hypoglycemia is increased when JARDIANCE was administered with insulin or a sulfonylurea. See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism.
Table 4: Incidence of Overalla and Severeb Hypoglycemia in Placebo-Controlled Clinical Studies
| Monotherapy (24 weeks) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo (n=229) | JARDIANCE 10 mg (n=224) | JARDIANCE 25 mg (n=223) | ||||||||||
| Overall (%) | 0.4 | 0.4 | 0.4 | |||||||||
| Severe (%) | 0 | 0 | 0 | |||||||||
| Background with Metformin (24 weeks) | ||||||||||||
Placebo + Metformin (n=206) | JARDIANCE 10 mg + Metformin (n=217) | JARDIANCE 25 mg + Metformin (n=214) | ||||||||||
| Overall (%) | 0.5 | 1.8 | 1.4 | |||||||||
| Severe (%) | 0 | 0 | 0 | |||||||||
| Background with Metformin + Sulfonylurea (24 weeks) | ||||||||||||
Placebo (n=225) | JARDIANCE 10 mg + Metformin + Sulfonylurea (n=224) | JARDIANCE 25 mg + Metformin + Sulfonylurea (n=217) | ||||||||||
| Overall (%) | 8.4 | 16.1 | 11.5 | |||||||||
| Severe (%) | 0 | 0 | 0 | |||||||||
| Background with Pioglitazone +/- Metformin (24 weeks) | ||||||||||||
Placebo (n=165) | JARDIANCE 10 mg + Pioglitazone +/- Metformin (n=165) | JARDIANCE 25 mg + Pioglitazone +/- Metformin (n=168) | ||||||||||
| Overall (%) | 1.8 | 1.2 | 2.4 | |||||||||
| Severe (%) | 0 | 0 | 0 | |||||||||
| In combination with MDI Insulin (18 weeks) | ||||||||||||
Placebo (n=53) | JARDIANCE 10 mg (n=58) | JARDIANCE 25 mg (n=52) | ||||||||||
| Overall (%) | 30.2 | 41.4 | 40.4 | |||||||||
| Severe (%) | 0 | 1.7 | 0 | |||||||||
| In combination with MDI Insulin + Metformin (18 weeks) | ||||||||||||
Placebo (n=135) | JARDIANCE 10 mg (n=128) | JARDIANCE 25 mg (n=137) | ||||||||||
| Overall (%) | 40 | 39.1 | 41.6 | |||||||||
| Severe (%) | 0.7 | 0 | 0.7 | |||||||||
| Patients with high CV risk (EMPA-REG OUTCOME) | ||||||||||||
Placebo (n=2333) | JARDIANCE 10 mg (n=2345) | JARDIANCE 25 mg (n=2342) | ||||||||||
| Overall (%) | 27.9 | 28.0 | 27.6 | |||||||||
| Severe (%) | 1.5 | 1.4 | 1.3 | |||||||||
| In Combination with metformin and linagliptin (24 weeks) | ||||||||||||
Placebo (n=110) | JARDIANCE 10 mg (n=112) | JARDIANCE 25 mg (n=110) | ||||||||||
| Overall (%) | 0.9 | 0.0 | 2.7 | |||||||||
| Severe (%) | 0.0 | 0.0 | 0.9 | |||||||||
aOverall hypoglycemic events: plasma or capillary glucose of less than or equal to 3.89 mmol/L
bSevere hypoglycemic events: requiring assistance regardless of blood glucose
Genital Mycotic Infections: In a pooled dataset of the five 24-week placebo-controlled clinical trials and 18-week data from the placebo-controlled study as add-on to insulin therapy, the frequency of vaginal moniliasis, vulvovaginitis, balanitis and other genital infections were reported more frequently for JARDIANCE 10 mg (4.1%) and JARDIANCE 25 mg (3.7%) compared to placebo (0.9%). Patients with a prior history of genital infections were more likely to experience a genital infection event.
Genital infection events were reported more frequently in female patients (5.4%, 6.4% and 1.5%, for JARDIANCE 10 mg, 25 mg, or placebo, respectively) than in male patients (3.1%, 1.6% and 0.4%, for JARDIANCE 10 mg, 25 mg, or placebo, respectively). Discontinuation from study due to genital infection occurred in 0.2% of patients treated with either JARDIANCE 10 or 25 mg and 0% of placebo treated patients.
In the EMPA-REG OUTCOME trial, genital infection events were reported more frequently in patients treated with JARDIANCE than placebo, and more frequently in female patients (9.2%, 10.8% and 2.6%, for JARDIANCE 10 mg, 25 mg, or placebo, respectively) than in male patients (5.4%, 4.6% and 1.5%, for JARDIANCE 10 mg, 25 mg, or placebo, respectively).
Phimosis occurred more frequently in patients treated with JARDIANCE 10 mg (less than 0.1%) and JARDIANCE 25 mg (0.1%) than placebo (0%) in the pooled 24-week placebo-controlled trials. In the subgroup of male patients in the EMPA-REG OUTCOME trial, phimosis was reported at an incidence of 0.3% in the empagliflozin 10 mg group, 0.8% in the empagliflozin 25 mg group, and 0.2% in the placebo group.
Increased Urination: In the pool of five placebo-controlled clinical trials, adverse reactions of increased urination (e.g., polyuria, pollakiuria, and nocturia) were reported by 3.4%, 3.2% and 1.0% of patients treated with JARDIANCE 10 mg, 25 mg and placebo, respectively. Nocturia was reported by 0.3%, 0.8%, and 0.4% of patients treated with JARDIANCE 10 mg, 25 mg, and placebo respectively.
Urinary Tract Infections: In a pooled dataset of the five 24-week placebo-controlled clinical trials and 18-week data from the placebo-controlled study as add-on to insulin therapy, the frequency of urinary tract infections (e.g., urinary tract infection, asymptomatic bacteriuria, and cystitis) occurred in 9.3%, 7.6%, and 7.6% of patients treated with JARDIANCE 10 mg, 25 mg, and placebo, respectively. Patients with a history of chronic or recurrent urinary tract infections were more likely to experience a urinary tract infection.
Urinary tract infection events were reported more frequently in female patients (18.3% and 15.5% for JARDIANCE 10 mg and 25 mg respectively, 12.5% for placebo) than in male patients (2.2% and 1.6% for JARDIANCE 10 mg and 25 mg respectively, 3.1% for placebo). The incidence of pyelonephritis and urosepsis with JARDIANCE was <0.1% and similar to placebo.
In elderly patients the incidence of urinary tract infections with JARDIANCE compared to placebo was greater than in younger patients. See 7 WARNINGS AND PRECAUTIONS, Genitourinary.
In the EMPA-REG OUTCOME trial, the incidence of urosepsis was greater in the empagliflozin groups than in the placebo group (0.3% for empagliflozin 10 mg, 0.5% for empagliflozin 25 mg, and 0.1% for placebo).
Volume Depletion and hypotension: Adverse reactions related to volume depletion (including the predefined terms blood pressure (ambulatory) decreased, blood pressure systolic decreased, dehydration, hypotension, hypovolaemia, orthostatic hypotension, and syncope) were reported for 0.5%, 0.3%, and 0.3% of patients treated with JARDIANCE 10 mg, 25 mg and placebo, respectively.
The incidence of volume depletion was increased in patients ≥75 years of age, with adverse events reported for 2.3%, 4.4%, and 2.1% of patients treated with JARDIANCE 10 mg, 25 mg, and placebo, respectively.
Blood creatinine increased and glomerular filtration rate decreased: In placebo-controlled, double-blind studies up to 76 weeks, increases in creatinine (mean change from baseline after 12 weeks: empagliflozin 10 mg 0.02 mg/dL, empagliflozin 25 mg 0.01 mg/dL) and decreases in estimated glomerular filtration rates (mean change from baseline after 12 weeks: empagliflozin 10 mg -1.34 mL/min/1.73m2, empagliflozin 25 mg -1.37 mL/min/1.73m2) have been observed. These changes were reversible in some patients during continuous treatment or after drug discontinuation.
In the EMPA-REG OUTCOME trial, the decrease in eGFR was observed to reverse after treatment discontinuation suggesting acute hemodynamic changes. See 8.4 Abnormal Laboratory Findings, Hematologic, Clinical Chemistry and Other Quantitative Data, Increases in serum creatinine and decreases in eGFR.
Patients with renal impairment: JARDIANCE was compared to placebo as add-on to pre-existing antidiabetic therapy over 52 weeks in 741 patients with type 2 diabetes and renal impairment. See 14 CLINICAL TRIALS, Use in Patients with Type 2 Diabetes and Renal Impairment.
The adverse reactions related to renal impairment, volume depletion and urinary tract and genital infections increased with worsening renal function. See 7 WARNINGS AND PRECAUTIONS, Renal.
Use of JARDIANCE was associated with increases in serum creatinine and decreases in eGFR, and patients with moderate renal impairment at baseline (eGFR 30 to <60 mL/min/1.73m2), displayed larger mean changes. In patients with moderate renal impairment, decreases in eGFR at Week 24 were -3.2 mL/min/1.73m2 versus 0.2 mL/min/1.73m2, for empagliflozin 25 mg and placebo, respectively, compared to the pooled 24 week clinical trial population, where eGFR decreased -1.4 mL/min/1.73m2 and -0.3 mL/min/1.73m2, for empagliflozin 25 mg and placebo, respectively.
Ketoacidosis: Cases of ketoacidosis, a serious life-threatening condition requiring urgent hospitalization, have been reported in patients with type 2 diabetes treated with JARDIANCE, or other SGLT2 inhibitors. Fatal cases of ketoacidosis have been reported in patients treated with JARDIANCE. JARDIANCE is not indicated, and should not be used, in patients with type 1 diabetes. In some cases, the presentation of the condition was atypical, with blood glucose levels only moderately elevated (<13.9 mmol/L (250 mg/dL)). See 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism.
In the EMPA-REG OUTCOME trial, serious adverse events of ketoacidosis occurred at a rate of 0.05/100 pt. yrs in the empagliflozin 10 mg group and 0.02/100 pt. yrs in the empagliflozin 25 mg group. One patient (0.02/100 pt. yrs with a non-serious ketoacidosis event was reported in the placebo group.
Cases of ketoacidosis have also been reported in patients without T2DM taking JARDIANCE.
Clinical Trial in Patients with Chronic Kidney Disease (EMPA-KIDNEY)
The EMPA-KIDNEY study included patients with chronic kidney disease (N = 6 609) treated with 10 mg empagliflozin or placebo. About 44% of the patients had type 2 diabetes mellitus. The most frequent adverse events in the EMPA-KIDNEY study while on treatment were gout (empagliflozin 7.0% vs placebo 8.0%), and acute kidney injury (empagliflozin 2.8% vs placebo 3.5%) which were more frequently reported in patients on placebo. The occurrence of lower limb amputations up to the final follow-up visit was reported in 28 (0.8%) patients in empagliflozin group and 19 (0.6%) patients in placebo, respectively, with toe amputation most commonly reported in both groups.
8.3 Less Common Clinical Trial Adverse Reactions (<1%)a
Infections and infestations: Balanitis, balanitis candida, candiduria, genital candidiasis, genital infection, genital infection fungal, genitourinary tract infection, penile infection, pyelonephritis, scrotal abscess, urinary tract infection bacterial, urogenital infection fungal, urosepsis, vaginitis bacterial, vulvovaginitis.
Investigations: Blood glucose decreased, blood creatinine increased, glomerular filtration rate decreased, hematocrit increased.
Metabolism and nutrition disorders: Dehydration, hypovolemia.
Renal and urinary disorders: Nocturia, oliguria, renal impairment, renal failure acute, dysuria.
Skin and subcutaneous disorders: Pruritus.
Vascular disorders: Hypotension, orthostatic hypotension.
aAdverse drug reactions (ADRs) were identified based on a comprehensive assessment of biological plausibility, mechanism of action, dose dependence in incidence rate, time of onset, seriousness, and consistency of findings across pivotal Phase 3 clinical studies.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Increases in serum creatinine and decreases in eGFR: In a pool of four-placebo-controlled trials, the mean change from baseline for eGFR (mL/min/1.73 m2) at week 24 was -0.55, -1.41 and - 0.32, for JARDIANCE 10 mg, 25 mg and placebo respectively. The mean change from baseline for creatinine (µmol/L) was 0.66, 1.28 and 0.35 for JARDIANCE 10 mg, 25 mg and placebo, respectively.
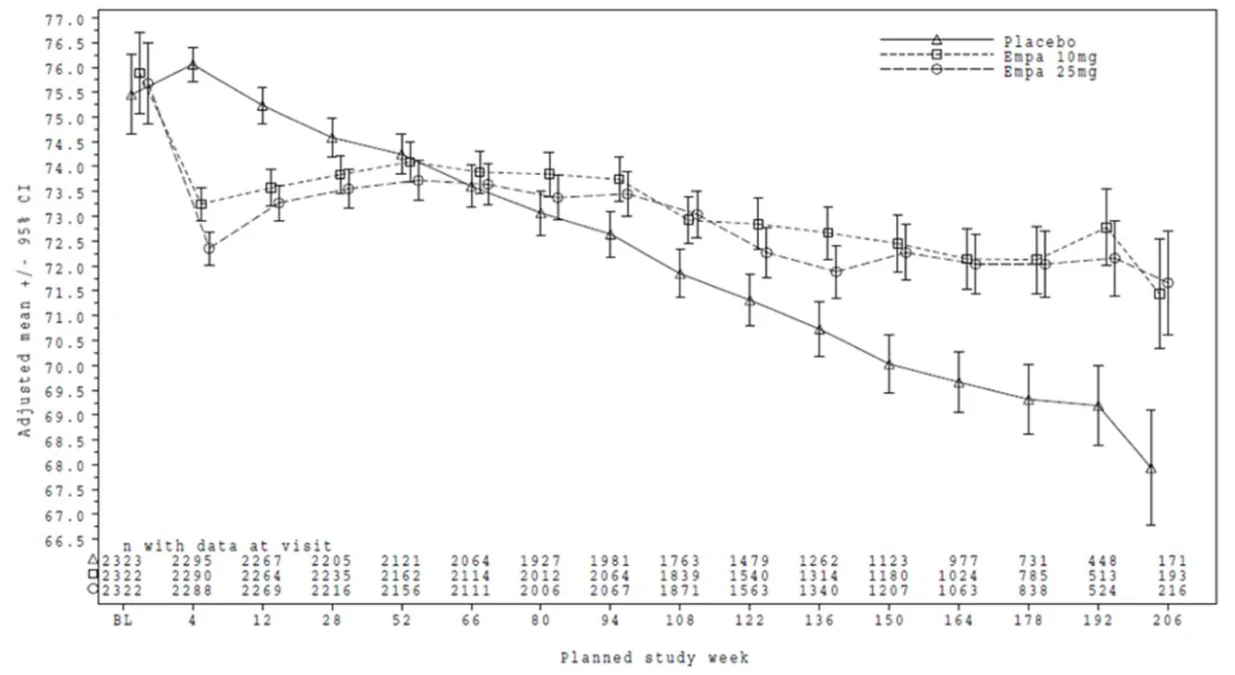
In the EMPA-REG OUTCOME trial, mean eGFR in the JARDIANCE 10 mg and 25 mg groups showed an initial decrease, and then stabilized, whereas mean eGFR in the placebo group showed a progressive decline (see Figure 1).
Figure 1: Time profile plot adjusted mean eGFR, individual empagliflozin doses vs placebo in the EMPA-REG OUTCOME trial
During treatment in the EMPEROR-Reduced trial, the JARDIANCE group had an initial decrease in eGFR at Week 4, which partially recovered at Week 12. Thereafter, a slower decline of eGFR was observed in the JARDIANCE group compared to the placebo group (see Figure 2).
Figure 2: Change in eGFR over time* in the EMPEROR-Reduced trial
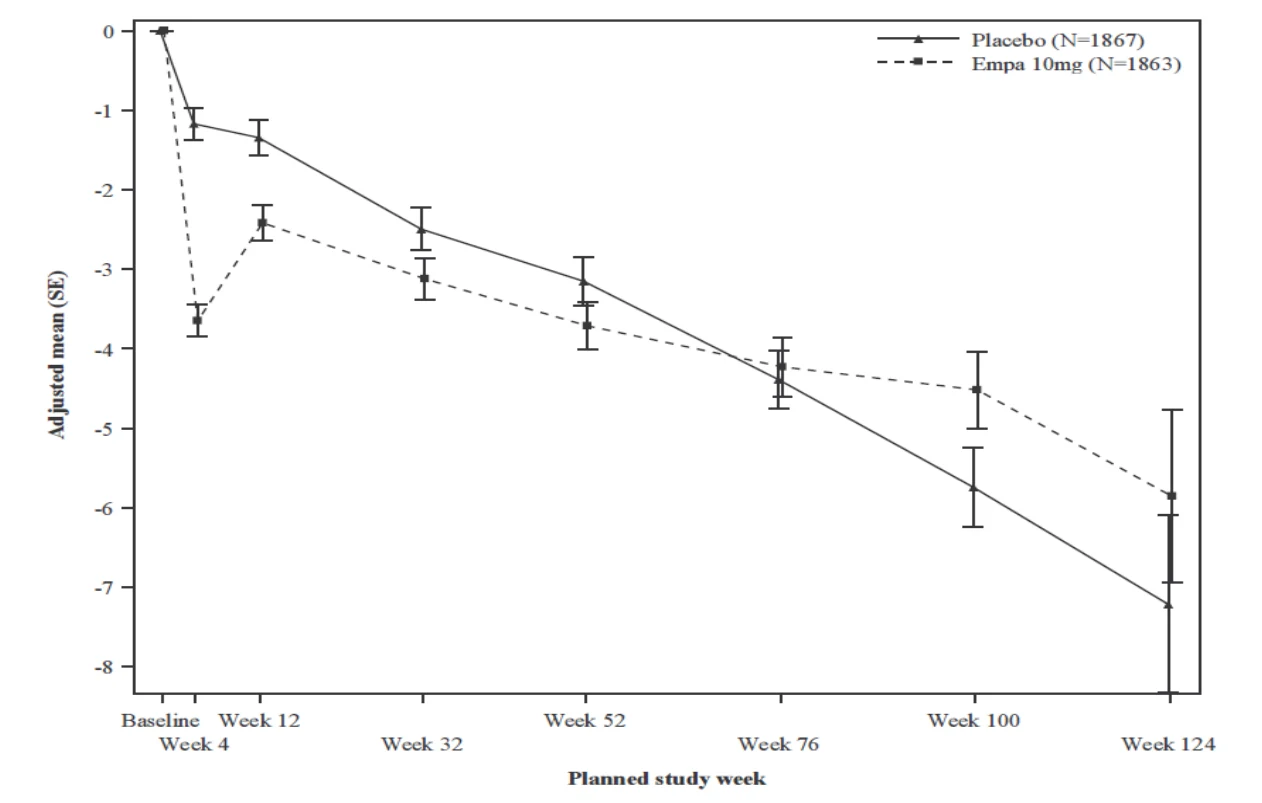
*eGFR (CKD-EPI) (mL/min/1.73m2) MMRM results over time - treated set. The number of patients who provided data at various time points (placebo, empagliflozin): at week 4 (1788, 1802); at week 12 (1729, 1756); at week 32 (1563, 1614); at week 52 (1211, 1228); at week 76 (801, 805); at week 100 (359, 386); and at week 124 (86, 91).
During treatment in the EMPEROR-Preserved trial, the JARDIANCE group had an initial decrease in eGFR at Week 4, which partially recovered at Week 12. Thereafter, a slower decline of eGFR was observed in the JARDIANCE group compared to the placebo group (see Figure 3).
Figure 3: Change in eGFR over time* EMPEROR-Preserved
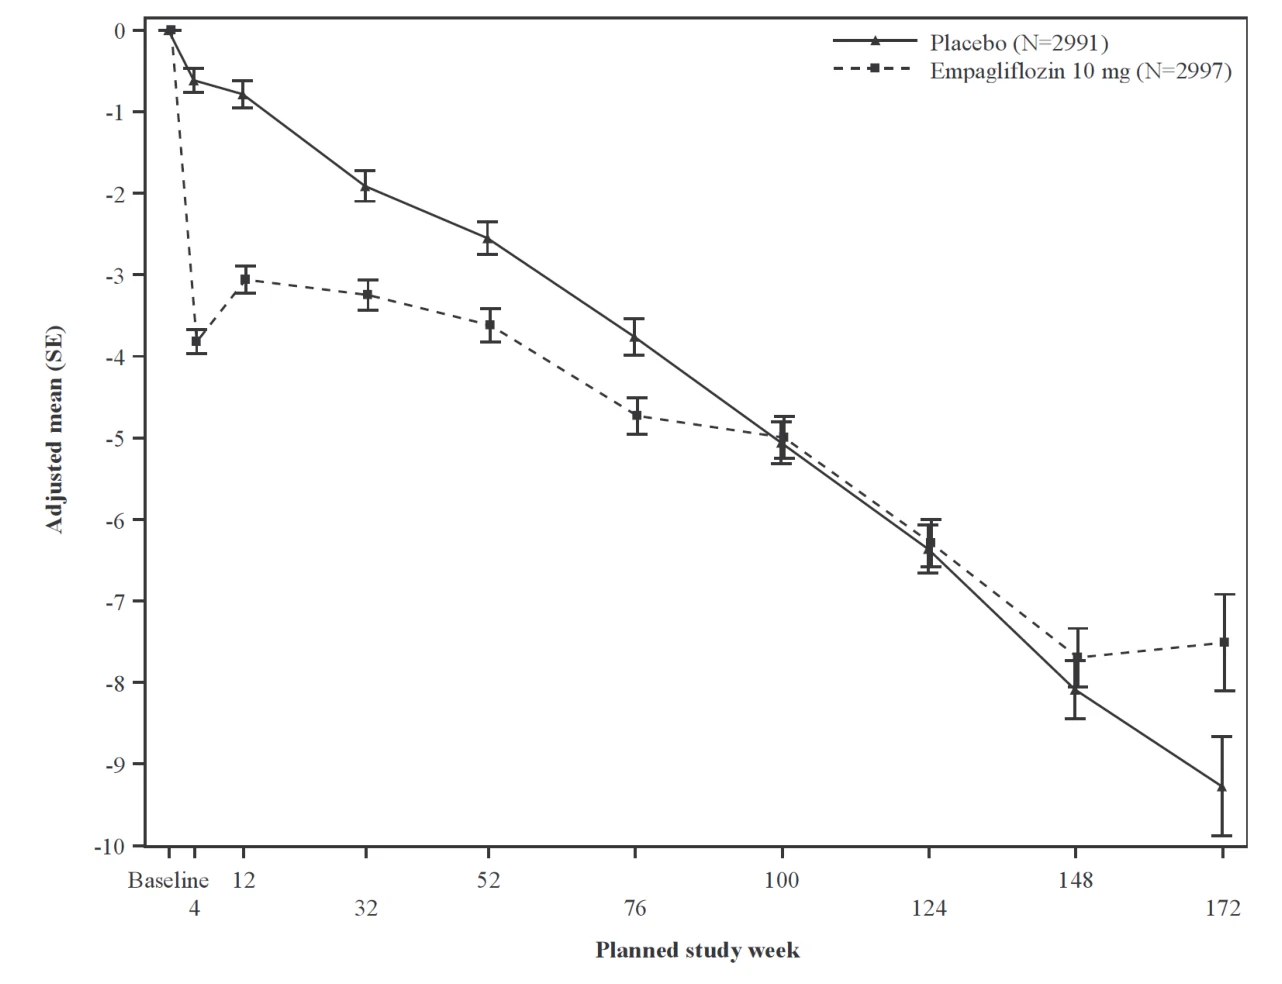
*eGFR (CKD-EPI) (mL/min/1.73m2) MMRM results over time - randomized set. The number of patients who provided data at various time points (placebo, empagliflozin): at week 4 (2910, 2931); at week 12 (2820, 2854); at week 32 (2590, 2629); at week 52 (2457, 2474); at week 76 (2123, 2114); at week 100 (1548, 1550); at week 124 (1091, 1122), at week 148 (695, 686), at week 172 (231, 243).
In the EMPA-KIDNEY study, there was an initial decrease in eGFR at 2 months in the JARDIANCE group, the adjusted mean change from baseline (mixed model with repeated measurements [MMRM] results) -2.76 mL/min/1.73 m2 (95% CI -2.95, -2.58) compared to -0.64 (95% CI -0.82, -0.45) in the placebo group. After the initial drop, a slower decline of eGFR was observed for JARDIANCE compared with placebo (see Figure 4).
Figure 4: Change in eGFR over time* EMPA-KIDNEY
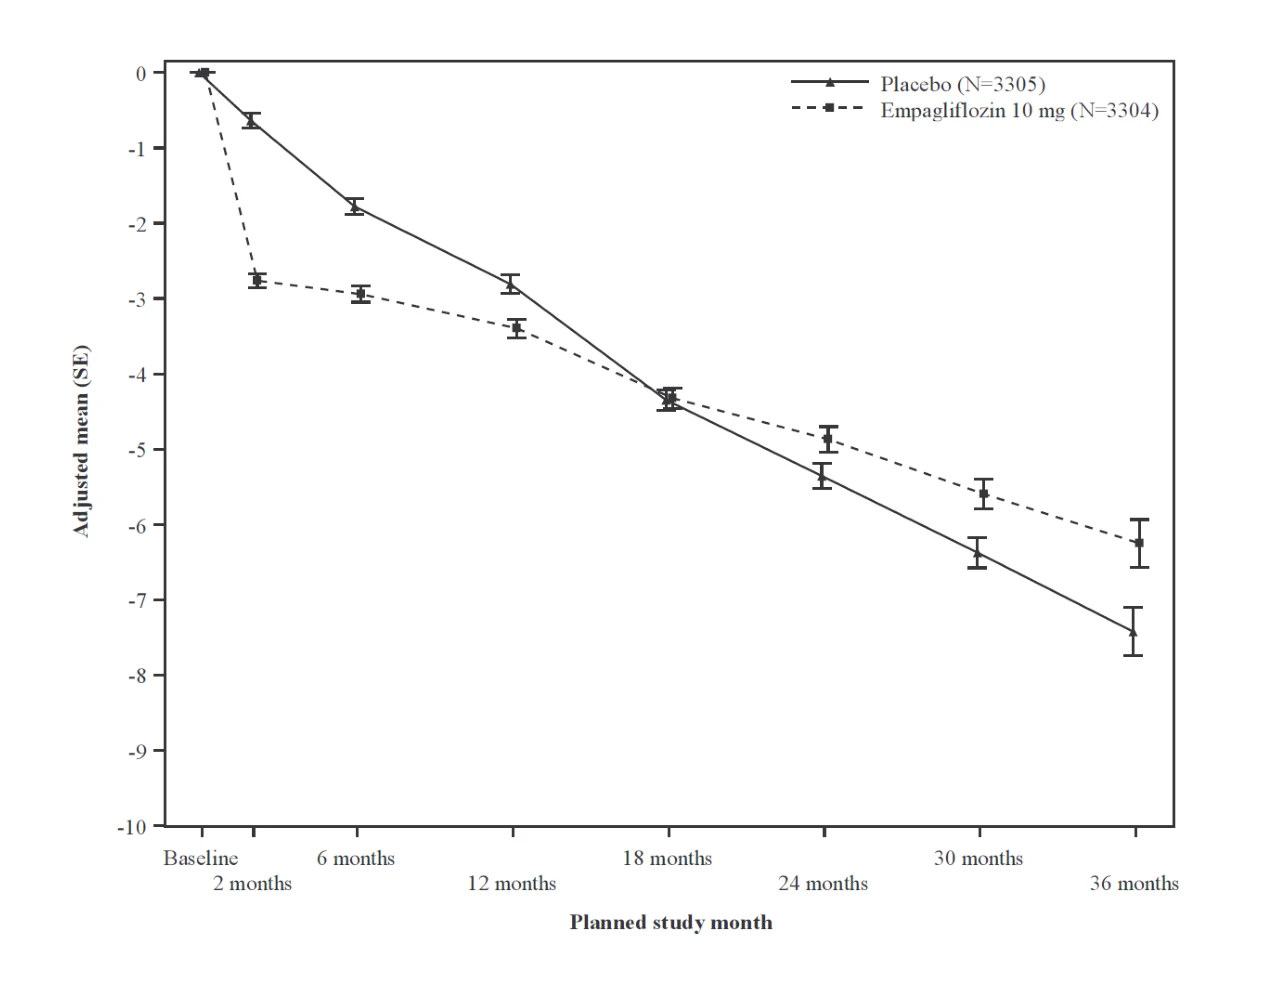
*eGFR (CKD-EPI) (mL/min/1.73m2) MMRM results over time - randomized set. The number of patients who provided data at scheduled time points (placebo, empagliflozin): Baseline (3184, 3190), 2 months (2911, 2875), 6 months (2861, 2809), 12 months (2821, 2820), 18 months (2621, 2605), 24 months (1723, 1752), 30 months (1204, 1239), 36 months (293, 298).
Electrolytes: The following statistically significant changes from baseline in serum electrolytes were observed during JARDIANCE treatment in the EMPA-REG OUTCOME trial (see Table 5).
Table 5: Placebo-Adjusted Mean Changes from Baseline in Electrolytes at Week 12 in EMPA-REG OUTCOME trial
| Analyte [normal range, unit] | Baseline, mean (SE) | Placebo-corrected change from baseline at Week 12, mean (95% CI) | p-value | ||||
|---|---|---|---|---|---|---|---|
| Sodium [135 – 145 mmol/L] | |||||||
| JARDIANCE 10 mg | 141.04 (0.06) | 0.46 (0.32, 0.60) | <0.0001 | ||||
| JARDIANCE 25 mg | 141.12 (0.07) | 0.55 (0.41, 0.69) | <0.0001 | ||||
| Potassium [3.5 – 5.0 mmol/L] | |||||||
| JARDIANCE 10 mg | 4.54 (0.01) | −0.02 (−0.04, 0.00) | 0.1034 | ||||
| JARDIANCE 25 mg | 4.54 (0.01) | −0.03 (−0.05, 0.00) | 0.0370 | ||||
| Magnesium [0.75 – 0.95 mmol/L] | |||||||
| JARDIANCE 10 mg | 0.77 (0.00) | 0.07 (0.07, 0.08) | <0.0001 | ||||
| JARDIANCE 25 mg | 0.78 (0.00) | 0.08 (0.08, 0.08) | <0.0001 | ||||
| Bicarbonate [24 – 30 mmol/L] | |||||||
| JARDIANCE 10 mg | 25.72 (0.07) | −0.35 (−0.50, −0.19) | <0.0001 | ||||
| JARDIANCE 25 mg | 25.76 (0.07) | −0.48 (−0.64, −0.33) | <0.0001 | ||||
| Phosphate [0.80 – 1.50 mmol/L] | |||||||
| JARDIANCE 10 mg | 1.16 (0.00) | 0.06 (0.05, 0.07) | <0.0001 | ||||
| JARDIANCE 25 mg | 1.16 (0.00) | 0.07 (0.06, 0.08) | <0.0001 | ||||
SE = standard error
ANCOVA for Week 12 includes baseline electrolyte and baseline HbA1c as linear covariates and baseline eGFR category, baseline BMI category, geographical region, and treatment as fixed effects.
The following shifts from normal range at baseline to below or above the normal range at worst value on treatment were reported in the treated set in EMPA-REG OUTCOME trial:
- Increases in serum sodium above the upper limit of normal occurred more frequently in patients receiving JARDIANCE than in those receiving placebo (6.8%, 6.7%, and 4.4% for JARDIANCE 10 mg, 25 mg, and placebo, respectively).
- Decreases in serum potassium below the lower limit of normal occurred slightly more frequently in patients receiving JARDIANCE than in those receiving placebo (4.8%, 4.4%, and 3.9% for JARDIANCE 10 mg, 25 mg, and placebo, respectively).
- Decreases in serum magnesium below the lower limit of normal occurred more frequently in patients receiving placebo (13.8%, 11.7%, and 35.0% for JARDIANCE 10 mg, 25 mg, and placebo, respectively), whilst increases in serum magnesium above the upper limit of normal occurred more frequently in patients receiving JARDIANCE than in those receiving placebo (2.0%, 2.7%, and 0.8% for JARDIANCE 10 mg, 25 mg, and placebo, respectively).
- Decreases of serum bicarbonate below the lower limit of normal occurred more frequently in patients receiving JARDIANCE than in those receiving placebo (43.0%, 44.2%, and 34.7% for JARDIANCE 10 mg, 25 mg, and placebo, respectively).
- Increases of serum phosphate above the upper limit of normal occurred more frequently in patients receiving JARDIANCE than in those receiving placebo (11.8%, 12.6% and 9.7% for JARDIANCE 10 mg, 25 mg, and placebo, respectively).
Elevations of serum phosphate above the normal range occurred more frequently in patients receiving empagliflozin than in those receiving placebo (1.5%, 1.9% and 0.4% for JARDIANCE 10 mg, 25 mg, and placebo, respectively) in a pool of four placebo-controlled trials.
Low density lipoprotein Cholesterol (LDL-C): In a pool of four placebo-controlled studies, LDL-C increases with JARDIANCE were observed. Placebo-corrected mean changes from baseline in LDL-C were 2.3 mg/dL (3.5%) for JARDIANCE 10 mg and 3.3 mg/dL (4.6%) for JARDIANCE 25 mg.
Uric Acid: In the EMPA-REG OUTCOME trial, statistically significant reductions in uric acid were observed at most time points during empagliflozin treatment. At week 12, the placebo-adjusted mean change from baseline was -0.36 mg/dL in both the empagliflozin 10 mg and 25 mg treatment groups (p<0.0001).
Hematocrit: In a pool of four placebo-controlled studies, hematocrit increases with JARDIANCE were observed. Mean changes from baseline in hematocrit were 2.3%, 2.6% and -0.8% for JARDIANCE 10 mg, 25 mg and placebo respectively. Elevations of hematocrit or hemoglobin above the normal ranges occurred more frequently in patients receiving empagliflozin than in those receiving placebo (2.5%, 3.2% and 0.5% for JARDIANCE 10 mg, 25 mg, and placebo, respectively).
In the EMPA-REG OUTCOME trial, statistically significant (p<0.0001) differences from placebo in mean change from baseline in hematocrit were observed from week 12 to week 206, inclusive (2.21% in the empagliflozin 10 mg group and 2.56% in the empagliflozin 25 mg group at week 12).
8.5 Post-Market Adverse Reactions
The following additional adverse reactions have been identified during post-approval use. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Hepatic/Biliary/Pancreatic: Acute pancreatitis
Infections and Infestations: Necrotizing fasciitis of the perineum (Fournier´s gangrene)
Metabolism: Ketoacidosis
Reproductive system and breast disorders: Acquired phimosis
Skin and Subcutaneous Tissue Disorders: Allergic skin reactions (e.g., rash, angioedema and urticaria)
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
In vitro assessment of interactions
In vitro data suggest that the primary route of metabolism of empagliflozin in humans is glucuronidation by the uridine 5'-diphospho-glucuronosyltransferases UGT2B7, UGT1A3, UGT1A8, and UGT1A9. The relative contribution of each isoform to empagliflozin clearance has not been determined.
Empagliflozin does not inhibit, inactivate, or induce CYP450 isoforms. Empagliflozin does not inhibit UGT1A1. Therefore, no effect of empagliflozin is anticipated on concomitantly administered drugs that are substrates of the major CYP450 isoforms or UGT1A1. The effect of UGT induction on empagliflozin exposure has not been evaluated.
Empagliflozin is a substrate for P-glycoprotein (P-gp) and breast cancer resistance protein (BCRP), but it does not inhibit these efflux transporters at therapeutic doses. Based on in vitro studies, JARDIANCE is considered unlikely to cause interactions with drugs that are P-gp substrates. Empagliflozin is a substrate of the human uptake transporters OAT3, OATP1B1, and OATP1B3, but not OAT1 and OCT2. JARDIANCE does not inhibit any of these human uptake transporters at clinically relevant plasma concentrations therefore, no effect of JARDIANCE is anticipated on concomitantly administered drugs that are substrates of these uptake transporters.
9.3 Drug-Behavioural Interactions
The effects of smoking, diet, and alcohol use on the pharmacokinetics of JARDIANCE have not been specifically studied.
No studies on the effects on the ability to drive and use machines have been performed. However, patients should be alerted to the elevated risk of adverse reactions related to reduced intravascular volume, such as postural hypotension, and to the risk of hypoglycemia when JARDIANCE is used in combination with insulin or an insulin secretagogue.
9.4 Drug-Drug Interactions
The drugs listed in the table below are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Effects of other co-administered drugs on JARDIANCE
In clinical studies, JARDIANCE pharmacokinetics were similar with and without co-administration of metformin, glimepiride, pioglitazone, sitagliptin, linagliptin, warfarin (CYP2C9 substrate), verapamil (P-gp inhibitor), ramipril, and simvastatin (CYP3A4, OATP1B1, OATP1B3 substrate) in healthy volunteers (see Table 6). Torasemide and hydrochlorothiazide had no clinically relevant effect on the pharmacokinetics of JARDIANCE in T2DM patients.
JARDIANCE overall exposure (AUC) increased by 59%, 35% and 53%, when co-administered with gemfibrozil (CYP2C8 and OATP1B1 inhibitor), rifampicin (OATP1B1 and 1B3 inhibitor) and probenecid (UGT, OAT3 inhibitor) respectively and were not considered clinically relevant. In subjects with normal renal function, co-administration of JARDIANCE with probenecid resulted in a 30% decrease in the fraction of JARDIANCE excreted in urine without any effect on 24-hour urinary glucose excretion. The relevance of this observation to patients with renal impairment is unknown.
The pharmacokinetic parameters of empagliflozin and linagliptin in patients administered empagliflozin and linagliptin in a fixed dose combination were not studied. The lack of pharmacokinetic interaction between linagliptin and empagliflozin was demonstrated in a drug-drug interaction study with linagliptin 5 mg and empagliflozin 50 mg.
Table 6: Effect of Other Co-Administered Drugs on Pharmacokinetics of JARDIANCE
| Co-administered drug | Source of Evidence | Dose of co-administered drug | Dose of JARDIANCE | Geometric Mean ratio (Ratio with/without co-administered drug) No effect=1.0 | Clinical comment | |||||
|---|---|---|---|---|---|---|---|---|---|---|
AUC (90% CI) | Cmax (90% CI) | |||||||||
| Metformin | CT | 1000 mg, bid, 5 days | 50 mg, qd, 5 days | 0.97 (0.92; 1.02) | 1.00 (0.89; 1.14) | No dose adjustment of JARDIANCE required | ||||
| Glimepiride | CT | 1 mg, single dose | 50 mg, qd, 6 days | 0.95 (0.92; 0.99) | 0.96 (0.88; 1.03) | No dose adjustment of JARDIANCE required | ||||
| Pioglitazone | CT | 45 mg, qd, 7 days | 50 mg, qd, 7 days | 1.00 (0.96; 1.05) | 0.93 (0.85; 1.03) | No dose adjustment of JARDIANCE required | ||||
| Warfarin | CT | 25 mg, single dose | 25 mg, qd, 7 days | 1.01 (0.97; 1.05) | 1.01 (0.90; 1.13) | No dose adjustment of JARDIANCE required | ||||
| Sitagliptin | CT | 100 mg, qd, 5 days | 50 mg, qd, 5 days | 1.10 (1.04; 1.17) | 1.08 (0.97; 1.19) | No dose adjustment of JARDIANCE required | ||||
| Linagliptin | CT | 5 mg, qd, 7 days | 50 mg, qd, 7 days | 1.02 (0.97; 1.07) | 0.88 (0.79; 0.99) | No dose adjustment of JARDIANCE required | ||||
| Hydrochloro-thiazide | CT | 25 mg, qd, 5 days | 25 mg, qd, 5 days | 1.07 (0.97; 1.18) | 1.03 (0.89; 1.19) | No dose adjustment of JARDIANCE required | ||||
| Torasemide | CT | 5 mg, qd, 5 days | 25 mg, qd, 5 days | 1.08 (1.00; 1.16) | 1.08 (0.98; 1.18) | No dose adjustment of JARDIANCE required | ||||
| Verapamil | CT | 120 mg, single dose | 25 mg, single dose | 1.03 (0.99; 1.07) | 0.92 (0.85; 1.00) | No dose adjustment of JARDIANCE required | ||||
| Ramipril | CT | 5 mg, qd, 5 days | 25 mg, qd, 5 days | 0.97 (0.93; 1.00) | 1.04 (0.98; 1.12) | No dose adjustment of JARDIANCE required | ||||
| Gemfibrozil | CT | 600 mg, bid, 5 days | 25 mg, single dose | 1.59 (1.52; 1.66) | 1.15 (1.06; 1.25) | No dose adjustment of JARDIANCE required | ||||
| Simvastatin | CT | 40 mg, single dose | 25 mg, single dose | 1.02 (0.99; 1.05) | 1.09 (0.97; 1.24) | No dose adjustment of JARDIANCE required | ||||
| Rifampicin | CT | 600 mg, single dose | 10 mg, single dose | 1.35 (1.30; 1.41) | 1.75 (1.60; 1.92) | No dose adjustment of JARDIANCE required | ||||
| Probenecid | CT | 500 mg, bid, 4 days | 10 mg, single dose | 1.53 (1.46; 1.61) | 1.26 (1.14; 1.39) | No dose adjustment of JARDIANCE required | ||||
For single dose, AUC is AUC0-∞; for multiple dose, AUC is AUCτ,ss
Legend: CT = Clinical Trial
Effects of JARDIANCE on other co-administered drugs
In clinical studies, JARDIANCE had no clinically relevant effect on the pharmacokinetics of metformin, glimepiride, pioglitazone, sitagliptin, linagliptin, warfarin (CYP2C9 substrate), digoxin (P-gp substrate), ramipril, simvastatin (CYP3A4, OATP1B1, OATP1B3 substrate), and oral contraceptives ethinyl estradiol and norgestrel (CYP3A4 substrate) when co-administered in healthy volunteers. JARDIANCE had no clinically relevant effect on the pharmacokinetics of torasemide and hydrochlorothiazide in patients with T2DM (see Table 7).
Table 7: Effect of JARDINACE on Pharmacokinetics of Other Co-Administered Drugs Co-administered drug
| Co-administered drug | Source of Evidence | Dose of co-administer ed drug | Dose of JARDIANCE | Geometric Mean ratio (Ratio with/without co-administered drug) No effect=1.0 | Clinical comment | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Co-administered drug | Source of Evidence | Dose of co-administer ed drug | Dose of JARDIANCE | Geometric Mean ratio (Ratio with/without co-administered drug) No effect=1.0 | Clinical comment | ||||||||||||
AUC (90% CI) | Cmax (90% CI) | ||||||||||||||||
AUC (90% CI) | Cmax (90% CI) | ||||||||||||||||
| Metformin | CT | 1000 mg, bid, 5 days | 50 mg, qd, 5 days | 1.01 (0.96; 1.06) | 1.04 (0.97; 1.11) | No dose adjustment required for metformin | |||||||||||
| Glimepiride | CT | 1 mg, single dose | 50 mg, qd, 6 days | 0.93 (0.86; 1.01) | 1.04 (0.89; 1.21) | No dose adjustment required for glimepiride | |||||||||||
| Pioglitazone | CT | 45 mg, qd, 7 days | 50 mg, qd, 7 days | 1.58 (1.48; 1.69) | 1.88 (1.66; 2.12) | No dose adjustment required for pioglitazone | |||||||||||
| CT | 45 mg, qd, 7 days | 10 mg, qd, 9d | 0.90 (0.78; 1.04) | 0.88 (0.74; 1.04) | |||||||||||||
| CT | 45 mg, qd, 7 days | 25 mg, qd, 9d | 0.89 (0.73; 1.09) | 0.90 (0.67; 1.22) | |||||||||||||
| CT | 45 mg, qd, 7 days | 50 mg, qd, 9d | 0.91 (0.77; 1.07) | 0.90 (0.71; 1.14) | |||||||||||||
Warfarin (R-warfarin) | CT | 25 mg, single dose | 25 mg, qd, 7 days | 0.98 (0.95; 1.02) | 0.98 (0.91; 1.05) | No dose adjustment required for warfarin | |||||||||||
| (S-warfarin) | CT | 0.96 (0.93; 0.98) | 0.99 (0.92; 1.06) | ||||||||||||||
| Sitagliptin | CT | 100 mg, qd, 5 days | 50 mg, qd, 5 days | 1.03 (0.99; 1.07) | 1.08 (1.01; 1.17) | No dose adjustment required for sitagliptin | |||||||||||
| Linagliptin | CT | 5 mg, qd, 7 days | 50 mg, qd, 7 days | 1.03 (0.96; 1.11) | 1.01 (0.87; 1.19) | No dose adjustment required for linagliptin | |||||||||||
| Digoxin | CT | 0.5 mg, single | 25 mg, qd, | 1.06 | 1.14 | No dose adjustment required for digoxin | |||||||||||
| dose | 8 days | (0.97; 1.16) | (0.99; 1.31) | ||||||||||||||
Microgynon® tablet | CT | Ethinyl-estradiol, 30 μg, qd, 7 days | 25 mg, qd, 7 days | 1.03 (0.98; 1.08) | 0.99 (0.93; 1.05) | No dose adjustment required for oral contraceptives | |||||||||||
| CT | Levonor-gestrel 150 μg, qd, 7 days | 1.02 (0.99; 1.05) | 1.06 (0.99; 1.13) | ||||||||||||||
| Hydrochloro-thiazide | CT | 25 mg, qd, 5 days | 25 mg, qd, 5 days | 0.96 (0.89; 1.04) | 1.02 (0.89; 1.17) | No dose adjustment required for hydrochlorothiazide | |||||||||||
| Torasemide | CT | 5 mg, qd, 5 days | 25 mg, qd, 5 days | 1.01 (0.99; 1.04) | 1.04 (0.94; 1.16) | No dose adjustment required for torasemide | |||||||||||
| CT | M1 meta-bolite | 1.04 (1.00; 1.09) | 1.03 (0.94; 1.12) | ||||||||||||||
| CT | M3 meta-bolite | 1.03 (0.96; 1.11) | 1.02 (0.98; 1.07) | ||||||||||||||
| Ramipril | CT | 5 mg, qd, 5 days | 25 mg, qd, 5 days | 1.08 (1.01; 1.16) | 1.04 (0.90; 1.20) | No dose adjustment required for ramipril | |||||||||||
| CT | Rami-prilat | 0.99 (0.96; 1.01) | 0.98 (0.93; 1.04) | ||||||||||||||
| Simvastatin | CT | 40 mg, single dose | 25 mg, single dose | 1.01 (0.80; 1.28) | 0.97 (0.76; 1.24) | No dose adjustment required for simvastatin | |||||||||||
| CT | Simv- astatin acid | 1.05 (0.90; 1.22) | 0.97 (0.85; 1.11) | ||||||||||||||
For single dose, AUC is AUC0-∞; for multiple dose, AUC is AUCτ,ss
Legend:CT = Clinical Trial
Pharmacodynamic interactions
Diuretics: JARDIANCE may add to the diuretic effect of loop diuretics and may increase the risk of dehydration and hypotension. Caution is recommended when JARDIANCE is co-administered with diuretics; particularly loop diuretics. See 4.1 Dosing Considerations, Diuretics and 7 WARNINGS AND PRECAUTIONS, Renal.
Pharmacokinetic Interactions
Lithium: Concomitant use of JARDIANCE or other SGLT2 inhibitors with lithium may decrease blood lithium levels through increased renal lithium elimination. Therefore, serum lithium concentration should be monitored more frequently with JARDIANCE initiation or following dose changes or following discontinuation. Patient should be referred to the lithium prescribing doctor to monitor serum lithium concentration so as to maintain clinical supervision as required during treatment.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Due to its mechanism of action, patients taking JARDIANCE will test positive for glucose in their urine. Monitoring glycemic control with 1,5-AG assay is not recommended as measurements of 1,5AG are unreliable in assessing glycemic control in patients taking SGLT2 inhibitors. Use alternative methods to monitor glycemic control.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Sodium-glucose co-transporter 2 (SGLT2) is the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. SGLT2 is selectively expressed in the kidney. Empagliflozin is an inhibitor of SGLT2. In patients with type 2 diabetes mellitus (T2DM), by inhibiting SGLT2, empagliflozin improves both fasting and post-prandial plasma glucose levels by reducing renal reabsorption of filtered glucose and lowering the renal threshold for glucose, and thereby increasing urinary glucose excretion. The amount of glucose removed by the kidney through this mechanism is dependent upon the blood glucose concentration and GFR. Empagliflozin does not impair normal endogenous glucose production in response to hypoglycemia. Empagliflozin acts independently of insulin secretion and insulin action.
Urinary glucose excretion (glucuresis) induced by empagliflozin is associated with caloric loss and reduction in weight. Inhibition of glucose and sodium co-transport by empagliflozin is also associated with mild diuresis and transient natriuresis.
Empagliflozin also reduces sodium reabsorption and increases the delivery of sodium to the distal tubule. This may influence several physiological functions including, but not restricted to, increasing tubuloglomerular feedback and reducing intraglomerular pressure, lowering pre- and afterload of the heart, improving cardiac remodelling, improving diastolic function, and reducing left ventricular wall stress as evidenced by lower NT-proBNP values. Some of these mechanisms may preserve kidney function and structure.
Secondary effects of SGLT2 inhibition with empagliflozin also include an increase in hematocrit.
The cardiovascular and renal benefits of empagliflozin are not solely dependent on the blood glucose lowering effect and are not limited to patients with diabetes.
10.2 Pharmacodynamics
Urinary Glucose Excretion: In patients with type 2 diabetes, urinary glucose excretion increased immediately following a dose of JARDIANCE and was maintained at the end of a 4-week treatment period averaging at approximately 64 grams per day with 10 mg empagliflozin and 78 grams per day with 25 mg JARDIANCE once daily.
Urinary Volume: In a 5-day study, mean 24-hour urine volume increase from baseline was 341 mL on Day 1 and 135 mL on Day 5 of empagliflozin 25 mg treatment.
Cardiac Electrophysiology: In a randomized, double-blind, placebo-controlled, active-comparator, crossover study, 30 healthy subjects were administered a single oral dose of empagliflozin 25 mg, empagliflozin 200 mg (8 times the maximum recommended dose), moxifloxacin, and placebo. The empagliflozin 25 mg and 200 mg treatments were not observed to affect the QTc interval, the QRS duration, the PR interval, or heart rate.
10.3 Pharmacokinetics
Table 8: Summary of JARDIANCE Pharmacokinetic Parameters in T2DM Patients
| Single dose mean | Cmax,ss (nmol/L) mean (% CV) | Tmax,ss (h) (% CV) | t½ (h) | AUC0-∞τ,ss (nmol•h/L) (% CV) | CL/Fss (mL/min) (% CV) | Vd |
| 25 mg qd | 687 (18.4) | 1.5 (49.9) | -- | 4740 (21.2) | 203 (21.4) | -- |
| 10 mg qd | 259 (24.8) | 1.72 (42.5) | -- | 1870 (15.9) | 202 (15.9) | -- |
Absorption: After oral administration in patients with T2DM, empagliflozin was rapidly absorbed with peak plasma concentrations occurring at a median Tmax 1.5 h post-dose. Thereafter, plasma concentrations declined in a biphasic manner with a rapid distribution phase and a relatively slow terminal elimination phase. The steady state mean plasma AUC and Cmax were 1870 nmol•h/L and 259 nmol/L, respectively, with 10 mg empagliflozin once daily treatment, and 4740 nmol•h/L and 687 nmol/L, respectively, with 25 mg empagliflozin once daily treatment. Population pharmacokinetic analysis results suggested that empagliflozin exposure (AUC) in T2DM patients is approximately 33% higher for doses less than 400 mg compared to healthy volunteers.
Administration of 25 mg empagliflozin after intake of a high-fat and high calorie meal resulted in slightly lower exposure; AUC decreased by approximately 16% and Cmax decreased by approximately 37%, compared to fasted condition. The observed effect of food on empagliflozin pharmacokinetics was not considered clinically relevant and empagliflozin may be administered with or without food.
Distribution: The apparent steady-state volume of distribution was estimated to be 73.8 L, based on a population pharmacokinetic analysis. Following administration of an oral [14C]-empagliflozin solution to healthy subjects, the red blood cell partitioning was approximately 36.8% and plasma protein binding was 86.2%, mainly to albumin. Protein binding is independent of plasma empagliflozin concentration. There were no relevant changes in protein binding of empagliflozin due to renal or hepatic impairment.
Metabolism: No major metabolites of empagliflozin were detected in human plasma and the most abundant metabolites were three glucuronide conjugates (2-O-, 3-O-, and 6-O-glucuronide). Systemic exposure of each metabolite was less than 10% of total drug-related material. In vitro studies suggested that the primary route of metabolism of empagliflozin in humans is glucuronidation by the uridine 5'-diphospho-glucuronosyltransferases UGT2B7, UGT1A3, UGT1A8, and UGT1A9.
Elimination: The apparent terminal elimination half-life of empagliflozin was estimated to be 12.4h and apparent oral clearance was 10.6 L/h based on the population pharmacokinetic analysis. Following administration of an oral [14C]-empagliflozin solution to healthy subjects, approximately 95.6% of the drug related radioactivity was eliminated in faeces (41.2%) or urine (54.4%). The majority of drug related radioactivity recovered in faeces was unchanged parent drug and approximately half of drug related radioactivity excreted in urine was unchanged parent drug.
Dose Proportionality, Accumulation and Steady-state Pharmacokinetics
Systemic exposure of multiple dose empagliflozin in male and female diabetic patients increased in a dose-proportional manner between the doses of 2.5 mg to 100 mg qd for both AUC and Cmax. The single-dose and steady-state pharmacokinetics parameters of empagliflozin were similar suggesting linear pharmacokinetics with respect to time.
With once-daily dosing, steady-state plasma concentrations of empagliflozin were reached by the fifth dose. Consistent with half-life, up to 23% accumulation with respect to plasma AUC, was observed at steady state.
Special Populations and Conditions
- Pediatrics (<18 years of age): Studies characterizing the pharmacokinetics of empagliflozin in pediatric patients have not been performed.
- Geriatrics (≥65 years of age): Age did not have a clinically meaningful impact on the pharmacokinetics of empagliflozin based on the population pharmacokinetic analysis. The changes in AUCτ,ss were decreased by 8.06% for patients 35 years of age and increased by 6.43%, and 10.1% for patients 65 and 75 years of age, respectively, compared to patients with an age of 50 years and assuming normal renal function (eGFR 100 mL/min/1.73 m2).
- Sex: Gender had no clinically relevant effect on the pharmacokinetics of empagliflozin based on the population pharmacokinetic analysis. AUCτ,ss in females was 12.8% higher compared to males.
- Genetic Polymorphism: The influence of UGT1A9 and other UGT genetic polymorphisms on the pharmacokinetics of JARDIANCE have not been evaluated.
- Ethnic Origin: Based on the population pharmacokinetic analysis, AUC was estimated to be 13.5% higher in Asian patients with a BMI of 25 kg/m2 compared to non-Asian patients with a BMI of 25 kg/m2. These changes are not considered clinically meaningful.
Hepatic Insufficiency: In subjects with mild, moderate, and severe hepatic impairment according to the Child-Pugh classification, AUC of empagliflozin increased approximately by 23%, 47%, and 75% and Cmax by approximately 4%, 23%, and 48%, respectively, compared to subjects
- with normal hepatic function. Experience in patients with severe hepatic impairment is limited.
- Renal Insufficiency: In patients with mild (eGFR: 60 - <90 mL/min/1.73m2), moderate (eGFR: 30 - <60 mL/min/1.73m2), severe (eGFR: <30 mL/min/1.73m2) renal impairment and patients with kidney failure/ESRD patients, AUC of empagliflozin increased by approximately 18%, 20%, 66%, and 48%, respectively, compared to subjects with normal renal function. Peak plasma levels of empagliflozin were similar in subjects with moderate renal impairment and kidney failure/ESRD compared to patients with normal renal function. Peak plasma levels of empagliflozin were roughly 20% higher in subjects with mild and severe renal impairment as compared to subjects with normal renal function. Population pharmacokinetic analysis showed that the apparent oral clearance of empagliflozin decreased with a decrease in eGFR leading to an increase in drug exposure. However, the fraction of empagliflozin that was excreted unchanged in urine, and urinary glucose excretion, declined with decrease in eGFR.
- Obesity: BMI had no clinically relevant effect on the pharmacokinetics of empagliflozin based on the population pharmacokinetic analysis. The changes in AUCτ,ss were increased by 7.48% for patients with BMI of 20 kg/m2 and decreased by 5.82%, 10.4%, and 17.3% for patients with BMI of 30, 35 and 40 kg/m2, respectively, compared to patients with a BMI of 25 kg/m2.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15-30°C). Do not flush medicines down the toilet or sink. Bring unused and expired prescription drugs, over-the-counter medications and natural health products to your local pharmacist for proper disposal.
12 SPECIAL HANDLING INSTRUCTIONS
Store in a safe place and out of the reach of children.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Empagliflozin
Chemical name: (1S)-1,5-anhydro-1-(4-chloro-3-{4-[(3S)-tetrahydrofuran-3yloxy]benzyl}phenyl)-D-glucitol
Molecular formula and molecular mass: C23H27ClO7; 450.91 g/mol
Structural formula:
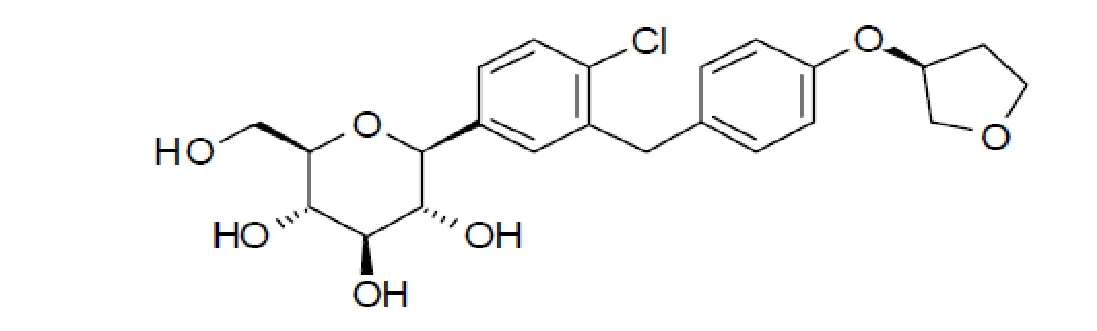
Physicochemical properties: Empagliflozin is a white to yellowish, not hygroscopic solid powder, very slightly soluble in water (0.28 mg/mL), sparingly soluble in methanol (33.4 mg/mL), slightly soluble in ethanol (8.0 mg/mL), slightly soluble in acetonitrile (2.6 mg/mL), slightly soluble in 50% methanol in water (6.4 mg/mL), soluble in 50% acetonitrile in water (68 mg/mL), and practically insoluble in toluene (<0.001 mg/mL).
Solubility data of empagliflozin in aqueous media at room temperature:
Water (pH 8.6) 0.28 mg/mL;
0.1N HCl (pH 1.1) 0.30 mg/mL;
McIlvaine buffer pH 4.0 (pH 4.1) 0.21 mg/mL;
McIlvaine buffer pH 7.4 (pH 7.5) 0.14 mg/mL.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Type 2 diabetes mellitus (T2DM)
Table 9: Summary of patient demographics for clinical trials in patients with T2DM
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) randomized/ treated | Mean age (Range) | Sex (%M/F) | ||||||
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) randomized/ treated | Mean age (Range) | Sex (%M/F) | ||||||
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) randomized/ treated | Mean age (Range) | Sex (%M/F) | ||||||
| Monotherapy | |||||||||||
| 1245.20 | Randomized, multicentre, double-blind, active and placebo-controlled parallel group | Empagliflozin 10 mg or 25 mg vs placebo or vs. Sitagliptin 100 mg Tablets, orally, once daily Run-in: 2 weeks placebo open-label Randomized treatment: 24 weeks Extension: up to 76 weeks Follow-up: 1 week | Total: 986/986 Empagliflozin: 10 mg: 224/224 25 mg: 224/224 Placebo: 228/228 Sitagliptin: 223/223 | Empagliflozin: 10 mg: 56.2 (11.6) 25 mg: 53.8 (11.6) Placebo: 54.6 (10.9) Sitagliptin: 55.1 (9.9) | Empagliflozin: 10 mg: 63/37 25 mg: 65/35 Placebo: 54/46 Sitagliptin: 63/37 | ||||||
| Add-on Combination Therapy with Metformin | |||||||||||
| 1245.23 | Randomized, multicentre, double-blind, placebo-controlled, parallel group | Empagliflozin 10 mg, 25 mg, placebo tablets, Tablets, orally, once daily Run-in: 2 weeks placebo open-label Randomized Treatment: 24 weeks Extension: up to 76 weeks Follow-up: 1 week | Total: 707/706 Empagliflozin: 10 mg: 217/217 25 mg: 214/213 Placebo: 207/207 | Empagliflozin: 10 mg: 55.5 (9.9) 25 mg: 55.6 (10.2) Placebo: 56.0 (9.7) | Empagliflozin: 10 mg: 58/42 25 mg: 56/44 Placebo: 56/44 | ||||||
| 1245.28 | Randomized, multicentre, double blind, active-controlled, parallel-group | Empagliflozin 25 mg Glimepiride (Amaryl®):1 to 4 mg Placebo (run-in period) tablets, oral, once | Total: 1549/1545 (until interim database lock) | ||||||||
daily Run-in: 2 weeks Treatment: 104 weeks Extension: 104 weeks Follow-up: 4 weeks | Empagliflozin: 25 mg: 769/765 Glimepiride 1 to 4 mg: 780/780 | Empagliflozin: 25 mg: 56.2 (10.3) Glimepiride: 55.7 (10.4) | Empagliflozin: 25 mg: 56/43 Glimepiride: 54/46 | ||||||||
| Add-on Combination Therapy with Metformin and a Sulfonylurea | |||||||||||
| 1245.23+ | Randomized, multicentre, double-blind, placebo-controlled, parallel group | Empagliflozin 10 mg, 25 mg, placebo tablets, orally, once daily Run-in: 2 weeks placebo open-label Randomized treatment: 24 weeks Extension: up to 76 weeks Follow-up: 1 week | Total: 669/666 Empagliflozin: 10 mg: 226/225 25 mg: 218/216 Placebo: 225/225 | Empagliflozin: 10 mg: 57.0 (9.2) 25 mg: 57.4 (9.3) Placebo: 56.9 (9.2) | Empagliflozin: 10 mg: 50/50 25 mg: 53/47 Placebo: 50/50 | ||||||
| Add-on Combination Therapy with Pioglitazone | |||||||||||
| 1245.19 | Randomized, multicentre, double-blind, placebo-controlled parallel group | Empagliflozin 10mg or 25 mg vs placebo Tablets, orally, once daily Run-in: 2 weeks placebo open-label Randomized treatment: 24 weeks Extension: up to 76 weeks Follow-up: 1 week | Total 499/498 patients Empagliflozin 10 mg: 165/165 25 mg: 168/168 Placebo: 166/165 | Empagliflozin: 10 mg: 54.7 (9.9) 25 mg: 54.2 (8.9) Placebo: 54.6 (10.5) | Empagliflozin: 10 mg: 50/50 25 mg: 50/50 Placebo: 44/56 | ||||||
| Add-on Combination Therapy with MDI of Basal and Prandial Insulin (with or without Metformin) | |||||||||||
| 1245.49 | Randomized, multicentre, double-blind, placebo-controlled, parallel group | E 10mg, 25 mg Placebo tablets, oral, once daily Randomized treatment: 52 weeks Week 1-18 &41-52 - | Total: 566/563 Empagliflozin: 10 mg: 187/186 25 mg: 190/189 Placebo: 189/188 | Empagliflozin: 10 mg: 56.7 (8.7) 25 mg: 58.0 (9.4) Placebo: 55.3 (10.1) | Empagliflozin: 10 mg: 52/48 25 mg: 44/56 Placebo: 40/60 | ||||||
stable insulin dose Week 19-40, treat-to-target insulin dose | |||||||||||
| Patients With Type 2 Diabetes and Established Cardiovascular Disease | |||||||||||
| 1245.25 | Randomized, multicentre, double-blind, placebo-controlled | E 10mg, 25 mg Placebo tablets, oral, once daily + standard of care treatment: event-driven follow up: about 3 years | Total: 7028/7020 Empagliflozin: 10 mg: 2347/2345 25 mg: 2344/2342 Placebo: 2337/2333 | Empagliflozin: 10 mg: 63.0 (8.6) 25 mg: 63.2 (8.6) Placebo: 63.2 (8.8) | Empagliflozin: 10 mg: 70/30 25 mg: 72/28 Placebo: 72/28 | ||||||
| Patients with T2DM Inadequately Controlled on Linagliptin and Metformin (GLYXAMBI) | |||||||||||
| 1275.9 | GLYXAMBI 10/5 + metformin GLYXAMBI 25/5 + metformin Lina 5 + metformin Tablets, orally, once daily treatment: 24-week | n = 109 n = 110 n = 108 | 54.3 (9.6) 55.4 (9.9) 55.9 (9.7) | 61/39 65/35 56/44 | |||||||
JARDIANCE (empagliflozin) was studied as monotherapy and in combination with other antidiabetic medications, including metformin, metformin and sulfonylurea, pioglitazone, linagliptin or basal or prandial insulin (with or without metformin) (see Table 9). JARDIANCE was also studied in patients with type 2 diabetes and cardiovascular disease and in patients with different degrees of renal impairment.
Treatment with JARDIANCE as monotherapy and in combination with metformin, glimepiride, pioglitazone, linagliptin, or basal and prandial insulin (with or without metformin) produced clinically relevant and statistically significant improvements in mean change from baseline at Week 24 in HbA1c, fasting plasma glucose (FPG), blood pressure and 2-hour post-prandial glucose (where measured), compared to placebo or control. In the double-blind placebo-controlled extension of these studies, reductions of HbA1c and body weight were sustained up to Week 76. HbA1c reductions were seen across subgroups including gender, age, race, duration of disease, baseline BMI and patients with high baseline HbA1c >10%.
Monotherapy (Study 1245.20)
The efficacy and safety of JARDIANCE as monotherapy was evaluated in a double-blind, placebo- and active-controlled study of 24 weeks duration in treatment-naïve patients. As shown in Table 10, statistically significant reductions (p<0.0001) in HbA1c and body weight relative to placebo were observed with JARDIANCE 10 mg and 25 mg at Week 24. Statistically significant changes from baseline in systolic blood pressure (SBP, mmHg) of -2.9, -3.7, and -0.3 were observed for JARDIANCE 10 mg, 25 mg, and placebo, respectively.
Table 10: Results at Week 24 (LOCF) in a Placebo-Controlled Study of JARDIANCE Monotherapy in Patients with Type 2 Diabetes
| Efficacy Parameter | Placebo | JARDIANCE 10 mg | JARDIANCE 25 mg | Sitagliptina | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| N | 228 | 224 | 224 | 223 | ||||||||
| HbA1c (%) | ||||||||||||
| Baseline (mean) | 7.91 | 7.87 | 7.86 | 7.85 | ||||||||
| Change from baseline1 | 0.08 | -0.66 | -0.78 | -0.66 | ||||||||
| Difference from placebo1 (97.5% CI) | -0.74* (-0.90, -0.57) | -0.85* (-1.01, -0.69) | -0.73 (-0.88, -0.59)2 | |||||||||
| N | 208 | 204 | 202 | 200 | ||||||||
| Patients3 (%) achieving HbA1c <7% | 15.4 | 39.3 | 46.0 | 41.7 | ||||||||
| N | 228 | 224 | 224 | 223 | ||||||||
| Body Weight (kg) | ||||||||||||
| Baseline (mean) | 78.23 | 78.35 | 77.80 | 79.31 | ||||||||
| Change from baseline1 | -0.33 | -2.26 | -2.48 | 0.18 | ||||||||
| Difference from placebo1 (97.5% CI) | -1.93* (-2.48, -1.38) | -2.15* (-2.70,-1.60) | 0.52 (-0.04, 1.00)2 | |||||||||
a Sitagliptin 100 mg per day
1 mean adjusted for baseline value
2 95% CI
3 The HbA1c responder analyses were performed on FAS with a noncompleters considered failure (NCF) imputation approach by determining the percentage of patients that fulfil responder criteria.
*<0.0001
The first measurement of HbA1c after initiation of the treatment period occurred at week 6 and resulted in significant reductions in HbA1c with JARDIANCE 10 mg and 25 mg vs placebo (-0.5% and -0.55% respectively; p<0.0001) which were sustained over time.
Add-on Therapy with Metformin (Study 1245.23)
A double-blind, placebo-controlled study of 24 weeks duration was conducted to evaluate the efficacy and safety of JARDIANCE in patients not sufficiently treated with metformin. As shown in Table 11, statistically significant (p<0.0001) reductions in HbA1c, FPG and body weight relative to placebo were observed with JARDIANCE 10 mg and 25 mg at Week 24.
Table 11: Results of a 24-Week (LOCF) Placebo-Controlled Study of JARDIANCE in Add-on Combination with Metformin
| Efficacy Parameter | Placebo | JARDIANCE 10 mg | JARDIANCE 25 mg |
|---|---|---|---|
| N | 207 | 217 | 213 |
| HbA1c (%) | |||
| Baseline (mean) | 7.90 | 7.94 | 7.86 |
| Change from baseline1 | -0.13 | -0.70 | -0.77 |
| Difference from placebo1 (97.5% CI) | -0.57* (-0.72, -0.42) | -0.64* (-0.79, -0.48) | |
| N | 184 | 199 | 191 |
| Patients2 (%) achieving HbA1c <7% | 16.4 | 40.6 | 40.8 |
| N | 207 | 216 | 213 |
| FPG (mmol/L) | |||
| Baseline (mean) | 8.66 | 8.58 | 8.29 |
| Change from baseline1 | 0.35 | -1.11 | -1.24 |
| Difference from placebo1 (95% CI) | -1.47 (-1.74, -1.20) | -1.59 (-1.86, -1.32) | |
| N | 207 | 217 | 213 |
| Body Weight (kg) | |||
| Baseline (mean) | 79.73 | 81.59 | 82.21 |
| Change from baseline1 | -0.45 | -2.08 | -2.46 |
| Difference from placebo1(97.5% CI) | -1.63* (-2.17, -1.08) | -2.01* (-2.56, -1.46) | |
1 mean adjusted for baseline value
2 The HbA1c responder analyses were performed on FAS with a noncompleters considered failure (NCF) imputation approach by determining the percentage of patients that fulfil responder criteria.
*p-value <0.0001
The first measurement of HbA1c after initiation of the treatment period occurred at week 6 and resulted in significant reductions in HbA1c with JARDIANCE 10 mg and 25 mg vs placebo (-0.46% and -0.51% respectively; p<0.0001) which were sustained over time.
Add-on Therapy with Metformin - Active-Controlled Study versus Glimepiride (Study 1245.28)
In a study comparing the efficacy and safety of JARDIANCE 25 mg versus glimepiride (4 mg) in patients with inadequate glycemic control on metformin alone, as shown in Table 12, JARDIANCE daily resulted in a statistically significant (p<0.0001) reduction in HbA1c, FPG and body weight at Week 104. Systolic blood pressure (SBP, mmHg) change from baseline was -3.1, and 2.5 for JARDIANCE 25 mg, and glimepiride respectively.
Treatment with JARDIANCE resulted in statistically significantly lower proportion of patients with hypoglycemic events compared to glimepiride (2.5% for JARDIANCE 25 mg, 24.2% for glimepiride, p<0.0001).
Table 12: Results at 104-Week (LOCF) in an Active-Controlled Study Comparing JARDIANCE to Glimepiride as Add-on to Metformin
| Efficacy Parameter | JARDIANCE 25 mg | Glimepiride | ||||
|---|---|---|---|---|---|---|
| N | 765 | 780 | ||||
| HbA1c (%) | ||||||
| Baseline (mean) | 7.92 | 7.92 | ||||
| Change from baseline1 | -0.66 | -0.55 | ||||
| Difference from glimepiride1 (97.5% CI) | -0.11*(-0.20, -0.01) | |||||
| N | 690 | 715 | ||||
| Patients2 (%) achieving HbA1c <7% | 37.5 | 32.6 | ||||
| N | 764 | 779 | ||||
| FPG (mmol/L) | ||||||
| Baseline (mean) | 8.33 | 8.32 | ||||
| Change from baseline1 | -0.85 | -0.17 | ||||
| Difference from glimepiride1 (95% CI) | -0.69 (-0.86, -0.52) | |||||
| N | 765 | 780 | ||||
| Body Weight (kg) | ||||||
| Baseline (mean) | 82.52 | 83.03 | ||||
| Change from baseline1 | -3.12 | 1.34 | ||||
| Difference from glimepiride1 (97.5% CI) | -4.46** (-4.87, -4.05) | |||||
1 mean adjusted for baseline value
2 The HbA1c responder analyses were performed on FAS with a noncompleters considered failure (NCF) imputation approach by determining the percentage of patients that fulfil responder criteria.
* p<0.0001 for non-inferiority, p<0.0153 for superiority
** p-value <0.0001
The first measurement of HbA1c after initiation of the treatment period occurred at week 4 and resulted in reductions in HbA1c with JARDIANCE 25 mg and glimepiride vs baseline (-0.41% and -0.43% respectively) which were sustained over time.
Add-on Therapy with Metformin and Sulfonylurea (Study 1245.23+)
A double-blind, placebo-controlled study of 24 weeks duration was conducted to evaluate the efficacy and safety of JARDIANCE in patients not sufficiently treated with a combination of metformin and a sulphonylurea. As shown in Table 13, treatment with JARDIANCE resulted in statistically significant (p<0.0001) reductions in HbA1c and body weight, and clinically meaningful reductions in FPG compared to placebo at Week 24.
Table 13: Results of a 24-Week (LOCF) Placebo-Controlled Study of JARDIANCE as Add-on Therapy to Metformin with a Sulfonylurea
| Efficacy Parameter | Placebo | JARDIANCE 10 mg | JARDIANCE 25 mg |
|---|---|---|---|
| N | 225 | 225 | 216 |
| HbA1c (%) | |||
| Baseline (mean) | 8.15 | 8.07 | 8.10 |
| Change from baseline1 | -0.17 | -0.82 | -0.77 |
| Difference from placebo1 (97.5% CI) | -0.64* (-0.79, -0.49) | -0.59* (-0.74, -0.44) | |
| N | 216 | 209 | 202 |
| Patients2 (%) achieving HbA1c <7% | 11.1 | 31.1 | 34.3 |
| N | 224 | 225 | 215 |
| FPG (mmol/L) | |||
| Baseline (mean) | 8.42 | 8.38 | 8.68 |
| Change from baseline1 | 0.31 | -1.29 | -1.29 |
| Difference from placebo1 (95% CI) | -1.60 (-1.90, -1.30) | -1.60 (-1.90, -1.29) | |
| N | 225 | 225 | 216 |
| Body Weight (kg) | |||
| Baseline (mean) | 76.23 | 77.08 | 77.50 |
| Change from baseline1 | -0.39 | -2.16 | -2.39 |
| Difference from placebo1(97.5% CI) | -1.76* (-2.25, -1.28) | -1.99* (-2.48, -1.50) | |
1 mean adjusted for baseline value
2 The HbA1c responder analyses were performed on FAS with a noncompleters considered failure (NCF) imputation approach by determining the percentage of patients that fulfil responder criteria.
*p-value <0.0001
The first measurement of HbA1c after initiation of the treatment period occurred at week 6 and resulted in significant reductions in HbA1c with JARDIANCE 10 mg and 25 mg vs placebo (-0.58% and -0.6% respectively; p<0.0001) which were sustained over time.
Add-on Therapy with Pioglitazone (with or without Metformin, Study 1245.19)
The efficacy and safety of JARDIANCE were evaluated in a double-blind, placebo-controlled study of 24 weeks duration in patients not sufficiently treated with a combination of metformin and pioglitazone or pioglitazone alone. As shown in Table 14, JARDIANCE in combination with pioglitazone (mean dose ≥30 mg) with or without metformin resulted in statistically significant (p<0.0001) reductions in HbA1c, fasting plasma glucose, and body weight compared to placebo at Week 24.
Table 14: Results of a 24-Week (LOCF) Placebo-Controlled Study of JARDIANCE as Add-on to Pioglitazone
| Efficacy Parameter | Placebo | JARDIANCE 10 mg | JARDIANCE 25 mg |
|---|---|---|---|
| N | 165 | 165 | 168 |
| HbA1c (%) | |||
| Baseline (mean) | 8.16 | 8.07 | 8.06 |
| Change from baseline1 | -0.11 | -0.59 | -0.72 |
| Difference from placebo1 (97.5% CI) | -0.48* (-0.69, -0.27) | -0.61* (-0.82, -0.40) | |
| N | 155 | 151 | 160 |
| Patients2 (%) achieving HbA1c <7% | 9.7 | 27.9 | 31.5 |
| N | 165 | 163 | 168 |
| FPG (mmol/L) | |||
| Baseline (mean) | 8.43 | 8.44 | 8.43 |
| Change from baseline1 | 0.37 | -0.94 | -1.23 |
| Difference from placebo1 (97.5% CI) | -1.32 (-1.72, -0.91) | -1.61 (-2.01, -1.21) | |
| N | 165 | 165 | 168 |
| Body Weight (kg) | |||
| Baseline (mean) | 78.1 | 77.97 | 78.93 |
| Change from baseline1 | 0.34 | -1.62 | -1.47 |
| Difference from placebo1 (97.5% CI) | -1.95* (-2.64, -1.27) | -1.81* (-2.49, -1.13) | |
1 mean adjusted for baseline value
2 The HbA1c responder analyses were performed on FAS with a noncompleters considered failure (NCF) imputation approach by determining the percentage of patients that fulfil responder criteria.
*p-value <0.0001
The first measurement of HbA1c after initiation of the treatment period occurred at week 6 and resulted in significant reductions in HbA1c with JARDIANCE 10 mg and 25 mg vs placebo (-0.4% and -0.51% respectively; p<0.0001) which were sustained over time.
Patients with T2DM Inadequately Controlled on Linagliptin and Metformin (Study 1275.9)
Following a 16-week open-label period with metformin (≥1500 mg/day) and linagliptin 5 mg, patients with T2DM who did not achieve adequate glycemic control were randomized (1:1:1) to receive 24-week double-blind treatment with either metformin + GLYXAMBI 10/5 (empagliflozin 10 mg + linagliptin 5 mg), metformin + GLYXAMBI 25/5 (empagliflozin 25 mg + linagliptin 5 mg) or metformin + linagliptin 5 mg (background therapy). The study was not designed to evaluate the efficacy of GLYXAMBI 25/5 in patients with T2DM inadequately controlled with GLYXAMBI 10/5.
Approximately 15% of randomized patients were aged ≥65 years (2% aged ≥75 years). Approximately 58% were White, 27% were Asian and 9% were Black. The mean body mass index (BMI) was 30.2 kg/m2. Approximately 62% of patients had been diagnosed with T2DM for longer than 5 years, and approximately 7% for less than or equal to 1 year.
The primary endpoint of the study was the difference in change from baseline HbA1c at week 24. Key secondary endpoints were change from baseline fasting plasma glucose (FPG) and body weight, at week 24. Metformin + GLYXAMBI 10/5 and metformin + GLYXAMBI 25/5 each provided statistically significant improvements in HbA1c, FPG and body weight after 24 weeks of treatment compared to metformin + linagliptin 5 mg (see Table 15).
The proportion of patients with a baseline HbA1c ≥7.0% who achieved a target HbA1c of <7% at week 24 was 37.0% in the metformin + GLYXAMBI 10/5 group, 32.7% in the metformin + GLYXAMBI 25/5, and 17.0% in the metformin + linagliptin 5 mg group.
Table 15: Efficacy Parameters in the Clinical Study Comparing GLYXAMBI + Metformin to Linagliptin + Metformin in Patients with T2DM Inadequately Controlled on Linagliptin + Metformin (Study 1275.9)
| GLYXAMBI 10/5 + Metformin | GLYXAMBI 25/5 + Metformin | Lina 5 + Metformin | |||||||
|---|---|---|---|---|---|---|---|---|---|
| Efficacy Parameter | |||||||||
| HbA1c (%) - 24 weeks2 | |||||||||
| N1 | 109 | 110 | 106 | ||||||
| Baseline (mean) | 7.97 | 7.97 | 7.96 | ||||||
Change from baseline (adjusted mean) | -0.65 | -0.56 | 0.14 | ||||||
Difference from Lina 5 + Metformin (adjusted mean) (95% CI) | -0.79 (-1.02, -0.55) p<0.001 | -0.70 (-0.93, -0.46) p<0.001 | |||||||
| FPG (mmol/L) – 24 weeks2 | |||||||||
| N1 | 109 | 109 | 106 | ||||||
Abbreviations: GLYXAMBI 10/5 = empagliflozin 10 mg + linagliptin 5 mg; GLYXAMBI 25/5 = empagliflozin 25 mg + linagliptin 5 mg; Lina 5 = linagliptin 5 mg
1N = Full Analysis Set (FAS): treated patients with a pre-randomization baseline and at least one on-treatment HbA1c assessment
2MMRM (mixed model repeated measures) model on FAS (observed case) includes baseline HbA1c, baseline eGFR (modification of diet in renal disease), geographical region, visit treatment, and treatment by visit interaction. For FPG, baseline FPG is also included. For weight, baseline weight is also included.
Add-on Therapy with MDI of Basal and Prandial Insulin (with or without Metformin) (Study 1245.49)
The efficacy and safety of JARDIANCE as add on to multiple daily injections of basal and prandial insulin with or without metformin were evaluated at Week 18 and Week 52 in a randomized, double-blind, placebo-controlled study of empagliflozin 10 mg and 25 mg. From Week 1 to Week 18, patients were to maintain a stable insulin dose. From Week 19 to 40, treat-to-target insulin dose adjustments were to be made as needed in order to achieve glucose treat-to-target values (pre-prandial 5.5 mmol/L and post-prandial 7.8 mmol/L). From Week 41 to Week 52, patients were to maintain a stable insulin dose, and adjustments were to be made for safety reasons only. Insulin mix, regular and/or analogue mix, have not been studied.
The primary endpoint was the change from baseline in HbA1c after 18 weeks of treatment, analyzed on the full analysis set (FAS-18). As shown in Table 16, statistically significant reduction in HbA1c relative to placebo was observed with JARDIANCE 10 mg and 25 mg at Week 18.
| GLYXAMBI 10/5 + Metformin | GLYXAMBI 25/5 + Metformin | Lina 5 + Metformin | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Efficacy Parameter | ||||||||||
| HbA1c (%) - 24 weeks2 | ||||||||||
| N1 | 109 | 110 | 106 | |||||||
| Baseline (mean) | 9.32 | 9.44 | 9.04 | |||||||
Change from baseline (adjusted mean) | -1.46 | -1.75 | 0.34 | |||||||
Difference from Lina 5 + Metformin (adjusted mean) (95% CI) | -1.80 (-2.31, -1.28) p<0.01 | -2.09 (-2.61, -1.57) p<0.01 | ||||||||
| Body Weight (kg) – 24 weeks2 | ||||||||||
| N1 | 109 | 110 | 106 | |||||||
| Baseline (mean) in kg | 88.4 | 84.4 | 82.3 | |||||||
| Change from baseline (adjusted mean) | -3.1 | -2.5 | -0.3 | |||||||
Difference from Lina 5 + Metformin (adjusted mean) (95% CI) | -2.8 (-3.5, -2.1) p<0.01 | -2.2 (-2.9, -1.5) p<0.01 | ||||||||
Table 16: Results of 18-Week Placebo-Controlled Study-FAS (LOCF-18) of JARDIANCE in Combination with Insulin alone or with Metformin
| Efficacy Parameter | Placebo | JARDIANCE 10 mg | JARDIANCE 25 mg | ||||||||||
| All patients, N | 188 | 186 | 189 | ||||||||||
| Insulin only, N (%) | 53 (28.2) | 58 (31.2) | 52 (27.5) | ||||||||||
| HbA1c (%) | |||||||||||||
| Baseline2 (mean) (SE) | 8.44 (0.10) | 8.32 (0.10) | 8.31 (0.11) | ||||||||||
| Change from baseline1 mean (SE) (at Week 18) | -0.33 (0.10) | -0.79 (0.10) | -0.96 (0.10) | ||||||||||
Difference from placebo1 97.5% confidence interval | -- | -0.46 (-0.78, -0.14) | -0.62 (-0.95, -0.29) | ||||||||||
| p-value | -- | 0.0016 | <0.0001 | ||||||||||
| Insulin + metformin, N (%) | 135 (71.8) | 128 (68.8) | 137 (72.5) | ||||||||||
| HbA1c (%) | |||||||||||||
| Baseline2 (mean) (SE) | 8.29 (0.06) | 8.42 (0.06) | 8.29 (0.06) | ||||||||||
| Change from baseline1 mean (SE) (at Week 18) | -0.58 (0.06) | -0.99 (0.06) | -1.03 (0.06) | ||||||||||
Difference from placebo1 97.5% confidence interval | -- | -0.41 (-0.61, -0.21) | -0.45 (-0.65, -0.25) | ||||||||||
| p-value | -- | <0.0001 | <0.0001 | ||||||||||
During the first 18 weeks of treatment, the background insulin dose was not to be changed.
SE= standard error
1 adjusted mean for baseline HbA1c, eGFR and geographical region
2 Model included baseline HbA1c (p<0.0001) as a linear covariate, baseline eGFR (MDRD) (p=0.7812), treatment (p<0.0001), baseline background medication (p=0.0541), and treatment by baseline background medication interaction (p=0.3254) as fixed effects.
Blood pressure
The effects of JARDIANCE on blood pressure were evaluated in a double-blind, placebo-controlled study of 12 weeks duration in patients with type 2 diabetes and high blood pressure on different antidiabetic and up to 2 antihypertensive therapies. Treatment with JARDIANCE once daily resulted in statistically significant reduction in 24-hour mean systolic and diastolic blood pressure as determined by ambulatory blood pressure monitoring (see Table 17).
Treatment with JARDIANCE also provided reductions in seated SBP (change from baseline of -0.67 mmHg for placebo -4.60 mmHg for empagliflozin 10 mg and -5.47 mmHg for empagliflozin 25 mg) and seated DBP (change from baseline of -1.13 mmHg for placebo and -3.06 mmHg for empagliflozin 10 mg and -3.02 mmHg for empagliflozin 25 mg) at week 12.
Table 17: 24-Hour Ambulatory Blood Pressure Results at 12-week (LOCF) in a placebo-controlled study of JARDIANCE in patients with type 2 diabetes and uncontrolled blood pressure# (Full Analysis Set)
| Efficacy Parameter | Placebo | JARDIANCE 10 mg | JARDIANCE 25 mg | |||||||
|---|---|---|---|---|---|---|---|---|---|---|
| N | 271 | 276 | 276 | |||||||
| 24-hour SBP at week 12 | ||||||||||
| Baseline (mean) | 131.72 | 131.34 | 131.18 | |||||||
| Change from baseline1 | 0.48 | -2.95 | -3.68 | |||||||
Difference from placebo1 (95% CI) | -3.44* (-4.78, -2.09) | -4.16* (-5.50, -2.83) | ||||||||
| 24-hour DBP at week 12 | ||||||||||
| Baseline (mean) | 75.16 | 75.13 | 74.64 | |||||||
| Change from baseline1 | 0.32 | -1.04 | -1.40 | |||||||
Difference from placebo1 (95% CI) | -1.36** (-2.15, -0.56) | -1.72* (-2.51, -0.93) | ||||||||
a completer analysis
# Patients with mean seated SBP 130 to 159 mmHg and DBP 80 to 99 mmHg at screening
1 mean adjusted for baseline value
*p-value <0.0001
**p-value=0.0008
Use in Patients with Type 2 Diabetes and Established Cardiovascular Disease (EMPA-REG OUTCOME; study 1245.25)
The EMPA-REG OUTCOME study is a multi-centre, multi-national, randomized, double-blind, placebo-controlled, parallel-group, event-driven trial, investigating the effect of JARDIANCE as adjunct to standard care therapy in reducing cardiovascular events in patients with type 2 diabetes and one or more of the following established cardiovascular diseases: coronary artery disease, peripheral artery disease, history of myocardial infarction (MI), and history of stroke.
The study was conducted in patients with an eGFR ≥30 mL/min/1.73m2.
The primary endpoint was the time to first event in the composite of CV death, nonfatal MI, or nonfatal stroke (Major Adverse Cardiovascular Events [MACE-3]). The key secondary composite outcome was MACE-4 (i.e., MACE-3 plus hospitalization for unstable angina). Additional pre-specified, adjudicated endpoints included CV death, fatal/nonfatal myocardial infarction, fatal/non-fatal stroke, hospitalization for heart failure, and all-cause mortality. Patients without events were considered censored at the end of their individual observation periods.
A total of 7020 patients were treated (empagliflozin 10 mg: 2345, empagliflozin 25 mg: 2342, placebo: 2333) for a median duration of 2.6 years and followed for a median of 3.1 years. Baseline demographic and other characteristics, including background medications for diabetes and cardiovascular disease, were balanced across the treatment groups.
The population was 72.4% Caucasian, 21.6% Asian, and 5.1% Black. The mean age was 63 years (9.3% patients at least 75 years old) and 71.5% were male.
At randomisation, 75.6% of patients had coronary artery disease (including 46.6% with a history of myocardial infarction), 23.3% had a history of stroke, and 20.8% had peripheral artery disease. In total,
80.3% of patients had only 1 of these 3 factors reported at baseline, while 17.3% had 2 of the 3 factors and 1.6% had all 3 high-risk factors. A history of heart failure was reported for 10% of the patients.
At baseline, approximately 81% of patients were being treated with renin angiotensin system inhibitors, 65% with beta-blockers, 43% with diuretics, 89% with anticoagulants, and 81% with lipid-lowering medication. Approximately 74% of patients were being treated with metformin at baseline, 48% with insulin, and 43% with sulphonylurea.
Mean HbA1C was 8.1% at baseline.
At baseline 52.2% of patients had an eGFR of 60-90 mL/min/1.73 m2, 17.8% had an eGFR of 45-60 mL/min/1.73 m2 and 7.7% had eGFR of 30-45 mL/min/1.73 m2.
Mean systolic BP was 135 mmHg, diastolic BP 77 mmHg, LDL 2.22 mmol/L, and HDL 1.14 mmol/L at baseline.
Primary MACE Composite Endpoint: The primary analysis of MACE-3 was based on the treated set (TS), considering all events up to individual trial completion. According to hierarchical testing for non-inferiority and superiority, the pooled empagliflozin 10 and 25 mg treatment group (all empagliflozin) was found to be:
- Non-inferior to placebo, since the upper bound of the 95.02% CI was below 1.3, and
- Superior to placebo, since the upper bound of the 95.02% CI was also below 1.0
Table 18: Cox regression for time to first 3-point MACE, all JARDIANCE vs. placebo – TS
| Placebo | All JARDIANCE | |
|---|---|---|
| Analysed patients, N (100%) | 2333 | 4687 |
| Patients with event, N (%) | 282 (12.1) | 490 (10.5) |
| Incidence rate per 1000 years at risk | 43.9 | 37.4 |
| Hazard ratio vs. placebo | -- | 0.86 |
| (95.02% CI) 1 | (0.74, 0.99) | |
| (95% CI) | (0.74, 0.99) | |
| p−value for HR≥1.3 (1-sided) | <0.0001 | |
| p−value for HR≥1.0 (1-sided) | 0.0191 | |
| p−value (2-sided) | 0.0382 |
1 Based on the reduced alpha level of 0.0249 resulting from the interim analysis
The treatment effect reflected a significant reduction in cardiovascular death with no significant change in non-fatal MI, or non-fatal stroke.
Results for the MACE-4 composite endpoint, including hospitalization for unstable angina, were non-inferior, but not superior, to placebo.
Other Adjudicated Cardiovascular Endpoints
Mortality Endpoints
JARDIANCE decreased all-cause mortality which was driven by a reduction in cardiovascular death. There was no statistically significant difference between JARDIANCE and placebo in non-cardiovascular mortality.
Table 19: Summary of endpoints of death – TS
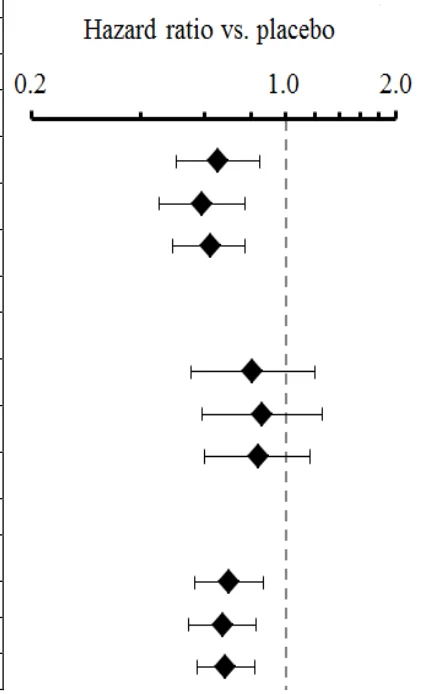
For the graph: the diamond indicates the HR and the bars 95% CIs for the HR of empagliflozin vs. placebo
| Treatment | Patients with event, n (%) | Incidence /1000 p-y | Comparison vs. placebo | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| HR | 95% CI | p-value | |||||||||||
| CV death | |||||||||||||
| Placebo | 137 (5.9) | 20.2 | -- | -- | -- | -- | |||||||
| Empa 10 mg | 90 (3.8) | 13.0 | 0.65 | 0.50 | 0.85 | 0.0016 | |||||||
| Empa 25 mg | 82 (3.5) | 11.8 | 0.59 | 0.45 | 0.77 | 0.0001 | |||||||
| All empa | 172 (3.7) | 12.4 | 0.62 | 0.49 | 0.77 | <0.0001 | |||||||
| Non-CV death | |||||||||||||
| Placebo | 57 (2.4) | 8.4 | -- | -- | -- | -- | |||||||
| Empa 10 mg | 47 (2.0) | 6.8 | 0.81 | 0.55 | 1.20 | 0.2909 | |||||||
| Empa 25 mg | 50 (2.1) | 7.2 | 0.86 | 0.59 | 1.26 | 0.4400 | |||||||
| All empa | 97 (2.1) | 7.0 | 0.84 | 0.60 | 1.16 | 0.2852 | |||||||
| All-cause mortality | |||||||||||||
| Placebo | 194 (8.3) | 28.6 | -- | -- | -- | -- | |||||||
| Empa 10 mg | 137 (5.8) | 19.8 | 0.70 | 0.56 | 0.87 | 0.0013 | |||||||
| Empa 25 mg | 132 (5.6) | 19.0 | 0.67 | 0.54 | 0.83 | 0.0003 | |||||||
| All empa | 269 (5.7) | 19.4 | 0.68 | 0.57 | 0.82 | <0.0001 | |||||||
Figure 5: Estimated incidence function for time to CV death, individual empagliflozin doses vs placebo – treated set
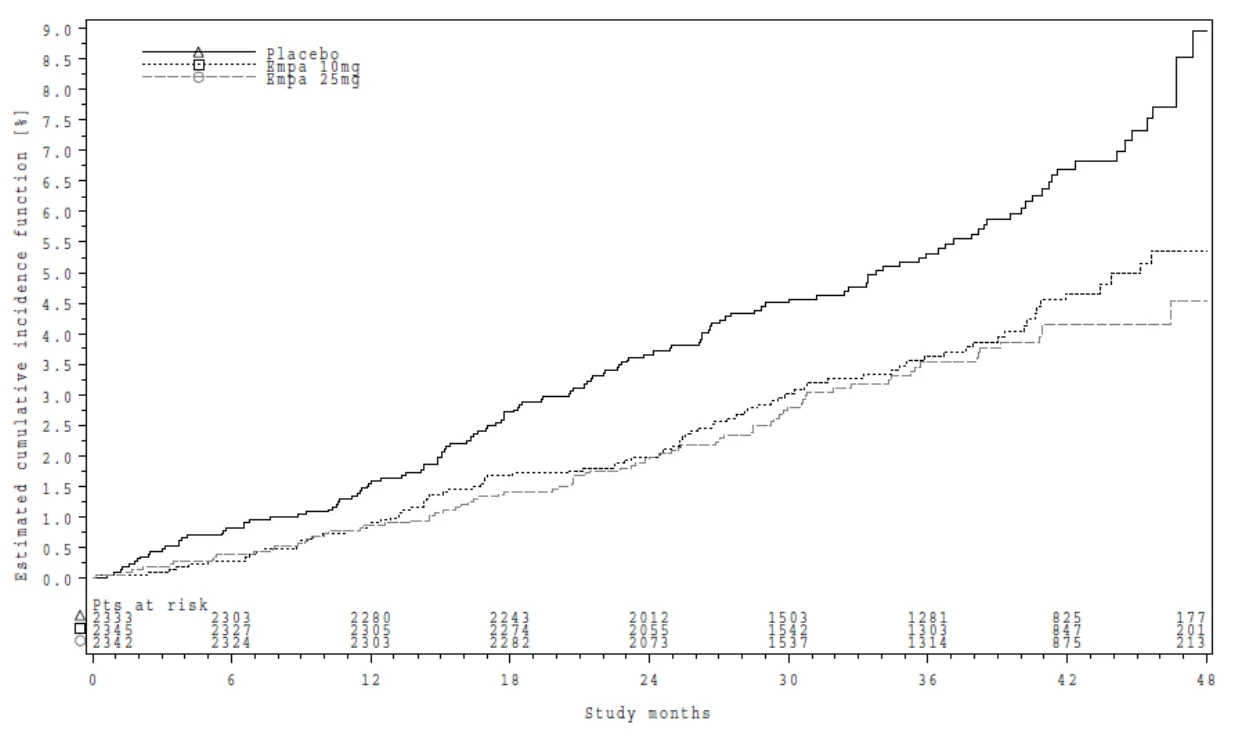
In this trial, there were 1819 patients with eGFR below 60 mL/min/1.73 m2. The cardiovascular death findings in this subgroup were consistent with the overall findings. The efficacy and safety of JARDIANCE have not been established in patients with severe renal impairment, with ESRD, or receiving dialysis.
Myocardial Infarction (MI) and Hospitalization for Unstable Angina
No statistically significant difference was observed between JARDIANCE and placebo for fatal/non-fatal MI, non-fatal MI, or hospitalization for unstable angina.
Table 20: Summary of MI-related endpoints – TS
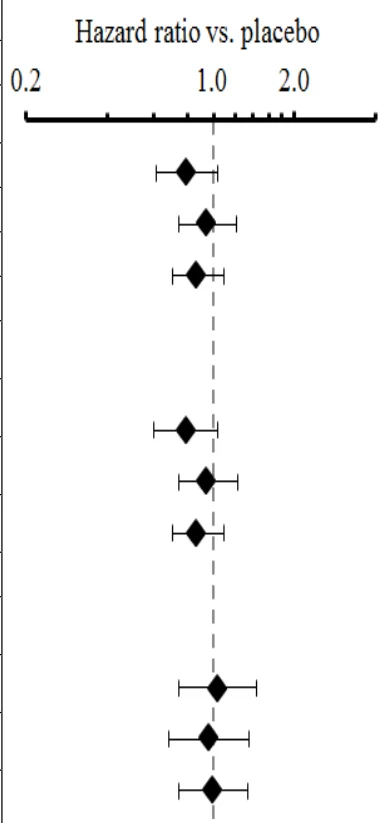
Stroke
For the endpoints fatal/non-fatal stroke and non-fatal stroke, non-significant unfavourable trends were observed in the empagliflozin groups. Much of this imbalance was driven by events that occurred off-treatment (more than 90 days after stop of treatment). For transient ischemic attacks, a non-significant favourable trend was observed. The majority of the stroke events were ischemic (149 of 164 for empagliflozin, 62 of 69 for placebo).
| Treatment | Patients with event, n (%) | Incidence /1000 p-y | Comparison vs. placebo | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| HR | 95% CI | p-value | |||||||||||
| MI (fatal/non-fatal) | |||||||||||||
| Placebo | 126 (5.4) | 19.3 | -- | -- | -- | -- | |||||||
| Empa 10 mg | 101 (4.3) | 15.2 | 0.79 | 0.61 | 1.03 | 0.0852 | |||||||
| Empa 25 mg | 122 (5.2) | 18.3 | 0.95 | 0.74 | 1.22 | 0.7141 | |||||||
| All empa | 223 (4.8) | 16.8 | 0.87 | 0.70 | 1.09 | 0.2302 | |||||||
| Non-fatal MI | |||||||||||||
| Placebo | 121 (5.2) | 18.5 | -- | -- | -- | -- | |||||||
| Empa 10 mg | 96 (4.1) | 14.4 | 0.79 | 0.60 | 1.03 | 0.0769 | |||||||
| Empa 25 mg | 117 (5.0) | 17.6 | 0.95 | 0.74 | 1.23 | 0.7114 | |||||||
| All empa | 213 (4.5) | 16.0 | 0.87 | 0.70 | 1.09 | 0.2189 | |||||||
| Hospitalization for unstable angina | |||||||||||||
| Placebo | 66 (2.8) | 10.0 | -- | -- | -- | -- | |||||||
| Empa 10 mg | 69 (2.9) | 10.4 | 1.03 | 0.74 | 1.45 | 0.8509 | |||||||
| Empa 25 mg | 64 (2.7) | 9.5 | 0.96 | 0.68 | 1.35 | 0.7981 | |||||||
| All empa | 133 (2.8) | 10.0 | 0.99 | 0.74 | 1.34 | 0.9706 | |||||||
Table 21: Summary of cerebrovascular disease-related endpoints – TS
| Treatment | Patients with event, n (%) | Incidence /1000 p-y | Comparison vs. placebo | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| HR | 95% CI | p-value | ||||||||||||
| Stroke (fatal/non-fatal) | ||||||||||||||
| Placebo | 69 (3.0) | 10.5 | -- | -- | -- | -- | ||||||||
| Empa 10 mg | 85 (3.6) | 12.7 | 1.22 | 0.89 | 1.68 | 0.2119 | ||||||||
| Empa 25 mg | 79 (3.4) | 11.8 | 1.13 | 0.82 | 1.56 | 0.4594 | ||||||||
| All empa | 164 (3.5) | 12.3 | 1.18 | 0.89 | 1.56 | 0.2567 | ||||||||
| Non-fatal stroke | ||||||||||||||
| Placebo | 60 (2.6) | 9.1 | -- | -- | -- | -- | ||||||||
| Empa 10 mg | 77 (3.3) | 11.5 | 1.27 | 0.91 | 1.79 | 0.1593 | ||||||||
| Empa 25 mg | 73 (3.1) | 10.9 | 1.20 | 0.85 | 1.69 | 0.2954 | ||||||||
| All empa | 150 (3.2) | 11.2 | 1.24 | 0.92 | 1.67 | 0.1638 | ||||||||
| Fatal stroke | ||||||||||||||
| Placebo | 11 (0.5) | 1.6 | -- | -- | -- | -- | ||||||||
| Empa 10 mg | 9 (0.4) | 1.3 | 0.82 | 0.34 | 1.98 | 0.6572 | ||||||||
| Empa 25 mg | 7 (0.3) | 1.0 | 0.62 | 0.24 | 1.61 | 0.3275 | ||||||||
| All empa | 16 (0.3) | 1.2 | 0.72 | 0.33 | 1.55 | 0.4015 | ||||||||
| Treatment-emergent stroke (fatal/non-fatal)* | ||||||||||||||
| Placebo | 66 (2.8) | 11.1 | -- | -- | -- | -- | ||||||||
| Empa 10 mg | 74 (3.2) | 12.0 | 1.10 | 0.79 | 1.53 | 0.5773 | ||||||||
| Empa 25 mg | 72 (3.1) | 11.6 | 1.06 | 0.76 | 1.48 | 0.7229 | ||||||||
| All empa | 146 (3.1) | 11.8 | 1.08 | 0.81 | 1.45 | 0.6014 | ||||||||
| Transient ischemic attack (TIA) | ||||||||||||||
| Placebo | 23 (1.0) | 3.5 | -- | -- | -- | -- | ||||||||
| Empa 10 mg | 19 (0.8) | 2.8 | 0.83 | 0.45 | 1.53 | 0.5603 | ||||||||
| Empa 25 mg | 20 (0.9) | 2.9 | 0.87 | 0.48 | 1.58 | 0.6357 | ||||||||
| All empa | 39 (0.8) | 2.9 | 0.85 | 0.51 | 1.42 | 0.5368 | ||||||||
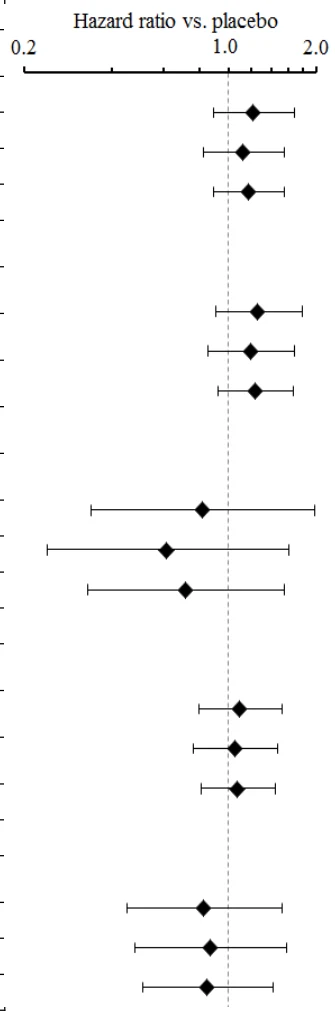
*Including all events up to 90 days after stop of treatment
Reductions in risk of heart failure requiring hospitalization or death from heart failure
JARDIANCE significantly reduced the risk of heart failure requiring hospitalization and heart failure requiring hospitalization or death from heart failure compared with placebo.
Table 22: Summary of heart failure-related endpoints – TS
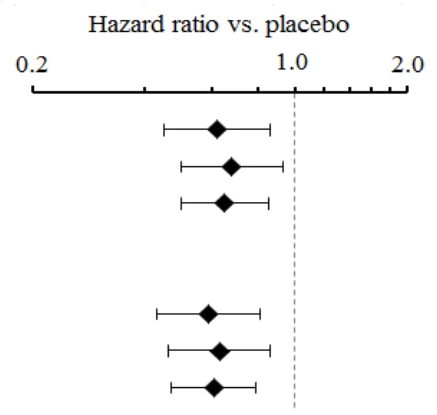
Figure 6: Estimated cumulative incidence function for time to first hospitalization for heart failure (HF) or death from worsening of heart failure, individual empagliflozin vs placebo – treated set
| Treatment | Patients with event, n (%) | Incidence /1000 p-y | Comparison vs. placebo | |||
|---|---|---|---|---|---|---|
| HR | 95% CI | p-value | ||||
| Heart failure requiring hospitalization | ||||||
| Placebo | 95 (4.1) | 14.5 | -- | -- | -- | -- |
| Empa 10 mg | 60 (2.6) | 8.9 | 0.62 | 0.45 | 0.86 | 0.0044 |
| Empa 25 mg | 66 (2.8) | 9.8 | 0.68 | 0.50 | 0.93 | 0.0166 |
| All empa | 126 (2.7) | 9.4 | 0.65 | 0.50 | 0.85 | 0.0017 |
| Heart failure requiring hospitalization or death from heart failure | ||||||
| Placebo | 104 (4.5) | 15.8 | -- | -- | -- | -- |
| Empa 10 mg | 62 (2.6) | 9.2 | 0.59 | 0.43 | 0.81 | 0.0010 |
| Empa 25 mg | 67 (2.9) | 9.9 | 0.63 | 0.46 | 0.86 | 0.0034 |
| All empa | 129 (2.8) | 9.6 | 0.61 | 0.47 | 0.79 | 0.0002 |
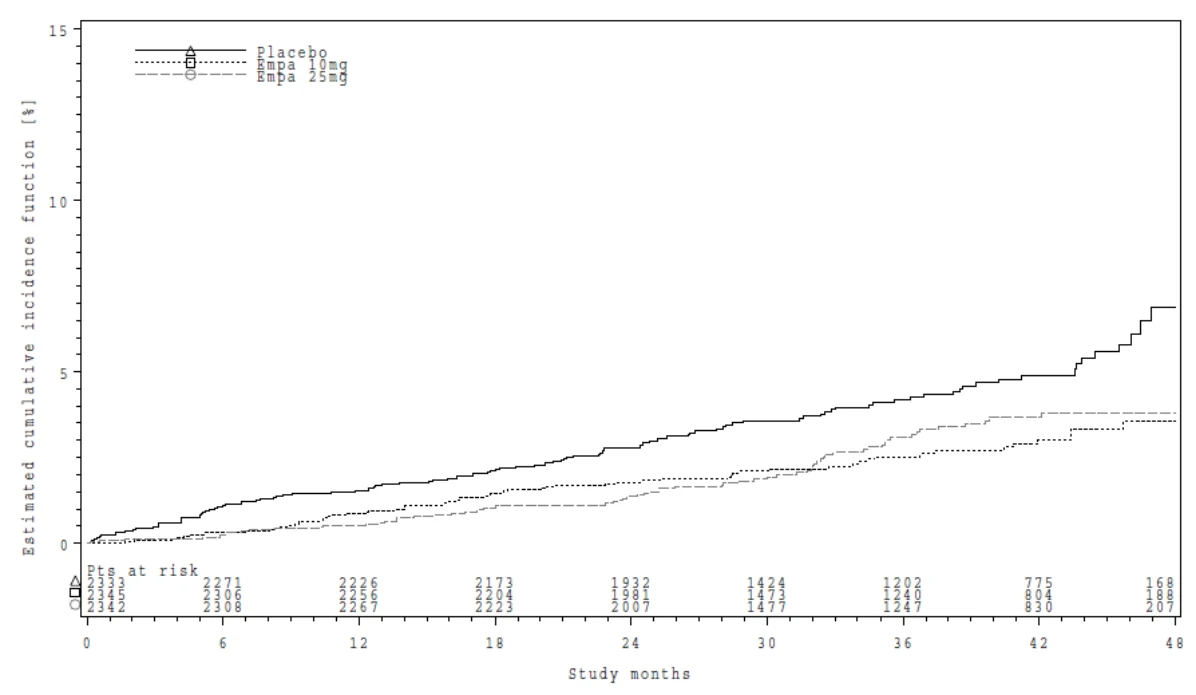
Other
Use in Patients with Type 2 Diabetes and Renal Impairment (Study 1245.36)
The efficacy and safety of JARDIANCE as add-on to antidiabetic therapy were evaluated in patients with type 2 diabetes and different degrees of renal impairment. A total of 738 patients with a baseline eGFR less than 90 mL/min/1.73 m2 participated in a 52-week randomized, double-blind, placebo-controlled, parallel-group study.
In patients with mild renal impairment, treatment with JARDIANCE 10 mg and 25 mg led to statistically significant reduction of HbA1c at Week 24 compared to placebo. Although the 10 mg dose is the recommended starting dose of JARDIANCE, this dose was only studied in patients with mild renal impairment. For patients with type 2 diabetes with moderate or severe renal impairment, the 25 mg dose of JARDIANCE was used. The glucose lowering efficacy of JARDIANCE 25 mg decreased with decreasing renal function (see Table 23). In patients with severe renal impairment, JARDIANCE 25 mg did not reduce HbA1c at Week 24 and more adverse events were noted.
Table 23: Results at 24-Week (LOCF) in a Placebo-Controlled Study of Jardiance in Renally Impaired Type 2 Diabetes Patients (Full Analysis Set)
| Efficacy Parameter | Placebo | JARDIANCE | Placebo | JARDIANCE 25 mg | Placebo | JARDIANCE 25 mg | |
|---|---|---|---|---|---|---|---|
| 10 mg | 25 mg | ||||||
Mild (eGFR ≥60 to <90 mL/min/1.73m²) | Moderate 3A (eGFR ≥45 to <60 mL/min/1.73m² | Moderate 3B (eGFR ≥30 to <45 mL/min/1.73m²) | |||||
| N (%) | 95 (12.9) | 98 (13.3) | 97 (13.1) | 89 (12.1) | 91 (12.3) | 98 (13.3) | 96 (13.0) |
| HbA1c (%) | |||||||
| Baseline (mean) | 8.09 | 8.02 | 7.96 | 8.08 | 8.12 | 8.01 | 7.95 |
| Change from baseline1 | 0.06 | -0.46 | -0.63 | -0.09 | -0.54 | 0.17 | -0.21 |
| Difference from placebo1 (95% CI) | -0.52* (-0.72, -0.32) | -0.68* (-0.88,-0.49) | -0.46* (-0.66, -0.27) | -0.39* (-0.58, -0.19) | |||
1 mean adjusted for baseline value
* p<0.0001
Heart Failure
Table 24: Summary of patient demographics for clinical trials in patients with Heart Failure
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) randomized / treated | Mean age (Range) | Sex (%M/F) |
1245.121 EMPEROR-Reduced | randomized, double-blind, placebo-controlled study | Empagliflozin 10 mg vs placebo + standard of care Tablets, orally, once daily treatment: event-driven follow up: about 15.7 months | Total: 3730/3726 Empagliflozin: 10 mg: 1863/1863 Placebo: 1867/1863 | 66.8 years (range: 25-94 years), | 76.1% M/ 23.9% F |
1245.110 EMPEROR-Preserved | randomized, double-blind, placebo-controlled study | Empagliflozin 10 mg vs placebo + standard of care Tablets, orally, once daily treatment: event-driven follow up: about 26.2 months | Total: 5988/5985 Empagliflozin: 10 mg: 2997/2996 Placebo: 2991/2989 | 71.9 years (range: 22-100 years), | 55.3 % M/ 44.7 % F |
1245.204 EMPULSE | randomized, double-blind, placebo-controlled study | Empagliflozin 10 mg vs placebo + standard of care Tablets, orally, once daily treatment: 90 days after clinical stability. | Total: 530/524 Empagliflozin: 10 mg: 265/260 Placebo: 265/264 | 68.5 years (range: 22-98 years) | 66% M/ 34% F |
JARDIANCE was studied in a randomized, double-blind, placebo-controlled study (EMPEROR-Reduced) in patients with chronic heart failure and reduced ejection fraction (LVEF ≤40 %) as adjunct to standard of care and in a randomized, double-blind, placebo-controlled study (EMPEROR-Preserved) in patients with chronic heart failure and preserved ejection fraction (LVEF >40 %) as adjunct to standard of care.
JARDIANCE was studied in a randomized, double-blind, placebo-controlled, parallel-group trial (EMPULSE) in patients hospitalized for acute heart failure (de novo or decompensated chronic heart failure) regardless of ejection fraction, after initial stabilisation.
Use in Patients with chronic heart failure and reduced ejection fraction (LVEF ≤40 %) (EMPEROR-Reduced; study 1245.121)
A randomized, double-blind, placebo-controlled study (EMPEROR-Reduced) was conducted in 3730 patients with chronic heart failure and reduced ejection fraction (LVEF ≤40 %) to evaluate the efficacy and safety of JARDIANCE 10 mg once daily as adjunct to standard of care heart failure therapy.
A total of 1863 patients were randomized to JARDIANCE 10 mg (placebo: 1867 patients) and followed for a median of 15.7 months. The study population consisted of 76.1% men and 23.9% women with a mean age of 66.8 years (range: 25-94 years); 62% of randomized patients with HFrEF were 65 years of age and older, 26.8% were 75 years of age or older.
Of the study population 70.5% were White, 18.0% Asian and 6.9% Black/African American.
Heart Failure therapy at baseline included ACE inhibitors/angiotensin receptor blockers/angiotensin receptor-neprilysin inhibitor (88.3%), 19.5% of patients were receiving an angiotensin receptor-neprilysin inhibitor, beta blockers (94.7%), diuretics (95.0%) and mineralocorticoid receptor antagonists (71.3%). 31.4% of patients had an implanted cardiac defibrillator and 11.8% of patients had cardiac resynchronization therapy.
At randomization, 75.1% of patients were NYHA class II, 24.4% were class III and 0.5% were class IV. The mean LVEF was 27.5%, with 73.2% of patients having an LVEF ≤30%. Approximately half of patients (49.8%) had diabetes.
The study enrolled patients with eGFR equal to or above 20 mL/min/1.73 m2. At baseline, the mean eGFR was 62.0 mL/min/1.73 m2 and the median urinary albumin to creatinine ratio (UACR) was 22 mg/g (2.49 mg/mmol). About half of the patients (51.7%) had an eGFR of ≥60 mL/min/1.73 m2, 24.1% had an eGFR of 45 to <60 mL/min/1.73 m2, 18.6% had an eGFR of 30 to <45 mL/min/1.73 m2 and 5.3% had an eGFR 20 to <30 mL/min/1.73 m2.
The primary endpoint was the time to adjudicated first event of either cardiovascular (CV) death or hospitalization for heart failure (HHF). Occurrence of adjudicated HHF (first and recurrent) was included in the confirmatory testing.
JARDIANCE was superior in reducing the risk of the primary composite endpoint of cardiovascular death or hospitalization for heart failure compared with placebo. Additionally, JARDIANCE significantly reduced the risk of occurrence of HHF (first and recurrent), see (Table 25 and Figure 7).
Table 25: Treatment effect for the primary composite endpoint, its components and the key secondary endpoint included in the pre-specified confirmatory testing
| Placebo | JARDIANCE 10 mg | |
|---|---|---|
| N | 1867 | 1863 |
| Time to first event of CV death or HHF, N (%) | 462 (24.7) | 361 (19.4) |
| Hazard ratio vs. placebo (95.04% CI)** | 0.75 (0.65, 0.86) | |
| p−value for superiority | <0.0001 | |
| CV Death, N (%)* | 202 (10.8) | 187 (10.0) |
| Hazard ratio vs. placebo (95% CI) | 0.92 (0.75, 1.12) | |
| p-value | 0.4113 | |
| HHF (first occurrence), N (%)* | 342 (18.3) | 246 (13.2) |
| Hazard ratio vs. placebo (95% CI) | 0.69 (0.59, 0.81) | |
| p−value | <0.0001 | |
| HHF (first and recurrent), N of events | 553 | 388 |
| Hazard ratio vs. placebo (95.04% CI)** | 0.70 (0.58, 0.85) | |
| p−value | 0.0003 |
CV = cardiovascular, HHF = hospitalization for heart failure,
*not controlled for type 1 error
**Due to an interim analysis, a two-sided 95.04% confidence interval was applied which corresponds to a p-value less than 0.0496 for significance. CV death and HHF events were adjudicated by an independent clinical event committee and analyzed based on the randomized set.
Figure 7: Time to First Occurrence of the Primary Composite Endpoint of Cardiovascular Death or Hospitalization for Heart Failure
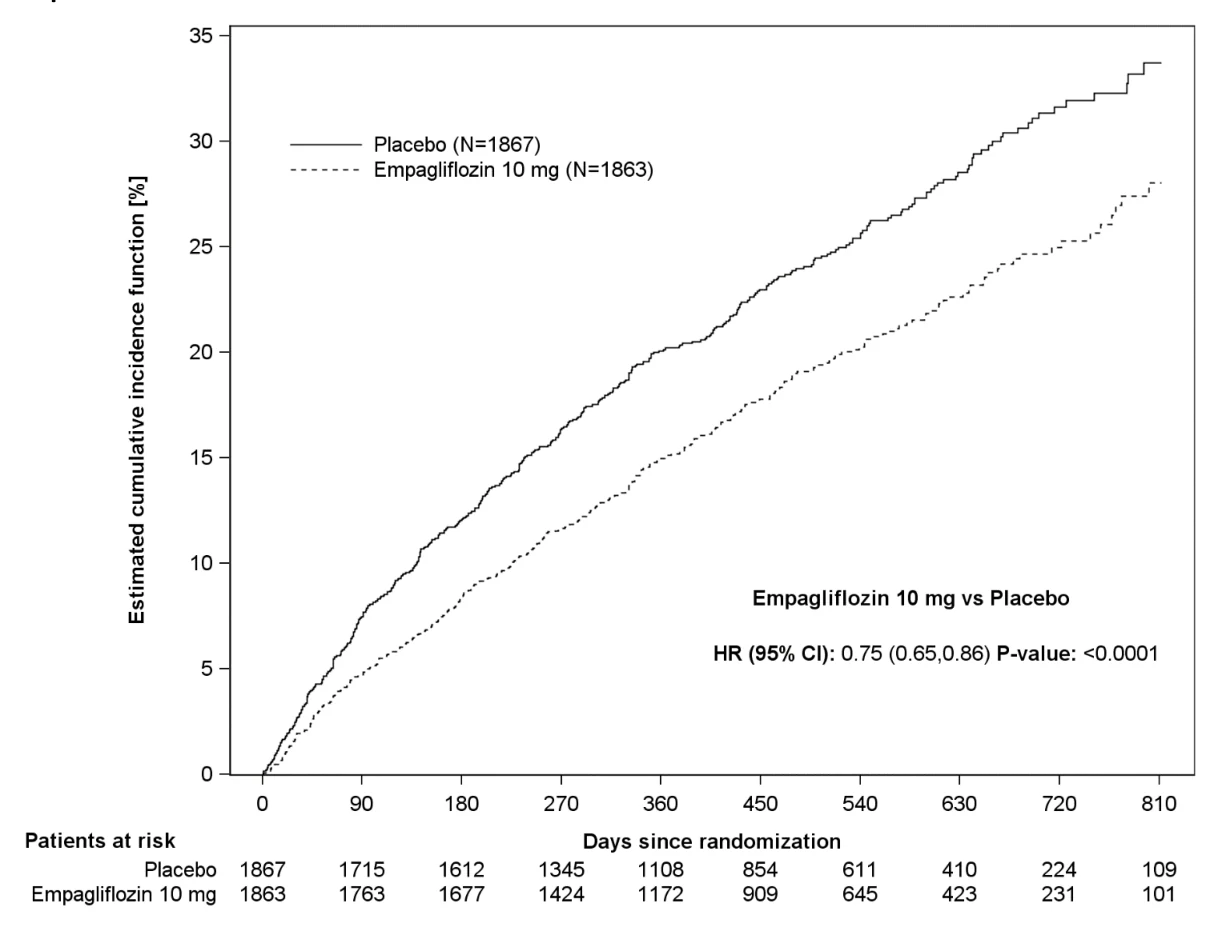
Figure 8: Occurrence of adjudicated HHF (first and recurrent), mean cumulative function
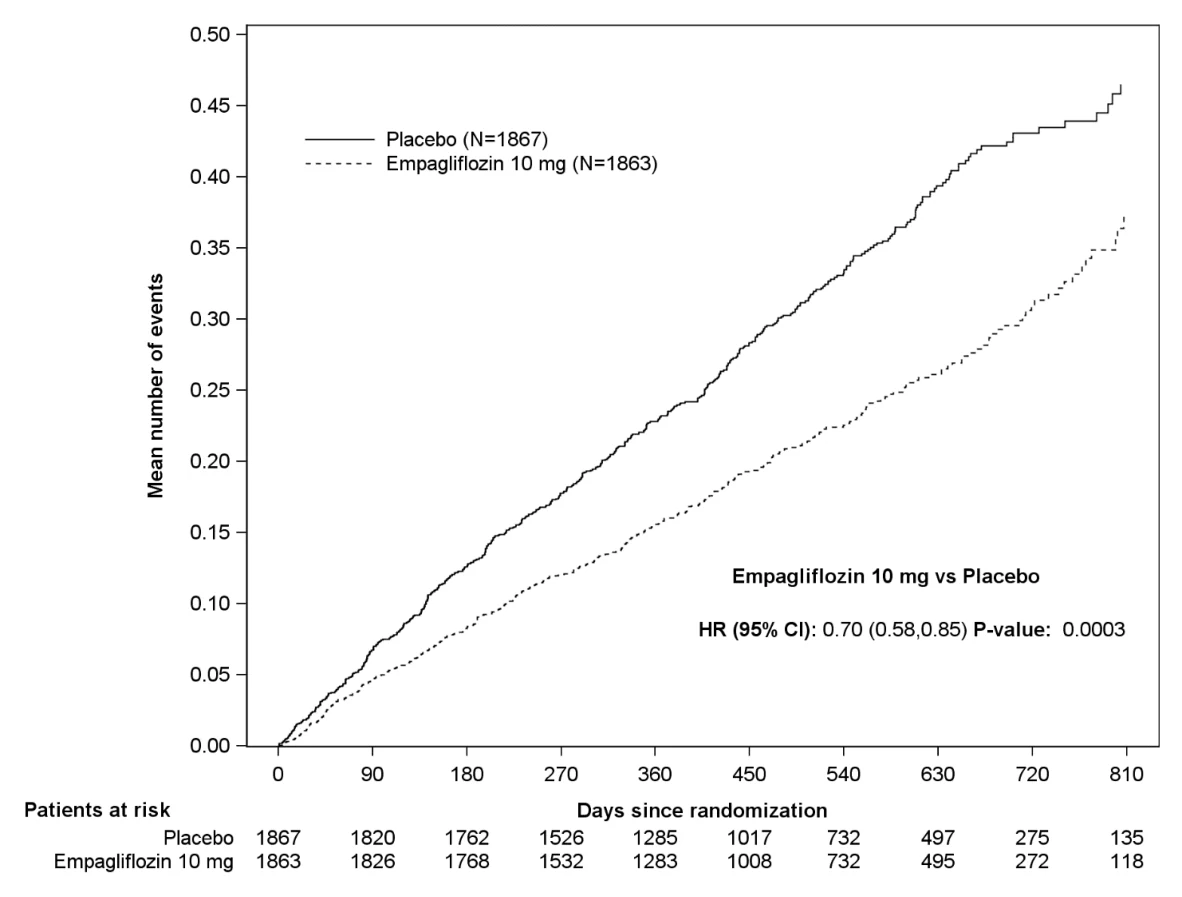
The results of the primary composite endpoint were generally consistent across the pre-specified subgroups, including heart failure patients with and without type 2 diabetes mellitus (Figure 9).
Figure 9: Treatment Effects for the Primary Composite Endpoint (Cardiovascular Death and Hospitalization for Heart Failure) Subgroup Analysis (EMPEROR-Reduced)
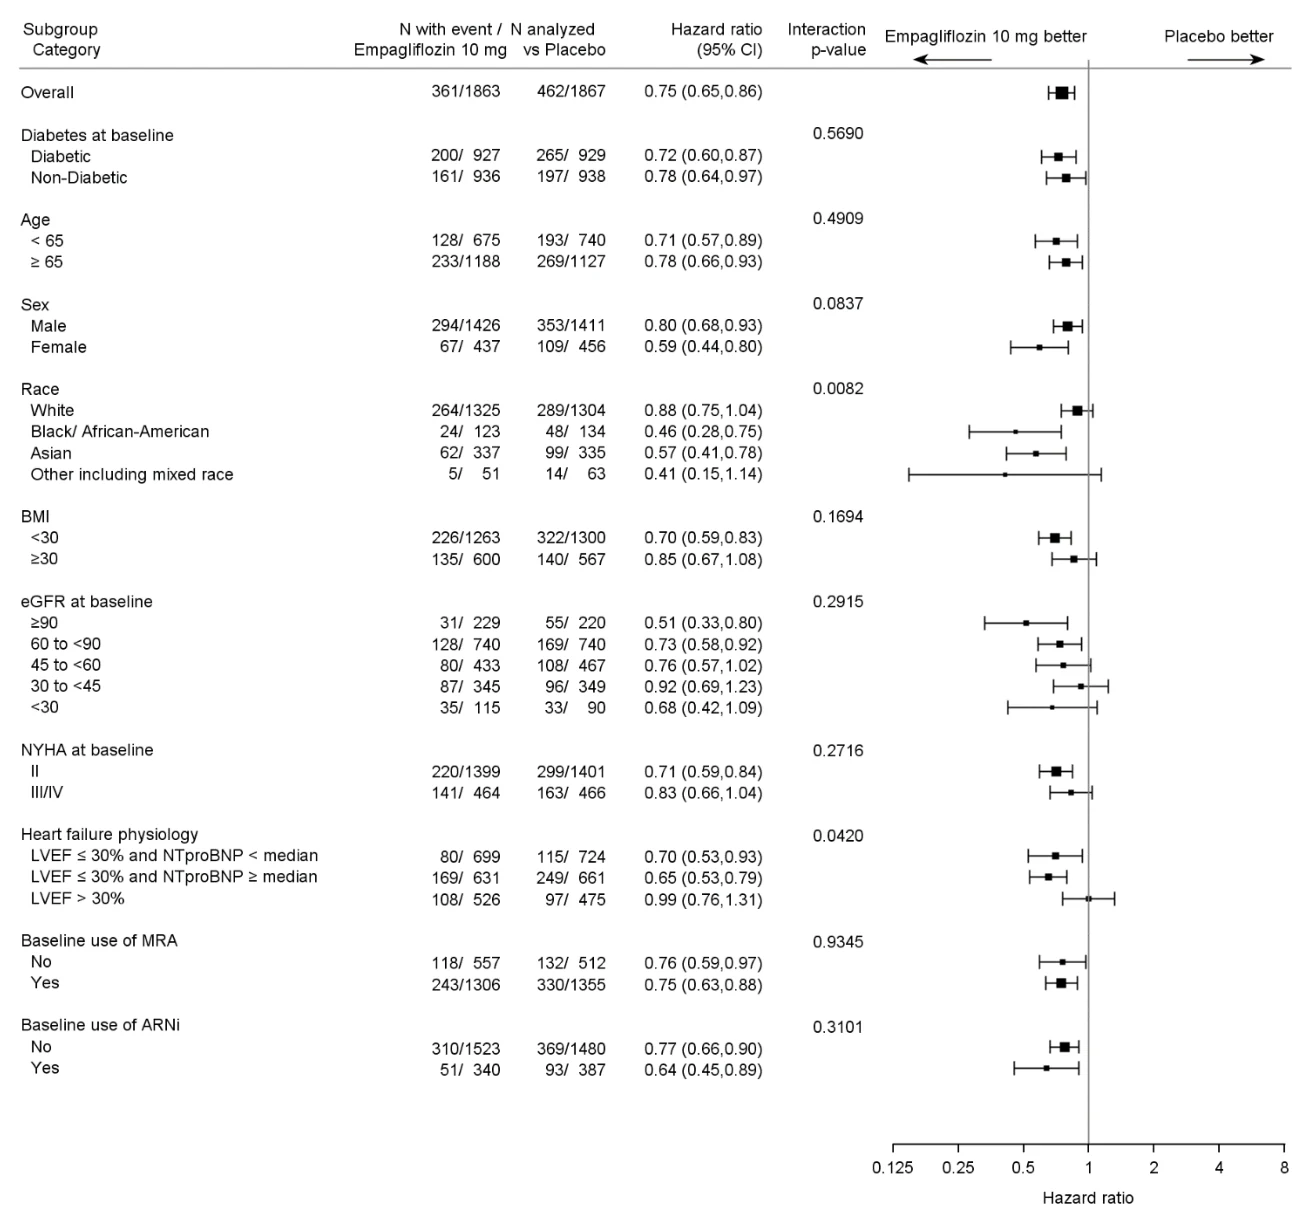
LVEF >30%: Includes both above and below the median NTproBNP. To be eligible for inclusion, patients with an LVEF >30% were required to meet a higher NTproBNP threshold than those with LVEF ≤30%, unless they additionally had a history of HHF within the past 12 months.
Figure 10: Primary and key secondary endpoint by baseline T2DM status in patients with HFrEF
Time to the first CV death or HHF, Cox regression, randomized set
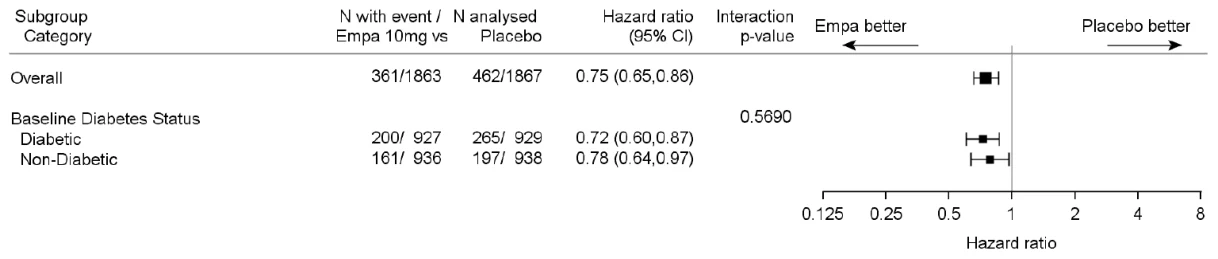
HHF (first and recurrent), joint frailty model, randomized set
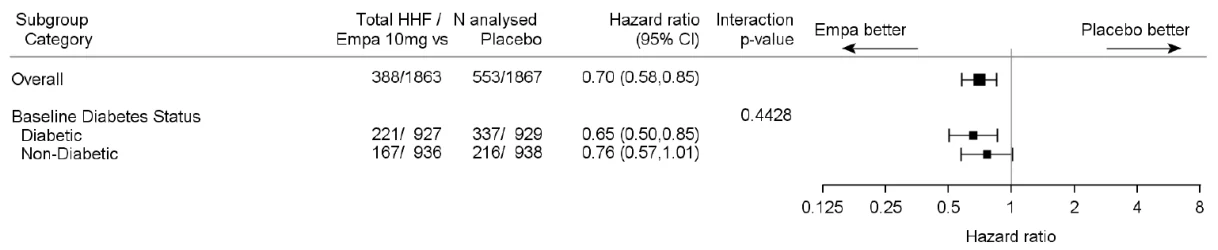
Use in Patients with chronic heart failure and preserved ejection fraction (LVEF >40 %) (EMPEROR-Preserved; study 1245.110)
A randomized, double-blind, placebo-controlled study (EMPEROR-Preserved) was conducted in 5988 patients with chronic heart failure (NYHA II-IV) and preserved ejection fraction (LVEF >40%) to evaluate the efficacy and safety of empagliflozin 10 mg once daily as adjunct to standard of care therapy.
The primary endpoint was the time to adjudicated first event of either cardiovascular (CV) death or hospitalization for heart failure (HHF). Occurrence of adjudicated HHF (first and recurrent), and eGFR (CKD-EPI)cr slope of change from baseline were included in the confirmatory testing. Baseline therapy included angiotensin-converting enzyme (ACE) inhibitors/angiotensin receptor blockers (ARB)/angiotensin receptor-neprilysin inhibitor (ARNi) (80.7%), beta blockers (86.3%), mineralocorticoid receptor antagonists (37.5%) and diuretics (86.2%).
A total of 2997 patients were randomized to empagliflozin 10 mg (placebo: 2991) and followed for a median of 26.2 months. The study population consisted of 55.3% men and 44.7% women with a mean age of 71.9 years (range: 22-100 years), 43.0% were 75 years of age or older. 75.9% of the study population were White, 13.8% Asian and 4.3% Black/African American. At randomization, 81.5% of patients were NYHA class II, 18.1% were NYHA class III and 0.3% were NYHA class IV.
The mean LVEF was 54.3%; LVEF <50% (33.1%), LVEF 50 to <60% (34.4%) and LVEF ≥60% (32.5%). The main cause of HF was ischemic (35.4%), hypertensive (36.5%), idiopathic (9.2%), and valvular heart disease (5.9%). Patients with prior diagnosis of cardiomyopathy based on infiltrative diseases (e.g., amyloidosis) were excluded. Approximately half of patients (49.1%) had diabetes (48.9% T2DM).
At baseline, the mean eGFR was 60.6 mL/min/1.73 m2 and the median urinary albumin to creatinine ratio (UACR) was 2.4 mg/mmol. About half of the patients (50.1%) had an eGFR of ≥60 mL/min/1.73 m2, 26.1% of 45 to <60 mL/min/1.73 m2, 18.6% of 30 to <45 mL/min/1.73 m2 and 4.9% 20 to <30 mL/min/1.73 m2.
Empagliflozin significantly reduced the risk of the primary composite endpoint of cardiovascular death or hospitalization for heart failure compared with placebo (HR 0.79; 95.03%CI 0.69 to 0.90, p= 0.0003). The separation of the estimated cumulative incidence of CV death or first HHF between empagliflozin and placebo started shortly after randomisation and was maintained throughout the trial. Additionally, empagliflozin significantly reduced the risk of occurrence of HHF (first and recurrent) (see Table 26 and Figures 11 and 12).
Table 26: Treatment effect for the primary composite endpoint, its components and the two key secondary endpoints included in the pre-specified confirmatory testing in EMPEROR-Preserved
| Placebo | JARDIANCE 10 mg | |
|---|---|---|
| N | 2991 | 2997 |
| Time to first event of CV death or HHF, N (%) | 511 (17.1) | 415 (13.8) |
| Hazard ratio vs. placebo (95.04% CI)** | 0.79 (0.69, 0.90) | |
| p−value for superiority | 0.0003 | |
| CV Death, N (%)* | 244 (8.2) | 219 (7.3) |
| Hazard ratio vs. placebo (95% CI) | 0.91 (0.76, 1.09) | |
| p-value | 0.2951 | |
| HHF (first occurrence), N (%)* | 352 (11.8) | 259 (8.6) |
| Hazard ratio vs. placebo (95% CI) | 0.71 (0.60, 0.83) | |
| p−value | <0.0001 | |
| HHF (first and recurrent), N of events | 541 | 407 |
| Hazard ratio vs. placebo (95.04% CI)** | 0.73 (0.61, 0.88) | |
| p−value | 0.0009 |
CV = cardiovascular, HHF = hospitalization for heart failure, eGFR = Estimated glomerular filtration rate, CKD EPI = Chronic kidney disease epidemiology collaboration equation
*not controlled for type 1 error
**Due to an interim analysis, a two-sided 95.04% confidence interval was applied which corresponds to a p-value less than 0.0496 for significance. CV death and HHF events were adjudicated by an independent clinical event committee and analyzed based on the randomized set.
Figure 11: Time to first event of adjudicated CV death or Hospitalization for Heart Failure (EMPEROR-Preserved)
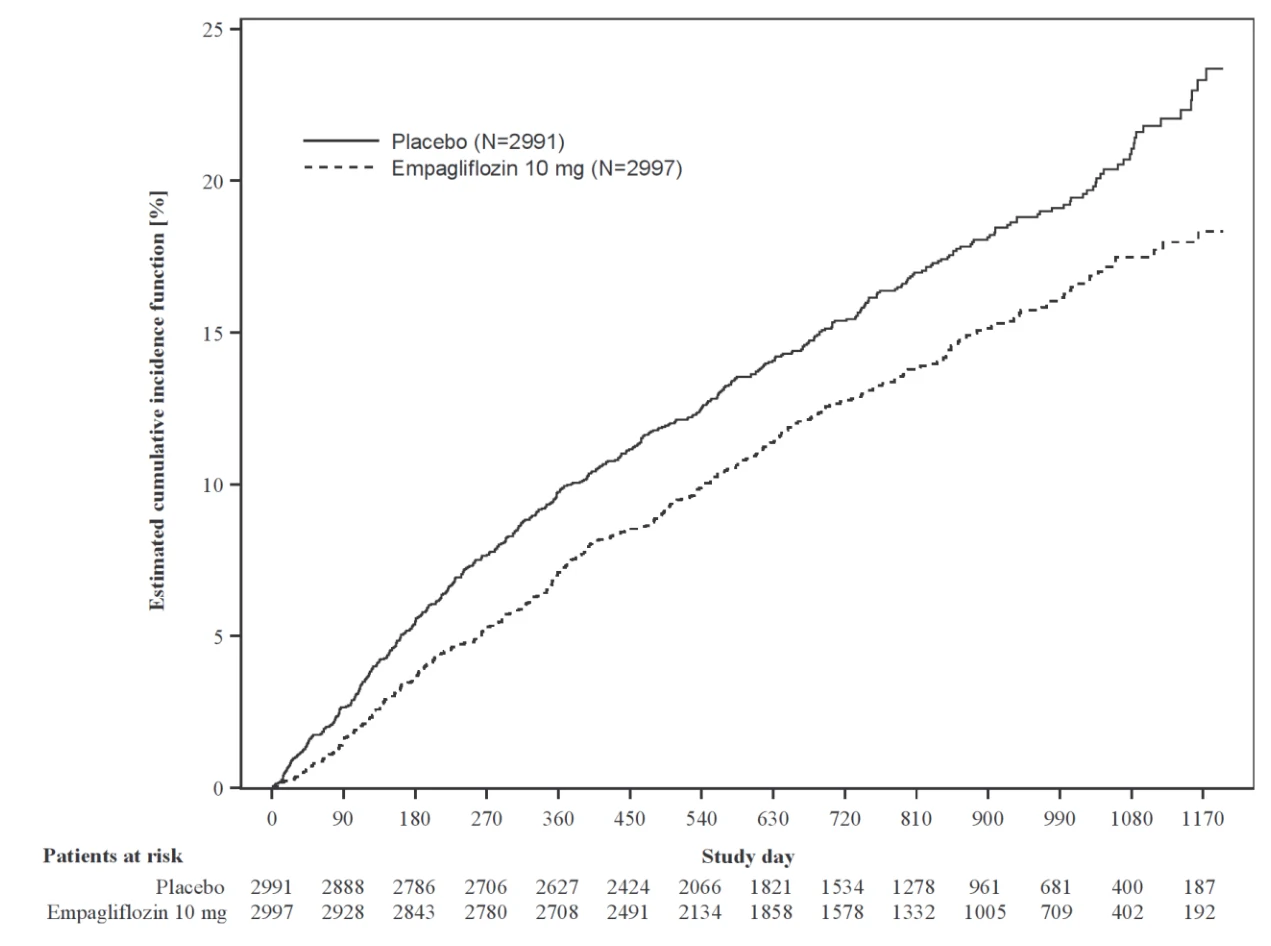
Figure 12: Time to event of adjudicated HHF (first and recurrent, EMPEROR-Preserved)
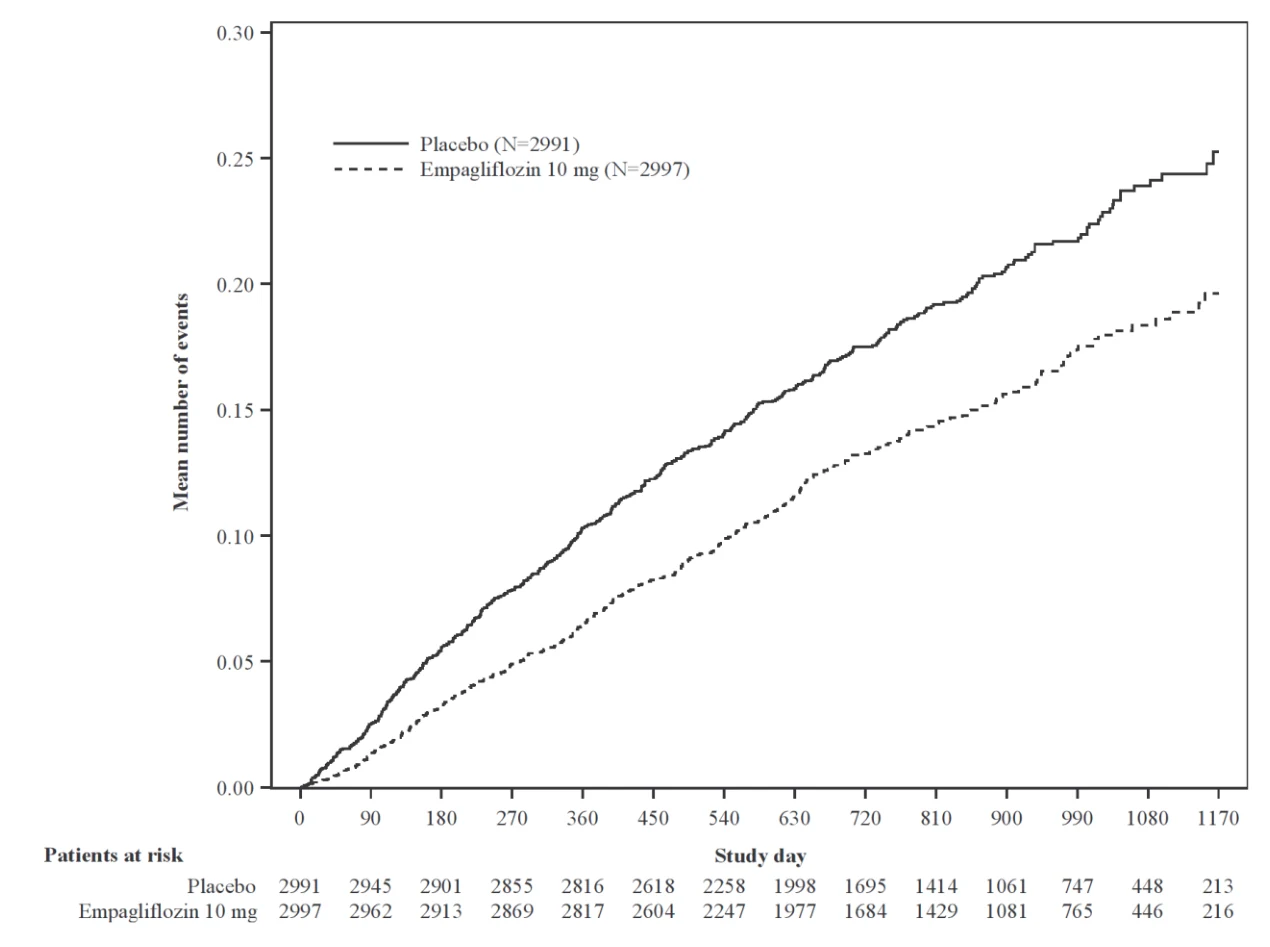
The results of the primary composite endpoint were consistent across each of the pre-specified subgroups (see Figure 13).
Figure 13: Treatment Effects for the Primary Composite Endpoint (Cardiovascular Death and Hospitalization for Heart Failure) Subgroup Analysis (EMPEROR-Preserved)
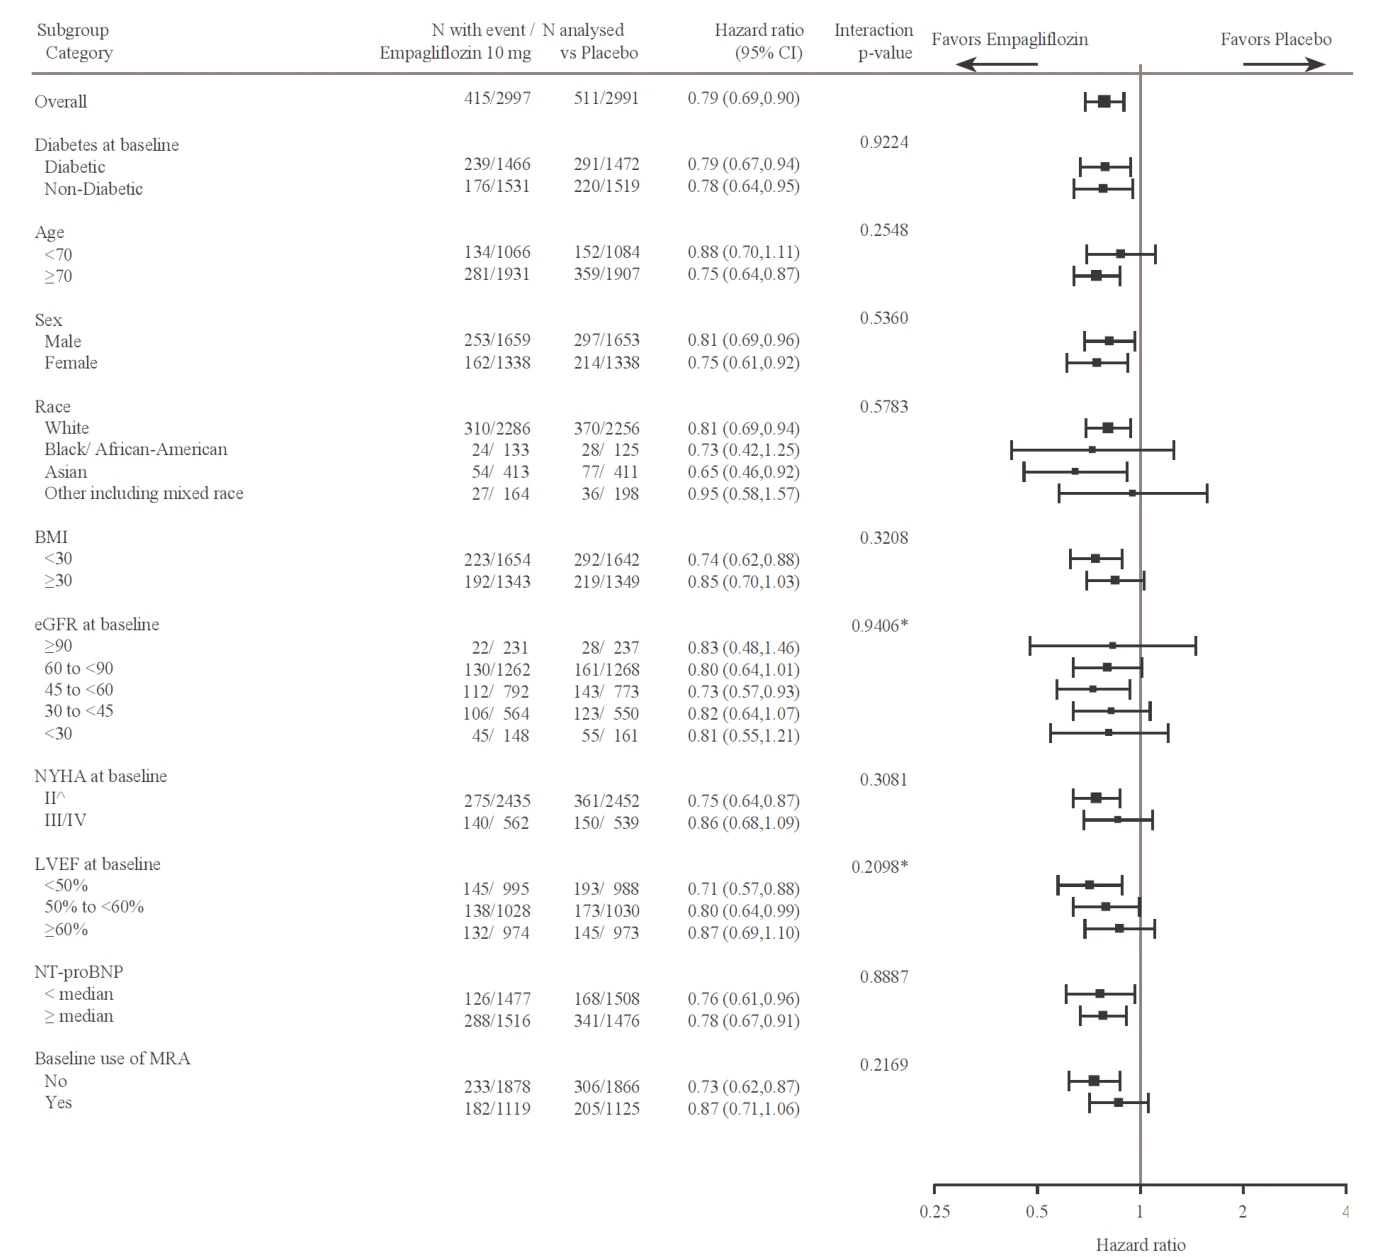
^4 patients with NYHA class I are counted in subgroup NYHA class II
*trend test
Figure 14: Primary and key secondary endpoints by baseline T2DM status in patients from EMPEROR-Preserved)
Time to first event of adjudicated HHF or CV death
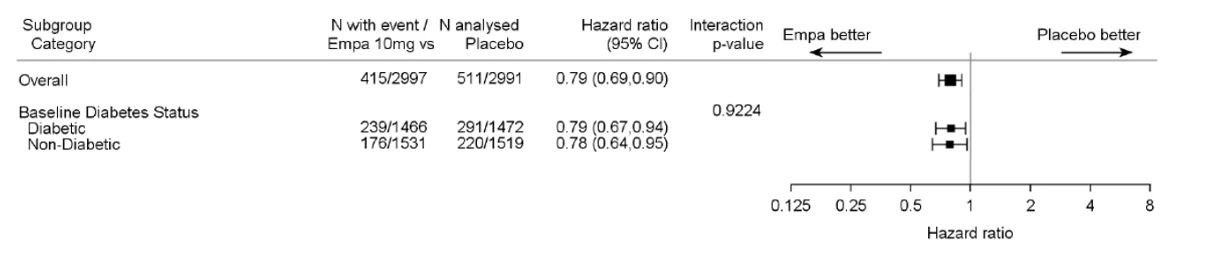
Joint frailty model of adjudicated hospitalization for heart failure and adjudicated CV death
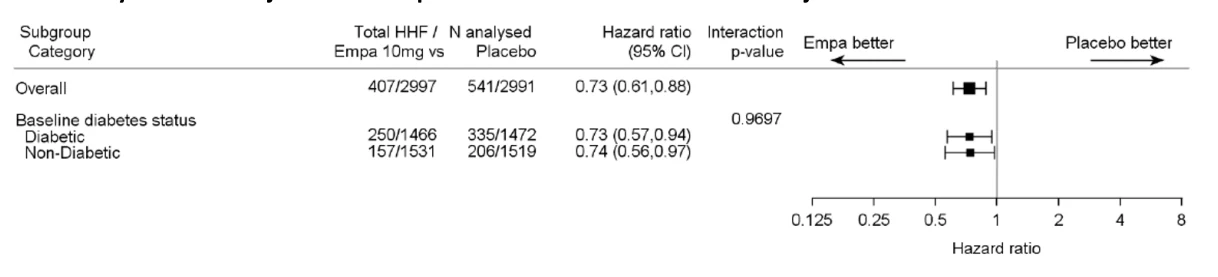
In a pooled analysis of the relationship between LVEF and primary composite endpoint in EMPEROR-Reduced and EMPEROR-Preserved, a consistent beneficial treatment effect of JARDIANCE was observed in patients across the LVEF spectrum (see Figure 15).
Figure 15: Treatment Effect for the Primary Composite Endpoint (Cardiovascular Death or Hospitalization for Heart Failure) by baseline LVEF in EMPEROR-Reduced and EMPEROR-Preserved
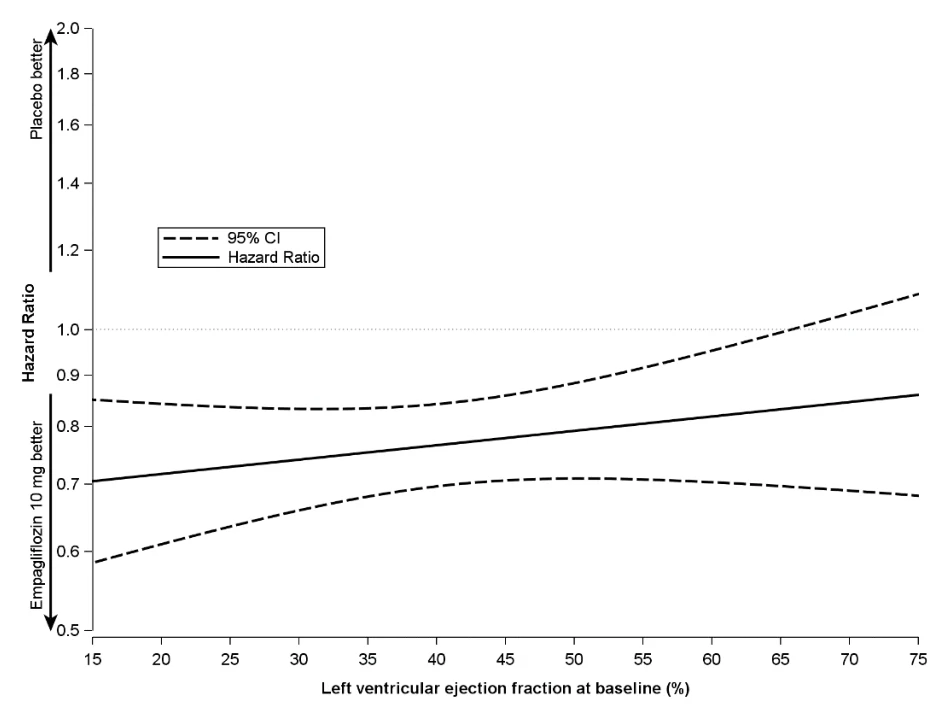
Use in patients hospitalized for acute heart failure who have been stabilised (EMPULSE, 1245-0204)
A randomized, double-blind, placebo-controlled study (EMPULSE) was conducted in 530 patients hospitalized for acute heart failure (33% with de novo and 67% with decompensated chronic heart failure) irrespective of LVEF who have been stabilised. The index hospitalization was primarily triggered by intravascular volume overload. Patients with recent acute coronary syndrome, myocardial infarction or transient ischemic attack were excluded.
The study evaluated the clinical benefit and safety of JARDIANCE 10 mg once daily as adjunct to standard of care therapy for heart failure. Treatment was initiated in the hospital once stabilisation was confirmed and continued for 90 days. The primary endpoint was a hierarchical composite of death, number of heart failure events (including hospitalizations for heart failure, urgent heart failure visits and unplanned outpatient visits), time to first heart failure event, and change from baseline in Kansas City Cardiomyopathy Questionnaire Total Symptom Score (KCCQ-TSS), which determines self-reported burden and frequency of heart failure symptoms, after 90 days of treatment assessed by the win ratio. Baseline therapy included angiotensin-converting-enzyme (ACE) inhibitors/angiotensin receptor blockers/angiotensin receptor-neprilysin inhibitor (70.0%), beta blockers (79.4%), and diuretics (90.6%). According to the clinical trial protocol JARDIANCE was added as adjunct to standard therapy for heart failure with or without reduced ejection fraction and did not replace any other treatment indicated to manage heart failure.
Participants were equally randomized to JARDIANCE 10 mg or placebo and followed for a median of 98 days. The study population consisted of 66% men and 34% women with a mean age of 68.5 years (range: 22-98 years); 37% were 75 years of age or older; 78% of the study population were White, 11% Asian and 10% Black/African American.
At randomization, 3% of patients were in NYHA class I, 35% in class II, 53% in class III, 9% in class IV and 45% of patients had T2DM. The EMPULSE study population included 67% of patients with LVEF ≤40%, and 32% with LVEF >40%. At baseline, 37% of patients had an eGFR of ≥60 ml/min/1.73 m2, 23% of 45 to <60 ml/min/1.73 m2, 25% of 30 to <45 ml/min/1.73 m2, and 10% of <30 ml/min/1.73 m2.
In the primary analysis, each patient in the JARDIANCE group was compared to every patient in the placebo group within each stratum (de novo or decompensated chronic heart failure). Pairwise comparisons were performed in a hierarchical fashion and stopped when the winning treatment could be determined in each pair for time to death, followed by number of heart failure events, time to first heart failure event, and finally a ≥5 point between-participant difference in change from baseline in KCCQ-TSS. The stratified win ratio was then calculated by combining the number of wins in the JARDIANCE group divided by the number of losses across strata.
Overall, participants taking JARDIANCE were 36% more likely to experience a clinical benefit compared to placebo (win ratio 1.36, 95% CI 1.09, 1.68; p = 0.0054; see Figure 16). The majority of the benefit was observed in the KCCQ-TSS endpoint.
The benefits were generally consistent across the pre-specified subgroups, including de novo heart failure and decompensated chronic heart failure, and were independent of LVEF.
Figure 16: Primary efficacy endpoint: win ratio of clinical benefit, overall and by subgroup (EMPULSE)
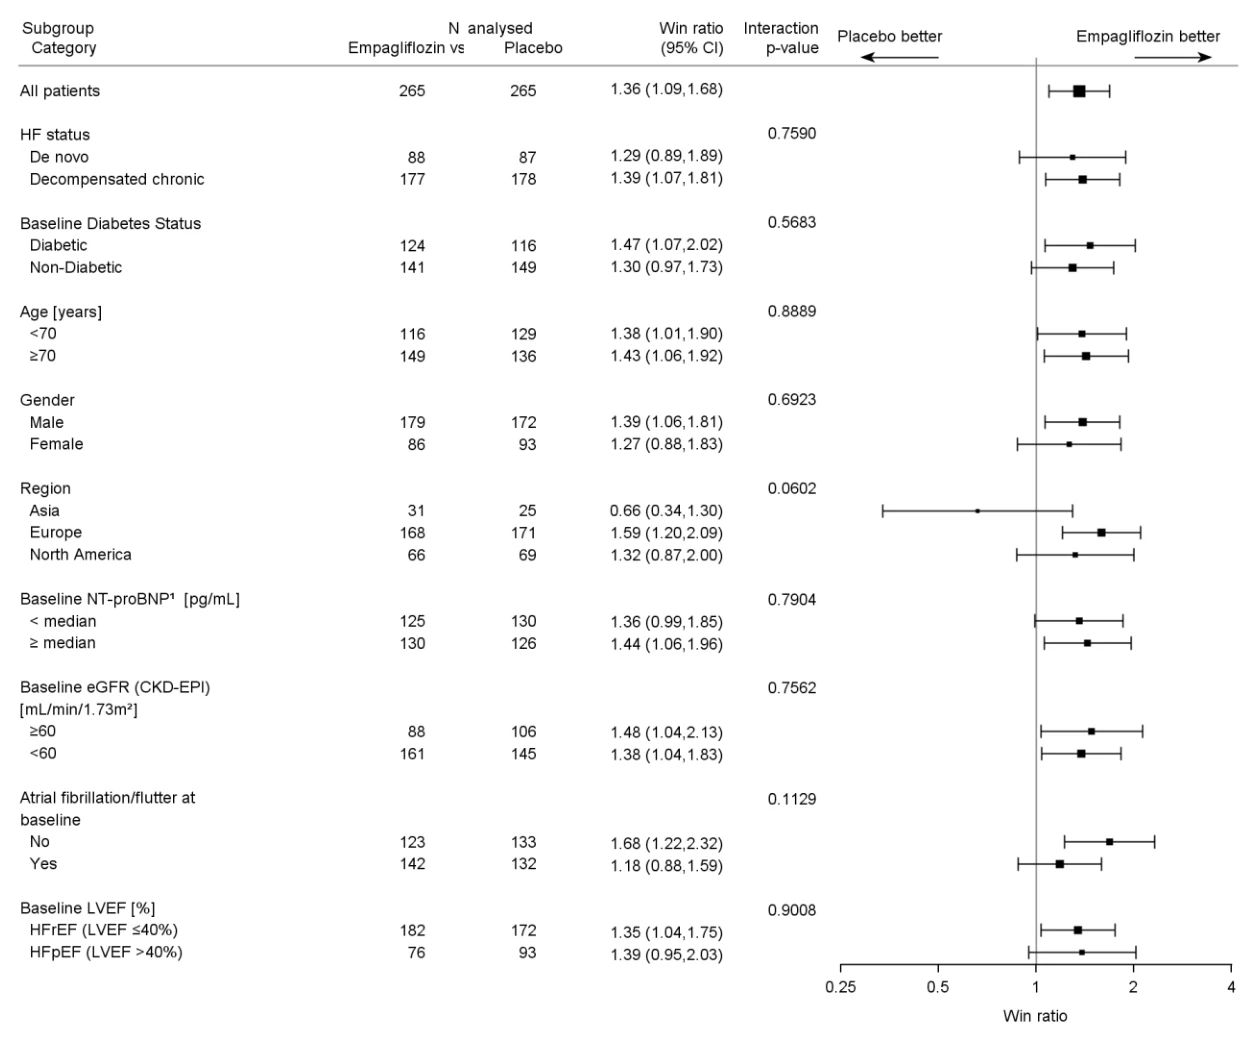
Chronic Kidney Disease
Table 27: Summary of patient demographics for clinical trials in patients with Chronic Kidney Disease
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) randomized | Mean age (Range) | Sex (%M/F) |
1245.137 EMPA-KIDNEY Study | randomized, double-blind, placebo-controlled study | Empagliflozin 10 mg vs placebo + standard of care Tablets, orally, once daily treatment: event-driven follow up: about 24.3 months | Total: 6609 Empagliflozin: 10 mg: 3304 Placebo: 3305 | 63.3 years (Range: 18-94 years) | 66.8% M/ 33.2% F |
Use in Patients with chronic kidney disease (EMPA-KIDNEY Study)
A randomized, double-blind, placebo-controlled study of JARDIANCE 10 mg once daily (EMPA-KIDNEY) was conducted in patients (N= 6609) with chronic kidney disease (eGFR ≥20 -to <45 mL/min/1.73m2; or eGFR ≥45 -to <90 mL/min/1.73m2 with UACR ≥200 mg/g) to assess cardio-renal outcomes as adjunct to standard of care therapy. Patients with polycystic kidney disease, or patients requiring or with a recent history (within 3 months) of intravenous immunosuppressive therapy or greater than 45 mg of prednisone or equivalent were excluded from the study.
The primary endpoint was the time to first occurrence of kidney disease progression (sustained ≥40% eGFR decline from randomization, sustained eGFR <10 mL/min/1.73m², end-stage kidney disease, or renal death) or CV death. Key secondary endpoints assessed were all-cause hospitalization (first and recurrent), first occurrence of hospitalization for heart failure or CV death, and all-cause mortality. Baseline therapy included an appropriate use of a RAS-inhibitor (85.2% ACE inhibitor or angiotensin receptor blocker).
A total of 3304 patients were randomized to JARDIANCE 10 mg once daily (placebo: 3305) and followed for a median of 24.3 months. The study population consisted of 66.8% men and 33.2% women with a mean age of 63.3 years (range: 18-94 years), 23.0% were 75 years of age or older. 58.4% of the study population were White, 36.2% Asian and 4.0% Black/African American. Approximately 44.4% (N= 2936) of the patients had type 2 diabetes mellitus.
At baseline, the mean eGFR was 37.3 mL/min/1.73 m2, 21.2% patients had an eGFR of ≥45 mL/min/1.73 m2, 44.3% of 30 to <45 mL/min/1.73 m2 and 34.5% <30 mL/min/1.73 m2 including 254 patients with an eGFR <20 mL/min/1.73 m2. The median UACR was 329 mg/g, 20.1% patients had an UACR <30 mg/g, 28.2% had an UACR 30 to ≤300mg/g and 51.7% had an UACR >300 mg/g. Primary causes of chronic kidney disease were diabetic nephropathy/diabetic kidney disease (31%), glomerular disease (25%), hypertensive/renovascular disease (22%) and other/unknown (22%).
JARDIANCE was superior in reducing the risk of the primary composite endpoint of sustained ≥40% eGFR decline, sustained eGFR <10 mL/min/1.73m², ESKD, renal death or CV death compared with placebo. Additionally, JARDIANCE significantly reduced the risk of all-cause hospitalization, first and recurrent.
Table 28: Treatment effect for the primary composite endpoint, its components, and key secondary endpoint
| Placebo | Empagliflozin 10 mg | |
|---|---|---|
| N | 3305 | 3304 |
| Time to first occurrence of composite of sustained ≥40% eGFR decline, sustained eGFR <10 mL/min/1.73m², ESKD*, renal death or CV death, N (%) | 558 (16.9) | 432 (13.1) |
| Hazard ratio vs. placebo (95% CI) | 0.72 (0.64, 0.82) | |
| p−value for superiority | <0.0001 | |
| Sustained ≥40% eGFR decline from randomization, N (%) | 474 (14.3) | 359 (10.9) |
| Hazard ratio vs. placebo (95% CI) | 0.70 (0.61, 0.81) | |
| p-value | <0.0001 | |
| Sustained eGFR <10 mL/min/1.73m², N (%) | 167 (5.1) | 116 (3.5) |
| Hazard ratio vs. placebo (95% CI) | 0.69 (0.54, 0.87) | |
| p-value | 0.0021 | |
| ESKD*, N (%) | 158 (4.8) | 108 (3.3) |
| Hazard ratio vs. placebo (95% CI) | 0.67 (0.52, 0.85) | |
| p-value | 0.0012 | |
| Renal death, N (%)** | 4 (0.1) | 4 (0.1) |
| CV Death, N (%) | 69 (2.1) | 59 (1.8) |
| Hazard ratio vs. placebo (95% CI) | 0.84 (0.60, 1.19) | |
| p-value | 0.3366 | |
| All-cause hospitalizations (first and recurrent), N of events | 1895 | 1611 |
| Hazard ratio vs. placebo (95% CI) | 0.86 (0.78, 0.95) | |
| p-value | 0.0025 |
CV = cardiovascular, eGFR = Estimated glomerular filtration rate
* End-stage kidney disease (ESKD) is defined as the initiation of maintenance dialysis or receipt of a kidney transplant.
** There were too few events of renal death to compute a reliable hazard ratio.
Figure 17: Time to First Occurrence of the Primary Composite Endpoint, Sustained ≥40% eGFR Decline from Randomization, Sustained eGFR <10 mL/min/1.73 m2, ESKD or Renal Death, or CV Death
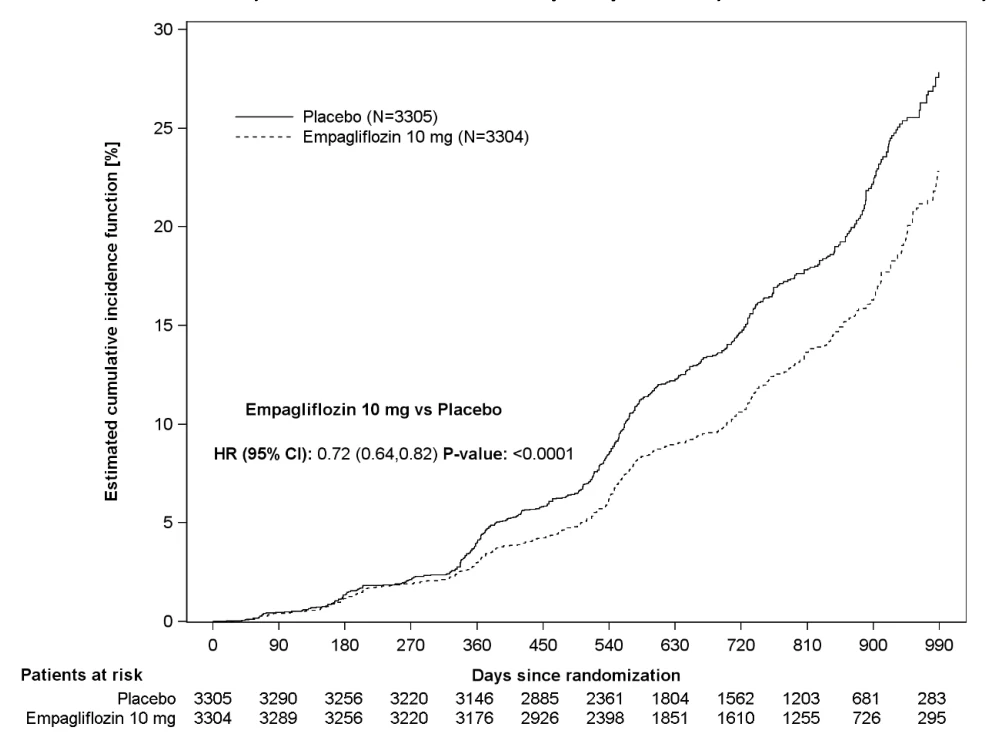
Figure 18: Treatment Effects for the Primary Composite Endpoint (Sustained ≥40% eGFR Decline,Sustained eGFR <10 mL/min/1.73 m2, ESKD, Renal Death, or CV Death) Subgroup Analysis
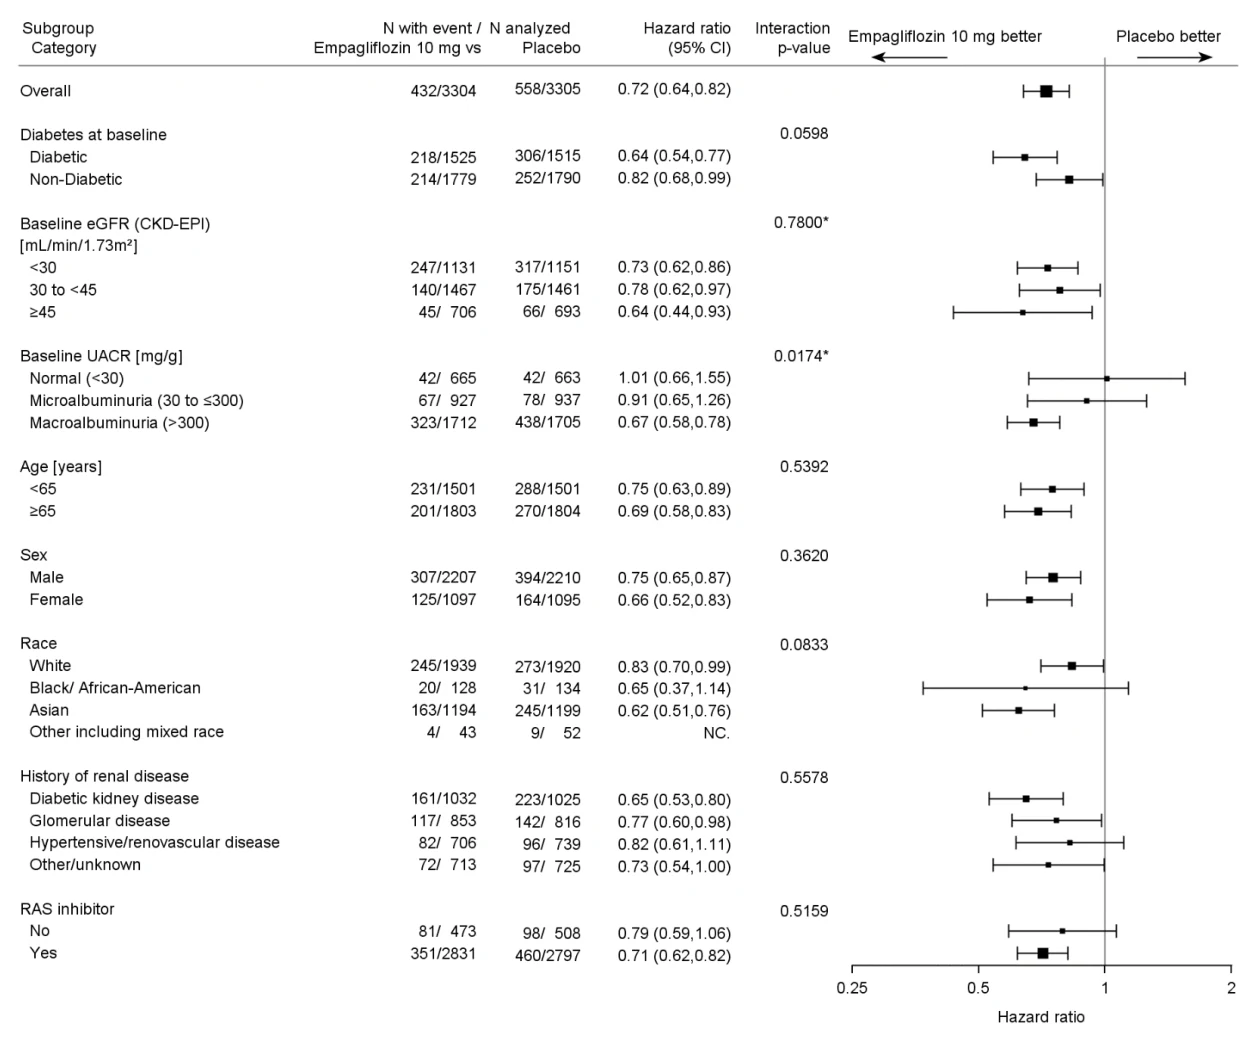
The results of the primary composite endpoint were generally consistent across the pre-specified subgroups examined, including eGFR categories, underlying cause of renal disease, diabetes status, or background use of RAS inhibitors. The treatment benefits with JARDIANCE were more clearly evident in patients with high levels of albuminuria than patients with low levels of albuminuria.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute toxicity: Empagliflozin demonstrated low acute toxicity. The single lethal oral dose of empagliflozin was greater than 2000 mg/kg in mice and rats.
Sub-chronic and chronic toxicity: Repeat-dose oral toxicity studies were conducted in mice, rats and monkeys for up to 13, 26, and 52 weeks, respectively. Signs of toxicity were generally observed at exposures greater than or equal to 10 times the human exposure (AUC) at the maximum recommended dose of 25 mg. Most toxicity was consistent with secondary pharmacology related to urinary glucose loss and included decreased body weight and body fat, increased food consumption, diarrhea, dehydration, decreased serum glucose and increases in other serum parameters reflective of increased protein metabolism, gluconeogenesis and electrolyte imbalances, urinary changes such as polyuria and glycosuria. Increases in liver weight, elevated hepatic enzyme activities (e.g., AST and ALT) and hepatocellular vacuolation were observed in mice, rats and dogs. These changes in the liver may be related to gluconeogenesis and/or mobilization of lipid for energy production. The main target organ of empagliflozin toxicity was the kidney. Microscopic changes in the kidney were observed across species and included tubular karyomegaly, single cell necrosis, cystic hyperplasia and hypertrophy (mouse), renal mineralization and cortical tubular vacuolation (rat), and tubular nephropathy and interstitial nephritis (dog).
In a 2-year study in mice, mortality associated with urinary tract lesions was dose-dependently increased for males given empagliflozin at oral doses of ≥100 mg/kg/day (≥4 times the clinical dose of 25 mg based on AUC comparisons).
Carcinogenicity: The carcinogenic potential of empagliflozin was evaluated in 2-year studies in mice and rats. Empagliflozin did not increase the incidence of tumors in female rats up to the highest dose of 700 mg/kg/day (up to 72 times the clinical dose of 25 mg based on AUC comparisons). In male rats, treatment-related benign vascular proliferative lesions (hemangiomas) of the mesenteric lymph node were observed at 700 mg/kg/day (approximately 42 times the clinical dose of 25 mg based on AUC comparisons), but not at 300 mg/kg/day which corresponds to approximately 26 times the clinical exposure from 25 mg dose. These tumors are common in rats and the incidence (18%) was within literature historical control (0-26%). No vascular lesions were seen in the mouse and dog. Empagliflozin did not increase the incidence of tumors in female mice at doses up to 1000 mg/kg/day (up to, approximately 62 times the clinical dose of 25 mg based on AUC comparisons). Renal tumors were observed in male mice at 1000 mg/kg/day (approximately 45 times the clinical dose of 25 mg based on AUC comparisons), but not at 300 mg/kg/day which corresponds to approximately 11 times the clinical exposure from a 25 mg dose. The mode of action for these tumors may be dependent on the natural predisposition of the male mouse to renal pathology which is exacerbated by a male mouse kidney-specific cytotoxic oxidative metabolite. Therefore, the renal tumors found in mice may not be relevant to patients given clinical doses of empagliflozin.
Genotoxicity: Empagliflozin was not genotoxic in the Ames bacterial mutagenesis test, the L5178/tk+/-mouse lymphoma assay, or the in vivo rat micronucleus test.
Reproductive and Developmental Toxicology: In a study of fertility and early embryonic development in rats, empagliflozin had no effects on mating and fertility in males or females or early embryonic development up to the highest dose of 700 mg/kg/day (approximately 50 times the clinical dose of 25 mg based on AUC comparisons). Empagliflozin administered during the period of organogenesis was not teratogenic at doses up to 300 mg/kg/day in the rat or rabbit, which corresponds to approximately 48 times or 128 times the clinical dose of 25 mg based on AUC comparisons, respectively. Doses of empagliflozin causing maternal toxicity in the rat also caused the malformation of bent limb bones at exposures approximately 155 times the clinical exposure from a 25 mg dose. Maternally toxic doses in the rabbit also caused increased embryofetal loss at doses approximately 139 times the clinical dose of 25 mg based on AUC comparisons.
In a pre- and postnatal toxicity study in rats, empagliflozin was administered from gestation day 6 through to lactation day 20 (weaning) at 10, 30 and 100 mg/kg/day, and pups were indirectly exposed in utero and throughout lactation. There was no evidence of maternal toxicity up to the high dose of 100 mg/kg/day; however, a reduction in F1 pup body weight gains, mainly during lactation, was observed at doses of ≥30 mg/kg/day (≥4 times the clinical dose of 25 mg based on AUC comparisons). The F1 male pups also had learning and memory deficits at 100 mg/kg (approximately 16 times the clinical dose of 25 mg based on AUC comparisons) on postnatal day (PND) 22, but not on PND 62. These neurobehavioral effects were likely to be secondary to the retarded growth rates of the F1 male pups. The NOAEL for F1 neonatal toxicity was 10 mg/kg/day (approximately 1.4 times the clinical dose of 25 mg based on AUC comparisons).
Special Toxicity: Empagliflozin demonstrated good in vitro potency towards inhibition of human (IC50 of 1.3 nM) and rat (IC50 of 1.7 nM) renal SGLT2 transporters. The three major human metabolites of empagliflozin, all glucuronides, exhibited very weak activity toward the SGLT2 transporter in vitro, with IC50 values ranging from 860 – 1435 nM. Oral doses of empagliflozin increased urinary glucose excretion in diabetic rodents and normoglycemic dogs. This triggered the lowering of blood glucose in diabetic rodents after single oral dosing, as well as after chronic treatment.
Juvenile Toxicity: In a juvenile toxicity study, empagliflozin was administered directly to young rats from post-natal day 21 until postnatal day 90 at oral doses of 1, 10, 30 and 100 mg/kg/day. Increases in kidney weights were observed in males at ≥ 10 mg/kg/day (≥ 0.7 times the clinical dose of 25 mg based on AUC comparisons) and in females at ≥ 30 mg/kg/day (≥ 4 times the clinical dose of 25 mg based on AUC comparisons). Minimal to mild renal tubular and pelvic dilation was seen at 100 mg/kg/day, which approximates 11-times the clinical dose of 25 mg based on AUC comparisons. These findings were absent after a 13-week, drug-free recovery period.