


Product Monograph - Kengrexal
1 INDICATIONS
KENGREXAL (cangrelor) is indicated for reducing the risk of thrombotic cardiovascular events (periprocedural myocardial infarction (MI), repeat coronary revascularization, and stent thrombosis (ST)) in patients with coronary artery disease undergoing percutaneous coronary intervention who have not been treated with an oral P2Y12 platelet inhibitor and are not being given a glycoprotein IIb/IIIa inhibitor.
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥75 years of age): No overall differences in safety or effectiveness were observed between the geriatric population and patients <75 years of age.
2 CONTRAINDICATIONS
KENGREXAL is contraindicated in:
- patients with significant active bleeding or an increased risk of bleeding (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS).
- patients who had an ischemic stroke or any previous hemorrhagic stroke.
- patients with known hypersensitivity (e.g., anaphylaxis) to KENGREXAL or any component of the product, including any non-medicinal ingredient or component of the container (see 8 ADVERSE REACTIONS). For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- KENGREXAL is intended for intravenous injection or infusion only, in an acute and hospital setting
Transitioning Patients to Oral P2Y12 Therapy
To maintain platelet inhibition after discontinuation of KENGREXAL infusion, administer an oral P2Y12 platelet inhibitor, as described below:
- Ticagrelor: 180 mg immediately after discontinuation of KENGREXAL (see 9 DRUG INTERACTIONS and 10 CLINICAL PHARMACOLOGY).
- Prasugrel: 60 mg immediately after discontinuation of KENGREXAL. Do not administer prasugrel prior to discontinuation of KENGREXAL (see 9 DRUG INTERACTIONS and 10 CLINICAL PHARMACOLOGY).
- Clopidogrel: 600 mg immediately after discontinuation of KENGREXAL. Do not administer clopidogrel prior to discontinuation of KENGREXAL (see 9 DRUG INTERACTIONS and 10 CLINICAL PHARMACOLOGY).
4.2 Recommended Dose and Dosage Adjustment
- The recommended dosage of KENGREXAL is a 30 µg/kg IV bolus followed immediately by a 4 µg/kg/min IV infusion. Initiate the bolus infusion prior to PCI. The maintenance infusion should ordinarily be continued for at least 2 hours or for the duration of PCI, whichever is longer. The infusion may be continued for maximal duration of 4 hours.
- No dosage adjustment is required for patients with mild, moderate, or severe renal impairment (see 10 CLINICAL PHARMACOLOGY).
- KENGREXAL has not been studied in patients with hepatic impairment. The metabolism of KENGREXAL is not dependent of hepatic function, so dosage adjustment is not expected to be required for patients with hepatic impairment (see 10 CLINICAL PHARMACOLOGY).
- Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use (see 1 INDICATIONS, 1.1 Pediatrics).
- Geriatrics (≥75 years of age): No dose adjustment is needed in older patients.
4.3 Reconstitution
KENGREXAL is intended for IV administration, after reconstitution and dilution.
Aseptic procedures should be used for the preparation of KENGREXAL.
Preparation
Reconstitute the vial prior to dilution in a bag. For each 50 mg/vial, reconstitute by adding 5 mL of Sterile Water for Injection (see Table 1). Swirl gently until all material is dissolved. Avoid vigorous mixing. Allow any foam to settle. Ensure that the contents of the vial are fully dissolved and the reconstituted material is a clear, colourless to pale yellow solution. Parenteral drug products should be inspected visually for particulate matter after reconstitution.
Table 1: Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Concentration per mL |
| 10 mL | 5 mL Sterile Water for Injection | 5 mL | 10 mg/mL |
Before administration, each reconstituted vial must be diluted further with Normal Saline (Sodium Chloride Injection 0.9% USP) or 5% Dextrose Injection USP.
Withdraw the contents from one reconstituted vial and add to one 250 mL saline bag. Mix the bag thoroughly. This dilution will result in a concentration of 200 µg/mL and should be sufficient for at least 2 hours of dosing. Patients 100 kg and over will require a minimum of two bags.
Reconstituted KENGREXAL should be diluted immediately. Diluted KENGREXAL is stable for up to 12 hours in 5% Dextrose Injection and 24 hours in normal saline at room temperature. Discard any unused portion of reconstituted solution remaining in the vial.
4.4 Administration
Administer KENGREXAL in a dedicated IV line.
Administer the bolus volume rapidly (<1 minute) from the diluted bag via manual IV push or pump. Ensure bolus is completely administered before the start of PCI. Start the infusion immediately after administration of the bolus (see 4 DOSAGE AND ADMINISTRATION).
4.5 Missed Dose
Not applicable.
5 OVERDOSAGE
There is no specific treatment to reverse the antiplatelet effect of KENGREXAL but platelet function is restored within 1 hour after KENGREXAL is discontinued.
In clinical trials, 36 patients received an overdose of KENGREXAL, ranging from 36 to 300 µg/kg (bolus dose) or 4.8 to 13.7 µg/kg/min (infusion dose). The maximum overdose received was 10 times the PCI bolus dose or 3.5 times the PCI infusion dose in 4 patients.
Bleeding was the most frequently observed adverse event and occurred in 3 patients of the 36 who overdosed (one GUSTO moderate and 2 GUSTO mild bleedings).
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2: Dosage Forms, Strengths, Composition and Packaging
KENGREXAL is supplied as a sterile lyophilized powder in single-use 10 mL vials containing 50 mg cangrelor.
7 WARNINGS AND PRECAUTIONS
Cardiovascular
Cardiac tamponade
Treatment with KENGREXAL may increase the risk of cardiac tamponade. In the CHAMPION program studies conducted in patients undergoing PCI, there were more cardiac tamponades at 30 days with cangrelor (0.12%) than with clopidogrel (0.02%).
Endocrine and Metabolism
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous injection | 50 mg of KENGREXAL lyophilized powder in a single-use 10 mL glass vial for reconstitution | Mannitol, sodium hydroxide (for pH adjustment), sorbitol |
Fructose intolerance
KENGREXAL contains sorbitol. Patients with rare hereditary problems of fructose intolerance should not take this medicine.
Hematologic
Risk of bleeding
KENGREXAL increases the risk of bleeding.
In CHAMPION PHOENIX, bleeding events of all severities were more common with KENGREXAL than with clopidogrel (see 8 ADVERSE REACTIONS). Bleeding complications with KENGREXAL were consistent across a variety of clinically important subgroups (see Figure 1). In patients with severe renal impairment a higher rate of GUSTO moderate bleeding was reported in the cangrelor group (6.7%) compared to clopidogrel (1.4%).
Once KENGREXAL is discontinued, platelet function is restored after 1 hour (see 10 CLINICAL PHARMACOLOGY).
Although most bleeding associated with the use of cangrelor occurs at the site of arterial puncture, hemorrhage can occur at any site. Any unexplained fall in blood pressure or hematocrit should lead to the serious consideration of a hemorrhagic event and the cessation of cangrelor administration. Cangrelor should be used with caution in patients with disease states associated with an increased bleeding risk and in patients taking medications that may increase the risk of bleeding.
Intracranial hemorrhage
Treatment with KENGREXAL may increase the risk of intracranial hemorrhage. In the pooled safety analysis of CHAMPION program studies conducted in patients undergoing PCI, there were more intracranial bleeds at 30 days with cangrelor (0.07%) than with clopidogrel (0.02%), of which 4 bleeds with cangrelor and 1 bleed with clopidogrel were fatal. KENGREXAL is contraindicated in patients who had an ischemic stroke or any previous hemorrhagic stroke (see 2 CONTRAINDICATIONS).
Immune
Hypersensitivity
Hypersensitivity reactions may occur after treatment with KENGREXAL. A higher rate of serious cases of hypersensitivity were recorded with cangrelor (0.05%) than with control (0.02%). These included cases of anaphylactic reactions/shock, angioedema, bronchospasm (8 ADVERSE REACTIONS).
Renal
Effects on renal function
Cangrelor should be used with caution in patients with severe renal impairment. In patients with severe renal impairment (creatinine clearance 15 to 30 mL/min) a higher rate of worsening in renal function (3.2%) was reported in the cangrelor group compared to clopidogrel (1.4%). In addition, a higher rate of GUSTO moderate bleeding was reported in the cangrelor group (6.7%) compared to clopidogrel (1.4%). In the CHAMPION program studies conducted in patients undergoing PCI, events of acute renal failure (0.1%), renal failure (0.1%), and increased serum creatinine (0.2%) were reported to occur after administration of cangrelor in clinical trials (see 8 ADVERSE REACTIONS).
Reproductive Health: Female and Male Potential
Fertility
No human data on the effect of cangrelor on fertility is available. Animal studies with cangrelor demonstrate a risk of impaired male fertility at high exposure doses (12 times the maximum recommended human dose [MRHD]). Female fertility was not impacted with cangrelor treatment, however, reduced post-implantation survival of embryos was observed at dose 3 times MRHD (see 16 NON-CLINICAL TOXICOLOGY).
Respiratory
Risk of dyspnea
Treatment with cangrelor may increase the risk of dyspnea. In the CHAMPION program studies conducted in patients undergoing PCI dyspnea (including exertional dyspnea) occurred more commonly in patients treated with cangrelor (1.3%) than clopidogrel (0.4%). Most dyspnea events were mild or moderate in severity. The mean duration of dyspnea was 12.7 hours, and the median duration of dyspnea was 2 hours in patients receiving cangrelor (see 8 ADVERSE REACTIONS). In most cases dyspnea started during cangrelor infusion and ended after infusion completion.
7.1 Special Populations
7.1.1 Pregnant Women
There are no available data on cangrelor use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In the animal studies in pregnant rabbits and rats no treatment related maternal toxicity was observed at doses approximately 3 times MRHD. However, increased incidence of intrauterine deaths is observed in animals at this dose. Exposure of cangrelor in pregnant rats and rabbits resulted in increased incidence of incomplete ossification of skull and sternebrae bone and retarded fetal development at levels those expected in humans (see 16 NON-CLINICAL TOXICOLOGY).
KENGREXAL should not be used during pregnancy unless there has been careful consideration of the benefit for the mother and the risk to the fetus (see 7 WARNINGS AND PRECAUTIONS and 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
There are no data on the presence of cangrelor in human milk or animal milk, the effects on the breastfed infant, or the effects on milk production. Due to its short half-life, cangrelor exposure is expected to be very low in the breastfed infant. However, risk to breastfed infant cannot be excluded.
7.1.3 Pediatrics
Pediatrics (<18 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
In CHAMPION PHEONIX, 18% of patients were ≥75 years of age. No overall differences in safety or effectiveness were observed between these patients and those patients <75 years (see 14 CLINICAL TRIALS).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common adverse reactions with cangrelor include mild and moderate bleeding and dyspnea. Serious adverse reactions associated with cangrelor in patients with coronary artery disease include severe/life threatening bleeding and hypersensitivity.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials, therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety of KENGREXAL has been evaluated in 13,301 subjects in controlled trials, of whom 5529 were in the CHAMPION PHOENIX trial.
Bleeding
There was a greater incidence of bleeding with KENGREXAL than with clopidogrel. No baseline demographic factor altered the relative risk of bleeding with KENGREXAL (see Table 3 and Figure 1).
Table 3: Major Bleeding Results in the CHAMPION PHOENIX Study (Non-CABG Related Bleeding)
| CHAMPION PHOENIX | KENGREXAL (N=5529) | Clopidogrel (N=5527) | ||||
| Any GUSTO bleeding, n (%) | 857 (15.5) | 602 (10.9) | ||||
| Severe/life-threateninga | 11 (0.2) | 6 (0.1) | ||||
| Moderateb | 21 (0.4) | 14 (0.3) | ||||
| Mildc | 825 (14.9) | 582 (10.5) | ||||
| Any TIMI bleeding, n (%) | 45 (0.8) | 17 (0.3) | ||||
| Majord | 12 (0.2) | 6 (0.1) | ||||
| Minore | 33 (0.6) | 11 (0.2) | ||||
CABG = coronary artery bypass grafting; GUSTO = Global Utilization of Streptokinase and Tissue Plasminogen Activator for Occluded Arteries; TIMI = Thrombolysis in Myocardial Infarction a Intracranial hemorrhage or bleeding resulting in substantial hemodynamic compromise requiring treatment. b Requiring blood transfusion but not resulting in hemodynamic compromise. c All other bleeding not included in severe or moderate. d Any intracranial hemorrhage, or any overt bleeding associated with a reduction in hemoglobin of ≥5 g/dL (or, when hemoglobin is not available, an absolute reduction in hematocrit ≥15%). e Any overt sign of bleeding (including observation by imaging techniques) that is associated with a reduction in hemoglobin of ≥3 g/dL and <5 g/dL (or, when hemoglobin is not available, an absolute reduction in hematocrit of ≥9% and <15%). Note: Safety population is all randomized subjects who received at least one dose of study drug. | ||||||
Figure 1: Bleeding Results in the CHAMPION PHOENIX Study (All Non-CABG Related)
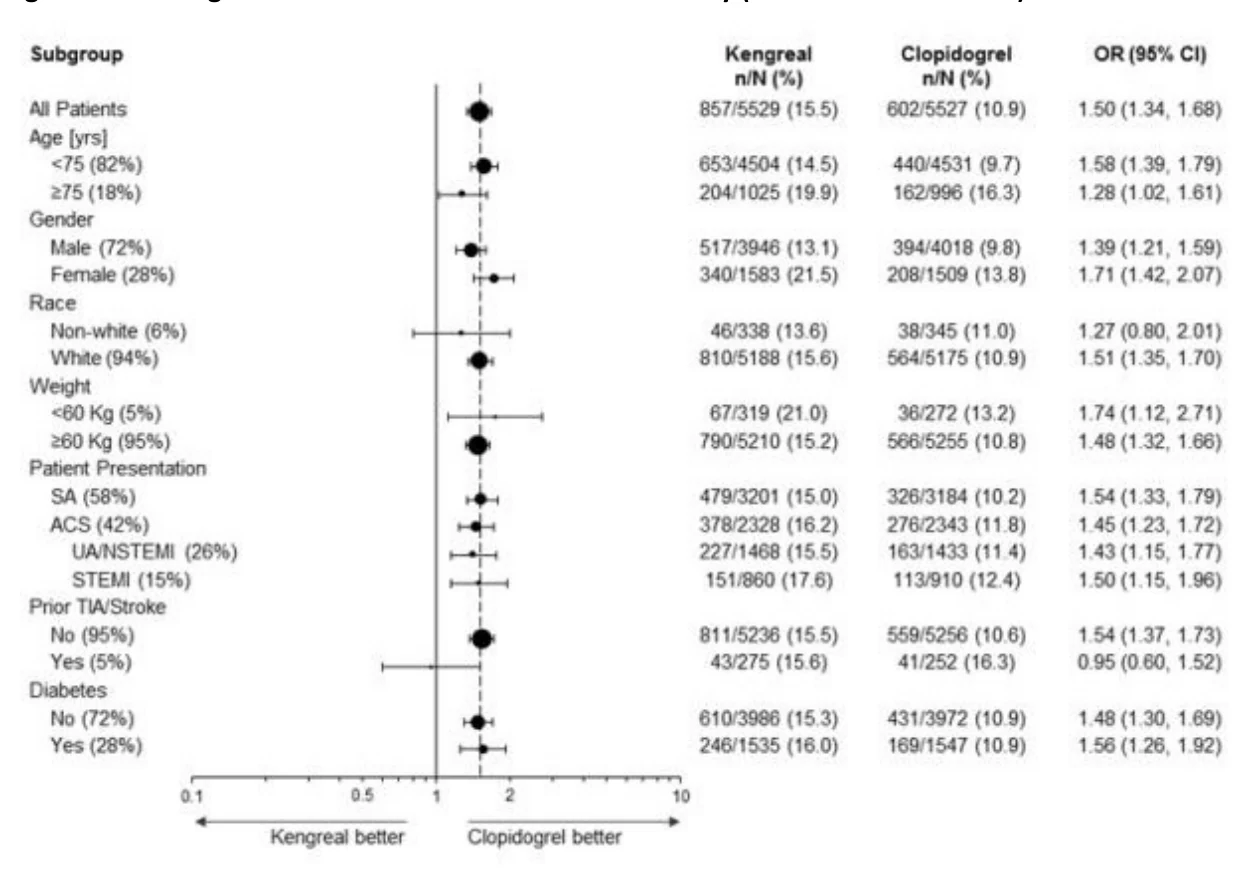
ACS = acute coronary syndrome; CABG = coronary artery bypass graft; CI = confidence interval; Kengreal = KENGREXAL; OR = odds ratio; SA =stable angina; STEMI = ST-segment elevation myocardial infarction; TIA = transient ischemic attack; UA/NSTEMI = unstable angina and non-ST-segment elevation myocardial infarction
Note: Safety population is all randomized subjects who received at least one dose of study drug.
Note: The figure above presents effects in various subgroups most of which are baseline characteristics and most of which were pre-specified (patient presentation and weight were not pre-specified subgroups). The 95% confidence limits that are shown do not take into account how many comparisons were made, nor do they reflect the effect of a particular factor after adjustment for all other factors. Apparent homogeneity or heterogeneity among groups should not be over-interpreted.
Drug Discontinuation
In CHAMPION PHOENIX the rate of discontinuation for bleeding events was 0.3% for KENGREXAL and 0.1% for clopidogrel. Discontinuation for non-bleeding adverse events was low and similar for KENGREXAL (0.6%) and for clopidogrel (0.4%). Coronary artery dissection, coronary artery perforation, and dyspnea were the most frequent events leading to discontinuation in patients treated with KENGREXAL.
Non-bleeding Adverse Reactions
Hypersensitivity
Serious cases of hypersensitivity were more frequent with KENGREXAL (0.05%) than with control (0.02%). These included anaphylactic reactions, anaphylactic shock, bronchospasm, angioedema, and stridor.
Decreased renal function
Worsening renal function was reported in 3.2% of KENGREXAL patients with severe renal impairment (creatinine clearance <30 mL/min) compared to 1.4% of clopidogrel patients with severe renal impairment.
Dyspnea
Dyspnea was reported more frequently in patients treated with KENGREXAL (1.3%) than with control (0.4%).
Table 4: Summary of Most Frequently Report TEAEs (≥1.0% of Patients in Either Treatment Arm) in the CHAMPION PHOENIX Study (Safety Population)
Cangrelor n = 5529 n (%) | Clopidogrel n = 5527 n (%) | |
| Gastrointestinal disorders | ||
| Nausea | 117 (2.1) | 107 (1.9) |
| Vomiting | 70 (1.3) | 53 (1.0) |
| General disorders and administration site conditions | ||
| Vessel puncture site pain | 114 (2.1) | 102 (1.8) |
| Musculoskeletal and connective tissue disorders | ||
| Back pain | 147 (2.7) | 155 (2.8) |
| Nervous system disorders | ||
| Headache | 101 (1.8) | 110 (2.0) |
| Respiratory, thoracic and mediastinal disorders | ||
| Dyspnea | 65 (1.2) | 18 (0.3) |
| Vascular disorders | ||
| Hypertension | 112 (2.0) | 93 (1.7) |
| Hypotension | 63 (1.1) | 48 (0.9) |
8.3 Less Common Clinical Trial Adverse Reactions
Adverse reactions occurring at a frequency ≥0.1% and <1% in the CHAMPION PHOENIX trial included:
Cardiac disorders: bradycardia
Gastrointestinal disorders: diarrhoea, dyspepsia
General disorders and administration site conditions: malaise, pyrexia, vessel puncture site swelling
Infections and infestations: bronchitis, pneumonia, urinary tract infection
Nervous system disorders: presyncope
Skin and subcutaneous tissue disorders: pruritus, rash
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Table 5: Patients with Potentially Clinically Significant Values in Hematology Parameters in the CHAMPION PHOENIX Study (Safety Population)
Cangrelor n = 5529 n/N (%) | Clopidogrel n = 5527 n/N (%) | |
| Hematocrit ≤0.8×LLN | 147/5161 (2.8) | 119/5152 (2.3) |
| Hemoglobin ≤0.8×LLN | 166/5148 (3.2) | 109/5149 (2.1) |
| Platelet count ≥700 1000/mm3 | 1/5250 (0.0) | 0/5226 (0.0) |
| Platelet count ≤75 1000/mm3 | 4/5250 (0.1) | 5/5226 (0.1) |
No differences between adults, geriatrics, and/or pediatrics can be ascertained.
Post-Market Findings
The following preferred terms related to Abnormal Laboratory Findings occurred in the post-market experience.
Table 6: Abnormal Laboratory Finding Adverse Drug Reactions from Post-market Sources
Eventsa,b N = 625 n/N (%) | ICSRsa,b N = 285 n/N (%) | ||
| Acidosis | 1 (0.2) | 1 (0.4) | |
| Blood loss anemia | 1 (0.2) | 1 (0.4) | |
| Electrocardiogram ST segment elevation | 5 (0.8) | 5 (1.8) | |
| Hematuria | 1 (0.2) | 1 (0.4) | |
| Hemoglobin decreased | 3 (0.5) | 3 (1.1) | |
| Hemolytic anemia | 3 (0.5) | 1 (0.4) | |
| Hyperglycemia | 1 (0.2) | 1 (0.4) | |
| Lactic acidosis | 1 (0.2) | 1 (0.4) | |
Eventsa,b N = 625 n/N (%) | ICSRsa,b N = 285 n/N (%) | ||
| Platelet function test abnormal | 1 (0.2) | 1 (0.4) | |
| Thrombocytopenia | 4 (0.7) | 4 (1.4) | |
ICSR = Individual Case Safety Report a Total number of adverse events that occurred in the post-market experience is equal to 625. b 642 adverse events correspond to 285 different ICSRs. | |||
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of KENGREXAL. Because these reactions are reported voluntarily from a population of unknown size, it is not always possible to reliably estimate their frequency.
Blood and lymphatic system disorders: blood loss anemia, hemolytic anemia
Cardiac disorders: acute myocardial infarction, atrioventricular block, cardiac arrest, cardiac failure, cardio-respiratory arrest, cardiogenic shock, coronary artery dissection, coronary artery thrombosis, myocardial infarction, pericardial effusion, ventricular fibrillation, ventricular tachycardia
Gastrointestinal disorders: glossodynia, pancreatitis, paraesthesia oral, retroperitoneal hematoma, tongue pigmentation
General disorders and administration site conditions: catheter site swelling, chest discomfort, chest pain, feeling abnormal, hyperthermia, infusion site extravasation, multiple organ dysfunction syndrome, pain, vascular stent thrombosis, vessel puncture site hematoma
Infections and infestations: sepsis
Injury, poisoning and procedural complications: coronary artery restenosis, fall, graft thrombosis, head injury, post procedural hematoma, subdural hematoma, traumatic hemothorax, vasoplegia syndrome
Investigations: ejection fraction decreased, electrocardiogram ST segment elevation, international normalised ratio increased, platelet function test abnormal
Metabolism and nutrition disorders: hyperglycemia
Nervous system disorders: brain edema, central nervous system lesion, cerebral hypoperfusion, cerebrovascular accident, hemorrhagic stroke, hemiparesis, intracranial aneurysm
Psychiatric disorders: anxiety, delirium, drug abuse
Renal and urinary disorders: hematuria
Respiratory, thoracic and mediastinal disorders: asphyxia, epistaxis, lung infiltration, pneumonia aspiration, pneumothorax, pulmonary edema, respiratory distress, respiratory failure
Skin and subcutaneous tissue disorders: hyperhidrosis
Vascular disorders: hematoma, shock, thrombosis
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
When clopidogrel or prasugrel are administered early during KENGREXAL infusion the expected antiplatelet effect is reduced or abolished following KENGREXAL discontinuation and until the next dose is administered. Therefore, administer clopidogrel or prasugrel only after KENGREXAL infusion is discontinued (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY).
Thienopyridines, such as clopidogrel and prasugrel, have pharmacokinetic properties distinct from cangrelor, with a longer interval between administration and P2Y12 inhibition. Administration of clopidogrel or prasugrel immediately after cangrelor discontinuation leads to a period of 1 hour in which ADP-mediated platelet aggregation recovers to baseline values. This is followed by the progressive onset of clopidogrel- or prasugrel-mediated P2Y12 inhibition.
This time course of platelet inhibition reflects the pharmacokinetics of cangrelor (offset) followed by the absorption and metabolism of clopidogrel and prasugrel to active metabolites (onset).
A pharmacodynamic interaction study has also been conducted with cangrelor and ticagrelor, a reversible P2Y12 platelet inhibitor. The antiplatelet effect of a 180 mg ticagrelor loading dose was not altered significantly when ticagrelor was administered during cangrelor infusion.
Administration of ticagrelor during the cangrelor infusion led to a minimal decrease in platelet inhibition for approximately 0.5 hours following discontinuation of the cangrelor infusion. Administering ticagrelor during cangrelor infusion does not attenuate the anti-platelet effect of ticagrelor.
Co-administration of cangrelor with unfractionated heparin, aspirin, and nitroglycerin was formally studied in healthy subjects, with no evidence of an effect on the pharmacokinetics/pharmacodynamics (PK/PD) of cangrelor.
In clinical trials cangrelor has been co-administered with bivalirudin, low molecular weight heparin, clopidogrel, prasugrel, and ticagrelor without clinically detectable interactions on cangrelor.
In vitro studies suggest that neither cangrelor nor its major metabolites inhibit the activity of the hepatic CYP isoenzymes at therapeutic concentrations. Therefore, cangrelor administration is not expected to interfere with the hepatic metabolism of other concomitantly administered therapeutic agents.
In vitro inhibition of BCRP by the metabolite AR-C69712XX at clinically relevant concentrations has been observed. Since AR-C69712 is not a substrate for transporters that work in concert with BCRP including the OATP1B or OAT transporters, clinically relevant interaction of AR-C69712 with BCRP is unlikely. Since the possible interactions are not investigated for the in vivo situation, caution is advised when cangrelor is to be combined with a BCRP substrate. AR-C69712XX did not inhibit any of the other ABC or SLC transporters at clinically relevant concentrations.
9.3 Drug-Behavioural Interactions
Interactions with behavioural risks have not been established.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 7: Established or Potential Drug-Drug Interactions
| Common Name | Source of Evidence | Effect | Clinical comment | |||
| BCRP substrates | T | In vitro inhibition of BCRP by the metabolite AR-C69712XX at clinically relevant concentrations | Caution is advised when cangrelor is to be combined with a BCRP substrate | |||
| CS = case study; CT = clinical trial; T = theoretical | ||||||
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Cangrelor is a direct P2Y12 platelet receptor inhibitor that blocks ADP binding to the receptor and consequent ADP-induced platelet activation and aggregation. Cangrelor is an ATP structural analogue that binds selectively and reversibly to the P2Y12 receptor to prevent further signaling and platelet activation. The inhibition of ADP-induced platelet activation and aggregation during PCI reduces the risk of thrombotic cardiovascular events.
The binding of cangrelor to the P2Y12 receptor is suspected to prevent the binding of thienopyridines active metabolites. This mechanism is believed to be responsible for the loss of expected efficacy of thienopyridines when administered during cangrelor IV infusion.
In plasma, cangrelor undergoes rapid inactivation by dephosphorylation to the major circulating metabolite, the nucleoside AR-C69712XX, which shows no pharmacological activity.
10.2 Pharmacodynamics
Cangrelor inhibits activation and aggregation of platelets. After administration of a 30 µg/kg IV bolus followed by a 4 µg/kg/min IV infusion, platelet inhibition occurs within 2 minutes.
Figure 2 shows the effect on platelet activity, and its relation to cangrelor plasma concentration, of administering a 30 µg/kg IV bolus, followed by a 1-hour 4 µg/kg/min IV infusion of cangrelor. The anti-platelet effect is maintained for the duration of the infusion. After discontinuation of the infusion, the anti-platelet effect decreases rapidly and platelet function returns to normal within 1 hour.
Figure 2: Cangrelor Pharmacodynamic Characteristics
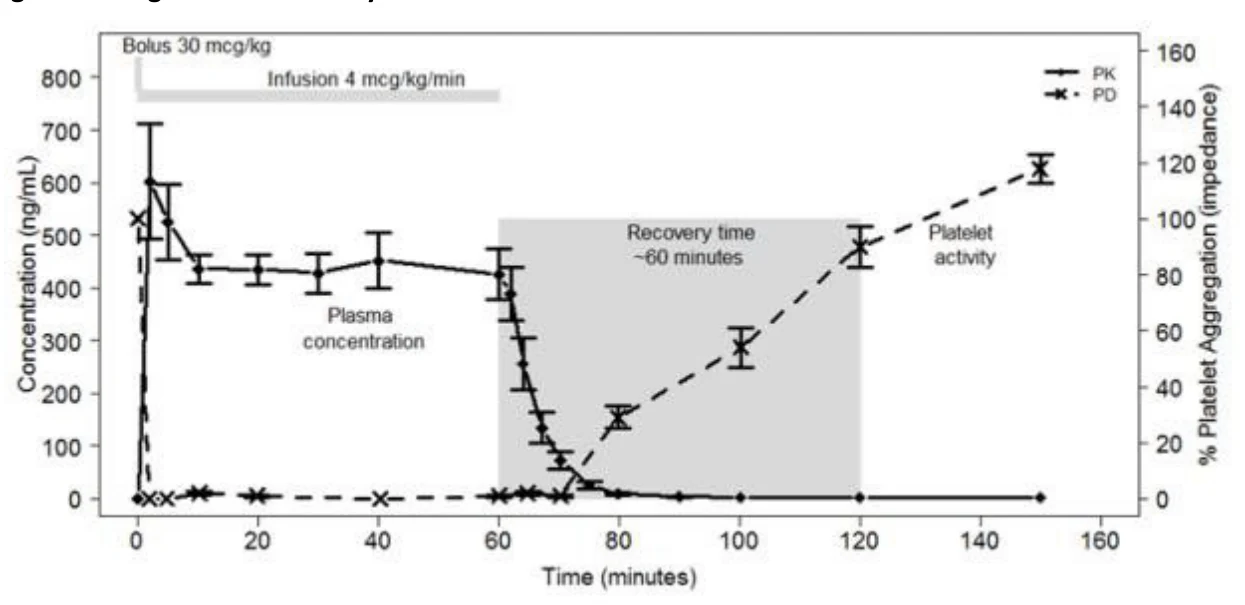
PD = pharmacodynamics; PK = pharmacokinetics
Cardiac Electrophysiology
In a randomized, double-blind, placebo- and positive-controlled, 4-way crossover ECG study, 60 healthy subjects were treated; all receiving cangrelor at therapeutic (30 µg/kg IV bolus plus 4 µg/kg/min of IV infusion for 3 h) and supratherapeutic (60 µg/kg IV bolus plus 8 µg/kg/min IV infusion for 3 h) doses. At the doses tested, cangrelor did not prolong the QTc interval to any clinically relevant extent. At the therapeutic dose, change from baseline in mean heart rate was significantly different from placebo at 2, 30, 60, and 120 minutes post cangrelor administration. The maximum difference from placebo in mean change from baseline heart rate was 5.3 bpm at the therapeutic dose and 6.5 bpm at the supratherapeutic dose, both at 120 min post-dose. There was in increased incidence of heart rate outliers associated with cangrelor treatment. The number of subjects with heart rate > 90 bpm were 4 (7%), 8 (14%), 8 (14%), for the placebo, cangrelor therapeutic, and cangrelor supratherapeutic groups, respectively.
10.3 Pharmacokinetics
Table 8: Summary of Cangrelor Pharmacokinetic Parameters in Healthy Volunteers
| Cmax (ng/mL) | Tmax (min) | t½ (min) | AUC0-∞ (ng·h/mL) | CL (L/h) | Vz (L) | ||||||
| 30 µg/kg IV bolus plus 4 µg/kg/min IV infusion | 665±213 | 3 (2-30) | 3.6±1.2 | 488±94 | 43.9±8.03 | 3.88±1.18 | |||||
| AUC0-∞ = area under the concentration time curve extrapolated to infinity; CL = plasma clearance; Cmax = maximum concentration; t1/2 = half-life; Tmax = time to maximal concentration; Vz = volume of distribution | |||||||||||
Absorption
KENGREXAL administered IV has linear pharmacokinetics in both healthy volunteers and patients. KENGREXAL is rapidly distributed and metabolized, reaching Cmax within 2 minutes after administration of an IV bolus followed by infusion. The bioavailability of cangrelor is complete and immediate. A steady state concentration of 488 ng/mL is rapidly reached within 10 minutes.
Distribution
In a study in healthy volunteers, KENGREXAL administration at a dose of 30 µg/kg bolus plus 4 µg/kg/min showed a volume of distribution of 3.9 L. Plasma protein binding of KENGREXAL is about 97% to 98%.
Metabolism
KENGREXAL is deactivated rapidly in the circulation by dephosphorylation to its primary metabolite, a nucleoside, which has negligible anti-platelet activity. KENGREXAL’s metabolism is independent of hepatic function and it does not interfere with other drugs metabolized by hepatic enzymes.
Elimination
Following IV administration of 2 µg/kg/min [3H]Kengrexal to healthy males, 58% of radioactivity was recovered in urine. The remaining 35% of radioactivity was in feces, presumably following biliary excretion. The average half-life of KENGREXAL is about 3 to 6 minutes.
Special Populations and Conditions
- Pediatrics: Cangrelor has not been evaluated in a pediatric population.
- Age: In a population pharmacokinetics analysis, KENGREXAL pharmacokinetics were not affected by age (18 to 66 years). No dose adjustment is needed.
- Sex: KENGREXAL pharmacokinetics are not affected by sex. No dose adjustment is needed.
- Hepatic Insufficiency: KENGREXAL pharmacokinetics are not affected by hepatic function. No dose adjustment is needed.
- Renal Insufficiency: Exposure to cangrelor was higher in patients with renal insufficiency, in comparison to healthy volunteers, following a plateau infusion of cangrelor at 4 µg/kg/min. In patients with renal insufficiency, Cmax and AUC were 1.49- and 1.59-times higher, respectively, in renal insufficient patients. KENGREXAL pharmacokinetics are not affected by renal status. No safety concerns were identified with the increased exposure and the observed effect is not considered clinically relevant to warrant dose adjustment.
- Obesity: In a population pharmacokinetics analysis, weight was found to be a significant covariate affecting the PK of KENGREXAL. The impact of weight on the PK is accounted for by the use of weight-based dosing.
11 STORAGE, STABILITY AND DISPOSAL
Vials of KENGREXAL should be stored at Room Temperature (15°C to 30°C).
12 SPECIAL HANDLING INSTRUCTIONS
Following reconstitution and subsequent dilution of the powder, the storage period should not exceed 12 hours in 5% dextrose solution and 24 hours in normal saline at room temperature prior to use. Do not refrigerate.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: cangrelor
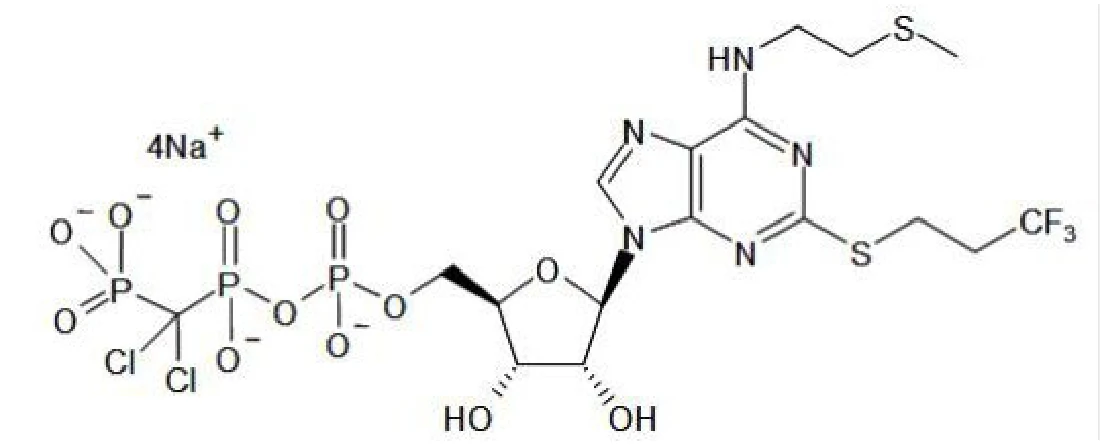
Chemical name: tetrasodium salt of N6-[2-(methylthio)ethyl]-2-[(3,3,3,-trifluoropropyl)-5’-adenylic acid, monanhydride with (dichloromethylene) bisphosphonic acid
Molecular formula and molecular mass: C17H21N5Cl2F3Na4O12P3S2 and the molecular weight is 864.3 g/mol
Structural formula:
Physicochemical properties: Cangrelor for Injection is a sterile white to off-white lyophilized powder for IV infusion.
Product Characteristics:
KENGREXAL is a direct-acting PY212 platelet receptor inhibitor that blocks ADP-induced platelet activation and aggregation. The chemical structure is similar to adenosine triphosphate (ATP).
14 CLINICAL TRIALS
14.1 Clinical Trial by Indication
PCI
Table 9: Summary of Patient Demographics for Clinical Trials in Patients at the Time of Percutaneous Coronary Intervention
| Study | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (Range) | Sex |
| CHAMPION PHOENIX | Randomized, double-blind, active comparator | KENGREXAL: 30 µg/kg bolus followed by 4 µg/kg/min infusion for 2-4 hours; clopidogrel 600 mg after infusion Clopidogrel: 300 mg or 600 mg shortly before or after PCI | KENGREXAL: 5472 Clopidogrel: 5470 | KENGREXAL: 64.0 (56, 72) Clopidogrel: 64.0 (56, 72) | Male KENGREXAL: 3914 (71.5) Clopidogrel: 3977 (72.7) Female: KENGREXAL: 1558 (28.5) Clopidogrel: 1493 (27.3) |
The CHAMPION PHOENIX trial was intended to test whether faster platelet inhibition with cangrelor at the time of PCI would reduce the rate of periprocedural thrombotic events compared to a drug with a slower antiplatelet effect, clopidogrel, given at about the time of PCI. It was a randomized, double-blind, superiority study in which patients with coronary artery disease (stable angina, unstable angina and non-ST-segment elevation myocardial infarction [UA/NSTEMI], ST-segment elevation myocardial infarction [STEMI]) requiring PCI and receiving standard therapy including aspirin and heparin or bivalirudin were randomized 1:1 to KENGREXAL (n=5472) or to clopidogrel 300 or 600 mg (n=5470). The median duration of cangrelor infusion was 129 minutes. Patients who had already taken an oral P2Y12 platelet inhibitor, patients administered glycoprotein IIb/IIIa inhibitors (GPI) or for whom GPI use was planned were not eligible to enroll. PHOENIX trial included patients undergoing PCI who had not been previously treated with anti-platelet therapy other than aspirin.
The primary outcome measure was the first occurrence of any one of the composite endpoint of all-cause mortality, MI, ischemia-driven revascularization (IDR), and stent thrombosis (ST) within 48 hours after randomization.
KENGREXAL was administered as a 30 µg/kg bolus followed by 4 µg/kg/min infusion for 2 to 4 hours. Clopidogrel 600 mg was administered immediately at the end of the KENGREXAL infusion in patients randomized to KENGREXAL. Clopidogrel 300 mg or 600 mg was administered shortly before PCI or shortly afterward in patients randomized to clopidogrel.
KENGREXAL significantly reduced the occurrence of primary composite endpoint events compared to clopidogrel (relative risk reduction 22%). Most of the effect was a reduction in post-procedural MI detected solely by elevations in CK-MB (type 4a MI). KENGREXAL did not reduce the risk of death. Table 10 shows the study results for the primary composite endpoint and the contribution of each component to the primary endpoint.
Table 10: Primary Endpoint and its Component Events at 48 hours in CHAMPION PHOENIX (mITT Population)
KENGREXAL (N=5470) n (%) | Clopidogrel (N=5469) n (%) | KENGREXAL vs. clopidogrel | |||||||
| OR (95% CI) | p-value | ||||||||
| Primary Endpoint (Death/MI/IDR/ST) | 257 (4.7) | 322 (5.9) | 0.78 (0.66, 0.93)a | 0.005 | |||||
| Death | 18 (0.3) | 18 (0.3) | 1.00 (0.52, 1.92)a | >0.999 | |||||
| MI | 207 (3.8) | 255 (4.7) | 0.80 (0.67, 0.97)a | 0.022 | |||||
| IDR | 28 (0.5) | 38 (0.7) | 0.74 (0.45, 1.20)a | 0.217 | |||||
| ST | 46 (0.8) | 74 (1.4) | 0.62 (0.43, 0.90)a | 0.010 | |||||
CI = confidence interval; IDR = ischemia-driven revascularization; MI = myocardial infarction; mITT = modified intent-to-treat; OR = odds ratio; PCI = percutaneous coronary intervention; ST = stent thrombosis a Based on logistic model adjusted for loading dose and baseline patient status for primary endpoint Note: The mITT population is all randomized subjects who received at least one dose of study drug and underwent the index PCI procedure. | |||||||||
The effect of KENGREXAL appeared to be consistent in a variety of pre-specified and other clinically important subgroups (see Figure 3).
Figure 3: CHAMPION PHOENIX Study: Primary Efficacy Endpoint by Subgroup (mITT Population)
Note: The mITT population is all randomized subjects who received at least one dose of study drug and underwent the index PCI procedure.
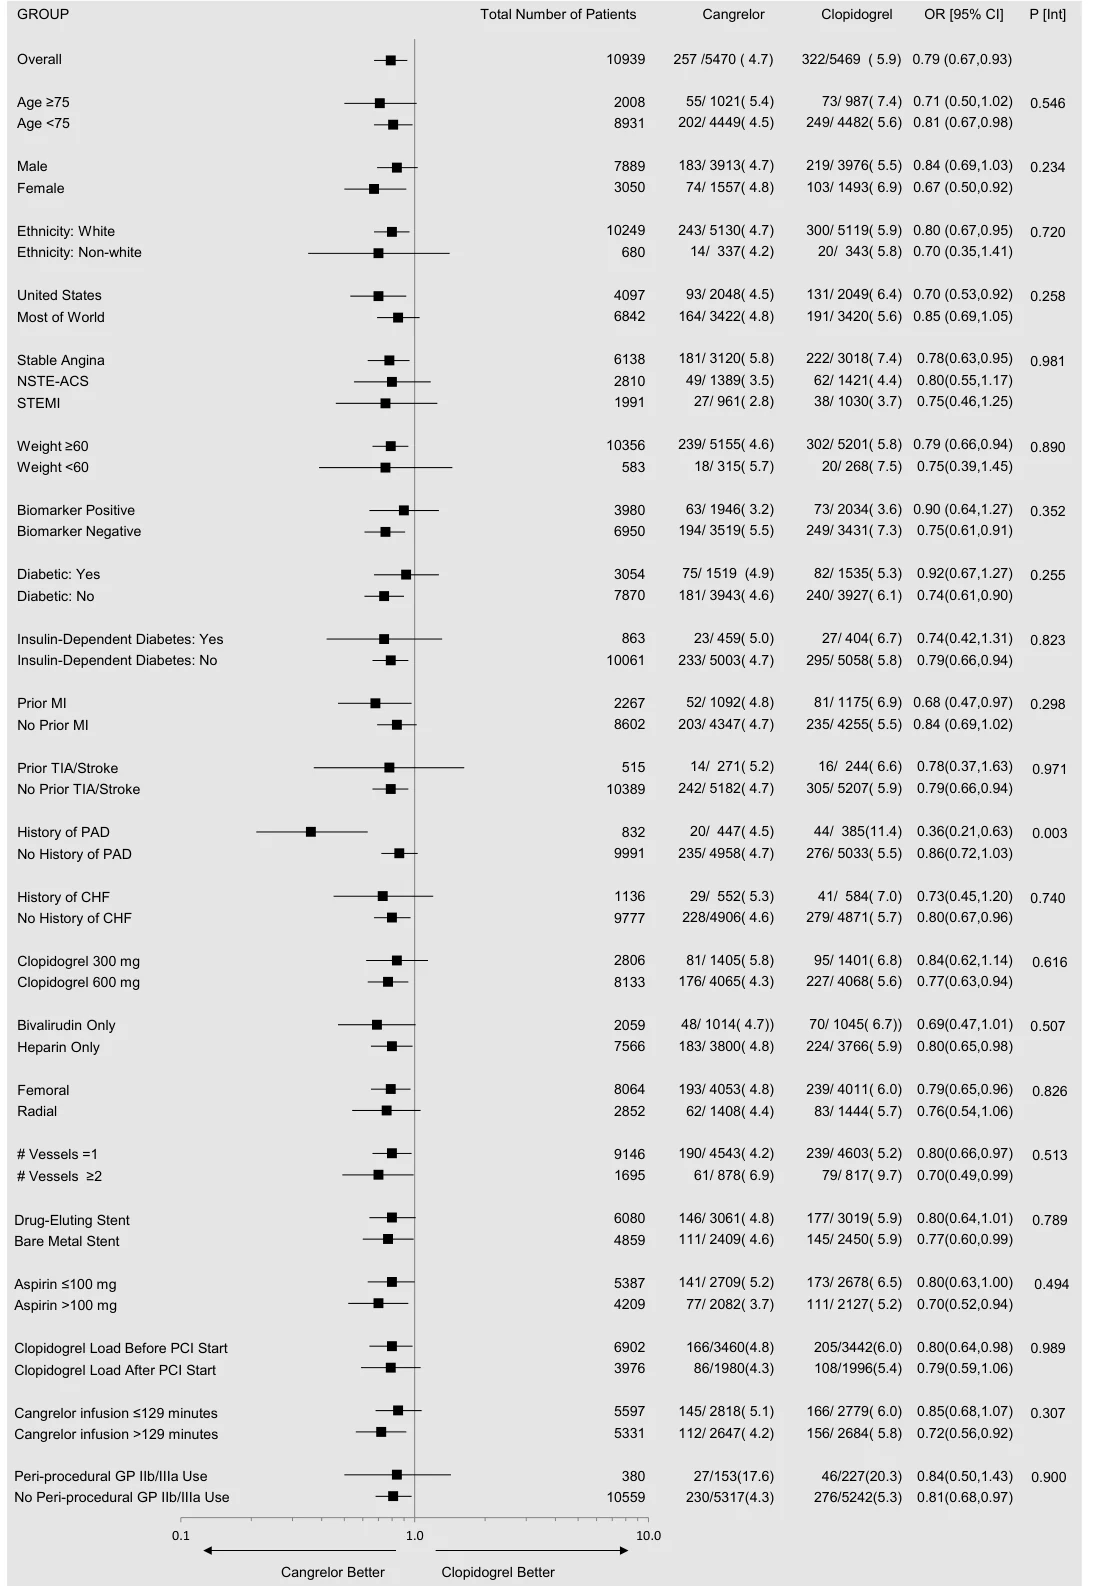
The figure above presents effects in various subgroups most of which are baseline characteristics and most of which were pre-specified (patient presentation and weight were not prespecified subgroups). The 95% confidence limits that are shown do not take into account how many comparisons were made, nor do they reflect the effect of a particular factor after adjustment for all other factors. Apparent homogeneity or heterogeneity among groups should not be over-interpreted.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Repeat Dose Toxicity
Continuous intravenous infusion of cangrelor in rats and dogs showed evidence of toxicity in a time dependent manner. Continuous intravenous infusion of 60 µg/kg/min dose in male dogs for 7 days showed presence of inflammatory cells in urothelium epithelium, renal pelvis, ureter and urinary bladder. Continuous administration of cangrelor for 28 days demonstrated histological changes including inflammation of renal pelvis and urethra, interstitial nephritis, urothelial and tubular necrosis, tubular dilatation, distension of bladder, and urothelial hyperplasia in kidney, ureter, and urinary bladder in rats and dogs at dose of about 12 and 15 times respectively the human dose. Gastritis with ulceration, necrosis of gastric mucosa and inflammatory changes in colon and rectum were observed in male and female dogs treated with 60 µg/kg/min dose (15 times MRHD). No histological changes were observed at doses of 12 μg/kg/min (3 times human exposure) and 15 μg/kg/min (3.75 times human exposure), in rats and dogs respectively.
Dose related increase in liver enzymes, AST and ALT, were observed in both rats and dogs at dose of about 12 and 15 times respectively the human dose with no evidence of histopathological changes in liver.
While no changes in EGC parameters or heart rate were observed at any dose, an increase in the frequency of asynchronous premature ventricular contractions (PVC) was observed in one animal receiving 60 µg/kg/min dose (15 times MRHD).
Continuous infusion of cangrelor for 28 days at the dose of human exposure did not demonstrate any adverse effect in both rats and dogs.
Histological changes of renal toxicity correlated with increase in levels of plasma and urinary creatinine, as well as increased levels of urea, white blood cells, protein and glucose in urine were observed in rats and dogs as early as 3 times or 3.75 times human exposure respectively.
Carcinogenicity: No carcinogenicity studies were conducted.
Genotoxicity: Cangrelor was non-mutagenic and non-clastogenic in genetic toxicology studies, including in vitro bacterial gene mutation assay, mouse lymphoma thymidine kinase assay, chromosome aberration assay in human peripheral lymphocytes, and in vivo bone marrow micronucleus assay in mice. Cangrelor and its base metabolites are considered non-genotoxic since no gene mutations or chromosomal damage were observed in bacterial mutagenicity study.
Reproductive and Developmental Toxicology:
Cangrelor had no significant effect on male or female rat fertility treated by continuous infusion for 28 days, or on early embryonic development at steady state plasma concentration approximately the same as that achieved in the PCI setting at the MRHD. Impact on fertility in male rats including reduction in the ability to produce pregnancy in mated females, reduction in sperm count, motility and abnormal sperm morphology were observed at cangrelor dose of 12 times MRHD. Increased evidence of epididymal spermatocele formation, testes tubular epithelial atrophy and oligospermia were also noted at this dose. These effects were reversed upon dose off period of 8 weeks. Cangrelor did not impact fertility in female rats at dose of 12 times MRHD. However, a reduction in post-implantation survival of embryos were observed at this dose.
A prenatal and postnatal development study in female rats demonstrated incidence of maternal mortality in dams treated at 30 µg/kg/min cangrelor (approximately 7.5 times the MRHD) continuous infusion from Day 6 of gestation up to Day 23 post-partum. Pregnancy rates, gestation index, length of gestation, numbers of live, dead, and malformed pups, sex ratio, live birth index, and lactation of the maternal animals were unaffected. Survival, physical development, behaviour, or reproductive performance for the offsprings was not affected.
An embryo-fetal development study in rabbits administered 4, 12, or 36 µg/kg/min cangrelor continuous IV infusion from Day 6 to Day 19 post-coitum resulted in increased incidences of abortion and intrauterine losses at ≥12 µg/kg/min (3 times the MRHD). Fetal growth retardation occurred at 36 µg/kg/min (9 times the MRHD) and was characterized by decreased fetal weights, slight reduction in ossification, and a slight increase in skeletal variants. Whereas treatment with 4, 12, or 36 µg/kg/min cangrelor in pregnant rats from Day 6 to Day 17 post-coitum resulted in dose-related fetal growth retardation characterized by increased incidences of incomplete ossification and unossified hind limb metatarsals at dose levels ≥3 µg/kg/min. A dose dependent and species dependent differences in severity were observed.
Cangrelor did not produce malformations in either the rat or rabbit embryo-fetal development studies and is not considered to be a teratogen.
Special Toxicology: The antigenicity of cangrelor was investigated in animals using the active systemic anaphylaxis and passive cutaneous anaphylaxis studies. Cangrelor exhibited no indication of antigenicity in both tests.