


Product Monograph - Librax
RECENT MAJOR LABEL CHANGES
| 1 Indications, 1.2 Geriatrics | 12/2021 |
| 2 Contraindications | 12/2021 |
| 3 Serious Warnings and Precautions Box | 12/2021 |
| 4 Dosage and Administration, 4.1 Dosing Considerations | 12/2021 |
| 7 Warnings and Precautions | 12/2021 |
| 7 Warnings and Precautions, 7.1.4 Geriatrics | 12/2021 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed
RECENT MAJOR LABEL CHANGES..............................................................................................2
TABLE OF CONTENTS ................................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION .......................................................................4
1 INDICATIONS ................................................................................................................4
1.1 Pediatrics...........................................................................................................4
1.2 Geriatrics ...........................................................................................................4
2 CONTRAINDICATIONS ...................................................................................................4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ..............................................................5
4 DOSAGE AND ADMINISTRATION...................................................................................5
4.1 Dosing Considerations........................................................................................5
4.2 Recommended Dose and Dosage Adjustment .....................................................6
4.4 Administration ...................................................................................................6
4.5 Missed Dose ......................................................................................................6
5 OVERDOSAGE ...............................................................................................................6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ...................................7
7 WARNING AND PRECAUTIONS......................................................................................7
7.1 Special Populations .......................................................................................... 12
7.1.1 Pregnant Women ............................................................................................. 12
7.1.2 Breast-feeding ................................................................................................. 12
7.1.3 Pediatrics......................................................................................................... 13
7.1.4 Geriatrics ......................................................................................................... 13
8 ADVERSE REACTIONS .................................................................................................. 13
8.1 Adverse Reaction Overview .............................................................................. 13
8.5 Post-Market Adverse Reactions ........................................................................ 14
9 DRUG INTERACTIONS.................................................................................................. 14
9.1 Serious Drug Interactions ................................................................................. 14
9.2 Drug Interactions Overview .............................................................................. 15
9.3 Drug-Behavioural Interactions .......................................................................... 15
9.4 Drug-Drug Interactions..................................................................................... 15
9.5 Drug-Food Interactions .................................................................................... 15
9.6 Drug-Herb Interactions..................................................................................... 15
9.7 Drug-Laboratory Test Interactions .................................................................... 15
10 CLINICAL PHARMACOLOGY ......................................................................................... 16
10.1 Mechanism of Action ....................................................................................... 16
10.2 Pharmacodynamics .......................................................................................... 16
10.3 Pharmacokinetics............................................................................................. 16
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 17
12 SPECIAL HANDLING INSTRUCTIONS............................................................................. 17
PART II: SCIENTIFIC INFORMATION ........................................................................................ 18
13 PHARMACEUTICAL INFORMATION.............................................................................. 18
14 CLINICAL TRIALS.......................................................................................................... 18
15 MICROBIOLOGY .......................................................................................................... 19
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 19
PATIENT MEDICAL INFORMATION.......................................................................................... 20
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
LIBRAX (chlordiazepoxide hydrochloride and clidinium bromide) is indicated for the following conditions when they are associated with excessive anxiety and tension:
- as adjunctive therapy in the treatment of peptic ulcer
- in the treatment of the irritable bowel syndrome (irritable colon, spastic colon, mucous colitis)
- in the treatment of acute enterocolitis
1.1 Pediatrics
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics: Geriatrics (>65 years of age): Evidence from experience suggests that use in the geriatric population is associated with differences in safety or effectiveness.
Long-term use of LIBRAX should be avoided in geriatric patients. Enhanced monitoring is recommended (see 4.1 Dosing considerations; 7 WARNINGS AND PRECAUTIONS, Falls and Fractures).
2 CONTRAINDICATIONS
LIBRAX is contraindicated in patients with:
- hypersensitivity to chlordiazepoxide, clidinium or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- cardiovascular instability
- a history of drug abuse or dependence (chlordiazepoxide may predispose to habituation and dependence)
- angle-closure, or predisposition to glaucoma (clidinium has a possible mydriatic effect resulting in increased intraocular pressure may precipitate an acute attack of angle-closure glaucoma)
- impaired hepatic function (because of decreased metabolism)
- hiatal hernia with reflux esophagitis (clidinium may aggravate condition)
- intestinal atony of the elderly or debilitated (may result in obstruction due to clidinium's anticholinergic/antispasmodic effect)
- intestinal obstruction (may be exacerbated by clidinium)
- myasthenia gravis (clidinium may aggravate condition because of inhibition of acetylcholine action)
- prostatic hypertrophy or urinary retention (anticholinergic effects may precipitate or aggravate urinary retention)
- ulcerative colitis (clidinium may suppress intestinal motility and cause paralytic ileus; also, use may precipitate or aggravate the serious complications of toxic megacolon)
- severe respiratory insufficiency
- psychotic disorders
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Addiction, Abuse and Misuse The use of benzodiazepines, including LIBRAX, can lead to abuse, misuse, addiction, physical dependence and withdrawal reactions. Abuse and misuse can result in overdose or death, especially when benzodiazepines are combined with other medicines, such as opioids, alcohol or illicit drugs.
Withdrawal Benzodiazepines, like LIBRAX, can produce severe or life-threatening withdrawal symptoms.
(see 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance) Risks from Concomitant use with Opioids Concomitant use of LIBRAX and opioids may result in profound sedation, respiratory depression, coma and death (see 7 WARNINGS AND PRECAUTIONS, General, Concomitant use with opioids).
|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- LIBRAX should always be prescribed at the lowest effective dose for the shortest duration possible.
- Dosage should be individualized to each patient.
- Prolonged use of larger than usual therapeutic doses of chlordiazepoxide may result in psychic or physical dependence.
Discontinuation
LIBRAX can produce withdrawal signs and symptoms or rebound phenomena following abrupt discontinuation or rapid dose reduction (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Withdrawal; 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance). Abrupt discontinuation
- should be avoided and treatment - even if only of short duration - should be terminated by gradually tapering the dosage schedule under close monitoring.
- Tapering should be tailored to the specific patient. Special attention should be given to patients with a history of seizure.
- If a patient experiences withdrawal signs and symptoms, consider postponing the taper or raising the benzodiazepine to the previous dosage prior to proceeding with a gradual taper.
Geriatric and/or Debilitated Patients
- Geriatric and debilitated patients may respond to the usual doses with excitement, agitation, drowsiness, or confusion; lower doses may be required for such patients.
- Geriatric patients in particular may be more sensitive to benzodiazepines (see 7 WARNINGS AND PRECAUTIONS, Falls and Fractures).
- Long-term use of LIBRAX should be avoided in geriatric patients. Enhanced monitoring is recommended.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
Adults: 1 or 2 capsules, one to four times a day, thirty to sixty minutes before meals or food, the dosage then being adjusted as needed and tolerated.
Prescribing limit: up to a total of 8 capsules daily (40 mg of chlordiazepoxide hydrochloride and 20 mg of clidinium bromide)
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
Geriatrics (>65 years of age): Initially no more than 1 capsule two times a day, the dosage then being adjusted as needed and tolerated. Dosage should be limited to the smallest effective amount to preclude the development of ataxia, oversedation or confusion.
4.4 Administration
Administration of LIBRAX® 30 to 60 minutes before meals is recommended to maximize absorption and, when used for reducing stomach acid formation, to allow its effect to coincide better with any antacid administration following the meal.
4.5 Missed Dose
If the patient misses a dose, instruct the patient to take the dose as soon as they remember. If it is almost time for the next dose, inform the patient to skip the missed dose and continue the regular dosing schedule.
5 OVERDOSAGE
Symptoms
Confusion; difficulty in urination; severe drowsiness; severe dryness of mouth, nose, or throat; fast heartbeat; unusual warmth, dryness, and flushing of the skin.
Treatment
Employ general supportive measures, the recommended treatment of overdosage includes:
- emesis
- subcutaneous administration of 5 mg of pilocarpine, repeated as needed, until mouth is moist
- norepinephrine bitartrate or metaraminol infusions, to restore blood pressure
- caffeine and sodium benzoate, to treat CNS depression
- if excitation occurs, barbiturates should not be used since they may exacerbate excitation and/or prolong CNS depression
- monitor respiration, pulse and blood pressure and provide artificial respiration, if needed, for respiratory depression
- administer i.v. fluids
- symptomatic treatment as necessary
- dialysis is of limited value
| For management of a suspected drug overdose, contact your regional poison control centre |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Each green #4 capsule imprinted with LIBRAX contains 5 mg chlordiazepoxide hydrochloride and 2.5 mg clidinium bromide. Available in bottles of 100 capsules.
7 WARNING AND PRECAUTIONS
General
Body Temperature: When clidinium is given to patients where the environmental temperature is high, there is risk of a rapid increase in body temperature because of suppression of sweat gland activity.
Concomitant use with opioids: Concomitant use of benzodiazepines, including LIBRAX, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are not possible (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Risks from Concomitant use with Opioids; 9.1 Serious Drug Interactions).
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | Capsule chlordiazepoxide hydrochloride, 5mg clidinium bromide, 2.5mg | Gelatin, lactose monohydrate, starch, talc, titanium dioxide, D&C Yellow # 10, FD&C Green, black imprinting ink. |
alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with benzodiazepines.
If a decision is made to prescribe LIBRAX concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of LIBRAX than indicated, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking LIBRAX, prescribe a lower initial dose of the opioid analgesic and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation (see 5 OVERDOSAGE).
Advise both patients and caregivers about the risks of respiratory depression and sedation when LIBRAX is used with opioids.
Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the opioid have been determined.
Cardiovascular
Hypertension may be aggravated by clidinium bromide. Risk-benefit should be considered when prescribing LIBRAX to patients with hypertension.
Dependence/Tolerance
Use of benzodiazepines, such as LIBRAX, can lead to abuse, misuse, addiction, physical dependence (including tolerance) and withdrawal reactions. Abuse and misuse can result in overdose or death, especially when benzodiazepines are combined with other medicines, such as opioids, alcohol, or illicit drugs.
The risk of dependence increases with higher doses and longer term use but can occur with short-term use at recommended therapeutic doses. The risk of dependence is greater in patients with a history of psychiatric disorders and/or substance (including alcohol) use disorder.
- Discuss the risks of treatment with LIBRAX with the patient, considering alternative (including non-drug) treatment options.
- Carefully evaluate each patient’s risk of abuse, misuse and addiction, considering their medical condition and concomitant drug use, prior to prescribing LIBRAX. In individuals prone to substance use disorder, LIBRAX should only be administered if deemed medically necessary, employing extreme caution and close supervision.
- LIBRAX should always be prescribed at the lowest effective dose for the shortest duration possible.
- All patients receiving benzodiazepines should be routinely monitored for signs and symptoms of misuse and abuse. If a substance use disorder is suspected, evaluate the patient and refer them for substance abuse treatment, as appropriate.
Withdrawal: Benzodiazepines, such as LIBRAX, can produce withdrawal signs and symptoms, ranging from mild to severe and even life threatening, following abrupt discontinuation or rapid dose reduction. Other factors that may precipitate withdrawal are switching from a long-acting to a short-acting benzodiazepine, decreasing blood levels of the drug or administration of an antagonist. The risk of withdrawal is higher with higher dosages and/or prolonged use, but can occur with short-term use at recommended therapeutic doses.
The onset of withdrawal signs and symptoms can range from hours to weeks following drug cessation and occur even with tapered dosage. Some symptoms can persist for months. Since symptoms are often similar to those for which the patient is being treated, it may be difficult to distinguish from a relapse of the patient’s condition.
Severe or life-threatening signs and symptoms of withdrawal include catatonia, delirium tremens, depression, dissociative effects (e.g. hallucinations), mania, psychosis, seizures (including status epilepticus) and suicidal ideation and behaviour.
Other withdrawal signs and symptoms include abdominal cramps, cognitive impairment, diarrhea, dysphoria, extreme anxiety or panic attacks, headache, hypersensitivity to light, noise and physical contact, insomnia, irritability, muscle pain or stiffness, paresthesia, restlessness, sweating, tension, tremors and vomiting. There is also a possibility of rebound anxiety or rebound insomnia, a transient syndrome whereby the symptoms that led to treatment with a benzodiazepine recur in an enhanced form, on withdrawal of treatment.
- Abrupt discontinuation should be avoided and treatment - even if only of short duration - should be terminated by gradually tapering the dosage schedule under close monitoring.
- Tapering should be tailored to the specific patient. Special attention should be given to patients with a history of seizure.
- If a patient experiences withdrawal symptoms, consider postponing the taper or raising the benzodiazepine to the previous dosage prior to proceeding with a gradual taper.
- Inform patients of risk of discontinuing abruptly, reducing dosage rapidly or switching medications.
- Stress the importance of consulting with their health care professional in order to discontinue safely.
- Patients experiencing withdrawal symptoms should seek immediate medical attention.
(see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Addiction, Abuse and Misuse; Withdrawal; 4.1 Dosing Considerations)
Driving and Operating Machinery
Patients receiving LIBRAX should be cautioned against engaging in hazardous activities requiring complete mental alertness, judgement and physical coordination, such as operating machinery or a motor vehicle.
Endocrine and Metabolism
Risk-benefit should be considered when prescribing LIBRAX to a patient with hyperthyroidism characterized by tachycardia, which may be increased by clidinium bromide.
Falls and Fractures
There have been reports of falls and fractures among benzodiazepine users due to adverse reactions such as sedation, dizziness and ataxia. The risk is increased in those taking concomitant sedatives (including alcoholic beverages), geriatric or debilitated patients.
Gastrointestinal
Prolonged use of clidinium bromide may decrease or inhibit salivary flow, thus contributing to the development of caries, periodontal disease, oral candidiasis, and discomfort. Risk-benefit should be considered when prescribing LIBRAX to patients with xerostomia.
Immune
Severe Anaphylactic and Anaphylactoid Reactions: Rare cases of angioedema involving the tongue, glottis or larynx have been reported in patients after taking the first or subsequent doses of benzodiazepines, including LIBRAX. Some patients have had additional symptoms such as dyspnea, throat closing or nausea and vomiting that suggest anaphylaxis. Some patients have required medical therapy in the emergency department. If angioedema involves the throat, glottis or larynx, airway obstruction may occur and be fatal. Patients who develop angioedema after treatment with RESTORIL should not be rechallenged with the drug.
Monitoring and Laboratory Tests
Periodic blood counts and liver function tests are recommended if the medication is administered over a protracted period of time.
Neurologic
Complex sleep-related behaviours: Complex sleep-related behaviours such as “sleep- driving” (i.e., driving while not fully awake after ingestion of a sedative-hypnotic, with amnesia for the event) have been reported in patients who have taken LIBRAX. Other potentially dangerous behaviours have been reported in patients who got out of bed after taking a sedative-hypnotic and were not fully awake, including preparing and eating food, making phone calls, leaving the house, etc. As with “sleep-driving”, patients usually do not remember these events. The use of alcohol and other CNS-depressants with LIBRAX appears to increase the risk of such behaviours, as does the use of LIBRAX at doses exceeding the maximum recommended dose. LIBRAX is not to be taken with alcohol. Caution is needed with concomitant use of other CNS depressant drugs. Due to the risk to the patient and the community, discontinuation of LIBRAX should be strongly considered for patients who report any such complex sleep-related behaviours.
Memory Disturbance: Anterograde amnesia may occur with therapeutic doses of benzodiazepines and may be associated with inappropriate behaviour. Anterograde amnesia is a dose-related phenomenon and geriatric patients may be at particular risk.
Ophthalmologic
Glaucoma: LIBRAX is contraindicated in patients with angle-closure, or predisposition to glaucoma (see 2 CONTRAINDICATIONS). Clidinium bromide's possible mydriatic effect may cause increase in intraocular pressure. This may precipitate an acute attack of angle-closure glaucoma.
Psychiatric
Confusion: Benzodiazepines affect mental efficiency, e.g. concentration, attention and vigilance. The risk of confusion is greater in the elderly and in patients with cerebral impairment.
Mental and Emotional Disorders: Chlordiazepoxide hydrochloride may increase depression. Caution should be exercised if LIBRAX is prescribed to patients with signs or symptoms of depression that could be intensified by benzodiazepines. The potential for self-harm is high in patients with depression. Employ the usual precautions in treatment of anxiety states with evidence of impending depression; suicidal tendencies may be present and protective measures necessary.
Paradoxical Reactions: Paradoxical reactions such as restlessness, agitation, irritability, rage, aggressive or hostile behaviour, anxiety, delusion, anger, increased muscle spasticity, sleep disturbances, nightmares, hallucinations and other adverse behavioural effects may occur due to chlordiazepoxide rare instances and in a random fashion. Should these occur, use of the drug should be discontinued. They are more likely to occur in children and in the elderly.
Since excitement and other paradoxical reactions can result from the use of anxiolytic sedatives in psychotic patients, chlordiazepoxide should not be used in ambulatory patients suspected of having psychotic tendencies.
These reactions may be secondary to the relief of anxiety symptoms and should be watched for particularly in the early phase of medication.
Renal
Decreased excretion may increase risk of side effects in patients with renal function impairment. LIBRAX should be administered with caution to patients with a history of renal disease.
Reproductive Health: Female and Male Potential
- Teratogenic Risk
There are no adequate and well-controlled studies of LIBRAX in pregnant women. Animal studies with other anxiolytic-sedative agents have suggested increased risk of congenital malformations (see 7.1.1 Pregnant women; 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Chronic use of chlordiazepoxide during pregnancy may cause physical dependence with resulting withdrawal symptoms in the neonate. Use of chlordiazepoxide just prior to or during labour may cause neonatal flaccidity. (see 7.1.1 Pregnant Women)
Respiratory
Severe Chronic Obstructive Pulmonary Disease: Anticholinergic effects may cause thickening of secretions and impair expectorations; ventilatory failure may be exacerbated with the use of chlordiazepoxide hydrochloride. Risk-benefit should be considered when prescribing LIBRAX to patients with severe chronic obstructive pulmonary disease.
Sensitivity/Resistance
Patients who are sensitive to other benzodiazepines or any of the belladonna alkaloids may be sensitive to LIBRAX as well.
7.1 Special Populations
7.1.1 Pregnant Women
The use of LIBRAX® (anticholinergic and anxiolytic combination) in pregnancy is not recommended.
Chlordiazepoxide: Chlordiazepoxide crosses the placenta. Several studies have suggested an increased risk of congenital malformations (e.g. congenital malformations of the heart, cleft lip and/or palate) associated with the use of diazepam, chlordiazepoxide and meprobamate during the first trimester of pregnancy. Therefore, the administration of chlordiazepoxide is rarely justified in women of childbearing potential. If the drug is prescribed for a woman of childbearing potential, she should be warned to contact her physician regarding discontinuation of the drug if she intends to become, or suspects that she is pregnant. Because use of these drugs is rarely a matter of urgency, their use during this period should almost always be avoided.
Chronic use of chlordiazepoxide during pregnancy may cause physical dependence with resulting withdrawal symptoms in the neonate. Symptoms such as hypoactivity, hypotonia, hypothermia, respiratory depression, apnea, feeding problems, and impaired metabolic response to cold stress have been reported in neonates born of mothers who have received benzodiazepines during the late phase of pregnancy or at delivery. Use of chlordiazepoxide just prior to or during labour may cause neonatal flaccidity.
Clidinium: appropriate studies in humans have not been performed. However, reproduction studies in rats have not shown that clidinium has adverse effects on the foetus.
7.1.2 Breast-feeding
Chlordiazepoxide or its metabolites may be excreted in breast milk; use by breast-feeding mothers may cause sedation in the infant.
Clidinium may inhibit lactation.
LIBRAX should not be administered to breast-feeding women, unless the expected benefit to the mother outweighs the potential risk to the infant.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use.
No information is available on the relationship of age to the effect of chlordiazepoxide and clidinium in pediatric patients. However, it is known that infants and young children are especially susceptible to the toxic effects of atropine-like drugs, such as clidinium, and to the central nervous system effects of benzodiazepines, such as chlordiazepoxide.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Dosage should be limited to the smallest effective amount to preclude the development of ataxia, oversedation or confusion.
Geriatric patients may respond to usual doses of chlordiazepoxide and clidinium with excitement, agitation, drowsiness, or confusion.
Geriatric patients are especially susceptible to the anticholinergic side effects, such as constipation, dryness of mouth, and urinary retention (especially in males), of clidinium. If these side-effects occur and continue or are severe, medication should be discontinued.
Caution is also recommended when clidinium is given to geriatric patients, because of the danger of precipitating undiagnosed glaucoma.
Memory may become severely impaired in geriatric patients, especially those who already have memory problems, with the continued use of clidinium since this medication blocks the action of acetylcholine, which is responsible for many functions of the brain, including memory function.
Long-term use of LIBRAX should be avoided in geriatric or debilitated patients who may be more sensitive to benzodiazepines. There is an increased risk of cognitive impairment, delirium, falls, fractures, hospitalizations and motor vehicle accidents in these users. Enhanced monitoring is recommended in this population. (see 7 WARNINGS AND PRECAUTIONS, Falls and Fractures)
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The following adverse reactions have been reported with the use of LIBRAX:
Blood and Lymphatic System Disorders: agranulocytosis; granulocytopenia; leukopenia
Eye Disorders: increased intraocular pressure (eye pain); blurred vision
Gastrointestinal Disorders: decreased peristalsis - possible paralytic ileus (constipation); bloated feeling; dryness of mouth; nausea; stomach cramps. Constipation has occurred more often when LIBRAX therapy has been combined with other spasmolytic agents and/or a low residue diet
General Disorders and Administration Site Conditions: edema, unusual tiredness or weakness
Hepatobiliary Disorders: hepatic dysfunction; jaundice
Musculoskeletal and Connective Tissue Disorders: muscle cramps
Nervous System Disorders: CNS depression (slow heartbeat, shortness of breath, or troubled breathing); dizziness; drowsiness; confusion; ataxia; headache; trembling; seizures; syncope; extrapyramidal symptoms; changes in EEG patterns (low-voltage fast activity) have been observed in patients during and after chlordiazepoxide hydrochloride treatment
Psychiatric Disorders: paradoxical reaction (trouble in sleeping; unusual excitement; nervousness, or irritability); decreased sexual ability
Renal and Urinary Disorders: urinary hesitancy
Reproductive System and Breast Disorders: increased and decreased libido; minor menstrual irregularities
Skin and Subcutaneous Tissue Disorders: skin rash or hives; decreased sweating
From the adverse reactions listed above, skin eruptions, edema, minor menstrual irregularities, nausea and constipation, extrapyramidal symptoms, as well as increased and decreased libido have been infrequent and are generally controlled with reduction of dosage.
8.5 Post-Market Adverse Reactions
Injury, Poisoning and Procedural Complications
There have been reports of falls and fractures in benzodiazepine users due to adverse reactions such as sedation, dizziness and ataxia. The risk is increased in those taking concomitant sedatives (including alcoholic beverages), the elderly and debilitated patients.
Dependence/Withdrawal
Development of physical dependence and withdrawal following discontinuation of therapy has been observed with benzodiazepines such as LIBRAX. Severe and life-threatening symptoms have been reported. (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Addiction, Abuse and Misuse; 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance)
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions Concomitant use of LIBRAX and opioids may result in profound sedation, respiratory depression, coma and death.
(see 7 WARNINGS AND PRECAUTIONS, General, Risks from Concomitant use with Opioids) |
9.2 Drug Interactions Overview
Benzodiazepines, including LIBRAX, may produce additive CNS depressant effects when co-administered with alcohol, and medications, including opioids, which themselves can produce CNS depression.
The activity of benzodiazepines, including LIBRAX, may be enhanced by compounds which inhibit certain hepatic enzymes such as cytochrome P450 enzymes.
9.3 Drug-Behavioural Interactions
Benzodiazepines, including LIBRAX, may produce additive CNS depressant effects when co-administered with alcohol. Patients should be cautioned not to take alcohol because of the potentiation of effect that might occur.
9.4 Drug-Drug Interactions
CNS depressant drugs: Benzodiazepines, including LIBRAX, may produce additive CNS depressant effects when co-administered sedative antihistamines, narcotic analgesics, anticonvulsants, antipsychotics (neuroleptics), anesthetics, antidepressant agents or psychotropic medications which themselves can produce CNS depression.
Cytochrome P450: Compounds which inhibit certain hepatic enzymes (particularly cytochrome P450) may enhance the activity of benzodiazepines and benzodiazepine-like agents. Examples include cimetidine, erythromycin, ketoconazole, itroconazole, nefazodone and several HIV protease inhibitors.
Opioids: Due to additive CNS depressant effect, the concomitant use of benzodiazepines, including LIBRAX, and opioids increases the risk of profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations of concomitant use of benzodiazepines and opioids to the minimum required. Follow patients closely for respiratory depression and sedation (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Risks from Concomitant use with Opioids; 7 WARNINGS AND PRECAUTIONS, General, Concomitant use with opioids).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Chlordiazepoxide hydrochloride
Benzodiazepines, such as chlordiazepoxide hydrochloride, act as depressants of the central nervous system, producing all levels of CNS depression from mild sedation to hypnosis to coma depending on the dose taken.
Clidinium bromide
Anticholinergics, such as clidinium bromide, inhibit the muscarinic actions of acetylcholine on structures innervated by postganglionic cholinergic nerves as well as on smooth muscles that respond to acetylcholine but lack cholinergic innervation. These postganglionic receptor sites are present in the autonomic effector cells of the smooth muscle, cardiac muscle, sinoatrial and atrioventricular nodes, and exocrine glands. Depending on the dose, anticholinergics may reduce the motility and secretory activity of the gastrointestinal system. (see 7 WARNINGS AND PRECAUTIONS, Gastrointestinal)
10.2 Pharmacodynamics
Chlordiazepoxide hydrochloride
Pharmacologic experiments have shown that chlordiazepoxide hydrochloride is a potent central nervous system depressant and muscle relaxant.
The dose which induces definite neurologic symptoms in various animal species is in the range of 10-40 mg/kg p.o.; effects on behaviour and aggression can be seen with administration of 1-3 mg/kg, p.o., in more sensitive tests. Hostile monkeys were made tame by oral doses which did not cause sedation but eliminated fear and aggression. The taming effect was further demonstrated in rats made vicious by lesions in the septal area in the brain.
Clidinium bromide
Clidinium bromide is a quaternary ammonium compound with anticholinergic and antispasmodic activity. Clidinium bromide inhibits gastrointestinal motility and gastric secretions. As an anticholinergic agent, its activity approximates that of atropine sulfate against acetylcholine-induced spasms in isolated intestinal strips. In mice, oral administration proved it to be an effective antisialagogue in preventing pilocarpine-induced salivation. Spontaneous intestinal motility in both rats and dogs is reduced following oral dosing with 0.1 to 0.25 mg/kg.
Potent cholinergic ganglionic blocking effects (vagal) are produced with intravenous usage in anaesthetized dogs. Oral doses of 2.5 mg/kg to dogs produced signs of nasal dryness and slight pupillary dilation. In monkeys and rabbits, doses of 5 mg/kg p.o., given 3 times daily for 5 days did not produce apparent secretory or visual changes.
10.3 Pharmacokinetics
Absorption
Chlordiazepoxide hydrochloride is well absorbed from the gastrointestinal tract within 1 to 2 hours. Metabolic studies in animals and man have indicated that oral chlordiazepoxide hydrochloride is rapidly absorbed from the gastro-intestinal tract.
Clidinium bromide is poorly and very irregularly absorbed from the gastrointestinal tract. The action of clidinium bromide starts at about 1 hour after ingestion and lasts for approximately 3 hours.
Distribution
Chlordiazepoxide hydrochloride is highly protein bound (96 %).
Metabolism
Chlordiazepoxide hydrochloride and clidinium bromide are both metabolized in the liver. Chlordiazepoxide hydrochloride is demethylated to a metabolite identified as Ro 5-0883, deaminated to the "lactam" Ro 5-2092 and finally converted to the "open lactam" which is pharmacologically inert and is excreted in the urine as such or in the form of alkali-labile conjugates. Repeated administration of 20 mg of chlordiazepoxide b.i.d. for 14 days to adult subjects produced serum levels of about 2 µg/mL of chlordiazepoxide, 1 µg/mL of the demethylated metabolite Ro 5-0883, and 1 µg/mL of the "lactam" Ro 5-2092.
Elimination
The biological half-life for chlordiazepoxide hydrochloride is between 5 and 30 hours. In man, the half-life of chlordiazepoxide hydrochloride in plasma is 22-24 hours; in dogs 10-14 hours. Chlordiazepoxide hydrochloride is eliminated by the kidneys and clidinium bromide by the kidneys and in the feces.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15oC to 30oC)
12 SPECIAL HANDLING INSTRUCTIONS
None.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
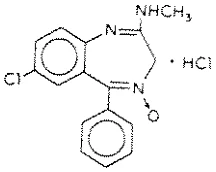
Chlordiazepoxide hydrochloride
Proper name: chlordiazepoxide hydrochloride
Chemical name: (1) 3H-1,4-Benzodiazepin-2-amine, 7-chloro-N-methyl-5-phenyl-, 4-oxide, monohydro-chloride
(2) 7-Chloro-2-(methylamino)-5-phenyl-3-H-1,4-benzodiazepine 4-oxide monohydro-chloride
Molecular formula and molecular mass: C16H14ClN30.HCl and 336.22g/mol
Structural formula:
Clidinium bromide
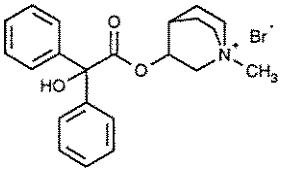
Proper name: clidinium bromide
Chemical name: (1) 1-Azoniabicyclo [2.2.2] octane, 3-[(hydroxy-diphenylacetyl) oxy]-1-methyl; bromide;
(2) 3-Hydroxy-1-methylquinuclidinium bromide benzilate
Molecular formula and molecular mass: C22H26BrN03 and 432.36 g/mol
Structural formula:
14 CLINICAL TRIALS
The clinical trial data on which the original indication was authorized is not available.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Chlordiazepoxide hydrochloride
The oral LD50 of single doses of chlordiazepoxide hydrochloride is 720±51 mg/kg, as determined in mice observed for a period of five days following dosage.
Chronic toxicity studies in rats, dogs, monkeys and chicken have shown that chlordiazepoxide hydrochloride did not exhibit specific organotoxic properties.
Clidinium bromide
The oral LD50 of single doses of clidinium bromide is 860±57 mg/kg as determined in mice observed for a period of 5 days following dosage.
Reproductive and Developmental Toxicology
Chlordiazepoxide hydrochloride
In rats, reproduction studies in which chlordiazepoxide hydrochloride was administered orally at doses of 10, 20, and 80 mg/kg/day showed no congenital anomalies, no effect on lactation or growth of the off-spring.
However, at an oral dose of 100 mg/kg/day, there was observed a significant decrease in the fertilization rate and a marked decrease in the viability and body weight of the offspring which may be attributed to sedation of dams.
Clidinium bromide
Studies in rats employing dosages of 2.5 and 10 mg/kg/day of clidinium bromide showed no significant effects on fertility, gestation, viability of off-spring, lactation, or fetal abnormalities.
Chlordiazepoxide hydrochloride and Clidinium bromide combination
In a rat reproductive study, oral daily doses were administered through two successive matings, in two concentrations of 2.5 mg/kg chlordiazepoxide hydrochloride with 1.25 mg/kg clidinium bromide, or 25 mg/kg chlordiazepoxide hydrochloride with 12.5 mg/kg clidinium bromide. No significant differences were noted between the control and treated groups, except a slight decrease in the number of animals surviving through lactation at the highest dosage in the first mating, and a slight decrease in the number of pregnant females and in the percentage of off-spring surviving until weaning in the second mating.