


Product Monograph - Mar-Eszopiclone
RECENT MAJOR LABEL CHANGES
Sections or subsections that are not applicable at the time of authorization are not listed.
Table of Contents
RECENT MAJOR LABEL CHANGES ................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION ......................................................... 4
- 1.
INDICATIONS .......................................................................................................... 4
1.1 Pediatrics ............................................................................................................ 4
1.2 Geriatrics ............................................................................................................. 4
- 2. CONTRAINDICATIONS ........................................................................................... 4
- 3. SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................. 5
- 4.
DOSAGE AND ADMINISTRATION .......................................................................... 6
4.1 Dosing Considerations ........................................................................................ 6
4.2 Recommended Dose and Dosage Adjustment ................................................... 6
4.4 Administration ..................................................................................................... 7
4.5 Missed Dose ....................................................................................................... 7
- 5. OVERDOSAGE ........................................................................................................ 7
- 6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................. 8
- 7.
WARNINGS AND PRECAUTIONS .......................................................................... 9
7.1 Special Populations .......................................................................................... 14
7.1.1 Pregnant Women ...................................................................................... 14
7.1.2 Breast-feeding ........................................................................................... 15
7.1.3 Pediatrics .................................................................................................. 15
7.1.4 Geriatrics ................................................................................................... 15
7.1.5 Hepatic Impairment ................................................................................... 15
7.1.6 Renal Impairment ..................................................................................... 15
- 8.
ADVERSE REACTIONS ......................................................................................... 16
8.1 Adverse Drug Reaction Overview ..................................................................... 16
8.2 Clinical Trial Adverse Reactions ....................................................................... 16
8.3 Less Common Clinical Trial Adverse Drug Reactions ....................................... 18
8.5 Post-Market Adverse Drug Reactions ............................................................... 20
- 9.
DRUG INTERACTIONS .......................................................................................... 21
9.1 Serious Drug Interactions ................................................................................. 21
9.2 Drug Interactions Overview ............................................................................... 21
9.3 Drug-Behavioural Interactions Alcohol .............................................................. 21
9.4 Drug-Drug Interactions CNS Depressants ........................................................ 21
9.5 Drug-Food Interactions ..................................................................................... 23
9.6 Drug-Herb Interactions...................................................................................... 23
9.7 Drug-Laboratory Interactions ............................................................................ 23
- 10.
CLINICAL PHARMACOLOGY ............................................................................... 24
10.1 Mechanism of Action .................................................................................... 24
10.2 Pharmacodynamics ...................................................................................... 24
10.3 Pharmacokinetics ......................................................................................... 24
- 11. STORAGE, STABILITY AND DISPOSAL .............................................................. 27
- 12. SPECIAL HANDLING INSTRUCTIONS ................................................................. 27
PART II: SCIENTIFIC INFORMATION .............................................................................. 28
- 13. PHARMACEUTICAL INFORMATION .................................................................... 28
- 14.
CLINICAL TRIALS ................................................................................................. 29
14.1 Trial Design and Study Demographics ......................................................... 29
14.2 Study Results ............................................................................................... 29
- 15. MICROBIOLOGY ................................................................................................... 31
- 16. NON-CLINICAL TOXICOLOGY ............................................................................. 31
- 17. SUPPORTING PRODUCT MONOGRAPHS ........................................................... 35
PATIENT MEDICATION INFORMATION .......................................................................... 36
READ THIS FOR SAFE AND EFFECTIVE USE OF YOUR MEDICINE ............................ 36
PART I: HEALTH PROFESSIONAL INFORMATION
1. INDICATIONS
MAR-ESZOPICLONE(eszopiclone) is indicated for short-term (usually not exceeding 7-10 days) use for:
- treatment and symptomatic relief of insomnia characterized by difficulty falling asleep
- frequent nocturnal awakenings and/or early morning awakenings
where disturbed sleep results in impaired daytime functioning (see 4.4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations).
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. [see also 7.1.3 Pediatrics].
1.2 Geriatrics
Geriatrics (>65 years of age): There is a risk for greater sensitivity to the drug effects in the elderly [see also 7.1.4 Geriatrics]. A lower maximum dose is recommended in the elderly (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics).
Long-term use of MAR-ESZOPICLONE should be avoided, including in geriatric patients. Enhanced monitoring is recommended (see 7 WARNINGS AND PRECAUTIONS, Falls and Fractures; 4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Considerations).
2. CONTRAINDICATIONS
MAR-ESZOPICLONE (eszopiclone) is contraindicated in:
- Patients who are hypersensitive to this drug or to zopiclone (marketed in Canada as IMOVANE), or to any ingredient in the formulation or component of the container. Observed reactions to eszopiclone have included angioedema and anaphylaxis (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity). For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section.
- Patients with myasthenia gravis.
- Severe respiratory impairment (e.g., significant sleep apnea syndrome).
- Elderly patients receiving concomitant potent CYP3A4 inhibitors or having severe hepatic insufficiency.
- Patients who have experienced complex sleep-related behaviours after taking Eszopiclone tablets or any other hypnotic agent (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, COMPLEX SLEEP-RELATED BEHAVIOURS)
- SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Addiction, Abuse and Misuse The use of benzodiazepines, or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, can lead to abuse, misuse, addiction, physical dependence and withdrawal reactions. Abuse and misuse can result in overdose or death, especially when benzodiazepines, or other sedative- hypnotic drugs, such as Mar Eszopiclone, are combined with other medicines, such as opioids, alcohol or illicit drugs.
Withdrawal Benzodiazepines, or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, can produce severe or life-threatening withdrawal symptoms.
(see 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance) Risks from Concomitant Use with Opioids Concomitant use of MAR-ESZOPICLONE and opioids may result in profound sedation, respiratory depression, coma and death (see 7 WARNINGS AND PRECAUTIONS, General, Concomitant Use with Opioids).
Complex Sleep-Related Behaviours: Complex sleep behaviours including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur following use of non-benzodiazepine sedative- hypnotics. Some of these events may result in serious injuries, including death. Discontinue MAR-ESZOPICLONE immediately if a patient experiences a complex sleep behavior. (See 7 WARNINGS AND PRECAUTIONS, Complex Sleep-related Behaviours) |
|---|
4. DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Sleep disturbance may be the presenting manifestation of a physical and/or psychiatric disorder. Consequently, a decision to initiate symptomatic treatment of insomnia should only be made after the patient has been carefully evaluated.
- The use of hypnotics should be restricted for insomnia where disturbed sleep results in impaired daytime functioning.
- The length of treatment should be for the minimum duration necessary for the patient. Treatment with MAR-ESZOPICLONE should usually not exceed 7-10 consecutive days. Use for more than 2-3 consecutive weeks requires complete re-evaluation of the patient. Prescriptions for MAR-ESZOPICLONE should be written for short-term use (7-10 days) and it should not be prescribed in quantities exceeding a 1-month supply.
- MAR-ESZOPICLONE should always be prescribed at the lowest effective dose for the shortest duration possible.
Discontinuation
- MAR-ESZOPICLONE can produce withdrawal signs and symptoms or rebound phenomena following abrupt discontinuation or rapid dose reduction (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Withdrawal; 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance; 8. ADVERSE REACTIONS, Withdrawal Events.).
- Abrupt discontinuation should be avoided and treatment - even if only of short duration - should be terminated by gradually tapering the dosage schedule under close monitoring.
- Tapering should be tailored to the specific patient. Special attention should be given to patients with a history of seizure.
- If a patient experiences withdrawal signs and symptoms, consider postponing the taper or raising MAR-ESZOPICLONE to the previous dosage prior to proceeding with a gradual taper.
Geriatric
- Geriatric patients in particular may be more sensitive to MAR-ESZOPICLONE (see 7 WARNINGS AND PRECAUTIONS, Falls and Fractures).
- Long-term use of MAR-ESZOPICLONE should be avoided, including in geriatric patients. Enhanced monitoring is recommended.
Food effect
- Taking MAR-ESZOPICLONE with or immediately after a heavy, high-fat meal results in slower absorption and would be expected to reduce the effect of MAR-ESZOPICLONE on sleep latency (see 10 CLINICAL PHARMACOLOGY)
4.2 Recommended Dose and Dosage Adjustment
The recommended starting dose is 1 mg. The dose can be increased to 2 mg or 3 mg if clinically indicated. Use the lowest effective dose of MAR-ESZOPICLONE possible for the patient. In some patients, the higher morning blood levels of MAR-ESZOPICLONE following use of the 2 mg or 3 mg dose, increase the risk of next day impairment of driving and other activities that require full alertness. The total dose of MAR-ESZOPICLONE should not exceed 3 mg, once daily immediately before bedtime (see 7 WARNINGS AND PRECAUTIONS, CNS Depressant Effects and Next-Day Impairment).
Geriatrics (> 65 years of age)
In elderly or debilitated patients, the total dose of MAR-ESZOPICLONE should not exceed 2 mg.
Pediatrics (< 18 years of age)
MAR-ESZOPICLONE is not indicated for patients under 18 years of age.
Hepatic Impairment, Renal Impairment or Use with Potent CYP 3A4 Inhibitors
In patients with severe hepatic or renal impairment or in patients coadministered MAR-ESZOPICLONE with potent CYP3A4 inhibitors, the total dose of MAR-ESZOPICLONE should not exceed 2 mg.
Use with CNS Depressants
Dosage adjustments may be necessary when MAR-ESZOPICLONE is combined with other CNS depressant drugs because of the potentially additive effects.
4.4 Administration
- MAR-ESZOPICLONE should be taken orally immediately before retiring or when in bed.
- MAR-ESZOPICLONE tablets must not be broken or crushed prior to ingestion.
4.5 Missed Dose
If a dose is missed, do not take in the middle of the night. Patients should wait and take the next dose at bedtime the next night, if a dose is needed.
5. OVERDOSAGE
In clinical studies with eszopiclone, one case of overdose with up to 36 mg of eszopiclone was reported in which the subject fully recovered. Since commercial marketing began, spontaneous cases of overdose up to 270 mg (90 times the maximum recommended dose of eszopiclone) have been reported, in which patients have recovered. Fatal overdose is more likely to occur when eszopiclone is taken in combination with other CNS depressants including alcohol.
Signs and symptoms of overdose effects of CNS depressants can be expected to present as exaggerations of the pharmacological effects noted in preclinical testing. Impairment of consciousness ranging from somnolence to coma has been described. Rare individual instances of fatal outcomes following overdose with racemic zopiclone have been reported in European post-marketing reports, most often associated with overdose with other CNS- depressant agents. Methemoglobinemia in association with overdose of racemic zopiclone has been reported. General symptomatic and supportive measures should be used along with immediate gastric lavage where appropriate. Intravenous fluids should be administered as needed. Flumazenil may be useful; however, flumazenil administration may contribute to the appearance of neurological symptoms (agitation, anxiety, convulsions and emotional lability).
As in all cases of drug overdose, respiration, pulse, blood pressure, and other appropriate signs should be monitored and general supportive measures employed. Hypotension and CNS depression should be monitored and treated by appropriate medical intervention. Consider monitoring methemoglobin in the setting of high dose overdosage. The value of dialysis in the treatment of overdosage has not been determined.
As with the management of all overdosage, the possibility of multiple drug ingestion should be considered. The physician may wish to consider contacting a poison control center for up -to- date information on the management of hypnotic drug product overdosage.
6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet/1 mg, 2 mg, and 3 mg/eszopiclone | Tablets: Croscarmellose Sodium, Lactose monohydrate, Magnesium Stearate, Microcrystalline Cellulose Film-coat: Opadry II Blue 33G90514 (1mg only) – Hypromellose, Lactose Monohydrate, Polyethylene Glycol, Titanium Dioxide, Triacetin, FD&C Blue #2, Opadry II white 33G28435 (2mg only) - Hypromellose, Lactose Monohydrate, Polyethylene Glycol, Titanium Dioxide, Triacetin Opadry II Blue 33G505001 (3mg only) - Hypromellose, Lactose Monohydrate, Polyethylene Glycol, Titanium Dioxide, Triacetin, FD&C Blue #2 |
MAR-ESZOPICLONE (eszopiclone) is a round tablet containing 1 mg, 2 mg, or 3 mg of eszopiclone. Tablets are film coated and debossed on one side.
- MAR-ESZOPICLONE 1 mg tablets are light blue coloured, round, biconvex, film coated, debossed with “195” on one side and plain on other side
- MAR-ESZOPICLONE2 mg tablets are white to off-white colored, round biconvex film coated tablets debossed with “196” on one side and plain on other side
- MAR-ESZOPICLONE 3 mg tablets are dark blue coloured, round biconvex film coated tablets debossed with “197” on one side and plain on other side
The 1 mg tablets are supplied in bottles of 30 tablets, cartons of 100 tablets (10 x10 tablets PVC/PE/PVdC Blister Pack and 10 x10 tablets Alu-Alu blister pack) and cartons of 3 tablets (1x3 tablets Alu-Alu blister pack and 1x3 tablets PVC/PE/PVDC blister pack). The 2 mg tablets are supplied in bottles of 100 tablets. The 3 mg tablets are supplied in cartons of 100 tablets (10x10 tablets PVC/PE/PVdC Blister Pack and 10 x10 tablets Alu-Alu blister pack) and cartons of 3 tablets (1x3 tablets Alu-Alu blister pack and 1x3 tablets PVC/PE/PVDC blister pack).
7. WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Because sleep disturbances may be the presenting manifestation of a physical and/or psychiatric disorder, symptomatic treatment of insomnia should be initiated only after a careful evaluation of the patient to identify the underlying cause whenever possible. The failure of insomnia to remit after 7 to 10 days of treatment may indicate the presence of a primary psychiatric and/or medical illness that should be evaluated. Worsening of insomnia or the emergence of new thinking or behaviour abnormalities may be the consequence of an unrecognized psychiatric or physical disorder. Such findings have emerged during the course of treatment with sleep-inducing drugs, including MAR-ESZOPICLONE (eszopiclone).
Because some of the important adverse effects of MAR-ESZOPICLONE appear to be dose-related, it is important to use the lowest possible effective dose, especially in the elderly. Inappropriate, heavy sedation in the elderly, may result in accidental events including falls. The use of the lowest effective dose is also consistent with management of other dose -related risks associated with eszopiclone (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, COMPLEX SLEEP-RELATED BEHAVIOURS, 7 WARNINGS AND PRECAUTIONS, Neurologic, Amnesia, Complex Sleep-related Behaviours, CNS Depressant Effects and Next-Day Impairment Dependence/Tolerance).
MAR-ESZOPICLONE should be taken immediately before bedtime. Taking a hypnotic agent while still up and about may result in short-term memory impairment, hallucinations, impaired coordination, dizziness, and lightheadedness (see 7 WARNINGS AND PRECAUTIONS, Neurologic and Psychiatric).
Benzodiazepines and benzodiazepine-like agents are to be used with extreme caution in patients with a history of alcohol or substance abuse.
Concomitant Use with Opioids: Concomitant use of MAR-ESZOPICLONE and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are not possible (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Risks and Concomitant Use with Opioids; 9 DRUG INTERACTIONS, Serious Drug Interactions).
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs, such as MAR-ESZOPICLONE, with opioids.
If a decision is made to prescribe MAR-ESZOPICLONE concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of MAR-ESZOPICLONE than indicated, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking MAR-ESZOPICLONE, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response.
Follow patients closely for signs and symptoms of respiratory depression and sedation (see 5 OVERDOSAGE).
Advise both patients and caregivers about the risks of respiratory depression and sedation when MAR-ESZOPICLONE is used with opioids.
Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the opioid have been determined (see 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery).
Complex Sleep-related Behaviours
Complex sleep-related behaviours including sleep-walking, sleep-driving, and engaging in other potentially dangerous activities while not fully awake may occur following the first or any subsequent use of MAR-ESZOPICLONE. Patients may seriously injure themselves or others during complex sleep-related behaviours. Fatal outcomes have been reported. Other complex sleep- related behaviours (e.g., preparing and eating food, making phone calls, or having sex) have also been reported. Patients usually do not remember these events. Post-marketing reports have shown that complex sleep-related behaviours may occur with MAR-ESZOPICLONE alone at recommended doses, with or without the concomitant use of alcohol or other CNS-depressants (see 9 DRUG INTERACTIONS). However, when taken together, alcohol or CNS depressants may increase the risk of such behaviours, as does the use of MAR-ESZOPICLONE at doses exceeding the maximum recommended dose. Discontinue MAR-ESZOPICLONE immediately if a patient experiences a complex sleep-related behaviour.
MAR-ESZOPICLONE is not to be taken with alcohol.
Caution is needed with concomitant use of other CNS depressants drugs.
Caution is recommended in patients with a personal or family history of sleepwalking. Although complex sleep-related behaviours have been reported in patients with or without history of sleepwalking, it is possible that some predisposed patients are at increased risk of experiencing these complex behaviours during treatment with MAR-ESZOPICLONE.
The use of MAR-ESZOPICLONE in patients with other disorders known to affect sleep and induce frequent awakenings (e.g. sleep apnea, Periodic Limb Movement Disorder, Restless Legs Syndrome) is discouraged, as they may be also at increased risk of complex sleep-related behaviours.
Treatment with MAR-ESZOPICLONE is limited to a short duration (see 1 INDICATIONS, 4 DOSAGE AND ADMINISTRATION).
Patients should be instructed not to exceed the recommended dose.
Caution should be exercised with concomitant use of potent CYP3A4 inhibitors (see 9 DRUG INTERACTIONS).
Dependence/Tolerance
Use of benzodiazepines or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, can lead to abuse, misuse, addiction, physical dependence (including tolerance) and withdrawal reactions. Abuse and misuse can result in overdose or death, especially when benzodiazepines, or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, are combined with other medicines, such as opioids, alcohol, or illicit drugs.
The risk of dependence increases with higher doses and longer term use but can occur with short-term use at recommended therapeutic doses. Cases of dependence have been reported more frequently in patients treated with sedative-hypnotic drugs, such as MAR-ESZOPICLONE, for longer than 4 weeks. The risk of dependence is greater in patients with a history of psychiatric disorders and/or substance (including alcohol) use disorder. Interdose daytime anxiety and rebound anxiety may increase the risk of dependency in MAR-ESZOPICLONE treated patients.
- Discuss the risks of treatment with MAR-ESZOPICLONE with the patient, considering alternative (including non-drug) treatment options.
- Carefully evaluate each patient’s risk of abuse, misuse and addiction, considering their medical condition and concomitant drug use, prior to prescribing MAR-ESZOPICLONE. In individuals prone to substance use disorder, MAR-ESZOPICLONE should only be administered if deemed medically necessary, employing extreme caution and close supervision.
- MAR-ESZOPICLONE should always be prescribed at the lowest effective dose for the shortest duration possible.
- All patients receiving benzodiazepines or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, should be routinely monitored for signs and symptoms of misuse and abuse. If a substance use disorder is suspected, evaluate the patient and refer them for substance abuse treatment, as appropriate.
Once physical dependence has developed, abrupt termination of treatment will be accompanied by withdrawal symptoms.
Rebound Insomnia: A transient syndrome whereby the symptoms that led to treatment with sedative/hypnotic agents recur in an enhanced form may occur on withdrawal of hypnotic treatment. It may be accompanied by other reactions including mood changes, anxiety and restlessness.
Rebound insomnia manifested as an increase in sleep latency for one to two nights has been observed following cessation of MAR-ESZOPICLONE treatment. These events resolved without intervention. It is important that patients be aware of the possibility of rebound phenomena, thereby minimising anxiety should such symptoms develop when the medicinal product is discontinued.
Withdrawal: Benzodiazepines or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, can produce withdrawal signs and symptoms, ranging from mild to severe and even life threatening, following abrupt discontinuation or rapid dose reduction. The risk of withdrawal is higher with higher dosages and/or prolonged use, but can occur with short -term use at recommended therapeutic doses. Patients given therapeutic dosages for as few as 1 -2 weeks can also have withdrawal symptoms including daytime anxiety between nightly doses.
Since symptoms of withdrawal are often similar to those for which the patient is being treated, it may be difficult to distinguish from a relapse of the patient’s condition.
Severe or life-threatening signs and symptoms of withdrawal include delirium, derealisation, depersonalisation, hallucinations, hyperacusis, seizures (including status epilepticus). (See 8.5 Post-Market Adverse Reactions, Dependence/Withdrawal).
Other withdrawal signs and symptoms, similar in character to those noted with barbiturates and alcohol, include abdominal and muscle cramps, cognitive impairment, convulsions, diarrhea, dysphoria, extreme anxiety, headache, hypersensitivity to light, noise and physical contact, insomnia, irritability, muscle pain or stiffness, paresthesia, perceptual disturbances, restlessness, sweating, tension, tremors and vomiting. There is also a possibility of rebound anxiety or rebound insomnia.
- Abrupt discontinuation should be avoided and treatment - even if only of short duration - should be terminated by gradually tapering the dosage schedule under close monitoring.
Tapering should be tailored to the specific patient. Special attention should be given to
- If a patient experiences withdrawal symptoms, consider postponing the taper or raising the MAR-ESZOPICLONE dose to the previous dosage prior to proceeding with a gradual taper.
- Inform patients of risk of discontinuing abruptly, reducing dosage rapidly or switching medications.
- As with all hypnotics, repeat prescriptions should be limited to those who are under medical supervision.
- Stress the importance of consulting with their health care professional in order to discontinue safely.
- It may be useful to inform the patient when treatment is started that it will be of limited duration and to explain precisely how the dosage will be progressively decreased.
- Patients experiencing withdrawal symptoms should seek immediate medical attention. (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Addiction, Abuse and Misuse, Withdrawal; 4 DOSAGE AND ADMINISTRATION, Dosing Considerations)
Driving and Operating Machinery
CNS Depressant Effects and Next-Day Impairment: Like other sedative/hypnotic drugs, MAR-ESZOPICLONE has CNS-depressant effects. Due to the rapid onset of action, MAR-ESZOPICLONE should be ingested immediately prior to going to bed.
Patients should be cautioned against engaging in hazardous occupations requiring complete mental alertness or motor coordination such as operating machinery or driving a motor vehicle after ingesting the drug.
This includes potential impairment of the performance of such activities that may occur the day following ingestion of MAR-ESZOPICLONE A. The risk of next day psychomotor impairment, including impaired driving, is increased if MAR-ESZOPICLONE is taken with less than a full night of sleep remaining; if a higher dose than the recommended dose is taken; if co-administered with other CNS depressants; if co-administered with other drugs that increase the blood level of eszopiclone or in patients with severe hepatic impairment. Patients should be cautioned against taking MAR-ESZOPICLONE in these circumstances.
Because MAR-ESZOPICLONE can cause drowsiness and a decreased level of consciousness, patients, particularly the elderly, are at higher risk of falls.
The lowest effective dose for the patient should be used.
MAR-ESZOPICLONE is not to be taken with alcohol or other sedative hypnotics at bedtime or the middle of the night. If concomitant use of another CNS depressant or a drug that increases eszopiclone blood levels is clinically warranted, dosage adjustments of MAR-ESZOPICLONE may be necessary.
Even if MAR-ESZOPICLONE is taken as instructed, some patients may still have eszopiclone blood levels in the morning high enough to produce impairment (see 4 DOSAGE AND ADMINISTRATION and 9 DRUG INTERACTIONS).
Patient counseling information regarding next-day impairment: Tell patients that MAR-ESZOPICLONE has the potential to cause next-day impairment, and that this risk is increased if dosing instructions are not carefully followed. Tell patients not to drive a car or engage in hazardous activities requiring complete alertness until they experience how the drug affects them the next day. Tell patients that if they took MAR-ESZOPICLONE as instructed and do not feel drowsy in the morning, they still have to wait for at least 12 hours after dosing before driving or engaging in other activities requiring full mental alertness, especially for elderly patients, patients with severe hepatic impairment and for patients who take the 3 mg dose. Inform patients that impairment can be present despite feeling fully awake. Advise patients that increased drowsiness and decreased consciousness may increase the risk of falls in some patients.
Falls and Fractures
There have been reports of falls and fractures among users of benzodiazepines or other sedative-hypnotic drugs, such as MAR-ESZOPICLONE, due to adverse reactions such as sedation, dizziness and ataxia. The risk is increased in those taking concomitant sedatives (including alcoholic beverages), and for geriatric or debilitated patients.
Hypersensitivity
Severe Anaphylactic and Anaphylactoid Reactions: Rare cases of angioedema involving the tongue, glottis, or larynx have been reported in patients after taking the first or subsequent doses of a sleep-inducing agent, including MAR-ESZOPICLONE. Some patients have had additional symptoms such as dyspnea, throat closing, or nausea and vomiting that suggest anaphylaxis. Some patients have required medical therapy in the emergency department. If angioedema involves the tongue, glottis, or larynx, airway obstruction may occur and be fatal. Patients who develop angioedema after treatment with MAR-ESZOPICLONE should not be rechallenged with the drug.
Neurologic
Amnesia: Anterograde amnesia of varying severity has been reported following therapeutic doses of benzodiazepines or benzodiazepine-like agents. The event is rare with MAR-ESZOPICLONE. Anterograde amnesia is more likely to occur when sleep is interrupted or when retiring to bed is delayed after intake of the tablet. Anterograde amnesia is a dose-related phenomenon and elderly subjects may be at particular risk.
Cases of transient global amnesia and “traveler’s amnesia” have also been reported in association with benzodiazepines, the latter in individuals who have taken the drug, often in the middle of the night, to induce sleep while travelling. Transient global amnesia and traveler’s amnesia are unpredictable and not necessarily dose-related phenomena.
To reduce the possibility of anterograde amnesia, patients should ensure that they take the tablet strictly when retiring for the night. Patients should be warned not to take MAR-ESZOPICLONE under circumstances in which a full night’s sleep and clearance of the drug from the body are not possible before they need again to resume full activity.
Cognitive Function: Benzodiazepines and benzodiazepine-like compounds may affect concentration, attention and vigilance. This risk is greater in the elderly and in patients with cerebral impairment.
Psychomotor Impairment: Benzodiazepines and benzodiazepine-like agents may induce psychomotor impairment, including accidental injury and falls. In particular, elderly patients may be more vulnerable to falls resulting in injuries such as hip fractures. Psychomotor impairment most often occurs several hours after ingesting the product and therefore patients are to ensure they will have an uninterrupted sleep period of 7-8 hours (see also 7 WARNINGS AND PRECAUTIONS, CNS Depressant Effects and Next-Day Impairment, and 7.1 Special Populations, 7.1.4 Geriatrics).
Psychiatric
Abnormal Thinking and Behavioural Changes: Reactions like restlessness, aggravated insomnia, agitation, irritability, aggressiveness, delusion, rages, nightmares, parasomnia, depersonalization, hallucinations, psychoses, inappropriate behaviour, and other adverse behavioural effects are known to occur when using benzodiazepines or benzodiazepine-like agents. They may be drug-induced, spontaneous in origin, or a result of an underlying psychiatric or physical disorder. Caution is warranted in patients with a history of violent behaviour and a history of unusual reactions to sedatives including alcohol and the benzodiazepines or benzodiazepine-like agents. These reactions are more likely to occur in the elderly. If this occurs, discontinuation of MAR-ESZOPICLONE is to be considered until further evaluation. Any new behavioural sign or symptom requires careful and immediate evaluation.
Anxiety, restlessness: An increase in daytime anxiety and/or restlessness have been observed during treatment with MAR-ESZOPICLONE. This may be a manifestation of interdose withdrawal, due to the short elimination half-life of the drug.
Depression: In primary depressed patients, worsening of depression, including suicidal thoughts and actions (including completed suicides), have been reported in association with the use of sedative/hypnotics. Benzodiazepines and benzodiazepine-like agents are not to be used alone to treat patients with depression or anxiety associated with depression (suicide may be precipitated in such patients). These agents should be administered with caution to patients exhibiting signs and symptoms of depression. Intentional overdose is more common in this group of patients and the least amount of drug that is feasible should be prescribed for the patient at any one time.
Reproductive Health: Female and Male Potential
- Fertility
A human clinical study of adult males did not show any evidence of impaired fertility. In a human clinical study there were no observed changes in female menstrual cycling. Animal studies with eszopiclone demonstrated reduced male and female fertility at exposures considered to be sufficiently in excess of the maximum human exposure.
Respiratory
A study in healthy volunteers did not reveal respiratory-depressant effects at doses up to 7 mg (2.5-folds the maximum recommended dose). Since sedative/hypnotics have the capacity to depress respiratory drive, caution is advised if MAR-ESZOPICLONE is prescribed to patients with compromised respiratory function.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. MAR-ESZOPICLONE is not recommended during pregnancy and should be used only if the potential benefit justifies the potential risk to the fetus.
Animal data indicate possible effects at supratherapeutic doses (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
Animal and human studies have demonstrated transfer of racemic zopiclone into breast milk. It is not known whether MAR-ESZOPICLONE is excreted in human milk. The excretion of eszopiclone in milk has not been studied in animals. Because many drugs are excreted in human milk, administration of MAR-ESZOPICLONE to a nursing woman is not recommended.
7.1.3 Pediatrics
The safety and effectiveness of eszopiclone in children below the age of 18 have not been established. MAR-ESZOPICLONE failed to demonstrate efficacy in controlled clinical studies of pediatric patients with insomnia associated with Attention Deficit/Hyperactivity Disorder (ADHD).
In a clinical study of patients aged 6-17 years with insomnia associated with ADHD (most of whom were using ADHD treatments), psychiatric and nervous system disorders comprised the most frequent treatment emergent adverse events when MAR-ESZOPICLONE was compared to placebo and included dysgeusia (9% vs. 1%), dizziness (6% vs. 2%), hallucinations (2% vs. 0%), and suicidal ideation (0.3% vs. 0%).
7.1.4 Geriatrics
Impaired motor and/or cognitive performance after repeated exposure or unusual sensitivity to benzodiazepine and benzodiazepine-like drugs is a concern in the treatment of the elderly. Inappropriate, heavy sedation may result in accidental events/fall. Subjects 65 years and older had 41% higher exposure (AUC) and prolonged elimination of eszopiclone (t½ approximately 9 hours) compared to non-elderly adults. The maximum nightly dose of M A R - E S Z O P I C L O N E must not exceed 2 mg in elderly patients. (see also 4 DOSAGE AND ADMINISTRATION, 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Geriatrics).
Long-term use of MAR-ESZOPICLONE should be avoided, including in geriatric patients or debilitated patients who may be more sensitive to MAR-ESZOPICLONE. There is an increased risk of cognitive impairment, delirium, falls, fractures, hospitalizations and motor vehicle accidents in these users. Enhanced monitoring is recommended in this population.
7.1.5 Hepatic Impairment
Eszopiclone exposure was increased 2-fold and elimination half-life was prolonged by 8 hours (from 6.7 hrs to 15.3 hrs) in patients with severe hepatic impairment compared with the healthy volunteers. The dose of MAR-ESZOPICLONE should not exceed 2 mg in patients with severe hepatic impairment (see 4 DOSAGE AND ADMINISTRATION). No dose adjustment is necessary for patients with mild-to-moderate hepatic impairment.
7.1.6 Renal Impairment
Compared with healthy subjects, subjects with severe renal impairment had an increase in eszopiclone exposure of 47%. The dose of MAR-ESZOPICLONE in patients with severe renal impairment should not exceed 2 mg (see 4 DOSAGE AND ADMINISTRATION). No dose adjustment is necessary for patients with mild-to-moderate renal impairment.
8. ADVERSE REACTIONS
8.1 Adverse Drug Reaction Overview
In placebo-controlled, parallel-group clinical trials in the elderly, 3.8% of 208 patients who received placebo, 2.3% of 215 patients who received 2 mg Eszopiclone tablets, and 1.4% of 72 patients who received 1 mg Eszopiclone tablets discontinued treatment due to an adverse reaction. In the 6 -week parallel-group study in adults, no patients in the 3 mg arm discontinued because of an adverse reaction. In the long-term 6-month study in adult insomnia patients, 7.2% of 195 patients who received placebo and 12.8% of 593 patients who received 3 mg Eszopiclone tablets discontinued due to an adverse reaction. No reaction that resulted in discontinuation occurred at a rate of greater than 2%.
The most frequently observed adverse events during these trials were expected from the known pharmacologic properties of eszopiclone. These include unpleasant taste (dysgeusia), dizziness, somnolence, and dry mouth. The overall incidence of serious adverse events was similar between treatment groups (placebo: 1.0 to 2.1%; eszopiclone: 1.2 to 2.3%).
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates. Adverse events reported in this section were reported from a total of 11 studies that enrolled just over 4400 subjects. These trials were conducted in patients with insomnia using night time administration of eszopiclone. Study duration ranged from short-term dosing (1-7 days) to 6 months, with doses ranging from 1 to 3 mg. Study populations included non-elderly adults with and without medical co-morbidities and elderly adults. Treatment emergent adverse events (TEAEs) include those events that occurred or worsened upon or after administration of the first dose of double-blind study medication.
Treatment Emergent Adverse Events in Placebo-Controlled Clinical Trials with Dosing up to 2 weeks in Elderly Subjects
The most frequently reported adverse events are summarized in Table 2.
Table 2. All Treatment Emergent Adverse Events with an Incidence >2%in Either Active Group1 in the Pooled (2 Weeks) Studies in Elderly Subjects
| BODY SYSTEM | All TEAEs | ||
|---|---|---|---|
| Preferred Term Subject n (%) | Placebo (N=208) | ESZ 1 mg (N=72) | ESZ 2 mg (N=215) |
| AT LEAST ONE AE | 91 (43.8) | 29 (40.3) | 100 (46.5) |
| BODY AS A WHOLE | |||
| Headache | 29 (13.9) | 11 (15.3) | 29 (13.5) |
| Pain | 4 (1.9) | 3 (4.2) | 10 (4.7) |
| Accidental injury | 2 (1.0) | 0 | 6 (2.8) |
| DIGESTIVE | |||
| Dry mouth | 4 (1.9) | 2 (2.8) | 14 (6.5) |
| Diarrhoea | 5 (2.4) | 3 (4.2) | 5 (2.3) |
| Dyspepsia | 5 (2.4) | 4 (5.6) | 4 (1.9) |
| NERVOUS | |||
| BODY SYSTEM | All TEAEs | ||
|---|---|---|---|
| Preferred Term Subject n (%) | Placebo (N=208) | ESZ 1 mg (N=72) | ESZ 2 mg (N=215) |
| Somnolence | 14 (6.7) | 5 (6.9) | 12 (5.6) |
| Dizziness | 5 (2.4) | 1 (1.4) | 12 (5.6) |
| Nervousness | 3 (1.4) | 0 | 5 (2.3) |
| Abnormal dreams | 1 (0.5) | 2 (2.8) | 2 (0.9) |
| Neuralgia | 0 | 2 (2.8) | 0 |
| SKIN AND APPENDAGES | |||
| Pruritus | 3 (1.4) | 3 (4.2) | 3 (1.4) |
| Rash | 5 (2.4) | 0 | 5 (2.3) |
| SPECIAL SENSES | |||
| Unpleasant taste | 1 (0.5) | 6 (8.3) | 26 (12.1) |
| UROGENITAL SYSTEM | |||
| Urinary tact | 1 (0.5) | 2 (2.8) | 0 |
1: And more frequent in at least one active treatment group than the placebo group.
TEAE=treatment emergent adverse event; ESZ=eszopiclone COSTART Coding, ITT Population
The overall incidence of treatment-emergent adverse events (TEAE) was similar in placebo- treated and eszopiclone 1 mg and 2 mg-treated subjects at 43.8%, 40.3%, and 46.5%, respectively. Although not considered potentially related by the investigators, accidental injury was more prevalent among 2 mg eszopiclone-treated subjects than placebo-treated subjects (1.0% and 2.8%).
Treatment Emergent Adverse Events in a Placebo-Controlled Clinical Trial with 6 weeks Dosing in Non-Elderly Adults
The most frequently reported adverse events are summarized in Table 3.
Table 3. All Treatment Emergent Adverse Events with an Incidence >2%in Either Active Group1 in a 6 Week Study in Non-Elderly Adults
BODY SYSTEM | All TEAEs | ||
|---|---|---|---|
Preferred Term Subject n (%) | Placebo (N=99) | ESZ 2 mg (N=104) | ESZ 3 mg (N=105) |
| OVERALL | 51 (51.5) | 69 (66.3) | 74 (70.5) |
| BODY AS A WHOLE | |||
Accidental injury | 5 (5.1) | 3 (2.9) | 7 (6.7) |
| Headache | 12 (12.1) | 20 (19.2) | 17 (16.2) |
| Infection | 3 (3.0) | 5 (4.8) | 11 (10.5) |
| Viral infection | 1 (1.0) | 3 (2.9) | 3 (2.9) |
| DIGESTIVE | |||
| Dry mouth | 3 (3.0) | 5 (4.8) | 6 (5.7) |
| Dyspepsia | 4 (4.0) | 4 (3.8) | 5 (4.8) |
| Nausea | 4 (4.0) | 5 (4.8) | 4 (3.8) |
| Vomiting | 1 (1.0) | 3 (2.9) | 0 |
| NERVOUS | |||
|---|---|---|---|
| Abnormal dreams | 2 (2.0) | 3 (2.9) | 2 (1.9) |
| Anxiety | 0 | 3 (2.9) | 1 (1.0) |
| Depression | 0 | 4 (3.8) | 1 (1.0) |
| Dizziness | 4 (4.0) | 5 (4.8) | 6 (5.7) |
| Hallucinations | 0 | 1 (1.0) | 3 (2.9) |
| Libido decreased | 0 | 0 | 3 (2.9) |
| Nervousness | 2 (2.0) | 5 (4.8) | 0 |
| Somnolence | 3 (3.0) | 9 (8.7) | 8 (7.6) |
| SKIN & APPENDAGES | |||
| Rash | 1 (1.0) | 3 (2.9) | 4 (3.8) |
| SPECIAL SENSES | |||
| Unpleasant taste | 3 (3.0) | 17 (16.3) | 36 (34.3) |
1: And more frequent in at least one active treatment group than the placebo group.
TEAE=treatment emergent adverse event; ESZ=eszopiclone COSTART Coding, ITT Population
Treatment Emergent Adverse Events in Placebo-Controlled Clinical Trials with Dosing up to 6-months in Non-Elderly Adults
The types of adverse events reported were similar to those observed during the 6 -week trial in the same population. Additional adverse events reported more frequently with eszopiclone compared to placebo included nausea (7.4% vs 5.2%) and pharyngitis (8.1% vs 4.4%).
Treatment-Emergent Adverse Events in Patients with Medical Co-morbidities
In 2 clinical studies of 8 weeks duration where eszopiclone was administered in combination with a selective serotonin reuptake inhibitor (SSRI) in non-elderly adults with Major Depressive Disorder or General Anxiety Disorder, incidences of adverse events were usually similar between the placebo and the eszopiclone groups. Adverse events that were reported more frequently in the eszopiclone group compared to the placebo group included asthenia (7.5% vs 5.1%), dry mouth (12.6% vs 9.2%), somnolence (11.5% vs 8.7%), dizziness (7.5% vs 4.0%), pharyngitis (5.9% vs 3.7%) and unpleasant taste (23.4% vs 2.3%) respectively.
In a 4-week study including non-elderly adults with insomnia and rheumatoid arthritis (RA) reported adverse events were generally similar to those reported in the 4 -6-week studies in non- elderly adults, with the following exceptions. In this study, asthenia (6.5% and 1.3%), pharyngitis (5.2% and 0%), and RA (18.2% and 9.2%, captured as adverse events in this trial) were more prevalent among 3 mg eszopiclone-treated subjects compared with placebo-treated subjects, respectively. Treatment with eszopiclone 3 mg did not result in any worsening of the underlying RA in these subjects.
8.3 Less Common Clinical Trial Adverse Drug Reactions
Reactions are further categorized by body system and listed in order of decreasing frequency according to the following definitions: frequent adverse reactions are those that occurred on one or more occasions in at least 1/100 patients; infrequent adverse reactions are those that occurred in fewer than 1/100 patients but in at least 1/1,000 patients; rare adverse reactions are those that occurred in fewer than 1/1,000 patients. Gender-specific reactions are categorized based on their incidence for the appropriate gender.
Body as a Whole: Frequent: chest pain; Infrequent: allergic reaction, cellulitis, face edema, fever, halitosis, heat stroke, hernia, malaise, neck rigidity, photosensitivity.
Cardiovascular System: Frequent: migraine; Infrequent: hypertension; Rare: thrombophlebitis.
Digestive System: Infrequent: anorexia, cholelithiasis, increased appetite, melena, mouth ulceration, thirst, ulcerative stomatitis; Rare: colitis, dysphagia, gastritis, hepatitis, hepatomegaly, liver damage, stomach ulcer, stomatitis, tongue edema, rectal hemorrhage.
Hemic and Lymphatic System: Infrequent: anemia, lymphadenopathy.
Metabolic and Nutritional: Frequent: peripheral edema; Infrequent: hypercholesterolemia, weight gain, weight loss; Rare: dehydration, gout, hyperlipemia, hypokalemia.
Musculoskeletal System: Infrequent: arthritis, bursitis, joint disorder (mainly swelling, stiffness, and pain), leg cramps, myasthenia, twitching; Rare: arthrosis, myopathy.
Nervous System: Infrequent: agitation, apathy, ataxia, emotional lability, hostility, hypertonia, hypesthesia, incoordination, insomnia, memory impairment, neurosis, nystagmus, paresthesia, reflexes decreased, thinking abnormal (mainly difficulty concentrating), vertigo; Rare: abnormal gait, euphoria, hyperesthesia, hypokinesia, neuritis, neuropathy, stupor, tremor.
Respiratory System: Infrequent: asthma, bronchitis, dyspnea, epistaxis, hiccup, laryngitis.
Skin and Appendages: Infrequent: acne, alopecia, contact dermatitis, dry skin, eczema, skin discoloration, sweating, urticaria; Rare: erythema multiforme, furunculosis, herpes zoster, hirsutism, maculopapular rash, vesiculobullous rash. Special Senses: Infrequent: conjunctivitis, dry eyes, ear pain, otitis externa, otitis media, tinnitus, vestibular disorder; Rare: hyperacusis, iritis, mydriasis, photophobia, ptosis.
Urogenital System: Infrequent: amenorrhea, breast engorgement, breast enlargement, breast neoplasm, breast pain, cystitis, dysuria, female lactation, hematuria, kidney calculus, kidney pain, mastitis, menorrhagia, metrorrhagia, urinary frequency, urinary incontinence, uterine hemorrhage, vaginal hemorrhage, vaginitis; Rare: oliguria, pyelonephritis, urethritis.
Studies Pertinent to Safety Concerns for Sedative/Hypnotic Drugs
Next-Day Residual Effects
In a double-blind study of 91 healthy adults age 25- to 40- years, the effects of Eszopiclone tablets 3 mg on psychomotor function were assessed between 7.5 and 11.5 hours the morning after dosing. Measures included tests of psychomotor coordination that are correlated with ability to maintain a motor vehicle in the driving lane, tests of working memory, and subjective perception of sedation and coordination. Compared with placebo, Eszopiclone tablets 3 mg was associated with next- morning psychomotor and memory impairment that was most severe at 7.5 hours, but still present and potentially clinically meaningful at 11.5 hours. Subjective perception of sedation and coordination from Eszopiclone tablets 3 mg was not consistently different from placebo, even though subjects were objectively impaired.
In a 6-week adult study of nightly administered Eszopiclone tablets, confusion was reported by 3% of patients treated with Eszopiclone tablets 3 mg compared to 0% of subjects treated with placebo. In the same study, memory impairment was reported by 1% of patients treated with either 2 mg or 3 mg Eszopiclone tablets, compared to 0% treated with placebo.
In a 6-month double-blind, placebo-controlled trial of nightly administered Eszopiclone tablets 3 mg, memory impairment was reported by 1.3% (8/593) of subjects treated with Eszopiclone tablets 3 mg compared to 0% (0/195) of subjects treated with placebo.
In a 2-week study of 264 elderly insomniacs, 1.5% of patients treated with MAR-ESZOPICLONE 2 mg reported memory impairment compared to 0% treated with placebo. In another 2 -week study of 231 elderly insomniacs, 2.5% of patients treated with MAR-ESZOPICLONE 2 mg reported confusion compared to 0% treated with placebo.
Withdrawal Events
In a 6-month double-blind, placebo-controlled study of nightly administration of Eszopiclone tablets 3 mg, rates of anxiety reported as an adverse event were 2.1% in the placebo arm and 3.7% in the Eszopiclone tablets arm. In a 6-week adult study of nightly administration, anxiety was reported as an adverse event in 0%, 2.9%, and 1.0% of the placebo, 2 mg, and 3 mg treatment arms, respectively. In this study, single-blind placebo was administered on nights 45 and 46, the first and second days of withdrawal from study drug. New adverse events were recorded during the withdrawal period, beginning with day 45, up to 14 days after discontinuation. During this withdrawal period, 105 subjects previously taking nightly Eszopiclone tablets 3 mg for 44 nights spontaneously reported anxiety (1%), abnormal dreams (1.9%), hyperesthesia (1%), and neurosis (1%), while none of 99 subjects previously taking placebo reported any of these adverse events during the withdrawal period.
Rebound Insomnia
Rebound insomnia, defined as a dose-dependent temporary worsening in sleep parameters compared with baseline following discontinuation of treatment, is observed with short- and intermediate-acting hypnotics. Rebound insomnia with Eszopiclone tablets was assessed objectively in a 6-week adult study on the first 2 nights of discontinuation (nights 45 and 46) following 44 nights of active treatment with 2 mg or 3 mg. In the Eszopiclone tablets 2 mg group, compared with baseline, there was a significant increase in WASO and a decrease in sleep efficiency, both occurring only on the first night after discontinuation of treatment. No changes from baseline were noted in the Eszopiclone tablets 3 mg group on the first night. Comparisons of changes from baseline between Eszopiclone tablets and placebo were also performed. On the first night after discontinuation of Eszopiclone tablets 2 mg, LPS and WASO were significantly increased and sleep efficiency was reduced; there were no significant differences on the second night. On the first night following discontinuation of Eszopiclone tablets 3 mg, sleep efficiency was significantly reduced. No other differences from placebo were noted in any other sleep parameter on either the first or second night following discontinuation. For both doses, the discontinuation-emergent effect was mild, had the characteristics of the return of the symptoms of chronic insomnia, and appeared to resolve by the second night after Eszopiclone tablets discontinuation.
8.5 Post-Market Adverse Drug Reactions
In addition to the adverse reactions observed during clinical trials, dysosmia, an olfactory dysfunction that is characterized by distortion of the sense of smell, has been reported during post-marketing surveillance with Eszopiclone tablets. Because this event is reported spontaneously from a population of unknown size, it is not possible to estimate the frequency of this event.
Injury, Poisoning and Procedural Complications: There have been reports of falls and fractures in users of benzodiazepines or other sedative-hypnotic drugs, such as Eszopiclone tablets, due to adverse reactions such as sedation, dizziness and ataxia. The risk is increased in those taking concomitant sedatives (including alcoholic beverages), geriatric and debilitated patients.
Dependence/Withdrawal: Development of physical dependence and withdrawal following discontinuation of therapy has been observed with benzodiazepines or other sedative -hypnotic drugs, such as Eszopiclone tablets . Severe and life-threatening symptoms have been reported. (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Addiction, Abuse and Misuse 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance).
9. DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions Concomitant use of Mar-Eszopiclone and opioids may result in profound sedation, respiratory depression, coma and death.
|
|---|
9.2 Drug Interactions Overview
Because eszopiclone is metabolized by CYP3A4 and CYP2E1 via demethylation and oxidation, there is a potential for interaction with other drugs metabolized by these enzymes. The exposure of eszopiclone was increased by co-administration of ketoconazole, a potent inhibitor of CYP3A4 (see also Table 4). Other potent inhibitors of CYP3A4 would be expected to behave similarly.
Concomitant use with alcohol and other CNS-depressants may enhance the sedative effects of eszopiclone.
9.3 Drug-Behavioural Interactions Alcohol
Concomitant intake with alcohol is not recommended (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, COMPLEX SLEEP-RELATED BEHAVIOURS). MAR-ESZOPICLONE may produce additive CNS depressant effects when co-administered with alcohol.
9.4 Drug-Drug Interactions CNS Depressants
MAR-ESZOPICLONE may produce additive CNS depressant effects when co-administered with sedative antihistamines, anticonvulsants, narcotic analgesics, anesthetics, or psychotropic medications such as antipsychotics (neuroleptics), hypnotics, anxiolytics/sedatives, and antidepressant agents which themselves can produce CNS depression. In the case of narcotic analgesics, enhancement of euphoria may also occur, leading to an increase in psychological dependence.
Opioids
Due to additive CNS depressant effect, the concomitant use of benzodiazepines or other CNS depressants, including MAR-ESZOPICLONE, and opioids increases the risk of profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations of concomitant use of benzodiazepines and opioids to the minimum required. Follow patients closely for respiratory depression and sedation (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, RISKS FROM CONCOMITANT USE WITH OPIOIDS, and 7 WARNINGS AND PRECAUTIONS, Concomitant Use with Opioids).
Table 4. Established or Potential Drug-Drug Interactions
| Drug name | Ref | Effect | Clinical comment |
|---|---|---|---|
| Ethanol | CT | An additive effect on psychomotor performance was seen with co- administration of eszopiclone and ethanol 0.70 g/kg for up to 4 hr after ethanol administration. | Caution is warranted when eszopiclone tablets is administered with ethanol. See 4 DOSAGE AND ADMNISTRATION, Special Populations, Use with CNS Depressants. |
| Paroxetine | CT | Co-administration of single doses of eszopiclone 3 mg and paroxetine 20 mg daily for 7 days produced no pharmacokinetic or pharmacodynamic interaction. | No dosage adjustment is necessary when eszopiclone tablets is administered with paroxetine. |
| Lorazepam | CT | Coadministration of single doses of eszopiclone and lorazepam did not have clinically relevant effects on the pharmacodynamics or pharmacokinetics of either drug. | No dosage adjustment is necessary when eszopiclone tablets is administered with lorazepam. See also 4 DOSAGE AND ADMINISTRATION, Special Populations, Use with CNS Depressants. |
| Olanzapine | CT | Co-administration of eszopiclone 3 mg and olanzapine 10 mg produced a decrease in DSST scores. The interaction was pharmacodynamic; there were no alterations in the pharmacokinetics of either drug. | A reduction in dose is necessary when eszopiclone is administered with agents having known CNS-depressant effects. |
| Ketoconazole | CT | The AUC of eszopiclone was increased 2.2-fold by co- administration with ketoconazole 400 mg daily for 5 days. Cmax and t½ was increased 1.4-fold and 1.3- fold, respectively. See 10.3 Pharmacokinetics. | A reduction in dose may be warranted in patients taking eszopiclone tablets with ketoconazole and other potent CYP3A4 inhibitors. The dose should not exceed 2 mg. |
| Rifampin | CT | Racemic zopiclone exposure was decreased by 80% by concomitant use of rifampin. | A similar effect would be expected with eszopiclone. |
| Digoxin | CT | A single dose of eszopiclone 3 mg did not affect the pharmacokinetics of digoxin measured at steady state following dosing of 0.5 mg twice daily for one day and 0.25 mg daily for the next 6 days. | No dosage adjustment is necessary when eszopiclone tablets is administered with digoxin. |
|---|---|---|---|
| Warfarin | CT | Eszopiclone 3 mg administered daily for 5 days did not affect the pharmacokinetics of (R)- or (S)-warfarin, nor were there any changes in the pharmacodynamic profile following a single 25 mg oral dose of warfarin. | No dosage adjustment is warranted when eszopiclone tablets is administered with warfarin. |
Legend: CT = Clinical Trial
In patients with mood disorders, co-administration of eszopiclone with fluoxetine or escitalopram did not adversely affect the pharmacodynamic effects of eszopiclone or the antidepressant agents.
9.5 Drug-Food Interactions
Co-administration of MAR-ESZOPICLONE with or immediately after a high-fat meal results in slower absorption. Therefore, the effects of MAR-ESZOPICLONE on sleep onset may be slightly reduced if it is taken with or immediately after a high-fat or heavy meal (see 10 CLINICAL PHARMACOLOGY).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
10. CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
MAR-ESZOPICLONE is a non-benzodiazepine hypnotic agent, which is a pyrrolopyrazine derivative of the cyclopyrrolone class with a chemical structure unrelated to pyrazolopyrimidines, imidazopyridines, benzodiazepines or barbiturates. The effects of eszopiclone are due to modulation of gamma-aminobutyric acid (GABA)-A-receptor macromolecular complexes, containing alpha-1, alpha-2, alpha-3 and alpha-5 sub-units. GABA-evoked chloride conductance is increased resulting in neuronal hyperpolarisation and thereby inhibiting neuronal transmission and causing sleep. As compared to racemic zopiclone whose effects are mediated predominantly through α1, the effects of eszopiclone are mediated predominantly through the alpha-2 and alpha-3 GABAA.
10.2 Pharmacodynamics
Transient Insomnia: In a single night model of transient insomnia in healthy adult volunteers, a 3 mg dose of Eszopiclone tablets was superior to placebo on measures of sleep onset and sleep maintenance using objective polysomnography. In addition, self -reported scores for sleep quality and sleep depth were significantly better for Eszopiclone tablets compared to placebo and there were statistically significant treatment differences for several sleep architecture parameters.
Abuse Liability: In a study of abuse liability conducted in individuals with known histories of benzodiazepine abuse, eszopiclone at doses of 6 and 12 mg produced euphoric effects similar to those of diazepam 20 mg. In this study, at doses 2-fold or greater than the maximum recommended doses, a dose-related increase in reports of amnesia and hallucinations was observed for both Eszopiclone tablets and diazepam.
Tolerance: In clinical studies with Eszopiclone tablets, no development of tolerance to any median parameter of sleep measurements was observed during treatment periods of up to 12 months. Development of tolerance in some patients cannot be excluded.
10.3 Pharmacokinetics
Table 5. Steady-State Pharmacokinetic Parameters of Eszopiclone in Healthy Volunteers
| Cmax (ng/ml) | t½ (h) | AUC0- | Tmax (h) | |
|---|---|---|---|---|
| Eszopiclone | ||||
| 3 mg | 26.18 ± 6.56 | 7.03 ± 4.00 | 191.07 ± 60.88 | 1.13 ± 0.48 |
Absorption: Eszopiclone is rapidly absorbed, with a time to peak concentration (tmax) of approximately 1 hour and a terminal-phase elimination half-life (t½) of approximately 7 hours.
In healthy adults, Eszopiclone tablets does not accumulate with once-daily administration, and its exposure is dose-proportional over the range of 1 to 6 mg.
In healthy adults, administration of eszopiclone after a high fat meal resulted in no change in AUC, a reduction in mean Cmax of 21%, and delayed tmax by approximately 1 hour. The half-life remained unchanged. The effects of Eszopiclone tablets on sleep onset may be slightly reduced if it is taken with or immediately after a high-fat or heavy meal.
Eszopiclone was rapidly absorbed following oral administration, with tmax occurring at 1 hour post- dose in healthy subjects.
The plasma concentration profile of eszopiclone was characterized by a bi-exponential decline with an apparent terminal phase t½ of approximately 7 hours. Eszopiclone exhibited dose- proportional pharmacokinetics over the range of 1 to 6 mg once daily. No accumulation of eszopiclone was observed following 7 days of once daily drug administration.
The steady-state pharmacokinetic profile of eszopiclone following multiple daily administration of 3 mg eszopiclone in healthy elderly subjects demonstrated an increased AUC and exposure in the elderly by 41% and 56%, respectively, compared to non-elderly subjects. The t½ was approximately 2.5 hours longer in the elderly. A decrease in eszopiclone dose to 2 mg is recommended in the elderly.
The effect of a high fat meal on the pharmacokinetics of single doses of eszopiclone was examined and no effect on the AUC was found. There was a decrease in peak plasma concentration of eszopiclone with food (21-39% decrease in Cmax). The rate of absorption of eszopiclone (tmax) was prolonged by 1.0 – 1.5 hours in the presence of food.
The pharmacokinetics of a 2 mg dose were assessed in subjects with mild, moderate, and severe liver disease and compared to healthy volunteers. Eszopiclone Cmax decreased by 13%, 29%, and 25% in subjects with mild, moderate, and severe hepatic impairment, respectively. AUC(0-last) was unchanged in subjects with mild or moderate hepatic impairment; however, systemic exposure was increased by 74% in subjects with severe hepatic impairment. No dose adjustment is required in patients with mild or moderate hepatic impairment. The dose should not exceed 2 mg in non-elderly patients with severe hepatic impairment.
During multiple daily dose co-administration of 3 mg eszopiclone and 400 mg ketoconazole, eszopiclone AUC(0-τ) was increased by 125%, Cmax by 43% and t½ by 2.2 hours. The rate of absorption was unchanged, suggesting that the increased exposure resulted from CYP3A4 inhibition rather than from an interaction at the absorption level. A decrease in eszopiclone dose to 2 mg is recommended upon co-administration with ketoconazole or compounds which similarly inhibit CYP3A4.
Distribution: Eszopiclone is weakly bound to plasma protein (52-59%). Therefore, eszopiclone disposition is unlikely to be affected by drug-drug interactions caused by protein binding. The blood-to-plasma ratio for eszopiclone is less than one, indicating no selective uptake by red blood cells.
In vitro protein binding of eszopiclone in human plasma was 52 -59% over the concentration range of 5-500 ng/mL of [14C]-eszopiclone. Non-specific binding of eszopiclone was less than 5% at concentrations of 1000 ng/mL or below. The relatively low plasma protein binding suggest that reduction in albumin concentration typically observed in severe renal and liver diseases would be expected to result in a negligible change in unbound eszopiclone concentration.
Racemic zopiclone was widely distributed with an absolute volume of distribution of approximately 90 L. Eszopiclone would be expected to exhibit similar distributive properties. A relatively high free fraction (eszopiclone was 52-59% bound to plasma proteins in healthy subjects) was also consistent with a large volume of distribution.
Metabolism: Following oral administration, eszopiclone is extensively metabolized by oxidation and demethylation. The primary plasma metabolites are (S)-zopiclone-N-oxide and (S)-N- desmethyl zopiclone; the latter compound binds to GABA receptors with substantially lower potency than eszopiclone, and the former compound shows no significant binding to this receptor. In vitro studies have shown that CYP3A4 and CYP2E1 enzymes are involved in the metabolism of eszopiclone. Eszopiclone did not show any inhibitory potential on CYP450 1A2, 2A6, 2C9, 2C19, 2D6, 2E1, and 3A4 in cryopreserved human hepatocytes. In humans, co- administration with ketoconazole resulted in increased exposure to eszopiclone. Potent inducers of CYP3A4 would be expected to reduce systemic exposure to eszopiclone.
The ability of different CYP450 isoforms to metabolize eszopiclone was determined by incubating eszopiclone and human liver microsomes in the presence or absence of selective CYP450 isoform inhibitors. The rate of disappearance of eszopiclone, 10, 100 and 200 µM, was decreased by 63% to 74% in human liver microsomes preincubated with the CYP2E1 inhibitor 4-methylpyrazole. In the presence of ketoconazole, a standard inhibitor of CYP3A4, the rate of disappearance of eszopiclone declined by 44% to 72% as compared to control (over 30 minutes). No significant decline in the disappearance of eszopiclone was seen in human liver microsomes preincubated with other cytochrome isoform inhibitors. This indicated that the metabolism of eszopiclone was catalyzed by CYP3A4 and CYP2E1.
The potential of eszopiclone to inhibit human liver CYP450 isoforms was determined in cryopreserved human hepatocytes in the presence and absence of standard probe substrates. Eszopiclone did not cause inhibition of the metabolism of specific substrates of the CYP450 isoforms 1A2, 2A6, 2C8, 2C9, 2C19, 2D6, 2E1, and 3A4 in human hepatocytes at concentrations up to 100 µM. This demonstrated that eszopiclone was not a CYP450 inhibitor.
In vivo studies indicated that eszopiclone is metabolized by CYP3A4 and CYP2E1 into two primary metabolites, (S)-desmethylzopiclone and zopiclone N-oxide. These metabolites did not possess significant sleep-inducing activity in preclinical models.
Excretion: After oral administration, eszopiclone is eliminated with a mean t½ of approximately 7 hours. Up to 75% of an oral dose of racemic zopiclone is excreted in the urine, primarily as metabolites. A similar excretion profile would be expected for eszopiclone, the S-isomer of racemic zopiclone. Less than 10% of the orally administered eszopiclone dose is excreted in the urine as parent drug.
Pharmacokinetic studies demonstrated that renal excretion is the principal route of elimination of eszopiclone and its metabolites. Up to 75% of an oral dose of racemic zopiclone is excreted in the urine primarily as metabolites. A similar excretion profile would be expected for eszopiclone. Less than 10% of the dose was excreted in the urine as unchanged drug. The formation and disposition of the primary metabolites were consistent with a linear pharmacokinetic system.
Special Populations and Conditions
Geriatrics: Compared with non-elderly adults, subjects 65 years and older had an increase of 41% in exposure (AUC) and prolonged elimination of eszopiclone (t½ approximately 9 hours). Cmax was unchanged. Therefore, in elderly patients the dose of MAR-ESZOPICLONE must not exceed 2 mg.
Hepatic Insufficiency: Pharmacokinetics of a 2 mg dose were assessed in 8 subjects with mild, moderate, and severe liver disease and compared to 16 healthy volunteers. Exposure was increased 2-fold and elimination of eszopiclone prolonged (t½ approximately 15 hrs) in severely impaired patients compared with healthy volunteers. Cmax and tmax were unchanged. No dose adjustment is necessary for patients with mild-to-moderate hepatic impairment. In non- elderly adults with severe hepatic impairment, the recommended dose is 2 mg. MAR-ESZOPICLONE is contraindicated in elderly patients with severe hepatic impairment.
Renal Insufficiency: The pharmacokinetics of eszopiclone were studied in 24 subjects with mild, moderate or severe renal impairment. Compared with healthy subjects, subjects with severe renal impairment had an increase in exposure (AUC) of 47%. The dose of MAR-ESZOPICLONE in patients with severe renal impairment should not exceed 2 mg. No dose adjustment is necessary in patients with mild or moderate renal impairment.
- 11. STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15 to 30oC). Keep out of the reach and sight of children.
- 12. SPECIAL HANDLING INSTRUCTIONS
None.
PART II: SCIENTIFIC INFORMATION
- 13. PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Eszopiclone
Chemical name: (+)-(5S)-6-(5-chloropyridin-2-yl)-7-oxo-6,7-dihydro-5H-pyrrolo[3,4-b] pyrazin-5-yl 4-methylpiperazine-1-carboxylate
Molecular formula and molecular mass: C17H17ClN6O3
388.81
Structural formula:
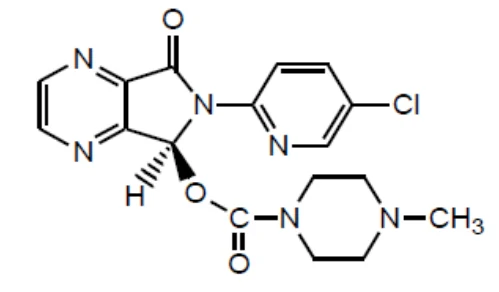
Physicochemical properties: Eszopiclone is a white to light-yellow crystalline solid.
Freely soluble in methylene chloride; soluble in dilute mineral acids; slightly soluble in alcohol; very slightly soluble in water.
Eszopiclone has a single chiral centre with an (S)- configuration.
14. CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The effect of eszopiclone tablets on sleep latency and sleep maintenance was studied in four clinical trials involving 1441 patients of which 827 received eszopiclone 1, 2, or 3 mg. Two of these trials were in elderly patients (n=523), one was a 6-week trial in non-elderly adults (n=308), and one was a 6-month trial (n=828).
All studies were randomized, double-blind, and placebo-controlled. The primary efficacy measures of the studies were:
- objective (polysomnographic) latency to persistent sleep (LPS) in 3 studies ;
- objective LPS and objective sleep efficiency (as co-primary endpoints) in one study;
- subjective sleep latency (measured with an interactive phone system) in 2 studies.
Secondary measures of efficacy included quality of sleep, sleep architecture, Insomnia Severity Index (ISI) total scores, Epworth Sleep Scale (ESS) scores, and quality of life measures.
14.2 Study Results
Overall, at the usual effective adult dose (2-3 mg) and elderly dose (1-2 mg), eszopiclone tablets significantly decreased sleep latency and improved measures of sleep maintenance [objectively measured as wake time after sleep onset (WASO) and subjectively measured as total sleep time (TST)]. In non-elderly adults, a 1 mg dose demonstrated inconsistent efficacy in improving sleep onset or wakefulness and did not improve total sleep time in any study.
Adults
In the first study, adults with insomnia (n=308) were evaluated in a double-blind, parallel-group trial of 6 weeks’ duration comparing eszopiclone tablets 2 mg and 3 mg with placebo. Objective (polysomnographic) endpoints were measured for 4 weeks. For the primary endpoint, LPS, both 2 mg and 3 mg were superior to placebo at 4 weeks. The 3 mg dose was superior to placebo on WASO.
In a long term 6 month, double-blind, placebo controlled study, eszopiclone 3 mg was superior to placebo in reduction in subjective sleep latency for the month 4-6 average (pairwise test, p<0.0001). Subjective sleep latency for the month 1-3 average, total sleep time and WASO were also improved when eszopiclone 3 mg was compared to placebo.
Elderly
Elderly subjects (ages 65-86) with insomnia were evaluated in two double-blind, parallel-group trials of 2 weeks duration. One study (n=231) compared the effects of 1 and 2 mg of eszopiclone tablets with placebo on subjective outcome measures, and the other (n=292) compared the effects of 2 mg with placebo on objective and subjective outcome measures. All doses were superior to placebo on measures of sleep latency. In both studies, sleep maintenance was improved with 2 mg of eszopiclone tablets compared to placebo.
14.3 Comparative Bioavailability Studies
A double blind, randomized, two treatment, two sequence, two period, cross-over, oral bioequivalence study of MAR-ESZOPICLONE and PrLUNESTA® (eszopiclone) tablets 3 mg was conducted in 27 healthy, adult, male subjects. The test and reference products were administered as single oral doses of 1 x 3 mg of eszopiclone under fasting conditions. The results are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Eszopiclone (1 x 3 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 334.85 339.98 (18.31) | 319.47 322.28 (14.08) | 104.8 | 99.9 – 109.9 |
AUCI (ng·h/mL) | 374.93 381.98 (20.46) | 362.29 367.84 (18.95) | 103.5 | 98.3 – 109.0 |
Cmax (ng/mL) | 49.37 51.15 (28.71) | 42.70 43.67 (22.26) | 115.6 | 105.2 – 127.0 |
Tmax3 (h) | 0.67 (0.33 – 3.00) | 1.00 (0.50 – 4.00) | ||
T½4 (h) | 7.49 (20.62) | 7.83 (23.36) | ||
1 MAR-ESZOPICLONE (eszopiclone) tablets 3 mg (Marcan Pharmaceuticals Inc.)
2 LUNESTA® (eszopiclone) tablets 3 mg (Sunovion Pharmaceuticals Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only.
15. MICROBIOLOGY
No microbiological information is required for this drug product.
16. NON-CLINICAL TOXICOLOGY
Single-Dose Toxicity Studies:
Acute toxicity testing demonstrated that eszopiclone possesses a low order of acute toxicity. Signs of toxicity included those effects expected for hypnotic agents and were comparable across test articles at the toxic doses evaluated. The safety margin for an acute oral dose is high relative to the maximum clinical daily dose of eszopiclone.
Results from acute toxicity studies are presented in Table 6.
Table 6. Results of Single-Dose Toxicity Studies
Species/ Strains | Route | Dose Levels (mg/kg) | Max. Non- Lethal Dose (mg/kg) | Noteworthy Findings |
|---|---|---|---|---|
Mouse/ CD-1 | Oral gavage | 900, 1200, 1500 | <900 |
oral administration in mice exceeds 900 mg/kg for eszopiclone
|
| Rats/ Sprague- Dawley | IV | 1, 10, 25, 75, 100, 250 | 1 M 75 F |
|
Repeat-Dose Toxicity Studies:
Subchronic studies in mice demonstrated that eszopiclone was well tolerated at oral doses up to 200 mg/kg/day for 3 months. Subchronic studies in rats demonstrated that eszopiclone was tolerated at doses up to 100 mg/kg/day for 28 days with lethalities observed at doses >200 mg/kg/day for 28 days. Subchronic studies in dogs demonstrated that eszopiclone was tolerated at doses of 2 mg/kg/day (males) and 20 mg/kg/day (females) for 28 days and doses of 2.5 mg/kg/day (males) or 10 mg/kg/day (females) for 3 months.
Treatment-related findings were consistent with exaggerations of the known pharmacologic effects of eszopiclone and were demonstrated to be fully reversible.
Table 7. Results of Repeat-Dose Toxicity Studies
Species/ Strains | Study Duration | Dose Range (mg/kg/day) | Noteworthy Findings |
|---|---|---|---|
Mouse/ CD-1 | 1 & 3 mths | 50 to 400 NOAEL: 200 mg/kg/day |
unsteady gait, labored breathing, hunched posture, etc.), decreased food consumption and body weight.
|
Species/ Strains | Study Duration | Dose Range (mg/kg/day) | Noteworthy Findings |
|---|---|---|---|
Rats/ Sprague- Dawley | 1, 3 & 18a mths | 20 to 300 NOAEL: M <25 mg/kg/day F 100 mg/kg/day |
demonstrated to be fully reversible: decreased body weight.
humans. |
Dogs/ Beagle | 1, 3 & 12a mths | 2 to 25 NOAEL: M 2.5 mg/kg/day F 10 mg/kg/day |
demonstrated to be fully reversible, decreased body weight
|
a Data from racemic (RS) zopiclone (not shown)
Genotoxicity:
Eszopiclone was positive in the mouse lymphoma chromosomal aberration assay and produced an equivocal response in the Chinese hamster ovary cell chromosomal aberration assay. It was not mutagenic or clastogenic in the bacterial Ames gene mutation assay, in an unscheduled DNA synthesis assay, or in an in vivo mouse bone marrow micronucleus assay.
(S)-N-desmethyl zopiclone, a metabolite of eszopiclone, was positive in the Chinese hamster ovary cell and human lymphocyte chromosomal aberration assays. It was negative in the bacterial Ames mutation assay, in an in vitro 32P-postlabeling DNA adduct assay, and in an in vivo mouse bone marrow chromosomal aberration and micronucleus assay.
Carcinogenicity:
In a carcinogenicity study in Sprague-Dawley rats in which eszopiclone was given by oral gavage, no increases in tumours were seen; plasma levels (AUC) of eszopiclone at the highest dose used in this study (16 mg/kg/day) are estimated to be 80 (females) and 20 (males) times those in humans receiving the maximum recommended human dose (MRHD). However, in a carcinogenicity study in Sprague-Dawley rats in which racemic zopiclone was given in the diet, and in which plasma levels of eszopiclone were reached that were greater than those reached in the above study of eszopiclone, an increase in mammary gland adenocarcinomas in females and an increase in thyroid gland follicular cell adenomas and carcinomas in males were seen at the highest dose of 100 mg/kg/day. Plasma levels of eszopiclone at this dose are estimated to be 150 (females) and 70 (males) times those in humans receiving the MRHD. The mechanism for the increase in mammary adenocarcinomas is unknown. The increase in thyroid tumours is thought to be due to increased levels of TSH secondary to increased metabolism of circulating thyroid hormones, a mechanism that is not considered to be relevant to humans.
In a carcinogenicity study in B6C3F1 mice in which racemic zopiclone was given in the diet, an increase in pulmonary carcinomas and carcinomas plus adenomas in females and an increase in skin fibromas and sarcomas in males were seen at the highest dose of 100 mg/kg/day.
Plasma levels of eszopiclone at this dose are estimated to be 8 (females) and 20 (males) times those in humans receiving the MRHD. The skin tumours were due to skin lesions induced by aggressive behaviour, a mechanism that is not relevant to humans. A carcinogenicity study was also performed in which CD-1 mice were given eszopiclone at doses up to 100 mg/kg/day by oral gavage; although this study did not reach a maximum tolerated dose, and was thus inadequate for overall assessment of carcinogenic potential, no increases in either pulmonary or skin tumours were seen at doses producing plasma levels of eszopiclone estimated to be 90 times those in humans receiving the MRHD — i.e., 12 times the exposure in the racemate study.
Eszopiclone did not increase tumours in a p53 transgenic mouse bioassay at oral doses up to 300 mg/kg/day.
Reproduction and Development Toxicity:
Eszopiclone was given by oral gavage to male rats at doses up to 45 mg/kg/day from 4 weeks premating through mating and to female rats at doses up to 180 mg/kg/day from 2 weeks premating through day 7 of pregnancy. An additional study was performed in which only females were treated, up to 180 mg/kg/day. Eszopiclone decreased fertility with no females becoming pregnant when both males and females were treated with the highest dose; the no - effect dose in both sexes was 5 mg/kg (16 times the MRHD on a mg/m2 basis). Other effects included increased pre-implantation loss (no-effect dose 25 mg/kg), abnormal estrus cycles (no- effect dose 25 mg/kg), and decreases in sperm number and motility and increases in morphologically abnormal sperm (no-effect dose 5 mg/kg).
Oral administration of eszopiclone to pregnant rats (62.5, 125, or 250 mg/kg/day) and rabbits (4, 8, or 16 mg/kg/day) throughout organogenesis showed no evidence of teratogenicity up to the highest doses tested. In rats, reduced fetal weight and increased incidences of skeletal variations and/or delayed ossification were observed at the mid and high doses. The no- observed-effect dose for adverse effects on embryofetal development is 200 times the maximum recommended human dose (MRHD) of 3 mg/day on a mg/m2 basis. No effects on embryofetal development were observed in rabbits; the highest dose tested is approximately 100 times the MRHD on a mg/m2 basis.
Oral administration of eszopiclone (60, 120, or 180 mg/kg/day) to pregnant rats throughout the pregnancy and lactation resulted in increased post-implantation loss, decreased postnatal pup weights and survival, and increased pup startle response at all doses. The lowest dose tested is approximately 200 times the MRHD on a mg/m2 basis. Eszopiclone had no effects on other developmental measures or reproductive function in the offspring.
Eszopiclone administered by oral gavage to pregnant rats and rabbits during the period of organogenesis showed no evidence of teratogenicity up to the highest doses tested (250 and 16 mg/kg/day in rats and rabbits, respectively; these doses are 800 and 100 times, respectively, the MHRD on a mg/m2 basis). In the rat, slight reductions in fetal weight and evidence of developmental delay were seen at maternally toxic doses of 125 and 150 mg/kg/day, but not at 62.5 mg/kg/day (200 times the MRHD on a mg/m2 basis).
Eszopiclone was also administered by oral gavage to pregnant rats throughout the pregnancy and lactation periods at doses of up to 180 mg/kg/day. Increased post -implantation loss, decreased postnatal pup weights and survival, and increased pup startle response were seen at all doses; the lowest dose tested, 60 mg/kg/day, is 200 times the MRHD on a mg/m2 basis.
These doses did not produce significant maternal toxicity. Eszopiclone had no effects on other behavioural measures or reproductive function in the offspring.
Juvenile Toxicity:
In studies in which eszopiclone (2 to 300 mg/kg/day) was orally administered to young rats from weaning through sexual maturity, neurobehavioural impairment (altered auditory startle response) and reproductive toxicity (adverse effects on male reproductive organ weights and histopathology) were observed at doses ≥ 5 mg/kg/day. Delayed sexual maturation was noted in males and females at ≥10 mg/kg/day. The no-effect dose (2 mg/kg) was associated with plasma exposures (AUC) for eszopiclone and metabolite (S)-desmethylzopiclone [(S)-DMZ] approximately 2 times plasma exposures in humans at the maximum recommended dose (MRHD) in adults (3 mg/day).
When eszopiclone (doses from 1 to 50 mg/kg/day) was orally administered to young dogs from weaning through sexual maturity, neurotoxicity (convulsions) was observed at doses ≥ 5 mg/kg/day. Hepatotoxicity (elevated liver enzymes and hepatocellular vacuolation and degeneration) and reproductive toxicity (adverse effects on male reproductive organ weights and histopathology) were noted at dose ≥10 mg/kg/day. The no-effect dose (1 mg/kg) was associated with plasma exposures (AUC) to eszopiclone and (S)-DMZ approximately 3 and 2 times, respectively, plasma exposures in humans at the MRHD in adults.
17. SUPPORTING PRODUCT MONOGRAPHS
- 1. Pr LUNESTA® Eszopiclone Tablets 1 mg, 2 mg and 3 mg, Submission Control: 284580, Product Monograph, Sumitomo Pharma Canada Inc. APR 18, 2024