


Product Monograph - Mar-Methimazole
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions | 01/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
- 1.1. Pediatrics ................................................................................................................ 4
- 1.2. Geriatrics ................................................................................................................ 4
- 2 CONTRAINDICATIONS ................................................................................................. 4
- 3 SERIOUS WARNINGS AND PRECAUTIONS BOX ................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 4
4.1 Dosing Considerations………………………………………………………………………………………….4
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
- 4.4 Administration ....................................................................................................... 5
- 4.5 Missed Dose ........................................................................................................... 5
- 5 OVERDOSAGE.............................................................................................................. 5
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
7 WARNINGS AND PRECAUTIONS ................................................................................... 6
- 7.1 Special Populations ................................................................................................ 9
- 7.1.1 Pregnant Women ............................................................................................. 9
- 7.1.2 Breast-feeding .................................................................................................. 9
- 7.1.3 Pediatrics .......................................................................................................... 9
- 7.1.4 Geriatrics .......................................................................................................... 9
8 ADVERSE REACTIONS ................................................................................................ 10
- 8.1 Adverse Reaction Overview .................................................................................. 10
- 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 10
- 8.5 Post-Market Adverse Reactions ........................................................................... 10
9 DRUG INTERACTIONS ................................................................................................ 10
9.2 Drug Interactions Overview .................................................................................. 10
- 9.4 Drug-Drug Interactions ......................................................................................... 10
- 9.5 Drug-Food Interactions ........................................................................................ 11
- 9.6 Drug-Herb Interactions ......................................................................................... 11
- 9.7 Drug-Laboratory Test Interactions ........................................................................ 11
10 CLINICAL PHARMACOLOGY ........................................................................................11
- 10.1 Mechanism of Action ...................................................................................... 11
- 10.2 Pharmacodynamics ........................................................................................ 11
- 10.3 Pharmacokinetics ........................................................................................... 12
- 11 STORAGE, STABILITY AND DISPOSAL .............................................................................. 12
- 12 SPECIAL HANDLING INSTRUCTIONS ............................................................................12
PART II: SCIENTIFIC INFORMATION ........................................................................................13
- 13 PHARMACEUTICAL INFORMATION .............................................................................13
14 CLINICAL TRIALS……………………………………………………………………………………………………… 14
14.3 Comparative Bioavailability Studies………………………………………………………..……14
- 15 MICROBIOLOGY .........................................................................................................15
- 16 NON-CLINICAL TOXICOLOGY .......................................................................................15
- 17 SUPPORTING PRODUCT MONOGRAPHS…………………………………………………………………..15
PATIENT MEDICATION INFORMATION ...................................................................................16
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
MAR-METHIMAZOLE is indicated in adults for:
- The medical treatment of hyperthyroidism. Long-term therapy may lead to remission of the disease.
- Amelioration of hyperthyroidism in preparation for subtotal thyroidectomy or radioactive iodine therapy.
- Use when thyroidectomy is contraindicated or not advisable.
1.1. Pediatrics
Pediatrics (<18 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥ 65 years): Clinical studies did not include sufficient numbers of subjects aged 65 years or older to determine the safety and efficacy of methimazole in this geriatric population (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
MAR-METHIMAZOLE is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition and Packaging.
- Breastfeeding women, as the drug is excreted in breast milk.
- Patients with history of acute pancreatitis after administration of methimazole.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- MAR-METHIMAZOLE treatment can cause hypothyroidism and adjustments in dosing are necessary to maintain a euthyroid state (see Endocrine and Metabolism, Hypothyroidism). Excess dosage should be avoided as it can lead to sub-clinical or clinical hypothyroidism and goitre growth (see Respiratory). Periodic monitoring of thyroid function should be performed with dosage adjustments
Serious Warnings and Precautions
- Agranulocytosis (see 7 Warnings and Precautions, Hematologic and 8 Adverse Reactions)
Liver toxicity (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic))
as necessary and with more careful monitoring in patients with large goitres (see Monitoring and Laboratory Tests).
- Concomitant administration of MAR-METHIMAZOLE and warfarin necessitates intensive and frequent monitoring, particularly when initiating, discontinuing, or changing doses of methimazole (see Hematologic, Anticoagulant Therapy and 9.4 Drug-Drug Interactions).
MAR-METHIMAZOLE can only be administered during pregnancy after a strict individual benefit/risk assessment and only at the lowest effective dose, without additional administration of thyroid hormones. Women of childbearing potential should use effective methods of contraception during MAR-METHIMAZOLE therapy (see 7.1.1 Pregnant Women).
4.2 Recommended Dose and Dosage Adjustment
Adult (≥18 years of age): The initial daily dose is 15 mg for mild hyperthyroidism, 30 to 40 mg for moderately severe hyperthyroidism and 60 mg for severe hyperthyroidism, divided into three doses at eight-hour intervals. The maintenance dosage is 5 to 15 mg daily.
Geriatric (≥65 years of age): Clinical studies of methimazole did not include sufficient numbers of subjects aged 65 or over to determine whether they respond differently from younger subjects.
In general, dose selection for an elderly patient should be cautious reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Pediatric (<18 years of age): Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
Hepatic impairment: The dose should be kept as low as possible and patients should be closely monitored as the plasma clearance of methimazole is reduced (see Monitoring and Laboratory Tests).
Renal impairment: The dose should be kept as low as possible and careful individual dose adjustment under close monitoring is recommended as there is a lack of data regarding the pharmacokinetic behaviour of methimazole in patients with renal impairment.
4.4 Administration
- MAR-METHIMAZOLE is administered orally.
- MAR-METHIMAZOLE is usually given in three equal doses per day at approximately eight-hour intervals.
- Patients should wash their hands with soap and water after handling the tablet, particularly if they have to break the tablet.
- Methimazole should not be handled by pregnant women and children.
4.5 Missed Dose
If a dose is missed, patients should contact their healthcare professional. Patients should not take a double dose to make up for a forgotten dose. Patients should take their next scheduled dose as usual.
5 OVERDOSAGE
Symptoms: Symptoms may include nausea, vomiting, epigastric distress, headache, fever, joint pain, pruritus and edema. Aplastic anemia (pancytopenia) or agranulocytosis may be manifested in hours to days. Less frequent events are hepatitis, nephrotic syndrome, exfoliative dermatitis, neuropathies and CNS stimulation or depression. Although not well studied, methimazole-induced agranulocytosis is generally associated with doses of 40 mg or more in patients older than 40 years of age.
Overdose may also lead to hypothyroidism with corresponding symptoms of a reduced metabolism and, through the feedback effect, to activation of the adenohypophysis with subsequent goitre growth. This can be avoided by dose reduction as soon as a euthyroid metabolic condition is achieved.
No information is available on the median lethal dose (LD50) of the drug or the concentration of methimazole in biologic fluids associated with toxicity and/or death.
Treatment: In managing overdosage, consider the possibility of multiple drug overdoses, interaction among drugs, and unusual drug kinetics in your patient.
The patient’s bone marrow function should be monitored.
In case of suspected overdose, patients should be closely monitored for signs or symptoms of adverse reactions and appropriate symptomatic treatment should be instituted as required.
Forced diuresis, peritoneal dialysis, hemodialysis or charcoal hemoperfusion have not been established as beneficial for an overdose of methimazole.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet 5 mg and 10 mg of methimazole | lactose monohydrate, magnesium stearate, starch and talc |
5 mg tablets: Round white to off white bi-convex tablet. Debossed HP bisect 70 on one side and plain on reverse side.
10 mg tablets: Round white to off white bi-convex tablet. Debossed HP bisect 71 on one side and plain on reverse side.
MAR-METHIMAZOLE tablets are supplied in bottles of 100.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Patients who receive methimazole should be under close surveillance. Physicians should encourage patients to immediately report any evidence of illness or unusual clinical symptoms, particularly sore
For management of a suspected drug overdose, contact your regional poison control centre.
throat, skin eruptions, fever, headache or general malaise. In such cases, white blood cell and differential counts should be made to determine whether agranulocytosis has developed. Particular care should be exercised with patients who are receiving additional drugs known to cause agranulocytosis.
The development of arthralgias should prompt drug discontinuation, since this symptom may indicate a severe transient migratory polyarthritis known as “the antithyroid arthritis syndrome”.
Carcinogenesis and Mutagenesis
Animal data has shown thyroid hyperplasia, thyroid adenoma and carcinoma formation (see 16 NON-CLINICAL TOXICOLOGY – carcinogenicity).
Cardiovascular
Vasculitis
Cases of vasculitis have been observed very rarely in patients receiving methimazole therapy. The cases of vasculitis include: leukocytoclastic cutaneous vasculitis, glomerulonephritis, and systemic vasculitis (with fatal outcome). Many cases were associated with anti-neutrophilic cytoplasmic antibodies
(ANCA)-positive vasculitis. Early recognition of vasculitis is important to prevent long-term organ damage and/or death. Inform patients to promptly report symptoms that may be associated with vasculitis including rash, hematuria or decreased urine output, dyspnea or hemoptysis. If vasculitis is suspected, discontinue methimazole therapy and initiate appropriate intervention.
Driving and Operating Machinery
Patients should be warned to exercise caution when driving or operating machinery while on treatment with MAR-METHIMAZOLE. Adverse reactions of vertigo and drowsiness were reported with MAR-METHIMAZOLE treatment (see 8.1 Adverse Reaction Overview).
Endocrine and Metabolism
Hypothyroidism
Methimazole can cause hypothyroidism necessitating routine monitoring of TSH and free T4 levels with adjustments in dosing to maintain a euthyroid state. Excess dosage can lead to sub- clinical or clinical hypothyroidism and goitre growth due to TSH increase (see Respiratory).
Lactose
MAR-METHIMAZOLE contains lactose monohydrate. Patients with hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this product.
Hematologic
Agranulocytosis
Agranulocytosis is potentially the most serious side effect of therapy with methimazole. Patients should be instructed to report to their physicians any symptoms of agranulocytosis, such as fever or sore throat. Leukopenia, thrombocytopenia, and aplastic anemia (pancytopenia) may also occur. The drug should be discontinued in the presence of agranulocytosis or aplastic anemia (pancytopenia). The patient’s bone marrow function should be monitored. See Monitoring and Laboratory Tests.
Anticoagulant Therapy
Treating patients with both methimazole and warfarin necessitates intensive and frequent monitoring, in particular when initiating, discontinuing or changing doses of methimazole, since alterations in the thyroid function affect the response to anticoagulation. See 9.4 Drug-Drug Interactions.
Hepatic/Biliary/Pancreatic
Hepatotoxicity is a rare adverse reaction in patients treated with methimazole. Although there have been reports of hepatotoxicity (including acute liver failure) associated with methimazole, the risk of hepatotoxicity appears to be less with methimazole than with propylthiouracil, especially in the pediatric population. There have been rare reports of fulminant hepatitis, hepatic necrosis, encephalopathy and death. Cholestatic jaundice has occurred rarely. Patients should be instructed to report symptoms of hepatic dysfunction such as jaundice, anorexia, pruritus, and/or right upper-quadrant pain. Their presence should prompt evaluation of liver function tests and discontinuation of methimazole. Drug treatment should be discontinued promptly in the event of clinically significant evidence of liver abnormality, including hepatic transaminase values exceeding 3 times the upper limit of normal. See Monitoring and Laboratory Tests.
There have been post-marketing reports of acute pancreatitis in patients receiving methimazole. In case of acute pancreatitis, methimazole should be discontinued immediately. Do not start treatment in patients with a history of acute pancreatitis that has been attributed to methimazole. Re-exposure may result in recurrence of acute pancreatitis with decreased time to onset. See 8.5 Post-Market Adverse Reactions section.
Monitoring and Laboratory Tests
The patient’s liver function, hepatic transaminase levels, and the complete blood count should be closely monitored. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 7 WARNINGS AND PRECAUTIONS, Hematologic and Hepatic/Biliary/Pancreatic. Because methimazole may cause hypoprothrombinemia and bleeding, prothrombin time/INR should also be monitored during therapy with the drug, especially before surgical procedures.
Periodic monitoring of thyroid function is warranted. A laboratory result indicating elevated TSH warrants a decrease in the dosage of methimazole. Once clinical evidence of hyperthyroidism has resolved, the finding of a rising serum TSH indicates that a lower maintenance dose of methimazole should be employed. Careful monitoring is necessary in patients with large goitres with constriction of the trachea because of the risk of goitre growth.
Reproductive Health: Female and Male Potential
see 7.1.1 Pregnant Women.
- Fertility
No data exist regarding the effect of MAR-METHIMAZOLE on fertility.
- Teratogenic Risk
Methimazole can cause fetal harm when administered to a pregnant woman. Methimazole has been reported to cause congenital malformations when administered during pregnancy, particularly in the first trimester of pregnancy and at high doses. If MAR-METHIMAZOLE is used during pregnancy or if the patient becomes pregnant while taking MAR-METHIMAZOLE, the patient should be warned of the potential hazard to the fetus. Women of childbearing potential should use effective methods of contraception during methimazole therapy (see 7.1.1 Pregnant Women).
Respiratory
Treating patients with intrathoracic goitres necessitates caution and monitoring since intrathoracic goitre can grow during treatment causing tracheal obstruction. Goitre growth due to increased TSH levels may indicate excess dosage.
Skin
The drug should be discontinued in the presence of exfoliative dermatitis.
7.1 Special Populations
- 7.1.1 Pregnant Women
Pregnant Women: Hyperthyroidism in pregnant women should be adequately treated to prevent serious maternal and fetal complications.
Methimazole can cause fetal harm when administered to a pregnant woman. Methimazole readily crosses the placental membranes and can induce goiter and hypothyroidism in the developing fetus.
Based on human experience from epidemiological studies and spontaneous reporting, methimazole is suspected to cause congenital malformations when administered during pregnancy, particularly in the first trimester of pregnancy and at high doses. Reported malformations include aplasia cutis congenital, craniofacial malformations (choanal atresia; facial dysmorphism), exomphalos, oesophageal atresia, omphalomesenteric duct anomaly and ventricular septal defect.
Methimazole must only be administered during pregnancy after a strict individual benefit/risk assessment and only at the lowest effective dose, without additional administration of thyroid hormones. If methimazole is used during pregnancy or if the patient becomes pregnant while taking methimazole, the patient should be warned of the potential hazard to the fetus. Close maternal, fetal and neonatal monitoring is recommended, with adjustment of methimazole as necessary.
Women of Childbearing potential: Women of childbearing potential should use effective methods of contraception during methimazole therapy.
7.1.2 Breast-feeding
Methimazole is excreted in human breast milk and its use is contraindicated in breastfeeding women (see 2 CONTRAINDICATIONS).
7.1.3 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥ 65 years) Clinical studies of methimazole did not include sufficient numbers of subjects aged 65 or over to determine whether they respond differently from younger subjects.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Serious adverse reactions (which occur less frequently than the minor less serious adverse reactions) include inhibition of myelopoiesis (agranulocytosis, granulocytopenia and thrombocytopenia), aplastic anemia, drug fever, a lupus-like syndrome, insulin autoimmune syndrome (which can result in hypoglycemic coma), hepatitis (jaundice may persist for several weeks after discontinuation of the drug), periarteritis and hypoprothrombinemia. Nephritis occurs very rarely. Cholestatic jaundice, fulminant hepatitis, encephalopathy, hepatic necrosis and death have been rarely reported. See 7 WARNINGS AND PRECAUTIONS.
Less serious adverse reactions include skin rash, urticaria, nausea, vomiting, epigastric distress, arthralgia, paresthesia, loss of taste, abnormal loss of hair, myalgia, headache, pruritus, drowsiness, neuritis, edema, vertigo, skin pigmentation, jaundice, sialadenopathy, anorexia, right upper-quadrant pain and lymphadenopathy.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data Clinical Trial Findings
It should be noted that about 10% of patients with untreated hyperthyroidism have leucopenia (white- blood-cell count of less than 4,000/mm3), often with relative granulopenia.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been reported from marketing experience with methimazole. Acute pancreatitis (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Vasculitis (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Cases of congenital anomalies have been reported in neonates, whose mothers were treated with methimazole during pregnancy: aplasia cutis congenital, craniofacial malformations (choanal atresia; facial dysmorphism), exomphalos, oesophageal atresia, omphalomesenteric duct anomaly, and ventricular septal defect (see 7.1.1 Pregnant Women).
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Methimazole may interact with anticoagulants and treatment of patients with both methimazole and warfarin necessitates intensive and frequent monitoring (see 7 WARNINGS AND PRECAUTION, Hematologic, Anticoagulant Therapy).
9.4 Drug-Drug Interactions
Increases and decreases in warfarin-induced anticoagulation have been reported in patients taking methimazole. In hyperthyroid patients, the metabolism of vitamin K clotting factors is increased, resulting in increased sensitivity to oral anticoagulants. Antithyroid drugs, by reducing the extent of hyperthyroidism, decrease the metabolism of clotting factors and thus reduce the effects of oral anticoagulants. On the other hand, patients on anticoagulant therapy who are euthyroid due to antithyroid agents may develop marked hypoprothrombinemia if the antithyroid medications are ceased and they become thyrotoxic again. Treating patients with both methimazole and warfarin necessitates intensive and frequent monitoring, in particular when initiating, discontinuing or changing doses of methimazole, since alterations in thyroid function affect the response to anticoagulation.
As methimazole is used in the treatment of hyperthyroidism, once a patient becomes euthyroid, the following drug interactions may need to be considered:
- β-adrenergic blocking agents: Hyperthyroidism may cause an increased clearance of beta blockers with a high extraction ratio. A dose reduction of beta-adrenergic blockers may be needed when a hyperthyroid patient becomes euthyroid.
- Digitalis glycosides: Serum digitalis levels may be increased when hyperthyroid patients on a stable digitalis glycoside regimen become euthyroid; a reduced dosage of digitalis glycosides may be needed.
- Theophylline: Theophylline clearance may decrease when hyperthyroid patients on a stable theophylline regimen become euthyroid; a reduced dose of theophylline may be needed.
9.5 Drug-Food Interactions
Interactions with foods have not been studied.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been studied.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been studied.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Methimazole inhibits the synthesis of thyroid hormones and thus is effective in the treatment of hyperthyroidism. The drug does not inactivate existing thyroxine and triiodo-thyroxine that are stored in the thyroid or circulating in the blood, nor does it interfere with the effectiveness of thyroid hormones given by mouth or by injection.
The actions and use of methimazole are similar to those of propylthiouracil. On a weight basis, the drug is at least ten times as potent as propylthiouracil, but methimazole may be less consistent in action.
10.2 Pharmacodynamics
Methimazole inhibits dose-dependently the incorporation of iodine into tyrosine and thereby the neosynthesis of thyroid hormones. This property permits symptomatic therapy of hyperthyroidism regardless of its cause. Whether methimazole furthermore affects the ‘natural course’ taken by the immunologically induced type of hyperthyroidism (Graves’ disease), i.e. whether it suppresses the underlying immunopathogenitic process, can presently not be decided with certainty. The release of previously synthesized thyroid hormones from the thyroid is not affected. This explains why the length of the latency period until normalization of the serum concentrations of thyroxine and triiodothyronine, and thus until clinical improvement, differs in individual cases. Hyperthyroidism due to the release of hormones after destruction of thyroid cells, e.g. after radioiodine therapy or in thyroiditis, is also not affected.
10.3 Pharmacokinetics
Absorption: Methimazole is readily absorbed from the gastrointestinal tract.
Metabolism: Methimazole is metabolized rapidly in the liver and requires frequent administration.
Elimination: Methimazole is excreted in the urine.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15 °C to 30 oC). Protect from light. Keep tightly closed. Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
None required.
PART II: SCIENTIFIC INFORMATION
- 13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Methimazole / Thiamazole
Chemical name: 2H-Imidazole-2-thione
Molecular formula and molecular mass: C4H6N2S
114.2 g / mol
Structural formula:
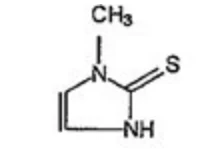
Physicochemical properties:
Description: White to pale buff crystalline powder with a characteristic odour.
It differs chemically from the drugs of the thiouracil series primarily because it has a five- instead of a six-membered ring.
Melting range: 143 - 146°C
Solubility: Freely soluble in water, alcohol and in acetone
14 CLINICAL TRIALS
The clinical trial data on which the original indication was authorized are not available.
14.3 Comparative Bioavailability Studies
A randomized, double-blind, balanced, two-treatment, two-period, two-sequence, single dose, two-way crossover, bioequivalence study of Mar-Methimazole (Methimazole) 10 mg tablets (Marcan Pharmaceuticals Inc.) with PrTAPAZOLE® (Methimazole) 10 mg tablets (Paladin Labs Inc.) in 34 healthy, adult, human male subjects, under fasting conditions.
Methimazole (1 x 10 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/mL) | 1925.58 1952.39 (16.85) | 1915.94 1944.09 (17.65) | 100.50 | 97.97 – 103.11 |
AUCI (ng.h/mL) | 2163.70 2201.02 (18.90) | 2157.42 2200.10 (20.67) | 100.29 | 97.29 – 103.38 |
Cmax (ng/mL) | 274.57 282.06 (23.44) | 292.92 300.08 (22.52) | 93.74 | 86.26 – 101.86 |
Tmax§ (h) | 0.50 (0.17-1.50) | 0.50 (0.33-1.50) | ||
T½€ (h) | 7.62 (15.65) | 7.75 (21.43) | ||
* Mar-Methimazole 10 mg tablets; Manufactured by Marcan Pharmaceuticals Inc., Ottawa, Canada
† PrTapazole (Methimazole 10 mg tablets); Manufactured by Paladin Labs Inc., Canada, was purchased in Canada.
§ Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Carcinogenicity:
Rats treated for 2 years with methimazole demonstrated thyroid hyperplasia and thyroid adenoma and carcinoma formation. Such findings are seen with continuous suppression of thyroid function by sufficient doses of a variety of antithyroid agents. Pituitary adenomas have also been observed (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis).
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. TAPAZOLE®, Tablets, 5 mg and 10 mg submission control number 270311, Product Monograph, Paladin Labs Inc. April 13, 2023.