


Product Monograph - Mar-Pregabalin
RECENT MAJOR LABEL CHANGES
4 DOSAGE AND ADMINISTRATION, 4.2.1 Discontinuing Treatment | 01/2025 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Dependence, Tolerance and/or Abuse Liability | 01/2025 |
7 WARNINGS AND PRECAUTIONS 7 WARNINGS AND PRECAUTIONS, 7.1.1. Pregnant Women | 09/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
- 1.
INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................... 4
1.2 Geriatrics .................................................................................................................... 4
- 2. CONTRAINDICATIONS .................................................................................................. 4
- 3. SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 4
- 4.
DOSAGE AND ADMINISTRATION .................................................................................. 4
4.1 Dosing Considerations ............................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ........................................................... 5
4.2.1 Discontinuing Treatment ........................................................................................... 7
4.4 Administration ........................................................................................................... 8
- 5. OVERDOSAGE .............................................................................................................. 8
- 6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................... 8
- 7.
WARNINGS AND PRECAUTIONS ................................................................................. 10
7.1 Special Populations .................................................................................................. 19
7.1.1 Pregnant Women ..................................................................................................... 19
7.1.2 Breast-feeding.......................................................................................................... 20
7.1.3 Pediatrics ................................................................................................................. 21
7.1.4 Geriatrics .................................................................................................................. 21
- 8.
ADVERSE REACTIONS ................................................................................................. 21
8.2 Clinical Trial Adverse Reactions ............................................................................... 21
8.3 Less Common Clinical Trial `Adverse Reactions (< 2%) ............................................ 34
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ..................................................................................................... 39
8.5 Post-Market Adverse Reactions ............................................................................... 39
- 9.
DRUG INTERACTIONS ................................................................................................. 43
9.1 Serious Drug Interaction .......................................................................................... 43
9.2 Drug Interactions Overview ..................................................................................... 43
9.4 Drug-Drug Interactions............................................................................................. 43
9.5 Drug-Food Interactions ............................................................................................ 45
9.6 Drug-Herb Interactions ............................................................................................ 45
9.7 Drug-Laboratory Test Interactions ............................................................................ 45
- 10.
CLINICAL PHARMACOLOGY ........................................................................................ 45
10.1 Mechanism of Action ............................................................................................... 45
10.2 Pharmacodynamics ................................................................................................... 45
10.3 Pharmacokinetics ...................................................................................................... 46
- 11. STORAGE, STABILITY AND DISPOSAL ........................................................................... 49
- 12. SPECIAL HANDLING INSTRUCTIONS ............................................................................ 49
PART II: SCIENTIFIC INFORMATION ....................................................................................... 50
- 13. PHARMACEUTICAL INFORMATION ............................................................................. 50
- 14.
CLINICAL TRIALS ......................................................................................................... 51
14.1 Clinical Trials by Indication ...................................................................................... 51
Diabetic Peripheral Neuropathy ........................................................................................ 51
Postherpetic Neuralgia ...................................................................................................... 53
Spinal Cord Injury ............................................................................................................... 56
Fibromyalgia....................................................................................................................... 57
14.3 Comparative Bioavailability Studies ......................................................................... 60
- 15. MICROBIOLOGY ......................................................................................................... 61
- 16. NON-CLINICAL TOXICOLOGY ...................................................................................... 61
- 17. SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 65
PATIENT MEDICATION INFORMATION .................................................................................. 66
PART I: HEALTH PROFESSIONAL INFORMATION
1. INDICATIONS
Adults
MAR-PREGABALIN (Pregabalin capsules) is indicated for the management of neuropathic pain associated with:
- Diabetic peripheral neuropathy;
- Postherpetic neuralgia;
- Spinal cord injury
MAR-PREGABALIN is indicated for the management of pain associated with fibromyalgia.
The efficacy of pregabalin in the management of pain associated with fibromyalgia for up to 6 months was demonstrated in a placebo-controlled trial in patients who had initially responded to pregabalin during a 6-week open-label phase.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics: Pregabalin oral clearance tended to decrease with increasing age. This decrease in pregabalin oral clearance is consistent with age-related decreases in creatinine clearance.
Reduction of pregabalin dose may be required in patients who have age-related compromised renal function (see 7.1.4 Geriatrics).
2. CONTRAINDICATIONS
MAR-PREGABALIN is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3. SERIOUS WARNINGS AND PRECAUTIONS BOX
Life-threatening Respiratory Depression Concomitant use of MAR-PREGABALIN with opioids may result in respiratory depression, profound sedation, syncope, and death. (see 7 WARNINGS AND PRECAUTIONS, Respiratory Depression; Concomitant use with Opioids; 9.2 Drug Interactions Overview).
|
|---|
4. DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
In accordance with current clinical practice, if MAR-PREGABALIN (pregabalin) has to be discontinued, it is recommended this should be done gradually over a minimum of 1 week (see 4.2.1 Discontinuing Treatment).
Patients with Impaired Renal Function
Pregabalin is primarily eliminated from the systemic circulation by renal excretion as unchanged drug. In some elderly patients and those with a medical history of significant renal insufficiency, daily dosages should be reduced accordingly (see 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment Based on Renal Function).
4.2 Recommended Dose and Dosage Adjustment
Adults
Neuropathic Pain Associated with Diabetic Peripheral Neuropathy
The recommended starting dose for MAR-PREGABALIN is 150 mg/day, given in two or three divided doses (75 mg BID or 50 mg TID), with or without food in patients with a creatinine clearance rate of at least 60 mL/min. Efficacy of pregabalin has been demonstrated within the first week. Based on individual patient response and tolerability, the dose may be increased to 150 mg BID (300 mg/day) after one week.
For patients who experience significant and ongoing pain and can tolerate pregabalin 300 mg/day well, maximum daily dose of 600 mg (300 mg twice a day, BID) can be used. However, in clinical trials, pregabalin 600 mg/day did not provide additional significant efficacy and patients treated with this dose experienced markedly higher rates of adverse events and discontinued the trial more frequently (see 8.2 Clinical Trial Adverse Reactions, Table 6). Doses above 600 mg/day have not been studied and are not recommended.
Neuropathic Pain Associated with Postherpetic Neuralgia
The recommended starting dose for MAR-PREGABALIN is 150 mg/day, given in two or three divided doses (75 mg BID or 50 mg TID), with or without food in patients with a creatinine clearance rate of at least 60 mL/min. Efficacy of pregabalin has been demonstrated within the first week. Based on individual patient response and tolerability, the dose may be increased to 150 mg BID (300 mg/day) after one week.
For patients who experience significant and ongoing pain and can tolerate pregabalin 300 mg/day well, maximum daily dose of 600 mg (300 mg twice a day, BID) can be used.
However, in clinical trials, pregabalin 600 mg/day did not provide additional significant efficacy and patients treated with this dose experienced markedly higher rates of adverse events and discontinued the trial more frequently (see 8.2 Clinical Trial Adverse Reactions, Table 4 and Table 7). Doses above 600 mg/day have not been studied and are not recommended.
Neuropathic Pain Associated with Spinal Cord Injury
The recommended starting dose for MAR-PREGABALIN is 150 mg/day, given in two divided doses (75 mg BID), with or without food in patients with a creatinine clearance rate of at least 60 mL/min. Efficacy of pregabalin has been demonstrated within the first week. Based on individual patient response and tolerability, the dose may be increased to 150 mg BID (300 mg/day) after one week.
For patients who experience significant and ongoing pain and can tolerate pregabalin 300 mg/day well, maximum daily dose of 600 mg (300 mg twice a day, BID) may be considered. Doses above 600 mg/day have not been studied and are not recommended.
Pain Associated with Fibromyalgia
The recommended dosage is 300 to 450 mg/day, given in two divided doses. The recommended starting dose for MAR-PREGABALIN is 150 mg/day, given in two divided doses (75 mg BID), with or without food in patients with a creatinine clearance rate of at least 60 mL/min. Based on individual response and tolerability, the dose may be increased to 150 mg BID (300 mg/day) after one week. Patients who do not experience sufficient benefit with 300 mg/day may be further increased to 225 mg BID (450 mg/day). In some patients, efficacy of pregabalin has been demonstrated within the first week.
For patients who experience significant and ongoing pain and can tolerate pregabalin 300 mg/day well, maximum daily dose of 600 mg (300 mg twice a day, BID) can be used.
However, in clinical trials of fibromyalgia, pregabalin 600 mg/day did not provide additional significant efficacy and patients treated with this dose experienced significantly higher rates of adverse events and discontinued the trial more frequently (see 8.2 Clinical Trial Adverse Reaction, Table 8 and Table 11). In view of the dose-related adverse events, the decision to treat patients with doses above 450 mg/day should be based on clinical judgment of the treating physician. Doses above 600 mg/day have not been studied and are not recommended.
Dosage Adjustment Based on Renal Function
Pregabalin is primarily eliminated by renal excretion. Therefore, the dose should be adjusted for patients with reduced renal function. Pregabalin clearance is directly proportional to creatinine clearance. Therefore, dosing adjustment should be based on creatinine clearance (CLCr), as indicated in Table 1.
To use this dosing table, an estimate of the patient's creatinine clearance (CLCr) in mL/min is needed. CLCr in mL/min may be estimated from serum creatinine (mg/dL) determination using the Cockcroft and Gault equation:
| CLcr= | [140 - age (years)] x weight (kg) | (x 0.85 for female patients) | |
|---|---|---|---|
| 72 x serum creatinine (mg/dL) | |||
Pregabalin is effectively removed from plasma by hemodialysis. Over a 4-hour hemodialysis treatment, plasma pregabalin concentrations are reduced by approximately 50%. For patients receiving hemodialysis, pregabalin daily dose should be adjusted based on renal function. In addition to the daily dose adjustment, a supplemental dose should be given immediately following every 4-hour hemodialysis treatment (see Table 1).
Table 1. Pregabalin Dosage Adjustment Based on Renal Function
Creatinine Clearance (CLcr) (mL/min) | Total Pregabalin Daily Dose (mg/day)a Recommended Dose Escalation* | Dose Regimen | |||
|---|---|---|---|---|---|
| Starting Dose | up to | Maximum daily dose | |||
| ≥ 60 | 150 | 300 | 450 | 600 | BID or TID |
| 30 - 60 | 75 | 150 | 225 | 300 | BID or TID |
| 15 - 30 | 25-50 | 75 | 100-150 | 150 | QD or BID |
| < 15 | 25 | 25-50 | 50-75 | 75 | QD |
| Supplementary dosage following hemodialysis (mg)b | |||||
| Patients on the 25 mg QD regimen: take one supplemental dose of 25 mg or 50 mg Patients on the 25 - 50 mg QD regimen: take one supplemental dose of 50 mg or 75 mg Patients on the 50 - 75 mg QD regimen: take one supplemental dose of 75 mg or 100 mg Patients on the 75 mg QD regimen: take one supplemental dose of 100 mg or 150 mg | |||||
TID = Three divided doses; BID = Two divided doses; QD = Single daily dose.
* Based on individual patient response and tolerability.
a Total daily dose (mg/day) should be divided as indicated by dose regimen to provide mg/dose.
b Supplementary dose is a single additional dose.
Geriatrics (> 65 years): Pregabalin oral clearance tended to decrease with increasing age. This decrease in pregabalin oral clearance is consistent with age-related decreases in creatinine clearance. Reduction of pregabalin dose may be required in patients who have age-related compromised renal function.
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
4.2.1 Discontinuing Treatment
Abrupt or Rapid Discontinuation
Following abrupt or rapid discontinuation of pregabalin, some patients reported symptoms including insomnia, nausea, headache, anxiety, hyperhidrosis, and diarrhea. Convulsions, including status epilepticus and grand mal convulsions, have occurred in non-epileptic patients during treatment with pregabalin or after abrupt discontinuation (see 8.2 Clinical Trial Adverse Reactions, Adverse Events Following Abrupt or Rapid Discontinuation).
Pregabalin should be tapered gradually over a minimum of one week rather than discontinued abruptly
4.4 Administration
MAR-PREGABALIN (pregabalin) is given orally with or without food (see 9.5 Drug-Food Interactions).
5. OVERDOSAGE
Signs, Symptoms and Laboratory Findings of Acute Overdosage in Humans
The highest known dose of pregabalin received in the clinical development program in which there was no fatal outcome was 15,000 mg in 1 patient. The types of adverse events experienced by patients who received an overdose were not clinically different from other patients receiving recommended doses of pregabalin.
In post-marketing experience, fatal outcomes in cases in which pregabalin has been taken in combination with other medications have been reported with a pregabalin overdose as low as 800 mg in a day. In none of these cases has pregabalin been established as the cause of death or in pregabalin monotherapy. The lowest fatal dose with pregabalin alone has not yet been identified.
The most commonly reported adverse events observed when pregabalin was taken in overdose (dose range from 800 mg/day up to 11,500 mg as a single dose) included affective disorder, somnolence, confusional state, depression, agitation, and restlessness. Seizures were also reported.
Treatment or Management of Overdose
There is no specific antidote for overdose with pregabalin. Usual precautions should be observed to maintain the airway. General supportive care of the patient is indicated including monitoring of vital signs and observation of the clinical status of the patient. A Certified Poison Control Center should be contacted for up-to-date information on the management of overdose with pregabalin.
Hemodialysis
Standard hemodialysis procedures result in significant clearance of pregabalin (approximately 50% in 4 hours) and should be considered in cases of overdose. Although hemodialysis has not been performed in the few known cases of overdose, it may be indicated by the patient's clinical state or in patients with significant renal impairment.
6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| For management of a suspected drug overdose, contact your regional poison control centre. or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Capsules, 25 mg, 50 mg, 75 mg, 100 mg, 150 mg, 200 mg, 225 mg, 300 mg | Pre-gelatinized starch and Talc. Capsule shells contain gelatin and titanium dioxide. In addition, orange capsule shells contain red iron oxide. The markings on the capsules are in black ink, which contains ammonia solution, black iron oxide, butyl alcohol, dehydrated alcohol, isopropyl alcohol, potassium hydroxide, propylene glycol, shellac and water. |
Dosage Forms
MAR-PREGABALIN (pregabalin) supplied as a hard gelatin capsule for daily oral administration.
25 mg capsules: Opaque White/Opaque white size ‘4’ hard gelatin capsules, radially imprinted with ‘PG’ on cap and ‘25’ on body with black ink, filled with white to off white powder.
50 mg capsules: Opaque White/Opaque white size ‘2’ hard gelatin capsules, radially imprinted with ‘PG’ on cap and ‘50’ on body and band on body with black ink, filled with white to off white powder.
75 mg capsules: Opaque Orange/Opaque White size ‘4’ hard gelatin capsules, radially imprinted with ‘PG’ on cap and ‘75’ on body with black ink, filled with white to off white powder.
100 mg capsules: Orange Opaque/ Orange Opaque size ‘3’ hard gelatin capsules, radially imprinted with ‘A’ on cap and ‘143’ on body with black ink, filled with white to off white powder.
150 mg capsules: Opaque White/Opaque white size ‘2’ hard gelatin capsules, radially imprinted with ‘PG’ on cap and ‘150’ on body with black ink, filled with white to off white powder.
200 mg capsules: Orange Opaque/ Orange Opaque size ‘1’ hard gelatin capsules, radially imprinted with ‘A’ on cap and ‘145’ on body with black ink, filled with white to off white powder.
225 mg capsules: Opaque White/ Light Orange size ‘1’ hard gelatin capsules, radially imprinted with ‘A’ on cap and ‘146’ on body with black ink, filled with white to off white powder.
300 mg capsules: White/Orange, size '0', hard gelatin capsules, radially imprinted with
'PG' on Cap and '300' on the body with black ink, filled with white to off-white powder.
Packaging
25 mg, 50 mg, 75 mg and 150 mg capsules are available in the packs of HDPE bottles of 100’s or 500’s.
100 mg, 200 mg and 225 mg capsules are available in HDPE bottles of 1000’s.
300 mg capsules are available in the packs of HDPE bottles of 500’s or 100’s.
7. WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Peripheral Edema
Pregabalin may cause peripheral edema. In controlled peripheral neuropathic pain and fibromyalgia clinical trials, pregabalin treatment caused peripheral edema in 9% of patients compared with 3% of patients in the placebo group. In these studies, 0.7% of pregabalin patients and 0.3% of placebo patients withdrew due to peripheral edema (see 8.3 Less Common Clinical Trial Adverse Reactions (<2%), Peripheral Edema).
In controlled clinical trials of up to 13 weeks in duration of patients without clinically significant heart or peripheral vascular disease, there was no apparent association between peripheral edema and cardiovascular complications such as hypertension or congestive heart failure. In the same trials, peripheral edema was not associated with laboratory changes suggestive of deterioration in renal or hepatic function.
Higher frequencies of weight gain and peripheral edema were observed in patients taking both pregabalin and a thiazolidinedione antidiabetic agent compared to patients taking either drug alone. The majority of patients using thiazolidinedione antidiabetic agents in the overall safety database were participants in studies of pain associated with diabetic peripheral neuropathy. In this population, peripheral edema was reported in 3% (2/60) of patients who were using thiazolidinedione antidiabetic agents only, 8% (69/859) of patients who were treated with pregabalin only, and 19% (23/120) of patients who were on both pregabalin and thiazolidinedione antidiabetic agents. Similarly, weight gain was reported in 0% (0/60) of patients on thiazolidinediones only; 4% (35/859) of patients on pregabalin only; and 7.5% (9/120) of patients on both drugs.
As the thiazolidinedione class of antidiabetic drugs can cause weight gain and/or fluid retention, possibly exacerbating or leading to heart failure, care should be taken when co-administering pregabalin and these agents.
Encephalopathy
There have been serious post-marketing reports of encephalopathy, mostly in patients with underlying conditions that may precipitate encephalopathy. Some cases were reported in patients with a history of kidney or liver disease. Since there have been rare reports of renal failure with pregabalin, specific caution should be exercised when prescribing pregabalin to the elderly with age-related compromised renal function and patients with kidney disease or risk factors for renal failure (see 7 WARNINGS AND PRECAUTIONS, Renal Failure and 8.5 Post-Market Adverse Reactions, Urinary and Renal Disorder).
Patient Counselling Information
Patients receiving MAR-Pregabalin should be given the following instructions by the physician:
- 1. Angioedema: Patients should be advised that MAR-Pregabalin may cause angioedema, with swelling of the face, mouth (lip, gum, tongue) and neck (larynx and pharynx) that can lead to life-threatening respiratory compromise. Instruct patients to discontinue MAR-Pregabalin and immediately seek medical care if they experience these symptoms.
- 2. Hypersensitivity: Patients should be advised that MAR-Pregabalin has been associated with hypersensitivity reactions such as wheezing, dyspnea, rash, hives, and blisters. Instruct patients to discontinue MAR-Pregabalin and immediately seek medical care if they experience these symptoms.
- 3. Suicidal Behaviour and Ideation: Patients, their caregivers, and families should be counselled to monitor for signs of suicidal ideation and behaviours and should be encouraged to report any distressing thoughts or feelings at anytime to their healthcare professional.
- 4. Dizziness and Somnolence: Patients should be counseled that MAR-Pregabalin may cause dizziness, somnolence, blurred vision and other CNS signs and symptoms. Accordingly, they should be advised not to drive, operate complex machinery, or engage in other hazardous activities until they have gained sufficient experience on pregabalin to gauge whether or not it affects their mental, visual, and/or motor performance adversely.
- 5. Edema and Weight Gain: Patients should be counseled that MAR-Pregabalin may cause edema and weight gain. Patients should be advised that concomitant treatment with MAR-Pregabalin and a thiazolidinedione antidiabetic agent may lead to an additive effect on edema and weight gain. For patients with preexisting cardiac conditions, this may increase the risk of heart failure.
- 6. Abrupt or Rapid Discontinuation: Patients should be advised to take MAR-Pregabalin as prescribed. Abrupt or rapid discontinuation may result in insomnia, nausea, headache, anxiety, hyperhidrosis, or diarrhea.
- 7. Visual Disturbances: Patients should be counseled that MAR-Pregabalin may cause visual disturbances. Patients should be informed that if changes in vision occur, they should notify their physician (see 7 WARNINGS AND PRECAUTIONS, Ophthalmological Effects).
- 8. Muscle Pain, Tenderness or Weakness: Patients should be instructed to promptly report unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever.
- 9.
Concomitant Treatment with CNS Depressants, Alcohol: Patients who require concomitant treatment with central nervous system depressants such as opiates or benzodiazepines should be informed that they may experience additive CNS side effects, such as somnolence.
In post-marketing experience, there are reports of respiratory failure, coma and deaths in patients taking pregabalin alone or in combination with other CNS depressants, including in patients with substance use disorders.
Patients should be told to avoid consuming alcohol while taking MAR-Pregabalin, as MAR-Pregabalin may potentiate the impairment of motor skills and sedation of alcohol.
- 10.
Pregnant Women: Patients should be instructed to notify their physician if they become pregnant or intend to become pregnant during their therapy, and to notify their physician if they are breast-feeding or intend to breast-feed during therapy.
Patients should be encouraged to enroll in the North American Antiepileptic Drug Pregnancy Registry (NAAED) if they become pregnant. This registry is collecting information about the safety of anticonvulsant medications that can be taken by women during pregnancy to treat disorders such as epilepsy, mood disorder, and chronic pain. To enroll, patients can call the toll free number 1-888-233-2334. Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/ (see 7.1.1 Pregnant Women).
- 11. Animal Studies in Male Reproduction: Men being treated with MAR-Pregabalin who plan to father a child should be informed of the potential risk of male-mediated teratogenicity. In preclinical studies in rats, pregabalin was associated with an increased risk of male-mediated teratogenicity (see 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential). The clinical significance of this finding is uncertain.
- 12.
Skin: Diabetic patients should be instructed to pay particular attention to skin integrity while being treated with MAR-PREGABALIN. Some animals treated with pregabalin developed skin ulcerations, although no increased incidence of skin lesions associated with pregabalin was observed in clinical trials (see 16 NON- CLINICAL TOXICOLOGY, Repeated-Dose Toxicity).
Patients should be informed of the availability of a patient information leaflet, and they should be instructed to read the leaflet prior to taking MAR-Pregabalin.
Carcinogenesis and Mutagenesis
Tumorigenic Potential
In standard preclinical in vivo lifetime carcinogenicity studies of pregabalin, a high incidence of hemangiosarcoma was identified in two different strains of mice (see 16 NON-CLINICALTOXICOLOGY, Carcinogenicity). The clinical significance of this finding is uncertain.
Clinical experience during pregabalin’s premarketing development provides no direct means to assess its potential for inducing tumors in humans.
In clinical studies across various patient populations, comprising 6396 patient-years of exposure in 8666 patients ranging in age from 12 to 100 years, new or worsening-preexisting tumors were reported in 57 patients. The most common malignant tumor diagnosed was skin carcinoma (17 patients) followed by breast carcinoma (8 patients), prostatic carcinoma (6 patients), carcinoma not otherwise specified (6 patients), and bladder carcinoma (4 patients). Without knowledge of the background incidence and recurrence in similar populations not treated with pregabalin, it is impossible to know whether the incidence seen in these cohorts is or is not affected by treatment.
Cardiovascular
Congestive Heart Failure
In controlled clinical studies, events of congestive heart failure were reported at an infrequent rate (between 0.1% and 1%; see 8.3 Less Common Clinical Trial Adverse Reactions (< 2%)).
There have been post-marketing reports of congestive heart failure in some patients receiving pregabalin (see 8.5 Post-Market Adverse Reactions). Although this adverse reaction has mostly been observed in elderly cardiovascular compromised patients during pregabalin treatment for a neuropathic pain indication, some cases have occurred in patients without reported edema or previous history of cardiovascular disease. Pregabalin should be used with caution in these patients. Discontinuation of pregabalin may resolve the reaction.
ECG Changes, PR Interval Prolongation
Pregabalin treatment was associated with mild PR interval prolongation. In analyses of clinical trial ECG data, the mean PR interval increase was 3-6 msec at pregabalin doses
≥ 300 mg/day. This mean change difference was not associated with an increased risk of PR increase ≥ 25% from baseline, an increased percentage of subjects with on-treatment PR > 200 msec, or an increased risk of adverse events of second or third degree AV block.
Dependence, Tolerance and/or Abuse Liability
Pregabalin can cause drug dependence, which may occur at therapeutic doses. Cases of misuse, abuse and dependence have been reported. in individuals with and without a history of substance abuse. Caution should be exercised in prescribing pregabalin to patients with current substance abuse, a history of substance abuse, or an individual who is at a higher risk for pregabalin abuse. Patients treated with pregabalin should be monitored for signs and symptoms of pregabalin misuse, abuse or dependence (development of tolerance, dose escalation, drug-seeking behaviour have been reported) (see 4.2.1 Discontinuing Treatment).
Driving and Operating Machinery
Patients should be advised not to drive or operate complex machinery or engage in other hazardous activities until they have gained sufficient experience on pregabalin to gauge whether or not it affects their mental and/or motor performance adversely (see PATIENT MEDICATION INFORMATION).
Endocrine and Metabolism
Weight Gain
Pregabalin may cause weight gain. In pregabalin-controlled peripheral neuropathic pain and fibromyalgia clinical trials with durations of up to 14 weeks, a gain of 7% or more over baseline weight was observed in 8% of pregabalin-treated patients and 3 % of placebo-treated patients. Few patients treated with pregabalin (0.6%) withdrew from controlled trials due to weight gain (see 8 ADVERSE REACTIONS, Weight Gain).
Pregabalin-associated weight gain was related to dose and duration of exposure. Pregabalin-associated weight gain did not appear to be associated with baseline BMI, gender, or age. Weight gain was not limited to patients with edema and was not necessarily due to edema-related events (see 7 WARNINGS AND PRECAUTIONS, Peripheral Edema).
Although weight gain was not associated with clinically important changes in blood pressure in short-term controlled studies, the long-term cardiovascular effects of pregabalin-associated weight gain are unknown.
Among diabetic patients, pregabalin-treated patients gained an average of 1.6 kg (range: -16 to 16 kg), compared to an average 0.3 kg (range: -10 to 9 kg) weight gain in placebo patients. In a cohort of 333 diabetic patients who received pregabalin for at least 2 years, the average weight gain was 5.2 kg.
In the controlled fibromyalgia clinical trials, 10.7% of pregabalin-treated patients experienced weight gain of 7% or greater compared to 4.9% of placebo-treated patients. Pregabalin-treated patients gained an average of 1.7 Kg compared to an average of 0.7 Kg weight gain in placebo patients.
While the effects of pregabalin-associated weight gain on glycemic control have not been systematically assessed, in controlled and longer-term open label clinical trials with diabetic patients, pregabalin treatment did not appear to be associated with loss of glycemic control (as measured by HbA1C).
Gastrointestinal
There have been post-marketing reports of events related to reduced lower gastrointestinal tract function (e.g., intestinal obstruction, paralytic ileus, and constipation) in patients, some without reported previous history/episode(s), during initial/acute and chronic treatment with pregabalin, primarily in combination with other medications that have the potential to produce constipation. Some of these events were considered serious and required hospitalization. In a number of instances, patients were taking opioid analgesics including tramadol.
Caution should be exercised when pregabalin and opioid analgesics are used in combination, and measures to prevent constipation may be considered, especially in female patients and elderly as they may be at increased risk of experiencing lower gastrointestinal-related events (see 8.5 Post-Market Adverse Reactions, Gastrointestinal).
Hematologic
Laboratory Changes, Decreased Platelet Count
Pregabalin treatment was associated with a decrease in platelet count. Pregabalin-treated subjects experienced a mean maximal decrease in platelet count of
20 x 103/mcL, compared to 11 x 103/mcL in placebo patients. In the overall database of controlled trials, 2% of placebo patients and 3% of pregabalin patients experienced a potentially clinically significant decrease in platelets, defined as 20% below baseline value and < 150 x 103/mcL.
In randomized controlled trials, pregabalin was not associated with an increase in bleeding related adverse events.
Immune
Angioedema
There have been post-marketing reports of angioedema in patients, some without reported previous history/episode(s), during initial/acute and chronic treatment with pregabalin. Specific symptoms included swelling of the face, mouth (tongue, lips, and gums), neck, throat, and larynx/upper airway. There have been reports of life - threatening angioedema with respiratory compromise requiring emergency treatment. Some of these patients did not have reported previous history/episode(s) of angioedema. MAR-Pregabalin should be immediately discontinued in patients with these symptoms. During the pre-marketing assessment of pregabalin in clinical trials, angioedema was reported as a rare reaction (see 8.3 Less Common Clinical Trial Adverse Reactions (< 2%); 8.5 Post-Market Adverse Reactions).
Caution should be exercised when prescribing MAR-Pregabalin to patients with previous history/episode(s) of angioedema and related events. In addition, patients who are taking other drugs associated with angioedema (e.g., ACE-inhibitors) may be at increased risk of developing this condition.
Hypersensitivity
There have been postmarketing reports of hypersensitivity reactions (e.g., skin redness, blisters, hives, rash, dyspnea, and wheezing). Pregabalin should be discontinued immediately if such symptoms occur (see 8.5 Post-Market Adverse Reactions).
Monitoring and Laboratory Tests
Routine therapeutic drug monitoring or clinical laboratory testing is not required for patients treated with MAR-Pregabalin (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data).
Musculoskeletal
Creatine Kinase Elevations
Pregabalin treatment was associated with creatine kinase elevations. Mean changes in creatine kinase from baseline to the maximum value were 60 U/L for pregabalin- treated patients and 28 U/L for the placebo patients. In all controlled trials across multiple patient populations, 2% of patients on pregabalin and 1% of placebo patients had a value of creatine kinase at least three times the upper limit of normal. Three pregabalin-treated subjects had events reported as rhabdomyolysis in premarketing clinical trials. The relationship between these myopathy events and pregabalin is not completely understood because the cases had documented factors that may have caused or contributed to these events. Prescribers should instruct patients to promptly report unexplained muscle pain, tenderness, or weakness, particularly if these muscle symptoms are accompanied by malaise or fever. Pregabalin treatment should be discontinued if myopathy is diagnosed or suspected or if markedly elevated creatine kinase levels occur.
Neurologic
Respiratory Depression
Pregabalin has been associated with central nervous system (CNS) depression including sedation, somnolence, loss of consciousness as well as serious cases of respiratory depression. Patients with compromised respiratory function, respiratory or neurological disease, renal impairment and the elderly are at higher risk of experiencing these severe adverse effects. Concomitant use of CNS depressants with pregabalin is also a contributing factor.
Concomitant Use With Opioids
Caution is advised when prescribing MAR-Pregabalin concomitantly with opioids due to risk of CNS depression. Concomitant use of opioids with MAR-PREGABALIN potentiates the risk of respiratory depression, profound sedation, syncope, and death. In an observational study of opioid users, those patients who took pregabalin concomitantly with an opioid had an increased risk for opioid-related death compared to opioid use alone (adjusted odds ratio [aOR], 1.68 [95% CI, 1.19 to 2.36]).
Patients who require concurrent treatment with opioids or other CNS depressants should be observed carefully for signs and symptoms of CNS depression, and the dose of pregabalin or opioid should be reduced accordingly (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS, Patient Counselling Information).
Dizziness and Somnolence
MAR-Pregabalin may cause dizziness and somnolence. In controlled peripheral neuropathic pain and fibromyalgia studies, pregabalin caused dizziness in 32% of patients compared to 8% in placebo. Somnolence was experienced by 17% and 4% of the patients treated with pregabalin and placebo, respectively. These events begin shortly after the initiation of therapy and generally occur more frequently at higher doses. In these studies, dizziness and somnolence led to withdrawal of 5% (placebo: 0.5%) and 3% (placebo: 0.1%) of the pregabalin-treated patients, respectively. For the remaining patients who experienced these events, dizziness and somnolence persisted until the last dose of pregabalin in 35% and 49% of the patients, respectively (see 8.2 Clinical Trial Adverse Reactions, Table 3, Table 5, and Table 12, and 8.5 Post-Market Adverse Reactions).
Ophthalmologic
Ophthalmological Effects
In controlled studies, pregabalin treatment was associated with vision-related adverse events such as blurred vision (amblyopia) [6% pregabalin and 2% placebo] and diplopia (2% pregabalin and 0.5% placebo). Approximately 1% of pregabalin-treated patients discontinued treatment due to vision-related adverse events (primarily blurred vision).
Of the patients who did not withdraw, the blurred vision resolved with continued dosing in approximately half of the cases (see 8.5 Post-Market Adverse Reactions, Eye disorder).
Prospectively planned ophthalmologic testing, including visual acuity testing, formal visual field testing and dilated funduscopic examination, was performed in over 3600 patients. In these patients, visual acuity was reduced in 7% of patients treated with pregabalin, and 5% of placebo-treated patients. Visual field changes were detected in 13% of pregabalin-treated, and 12% of placebo-treated patients. Funduscopic changes were observed in 2% of pregabalin-treated and 2% of placebo-treated patients. At this time, clinical significance of the ophthalmologic findings is unknown.
Patients should be informed that if changes in vision occur, they should notify their physician. If visual disturbance persists, further assessment, including discontinuation of pregabalin, should be considered. More frequent assessments should be considered for patients who are already routinely monitored for ocular conditions.
Psychiatric
Suicidal Behaviour and Ideation
There have been post-marketing reports of suicide-related events, including completed suicide, suicide attempt, and suicidal ideation in patients treated with pregabalin for a variety of indications such as neuropathic pain, fibromyalgia, etc. In some of these reports, underlying psychiatric disorders may have contributed to the event. The mechanism of this risk is not known. Patients should be monitored for signs of suicidal ideation and behaviours and appropriate treatment should be considered. Patients should be encouraged to report any distressing thoughts or feelings at any time to their healthcare professional (see 8.5 Post-Market Adverse Reactions, Suicidal Behaviour and Ideation).
Renal
Renal Failure
In both clinical trials of various indications and post-marketing database, there are reports of patients, with or without previous history, experiencing renal failure while receiving pregabalin alone or in combination with other medications. Discontinuation of pregabalin should be considered as it has shown reversibility of this event in some cases. Caution is advised when prescribing pregabalin to the elderly or those with any degree of renal impairment (see 7.1 Special Populations, Renal; 4.2.1 Discontinuing Treatment, 8.5 Post-Market Adverse Reactions, Urinary and Renal Disorder and 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment Based on Renal Function).
Reproductive Health: Female and Male Potential
Fertility
Impairment of Male Fertility
Preclinical Data
In fertility studies in which male rats were orally administered pregabalin (50 to 2500 mg/kg) prior to and during mating with untreated females, a number of adverse reproductive and developmental effects were observed. These included decreased sperm counts and sperm motility, increased sperm abnormalities, reduced fertility, increased preimplantation embryo loss, decreased litter size, decreased fetal body weights, and an increased incidence of fetal abnormalities. Effects on sperm and fertility parameters were reversible in studies of this duration (3-4 months). The no- effect dose for male reproductive toxicity in these studies (100 mg/kg) was associated with a plasma pregabalin exposure (AUC) approximately 3 times human exposure at the maximum recommended dose (MRD) of 600 mg/day.
In addition, adverse effects on reproductive organ (testes, epididymides) histopathology were observed in male rats exposed to pregabalin (500 to 1250 mg/kg) in general toxicology studies of 4 weeks or greater duration. The no-effect dose for male reproductive organ histopathology in rats (250 mg/kg) was associated with a plasma exposure approximately 8 times human exposure at the MRD.
In a fertility study in which female rats were given pregabalin (500, 1250, or 2500 mg/kg) orally prior to and during mating and early gestation, disrupted estrous cyclicity and an increased number of days to mating were seen at all doses, and embryolethality occurred at the highest dose. The low dose in this study produced a plasma exposure approximately 9 times that in humans receiving the MRD. A no-effect dose for female reproductive toxicity in rats was not established. The clinical significance of female fertility findings in animals is unknown.
Human Data
In a double-blind, placebo-controlled clinical trial to assess the effect of pregabalin on sperm motility, 30 healthy male subjects were exposed to pregabalin 600 mg/day for 3 months (one complete sperm cycle). Pregabalin did not exhibit significant detrimental effects on the reproductive function of healthy male subjects, as measured by semen analysis, when compared with placebo (n = 16). However, due to the small sample size and short-term exposure to pregabalin (only one complete sperm cycle), no conclusions can be made regarding possible reproductive effects of pregabalin during long-term exposure. Effects on other male reproductive parameters in humans have not been adequately studied.
Teratogenic Risk
Pregabalin was not teratogenic in mice, rats, or rabbits. Pregabalin induced fetal toxicity in rats and rabbits at ≥ 39 times the mean human exposure at the maximum recommended clinical dose of 600 mg/day [AUC (0-24) of 123 mcg•hr/mL]. In the prenatal-postnatal toxicity study, pregabalin induced offspring developmental toxicity in rats at ≥ 5 times the maximum recommended human exposure. No developmental effects occurred at 2 times the maximum recommended human exposure (see 16 NON- CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Skin
Serious Skin Reactions
There have been very rare post-marketing reports of serious cutaneous reactions, including Stevens-Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN), dermatitis exfoliative, bullous skin reactions, and erythema multiforme in patients treated with pregabalin (see 8.5 Post-Market Adverse Reactions, Serious Skin Reactions). Post-market reporting rate is generally accepted to be an underestimate due to under-reporting. Most of the reports were in patients taking concomitant medications also associated with the potential development of these serious skin reactions. Therefore, in most cases, causality in relation to pregabalin could not be clearly established. Patients should be advised that if they experience a skin rash, they should discontinue MAR-Pregabalin treatment and contact their physician for assessment and advice.
7.1 Special Populations
Renal
There have been reports of patients, with or without previous history, experiencing renal failure while receiving pregabalin alone or in combination with other medications. Discontinuation of pregabalin showed reversibility of this event in some cases (see 7 WARNINGS AND PRECAUTIONS, Renal; 8.5 Post-Market Adverse Reactions, Urinary and Renal Disorder; and 4.1 Dosing Consideration). Because pregabalin is eliminated primarily by renal excretion, the dose of pregabalin should be adjusted as noted for elderly patients or those with renal impairment (see 10.3 Pharmacokinetics, Elimination and 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment Based on Renal Function).
Adjustment of Dose in Renally-Impaired Patients
In patients with a medical history of significant renal insufficiency, daily dosages should be reduced accordingly (see 4.2 Recommended Dose and Dosage Adjustment, Table 1).
7.1.1 Pregnant Women
Pregabalin should not be used during pregnancy unless the benefit of the drug to the mother clearly outweighs the potential risk to the fetus. If women decide to become pregnant while taking pregabalin, the use of this product should be carefully re-evaluated. If therapy with pregabalin is considered necessary during pregnancy, the lowest possible therapeutic dose should be used.
Women of childbearing potential must use effective contraception during treatment with MAR-PREGABALIN.
Major congenital malformations
MAR-PREGABALIN use in the first-trimester of pregnancy can cause major birth defects in the unborn child.
Data from a Nordic observational study of more than 2700 pregnancies exposed to pregabalin in the first trimester showed a higher prevalence of major congenital malformations (MCM) among the pediatric population (live or stillborn) exposed to pregabalin compared to the unexposed population (5.9% vs. 4.1%).
In the Nordic study, the risk of MCM among the pediatric population exposed to pregabalin in the first trimester was slightly higher compared to the unexposed population (adjusted prevalence ratio and 95% confidence interval: 1.14 (0.96-1.35).
The analyses on specific malformations showed higher risks for malformations of the nervous system, the eye, orofacial clefts, urinary and genital malformations, but numbers were small and estimates imprecise.
Birth and postnatal neurodevelopmental outcomes
In the Nordic study, there was a significantly higher prevalence of stillbirth and “small for gestational age” in the pregabalin -exposed population compared to the unexposed population (adjusted prevalence ratio and 95% confidence interval: 1.72 (1.02-2.91) and 1.21 (1.01-1.44), respectively.
There were no statistically significant findings for low birth weight, preterm birth, low Apgar score, and microcephaly.
Pregnancy Registry
Patients should be encouraged to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry if they become pregnant. This registry is collecting information about the safety of anticonvulsant medications that can be taken by women during pregnancy to treat disorders such as epilepsy, mood disorder, and chronic pain. The primary goal is to determine the frequency of major malformations, such as heart defects, spina bifida and cleft lip, in the infants exposed during pregnancy to anticonvulsant drugs. To enroll, patients can call the toll - free number, 1-888-233-2334. Information on the registry can be also found at the website http://www.aedpregnancyregistry.org/ (see 7 WARNINGS AND PRECAUTIONS, General, and 7 WARNINGS AND PRECAUTIONS, Patient Counselling Information).
Labour and Delivery
The effects of pregabalin on labour and delivery in pregnant women are unknown. In the prenatal-postnatal study in rats, pregabalin prolonged gestation and induced dystocia at exposures ≥ 47 times the mean human exposure [AUC(0-24) of 123 mcg•hr/mL] at the maximum recommended clinical dose of 600 mg/day (see 16 NON- CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1.2 Breast-feeding
Pregabalin is excreted in the milk of lactating women. As the safety of pregabalin in infants is not known, breast-feeding is not recommended during treatment with pregabalin. A decision must be made whether to discontinue breast-feeding or to discontinue from pregabalin therapy taking into account the benefit of breast feeding for the child and the benefit of therapy for the women (see 16 NON- CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Patients should be advised to notify their physician if they are breast-feeding.
The pharmacokinetics of 150 mg pregabalin given every 12 hours (300 mg daily dose) was evaluated in 10 lactating women who were at least 12 weeks postpartum. Pregabalin was excreted into breast milk with average peak and steady-state concentrations approximately 53 and 76% of those in maternal plasma, respectively. The estimated average daily infant dose of pregabalin from breast milk (assuming mean milk consumption of 150 mL/kg/day) was 0.31 mg/kg/day, which on a mg/kg basis would be approximately 7% of the total maternal daily dose.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Of the 1831 patients who received pregabalin in neuropathic pain studies, 528 were 65 to 74 years of age, and 452 were 75 years of age or older. No significant differences in efficacy were observed between these patients and younger patients. Pregabalin oral clearance tended to decrease with increasing age. This decrease in pregabalin oral clearance is consistent with age-related decreases in creatinine clearance. Reduction of pregabalin dose may be required in patients who have age-related compromised renal function. In general, the incidence of adverse events did not increase with age.
8. ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In all controlled and uncontrolled trials during the pre-marketing development of pregabalin, more than 8666 patients have received pregabalin, with 83% of exposure at dosages of 300 mg/day or above and 32% at dosages of 600 mg/day or higher. Approximately 4010 patients had at least 6 months of exposure, 2415 had at least 1 year of exposure, and 939 had at least 2 years of exposure to pregabalin. In controlled trials, 1831 patients with neuropathic pain received pregabalin. In all controlled and uncontrolled studies in fibromyalgia, 3446 patients have received pregabalin doses of 150-600 mg/day. A total of 969 patients had at least 6 months of exposure and 440 patients had at least 1 year exposure to pregabalin. Doses above 600 mg/day have not been studied.
In a controlled study of neuropathic pain due to spinal cord injury, 137 patients were randomized to receive placebo (n = 67) or escalating doses (150-600 mg/day) of pregabalin, (n = 70). The controlled study was followed by an open-label trial in which 103 patients received pregabalin (150-600 mg/day). The median duration of therapy across the double-blind and open-label studies for those subjects treated in the open-label extension was 608 days (range 14-1248). Sixty-nine (67%) subjects received at least 1 year of open-label pregabalin and 31 (30.1%) received at least 2 years of open-label pregabalin.
Most Common Adverse Events in All Pre-marketing Controlled Clinical Studies of Neuropathic Pain
The most commonly observed adverse events (≥ 5% and twice the rate of that seen in placebo) in pregabalin-treated patients in pre-marketing studies were: dizziness, somnolence, peripheral edema, and dry mouth. Adverse events were usually mild to moderate in intensity.
Discontinuation Due to Adverse Events in Pre-marketing Controlled Clinical Studies
In all pre-marketing controlled studies, the discontinuation rate due to adverse events was 14% for patients receiving pregabalin and 7% for patients receiving placebo. The most common reasons for discontinuation due to adverse events (≥ 2%) in the pregabalin treatment groups were dizziness and somnolence. Other adverse events that led to withdrawal more frequently in the pregabalin group than the placebo group were ataxia (1%), and asthenia, confusion, headache and nausea (< 1% each).
In pre-marketing controlled neuropathic pain studies, the discontinuation rate due to adverse events was 11% for pregabalin and 5% for placebo. The most common reasons for discontinuation due to adverse events (≥ 2%) in the pregabalin treatment groups were dizziness and somnolence. Other adverse events that led to withdrawal more frequently in the pregabalin group than the placebo group were confusion (1%) and asthenia, peripheral edema and ataxia (< 1% each).
Incidence of Adverse Events in Pre-marketing Controlled Clinical Studies of Neuropathic Pain
In summaries of adverse events, investigator's terms for individual adverse events have been grouped into a smaller number of standardized categories using the COSTART IV dictionary. The prescriber should be aware that the percentages in Table 2 through Table 9 cannot be used to predict the frequency of adverse events in the course of usual medical practice where patient characteristics and other factors may differ from those prevailing during clinical studies. Similarly, the cited frequencies cannot be directly compared with figures obtained from other clinical investigations involving different treatments, uses or investigators. An inspection of these frequencies, however, does provide the prescriber with one basis to estimate the relative contribution of drug and non-drug factors to the adverse event incidences in the population studied.
Adverse Events From Pre-marketing Controlled Clinical Studies of Neuropathic Pain Diabetic Peripheral Neuropathy
Table 2 lists all adverse events, regardless of causality, occurring in ≥ 2% of patients with neuropathic pain associated with diabetic peripheral neuropathy receiving pregabalin for at least one of the pregabalin groups, and for which the incidence was greater than in the placebo group. A majority of pregabalin-treated patients in these studies had adverse events with a maximum intensity of mild or moderate. In these studies, 979 patients received pregabalin and
459 patients received placebo for up to 13 weeks.
Table 2. Incidence (%) of Treatment-Emergent Adverse Events in Placebo-Controlled Studies in Neuropathic Pain Associated with Diabetic Peripheral Neuropathy (Events in at Least 2% of Patients Receiving Pregabalin and More Frequent Than in Placebo-Treated Patients)
Body System Preferred Term | Placebo (n = 459) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
75 (n = 77) % | 150 (n = 212) % | 300 (n = 321) % | 600 (n = 369) % | |||
| Body as a whole | ||||||
| Infection | 6.1 | 3.9 | 7.5 | 8.4 | 4.6 | |
| Asthenia | 2.4 | 3.9 | 1.9 | 4.4 | 7.3 | |
| Pain | 3.9 | 5.2 | 4.2 | 2.5 | 4.9 | |
| Accidental injury | 2.8 | 5.2 | 2.4 | 2.2 | 5.7 | |
| Back pain | 0.4 | 0.0 | 2.4 | 1.2 | 1.9 | |
| Chest pain | 1.1 | 3.9 | 1.4 | 1.2 | 1.6 | |
| Face edema | 0.4 | 0.0 | 0.9 | 0.9 | 2.2 | |
| Digestive system | ||||||
| Dry mouth | 1.1 | 2.6 | 1.9 | 4.7 | 6.5 | |
| Constipation | 1.5 | 0.0 | 2.4 | 3.7 | 6.0 | |
| Diarrhea | 4.8 | 5.2 | 2.8 | 1.9 | 3.0 | |
| Flatulence | 1.3 | 2.6 | 0 | 2.2 | 2.7 | |
| Vomiting | 1.5 | 1.3 | 0.9 | 2.2 | 1.1 | |
| Hemic and lymphatic system | ||||||
| Ecchymosis | 0.2 | 2.6 | 0.5 | 0.6 | 0.3 | |
| Metabolic and nutritional disorders | ||||||
| Peripheral edema | 2.4 | 3.9 | 6.1 | 9.3 | 12.5 | |
| Weight gain | 0.4 | 0.0 | 4.2 | 3.7 | 6.2 | |
| Edema | 0.0 | 0.0 | 1.9 | 4.0 | 1.9 | |
| Hypoglycemia | 1.1 | 1.3 | 3.3 | 1.6 | 1.1 | |
| Nervous system | ||||||
| Dizziness | 4.6 | 7.8 | 9.0 | 23.1 | 29.0 | |
| Somnolence | 2.6 | 3.9 | 6.1 | 13.1 | 16.3 | |
| Neuropathy | 3.5 | 9.1 | 1.9 | 2.2 | 5.4 | |
| Ataxia | 1.3 | 6.5 | 0.9 | 2.2 | 4.3 | |
Body System Preferred Term | Placebo (n = 459) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
75 (n = 77) % | 150 (n = 212) % | 300 (n = 321) % | 600 (n = 369) % | |||
| Vertigo | 1.1 | 1.3 | 1.9 | 2.5 | 3.5 | |
| Confusion | 0.7 | 0.0 | 1.4 | 2.2 | 3.3 | |
| Euphoria | 0.0 | 0.0 | 0.5 | 3.4 | 1.6 | |
| Thinking abnormala | 0.0 | 1.3 | 0.0 | 0.9 | 3.0 | |
| Abnormal gait | 0.0 | 1.3 | 0.0 | 0.6 | 2.7 | |
| Reflexes decreased | 1.7 | 3.9 | 0.5 | 1.2 | 1.4 | |
| Amnesia | 0.2 | 2.6 | 0.9 | 0.0 | 2.2 | |
| Hypesthesia | 0.7 | 2.6 | 0.0 | 0.0 | 0.8 | |
| Hyperalgesia | 0.2 | 2.6 | 0.0 | 0.0 | 0.3 | |
| Respiratory system | ||||||
| Dyspnea | 0.7 | 2.6 | 0.0 | 1.9 | 1.9 | |
| Skin and appendages | ||||||
| Pruritus | 1.3 | 2.6 | 0.0 | 0.9 | 0.0 | |
| Special senses | ||||||
| Blurred visionb | 1.5 | 2.6 | 1.4 | 2.8 | 5.7 | |
| Conjunctivitis | 0.2 | 2.6 | 1.4 | 0.6 | 0.3 | |
a Thinking abnormal primarily consists of events related to difficulty with concentration/attention but also includes events related to cognition and language problems and slow thinking.
b Investigator term; summary level term is amblyopia.
Discontinuation in Controlled Clinical Studies of Diabetic Peripheral Neuropathy
Approximately 9% of patients receiving pregabalin and 4% receiving placebo discontinued from controlled diabetic peripheral neuropathy studies due to adverse events. The adverse events most commonly leading to discontinuation are presented in Table 3.
Table 3. Adverse Events Most Frequently (≥ 2% of patients) Leading to Discontinuation in Placebo-Controlled Studies in Patients With Neuropathic Pain Associated with Diabetic Peripheral Neuropathy
| Number (%) of Patients | ||||||
|---|---|---|---|---|---|---|
COSTART Preferred Term | Placebo (n = 459) | Pregabalin (mg/day) | ||||
75 (n = 77) | 150 (n = 212) | 300 (n = 321) | 600 (n = 369) | |||
| Dizziness | 2 (0.4) | 0 (0.0) | 3 (1.4) | 6 (1.9) | 21 (5.7) | |
| Number (%) of Patients | ||||||
|---|---|---|---|---|---|---|
COSTART Preferred Term | Placebo (n = 459) | Pregabalin (mg/day) | ||||
75 (n = 77) | 150 (n = 212) | 300 (n = 321) | 600 (n = 369) | |||
| Somnolence | 0 (0.0) | 0 (0.0) | 0 (0.0) | 5 (1.6) | 15 (4.1) | |
Post-herpetic Neuralgia
Table 4 lists all adverse events, regardless of causality, occurring in ≥ 2% of patients with neuropathic pain associated with postherpetic neuralgia receiving pregabalin for at least one of the pregabalin groups, and for which the incidence was greater than in the placebo group. A majority of pregabalin-treated patients in these studies had adverse events with a maximum intensity of mild or moderate. In these studies, 852 patients received pregabalin and 398 patients received placebo for up to 13 weeks.
Table 4. Incidence (%) of Treatment-Emergent Adverse Events in Placebo-Controlled Studies in Neuropathic Pain Associated with Postherpetic Neuralgia (Events in at Least 2% of Patients Receiving Pregabalin and More Frequent Than in Placebo-Treated Patients)
Body System Preferred Term | Placebo (n = 398) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
75 (n = 84) % | 150 (n = 302) % | 300 (n = 312) % | 600 (n = 154) % | |||
| Body as a whole | ||||||
| Infection | 3.5 | 14.3 | 8.3 | 6.4 | 2.6 | |
| Headache | 5.3 | 4.8 | 8.9 | 4.5 | 8.4 | |
| Pain | 3.8 | 4.8 | 4.3 | 5.4 | 4.5 | |
| Asthenia | 4.0 | 3.6 | 5.0 | 2.6 | 5.2 | |
| Accidental injury | 1.5 | 3.6 | 2.6 | 3.2 | 5.2 | |
| Flu syndrome | 1.3 | 1.2 | 1.7 | 2.2 | 1.3 | |
| Face edema | 0.8 | 0.0 | 1.7 | 1.3 | 3.2 | |
| Malaise | 1.0 | 2.4 | 0.3 | 0.6 | 0.0 | |
| Cardiovascular system | ||||||
| Vasodilatation | 1.3 | 2.4 | 1.0 | 0.6 | 0.0 | |
| Digestive system | ||||||
| Dry mouth | 2.8 | 7.1 | 7.0 | 6.1 | 14.9 | |
| Constipation | 2.3 | 3.6 | 4.6 | 5.4 | 5.2 | |
| Diarrhea | 4.0 | 2.4 | 4.3 | 3.5 | 4.5 | |
| Flatulence | 1.0 | 2.4 | 1.3 | 1.6 | 3.2 | |
Body System Preferred Term | Placebo (n = 398) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
75 (n = 84) % | 150 (n = 302) % | 300 (n = 312) % | 600 (n = 154) % | |||
| Vomiting | 0.8 | 1.2 | 0.7 | 2.9 | 2.6 | |
| Metabolic and nutritional disorders | ||||||
| Peripheral edema | 3.5 | 0.0 | 7.9 | 15.7 | 16.2 | |
| Weight gain | 0.3 | 1.2 | 1.7 | 5.4 | 6.5 | |
| Edema | 1.3 | 0.0 | 1.0 | 2.2 | 5.8 | |
| Hyperglycemia | 0.8 | 2.4 | 0.3 | 0.0 | 0.0 | |
| Nervous system | ||||||
| Dizziness | 9.3 | 10.7 | 17.9 | 31.4 | 37.0 | |
| Somnolence | 5.3 | 8.3 | 12.3 | 17.9 | 24.7 | |
| Ataxia | 0.5 | 1.2 | 2.0 | 5.4 | 9.1 | |
| Abnormal gait | 0.5 | 0.0 | 2.0 | 3.8 | 7.8 | |
| Confusion | 0.3 | 1.2 | 2.3 | 2.9 | 6.5 | |
| Thinking abnormala | 1.5 | 0.0 | 1.7 | 1.3 | 5.8 | |
| Incoordination | 0.0 | 2.4 | 1.7 | 1.3 | 2.6 | |
| Amnesia | 0.0 | 0.0 | 1.0 | 1.3 | 3.9 | |
| Speech disorder | 0.0 | 0.0 | 0.3 | 1.3 | 3.2 | |
| Insomnia | 1.8 | 0.0 | 0.7 | 2.2 | 0.0 | |
| Euphoria | 0.0 | 2.4 | 0.0 | 1.3 | 1.3 | |
| Nervousness | 0.5 | 0.0 | 1.0 | 0.3 | 2.6 | |
| Tremor | 1.5 | 1.2 | 0.0 | 1.0 | 2.6 | |
| Hallucinations | 0.0 | 0.0 | 0.3 | 0.3 | 3.2 | |
| Hyperesthesia | 0.3 | 2.4 | 0.3 | 0.0 | 1.3 | |
| Respiratory system | ||||||
| Bronchitis | 0.8 | 0.0 | 1.3 | 1.0 | 2.6 | |
| Pharyngitis | 0.8 | 0.0 | 2.6 | 0.6 | 0.6 | |
| Rhinitis | 1.8 | 1.2 | 0.7 | 0.6 | 3.2 | |
| Skin and appendages | ||||||
| Rash | 3.0 | 2.4 | 2.0 | 2.9 | 5.2 | |
| Special senses | ||||||
Body System Preferred Term | Placebo (n = 398) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
75 (n = 84) % | 150 (n = 302) % | 300 (n = 312) % | 600 (n = 154) % | |||
| Blurred visionb | 2.5 | 1.2 | 5.0 | 5.1 | 9.1 | |
| Diplopia | 0.0 | 0.0 | 1.7 | 1.9 | 3.9 | |
| Abnormal vision | 0.3 | 0.0 | 1.0 | 1.6 | 5.2 | |
| Urogenital system | ||||||
| Urinary tract infection | 1.5 | 0.0 | 2.3 | 1.6 | 3.2 | |
a Thinking abnormal primarily consists of events related to difficulty with concentration/attention but also includes events related to cognition and language problems and slow thinking.
b Investigator term; summary level term is amblyopia.
Discontinuation in Controlled Clinical Studies of Postherpetic Neuralgia
Approximately 14% of patients receiving pregabalin and 7% receiving placebo discontinued from controlled postherpetic neuralgia studies due to adverse events. The adverse events most commonly leading to discontinuation are presented in Table 5.
Table 5. Adverse Events Most Frequently (≥ 2% of patients) Leading to Discontinuation in Placebo-Controlled Studies in Patients With Neuropathic Pain Associated with Postherpetic Neuralgia
| Number (%) of Patients | ||||||
|---|---|---|---|---|---|---|
COSTART Preferred Term | Placebo (n = 398) | Pregabalin (mg/day) | ||||
75 (n = 84) | 150 (n = 302) | 300 (n = 312) | 600 (n = 154) | |||
| Dizziness | 3 (0.8) | 0 (0.0) | 11 (3.6) | 12 (3.8) | 12 (7.8) | |
| Somnolence | 1 (0.3) | 0 (0.0) | 6 (2.0) | 12 (3.8) | 10 (6.5) | |
| Confusion | 1 (0.3) | 0 (0.0) | 2 (0.7) | 5 (1.6) | 8 (5.2) | |
| Peripheral edema | 1 (0.3) | 0 (0.0) | 2 (0.7) | 5 (1.6) | 5 (3.2) | |
| Ataxia | 0 (0.0) | 0 (0.0) | 1 (0.3) | 5 (1.6) | 4 (2.6) | |
| Abnormal gait | 0 (0.0) | 0 (0.0) | 0 (0.0) | 4 (1.3) | 4 (2.6) | |
| Hallucinations | 0 (0.0) | 0 (0.0) | 0 (0.0) | 1 (0.3) | 4 (2.6) | |
| Dry mouth | 1 (0.3) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 4 (2.6) | |
Incidence of Most Common Dose-Related Treatment-Emergent Adverse Events
Most common dose-related treatment-emergent adverse events are presented in Table 6 (diabetic peripheral neuropathy), Table 7 (postherpetic neuralgia), and Table 8 (fibromyalgia).
Table 6. Incidence (%) of Most Common Dose-Related Treatment-Emergent Adverse Events in Placebo-Controlled Studies in Neuropathic Pain Associated with Diabetic Peripheral Neuropathy
| Adverse Event Preferred Term | Placebo (n = 459) % | Pregabalin (mg/day) | |||||
|---|---|---|---|---|---|---|---|
75 (n =77) % | 150 (n = 212) % | 300 (n = 321) % | 600 (n = 369) % | ||||
| Dizziness | 4.6 | 7.8 | 9.0 | 23.1 | 29.0 | ||
| Somnolence | 2.6 | 3.9 | 6.1 | 13.1 | 16.3 | ||
| Peripheral edema | 2.4 | 3.9 | 6.1 | 9.3 | 12.5 | ||
| Asthenia | 2.4 | 3.9 | 1.9 | 4.4 | 7.3 | ||
| Dry mouth | 1.1 | 2.6 | 1.9 | 4.7 | 6.5 | ||
| Weight gain | 0.4 | 0.0 | 4.2 | 3.7 | 6.2 | ||
| Constipation | 1.5 | 0.0 | 2.4 | 3.7 | 6.0 | ||
| Blurred visiona | 1.5 | 2.6 | 1.4 | 2.8 | 5.7 | ||
a Investigator term; summary level term is amblyopia.
Table 7. Incidence (%) of Most Common Dose-Related Treatment-Emergent Adverse Events in Placebo-Controlled Studies in Neuropathic Pain Associated with Postherpetic Neuralgia
| Adverse Event Preferred Term | Placebo (n = 398) % | Pregabalin (mg/day) | |||
|---|---|---|---|---|---|
75 (n = 84) % | 150 (n = 302) % | 300 (n = 312) % | 600 (n = 154) % | ||
| Dizziness | 9.3 | 10.7 | 17.9 | 31.4 | 37.0 |
| Somnolence | 5.3 | 8.3 | 12.3 | 17.9 | 24.7 |
| Peripheral edema | 3.5 | 0.0 | 7.9 | 15.7 | 16.2 |
| Dry mouth | 2.8 | 7.1 | 7.0 | 6.1 | 14.9 |
| Blurred visiona | 2.5 | 1.2 | 5.0 | 5.1 | 9.1 |
| Ataxia | 0.5 | 1.2 | 2.0 | 5.4 | 9.1 |
| Weight gain | 0.3 | 1.2 | 1.7 | 5.4 | 6.5 |
| Abnormal gait | 0.5 | 0.0 | 2.0 | 3.8 | 7.8 |
a Investigator term; summary level term is amblyopia.
Table 8. Incidence (%) of Most Common Dose-Related Treatment-Emergent Adverse Events in Placebo-Controlled Studies in Pain Associated with Fibromyalgia
System Organ Class and Preferred Term (MedDRA version 10.1) | Placebo (n = 689) % | Pregabalin (mg/day) | |||
|---|---|---|---|---|---|
150 (n = 132) % | 300 (n = 685) % | 450 (n = 687) % | 600 (n = 564) % | ||
| Dizziness | 10.4 | 22.7 | 32.6 | 42.5 | 46.5 |
| Somnolence | 4.6 | 12.9 | 18.5 | 19.9 | 20.7 |
| Weight increased | 2.5 | 7.6 | 11.1 | 10.0 | 13.7 |
| Peripheral edema | 2.5 | 5.3 | 6.7 | 6.4 | 10.8 |
| Dry mouth | 1.7 | 6.8 | 6.7 | 9.2 | 9.4 |
| Constipation | 2.8 | 3.8 | 5.8 | 6.8 | 9.2 |
| Fatigue | 5.4 | 4.5 | 7.2 | 8.4 | 8.2 |
| Balance disorder | 0.1 | 1.5 | 3.2 | 4.9 | 6.9 |
| Disturbance in attention | 1.3 | 3.8 | 4.4 | 6.4 | 6.9 |
| Increased appetite | 1.3 | 3.8 | 3.4 | 4.5 | 5.5 |
| Euphoria | 0.9 | 1.5 | 4.1 | 4.8 | 5.1 |
Adverse Events From a Controlled Clinical Study in Neuropathic Pain Associated With Spinal Cord Injury
The most commonly observed treatment-related adverse events (≥ 5% and twice the rate of that seen in placebo) in pregabalin-treated patients were: somnolence, dizziness, asthenia, dry mouth, edema, myasthenia, constipation, thinking abnormal, amblyopia, and amnesia.
Adverse events were usually mild to moderate in intensity.
Table 9 lists all adverse events, regardless of causality, occurring in ≥ 2% of patients receiving pregabalin and for which the incidence was greater than in the placebo group. A majority of pregabalin-treated patients had adverse events with a maximum intensity of mild or moderate. In this study, 70 patients received pregabalin and 67 patients received placebo for up to 12 weeks.
Table 9. Incidence (%) of Treatment-Emergent Adverse Events in a Placebo-Controlled Study in Neuropathic Pain Associated With Spinal Cord Injury (Events in at Least 2% of Patients Receiving Pregabalin and More Frequent Than in Placebo-Treated Patients)
| Body System Preferred Term | Placebo n = 67 % | Pregabalin (150 - 600 mg/day) n = 70 % | |
|---|---|---|---|
| Body as a whole | |||
| Asthenia | 6.0 | 15.7 | |
| Infection | 6.0 | 8.6 | |
| Body System Preferred Term | Placebo n = 67 % | Pregabalin (150 - 600 mg/day) n = 70 % | |
|---|---|---|---|
| Abdomen enlarged | 0.0 | 4.3 | |
| Pain | 1.5 | 4.3 | |
| Back pain | 1.5 | 2.9 | |
| Cellulitis | 0.0 | 2.9 | |
| Flu syndrome | 1.5 | 2.9 | |
| Neck pain | 1.5 | 2.9 | |
| Cardiovascular system | |||
| Hypotension | 0.0 | 2.9 | |
| Digestive system | |||
| Dry mouth | 3.0 | 15.7 | |
| Constipation | 6.0 | 12.9 | |
| Gastroenteritis | 0.0 | 2.9 | |
| Increased appetite | 0.0 | 2.9 | |
| Metabolic and nutritional disorders | |||
| Edema | 0.0 | 12.9 | |
| Peripheral edema | 6.0 | 10.0 | |
| Weight gain | 0.0 | 4.3 | |
| Musculoskeletal system | |||
| Myasthenia | 4.5 | 8.6 | |
| Joint disorder | 0.0 | 2.9 | |
| Nervous system | |||
| Somnolence | 9.0 | 41.4 | |
| Dizziness | 9.0 | 24.3 | |
| Amnesia | 3.0 | 10.0 | |
| Thinking abnormala | 1.5 | 8.6 | |
| Paresthesia | 1.5 | 5.7 | |
| Euphoria | 0.0 | 4.3 | |
| Speech disorder | 1.5 | 4.3 | |
| Twitching | 0.0 | 4.3 | |
| Body System Preferred Term | Placebo n = 67 % | Pregabalin (150 - 600 mg/day) n = 70 % | |
|---|---|---|---|
| Withdrawal syndrome | 0.0 | 4.3 | |
| Skin and appendages | |||
| Skin ulcer | 1.5 | 4.3 | |
| Alopecia | 0.0 | 2.9 | |
| Vesiculobullous rash | 0.0 | 2.9 | |
| Special senses | |||
| Blurred visionb | 3.0 | 8.6 | |
| Diplopia | 1.5 | 2.9 | |
| Tinnitus | 0.0 | 2.9 | |
| Urogenital system | |||
| Urinary incontinence | 3.0 | 5.7 | |
a Thinking abnormal primarily consists of events related to difficulty with concentration/attention but also includes events related to cognition and language problems and slow thinking.
b Investigator term; summary level term is amblyopia.
Discontinuation in a Controlled Clinical Study in Neuropathic Pain Associated With Spinal Cord Injury
Approximately 21% of patients receiving pregabalin and 13% receiving placebo discontinued due to adverse events. The adverse events most commonly leading to discontinuation are presented in Table 10.
Table 10. Adverse Events Most Frequently (≥ 2% of patients) Leading to Discontinuation in a Placebo-Controlled Study in Patients With Neuropathic Pain Associated with Spinal Cord Injury
| Number (%) of Patients | ||
|---|---|---|
COSTART Preferred Term | Placebo (n = 67) | Pregabalin 150 – 600 mg/day (n = 70) |
| Somnolence | 0 (0.0) | 4 (5.7) |
| Edema | 0 (0.0) | 4 (5.7) |
| Asthenia | 0 (0.0) | 3 (4.3) |
Overall, the most frequent treatment-related adverse events in the open-label study were related to the nervous system and included: somnolence (18.4%), dizziness (16.5%), and insomnia (10.7%). Other frequent treatment-related adverse events included: asthenia (12.6%), nausea (11.7%), and constipation (10.7%).
Most Common Adverse Events in Controlled Clinical Studies in Fibromyalgia
The most commonly observed treatment-related adverse events (≥ 5% and twice the rate of that seen in placebo) in pregabalin-treated patients were: dizziness (37.5%), somnolence (18.6%), weight gain (10.6%), dry mouth (7.9%), blurred vision (6.7%), peripheral edema (6.1%), constipation (5.8%), and disturbance in attention (5.3%). Adverse events were usually mild to moderate in intensity.
Adverse Events from Controlled Clinical Studies in Fibromyalgia
Table 11 lists all adverse events occurring in ≥ 2% of patients receiving pregabalin and for which the incidence was greater than in the placebo group. A majority of pregabalin-treated patients in these studies had adverse events with mild or moderate intensity. There was a dose-related increase in the incidence of adverse events (see Table 8). Severe adverse events occurred at roughly the same rate in low versus high doses of pregabalin.
Table 11. Incidence (%) of Treatment-Emergent Adverse Events in Controlled Fibromyalgia Studies (in at Least 2% of Pregabalin-Treated Patients and More Frequent Than in Placebo- Treated Patients)
System Organ Class and Preferred Term (MedDRA version 10.1) | Placebo (n = 689) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
150 (n = 132) % | 300 (n = 685) % | 450 (n = 687) % | 600 (n = 564) % | |||
| Ear and labyrinth disorders | ||||||
| Vertigo | 0.9 | 1.5 | 3.1 | 3.2 | 3.5 | |
| Eye disorders | ||||||
| Blurred visiona | 1.0 | 8.3 | 5.8 | 6.4 | 10.1 | |
| Gastrointestinal disorders | ||||||
| Dry mouth | 1.7 | 6.8 | 6.7 | 9.2 | 9.4 | |
| Constipation | 2.8 | 3.8 | 5.8 | 6.8 | 9.2 | |
| Abdominal distention | 1.5 | 2.3 | 2.2 | 1.9 | 2.0 | |
| Flatulence | 1.0 | 0.8 | 0.9 | 2.0 | 2.3 | |
| General disorders and administration site conditions | ||||||
| Fatigue | 5.4 | 4.5 | 7.2 | 8.4 | 8.2 | |
| Peripheral edema | 2.5 | 5.3 | 6.7 | 6.4 | 10.8 | |
| Feeling abnormal | 0.3 | 0.8 | 1.9 | 1.9 | 2.0 | |
| Feeling drunk | 0 | 0.8 | 2.3 | 1.5 | 2.1 | |
System Organ Class and Preferred Term (MedDRA version 10.1) | Placebo (n = 689) % | Pregabalin (mg/day) | ||||
|---|---|---|---|---|---|---|
150 (n = 132) % | 300 (n = 685) % | 450 (n = 687) % | 600 (n = 564) % | |||
| Infections and infestations | ||||||
| Sinusitis | 3.0 | 3.8 | 3.6 | 5.2 | 4.1 | |
| Investigations | ||||||
| Weight increased | 2.5 | 7.6 | 11.1 | 10.9 | 13.7 | |
| Metabolism and nutritional disorders | ||||||
| Increased appetite | 1.3 | 3.8 | 3.4 | 4.5 | 5.5 | |
| Fluid retention | 0.7 | 1.5 | 2.2 | 2.0 | 2.0 | |
| Musculoskeletal and connective tissue disorders | ||||||
| Arthralgia | 2.5 | 3.8 | 3.6 | 3.2 | 4.6 | |
| Muscle spasm | 1.9 | 2.3 | 3.4 | 3.3 | 3.2 | |
| Nervous system disorders | ||||||
| Dizziness | 10.4 | 22.7 | 32.6 | 42.5 | 46.5 | |
| Somnolence | 4.6 | 12.9 | 18.5 | 19.9 | 20.7 | |
| Disturbance in attention | 1.3 | 3.8 | 4.4 | 6.4 | 6.9 | |
| Balance Disorder | 0.1 | 1.5 | 3.2 | 4.9 | 6.9 | |
| Memory Impairment | 0.6 | 0.8 | 2.6 | 3.5 | 3.5 | |
| Hypoesthesia | 0.6 | 1.5 | 2.0 | 2.8 | 2.3 | |
| Tremor | 0.6 | 0 | 0.6 | 2.9 | 3.0 | |
| Lethargy | 0.4 | 2.3 | 1.3 | 0.7 | 1.4 | |
| Psychiatric disorders | ||||||
| Euphoria | 0.9 | 1.5 | 4.1 | 4.8 | 5.1 | |
| Anxiety | 0.9 | 1.5 | 1.9 | 2.5 | 1.8 | |
| Confusion | 0.1 | 0 | 2.0 | 1.9 | 2.7 | |
a Investigator term; summary level term is amblyopia.
Discontinuation Due to Adverse Events in Controlled Clinical Studies in Fibromyalgia
Approximately 20% of patients receiving pregabalin and 11% receiving placebo discontinued due to adverse events. The adverse events most commonly leading to discontinuation were dizziness (6.1%) and somnolence (3.3%) as presented in Table 12. Other events leading to discontinuation in clinical trials of fibromyalgia included weight gain (1.1%), vision blurred (0.8%)
and peripheral edema (0.6%). There was a dose-dependent increase in rate of discontinuation due to adverse events.
Table 12. Adverse Events Most Frequently (≥ 2% of patients) Leading to Discontinuation in Placebo-Controlled Studies in Patients With Pain Associated with Fibromyalgia
| Number (%) of Patients | |||||
|---|---|---|---|---|---|
| System Organ Class and Preferred Term (MedDRA version 10.1) | Placebo (n = 689) | Pregabalin (mg/day) | |||
150 (n =132) | 300 (n = 675) | 450 (n = 687) | 600 (n = 564) | ||
| Dizziness | 0.4% | 1.5% | 4.1% | 6.6% | 9.2% |
| Somnolence | 0.1% | 0.8% | 2.9% | 3.2% | 4.6% |
Adverse Events Following Abrupt or Rapid Discontinuation
Following abrupt or rapid discontinuation of pregabalin, some patients reported symptoms including insomnia, nausea, headache, anxiety, hyperhidrosis, and diarrhea. Pregabalin should be tapered gradually over a minimum of one week rather than discontinued abruptly (see 4.2.1 Discontinuing Treatment).
In controlled clinical studies in over 5500 patients, 4% of pregabalin -treated patients and 1% of placebo-treated patients overall reported euphoria as an adverse event.(see 4.2.1 Discontinuing Treatment; see 7 WARNINGS AND PRECAUTIONS, Dependence, Tolerance and/or Abuse Liability).
Other Events Observed During the Premarketing Evaluation of MAR-PREGABALIN
Following is a list of treatment-emergent adverse events reported during premarketing assessment of pregabalin in clinical trials (over 8600 adult subjects) except those already listed in the previous tables or elsewhere in labeling. In the tabulations that follow, a COSTART-based dictionary of terminology has been used to classify reported adverse events. The frequencies presented, therefore, represent the proportion of the over 8600 adult individuals exposed to multiple doses of pregabalin who experienced an event of the type cited on at least 1 occasion while receiving pregabalin. It is important to emphasize that although the events reported occurred during treatment with pregabalin, they were not necessarily caused by it.
8.3 Less Common Clinical Trial `Adverse Reactions (< 2%)
Events are further categorized by body system and listed in order of decreasing frequency according to the following definitions: frequent adverse events are those occurring on 1 or more occasions in at least 1/100 patients; infrequent adverse events are those occurring in 1/100 to 1/1000 patients; rare events are those occurring in fewer than 1/1000 patients.
| Body System | Adverse Events |
|---|---|
| Body as a whole | |
| Body System | Adverse Events |
|---|---|
| Frequent | Flu syndrome, back pain, allergic reaction, fever, generalized edema |
| Infrequent | Neck pain, neoplasm, cellulitis, cyst, chills, malaise, overdose, moniliasis, hernia, viral infection, photosensitivity reaction, pelvic pain, abdomen enlarged, abscess, neck rigidity, lab test abnormal, drug level increased, carcinoma, sepsis, suicide attempt, reaction unevaluable |
| Rare | Infection fungal, unexpected benefit, chills and fever, body odor, drug level decreased, halitosis, hangover effect, injection site reaction, hormone level altered, hypothermia, infection bacterial, injection site hemorrhage, intentional overdose, mucous membrane disorder, accidental overdose, adenoma, anaphylactoid reaction, ascites, chest pain substernal, death, sarcoidosis, sudden death, immune system disorder, increased drug effect, injection site pain, Lupus Erythematosus syndrome, medication error, sarcoma, shock, tolerance decreased |
| Cardiovascular | |
| Frequent | Hypertension, vasodilatation |
| Infrequent | Palpitation, migraine, tachycardia, peripheral vascular disorder, electrocardiogram abnormal, cardiovascular disorder, angina pectoris, congestive heart failure, hemorrhage, myocardial infarct, hypotension, postural hypotension, ventricular extrasystoles, atrial fibrillation, coronary artery disorder, bradycardia, cerebrovascular accident, arrhythmia, cerebral ischemia, vascular disorder, sinus bradycardia, myocardial ischemia, bundle branch block, AV block first degree, arteriosclerosis, deep thrombophlebitis, phlebitis, arterial anomaly, heart failure, pulmonary embolus, retinal vascular disorder, varicose vein |
| Rare | Heart arrest, vascular anomaly, occlusion, supraventricular tachycardia, atrial arrhythmia, atrial flutter, cerebral infarct, coronary occlusion, thrombophlebitis, thrombosis, cardiomegaly, extrasystoles, pallor, AV block, AV block second degree, cardiomyopathy, peripheral gangrene, QT interval prolonged, retinal artery occlusion, supraventricular extrasystoles, cerebral hemorrhage, digitalis intoxication, ventricular arrhythmia, aortic stenosis, bigeminy, cerebrovascular disorder, left heart failure, ventricular tachycardia, AV block complete, carotid occlusion, carotid thrombosis, cor-pulmonale, embolus lower extremity, endocarditis, heart block, increased capillary fragility, intracranial aneurysm, nodal tachycardia, QT interval shortened, retinal vein thrombosis, ST elevated, T inverted, vascular headache, vasculitis |
| Digestive system | |
| Frequent | Nausea, diarrhea, anorexia, gastrointestinal disorder |
| Infrequent | Gastroenteritis, tooth disorder, periodontal abscess, colitis, gastritis, liver function tests abnormal, increased salivation, thirst, nausea and vomiting, rectal disorder, gingivitis, dysphagia, stomatitis, mouth ulceration, cholelithiasis, rectal hemorrhage, gastrointestinal hemorrhage, glossitis, tooth caries, abnormal stools, cholecystitis, melena, oral moniliasis, esophagitis, tongue disorder, cheilitis, tongue edema |
| Body System | Adverse Events |
|---|---|
| Rare | Eructation, pancreatitis, stomach ulcer, ulcerative stomatitis, esophageal stenosis, fecal incontinence, gum hemorrhage, intestinal obstruction, enteritis, peptic ulcer, enterocolitis, gum hyperplasia, hepatomegaly, liver fatty deposit, tenesmus, biliary pain, fecal impaction, jaundice, periodontitis, ulcerative colitis, aphthous stomatitis, cholestatic jaundice, gastrointestinal carcinoma, hemorrhagic gastritis, hepatitis, liver tenderness, nausea, vomiting and diarrhea, salivary gland enlargement, stomach atony, bloody diarrhea, cardiospasm, duodenal ulcer, gamma glutamyl transpeptidase increased, hematemesis, hepatoma, intestinal perforation, intestinal stenosis, intestinal ulcer, leukoplakia of mouth, necrotizing pancreatitis, pancreas disorder, pseudomembranous colitis, sialadenitis, stomach ulcer hemorrhage, tongue discoloration |
| Endocrine system | |
| Infrequent | Diabetes mellitus, hypothyroidism |
| Rare | Goiter, prolactin increased, thyroid disorder, gonadotropic follicle stim hormone increase, hyperthyroidism, thyroiditis, adrenal insufficiency, parathyroid disorder, thyroid carcinoma, thyroid neoplasia, virilism |
| Hemic and lymphatic | |
| Infrequent | Anemia, leukopenia, thrombocytopenia, lymphadenopathy, hypochromic anemia, leukocytosis, eosinophilia |
| Rare | Lymphocytosis, petechia, iron deficiency anemia, cyanosis, lymphedema, polycythemia, lymphoma like reaction, megaloblastic anemia, splenomegaly, purpura, thrombocythemia, thrombocytopenic purpura, chronic leukemia, coagulation disorder, erythrocytes abnormal, leukemoid reaction, lymphangitis, macrocytic anemia, neutropenia, pancytopenia, prothrombin decreased, rupture of spleen, sedimentation rate increased |
| Metabolic and nutritional | |
| Infrequent | Hyperglycemia, SGPT increased, hypoglycemia, hypokalemia, hypercholesteremia, SGOT increased, weight loss, hyperlipemia, amylase increased, hyperuricemia, alkaline phosphatase increased, creatinine increased, hyponatremia, gout, dehydration, BUN increased, healing abnormal |
| Rare | Hypercalcemia, hyperkalemia, hypocalcemia, bilirubinemia, alcohol intolerance, hypoglycemic reaction, ketosis, calcium disorder, hypochloremia, hypomagnesemia, hypoproteinemia, NPN increased, uremia, acidosis, avitaminosis, enzymatic abnormality, gamma globulins increased, hypernatremia, hypophosphatemia, lactic acidosis, obesity |
| Musculoskeletal system | |
| Frequent | Arthralgia, myalgia, arthritis, leg cramps, myasthenia |
| Infrequent | Tendon disorder, arthrosis, joint disorder, bone disorder, tenosynovitis, bursitis, tendinous contracture, osteoporosis, tendon rupture, bone pain |
| Body System | Adverse Events |
|---|---|
| Rare | Rheumatoid arthritis, osteomyelitis, rhabdomyolysis, myopathy, muscle atrophy, myositis, pyogenic arthritis, bone neoplasm, musculoskeletal congenital anomaly, pathological fracture |
| Nervous system | |
| Frequent | Insomnia, anxiety, libido decreased, depersonalization, hypertonia, neuropathy |
| Infrequent | Reflexes decreased, sleep disorder, abnormal dreams, hostility, hallucinations, hyperkinesia, personality disorder, dysarthria, hyperesthesia, hypokinesia, circumoral paresthesia, libido increased, neuralgia, vestibular disorder, aphasia, movement disorder, hyperalgesia, apathy, hypotonia, convulsion, facial paralysis, psychosis |
| Rare | Drug dependence, neuritis, paranoid reaction, CNS depression, CNS neoplasia, manic reaction, neurosis, extrapyramidal syndrome, meningitis, hemiplegia, reflexes increased, akathisia, delirium, paralysis, withdrawal syndrome, brain edema, CNS stimulation, dyskinesia, encephalopathy, foot drop, grand mal convulsion, hypalgesia, peripheral neuritis, psychotic depression, addiction, arachnoiditis, cerebellar syndrome, cogwheel rigidity, dementia, dystonia, Guillain-Barre syndrome, intracranial hemorrhage, multiple sclerosis, myelitis, schizophrenic reaction, subarachnoid hemorrhage, torticollis |
| Respiratory system | |
| Frequent | Sinusitis, rhinitis, dyspnea, cough increased, pneumonia, lung disorder |
| Infrequent | Asthma, epistaxis, laryngitis, voice alteration, respiratory disorder, sputum increased |
| Rare | Apnea, emphysema, aspiration pneumonia, hyperventilation, lung edema, pleural disorder, atelectasis, hemoptysis, hiccup, hypoxia, laryngismus, lung fibrosis, pleural effusion, lung function decreased, pulmonary hypertension, yawn, bronchiectasis, bronchiolitis, carcinoma of lung, hypoventilation, laryngeal neoplasia, nasal septum disorder, pneumothorax |
| Skin and appendages | |
| Infrequent | Pruritus, sweating, skin disorder, acne, dry skin, alopecia, skin ulcer, herpes simplex, urticaria, nail disorder, eczema, herpes zoster, skin benign neoplasm, fungal dermatitis, maculopapular rash, vesiculobullous rash, skin carcinoma, furunculosis, skin discoloration, skin hypertrophy, psoriasis, seborrhea, hirsutism |
| Rare | Skin nodule, angioedema, cutaneous moniliasis, skin atrophy, exfoliative dermatitis, pustular rash, ichthyosis, skin melanoma, subcutaneous nodule, sweating decreased, hair disorder, lichenoid dermatitis, melanosis, miliaria, purpuric rash, skin necrosis, Stevens Johnson Syndrome |
| Special sense | |
| Frequent | Eye disorder, conjunctivitis, otitis media |
| Body System | Adverse Events |
|---|---|
| Infrequent | Retinal disorder, tinnitus, eye pain, cataract specified, dry eyes, taste perversion, ear pain, lacrimation disorder, ear disorder, deafness, eye hemorrhage, photophobia, glaucoma, vitreous disorder, corneal lesion, otitis externa, refraction disorder, blepharitis, retinal edema, taste loss, abnormality of accommodation |
| Rare | Hyperacusis, keratitis, mydriasis, parosmia, ptosis, retinal hemorrhage, color blindness, retinal depigmentation, retinal detachment, corneal opacity, corneal ulcer, iritis, night blindness, optic atrophy, retinal degeneration, cataract NOS, scleritis, strabismus, anisocoria, blindness, exophthalmos, keratoconjunctivitis, ophthalmoplegia, papilledema |
| Urogenital system | |
| Frequent | Anorgasmia |
| Infrequent | Urinary frequency, urinary incontinence, cystitis, abnormal ejaculation, urination impaired, dysuria, metrorrhagia, hematuria, vaginal moniliasis, prostatic disorder, vaginitis, dysmenorrhea, urinary urgency, kidney calculus, breast pain, menstrual disorder, amenorrhea, menorrhagia, kidney function abnormal, nephritis, urine abnormality, vaginal hemorrhage, urinary retention, urinary tract disorder, leukorrhea, breast neoplasm, menopause, oliguria, polyuria, albuminuria, pyuria |
| Rare | Breast carcinoma, penis disorder, papanicolau smear suspicious, fibrocystic breast, prostatic carcinoma, uterine fibroids enlarged, acute kidney failure, creatinine clearance decreased, nephrosis, nocturia, polycystic kidney, bladder carcinoma, breast enlargement, cervicitis, cervix disorder, female lactation, glycosuria, gynecomastia, hypomenorrhea, kidney pain, mastitis, pyelonephritis, kidney failure, breast abscess, epididymitis, orchitis, prostate neoplasia, prostatic specific antigen increase, salpingitis, urogenital disorder, urolithiasis, uterine disorder, vulvovaginal disorder, balanitis, bladder calculus, calcium crystalluria, cervix neoplasm, dyspareunia, endometrial carcinoma, endometrial disorder, glomerulitis, hydronephrosis, ovarian cancer, unintended pregnancy, urethral pain, urethritis, urogenital anomaly, urogenital neoplasia, uterine hemorrhage |
Comparison of Gender and Race
The overall adverse event profile of pregabalin was similar between women and men. There are insufficient data to support a statement regarding the distribution of adverse experience reports by race.
Peripheral Edema
Incidence of peripheral edema in pre-marketing controlled peripheral neuropathic pain studies was 10.4% in the pregabalin group compared with 2.9% in the placebo group. The incidence in the controlled fibromyalgia studies was 7.6% in the pregabalin group compared with 2.5% in the placebo group. In clinical trials, these events of peripheral edema were dose-related, mostly mild to moderate in intensity and rarely led to withdrawal. Peripheral edema was not associated with cardiovascular complications such as hypertension or congestive heart failure and there was no evidence of hemodilution or changes in any laboratory parameters indicative of underlying organ dysfunction (see 7 WARNINGS AND PRECAUTIONS, General and 7 WARNINGS AND PRECAUTIONS, Peripheral Edema).
Weight Gain
In the pre-marketing controlled peripheral neuropathic pain studies, patients on pregabalin had a higher incidence (5.9%) of weight gain as defined by a ≥ 7% increase from baseline weight as compared with the placebo group (1.6%). The mean change in the pregabalin group was an increase of 1.5 kg compared with 0.2 kg in the placebo group; few patients (0.1%) withdrew due to weight gain.
The incidence in the controlled fibromyalgia studies was 11.5% in the pregabalin group compared with 2.5% in the placebo group; approximately 1% of pregabalin-treated patients withdrew due to weight gain.
This weight gain was dose-related, and not associated with clinically important changes in blood pressure or cardiovascular adverse events. There was no relationship between baseline body mass index and the incidence of ≥ 7% weight gain in the controlled trials.
Based on the results of a controlled study of reproductive function in healthy male volunteers, the ≥ 7% weight gain on pregabalin appeared to be reversible. In this study, there were no reports of peripheral edema(see 7 WARNINGS AND PRECAUTIONS, General, and 7 WARNINGS AND PRECAUTIONS, Weight Gain).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
In all pre-marketing controlled trials, 1.0% of patients on pregabalin and 0.5% of placebo patients had an increase in creatine kinase of ≥ 3X upper limit of normal. Renal dysfunction was generally not associated with the elevated creatine kinase in these patients. Mean changes in creatine kinase ranged from 9.6 to 26.3 U/L for pregabalin-treated patients and 4.8 U/L for the placebo patients (see 4.1 Dosing Considerations, Patients With Impaired Renal Function). Routine therapeutic drug monitoring or clinical laboratory testing is not required for patients treated with MAR-PREGABALIN (see 7 WARNINGS AND PRECAUTIONS, Creatinine Kinase Elevations).
8.5 Post-Market Adverse Reactions
Since the first global approval of pregabalin on 06 July 2004 through 31 March 2012, there has been an estimated 15,951,859 patient-years of exposure to pregabalin Table 13 is based on post- market spontaneous adverse event reports. The percentages shown are calculated by dividing the number of adverse events reported to the company by the estimated number of patient years exposed to pregabalin. Because these adverse reactions are reported spontaneously from a population of uncertain size, it is not possible to reliably estimate their frequency.
Furthermore, a causal relationship between pregabalin and the emergence of these events has not been clearly established.
Table 13. Post-Market Spontaneous Adverse Event Reports
| Adverse Event | Frequency | |||||
|---|---|---|---|---|---|---|
Common ≥ 1% | Uncommon < 1% and ≥ 0.1% | Rare < 0.1% and ≥ 0.01% | Very rare < 0.01% | |||
| Cardiovascular | ||||||
| congestive heart failurea | X | |||||
| Eye disordersb | ||||||
| diplopia | X | |||||
| vision blurred | X | |||||
| visual disturbance | X | |||||
| vision loss | X | |||||
| Psychiatric disorders | ||||||
| aggression | X | |||||
| confusional state | X | |||||
| depression | X | |||||
| euphoric mood | X | |||||
| insomnia | X | |||||
| psychotic disorderc | X | |||||
| Gastrointestinal disorders | ||||||
| diarrhea | X | |||||
| dry mouth | X | |||||
| nausea | X | |||||
| vomiting | X | |||||
| intestinal obstructiond | X | |||||
| paralytic ileusd | X | |||||
| General disorders and administration site conditions | ||||||
| fatigue | X | |||||
| feeling abnormal | X | |||||
| pain | X | |||||
| Adverse Event | Frequency | |||||
|---|---|---|---|---|---|---|
Common ≥ 1% | Uncommon < 1% and ≥ 0.1% | Rare < 0.1% and ≥ 0.01% | Very rare < 0.01% | |||
| Immune system disorders | ||||||
| angioedemae | X | |||||
| hypersensitivity f | X | |||||
| Nervous system disorders | ||||||
| ataxia | X | |||||
| coordination abnormal | X | |||||
| dizzinessg | X | |||||
| dysarthria | X | |||||
| headache | X | |||||
| memory impairment | X | |||||
| paresthesia | X | |||||
| somnolenceg | X | |||||
| speech disorder | X | |||||
| tremor | X | |||||
| coma | X | |||||
| loss of consciousness | X | |||||
| mental impairment | X | |||||
| Renal and urinary disorders | ||||||
| urinary retention | X | |||||
| Respiratory, thoracic and mediastinal disorders | ||||||
| dyspnea | X | |||||
| pulmonary edema | X | |||||
| Skin and subcutaneous tissue disorders | ||||||
| hyperhidrosis | X | |||||
| pruritus | X | |||||
a These reactions are mostly seen in elderly cardiovascular compromised patients during pregabalin treatment for a neuropathic pain indication (see 7 WARNINGS AND PRECAUTIONS, Congestive Heart Failure)
b There have also been rare reports of accommodation disorder, eyelid edema and eye redness (see 7 WARNINGS AND PRECAUTIONS, Ophthalmological Effects)
c There have been rare reports of psychotic disorders in patients receiving pregabalin
d See below and 7 WARNINGS AND PRECAUTIONS, Gastrointestinal
e see 7 WARNINGS AND PRECAUTIONS, Angioedema
f see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity
g see 7 WARNINGS AND PRECAUTIONS, Dizziness and Somnolence
Gastrointestinal: There have been post-marketing events related to reduced lower gastrointestinal tract function (e.g., intestinal obstruction, paralytic ileus, and constipation) primarily reported when pregabalin was given in combination with other medications that have the potential to produce constipation, such as opioid analgesics (see 7 WARNINGS AND PRECAUTIONS, Gastrointestinal).
Urinary and Renal Disorder: renal failure. There have been rare post-marketing reports of patients, with or without previous history, experiencing renal failure while receiving pregabalin alone or in combination with other medications. Discontinuation of pregabalin showed reversibility of this event in some cases. Caution is advised when prescribing MAR-PREGABALIN to the elderly or those with impaired renal function (see 7.1 Special Populations, Renal; 7 WARNINGS and PRECAUTIONS, Renal Failure, and 4 DOSAGE AND ADMINISTRATION).
Cardiovascular: congestive heart failure. These reactions are mostly seen in elderly cardiovascular compromised patients during pregabalin treatment for a neuropathic pain indication (see 7 WARNINGS AND PRECAUTIONS, Congestive Heart Failure).
Respiratory, Thoracic and Mediastinal Disorder: pulmonary edema. There have been post- marketing reports of pulmonary edema in patients receiving pregabalin. Although this adverse reaction has mostly been observed in elderly patients with predisposing factors, some cases have occurred in patients with no known previous history or predisposing conditions.
Eye disorders: diplopia, vision blurred, visual disturbance and vision loss. There have also been rare reports of accommodation disorder, eyelid edema and eye redness (see 7 WARNINGS AND PRECAUTIONS, Ophthalmological Effects).
Encephalopathy: There have been serious post-marketing reports of encephalopathy, mostly in patients with underlying conditions that may precipitate encephalopathy. Some cases were reported in patients with a history of kidney or liver disease. Since there have been rare reports of renal failure with pregabalin, specific caution should be exercised when prescribing MAR-PREGABALIN to the elderly with age-related compromised renal function and patients with kidney disease or risk factors for renal failure (see 7 WARNINGS AND PRECAUTIONS, Renal Failure and 7 WARNINGS AND PRECAUTIONS, Encephalopathy).
Convulsions: convulsions, including status epilepticus and grand mal convulsions, have been reported in non-epileptic patients during treatment with pregabalin or following abrupt discontinuation (see 4.2.1 Discontinuing Treatment ).
Suicidal Behaviour and Ideation: There have been post-marketing reports of suicide-related events, including completed suicide, suicide attempt, and suicidal ideation in patients treated with pregabalin for a variety of indications such as neuropathic pain, fibromyalgia, etc. In some of these reports, underlying psychiatric disorders may have contributed to the event. The mechanism of this risk is not known. Patients should be monitored for signs of suicidal ideation and behaviours and appropriate treatment should be considered. Patients should be encouraged to report any distressing thoughts or feelings at anytime to their healthcare professional (see 7 WARNINGS AND PRECAUTIONS, Suicidal Behaviour and Ideation).
Serious Skin Reactions
There have been very rare post-marketing reports of serious cutaneous reactions, including Stevens-Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN), dermatitis exfoliative, bullous skin reactions, and erythema multiforme in patients treated with pregabalin (see 7 WARNINGS AND PRECAUTIONS, Serious Skin Reactions). Post-market reporting rate is generally accepted to be an underestimate due to under-reporting. Most of the reports were in patients taking concomitant medications also associated with the potential development of these serious skin reactions. Therefore, in most cases, causality in relation to pregabalin could not be clearly established. Patients should be advised that if they experience a skin rash, they should discontinue MAR-PREGABALIN treatment and contact their physician for assessment and advice.
9. DRUG INTERACTIONS
9.1 Serious Drug Interaction
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Due to additive pharmacologic effect, the concomitant use of CNS depressants (e.g., gabapentin, pregabalin, baclofen, and alcohol) and opioids increases the risk of respiratory depression, profound sedation, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Monitor patients closely for signs of respiratory depression and sedation (see 7 WARNINGS AND PRECAUTIONS, Respiratory Depression; Concomitant use with Opioids and 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery).
Since pregabalin is predominately excreted unchanged in the urine, undergoes negligible metabolism in humans (≤ 2% of a dose recovered in urine as metabolites), does not inhibit drug metabolism in vitro, and is not bound to plasma proteins, pregabalin is unlikely to produce, or be subject to, pharmacokinetic interactions.
9.4 Drug-Drug Interactions
Pharmacokinetic
In Vitro Studies: In vitro drug metabolism studies revealed that pregabalin at concentrations which were, in general, 10-fold greater than observed in Phase 2/3 clinical trials, does not inhibit human CYP1A2, CYP2A6, CYP2C9, CYP2C19, CYP2D6, CYP2E1, and CYP3A4 enzyme systems.
In Vivo Studies: The drug interaction data described in this section were obtained from studies involving healthy adults, patients with epilepsy, and patients with chronic pain disorders.
Carbamazepine, valproic acid, lamotrigine, phenytoin, phenobarbital, and topiramate: In vitro and in vivo studies showed that pregabalin is unlikely to be involved in significant pharmacokinetic drug interactions. Specifically, there are no clinically significant pharmacokinetic interactions between pregabalin and the following antiepileptic drugs: carbamazepine, valproic acid, lamotrigine, phenytoin, phenobarbital, and topiramate. Important pharmacokinetic interactions would also not be expected to occur between pregabalin and commonly used antiepileptic drugs.
Tiagabine: The results of a population pharmacokinetic analysis indicated that in patients with partial seizures tiagabine had no clinically significant effect on pregabalin clearance.
Gabapentin: The pharmacokinetics of pregabalin and gabapentin were investigated in
12 healthy subjects following concomitant single dose administration of 100 mg pregabalin and 300 mg gabapentin, and in 18 healthy subjects following concomitant multiple dose administration of 200 mg pregabalin q8h and 400 mg gabapentin q8h. Gabapentin pharmacokinetics following single and multiple dose administration were unaltered by pregabalin coadministration. The rate of pregabalin absorption was reduced by approximately 26% (single dose administration) and 18% (multiple dose administration) based on lower Cmax values; however, the extent of pregabalin absorption was unaffected by gabapentin coadministration.
Oral Contraceptives: Pregabalin coadministration (200 mg TID) had no effect on the steady state pharmacokinetics of norethindrone and ethinyl estradiol (1 mg/35 mcg, respectively) in healthy subjects.
Lorazepam: Multiple dose administration of pregabalin (300 mg BID) in healthy subjects had no effect on the rate and extent of lorazepam single dose pharmacokinetics and single dose administration of lorazepam (1 mg) had no clinically significant effect on the steady state pharmacokinetics of pregabalin.
Oxycodone: Multiple dose administration of pregabalin (300 mg BID) in healthy subjects had no effect on the rate and extent of oxycodone single dose pharmacokinetics. Single dose administration of oxycodone (10 mg) had no clinically significant effect on the steady state pharmacokinetics of pregabalin.
Ethanol: Multiple dose administration of pregabalin (300 mg BID) in healthy subjects had no effect on the rate and extent of ethanol single dose pharmacokinetics and single dose administration of ethanol (0.7 g/kg) had no clinically significant effect on the steady state pharmacokinetics of pregabalin.
Diuretics, Oral Hypoglycemics, and Insulin: A population pharmacokinetic analysis in patients with chronic pain showed no clinically significant effect on pregabalin clearance with the concomitant use of diuretics, oral hypoglycemics, and insulin.
Pharmacodynamic
Opioids, benzodiazepines and alcohol: Pregabalin appears to be additive in the impairment of cognitive and gross motor function caused by opioids, benzodiazepines and alcohol.
In post-marketing experience, there are reports of respiratory failure, coma and deaths in patients taking pregabalin alone or in combination with other CNS depressants, including in patients with substance use disorders.
Thiazolidinedione Antidiabetic Agents: Higher frequencies of weight gain and peripheral edema were observed in patients taking both pregabalin and a thiazolidinedione antidiabetic agent compared to patients taking either drug alone. The majority of patients using thiazolidinedione antidiabetic agents in the overall safety database were participants in studies of pain associated with diabetic peripheral neuropathy.
As the thiazolidinedione class of antidiabetic drugs or MAR-PREGABALIN can cause weight gain and/or fluid retention alone or together, possibly exacerbating or leading to heart failure, caution should be exercised when co-administering MAR-PREGABALIN and these agents (see 7 WARNINGS AND PRECAUTIONS, Peripheral Edema).
9.5 Drug-Food Interactions
The rate of pregabalin absorption is decreased when given with food resulting in a decrease in Cmax by approximately 25% to 30% and an increase in Tmax to approximately 3 hours. However, administration of pregabalin with food has no clinically relevant effect on the total amount of pregabalin absorbed. Therefore, pregabalin can be taken with or without food.
9.6 Drug-Herb Interactions
Pregabalin has no known drug-herb interactions.
9.7 Drug-Laboratory Test Interactions
Pregabalin has no known drug-laboratory test interactions.
10. CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Pregabalin binds to the α2-δ subunit of the voltage-gated calcium channels in central nervous system tissues. In vitro, pregabalin reduces calcium influx at nerve terminals, which may inhibit the release of excitatory neurotransmitters such as glutamate. Through this mechanism, pregabalin may modulate nerve impulses involved in the transmission of pain. However, the clinical relevance of these findings in man is unknown.
10.2 Pharmacodynamics
Drug Likability Study
In a study of recreational users (n = 15) of sedative/hypnotic drugs, including alcohol, a single dose of pregabalin 450 mg received subjective ratings of “good drug effect”, “high”, and “liking” to a degree that was similar to a single dose of diazepam 30 mg. (see 7 WARNINGS AND PRECAUTIONS, Dependence, Tolerance and/or Abuse Liability)
Pregabalin is not known to be active at receptor sites associated with drugs of abuse. As with any CNS active drug, physicians should carefully evaluate patients for history of drug abuse and observe them for signs of pregabalin misuse or abuse (e.g., development of tolerance, dose escalation, drug-seeking behaviour).
Pregabalin binds with high affinity to the alpha2-delta protein (a calcium channel subunit) of brain tissues and has analgesic, antiepileptic, and anxiolytic activity. Pregabalin is known chemically as (S)-3-(aminomethyl)-5-methylhexanoic acid.
Although the mechanism of action of pregabalin is unknown, results with genetically modified mice and with compounds structurally-related to pregabalin indicate that selective binding to the alpha2-delta protein is required for analgesic, antiepileptic and anxiolytic action in animal models. In vitro, pregabalin reduces the release of several neurotransmitters, suggesting a modulatory action on calcium channel function.
Pregabalin does not mimic GABA at GABAA or GABAB receptors, nor does it augment GABAA responses like benzodiazepines or barbiturates. In contrast to vascular calcium channel blockers, pregabalin does not alter systemic blood pressure or cardiac function. Various in vitro and in vivo results differentiate pregabalin from GABA uptake inhibitors or GABA transaminase inhibitors. In addition, pregabalin does not block sodium channels, it is not active at opiate receptors, it does not alter cyclooxygenase enzyme activity, it is not a serotonin agonist, it is not a dopamine antagonist, and it is not an inhibitor of dopamine, serotonin or noradrenaline reuptake.
Pregabalin treatment reduces pain-related behavior in neuropathic animal models of diabetes, peripheral nerve damage or chemotherapeutic insult and in a model of musculoskeletal-associated pain. Pregabalin given intrathecally prevents pain-related behaviors and reduces pain-related behavior caused by spinally administered agents, suggesting that it acts directly on tissues of the spinal cord or brain.
10.3 Pharmacokinetics
All pharmacological actions following pregabalin administration are due to the activity of the parent compound; pregabalin is not appreciably metabolized in humans. Mean steady-state plasma pregabalin concentration-time profiles following 75, 300, and 600 mg/day given in equally divided doses every 8 hours (TID) and 600 mg/day given in equally divided doses every 12 hours (BID) are shown in Table 14. Pregabalin pharmacokinetics are linear over the recommended daily dose range. Inter-subject pharmacokinetic variability for pregabalin is low (< 20%).
Table 14. Pregabalin Mean (CV%a) Steady-State Pharmacokinetic Parameter Values in Healthy Volunteers
| Dose (mg) | Regimen | Daily Dose (mg/day) | n | Cmaxss (mcg/mL) | tmax (hr) | Cminss (mcg/mL) | AUC(0-t) (mcg•hr/mL) | t½ (hr) | CL/F (mL/min) |
|---|---|---|---|---|---|---|---|---|---|
| 25 | TIDb | 75 | 8 | 1.39 | 0.9 | 0.45 | 6.7 | 5.9 | 64.1 |
| -19.5 | -34.2 | -25 | -18.3 | -17.3 | -16.1 | ||||
| 100 | TID | 300 | 6 | 5.03 | 0.8 | 1.94 | 25.2 | 6.3 | 68.9 |
| -21.3 | -31 | -33.6 | -23 | -19.6 | -20.9 | ||||
| 200 | TID | 600 | 11 | 8.52 | 0.9 | 3.28 | 41.7 | 6.3 | 81 |
| -14.8 | -22.2 | -29.2 | -12.8 | -13.6 | -11.7 | ||||
| 300 | BIDc | 600 | 8 | 9.07 | 1.4 | 2.6 | 59 | 6.7 | 85.1 |
| -10.5 | -57.1 | -15.5 | -6.4 | -16.2 | -6.4 |
Cmaxss: Steady-state peak plasma concentration.
tmax: Time of peak plasma concentration at steady state. Cminss: Steady-state trough plasma concentration
AUC(0-t): Area under the plasma concentration-time curve during one dosing interval at steady state t½: Elimination half-life
CL/F: Oral clearance
a: Percent coefficient of variation
b: Total daily dose given in equally divided doses every 8 hours
c: Total daily dose given in equally divided doses every 12 hours
Absorption
Pregabalin is rapidly absorbed when administered in the fasted state, with peak plasma concentrations occurring within 1.5 hours following both single- and multiple-dose administration. Pregabalin oral bioavailability is ≥ 90% and is independent of dose. Cmax (Figure 1) and AUC values increase proportionally following single- and multiple-dose administration. Following repeated administration, steady state is achieved within 24 to 48 hours. Multiple dose pharmacokinetics are predictable from single-dose data.
Figure 1. Individual and Mean Steady-State Pregabalin Cmax Values Following 75, 300 and 600 mg/day Given in Equally Divided Doses TID (q8h) to Healthy Volunteersa
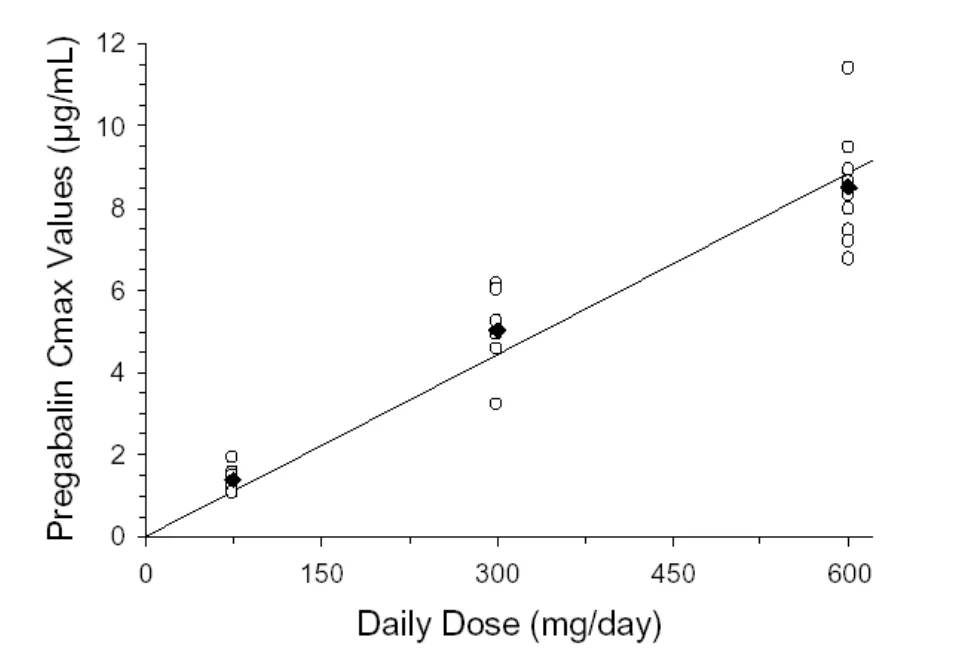
a: Solid line is the regression line going through the origin; individual (○) and mean ( ) values.
Distribution
In preclinical studies, pregabalin has been shown to readily cross the blood brain barrier in mice, rats, and monkeys. Pregabalin is a substrate for system L transporter which is responsible for the transport of large amino acids across the blood-brain barrier. Pregabalin has been shown to cross the placenta in rats and is present in the milk of lactating rats. In humans, the apparent volume of distribution of pregabalin following oral administration is approximately 0.5 L/kg. Pregabalin is not bound to plasma proteins. At clinically efficacious doses of 150 and 600 mg/day, the average steady-state plasma pregabalin concentrations were approximately 1.5 and 6.0 mcg/mL, respectively.
Metabolism
Pregabalin undergoes negligible metabolism in humans. Following a dose of radiolabeled pregabalin, approximately 98% of the radioactivity recovered in the urine was unchanged pregabalin. The N-methylated derivative of pregabalin, the major metabolite of pregabalin found in urine, accounted for 0.9% of the dose. In preclinical studies, pregabalin (S- enantiomer) did not undergo racemization to the R-enantiomer in mice, rats, rabbits, or monkeys.
Elimination
Pregabalin is eliminated from the systemic circulation primarily by renal excretion as unchanged drug. Pregabalin mean t½ is 6.3 hours. Pregabalin elimination is proportional to creatinine clearance. Pregabalin clearance is reduced in patients with impaired renal function (see 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment Based on Renal Function).
Special Populations and Conditions
Pregabalin undergoes negligible metabolism, is not bound to plasma proteins, and is eliminated predominately as unchanged drug by renal excretion. Clinically important differences in pregabalin pharmacokinetics due to race and gender have not been observed and are not anticipated.
- Pediatrics Pharmacokinetics of pregabalin have not been studied in pediatric patients. No data are available to Health Canada; therefore, health Canada has not authorized an indication for pediatric use.
- Geriatrics Pregabalin oral clearance tended to decrease with increasing age. This decrease in pregabalin oral clearance is consistent with age-related decreases in creatinine clearance. Reduction of pregabalin dose may be required in patients who have age-related compromised renal function (see 7.1.4 Geriatrics and 4.2 Recommended Dose and Dosage Adjustment, Geriatrics (> 65 years)).
- Gender A population pharmacokinetic analysis of the Phase 2/3 clinical program showed that the relationship between daily dose and pregabalin drug exposure is similar between genders when adjusted for gender-related differences in creatinine clearance.
- Race A population pharmacokinetic analysis of the Phase 2/3 clinical program showed that the relationship between daily dose and pregabalin drug exposure is similar among Caucasians, Blacks, and Hispanics.
- Renal Insufficiency Because renal elimination is the major elimination pathway, dosage reduction in patients with renal dysfunction is necessary. Pregabalin is effectively removed from plasma by hemodialysis. Following a 4-hour hemodialysis treatment, plasma pregabalin concentrations are reduced by approximately 50%. For patients on hemodialysis, dosing must be modified (see 4.2 Recommended Dose and Dosage Adjustment, Dosage Adjustment Based on Renal Function).
- STORAGE, STABILITY AND DISPOSAL
Store at 15°C – 30°C. Keep out of the reach and sight of children.
- 12. SPECIAL HANDLING INSTRUCTIONS
There are no special handling requirements for this drug product.
PART II: SCIENTIFIC INFORMATION
- 13. PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: pregabalin
Chemical name: (S)-3-(aminomethyl)-5-methylhexanoic acid Molecular formula and molecular mass: C8H17NO2, 159.23 g/mol Structural formula:
CO2H NH2
Physicochemical properties: Pregabalin is a white crystalline solid. It is soluble in water and in both basic and acidic aqueous solutions.
MAR-PREGABALIN (Pregabalin) Capsules
14. CLINICAL TRIALS
14.1 Clinical Trials by Indication
Diabetic Peripheral Neuropathy
Table 15. Summary of Patient Demographics for Clinical Trials in Diabetic Peripheral Neuropathy
Study # | Study Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex |
|---|---|---|---|---|---|
| DPN1 | Double-blind, fixed-dose, placebo- controlled, multicenter | 150 or 600 mg/day (TID regimen), oral, 6 weeks | 246 | 57 (46 – 67) | 149M 97F |
| DPN2 | Double-blind, fixed-dose, placebo- controlled, multicenter | 75, 300, or 600 mg/day (TID regimen), oral, 5 weeks | 337 | 59 (26 – 85) | 202M 135F |
| DPN3 | Double-blind, fixed-dose, placebo- controlled, multicenter | 300 mg/day (100 mg TID), oral, 8 weeks | 146 | 59 (48 – 71) | 82M 64F |
| DPN4 | Double-blind, fixed-dose, placebo- controlled, multicenter | 150, 300, or 300/600 mg/day For the 300/600 mg/day pregabalin group, to achieve equivalent exposures, patients received either 300 or 600 mg/day depending on the creatinine clearance rate (BID regimen) Oral, 12 weeks | 395 | 58 (47 – 70) | 219M 176F |
Studies DPN1, DPN2, DPN3 and DPN4 enrolled a total of 1124 patients with type 1 or 2 diabetes mellitus who had painful distal symmetrical sensorimotor polyneuropathy for 1 to 5 years. Across all 4 studies, the baseline mean pain scores ranged from 6.3 to 6.7. The analysis population for all primary and secondary analyses for each study was the intent-to-treat population. Among the pregabalin-treated patients enrolled in these studies, the completion rate was 86%.
Table 16. Results of Study DPN1 in Diabetic Peripheral Neuropathy
MAR-PREGABALIN (Pregabalin) Capsules
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 150 mg/day: not significantly better than placebo 600 mg/day: significantly better than placebo (p = 0.0002) | |
Proportion of responders | 600 mg/day: 39% | 15% (p = 0.002) |
The 600 mg/day arm was associated with higher reporting of adverse events and withdrawals due to adverse events (see 8.2 Clinical Trial Adverse Reactions).
Table 17. Results of Study DPN2 in Diabetic Peripheral Neuropathy
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 300 mg/day: significantly better than placebo (p = 0.0001) 600 mg/day: significantly better than placebo (p = 0.0001) | |
Proportion of responders | 300 mg/day: 46% 600 mg/day: 48% | 18% (p = 0.001 for each dose) |
Compared to 300 mg/day treatment arm, patients treated with 600 mg/day experienced more adverse reactions and discontinued the study more frequently (see Tables 2 and 3, 8.2 Clinical Trial Adverse Reactions ).
Table 18. Results of Study DPN3 in Diabetic Peripheral Neuropathy
MAR-PREGABALIN (Pregabalin) Capsules
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 300 mg/day: significantly better than placebo (p = 0.0001) | |
| Proportion of responders | 300 mg/day: 40% | 15% (p = 0.001) |
Table 19. Results of Study DPN4 in Diabetic Peripheral Neuropathy
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 150 or 300 mg/day: not significantly better than placebo 300/600 mg/day: significantly better than placebo (p = 0.0054) | |
Proportion of responders | 300/600 mg/day: 46% | 30% (p = 0.036) |
Patients recorded their pain on a daily diary using an 11-point numerical pain rating scale ranging from 0 = "no pain" to 10 = "worst possible pain." To enter the study, patients had to have moderate to severe pain, i.e., mean baseline score (mean of the last 7 daily diary pain score prior to study medication) of ≥ 4. The primary measure of efficacy was reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication). Supplemental analyses included mean pain scores computed for each week during the study, and the proportion of responders (those patients reporting at least 50% reduction in endpoint mean pain score compared to baseline). Secondary outcome variables included daily sleep interference scores, and the Patient Global Impressions of Change (PGIC). Mean sleep scores were computed at endpoint and for each week during the study. The PGIC was completed at the end of the study and measured the patient's overall status compared to baseline using a 7- point categorical scale ranging from "very much improved" to "very much worse."
Postherpetic Neuralgia
Table 20. Summary of Patient Demographics for Clinical Trials in Postherpetic Neuralgia
MAR-PREGABALIN (Pregabalin) Capsules
Study # | Study Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex |
|---|---|---|---|---|---|
| PHN1 | Double-blind, fixed-dose, placebo- controlled, multicenter | 150 or 300 mg/day (TID regimen), oral, 8 weeks | 238 | 72 (32 – 96) | 107M 131F |
| PHN2 | Double-blind, fixed-dose, placebo- controlled, multicenter | 300 or 600 mg/day depending on patient creatinine clearance rate, oral, 8 weeks | 173 | 71 (60 – 82) | 81M 92F |
| PHN3 | Double-blind, fixed-dose, placebo- controlled, multicenter | 150, 300, or 300/600 mg/day For the 300/600 mg/day pregabalin group, to achieve equivalent exposures, patients received either 300 or 600 mg/day depending on the creatinine clearance rate (BID regimen) Oral, 13 weeks | 368 | 71 (18 – 92) | 168M 200F |
Studies PHN1, PHN2 and PHN3 enrolled 779 patients with postherpetic neuralgia who continued to have pain for at least 6 months (Study PHN1) or 3 months (Study PHN2 and PHN3) after healing of the herpes zoster skin rash. Across all 3 studies, the baseline mean pain scores ranged from 6.4 to 6.8. The analysis population for all primary and secondary analyses for each study was the intent-to-treat population. Among the pregabalin treated patients enrolled in these studies, the completion rate was 71%.
Patients were randomly assigned to one of the treatment arms depending on their creatinine clearance rate. Compared to patients with creatinine clearance rate ≥ 60 mL/min, those with decreased creatinine clearance rate (≤ 60 mL/min) experienced markedly higher rates of adverse events and discontinued the trial more frequently.
Table 21. Results of Study PHN1 in Postherpetic Neuralgia
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 150 mg/day: significantly better than placebo (p = 0.0002) 300 mg/day: significantly better than placebo (p = 0.0002) | |
| Proportion of responders | 150 mg/day: 26% 300 mg/day: 28% | 10% (p = 0.006 for each dose) |
This trial included patients with decreased creatinine clearance rate (30-60 mL/min) who were
MAR-PREGABALIN (Pregabalin) Capsules
randomly assigned to one of the treatment arms.
Table 22. Results of Study PHN2 in Postherpetic Neuralgia
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 300/600 mg/day: significantly better than placebo (p = 0.0001) | |
Proportion of responders | 300/600 mg/day: 50% | 20% (p≤ 0.001) |
Table 23. Results of Study PHN3 in Postherpetic Neuralgia
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | 150 mg/day: significantly better than placebo (p = 0.0077) 300 mg/day: significantly better than placebo (p = 0.0016) 300/600 mg/day: significantly better than placebo (p = 0.0003) | |
| Proportion of responders | 150 mg/day: 26% 300 mg/day: 27% 300/600 mg/day: 38% | 8% (p = 0.001 for each dose) |
Patients recorded their pain on a daily diary using an 11-point numerical pain rating scale ranging from 0 = "no pain" to 10 = "worst possible pain." To enter the study, patients had to have moderate to severe pain, i.e., mean baseline score (mean of the last 7 daily diary pain score prior to study medication) of ≥ 4. The primary measure of efficacy was reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication). Supplemental analyses included mean pain scores computed for each week during the study, and the proportion of responders (those patients reporting at least 50% reduction in endpoint mean pain score compared to baseline). Secondary outcome variables included daily sleep interference scores, and the Patient Global Impressions of Change (PGIC). Mean sleep scores were computed at endpoint and for each week during the study. The PGIC was completed at the end of the study and measured the patient's overall status compared to baseline using a 7-point categorical scale ranging from "very much improved" to "very much worse."
Overall Analysis of Diabetic Peripheral Neuropathy and Postherpetic Neuralgia Studies
MAR-PREGABALIN (Pregabalin) Capsules
When endpoint mean pain scores are combined across all controlled diabetic neuropathic pain and postherpetic neuralgia studies, no significant differences in efficacy based on gender, or race, were observed.
In controlled diabetic neuropathy and postherpetic neuralgia clinical trials, pregabalin, at doses of 150, 300, and 600 mg/day, was statistically significantly more effective than placebo in reducing sleep disturbance and improving PGIC.
Spinal Cord Injury
Table 24. Summary of Patient Demographics for Clinical Trials in Spinal Cord Injury
Study # | Study Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex |
|---|---|---|---|---|---|
| SCI1 | Double-blind, randomized, placebo-controlled, multicenter Double-blind, randomized, placebo-controlled, multicenter | Escalating doses of 150 mg/day, 300 mg/day and 600 mg/day (BID regimen) with doses adjusted based on patient response and tolerability at weekly intervals up to the third week of treatment, after which patients were maintained on a fixed dose for the remainder of the study, oral, 12 weeks | 137 | 50 (21 to 80) | 114M 23F |
Patients recorded their pain on a daily diary using an 11-point numerical scale ranging from 0 = “no pain” to 10 = “worst possible pain”. To enter the study, patients had to have moderate to severe pain, i.e., mean baseline score (mean of the last 7 daily pain scores prior to study medication) of ≥ 4. In both the placebo and pregabalin groups, the majority of patients were taking concomitant analgesics, anti-inflammatories, and anti-depressants for pain during the study. The placebo group received a BID regimen, following the same blinded adjustment for the 12-week double-blind treatment as in the pregabalin group. 70% of patients in the pregabalin group completed the study as compared to the placebo group (55.2%).
Following the 12-week double-blind placebo-controlled study, 103 patients were treated with pregabalin in an open-label extension study (see 8.2 Clinical Trial Adverse Reactions). Mandatory drug holidays (from 3 to 28 days) occurred every 3 months for the duration of the open-label study. Subjects who relapsed during the drug holiday were allowed to restart pregabalin therapy for an additional 3-month period. The median duration of open-label therapy was 545 days. The median duration of therapy across the double-blind and open-label studies for those subjects was 608 days.
During the drug holidays, most subjects indicated that their pain increased after temporarily stopping pregabalin.
Table 25. Results of Study SCI1 in Spinal Cord Injury
MAR-PREGABALIN (Pregabalin) Capsules
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction inendpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | Significantly larger reduction from baseline, (p < 0.001). Treatment differences were significant as early as the first week of treatment and were maintained for the duration of the study. | |
| Proportion of responders | ≥ 30%: 42% ≥ 50%: 22% | 30%: 16% 50%: 8% |
Fibromyalgia
Table 26. Summary of Patient Demographics for Clinical Trials in Fibromyalgia
Study # | Study Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Sex |
|---|---|---|---|---|---|
| F1 | Multicentre, parallel, double- blind, randomized, placebo- controlled | 150, 300 or 450 mg/day (TID regimen), oral, 8 weeks | 529 | 48.6 (20 to 78) | 45M 484F |
| F2 | Multicentre, parallel, double- blind, randomized, placebo- controlled | 300, 450 or 600 mg/day (BID regimen), oral, 13 weeks | 748 | 48.8 (18 to 82) | 42M 706F |
| F3 | Multicentre, parallel, double- blind, randomized, placebo- controlled, using enriched population, only | 300, 450 or 600 mg/day (BID regimen), oral, 14 weeks | 745 | 50.1 (18 to 81) | 41M 704F |
| F4 | Multicentre, parallel, double- blind, randomized, placebo- controlled, using enriched population, only | 300, 450 or 600 mg/day (BID regimen), oral, 14 weeks | 735 | 48.5 (20 to 81) | 63M 672F |
To enter the study, patients had to have moderate to severe pain, i.e., mean baseline score (mean of the last 7 daily diary pain scores prior to study medication) of ≥ 4, and a diagnosis of fibromyalgia based on the American College of Rheumatology criteria (history of widespread pain for 3 months, and pain present at 11 or more out of 18 specific tender points). During all studies described below, patients were allowed to take acetaminophen up to 4 g per day as needed for pain relief.
MAR-PREGABALIN (Pregabalin) Capsules
Table 27. Results of Study F1 in Fibromyalgia
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | Significantly larger reduction from baseline, (p < 0.005) only at 150 mg TID. | |
| Proportion of responders | 50 mg TID: 78% 100 mg TID: 83% 150 mg TID: 75% | 74% |
A dose-related increase in adverse events and withdrawals due to adverse events was observed (see 8.2 Clinical Trial Adverse Reactions).
Table 28. Results of Study F2 in Fibromyalgia
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | Significantly larger reduction from baseline, (p < 0.05) at all doses studied. | |
| Proportion of responders | 150 mg TID: 66% 225 mg TID: 66% 300 mg TID: 58% | 68% |
A dose-related increase in adverse events and withdrawals due to adverse events was observed (see 8.2 Clinical Trial Adverse Reactions).
Table 29. Results of Study F3 in Fibromyalgia
MAR-PREGABALIN (Pregabalin) Capsules
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | Significantly larger reduction from baseline, (p < 0.0005) at all doses studied. | |
| Proportion of responders | 150 mg BID: 67.2% 225 mg BID: 65.8% 300 mg BID: 60.1% | 67.9% |
A dose-related increase in adverse events and withdrawals due to adverse events was observed (see 8.2 Clinical Trial Adverse Reactions).
Table 30. Results of Study F4 in Fibromyalgia
| Primary Endpoints | Associated Value and Statistical Significance for Drug at Specific Dosages | Associated Value and Statistical Significance for Placebo |
|---|---|---|
| Reduction in endpoint mean pain scores (mean of the last 7 daily pain scores while on study medication) | Significantly larger reduction from baseline, (p < 0.05) only at 225 mg BID. | |
| Proportion of responders | 150 mg BID: 67% 225 mg BID: 73% 300 mg BID: 65% | 76% |
A dose-related increase in adverse events and withdrawals due to adverse events was observed (see 8.2 Clinical Trial Adverse Reactions).
Patients recorded their pain on a daily diary using an 11-point numerical pain rating (Likert) scale ranging from 0=“no pain” to 10=“worst possible pain”. Treatment differences, defined as the change in endpoint mean pain scores for pregabalin versus placebo (drug – placebo), were calculated.
The primary efficacy endpoint in the 26-week long-term relapse observation study was the time to loss of therapeutic response as determined from the Pain Visual Analog Scale (VAS) or from worsening of fibromyalgia symptoms necessitating an alternative treatment per the clinical judgment of the principal investigator. Secondary endpoints included the time to worsening of PGIC, FIQ, and MOS-SS scores.
A 26-week long-term relapse observation study compared pregabalin with placebo. Patients who met the American College of Rheumatology criteria for fibromyalgia (history of widespread
MAR-PREGABALIN (Pregabalin) Capsules
pain for 3 months, and pain present at 11 or more out of 18 specific tender points) and with a score of ≥ 40 mm on the pain Visual Analog Scale (VAS) were eligible to enter a 6-week, open- label, dose-optimization phase. During this phase, patients were titrated up to a total daily dose of 300 mg, 450 mg, or 600 mg. Patients were considered to be pregabalin responders if they had both at least a 50% reduction in pain on the VAS and rated their overall improvement on the PGIC as “much improved” or “very much improved.” A total of 566 pregabalin responders were then randomized in the double-blind phase to either their optimized pregabalin dose (279 patients) achieved in the open-label phase (therapy continued) or to placebo (287 patients; therapy discontinued). Patients were treated for up to 26 weeks in the double-blind phase. Treatment with pregabalin resulted in a significantly longer time to loss of therapeutic response than treatment with placebo (p < 0.0001), with fewer relapses on pregabalin (32%) compared to placebo (61%). Of the pregabalin responders entering the double-blind phase assigned to remain on pregabalin, 38% completed 26 weeks of treatment, versus 19% of those assigned to receive placebo. All supplemental and secondary endpoints were supportive of the primary efficacy measure.
14.3 Comparative Bioavailability Studies
A double blinded, randomized, two-treatment, two period, single-dose, cross-over bioequivalence study comparing MAR-Pregabalin 25mg capsules, (Marcan Pharmaceuticals Inc.) to PrLYRICA® 25mg capsules (Pfizer Canada Inc.) was conducted in 31 healthy adult, human male subjects under fasting conditions. The results are presented in the table below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Pregabalin (1x 25 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | Confidence Interval |
| AUC0-t (ng*hr/mL) | 6200.84 6262.05 (14.10) | 6095.23 6144.78 (12.83) | 101.83 | 99.82-103.88 |
| AUC0-∞ (ng*hr/mL) | 6551.67 6612.57 (13.73) | 6457.78 6505.830 (12.35) | 101.54 | 99.65-103.46 |
Cmax (ng/mL) | 959.32 984.84 (23.76) | 896.93 913.13 (19.25) | 106.80 | 99.37-114.79 |
Tmax3 (h) | 0.83 (0.50-1.83) | 0.83 (0.50-2.25) | Not Applicable | Not Applicable |
t1/24 (h) | 6.33 (11.43) | 6.42 (13.03) | Not Applicable | Not Applicable |
1 MAR-Pregabalin 25 mg capsules (Marcan Pharmaceuticals Inc.)
2 PrLYRICA® 25 mg capsules (Pfizer Canada Inc.,) purchased in Canada.
3 Expressed as the median (range).
4 Expressed as the arithmetic mean (CV %) only.
MAR-PREGABALIN (Pregabalin) Capsules
A double blinded, randomized, two-treatment, two period, single-dose, cross-over bioequivalence study comparing MAR-Pregabalin 300mg capsules, (Marcan Pharmaceuticals Inc.) to PrLYRICA® 300mg capsules (Pfizer Canada Inc.) was conducted in 29 healthy adult, human male subjects under fasting conditions. The results are presented in the table below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Pregabalin (1x 300 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | Confidence Interval |
| AUC0-t (ng*hr/mL) | 63901.95 64300.34 (11.27) | 63738.14 64062.84 (10.07) | 100.28 | 98.84-101.74 |
| AUC0-∞ (ng*hr/mL) | 66262.14 66747.69 (12.32) | 65963.88 66332.38 (10.56) | 100.48 | 98.94-102.05 |
| Cmax (ng/mL) | 7724.77 7806.27 (14.44) | 7907.71 8003.39 (15.69) | 97.59 | 93.51-101.84 |
Tmax3 (h) | 1.50 (0.67-3.00) | 1.50 (0.50-2.25) | Not Applicable | Not Applicable |
t1/2 4 (h) | 6.09 (12.36) | 5.96 (11.84) | Not Applicable | Not Applicable |
1 MAR-Pregabalin 300 mg capsules (Marcan Pharmaceuticals Inc.).
2 PrLyrica® 300 mg capsules (Pfizer Canada Inc.,) were purchased in Canada.
3 Expressed as the median (range)
4 Expressed as the arithmetic mean (CV %) only
15. MICROBIOLOGY
No microbiological information is required for this drug product.
16. NON-CLINICAL TOXICOLOGY
General Toxicology
The acute toxicity of pregabalin is low. Animals given oral doses of pregabalin in acute and repeated-dose studies were hypoactive, hyperactive, and/or ataxic, signs commonly observed with CNS-active drugs. No significant target organ toxicity was observed in rats treated for up to 52 weeks or in monkeys treated for up to 69 weeks at exposures at least 8 times the mean human exposure at the maximum recommended dose of 600 mg/day. Effects of pregabalin in juvenile animals were similar to those in adults.
Acute Toxicity
Acute oral and IV studies were conducted in mice and rats. Hypoactivity in mice and rats, and diarrhea and urine staining in rats, but no deaths or changes in clinical biochemical parameters,
MAR-PREGABALIN (Pregabalin) Capsules
occurred following administration of single oral doses of 5000 mg/kg or single IV doses of 300 mg/kg, the highest IV dose achievable based on solubility and dose volume limitations. No drug-related gross or histopathologic changes were observed in rodents given single oral or IV doses.
Repeated-Dose Toxicity
Repeated-dose studies in definitive toxicology species are listed in Table 16 and results are discussed in the sections below.
Table 31. Repeated-Dose Oral Studies with Pregabalin
| Species | Duration (Weeks) | Dose Range (mg/kg) |
|---|---|---|
| Rat | 2 | 500 – 2500 |
| 4 | 500 – 5000 | |
| 4 | 50 – 250 | |
| 13 | 50 – 1250 | |
| 26/52 | 50 – 500 | |
| Monkey | Escalating-Dose | 50 – 2000 |
| 2 | 100 – 2000 | |
| 4 | 100 – 2000 | |
| 4-day (toxicokinetic) | 500 – 1000 | |
| 4 | 25 - 500 BID | |
| 13 | 10 – 500 | |
| 65-69 | 10 -500 |
Rat: Ataxia and hypoactivity were seen in rats given repeated oral doses ≥ 500 mg/kg with associated AUC (0-24) ≥ 1280 mcg•hr/mL; tail dermatopathy and urine staining were seen at
≥ 250 mg/kg with associated AUC(0-24) ≥ 802 mcg•hr/mL. Body weight gain decreased 18% to 70% in rats given pregabalin at 500 to 5000 mg/kg for 4, 13, or 52 weeks. No effects on body weight gain occurred at 50 or 250 mg/kg for 52 weeks with associated exposures
≤ 1210 mcg•hr/mL. Urinary bladder changes (dilatation, edema, and hemorrhage) and sporadic mortality associated with pyelonephritis and/or cystitis occurred in rats at ≥ 250 mg/kg; associated AUC(0-24) was ≥ 802 mcg•hr/mL. Red blood cell (RBC) parameters increased 6% to 16% in rats given pregabalin at 500 to 5000 mg/kg for 4 weeks, and were reversible. RBC count only increased 5% to 11% at 50 to 1250 mg/kg in Weeks 13, 26, and 52 with associated exposures ≥ 228 mcg•hr/mL. Platelet count decreased 14% to 36% in male rats given ≥ 50 mg/kg and in female rats given ≥ 100 mg/kg for up to 52 weeks with associated AUC(0- 24) ≥ 228 mcg•hr/mL. Changes in platelet count were reversed during a 4-week withdrawal period after 4 weeks of dosing. Total nucleated cells in the bone marrow decreased 18% to 44% in rats given
MAR-PREGABALIN (Pregabalin) Capsules
pregabalin at 250 to 1250 mg/kg for 13, 26, or 52 weeks. No drug-related effects on bone marrow occurred at 50 mg/kg for up to 52 weeks with associated exposures ≤ 228 mcg•hr/mL. In rats given pregabalin for 4 weeks, epididymal hypospermia occurred at ≥ 500 mg/kg and spermatogenic epithelial degeneration occurred at 1250 mg/kg with associated AUC(0-24) ≥ 1690 mcg•hr/mL. Similar changes were not seen in the 52-week study at doses up to 500 mg/kg. No adverse effects were observed in rats given 50 mg/kg for 13 weeks, with associated combined-sex AUC(0-24) of 188 mcg•hr/mL; effects at this dose in the 52-week study were minimal.
Monkeys: Nasal discharge and soft feces/diarrhea occurred in monkeys given repeated oral doses ≥ 100 mg/kg for up to 13 weeks, with associated AUC(0-24) ≥ 398 mcg•hr/mL. Hypoactivity occurred at ≥ 500 mg/kg; AUC(0-24) was at least 974 mcg•hr/mL. Deaths occurred within 3 days after treatment initiation in monkeys given 500 mg/kg BID or 1000 or 2000 mg/kg. Although toxicokinetic data were not available for all these monkeys, the lowest AUC(0-24) in an animal that died was 1640 mcg•hr/mL. Myocardial effects seen in monkeys at ≥ 50 mg/kg in 4-week studies were not seen in subchronic and chronic studies and, therefore, not considered drug-related. There were no effects on body weight gain, hematology, or bone marrow parameters in monkeys given pregabalin at 10 to 500 mg/kg for up to 69 weeks. Sperm count, motility, and morphology were not affected in monkeys given up to 500 mg/kg for 69 weeks. Tail dermatopathy was observed in monkeys at ≥ 25 mg/kg. With the exception of tail dermatopathy, no significant effects were observed in monkeys given up to 500 mg/kg up to 69 weeks with associated plasma concentrations up to 76.2 mcg/mL. Based on the 4- week toxicokinetic profiles and single time point samples in Week 52, combined-sex AUC(0-24) was estimated to be 1040 mcg•hr/mL.
The etiology of these skin lesions seen in both rats and monkeys in repeated-dose toxicology studies is unknown. At the maximum recommended human dose (MRD) of 600 mg/day, there is a 2-fold safety margin for the dermatological lesions. The more severe dermatopathies involving necrosis were associated with pregabalin exposures (as expressed by plasma AUCs) of approximately 3 to 8 times those achieved in humans given the MRD. No increase in incidence of skin lesions was observed in clinical studies.
Genotoxicity
The genotoxic potential of pregabalin was evaluated in an extensive battery of tests. Pregabalin was not mutagenic in bacteria up to 5000 mcg/plate with or without metabolic activation provided by postmitochondrial supernatant fractions from livers of B6C3F1 or
CD-1 mice or Wistar rats treated with Arochlor 1254. In mammalian cells in vitro, no evidence of mutagenicity or structural chromosome aberrations was observed up to 1600 mcg/mL with or without metabolic activation. Pregabalin did not induce unscheduled DNA synthesis in hepatocytes of B6C3F1 or CD-1 mice or Wistar rats given single oral doses up to 2000 mg/kg. Micronucleus frequency was not increased in bone marrow from B6C3F1 or CD-1 mice or Wistar rats given single oral doses of pregabalin up to 2000 mg/kg.
These results demonstrate pregabalin is not genotoxic in vitro or in vivo.
Mutagenenicity Pregabalin is not genotoxic based on results of a battery of in vitro and in vivo tests. Pregabalin was not mutagenic in bacteria or in mammalian cells in vitro, was not
MAR-PREGABALIN (Pregabalin) Capsules
clastogenic in mammalian systems in vitro and in vivo, and did not induce unscheduled DNA synthesis in mouse or rat hepatocytes.
Carcinogenicity
Dose-dependent increase in the incidence of malignant vascular tumors (hemangiosarcomas) was observed in two strains of mice (B6C3F1 and CD-1) given pregabalin (200, 1000, or
5000 mg/kg) in the diet for two years. Plasma pregabalin exposure (AUC) in mice receiving the lowest dose that increased hemangiosarcomas was approximately equal to the human exposure at the maximum recommended dose (MRD) of 600 mg/day. A no-effect dose for induction of hemangiosarcomas in mice was not established. In an investigative study in female B6C3F1 mice, chronic treatment (24 months) with pregabalin at 1000 mg/kg caused an increased incidence of hemangiosarcoma, consistent with previous studies, but not at 50 or 200 mg/kg. Discontinuation of treatment after 12 months at 1000 mg/kg did not significantly reduce the incidence of hemangiosarcoma at 24 months. Evidence of carcinogenicity was not seen in two studies in Wistar rats following dietary administration of pregabalin for two years at doses (50, 150, or 450 mg/kg in males and 100, 300, or 900 mg/kg in females) that were associated with plasma exposures in males and females up to approximately 14 and 24 times, respectively, human exposure at the MRD. The clinical significance in humans of this finding in mice is unknown.
Ocular lesions (characterized by retinal atrophy [including loss of photoreceptor cells] and/or corneal inflammation/mineralization) were observed in two lifetime carcinogenicity studies in Wistar rats. These findings were observed at plasma pregabalin exposures (AUC) ≥ 2 times those achieved in humans given the maximum recommended dose of 600 mg/day. A no-effect dose for ocular lesions was not established. Similar lesions were not observed in lifetime carcinogenicity studies in two strains of mice or in monkeys treated for 1 year. The clinical significance of this finding in rats is unknown.
Reproductive and Developmental Toxicology
In female rats, although estrus and diestrus stages were prolonged at 1250 and 2500 mg/kg, no effects on fertility were observed in females given 500 to 2500 mg/kg prior to mating with untreated males. In male rats, pregabalin administration resulted in decreased sperm motility and decreased fertility at exposures ≥ 27 times the mean human exposure at the maximum recommended clinical dose and were reversible. There were no drug-related effects on sperm parameters in monkeys treated for 69 weeks with exposures up to 8 times the maximum human exposure.
In a double-blind, placebo-controlled clinical trial to assess the effect of pregabalin on sperm motility, 30 healthy male subjects were exposed to pregabalin at a dose of 600 mg/day. After 3 months of treatment (one complete sperm cycle), the difference between placebo- and pregabalin-treated subjects in mean percent sperm with normal motility was < 4% and neither group had a mean change from baseline of more than 2%. Effects on other male reproductive parameters in humans have not been adequately studied (see 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential).
Pregabalin induced maternal toxicity in embryo-fetal development studies in rats at ≥ 500 mg/kg
MAR-PREGABALIN (Pregabalin) Capsules
and rabbits at ≥ 250 mg/kg, and fetal toxicity in rats at 2500 mg/kg and in rabbits at 1250 mg/kg. Pregabalin was not teratogenic in mice, rats, or rabbits at exposures 31 to 77 times the mean human exposure at the maximum recommended clinical dose of 600 mg/day. In the prenatal-postnatal toxicity study in rats, pregabalin induced offspring developmental toxicity at exposures ≥ 5 times the mean human exposure. No effects occurred at exposures twice the mean human exposure at the maximum recommended clinical dose (see 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential).
Pregabalin is excreted in milk of lactating rats. Because of the potential exposure in breast- feeding infants, breast feeding is not recommended (see 7 WARNINGS AND PRECAUTIONS, Patient Counselling Information).
17. SUPPORTING PRODUCT MONOGRAPHS
- 1. PrLYRICA®, Capsules, 25, 50, 75, 150, 225, 300 mg, Submission Control 279480, Product Monograph, BGP Pharma ULC. (MAR 04, 2024).