


Product Monograph - Menjugate
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength per 0.5mL dose of reconstituted vaccine | Clinically Relevant Nonmedicinal Ingredients |
| Intramuscular (IM) Injection | Powder for Suspension for reconstitution with a diluent 10 μg Meningococcal Group C Oligosaccharide conjugated to 12.5 to 25 μg CRM197 | Aluminum hydroxide adjuvant For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Menjugate (Meningococcal Group C–CRM197 Conjugate Vaccine) is indicated for the active immunization of children from 2 months of age, adolescents and adults, for the prevention of invasive disease caused by Neisseria meningitidis serogroup C.
CONTRAINDICATIONS
Menjugate (Meningococcal Group C–CRM197 Conjugate Vaccine) is contraindicated in persons with a known hypersensitivity to any component of the vaccine and in persons who have shown signs of hypersensitivity after previous administration of Menjugate.
As with other vaccines, administration of Menjugate should be postponed in subjects with an acute severe febrile illness.
WARNINGS AND PRECAUTIONS
General
Before the injection of any biological, the health professional responsible for administration should take all precautions known for the prevention of allergic or any other reactions. As with all injectable vaccines, appropriate medical treatment and supervision should always be readily available in case of a rare anaphylactic event following administration of the vaccine.
Prior to administration of any dose of Menjugate (Meningococcal Group C-CRM 197 Conjugate Vaccine), the vaccine recipient (or parent or guardian) should be asked about personal history, family history, and recent health status, including immunization history, current health status and any adverse event associated with previous immunizations.
Menjugate (Meningococcal Group C-CRM197 Conjugate Vaccine) will not protect against meningococcal diseases caused by any of the other types of meningococcal bacteria (A, B, 29-E, H, I, K, L, W-135, X, Y, or Z, including non-typed). Complete protection against meningococcal serogroup C infection cannot be guaranteed.
Although symptoms of meningism such as neck pain/stiffness or photophobia have been reported, there is no evidence that the vaccine causes meningococcal C meningitis. Clinical alertness to the possibility of co-incidental meningitis should therefore be maintained.
Conjugate vaccines containing Cross Reacting Material 197 (CRM197) should not be considered as immunizing agents against diphtheria. No changes in the schedule for administering vaccines containing diphtheria toxoid are recommended.
Any acute infection or febrile illness is reason for delaying the use of Menjugate except when, in the opinion of the physician, withholding the vaccine entails a greater risk. A minor afebrile illness, such as a mild upper respiratory infection, is not usually reason to defer immunization.
The vaccine must not be injected intravenously, subcutaneously or intradermally.
Parents should be informed of the immunization schedule for this vaccine. Precautions such as use of antipyretic measures should be relayed to the parent or guardian, as well as the need to report any adverse event.
The tip cap of the diluent syringe contains 10% Dry Natural Rubber. Although the risk for developing allergic latex reactions is very small, healthcare professionals are encouraged to consider the benefit risk prior to administering this vaccine to patients with known history of hypersensitivity to latex.
Hematologic
Menjugate has not been evaluated in persons with thrombocytopenia or other bleeding disorders. The risk versus benefit for persons at risk of hemorrhage following intramuscular injection must be evaluated.
Immune
In individuals deficient in antibody production, vaccination may not result in an appropriate protective antibody response. While HIV infection is not a contraindication to vaccination, Menjugate has not been specifically evaluated in an immunocompromised population.
Individuals with complement deficiencies and individuals with functional or anatomical asplenia may mount an immune response to meningococcal C conjugate vaccines; however, the degree of protection that would be afforded is unknown.
Special Populations
Pregnant Women: Animal studies have not demonstrated a risk to the fetus following administration of Menjugate. However, since no specific studies in humans have been carried out, caution is advised. The vaccine should not be used during pregnancy unless there is defined risk of meningococcal C disease, in which case the risk-benefit ratio should be evaluated.
Nursing Women: The effect on breast-fed infants of the administration of Menjugate to their mothers has not been studied. The risk-benefit ratio should be examined before making the decision as to whether to immunize during lactation.
Geriatrics (> 65 years of age): There are no data in adults aged 65 years and older.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In controlled clinical studies performed in all age groups, signs and symptoms were actively monitored and recorded on diary cards following administration of the vaccine.
Of the local solicited symptoms, the most frequently reported were injection-site pain, erythema and swelling, which were normally mild and resolved within 24-72 hours following vaccination.
The general symptoms that have been solicited and reported were predominantly mild and resolved spontaneously. These include headache, malaise, nausea, arthralgia and myalgia in adolescents and adults; and irritability, change in appetite, diarrhea and fever in younger children. These solicited general symptoms were also reported in the control groups and have been reported when Menjugate (Meningococcal Group C–CRM197 Conjugate Vaccine) was administered concomitantly with other vaccines.
In infants and toddlers symptoms including crying, irritability, drowsiness, impaired sleeping, anorexia, diarrhea and vomiting were common after vaccination but there was no evidence that these were related to Menjugate rather than concomitant vaccines, particularly DTP.
Toddlers Through Adults:
Table 1 presents an analysis of local and systemic reactions occurring within 7 days after one immunization with Menjugate. Data are pooled from 11 studies, representing approximately 1400 subjects. Most local and systemic reactions occurred by day 1 following immunization. In general, lower percentages of local and systemic reactions were present on days 2 through 6 following the first immunization.
Table 1 - Summary of Local and Systemic Post immunization Reactions Within 7 Days Following One Immunization of Menjugate, by Age Group at Enrollment*
| Percentage of Subjects | ||||||
Menjugate 1-2 years n=942 (%) | Menjugate 3-5 years n=198 (%) | Menjugate 11-64 years n=269 (%) | ||||
| Injection Site | ||||||
Pain (Any) Severe | 22 <1 | 25 0 | 81 2 | |||
Temperature (Any) Hot | 15 <1 | 5 1 | 47 8 | |||
Erythema (Any) >50 mm | 28 <1 | 16 0 | 19 1 | |||
Induration (Any) >50 mm | 16 <1 | 7 0 | 24 1 | |||
| Systemic | ||||||
| Change in Eating Habits | 16 | 6 | - | |||
| Sleepiness | 19 | 9 | - | |||
| Unusual Crying | 4 | 1 | - | |||
| Persistent Crying | 1 | 0 | - | |||
| Irritability | 30 | 10 | - | |||
| Vomiting | 9 | 5 | - | |||
| Diarrhea | 18 | 8 | - | |||
| Rash | 9 | 4 | - | |||
| Chills | - | - | 13 | |||
| Nausea | - | - | 16 | |||
| Malaise | - | - | 25 | |||
| Myalgia | - | - | 29 | |||
| Arthralgia | - | - | 16 | |||
| Headache | - | - | 34 | |||
| Temp ≥38°C | 9 | 4 | 2 | |||
| Stayed Home Due to Reaction | - | - | 7 | |||
| Analgesic/ Antipyretic Medication used | 25 | 9 | 18 | |||
*This is a summary of data derived from a meta-analysis of 11 studies conducted in the United States, United Kingdom, Netherlands, and Canada. The recording of systemic reactions varied by age group, not all reactions were collected in all studies.
In clinical studies where subjects received Menjugate or a meningococcal polysaccharide vaccine, the rates of local pain and warmth were significantly lower with Menjugate in toddlers and children 3 to 5 years of age; no differences were seen in the older subjects. In children 3 to 5 years of age, severe pain was seen in 9% of subjects with the polysaccharide vaccine and no subjects with Menjugate. The systemic reactions that were significantly less common in Menjugate subjects were fever, change in eating habits, irritability, and analgesic/antipyretic use in toddlers, and irritability and analgesic/antipyretic use in children 3 to 5 years of age.
In adolescents and adults, the rates of all postimmunization reactions were similar after Menjugate or polysaccharide vaccine administration. The only difference seen in this age group was a tendency for injection-site pain to persist somewhat longer in Menjugate recipients (72 hours) than in polysaccharide vaccine recipients (48 hours). This difference may be due to the aluminum hydroxide adjuvant, which is present in Menjugate but not the polysaccharide vaccine.
Infants:
Table 2 presents a summary of clinical safety data from two clinical studies in infants who received up to three immunizations with Menjugate, beginning at the age of two months.
Table 2- Summary of Local and Systemic Post immunization Reactions Within 7 Days Following 1, 2 or 3 Injections of Menjugate
| Percentage of Subjects | ||||||||||||
UK (Multicenter) (N=467) | Canada (Multicenter) (N=175) | |||||||||||
| Age at First Immunization | 2 months | 2 months | ||||||||||
| Schedule | 3 doses 1 month apart | 3 doses 2 months apart | ||||||||||
| Concomitant Vaccine | DTP, HIB, OPV | DTaP, HIB, IPV (PENTACEL) | ||||||||||
| Local Reactions: | ||||||||||||
| Tenderness | 31% | 22% | ||||||||||
| Erythema>25 mm | 7% | 0% | ||||||||||
| Induration>25 mm | 4% | 0% | ||||||||||
| Systemic Reactions: | ||||||||||||
| Irritability | 81% | 68% | ||||||||||
| Sleepiness | 69% | 54% | ||||||||||
| Change in Eating Habits | 46% | 39% | ||||||||||
| Diarrhea | 43% | 28% | ||||||||||
| Vomiting | 34% | 19% | ||||||||||
| Rash | 16% | --* | ||||||||||
| Temp≥38°C | 4% | 21% | ||||||||||
| High-pitched crying | 38% | --* | ||||||||||
| Persistent crying | 16% | 4% | ||||||||||
* Data not collected
In a randomized, controlled clinical study performed in infants at three centers in Canada, the profile for Menjugate administered at 2, 4, and 6 months of age with concomitant PENTACEL (DTaP/Hib/IPV) was similar to that observed in earlier infant studies (See Tables 3 and 4 below). The frequency of two local adverse events, induration and erythema, was higher in Menjugate recipients than in the control HBV vaccine subjects, however the incidence of these reactions was lower among Menjugate or HBV subjects than following the routine vaccine (DTaP/Hib/IPV) in these same subjects. These differences between the Menjugate and HBV groups may in part be related to the lower dose of aluminum hydroxide in the HBV vaccine relative to the Menjugate vaccine (i.e., 0.5 mg per dose in HBV compared with 1 mg per dose in Menjugate). The most frequently reported systemic reactions were irritability, analgesic/antipyretic medication use, sleepiness and change in eating habits, which were reported with similar frequency in Menjugate and HBV vaccine subjects.
Table 3- Local Reactogenicity Within 7 Days Following Any Immunization Infant Study - Canada (Multicenter)
Menjugate group N=175 | HBV group N=176 | P-value MenC vs HBV group | |||||||||||
| Local Reactions | Menjugate | PENTACEL | HBV | PENTACEL | Study Vaccine | PENTACEL | |||||||
Tenderness (Any) (Cried when injected leg moved) | 38 (22%) 0 | 53 (30%) 3 (2%) | 31 (18%) 0 | 35 (20%) 0 | .33 | .025 | |||||||
Erythema (Any) >25 mm | 55 (31%) 0 | 67 (38%) 5 (3%) | 33 (19%) 0 | 63 (36%) 4 (3%) | .006 | .63 | |||||||
Induration (Any) >25 mm | 42 (24%) 0 | 65 (37%) 6 (3%) | 19 (11%) 1 (1%) | 70 (40%) 2 (1%) | .001 | .61 | |||||||
Table 4- Systemic Reactogenicity Within 7 Days Following Any Immunization Infant Study - Canada (Multicenter)
| Systemic Reactions | Menjugate group N=175 | HBV group N=176 | P-value |
| Change in Eating Habits | 68 (39%) | 63 (36%) | .55 |
| Sleepiness | 94 (54%) | 98 (56%) | .71 |
| Persistent Crying | 7 (4%) | 4 (2%) | .35 |
| Irritability | 119 (68%) | 124 (70%) | .62 |
| Vomiting | 34 (19%) | 39 (22%) | .53 |
| Diarrhea | 49 (28%) | 44 (25%) | .52 |
| Rectal temp ≥ 38°C | 37 (21%) | 47 (27%) | .22 |
| Analgesic/antipyretic medication required | 96 (55%) | 105 (60%) | .36 |
Less Common Clinical Trial Adverse Drug Reactions (<1%)
In clinical trials of Menjugate, approximately 6700 infants through adults were evaluated/ monitored for the occurrence of serious adverse experiences (SAEs). There were four SAEs which were considered to be at least possibly related to vaccine. These were one report each of: hypotonia, screaming syndrome, maculopapular rash and agitation, all of which occurred in an open label infant study conducted in the United Kingdom (UK), in which Menjugate was administered concomitantly with DTP, Hib and OPV vaccines. Because these reactions have been reported previously in conjunction with DTP vaccines alone, a causal relationship between these experiences and Menjugate administration cannot be established.
Post-Market Adverse Drug Reactions
The most commonly reported suspected reactions in post marketing surveillance include dizziness, pyrexia, headache, nausea, vomiting and faints.
The frequencies given below are based on spontaneous reporting rates, for this and other Meningococcal C Conjugate vaccines and have been calculated using the number of reports received as the numerator and the total number of doses distributed as the denominator.
Immune System Disorders:
Very rare (<0.01%): lymphadenopathy, anaphylaxis (including anaphylactic shock), hypersensitivity reactions including bronchospasm, facial edema and angioedema.
Neurologic:
Very rare (<0.01%): dizziness, convulsions including febrile convulsions, faints, hypesthesia, paresthesia and hypotonia.
There have been very rare reports of seizures following Menjugate vaccination; individuals have usually recovered rapidly. Some of the reported seizures may have been faints. The reporting rate of seizures was below the background rate of epilepsy in children. In infants seizures were usually associated with fever and were likely to be febrile convulsions.
There have been very rare reports of visual disturbances and photophobia following vaccination with Meningococcal group C conjugate vaccines, usually in conjugation with other neurological symptoms like headache and dizziness.
Skin and Subcutaneous tissue disorders:
Very rare (<0.01%): rash, urticaria, pruritus, purpura, erythema multiforme and Stevens-Johnson Syndrome.
Gastrointestinal:
Very rare (<0.01%): nausea, vomiting and diarrhea.
General disorders and administrative site conditions
Extensive swelling of the vaccinated limb
Musculoskeletal, connective tissue and bone disorders:
Very rare (<0.01%): myalgia and arthralgia.
Renal:
Relapse of nephrotic syndrome has been reported in association with Meningococcal group C conjugate vaccines.
DRUG INTERACTIONS
Drug-Drug Interactions
Administration of Menjugate at the same time as IPV, DTP, Hib, DTaP, DT, Td, MMR and HBV1 vaccines or with OPV does not reduce immunological responses to any of these other antigens. 2 Menjugate should not however, be administered via the same injection as other vaccines. Minor variations in GMT antibody titers were observed between studies; however, the clinical significance, if any, of these observations is not established.
Table 5 presents data on the immunological response of infants to concomitant vaccines, as measured one month after the third dose of Menjugate or HBV vaccine.
Table 5- Response to Routine Infant Concomitant Vaccine (PENTACEL) Antigens Among Menjugate vs HBV Vaccine Recipients Measured at 1 Month After Third Dose
Infant Study - Canada (Multicenter) 3
| Concomitant Vaccine Antigen, Measure of Response | Group | ||||||||||
| MenC | HBV | P-value | |||||||||
| N=64 | N=61 | ||||||||||
| Polio type I | % with antibody titers ≥1:8 | 97% | 95% | .53 | |||||||
| Polio type II | % with antibody titers ≥1:8 | 98% | 100% | .32 | |||||||
| Polio type III | % with antibody titers ≥1:8 | 98% | 98% | .94 | |||||||
Diphtheria toxin antibody responses | GMT (IU/mL) | 4.7 | 1.9 | < .001 | |||||||
| % ≥ 0.10 IU/mL | 100% | 100% | 1.0 | ||||||||
| Tetanus antibody response | GMT (IU/mL) | 2.4 | 2.5 | .76 | |||||||
| % ≥ 0.1 IU/mL | 100% | 100% | 1.0 | ||||||||
| N=91 | N=89 | ||||||||||
| Anti-pertussis with 69K antigen | GMT (EU/mL) | 31 | 36 | .29 | |||||||
| Anti-pertussis with FHA antigen | GMT (EU/mL) | 26 | 31 | .12 | |||||||
| Anti-pertussis with PT antigen | GMT (EU/mL) | 23 | 25 | .31 | |||||||
| N=148 | N=148 | ||||||||||
| PRP-T/Hib antibody responses | GMT (μg /mL) | 3.1 | 3.7 | .28 | |||||||
| % ≥ 1.0 μg/mL | 81% | 83% | .40 | ||||||||
DOSAGE AND ADMINISTRATION
Dosing Considerations
There are no data on the use of different meningococcal group C conjugate vaccines within the primary series or for boosting. Whenever possible, the same vaccine should be used throughout.
Recommended Dose and Dosage Adjustment
Primary Immunization: Infants 2-12 months should receive 3 doses of 0.5 mL each, with an interval of at least 1 month between doses.
Children older than 12 months, adolescents and adults should receive a single dose of 0.5 mL.
Booster doses
It is recommended that a booster dose should be given after completion of the primary immunization series in infants. The timing of this booster should be in accordance with NACI recommendations. The need for booster doses in subjects primed with a single dose (i.e. aged 12 months or more when first immunized) has not yet been established.
Administration
Do not inject intravenously, subcutaneously or intradermally. Menjugate (Meningococcal Group C–CRM197 Conjugate Vaccine) is to be administered by deep intramuscular injection only, preferably in the anterolateral thigh in infants and in the deltoid region in older children, adolescents and adults.
Care must be taken to ensure the vaccine is not injected into a blood vessel.
Menjugate should not be mixed with other vaccines in the same syringe. Separate injection sites should be used if more than one vaccine is being administered on the same date.
Reconstitution:
The following instructions should be adhered to with respect to the reconstitution of lyophilized Menjugate. Use aseptic technique.
Vial of vaccine plus vial of diluent:
Gently agitate the aluminum hydroxide diluent vial. Withdraw 0.6 mL of the suspension and inject it into the Menjugate vial. Gently shake the vial until the cake is dissolved (this will ensure the antigen is bound to the adjuvant). Withdraw 0.5 mL of reconstituted vaccine.
Vial of vaccine plus syringe of diluent:
Gently agitate the syringe containing the aluminum hydroxide diluent. Remove the tip cap from the syringe and attach a suitable needle. Use the whole content of the syringe (0.6 mL of suspension) to reconstitute the Menjugate vial.
Gently shake the reconstituted vial until the vaccine is dissolved (this will ensure the antigen is bound to the adjuvant). Taking care not to withdraw the plunger completely out of the barrel of the syringe, withdraw the full contents of the vial into the syringe. Note that it is normal for a small residual amount of liquid to remain in the vial following withdrawal of the dose.
The amount of reconstituted vaccine in the syringe can be compared to the scale in the drawing below, to confirm that a sufficient dose of the vaccine has been withdrawn.
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL |
| 3ml vial containing lyophilised vaccine | 0.6 mL | 0.5 mL following reconstitution | Meningococcal Group C Oligosaccharide (20 µg) conjugated to CRM197 (25.0 to 50.0 µg) |
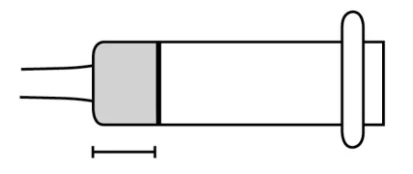
recommended dose (0.5 mL)
A new needle with a gauge and length suitable for intramuscular injection should be used to administer the product. Ensure that no air bubbles are present in the syringe before injecting the vaccine.
Following reconstitution, Menjugate should be used immediately.
OVERDOSAGE
There is no experience of overdosage with Menjugate.
ACTION AND CLINICAL PHARMACOLOGY
Menjugate (Meningococcal Group C–CRM197 Conjugate Vaccine) is intended for the prevention of meningitis and/or septicemia caused by Neisseria meningitidis group C in infants and older age groups. Menjugate is composed of meningococcal group C oligosaccharides conjugated to a protein carrier, a non-toxic mutant of diphtheria toxin, CRM197. In the final vaccine, aluminum hydroxide is used as an adjuvant.
As shown in clinical trials, Menjugate is highly immunogenic 4,5 and induces protective levels of bactericidal antibodies6-8 in a significant number of subjects after vaccination. (See CLINICAL TRIALS.)
Compared to licensed unconjugated polysaccharide vaccines, the primary immune response induced by Menjugate is superior in toddlers, children and adolescents,9 and is comparable in adults.
Additionally, unlike unconjugated polysaccharide vaccines,10 Menjugate has been shown to induce immunologic memory in infants, toddlers and older children.2,11,12
No pharmacodynamic or pharmacokinetic studies have been conducted with Menjugate, in accordance with its status as a vaccine. Several immunogenicity studies were conducted in animals, showing that Menjugate induced antibody titers that were dose dependent. (See Detailed Pharmacology).
STORAGE AND STABILITY
Primary storage condition: Store under refrigeration (+2°C to +8°C). Do not freeze. Protect from exposure to light. Stability studies have indicated that the lyophilized product has a shelf life of 36 months. Menjugate vials and the vials or syringes of aluminum hydroxide diluent may have different expiry dates, so health care professionals are advised that the outer carton bears the earlier of the two dates and that this date must be respected. The carton and ALL its contents should be discarded on reaching this outer carton expiry date.
Alternative storage condition (Before reconstitution): Do not store above 25°C. Do not freeze. Protect from exposure to light. The product should be used or discarded within 6 months of the date of removal from the refrigerator (+2 to +8°C) or on reaching the other carton expiry date (whichever comes first).
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage Forms
Menjugate is supplied as a 0.5 mL dose, consisting of one vial of vaccine and one vial or syringe of diluent.
The product is provided as a vial of sterile white lyophilised powder (Menjugate) together with a vial or syringe of aluminium hydroxide diluent. The diluent is a sterile white opalescent suspension Following reconstitution the vaccine is a slightly opaque homogeneous suspension, free from foreign particles.
Composition
Each single dose (0.5 mL) of reconstituted vaccine contains:
| Active Ingredients | |
| Neisseria meningitidis group C (strain C11) oligosaccharide - Conjugated to | 10 µg |
| Corynebacterium diphtheriae15 CRM-197 protein | 12.5 to 25.0 µg |
| Adjuvant | |
| Aluminium hydroxide | 1 mg |
| Excipients | |
| Sodium chloride | 3.5 mg |
| Sodium dihydrogen phosphate monohydrate | 0.092 mg |
| Diodium phosphate heptahydrate | 0.48 mg |
| Mannitol | 7.3 mg |
| Water for Injections | to 0.5 mL |
Menjugate contains no preservative.
Packaging
Both the diluent and the lyophilized vaccine are presented in Type I glass vials, with bromobutyl rubber stoppers. The diluent can also be presented in Type I glass syringes with Type I rubber plunger stoppers and tip caps: either chlorobutyl rubber or styrene butadiene rubber tip cap are used. The chlorobutyl rubber tip cap of the diluent syringe contains 10% Dry Natural Rubber.
Vial of vaccine plus vial of diluent: Pack sizes containing one and five doses are available.
Vial of vaccine plus syringe of diluent: Pack sizes containing one, five and ten doses are registered (although not all pack-sizes may be available on the Canadian Market).
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Meningococcal Group C–CRM197 Conjugate Vaccine
Chemical name: Not applicable
Molecular formula and molecular mass: Not applicable
Structural formula: Not applicable
Physicochemical properties: Not applicable
CLINICAL TRIALS
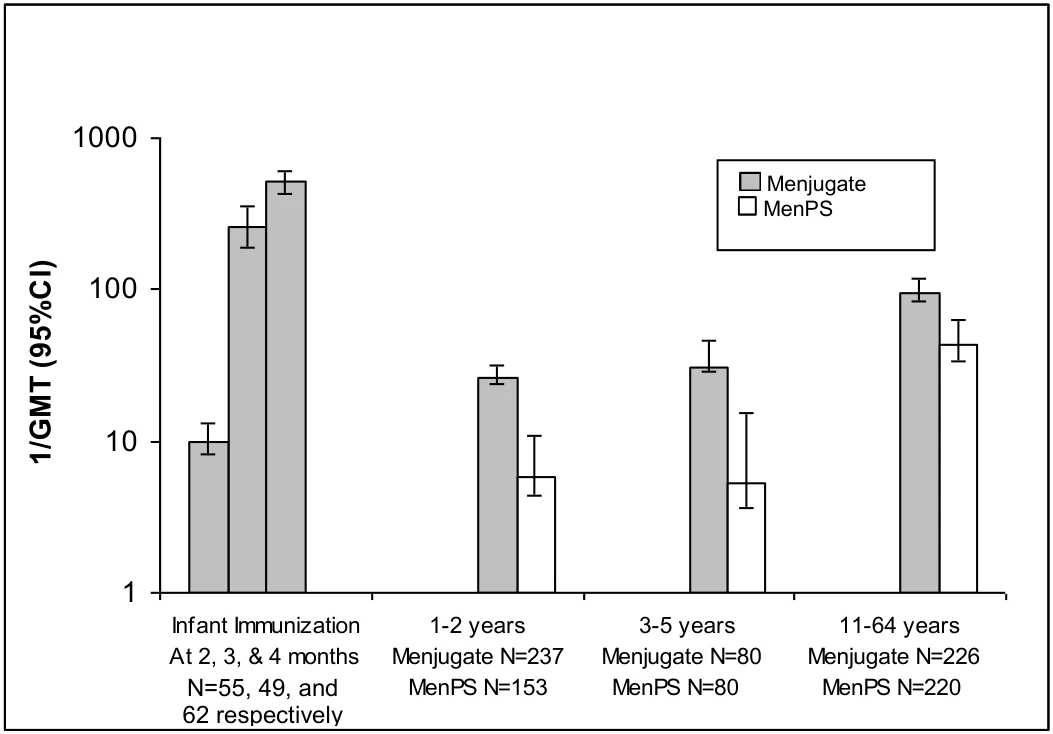
As shown in clinical trials, Menjugate is highly immunogenic4,5 and induces protective levels of bactericidal antibodies6-8 in a significant number of subjects after vaccination. (See Figure 1 below.) 9,11,13 Data from trials in infants using a 2, 3, 4 month schedule demonstrate that >98% of infants developed serum bactericidal antibody titers of at least 1:8 one month after the second and third dose.2 A booster dose in the second year of life induces an anamnestic response. 11,12,14
Compared to licensed unconjugated polysaccharide vaccines, the primary immune response induced by Menjugate is superior in toddlers, children and adolescents,9 and is comparable in adults.
Additionally, unlike unconjugated polysaccharide vaccines, 10 Menjugate has been shown to induce immunologic memory in infants, toddlers and older children. 2,11,12
Figure 1: Bactericidal Responses 1 Month following Menjugate or Meningococcal Polysaccharide (MenPS) Vaccine by Age*
*Infants did not receive MenPS vaccine
1/GMT (95% CI) = reciprocal geometric mean titer (95% confidence interval)
No pharmacodynamic or pharmacokinetic studies have been conducted with Menjugate, in accordance with its status as a vaccine. Several immunogenicity studies were conducted in animals, showing that Menjugate induced antibody titers that were dose dependent. (See DETAILED PHARMACOLOGY).
DETAILED PHARMACOLOGY
No pharmacodynamics studies and no pharmacokinetics studies have been conducted with Menjugate (Meningococcal Group C–CRM197 Conjugate Vaccine), in accordance with its status as a vaccine.
Animal Immunogenicity
Multiple immunogenicity studies were conducted in mice and guinea pigs to evaluate different subcutaneous dose levels of Meningococcal Group C–CRM197 conjugate (MenC conjugate) with and without the adjuvant aluminum hydroxide. Results showed that the induced antibody
titers were dose-dependent and were higher when the MenC conjugate was combined with the adjuvant. The number of animals responding increased with dose.
An immunogenicity study in infant baboons was also conducted16. Five infant baboons (1.5 to 4 months of age) per group were immunized with three intramuscular injections (0.5 mL each) of MenC conjugate in combination with a Hib conjugated vaccine reconstituted either with aluminum hydroxide or phosphate buffered saline (PBS). Injections were given four weeks apart.
Titers of serum antibodies to MenC conjugate were measured by an enzyme-linked immunosorbent assay (ELISA). Complement-mediated bactericidal activity against N meningitidis group C was measured in a bactericidal assay.
The MenC conjugate was well tolerated; there was no evidence of specific local reactions at the injection sites when animals were inspected four weeks after the injection. After two injections, high antibody titers to meningococcus group C (bactericidal) were observed in animals vaccinated with MenC conjugate adjuvanted with aluminum hydroxide, while MenC conjugate in PBS (no adjuvant) showed low titers at all times. The bactericidal assay response paralleled the ELISA results.
TOXICOLOGY
The nonclinical safety of intramuscular injections of single and multiple doses of Meningococcal Group C–CRM197 Conjugate Vaccine (equivalent to Menjugate®) was evaluated in rabbits. In each study, the human dose was administered to rabbits. Five studies were performed under Good Laboratory Practices (GLPs)17:
| 1 | Single dose intramuscular toxicity study | The vaccine was well tolerated. Slight, transient intramuscular injection site inflammation was seen, and was consistent with other alum-containing products. |
| 2 | Repeat-dose subacute toxicity study (three intramuscular injections) | Three injections of the vaccine were well tolerated (no effects on clinical signs including skin irritation, body temperature or weight, hematology or serum chemistry, ophthalmologic exams, or organ weights). Microscopic examination of muscle injection sites indicated mild inflammation. The mild inflammatory changes generally resolved within 2 weeks. |
| 3 | Repeat-dose subacute toxicity study (five intramuscular injections) | Five injections of the vaccine were well tolerated (no effects on clinical signs including skin irritation, body temperature or weight, hematology or serum chemistry, ophthalmologic exams, or organ weights). Slight to moderate |
| inflammatory changes in muscle injection sites were seen and were generally resolved within 2 weeks. | ||
| 4 | Dose range-finding study of the effects on embryo/fetal development (eight intramuscular injections) | Three doses of vaccine were administered prior to conception and five doses were given during gestation. No clinically relevant maternal toxicity was seen and there were no vaccine-related effects on the external appearance of fetuses. |
| 5 | Study of the effects on embryo/fetal development (eight intramuscular injections) | Three doses of vaccine were administered prior to conception and five doses were given during gestation. No clinically relevant maternal toxicity was seen and there were no vaccine-related effects on fetuses based on evaluation of external, soft tissue, skeletal, and developmental parameters. |
Overall, the vaccine was well tolerated and was associated with injection site findings consistent with the administration of any alum-adjuvanted vaccine.
REFERENCES
- 1. Schmitt HJ, Steul KS, Borkowski A, Ceddia F, Ypma E, Knuf M, Two versus three doses of a meningococcal C conjugate vaccine concomitantly administered with a hexavalent DTaP-IPV-HBV/Hib vaccine in healthy infants. Vaccine 2008; 26: 2242-2252
- 2. MacLennan JM, Shackley F, Heath PT, et al. Safety, immunogenicity, and induction of immunologic memory by a serogroup C meningococcal conjugate vaccine in infants: a randomized controlled trial. JAMA. 2000;283:2795-2801.
- 3. Data on File
- 4. Granoff DM, Maslanka SE, Carlone GM, et al. A modified enzyme-linked immunosorbent assay for measurement of antibody responses to meningococcal C polysaccharide that correlate with bactericidal responses. Clin Diagn Lab Immunol. 1998;5:479-485
- 5. Maslanka SE, Gheesling LL, Libutti DE, et al. Standardization and a multilaboratory comparison of Neisseria meningitidis serogroup A and C serum bactericidal assays. Clin Diag Lab Immunol. 1997;4:156-167.
- 6. Mandrell RE, Azmi FH, Granoff DM. Complement-mediated bactericidal activity of human antibodies to poly α 2→8 N-acetylneuraminic acid, the capsular polysaccharide of Neisseria meningitidis serogroup B. J Infect Dis. 1995;172:1279-1289.
- 7. Goldschneider I, Gotschlich EC, Artenstein MS. Human immunity to the meningococcus. I. The role of humoral antibodies. J Exp Med. 1969;129:1307-1326
- 8. Santos G, Wacknov B, Borrow R, et al. Comparison of bactericidal assays used to measure immunological responses to vaccines developed against Neisseria meningitidis serogroup C. ICAAC 2000; 17-20 October 2000; Toronto, Canada (accepted for poster presentation).
- 9. Choo S, Zuckerman J, Goilav C, et al. Immunogenicity and reactogenicity of a group C meningococcal conjugate vaccine compared with a group A+C meningococcal polysaccharide vaccine in adolescents in a randomised observer-blind controlled trial. Vaccine. 2000;18:2686-2692..
- 10. De Wals P, De Serres G, Niyonsenga T. Effectiveness of a mass immunization campaign against serogroup C meningococcal disease in Quebec. JAMA. 2001;285:177-181.
- 11. MacDonald NE, Halperin SA, Law BJ, et al. Induction of immunologic memory by conjugated versus plain meningococcal polysaccharide vaccine in toddlers: a randomized controlled trial. JAMA. 1998;280:1685-1689.
- 12. Richmond P, Borrow R, Goldblatt D, et al. Ability of 3 different meningococcal C conjugate vaccines to induce immunologic memory after a single dose in UK toddlers. J Infect Dis. 2001;183:160-163.
- 13. MacDonald NE, Halperin SA, Law BJ, et al. Can meningococcal C conjugate vaccine overcome immune hyporesponsiveness induced by previous administration of multiple doses of plain polysaccharide vaccine? JAMA. 2000;283:1826-1827.
- 14.
Trotter CL, Andrews NJ, Kaczmarski EB, Miller E, Ramsay ME, Effectiveness of meningococcal serogroup C conjugate vaccine 4 years after introduction. The Lancet.
2004;364:365-367
- 15. Rappuoli R. Isolation and characterization of Corynebacterium diphtheriae nontandem double lysogens hyperproducing CRM197. Appl Env Microbiol. 1983;46:560-564.
- 16. Granoff DM, McHugh YE, Raff HV, et al. MF59 adjuvant enhances antibody responses of infant baboons immunized with Haemophilus influenzae type b and Neisseria meningitidis group C oligosaccharide-CRM197 conjugate vaccine. Infect Immun. 1997;65:1710-1715.
- 17. Data on File