


Product Monograph - Micafungin for Injection
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
|---|---|---|
| Intravenous infusion | Lyophilized Powder for Injection/ 50 mg and 100 mg per vial | Lactose monohydrate, citric acid and/or sodium hydroxide |
INDICATIONS AND CLINICAL USE
Micafungin for Injection (micafungin sodium) is indicated for use in adults and children 4 months and older for:
Treatment of patients with Candidemia, Acute Disseminated Candidiasis, Candida Peritonitis and Abscesses infections. Micafungin for Injection has not been adequately studied in patients with endocarditis, osteomyelitis and meningitis due to Candida infections.
Treatment of patients with esophageal candidiasis.
Prophylaxis of Candida infections in patients undergoing hematopoietic stem cell transplantation.
Geriatrics (>65 years of age): No overall differences in safety or effectiveness have been observed between geriatric subjects (>65 years) and younger subjects in clinical studies.
Pediatrics (4 months - 16 years): The safety and effectiveness of micafungin sodium in pediatric patients aged four (4) months to 16 years of age have been supported by evidence from adequate and well- controlled studies in adult and pediatric patients as well as pharmacokinetic data in pediatric patients.
The safety and efficacy of micafungin sodium in pediatric patients below the age of 4 months has not been established.
NOTE: The efficacy of micafungin sodium against infections caused by fungi other than Candida has not been established.
CONTRAINDICATIONS
Micafungin for Injection is contraindicated in patients with hypersensitivity to micafungin, echinocandins or any component of this drug product (For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph).
WARNINGS AND PRECAUTIONS
General
Isolated cases of serious hypersensitivity (anaphylaxis and anaphylactoid) reactions (including shock), Stevens-Johnson syndrome, and toxic epidermal necrolysis have been reported in patients receiving micafungin. If these reactions occur, micafungin infusion should be discontinued and appropriate treatment administered (See ADVERSE REACTIONS).
Carcinogenesis, Mutagenesis, Impairment of Fertility
Hepatic carcinomas and adenomas were observed in a 6-month intravenous toxicology study with an 18-month recovery period of micafungin sodium in rats designed to assess the reversibility of hepatocellular lesions. Micafungin for Injection should not be used in higher than recommended doses and for prolonged duration because the potential risk of liver tumor formation cannot be fully excluded.
Rats administered micafungin sodium for 3 months at 32 mg/kg/day (corresponding to 8 times the highest recommended human dose [150 mg/day], based on AUC comparisons), exhibited coloured patches/zones, multinucleated hepatocytes and altered hepatocellular foci after 1- or 3-month recovery periods, and adenomas were observed after a 20-month recovery period. Rats administered micafungin sodium at the same dose for 6 months exhibited adenomas after a 12-month recovery period; after an 18-month recovery period, an increased incidence of adenomas was observed, and additionally, carcinomas were detected. A lower dose of micafungin sodium (equivalent to 5 times the human AUC) in the 6-month rat study resulted in a lower incidence of adenomas and carcinomas following 18 months recovery. The duration of micafungin dosing in these rat studies (3 or 6 months) exceeds the usual duration of Micafungin for Injection dosing in patients, which is typically less than 1 month for treatment of esophageal candidiasis, but dosing may exceed 1 month for Candida prophylaxis.
Although the increase in carcinomas in the 6-month rat study did not reach statistical significance, the persistence of altered hepatocellular foci subsequent to micafungin dosing, and the presence of adenomas and carcinomas in the recovery periods suggest a causal relationship between micafungin sodium, altered hepatocellular foci, and hepatic neoplasms. Whole-life carcinogenicity studies of micafungin sodium in animals have not been conducted, and it is not known whether the hepatic neoplasms observed in treated rats also occur in other species, or if there is a dose threshold for this effect (See TOXICOLOGY).
Hepatic
Laboratory abnormalities in liver function tests have been seen in healthy volunteers and patients treated with micafungin sodium. In some patients with serious underlying conditions who were receiving micafungin along with multiple concomitant medications, clinical hepatic abnormalities have occurred, and isolated cases of significant hepatic impairment, hepatitis, or worsening hepatic failure have been reported. Patients with hepatic impairment or who develop abnormal liver function tests during Micafungin for Injection therapy should be monitored for evidence of worsening hepatic function and evaluated for the risk/benefit of continuing Micafungin for Injection therapy (See ADVERSE REACTIONS).
Renal
Elevations in BUN and creatinine, and isolated cases of significant renal impairment or acute renal failure have been reported in patients who received micafungin sodium. In fluconazole-controlled studies, the incidence of drug-related renal adverse events was 0.4% for micafungin sodium treated patients and 0.5% for fluconazole treated patients. Patients who develop abnormal renal function tests during Micafungin for Injection therapy should be monitored for evidence of worsening renal function (See ADVERSE REACTIONS).
Hematological Effects
Acute intravascular hemolysis and hemoglobinuria were seen in a healthy volunteer during infusion of micafungin sodium (200 mg) and oral prednisolone (20 mg). This event was transient, and the subject did not develop significant anemia. Isolated cases of significant hemolysis and hemolytic anemia have also been reported in patients treated with micafungin sodium. Patients who develop clinical or laboratory evidence of hemolysis or hemolytic anemia during Micafungin for Injection therapy should be monitored closely for evidence of worsening of these conditions and evaluated for the risk/benefit of continuing Micafungin for Injection therapy (See ADVERSE REACTIONS).
Sexual Function/Reproduction
Male rats treated intravenously with micafungin sodium for 9 weeks showed vacuolation of the epididymal ductal epithelial cells at or above 10 mg/kg (about 0.6 times the recommended clinical dose for esophageal candidiasis, based on body surface area comparisons). Higher doses (about twice the recommended clinical dose, based on body surface area comparisons) resulted in higher epididymis weights and reduced numbers of sperm cells. In a 39-week intravenous study in dogs, seminiferous tubular atrophy and decreased sperm in the epididymis were observed at 10 and 32 mg/kg, doses equal to about 2 and 7 times the recommended clinical dose, based on body surface area comparisons. There was no impairment of fertility in animal studies with micafungin sodium (See TOXICOLOGY).
Special Populations
Pregnant Women: No adequate, well-controlled studies have been conducted in pregnant women. Micafungin for Injection should be used during pregnancy only if the benefits outweigh the potential risks.
Micafungin sodium administration to pregnant rabbits (intravenous dosing on days 6 to 18 of gestation) resulted in visceral abnormalities and abortion at 32 mg/kg, a dose equivalent to about four times the recommended dose based on body surface area comparisons. Visceral abnormalities included abnormal lobation of the lung, levocardia, retrocaval ureter, anomalous right subclavian artery, and dilatation of the ureter. However, animal studies are not always predictive of human response (See TOXICOLOGY).
Nursing Women: It is not known whether micafungin is excreted in human milk. Micafungin was found in the milk of lactating, drug-treated rats. Caution should be exercised when Micafungin for Injection is administered to a nursing woman.
Pediatrics (< 4 months): The safety and efficacy of micafungin sodium in pediatric patients below the age of 4 months has not been established. Micafungin for Injection should not be used in children less than 4 months of age.
Geriatrics (> 65 years of age): A total of 418 subjects in clinical studies of micafungin sodium were 65 years of age and older, and 124 subjects were 75 years of age and older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Possible histamine-mediated symptoms have been reported with micafungin sodium, including rash, pruritus, facial swelling, and vasodilatation. Serious hypersensitivity (anaphylaxis and anaphylactoid) reactions (including shock) have been reported during administration of micafungin sodium.
Injection site reactions, including phlebitis and thrombophlebitis have been reported, at micafungin sodium doses of 50-150 mg/day. These reactions tended to occur more often in patients receiving micafungin sodium via peripheral intravenous administration.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adults
Candidemia and Other Candida Infections:
In a phase III, randomized, double-blind study for treatment of candidemia and other Candida infections, treatment-emergent adverse events occurred in 183/200 (92%), 187/202 (93%) and 171/193 (89%) adult patients in the micafungin sodium 100 mg/day, micafungin sodium 150 mg/day, and caspofungin (70/50 mg/day) treatment groups, respectively. Selected treatment-emergent adverse events occurring in ≥ 5% of the patients in any treatment study groups are shown in Table 1.
Table 1: Selected Treatment-Emergent Adverse Events* in Adult Patients with Candidemia and Other Candida Infections | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
System Organ Class† (Preferred Term)‡ | Micafungin Sodium 100 mg n (%) | Micafungin Sodium 150 mg n (%) | Comparator§ n (%) | ||||||||
| Number of Patients | 200 | 202 | 193 | ||||||||
| Gastrointestinal Disorders | 81 (41) | 89 (44) | 76 (39) | ||||||||
| Diarrhea | 15 (8) | 26 (13) | 14 (7) | ||||||||
| Nausea | 19 (10) | 15 (7) | 20 (10) | ||||||||
| Vomiting | 18 (9) | 15 (7) | 16 (8) | ||||||||
| Metabolism and Nutrition Disorders | 77 (39) | 83 (41) | 73 (38) | ||||||||
| Hypoglycemia | 12 (6) | 14 (7) | 9 (5) | ||||||||
| Hypernatremia | 8 (4) | 13 (6) | 8 (4) | ||||||||
| Hyperkalemia | 10 (5) | 8 (4) | 5 (3) | ||||||||
| General Disorders/Administration Site Conditions | 59 (30) | 56 (28) | 51 (26) | ||||||||
| Pyrexia | 14 (7) | 22 (11) | 15 (8) | ||||||||
| Investigations | 36 (18) | 49 (24) | 37 (19) | ||||||||
| Blood Alkaline Phosphatase Increased | 11 (6) | 16 (8) | 8 (4) | ||||||||
| Cardiac Disorders | 35 (18) | 48 (24) | 36 (19) | ||||||||
| Atrial Fibrillation | 5 (3) | 10 (5) | 0 | ||||||||
Patient base: all randomized patients who received at least 1 dose of study drug
*During IV treatment + 3 days
†MedDRA v5.0
‡Within a system organ class patients may experience more than 1 adverse event.
§70 mg loading dose on day 1 followed by 50 mg/day thereafter (caspofungin)
In a second phase III, randomized, double-blind study for treatment of candidemia and other Candida infections, treatment-emergent adverse events occurred in 245/264 (93%) and 250/265 (94%) patients in the micafungin sodium (100 mg/day) and AmBisome (3 mg/kg/day) treatment groups, respectively. The following treatment-emergent adverse events in patients at least 16 years of age were notable: nausea (10% vs. 8%), diarrhea (11% vs. 11%), vomiting (13% vs. 9%), abnormal liver function tests (4% vs. 3%), increased aspartate aminotransferase (3% vs. 2%) and increased blood alkaline phosphatase (3% vs. 2%) in the micafungin sodium and AmBisome treatment groups, respectively.
Esophageal Candidiasis: In a phase III, randomized, double-blind study for treatment of esophageal candidiasis, a total of 202/260 (78%) adult patients who received micafungin sodium 150 mg/day and 186/258 (72%) patients who received intravenous fluconazole 200 mg/day experienced an adverse event. Treatment-emergent adverse events resulting in discontinuation were reported in 17 (7%) micafungin sodium treated patients; and in 12 (5%) fluconazole treated patients. Selected treatment-emergent adverse events occurring in ≥ 5% of the patients in either treatment group are shown in Table 2.
| Table 2: Selected Treatment-Emergent Adverse Events* in Adult Patients with Esophageal Candidiasis | ||||||||
|---|---|---|---|---|---|---|---|---|
System Organ Class† (Preferred Term)‡ | Micafungin Sodium 150 mg/day n (%) | Comparator§ n (%) | ||||||
| Number of Patients | 260 | 258 | ||||||
| Gastrointestinal Disorders | 84 (32) | 93 (36) | ||||||
| Diarrhea | 27 (10) | 29 (11) | ||||||
| Nausea | 20 (8) | 23 (9) | ||||||
| Vomiting | 17 (7) | 17 (7) | ||||||
| Abdominal Pain NOS | 10 (3.8) | 15 (5.8) | ||||||
| General Disorders / Administration Site Conditions | 52 (20) | 45 (17) | ||||||
| Pyrexia | 34 (13) | 21 (8) | ||||||
| Nervous System Disorders | 42 (16) | 40 (16) | ||||||
| Headache | 22 (9) | 20 (8) | ||||||
| Vascular Disorders | 54 (21) | 21 (8) | ||||||
| Phlebitis | 49 (19) | 13 (5) | ||||||
| Skin and Subcutaneous Tissue Disorders | 36 (14) | 26 (10) | ||||||
| Rash | 14 (5) | 6 (2) | ||||||
Patient base: all randomized patients who received at least 1 dose of study drug
*During treatment + 3 days
†MedDRA v5.0
‡Within a system organ class patients may experience more than 1 adverse event
§Fluconazole 200 mg/day
Prophylaxis of Candida Infections in Hematopoietic Stem Cell Transplant Recipients: A double-blind, Phase III study was conducted in a total of 791 adult patients scheduled to undergo an autologous or allogeneic hematopoietic stem cell transplant. The median duration of treatment was 18 days (range 1 to 46 days) in both treatment arms.
All patients who received micafungin sodium (382) and all patients who received fluconazole (409) experienced at least one adverse event during the study. Treatment-emergent adverse events resulting in micafungin sodium discontinuation were reported in 15 (4%) patients while those resulting in fluconazole discontinuation were reported in 32 (8%) patients. Selected treatment-emergent adverse events occurring in ≥ 15% of the patients in either treatment group are shown in Table 3.
Table 3: Selected Treatment-Emergent Adverse Events* in Adult Patients During Prophylaxis of Candida Infection in Hematopoietic Stem Cell Transplant Recipients | ||
|---|---|---|
System Organ Class¥ (Preferred Term) † | Micafungin Sodium 50 mg/day n (%) | Comparator‡ n (%) |
| Number of Patients | 382 | 409 |
| Gastrointestinal Disorders | 377 (99) | 404 (99) |
| Diarrhea | 294 (77) | 327 (80) |
| Nausea | 270 (71) | 290 (71) |
| Vomiting | 252 (66) | 274 (67) |
| Abdominal Pain | 100 (26) | 93 (23) |
| Blood and Lymphatic System Disorders | 368 (96) | 385 (94) |
| Neutropenia | 288 (75) | 297 (73) |
| Thrombocytopenia | 286 (75) | 280 (69) |
| Skin and Subcutaneous Tissue Disorders | 257 (67) | 275 (67) |
| Rash | 95 (25) | 91 (22) |
| Nervous System Disorders | 250 (65) | 254 (62) |
| Headache | 169 (44) | 154 (38) |
| Psychiatric Disorders | 233 (61) | 235 (58) |
| Insomnia | 142 (37) | 140 (34) |
| Anxiety | 84 (22) | 87 (21) |
| Cardiac Disorders | 133 (35) | 138 (34) |
| Tachycardia | 99 (26) | 91 (22) |
Patient base: all randomized adult patients who received at least 1 dose of study drug
*During treatment + 3 days
¥MedDRA v12.0
†Within a system organ class patients may experience more than 1 adverse reaction.
‡Fluconazole 400 mg/day
Selected Treatment-Emergent Adverse Events < 5% in All Adult Clinical Studies
The overall safety of micafungin sodium was assessed in 2748 adult patients and 520 volunteers in 40 clinical studies, including the invasive candidiasis, esophageal candidiasis and prophylaxis studies, who received single or multiple doses of micafungin sodium, ranging from 12.5 mg to ≥ 150 mg/day in adult patients. The mean duration of treatment was 18.9 days.
Overall, 2497 (91%) adult patients who received micafungin sodium experienced an adverse event.
The most common serious adverse events in adult patients treated with micafungin sodium were sepsis 63 (2%), respiratory failure 86 (3%), septic shock 50 (2%), pneumonia 39 (1%), hypotension 36 (1%), multi-organ failure 32 (1%), renal failure 32 (1%), cardiac arrest 24 (1%), pyrexia 23 (1%), and bacterial sepsis 21 (1%).
Other selected treatment-adverse events reported in <5% in all adult patients treated with micafungin sodium are listed below:
- Blood and lymphatic system disorders: coagulopathy, pancytopenia, thrombotic thrombocytopenic purpura
- Cardiac disorders: cardiac arrest, myocardial infarction, pericardial effusion
- General disorders and administration site conditions: infusion reaction, injection site thrombosis
- Hepatobiliary disorders: hepatocellular damage, including fatal cases, hepatomegaly, jaundice, hepatic failure
- Immune system disorders: hypersensitivity, anaphylactic reaction
- Nervous system disorders: convulsions, encephalopathy, intracranial hemorrhage
- Psychiatric disorders: delirium
- Skin and subcutaneous tissue disorders: urticarial
Pediatrics
The overall safety of micafungin sodium was assessed in 479 patients, aged 3 days through 16 years of age, who received at least one dose of micafungin in 11 clinical studies. The mean treatment duration was 24.8 days. A total of 246 patients received at least one dose of micafungin 2 mg/kg or higher.
Of these pediatric patients, 264 (55%) were male and 319 (67%) were Caucasian. The age distribution was as follows: 116 (24%) less than 2 years, 108 (23%) between 2 and 5 years, 140
(29%) between 6 and 11 years, and 115 (24%) between 12 and 16 years of age.
In all pediatric studies with micafungin sodium, 439/479 (92%) patients experienced at least one treatment-emergent adverse event.
Two studies that included pediatric patients were randomized, double-blind, and active-controlled: The invasive candidiasis and candidemia study investigated the efficacy and safety of micafungin sodium (2 mg/kg/day for patients weighing ≤ 40 kg and 100 mg/day for patients weighing > 40 kg) compared to AmBisome (3 mg/kg/day) in 112 pediatric patients. Treatment-emergent adverse events occurred in 51/56 (91%) of patients in the micafungin sodium group and 52/56 (93%) of patients in the AmBisome group. Treatment-emergent adverse events resulting in micafungin sodium discontinuation were reported in 2 (4%) pediatric patients; these events were acute renal failure and cardiac arrest.
The prophylaxis study in patients undergoing HSCT investigated the efficacy of micafungin sodium (1 mg/kg/day for patients weighing ≤ 50 kg and 50 mg/day for patients weighing > 50 kg) as compared to fluconazole (8 mg/kg/day for patients weighing ≤ 50 kg and 400 mg/day for patients weighing > 50 kg). All 91 pediatric patients experienced at least one treatment-emergent adverse event. Three (7%) pediatric patients discontinued micafungin sodium due to adverse events; these events were arthralgia, intracranial hemorrhage and meningitis.
The incidence of the following treatment-emergent adverse events was higher in pediatric patients than in adult patients: rash, pruritis, urticaria, infusion related reactions, and alanine aminotransferase increased.
The selected treatment-emergent adverse events (≥ 15%) occurring in pediatric patients and more frequently in a micafungin sodium group, for all micafungin sodium pediatric studies and for the two comparative studies (candidemia and prophylaxis) described in the above section are shown in Table 4.
| Table 4: Selected Treatment-Emergent Adverse Events ≥ 15% in Pediatric Patients from All Clinical Studies, in Pediatric Patients with Candidemia and Other Candida Infections (C/IC), and in Hematopoietic Stem-Cell Transplant Recipients During Prophylaxis of Candida Infections | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
System Organ Class¥ (Preferred Term)† | All Micafungin- treated Patients n = 479 n (%) | C/IC | Prophylaxis | ||||||||||||||||
| Micafungin Sodium n = 56 n (%) | Comparator‡ n = 56 n (%) | Micafungin Sodium n = 43 n (%) | Comparator§ n = 48 n (%) | ||||||||||||||||
| Gastrointestinal disorders | 285 (60) | 22 (40) | 18 (32) | 43 (100) | 45 (94) | ||||||||||||||
| Vomiting | 146 (31) | 10 (18) | 8 (14) | 28 (65) | 32 (67) | ||||||||||||||
| Diarrhea | 106 (22) | 4 (7) | 5 (9) | 22 (51) | 31 (65) | ||||||||||||||
| Nausea | 91 (19) | 4 (7) | 4 (7) | 30 (70) | 25 (52) | ||||||||||||||
| Abdominal pain | 76 (16) | 2 (4) | 2 (4) | 15 (35) | 12 (25) | ||||||||||||||
| Abdominal distension | 29 (6) | 1 (2) | 1 (2) | 8 (19) | 6 (13) | ||||||||||||||
| General disorders and administration site conditions | 256 (53) | 14 (25) | 14 (25) | 41 (95) | 46 (96) | ||||||||||||||
| Pyrexia | 103 (22) | 5 (9) | 9 (16) | 26 (61) | 31 (65) | ||||||||||||||
| Infusion related reaction | 24 (5) | 0 | 3 (5) | 7 (16) | 4 (8) | ||||||||||||||
| Skin and subcutaneous tissue disorders | 197 (41) | 11 (20) | 8 (14) | 33 (77) | 38 (79) | ||||||||||||||
| Pruritus | 54 (11) | 0 | 1 (2) | 14 (33) | 15 (31) | ||||||||||||||
| Rash | 55 (12) | 1 (2) | 1 (2) | 13 (30) | 13 (27) | ||||||||||||||
| Urticaria | 24 (5) | 0 | 1 (2) | 8 (19) | 4 (8) | ||||||||||||||
| Respiratory, thoracic and mediastinal disorders | 194 (41) | 9 (16) | 13 (23) | 30 (70) | 33 (69) | ||||||||||||||
| Epistaxis | 45 (9) | 0 | 0 | 4 (9) | 8 (17) | ||||||||||||||
| Blood and lymphatic system disorders | 161 (34) | 17 (30) | 13 (23) | 40 (93) | 44 (92) | ||||||||||||||
| Thrombocytopenia | 70 (15) | 5 (9) | 3 (5) | 31 (72) | 37 (77) | ||||||||||||||
| Neutropenia | 61 (13) | 3 (5) | 4 (7) | 33 (77) | 34 (71) | ||||||||||||||
| Anemia | 63 (13) | 10 (18) | 6 (11) | 22 (51) | 24 (50) | ||||||||||||||
| Febrile neutropenia | 23 (5) | 0 | 0 | 7 (16) | 7 (15) | ||||||||||||||
| Investigations | 191 (40) | 12 (21) | 8 (14) | 24 (56) | 25 (52) | ||||||||||||||
| Alanine aminotransferase increased | 45 (10) | 0 | 0 | 7 (16) | 1 (2) | ||||||||||||||
| Urine output decreased | 18 (4) | 0 | 0 | 10 (23) | 8 (17) | ||||||||||||||
| Cardiac disorders | 97 (20) | 7 (13) | 3 (5) | 10 (23) | 17 (35) | ||||||||||||||
| Tachycardia | 47 (10) | 2 (4) | 1 (2) | 7 (16) | 12 (25) | ||||||||||||||
| Renal and urinary disorders | 78 (16) | 4 (7) | 4 (7) | 16 (37) | 15 (31) | ||||||||||||||
| Hematuria | 18 (4) | 0 | 0 | 10 (23) | 7 (15) | ||||||||||||||
| Psychiatric disorders | 80 (17) | 3 (5) | 1 (2) | 20 (47) | 9 (19) | ||||||||||||||
| Anxiety | 35 (7) | 0 | 0 | 10 (23) | 3 (6) | ||||||||||||||
Patient base: all randomized patients who received at least one dose of study drug.
¥MedDRA v12.0
†Within a system organ class, patients may experience more than 1 adverse reaction.
‡AmBisome
§Fluconazole
Other selected treatment-emergent adverse events reported in < 15% of pediatric patients receiving micafungin in all clinical studies were:
- Hepatobiliary disorders: hyperbilirubinemia, hepatomegaly
- Immune system disorders: anaphylactoid reaction
- Investigations: aspartate aminotransferase increased
- Renal disorders: renal failure
Post-Market Adverse Drug Reactions
The following adverse events have been identified during the post-approval use of micafungin sodium. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency.
- Blood and lymphatic system disorders: hemolytic anemia, disseminated intravascular coagulation
- Hepatobiliary disorders: hyperbilirubinemia, hepatic disorder, hepatocellular damage
- Investigations: hepatic function abnormal, white blood cell count decreased
- Renal and urinary disorders: acute renal failure and renal impairment
- Skin and subcutaneous tissue disorders: Stevens-Johnson syndrome, toxic epidermal necrolysis, erythema multiforme
- Vascular disorders: shock
DRUG INTERACTIONS
Drug-Drug Interactions
A total of 14 clinical drug-drug interaction studies were conducted in healthy volunteers to evaluate the potential for interaction between micafungin sodium and amphotericin B, mycophenolate mofetil, cyclosporine, tacrolimus, prednisolone, sirolimus, nifedipine, fluconazole, itraconazole, voriconazole, ritonavir, or rifampin. In these studies, no interaction that altered the pharmacokinetics of micafungin was observed.
Co-administration of micafungin sodium and amphotericin B deoxycholate was associated with a 30% increase in amphotericin B deoxycholate exposure. The clinical significance of this increase is unclear however this co-administration should only be used when the benefits clearly outweigh the risks, with close monitoring of amphotericin B deoxycholate toxicities.
Co-administration of voriconazole with micafungin sodium was associated with approximately 20% reduction of voriconazole exposure on average. In the same study co-administration of placebo and voriconazole was associated with a similar reduction of voriconazole exposure. When the effect of micafungin sodium was corrected for the effect of placebo, there was no significant effect of micafungin sodium on the pharmacokinetics of voriconazole.
There was no effect of a single dose or multiple doses of micafungin sodium on mycophenolate mofetil, cyclosporine, tacrolimus, prednisolone, voriconazole and fluconazole pharmacokinetics.
Sirolimus AUC was increased by 21% with no effect on Cmax in the presence of steady-state micafungin sodium compared with sirolimus alone. Nifedipine AUC and Cmax were increased by 18% and 42%, respectively, in the presence of steady-state micafungin sodium compared with nifedipine alone.
Itraconazole AUC and Cmax were increased by 22% and 11%, respectively, in the presence of steady-state micafungin compared with itraconazole alone. Patients receiving sirolimus, itraconazole or nifedipine in combination with Micafungin for Injection should be monitored for sirolimus, itraconazole or nifedipine toxicity. The sirolimus, itraconazole or nifedipine dosage should be reduced if necessary.
Micafungin is not an inhibitor of P-glycoprotein and, therefore, would not be expected to alter P-lycoprotein-mediated drug transport activity.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbs have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Do not mix or co-infuse Micafungin for Injection with other medications. Micafungin for Injection has been shown to precipitate when mixed directly with a number of other commonly used medications.
Micafungin for Injection should be administered by a slow intravenous infusion over the period of 1 hour. More rapid infusions may result in more frequent histamine mediated reactions.
NOTE: An existing intravenous line should be flushed with 0.9% Sodium Chloride Injection, USP, prior to infusion of Micafungin for Injection.
Recommended Dose and Dosage Adjustment
| Table 5: Micafungin for Injection Dosage in Adults | |||||
|---|---|---|---|---|---|
| Indication | Recommended Dose | ||||
| Adults | |||||
| Treatment of Candidemia, Acute Disseminated Candidiasis, Candida Peritonitis and Abscesses infections | 100 mg/day1 | ||||
| Prophylaxis of Candida Infections in HSCT Recipients | 50 mg/day2 | ||||
| Treatment of Esophageal Candidiasis | 150 mg/day3 | ||||
1In patients treated successfully for candidemia and other Candida infections, the mean duration of treatment was 15 days (range 10-47 days)
2In hematopoietic stem cell transplant (HSCT) recipients who experienced success of prophylactic therapy, the mean duration of prophylaxis was 19 days (range 6-51 days)
3In patients treated successfully for esophageal candidiasis, the mean duration of treatment was 15 days (range 10- 30 days)
Micafungin for Injection Dose and Schedule for Pediatric Patients
The recommended doses for pediatric patients based on indication and weight are shown in Table 6.
| Table 6: Micafungin for Injection Dosage in Pediatric Patients 4 Months or Older | |||||||
|---|---|---|---|---|---|---|---|
| Indication | Pediatrics (aged ≥ 4 months) Dose Given Once Daily | ||||||
| 30 kg or less | Greater than 30 kg | ||||||
| Treatment of Candidemia, Acute Disseminated Candidiasis, Candida Peritonitis and Abscesses infections | 2 mg/kg maximum daily dose 100 mg | ||||||
| Prophylaxis of Candida Infections in HSCT Recipients | 1 mg/kg maximum daily dose 50 mg | ||||||
| Treatment of Esophageal Candidiasis | 3 mg/kg | 2.5 mg/kg maximum daily dose 150 mg | |||||
A loading dose is not required; typically, 85% of the steady-state concentration is achieved after three daily Micafungin for Injection doses.
Gender/Race: No dose adjustment is required based on gender or race (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations).
Use in Patients with Renal Impairment: No dose adjustment is required in patients with renal impairment (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations). Supplementary dosing is not required following hemodialysis (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations).
Use in Patients with Hepatic Impairment: No dose adjustment is required in patients with mild, moderate or severe hepatic impairment (see ACTION AND CLINICAL PHARMACOLOGY – Special Populations).
Use with Other Drugs: No dose adjustment for Micafungin for Injection is required with concomitant use of mycophenolate mofetil, cyclosporine, tacrolimus, prednisolone, sirolimus, nifedipine, fluconazole, voriconazole, itraconazole, amphotericin B, ritonavir, or rifampin (see DRUG INTERACTIONS).
Reconstitution
Please read this entire section carefully before beginning reconstitution.
Reconstitute Micafungin for Injection vials by aseptically adding 5 mL of one of the following compatible solutions:
- 0.9% Sodium Chloride Injection, USP (without a bacteriostatic agent)
- 5% Dextrose Injection, USP
To minimize excessive foaming, Gently dissolve the Micafungin for Injection powder by swirling the vial. Do Not Vigorously Shake The Vial. Visually inspect the vial for particulate matter.
Micafungin for Injection 50 mg vial: after reconstitution each mL contains 10 mg of micafungin sodium.
Micafungin for Injection 100 mg vial: after reconstitution each mL contains 20 mg of micafungin sodium.
As with all parenteral drug products, reconstituted Micafungin for Injection should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not use material if there is any evidence of precipitation or foreign matter. Aseptic technique must be strictly observed in all handling since no preservative or bacteriostatic agent is present in Micafungin for Injection or in the materials specified for reconstitution and dilution.
Dilution and Preparation
Adult Patients:
- 1. Add the appropriate volume of reconstituted Micafungin for Injection into 100 mL of 0.9% Sodium Chloride Injection, USP or 100 mL of 5% Dextrose Injection, USP.
- 2. Appropriately label the bag.
Pediatric Patients:
- 1. Calculate the total Micafungin for Injection dose in milligrams (mg) by multiplying the recommended pediatric dose (mg/kg) for a given indication [see Table 6] and the weight of the patient in kilograms (kg).
- 2.
To calculate the volume (mL) of drug needed, divide the calculated dose (mg) from step 1 by the final concentration of the selected reconstituted vial(s) (either 10 mg/mL for the 50 mg vial or 20 mg/mL for the 100 mg vial), see example below:
Using 50 mg vials:
Divide the calculated mg dose (from step 1) by 10 mg/mL to determine the volume (mL) needed.
OR
Using 100 mg vials:
Divide the calculated mg dose (from step 1) by 20 mg/mL to determine the volume (mL) needed.
- 3.
Withdraw the calculated volume (mL) of drug needed from the selected concentration and
- size of reconstituted Micafungin for Injection vial(s) used in Step 2 (ensure the selected concentration and vial size used to calculate the dose is also used to prepare the infusion).
- 4.
Add the withdrawn volume of drug (step 3) to a 0.9% Sodium Chloride Injection, USP or 5% Dextrose Injection, USP intravenous infusion bag or syringe. Ensure that the final concentration of the solution is between 0.5 mg/mL to 4 mg/mL.
Note: To minimize the risk of infusion reactions, concentrations of greater than 1.5 mg/mL should be administered via central catheter.
- 5. Appropriately label the infusion bag or syringe. For concentrations above 1.5 mg/mL, if required, label to specifically warn to administer the solution via central catheter.
Micafungin for Injection is preservative-free. Discard partially used vials.
The diluted solution should be protected from light. It is not necessary to cover the infusion drip chamber or the tubing.
OVERDOSAGE
| For management of a suspected drug overdose, please contact your regional Poison Control Centre. |
|---|
Micafungin sodium is highly protein bound and, therefore, is not dialyzable. No cases of micafungin sodium overdosage have been reported. Repeated daily doses of up to 8 mg/kg (maximum total dose of 896 mg) in adult patients, up to 6 mg/kg in pediatric patients ≥ 4 months of age, and up to 10 mg/kg in pediatric patients < 4 months of age have been administered in clinical studies with no reported dose-limiting toxicity. The minimum lethal dose of micafungin is 125 mg/kg in rats, equivalent to 8 times the highest recommended adult clinical dose (150 mg) and approximately 7 times the highest pediatric clinical dose (3 mg/kg) based on body surface area comparisons.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Micafungin is a semisynthetic lipopeptide (echinocandin) compound synthesized by a chemical modification of a fermentation product of Coleophoma empetri F-11899. Micafungin is a member of a class of antifungal drugs known as echinocandins. Micafungin inhibits the synthesis of 1,3- beta-D glucan, an essential component of fungal cell walls, which is not present in mammalian cells.
Drug Resistance
There have been reports of clinical failures in patients receiving micafungin therapy due to the development of drug resistance. Some of these reports have identified specific mutations in the FKS protein component of the glucan synthase enzyme that are associated with higher MICs and breakthrough infection.
Pharmacokinetics
The pharmacokinetics of micafungin were determined in healthy subjects, hematopoietic stem cell transplant recipients, and patients with esophageal candidiasis or invasive candidiasis up to a maximum daily dose of 8 mg/kg body weight.
The relationship of area under the concentration-time curve (AUC) to micafungin dose was linear over the daily dose range of 50 mg to 150 mg and 3 mg/kg to 8 mg/kg body weight.
Steady-state pharmacokinetic parameters in relevant patient populations after repeated daily administration are presented in Table 7.
| Table 7: Pharmacokinetic Parameters of Micafungin in Adult Patients | ||||||
|---|---|---|---|---|---|---|
| Population | N | Dose (mg) | Pharmacokinetic Parameters (Mean ± Standard Deviation) | |||
| Cmax (mcg/mL) | AUC 0-24 (mcg∙h/mL) | T1/2 (h) | Cl (mL/min/kg) | |||
| Patients with IC | 20 | 100 | 5.7±2.2 | 83±51 | 14.5±7.0 | 0.359 ±0.179 |
| [Day 1] | ||||||
| [Steady State] | 20 | 100 | 10.1±4.4 | 97±29 | 13.4±2.0 | 0.298 ±0.115 |
| HIV-Positive | 20 | 50 | 4.1±1.4 | 36±9 | 14.9±4.3 | 0.321 ±0.098 |
| Patients with EC | ||||||
| [Day 1] | ||||||
| 20 | 100 | 8.0±2.4 | 108±31 | 13.8±3.0 | 0.327 ±0.093 | |
| 14 | 150 | 11.6±3.1 | 151±45 | 14.1±2.6 | 0.340 ±0.092 | |
| [Day 14 or 21] | 20 | 50 | 5.1±1.0 | 54±13 | 15.6±2.8 | 0.300±0.063 |
| 20 | 100 | 10.1±2.6 | 115±25 | 16.9±4.4 | 0.301±0.086 | |
| 14 | 150 | 16.4±6.5 | 167±40 | 15.2±2.2 | 0.297±0.081 | |
| HSCT | 8 | Per kg | 21.1±2.84 | 234±34 | 14.0±1.4 | 0.214±0.031 |
| Recipients | 3 | |||||
| [Day 7] | 10 | 4 | 29.2±6.2 | 339±72 | 14.2±3.2 | 0.204±0.036 |
| 8 | 6 | 38.4±6.9 | 479±157 | 14.9±2.6 | 0.224±0.064 | |
| 8 | 8 | 60.8±26.9 | 663±212 | 17.2±2.3 | 0.223±0.081 | |
HIV = human immunodeficiency virus; EC = esophageal candidiasis; HSCT = hematopoietic stem cell transplant;
IC = Candidemia and other Candida infections; *AUC0-infinity is presented for day 1 and AUC0-24 is presented for steady state.
Distribution: The mean ± standard deviation volume of distribution of micafungin at terminal phase was 0.39 ± 0.11 L/kg body weight when determined in adult patients with esophageal candidiasis at the dose range of 50 mg to 150 mg. Micafungin is highly (> 99%) protein bound in vitro, independent of plasma concentrations over the range of 10 to 100 mcg/mL. The primary binding protein is albumin; however, micafungin, at therapeutically relevant concentrations, does not competitively displace bilirubin binding to albumin. Micafungin also binds to a lesser extent to α1-acid-glycoprotein.
Metabolism: Micafungin is metabolized to M-1 (catechol form) by arylsulfatase, with further metabolism to M-2 (methoxy form) by catechol-O-methyltransferase. M-5 is formed by hydroxylation at the side chain (ω-1 position) of micafungin catalyzed by cytochrome P450 (CYP) isozymes. Even though micafungin is a substrate for and a weak inhibitor of CYP3A in vitro, hydroxylation by CYP3A is not a major pathway for micafungin metabolism in vivo. Micafungin is neither a P-glycoprotein substrate nor inhibitor in vitro.
In four healthy volunteer studies, the ratio of metabolite to parent exposure (AUC) at a dose of 150 mg/day was 6% for M-1, 1% for M-2, and 6% for M-5. In patients with esophageal candidiasis, the ratio of metabolite to parent exposure (AUC) at a dose of 150 mg/day was 11% for M-1, 2% for M-2, and 12% for M-5.
Excretion: The excretion of radioactivity following a single intravenous dose of 14C-micafungin sodium (25 mg) was evaluated in healthy volunteers. At 28 days after administration, mean urinary and fecal recovery of total radioactivity accounted for 82.5% (76.4% to 87.9%) of the administered dose. Fecal excretion is the major route of elimination (total radioactivity at 28 days was 71.0% of the administered dose).
Special Populations
Pediatrics (4 months – 16 years): Micafungin pharmacokinetics in 229 pediatric patients ≥ 4 months through 16 years of age were characterized using population pharmacokinetics. Population pharmacokinetic analysis in pediatric patients identified body weight as the major determinant of total systemic clearance. As a result, weight-based (mg/kg) dosing was used to reduce between-subject variability in exposure and to equate pediatric exposure with adult exposure. Micafungin exposure was dose proportional across the dose and age range studied (Table 8).
Table 8: Summary (Mean +/- Standard Deviation) of Micafungin Pharmacokinetics For Pediatric Patients ≥ 4 Months of Age and Older (Steady-State) | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Body weight group | N | Dose§ mg/kg | Cmax.ss† (mcg/mL) | AUC.ss† (mcg·h /mL) | t½‡ (h) | CL‡ (mL/min/kg) | ||||||
| 30 kg or less | 149 | 1.0 | 7.1 +/- 4.7 | 55 +/- 16 | 12.5 +/- 4.6 | 0.328 +/- 0.091 | ||||||
| 2.0 | 14.2 +/- 9.3 | 109 +/- 31 | ||||||||||
| 3.0 | 21.3 +/- 14.0 | 164 +/- 47 | ||||||||||
| Greater than 30 kg | 80 | 1.0 | 8.7 +/- 5.6 | 67 +/- 17 | 13.6 +/- 8.8 | 0.241 +/- 0.061 | ||||||
| 2.0 | 17.5 +/- 11.2 | 134 +/- 33 | ||||||||||
| 2.5 | 23.0 +/- 14.5 | 176 +/- 42 | ||||||||||
§ Or the equivalent if receiving the adult dose (50, 100, or 150 mg)
† Derived from simulations from the population PK model
‡ Derived from the population PK model
Geriatric (≥ 65 years): The exposure and disposition of a 50 mg micafungin sodium dose administered as a single 1-hour infusion to 10 healthy subjects aged 66-78 years were not significantly different from those in 10 healthy subjects aged 20-24 years. No dose adjustment is necessary for the elderly.
Race and Gender: No dose adjustment of Micafungin for Injection is required based on gender or race. After 14 daily doses of 150 mg to healthy subjects, micafungin AUC in women was greater by approximately 23% compared with men, due to smaller body weight. No notable differences among white, black, and Hispanic subjects were seen. The micafungin AUC was greater by 26% in Japanese subjects compared to blacks, due to smaller body weight.
Renal Impairment: Micafungin for Injection does not require dose adjustment in patients with renal impairment. A single 1-hour infusion of 100 mg micafungin sodium was administered to 9 adult subjects with severe renal impairment (creatinine clearance < 30 mL/min) and to 9 age-, gender-, and weight-matched subjects with normal renal function (creatinine clearance > 80 mL/min). The maximum concentration (Cmax) and AUC were not significantly altered by severe renal impairment.
Since micafungin is highly protein bound, it is not dialyzable. Supplementary dosing should not be required following hemodialysis.
Hepatic Impairment: A single 1-hour infusion of 100 mg micafungin sodium was administered to 8 adult subjects with moderate hepatic impairment (Child-Pugh score 7-9) and 8 age-, gender-, and weight-matched subjects with normal hepatic function. The Cmax and AUC values of micafungin were lower by approximately 22% in subjects with moderate hepatic impairment compared to normal subjects. This difference in micafungin exposure does not require dose adjustment of Micafungin for Injection in patients with moderate hepatic impairment.
A single 1-hour infusion of 100 mg micafungin sodium was administered to 8 adult subjects with severe hepatic impairment (Child-Pugh score 10-12) and 8 age-, gender-, ethnic- and weight-matched subjects with normal hepatic function. The mean Cmax and AUC values of micafungin were lower by approximately 30% in subjects with severe hepatic impairment compared to normal subjects. The mean Cmax and AUC values of M-5 metabolite were approximately 2.3-fold higher in subjects with severe hepatic impairment compared to normal subjects; however, this exposure (parent and metabolite) was comparable to that in patients with systemic Candida infection. Therefore, no micafungin dose adjustment is necessary in patients with severe hepatic impairment.
Studies in pediatric subjects with hepatic impairment have not been conducted.
STORAGE AND STABILITY
Stability and Storage Recommendations
Unopened vials of lyophilized material should be stored, protected from light, at controlled room temperature, 15-30° C.
Storage of Reconstituted Product Concentrate
The reconstituted product may be stored in the original vial for up to 24 hours at room temperature, 25° C.
Storage of Diluted Product
The diluted infusion should be protected from light and may be stored for up to 24 hours at room temperature, 25° C.
Note: Micafungin for Injection is preservative-free. Discard partially used vials.
SPECIAL HANDLING INSTRUCTIONS
Not applicable.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Micafungin for Injection (micafungin sodium) is available as a sterile, non-pyrogenic, white lyophilized powder for intravenous infusion containing 50 mg or 100 mg of micafungin (as micafungin sodium) per vial. The vials are single-use vials.
Non-medicinal ingredients include lactose monohydrate, citric acid and/or sodium hydroxide (used for pH adjustment). Following reconstitution with 0.9% Sodium Chloride for Injection, USP, the resulting pH of the solution is between 5.0 – 7.0.
Micafungin for Injection is supplied in 10 mL USP Type 1 glass vials that are packaged in individual cartons. The vials are being capped with red and royal blue flip-off aluminium seal and stoppered with gray bromobutyl stoppers. The bromobutyl rubber stopper is not made with natural rubber latex. The glass vials are covered with a light protective film.
PART II : SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: micafungin sodium
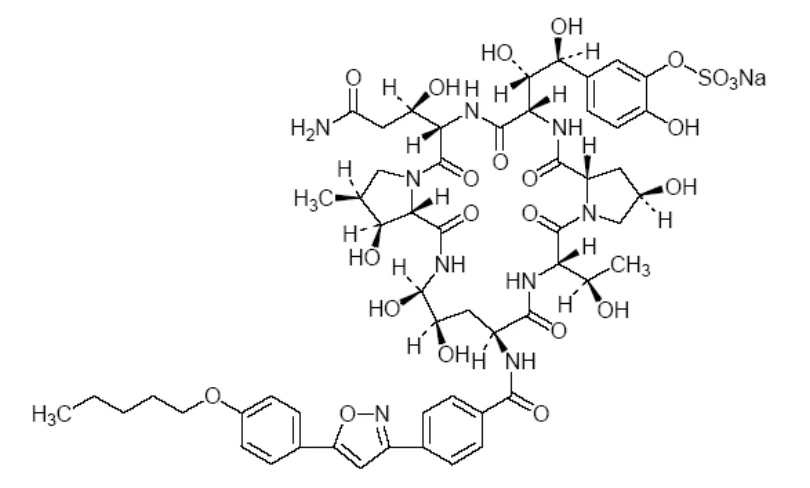
Chemical name: Pneumocandin A0, 1-[(4R,5R)-4,5-dihydroxy-N2-[4-[5-[4- (pentyloxy)phenyl]-3- isoxazolyl]benzoyl]-L-ornithine]-4-[(4S)-4-hydroxy- 4-[4-hydroxy-3-(sulfooxy)phenyl]-L-threonine]-, monosodium salt.
Molecular formula: C56H70N9NaO23S
Molecular mass: 1292.26 g/mol
Structural formula:
Physicochemical
properties: Physical Form: Micafungin sodium is a light-sensitive, hygroscopic white powder that is freely soluble in water, isotonic sodium chloride solution, N,N-dimethylformamide and dimethylsulfoxide, slightly soluble in methyl alcohol, and practically insoluble in acetonitrile, ethyl alcohol (95%), acetone, diethyl ether and n-hexane.
pH: The pH of the reconstituted solution, with 0.9% Sodium Chloride Injection, USP, is between 5.0 – 7.0.
CLINICAL TRIALS
The results from clinical studies by indication are presented below.
The safety and effectiveness of micafungin in pediatric patients aged four (4) months to 16 years of age have been supported by evidence from 2 studies that enrolled adult and pediatric patients, as well as pharmacokinetic data in pediatric patients.
Treatment of Candidemia and Other Candida Infections
Study demographics and trial design
| Table 9: Summary of Patient Demographics for Micafungin Sodium Clinical Studies in the Treatment of Candidemia and Other Candida Infections | |||||||
|---|---|---|---|---|---|---|---|
| Dosage, Route of Administration and Duration | Number of Study Subjects | Mean Age (Range) | Gender | Race | |||
| Study 03-0-192: Phase III, randomized (1:1:1), double-blind, parallel group non-inferiority study (in Adult Patients Only) | |||||||
| Micafungin Sodium 100 mg/day, intravenous infusion, minimum 14 days to a maximum of 4 weeks*. | 191 | 56.61 | M = 107 (56%) | Caucasian = 134 (70%) | |||
| (18 – 92) | F = 84 (44%) | Black = 21 (11%) | |||||
| Other = 36 (19%) | |||||||
| Micafungin Sodium 150 mg/day, intravenous infusion, minimum of 14 days to a maximum of 4 weeks*. | 199 | 55.41 | M = 117 (59%) | Caucasian = 129 (65%) | |||
| (18 – 90) | F = 82 (41%) | Black = 36 (18%) | |||||
| Other =34 (17%) | |||||||
| Caspofungin 70 mg on day 1 and 50 mg/day thereafter, intravenous infusion, minimum 14 days to a maximum of 4 weeks*. | 188 | 55.84 | M = 112 (60%) | Caucasian = 129 (69%) | |||
| (19 – 95) | F = 76 (40%) | Black = 26 (14%) | |||||
| Other = 33 (18%) | |||||||
| Study FG-463-21-08: Phase III, randomized, double-blind, parallel group study (Adult and Pediatric Patients) | |||||||
| Once daily IV infusion of micafungin 100 mg/day† in patients less than 40 kg and 2 mg/kg in patients weighing 40 kg or more for a minimum of 14 days to a maximum of 4 weeks*. | Adults | ||||||
| 247‡ | 52.7 | M = 155 (63%) | Caucasian = 149 (60%) | ||||
| (18 – 89) | F = 92 (37%) | Black = 13 (5%) | |||||
| Other = 85 (34%) | |||||||
| Pediatrics | |||||||
| 48 | 4.0 | M = 31 (65%) | Caucasian = 27 (56%) | ||||
| (0 – 15) | F = 17 (35%) | Black = 5 (10%) | |||||
| Other = 16 (33%) | |||||||
| Once daily IV infusion of AmBisome 3 mg/kg for a minimum of 14 days to a maximum of 4 weeks*. | Adults | ||||||
| 247‡ | 53.6 | M = 147 (60%) | Caucasian = 153 (62%) | ||||
| (16 – 97) | F = 100 (40%) | Black = 10 (4%) | |||||
| Other = 84 (34%) | |||||||
| Pediatrics | |||||||
| 50 | 2.2 | M = 30 (60%) | Caucasian = 25 (50%) | ||||
| (0 – 15) | F = 20 (40%) | Black = 9 (18%) | |||||
| Other = 16 (32%) | |||||||
* Administration of study drug could be prolonged up to a maximum of 8 weeks for patients with chronic disseminated candidiasis, Candida osteomyelitis or Candida endocarditis.
† Micafungin sodium dose increases to 200 mg/day (patients weighing > 40 kg) or 4 mg/kg/day (patients weighing < 40 kg) were permitted. AmBisome dose increases up to 5 mg/kg were permitted.
‡ In the presentation of the Efficacy Analysis for study FG-463-21-08 (Table 11), the Independent Data Review Board modified Full Analysis Set (IDRB-mFAS) was used. The IDRB-mFAS population was N=248 for micafungin and N = 246 for AmBisome.
Study Results
Adult Only Study
Two dose levels of micafungin sodium were evaluated in a phase III, randomized, double-blind study to determine the efficacy and safety versus caspofungin in adult patients with invasive candidiasis and candidemia. Patients were randomized to receive once daily intravenous infusions (IV) of micafungin sodium, either 100 mg/day or 150 mg/day or caspofungin (70 mg loading dose followed by 50 mg maintenance dose). Patients were stratified by APACHE II score (≤ 20 or > 20) and by geographic region. Patients with Candida endocarditis were excluded from this analysis. Outcome was assessed by overall treatment success based on clinical (complete resolution or improvement in attributable signs and symptoms and radiographic abnormalities of the Candida infection and no additional antifungal therapy) and mycological (eradication or presumed eradication) response at the end of IV therapy. Deaths that occurred during IV study drug therapy were treated as failures.
In this study, 111/578 (19.2%) of the patients had baseline APACHE II scores of > 20, and 50/578 (8.7%) were neutropenic at baseline (absolute neutrophil count less than 500 cells/mm3).
Outcome, relapse and mortality data are shown for the recommended dose of micafungin sodium (100 mg/day) and caspofungin in Table 10.
| Table 10: Efficacy Analysis: Treatment Success in Patients with Candidemia and other Candida Infection in Study 03-0-192 (Adult Patients Only) | ||||||
|---|---|---|---|---|---|---|
Micafungin Sodium 100 mg/day n (%) % treatment difference (95% CI) | Comparator1 n (%) | |||||
| Treatment Success at End of IV Therapy2 | 135/191 (70.7) 7.4 (-2.0, 16.3) | 119/188 (63.3) | ||||
| Success in Patients with Neutropenia at Baseline | 14/22 (63.6) | 5/11 (45.5) | ||||
| Table 10: Efficacy Analysis: Treatment Success in Patients with Candidemia and other Candida Infection in Study 03-0-192 (Adult Patients Only) | |||||||
|---|---|---|---|---|---|---|---|
Micafungin Sodium 100 mg/day n (%) % treatment difference (95% CI) | Comparator1 n (%) | ||||||
Success by Site of Infection Candidemia Abscess Acute disseminated3 Endophthalmitis Chorioretinitis Skin Kidney Pancreas Peritoneum Lung/Skin Lung/Spleen Liver Intraabdominal abscess Chronic disseminated Peritonitis | 116/163 (71.2) 4/5 (80) 6/13 (46.2) 1/3 0/3 1/1 2/2 1/1 1/1 0/1 0/1 0 0 0/1 4/6 (66.7) | 103/161 (64) 5/9 (55.6) 5/9 (55.6) 1/1 0 0 1/1 0 0 0 0 0/2 3/5 0 2/5 (40.0) | |||||
| Success by Organism4 | |||||||
C. albicans C. glabrata C. tropicalis C. parapsilosis C. krusei C. guilliermondii C. lusitaniae | 57/81 (70.4) 16/23 (69.6) 17/27 (63) 21/28 (75) 5/8 (62.5) ½ 2/3 (66.7) | 45/73 (61.6) 19/31 (61.3) 22/29 (75.9) 22/39 (56.4) 2/3 (66.7) 0/1 2/2 | |||||
Relapse through 6 Weeks5 Overall Culture confirmed relapse Required systemic antifungal therapy Died during follow-up Not assessed | 49/135 (36.3) 5 11 17 16 | 44/119 (37) 4 5 16 19 | |||||
Overall study mortality Mortality during IV therapy Mortality attributed to fungal infection | 58/200 (29) 28/200 (14) 7/200 (3.5) | 51/193 (26.4) 27/193 (14) 7/193 (3.6) | |||||
1 70 mg loading dose on day 1 followed by 50 mg/day thereafter (caspofungin)
2 All patients who received at least one dose of study medication and had documented invasive candidiasis or candidemia. Patients with Candida endocarditis were excluded from the analyses.
3 A patient may have had > 1 organ of dissemination
4 A patient may have had > 1 baseline infection species
5 All patients who had a culture confirmed relapse or required systemic antifungal therapy in the post treatment period for a suspected or proven Candida infection. Also includes patients who died or were not assessed in follow-up.
Adult and Pediatric Study
Adults
In a second phase III, randomized, double-blind, parallel group study in 494 adult and 98 pediatric patients, the efficacy and safety of micafungin sodium versus AmBisome were determined in non-neutropenic and neutropenic (absolute neutrophil count [ANC] < 500 cells/mcL) patients with invasive candidiasis or candidemia. Patients received an initial dose of IV micafungin 100 mg qd (2.0 mg/kg for patients weighing ≤40 kg) or IV AmBisome 3 mg/kg by 1-hour infusion in a blinded manner.
The primary endpoint was success based on clinical (complete or partial) and mycological (eradication or presumed eradication) response at the end of IV therapy and no additional systemic antifungal therapy. Deaths that occurred during IV study drug therapy were treated as failures.
In this study a total of 32/248 (12.9%) of adult patients in the micafungin group and 25/246 (10%) of adult patients in the AmBisome group were neutropenic at baseline (absolute neutrophil count less than 500 cells/mcL). A baseline APACHE II score of > 20 was recorded for 61/226 (27%) of patients in the micafungin group and 53/219 (24.2%) in the AmBisome group. Outcome, relapse and mortality data from adults are shown for the recommended dose of micafungin sodium (100 mg/day) and AmBisome in Table 11.
| Table 11: Efficacy Analysis: Treatment Success in Patients with Candidemia and other Candida Infection in Study FG-463-21-08 (Adult Patients) | ||||||||
|---|---|---|---|---|---|---|---|---|
Micafungin Sodium 100 mg/day n (%) | Comparator† n (%) | |||||||
Treatment Success at End of IV Therapy1 % treatment difference (95% CI) 2 | 156/248 (62.9) 2.3 (-5.7, 11.4) | 149/246 (60.6) | ||||||
| Success in Patients with Neutropenia at Baseline3 | 15/32 (46.9) | 11/25 (44.0) | ||||||
Success by Type of Infection Candidemia Invasive Candidiasis | 131/206 (63.6) 24/40 (60.0) | 129/209 (61.7) 20/37 (54.1) | ||||||
Success by Site of Infection Abscess Blood Bone Central Line/Catheter Associated Disseminated Endocardium Kidney Peritonitis | 4/5 (80) 127/203 (62.6) 0/0 4/4 (100.0) 5/10 (50.0) 1/2 (50.0) 0/0 13/20 (65.0) | 4/6 (66.7) 129/207 (62.3) 0/1 (0.0) 0/2 (0.0) 5/10 (50.0) 3/5 (60.0) 0/1 (0.0) 8/14 (57.1) | ||||||
| Success by Organism4 | ||||||||
C. albicans C. dubliniensis C. famata C. glabrata C. guilliermondii C. inconspicua C. intermedia C. kefyr C. krusei C. lipolytica C. lusitaniae C. non-albicans C. palmioleophila | 67/103 (65.0) 1/1 (100.0) 3/3 (100.0) 14/30 (46.7) 4/5 (80.0) 1/1 (100.0) 0/0 0/0 4/9 (44.4) 0/0 1/1 (100.0) 0/0 0/0 | 65/109 (59.6) 1/1 (100.0) 1/1 (100.0) 8/19 (42.1) 4/5 (80.0) 0/0 2/3 (66.7) 1/2 (50.0) 5/10 (50.0) 1/1 (100.0) 1/2 (50.0) 0/1 (0.0) 0/1 (0.0) | ||||||
| Table 11: Efficacy Analysis: Treatment Success in Patients with Candidemia and other Candida Infection in Study FG-463-21-08 (Adult Patients) | |||||||
|---|---|---|---|---|---|---|---|
Micafungin Sodium 100 mg/day n (%) | Comparator† n (%) | ||||||
C. parapsilosis C. pelliculosa C. rugosa C. sake C. sp. nos C. tropicalis C. utilis Trichosporon asahii Yeast sp. nos | 30/42 (71.4) 0/0 0/2 (0.0) 0/0 3/3 (100.0) 39/66 (59.1) 1/1 (100.0) 0/1 (0.0) 1/1 (100.0) | 24/38 (63.2) 0/4 (0.0) 1/1 (100.0) 2/3 (66.7) 4/7 (57.1) 39/62 (62.9) 0/1 (0.0) 0/0 3/3 (100.0) | |||||
Relapse through end of study Overall Culture confirmed relapse Systemic antifungal therapy during post- treatment Died during follow-up5 | 57/156 (36.5) 6/156 (3.8) 18/156 (11.5) 33/156 (21.2) | 60/149 (40.3) 5/149 (3.4) 19/149 (12.8) 36/149 (24.2) | |||||
Overall study mortality Mortality during IV therapy6 Mortality attributed to fungal infection | 106/264 (40.2) 50/264 (18.9) 34/264 (12.9) | 108/267 (40.4) 53/267 (19.9) 25/267 (9.4) | |||||
† AmBisome 3 mg/day
1 Success is defined as a positive clinical response (complete or partial) and a positive microbiological response (eradication or presumed eradication) at the end of blinded therapy. Patients that died during treatment (first dose through last dose day +1), missed evaluation, or met one of following 3 criteria of systemic antifungal therapy were considered a failure: i. pre-treatment (within 72 hours of study drug administration) systemic (IV, PO, CIV) antifungal use for therapeutic, non-prophylaxis purposes for > 2 days; ii. Any on study treatment systemic antifungal use for > 1 day; or iii. Post-treatment systemic antifungal use for therapeutic purposes initiated within 48 hours of discontinuation of study therapy.
2 Micafungin 100 – AmBisome. 95% CI for difference based on the Cochran-Mantel-Haenszel method controlling for baseline neutropenia status.
3 Neutropenia was assessed by Investigator
4 A patient may have had more than one baseline fungal infection species.
5 Death day > Last dose day + 1
6 IV therapy duration is from first dose day through last dose day + 1
Pediatrics
The response rate at the end of therapy for micafungin sodium treated pediatric patients was 32/48 (67%) compared to 32/50 (64%) for AmBisome treated patients. In the micafungin treated group, 3 pediatric patients with treatment success had proven recurrent infection. In the AmBisome group, none of the successfully treated pediatric patients had a recurrent infection.
Treatment of Esophageal Candidiasis
Study demographics and trial design
| Table 12: Summary of Patient Demographics for Micafungin Sodium Clinical Studies for Esophageal Candidiasis (Adult Patients Only) | ||||
|---|---|---|---|---|
| Dosage, Route of Administration and Duration | Number of Study Subjects | Mean Age (Range) | Gender | Race |
| Study 03-7-005: Phase III, multicenter, randomized, multinational, double-blind, parallel, non-inferiority trial | ||||
| Micafungin Sodium: 150 mg/day once daily as an intravenous infusion for a minimum of 14 days or 7 days after resolution of clinical symptoms | 260 | 37.2 ± 10.59 (17.0 – 80.0) | M = 131 (50%) F = 129 (50%) | Black = 176 (68%) Caucasian = 38 (15%) Mestizo = 32 (12%) Other = 14 (5%) |
| Fluconazole: 200 mg/day once daily as an intravenous infusion for a minimum of 14 days or 7 days after resolution of clinical symptoms | 258 | 37.5 ± 11.16 (17.0 – 87.0) | M = 116 (45%) F = 142 (55%) | Black = 178 (69%) Caucasian = 35 (14%) Mestizo = 29 (11%) Other = 16 (6%) |
| Study FG463-21-09: Phase II, multicenter, prospective randomized, reference therapy controlled, double-blind, parallel, group study | ||||
| Micafungin sodium: 50 mg/day once daily as an intravenous infusion for 14 days | 64 | 33.9 ± 7.5 (19 – 54) | M = 30 F = 34 | Black = 31 (48%) Caucasian = 25 (39%) Other = 8 (13%) |
| Micafungin sodium: 100 mg/day once daily as an intravenous infusion for 14 days | 62 | 36.8 ± 8.1 (24 – 68) | M = 26 F = 36 | Black = 33 (53%) Caucasian = 26 (42%) Other = 3 (5%) |
| Micafungin sodium: 150 mg/day once daily as an intravenous infusion for 14 days | 59 | 36.7 ± 8.8 (23 – 68) | M = 33 F = 26 | Black = 30 (51%) Caucasian = 25 (42%) Other = 4 (7%) |
| Fluconazole: 200 mg/day once daily as an intravenous infusion for 14 days | 60 | 35.5 ± 8.1 (19 – 56) | M = 28 F = 32 | Black = 32 (53%) Caucasian = 22 (37%) Other = 6 (10%) |
Study Results
In two controlled studies involving 763 patients with esophageal candidiasis, 445 adults with endoscopically-proven candidiasis received micafungin sodium, and 318 received fluconazole for a median duration of 14 days (range 1-33 days).
Micafungin sodium was evaluated in a phase III, randomized, double-blind study which compared micafungin sodium 150 mg/day (n = 260) to intravenous fluconazole 200 mg/day (n = 258) in adults with endoscopically-proven esophageal candidiasis. Most patients in this study had HIV infection, with CD4 cell counts < 100 cells/mm3.
Outcome was assessed by endoscopy and by clinical response at the end of treatment. Endoscopic cure was defined as endoscopic grade 0, based on a scale of 0-3. Clinical cure was defined as complete resolution in clinical symptoms of esophageal candidiasis (dysphagia, odynophagia, and retrosternal pain). Overall therapeutic cure was defined as both clinical and endoscopic cure.
Mycological eradication was determined by culture, and by histological or cytological evaluation of esophageal biopsy or brushings obtained endoscopically at the end of treatment. As shown in Table 13 below, endoscopic cure, clinical cure, overall therapeutic cure, and mycological eradication were comparable for patients in the micafungin sodium and fluconazole treatment groups.
| Table 13: Endoscopic, Clinical, and Mycological Outcomes for Esophageal Candidiasis at End-of-Treatment | ||||||||
|---|---|---|---|---|---|---|---|---|
| Treatment Outcome* | Micafungin Sodium 150 mg/day N=260 | Comparator§ N=258 | % Difference† (95% CI) | |||||
| Endoscopic Cure | 228 (87.7%) | 227 (88.0%) | -0.3% (-5.9, +5.3) | |||||
| Clinical Cure | 239 (91.9%) | 237 (91.9%) | 0.06% (-4.6, +4.8) | |||||
| Overall Therapeutic Cure | 223 (85.8%) | 220 (85.3%) | 0.5% (-5.6, +6.6) | |||||
| Mycological Eradication | 141/189 (74.6%) | 149/192 (77.6%) | -3.0% (-11.6, +5.6) | |||||
*Endoscopic and clinical outcome were measured in modified intent-to-treat population, including all randomized patients who received ≥ 1 dose of study treatment. Mycological outcome was determined in the per protocol (evaluable) population, including patients with confirmed esophageal candidiasis who received at least 10 doses of study drug, and had no major protocol violations.
§Fluconazole 200 mg/day
†Calculated as micafungin sodium – fluconazole
Most patients (96%) in this study had Candida albicans isolated at baseline. The efficacy of micafungin sodium was evaluated in less than 10 patients with Candida species other than C. albicans, most of which were isolated concurrently with C. albicans.
Relapse was assessed at 2 and 4 weeks post-treatment in patients with overall therapeutic cure at end of treatment. Relapse was defined as a recurrence of clinical symptoms or endoscopic lesions (endoscopic grade > 0). There was no statistically significant difference in relapse rates at either 2 weeks or through 4 weeks post-treatment for patients in the micafungin sodium and fluconazole treatment groups, as shown in Table 14.
| Table 14: Relapse of Esophageal Candidiasis at Week 2 and through Week 4 Post-Treatment in Patients with Overall Therapeutic Cure at the End of Treatment | ||||||
|---|---|---|---|---|---|---|
| Relapse | Micafungin Sodium 150 mg/day N=223 | Comparator§ N=220 | % Difference* (95% CI) | |||
| Relapse† at Week 2 | 40 (17.9%) | 30 (13.6%) | 4.3% (-2.5, 11.1) | |||
Relapse† Through Week 4 (cumulative) | 73 (32.7%) | 62 (28.2%) | 4.6% (-4.0, 13.1) | |||
§Fluconazole 200 mg/day
*Calculated as micafungin sodium – fluconazole; N=number of patients with overall therapeutic cure (both clinical and endoscopic cure at end-of-treatment)
†Relapse included patients who died or were lost to follow-up, and those who received systemic anti-fungal therapy in the post-treatment period
In this study, 459 of 518 (88.6%) patients had oropharyngeal candidiasis in addition to esophageal candidiasis at baseline. At the end of treatment, 192/230 (83.5%) micafungin sodium treated patients and 188/229 (82.1%) of fluconazole treated patients experienced resolution of signs and symptoms of oropharyngeal candidiasis. Of these, 32.3% in the micafungin sodium group, and 18.1% in the fluconazole group (treatment difference = 14.2%; 95% confidence interval [5.6, 22.8]) had symptomatic relapse at 2 weeks post-treatment. Relapse included patients who died or were lost to follow-up, and those who received systemic antifungal therapy during the post-treatment period. Cumulative relapse at 4 weeks post-treatment was 52.1% in the micafungin sodium group and 39.4% in the fluconazole group (treatment difference 12.7%, 95% confidence interval [2.8, 22.7]).
Effectiveness in pediatric patients was determined based on an open-label clinical study and pharmacokinetic data.
Prophylaxis of Candida Infections in Hematopoietic Stem Cell Transplant Recipients
Study demographics and trial design
| Table 15: Summary of Patient Demographics for Micafungin Sodium Clinical Trial for Prophylaxis of Fungal Infections (Adult and Pediatric Patients) | |||||
|---|---|---|---|---|---|
| Dosage, Route of Administration and Duration | Number of Study Subjects | Mean Age | Gender | Race | |
| Study 98-0-050: Phase III, randomized, double-blind, comparative study | |||||
| Once daily IV infusion of micafungin sodium: 50 mg in patients greater than 50 kg and 1 mg/kg in patients weighing 50 kg or less for a maximum of 42 days. | Adults | ||||
| 382 | 47.7 (17.7 – 73.2) | M = 230 (60.2%) F = 152 (39.8%) | Caucasian = 350 (91.6%) Black = 26 (6.8%) Other = 6 (1.6%) | ||
| Pediatrics | |||||
| 43 | 8.7 (0.6 – 16.9) | M = 23 (53.5%) F = 20 (46.5%) | Caucasian = 37 (86.0%) Black = 4 (9.3%) Other = 2 (4.7%) | ||
| Fluconazole: Intravenous infusion of 400 mg in patients greater than 50 kg of weight and 8 mg/kg in patients weighing 50 kg or less for a maximum of 42 days. | Adults | ||||
| 409 | 46.4 (17 – 72) | M = 245 (59.9%) F = 164 (40.1%) | Caucasian = 368 (90.0%) Black = 33 (8.1%) Other = 8 (2.0%) | ||
| Pediatrics | |||||
| 48 | 8.2 (0.6 – 16.7) | M = 29 (60.4%) F = 19 (39.6%) | Caucasian = 43 (89.6%) Black = 4 (8.3%) Other = 1 (2.1%) | ||
Study Results
Adults
In a randomized, double-blind study, micafungin sodium (50 mg IV once daily) was compared to fluconazole (400 mg IV once daily) in 882 (791 adults and 91 pediatric) patients undergoing an autologous or syngeneic (46%) or allogeneic (54%) stem cell transplant. The status of the patients’ underlying malignancy at the time of randomization was: 365 (41%) patients with active disease, 326 (37%) patients in remission, and 195 (22%) patients in relapse. The more common baseline underlying diseases in the 476 allogeneic transplant recipients were: chronic myelogenous leukemia (22%), acute myelogenous leukemia (21%), acute lymphocytic leukemia (13%), and non-Hodgkin’s lymphoma (13%). In the 404 autologous and syngeneic transplant recipients the more common baseline underlying diseases were: multiple myeloma (37.1%), non-Hodgkin’s lymphoma (36.4%), and Hodgkin’s disease (15.6%). During the study, 198 of 882 (22.4%) transplant recipients had proven graft-versus-host disease; and 475 of 882 (53.9%) recipients received immunosuppressive medications for treatment or prophylaxis of graft-versus-host disease.
Study drug was continued until the patient had neutrophil recovery to an absolute neutrophil count (ANC) of ≥ 500 cells/mm3 or up to a maximum of 42 days after transplant. The average duration of drug administration was 18 days (range 1 to 51 days).
Successful prophylaxis was defined as the absence of a proven, probable, or suspected systemic fungal infection through the end of therapy (usually 18 days), and the absence of a proven or probable systemic fungal infection through the end of the 4-week post-therapy period. A suspected systemic fungal infection was diagnosed in patients with neutropenia (ANC < 500 cells/mm3); persistent or recurrent fever (while ANC < 500 cells/mm3) of no known etiology; and failure to respond to at least 96 hours of broad spectrum antibacterial therapy. A persistent fever was defined as four consecutive days of fever greater than 38ºC. A recurrent fever was defined as having at least one day with temperatures ≥ 38.5ºC after having at least one prior temperature > 38ºC; or having two days of temperatures > 38ºC after having at least one prior temperature > 38ºC. Transplant recipients who died or were lost to follow-up during the study were considered failures of prophylactic therapy.
Successful prophylaxis was documented in 80.7% of recipients who received micafungin sodium, and in 73.7% of recipients who received fluconazole (7.0% difference [95% CI = 1.5, 12.5]), as shown in Table 16, along with other study endpoints. The use of systemic antifungal therapy post-treatment was 42% in both groups.
The number of proven breakthrough Candida infections was 4 (0.9%) in the micafungin and 2 (0.4%) in the fluconazole group.
The efficacy of micafungin against infections caused by fungi other than Candida has not been established.
| Table 16: Results from Clinical Study of Prophylaxis of Candida Infections in Hematopoietic Stem Cell Transplant Recipients (Adult and Pediatric Patients) | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Outcome of Prophylaxis | Micafungin Sodium 50 mg/day (n=425) | Comparator§ (n=457) | |||||||
| Probable/Proven | Probable/Proven | ||||||||
| Success* | 343 (80.7%) | 337 (73.7%) | |||||||
| Failure: | 82 (19.3%) | 120 (26.3%) | |||||||
All Deaths1 Proven/probable fungal infection prior to death | 18 (4.2%) 1 (0.2%) | 26 (5.7%) 3 (0.7%) | |||||||
| Proven/probable fungal infection (not resulting in death)1 | 6 (1.4%) | 8 (1.8%) | |||||||
| Suspected fungal infection2 | 53 (12.5%) | 83 (18.2%) | |||||||
| Lost to follow-up | 5 (1.2%) | 3 (0.7%) | |||||||
§ Fluconazole 400 mg/day
* Defined as the absence of proven, probable or suspected fungal infections through the end of therapy and the absence of a proven or probable infection at the end of the 4-week post-treatment period. Difference (micafungin sodium–Fluconazole): +7.0% [95% CI=1.5, 12.5]
1 Through end-of-study (4 weeks post-therapy)
2 Through end-of-therapy
Pediatrics
Clinical success was reported in 72% (n=31) pediatric patients treated with micafungin sodium as compared to 54% (N=26) in comparator arms. Treatment failure was reported in 28% (n=12) and 46% (n=22) patients in micafungin sodium and comparator arms respectively. Mortality through the end- of-study (4 weeks post-therapy) was reported in 12% (n=5) and 13% (n=6) patients in micafungin sodium and comparator arms, respectively.
DETAILED PHARMACOLOGY
Human pharmacokinetics of micafungin were determined in healthy subjects, hematopoietic stem cell transplant recipients and patients with esophageal candidiasis up to a maximum of daily dose of 8 mg/kg body weight. The relationship of area under the curve (AUC) to micafungin dose was linear over the daily dose range of 50 mg to 150 mg and 3 mg/kg to 8 mg/kg body weight.
Detailed pharmacokinetics in relevant patient groups and special populations are described previously in the Action and Clinical Pharmacology section.
MICROBIOLOGY
Activity In Vitro
Micafungin exhibited in vitro activity against C. albicans, C. glabrata, C. guilliermondii, C. kefyr, C. krusei, C. lusitaniae, C. parapsilosis, C. pelliculosa and C. tropicalis.
Susceptibility Testing Methods
The interpretive standards for micafungin against Candida species are applicable only to tests performed using Clinical Laboratory and Standards Institute (CLSI) microbroth dilution (MIC; based on partial inhibition endpoint) and CLSI disk diffusion reference method; both MIC and zone diameter results are read at 24 hours.
When available, the clinical microbiology laboratory should provide the results of in vitro susceptibility test results for antimicrobial drug products used in resident hospitals to the physician as periodic reports that describe the susceptibility profile of pathogens. These reports should aid the physician in selecting an antifungal drug product for treatment. The techniques for Broth Microdilution and Disk Diffusion are described below.
Broth Microdilution Technique
Quantitative methods are used to determine antifungal MICs. These MICs provide estimates of the susceptibility of Candida species to antifungal agents. MICs should be determined using the standardized CLSI procedure. Standardized procedures are based on a microdilution method (broth) with standardized inoculum concentrations and standardized concentrations of micafungin powder. The MIC values should be interpreted according to the criteria provided in Table 17.
Disk Diffusion Technique
Qualitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of Candida species to antifungal agents. The CLSI procedure uses standardized inoculum concentrations and paper disks impregnated with 10 μg of micafungin should be used to test the susceptibility of Candida species to micafungin at 24 hours. Disk diffusion interpretive criteria are provided in Table 17.
| Table 17: Susceptibility Interpretive Criteria for Micafungin | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Broth Microdilution MIC (mcg/mL) at 24 hours | Disk Diffusion at 24 hours (Zone diameters in mm) | |||||||||||||||
| Susceptible (S) | Intermediate (I) | Resistant (R) | Susceptible (S) | Intermediate (I) | Resistant (R) | |||||||||||
| Candida albicans | ≤ 0.25 | 0.5 | ≥ 1 | ≥ 22 | 20-21 | ≤ 19 | ||||||||||
| Candida tropicalis | ≤ 0.25 | 0.5 | ≥ 1 | ≥ 22 | 20-21 | ≤ 19 | ||||||||||
| Candida krusei | ≤ 0.25 | 0.5 | ≥ 1 | ≥ 22 | 20-21 | ≤ 19 | ||||||||||
| Candida parapsilosis | ≤ 2 | 4 | ≥ 8 | ≥ 16 | 14-15 | ≤ 13 | ||||||||||
| Candida guilliermondii | ≤ 2 | 4 | ≥ 8 | ≥ 16 | 14-15 | ≤ 13 | ||||||||||
| Candida glabrata | ≤ 0.06 | 0.12 | ≥ 0.25 | Not applicable† | Not applicable† | Not applicable† | ||||||||||
MIC: minimum inhibitory concentration
† Disk diffusion zone diameters have not been established for this strain/antifungal agent combination.
A report of “Susceptible” indicates that the isolate is likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable.
The “Intermediate” category implies that an infection due to the isolate may be appropriately treated in body sites where the drug is physiologically concentrated or when a high dosage of drug is used. The “Resistant” category implies that the isolates are not inhibited by the concentrations of the drug usually achievable with normal dosage schedules and clinical efficacy of the drug against the pathogen has not been reliably shown in treatment studies.
Quality Control
Standardized susceptibility test procedures require the use of quality control organisms to monitor and ensure the accuracy and precision of supplies and reagents used in the assay, and the technique of the individual performing the test. Standard micafungin powder and 10 μg disks should provide the following range of values noted in Table 18.
| Table 18: Acceptable Quality Control Ranges for Micafungin to be Used in Validation of Susceptibility Test Results | ||||||
|---|---|---|---|---|---|---|
| QC strains | Broth microdilution (MIC in mcg /mL) at 24-hour | Disk Diffusion (Zone diameter in mm) at 24-hour | ||||
| Candida parapsilosis ATCC† 22019 | 0.5 – 2.0 | 14-23 | ||||
| Candida krusei ATCC 6258 | 0.12 – 0.5 | 23-29 | ||||
| Candida tropicalis ATCC 750 | Not applicable§ | 24-30 | ||||
| Candida albicans ATCC 90028 | Not applicable§ | 24-31 | ||||
MIC: minimum inhibitory concentration
†ATCC is a registered trademark of the American Type Culture Collection.
§ Quality control ranges have not been established for this strain/antifungal agent combination.
Activity In Animal Models
Micafungin sodium has shown activity in both mucosal and disseminated murine models of candidiasis. Micafungin sodium, administered to immunosuppressed mice in models of disseminated candidiasis prolonged survival and/or decreased the mycological burden.
TOXICOLOGY
High doses of micafungin sodium (5 to 8 times the highest recommended human dose, based on AUC comparisons) have been associated with irreversible changes to the liver when administered for 3 or 6 months, and these changes may be indicative of pre-malignant processes.
Carcinogenesis, Mutagenesis and Impairment of Fertility
Hepatic carcinomas and adenomas were observed in a 6-month intravenous toxicology study with an 18-month recovery period of micafungin sodium in rats designed to assess the reversibility of hepatocellular lesions.
Rats administered micafungin sodium for 3 months at 32 mg/kg/day (corresponding to 8 times the highest recommended human dose [150 mg/day], based on AUC comparisons), exhibited colored patches/zones, multinucleated hepatocytes and altered hepatocellular foci after 1- or 3-month recovery periods, and adenomas were observed after 20-month recovery period. Rats administered micafungin sodium at the same dose for 6 months exhibited adenomas after a 12-month recovery period; after an 18-month recovery period, an increased incidence of adenomas was observed, and additionally, carcinomas were detected. A lower dose of micafungin sodium (equivalent to 5 times the human AUC) in the 6-month rat study resulted in a lower incidence of adenomas and carcinomas following 18 months recovery. The duration of micafungin dosing in these rat studies (3 or 6 months) exceeds the usual duration of Micafungin for Injection dosing in patients, which is typically less than 1 month for treatment of esophageal candidiasis, but dosing may exceed 1 month for Candida prophylaxis.
Although the increase in carcinomas in the 6-month rat study did not reach statistical significance, the persistence of altered hepatocellular foci subsequent to micafungin dosing, and the presence of adenomas and carcinomas in the recovery periods suggest a causal relationship between micafungin sodium, altered hepatocellular foci, and hepatic neoplasms. Whole-life carcinogenicity studies of micafungin sodium in animals have not been conducted, and it is not known whether the hepatic neoplasms observed in treated rats also occur in other species, or if there is a dose threshold for this effect.
Micafungin sodium was not mutagenic or clastogenic when evaluated in a standard battery of in vitro and in vivo tests (i.e., bacterial reversion - S. typhimurium, E. coli; chromosomal aberration; intravenous mouse micronucleus).
Male rats treated intravenously with micafungin sodium for 9 weeks showed vacuolation of the epididymal ductal epithelial cells at or above 10 mg/kg (about 0.6 times the recommended clinical dose for esophageal candidiasis, based on body surface area comparisons). Higher doses (about twice the recommended clinical dose, based on body surface area comparisons) resulted in higher epididymis weights and reduced numbers of sperm cells. In a 39-week intravenous study in dogs, seminiferous tubular atrophy and decreased sperm in the epididymis were observed at 10 and 32 mg/kg, doses equal to about 2 and 7 times the recommended clinical dose, based on body surface area comparisons. There was no impairment of fertility in animal studies with micafungin sodium.
REFERENCES
- 1. De Wet NT, Bester AJ, Viljoen JJ. et al., A randomized, double blind, comparative trial of micafungin (FK463) vs. fluconazole for the treatment of oesophageal candidiasis. Aliment Pharmacol Ther 2005; 21:899–907.
- 2. De Wet N, Llanos-Cuentas A, Suleiman J. et al., A Randomized, Double-Blind, Parallel- Group, Dose-Response Study of Micafungin Compared with Fluconazole for the Treatment of Esophageal Candidiasis in HIV-Positive Patients. Clinical Infectious Diseases 2004; 39:842–9.
- 3. Kuse ER, Chetchotisakd P, da Cunha CA, et al. Micafungin versus liposomal amphotericin B for candidaemia and invasive candidosis: a phase III randomized double-blind trial. Lancet. 2007 May 5;369(9572):1519-27.
- 4. Pappas PG, Rotstein CMF, Betts RF, et al., Micafungin versus Caspofungin for Treatment of Candidemia and Other Forms of Invasive Candidiasis. Clinical Infectious Diseases 2007 Oct 1;45(7):883-93.
- 5. van Burik JA, Ratanatharathorn V, Stepan D, et al., Micafungin versus Fluconazole for Prophylaxis against Invasive Fungal Infections during Neutropenia in Patients Undergoing Hematopoietic Stem Cell Transplantation. Clinical Infectious Diseases 2004; 39:1407–16.
- 6. Clinical and Laboratory Standards Institute (CLSI). Reference Method for Broth Dilution Antifungal Susceptibility Testing of Yeasts – Approved Standard – Third Edition. CLSI document M27-A3. Clinical and Laboratory Standards Institute, Wayne, PA, USA, 2008.
- 7. Clinical and Laboratory Standards Institute (CLSI). Reference Method for Broth Dilution Antifungal Susceptibility Testing of Yeasts; Fourth Informational Supplement. CLSI document M27-S4. Clinical and Laboratory Standards Institute, Wayne, PA, USA, 2012.
- 8. Clinical and Laboratory Standards Institute (CLSI). Method for Antifungal Disk Diffusion Susceptibility Testing of Yeasts; Approved Guid–line - Second Edition. CLSI document M44-A2. Clinical and Laboratory Standards Institute, Wayne, PA, USA, 2009.
- 9. Mycamine (micafungin sodium for injection; 50 mg/vial and 100 mg/vial), Control #163602, Astellas Pharma Canada, Inc. Date of Revision: March 24, 2014