


Product Monograph - Milrinone Lactate Injection (Eugia Pharma)
ACTION AND CLINICAL PHARMACOLOGY
Milrinone is a positive inotrope and vasodilator, with little chronotropic activity, different in structure and mode of action from either the digitalis glycosides or catecholamines.
Milrinone, at relevant inotropic and vasorelaxant concentrations, is a selective inhibitor of peak
III cAMP phosphodiesterase isozyme in cardiac and vascular muscle. This inhibitory action is consistent with cAMP-mediated increases in intracellular ionized calcium and contractile force in cardiac muscle, as well as with cAMP-dependent contractile protein phosphorylation and relaxation in vascular muscle. Additional experimental evidence also indicates that it is not a beta-adrenergic agonist, nor does it inhibit sodium-potassium adenosine triphosphatase activity as do the digitalis glycosides.
Clinical studies in patients with congestive heart failure have shown that milrinone produces dose and plasma level-related increase in left ventricular dP/dt, increase in forearm blood flow indicating a direct arterial vasodilator activity of the drug, and improves diastolic function as evidenced by improvement in left ventricular diastolic relaxation.
Studies in normal subjects have shown that milrinone produces increases in the slope of the left ventricular pressure-dimension relationship, indicating a direct inotropic effect of the drug. Both the inotropic and vasodilatory effects have been observed over the therapeutic range of milrinone plasma concentrations of 100 - 300 ng/mL.
Pharmacokinetics
Following intravenous loading injections of 12.5 to 125.0 mcg/kg to congestive heart failure patients, intravenous milrinone had a volume of distribution of 0.38 L/kg, a mean terminal elimination half-life of 2.3 hours, and a clearance of 0.13 L/kg/hr. Following intravenous infusions of 0.20 to 0.70 mcg/kg/min to congestive heart failure patients, the drug had a volume of distribution of about 0.45 L/kg, a mean terminal elimination half-life of 2.4 hours, and a clearance of 0.14 L/kg/hr. These pharmacokinetic parameters were not dose-dependent, while the area under the plasma concentration versus time curve following loading injections was significantly dose-dependent.
The steady-state milrinone plasma levels after approximately 6 - 12 hours of unchanging maintenance infusion of 0.50 mcg/kg/min are approximately 200 ng/mL.
Milrinone has been shown (by ultracentrifugation) to be in excess of 70% bound to human plasma proteins at plasma concentrations of 70 - 400 ng/mL.
The primary route of excretion of milrinone in man is via the urine, with much smaller amounts recovered in the feces. The major urinary excretion products in man are milrinone (83%) and its
O-glucuronide metabolite (12%). Elimination in normal subjects via the urine is rapid, with approximately 60% recovered within the first two hours following dosing, and approximately
90% recovered within the first eight hours following dosing. The mean renal clearance of milrinone is approximately 0.3 L/min while that of the metabolites is even greater, indicative of active secretion.
In patients with moderate to severe renal impairment, both Cmax (210 ng/mL) and tmax (1.19 hr) were increased compared to subjects with normal renal function (162 ng/mL and 0.64 hr, respectively). The half-life of milrinone increased from 0.94 hr in subjects with normal renal function to 1.71 hr in patients with moderate renal impairment and to 3.09 hr in patients with severe renal impairment.
Pharmacodynamics
In patients with congestive heart failure, intravenous milrinone produces prompt, significant improvements in cardiac output, pulmonary capillary wedge pressure and vascular resistance without clinically significant increases in heart rate or myocardial oxygen consumption. Onset of action generally occurs within 5 to 15 minutes.
Improvement in left ventricular function and relief of congestive heart failure symptoms in patients with ischemic heart disease have been observed. The improvement has occurred without inducing symptoms or electrocardiographic signs of myocardial ischemia.
In studies in congestive heart failure patients, Milrinone administered as a loading injection followed by a maintenance infusion produced the following pharmacodynamic changes:
Dosage regimen
Loading Dose | Maintenance Infusion | CI | PCWP | SVR | HR | MAP | |||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| (mcg/kg) | (mcg/kg/min) | Percent Change | |||||||||
| 37.5 | 0.375 | +25 | -20 | -17 | +3 | -5 | |||||
| 50.0 | 0.50 | +38 | -23 | -21 | +3 | -5 | |||||
| 75.0 | 0.75 | +42 | -36 | -37 | +10 | -17 | |||||
Patients evaluated for 48 hours maintained improvements in hemodynamic function, with no evidence of diminished response (tachyphylaxis), and in a small number of patients no evidence of tachyphylaxis was seen for as long as 72 hours of infusion.
The duration of therapy should depend upon patient responsiveness. Patients have been maintained on infusion of milrinone up to five days.
Intravenous milrinone is effective in fully digitalized patients without affecting glycoside plasma levels.
Milrinone has been shown to enhance atrio-ventricular nodal conduction rate (see PRECAUTIONS).
INDICATIONS AND CLINICAL USE
Milrinone Lactate Injection is indicated for the short-term management of severe congestive heart failure including low output states following cardiac surgery. The majority of experience with the drug has been in patients receiving digoxin and diuretics. In some patients, milrinone has been shown to increase ventricular ectopy (see WARNINGS).
CONTRAINDICATIONS
Milrinone Lactate Injection is contraindicated in patients who are hypersensitive to it or to any of its ingredients.
WARNINGS
Supraventricular and ventricular arrhythmias have been observed in the high risk population of congestive heart failure patients treated with milrinone. In using the drug, consideration should be given to the fact that in some patients, milrinone has been associated with an increase in ventricular ectopy including ventricular tachycardia or fibrillation (see ADVERSE REACTIONS). The incidence of arrhythmias has not been shown to be related to the dose or plasma level of milrinone. Patients receiving Milrinone Lactate Injection should be closely monitored during infusion.
No clinical studies have been conducted in patients in the acute phase of post myocardial infarction. Until further clinical experience is gained, milrinone is not recommended in these patients.
PRECAUTIONS
Milrinone Lactate Injection should not be used in lieu of surgical relief of the obstruction in patients with severe obstructive aortic or pulmonic valvular disease or hypertrophic subaortic stenosis. Like other inotropic agents, it may aggravate outflow tract obstruction in hypertrophic subaortic stenosis.
Milrinone has been shown to enhance AV nodal conduction rate, indicating a potential for an increased ventricular response rate in patients with atrial flutter/fibrillation which is not being controlled with digitalis therapy. Digitalisation of these patients should be considered prior to the administration of milrinone.
During therapy with Milrinone Lactate Injection, blood pressure and heart rate should be monitored and the rate of infusion stopped in patients showing excessive decrease in blood pressure, until resolved, then resumed at a lower rate if resumption is considered.
Patients who have received vigorous diuretic therapy may have insufficient cardiac filling pressure to respond adequately to Milrinone Lactate Injection, in which case cautious liberalization of fluid and electrolyte intake may be indicated. For these patients milrinone lactate should be cautiously administered while monitoring blood pressure, heart rate and clinical symptomatology.
Fluid and electrolyte changes and renal function should be carefully monitored during therapy with Milrinone Lactate Injection.
Improvement in cardiac output with resultant diuresis may necessitate a reduction in the dose of diuretic. Potassium loss due to excessive diuresis may predispose digitalized patients to arrhythmias. Therefore, hypokalemia should be corrected by potassium supplementation in advance of or during milrinone administration.
Use in Renally Impaired Patients
Data obtained from patients with severe renal impairment (creatinine clearance = 0 - 30 mL/min)
but without congestive heart failure have demonstrated that the presence of renal impairment significantly increases the terminal elimination half-life of milrinone. Reductions in the infusion rate may be necessary in patients with renal impairment (see DOSAGE AND ADMINISTRATION).
Use in Elderly Patients
Experience so far suggests that no special dosage recommendations for the elderly patient are necessary.
Use in Pregnancy
Milrinone did not appear to be teratogenic when administered intravenously to pregnant rats at doses up to 3 mg/kg/day or pregnant rabbits at doses up to 12 mg/kg/day, although an increase in resorption rate was apparent at both 8 and 12 mg/kg/day (intravenous) in the latter species.
There are no studies in pregnant women. Milrinone Lactate Injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Use in Nursing Mothers
Caution should be exercised when Milrinone Lactate Injection is administered to nursing women, since it is not known whether it is excreted in human milk.
Use in Children
Safety and effectiveness in children have not been established. Therefore, milrinone lactate should only be used when the potential benefits outweigh the potential risks.
Drug Interactions
No untoward clinical manifestations have been observed in patients in whom milrinone was used concurrently with the following drugs: digitalis glycosides, lidocaine, quinidine, hydralazine, prazosin, isosorbide dinitrate, nitroglycerin, chlorthalidone, furosemide, hydrochlorothiazide, spironolactone, captopril, heparin, warfarin, diazepam, insulin, and potassium supplements.
Chemical Interactions
Precipitation occurs immediately when furosemide is mixed with milrinone solution. Therefore, furosemide should not be administered in intravenous lines containing milrinone.
Other drugs should not be mixed with Milrinone Lactate Injection until further compatibility data are available.
ADVERSE REACTIONS
In clinical trials involving 413 patients who received milrinone the most frequent adverse effects observed were ventricular arrhythmias (12.6%) and the most severe adverse effect observed was ventricular fibrillation (0.2%).
Adverse reactions occurring in patients treated with milrinone are shown below in order of decreasing frequency:
| Ventricular arrhythmias | 12.6% |
|---|---|
| Ventricular ectopic activity | 9.0% |
| Non sustained or sustained ventricular tachycardia | 3.6% |
| Ventricular fibrillation | 0.2% |
| Supraventricular arrhythmias | 3.6% |
| Hypotension | 3.1% |
| Headache, usually mild to moderate severity | 2.4% |
| Angina pectoris/Chest pain | 1.4% |
| Hypokalemia | 0.7% |
| Thrombocytopenia | 0.5% |
| Tremor | 0.5% |
The following adverse events have also been reported in postmarketing experience:
Adverse reactions that have occurred very rarely (<1/10,000) include torsades de pointes, anaphylactic shock, bronchospasm and skin reactions such as rash. Liver function tests abnormalities have been reported but are uncommon (≥1/1,000, <1/100).
SYMPTOMS AND TREATMENT OF OVERDOSAGE
No specific antidote to milrinone is known, but general measures for circulatory support should be taken. Milrinone may produce hypotension and cardiac arrhythmia because of its vasodilator effect. In case of overdose, administration of Milrinone Lactate Injection should be discontinued until the patient's condition stabilizes.
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
|---|
DOSAGE AND ADMINISTRATION
General Information
Prior correction or adjustment of fluid/electrolytes may be necessary to obtain a satisfactory
response with Milrinone Lactate Injection (see PRECAUTIONS).
Suitable diluents include Normal or Half Normal Saline Injection or sterile 5% Dextrose
Injection.
Diluted solutions should be used within 24 hours at room temperature or within 72 hours if
refrigerated (2°C − 8°C).
- Furosemide should not be added to Milrinone Lactate Injection due to a chemical interaction.
Drug Administration
Milrinone Lactate Injection should be administered with a loading dose followed by a continuous infusion (maintenance dose) according to the following guidelines:
LOADING DOSE 50 mcg/kg: administered slowly over 10 minutes (For ease of administration, Milrinone Lactate Injection may be diluted with suitable diluents or used undiluted if suitable infusion equipment is available.) | ||||
|---|---|---|---|---|
| MAINTENANCE DOSE | ||||
| Infusion Rate | Total Daily Dose (24 hours) | |||
| minimum | 0.375 | mcg/kg/min | 0.60 | mg/kg |
| standard | 0.50 | mcg/kg/min | 077 | mg/kg |
| maximum | 0.75 | mcg/kg/min | 1.13 | mg/kg |
| Administer as a continuous intravenous infusion. | ||||
The infusion rate should be adjusted according to hemodynamic and clinical response. Patients should be closely monitored. In controlled clinical studies, most patients showed an improvement in hemodynamic status as evidenced by increases in cardiac output and reduction in pulmonary capillary wedge pressure. Dosage may be titrated to the maximum hemodynamic effect but should not exceed 1.13 mg/kg/day. Duration of therapy should depend upon patient responsiveness.
Intravenous infusions of Milrinone Lactate Injection should be administered as described in the following chart.
INFUSION DELIVERY RATE
In order to calculate flow rate (mL/hr), multiply infusion delivery rate by patient weight in kilograms.
*Prepare by adding 180 mL diluent per 20 mg vial (20 mL) Milrinone Lactate Injection.
**Prepare by adding 113 mL diluent per 20 mg vial (20 mL) Milrinone Lactate Injection.
† Prepare by adding 80 mL diluent per 20 mg vial (20 mL) Milrinone Lactate Injection.
Dosage Adjustment in Renally Impaired Patients
The loading dosage is not affected, but reductions in the maintenance infusion rate may be necessary according to the following table. (see PRECAUTIONS, Use in Renally Impaired
Patients).
| Milirinone Lactate | Concentration of Milrinone in Infusion | ||
|---|---|---|---|
| Dosage (mcg/kg/min) | 100 mcg/mL* | 150 mcg/mL** | 200 mcg/mL† |
| DELIVERY RATE | |||
| (mL/kg/hr) | (mL/kg/hr) | (mL/kg/hr) | |
| 0.375 | 0.22 | 0.15 | 0.11 |
| 0.400 | 0.24 | 0.16 | 0.12 |
| 0.500 | 0.30 | 0.20 | 0.15 |
| 0.600 | 0.36 | 0.24 | 0.18 |
| 0.700 | 0.42 | 0.28 | 0.21 |
| 0.750 | 0.45 | 0.30 | 0.22 |
Creatinine Clearance (mL/min/1.73 m2) | Milrinone Lactate (mcg/kg/min) | Concentration of Milrinone in Infusion | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 100 mcg/mL* | 150 mcg/mL** | 200 mcg/mL† | |||||||||||
| Delivery Rate | |||||||||||||
| (mL/kg/hr) | (mL/kg/hr) | (mL/kg/hr) | |||||||||||
| 5 | 0.20 | 0.12 | 0.08 | 0.06 | |||||||||
In order to calculate flow rate (mL/hr), multiply infusion delivery rate by patient weight in kilograms.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Milrinone
Chemical Name: 1,6-Dihydro-2-methyl-6-oxo-[3,4'-bipyridine]-5-carbonitrile
Structural Formula:
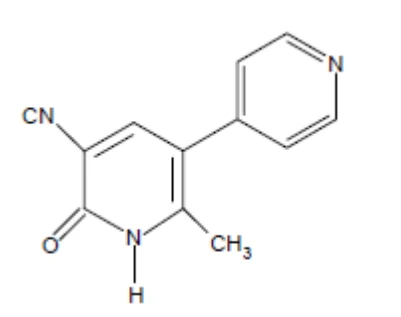
Molecular Formula: C12H9N3O
Molecular Weight: 211.22 g/mol
Physical Form: White to tan crystalline powder.
Solubility: Freely soluble in dimethyl sulfoxide; very slightly soluble in methanol; practically insoluble in water and in chloroform.
| 10 | 0.23 | 0.14 | 0.09 | 0.07 |
|---|---|---|---|---|
| 20 | 0.28 | 0.17 | 0.11 | 0.08 |
| 30 | 0.33 | 0.20 | 0.13 | 0.10 |
| 40 | 0.38 | 0.23 | 0.15 | 0.11 |
| 50 | 0.43 | 0.26 | 0.17 | 0.13 |
pKa: 9.67
Melting Point: More than 300ºC
Composition
Milrinone Lactate Injection is provided as a sterile, clear, colourless to pale yellow solution. The pH of Milrinone Lactate Injection is adjusted to between 3.2 and 4.0 with lactic acid or sodium hydroxide. Each mL contains milrinone lactate equivalent to 1 mg milrinone and dextrose monohydrate USP 51.7 mg, in Water for Injection. The total concentration of lactic acid can vary between 0.95 and 1.29 mg/mL.
STABILITY AND STORAGE RECOMMENDATIONS
Store between 15ºC to 30°C. Protect from freezing.
Diluted Solutions
For ease of administration Milrinone Lactate Injection may be diluted with suitable diluents such as Normal or Half Normal Saline Injection or sterile 5% Dextrose Injection, or may be used undiluted if suitable equipment is available.
Dilution as described under DOSAGE AND ADMINISTRATION, Drug Administration.
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration |
|---|---|---|---|
20 mg vial (20 mL) | 180 mL | 200 mL | 100 mcg/mL |
20 mg vial (20 mL) | 113 mL | 133 mL | 150 mcg/mL |
20 mg vial (20 mL) | 80 mL | 100 mL | 200 mcg/mL |
Diluted solutions should be used within 24 hours at room temperature (15°C to 30°C) or
72 hours if refrigerated (2°C to 8°C).
For detailed information regarding dilution, see DOSAGE AND ADMINISTRATION.
Precipitation occurs immediately when furosemide is mixed with milrinone solution. Therefore, furosemide should not be administered in intravenous lines containing Milrinone Lactate
Injection.
Note: As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discolouration and leakage prior to administration, whenever solution and container permit. Solution showing haziness, particulate matter, precipitate, discolouration or leakage should not be used. Discard unused portion.
AVAILABILITY OF DOSAGE FORMS
Each mL contains Milrinone lactate equivalent to 1 mg Milrinone USP. The total concentration of lactic acid can vary between 0.95 and 1.29 mg/mL.
| Dosage form | Solution | |||||
| Strength | 1mg/mL | |||||
| Description | Clear colourless to pale yellow solution, free from visible particles in clear glass vial. | |||||
| Composition | Non-medicinal Ingredients: Dextrose Monohydrate, lactic acid and sodium hydroxide. | |||||
| Packaging | 10 mL | 20 mL | ||||
| 10 mL single-dose vials in packages of 10 | 20 mL single-dose vials in packages of 10 | |||||
PHARMACOLOGY
Tissue distribution and biotransformation
Specific study of tissue distribution was conducted in the rat, following oral administration of milrinone at 4.5 mg/kg. At 30 minutes post-medication, the time of peak blood level, the only tissues, other than the G.I. tract, showing drug levels significantly higher than blood were the thyroid, kidney and liver. By 2 hrs, all tissue levels except the kidney were low and 45% of the dose had already been excreted in the urine.
The biotransformation of 14C-milrinone was studied in the rat, dog and monkey following oral administration. In all three species, milrinone was the major urinary excretion product, constituting from 67% (monkey) to 98% (rat) of urinary radioactivity. Five metabolites were observed and identified: the pyridyl-N-oxide, the carboxamide, and three glycosidic sugar conjugates of milrinone: a glucuronide, a glucoside and a riboside. The last two were observed only in the dog. Only the glucuronide might be considered a major metabolic pathway, representing 15% and 30% of urinary radioactivity in the dog and monkey, respectively.
Animal Pharmacology
The inotropic and chronotropic activities of milrinone were investigated in vitro, using isolated guinea pig, cat, rabbit, rat and hamster atria and papillary muscles. Milrinone, in concentrations ranging from 0.1 to 300 mcg/mL, caused concentration-dependent increases in papillary muscle and atrial developed tension, with minimal increases in atrial rate. Compared with the in vitro inotropic activity of amrinone, milrinone was approximately 30 times more potent.
Milrinone does not increase the sensitivity of the myofibrillar proteins to calcium.
In the anesthetized dog, the intravenous bolus administration of milrinone in doses of 0.01 to
0.3 mg/kg caused dose-dependent increases in cardiac contractile force with a minimal effect on blood pressure and heart rate. Milrinone also increases the rate of myocardial relaxation in a dose-related manner (lusitropic effect).
In the failing dog heart model, milrinone significantly reversed propranolol, verapamil and pentobarbital induced heart failure.
In the isolated rabbit renal artery preparation milrinone and amrinone were approximately equipotent against both potassium and norepinephrine-induced contractions, with nifedipine being considerably more potent than either milrinone or amrinone in this preparation.
Drug interaction studies
The inotropic potency of milrinone was not affected in anesthetized dogs pretreated with sodium nitroprusside, furosemide or diazepam. Milrinone, at 10 - 100 mcg/kg, increased cardiac contractile force in the presence of ouabain or dopamine.
Milrinone does potentiate the inotropic activity of beta adrenergic agonists.
Milrinone did not worsen or improve ouabain-induced arrhythmias and the inotropic response to milrinone was not altered in the presence of such arrhythmias.
In the canine hind limb preparations, milrinone, at doses of 0.03 to 0.3 mg/kg caused dose-related reductions in systolic and diastolic perfusion pressures. This effect was not blocked by either denervation, histamine receptor antagonists, cholinergic or beta adrenergic receptor antagonists or by prostaglandin synthetase inhibition.
In the 24 hour Harris dog model, in which arrhythmias are produced by ligation of the left anterior descending coronary artery, milrinone did not interfere with the antiarrhythmic effects of quinidine, procainamide and disopyramide and reduced their negative-inotropic and intracardiac conduction effects.
TOXICOLOGY
Acute Toxicity
| The following intravenous 7-day LD50 values were determined: | ||||||||
|---|---|---|---|---|---|---|---|---|
| Species | Age Range | Sex | LD50 (mg/base/kg) | |||||
| Mouse | Adults | M | 79 | |||||
| Mouse | Adults | F | 79 | |||||
| Rat | Adults | M | 76 | |||||
| Rat | Adults | M | 73 | |||||
Clinical observations for mice, rats and rabbits included ataxia, decreased motor activity, loss of righting reflex, tremors and clonic convulsions. In addition for mice and rats only, ptosis, lacrimation, salivation, spastic limb movements and loss of motor activity were observed. Observations made during necropsies of mice and rats treated with the highest dosages included: small black pitted areas in the glandular stomach, red or red-black material or mucus in the small intestine and lung consolidation (congestion). For rabbits, macroscopic and histomorphologic lesions: epicardial and endocardial hemorrhage, and papillary muscle fibrosis were observed at intravenous dosages of 12.6 mg base/kg and higher and were related to exaggerated pharmacologic effects of supra-therapeutic dosages.
B. Subacute/Chronic Toxicity
Toxicologic effects observed in oral and intravenous studies in various laboratory animal species including mice, rats, rabbits, dogs and monkeys were related to responses by animals with normal myocardial function to the exaggerated pharmacologic effects of inotropy and vasodilation. Clinical effects observed for one or more species included: increased heart rate, shortening of PR and QT intervals, conversion of sinus arrhythmia (common to dogs) to normal sinus rhythm, reddening of extremities, and decreases in systolic and diastolic blood pressure.
Similarly, pathologic effects observed in various species were related to exaggerated pharmacologic responses by the normal heart to excessive inotropic and vasodilator stimulation and included: myocardial degeneration, necrosis and fibrosis principally affecting the left ventricular papillary muscles, perivasculitis and/or vasculitis of epicardial arteries and subendocardial hemorrhage. Coronary vascular lesions characterized by periarterial edema and inflammation have been observed in dogs only. The myocardial/endocardial changes are similar to those produced by beta-adrenergic receptor agonists such as isoproterenol, while the vascular changes are similar to those produced by minoxidil and hydralazine. Doses within the recommended clinical dose range (up to 1.13 mg/kg/day) for congestive heart failure patients have not produced significant adverse effects in animals.
Results of intravenous studies in rats and dogs are summarized in the following table:
SUMMARY OF CARDIAC HISTOMORPHOLOGIC EFFECTS
IN INTRAVENOUS TOXICITY STUDIES OF MILRINONE IN RATS AND DOGS
Dosage: mg base/kg/day
| Rat | Adults | F | 73 | |||
|---|---|---|---|---|---|---|
| Rabit | Young Adults | F | 44 |
- a. Minimal myocardial fibrosis even for 2/20 rats (one of each sex)
- b. Mild myocardial fibrosis and/or degeneration observed for 5/20 rats
- c. Mild to marked myocardial fibrosis observed for 19/19 rats
- d. Minimal myocardial degeneration and/or inflammation observed for 2/4 dogs: coronary arteritis for 1/4 dogs
e. Minimal to moderate myocardial inflammation and/or fibrosis observed for 4/4 dogs at each dosage: coronary arteritis observed for 1/4 and 2/4 dogs at dosages of 6 and 18 mg base per kg/day,
respectively.
C. Carcinogenicity, Mutagenicity, Teratogenicity, Impairment of Fertility
Milrinone was not carcinogenic in life-time (two-year) oral studies conducted in mice and rats.
Milrinone was not genotoxic in in vitro tests for potential to induce gene mutation (Ames tests and mouse lymphoma cell assay) or in in vivo tests for potential to induce chromosomal damage
(micronucleus test and metaphase bone marrow analysis). An in vitro test for potential to induce chromosomal damage in Chinese Hamster Ovary cells was positive only when conducted in the presence of hepatic microsomes (metabolic activation). This single positive result in an in vitro test was not considered to be biologically important since a dose-dependent response was not observed, and negative results were obtained in in vitro tests conducted with dosages of milrinone that exceeded the recommended cumulative daily human oral and intravenous dosages by more than 25 fold.
Effects on fertility were not observed in male, female and 3-generation oral reproductive studies in rats. An increased rate of fetal resorptions was observed when milrinone was given as an intravenous bolus injection to rabbits at 7 times the cumulative maximum recommended human therapeutic dosage intended for administration by infusion during a period of 24 hours.
Milrinone was not teratogenic when administered orally or intravenously to rats and rabbits.
Species (N/group) | Dosage mg base/kg/day | Duration | No Adverse Effect | Threshold | Toxicity |
|---|---|---|---|---|---|
| Sprague-Dawley Rat | |||||
Study 1 (N=10M, 10F) | 2.5, 10, 40 | Bolus inj. Daily (4 weeks) | --- | 2.5a - 10.0b | 40.0c |
Study 2 (N=10M, 10F) | 0.01, 0.1, 1.0, 2.5 | Bolus inj. Daily (4 weeks) | 0.01, 0.1, 1.0, 2.5 | --- | --- |
| Beagle Dog | |||||
| (N=2M, 2F) | 2, 6, 18 | 4-hr Infusion (10 doses in 12 days) | --- | 2.0d | 6.0e 18.0e |
SELECTED BIBLIOGRAPHY
- 1.
Alousi, A.A., Canter, J.M., Montenaro, M.J., Fort, D.J. and Ferrari, R.A., Cardiotonic Activity of Milrinone, A New and Potent Cardiac Bipyridine, on the Normal and Failing Heart of
Experimental Animals. J. Cardiovascular Pharmacol. 1983; 5:792-803
- 2.
Alousi, A.A., Stankus, G.P., Stuart, J.C. and Walton, L.H., Characterization of the Cardiotonic
Effects of Milrinone, A New and Potent Cardiac Bipyridine, On Isolated Tissues from Several
Animal Species. J. Cardiovascular Pharmacol. 1983; 5:804-811.
- 3.
Anderson, J.L., Baim, D.S., Fein, S.A., Goldstein, R.A., LeJemtel, T.H., Likoff, M.J., Efficacy
and Safety of Sustained (48 hour) Intravenous Infusions of Milrinone in Patients With Severe
Congestive Heart Failure: A Multicenter Study. J. Am. Coll. Cardiol., 1987; 9(4):711-22.
- 4.
Baim, D.S., Monrad, E.S., McDowell, A.V., Smith, H., Lanoue, A., Braunwald, E. and
Grossman, W., Milrinone Therapy in Patients with Severe Congestive Heart Failure: Initial
Hemodynamic and Clinical Observations. In Braunwald, E. and Sonnenblick, E.H. et al, eds.
Milrinone: Investigation of New Inotropic Therapy For Congestive Heart Failure, New York,
Raven Press; 1984. p.143-153.
- 5.
Baker, J. F. and Edelson, J., Metabolism and Pharmacokinetics of Milrinone in Laboratory
Animals. In Braunwald, E., Sonnenblick, E.H., Chakrin, L.W. and Schwarz, R.P., eds.
Milrinone: Investigation of New Inotropic Therapy for Congestive Heart Failure, New York,
Raven Press; 1984. p. 49-53.
- 6.
Colucci, Was., Wright, R.F., Jaski, B.E., Fifer, M.A.,Braunwald, E., Milrinone and dobutamine
in severe heart failure: differing hemodynamic effects and individual patient responsiveness,
Circulation 1986; 73(suppl 111):111-175.
- 7. Davidenko, J.M. and Antzelevitch, C., The Effects of Milrinone on Conduction, Reflection, and Automaticity in Canine Purkinje Fibers. Circulation, 1984; 69 (5):1026-1035.
- 8.
Drobeck, H.P., Slighter, R.G., Jr. and Edelson, J., Toxicology Studies on Milrinone. In
Braunwald, E. and Sonnenblick, E.H. et al., eds. Milrinone: Investigation of New Inotropic
Therapy for Congestive Heart Failure, New York, Raven Press; 1984. p. 55-76.
- 9.
Goldstein, R. A., Geraci, S.A., Gray, E.L., Rinkenberger, R.L., Hamilton Dougherty, A.,
Naccarelli, G.V., Electrophysiologic Effects of Milrinone in Patients with Congestive Heart
Failure, Am. J. Cardiol. 1986; 57:624-628.
- 10.
Grose, R., Strain, J., Greenberg, M., LeJemtel, T.H., Systemic and Coronary Effects of
Intravenous Milrinone and Dobutamine in Congestive Heart Failure, J. Am. Coll. Cardiol.
1986; 7:1107-13.
- 11.
Jaski, B.E., Fifer, M.A., Wright, R.F., Braunwald, E., Colucci, W.S., Positive Inotropic and
Vasodilator Actions of Milrinone in Patients with Severe Congestive Heart Failure, J. Clin.
Invest. 1985; 75:643-649.
- 12. LeJemtel, T.H., Maskin, C.S., Chadwick, B. and Sonnenblick, E.H., Clinical Response to Long-Term Milrinone Therapy in Patients With Severe Congestive Heart Failure: 12-Month Experience. In Braunwald, E. and Sonnenblick, E.H. et. al., eds. Milrinone: Investigation of New Inotronic Therapy for Congestive Heart Failure, New York, Raven Press; 1984. p. 177-189.
- 13. Ludmer, P.L., Wright, R.F., Arnold, J.M.O., Ganz, P., Braunwald, E., Colucci, W.S., Separation of the direct myocardial and vasodilator actions of milrinone administered by an intracoronary infusion technique, Circulation 1986; 73(1):130-137.
- 14.
Maskin, C.S., Chadwick, B., Sonnenblick, E.H. and LeJemtel, T.H., Withdrawal and
Reinstitution of Long-Term Milrinone Therapy: Evidence of Drug-Dependent Improvement in Cardiac Performance Without Tachyphylaxis. In Braunwald, E. and Sonnenblick, E.H. et. al., eds. Milrinone Investigation of New Inotropic Therapy For Congestive Heart Failure, New York, Raven Press; 1984. p. 155-166.
- 15. Monrad, E.S., Baim, D.S., Smith, H.S., Lanoue, A., Braunwald, E. and Grossman, W., Effects of Milrinone on Coronary Hemodynamics and Myocardial Energetics In Patients With Congestive Heart Failure. Circulation 1985; 71(5):972-979.
- 16. Monrad, E.S., Baim, D.S., Smith, H.S., Lanoue, A.S., Milrinone, dobutamine, and nitroprusside: comparative effects on hemodynamics and myocardial energetics in patients with severe congestive heart failure, Circulation 1986; 73(suppl III):III-168-174.
- 17. Monrad, E.S., McKay, R.G., Baim, D.S., Colucci, W.S., Fifer, M.A., Heller, G. V., Royal, H. D., Grossman, W., Improvement in indexes of diastolic performance in patients with congestive heart failure treated with milrinone, Circulation 1984; 70(6):1030-1037.
- 18.
Simonton, C.A., Chatterjee, K., Cody, R.J., Kubo, S.H., Leonard, D., Daly, P. and Rutman, H.,
Milrinone in Congestive Heart Failure: Acute and Chronic Hemodynamic and Clinical
Evaluation. J. Am. Coll. Cardiol. 1985; 6(2):453-459.
- 19.
Sonnenblick, E.H., Grose, R., Strain, J., Zelcer, A.A., LeJemtel, T.H., Effects of milrinone on
left ventricular performance and myocardial contractility in patients with severe heart failure,
Circulation 1986; 73(suppl 111):111-162.
- 20.
Stroshane, R.M., Benziger, D.P. and Edelson, J., Pharmacokinetics of Milrinone in Congestive
Heart Failure Patients. In Braunwald, E. and Sonnenblick, E.H. et. al., eds. Milrinone:
Investigation of New Inotropic Therapy for Congestive Heart Failure. New York, Raven Press; 1984. p. 119-131.
- 21.
White, H.D., Ribeiro, J.P., Hartley, L.H., Colucci, W.S., Immediate Effects of Milrinone on
Metabolic and Sympathetic Responses to Exercise in Severe Congestive Heart Failure, Am.
J.Cardiol. 1985; 56:93-98.
- 22. Product Monograph - Pr Milrinone Lactate Injection 1 mg milrinone/mL, Fresenius Kabi Canada Ltd., Date of Revision: August 03, 2016, Control No: 197040.