


Product Monograph - Mylan-Lisinopril
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Oral | Tablet 5 mg, 10 mg and 20 mg | Corn starch, dibasic calcium phosphate, magnesium stearate, mannitol 60, talc and red iron oxide #30 |
INDICATIONS AND CLINICAL USE
Hypertension
MYLAN-LISINOPRIL (lisinopril) is indicated in the treatment of essential hypertension and in renovascular hypertension. It may be used alone or concomitantly with thiazide diuretics. A great majority of patients (>80%) with severe hypertension required combination therapy.
Heart Failure
MYLAN-LISINOPRIL is indicated in the management of symptomatic congestive heart failure as adjunctive treatment with diuretics, and where appropriate, digitalis. Treatment with MYLAN-LISINOPRIL should be initiated under close medical supervision, usually in a hospital.
High doses of MYLAN-LISINOPRIL reduce the risk of the combined outcomes of mortality and hospitalization (see ACTION AND CLINICAL PHARMACOLOGY, and DOSAGE AND ADMINISTRATION).
Treatment Following Acute Myocardial Infarction
MYLAN-LISINOPRIL is indicated in the treatment of hemodynamically stable patients as early as within 24 hours following acute myocardial infarction, to improve survival. Patients should receive, as appropriate, the standard recommended treatments such as thrombolytics, ASA and beta-blocker(s).
Therapy with MYLAN-LISINOPRIL should be reassessed after 6 weeks. If there is no evidence of symptomatic or asymptomatic left ventricular dysfunction, treatment with MYLAN-LISINOPRIL can be stopped.
MYLAN-LISINOPRIL should not be used if systolic blood pressure is <100 mm Hg, if clinically relevant renal failure is present, or if there is a history of bilateral stenosis of the renal arteries (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypotension Following Acute Myocardial Infarction; and WARNINGS AND PRECAUTIONS, Renal, Renal Impairment).
CONTRAINDICATIONS
MYLAN-LISINOPRIL (lisinopril) is contraindicated in patients who:
- Are hypersensitive to any component of this product;
- Have a known allergy to angiotensin converting enzyme (ACE) inhibitors;
- Have a history of angioedema relating to previous treatment with an ACE inhibitor;
- Have hereditary or idiopathic angioedema;
- Are taking aliskiren-containing drugs and have diabetes mellitus (type 1 or type 2) or moderate to severe renal impairment (GFR < 60 ml/min/1.73m2) (see WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System (RAS), PRECAUTIONS, Renal Impairment, and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions When used in pregnancy, ACE inhibitors can cause injury or even death of the developing fetus. When pregnancy is detected, MYLAN-LISINOPRIL should be discontinued as soon as possible (see WARNINGS AND PRECAUTIONS, Use in Pregnancy). |
Carcinogenesis and Mutagenesis
See TOXICOLOGY for discussion on animal data.
Cardiovascular
Hypotension
Symptomatic hypotension has occurred after administration of lisinopril, usually after the first or second dose or when the dose was increased. It is more likely to occur in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, vomiting, or possibly in patients with renin-dependant renovascular hypertension (see DOSAGE AND ADMINISTRATION). In patients with severe CHF, with or without associated renal insufficiency, excessive hypotension has been observed and may be associated with oliguria and/or progressive azotemia, and rarely with acute renal failure and/or death. Because blood pressure could potentially fall, patients at risk for hypotension should start therapy under very close medical supervision, usually in a hospital. Such patients should be followed closely for the first 2 weeks of treatment and whenever the dose of lisinopril and/or diuretic is increased. Similar considerations apply to patients with ischemic heart or cerebrovascular disease in whom an excessive fall in blood pressure could result in a myocardial infarction or cerebrovascular accident (see ADVERSE REACTIONS).
If hypotension occurs, the patient should be placed in supine position and, if necessary, receive an intravenous infusion of normal saline. A transient hypotensive response may not be a contraindication to further doses. These can usually be given to hypertensive patients without difficulty once the blood pressure has increased after volume expansion. However, lower MYLAN-LISINOPRIL doses and/or reduced concomitant diuretic therapy should be considered.
If hypotension occurs during treatment following acute myocardial infarction, consideration should be given to MYLAN-LISINOPRIL discontinuation (see ADVERSE REACTIONS, and DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Treatment Following Acute Myocardial Infarction).
In some patients with congestive heart failure who have normal or low blood pressure, additional lowering of systemic blood pressure may occur with MYLAN-LISINOPRIL. If hypotension occurs, a reduction of dose or discontinuation of therapy should be considered.
Hypotension Following Acute Myocardial Infarction
Lisinopril treatment following acute myocardial infarction must not be initiated in patients at risk of further serious hemodynamic deterioration after vasodilator treatment.
These include patients with systolic blood pressure of ≤100 mm Hg or those in cardiogenic shock.
During the first 3 days following the infarction, dosage reduction should occur if systolic blood pressure is between 100 and 120 mm Hg (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Treatment Following Acute Myocardial Infarction).
Patients with myocardial infarction in the GISSI-3 study treated with MYLAN-LISINOPRIL, had a higher (9.0% vs 3.7%) incidence of persistent hypotension (systolic blood pressure <90 mm Hg for more than 1 hour) than placebo.
Valvular Stenosis, Hypertrophic Cardiomyopathy
There is concern on theoretical grounds that patients with aortic stenosis or hypertrophic cardiomyopathy might be at particular risk of decreased coronary perfusion when treated with vasodilators.
MYLAN-LISINOPRIL should be given with caution to these patients.
Endocrine and Metabolism
Diabetic Patients
In diabetic patients treated with oral antidiabetics or insulin, glycemic control should be closely monitored during the first month of treatment with lisinopril (See DRUG INTERACTIONS).
Hematologic
Neutropenia/Agranulocytosis
Agranulocytosis and bone marrow depression have been caused by ACE inhibitors. Several cases of agranulocytosis and neutropenia have been reported in which a causal relationship to lisinopril cannot be excluded. Current experience with the drug shows the incidence to be rare. Periodic monitoring of white blood cell counts should be considered, especially in patients with collagen vascular disease and renal disease.
Hyperkalemia
In clinical trials with daily doses of 2.5 to 20 mg, hyperkalemia (serum potassium >5.7 mEq/L) occurred in approximately 2.2% of hypertensive patients and 4.0% of patients with CHF. In most cases these were isolated values which resolved despite continued therapy. Hyperkalemia was a cause of discontinuation of therapy in approximately 0.1% of hypertensive patients.
As shown in the ATLAS trial (see ACTION AND CLINICAL PHARMACOLOGY), high dose (≤35 mg) versus low dose (≤5 mg) treatment may predispose CHF patients to hyperkalemia (6.4% versus 3.5%). This event was manageable and rarely led to treatment withdrawal. Therapy discontinuation rates due to hyperkalemia for high versus low dose were 0.4% versus 0.1%, respectively. Risk factors for the development of hyperkalemia may include renal insufficiency, diabetes mellitus, and the concomitant use of potassium-sparing diuretics (e.g., spironolactone, triamterene or amiloride), potassium supplements, other drugs that may increase potassium levels (e.g., heparin, co-trimoxazole) and/or potassium-containing salt substitutes. (See WARNINGS AND PRECAUTIONS, DRUG INTERACTIONS).
Hepatic/Biliary/Pancreatic
Patients with Impaired Liver Function
Hepatitis – either hepatocellular or cholestatic, jaundice, marked elevations of liver enzymes and/or serum bilirubin have occurred during therapy with lisinopril in patients with or without pre-existing liver abnormalities (see ADVERSE REACTIONS). Very rarely, it has been reported that in some patients the undesirable development of hepatitis has progressed to hepatic failure. Patients receiving MYLAN-LISINOPRIL who develop jaundice or marketed elevation of hepatic enzymes should discontinue MYLAN-LISINOPRIL and receive appropriate medical follow-up (See WARNINGS AND PRECAUTIONS – Patients with Impaired Liver Function). Should the patient receiving MYLAN-LISINOPRIL experience any unexplained symptoms (see WARNINGS AND PRECAUTIONS, General, Information for Patients), particularly during the first weeks or months of treatment, it is recommended that a full set of liver function tests and any other necessary investigation be carried out. Discontinuation of MYLAN-LISINOPRIL should be considered when appropriate.
There are no adequate studies in patients with cirrhosis and/or liver dysfunction. MYLAN-LISINOPRIL should be used with particular caution in patients with pre-existing liver abnormalities. In such patients baseline liver function tests should be obtained before administration of the drug and close monitoring of response and metabolic effects should apply.
Immune
Angioedema
Angioedema has been uncommonly reported in patients treated with lisinopril and may occur at any time during therapy. Angioedema associated with laryngeal or tongue edema and/or shock may be fatal. If angioedema occurs, MYLAN-LISINOPRIL should be promptly discontinued and the patient should be treated, and observed until the swelling subsides. Where swelling is confined only to the tongue, without respiratory distress, patients may require prolonged observation since treatment with antihistamines and corticosteroids may not be sufficient. However, where there is involvement of the tongue, glottis or larynx, likely to cause airway obstruction, and especially in cases where there has been a history of airway surgery, emergency therapy should be administered promptly when indicated. This includes giving subcutaneous adrenaline (0.5 mL 1:1000), and/or maintaining a patent airway. The patient should be under close medical supervision until complete and sustained symptom resolution has occurred.
The incidence of angioedema during ACE inhibitor therapy has been reported to be higher in black than in non-black patients.
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see CONTRAINDICATIONS).
Patients receiving coadministration of ACE inhibitor and mTOR (mammalian target of rapamycin) inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema. Caution should be used when these drugs are used concomitantly (see DRUG INTERACTIONS).
Dual blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin converting enzyme (ACE) inhibitors, such as lisinopril, or of angiotensin receptor antagonists (ARBs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR <60 ml/min/1.73m2). Therefore, the use of lisinopril in combination with aliskiren-containing drugs is contraindicated in these patients (see CONTRAINDICATIONS).
Further, co-administration of ACE inhibitors, including lisinopril, with other agents blocking the RAS, such as ARBs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, decreased renal failure (including acute renal failure), and hyperkalemia.
Avoid the concomitant use of ACE inhibitors and ARBs in patients with diabetic nephropathy.
If dual blockade therapy is considered necessary, this should only occur under specialist supervision and subject to frequent close monitoring of renal function, electrolytes and blood pressure.
Anaphylactoid Reactions During Membrane Exposure
Anaphylactoid reactions have been reported in patients dialysed with high-flux membranes [e.g.: polyacrylonitrile (PAN) and during low-density lipoproteins (LDL) apheresis with dextran sulphate] and treated concomitantly with an ACE inhibitor. Dialysis should be stopped immediately if symptoms such as nausea, abdominal cramps, burning, angioedema, shortness of breath and severe hypotension occur. Symptoms are not relieved by antihistamines. In these patients consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent.
Anaphylactoid Reactions During Desensitization
There have been isolated reports of patients experiencing sustained life threatening anaphylactoid reactions while receiving ACE inhibitors during desensitizing treatment with hymenoptera (bees, wasps) venom. In the same patients, these reactions have been avoided when ACE inhibitors were temporarily withheld for at least 24 hours, but they have reappeared upon inadvertent rechallenge.
Nitritoid Reactions – Gold
Nitritoid reactions (symptoms of vasodilatation including flushing, nausea, dizziness and hypotension, which can be very severe) following injectable gold (for example, sodium aurothiomalate) have been reported more frequently in patients receiving ACE inhibitor therapy (see PRECAUTIONS, Drug Interactions).
Occupation Hazards
Ability to drive and use machines: dizziness or tiredness may occur during treatment with lisinopril.
Peri-Operative Considerations
Surgery/Anesthesia
In patients undergoing major surgery or during anesthesia with agents that produce hypotension, lisinopril blocks angiotensin II formation, secondary to compensatory renin release. If hypotension occurs and is considered to be due to this mechanism, it can be corrected by volume expansion.
Renal
Renal Impairment
As a consequence of inhibiting the RAAS, changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the RAAS, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe CHF, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk.
The use of ACE inhibitors, including lisinopril, or ARBs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR <60ml/min/1.73m2) (see CONTRAINDICATIONS and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACE inhibitors, or aliskiren-containing drugs).
In acute myocardial infarction, treatment with lisinopril should not be initiated in patients with evidence of renal dysfunction, defined as serum creatinine concentration exceeding 177 micromol/L and/or proteinuria exceeding 500 mg/24 h. If renal dysfunction develops during treatment with MYLAN-LISINOPRIL (serum creatinine concentration exceeding 265 micromol/L or a doubling from the pre-treatment value), then the physician should consider withdrawal of MYLAN-LISINOPRIL.
Use of MYLAN-LISINOPRIL (lisinopril) should include appropriate assessment of renal function.
Respiratory
Cough
A dry, persistent cough, which usually disappears only after withdrawal or lowering of the dose of MYLAN-LISINOPRIL, has been reported.
Such a possibility should be considered as part of the differential diagnosis of the cough.
Special Populations
Pregnant Women:
ACE inhibitors must be avoided during pregnancy because these agents can cause fetal and neonatal morbidity and mortality when administered to pregnant women. When pregnancy is detected, MYLAN-LISINOPRIL should be discontinued as soon as possible.
The use of ACE inhibitors during the second and third trimesters of pregnancy has been associated with fetal and neonatal injury including hypotension, neonatal skull hypoplasia, anuria, reversible or irreversible renal failure, and death. Oligohydramnios has also been reported, presumably resulting from decreased fetal renal function, associated with fetal limb contractures, craniofacial deformation, and hypoplastic lung development.
Prematurity, and patent ductus arteriosus and other structural cardiac malformations, as well as neurologic malformations, have also been reported following exposure in the first trimester of pregnancy.
Infants with a history of in utero exposure to ACE inhibitors should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed towards support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit.
Lisinopril has been removed from the neonatal circulation by peritoneal dialysis.
Animal Data
Lisinopril was not teratogenic in mice treated on days 6-15 of gestation with ≤1000 mg/kg/day (625 times the maximum recommended human dose). There was an increase in fetal resorptions at doses ≥100 mg/kg; at doses of 1000 mg/kg, this was prevented by saline supplementation. There was no fetotoxicity or teratogenicity in rats treated with ≤300 mg/kg/day (188x the maximum recommended dose) of lisinopril at days 6-17 of gestation. In rats receiving lisinopril from day 15 of gestation through day 21 postpartum, there was an increased incidence in pup deaths on days 2-7 postpartum and a lower average body weight of pups on day 21 postpartum. The increase in pup deaths and decrease in pup weight did not occur with maternal saline supplementation.
Lisinopril, at doses ≤1 mg/kg/day, was not teratogenic when given throughout the organogenic period in saline supplemented rabbits. Saline supplementation (physiologic saline in place of tap water) was used to eliminate maternotoxic effects and enable evaluation of the teratogenic potential at the highest possible dosage level.
Fetotoxicity was demonstrated in rabbits by an increased incidence of fetal resorptions at an oral dose of lisinopril of 1 mg/kg/day and by an increased incidence of incomplete ossification at the lowest dose tested (0.1 mg/kg/day). A single intravenous dose of 15 mg/kg of lisinopril administered to pregnant rabbits on gestation days 16, 21 or 26 resulted in 88-100% fetal death.
By whole body autoradiography, radioactivity was found in the placenta following administration of labeled lisinopril to pregnant rats, but none was found in the fetuses.
Use in Nursing Women:
The presence of concentrations of ACE inhibitor have been reported in human milk. Use of ACE inhibitors is not recommended during breast feeding.
Race:
ACE inhibitors cause a higher rate of angioedema in black patients than in non-black patients.
The antihypertensive effect of ACEinhibitors is generally lower in black patients (usually a low-renin hypertensive population) than in non-black patients.
Pediatrics (6-16 years old< 18 years of age):
Antihypertensive effects of lisinopril have been established in hypertensive pediatric patients aged 6 to 16 years. There are no data of the effects of lisinopril in hypertensive patients under the age of <6 or in patients with glomerular filtration rate GFR <30 mL/min/1.73 m2 (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Pharmacokinetics, DOSAGE AND ADMINISTRATION, Pediatric Patients).
Monitoring and Laboratory Tests
No data is available.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In controlled clinical trials involving 3269 patients, 2633 patients with hypertension and 636 patients with CHF, excluding the ATLAS CHF study patients (see ACTION and CLINICAL PHARMACOLOGY), the most frequent clinical adverse reactions were: dizziness (4.4%), headache (5.6%), asthenia/fatigue (2.7%), diarrhea (1.8%) and cough (3.0%), all of which were more frequent than in placebo-treated patients. Discontinuation of therapy was required in 5.9% of patients.
For adverse reactions which occurred in hypertensive patients and patients with CHF treated with lisinopril in controlled clinical trials, comparative incidence data are listed in the table below.
Adverse Events in Controlled Clinical Trials
Incidence of adverse reactions occurring in patients treated with lisinopril in controlled clinical trials.
Hypertension n=2 633 (%) | Congestive Heart Failure n=636 (%) | ||
|---|---|---|---|
| Cardiovascular | Hypotension orthostatic effects chest pain angina edema palpitation rhythm disturbances | 0.8 0.9 1.1 0.3 0.6 0.8 0.5 | 5.2 1.3 7.4 3.8 2.5 1.9 0.6 |
| Gastrointestinal | Diarrhea Nausea Vomiting Dyspepsia Anorexia Constipation flatulence | 1.8 1.9 1.1 0.5 0.4 0.2 0.3 | 6.1 4.9 2.4 1.9 1.4 0.8 0.5 |
| Nervous System | Dizziness Headache Paresthesia Depression Somnolence Insomnia vertigo | 4.4 5.6 0.5 0.7 0.8 0.3 0.2 | 14.2 4.6 2.8 1.1 0.6 2.4 0.2 |
| Respiratory | Cough Dyspnea orthopnea | 3.0 0.4 0.1 | 6.4 7.4 0.9 |
| Dermatologic | Rash pruritus | 1.0 0.5 | 5.0 1.4 |
| Musculoskeletal | muscle cramps back pain leg pain shoulder pain | 0.5 0.5 0.1 0.2 | 2.2 1.7 1.3 0.8 |
| Other | asthenia/fatigue blurred vision fever flushing gout decreased libido malaise | 2.7 0.3 0.3 0.3 0.2 0.2 0.3 | 7.1 1.1 1.1 0.3 1.7 0.2 1.1 |
Angioedema
Angioedema has been reported in patients receiving lisinopril (0.1%). In very rare cases, intestinal angioedema has been reported (See WARNINGS AND PRECAUTIONS, Immune, Angioedema).
Hypotension
In hypertensive patients, hypotension occurred in 0.8% and syncope occurred in 0.2% of patients. Hypotension or syncope was a cause for discontinuation of therapy in 0.3% of hypertensive patients (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypotension).
In patients with CHF, hypotension occurred in 5.2% and syncope occurred in 1.7% of patients. Hypotension and dizziness were causes for discontinuation of therapy in 1.7% of these patients.
As shown in the ATLAS trial (see ACTION AND CLINICAL PHARMACOLOGY), high dose (≤35 mg) versus low dose (≤5 mg) treatment may predispose patients to hypotension-related symptoms such as: dizziness (18.9% versus 12.1%), syncope (7.0% versus 5.1%), and hypotension (10.8% versus 6.7%). These events were manageable and rarely led to treatment withdrawal. Therapy discontinuation rates for high versus low dose were: dizziness 0.3 and 0%, hypotension 0.8% and 0.6%, and for syncope 0.3% and 0.3%, respectively.
Treatment Following Acute Myocardial Infarction
In a controlled, open trial, involving 19,394 acute myocardial infarction patients (GISSI-3; see INDICATIONS AND CLINICAL USE - Treatment Following Acute Myocardial Infarction), comparing lisinopril alone, transdermal glycerol trinitrate, lisinopril and transdermal glycerol trinitrate, or control (no treatment), the most frequent in-hospital adverse events were as follows:
| Event | Control | Lisinopril | Lisinopril + GTN | GTN Alone |
| n=4729 | n=4713 | n=4722 | n=4731 | |
| Persistent Hypertension | 3.6 | 8.8 | 9.3 | 3.9 |
| Shock | 2.5 | 2.8 | 2.2 | 1.9 |
| Renal Dysfunction | 1.1 | 2.4 | 2.4 | 1.1 |
| Stroke | 0.6 | 0.6 | 0.9 | 0.8 |
| Re-Infarction | 2.2 | 2.2 | 2.2 | 1.9 |
| Hemorrhagic Events | 1.2 | 1.3 | 1.1 | 0.9 |
| Post-Infarction Angina | 13.2 | 13.9 | 12.3 | 11.8 |
| Ventricular Fibrillation | 3.1 | 2.5 | 2.4 | 2.2 |
| Sustained Ventricular Tachycardia | 2.5 | 2.1 | 1.8 | 2.3 |
| Atrial Flutter or Fibrillation | 6.4 | 6.3 | 5.3 | 5.7 |
| Complete Atrioventricular Block | 2.4 | 2.9 | 2.5 | 2.1 |
| Asystole | 1.2 | 1.2 | 1.3 | 1.2 |
| Intraventricular Septal Rupture | 0.3 | 0.4 | 0.2 | 0.2 |
| Papillary Muscle Rupture | 0.3 | 0.4 | 0.5 | 0.4 |
| Late CHF (>4 days) | 4.5 | 4.5 | 4.2 | 4.2 |
Pediatric Patients (6-16 years old)
The adverse experience profile for pediatric patients appears to be similar to that seen in adult patients.
Laboratory Test Findings
Serum Electrolytes
Hyperkalemia (see WARNINGS AND PRECAUTIONS).
Creatinine, Blood Urea Nitrogen
Increases in blood urea nitrogen (BUN) and serum creatinine, usually reversible upon discontinuation of therapy, were observed in 1.1% and 1.6% of patients respectively with essential hypertension treated with lisinopril alone. Increases were more common in patients receiving concomitant diuretics and in patients with renal artery stenosis (see WARNINGS AND PRECAUTIONS). In patients with CHF on 2.5 to 20 mg lisinopril and concomitant diuretic therapy, reversible increases in BUN (14.5%) and serum creatinine (11.2%) were observed in approximately 12.0% of patients. Frequently, these abnormalities resolved when the dosage of the diuretic was decreased.
As shown in the ATLAS trial (see ACTION AND CLINICAL PHARMACOLOGY), high dose (≤35 mg) versus low dose (≤5 mg) treatment may predispose patients to increased serum creatinine (9.9% versus 7.0%). This event was manageable and rarely led to treatment withdrawal. Therapy discontinuation rates due to increased serum creatinine for high versus low dose were 0.3% versus 0.4%, respectively.
Hematology
Decreases in hemoglobin and hematocrit (mean decreases of approximately 0.9g % and 0.6 vol %, respectively) occurred frequently in patients treated with lisinopril but were rarely of clinical importance in patients without some other cause of anemia. Rarely, hemolytic anemia has been reported.
Agranulocytosis and bone marrow depression, manifested as anemia, cytopenia or leukopenia, have been caused by ACE inhibitors, including lisinopril. Several cases of agranulocytosis and neutropenia have been reported in which a causal relationship to lisinopril cannot be excluded (see WARNINGS AND PRECAUTIONS, Hematologic, Neutropenia/Agranulocytosis).
Hepatic
Elevations of liver enzymes and/or serum bilirubin have occurred (see WARNINGS AND PRECAUTIONS - Patients with Impaired Liver Function).
Discontinuations
Overall, 1.0% of patients discontinued therapy due to laboratory adverse experiences, principally elevations in BUN (0.8%), serum creatinine (0.1%) and serum potassium (0.1%).
Post-Marketing Experience
The following undesirable effects have been observed and reported during treatment with lisinopril with the following frequencies: Very common (≥10%), Common (≥1%, <10%), uncommon (≥0.1%, <1%), rare (≥0.01%, <0.1%), very rare (<0.01%) including isolated reports.
Blood and lymphatic system disorders
Very rare: agranulocytosis, anemia, bone marrow depression, = hemolytic anemia (see WARNINGS AND PRECAUTIONS – Neutropenia/Agranulocytosis), leucopenia, thrombocytopenia.
Endocrine disorders
Rare: inappropriate antidiuretic hormone secretion
Metabolism and nutrition disorders
Uncommon: hyperkalemia (see WARNINGS AND PRECAUTIONS – Hyperkalemia)
Rare: hyponatremia
Very rare: hypoglycaemia (see WARNINGS AND PRECAUTIONS – Diabetic Patients)
Nervous system and psychiatric disorders
Common: dizziness, headache.
Uncommon: hallucinations, mood alterations (including depressive symptoms), paresthesia, sleep disturbances, taste disturbance, vertigo.
Rare: mental confusions, olfactory disturbance.
Cardiac and vascular disorders
Common: orthostatic effects (including hypotension) (see WARNINGS AND PRECAUTIONS – Hypotension), syncope (frequency refers to congestive heart failure patient population, frequency in hypertensive patient population is
“uncommon”).
Uncommon: myocardial infarction or cerebrovascular accident (both possibly secondary to excessive hypotension in high risk patients, (see WARNINGS AND PRECAUTIONS – Hypotension Following Acute Myocardial Infarction), palpitations, tachycardia.
Respiratory, thoracic and mediastinal disorders;
Common: cough
Uncommon: rhinitis
Very rare: bronchospasm, sinusitis
Gastrointestinal disorders
Common: diarrhea, vomiting.
Uncommon: abdominal pain, indigestion, nausea.
Rare: dry mouth.
Very rare: intestinal angioedema (See WARNINGS AND PRECAUTIONS – Angioedema and ADVERSE EVENTS – Angioedema), pancreatitis,.
Hepato-biliary disorders
Very rare: hepatitis – either hepatocellular or cholestatic, jaundice, hepatic failure. Very rarely it has been reported that in some patients the undesirable development of hepatitis has progressed to hepatic failure. Patients receiving lisinopril who develop jaundice or marked elevation of hepatic enzymes should discontinue lisinopril and receive appropriate medical follow-up (See WARNINGS AND PRECAUTIONS – Patients with Impaired Liver Function).
Skin and subcutaneous tissue disorders
Uncommon: rash, pruritus, hypersensitivity/angioedema: angioedema of the face, extremities, lips, tongue, glottis, and/or larynx (see WARNINGS AND PRECAUTIONS –Angioedema).
Rare: alopecia, psoriasis, urticaria.
Very rare: cutaneous pseudolymphoma, diaphoresis, erythema multiforme, pemphigus, Stevens-Johnson Syndrome, toxic epidermal necrolysis,.
A symptom complex has been reported which may include one or more of the following: fever, vasculitis, myalgia, arthralgia/arthritis, a positive antinuclear antibodies (ANA), elevated red blood cell sedimentation rate (ESR), eosinophilia and leukocytosis. Rash, photosensitivity, or other dermatological manifestations may occur.
Renal and urinary disorders
Common: renal dysfunction.
Rare: acute renal failure, uremia.
Very rare: oliguria/anuria (see WARNINGS AND PRECAUTIONS – Renal Impairment).
Reproductive system and breast disorders
Uncommon: impotence.
General disorders and administration site conditions
Uncommon: asthenia, fatigue.
Investigations
Uncommon: increases in blood urea, increases in serum creatinine (see WARNINGS AND PRECAUTIONS – Renal Impairment), increases in liver enzymes (see WARNINGS AND PRECAUTIONS – Patients with Impaired Liver Function).
Rare: decreases in hemoglobin, decreases in hematocrit, increases in serum bilirubin (see WARNINGS AND PRECAUTIONS – Patients with Impaired Liver Function).
DRUG INTERACTIONS
Drug-Drug Interactions
Hypotension - Patients on Diuretic Therapy
Patients on diuretics and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with lisinopril. The possibility of symptomatic hypotension with lisinopril can be minimized by discontinuing the diuretic prior to initiation of treatment with lisinopril and/or lowering the initial dose of lisinopril (See WARNINGS AND PRECAUTIONS, Hypotension; and DOSAGE AND ADMINISTRATION).
Hypotension - Patients on Antihypertensive Therapy
When lisinopril is given to patients already treated with other antihypertensive agents, further falls in blood pressure may also occur.
Dual Blockade of the Renin-Angiotensin-System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs
Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs or ACE inhibitors and aliskiren-containing drugs is contraindicated in patients with diabetes and/or renal impairment (see CONTRAINDICATIONS). Co-administration of ARBs, ACE inhibitors or aliskiren-containing drugs is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, decreased renal function (including acute renal failure), and hyperkalemia when compared to the use of a single RAS-acting agent (see WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS) and Renal Impairment).
Potassium Supplements, potassium-sparing agents or potassium-containing salt substitutes and other drugs that may increase serum potassium levels
Since lisinopril decreases aldosterone production, elevation of serum potassium may occur. Potassium sparing diuretics such as spironolactone, triamterene or amiloride, or potassium supplements and other drugs that may increase potassium levels (e.g., heparin, co-trimoxazole) should be given only for documented hypokalemia and with caution and with frequent monitoring of serum potassium since they may lead to a significant increase in serum potassium. Potassium-containing salt substitutes should also be used with caution.
Agents Causing Renin Release
The antihypertensive effect of MYLAN-LISINOPRIL is augmented by antihypertensive agents that cause renin release (e.g. diuretics).
Agents Affecting Sympathetic Activity
Agents affecting sympathetic activity (e.g., ganglionic blocking agents or adrenergic neuron blocking agents) may be used with caution. Beta-adrenergic blocking drugs add some further antihypertensive effect to lisinopril.
Non-Steroidal Anti-Inflammatory Drugs (NSAIDS)
In some patients with compromised renal function, lisinopril co-administration with non-steroidal anti-inflammatory drugs (NSAIDs) may produce further renal function deterioration.
Indomethacin may diminish the antihypertensive efficacy of concomitantly administered MYLAN-LISINOPRIL.
Lithium Salts
As with other drugs which eliminate sodium, lithium elimination may be reduced. Therefore, the serum lithium levels should be monitored carefully if lithium salts are to be administered.
Gold
Nitritoid reactions (symptoms of vasodilatation including flushing, nausea, dizziness and hypotension, which can be very severe) following injectable gold (for example, sodium aurothiomalate) have been reported more frequently in patients receiving ACE inhibitor therapy.
Antidiabetics
Epidemiological studies have suggested that concomitant administration of ACE inhibitors and antidiabetic medicines (insulins, oral hypoglycemic agents) may cause an increased blood glucose lowering effect with risk of hypoglycemia. This phenomenon appeared to be more likely to occur during the first weeks of combined treatment and in patients with renal impairment.
Tissue Plasminogen Activators
Concomitant treatment with tissue plasminogen activators may increase the risk of angioedema. Monitor patients for potential development of angioedema after initiation of tissue plasminogen activator infusion.
Mammalian Target of Rapamycin (mTOR) Inhibitors (e.g., temsirolimus, sirolimus, everolimus)
Patients taking concomitant mTOR inhibitor therapy may be at increased risk for angioedema. Caution should be used when these drugs are used concomitantly (see WARNINGS, Angioedema).
Drug-Food Interactions
Since absorption of MYLAN-LISINOPRIL tablets (lisinopril) is not affected by food, the tablets may be administered before, during or after meals.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Since absorption of MYLAN-LISINOPRIL tablets (lisinopril) is not affected by food, the tablets may be administered before, during or after meals. MYLAN-LISINOPRIL should be administered in a single daily dose. MYLAN-LISINOPRIL should be taken at the same time each day.
Dosage must be individualized and should be adjusted according to blood pressure response.
Recommended Dose and Dosage Adjustment
Essential Hypertension
In patients with essential hypertension, not on diuretic therapy, the usual recommended starting dose is 10 mg once a day. The usual dosage range is 10 to 40 mg per day, administered in a single daily dose. The antihypertensive effect may diminish toward the end of the dosing interval regardless of the administered dose, but most commonly with a dose of 10 mg daily. This can be evaluated by measuring blood pressure just prior to dosing to determine whether satisfactory control is being maintained for 24 hours. If it is not, an increase in dose should be considered. The maximum dose used in long-term controlled clinical trials was 80 mg/day. If blood pressure is not controlled with MYLAN-LISINOPRIL alone, a low dose of diuretic may be added. Hydrochlorothiazide 12.5 mg has been shown to provide an additive effect. After the addition of diuretic, it may be possible to reduce the dose of MYLAN-LISINOPRIL.
Diuretic Treated Patients
In hypertensive patients who are currently being treated with a diuretic, symptomatic hypotension may occur occasionally following the initial dose of MYLAN-LISINOPRIL. The diuretic should be discontinued, if possible, for 2-3 days before beginning therapy with MYLAN-LISINOPRIL to reduce the likelihood of hypotension (see WARNINGS AND
PRECAUTIONS). The dosage of MYLAN-LISINOPRIL should be adjusted according to blood pressure response. If the patient's blood pressure is not controlled with MYLAN-LISINOPRIL alone, diuretic therapy may be resumed as described above.
If the diuretic cannot be discontinued, an initial dose of 5 mg should be used under medical supervision for ≥2 hours and until blood pressure has stabilized for ≥additional hour (see WARNINGS AND PRECAUTIONS, Hypotension; and DRUG INTERACTIONS).
A lower starting dose is required in the presence of renal impairment, in patients in whom diuretic therapy cannot be discontinued, patients who are volume and/or salt-depleted for any reason, and in patients with renovascular hypertension.
Dosage Adjustment in Renal Impairment
Dosage in patients with renal impairment should be based on creatinine clearance as outlined in the Table below:
| Creatinine Clearance | Starting Dose mg/day | |
| mL/s | mL/min | |
| 0.50-1.17 | 31-70 | 5.0-10.0 |
| 0.17-0.50 | 10-30 | 2.5-5.0 |
<0.17 (including patients on dialysis) | <10 (including patients on dialysis) | 2.5* |
*Dosage and/or frequency of administration should be adjusted depending on the blood pressure response.
The dosage may be titrated upward until blood pressure is controlled or to a maximum of 40 mg daily.
Dosage in the Elderly
In general, blood pressure response and adverse experiences were similar in younger and older patients given similar doses of lisinopril. Pharmacokinetic studies, however, indicate that maximum blood levels and area under the plasma concentration time curve (AUC) are doubled in older patients so that dosage adjustments should be made with particular caution.
Renovascular Hypertension
Some patients with renovascular hypertension, especially those with bilateral renal artery stenosis or stenosis of the artery to a solitary kidney, may develop an increased risk of severe hypotension and renal insufficiency to the first dose of MYLAN-LISINOPRIL. In these patients, treatment should be started at low doses (2.5 or 5 mg), under close medical supervision. Thereafter, the dosage may be adjusted according to the blood pressure response. Doses should be carefully titrated.
Congestive Heart Failure
MYLAN-LISINOPRIL is to be used in conjunction with diuretics, and where appropriate, digitalis. Therapy must be initiated under close medical supervision, usually in a hospital. Blood pressure and renal function should be monitored, both before and during treatment with
MYLAN-LISINOPRIL, because severe hypotension and, more rarely, consequent renal failure have been reported (see WARNINGS AND PRECAUTIONS, Hypotension; and WARNINGS AND PRECAUTIONS, Renal Impairment).
Initiation of therapy requires consideration of recent diuretic therapy and the possibility of severe salt/volume depletion. If possible, the dose of diuretic should be reduced before beginning treatment.
The recommended initial dose is 2.5 mg per day. The MYLAN-LISINOPRIL dose should be increased:
- by increments of ≤ 10 mg,
- at intervals of ≥2 weeks, up to a maximum of 35 mg once daily. Dose adjustment should be based on the individual patient’s tolerance and clinical response.
Treatment Following Acute Myocardial Infarction
Treatment with MYLAN-LISINOPRIL may be started as early as within 24 hours following the onset of symptoms in hemodynamically stable patients. Patients should receive, as appropriate, the standard recommended treatments such as thrombolytics, ASA and beta-blocker(s) (see INDICATION AND CLINICAL USE - Treatment Following Acute Myocardial Infarction).
The first dose of MYLAN-LISINOPRIL is 5 mg given orally, followed by 5 mg after 24 hours, 10 mg after 48 hours and then 10 mg once daily thereafter.
Patients with a low systolic blood pressure (between 100 and 120 mm Hg) when treatment is started or during the first 3 days after the infarct should be given a lower dose - 2.5 mg orally. Treatment with MYLAN-LISINOPRIL must not be initiated in patients who are at risk of serious hemodynamic deterioration (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypotension Following Acute Myocardial Infarction). After three days, if hypotension occurs (systolic blood pressure ≤ 100 mm Hg), a daily maintenance dose of 5 mg may be given with temporary reductions to 2.5 mg if needed. If prolonged hypotension occurs (systolic blood pressure <90 mm Hg for >1 hour), MYLAN-LISINOPRIL should be withdrawn.
Renal function should be assessed before and during therapy with MYLAN-LISINOPRIL (see WARNINGS AND PRECAUTIONS, Renal Impairment).
Dosing should normally continue for 6 weeks. At that time, patients with signs or symptoms of heart failure should continue with MYLAN-LISINOPRIL (see DOSAGE AND ADMINISTRATION - Congestive Heart Failure).
MYLAN-LISINOPRIL is compatible with intravenous or transdermal glyceryl trinitrate.
Pediatric Patients (6-16 years old)
For patients who can swallow tablets, the dose should be individualized according to patient profile and blood pressure response. The recommended initial dose is 2.5 mg in patients 20 to <50 kg and 5 mg in patients ≥ 50 kg. MYLAN-LISINOPRIL is given once daily. The dosage should be adjusted according to the needs of the patient to a maximum of 20 mg daily in patients 20 to <50 kg and 40 mg in patients ≥ 50 kg (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Pharmacokinetics).
MYLAN-LISINOPRIL is not recommended in pediatric patients <6 years or with GFR <30 mL/min/1.73 m2 (see ACTION AND CLINICAL PHARMACOLOGY,
Pharmacodynamics, Pharmacokinetics).
Missed Dose
If a dose of this medication is missed, it is not necessary to make up the missed dose. Skip the missed dose and continue with the next scheduled dose. Do not double doses.
Administration
Since absorption of MYLAN-LISINOPRIL tablets (lisinopril) is not affected by food, the tablets may be administered before, during or after meals. MYLAN-LISINOPRIL should be administered in a single daily dose. MYLAN-LISINOPRIL should be taken at the same time each day.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
Overdose symptoms include severe hypotension, electrolyte disturbances, and renal failure. Overdosed patients should be kept under very close observation. Therapeutic measures depend on the nature and severity of symptoms. Measures to prevent absorption and methods to speed elimination should be employed. If severe hypotension occurs, place the patient in the shock position and infuse intravenous normal saline immediately. Vasopressors including angiotensin II may be considered if fluid replacement is inadequate or contraindicated. Circulating lisinopril may be removed by hemodialysis. Avoid high-flux polyacrylonitrile dialysis membranes (see WARNINGS AND PRECAUTIONS, Anaphylactoid Reactions during membrane exposure). Serum electrolytes and creatinine should be monitored frequently.
ACTION AND CLINICAL PHARMACOLOGY
Lisinopril is an angiotensin converting enzyme (ACE) inhibitor which is used in the treatment of hypertension, congestive heart failure and following myocardial infarction in hemodynamically stable patients.
Mechanism of Action
Angiotensin converting enzyme (ACE) is a peptidyl dipeptidase which catalyzes the conversion of angiotensin I to the pressor substance, angiotensin II. Inhibition of ACE results in decreased plasma angiotensin II, which leads to increased plasma renin activity (due to removal of negative feedback of renin release) and decreased aldosterone secretion. Although the latter decrease is small, it results in a small increase in serum potassium. In patients treated with lisinopril and a thiazide diuretic there was essentially no change in serum potassium (see WARNINGS AND PRECAUTIONS).
ACE is identical to kininase II. Thus, lisinopril may also block the degradation of bradykinin, a potent vasodilator peptide. However, the role that this plays in the therapeutic effects of lisinopril is unknown.
While the mechanism through which lisinopril lowers blood pressure is believed to be primarily the suppression of the renin-angiotensin-aldosterone system (RAAS), lisinopril also lowers blood pressure in patients with low-renin hypertension.
Pharmacodynamics
Hypertension
Adults: Administration of lisinopril to patients with hypertension results in a reduction of both supine and standing blood pressure. Abrupt withdrawal of lisinopril has not been associated with a rapid increase in blood pressure. In most patients studied, after oral administration of an individual dose of lisinopril, the onset of antihypertensive activity is seen at one hour with peak reduction of blood pressure achieved by 6 hours. Although an antihypertensive effect was observed 24 hours after dosing with recommended single daily doses, the effect was more consistent and the mean effect was considerably larger in some studies with doses of ≥20 mg than with lower doses. However, at all doses studied, the mean antihypertensive effect was substantially smaller 24 hours after dosing than it was 6 hours after dosing. On occasion, achievement of optimal blood pressure reduction may require 2 to 4 weeks of therapy.
Pediatrics (6-16 years old): In a clinical study involving 115 hypertensive pediatric patients 6 to 16 years of age, patients who weighed <50 kg received either 0.625, 2.5, or 20 mg of lisinopril daily and patients who weighed ≥50 kg received either 1.25, 5, or 40 mg of lisinopril daily. At the end of 2 weeks, lisinopril administered once daily lowered trough blood pressure in a dose-dependent manner with consistent antihypertensive efficacy demonstrated at doses >1.25 mg (0.02 mg/kg). This effect was confirmed in a withdrawal phase, where the diastolic pressure rose by about 9 mmHg more in patients randomized to placebo than it did in patients who were randomized to remain on the middle and high doses of lisinopril. The dose-dependent antihypertensive effect of lisinopril was consistent across several demographic subgroups: age, Tanner stage, gender, race. In this study, lisinopril was generally well-tolerated.
Adults: In hemodynamic studies in patients with essential hypertension, blood pressure reduction was accompanied by a reduction in peripheral arterial resistance with little or no change in cardiac output and in heart rate. In a study in 9 hypertensive patients, following administration of lisinopril, there was an increase in mean renal blood flow that was not significant. Data from several small studies are inconsistent with respect to the effect of lisinopril on glomerular filtration rate in hypertensive patients with normal renal function, but suggest that changes, if any, are not large.
When lisinopril is given together with thiazide-type diuretics, its blood pressure lowering effect is approximately additive.
Congestive heart failure
Administration of lisinopril to patients with congestive heart failure reduces afterload and preload of the heart, resulting in an increase in cardiac output, without reflex tachycardia. Exercise tolerance is improved.
In the Assessment of Treatment with Lisinopril and Survival Study (ATLAS) higher doses of lisinopril ≤ 35 mg once daily reduced the risk of the combined outcome of mortality and hospitalization in patients with chronic congestive heart failure (CHF). The ATLAS study was an international, multicenter, double-blind, parallel group clinical trial which evaluated the effects of low doses, 2.5 mg-5.0 mg, versus high doses, 32.5 mg-35.0 mg lisinopril on mortality and morbidity in patients with chronic CHF. A total of 1596 patients were randomized into the low dose and 1568 into the high dose groups. Patients entered into the ATLAS study were NYHA Class II, III, or IV, were treated with diuretics for at least 60 days prior to entry into the study, and had a left ventricular ejection fraction (LVEF) ≤ 30%. Class II patients were eligible only if they were hospitalized or received emergency room treatment in the previous 6 months. Prior treatment with ACE inhibitors and digoxin was permitted, and patients were permitted routine therapies, other than ACE inhibitors, for the duration of the study. The median follow-up period was 46 months. The protocol excluded patients with recent cardiac surgery, unstable coronary artery disease, unstable ventricular arrhythmias, unstable CHF, or a non-CHF disorder that may have limited survival during the course of the trial. Overall, 77% of patients were NYHA class III; 89% had previous ACE inhibitor treatment. For the principal secondary endpoint, all-cause mortality and all-cause hospitalization, high dose lisinopril was associated with an 11.6% (p=0.002) risk reduction over low dose (2.5 and 5 mg). High dose lisinopril was also associated with an 8.4% risk reduction in all-cause mortality and cardiovascular hospitalizations (p =0.036). The total number of hospitalizations per patient for heart failure was reduced by 23.2% (p=0.002).
Pharmacokinetics
Absorption:
After oral administration of lisinopril, peak serum concentrations of lisinopril occur within approximately 7 hours, although patients with recent myocardial infarction have demonstrated an increase in time to peak serum concentration to about 8 to 10 hours. Declining serum concentrations exhibit a prolonged terminal phase which does not contribute to drug accumulation. This terminal phase probably represents saturable binding to ACE and is not proportional to dose. Lisinopril does not bind serum proteins other than ACE.
Lisinopril does not undergo metabolism and is excreted unchanged entirely in the urine. Based on urinary recovery, the extent of absorption of lisinopril is approximately 25%, with large inter-subject variability (6-60% at all doses tested (5-80 mg).
Lisinopril absorption is not influenced by the presence of food in the gastrointestinal tract.
Following multiple doses of lisinopril, the effective half-life of accumulation is 12 hours.
Adults: In a study in elderly healthy subjects (≥65 years), a single dose of lisinopril 20 mg produced higher serum concentrations and higher values for the area under the plasma curve (AUC) than those seen in young healthy adults given a similar dose. In another study, single daily doses of lisinopril 5 mg were given for 7 consecutive days to young and elderly healthy volunteers and to elderly patients with CHF. Maximum serum concentrations of lisinopril on Day 7 were higher in the elderly volunteers than in the young, and still higher in the elderly patients with CHF. Renal clearance of lisinopril was decreased in the elderly, particularly in the presence of CHF.
Impaired renal function decreases elimination of lisinopril. This decrease becomes clinically important when the glomerular filtration rate (GFR) is <below 30 mL/min (see PRECAUTIONS, Renal Impairment, and DOSAGE AND ADMINISTRATION).
Lisinopril can be removed by dialysis.
Pediatrics (6-16 years old): The pharmacokinetics of lisinopril were studied in 29 pediatric hypertensive patients between 6 years and 16 years with GFR is >30 mL/min/1.73 m2. After doses of 0.1 to 0.2 mg/kg, steady state peak plasma concentrations of lisinopril occurred within 6 hours and the extent of absorption based on urinary recovery was about 28%. These values are similar to those obtained previously in adults. The typical value of lisinopril oral clearance (systemic clearance/absolute bioavailability) in a child weighing 30 kg is 10 L/h, which increases in proportion to renal function.
Studies in rats indicate that lisinopril crosses the blood-brain barrier poorly.
Hepatic Insufficiency:
No data is available (see WARNINGS AND PRECAUTIONS, Hepatic / Biliary / Pancreatic).
Genetic Polymorphism:
No data is available.
STORAGE AND STABILITY
Store between 15°C and 30°C.
DOSAGE FORMS, COMPOSITION AND PACKAGING
MYLAN-LISINOPRIL is supplied as 5 mg, 10 mg and 20 mg tablets for oral administration. In addition to the active ingredient lisinopril, each tablet contains the following inactive ingredients: corn starch, dibasic calcium phosphate, magnesium stearate, mannitol 60, talc and red iron oxide #30.
MYLAN-LISINOPRIL 5 mg tablets are a pink, oval, biconvex tablet, with “G” over “L5” on one side and scored on the one side. Available in bottles of 100 and 500 tablets.
MYLAN-LISINOPRIL 10 mg tablets are pink, oval, biconvex tablet, with “G” over “L10” on one side and plain on the other side. Available in bottles of 100 and 500 tablets.
MYLAN-LISINOPRIL 20 mg tablets are pink, oval, biconvex tablet, with “G” over “L20” on one side and plain on the other side. Available in bottles of 100 and 500 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Lisinopril
Chemical name: (S)-1-[N2-(1-Carboxy-3-phenylpropyl)-L-lysyl]-L-proline dihydrate
L-Proline, 1-[N2-(1-carboxy-3-phenylpropyl)-L-lysyl]-, dihydrate, (S)-;
1-[N2-[(S)-1-Carboxy-3-phenylpropyl]-L-lysyl]-L-proline dehydrate
Structural formula:
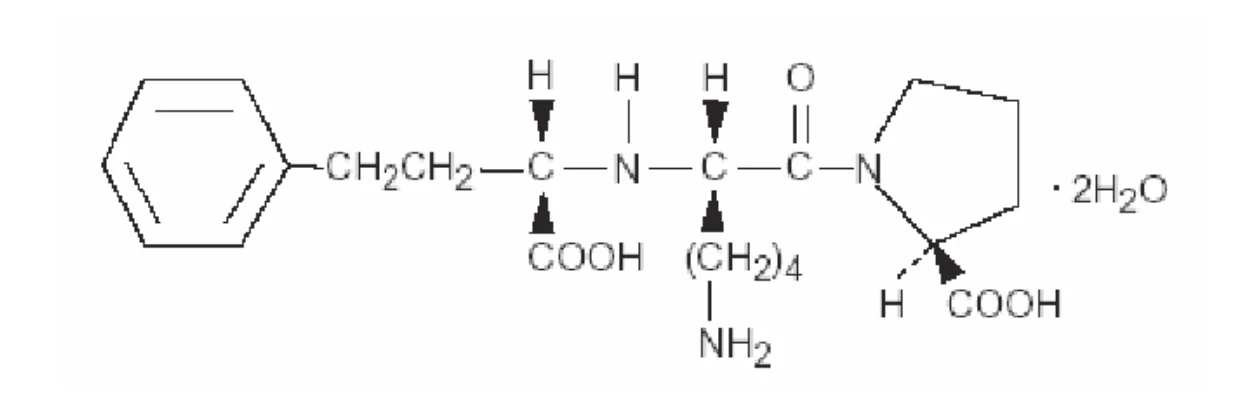
Molecular formula: C21H31N305.2H2O
Molecular mass: 441.52 g/mol
Description: Lisinopril is a white to off-white, crystalline powder. It is very soluble in water, sparingly soluble in methanol and practically insoluble in ethanol.
pH:
The pH is about 5.1 in a 1% aqueous solution at room temperature.
pKa:
Aqueous acidic/base potentiometric titration at 25°C yielded four pKa values:
pKa1 = 2.5
pKa2 = 4.0
pKa3 = 6.7
pKa4 = 10.1
CLINICAL TRIALS
Comparative Bioavailability Studies
Bioequivalence studies were performed to compare MYLAN-LISINOPRIL Tablets against Zestril® Tablets. Comparative bioavailability data have been submitted for the 5 mg and 20 mg strength. The studies performed were two-way, crossover, blinded, single-dose, fasting, bioequivalence studies of MYLAN-LISINOPRIL tablets versus Zestril® Tablets in 36 normal healthy non-smoking male subjects.
The pharmacokinetic data from these studies are presented in the following pages.
Lisinopril (1 x 5 mg) From measured data Uncorrected for potency Geometric Mean Arithmetic mean (CV %) | ||||
| Parameter | TEST* | REFERENCE† | % Ratio of Geometric Means | Confidence Interval (90%) |
| AUC0-72 (ng·hr/mL) | 303.66 323.35 (35.34) | 301.84 325.70 (39.23) | 99.72% | 92.46% to 107.55% |
AUCI (ng·hr/mL) | 338.53 356.62 (32.58) | 341.07 361.30 (34.73) | 99.25% | 93.00% - 105.93% |
Cmax (ng/mL) | 17.59 19.44 (42.37) | 17.40 19.54 (47.86) | 101.08% | 91.48% to 111.69% |
Tmax § (hr) | 8.00 (6.00-10.00) | 8.00 (6.00-10.00) | ||
T1/2 ║ (hr) | 23.71 (21.47) | 24.73 (34.42) | ||
* MYLAN-LISINOPRIL 5 mg Tablets (Mylan Pharmaceuticals ULC, Canada).
† Zestril® 5 mg Tablets (AstraZeneca Canada Inc.) was purchased in Canada.
§ Expressed as the median (range) only.
║ Expressed as the arithmetic mean (CV%) only.
Lisinopril (1 x 20 mg) From measured data Uncorrected for potency Geometric Mean Arithmetic mean (CV %) | ||||
| Parameter | TEST* | REFERENCE† | % Ratio of Geometric Means | Confidence Interval (90%) |
| AUC0-72 (ng·hr/mL) | 1256.27 1341.94 (36.04) | 1331.95 1399.56 (31.74) | 93.45% | 84.26% to 103.65% |
| AUCI (ng·hr/mL) | 1284.47 1364.49 (34.80) | 1333.55 1398.08 (31.25) | 96.33% | 87.52% to 106.02% |
Cmax (ng/mL) | 87.90 94.88 (37.69) | 91.32 96.68 (32.89) | 96.25% | 85.92% to 107.82% |
Tmax § (hr) | 7.50 (5.00-9.00) | 7.00 (4.00-9.00) | ||
T1/2 ║ (hr) | 13.50 (30.33) | 13.08 (32.11) | ||
* MYLAN-LISINOPRIL 20 mg Tablets (Mylan Pharmaceuticals ULC, Canada).
† Zestril® 20 mg Tablets (AstraZeneca Canada Inc.) was purchased in Canada.
§ Expressed as the median (range) only.
║ Expressed as the arithmetic mean (CV%) only.
DETAILED PHARMACOLOGY
Mechanism of Action
| Study | Species/Strain | Number of Animals/ Group | Route | Dose | Results |
|---|---|---|---|---|---|
| in vitro ACE inhibitory activity* | hog plasma | in vitro | IC50 = ± 0.5 nM | ||
| augmentation of contractile response to bradykinin | guinea pig ileum | 7 segments | in vitro | AC50 = 1.6 nM | |
| in vivo ACE inhibition in the rat** | male Sprague/Dawley | 8 | i.v. | ID50 = 2.3 (1.7-3.1) mcg/kg | |
| duration of ACE inhibitory activity of lisinopril in rats** | male Sprague/Dawley | 4 | i.v. | 3 & 10 mcg/kg | Duration approx. 110 min. |
| in vivo ACE inhibitory activity of lisinopril in conscious rats** | Sprague/Dawley | 3 - 5 | p.o. | 0.03-3.0 mg/kg (single dose) | Duration of at least 360 mins. |
| in vivo ACE inhibition in anesthetized dogs** | Mongrel | 6 | i.v. | 1-30 mcg/kg | ID50 = 6.5 mcg/kg |
| in vivo ACE inhibitory activity of lisinopril in conscious dogs** | Mongrel | 3 | p.o. | 0.05-1.0 mg/kg (single dose) | Duration of action of between 6-24 hrs. |
* Inhibition of enzymatic activity of hog plasma ACE using 14C labeled substrate.
** Blockage of functional (pressor) response to A1 challenge.
Effects on Blood Pressure
| Study | Species/Strain | Number of Animals/ Group | Route | Dose | Results |
|---|---|---|---|---|---|
| antihypertensive activity in renal hypertensive dogs (single doses) | Mongrel | 3 | p.o. | 0.3 mg/kg with and without hydro-chlorothiazide | After 2 hours: Lisinopril alone: 5% reduction in mean systolic pressure vs pretreatment. Lisinopril + HCTZ = 11% reduction in mean systolic pressure vs pretreatment. |
| antihypertensive activity in rats on a sodium-deficient diet | Male Sprague/Dawley | 5 | p.o. | 0.03-3.0 mg/kg daily for 4 days | After 2 hours: 11% reduction in mean systolic pressure vs pretreatment at 1 mg/kg. 22% reduction in mean systolic pressure vs pretreatment at 3 mg/kg. Consistent response over 4 days. |
| antihypertensive activity in 2 kidney Grollman hypertensive rats (single doses) | Male Sprague/Dawley | 6 – 7 | p.o. | 1 & 3 mg/kg | At 2 hours: approx. 6% reduction in mean systolic pressure vs pretreatment with the antihypertensive effect lasting up to 24 hours. |
| antihypertensive activity in spontaneously hypertensive rats with and without hydrochlorothiazide | SH rats | 3 – 6 | p.o. | 1.25 mg/kg HCTZ = 50 mg/kg daily for 3 days | Enhancement of hypotensive activity over 3-5 days. 2 hours after drug administration, lisinopril alone reduced the average mean arterial pressure from 198 to 161 mm Hg. In combination with HCTZ the average mean arterial pressure was reduced from 202 to 132 mm Hg. |
| antihypertensive activity in spontaneously hypertensive rats (single doses) | SH rats | 3 – 9 | p.o. & i.v. | 0.1-20 mg/kg | Slight fall in blood pressure at 0.312-5 mg/kg p.o. Pronounced fall at 20 mg/kg p.o. and 0.1 mg/kg i.v. with statistically significant reductions being observed for the majority of time points between 1/2-18 hours. |
MICROBIOLOGY
Not applicable.
TOXICOLOGY
Acute Toxicity of Lisinopril
LD50Values
| Route | Species | Sex | LD50 (g/kg) |
| Oral | Mouse | male | >20 |
| Mouse | female | >20 | |
| Rat | male | >20 | |
| Rat | female | >20 | |
| Dog | male | >6 | |
| Dog | female | >6 | |
| Intravenous | Mouse | male | >10 |
| Mouse | female | >10 | |
| Intraperitoneal | Rat | male | >10 |
| Rat | female | >10 |
Signs of toxicity: Following oral administration to mice decreased activity and one male death (1/10) occurred. No signs of toxicology occurred in rats after oral administration. Dogs given 6 g/kg had transient diarrhea and increases in serum urea nitrogen. Intravenous administration to mice produced bradypnea, ataxia, clonic convulsions, exophthalmia, and tremors. After intraperitoneal administration in rats, ataxia and one female death (1/10) occurred. No signs of toxicology or death occurred in the males.
Subacute/Chronic Toxicology
| Species | Duration | No. of Animal/Group | Route | Dose mg/kg/day | Effects |
|---|---|---|---|---|---|
| Rat | 2-week | 10 F + 10 M | Oral | 3,10,30 | At all doses, decreases of 2 to 16% in weight gain and 12 to 14% in heart weights were observed in female rats. |
| Rat | 3-month with 1-month Interim | 25 F + 25 M | Oral | 3,10,30 | At all doses, increased serum urea nitrogen values (up to approximately 2-fold) and decreased heart weights (7 to 10%) were observed in female rats. At 10 and 30 mg respectively weight gain decreased 11 to 14% in males. An increased incidence of focal erosions of the gastric mucosa and focal renal tubular basophilia were also seen. |
| Rat | 1-Year with 6-Month Interim | 25 F + 25 M | Oral | 2,5,10,30,90a | At all doses, a decrease in weight gain (up to 16%) was observed. Serum urea nitrogen increased up to 4-fold; serum sodium decreased (average down to 3 mEq/L) and serum potassium increased (average up to 0.5 mEq/L). At 2, 5, 10 and 30 mg heart weight decreased; at 5, 10 and 30 mg, kidney weight increased; and at 5, 10, 30 and 90 mg, renal tubular basophilia increased. At 10, 30 and 90 mg, focal interstitial nephritis was observed. |
| Rat | 3-Month with a 1-Month Interim and a 1-Month Recovery | 30 F + 30 M | Oral | 3,30,300, 3000 | At all doses, weight gain decreased by 5 to 11%, and increases were observed in serum urea nitrogen (up to approximately 3-fold) and serum potassium (average up to 0.4 mEq/L). At 30, 300 and 3000 mg there was an increased incidence of focal tubular basophilia persisted in rats given 300 or 3000 mg/kg/day. |
| Rat | 1-Month | 15 F + 15 M | Oral | 30,60 30,60 (with saline) | Saline supplementation prevented decreased weight gain and elevations in serum urea nitrogen at 30 and 60 mg. Decreases in cardiac weight at 30 and 60 mg, were suppressed by saline supplementation in males at 30 mg. At 30 and 60 mg renal changes produced due to a low salt diet, (renal tubular degeneration and renal tubular basophilia) were prevented by saline supplementation. Mild gastric erosions or necrotic changes were seen in 1 or 2 of 30 rats given 30 or 60 mg. These gastric changes were not seen in saline supplemented animals given these doses; however, the relationship of amelioration due to saline is uncertain because of the low incidence of this change, which is also occasionally seen in untreated animals. |
| Species | Duration | No. of Animal/Group | Route | Dose mg/kg/day | Effects |
|---|---|---|---|---|---|
| Rat | 5 Days 6 Day Recovery | 8 M | Oral | 5, 300 | Consumption of 2% saline increased during treatment at 5 mg and on Days 2 to 4 post-treatment at 300 mg. |
a Dosing terminated Week 11, rats killed Week 27.
Subacute/Chronic Toxicology (continued)
| Species | Duration | No. of Animal/Group | Route | Dose mg/kg/day | Effects |
|---|---|---|---|---|---|
| Dog | 2-week | 3 F + 3 M | Oral | 3,10,30 | At 30 mg, slight mineralization of the papilla muscle of the heart was seen in 1 of 6 dogs. |
| Dog | 3-Month with 1-Month Interim | 5 F + 5 M | Oral | 3,10,30 | At 10 mg, hemoglobin concentration, hematocrit, and erythrocyte count decreased in 2 dogs. Marked increases in serum urea nitrogen and creatinine were observed in 2 of 10 dogs. One of these dogs had marked renal tubular degeneration and ulcers of the tongue, gums, and gastric pyloric mucosa related to uremia. At 30 mg there was an increase in serum urea nitrogen (average up to 2-fold) and a decrease in serum sodium (down to 4 mEq/L) and serum chloride (down to 3 mEq/L). At 10 and 30 mg, average cardiac weight decreased (13 to 15%). |
| Dog | 1-Year with 6-Month Interim | 5 F + 5 M | Oral | 3,5,15 | At 15 mg, increases were observed in serum urea nitrogen (less than 2-fold). Decreases in serum sodium (average down to 2 mEq/L) and increases in serum potassium (average up to 0.5 mEq/L) occurred at all doses. |
| Dog | 18-Day | 3 F + 3 M | Oral | 60/90 with and without saline | Saline supplementation prevented increases in serum urea nitrogen in dogs given 60 mg for 8 days followed by 90 mg for 8 or 9 days. |
| Dog | 7-Day | 4 F + 4 M | i.v. | 60,90 | Decreases in blood pressure and increases in serum urea nitrogen occurred in dogs given 60 or 90 mg/kg/day. Supplementation with physiologic saline (25 mL/kg one hour prior to dosing and 4 hours after dosing) prevented these changes. Increased serum potassium (average up to 0.6 mEq/L) and decreased serum chloride (average down to 0.4 mEq/L) values were seen in both supplemented and unsupplemented animals. |
| Dog | 1-Month | 2 F + 2 M | Oral | 3,30,300 and 1000 | At 30 mg or greater, BUN increased and specific gravity of the urine decreased. Hyperplasia of renal epithelial cells was observed and deaths occurred. Dogs that died had dilation of distal renal tubules and fatty degeneration epithelium. No drug-related effects were observed at 3 mg. |
Subacute/Chronic Toxicology (continued)
| Species | Duration | No. of Animal/Group | Route | Dose mg/kg/day | Effects |
|---|---|---|---|---|---|
| Dog | 3-Month with 1-Month Recovery (high dose) | Control 5 M + 5 F 3, 10 & 30 mg/kg/day 3 M + 3 F 100 mg/kg/day 8 M + 8 F Recovery Control 2 M + 2 F 100 mg/kg/day 5 M + 5 F | Oral | 3,10,30 and 100 | Eight of 16 dogs given 100 mg died or were killed because of poor physical condition. One of 6 dogs given 30 mg was killed because of poor physical condition. At 10 mg or greater increased BUN and dilation of renal tubules was seen. Fatty degeneration of renal tubular epithelium occurred at the 2 highest dosage levels. The changes are reversible as only slight dilation of renal tubules was present in some animals given 100 mg after 4 weeks of recovery. |
| Rabbit | 2-Weeks | 6 F | Oral | 15 (1,6 & 13 doses) with and without saline | Renal tubular basophilia and renal tubular dilation (considered sequela to necrosis) were seen after 6 and 13 doses in unsupplemented rabbits. Two supplemented rabbits (6 doses) also had the same renal lesion. One rabbit drank very little saline and had increases in BUN, creatinine, and potassium. Increases in these parameters were seen in unsupplemented animals after 1, 6, and 13 doses. |
Teratology Studies
| Species | No. of Animal/Group | Dose mg/kg/day | Route | Duration of Dosing | Results |
|---|---|---|---|---|---|
| Mice | 25 | 100,300, 1000, 1000 with saline | Oral | Day 6 through Day 15 of gestation | No teratogenic effect was observed. There was an increased incidence of resorptions in all unsupplemented groups (no increase in serum urea nitrogen). |
| Rat | 35 | 30,100, 300, 300 with saline | Oral | Day 6 through Day 17 of gestation | No teratogenic effect was observed. Maternal effect was observed. Maternal weight gain decreased in all unsupplemented groups. The open field behavioral test (measure of spontaneous activity) showed increased activity in Week 5 postpartum F1 females at 300 mg with and without saline, but only in 300 mg with saline females in Week 6. When the open field test was repeated in males and females given 300 mg with and without saline in Week 11, no increase in activity was seen. |
| Rabbit (New Zealand) | 18 | 0.1, 0.3, 1.0 all groups with saline | Oral | Day 6 through Day 18 of gestation | No teratogenic effect was observed. At all doses there was an increased incidence of incomplete ossification (sternebrae, metacarpals, forefoot phalanges, pelvic bones and tali and/or calcanea) which was considered to represent a fetotoxic effect. At 1 mg one rabbit had a high incidence of resorptions. |
| Rabbit (New Zealand | 18 | 0.031, 0.125, 0.5 | Oral | Day 6 through Day 18 of gestation | No fetotoxicity, nor embryotoxicity was observed at maternotoxic doses. At 0.125 and 0.5 mg maternal deaths, decreased maternal weight gain and food consumption, as well as increases in BUN, creatinine and potassium were seen. In addition, doses of 0.5 mg produced decreases in serum sodium and chloride diffuse distention of the renal distal tubules and degeneration of renal tubules. |
Fertility and Late Gestation and Lactation with Postnatal Evaluation Studies
| Species | No. of Animal/Group | Route | Dose mg/kg/day | Duration of Dosing | Results |
|---|---|---|---|---|---|
| Rat | 24 F & 24 M | Oral | 30,100, 300 300 with saline | Males were dosed for 78 days prior to mating and females from 15 days prior to mating until sacrifice on Day 20 of gestation | Weight gain was reduced in unsupplemented males at all doses and during gestation in unsupplemented females. No effects on fertility and no signs of teratogenicity were observed. There was an increase in F1 pup deaths (3 to 8% vs control 1%) Day 1 to 7 postpartum in 100 and 300 mg (saline and nonsaline) groups. Decreased mean F1 pup weight (3 to 7% less than controls) on Day 0 postpartum was seen in all unsupplemented groups. |
| Rat | 20F | Oral | 30,100, 300 300 with saline | Day 15 of gestation through Day 21 postpartum | On Days 2 to 7 postpartum there was an increased number of dead pups (8 to 10% vs. Control 0%). On Day 21 postpartum, a decrease in pup weights (8% less than controls) was observed in the unsupplemented 100 and 300 mg groups. There was no effect in the supplemented group. Pup development was not altered. |
Genotoxicity Studies
| Study | Test System | Dose | Results |
|---|---|---|---|
Mutagenesis Microbial mutagen with and without metabolic activation | Salmonella typhimurium TA1535, TA1537, TA98, TA100 Escherichia coli WP2, WP2 uvrA | ≤ 2000 μg/plate ≤ 10 mg/plate | Negative for mutagenic potential. |
| In vitro V-79 mammalian cell mutagenesis with and without metabolic activation | Chinese Hamster Lung Cell | ≤ 10 mM (4.42 mg/mL) | Negative for mutagenic potential. |
DNA Damage In vitro alkaline elution | Rat Hepatocyte | ≤ 30 mM (13.25 mg/mL) | Negative for induction of DNA single strand breaks. |
Chromosomal Evaluation In vitro chromosomal aberration assay with and without metabolic activation | Chinese Hamster Ovary | ≤ 30 mM (13.25 mg/mL) | Negative for induction of chromosomal aberration. |
| In vivo chromosomal aberration assay | Bone Marrow Cells of Male Mice | ≤ 5000 mg/kg | Negative for increases in chromosomal aberrations. |
Carcinogenicity Studies
| Species | Duration of Dosing | No. of Animal/Group | Route | Dose mg/kg/day | Results |
|---|---|---|---|---|---|
Mice Cri:CD-1 (ICR) BR | 92 weeks | 50 F & 50 M | Oral | 15,45,135 mg/kg/day | No evidence of carcinogenic effect was observed. Decreased weight gain (7 to 15%) was seen in females at 135 mg. A greater incidence and severity of chronic nephritis in females and males given 45 and 135 mg was also seen. |
Rats Cri:CD (SD) BR | 105 weeks | 50 F & 50 M | Oral | 10,30,90 mg/kg/day | No evidence of carcinogenic effect was observed. Decreased weight gain (5 to 14%) in male drug-treated rats during the first 67 weeks of the study was observed. Focal sacculations of the retinal vessels was more prevalent in rats given 30 or 90 mg than in controls in Drug Week 100. An increased incidence of renal tubular hypertrophy in drug-treated males was seen at termination of the study (1 mg was considered the no-effect dose for this change in males based on an additional 105 week study at 1, 3, and 10 mg/kg/day). An increased incidence of chronic nephritis in drug-treated females (10 mg is the no-effect dose based on an additional 105 week study at 1, 3, and 10 mg/kg/day) was observed. |
REFERENCES
- 1.
Ajayi AA, Campbell BC, Howie CA, Reid JL.
Acute and chronic effects of the converting enzyme inhibitors enalapril and lisinopril on reflex control of heart rate in normotensive man. J Hypertens 1985;3:47-53.
- 2.
Biollaz J, Burnier M, Turini GA, Brunner DB, Porchet M, Gomez HJ, Jones KH, Feber
F, Abrams WB, Gavras H, Brunner HR.
Three new long-acting converting-enzyme inhibitors: relationship between plasma converting-enzyme activity and response to angiotensin I. Clin Pharmacol Ther 1981;29:665-670.
- 3.
Biollaz J, Schelling JL, Jacot des Combes B, Brunner DB, Desponds G, Brunner HR,
Ulm EH, Hichens M, Gomez HJ.
Enalapril maleate and a lysine analogue (MK-521) in normal volunteers: Relationship between plasma drug levels and the renin angiotensin system. Br J Clin Pharmacol 1982;14:363-368.
- 4.
Brunner DB, Desponds G, Biollaz J, Keller I, Feber F, Gavras H, Brunner HR, Schelling JL.
Effect of a new angiotensin converting enzyme inhibitor MK-421 and its lysine analogue on the components of the renin system in healthy subjects.
Br J Clin Pharmacol 1981;11:461-467.
- 5.
Bussien JP, Waeber B, Nussberger J, Gomez HJ, Brunner HR.
Once-daily lisinopril in hypertensive patients: Effect on blood pressure and the renin- angiotensin system. Current Therapeutic Research 1985;37:342-351.
- 6.
Chalmers JP, West MJ, Cyran J, De La Torre D, Englert M, Kramar M, Lewis GRJ, Maranhao MFL, Myburgh DP, Schuster P, Sialer S, Simon H, Stephens JD, Watson RDS.
Placebo-controlled study of lisinopril in congestive heart failure: A multicenter study. J Card Pharmacol 1987;9(Suppl 3):S82-S88.
- 7.
Cirillo VJ, Gomez HJ, Salonen J, Salonen R, Rissanen V, Bolognese JA, Nyberg R, Kristianson K.
Lisinopril: dose-peak effect relationship in essential hypertension.
Br J Clin. Pharmac 1988;25:533-538.
- 8.
Derkx FHM, Millar JA, Reid JL, Schalekamp MADH.
Pharmacodynamics of MK421 (enalapril) and its lysine analogue MK521.
Progress in Pharmacol 1984;5:93-105.
- 9.
Donohue JF, Kelly J, Laher MS, Doyle GD.
Lisinopril in the treatment of hypertensive patients with renal impairment.
Am J Med 1988;85(Suppl 3B):31-34.
- 10.
Giles TD, Katz R, Sullivan JM, Wolfson P, Haugland M, Kirlin P, Powers E, Rich S, Hackshaw B, Chiaramida A, Rouleau JL, Fisher MB, Pigeon J, Rush JE.
Short- and long-acting angiotensin-converting enzyme inhibitors: A randomized trial of lisinopril versus captopril in the treatment of congestive heart failure. J Am Coll Cardiol 1989;13(6):1240-1246.
- 11. GISSI-3 Gruppo Italiano per lo Studio della Sopravvivenza ell'Infarto Miocardico. GISSI-3: effects of lisinopril and transdermal glyceryl trinitrate singly and together on 6-week mortality and ventricular function after acute myocardial infarction. Lancet 1994;343:1115-1122.
- 12.
Laher MS, Natin D, Rao SK, Jones RW, Carr P.
Lisinopril in elderly patients with hypertension. J Card Pharmacol 1987;9(Suppl 3) S69-S71.
- 13. Massie BM, Cleland GFJ, Armstrong PW, Packer M, Poole-Wilson PA, Ryden L, for the Assessment of Treatment with Lisinopril and Survival (ATLAS) trial investigators. Regional differences in the characteristics and treatment of patients participating in an international heart failure trial. Journal of Cardiac Failure 1998;4:3-8.
- 14.
Millar JA, Derkx FHM, McLean K, Reid JL.
Pharmacodynamics of converting enzyme inhibition: The cardiovascular endocrine and autonomic effects of MK-421 (enalapril) and MK-521. Br J Clin Pharmacol 1982;14:347-355.
- 15.
Myers MG, Carruthers SG, Leenen FHH, Haynes RB.
Recommendations from the Canadian Hypertension Society Consensus Conference on the pharmacologic treatment of hypertension. CMAJ 1989;140:1141-1146.
- 16. Powers ER, Chiaramida A, DeMaria AN, Giles TD, Hackshaw B, Hart W, Haugland M, Johnston R, Katz R, Kirlin P, McCall M, Mohiuddin S, Rich S, Sullivan JM, Wolfson P and Co-investigators. A double-blind comparison of lisinopril with captopril in patients with symptomatic congestive heart failure. J Card Pharmacol 1987;9(Suppl 3):S82-S88.
- 17. Rotmensch HH, Vlasses PH, Swanson BN, Irvin JD, Harris KE, Merrill DD, Ferguson RD. Antihypertensive efficacy of once daily MK-521, a new nonsulfhydryl angiotensin-converting enzyme inhibitor. Am J Cardiol 1984;53(1):116-119.
- 18. Product Monograph for Zestril® (lisinopril tablets, USP) 5, 10 and 20 mg tablets, AstraZeneca Canada Inc. Date of Revision: , February 24 2016, Control No. 187922 .