


Product Monograph - Mylan-Perindopril Arginine
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Non Medicinal Ingredients |
| Oral | Tablet / 2.5 mg, 5 mg and 10 mg | FD&C blue #1 (5 mg and 10 mg), iron oxide yellow (5 mg and 10 mg), lactose monohydrate, magnesium stearate, maltodextrin, polyvinyl alcohol, povidone, quinoline yellow aluminium lake (5 mg and 10 mg), silica, sodium starch glycolate, soya lecithin, talc, titanium dioxide and xanthan gum. |
INDICATIONS AND CLINICAL USE
MYLAN-PERINDOPRIL ARGININE (perindopril arginine) is indicated for:
Hypertension
- The treatment of mild to moderate essential hypertension. It may be used alone or in association with other drugs, particularly thiazide diuretics.
The safety and efficacy of perindopril arginine in renovascular hypertension have not been established and therefore, its use in this condition is not recommended.
The safety and efficacy of concurrent use of perindopril arginine with antihypertensive agents, other than amlodipine and thiazide diuretics, have not been established.
Congestive Heart Failure
The treatment of mild to moderate congestive heart failure, generally as adjunctive therapy to diuretics, and where appropriate a digitalis glycoside.
- Treatment should be initiated under close medical supervision. The safety and efficacy of perindopril arginine have not been demonstrated for New York Heart Association Category IV patients.
Hypertensive and/or post-MI patients with stable coronary artery disease.
- The reduction of cardiovascular risk in patients with hypertension or post-myocardial infarction and stable coronary disease.
Perindopril erbumine has been demonstrated to reduce the risk of cardiovascular death, non-fatal myocardial infarction, and cardiac arrest in mild or moderately hypertensive patients with stable coronary artery disease, or in patients with a previous (>3 months ago) myocardial infarction and stable coronary artery disease, including patients with previous revascularization when administered as an add-on to conventional treatment such as platelet inhibitors, beta blockers, lipid-lowering agents, nitrates, calcium channel blockers or diuretics.
See DOSAGE AND ADMINISTRATION.
Geriatrics (>65 years of age)
Although clinical experience has not identified significant differences in response between the elderly (>65 years) and younger patients, greater sensitivity of some older individuals cannot be ruled out.
Pediatrics
The safety and effectiveness of perindopril arginine in children have not been established. Its use in this age group, therefore, is not recommended.
CONTRAINDICATIONS
MYLAN-PERINDOPRIL ARGININE (perindopril arginine) is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation. For a complete listing (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
- Patients with a history of hereditary/idiopathic angioedema, or angioedema related to previous treatment with an angiotensin converting enzyme inhibitor (see WARNINGS and PRECAUTIONS, General).
- Women who are pregnant, intend to become pregnant, or of childbearing potential who are not using adequate contraception (see WARNINGS and PRECAUTIONS, Special Populations, Pregnant Women).
- Nursing women (see WARNINGS AND PRECAUTIONS, Special Populations, Nursing Women).
- Patients with hereditary problems of galactose intolerance, glucose-galactose malabsorption, or the Lapp lactase deficiency as MYLAN-PERINDOPRIL ARGININE contains lactose (see WARNINGS AND PRECAUTIONS, Sensitivity/ Resistance).
- Combination with sacubitril/ valsartan due to an increased risk of angioedema.
- Combination with angiotension converting enzyme (ACE) inhibitors, including perindopril arginine, with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or 2) or moderate to severe renal impairment (GFR <60ml/min/1.73m2) (see WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) and Renal, and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs).
- Patients with extracorporeal treatments leading to contact of blood with negatively charged surfaces (see DRUG INTERACTIONS),
- Patients with bilateral renal artery stenosis or renal artery stenosis in a single functioning kidney (see WARNINGS AND PRECAUTIONS, Renal).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions When used in pregnancy, angiotensin converting enzyme (ACE) inhibitors can cause injury or even death of the developing fetus. When pregnancy is detected, MYLAN-PERINDOPRIL ARGININE should be discontinued as soon as possible. |
General
Driving a vehicle or performing other hazardous tasks
Perindopril can have minor or moderate influence on the ability to drive and use machines. If patients suffer from dizziness, headache, fatigue, weariness or nausea, the ability to react may be impaired. Caution is recommended with MYLAN-PERINDOPRIL ARGININE especially at the start of treatment.
Head and neck angioedema
Life-threatening angioedema has been reported with ACE inhibitors. The overall incidence is approximately 0.1-0.2%. The aetiology is thought to be non-immunogenic and may be related to accentuated bradykinin activity. Usually, the angioedema is non-pitting edema of the skin mucous membrane and subcutaneous tissue.
Angioedema involving the face, extremities, lips, tongue, glottis and/or larynx has been reported in patients treated with ACE inhibitors, including perindopril erbumine. Angioedema associated with laryngeal involvement may be fatal. If laryngeal stridor or angioedema of the face, tongue, or glottis occurs, MYLAN-PERINDOPRIL ARGININE should be discontinued immediately, the patient treated appropriately in accordance with accepted medical care, and carefully observed until the swelling disappears. In instances where swelling is confined to the face and lips, the condition generally resolves without treatment, although antihistamines may be useful in relieving symptoms. Where there is involvement of the tongue, glottis or larynx, angioedema may be fatal due to airway obstruction, appropriate therapy (including but not limited to 0.3 to 0.5 ml of subcutaneous epinephrine solution 1:1000 and oxygen) should be administered promptly (see ADVERSE REACTIONS).
Treatment of progressive angioedema should be aggressive. Failing a rapid response to medical therapy, mechanical methods to secure an airway should be used before massive edema complicates oral or nasal intubation.
Patients who respond to medical treatment should be observed carefully for a possible rebound phenomenon.
The onset of angioedema associated with use of ACE inhibitors may be delayed for weeks or months.
Patients may have multiple episodes of angioedema with long symptom-free intervals. Angioedema may occur with or without urticaria.
The incidence of angioedema during ACE inhibitor therapy has been reported to be higher in black than in non-black patients.
There are reports that switching a patient to another ACE inhibitor could be followed by a recurrence of angioedema. Because of the potential severity of this rare event, another ACE inhibitor should not be used in patients with a history of angioedema (see CONTRAINDICATIONS).
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see CONTRAINDICATIONS).
Concomitant use of mTOR inhibitors, DPP-IV inhibitors and NEP inhibitors
Patients taking a concomitant mTOR inhibitor (e.g. sirolimus, everolimus, temsirolimus), DPP-IV inhibitor (e.g. sitagliptin) or neutral endopeptidase (NEP) inhibitor may be at increased risk for angioedema. Caution should be used when initiating ACE inhibitor therapy in patients already taking an mTOR, DPP-IV or NEP inhibitor or vice versa (see DRUG INTERACTIONS).
Intestinal Angioedema
Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. Angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor. Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain.
Cardiovascular
Stable coronary artery disease
If an episode of unstable angina pectoris (major or not) occurs during the first month of perindopril treatment, a careful appraisal of the benefit/risk should be performed before treatment continuation.
Hypotension
Perindopril erbumine can cause symptomatic hypotension. Perindopril erbumine has been associated with hypotension in 0.3% of uncomplicated hypertensive patients in U.S. placebo-controlled trials. Symptoms related to orthostatic hypotension were reported in another 0.8% of patients. It is more likely to occur after the first or second dose or when the dose is increased and in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhoea, or vomiting or with impaired renal function. Volume and/or salt depletion should be corrected before initiation of therapy with perindopril arginine (see DOSAGE AND ADMINISTRATION). In patients with ischemic heart or cerebrovascular disease and/or severe congestive heart failure, with or without associated renal insufficiency, ACE inhibitors may cause an excessive fall in blood pressure which could result in syncope, a myocardial infarction, neurological deficits, oliguria and/or progressive azotemia and, rarely, in acute renal failure and/or death (see ADVERSE REACTIONS).
In all high-risk patients it is advisable to initiate treatment with perindopril arginine 2.5 mg.
Because of the potential fall in blood pressure in these patients, therapy with perindopril arginine should be started under very close medical supervision. Such patients should be followed closely for the first two weeks of treatment and whenever the dose of perindopril arginine and/or diuretic is increased.
In controlled studies versus placebo and other ACE inhibitors, the first administration of 2 mg of perindopril erbumine in patients with mild-moderate heart failure was not associated with any significant reduction in blood pressure as compared to placebo (see ACTIONS AND CLINICAL PHARMACOLOGY - Pharmacodynamics).
If hypotension occurs, the patient should be placed in a supine position and, if necessary, receive an intravenous infusion of 0.9% sodium chloride. A transient hypotensive response is not a contraindication to further doses which usually can be given without difficulty once the blood pressure has increased after volume expansion. However, lower doses of perindopril arginine and/or reduced concomitant diuretic therapy should be considered.
Aortic Stenosis/Hyperthrophic Cardiomyopathy
As with other ACE inhibitors, perindopril arginine should be given with caution to patients with mitral valve stenosis and obstruction in the outflow of the left ventricle such as aortic stenosis or hypertrophic cardiomyopathy. There is concern on theoretical grounds that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators including ACE inhibitors because they do not develop as much afterload reduction. Vasodilators may tend to drop diastolic pressure, and hence coronary pressure, without producing the concomitant reduction in myocardial oxygen demand that normally accompanies vasodilation.
Dual blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin converting enzyme (ACE) inhibitors, such as perindopril arginine, or of angiotensin receptor antagonists (ARBs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR <60 ml/min/1.73m2). Therefore, the use of perindopril arginine in combination with aliskiren-containing drugs is contraindicated in these patients (see CONTRAINDICATIONS).
Further, co-administration of ACE inhibitors, including perindopril arginine, with other agents blocking the RAS, such as ARBs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia.
Primary aldosteronism
Patients with primary aldosteronism generally will not respond to anti-hypertensive drugs acting through inhibition of the RAS. Therefore, the use of MYLAN-PERINDOPRIL ARGININE is not recommended in these patients.
Hematologic
Neutropenia/ Agranulocytosis/ Thrombocytopenia/ Anaemia:
Neutropenia/ agranulocytosis, thrombocytopenia and anaemia have been reported in patients receiving ACE inhibitors. In patients with normal renal function and no other complicating factors, neutropenia occurs rarely. Perindopril should be used with extreme caution in patients with collagen vascular disease such as systemic lupus erythematosus or scleroderma, and those on multiple drug therapy with agents known to be nephrotoxic or myelosuppressive (immunosuppressant therapy, treatment with allopurinol or procainamide), or a combination of these complicating factors, especially if there is pre-existing impaired renal function. Some of these patients developed serious infections, which in a few instances did not respond to intensive antibiotic therapy (see WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests). Patients should be instructed to report any sign of infection.
Hepatic
Hepatic Failure
Rarely, ACE inhibitors have been associated with a syndrome that starts with cholestatic jaundice and progresses to fulminant hepatic necrosis and (sometimes) death. The mechanism of this syndrome is not understood. Patients receiving ACE inhibitors who develop jaundice or marked elevations of hepatic enzymes should discontinue the ACE inhibitor and receive appropriate medical follow-up.
Immune
Anaphylactoid Reactions during Membrane Exposure (hemodialysis patients)
Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes (e.g. polyacrylonitrile [PAN]) and treated concomitantly with an ACE inhibitor. Dialysis should be stopped immediately if symptoms such as nausea, abdominal cramps, burning, angioedema, shortness of breath and severe hypotension occur. Symptoms are not relieved by antihistamines. In these patients, consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agents.
Anaphylactoid Reactions during LDL Apheresis
Rarely, patients receiving ACE inhibitors during low density lipoprotein apheresis with dextran sulfate absorption have experienced life-threatening anaphylactoid reactions. These reactions were avoided by temporarily withholding the ACE inhibitor therapy prior to each apheresis.
Anaphylactoid Reactions during Desensitization
There have been isolated reports of patients experiencing sustained, life-threatening anaphylactoid reactions while receiving ACE inhibitors during desensitization treatment with hymenoptera (bees, wasps) venom. In the same patients, these reactions have been avoided when ACE inhibitors were temporarily withheld for at least 24 hours, but they reappeared upon inadvertent rechallenge.
Nitritoid Reactions – Gold
Nitritoid reactions (symptoms include facial flushing, nausea, vomiting, and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including perindopril arginine (see DRUG
INTERACTIONS).
Peri-Operative Considerations
ACE inhibitors may augment the hypotensive effects of anaesthetics and analgesics. In patients undergoing major surgery or during anaesthesia with agents that produce hypotension, perindopril arginine will block the angiotensin II formation that could otherwise occur secondary to compensatory renin release. The treatment should be discontinued one day prior to the surgery. If hypotension occurs and is considered to be due to this mechanism, it can be corrected by volume expansion.
Renal
Impaired Renal Function
As a consequence of inhibiting the renin-angiotensin-aldosterone system (RAAS), changes in renal function may be anticipated in susceptible individuals.
In cases of renal impairment (creatinine clearance <60 ml/min) the initial perindopril dosage should be adjusted according to the patient’s creatinine clearance and then as a function of the patient’s response to treatment. Routine monitoring of potassium and creatinine are part of normal medical practice for these patients (see WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
The use of ACE inhibitors, including perindopril arginine, or ARBs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR < 60 ml/min/1.73m2). (See CONTRAINDICATIONS and DRUG INTERACTIONS, Dual Blockade of the ReninAngiotensin-System (RAS) with ARBs, ACE inhibitors, or aliskiren-containing drugs).
Hypertensive Patients with Congestive Heart Failure
In patients with severe congestive heart failure, where renal function may depend on the activity of the RAAS, treatment with ACE inhibitors, including perindopril arginine, may be associated with oliguria and/or progressive azotemia, and rarely with acute renal failure and/or death.
In patients with symptomatic heart failure, hypotension following the initiation of therapy with ACE inhibitors may lead to some further impairment in renal function. Acute renal failure, usually reversible, has been reported in this situation.
Hypertensive Patients with Renal Artery Stenosis
In clinical trials in hypertensive patients with unilateral or bilateral renal artery stenosis, increases in blood urea nitrogen and serum creatinine were observed in 20% of patients. Experience with ACE inhibitors suggests that these increases are usually reversible upon discontinuation of the drug. In such patients, renal function should be monitored during the first few weeks of therapy. ACE inhibitors should be avoided in patients with known or suspected renal artery stenosis. When an ACE inhibitor is given to a patient with stenosis of the renal artery supplying a solitary kidney, or bilateral artery stenosis, acute renal insufficiency may occur. ACE inhibition may also cause a decrease in renal function in patients with stenosis of the artery supplying a transplanted kidney. It is believed that renal artery stenosis reduces the pressure in the afferent glomerular arteriole, and transglomerular hydrostatic pressure is then maintained by angiotensin II- induced constriction of the efferent arteriole. When an ACE inhibitor is given, the efferent arteriole relaxes, glomerular filtration falls, and renal failure may result. The thrombotic occlusion of a stenosed renal artery can be precipitated by ACE inhibitors (see WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests).
Some hypertensive patients without apparent pre-existing renal vascular disease have developed increases in blood urea nitrogen and serum creatinine, usually minor and transient. These increases are more likely to occur in patients treated concomitantly with a diuretic and in patients with pre-existing renal impairment. Reduction of dosages of perindopril arginine, the diuretic or both may be required. In some cases, discontinuation of either or both drugs may be necessary. Evaluation of hypertensive patients should always include an assessment of renal function (see DOSAGE AND ADMINISTRATION). If deterioration in renal function has occurred after treatment with one ACE inhibitor, then it is likely to be precipitated by another and in these patients usage of another class of antihypertensive agent would be preferable. Patients with unilateral renal artery disease present a special problem as deterioration of function may not be apparent from measurement of blood urea and serum creatinine.
Proteinuria
Some ACE inhibitors have been associated with the occurrence (up to 0.7%) of proteinuria (<1 gram / 24 hours) and/or decline in renal function in patients with one or more of the following characteristics: old age, pre-existing renal disease, concomitant treatment with potassium-sparing diuretics or high doses of other diuretics, limited cardiac reserve, or treatment with a non-steroidal anti-inflammatory drug.
Perindoprilat, the active form of perindopril, is dialysable with a clearance of 70 ml/min (see DOSAGE AND ADMINISTRATION).
Hyperkalemia and agents increasing serum potassium
In clinical trials, hyperkalemia (serum potassium >5.5 mEq/L) occurred in approximately 2.2% of the hypertensive patients compared to 1.4% in placebo (see ADVERSE REACTIONS). In most cases, these were isolated values which resolved despite continued therapy. In controlled studies, no patient discontinued therapy due to hyperkalemia.
Risk factors for development of hyperkalemia may include renal impairment, worsening of renal function, diabetes mellitus, elderly patients, intercurrent events, in particular dehydration, acute cardiac decompensation, metabolic acidosis and the concomitant use of potassium-sparing diuretic (e.g. spironolactone, eplerenone, triamterene, or amiloride), potassium supplements, potassium-containing salt substitutes or any drugs associated with increase in serum potassium (e.g. aliskiren, NSAIDs, heparin, cyclosporine, tacrolimus, trimethoprim and fixed dose combination with sulfamethoxazole, angiotensin receptor blockers) which should be used cautiously, if at all, with perindopril arginine (see DRUG INTERACTIONS, Drug-Drug Interactions). The use of potassium supplements, potassium-sparing diuretics, or potassium-containing salt substitutes particularly in patients with impaired renal function may lead to a significant increase in serum potassium. Hyperkalemia can cause serious, sometimes fatal arrhythmias. In some patients hyponatremia may co-exist with hyperkalemia (see WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests). If concomitant use of the above mentioned agents is deemed appropriate, regular monitoring of serum potassium and urea is recommended.
Renovascular hypertension
There is an increased risk of hypotension and renal insufficiency when patient with bilateral renal artery stenosis or stenosis of the artery to a single functioning kidney are treated with ACE inhibitors (see CONTRAINDICATIONS). Treatment with diuretics may be a contributory factor. Loss of renal function may occur with only minor changes in serum creatinine even in patients with unilateral renal artery stenosis.
Respiratory
Cough
A dry, persistent cough, which usually disappears only after withdrawal or lowering of the dose of perindopril erbumine has been reported. Such possibility should be considered as part of the differential diagnosis of the cough.
The cough is often worse when lying down or at night, and has been reported more frequently in women (who account for 2/3 of the reported cases). Patients who cough may have increased bronchial reactivity compared with those who do not. The observed higher frequency of this side-effect in non-smokers may be due to a higher level of tolerance of smokers to cough.
The cough is most likely due to stimulation of the pulmonary cough reflex by kinins (bradykinin) and/or prostaglandins, which accumulate because of ACE inhibition. Once a patient has developed intolerable cough, an attempt may be made to switch the patient to another ACE inhibitor; the reaction may recur but this is not invariably the case. A change to another class of drugs may be required in severe cases.
Sensitivity/ Resistance
Due to the presence of lactose, patients with hereditary problems of galactose intolerance, glucose-galactose malabsorption or the Lapp lactase deficiency should not take MYLAN-PERINDOPRIL ARGININE.
Skin
Dermatological reactions characterised by maculo-papular pruritic rashes and sometimes photosensitivity has been reported with another ACE inhibitor. Rare and sometimes severe skin reactions (lichenoid eruptions, psoriasis, pemphigus like rash, rosacea, Stevens-Johnson syndrome, etc.) have occurred.
Patients who develop a cutaneous reaction with one ACE inhibitor might not when switched to another drug of the same class, but there are reports of cross-reactivity.
Special Populations
Pregnant Women
ACE inhibitors can cause fetal and neonatal morbidity and mortality when administered to pregnant women. When pregnancy is detected, perindopril arginine should be discontinued as soon as possible (see CONTRAINDICATIONS).
The use of ACE inhibitors is contraindicated during the second and third trimesters of pregnancy, because it has been associated with fetal and neonatal injury including hypotension, neonatal skull hypoplasia, anuria, reversible or irreversible renal failure, and death.
Oligohydramnios has also been reported, presumably resulting from decreased fetal renal function, associated with fetal limb contractures, craniofacial deformation, and hypoplastic lung development.
Prematurity, and patent ductus arteriosus and other structural cardiac malformations, as well as neurologic malformations, have also been reported following exposure in the first trimester of pregnancy.
Infants with a history of in utero exposure to ACE inhibitors should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit.
Perindoprilat, the active form of perindopril, can be removed from the body by hemodialysis (see ACTIONS AND CLINICAL PHARMACOLOGY - Pharmacokinetics and Metabolism, Special populations and conditions – Renal insufficiency).
Animal data
See Part II - Scientific information – TOXICOLOGY, Teratogenicity studies.
Nursing Women
The presence of concentrations of ACE inhibitor have been reported in human milk. Use of ACE inhibitors is contraindicated during breast-feeding (see CONTRAINDICATIONS).
Pediatrics
The safety and effectiveness of perindopril arginine in children have not been established. Its use in this age group, therefore, is not recommended.
Geriatrics (>65 years of age)
Although clinical experience has not identified significant differences in response between the elderly (> 65 years) and younger patients, greater sensitivity of some older individuals cannot be ruled out.
Renal insufficiency is commonly observed in elderly people. Care should therefore be taken when prescribing perindopril arginine to elderly patients. The initial dose of perindopril arginine in the elderly should always be 2.5 mg daily and patients should be monitored closely during the initial stages of treatment (see DOSAGE AND ADMINISTRATION).
In a study of 91 elderly patients with a mean age of 71.9 years, a 6% increase in serum potassium occurred in the first month of treatment and subsequently remained stable. There was no change in the group in blood urea, creatinine or creatinine clearance.
Particular care should be taken in elderly patients with congestive heart failure who have renal and/or hepatic insufficiency.
Diabetic patients
In diabetic patients treated with oral antidiabetic agents or insulin, glycemic control should be closely monitored during the first month of treatment with an ACE inhibitor.
Patients with Impaired Liver Function
Hepatitis (hepatocellular and/or cholestatic), elevations of liver enzymes and/or serum bilirubin have occurred during therapy with ACE inhibitors, in patients with or without pre-existing liver abnormalities. In most cases, the changes were reversed upon discontinuation of the drug.
Elevations of liver enzymes and/or serum bilirubin have been reported with perindopril erbumine (see ADVERSE REACTIONS). Should the patient receiving perindopril arginine experience any unexplained symptoms, particularly during the first weeks or months of treatment, it is recommended that a full set of liver function tests and any other necessary investigation be carried out. Discontinuation of perindopril arginine should be considered when appropriate.
Perindopril arginine should be used with particular caution in patients with pre-existing liver abnormalities. In such patients, baseline liver function tests should be obtained before administration of the drug and close monitoring of response and metabolic effects should apply.
Monitoring and Laboratory Tests
Hematological Monitoring
Periodic monitoring of white blood cell counts is advised in patients with collagen vascular disease such as systemic lupus erythematosus or scleroderma, and those on multiple drug therapy with agents known to be nephrotoxic or myelosuppressive (immunosuppressant therapy, treatment with allopurinol or procainamide), or a combination of these complicating factors, especially if there is pre-existing impaired renal function.
Renal Function Monitoring
Routine monitoring of potassium and creatinine is part of normal medical practice for renal impairment patients (creatinine clearance <60 ml/min). Particularly careful monitoring is required in hypertensive patients with renal artery stenosis. In such patients, renal function should be monitored during the first few weeks of therapy.
Electrolyte Monitoring
If concomitant use of potassium-sparing diuretics, potassium supplements, potassium-containing salt substitutes, drugs associated with increase in serum potassium, or other RAAS inhibitors is deemed appropriate, regular monitoring of serum potassium and urea is recommended.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most frequent adverse reactions observed with perindopril are: cough, dizziness, headache, asthenia, gastro-intestinal disorders (abdominal pain, nausea, and dyspepsia).
The most serious adverse reactions are: hypersensitivity reaction (angioedema), renal dysfunction (in high risk patients), pancreatitis, blood disorders (pancytopenia, agranulocytosis, and thrombocytopenia).
During the long-term safety assessment in heart failure patients, the severe adverse events occurring with the highest frequency were angina pectoris and orthostatic hypotension.
The most severe drug reactions from post-marketing experience were pancreatitis and blood disorders (pancytopenia, agranulocytosis, and thrombocytopenia).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
- Hypertension
Perindopril erbumine was evaluated for safety in approximately 3,400 patients with hypertension (1,216 patients in controlled clinical trials including 181 elderly patients). Perindopril erbumine was evaluated for long-term safety in approximately 1,000 patients that were treated for ≥1 year.
During clinical trials, the most severe adverse drug reactions occurring in hypertensive patients treated with perindopril were angioneurotic oedema and renal insufficiency.
In an open-labelled European study of about 47,000 patients with essential hypertension, seen in everyday medical practice, and treated for 1 year with perindopril erbumine, with or without multiple other medications, the most frequently observed adverse events were: cough (9.7%), digestive symptoms (2.0%), fatigue (1.8%), headache (1.4%) and dizziness (1.4%). In this study, in total, 5.1% of patients withdrew due to adverse events, 3.2% due to cough.
In placebo-controlled U.S. trials, 1,012 patients received either perindopril monotherapy (n=630), perindopril/HCT (n=159) or placebo (n=230). Table 1 presents adverse reactions that occurred in ≥1% of the patients treated with perindopril monotherapy or placebo.
| Table 1: | Adverse events without attribution to therapy, and those considered possibly or probably related to therapy, reported in ≥1% of patients treated for hypertension in placebo-controlled U.S. trials | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
Adverse Events, not treatment related | Possibly or Probably Treatment Related Adverse Events | ||||||||||
Perindopril n=630 | Placebo n=223 | Perindopril n=630 | Placebo n=223 | ||||||||
| Headache | 26.0 | 29.6 | 9.4 | 10.8 | |||||||
| Cough | 13.0 | 4.5 | 6.2 | 1.8 | |||||||
| Table 1: | Adverse events without attribution to therapy, and those considered possibly or probably related to therapy, reported in ≥1% of patients treated for hypertension in placebo-controlled U.S. trials |
|---|
Adverse Events, not treatment related | Possibly or Probably Treatment Related Adverse Events | |||||
|---|---|---|---|---|---|---|
| Asthenia | 8.7 | 9.9 | 5.4 | 4.0 | ||
| Dizziness | 8.6 | 8.5 | 4.9 | 5.8 | ||
| Upper respiratory infection | 7.9 | 8.5 | 0.0 | 0.9 | ||
| Diarrhoea | 4.6 | 4.0 | 1.8 | 0.5 | ||
| Oedema | 4.3 | 4.9 | 0.6 | 0.9 | ||
| Sleep disorder | 2.5 | 2.7 | 1.6 | 0.9 | ||
| Nervous | 1.4 | 1.4 | 1.1 | 0.9 | ||
| Depression | 1.9 | 1.4 | 1.1 | 0.5 | ||
| Proteinurea | 1.8 | 0.5 | 1.1 | 0.5 | ||
| Rash | 2.5 | 4.9 | 1.0 | 1.8 | ||
The incidence of premature discontinuation of therapy due to adverse events in the placebo-controlled U.S clinical trials was 6.5% in patients treated with perindopril and 6.7% in patients treated with placebo. The most common causes of premature discontinuation were cough, headache, asthenia and dizziness; cough was the reason for withdrawal in 1.3% and 0.4% of patients treated with perindopril and placebo, respectively. While dizziness was not reported more frequently in the perindopril group (8.2%) than in the placebo group (8.5%), it was clearly increased with dose, suggesting a causal relationship with perindopril.
Other reported adverse events (reported in ≥1% patients), regardless of causality, include: back pain (6.8%), rhinitis, sinusitis (each 5.2%), pain in lower extremities (5.1%), pharyngitis (3.7%), viral infection (3.3%), urinary tract infection (3.2%), pain in upper extremities (2.9%), nausea (2.7%), abdominal pain (2.5%), accidental injury, hypertonia, paresthesia (each 2.4%), non- specific chest-pain, abnormal ECG (each 2.2%), dyspepsia (2.1%), vomiting (1.9%), fever, seasonal allergy (each 1.8%), ALT increase (1.6%), generalized myalgia, neck pain, tinnitus (each 1.4%), joint pain, somnolence (each 1.1%), flatulence, arthritis, palpitations (each 1.0%).
Myocardial infarction and cerebrovascular accident occurred possibly secondary to excessive hypotension in high-risk patients (see WARNINGS and PRECAUTIONS – Cardiovascular).
Withdrawals
In total 56 of 1,275 patients studied (4.4%) stopped treatment because of adverse reactions. In a specific study of 632 patients, 36 (5.7%) patients withdrew because of adverse events. A plausible or probable relationship with perindopril erbumine treatment were considered to exist in 19 (3%) cases.
Adverse drug reactions that most commonly result in premature discontinuation of therapy were cough (0.5%), headache (0.5%), dizziness (0.5%) and asthenia (0.4%).
- Congestive Heart Failure
In heart failure trials, safety was evaluated in 167 patients treated with perindopril in 3-month placebo-controlled trials and long-term safety was assessed in 513 patients treated for ≥6months, 352 of which were followed for at least 1 year. Table 2 presents adverse drug reactions that occurred in ≥1% of the 167 patients treated with perindopril during the double-blind period lasting 3 months, as compared to the same adverse events occurring in the 170 patients receiving a placebo. Discontinuation of therapy due to adverse events was required in 5.4% of the 167 patients with perindopril, as compared to 4.7% of the 170 patients who received a placebo.
| Table 2: Drug-related Adverse Experience Reported in ≥1% of Patient Treated for Congestive Heart Failure (% ) | ||||
|---|---|---|---|---|
Perindopril n=167 | Placebo n=170 | |||
| Asthenia | 6.6 | 5.3 | ||
| Dizziness | 6.0 | 6.5 | ||
| Skin disorder | 4.2 | 2.4 | ||
| Abdominal pain upper / gastralgia | 4.2 | 2.9 | ||
| Nausea / vomiting | 3.6 | 1.2 | ||
| Headache | 3.0 | 2.4 | ||
| Palpitations | 2.4 | 1.8 | ||
| Muscular cramps | 2.4 | 0.0 | ||
| Cough | 1.8 | 0.6 | ||
| Chest pain - cardiac | 1.8 | 0.0 | ||
| Dyspnoea | 1.8 | 2.4 | ||
| Diarrhoea | 1.8 | 1.8 | ||
| Mood altered and sleep disturbance | 1.8 | 2.9 | ||
| Oedema | 1.2 | 1.8 | ||
| Sweating | 1.2 | 0.6 | ||
| Erectile dysfunction | 1.2 | 0.6 | ||
- Hypertensive and/or Post-MI Patients with Stable Coronary Artery Disease
Perindopril was evaluated for safety in the EUROPA trial. This was a double-blind, placebo-controlled study in 12,218 patients with stable coronary artery disease (CAD), the majority of which had hypertension and/or had survived a previous heart attack. The overall rate of discontinuation was 22.8% (1391 / 6110 patients) and 20.7% (1266 / 6108 patients) in the perindopril and placebo groups, respectively.
The most common reasons for discontinuation that were more frequent on perindopril erbumine than placebo were cough (2.7%), drug intolerance (2.4%), hypotension (1.0%) and kidney failure (0.3%).
Serious Adverse Events in EUROPA trial
There were no significant differences in the numbers of deaths between the perindopril (n=375) and control (n=420) groups. However, 10 patients died during the open run-in period of the study, of whom 7 from cardiovascular causes, including stroke. A total of 795 patients (out of 12,230; 6.5%) died during the study, 464 of the 795 (58%) died from a cardiovascular cause.
During the randomized period of the EUROPA study, only serious adverse events were collected. Few patients experienced serious adverse events: 16 (0.3%) of the 6,122 perindopril patients and 12 (0.2%) of the 6,107 placebo patients. In perindopril-treated patients, hypotension was observed in 6 patients, angioedema in 3 patients, and sudden cardiac arrest in 1 patient. More patients withdrew for cough, hypotension, or other intolerance on perindopril (6.0%, n=366) than on placebo (2.1%, n=129).
On the other hand, atrial cardioversion occurred significantly more frequently in the perindopril group (0.5%, n=42) than in the control group (0.3%, n=17).
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Adverse events, irrespective of causal relationship to the drug, which occurred in <1.0% of hypertensive and heart failure patients treated with perindopril erbumine in clinical trials, are listed as follows:
| Blood and lymphatic system disorders: | Haemolytic anaemia, leucopenia including neutropenia, thrombocytopenia, ecchymosis, haematoma. |
| Cardiac disorders: | Arrhythmia, ventricular extrasystole, conduction disorder, cardiac murmur, palpitations, bradycardia, myocardial infarction |
| Ear and labyrinth disorders: | Ear pain, tinnitus. |
| Eye disorders: | Visual disturbance, lacrimation increased, conjunctivitis. |
| Gastrointestinal disorders: | Constipation, dry mouth, dysgeusia, flatulence, haematemesis, G.I. haemorrhage, stomatitis, diarrhoea, vomiting, dyspepsia. |
| General disorders and administration site conditions: | Chest pain, pyrexia, malaise, pain, peripheral oedema, thirst, feeling cold and hot, rigors. |
| Immune system disorders: | Anaphylactic reaction, angioneurotic oedema (head, neck, face, extremities, lips, tongue, glottis and/or larynx). |
| Infections and infestations: | Herpes simplex, peritoneal infection (mesenteric infarction, 1 patient), bronchitis, pharyngitis, pneumonia, rhinitis, sinusitis, skin infection, tinea infection, gastroenteritis, vaginitis. |
| Metabolism and nutrition disorders: | Anorexia, increased appetite, gout. |
| Musculoskeletal and connective tissue disorders: | Neck pain, oedema, arthralgia, arthritis, bone pain, myalgia, myasthenia, sciatalgia, hypertonia/muscle cramps, back (lumbar) pain. |
| Nervous system disorders: | Hyperkinesia, amnesia, cerebrovascular accident (0.2%), cognitive disorders, memory impairment, perceptual distorsion, somnolence, speech disorder, syncope, tremor, migraine, vertigo. |
| Psychiatric disorders: | Abnormal dreams, agitation, confusional state, depression, mood altered, nervousness, illusion, sleep disturbance, libido disorder, anxiety, psychosexual disorder. |
| Renal and urinary disorders: | Haematuria, nephrolithiasis, nocturia, oliguria, polyuria, pollakiuria, urinary incontinence, urinary retention, fluid retention, renal insufficiency, flank pain. |
| Reproductive system and breast disorders: | Menstrual disorder, scrotal oedema, erectile dysfunction. |
| Respiratory, thoracic and mediastinal disorder: | Asthma, bronchospasm, dyspnoea, pulmonary fibrosis, throat irritation, rhinorrhoea, epistaxis, postnasal drip, hoarseness, sneezing. |
| Skin and subcutaneous tissue disorders: | Alopecia, erythema, dry skin, skin disorder, dermatitis, pemphigus, pruritus, purpura, rash, Steven-Johnson syndrome, hyperhidrosis, toxic skin eruption, urticaria, mucous membrane disorder. |
| Vascular disorders: | Hypotension, orthostatic hypotension, peripheral coldness, intermittent claudication, vasodilation, flushing, peripheral vascular disorder (impaired peripheral circulation, swollen legs). |
Potential Adverse Events Reported with ACE Inhibitors
Other medically important adverse events reported with other available ACE inhibitors include cardiac arrest, eosinophilic pneumonitis, neutropenia/agranulocytosis, pancytopenia, anemia (including hemolytic and aplastic), thrombocytopenia, acute renal failure, nephritis, hepatic failure, jaundice (hepatocellular or cholestatic), symptomatic hyponatremia, bullous pemphigus, acute pancreatitis, exfoliative dermatitis and a syndrome which may include: arthralgia/arthritis, vasculitis, serositis, myalgia, fever, rash or other dermatologic manifestations, a positive ANA, leukocytosis, eosinophilia or an elevated ESR. Many of these adverse events have also been reported for perindopril.
Taste disturbances (dysgeusia)
Taste disturbances were reported to be common (prevalence up to 12.5%) with high doses of another ACE inhibitor.
Taste disturbance with ACE inhibitors have been described as suppression of taste or a metallic sensation in the mouth. Any dysgeusia usually occurs in the first weeks of treatment and may disappear in most cases within 1-3 months.
Abnormal Hematologic and Clinical Chemistry Findings
Serum Electrolytes
In clinical trials, hyperkalemia (serum potassium >5.5 mEq/L) occurred in approximately 2.2% of the hypertensive patients treated with perindopril compared to 1.4% in placebo-treated patients. Hyperkalemia may occur especially in the presence of renal insufficiency, severe heart failure and renovascular hypertension (see WARNINGS AND PRECAUTIONS – Renal).
Blood Urea Nitrogen/ Serum Creatinine
Elevations of BUN (>40 mg/dl) or serum creatinine (>2.5 mg/dl) were observed in 0.2% and 0.3% of patients, respectively, treated with perindopril erbumine monotherapy. Decreases in serum sodium and increases in serum creatinine occurred more frequently in patients on concomitant diuretics than in those treated with perindopril erbumine alone. Increases in blood urea, plasma creatinine, and hematuria were observed and may occur especially in the presence of renal insufficiency.
Hematology
Small decreases in hemoglobin and hematocrit occurred in hypertensive patients treated with perindopril erbumine, but were rarely of clinical importance. In controlled clinical trials, no patient was discontinued from therapy due to the development of anemia.
Liver Function
Elevations of liver enzymes (ALT: 1.6% perindopril erbumine vs 0.9% placebo, AST: 0.5% perindopril erbumine vs 0.4% placebo) were observed in U.S. placebo-controlled clinical trials. Elevations in serum bilirubin were observed (see WARNINGS AND PRECAUTIONS – Special population).
Other
Elevations in serum cholesterol and plasma glucose were observed.
Post-Market Adverse Drug Reactions
The most frequent adverse events occurring in post-marketing experience were cough, gastro-intestinal symptoms (abdominal pain, nausea, and dyspepsia), asthenia, fatigue, dizziness and headache.
| Blood and lymphatic system disorders: | Agranulocytosis or pancytopenia, decreased haemoglobin and haematocrit, haemolytic anemia in patients with a congenital deficiency of G-6PDH, leukopenia/neutropenia, thrombocytopenia, eosinophilia. |
| Cardiac disorders: | Angina pectoris, arrhythmia, myocardial infarction, possibly secondary to excessive hypotension, palpitations, tachycardia. |
| Ear and labyrinth disorders: | Tinnitus. |
| Endocrine disorders: | syndrome of inappropriate antidiuretic hormone secretion (SIADH) |
| Eye disorders: | Vision disturbance. |
| Gastrointestinal disorders: | Abdominal pain (including upper), constipation, diarrhoea, dry mouth, dysgeusia, dyspepsia, nausea, pancreatitis, vomiting. |
| General disorders and administration site conditions: | Asthenia, chest pain, malaise, oedema peripheral, pyrexia, sweating. |
| Hepato-biliary disorders: | Cholestatic or cytolytic hepatitis. |
| Injury, poisoning and procedural complications: | Fall. |
| Metabolism and nutrition disorders: | Hypoglycemia, hyperkalaemia, reversible on discontinuation, hyponatraemia. |
| Musculoskeletal, connective tissue disorders: | Arthralgia, back pain, oedema, hypertonia, muscle cramps, pain in extremity, myalgia. |
| Nervous system disorders: | Confusion, dizziness, headache, paresthesia, somnolence, syncope, vertigo. |
| Psychiatric disorders: | mood or sleep disturbances. |
| Renal and urinary disorders: | Acute renal failure, renal insufficiency, proteinuria. |
| Reproductive system and breast disorders: | Erectile dysfunction. |
| Respiratory/Thoracic and Mediastinal disorders: | Bronchospasm, cough, dyspnoea, eosinophilic pneumonia, rhinitis. |
| Respiratory/Thoracic and Mediastinal disorders: | Bronchospasm, cough, dyspnoea, eosinophilic pneumonia, rhinitis. |
| Skin and sub-cutaneous tissue disorders: | Angioneurotic oedema (face, extremities, lips, mucous membranes, tongue, glottis and/or larynx, erythema multiforme), erythema multiforme, pruritis, rash, urticarial, eczema, photosensitivity reactions, pemphigoid, pemphigus, psoriasis aggravation |
| Vascular disorders: | Cerebrovascular attack (possibly secondary to excessive hypotension in high-risk patients), hypotension, peripheral vascular disorder (impaired peripheral circulation). |
Post-marketing experience with all ACE inhibitors suggests that exposure in utero may be associated with hypotension and decreased renal perfusion in the fetus. ACE inhibitors have also been associated with fetal death in utero. No ACE inhibitor should be used in pregnancy.
DRUG INTERACTIONS
Overview
Drug-Drug Interactions
| Table 3 - Established or Potential Drug-Drug Interactions | |||
|---|---|---|---|
| Proper name | Ref | Effect | Clinical comment |
| Agents Affecting Sympathetic Activity | CT C | Beta adrenergic blocking drugs add further antihypertensive effect to perindopril erbumine. | Agents affecting sympathetic activity (e.g. ganglionic blocking agents or adrenergic neuron blocking agents) may be used with caution. |
| Agents Causing Renin Release | CT C | The antihypertensive effect of perindopril erbumine is augmented by antihypertensive agents that cause renin release (e.g. diuretics). | |
| Agents Increasing Serum Potassium | CT | Since perindopril erbumine decreases aldosterone production, elevation of serum potassium may occur. | Potassium-sparing diuretics such as spironolactone, eplerenone, triamterene or amiloride, or potassium supplements, potassium-containing salt substitutes, or any drugs associated with increase in serum potassium (aliskiren, NSAIDs, heparin, cyclosporine, tacrolimus, trimethoprim, angiotensin receptor blockers and others) should be given only for documented hypokalemia and with caution and frequent monitoring of serum potassium, since they may lead to a significant increase in serum potassium. Salt substitutes which contain potassium should also be used with caution (see WARNINGS AND PRECAUTIONS, Renal, Hyperkalemia and agents increasing serum potassium). |
| Antihypertensive agents and vasodilators | Concomitant use of these agents may increase the hypotensive effects of perindopril. Concomitant use with nitroglycerin and other nitrates, or other vasodilators, may further reduce blood pressure. | ||
| Antidiabetic agents | Epidemiological studies have suggested that concomitant administration of ACE inhibitors and antidiabetic medicines (insulins, oral hypoglycaemic agents) may cause an increased blood-glucose lowering effect | This phenomenon appeared to be more likely to occur during the first weeks of combined treatment and in patients with renal impairment. | |
| Table 3 - Established or Potential Drug-Drug Interactions |
|---|
| Proper name | Ref | Effect | Clinical comment |
|---|---|---|---|
| with risk of hypoglycaemia. | |||
| Baclofen | Increased antihypertensive effect. | Monitor blood pressure and adapt antihypertensive dosage if necessary. | |
| Concomitant Diuretic Therapy | C | Patients concomitantly taking ACE inhibitors and diuretics, and especially those in whom diuretic therapy was recently instituted and who are volume and/or salt depleted may experience an excessive reduction of blood pressure after initiation of therapy. | The possibility of hypotensive effects after the first dose of MYLAN-PERINDOPRIL ARGININE can be minimized by either discontinuing the diuretic or increasing the volume or salt intake prior to initiation of treatment with low and progressive doses of MYLAN-PERINDOPRIL ARGININE. If it is not possible to discontinue the diuretic, the starting dose of MYLAN-PERINDOPRIL ARGININE can be reduced, and the patient should be closely observed for several hours following the initial dose and until blood pressure has stabilized. The rate and extent of perindopril absorption and elimination are not affected by concomitant diuretics. The bioavailability of perindoprilat was reduced by a diuretic and this was associated with a decrease in plasma ACE inhibition (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION). |
| Digoxin | C | A pharmacokinetic study has shown no effect on plasma digoxin concentration when co-administered with perindopril erbumine but an effect of digoxin on the plasma concentration of perindopril / perindoprilat has not been excluded. | |
| DDP-IV inhibitors (linagliptin, saxagliptin, sitagliptin) | Patients taking concomitant DDP-IV inhibitor therapy may be at increased risk for angioedema. | Caution should be used when initiating MYLAN-PERINDOPRIL ARGININE in patients already taking a DPP-IV inhibitor or vice versa (see WARNINGS AND PRECAUTIONS, General, Head and Neck Angioedema). | |
Dual blockade of the Renin-Angiotensin- System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs | CT | Increased incidence of severe hypotension, renal failure, and hyperkalemia. | Dual Blockade of the Renin Angiotensin-System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs is contraindicated in patients with diabetes and/or renal impairment, and is generally not |
| Table 3 - Established or Potential Drug-Drug Interactions |
|---|
| Proper name | Ref | Effect | Clinical comment |
|---|---|---|---|
| recommended in other patients (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS)). | |||
| Estramustine | Risk of increased adverse effects such as angioneurotic oedema (angioedema) | Use with caution when MYLAN-PERINDOPRIL ARGININE is co-administered with estramustine. | |
| Extracorporeal treatments | Extracorporeal treatments leading to contact of blood with negatively charged surfaces such as dialysis or haemofiltration with certain high-flux membranes (e.g. polyacrylonitrile membranes) and low density lipoprotein apheresis with dextran sulphate due to increased risk of severe anaphylactoid reactions (see CONTRAINDICATIONS). | If such treatment is required, consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent. | |
| Gentamicin | Animal data have suggested the possibility of interaction between perindopril and gentamicin. However, this has not been investigated in human studies. | Co-administration of both drugs should proceed with caution. | |
| Gold salts | CT | Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including perindopril. | Use with caution when MYLAN-PERINDOPRIL ARGININE is co-administered with gold salts. |
| Lithium | C | Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving concomitant lithium and ACE inhibitor therapy. | These drugs should be co-administered with caution and frequent monitoring of serum lithium levels is recommended. If a diuretic is also used, the risk of lithium toxicity may be further increased. |
mTOR inhibitors (e.g. sirolimus, everolimus, temsirolimus) | Patients taking concomitant mTOR inhibitors may be at increased risk for angioedema. | Caution should be used when initiating MYLAN-PERINDOPRIL ARGININE in patients already taking mTOR inhibitors or vice versa (see WARNINGS AND PRECAUTIONS, Head and Neck Angioedema). | |
| Non-steroidal anti-inflammatory drugs (NSAIDs) including | The administration of a NSAID may reduce the antihypertensive effect of ACE inhibitors. NSAIDs | These effects are usually reversible. Rarely, acute renal failure may occur, especially in patients with compromised |
| Table 3 - Established or Potential Drug-Drug Interactions |
|---|
| Proper name | Ref | Effect | Clinical comment |
|---|---|---|---|
| aspirin ≥ 3g/day | also exert an additive effect on the increase in serum potassium and may result in a deterioration of renal function. | renal function such as those who are elderly or dehydrated. | |
| Neutral endopeptidase inhibitor | ACE inhibitors are known to cause angioedema. This risk may be elevated when used concomitantly with a neutral endopeptidase inhibitor | Caution should be used when initiating MYLAN-PERINDOPRIL ARGININE in patients already taking a neutral endopeptidase inhibitor or vice versa (see WARNINGS AND PRECAUTIONS, General, Head and Neck Angioedema). | |
| Sympathomimetics | Sympathomimetics may reduce the antihypertensive effects of ACE inhibitors. | Use with caution when MYLAN-PERINDOPRIL ARGININE is co-administered with sympathomimetics | |
Tricyclic antidepressants / Antipsychotic / Anesthetics | Concomitant use of certain anesthetics, tricyclic antidepressants and antipsychotics with ACE inhibitors may result in further reduction of blood pressure. | Use with caution when MYLAN-PERINDOPRIL ARGININE is co-administered with these drugs | |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Drug-Food Interactions
The presence of food in the gastrointestinal tract does not affect the rate or extent of perindopril absorption. However, the extent of biotransformation of perindopril to perindoprilat is reduced, resulting in a decrease of perindoprilat bioavailability by 35%. Therefore it is recommended that perindopril arginine be taken before a meal.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory products/methods have not been established.
Drug-Lifestyle Interactions
Lifestyle interactions have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Dosage of MYLAN-PERINDOPRIL ARGININE must be individualized and adjustment is required in the elderly, and in case of renal impairment.
Recommended Dose and Dosage Adjustment
- Hypertension
Initiation of therapy requires consideration of recent antihypertensive drug treatment, the extent of blood pressure elevation and salt restriction. The dosage of other antihypertensive agents being used with MYLAN-PERINDOPRIL ARGININE may need to be adjusted. The presence of food in the gastrointestinal tract reduces the bioavailability of perindoprilat.
Monotherapy
The recommended initial dose of MYLAN-PERINDOPRIL ARGININE, in patients not on diuretics, is 5 mg once daily. Dosage should be adjusted according to blood pressure response, generally at intervals of at least 2 weeks. The usual maintenance dose is 5 to 10 mg daily administered in a single daily dose. No additional blood pressure lowering effects were achieved with doses greater than 10 mg daily.
In some patients treated once daily, the antihypertensive effect may diminish towards the end of the dosing interval. This can be evaluated by measuring blood pressure just prior to dosing to determine whether satisfactory control is maintained for 24 hours. If it is not, either twice daily administration with the same total daily dose, or an increase in dose should be considered. If blood pressure is not controlled with MYLAN-PERINDOPRIL ARGININE alone, a diuretic may be added. After the addition of a diuretic, it may be possible to reduce the dose of MYLAN-PERINDOPRIL ARGININE.
Concomitant Diuretic Therapy
Symptomatic hypotension occasionally may occur following the initial dose of MYLAN-PERINDOPRIL ARGININE and is more likely in patients who are currently being treated with a diuretic. The diuretic should, if possible, be discontinued for two or three days before beginning therapy with MYLAN-PERINDOPRIL ARGININE to reduce the likelihood of hypotension (see WARNINGS AND PRECAUTIONS). If the diuretic cannot be discontinued, an initial dose of 2.5 mg MYLAN-PERINDOPRIL ARGININE should be used with careful medical supervision for several hours and until blood pressure has stabilized. The dosage of MYLAN-PERINDOPRIL ARGININE should subsequently be titrated to the optimal response.
The Elderly
In the elderly, treatment should begin with a 2.5 mg dose in the morning. If necessary, after one month of treatment this dose can be increased to 5 mg daily and then to 10 mg depending on renal function given in one or two divided doses.
- Congestive Heart Failure
MYLAN-PERINDOPRIL ARGININE is generally used in conjunction with a diuretic and, where appropriate, a digitalis glycoside in patients with congestive heart failure. Therapy should be initiated under close medical supervision. Blood pressure and renal function should be monitored, both before and during treatment with perindopril because severe hypotension and, more rarely, consequent renal failure have been reported (see WARNINGS AND PRECAUTIONS).
Initiation of therapy requires consideration of recent diuretic therapy and the possibility of severe salt/ volume depletion. If possible, the dose of diuretic should be reduced before beginning treatment. Serum potassium should also be monitored (see DRUG INTERACTIONS, Drug- Drug Interactions).
The recommended initial dose is 2.5 mg once daily taken in the morning under close medical supervision. The dose may, in most instances, be increased to 5 mg once daily (once blood pressure acceptability has been demonstrated). The usual effective dose in clinical trials was
4 mg/day of perindopril erbumine administered as a single dose. Dose titration may be performed over a 2- to 4-week period.
The Elderly
No special dosage recommendation is required for elderly patients with congestive heart failure.
- Hypertensive and/or Post-MI Patients with Stable C Artery Disease
In patients with hypertension and stable coronary artery disease or in post-myocardial infarction patients with coronary artery disease, MYLAN-PERINDOPRIL ARGININE should be given at an initial dose of 5 mg once daily for 2 weeks, and then increased as tolerated, to a maintenance dose of 10 mg once daily, preferably to be taken early in the morning. In these patients, MYLAN-PERINDOPRIL ARGININE should be administered as add-on to the conventional treatment, such as platelet inhibitors, beta blockers, lipid-lowering agents, nitrates, calcium channel blockers or diuretics.
The Elderly
In elderly patients (>70 years), MYLAN-PERINDOPRIL ARGININE should be given as a 2.5 mg dose once daily in the first week, followed by 5 mg once daily in the second week and 10 mg once daily for maintenance dose if tolerated.
Renal Impairment
In case of renal impairment, the dosage of MYLAN-PERINDOPRIL ARGININE must be adjusted based on creatinine clearance. The following dosages are recommended:
| Creatinine clearance | Recommended dosage |
|---|
| Creatinine clearance | Recommended dosage |
|---|---|
| ≥60 ml/min (normal value) | 5 mg per day; (the daily dosage should not exceed 10 mg) |
| Between 30 and 60 ml/min | 2.5 mg per day |
| Between 15 and 30 ml/min | 2.5 mg every other day |
| Haemodialysed patients (<15 ml/min) | 2.5 mg on the day of dialysis (the dose should be taken after dialysis) |
In these patients, normal medical follow up includes periodic assessment of potassium and creatinine levels.
Missed Dose
If a dose is missed, a double dose should not be taken, but just carry on with the next dose at the normal time.
Administration
It is recommended that MYLAN-PERINDOPRIL ARGININE be taken once daily in the morning before a meal.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
Limited data are available regarding overdosage of perindopril arginine in humans. The most likely clinical manifestation would be symptoms attributable to severe hypotension. In the case of overdosage, gastric washout and intravenous infusion of a normal saline solution are recommended.
However, of the two cases reported in the perindopril clinical trials, one (dosage unknown) required ventilation assistance and the other developed hypothermia, circulatory arrest, and subsequently died, following ingestion of up to 180 mg of perindopril erbumine. Thus, intervention in perindopril arginine overdosage may require vigorous support.
Perindopril arginine can be removed by hemodialysis, with clearances of about 52 ml/min for perindopril and 67 ml/min for perindoprilat, the active metabolite (see ACTIONS AND CLINICAL PHARMACOLOGY – Special Populations and Conditions – Renal insufficiency).
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Perindopril arginine is a non-sulphydryl angiotensin converting enzyme (ACE) inhibitor, which is used in the treatment of hypertension and mild to moderate congestive heart failure.
Following oral administration, perindopril arginine is rapidly hydrolysed to perindoprilat, its principal active metabolite.
Angiotensin-converting enzyme catalyses the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex. Inhibition of ACE activity leads to decreased levels of angiotensin II, thereby resulting in decreased vasoconstriction and decreased aldosterone secretion. The latter change may result in a small increase in serum potassium (see WARNINGS AND PRECAUTIONS – Hyperkalemia and agents increasing serum potassium). Decreased levels of angiotensin II and the accompanying lack of negative feedback on renal renin secretion results in increases in plasma renin activity.
ACE is identical to kininase II. Thus, perindopril arginine administration may interfere with the degradation of the vasodepressor peptide bradykinin. It is not known whether this effect contributes to the therapeutic activity of perindopril arginine.
The mechanism through which perindopril arginine lowers blood pressure appears to result primarily from suppression of the RAAS.
Pharmacodynamics
In most patients with mild to moderate essential hypertension, administration of 4 to 8 mg daily of perindopril erbumine results in a reduction of both supine and standing blood pressure with little or no effect on heart rate. Antihypertensive activity commences within one hour with peak effects usually achieved by 4 to 6 hours after dosing. At recommended doses given once daily, antihypertensive effects persist over 24 hours. The blood pressure reductions observed at trough plasma concentration were 75-100% of peak effects. When once and twice daily dosing were compared, the twice daily regimen was slightly superior, but by no more than about 0.5 to 1.0 mmHg. Abrupt withdrawal of perindopril erbumine has not been associated with a rapid increase in blood pressure. In studies carried out in patients with mild to moderate essential hypertension, the reduction in blood pressure was accompanied by a reduction in peripheral resistance with no change in glomerular filtration rate. When perindopril erbumine is given together with thiazide like diuretics, the antihypertensive effects are synergistic.
In uncontrolled studies in patients with insulin-dependent diabetes, perindopril erbumine did not appear to affect glycemic control. In long term use in this population, no effect on urinary protein excretion was seen.
Administration of perindopril erbumine to patients with congestive heart failure reduces cardiac work by a decrease in preload and afterload. Clinical trials have demonstrated that perindopril decreases left and right ventricular filling pressures, reduces total peripheral vascular resistance, increases cardiac output with an improved cardiac index, and increases muscular regional blood flow. The exercise tolerance of these patients is improved and is associated with an improvement of clinical symptomatology. At the recommended doses, the hemodynamic effects are maintained throughout the 24-hour dosing interval in most patients.
In controlled studies versus placebo and other ACE inhibitors, the first administration of 2 mg of perindopril erbumine in patients with mild-moderate heart failure was not associated with any significant reduction in blood pressure as compared to placebo.
The efficacy of perindopril erbumine in reduction of cardiovascular risk in hypertension or post-myocardial infarction was based on one mortality/morbidity study (EUROPA trial, see CLINICAL TRIALS).
Pharmacokinetics
Perindopril arginine is a non-sulphydryl angiotensin converting enzyme (ACE) inhibitor. Following oral administration, perindopril arginine is rapidly hydrolysed to perindoprilat, its active metabolite. The clearance of perindoprilat and other metabolites is primarily by the renal pathway.
| Table 4a: | Summary of perindopril and perindoprilat pharmacokinetic parameters (mean +/- SD) following repeated oral administrations of three doses of perindopril arginine salt in healthy male volunteers (Cmax - T½ - AUC) | |||||||
Cmax (ng/mL) | T½,l (h) | AUC (ng.h/mL) | ||||||
2 mg of perindopril erbumine | Perindopril | 20 ± 4.9 | 0.41 ± 0.07 | 23 ± 3.9 | ||||
| Perindoprilat | 4.9 ± 1.2 | ND | 72 ± 15 | |||||
4 mg of perindopril erbumine | Perindopril | 36 ± 11 | 0.47 ± 0.13 | 47 ± 8.0 | ||||
| Perindoprilat | 11.0 ± 3.4 | ND | 122 ± 27 | |||||
8 mg of perindopril erbumine | Perindopril | 83 ± 27 | 0.41 ± 0.06 | 94 ± 16 | ||||
| Perindoprilat | 22 ± 6.5 | ND | 212 ± 38 | |||||
ND: Not determined
| Table 4b: | Summary of perindopril and perindoprilat pharmacokinetic parameters: population pharmacokinetics combined analysis (Clearance, central volume and peripheral volume) | ||||||
Clearance (mL/min) | Central volume (L) | Peripheral volume (L) | |||||
| Perindopril | 367 | 13 | 7.2 | ||||
| Perindoprilat | 167 | 32 | 93 | ||||
Absorption
After oral administration of perindopril erbumine, perindopril is rapidly absorbed with peak plasma concentrations occurring at about one hour, with a bioavailability of 24%. Following absorption, perindopril is converted into perindoprilat, its active metabolite, with a mean bioavailability of 25%.
The peak plasma concentration of perindoprilat is reached in about 4 hours after oral administration of perindopril erbumine.
The presence of food in the gastrointestinal tract does not affect the rate or extent of perindopril absorption after oral administration of perindopril erbumine. However, the extent of biotransformation of perindopril to perindoprilat is reduced, resulting in a decrease of perindoprilat bioavailability by 35%. Therefore it is recommended that perindopril erbumine is taken before a meal.
Distribution
Plasma protein binding of perindoprilat is low (10 to 35%), the binding is concentration dependent due to the saturable binding of perindoprilat to the circulating angiotensin-converting enzyme. The volume of distribution is approximately 0.5 L/kg for unbound perindoprilat.
Metabolism
Perindopril is extensively metabolised following oral administration, with only 4 to 12% of the dose recovered unchanged in the urine. Six metabolites have been identified. They include perindoprilat, the active form, and five others that do not possess appreciable therapeutic activity (perindopril glucuronide, perindoprilat glucuronide, a perindopril lactam, and two perindoprilat lactams).
The two main circulating metabolites of perindopril are perindoprilat and perindoprilat glucuronide.
Two different pathways identified and quantified for perindoprilat formation are the pre-systemic
(first pass effect) and systemic hydrolysis of perindopril. Perindopril is indeed sensitive to a pre- systemic first-pass effect, accounting for 63% of the perindoprilat formation. The systemic hydrolysis of perindopril into perindoprilat accounts for the remaining 37% left.
Excretion
The clearance of perindoprilat and other metabolites is primarily by the renal pathway. The systemic clearance of perindopril (367 ml/min) can be split into 39% leading to perindoprilat formation and 61% to renal excretion or other biotransformations.
The terminal plasma half-life of perindopril is very short (1.2h), thus leading to no accumulation with a once daily oral dosing regimen. The terminal plasma half-life of unbound perindoprilat is about 17 hours, resulting in a steady-state within 3 days.
Special Populations and Conditions
Pediatrics
The safety and effectiveness of perindopril arginine in children have not been established. Its use in this age group, therefore, is not recommended.
Geriatrics
In a pharmacokinetic study with single dose administration, mean peak plasma concentrations of perindoprilat were significantly higher in elderly healthy volunteers (32.5 ng/ml) than in younger volunteers (13.5 ng/ml) due to both higher bioavailability and reduced renal clearance in this group.
Single and multiple dose pharmacokinetics of perindopril were evaluated in a study of elderly hypertensive patients (72 to 91 years of age), Cmax and AUC were found to be approximately two-fold higher than in healthy younger subjects. The higher concentrations of perindoprilat observed in these patients were reflected in greater ACE inhibition (see WARNINGS and PRECAUTIONS - Geriatrics and DOSAGE AND ADMINISTRATION - Dosage adjustment).
Gender
The effectiveness of perindopril erbumine was not influenced by gender.
Race
The blood pressure lowering effects of angiotensin converting enzyme (ACE) inhibitors generally are lower in black persons than Caucasian patients. The cardiovascular benefits of ACE inhibitors, in terms of risk reduction in coronary artery disease, have not been extensively studied in blacks.
Hepatic Insufficiency
The bioavailability of perindoprilat is increased in patients with impaired hepatic function. Plasma concentrations in patients with hepatic impairment were about 50% higher than those observed in healthy subjects or hypertensive patients with normal liver function.
Renal Insufficiency
In patients with renal insufficiency, perindoprilat AUC increases with decreasing renal function. At creatinine clearances of 30-80 ml/min, AUC is about double that of 100 ml/min. When creatinine clearance drops below 30 ml/min, AUC increases more markedly. Therefore the dosage of perindopril should be adjusted in patients with a creatinine clearance below 30 ml/min.
Perindopril, and its active metabolite perindoprilat, are dialysable. In a limited number of patients studied, perindopril hemodialysis clearance ranged from 41.7 to 76.7 ml/min (mean 52.0 ml/min). Perindoprilat hemodialysis clearance ranged from 37.4 to 91.0 ml/min (mean 67.2 ml/min).
Heart Failure
Patients with heart failure have reduced perindoprilat clearance, which may result in a dose interval AUC that is increased up to 40% which should lead to an initial reduction of perindopril dosage.
Genetic Polymorphism
Pharmacokinetics differences due to genetic polymorphism have not been studied.
STORAGE AND STABILITY
Store at controlled room temperature (15-30°C).
SPECIAL HANDLING INSTRUCTIONS
No special requirements.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage form:
MYLAN-PERINDOPRIL ARGININE (perindopril arginine) tablets:
- 2.5 mg: Each white to off-white, film-coated, round, biconvex tablet debossed with M on one side of the tablet and PA over 1 on the other side contains: perindopril arginine 2.5 mg.
- 5 mg: Each green film-coated, capsule shaped, side-notched, biconvex tablet debossed with M on one side of the tablet and PA2 on the other side contains: perindopril arginine 5 mg.
- 10 mg: Each green film-coated, round, biconvex tablet debossed with M on one side of the tablet and PA3 on the other side contains: perindopril arginine 10 mg.
Composition
2.5 mg, 5 mg and 10 mg tablets
Active principle: Perindopril arginine
Excipients:
2.5 mg: lactose monohydrate, magnesium stearate, maltodextrin, polyvinyl alcohol, povidone, silica, sodium starch glycolate, soya lecithin, talc, titanium dioxide and xanthan gum.
5 mg and 10 mg: FD&C blue #1, iron oxide yellow, lactose monohydrate, magnesium stearate, maltodextrin, polyvinyl alcohol, povidone, quinoline yellow aluminium lake, silica, sodium starch glycolate, soya lecithin, talc, titanium dioxide and xanthan gum.
Packaging
Each dosage strength is available in bottles of 30, 100 and 500 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Perindopril arginine |
| Chemical name: | (2S, 3aS, 7aS)-1-[(2S)-2-{[(2S)-1-(ethoxy-1-oxopentan-2-yl]amino}propanoyl]octahydro-1H-indole-2-carboxylic acid L-Arginine |
| Molecular formula and molecular mass: | C19H32N2O5.C6H14N4O2 542.67 g/mol |
| Structural formula: | 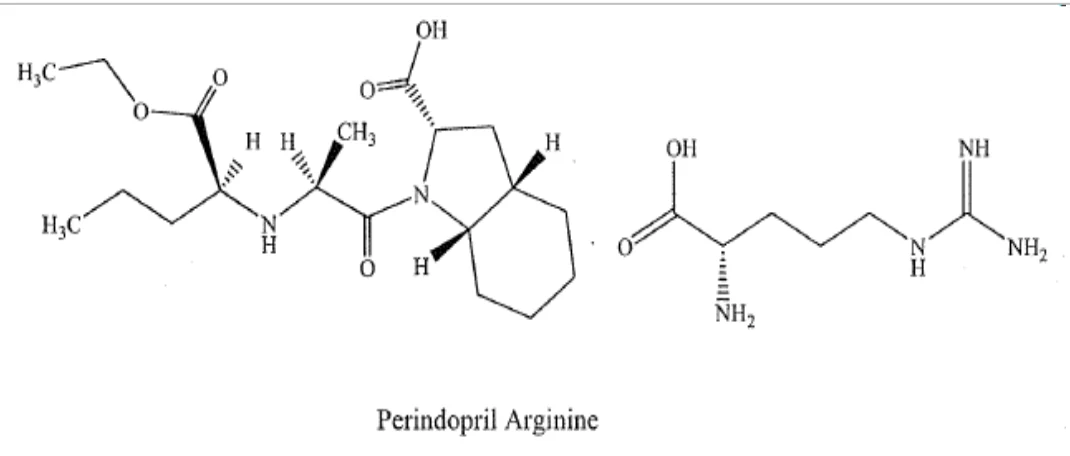 |
| Physicochemical properties: | White to off-white or light brown color powder. |
| Sr.no. | Name of solvent | Solubility (mg/mL) | Descriptive term (As defined in USP) |
| 1 | Methanol | 220 | Freely soluble |
| 2 | Ethanol | 37 | Soluble |
| 3 | Chloroform | < 0.1 | Practically insoluble |
| 4 | Dichloromethane | < 0.1 | Practically insoluble |
| 5 | Acetone | < 0.1 | Practically insoluble |
| 6 | Ethyl acetate | < 0.1 | Practically insoluble |
| 7 | Dimethyl formamide | < 0.1 | Practically insoluble |
| 8 | Dimethyl sulfoxide | 98 | Soluble |
| Quantitative aqueous pH solubility profile |
| Sr.no. | pH buffer | Solubility (mg/mL) | Descriptive term (As defined in USP) |
| 1 | pH 1.2 | 9 | Slightly soluble |
| 2 | pH 4.5 | 20 | Sparingly soluble |
| 3 | pH 6.0 | 31 | Sparingly soluble |
| 4 | pH 6.8 | 39 | Soluble |
| 5 | pH 8.0 | 38 | Soluble |
pH of 1% solution in water : 7.2 UV absorption maxima: 204 nm |
CLINICAL TRIALS
Comparative Bioavailability Studies
A double blinded, balanced, randomized, two-treatment, two-period, two-sequence, single-dose, crossover, comparative bioavailability study of Mylan-Perindopril Arginine (perindopril arginine) 10 mg tablets (Mylan Pharmaceuticals ULC) and PrCOVERSYL® (perindopril erbumine) 8 mg tablets (Servier Canada Inc.) was conducted with twenty-two (22) healthy adult Asian male subjects under fasting conditions. A summary of the bioavailability data is presented in the table below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Perindopril (1 x 10 mg perindopril arginine and 1 x 8 mg perindopril erbumine) From measured data Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/mL) | 161.0 167.0 (28.1) | 153.5 160.2 (31.9) | 104.9 | 101.0 to 109.0 |
AUCI (ng.h/mL) | 164.1 170.1 (27.7) | 156.0 162.8 (31.7) | 105.1 | 101.3 to 109.2 |
| Cmax(ng/mL) | 97.5 101.0 (27.0) | 96.9 101.1 (26.9) | 100.6 | 91.0 to 111.3 |
Tmax§ (h) | 0.8 (0.7- 2.0) | 0.7 (0.5 - 4.0) | ||
T1/2€ (h) | 1.1 (33.9) | 1.0 (19.6) | ||
* Mylan-Perindopril Arginine (perindopril arginine) 10 mg tablets (Mylan Pharmaceuticals ULC).
† Pr Coversyl® (perindopril erbumine) 8 mg tablets by Servier Canada Inc., Canada, were purchased in Canada.
§ Expressed as the median (range) only.
€ Expressed as the arithmetic mean (CV%) only.
Perindopril erbumine was first approved in France in 1988 and has been approved worldwide in 106 countries including European countries, USA and Japan. The efficacy and the safety of perindopril have also been established in a broad range of special patient populations.
Hypertension
Study demographics and trial design
The efficacy of perindopril erbumine in mild to moderate essential hypertension was demonstrated in two multicenter, double-blind, placebo-controlled U.S. studies (protocols PB and PC).
| Table 5 - Summary of patient demographics for pivotal US clinical trials in mild to moderate essential hypertension | ||||||||||
| Study | Trial Design | Dosage, Route of Administration, Duration | # Study subjects (randomized) | Mean age [range] | Gender (% ) M/F | |||||
| Efficacy studies | ||||||||||
| Protocol PB | Randomized, double-blind, placebo-controlled, parallel groups study preceded by a 4-week single-blind placebo run-in period | Placebo or Perindopril erbumine o.d. 2mg, 4mg, 8mg, or 16mg Oral route dose adjustment 12 weeks 24-month open extension | 293 (Efficacy: 258) Placebo: 58 Per 2mg: 62 Per 4mg: 57 Per 8mg: 59 Per 16mg: 57 | 53.1 [30-71] 51.1 [29-74] 56.3 [32-76] 51.2 [26-78] 51.2 [24-73] | 57.3/42.7 | |||||
| Protocol PC | Randomized, double-blind, parallel groups dose-ranging forced titration study preceded by a 4-week single-blind placebo run-in period | Placebo or Perindopril erbumine 4 to 16mg/day once- or twice-daily dosing Oral route Forced titration every 4 wks 16 weeks 24-month open extension | 289 Placebo: 59 once-a-day: 117 twice-a-day: 113 | 51.0 [23-72] 55.0 [27-82] 53.0 [22-79] | 63.0/37.0 | |||||
Efficacy results
The efficacy results from the two multicenter, double-blind, placebo-controlled U.S. studies (protocols PB and PC) evaluating the use of perindopril erbumine in patients with mild to moderate essential hypertension is presented in Table 6. In study PB, the blood pressure (BP) results are provided both at trough (measurements taken prior to dosing) and at peak (measurements taken 6 hrs post- dosing), while in study PC, only the trough (measurements taken prior to dosing) measurements of BP were collected. For both studies, the BP measurements were taken in the supine position.
Table 6 - Efficacy results for primary endpoints of pivotal placebo-controlled US clinical trials in mild to moderate essential hypertension
| Trough BP measurements | Peak BP measurements | T/P ratio | |||||||||||||||||||||||||||||
Baseline mean | Final visit mean | Mean change at final visit | BP variation Perindopril Placebo-subtracted | Baseline mean | Final visit mean | Mean change at final visit | BP variation Perindopril Placebo-subtracted | Variation at Trough / Variation at Peak | |||||||||||||||||||||||
| mmHg | mmHg | mmHg | mmHg | mmHg | mmHg | mmHg | mmHg | % | |||||||||||||||||||||||
| Study PB | |||||||||||||||||||||||||||||||
| Systolic BP | |||||||||||||||||||||||||||||||
| Placebo | 151.5 | 152.2 | 0.7 | -- | 153.8 | 150.9 | -2.9 | -- | -- | ||||||||||||||||||||||
| Per 2 | 153.6 | 150.9 | -2.7 | -3.4 | 154.7 | 147.2 | -7.5 | -4.6 | 73.9 | ||||||||||||||||||||||
| Per 4 | 153.8 | 149.1 | -4.7 | -5.4 | 154.1 | 144.9 | -9.21 | -6.3 | 85.7 | ||||||||||||||||||||||
| Per 8 | 152.5 | 141.3 | -11.21 | -11.9 | 153.0 | 137.1 | -15.91 | -13.0 | 91.5 | ||||||||||||||||||||||
| Per 16 | 154.2 | 144.6 | -9.61 | -10.3 | 154.6 | 139.1 | -15.51 | -12.6 | 81.7 | ||||||||||||||||||||||
| Diastolic BP | |||||||||||||||||||||||||||||||
| Placebo | 99.5 | 97.7 | -1.8 | -- | 99.6 | 94.8 | -4.8 | -- | -- | ||||||||||||||||||||||
| Per 2 | 99.3 | 94.8 | -4.5 | -2.7 | 100.4 | 93.2 | -7.2 | -2.4 | 112.5 | ||||||||||||||||||||||
| Per 4 | 101.2 | 95.3 | -5.91 | -4.1 | 99.8 | 91.4 | -8.41 | -3.6 | 113.9 | ||||||||||||||||||||||
| Per 8 | 100.2 | 92.3 | -7.91 | -6.1 | 100.1 | 89.0 | -11.11 | -6.3 | 96.8 | ||||||||||||||||||||||
| Per 16 | 100.0 | 92.7 | -7.31 | -5.5 | 99.1 | 86.9 | -12.21 | -7.4 | 74.3 | ||||||||||||||||||||||
| Study PC | |||||||||||||||||||||||||||||||
| Systolic BP | |||||||||||||||||||||||||||||||
| Placebo | 152.8 | 154.6 | 1.8 | -- | NM | NM | -- | -- | -- | ||||||||||||||||||||||
| Per 4-16 mg/d OD | 155.8 | 144.8 | -11.01 | -12.8 | NM | NM | -- | -- | -- | ||||||||||||||||||||||
| Per 4-16 mg/d BID | 151.8 | 140.4 | -11.41 | -13.2 | NM | NM | -- | -- | -- | ||||||||||||||||||||||
| Diastolic BP | |||||||||||||||||||||||||||||||
| Placebo | 100.5 | 97.9 | -2.6 | -- | NM | NM | -- | -- | -- | ||||||||||||||||||||||
| Per 4-16 mg/d OD | 100.3 | 92.1 | -8.21 | -5.6 | NM | NM | -- | -- | -- | ||||||||||||||||||||||
| Per 4-16 mg/d BID | 99.5 | 90.9 | -8.61 | -6.0 | NM | NM | -- | -- | -- | ||||||||||||||||||||||
- 1. Statistically significant difference between perindopril and placebo (p≤0.05)
NM Not measured – Blood pressure measurements at peak were not taken in Study PC.
OD Once-a-day
BID Twice-a-day
Congestive Heart Failure
Study demographics and trial design
The efficacy of perindopril erbumine in Congestive Heart Failure was based on two pivotal studies (NP00032 and NP05251) in the form of multicentre, randomized, double- blind placebo controlled studies in addition to the usual background therapy.
Table 7 - Summary of patient demographics for clinical trials in the indication of Congestive Heart Failure
| Study # | Trial design | Dosage, route of administration and duration | # Study subjects (randomized) | Mean age [range] in years | Gender (M/F) |
|---|---|---|---|---|---|
| Efficacy Studies | |||||
| NP00032 | Multicentre, randomized, double-blind placebo-controlled, parallel group study | Perindopril erbumine 2 mg then 4 mg (once-a-day), per os, baseline: diuretic or diuretic + digitalis therapy, 3 months | Perindopril: 61 Placebo: 64 | 59.5 ± 0.8 [37-75] | 75.2/24.8 |
| NP05251 | Multicentre, randomized, double-blind placebo-controlled, parallel group study | Perindopril erbumine 2 mg then 4 mg (once-a-day), per os, baseline: diuretic or diuretic + digitalis therapy, 6 months | Perindopril: 106 Placebo: 106 | 57.2 ± 10.2 [18-77] | 80.2/19.8 |
Efficacy results
The first pivotal trial (Report NP 32) was a phase III, multicentre, double-blind placebo controlled study. The aim of this trial was to assess the efficacy and the safety of perindopril erbumine (2-4 mg) once a day for 3 months, in 125 outpatients with chronic congestive heart failure (CHF) receiving baseline diuretic treatment with or without digitalis. Sixty-one (61) patients were randomly assigned to the perindopril group and 64 to the placebo group.
The main efficacy criterion was the number of patients with success on global efficacy assessment. Success was defined as the combination of the following items: improvement in overall HF severity score between Visit 0 (day 1) and visit 3 (day 90); increase in exercise test duration ≥10% between Visit 0 and Visit 3; stability or decrease in diuretic and/or digitalis dosing-regimen; no parenteral administration of diuretics or nitrates, no study premature discontinuation for the following reasons: patients death, adverse reaction, poor study drug compliance, patient lost to follow-up. Incomplete combinations of these items were considered as failures. The secondary efficacy criteria were Visit 3/Visit 0 evolutions in NYHA functional classes, overall HF severity scores, exercise test durations, cardiothoracic ratios (C/T) on chest X ray.
Concerning the efficacy results of the main criterion, the numbers (and percentages) of patients with success were 56% (34 out of 61) and 31% (20 out of 64) in perindopril and placebo groups respectively. This difference was statistically significant (p=0.006).
The safety assessment was obtained from numbers of patients with adverse events (AE) leading to study discontinuation, numbers of patients experiencing one or more AE (spontaneous and post-questioning complaints, except those already present on baseline records) and numbers of patients with clinically significant changes from baseline laboratory results.
This 3-month double-blind placebo controlled study showed that perindopril erbumine (2-4 mg per os once a day) resulted in an improvement of clinical signs and symptoms in patients with chronic mild to moderate congestive heart failure receiving baseline diuretic and digitalis therapy. The clinical improvement was confirmed by an increase in exercise test duration and was associated with a good clinical and laboratory safety profile.
Table 8 - Efficacy results for primary and secondary endpoints of studies in the indication of Congestive Heart Failure
| Endpoints | Associated value for perindopril | Associated value for placebo | p-value (FAS) |
| Study NP00032 | |||
Change from baseline: Exercise test duration | Perindopril: +130 ± 19 sec | Placebo: +23 ± 19 sec | p< 0.001 |
Secondary endpoints heart failure class total heart failure score cardiothoracic ratio | -0.6 ± 0.1 -3.1 ± 0.5 -0.023 ± 0.008 | -0.2 ± 0.1 -0.5 ± 0.5 -0.006 ± 0.005 | p= 0.017 p< 0.001 p= 0.071 |
| Study NP05251 | |||
Change from baseline: Exercise test duration NYHA class III-IV patients only | Perindopril: 75.4 ± 126.3 sec 106 ± 149 sec | Placebo: 46.9 ± 148.9 sec 1.2 ± 145 sec | p= 0.152 p= 0.023 |
The second pivotal trial (Report NP 5251) was also a phase III study. This trial entitled “Study of perindopril in chronic congestive heart failure. A six month multicenter double-blind study of perindopril versus placebo”. The aim of this study was to assess the efficacy and the safety of perindopril erbumine, 2-4 mg once a day for 6 months, in 212 outpatients with congestive heart failure (CHF) receiving baseline diuretic treatment with or without digitalis.
One hundred and six (106) patients were randomly assigned in the perindopril group and 106 to the placebo group.
The main efficacy criterion was the evolution of exercise test durations. The secondary efficacy criteria were: the evolution of overall HF severity scores and NYHA functional classes; the evolution of cardiothoracic ratios (C/T) on chest X ray; the evolution of left ventricular ejection fraction (LVEF), cardiac output (CO), maximal O2 consumption (VO2 max) and anaerobic threshold; the number of patients with success on global efficacy assessment.
The improvement of exercise test durations was more favourable in the perindopril group compared to the placebo group but the difference did not reach statistical significance; increases in durations were respectively 84.4 (126.4 SD) and 55.0 (148.5 SD) seconds (p=0.21) according to PP analysis. The p value was 0.15 as per ITT analysis.
The safety assessment was obtained from numbers of patients with adverse events (AE) leading to study discontinuation, numbers of patients experiencing one or more AE (spontaneous complaints, except those already present on baseline records) and numbers of patients with clinically significant changes from baseline laboratory results.
This 6-month double-blind placebo controlled study carried out in 212 patients showed that perindopril erbumine (2-4 mg per os once a day) resulted in an improvement of clinical signs and symptoms in patients with chronic congestive heart failure receiving baseline diuretic or diuretic and digitalis therapy. This improvement was clearly demonstrated and statistically significant in more severe patients.
Hypertensive and/or Post-MI Patients with Stable Coronary Artery Disease
Study demographics and trial design
The efficacy of perindopril erbumine in Reduction of cardiovascular risk in hypertension or post-myocardial infarction was based on one mortality/morbidity study (EUROPA trial, NP15314) which was a multi-centre, randomized, double-blind placebo controlled study looking at perindopril erbumine in addition to conventional therapy such as platelet inhibitors, β-blockers, lipid lowering agents, nitrates, calcium channel blockers or diuretics.
Table 9 - Summary of patient demographics for clinical trials in the indication of Reduction of the cardiovascular risk in hypertension or post-myocardial infarction
| Study # | Trial design | Dosage, route of administration and duration | # Study subjects (randomized) | Mean age [range] in years | Gender (M/F) |
| Mortality/morbidity study | |||||
NP15314 (EUROPA trial) | Multicentre, randomized, double-blind placebo-controlled study | perindopril erbumine 2mg then 4mg then titrated up to a 8mg (once-a-day), per os in addition to conventional therapy, 4.2 years | Perindopril: 6110 Placebo: 6108 | 60.1 ± 9.3 [26-89] | 85.4/14.6 |
The EURopean trial on reduction of cardiac events with Perindopril in stable coronary Artery disease (EUROPA) study was conducted in 12,218 patients (98% Caucasian) who had evidence of stable coronary artery disease without clinical heart failure. Patients had evidence of coronary artery disease documented by previous myocardial infarction more than 3 months before screening, coronary revascularisation more than 6 months before screening, angiographic evidence of stenosis (≥70% stenosis in ≥1 major coronary arteries), or a positive stress test in men with a history of chest pain. After a run-in period of 4 weeks during which all patients received perindopril 2 mg to 8 mg, the patients were randomly assigned to perindopril 8 mg once daily (n=6,110) or matching placebo (n=6,108), in addition to conventional therapy. The mean follow-up was 4.2 years.
The study examined the long-term effects of perindopril on time to first event of cardiovascular mortality, nonfatal myocardial infarction, or resuscitated cardiac arrest in patients with hypertension and/or previous myocardial infarction having stable coronary artery disease. Hypertension was defined as BP ≥140/90 mmHg, or being treated for hypertension, at baseline.
The mean age of patients was 60 years; 85% were male. The majority of patients were hypertensive (58%), had suffered a previous myocardial infarction (65%), or both. 92% were taking platelet inhibitors, 63% were taking β-blockers, 56% were taking lipid-lowering therapy,
43% were on nitrates, 31% were on calcium channel blockers, and 9% on diuretics.
Efficacy results
The EUROPA study showed that perindopril significantly reduced the relative risk for the primary endpoint events (ARR= -1.9%, Table 10). This beneficial effect is largely attributable to a reduction in the risk of nonfatal myocardial infarction. This beneficial effect of perindopril on the primary outcome, evident after about one year, became statistically significant after 3 years of treatment (Figure 1). Systolic and diastolic blood pressure reduction was 4.9 ± 16.3 mmHg and 2.4 ± 8.7 mmHg more in the perindopril group compared to the placebo group throughout the study (Figure 2).
Table 10 - Primary Endpoint and Relative Risk Reduction
Perindopril (N = 6,110) | Placebo (N = 6,108) | RRR [95% CI] | p | |
Combined Endpoint Cardiovascular mortality, nonfatal MI or cardiac arrest | 488 (8.0%) | 603 (9.9%) | 20% [9 to 29] | 0.0003 |
Component Endpoint Cardiovascular mortality Nonfatal MI Cardiac arrest | 215 (3.5%) 295 (4.8%) 6 (0.1%) | 249 (4.1%) 378 (6.2%) 11 (0.2%) | 14% [-3 to 28] 22% [10 to 33] 46% [-47 to 80] | 0.107 0.001 0.22 |
RRR: relative risk reduction; MI: myocardial infarction; CI = confidence interval
There were no significant differences in numbers of deaths between the groups (375 in the perindopril group and 420 deaths in the control group). However, ten patients died during the open run-in period of the study, of whom 7 from cardiovascular causes, including stroke. A total of 795 patients (out of 12,230; 6.5%) died during the study, 464 of the 795 died (58%) from a cardiovascular cause.
The outcome was similar across all predefined subgroups by age, underlying disease or concomitant medication (Figure 3).
Figure 1 - Time to First Occurrence of Primary Endpoint
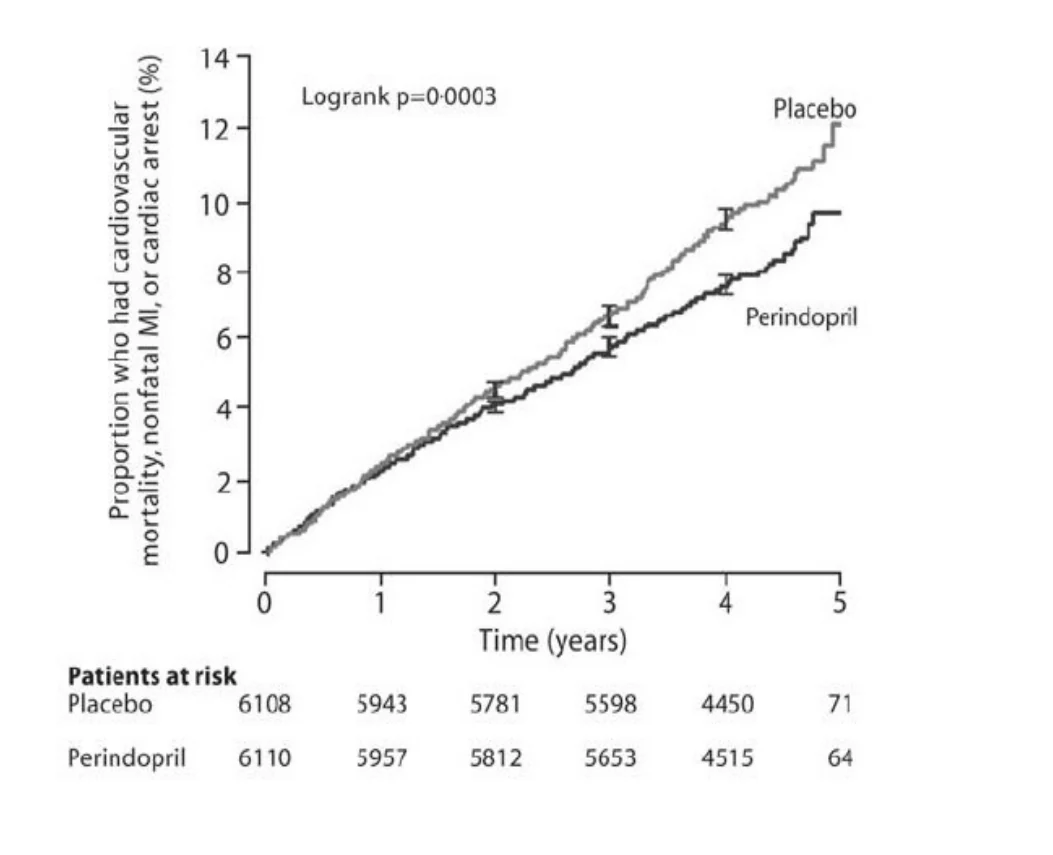
Figure 2 - Systolic and Diastolic Blood Pressure for the perindopril and placebo Treatment Arms (Double-blind treatment period)
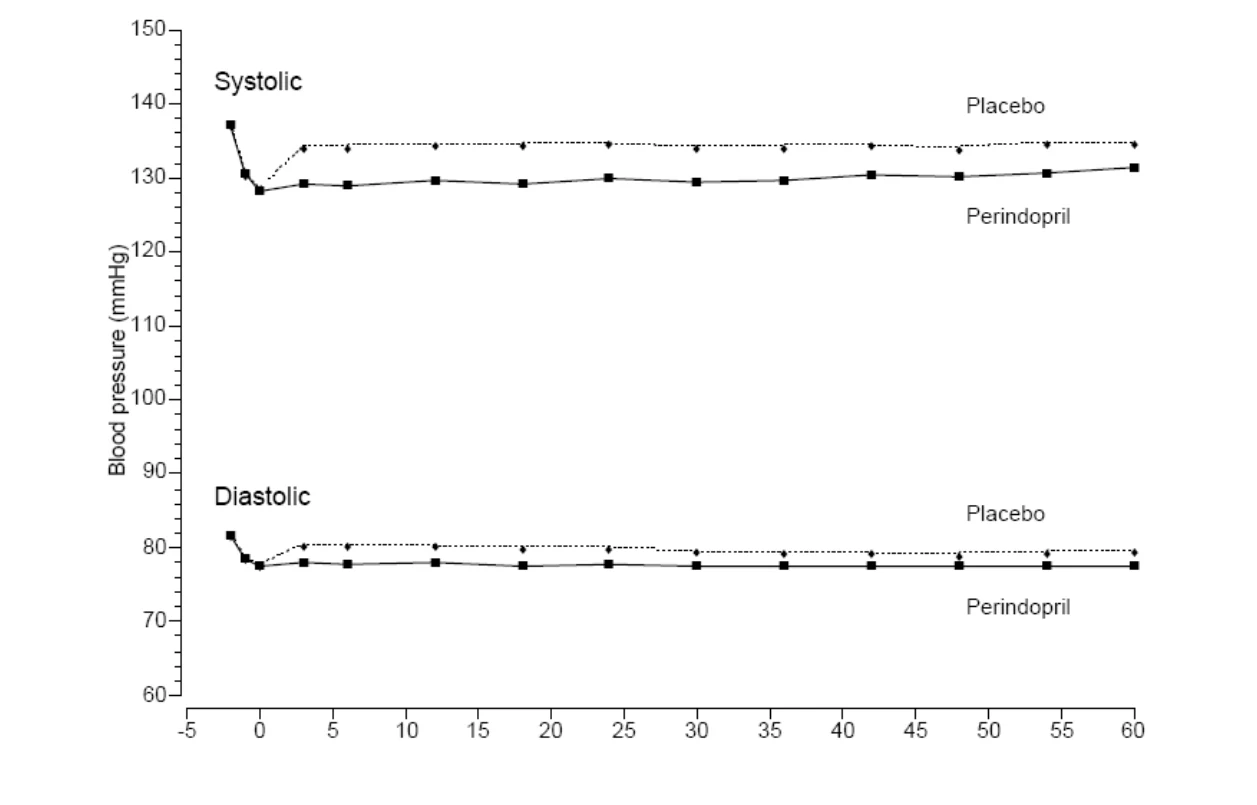
Figure 3 - Effect of Treatment with perindopril in Predefined Subgroups
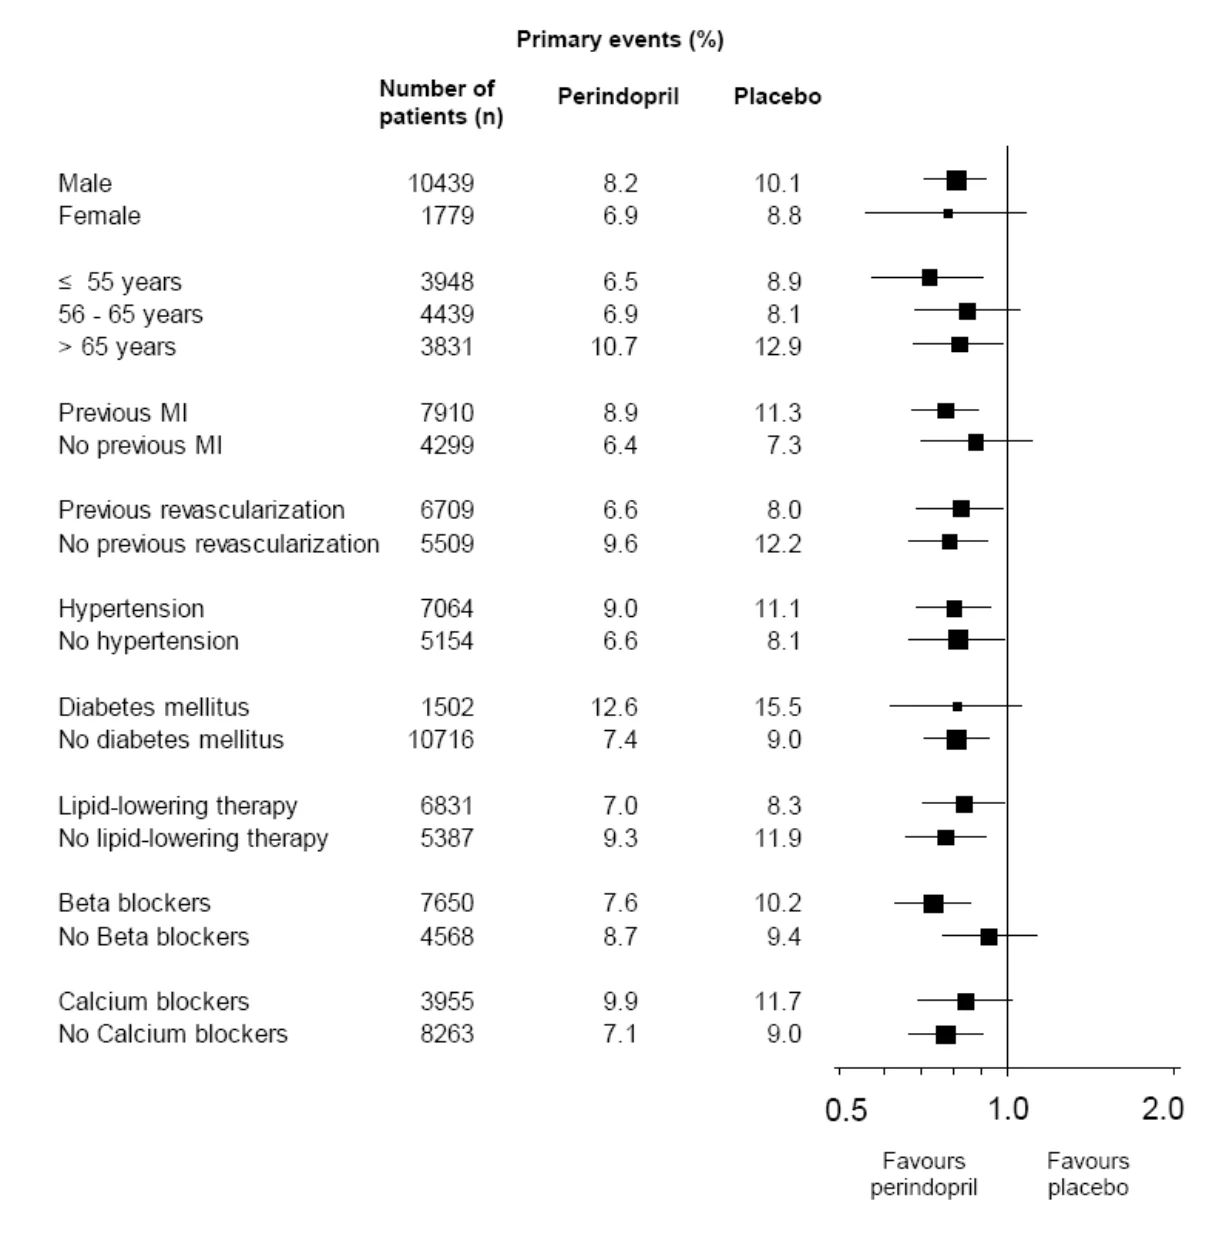
DETAILED PHARMACOLOGY
Mechanism of action
In Vitro Studies
Perindopril was shown to be an inhibitor of angiotensin converting enzyme (ACE) in both plasma and tissue. Perindoprilat, the diacid form of perindopril, exhibited greater inhibition of ACE activity than perindopril (IC50 = 2 x 10⁻⁹M and 800 x 10-9M respectively). The active diacids of perindopril (perindoprilat) and ramipril (ramiprilat) proved to possess a similar inhibitory potency against rat plasma converting enzyme (IC50 = 2 to 3 x 10⁻⁹M). Both diacids were more active than enalaprilat or captopril (IC50 = 1 to 6 x 10⁻⁸M).
In Vivo Studies
Following oral dosing of perindopril to normotensive (0.03 to 1 mg/kg) or hypertensive (0.3 to 3 mg/kg) rats, plasma ACE inhibition was assessed in vivo by the decrease in pressor response to intravenous angiotensin I. Orally administered to conscious dogs, perindopril produced a dose-dependent reduction (34% at 0.1 mg/kg, 60% at 0.3 mg/kg and 92% at 1 mg/kg) of angiotensin I
(150 ng/kg IV) pressor response, but had no effect on angiotensin II (100 ng/kg IV) response. In normotensive rats, plasma ACE was maximally inhibited (≥ 90%) by perindopril (1, 4 or 8 mg/kg p.o.) one hour following administration, then returned to control levels 24 hours later. After 4 weeks of oral treatment (10 mg/kg) in stroke-prone spontaneously hypertensive rats, converting enzyme inhibition was mostly demonstrated in kidney (96%), aorta (64%), heart (52%), lung (36%) and brain (26%). Perindopril orally administered at 1 mg/kg to sodium replete spontaneous hypertensive rats was shown to be more potent than enalapril (1 mg/kg) both in terms of intensity (91% of inhibition versus 64%, 4 hours after dosing) and duration of action (68% of inhibition versus 12%, 12 hours after dosing).
In human subjects perindopril at single oral doses of 4 to 8 mg/day produced 80% inhibition of plasma ACE activity between 2 and 8 hours post-dose, with 40 to 60% inhibition persisting at 24 hours post-dose. Multiple oral doses of perindopril over 7 days (4 to 8 mg/day) confirmed the inhibitory effect on plasma ACE and showed that it produces corresponding decreases in angiotensin II with significant increases in plasma renin activity.
TOXICOLOGY
Acute toxicity studies
| Species | Route of administration | Sex | LD50 (mg/kg) |
|---|---|---|---|
| Mouse | IV | M F | 704 (693-715) 679 (667-690) |
| Mouse | PO | M F | > 2 500 > 2 500 |
| Rat | IV | M F | 323 (315-331) 423 (407-440) |
| Rat | PO | M F | > 3 000 > 3 000 |
| Dog | PO | M F | > 1 600 > 1 600 |
No mortality occurred during the oral studies in the rat and mouse.
Signs of toxicity observed in animals treated intravenously were as follows:
- Convulsive symptoms and severe dyspnoea in mice
- Considerable hypermobility in rats
- Death, by respiratory arrest, occurring within minutes of the injection.
In the dog treated orally with increasing doses of perindopril erbumine, vomiting, reduction in activity, salivation and tachycardia were observed without mortality.
Chronic Toxicity Studies
| Species | Duration of Treatment | Number of Animals/Group | Administrat ion Route | Dosage mg/kg/day | Information |
|---|---|---|---|---|---|
| Rat (OFA) | 3 months | 10 M + 10 F | PO | 0, 1, 5, 30 | 1 mg/kg: non-toxic dose 5 mg/kg: effects on growth (mean weight gain compared to the control group was -16% and -4% in males and females respectively (Males: significant decrease from W9; females: no statistical difference)) and blood urea (+53% and +5% in males and females respectively with reference to the control groups). 30mg/kg: effects on red blood cell parameters (-12% and -9% in males and females respectively with reference to the control groups) and clear effects on mortality (2 deaths (1M, 1F) in the treated group, no death in the control group); growth (mean weight gain compared to the control-group was -25% and -10% in males and females, respectively (Males: significant decrease from W3 ; females : no statistical difference)); food consumption (-5% and - 8% with reference to the control groups in males and females respectively) : blood urea ( +244% and +104% with reference to the control group in males and females respectively) and creatinine (with reference to the control groups the increases ranged between +7.2% and +42% in males and between +4% and +42% in |
| Species | Duration of Treatment | Number of Animals/Group | Administrat ion Route | Dosage mg/kg/day | Information |
|---|---|---|---|---|---|
females). Tubular nephritis observed in 4 animals out of 20. | |||||
| Rat (Wistar) | 6 months | 20 M + 20 F | PO | 0, 1, 3, 12 | Slight reduction in food consumption at 3 mg/kg and 12 mg/kg (Males: in the 3 mg/kg/day group, there was a small transitory fall in food consumption in weeks 3 (-13%), 6 (-10%) and 7 (-8%). After week 7, the mean food consumption fluctuated around the control value ± 6%. In the 12 mg/kg/day group, the transitory fall in food consumption was particularly pronounced from W2 to W7: -8 to -16%. Then the value fluctuated between -6% to +1% around the control value. Females: no differences during the study). Marked polydipsia in all groups accompanied by polyuria, more so in males. Water consumption-relative to the control group-: Males : 1mg/kg/day : +29% to +51% from W9 3mg/kg/day : +93% to +139% from W7 12 mg/kg/day : +90% to +129% from W5 Polydipsia reversible as shown by the recovery study. Females: no significant difference between the treated groups versus the control group. Increase in water consumption in 1 and 3 mg/kg/day groups (+11 and +9% respectively) and moderate fall in consumption in the higher group (-2,8%) from W1 to W26. Urinary volume-relative to the control groups-: |
Males : 1 mg/kg/day : +93% 3 mg/kg/day : +108% 12 mg/kg/day : +63% | Females : 1 mg/kg/day : +49% 3 mg/kg/day : +59% 12 mg/kg/day : +17% |
In the male: biochemical changes related to disturbances in renal function. Throughout the study : Mean blood urea-relative to the control groups-: |
Males : 1 mg/kg/day : +19% 3 mg/kg/day : +226% 12 mg/kg/day : +363% | Females : 1 mg/kg/day : +1.5% 3 mg/kg/day : +8.7% 12 mg/kg/day : +15% |
| Mean plasma creatinine-relative to the control groups- |
Males : 1 mg/kg/day : -0.8% 3 mg/kg/day : +17% 12 mg/kg/day : +27% | Females : 1 mg/kg/day : -1.4% 3 mg/kg/day : -1.4% 12 mg/kg/day : +1.1% |
| Mean plasma sodium-relative to the control groups- |
Males : 1 mg/kg/day : -2.9% 3 mg/kg/day : -3.9% 12 mg/kg/day : -2.9% | Females : 1 mg/kg/day : -1.7% 3 mg/kg/day : -1.2% 12 mg/kg/day : +1.0% |
| Mean plasma potassium-relative to the control groups- |
Males : 1 mg/kg/day : +2.9% 3 mg/kg/day : +13.1% 12 mg/kg/day : +20% | Females : 1 mg/kg/day : +1.8% 3 mg/kg/day : +1.5% 12 mg/kg/day : +2.4% |
| Mean renal excretion of creatinine-relative to the control groups- |
| Species | Duration of Treatment | Number of Animals/Group | Administrat ion Route | Dosage mg/kg/day | Information |
|---|
Males : 1 mg/kg/day : +14% 3 mg/kg/day : +9.1% 12 mg/kg/day : +9.1% | Females : 1 mg/kg/day : +1.3% 3 mg/kg/day : +19% 12 mg/kg/day : +6.3% |
| Mean renal excretion of sodium-relative to the control groups- |
Males : 1 mg/kg/day : +32% 3 mg/kg/day : -15% 12 mg/kg/day : -33% | Females : 1 mg/kg/day : +6.5% 3 mg/kg/day : +0.8% 12 mg/kg/day : -15% |
| Mean renal excretion of potassium-relative to the control groups- |
Males : 1 mg/kg/day : +48% 3 mg/kg/day : +30% 12 mg/kg/day : +18% | Females : 1 mg/kg/day : +43% 3 mg/kg/day : +44% 12 mg/kg/day : +15% |
Increase in incidence of interstitial nephritis and tubular nephritis. Interstitial nephritis: |
| Control | 1 mg/kg/day | 3 mg/kg/day | 12 mg/kg/day | |
| Males | 0 | 0 | 3/16 | 10/15 |
| Females | 0 | 0 | 0 | 0 |
| Tubular nephritis: |
| Control | 1 mg/kg/day | 3 mg/kg/day | 12 mg/kg/day | |
| Males | 0 | 0 | 1/16 | 5/15 |
| Femal es | 0 | 0 | 0 | 0 |
Increase of kidney weight, in particular, at high doses (Males: increase in the treated groups relative to the control group by +6%, +16% and +15% respectively, statistically significant in the two higher dose groups. Females: increase of +6%, +4% and +9% respectively in the 3 doses groups, statistically significant in the 12 mg/kg/day group). All these renal function disorders were reversible. Reversible anemia and lymphocytosis in the males at the intermediate and high doses. Red cells count (RCC) : Males: 3 mg/kg/day: decrease from -2% to -7% (W14 statistically significant); 12 mg/kg/day: statistically significant decrease relative to the control group from -9% to -11%. Females: fall (-5%) in the RCC only in W26 at the highest dose. Lymphocytes: Males: 3 mg and 12 mg/kg/day: statistically significant increase of + 15% relative to the control group. Females: lymphocyte count comparable in all groups. Dose dependent increase in blood glucose (throughout the treatment period, males: +19% and +23%, females: +5.6% and +3.6% in the 3 and 12 mg/kg/day groups respectively, relative to the control group) and cholesterol (Females: the groups remained comparable throughout the study. Males: the control and the 1 mg/kg/day groups were comparable throughout the study; in the 3 and 12 mg/kg/day groups respectively, the increase in blood total cholesterol was +15% and +19% relative to the control group). Moderate hypoproteinemia (Males: the maximum fall was observed in W14, i.e.-3%, -7% and -6% relative to the control group in the 3 |
| Species | Duration of Treatment | Number of Animals/Group | Administrat ion Route | Dosage mg/kg/day | Information | |
|---|---|---|---|---|---|---|
treated groups respectively. Females: the maximum effect (-3%) was noted in the 3 mg/kg/day group in W14 and W26). Reduction in heart weight -relative to the control groups-: | ||||||
Males : 1 mg/kg/day : -12% 3 mg/kg/day : -23% 12 mg/kg/day : -10% | Females : 1 mg/kg/day : -8% 3 mg/kg/day : -9% 12 mg/kg/day : -10% |
all statistically lower than the control group. In all treated groups reversible after cessation of treatment. Emphysematous bullae more frequent in the lungs of treated animals: |
| Control | 1 mg/kg/day | 3 mg/kg/day | 12 mg/kg/day | |
| Males | 0 | 2/15 | 13/16 | 13/15 |
| Females | 4/15 | 09/15 | 11/15 | 13/15 |
| Rat (Fischer 344) | 18 months | 20 M + 20 F | PO | 0, 0.75, 2, 7.5 | At all doses: delay in growth (Males : diminution of weight gain relative to the control group throughout the study ranged between -9 to -16 % in the 0.75 mg/kg/day group and between -7% and - 11 % in the 2 higher dose groups. Females: -4 % to - 6 % relative to the control group from the second week of treatment, with a maximum of -11%, -10% and -7% in the 0.75, 2 and 7.5 mg/kg/day groups respectively) with a transient reduction in food intake (not exceeded -16 % in males, and -19 % in females). Dose dependent increase in blood urea (Males: during the first sequence of blood samples (12th week), increases of + 12%, +36%, +87% in the 0.75, 2, 7.5 mg/kg/day groups respectively versus the control group; at the end of the study the increase was + 136%, +225%, +254% respectively. Females : during the first sequence of blood samples -8%, +16% and +37% in the 3 treated groups respectively; at the end of the study the increase was +41%, +76% in the 2 lower dose groups and +125% at W53 for the higher dose group) and creatinine (Males : at the end of the study, the value reached + 21%, + 37%, + 37% in the 0.75, 2, 7.5 mg/kg/day groups respectively versus the control group. Females: due to a large number of missing values, no statistical heterogeneity was noted between the groups) and urinary sodium elimination (Males: differences with the control group reached +73% to +129%, + 34% to +82%, and +47% to +49% in the 3 treated groups respectively. Females: differences with the control groups reached +57% to +142%, +57% to +132% and +38% to +86% in the 3 treated groups respectively). The histological study confirmed the existence of renal lesions with signs of chronic nephropathy at high doses. Anemia noted (hemoglobin: Males: a significant reduction was noted in the treated animals in comparison with the control group, -3% from W52 onwards, -6 % to -8%, -3% to -9% in the 3 treated groups respectively. Females: the reduction was significant (-5%) only in the highest dose group). |
| Rat (Wistar) | 14 weeks | S-: 7 groups of 18M N: 5 groups of 12 M S+: 5 groups of 12 M | PO | S-: 0, 0.5, 1, 2, 4, 8, 16 N and S+: 0, 4, 8, 16, 32 | S-: renal symptoms appeared from 2 mg/kg S+: 32 mg/kg had no major renal effect even on histological findings. Reversibility of effects was improved by a return to |
| Species | Duration of Treatment | Number of Animals/Group | Administrat ion Route | Dosage mg/kg/day | Information |
|---|---|---|---|---|---|
| normal sodium diet | |||||
| Monkey (cynomolgus) | 3 months | 3 M + 3 F | PO | 0, 0.5, 2.5, 10 | All groups: loss of appetite Highest group only: reduction in body weight relative to the body weight before treatment (In males weight loss ranged between -21.9% to +5.2% in the control group and between -6.3% to -12.2% in the treated group. In females between -1.7% to -5.9% in the control group and between -6.7% to -12.9% in the treated group; no significant difference between the control-and the treated-groups). Histological examination (kidney and liver particularly) only showed abnormalities due to infectious agents |
| Monkey (cynomolgus) | 1 year | 6 M + 6 F (control and high dose groups) 4 M + 4 F (low and medium dose groups) | PO | 0, 1, 4, 16 | In the high dose group, 1 F and 2 M died or had been sacrificed for ethical reasons, due to significant diarrhea. Otherwise, the effects of treatment were deemed minor and only a reduction in body weight of treated males was drug related (i.e. 8%, 16% and 9% lower than control values for the 1, 4 and 16 mg/kg/day groups respectively). |
| Monkey (cynomolgus) | 27 to 63 days according to individual biochemical profile | 2 M + 2 F (control) 4 M + 4 F (treated) | PO | Initially 100 mg | At high doses, the product induced osmotic nephrosis-type renal lesions which were completely reversible upon cessation of treatment. |
| Dog (Beagle) | 6 months | 6 M + 6 F (control and high dose groups) 4 M + 4 F (other groups) | PO | 0, 1, 5, 25 | Changes in body weight (over the whole treatment period, relative to the control groups, the body weight was +39%, +6.8%, +11.3% in males and - 27%, -14%, -79% in females in the 1, 5, 25 mg/kg/day groups respectively). Fall in blood pressure, in particular, diastolic blood pressure at the high dose. Over the whole treatment period, mean DBP fall (measured in mmHg) relative to the control groups was : |
| 1.5 h after dosing | 24 h after dosing | |
| Males | -22% | -17% |
| Females | -23% | -17% |
S-: Low sodium diet N: Normal sodium diet S+: High sodium diet
Carcinogenicity
No evidence of carcinogenicity has been observed during the 104-week study in the B6 C3 F1 mouse treated with oral doses of 0.75, 2 and 7.5 mg/kg/day perindopril erbumine.
No evidence of carcinogenicity has been observed during the 104-week study in the Fischer 344 rat treated with oral doses of 0.75, 2 and 7.5 mg/kg/day perindopril erbumine.
At least one ACE inhibitor has caused an increase in the incidence of oxyphilic renal tubular cells and oncocytomas in rats. The potential of ACE inhibitors to cause this effect in man is unknown. Moreover, the progression of oxyphilic cells to oncocytomas is rare in humans and when it does occur, it is considered to be benign.
Genotoxicity
Perindopril erbumine was not shown to induce genic mutation (AMES test and mouse lymphoma test) nor chromosomal mutation (in vivo and in vitro clastogenicity tests and micronuleus test) in prokaryotes and eukaryotes, nor primary change of yeast DNA (gene conversion test).
Reproductive and Developmental Toxicity
Fertility Studies
Studies were performed by administrating perindopril erbumine by the oral route. Pivotal studies are tabulated hereafter.
| Species | Number of Animals/ Group | Dosage mg/kg/day | Administration Route | Information |
|---|---|---|---|---|
| Rat (Wistar) | 12 M + 24 F | 0, 1, 3, 10 M: 80 days before mating to sacrifice. F: 14 days before mating to PR7 | PO | Males: Reduction in growth with no disturbance of the reproductive function. Mean weight gain relative to the control group was -30%, -36%, -35% for the 1, 3, 10 mg/kg/day groups respectively. Females: Reduction in growth at the high dose. During treatment before mating, mean weight gain relative to the control group ranged between - 10% to -26%. Over the period of gestation during which the treatment was administered the mean weight gain relative to control was -23%, -21% and -48% in the 1, 3 and 10 mg/kg/day groups respectively. Reduction in the number of ovules produced in the three groups. The mean number of corporea lutea ranged between 9.4 (-15% relative to the control group) and 10.0 (-9.9%). No abnormality related to the migration of the egg, its implantation or embryonic and fetal development was demonstrated. |
| Rat (Wistar) | 30 M + 30 F | 0, 1, 2, 4 M: 80 days before mating to sacrifice. F: 14 days before mating to PR20 or up to parturition | PO | Growth in the animals was retarded. Fertility of males (100%, 93% and 90% in the 1, 2, 4 mg/kg/day groups respectively versus 97% in the control group) and libido of females were reduced at the intermediate and high doses (the percentage of effective mating of the GO female breeders in the 2 higher dose groups was 0.97 and 0.93 respectively versus 1.0 in the control group). There was no effect on the fertility of females. The fetus of dams treated with the high dose presented an increased frequency of dilatation of the renal pelvis (2.0%, 2.5% and 7.1% in the 1, 2, 4 mg/kg/day groups respectively, versus 3.3% in the control group) and delayed ossification of the sternum (18%, 20%, 38% in the 3 treated groups respectively), though there was no teratogenic effect. The mortality of the G1 pups was increased at the high dose (The mortality at birth was not alterated by the treatment. It was 0% in the lower dose groups and 1.7% in the higher dose group versus 0% in controls. The mortality between D1 and D21 of lactation was 0%, 1.8%, 5.4% in the 1, 2, 4 mg/kg/day groups respectively, versus 3.6% in the control group) and their growth and physical development were retarded. These changes did not affect the reproductive capacity of the G1 generation, the gestation of the G1 females and the characteristics of the G2 pups. |
| Species | Number of Animals/ Group | Dosage mg/kg/day | Administration Route | Information |
|---|
PR (n) = Days of pregnancy; G = Generation; D = Day
Teratogenicity Studies
| Species | Number of Animals/G roup | Dosage mg/kg/day | Administratio n Route | Information |
| Mice (NRMI) | Between 31 and 37 inseminated F | 0, 1, 4.5, 20 From PR6 to PR15 | PO | Apart from a slight, though non-significant reduction in body weight of the dams treated with the high dose between the 6th and 15th days of gestation ( relative to the control group: -14.9%), no abnormality, in particular, no embryotoxicity or teratogenicity were observed. |
| Rat (Wistar) | 25 treated F | 0, 1, 4, 16 From PR6 to PR7 | PO | Dams: increase in water consumption.(during the first week of treatment, the mean increase was +4.0, +5.0 and +3.9 g/day for the 1, 4, 16 mg/kg/day groups treatment respectively, i.e. +567%, +733%, + 550% relative to the control group ; during the second week of treatment, the increase in water consumption was +39%, +42% and +165% relative to the control group in the 3 treated groups respectively). The in-utero development of the fetus was unchanged though there was a higher incidence of hydronephrosis which appeared to be dose dependent (2 cases in the low and intermediate doses, 5 in the high dose) and a delayed ossification in the high group only (i.e. 11.5%, 15.5%, 21.1% in the 3 treated groups respectively, versus 11.6% in the control group). No sign of teratogenicity. |
| Rabbit (New Zealand) | Control C1: 18 F Control C2: 27 F treated: 18 F 27 F 24 F | Drink water without NaCl: 0 Drink water with 0.9% NaCl: 0 0.5 1.5 5.0 From PR6 to PR18 | PO | Under these conditions, there was no maternal toxicity or any embryotoxic or teratogenic effect on the fetuses. A slight increase in post-implantation losses at the highest dose (i.e. 21.2% versus 11% in the control group) was seen. |
| Monkey (cynomolg us) | 10 F pregnant 12 F pregnant 12 F pregnant 12 F pregnant | 0 1 4 16 From PR 20 to PR 50 | PO | 2 animals in each group died following episodes of diarrhea. At 16 mg/kg, maternal toxicity resulted in a reduction in the water consumption (- 45% relative to the control group), during the treatment period. Nevertheless, no adverse effects on the fetuses were noted. |
PR (n) = nth day of pregnancy
No teratogenic effects of perindopril were seen in studies of pregnant rats, mice, rabbits and cynomolgus monkeys. On a mg/m2 basis, the doses used in these studies were 6 times (in mice),
670 times (in rats), 50 times (in rabbits) and 17 times (in monkeys) the maximum recommended human dose (assuming a 50 kg adult). On a mg/kg basis, these multiples are 60 times (in mice),
3,750 times (in rats), 150 times (in rabbits) and 50 times (in monkeys) the maximum recommended human dose.
Post-Natal Studies
| Species | Number of Animals/G roup | Dosage mg/kg/day | Administratio n Route | Information |
| Rat (Wistar) | 4 groups of 30 mated F/group | 0 1 2 3 Once/day 7 days/week From PC 15 to PP 21 | PO | At the high dose, low but significant reductions in food consumption (in female (F0) the decrease in food consumption ranged between -3.8% to -9.3% relative to the control group). All the other parameters related to the dams or pups were unchanged. |
| Rat (Wistar) | 4 groups 25 F 25 F 25 F 25 F | 0 1 4 16 sodium content in rat-feed: 0.65 g.kg.-1 Once/day 7 days/week From PR 17 up to sacrifice | PO | At the intermediate and high doses, maternal toxicity was observed at the end of gestation and caused a reduction in food consumption (24.1 g/day, 22.0 g/day and 20.5 g/day in the 1, 4 and 16 mg/kg/day groups respectively, i.e. -4%, -12%, -18% relative to the control group) and weight gain (i.e. -3.7 g and +1.6 g in the dose groups respectively versus + 9.1 g in the control group). Dystocia caused the death of 4 F during parturition at the high dose. There were also significantly fewer neonates born at all 3 doses (i.e. at birth, mortality was 0.4% in the young born of control females and 3.2%, 4.5% and 2.3% in the young born of females groups 1, 4 and 16 mg/kg/day respectively), although the average body-weight of the G1 pups was unchanged. During the lactation period, the intermediate and high doses showed a dose related reduction in the weight gain of the G0 dams (i.e. weight gain was + 36.9 g, +24.2 g, +17.3 g and +8.4 g for the control, 1, 4 and 16 mg/kg/day groups respectively, i.e. -34%, -53%, -77% respectively relative to the control group), and of the G1 pups (i.e. weight gain during this period was +35.5 g, +36.1 g, +28.6 g and +22.8 g in the control, 1, 4 and 16 mg/kg/day groups respectively, i.e. +1.7%, -19%, -36% respectively relative to the control group), with an increase in post natal mortality (i.e. the viability index at the end of treatment was 0.95, 0.87, 0.79 and 0.43 in the control, 1, 4 and 16 mg/kg/day groups respectively). At the highest dose, there was delayed physical and behavioural development in the G1 pups (i.e. the percentage of success in the test of detachment of the pinna on LA2 was 56%, 24.5% and 0% in the control, 1 and 16 mg/kg/day groups respectively), reduced fertility in the G1 dams (determined by the percentage of pregnant females with respect to mated females, 100% in the control and 1 mg/kg/day groups and 95% and 74% in the 4 and 16 mg/kg/day groups respectively), polyuria in the G1 animals (Males: the urinary volume was 16.9 ml/24h in the control group compared to 37.4 ml/24h for the 16 mg/kg/day, i.e. an increase of 121%) and renal lesions in the G1 parents (diffuse nephropathies were found in 5% of the males in the 1 mg/kg/day group, and in 25% of the females and 60% of the males at the higher dose; sponge kidneys occurred with an incidence of 20% and 15% in males and females respectively in the higher dose group), though all these effects disappeared in the G2 generation. |
| Rat (Wistar) | 2 groups: 8 mated F 18 mated F | 0 16 Sodium content in rat-feed: 1.9.g.kg-1 Once/day 7 days/ week From PR 17 up to sacrifice of the dams | PO | Under those conditions of sodium content in feed, the product was much less toxic than in the previous study: although the growth of the dams was slower at the end of gestation (the gain in weight in the control group was +33.6 g compared with +27.9 g in the treated group, i.e. -17%), it became similar to that of the controls during lactation. The mean number of pups was lower (i.e. 12.8% per female in the control group compared with 11.2% in the treated group) and the post-natal mortality was 10 times higher, though body-weight and urine output of the G1 pups were normal and the renal lesions encountered were those that are normally observed in this strain. |
PC (n) = Days post-coitum; PP (n) = Days post-partum; PR (n) = Days of pregnancy; G = Generation
REFERENCES
- 1. Atkinson J. Perindopril. Cardiovascular Drug Reviews 1992;10(4):446-471
- 2. Chrysant SG, Mc Donald RH, Wright JT, Barden PL, Weiss RJ. Perindopril as monotherapy in hypertension: a multicenter comparison of two dosing regimens. Clin Pharmacol Ther 1993;53(4):479-484.
- 3. Degaute JP, Leeman M, Desche P. Long-term acceptability of perindopril: European multicenter trial on 856 patients. Am J Med 1992;(suppl 4B):84S-90S.
- 4. Denolle T, Renucci JF, Poggi L. 47 351 hypertendus traités par Coversyl en médecine générale pendant 1 an. Rev Prat Med Gen 1993;7(212 suppl):5-34.
- 5. Desché P, Antony I, Lerebours G, Violet I, Robert S, Weber C. Acceptability of perindopril in mild-to-moderate chronic congestive heart failure. Results of a long-term open study in 320 patients. Am J Cardiol 1993;71:61E-68E
- 6. Devissaguet JP, Ammoury N, Devissaguet M, Perret L. Pharmacokinetics of perindopril and its metabolites in healthy volunteers. Fundam Clin Pharmacol 1990; 4:175-189.
- 7. Dratwa M, Sennesael J, Taillard F, Baguet F, Suc JM, Lins RL, Lameire N. Long term tolerance of perindopril in hypertensive patients with impaired renal function. J Cardiovasc Pharmacol 1991;18(suppl 7):S40-S44.
- 8. Harrap SB, Nicolaci JA, Doyle AE. Persistent effects on blood pressure and renal haemodynamics following chronic angiotensin converting enzyme inhibition with perindopril. Clin Exp Pharmacol Physiol 1986;13:753-765
- 9. Lechat P, Garnham SP, Desché P, Bounhoure J-P. Efficacy and acceptability of perindopril in mild-to-moderate chronic congestive heart failure. Am Heart J 1993;(3 part 2):798-806
- 10. Louis WJ, Conway EL, Krum H, Workman B, Drummer OH, Lam W, Phillips P, Howes LG, Jackson B. Comparison of the pharmacokinetics and pharmacodynamics of perindopril, cilazapril and enalapril. Clin Exp Pharmacol Physiol 1992;19(suppl 19): 55-60
- 11. Speirs C, Wagniart F, Poggi L. Perindopril postmarketing surveillance: a 12 month study in 47 351 hypertensive patients. Br J Clin Pharmacol 1998;46:63-70
- 12. Todd PA, Fitton A. Perindopril - A review of its pharmacological properties and therapeutic use in cardiovascular disorders. Drugs 1991;42(1):90-114
- 13. PrCOVERSYL®, SERVIER CANADA INC., Product Monograph dated: February 12, 2018, Control No.: 212086.