


Product Monograph - Mylan-Telmisartan HCTZ
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| oral | tablet 80/12.5 mg and 80/25 mg | corn starch, iron oxide red (for 80/12.5 mg tablet only), iron oxide yellow (for 80/25 mg tablet only), lactose monohydrate, magnesium stearate, mannitol, meglumine, microcrystalline cellulose, povidone, sodium hydroxide, sodium starch glycolate |
INDICATIONS AND CLINICAL USE
MYLAN-TELMISARTAN HCTZ (80 mg telmisartan/12.5 mg hydrochlorothiazide) is indicated for:
- treatment of mild to moderate essential hypertension in patients in whom combination therapy is considered appropriate.
MYLAN-TELMISARTAN HCTZ (80 mg telmisartan/25 mg hydrochlorothiazide) is indicated for:
- treatment of patients whose blood pressure is not adequately controlled by MYLAN-TELMISARTAN HCTZ 80/12.5 mg or patients who have been previously stabilised on telmisartan and hydrochlorothiazide given separately.
These fixed-dose combinations are not indicated as initial therapy (see DOSAGE AND ADMINISTRATION).
Geriatrics (> 65 years of age):
No dosage adjustment is necessary. It should be recognized, however, that greater sensitivity in some older individuals cannot be ruled out.
Pediatrics (< 18 years of age):
Safety and efficacy of Telmisartan/Hydrochlorothiazide Tablets have not been established in children and in adolescents up to 18 years.
CONTRAINDICATIONS
MYLAN-TELMISARTAN HCTZ (telmisartan/hydrochlorothiazide) is contraindicated in:
- Concomitant use of angiotensin receptor antagonists (ARBs) – including the telmisartan component of MYLAN-TELMISARTAN HCTZ – with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or type 2) or moderate to severe renal impairment (GFR < 60 ml/min/1.73m2) is contraindicated (see WARNINGS and PRECAUTIONS, Cardiovascular, Dual Blockade of the Renin-Angiotensin System (RAS) and Renal, and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) with ARBs, ACEIs or aliskiren-containing drugs).
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph
- Pregnant women (see WARNINGS AND PRECAUTIONS, Special Populations – Pregnant Women)
- Nursing women (see WARNINGS AND PRECAUTIONS, Special Populations – Nursing Women)
- Patients with anuria due to the presence of hydrochlorothiazide
Patients with the rare hereditary condition of fructose intolerance
- Mannitol: MYLAN-TELMISARTAN HCTZ tablets contain 340 mg of mannitol per maximum recommended daily dose.
Patients with rare hereditary problems of galactose intolerance, e.g., galactosaemia, the Lapp Lactase deficiency or glucose-galactose malabsorption
- Lactose: MYLAN-TELMISARTAN HCTZ tablets contain 100 mg of lactose monohydrate in the dose strengths of 80/12.5 mg and 80/25 mg.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions When used in pregnancy, angiotensin receptor (AT1) blockers (ARB) can cause injury or even death of the developing fetus. When pregnancy is detected, MYLAN-TELMISARTAN HCTZ should be discontinued as soon as possible (see WARNINGS AND PRECAUTIONS, Special Populations). |
General
A case of rare but fatal angioedema occurred in a patient who had been medicated for about 6 months with telmisartan, one of the active components of MYLAN-TELMISARTAN HCTZ.
The Autopsy Report described evidence of edema of the laryngeal mucosa, with terminal respiratory and circulatory failure. This is in the context of approximately 5.2 million patient-years exposure to telmisartan annually.
If laryngeal stridor or angioedema of the face, extremities, lips, tongue, or glottis occurs, MYLAN-TELMISARTAN HCTZ should be discontinued immediately, the patient treated appropriately in accordance with accepted medical care, and carefully observed until the swelling disappears. In instances where swelling is confined to the face and lips, the condition generally resolves without treatment, although antihistamines may be useful in relieving symptoms. Where there is involvement of tongue, glottis, or larynx, likely to cause airway obstruction, appropriate therapy (including, but not limited to 0.3 to 0.5 ml of subcutaneous epinephrine solution 1:1000) should be administered promptly (see ADVERSE REACTIONS – Post Marketing Adverse Drug Reactions).
Patients with a known hypersensitivity (anaphylaxis) or angioedema to ARBs should not be treated with MYLAN-TELMISARTAN HCTZ (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions - All Clinical Trials, Immune System, Not known: angioedema and ADVERSE REACTIONS - Post Market Adverse Drug Reactions).
Carcinogenesis and Mutagenesis
See TOXICOLOGY, Carcinogenicity and Mutagenicity.
Cardiovascular
Hypotension
In patients who are volume-depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea or vomiting, symptomatic hypotension may occur after initiation of therapy with telmisartan.
Such conditions, especially volume and/or sodium depletion, should be corrected prior to administration of telmisartan. In these patients, because of the potential fall in blood pressure, therapy with telmisartan should be initiated under close medical supervision. Similar considerations apply to patients with ischemic heart or cerebrovascular disease, in whom an excessive fall in blood pressure could result in myocardial infarction or cerebrovascular accident.
Aortic and Mitral Valve Stenosis, Obstructive Hypertrophic Cardiomyopathy
As with other vasodilators, special caution is indicated in patients suffering from aortic or mitral stenosis, or obstructive hypertrophic cardiomyopathy. These patients are at risk of decreased coronary perfusion resulting from a cardiac output that is limited by a fixed cardiac vascular obstruction.
Dual blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin receptor antagonists (ARBs), such as the telmisartan component of MYLAN-TELMISARTAN HCTZ, or of angiotensin-converting-enzyme inhibitors (ACEIs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR < 60
ml/min/1.73m2). Therefore, the use of MYLAN-TELMISARTAN HCTZ in combination with aliskiren-containing drugs is contraindicated in these patients (see CONTRAINDICATIONS).
Further, co-administration of ARBs, including the telmisartan component of MYLAN-TELMISARTAN HCTZ, with other agents blocking the RAS, such as ACEIs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia.
Endocrine and Metabolism
Electrolyte and Metabolic Imbalances
Telmisartan & Hydrochlorothiazide
In controlled trials using telmisartan (80 mg) and hydrochlorothiazide (12.5 mg) in combination, there were no reports of hyperkalemia. Hypokalemia was reported in 1.4% of patients treated with the combination. No discontinuations due to hypokalemia occurred during treatment.
The absence of significant changes in serum potassium levels may be due to the opposing mechanisms of action of telmisartan and hydrochlorothiazide on potassium excretion by the kidney.
The use of a dual renin-angiotensin-aldosterone system (RAAS) blockade may lead to increased occurrence of hyperkalemia when given as add-on therapy in patients with controlled blood pressure.
Hydrochlorothiazide
During thiazide diuretic therapy, periodic determinations of serum electrolytes to detect possible electrolyte imbalances should be performed at appropriate intervals. All patients receiving thiazide therapy should be observed for clinical signs of fluid or electrolyte imbalance, particularly hyponatremia, hypokalemia and hypochloremic alkalosis. Serum and urine electrolyte determinations are particularly important when the patient experiences excessive vomiting or receives parenteral fluids.
Hypokalemia may develop especially with brisk diuresis, when severe cirrhosis is present or after prolonged therapy. Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia may induce cardiac arrhythmia and may also sensitize or exacerbate the response of the heart to the toxic effects of digitalis (e.g. increased ventricular irritability).
Although any chloride deficit is generally mild and usually does not require special treatment except under extraordinary circumstances (as in liver or renal disease), chloride replacement therapy may be required in the treatment of metabolic alkalosis.
Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction rather than administration of salt, except in rare instances when the hyponatremia is life-threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Calcium excretion is decreased by thiazide diuretics which may cause intermittent and slight elevation of serum calcium in the absence of known disorders of calcium metabolism. Marked hypercalcemia may also be evidence of hyperparathyroidism. In the event of significant hypercalcemia, MYLAN-TELMISARTAN HCTZ should be discontinued followed by assessment of parathyroid function.
Thiazide diuretics have been shown to increase the urinary excretion of magnesium, which may result in hypomagnesemia.
Hyperuricemia may occur, and an acute attack of gout may be precipitated in certain patients receiving thiazide therapy.
Insulin requirements in diabetic patients may be altered and latent diabetes mellitus may become manifest during thiazide diuretic therapy.
An increase in cholesterol and triglyceride levels has been associated with thiazide diuretic therapy.
Thiazide may decrease serum PBI levels without signs of thyroid disturbance.
Fertility
No studies on fertility in humans have been performed (see Part II: TOXICOLOGY, Reproduction).
Hepatic
Hepatic Impairment
As the predominant route of elimination of telmisartan is through biliary excretion, patients with cholestasis, biliary obstructive disorders or hepatic insufficiency have reduced clearance of telmisartan leading to increased systemic exposure. MYLAN-TELMISARTAN HCTZ should therefore be used with caution in these patients. Dosage reduction should be considered which would necessitate usage of the individual tablet formulations.
MYLAN-TELMISARTAN HCTZ is not recommended for patients with severe hepatic impairment. Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma (see DOSAGE AND ADMINISTRATION, Patients with Hepatic Impairment).
Neurologic
Effects on ability to drive and use machines
No studies on the effect on the ability to drive and use machines have been performed. However, when driving vehicles or operating machinery it should be taken into account that dizziness or drowsiness may occasionally occur when taking antihypertensive therapy.
Immune
Hypersensitivity Reactions
Hypersensitivity reactions to the hydrochlorothiazide component of MYLAN-TELMISARTAN HCTZ may occur in patients with or without a history of allergy or bronchial asthma.
Systemic Lupus Erythematosus
Thiazide diuretics have been reported to cause exacerbation or activation of systemic lupus erythematosus.
Renal
Renal Impairment
In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney or severe congestive heart failure, dual blockade of the renin-angiotensin-aldosterone system (e.g. concomitant use of an ARB with an ACE-inhibitor or the direct renin-inhibitor aliskiren) and treatment with agents that inhibit this system have been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk. Appropriate assessment of renal function should be conducted prior to use of MYLAN-TELMISARTAN HCTZ.
In studies of ACE inhibitors in patients with unilateral or bilateral renal artery stenosis, increases in serum creatinine or blood urea nitrogen were observed. Although there has been no long-term experience with telmisartan in this patient population, an effect similar to that observed with ACE inhibitors should be anticipated.
Due to the hydrochlorothiazide component, MYLAN-TELMISARTAN HCTZ is not recommended in patients with severe renal impairment (creatinine clearance ≤ 30 mL/min).
Thiazide diuretics should be used with caution in patients with renal impairment.
There is no experience regarding the administration of MYLAN-TELMISARTAN HCTZ in patients with a recent kidney transplant.
The use of ARBs – including the telmisartan component of MYLAN-TELMISARTAN HCTZ – or of ACEIs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR < 60 ml/min/1.73m2). (See CONTRAINDICATIONS and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) with ARBs, ACEIs, or aliskiren-containing drugs).
Azotemia
Azotemia may be precipitated or increased by the hydrochlorothiazide component of MYLAN-TELMISARTAN HCTZ. Cumulative effects of the drug may develop in patients with impaired renal function since the primary route of excretion is through the urine.
If increasing azotemia and oliguria occur during treatment of severe progressive renal disease, the diuretic should be discontinued.
Acute Myopia and Secondary Angle-Closure Glaucoma
Hydrochlorothiazide, a sulfonamide, has been associated with an idiosyncratic reaction resulting in acute transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to week of a drug initiation. Untreated acute-angle glaucoma can lead to permanent vision loss. The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatment may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle closure glaucoma may include a history of sulfonamide or penicillin allergy.
Special Populations
Pregnant Women:
Drugs that act directly on the renin-angiotensin-aldosterone-system (RAAS) can cause fetal and neonatal morbidity and death when administered to pregnant women. When pregnancy is detected, MYLAN-TELMISARTAN HCTZ should be discontinued as soon as possible.
The use of angiotensin receptor (AT1) blockers (ARBs) is not recommended during pregnancy and should not be initiated during pregnancy. Epidemiological evidence regarding the risk of teratogenicity following exposure to angotensin converting enzyme inhibitors (another class of therapeutic products interfering with the RAAS) during the first trimester of pregnancy has not been conclusive; however a small increase in risk cannot be excluded. Given the current evidence available on the risk with ARB, similar risks may exist for this class of drugs. Patients planning pregnancy should be changed to alternative anti-hypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with angiotensin II antagonists should be stopped immediately, and, if appropriate, alternative therapy should be started.
The use of ARBs during the second and third trimesters is known to induce human fetotoxicity (decreased renal function, oligohydramnios, skull ossification retardation) and neonatal toxicity (renal failure, hypotension, hyperkalemia).
Infants with a history of in utero exposure to ARBs should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion may be required as a means of reversing hypotension and/or substituting for disordered renal function; however, limited experience with those procedures has not been associated with significant clinical benefit.
There is limited experience with hydrochlorothiazide during pregnancy, especially during the first trimester. Hydrochlorothiazide crosses the placenta and appears in cord blood. Based on the pharmacological mechanism of action of hydrochlorothiazide its use during the second and third trimester may compromise feto-placental perfusion and may cause fetal and neonatal effects like icterus, disturbance of electrolyte balance, fetal or neonatal jaundice and thrombocytopenia.
Hydrochlorothiazide should not be used for gestational edema, gestational hypertension or preeclampsia due to the risk of decreased plasma volume and placental hypoperfusion, without a beneficial effect on the course of the disease. Hydrochlorothiazide should not be used for essential hypertension in pregnant women.
Diuretics do not prevent development of toxemia (preeclampsia) of pregnancy and there is no satisfactory evidence that they are useful in the treatment of toxemia.
There has been no clinical experience with Telmisartan/Hydrochlorothiazide Tablets in pregnancy.
Preclinical studies with telmisartan do not indicate teratogenic effect, but have shown fetotoxicity.
Nursing Women: MYLAN-TELMISARTAN HCTZ is contraindicated during lactation since it is not known whether telmisartan is excreted in human milk but significant levels have been found in the milk of lactating rats. Animal studies have shown excretion of telmisartan in breast milk. Because many drugs are excreted in human milk and because of their potential for affecting the nursing infant adversely, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother. Thiazide diuretics are excreted in human milk at low levels.
Diabetic Patients:
In diabetic patients with undiagnosed coronary artery disease (CAD) on blood pressure lowering therapy, the risk of fatal myocardial infarction and unexpected cardiovascular death may be increased. In patients with diabetes mellitus, CAD may be asymptomatic and therefore undiagnosed. These patients should undergo appropriate diagnostic evaluation, e.g. exercise stress testing, to detect and to treat CAD accordingly before initiating blood pressure lowering treatment with MYLAN-TELMISARTAN HCTZ.
Pediatrics (< 18 years of age): Safety and effectiveness of Telmisartan/Hydrochlorothiazide Tablets in pediatric patients have not been established.
Geriatrics (> 65 years of age): In clinical trials (n=1725) of patients treated with the combination of telmisartan and hydrochlorothiazide, 348 (20.2%) were 65 to 74 years of age and 78 (4.5%) were 75 years of age or older. No overall differences in the safety or efficacy profiles were observed in elderly patients compared with younger patients. It should be recognized however, that greater sensitivity of some older individuals cannot be ruled out.
Monitoring and Laboratory Tests
For specific monitoring and laboratory tests, see WARNINGS AND PRECAUTIONS (Cardiovascular, Endocrine and Metabolism, Hepatic and Renal) and DRUG INTERACTIONS sections.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Telmisartan and Hydrochlorothiazide Used in Combination
The overall incidence and pattern of adverse events reported with telmisartan/hydrochlorothiazide (80/25 mg) was comparable with telmisartan/hydrochlorothiazide (80/12.5 mg). A dose-relationship of undesirable effects was not established and they showed no correlation with gender, age or race of the patients.
The combination of telmisartan and hydrochlorothiazide has been evaluated for safety in 1725 patients including 716 treated for over six months and 420 for over one year. In clinical trials with the individual components used in combination, no unexpected adverse events have been observed. Adverse experiences have been limited to those that have been previously reported with telmisartan and hydrochlorothiazide monotherapy. In general, treatment with the combination was well tolerated; most adverse experiences were mild and transient in nature and did not require discontinuation of therapy.
Adverse events at an incidence of ≥1% in patients treated with 80/12.5 mg telmisartan/hydrochlorothiazide combination, irrespective of their causal relationship, are presented in the following table. This table includes the results of two pivotal studies. One study, a factorial design, compared the use of various doses of telmisartan tablets and hydrochlorothiazide tablets in combination to telmisartan alone, hydrochlorothiazide alone and placebo. The other study compared the fixed dose combination 80/12.5 mg of telmisartan/hydrochlorothiazide to telmisartan 80 mg alone.
Table 1: ADVERSE EVENTS OCCURRING IN ≥ 1% OF PATIENTS TREATED WITH 80/12.5 MG TELMISARTAN/HYDROCHLOROTHIAZIDE IN PIVOTAL CLINICAL TRIALS
| Telmisartan/ HCTZ 80/12.5 mg (n=320) % | Telmisartan 80 mg (n=322) % | HCTZ 12.5 mg (n=75) % | Placebo (n=74) % | |
|---|---|---|---|---|
| Total with any adverse event | 39.1 | 41.3 | 46.7 | 41.9 |
| Autonomic nervous system | ||||
| Sweating increased | 1.3 | 0.3 | 0 | 0 |
| Body as a whole | ||||
| Back Pain | 1.6 | 2.5 | 1.3 | 0 |
| Fatigue | 2.8 | 2.2 | 4.0 | 1.4 |
| Influenza-Like Symptoms | 1.6 | 1.2 | 2.7 | 1.4 |
| Pain | 2.2 | 2.2 | 4.0 | 6.8 |
| Central & peripheral nervous system | ||||
| Dizziness | 6.9 | 3.7 | 2.7 | 1.4 |
| Headache | 2.5 | 4.0 | 13.3 | 16.2 |
| Gastro-intestinal system | ||||
| Abdominal Pain | 1.6 | 0.9 | 0 | 0 |
| Diarrhoea | 4.1 | 1.6 | 0 | 0 |
| Nausea | 1.6 | 0.9 | 1.3 | 0 |
| Respiratory system | ||||
| Pharyngitis | 1.6 | 0.3 | 0 | 0 |
| Upper Respiratory Tract infection | 2.5 | 3.7 | 9.3 | 6.8 |
HCTZ = hydrochlorothiazide
Note: Telmisartan 80 mg open label treatment is not included in the Telmisartan 80 mg column
Additional adverse reactions reported in clinical trials with telmisartan plus hydrochlorothiazide are listed below according to system organ class:
Autonomic Nervous System: Impotence
Body as a Whole: Allergy, leg pain
Central and Peripheral Nervous System: Vertigo
Gastro-intestinal System: Dyspepsia, gastritis, gastro-intestinal disorder
Metabolic and Nutritional System: Hypokalaemia, loss of diabetic control, hyperuricaemia
Musculo-Skeletal System: Myalgia, arthralgia, arthrosis
Nervous System Disorders: Sleep disturbances
Psychiatric System: Anxiety
Respiratory System: Bronchitis, sinusitis
Skin and Appendages System: Eczema, skin disorder
Urinary System: Urinary tract infection
In controlled trials with 1017 patients, 0.3% of patients treated with telmisartan (80 mg) and hydrochlorothiazide (12.5 mg) used in combination discontinued due to hypotension.
Adverse events occurred at approximately the same rates in men and women, older and younger patients and black and non-black patients.
Abnormal Hematologic and Clinical Chemistry Findings
In controlled trials, clinically relevant changes in standard laboratory test parameters were rarely associated with administration of telmisartan and hydrochlorothiazide in combination.
Table 2: Laboratory Parameter Results in Patients Treated with Telmisartan and Hydrochlorothiazide in Combination
| Laboratory Parameter | % of Patients Treated with Telmisartan/ Hydrochlorothiazide | Clinical Comment |
|---|---|---|
Increases in Blood Urea Nitrogen (BUN) (≥ 11.2 mg/dL) | 2.8% | No patient discontinued treatment due to an increase in BUN. |
Increases in Serum Creatinine (≥ 0.5 mg/dL) | 1.4% | No patient discontinued treatment due to an increase in creatinine. |
Decreases in Hemoglobin (≥ 2 g/dL) | 1.2% | Changes in hemoglobin were not considered clinically significant and there were no discontinuations due to anemia. |
Decreases in Hematocrit (≥ 9%) | 0.6% | Changes in hematocrit were not considered clinically significant and there were no discontinuations due to anemia. |
Liver function Tests: Occasional elevations of liver enzymes and/or serum bilirubin have occurred. No telmisartan/hydrochlorothiazide treated patients discontinued therapy due to abnormal liver function.
Serum Electrolytes: see WARNINGS AND PRECAUTIONS.
Telmisartan
Additional side effects were reported in clinical trials with telmisartan in the indication hypertension or in patients 50 years or older at high risk of cardiovascular events.
Telmisartan has been evaluated for safety in 27 clinical trials involving 7968 patients. Of these 7968 patients, 5788 patients were treated with telmisartan monotherapy including 1058 patients treated for > 1 year and 1395 patients treated in placebo-controlled trials.
The following potentially serious adverse events have been reported rarely with telmisartan in controlled clinical trials: syncope and hypotension. In placebo-controlled trials, no serious adverse event was reported with a frequency ≥ 0.1% in telmisartan-treated patients.
All Clinical Trials
The adverse drug events listed below have been accumulated from 27 clinical trials including 5788 hypertensive patients treated with telmisartan. Adverse events have been ranked under headings of frequency using the following convention: very common (≥ 1/10); common (≥ 1/100, < 1/10); uncommon (≥ 1/1000, < 1/100); rare (≥ 1/10000, < 1/1000); very rare (< 1/10000)
Body as a Whole, General:
Common: Chest pain, influenza-like symptoms, symptoms of infection (e.g. urinary tract infection including cystitis), fatigue, conjunctivitis.
Uncommon: Hyperhidrosis, asthenia (weakness).
Blood and Lymphatic System:
Uncommon: Anemia.
Rare: Thrombocytopenia.
Unknown: Eosinophilia.
Cardiovascular System:
Common: Edema, palpitation.
Uncommon: Bradycardia, orthostatic hypotension, hypotension.
Rare: Tachycardia.
Central and Peripheral Nervous System:
Very Common: Headache.
Common: Dizziness, insomnia.
Uncommon: Vertigo.
Eye Disorders:
Rare: Visual disturbance.
Gastro-Intestinal System:
Common: Abdominal pain, diarrhoea, dyspepsia, nausea, constipation, gastritis.
Uncommon: Dry mouth, flatulence, vomiting.
Rare: Stomach discomfort.
Hepato-biliary Disorders:
Rare: Hepatic function abnormal/liver disorder*.
*Most cases of hepatic function abnormal / liver disorder from post-marketing experience with telmisartan occurred in patients in Japan, who are more likely to experience these adverse reactions
Immune System:
Rare: Hypersensitivity, Exacerbation or activation of systemic lupus erythematosus*
*based on post-marketing experience.
Unknown: Anaphylactic reaction, angioedema.
Infections and Infestations:
Uncommon: Upper respiratory tract infections, urinary tract infections.
Not known: Sepsis including fatal outcome.
Investigations:
Uncommon: Blood creatinine increased.
Rare: Blood uric acid increased, hepatic enzymes increased, blood creatinine phosphokinase increased, haemoglobin decreased.
Metabolism and Nutrition Disorders:
Uncommon: Hyperkalemia.
Rare: Hypoglycemia (in diabetic patients).
Musculo-Skeletal System:
Common: Arthralgia, muscle spasms (cramps in legs) or pain in extremity (leg pain), myalgia, arthritis, arthrosis.
Uncommon: Tendon pain (tendonitis like symptoms), back pain.
Nervous System:
Uncommon: Syncope (faint).
Psychiatric System:
Common: Anxiety, nervousness.
Uncommon: Depression.
Renal and Urinary System:
Uncommon: Renal impairment including acute renal failure.
Respiratory System:
Common: Upper respiratory tract infections including pharyngitis and sinusitis, bronchitis, coughing, dyspnea, rhinitis.
Skin and Appendages System:
Common: Skin disorders like rash.
Uncommon: Pruritus.
Rare: Erythema, drug eruption, eczema, toxic skin eruption.
Unknown: Urticaria.
Placebo-Controlled Trials
The overall incidence of adverse events reported with telmisartan (41.4%) was usually comparable to placebo (43.9%) in controlled clinical trials.
Adverse events occurring in ≥ 1% of 1395 hypertensive patients treated with telmisartan monotherapy in placebo-controlled clinical trials, regardless of drug relationship, include the following:
Table 3: Adverse Events Occurring in ≥ 1% of 1395 Hypertensive Patients Treated with Telmisartan Monotherapy
| Adverse Event, by System | Telmisartan/ Hydrochlorothiazide Total N=1395 % | Placebo N=583 % |
|---|---|---|
| Body as a Whole | ||
| Back Pain | 2.7 | 0.9 |
| Chest Pain | 1.3 | 1.2 |
| Fatigue | 3.2 | 3.3 |
| Influenza-Like Symptoms | 1.7 | 1.5 |
| Pain | 3.5 | 4.3 |
| Central & Peripheral Nervous System | ||
| Dizziness | 3.6 | 4.6 |
| Headache | 8.0 | 15.6 |
| Somnolence | 0.4 | 1.0 |
| Gastrointestinal System | ||
| Diarrhea | 2.6 | 1.0 |
| Dyspepsia | 1.6 | 1.2 |
| Nausea | 1.1 | 1.4 |
| Vomiting | 0.4 | 1.0 |
| Musculoskeletal System | ||
| Myalgia | 1.1 | 0.7 |
| Respiratory System | ||
| Coughing | 1.6 | 1.7 |
| Pharyngitis | 1.1 | 0.3 |
| Sinusitis | 2.2 | 1.9 |
| Adverse Event, by System | Telmisartan/ Hydrochlorothiazide Total N=1395 % | Placebo N=583 % |
|---|---|---|
| Upper Respiratory Tract Infection | 6.5 | 4.6 |
| Heart Rate and Rhythm Disorders | ||
| ECG abnormal specific | 0.2 | 1.0 |
| Palpitation | 0.6 | 1.0 |
| Cardiovascular Disorders, General | ||
| Hypertension | 1.0 | 1.7 |
| Oedema peripheral | 1.0 | 1.2 |
The incidence of adverse events was not dose-related and did not correlate with the gender, age, or race of patients.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
In addition, the following adverse events, with no established causality, were reported at an incidence <1% in placebo-controlled clinical trials:
Autonomic Nervous System Disorders: sweating increased.
Body as a Whole: abdomen enlarged, allergy, cyst nos, fall, fever, leg pain, rigors, syncope.
Cardiovascular Disorders, General: hypotension, hypotension-postural, leg edema.
Central & Peripheral Nervous System Disorder: hypertonia, migraine-aggravated, muscle contraction-involuntary.
Gastrointestinal System Disorders: anorexia, appetite increased, flatulence, gastrointestinal disorder nos, gastroenteritis, gastroesophageal reflux, melena, mouth dry, abdominal pain.
Heart Rate & Rhythm Disorders: arrhythmia, tachycardia.
Metabolic & Nutritional Disorders: diabetes mellitus, hypokalaemia.
Musculoskeletal System Disorders: arthritis, arthritis aggravated, arthrosis, bursitis, fascitis plantar, tendon pain.
Myo Endo Pericardial & Valve Disorders: myocardial infarction.
Psychiatric Disorders: nervousness.
Red Blood Cell Disorders: anemia.
Reproductive Disorders, Female: vaginitis.
Resistance Mechanism Disorders: abscess, infection, bacterial, moniliasis genital, otitis media.
Respiratory System Disorders: bronchospasm, epistaxis, pneumonia, bronchitis.
Skin & Appendage Disorders: rash, skin dry.
Urinary System Disorders: dysuria, hematuria, micturition disorder, urinary tract infection (including cystitis).
Vascular (Extracardiac) Disorders: cerebrovascular disorder, purpura.
Vision Disorders: vision abnormal.
Angioedema has been reported rarely in patients treated with telmisartan.
Abnormal Hematologic and Clinical Chemistry Findings
In placebo-controlled clinical trials involving 1041 patients treated with Telmisartan monotherapy, clinically relevant changes in standard laboratory test parameters were rarely associated with administration of telmisartan.
Table 4: Laboratory Parameter Results in Placebo-Controlled Clinical Trials Involving 1041 Patients Treated With Telmisartan Monotherapy
| Laboratory Parameter | % of Placebo Patients | % of Patients Treated with Telmisartan | Clinical Comment |
|---|---|---|---|
Increases in ALT > 3 times the upper limit of normal | 1.7% | 0.5% | No telmisartan-treated patients discontinued therapy due to abnormal hepatic function. |
Increases in AST > 3 times the upper limit of normal | 0.8% | 0.1% | No telmisartan-treated patients discontinued therapy due to abnormal hepatic function. |
| Increases in Blood Urea Nitrogen (BUN) ≥ 11.2 mg/dl | 0.3% | 1.5% | These increases occurred primarily with telmisartan in combination with hydrochlorothiazide. One telmisartan treated patient discontinued therapy due to increases in blood urea nitrogen and creatinine. |
Increases in Creatinine ≥ 0.5 mg/dl | 0.3% | 0.6% | These increases occurred primarily with telmisartan in combination with hydrochlorothiazide. One telmisartan treated |
| Laboratory Parameter | % of Placebo Patients | % of Patients Treated with Telmisartan | Clinical Comment |
|---|---|---|---|
| patient discontinued therapy due to increases in blood urea nitrogen and creatinine. | |||
Increases in Serum Potassium ≥ 1.4 mEq/L | 0.6% | 0.3% | Clinically significant changes in potassium (that exceeded 3 mEq/L) were found in 0.6% of telmisartan-treated patients, with 0.5% of these reported at baseline. The corresponding rates for placebo-treated patients were 0.6% and 0.8%. |
Decreases in Serum Potassium ≥ 1.4 mEq/L | 0.3% | 0.1% | Clinically significant changes in potassium (that exceeded 3 mEq/L) were found in 0.6% of telmisartan-treated patients, with 0.5% of these reported at baseline. The corresponding rates for placebo-treated patients were 0.6% and 0.8%. |
Increases in Serum Uric Acid ≥ 2.7 mg/dl | 0.0% | 1.7% | Clinically significant hyperuricemia (>10mEq/L) was observed in 2.3% of patients with telmisartan, with 0.4% reported in patients at baseline. Increases in serum uric acid were primarily observed in patients who received telmisartan in combination with hydrochlorothiazide. No patient was discontinued from treatment due to hyperuricemia. |
Hemoglobin, Hemotocrit
Clinically significant changes in hemoglobin and hematocrit (<10g/dl and <30%, respectively) were rarely observed with telmisartan treatment and did not differ from rates in placebo-treated patients. No patients discontinued therapy due to anemia.
Cholesterol
In placebo-controlled trials, marked increases in serum cholesterol were reported in a total of 6 telmisartan-treated patients (0.4%) and no placebo patients. Two of these patients were followed over time, in both cases cholesterol values reverted to baseline levels.
Serum elevations in cholesterol were reported as adverse events in 11 of 3445 patients (0.3%) in all clinical trials. There were no reported cases of hypercholesterolemia in telmisartan-treated patients in placebo-controlled trials.
Other Clinical Trials
Gastrointestinal: constipation
Respiratory: rhinitis, dyspnea
Special senses: conjunctivitis
Post-Market Adverse Drug Reactions
Telmisartan
Since the introduction of telmisartan in the market, cases of anxiety, dizziness, vision troubled, vertigo, abdominal distension, abdominal pain, retching, hyperhidrosis, arthralgia, myalgia, muscle spasm, back pain, asthenia, pain in extremity, fatigue, chest pain, blood creatinine increased, erythema, pruritus, syncope/faint, insomnia, depression, stomach discomfort, vomiting, hypotension (including orthostatic hypotension), bradycardia, tachycardia, abnormal hepatic function/liver disorder, renal impairment including acute renal failure, hyperkalemia, dyspnoea, anaemia, eosinophilia, thrombocytopenia and weakness have been reported. The frequency of these effects is unknown. As with other angiotensin II antagonists, rare cases of angioedema (with fatal outcome), pruritus, rash and urticaria have been reported.
Cases of muscle pain, muscle weakness, myositis and rhabdomyolysis have been reported in patients receiving angiotensin II receptor blockers.
In addition, since the introduction of telmisartan in the market, cases with increased blood creatinine phosphokinase (CPK) have been reported.
Hydrochlorothiazide
Adverse experiences that have been reported with hydrochlorothiazide alone without regard to causality are listed below:
Body as a Whole: fever
Gastro-Intestinal System: pancreatitis, sialadenitis, gastric irritation, anorexia, nausea, vomiting, diarrhea, constipation;
Hepatobiliary Disorders: Jaundice (hepatocellular cholestatic jaundice).
Blood and Lymphatic System: aplastic anemia, agranulocytosis, leukopenia, hemolytic anemia, thrombocytopenia, bone marrow depression;
Hypersensitivity: purpura
Respiratory Disorders: respiratory distress including pneumonia and pulmonary edema
Musculoskeletal: muscle spasm, weakness, cramps in legs
Metabolism and Nutrition Disorders: volume depletion, loss of appetite.
Nervous System Disorders: light-headedness.
Central and Peripheral Nervous System: dizziness, vertigo, paraesthesia, restlessness, nervousness;
Cardiovascular: orthostatic hypotension;
Heart rate and rhythm disorder: cardiac arrhythmias;
Renal: renal failure, renal dysfunction, interstitial nephritis;
Skin and Subcutaneous Tissue Disorders: rash, urticaria, erythema multiforme including
Stevens-Johnson syndrome, exfoliative dermatitis including toxic epidermal necrolysis, photosensitivity reactions, necrotizing angiitis (vasculitis, cutaneous vasculitis), anaphylactic reactions, cutaneous lupus erythematosus-like reactions, reactivation of cutaneous lupus erythematosus
Eye Disorders: transient blurred vision, xanthopsia, acute myopia, acute angle-closure glaucoma.
Laboratory Findings: Metabolic: hyperglycaemia, glucosuria, hyperuricaemia;
Other: electrolyte imbalances (including hyponatraemia and hypokalaemia), increases in triglycerides, hypercholesterolemia.
DRUG INTERACTIONS
Overview
Telmisartan
Cytochrome P450: Telmisartan is not metabolized by the cytochrome P450 (CYP) isoenzymes; as such, it is not expected that a pharmacokinetic interaction of telmisartan with drugs which inhibit or induce CYP isozymes will occur.
Hydrochlorothiazide
Cytochrome P450: Hydrochlorothiazide is not metabolized by humans; as such, no pharmacokinetic interaction with agents known to inhibit or induce CYP isozymes or other enzymes systems is expected.
Drug-Drug Interactions
Table 5 - Established or Potential Drug-Drug Interactions
| Telmisartan | Effect | Clinical comment |
|---|---|---|
| Diuretics | Patients on diuretics, and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with telmisartan. | The possibility of symptomatic hypotension with the use of telmisartan can be minimized by discontinuing the diuretic prior to initiation of treatment and/or lowering the initial dose of telmisartan (see WARNINGS - Hypotension and DOSAGE AND ADMINISTRATION). No drug interaction of clinical significance has been identified with thiazide diuretics. |
| Agents increasing serum potassium | Since the telmisartan component of MYLAN-TELMISARTAN HCTZ reduces the production of aldosterone, potassium-sparing diuretics or potassium supplements should be given only for documented hypokalemia and with frequent monitoring of serum potassium. Potassium-containing salt substitutes should also be used with caution. Concomitant thiazide diuretic use may attenuate any effect that telmisartan may have on serum potassium. | |
| Digoxin | When telmisartan was co- administered with digoxin, mean increases in digoxin peak plasma concentration (49%) and in trough concentration (20%) were observed. | It is recommended that digoxin levels be monitored with appropriate dose adjustments when initiating, adjusting or discontinuing MYLAN-TELMISARTAN HCTZ, to maintain appropriate plasma digoxin concentrations. |
Dual Blockade of the Renin-Angiotensin System (RAS) with ARBs, ACEIs or aliskiren-containing drugs | Dual Blockade of the renin-angiotensin system with ARBs, ACEIs or aliskiren-containing drugs is contraindicated in patients with diabetes and/or renal impairment, and is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia. (See CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System). | |
| Lithium Salts | Reversible increases in serum lithium concentrations and toxicity have been reported during concomitant administration of lithium with angiotensin converting enzyme inhibitors. Rare cases have also been reported with angiotensin II receptor antagonists including telmisartan. | Serum lithium level monitoring is advisable during concomitant use. |
Nonsteroidal Anti- Inflammatory Drugs | Combinations of angiotensin-II antagonists (telmisartan) and | Blood pressure and kidney function should be monitored more closely in this situation, as |
| Telmisartan | Effect | Clinical comment |
|---|---|---|
| (NSAIDs) | NSAIDs (including ASA and COX-2 inhibitors) might have an increased risk for acute renal failure and hyperkalemia. NSAIDs (including ASA and COX-2 inhibitors) and angiotensin-II receptor antagonists exert a synergistic effect on the decrease of glomerular filtration. In patients with pre-existing renal impairment, this may lead to acute renal failure. | occasionally there can be a substantial increase in blood pressure. Monitoring of renal function at the beginning and during the course of the treatment should be recommended. Co-administration of telmisartan did not result in a clinically significant interaction with ibuprofen. |
| Ramipril | In one study, the co-administration of telmisartan and ramipril led to an increase of up to 2.5 fold in the AUC0-24 and Cmax of ramipril and ramiprilat. | The clinical relevance of this observation is not known. |
| Warfarin | Telmisartan administered for 10 days slightly decreased the mean warfarin trough plasma concentration; this decrease did not result in a change in the International Normalized Ratio (INR). | |
Acetaminophen, amlodipine, glibenclamide, hydrochlorothiazide, or ibuprofen | Co-administration of telmisartan did not result in a clinically significant pharmacokinetic interaction |
Table 6 - Established or Potential Drug-Drug Interactions
| Hydrochlorothiazide | Ref. | Effect | Clinical comment |
|---|---|---|---|
| Alcohol, barbiturates and narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics. | Monitor of serum potassium level. |
Anti-diabetic drugs (e.g. oral hypoglycemic agents and insulin) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
| Antihypertensive drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, betablockers, vasodilators, calcium channel blockers, ACEI, ARB, and direct renin inhibitors). | |
Antineoplastic drugs, including cyclophosphamide and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
Bile acid sequestrants, e.g. cholestyramine and colestipol resins | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothiazide by 30-35%. | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of thiazide, if necessary. |
Calcium and vitamin D supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
Corticosteroids, and adrenocorticotropic hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia may occur. | Monitor serum potassium, and adjust medications, as required. |
| Hydrochlorothiazide | Ref. | Effect | Clinical comment |
|---|---|---|---|
| Digoxin | CT | Thiazide-induced electrolyte disturbances, e.g. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin levels closely. Supplement potassium or adjust doses of digoxin or thiazide, as required. |
Drugs that alter GI motility, i.e., anticholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretcs may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of thiazide may be required. |
Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RCS | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co-administration of hydrochlorothaizde and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Dosage adjustment of gout medications may be required. |
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high risk of lithium toxicity. | Concomitant use of thiazide diuretics with lithium is generally not recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor lithium levels closely. |
| Non-steroidal Anti- Inflammatory drugs (NSAIDs including ASA and COX-2 inhibitors) | CT | The co-administration of a non-steroidal anti-inflammatory agent can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics. The potential for acute renal insufficiency in patients who are dehydrated may be enhanced. NSAID-related retention of sodium and water antagonises the diuretic and antihypertensive effects of thiazides. | Patients receiving NSAIDs and MYLAN-TELMISARTAN HCTZ should be adequately hydrated and be monitored for renal function at the beginning of the combined treatment. Monitoring of renal function at the beginning and during the course of the treatment is recommended as well as regular hydration of the patient. Therefore, when MYLAN-TELMISARTAN HCTZ and NSAIDs are used concomitantly, the patient should be observed closely to determine whether the desired effect of the diuretic is obtained. If combination use is necessary, also monitor serum potassium and blood pressure closely. Dose adjustments |
| Hydrochlorothiazide | Ref. | Effect | Clinical comment |
|---|---|---|---|
| NSAID-induced inhibition of renal prostaglandins leading to decreases of renal blood flow, along with thiazide-induced decreases in GFR may lead to acute renal failure. Patients with heart failure may be at particular risk. | may be required. | ||
| Pressor amines (e.g. norepinephrine) | Decreased response to pressor amines may occur, but the effect is considered not sufficient to preclude their concurrent use. | ||
Selective serotonin reuptake inhibitors (SSRIs, e.g. citalopram, escitalopram, sertraline) | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
Skeletal muscle relaxants of the curare family e.g. tubocurare | C | Thiazide drugs may increase the responsiveness of some skeletal muscle relaxants, such as curare derivatives. | |
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. |
| -adrenergic receptor blocking agents propranolol, metoprolol, sotalol, or acebutolol | No significant pharmacokinetic interactions were noted when these agents were administered concomitantly, separately or in fixed combination. | ||
| Spironolactone, indomethacin, allopurinol and phenytoin. | No significant interactions have been noted. |
Legend: C = Case Study; RCS = Retrospective Cohort Study; CT = Clinical Trial; T = Theoretical
Drug-Food Interactions
When telmisartan is taken with food, the reduction in the area under the plasma concentration-time curve (AUC) of telmisartan varies from approximately 6% (40 mg) to approximately 19% (160 mg), and the reduction in Cmax varies from approximately 26% (40 mg) to 56% (160 mg). However, three hours after administration, plasma concentrations are similar whether telmisartan is taken with or without food.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
Interactions with lifestyle have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
MYLAN-TELMISARTAN HCTZ may be substituted in patients who have been stabilized on the individual telmisartan 80 mg and hydrochlorothiazide 12.5 mg components as described below.
MYLAN-TELMISARTAN HCTZ may be administered with or without food, however it should be taken consistently with regard to food intake.
Recommended Dose and Dosage Adjustment
MYLAN-TELMISARTAN HCTZ (telmisartan/hydrochlorothiazide) is not for initial therapy.
A patient whose blood pressure is not adequately controlled with telmisartan monotherapy 80 mg, may be switched to MYLAN-TELMISARTAN HCTZ, (telmisartan 80 mg/hydrochlorothiazide 12.5 mg) once daily.
A patient whose blood pressure is not adequately controlled with MYLAN-TELMISARTAN HCTZ (telmisartan 80 mg/hydrochlorothiazide 12.5 mg), may be switched to MYLAN-TELMISARTAN HCTZ (telmisartan 80 mg/hydrochlorothiazide 25 mg) once daily.
Telmisartan Monotherapy
The recommended dose of telmisartan is 80 mg once daily. The antihypertensive effect is present within 2 weeks and maximal reduction is generally attained after four weeks. If additional blood pressure reduction is required, a thiazide diuretic may be added.
No initial dosing adjustment is necessary for elderly patients or for patients with renal impairment but greater sensitivity in some older individuals cannot be ruled out. Markedly reduced telmisartan plasma levels were observed in patients on hemodialysis.
Diuretic Treated Patients
In patients receiving diuretics, telmisartan therapy should be initiated with caution, since these patients may be volume depleted and thus more likely to experience hypotension following initiation of additional antihypertensive therapy. Whenever possible, all diuretics should be discontinued two to three days prior to the administration of telmisartan to reduce the likelihood of hypotension. (See WARNINGS AND PRECAUTIONS, Hypotension). If this is not possible because of the patient’s condition, telmisartan should be administered with caution and the blood pressure monitored closely. Thereafter, the dosage should be adjusted according to the individual response of the patient.
Patients with Renal Impairment
The usual regimens of therapy with MYLAN-TELMISARTAN HCTZ may be followed as long as the patient's creatinine clearance is > 30 mL/min. In patients with more severe renal impairment, loop diuretics are preferred to thiazides; in this instance, MYLAN-TELMISARTAN HCTZ is not recommended.
Patients with Hepatic Impairment
For patients with hepatic impairment, a starting dose of 40 mg of telmisartan is recommended. MYLAN-TELMISARTAN HCTZ is not recommended for patients with severe hepatic impairment.
Missed Dose
If a dose is missed, patients should not take a double dose; patients should just carry on with the next dose at the usual time.
Administration
MYLAN-TELMISARTAN HCTZ may be administered with or without food, however it should be taken consistently with regard to food intake.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre Immediately. |
Limited information is available for Telmisartan/Hydrochlorothiazide Tablets with regard to overdose in humans. Serum electrolytes and creatinine should be monitored frequently. If hypotension occurs, the patient should be placed in a supine position, with salt and volume replacements given quickly. For the individual components of MYLAN-TELMISARTAN HCTZ, the following information is available:
Telmisartan
Based on limited data, the most prominent manifestations of overdose are hypotension, dizziness and tachycardia; bradycardia also occurred in this setting as a result of parasympathetic (vagal) stimulation. If symptomatic hypotension should occur, supportive treatment should be instituted.
Telmisartan is not removed by hemodialysis.
Hydrochlorothiazide
The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias.
The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
MYLAN-TELMISARTAN HCTZ (telmisartan/hydrochlorothiazide) is a combination of telmisartan, a selective angiotensin II antagonist and hydrochlorothiazide, a thiazide diuretic.
Telmisartan
Telmisartan is an orally active, AT1 selective angiotensin II receptor antagonist. By selectively blocking the binding of angiotensin II to the AT1 receptors, telmisartan inhibits the vasoconstrictor and aldosterone-secreting effects of angiotensin II. Telmisartan blocks AT1 receptors, and has essentially no affinity for the AT2 receptors. AT2 receptors have been found in many tissues; to date, they have not been found to be associated with cardiovascular homeostasis.
Telmisartan does not inhibit angiotensin converting enzyme (ACE, also known as kininase II), the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin, nor does it affect renin or other hormone receptors or ion channels involved in cardiovascular regulation of blood pressure and sodium homeostasis.
In hypertensive patients, antagonism of angiotensin II AT1 receptors results in two to three-fold increases in plasma renin and angiotensin II plasma concentrations. Long term effects of increased AT2 receptor stimulation by angiotensin II are unknown.
Hydrochlorothiazide
Hydrochlorothiazide is a thiazide diuretic which affects the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in the distal tubule, thus promoting water excretion. The diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss and decreases in serum potassium. The latter effects of the renin-aldosterone link are mediated by angiotensin II; as such, co-administration of an angiotensin II AT1 receptor antagonist may prevent the potassium loss associated with thiazide diuretics. The precise mechanism of the antihypertensive effect of thiazides however, is not fully understood.
Pharmacodynamics
Telmisartan
The antihypertensive effects of telmisartan were demonstrated in 6 placebo-controlled clinical trials, in a total of 1773 patients, 1031 of whom were treated with Telmisartan. Upon initiation of antihypertensive treatment with telmisartan, blood pressure was reduced after the first dose and there was a gradual increase in the antihypertensive effect during continued treatment for ≤12 weeks, with most of the increase occurring during the first month. Onset of antihypertensive activity occurs within 3 hours after administration of a single oral dose. The antihypertensive effect of once daily administration of telmisartan is maintained for the full 24- hour dose interval. The magnitude of blood pressure reduction from baseline, after placebo subtraction, was on average (SBP/DBP) -11.3/-7.3 mmHg for Telmisartan 40 mg once daily, and -13.7/-8.1 mmHg for Telmisartan 80 mg once daily. Upon abrupt cessation of treatment with Telmisartan, blood pressure gradually returned to baseline values over a period of several days. During long term studies (without placebo control) the effect of telmisartan appeared to be maintained for ≥1 year.
For those patients treated with telmisartan 80 mg once daily who required additional blood pressure reduction, addition of a low dose of hydrochlorothiazide (12.5 mg) resulted in incremental blood pressure reductions of -9.4/-7.0 mmHg.
There was essentially no change in heart rate in telmisartan-treated patients in controlled trials.
In clinical trials with post-dose in-clinic monitoring no excessive blood pressure lowering peak effect was observed even after the first dose, and the incidence of symptomatic orthostasis was very low (0.04%).
With automated ambulatory blood pressure monitoring, the 24-hour trough-to-peak ratio for telmisartan was determined to be at least 80% for both systolic and diastolic blood pressure.
The antihypertensive effect of telmisartan is not influenced by patient age, weight or body mass index. Blood pressure in hypertensive black patients is significantly reduced by telmisartan (compared to placebo), but less so than in non-black patients.
In hypertensive patients with normal renal function, no clinically significant effects on renal plasma flow, filtration fraction, or glomerular filtration rate were observed. In multiple dose studies in hypertensive patients, telmisartan had no adverse effect on renal function as measured by serum creatinine or blood urea nitrogen.
Diabetic Patients: Multiple exploratory post hoc analyses were carried out on the three cardiovascular (CV) outcome trials (ONTARGET, TRANSCEND and PRoFESS). In TRANSCEND and PRoFESS, an increased risk of unexpected CV death was seen with telmisartan versus placebo in diabetics without previously diagnosed coronary artery disease (CAD) but not in those with a documented history of CAD. No such increased risk was demonstrated in ONTARGET for telmisartan versus ramipril in diabetes patients without previously diagnosed CAD.
These findings in diabetics with added cardiovascular risk, could be related to a pre-existing but asymptomatic or silent CAD. Diabetics with undiagnosed and therefore untreated CAD may be at increased risk when lowering blood pressure too far, e.g. when initiating antihypertensive therapy, due to a further reduction of perfusion in an already narrowed coronary artery.
Hydrochlorothiazide
After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts 6 to 12 hours.
Telmisartan and Hydrochlorothiazide Combination
In a placebo-controlled clinical study, the combination of telmisartan and hydrochlorothiazide resulted in decreases in trough systolic blood pressure (SBP) and diastolic blood pressure (DBP) which were greater than the decreases induced by either agent administered as monotherapy.
In a controlled clinical trial directly comparing telmisartan/hydrochlorothiazide with telmisartan (80mg) monotherapy, trough SBP and DBP reductions observed with telmisartan/hydrochlorothiazide were significantly greater than with telmisartan alone.
Similarly, in other controlled studies with patients who did not achieve or maintain adequate response with telmisartan monotherapy, the addition of 12.5 mg hydrochlorothiazide to titrated doses of telmisartan further reduced systolic and diastolic pressure.
The antihypertensive effect of telmisartan/hydrochlorothiazide (80 mg/12.5 mg) was independent of age or gender. The overall response to the combination was similar for black and non-black patients.
There was essentially no change in heart rate in patients treated with the combination of telmisartan and hydrochlorothiazide in the placebo-controlled trial.
Pharmacokinetics
There are no pharmacokinetic interactions between telmisartan and hydrochlorothiazide as the pharmacokinetic parameters of the individual components are unchanged by their co- administration as telmisartan/hydrochlorothiazide. The results of a randomized, crossover study demonstrated that the bioavailabilities of telmisartan and hydrochlorothiazide were the same, whether administered as the fixed-dose combination or as the single entity formulations.
Table 7: Single Dose Pharmacokinetics in Normotensive Subjects (10 Male and 10 Female Caucasian Subjects, 18 to 45 years of age). Given are arithmetic means (%CV).
| Drug | Therapy | Cmax (ng/mL) | t½ (h) | AUC0-∞ (ng·h/mL) | Clearance (CL/f) (mL/min) | Volume of Distribution (Vz/f) (L) |
|---|---|---|---|---|---|---|
Telmisartan: monotherapy | A | 246 | 22.2 | 1439 | 1650 | 2908 |
| (%CV 69.4) | (%CV 30) | (%CV 94) | (%CV 62) | (%CV 60) | ||
Telmisartan: combination therapy | B | 266 | 24.4 | 1467 | 1565 | 3091 |
| (%CV 103) | (%CV 33) | (%CV 94) | (%CV 63) | (%CV 63) | ||
| Hydrochlorothiazide: | A | 75.3 | 11.4 | 580.4 | 380 | 363.8 |
| Drug | Therapy | Cmax (ng/mL) | t½ (h) | AUC0-∞ (ng·h/mL) | Clearance (CL/f) (mL/min) | Volume of Distribution (Vz/f) (L) |
|---|
| combination therapy | (%CV 26) | (%CV 43) | (%CV 27) | (%CV 23) | (%CV 43) | ||||||
Hydrochlorothiazide: monotherapy | B | 75.7 | 11.5 | 563.9 | 384 | 380.4 | |||||
| (%CV 22) | (%CV 36) | (%CV 20) | (%CV 20) | (%CV 40) | |||||||
Telmisartan
Absorption: Following oral administration, telmisartan is well absorbed with a mean absolute bioavailability of about 50%. Mean peak plasma concentrations (Cmax) of telmisartan are reached in 0.5 -1.0 hour after dosing. The pharmacokinetic profile is characterized by greater than proportional increases in plasma concentrations (Cmax and AUC) with increasing doses >40 mg. Telmisartan shows bi-exponential decay kinetics with terminal elimination half life of approximately 24 hours, and does not accumulate in plasma upon repeated once daily administration. Food slightly reduces the bioavailability of telmisartan.
Distribution: Telmisartan is extensively bound to plasma proteins (>99.5%) at concentrations achieved at the recommended dosage. The apparent volume of distribution is approximately 500 L, suggesting extensive tissue binding sites.
Metabolism: Telmisartan is metabolized by conjugation to form a pharmacologically inactive acylglucuronide; this is the only metabolite that has been detected in human plasma and urine. Following both oral dosing and intravenous administration of radiolabelled telmisartan, the parent compound represented approximately 85%, and the glucuronide approximately 11% of total radioactivity in plasma. The cytochrome P450 isoenzymes are not involved in the metabolism of telmisartan.
Excretion: Total plasma clearance of telmisartan is > 800 mL/min. Biliary excretion is the predominant route of elimination of telmisartan and its metabolite.
Hydrochlorothiazide
Absorption: Following oral administration, peak concentrations of hydrochlorothiazide were reached approximately 2.0 hours after dosing. Based on cumulative renal excretion of hydrochlorothiazide the absolute bioavailability was about 60% to 70%.
Distribution: Hydrochlorothiazide is 40% protein bound in the plasma and its apparent volume of distribution is 2 to 5 L/kg.
Excretion: Hydrochlorothiazide is not metabolized but is eliminated rapidly by the kidney. The plasma half-life has been observed to vary between 5.6 and 14.8 hours when the plasma levels can be followed for up to 24 hours. At least 61 percent of the oral dose is eliminated unchanged within 24 hours. Hydrochlorothiazide crosses the placenta but not the blood-brain barrier and is excreted in breast milk.
Special Populations and Conditions
Telmisartan
Pediatrics:
Telmisartan pharmacokinetics have not been investigated in patients < 18 years of age.
Geriatrics:
The pharmacokinetics of telmisartan does not differ between elderly patients and those younger than 65 years of age.
Gender:
Plasma concentrations of telmisartan are generally 2-3 times higher in females than in males administered the same oral dose. In clinical trials however, no significant increases in blood pressure response or in the incidence of orthostatic hypotension were found in women. No dosage adjustment is necessary on the basis of gender.
Hepatic Insufficiency:
In patients with hepatic insufficiency, plasma concentrations of telmisartan are increased, and absolute bioavailability approaches 100% (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION). Reduction of the dose of telmisartan should be considered which would necessitate usage of the individual tablet formulations.
Renal Insufficiency:
Renal excretion of telmisartan is negligible. In patients with mild to moderate renal impairment, (creatinine clearance of 30-80 mL/min), no dosage adjustment is necessary (see WARNINGS AND PRECAUTIONS, Renal Impairment and DOSAGE AND ADMINISTRATION, Patients with Renal Impairment). Telmisartan is not removed by hemodialysis.
As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function may be anticipated in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk. Appropriate assessment of renal function should be conducted prior to use of MYLAN-TELMISARTAN HCTZ.
In studies of ACE inhibitors in patients with unilateral or bilateral renal artery stenosis, increases in serum creatinine or blood urea nitrogen were observed. Although there has been no long-term experience with telmisartan in this patient population, an effect similar to that observed with ACE inhibitors should be anticipated.
Due to the hydrochlorothiazide component, MYLAN-TELMISARTAN HCTZ is not recommended in patients with severe renal impairment (creatinine clearance ≤ 30 mL/min).
Thiazide diuretics should be used with caution in patients with renal impairment.
There is no experience regarding the administration of telmisartan/hydrochlorothiazide in patients with a recent kidney transplant.
No initial dosing adjustment for telmisartan is necessary for elderly patients or for patients with renal impairment but greater sensitivity in some older individuals cannot be ruled out. Markedly reduced telmisartan plasma levels were observed in patients on hemodialysis.
The usual regimens of therapy with MYLAN-TELMISARTAN HCTZ may be followed as long as the patient’s creatinine clearance is >30 mL/min. In patients with more severe renal impairment, loop diuretics are preferred to thiazides; in this instance MYLAN-TELMISARTAN HCTZ is not recommended.
Azotemia
Azotemia may be precipitated or increased by the hydrochlorothiazide component of MYLAN-TELMISARTAN HCTZ. Cumulative effects of the drug may develop in patients with impaired renal function since the primary route of excretion is through the urine.
If increasing azotemia and oliguria occur during treatment of severe progressive renal disease, the diuretic should be discontinued.
Genetic Polymorphism:
No studies were conducted to evaluate the influence of genetic polymorphisms on the pharmacokinetics or pharmacodynamics of telmisartan.
STORAGE AND STABILITY
MYLAN-TELMISARTAN HCTZ tablets are packaged in bottles and blisters and should be stored at room temperature (15°C - 30°C). MYLAN-TELMISARTAN HCTZ tablets are hygroscopic and require protection from moisture. Tablets should not be removed from blisters until immediately prior to administration.
DOSAGE FORMS, COMPOSITION AND PACKAGING
MYLAN-TELMISARTAN HCTZ Tablets are available as;
MYLAN-TELMISARTAN HCTZ Tablets 80mg/12.5 mg;
Red and white to off-white, oblong shaped, uncoated, biconvex, bilayered tablets debossed with ‘TH2M’ on one side and plain on the other side. The white to off-white layer may contain red tinge/specs.
MYLAN-TELMISARTAN HCTZ Tablets 80mg/25 mg;
Yellow and white to off-white, oblong shaped, uncoated, biconvex, bilayered tablets debossed with ‘TH3M’ on one side and plain on the other side. The white to off-white layer may contain yellow tinge/specs.
MYLAN-TELMISARTAN HCTZ (telmisartan/hydrochlorothiazide, 80/12.5 mg and 80/25 mg) tablets are available in bottles of 500, bottles of 100 and cartons of 28.
MYLAN-TELMISARTAN HCTZ tablets are formulated for oral administration with a combination of 80 mg of telmisartan and 12.5 mg hydrochlorothiazide or 25 mg hydrochlorothiazide.
Non-medicinal ingredients (in alphabetical order): corn starch, iron oxide red (for 80/12.5 mg tablet only), iron oxide yellow (for 80/25 mg tablet only), lactose monohydrate, magnesium stearate, mannitol, meglumine, microcrystalline cellulose, povidone, sodium hydroxide, sodium starch glycolate.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance - Telmisartan
Proper name: Telmisartan
Chemical name: 4’-[[4-methyl-6-(1-methyl-1H-benzimidazol-2-yl)-2-propyl-1H-benzimidazol-1-yl] methyl] biphenyl-2-carboxylic acid
Molecular formula and molecular mass: C33H30N4O2, 514.6 g/mol
Structural formula:
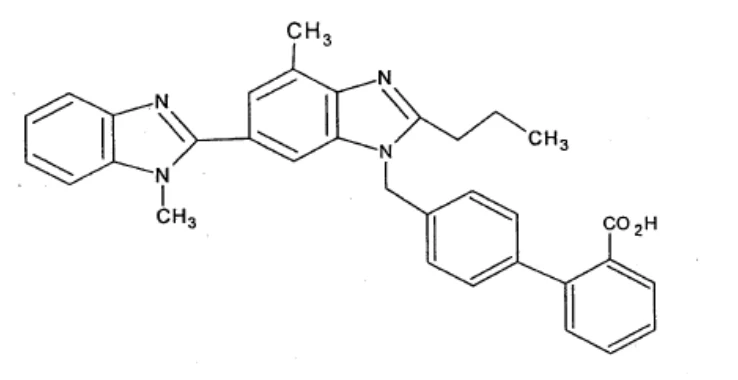
Physicochemical properties:
Description:
Telmisartan is a white or slightly yellowish, crystalline powder. It is practically insoluble in water, ethyl acetate, acetone, ethanol, pH=4.5 and 6.8 buffer. Telmisartan is very slightly soluble in 0.1N HCl.
Polymorphism:
Exhibits two different polymorphic modifications, Form A (thermodynamically more stable) and form B, and a third pseudo polymorphic form.
Melting Range:
265.0°C to 267.0°C
Drug Substance - Hydrochlorothiazide
Proper name: Hydrochlorothiazide
Chemical name: 6-chloro-3,4-dihydro-2H-1,2,4-benzothiadiazine-7-sulphonamide 1,1-dioxide
or
2H-1,2,4-benzothiadiazine-7-sulfonamide,6-chloro-3,4-dihydro-1,1-dioxide
Molecular formula and molecular mass: C7H8ClN3O4S2, 297.7 g/mol
Structural formula:
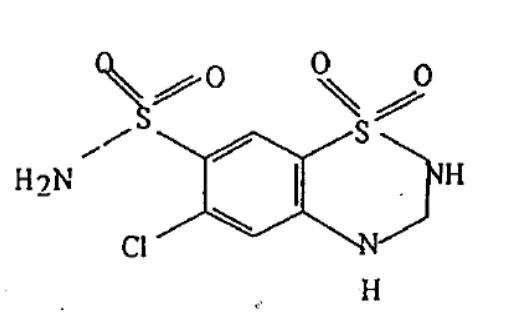
Physicochemical properties:
Description:
Hydrochlorothiazide is a white or almost white, crystalline powder. Hydrochlorothiazide is slightly soluble in water, 0.1NHCl, pH = 4.5, 6.5, 7.8 buffer, sparingly soluble in ethanol (96%) and soluble in acetone.
Melting Point:
270°C
CLINICAL TRIALS
Comparative Bioavailability Studies
A blinded, randomized, two-period, two-treatment, two-sequence, crossover, balanced, single dose bioequivalence study of Pr Mylan-Telmisartan HCTZ 80 mg/25 mg (Mylan Pharmaceuticals ULC) and Pr MICARDIS® PLUS (telmisartan/hydrochlorothiazide) 80 mg/25 mg (Boehringer Ingelheim (Canada) Ltd.) was performed in 27 healthy, Indian (South Asian) subjects under fasting conditions.
A summary of the results is presented in the following tables:
TELMISARTAN
Telmisartan ( 1 x 80 mg/25 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/ mL) | 1215.8 1429.6 (66.2) | 1191.0 1374.6 (63.5) | 102.09 | 97.16 to 107.26 |
AUCI (ng.h/ mL) | 1432.8 1731.9 (73.1) | 1438.0 1702.3 (72.0) | 99.64 | 91.26 to 108.78 |
Cmax (ng/mL) | 205.4 282.4 (107.7) | 228.8 272.6 (66.5) | 89.78 | 77.14 to 104.50 |
Tmax§ (h) | 1.33 (0.67-3.50) | 1.00 (0.33-3.00) | ||
T½€ (h) | 15.05 (38.19) | 18.50 (90.53) | ||
* Pr Mylan-Telmisartan HCTZ 80mg/25 mg Tablets, Mylan Pharmaceuticals ULC.
† Pr MICARDIS® PLUS 80mg/25 mg Tablets, Boehringer Ingelheim (Canada) Ltd. (purchased in Canada).
§ Expressed as the median (range) only.
€ Expressed as the arithmetic mean (CV %) only.
HYDROCHLOROTHIAZIDE
Hydrochlorothiazide ( 1 x 80 mg/25 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.h/ mL) | 1072.8 1112.9 (30.6) | 1100.2 1126.7 (23.7) | 97.51 | 93.66 to 101.52 |
AUCI (ng.h/ mL) | 1136.1 1181.0 (31.4) | 1164.4 1195.7 (25.1) | 97.57 | 93.67 to 101.63 |
Cmax (ng/mL) | 159.4 166.5 (32.3) | 159.7 167.1 (34.2) | 99.84 | 93.69 to 106.40 |
Tmax§ (h) | 1.67 (1.00-4.00) | 1.67 (1.00-3.00) | ||
T½€ (h) | 9.43 (12.24) | 9.63 (18.46) | ||
* Pr Mylan-Telmisartan HCTZ 80mg/25 mg Tablets, Mylan Pharmaceuticals ULC.
† Pr MICARDIS® PLUS 80mg/25 mg Tablets, Boehringer Ingelheim (Canada) Ltd. (purchased in Canada).
§ Expressed as the median (range) only.
€ Expressed as the arithmetic mean (CV %) only.
Study demographics and trial design
Table 13 - Summary of patient demographics for clinical trials
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| 502.261 | Randomised, double- blind | 80 mg telmisartan and 80/12.5 mg telmisartan/hydrochlo-rothiazide, oral, 8 weeks | 491 (245 telmisartan 80 mg; 246 telmisartan/ hydrochlorothiazide (80/12.5 mg) patients) | 55.3 (20 – 79) | males and females |
| 502.204 | Randomized, double- blind, placebo- controlled | Combinations of telmisartan & hydrochlorothiazide (T/H): 20/6.25, 20/12.5, 20/25, 40/6.25, 40/12.5, 40/25, 80/6.25, 80/12.5, 80/25, 160/6.25, 160/12.5/ 160/25 mg once daily, oral, 8 weeks | 818 | 53.0* (19 – 80) | males and females |
| 502.480 | Randomized, double- blind, placebo- controlled trial in non- responders of the 80/12.5 mg strength | 80 mg telmisartan/12.5 mg hydrochlorothiazide and 80 mg telmisartan/25 mg hydrochlorothiazide, | 713 (361 telmisartan/ hydrochlorothiazide (80/12.5 mg); 352 telmisartan/ hydrochlorothiazide (80/25 mg) | 57.2 (28 – 93) | males and females |
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender | |
|---|---|---|---|---|---|---|
| oral, 8 weeks | ||||||
* median age
T = telmisartan
H = hydrochlorothiazide
Study results
In controlled clinical trials 571 patients were exposed to telmisartan 80 mg and concomitant hydrochlorothiazide 12.5 mg.
Table 14
| Study # | Primary Measure of Efficacy | Patient Population | Summary of Results |
| 502.261 | Change from baseline in seated trough diastolic blood pressure (DBP) after 8 weeks of treatment. | Patients with mild to moderate hypertension who were taking no more than 3 antihypertensive agents at screening and who failed to respond adequately to telmisartan monotherapy | Treatment with telmisartan/ hydrochlorothiazide fixed dose combination (80/12.5 mg) lowered trough DBP by an additional 3.1 mmHg and systolic blood pressure (SBP) by 5.7 mmHg compared to telmisartan 80 mg monotherapy. Reductions in both DBP and SBP were clinically and statistically significant (p<0.01). |
| 502.204 | Change from baseline in supine trough DBP after 8 weeks of treatment. Over 800 patients completed this study with approximately 70 patients in each of the primary dose groups | Patients with mild to moderate essential hypertension | The combination of telmisartan and hydrochlorothiazide (80/12.5 mg) was significantly (p<0.01) better than either of its components administered as monotherapy in reducing trough supine diastolic blood pressure. Similar results were observed for supine systolic blood pressure and standing diastolic blood pressure. |
| 502.480 | Change from baseline in trough seated DBP after 8 weeks of treatment or at last trough observation during the double-blind treatment period | Patients without adequately controlled BP who failed to respond adequately to telmisartan/ hydrochlorothiazide (80/12.5 mg) | Treatment with T80/H25 in patients with hypertension not adequately controlled by T80/H12.5 led to an additional, clinically relevant BP reduction. T80/H25 was superior to T80/H12.5 in reducing trough seated DBP after 8 weeks of randomised treatment. All analyses of secondary efficacy endpoints such as trough seated SBP, standing BP, and BP control and response showed better results for the T80/H25 group than for the T80/H12.5 group. Both treatments were safe and well tolerated. |
BP = blood pressure
DBP = diastolic blood pressure
H = hydrochlorothiazide
SBP = systolic blood pressure
T = telmisartan
V = valsartan
Table 15: Observed Mean Reduction from Baseline in Trough Supine Diastolic Blood Pressure (mmHg)
| Placebo | Telmisartan 80 mg | |
| Placebo | 3.8 | 11.51 |
| HCTZ 12.5 mg | 7.31 | 14.92,3 |
1 compared to placebo; p<0.01
2 compared to HCTZ 12.5 mg alone; p<0.01
3 compared to telmisartan 80 mg alone; p<0.01
In 30 patients with mild to moderate hypertension, an 8-week randomized double-blind, parallel group comparison of the effect of telmisartan 80 mg versus telmisartan combined with hydrochlorothiazide (80/12.5 mg) on renal function in patients with mild to moderate hypertension was conducted. All patients randomized for the study had normal renal function. Renal parameters measured included: renal blood flow, effective renal plasma flow, glomerular filtration rate, urinary albumin, urinary protein, filtration fraction and renovascular resistance. Treatment with either regimen daily for 8 weeks did not significantly compromise renal function and there was no difference in renal function between telmisartan and telmisartan administered concomitantly with hydrochlorothiazide.
Study 502.480
At baseline, trough seated DBP means were comparable for both treatment groups with a mean of 95.0 mmHg for T80/H12.5 and 95.3 mmHg for T80/H25. Both groups showed a reduction in DBP by the end of study, with a larger reduction being observed in the T80/H25 treatment group. An adjusted mean change from baseline of -5.5 mmHg was observed for the T80/H12.5 group compared with an adjusted mean change of -7.1 mmHg for the T80/H25 group. The difference (95% CI) in the adjusted means of -1.6 mmHg (-2.5 mmHg, -0.6 mmHg) indicated the additional reduction in mean trough DBP present in the T80/H25 group. This difference was statistically significant (p=0.0012), which shows the superiority of T80/H25 over T80/H12.5 in reducing mean trough seated DBP in patients not responding adequately to T80/H12.5.
The analysis of the change from baseline in trough seated SBP at the last visit during the double-blind treatment phase was performed using the same methodology as for the primary endpoint. At baseline, trough seated SBP means of the 2 groups were comparable, with a mean of 147.4 mmHg for T80/H12.5 and 147.9 mmHg for T80/H25. Mean trough seated SBP decreased in both treatment groups by the end of study; the larger reduction was observed in the T80/H25 group. The adjusted mean change from baseline in the T80/H12.5 group was -7.1 mmHg, while for T80/H25 it was -9.8 mmHg. The difference (95% CI) between the groups in the adjusted means was -2.7 mmHg (-4.2 mmHg, -1.2 mmHg) with a p-value of 0.0003. The data show that treatment with T80/H25 reduced mean trough seated SBP more than T80/H12.5.
Table 16: Analysis of Change from Baseline to the End of Study in Trough Seated DBP (FAS)
| Trough Seated DBP [mmHg] | T80/H12.5 N = 347 | T80/H25 N = 340 | |||
| Baseline: | Mean (SD) | 95.0 | (4.4) | ||
| 95.3 | (4.7) | ||||
| End of Study: | Mean (SD) | 89.6 | (7.3) | 88.3 | (7.5) |
| Adjust Mean* (SE) | 89.6 | (0.4) | 88.0 | (0.5) | |
| Change to End of Study: | Mean (SD) |
| (6.4) |
| (6.8) |
| Adjusted Mean* (SE) |
| (0.4) |
| (0.5) | |
| Difference to T80/T12.5: | Adjusted Mean* (SE) |
| |||
| 95% CI | (-2.5, - 0.6) | ||||
| p-value | 0.0012 | ||||
*Adjusted for baseline trough seated DBP and pooled country.
Table 17: Analysis of Change from Baseline to the End of Study in Trough Seated SBP (FAS)
| Trough Seated SBP [mmHg] | T80/H12.5 N = 347 | T80/H25 N = 340 | |
| Baseline: | Mean (SD) | 147.4 (13.2) | 147.9 (12.8) |
| End of Study: | Mean (SD) | 141.8 (13.8) | 139.5 (12.3) |
| Adjust Mean* (SE) | 140.6 (0.7) | 137.9 (0.7) | |
| Change to End of Study: | Mean (SD) |
|
|
| Adjusted Mean* (SE) |
|
| |
| Difference to T80/T12.5: | Adjusted Mean* (SE) |
| |
| 95% CI | (- 4.2, - 1.2) | ||
| p-value | 0.0003 | ||
*Adjusted for baseline trough seated SBP and pooled country.
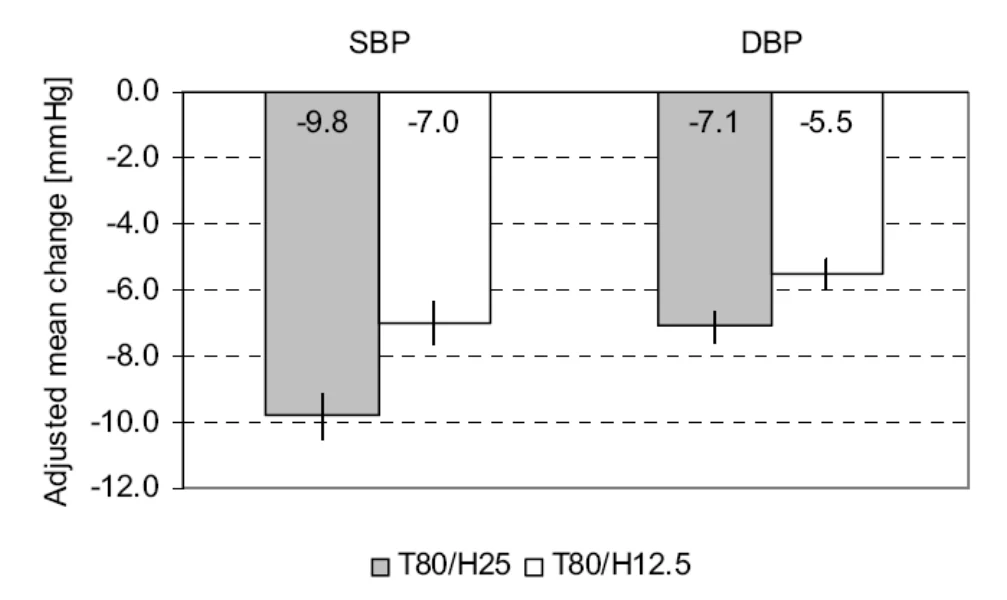
Figure 1: Adjusted (for baseline and country) mean change from baseline (with SE) of trough seated BP in the pivotal trial 502.480
In this study, both treatments were generally well tolerated as evidenced by a similar incidence of adverse event (AE) frequencies between T80/H12.5 (29.6%) and T80/H25 (31.5%) and the data obtained were consistent with the known safety profile of telmisartan/hydrochlorothiazide. Frequently reported AEs in one or the other treatment arm (overall incidence ≥1% or 8 patients) were back pain (1.9% of the T80/H12.5 patients and vs. 2.0% of the T80/H25 patients), bronchitis (2.2% vs. 1.1%), headache (2.8% vs. 0.6%), palpitations (1.4% vs. 0.9%), and nasopharyngitis (0.6% vs. 1.7%). The frequency of AEs events considered drug related was also similar (5.0% for T80/H12.5 and 5.7% for T80/H25). Two serious AEs considered drug-related by the investigators were reported in the trial (atrioventricular block third degree in the T80/H12.5 group and atrial flutter in the T80/H25 group).
Comparative Bioavailability Studies
An open-label, randomized, 4-way crossover, replicate-design study was conducted to compare the bioavailability following single oral administration of telmisartan (80 mg) and hydrochlorothiazide (12.5 mg) administered as either telmisartan/hydrochlorothiazide or as the individual monotherapy formulations. Twenty (10M/10F) healthy subjects participated in this study. Comparative measures of exposure to telmisartan and hydrochlorothiazide were based on AUC and Cmax. The results of this study demonstrated that both telmisartan and hydrochlorothiazide had similar bioavailabilities administered as either telmisartan/hydrochlorothiazide or as the single entity formulations.
Conventional average bioequivalence, average scaled bioequivalence, and individual bioequivalence (as a secondary analysis) using a moment-based scaled approach were evaluated with respect to Telmisartan pharmacokinetic variables. With respect to HCTZ pharmacokinetic variables, conventional average bioequivalence was evaluated. The upper bounds of the one- sided 95% confidence interval for the average, scaled bioequivalence measure Mas are, on the ratio scale, 109.4% and 113.8% for the primary pharmacokinetic variables AUC0-∞ and Cmax, respectively. These upper bounds of the confidence intervals are below the upper bound of the bioequivalence range, 125%. Thus average, scaled bioequivalence with respect to the variables AUC0-∞ and Cmax is shown. Similarly, average, scaled bioequivalence with respect to the secondary variable AUC0-48h was shown. The 90% confidence intervals for the “test/reference” mean ratio for the primary pharmacokinetic variables AUC0-∞ and Cmax are 100.0% to 111.0% and 106.8% to 129.0%, respectively. The confidence interval for AUC0-∞ falls in the bioequivalence range of 80% to 125%, while the confidence interval for Cmax falls in the bioequivalence range of 75% to 133%. The confidence interval for the “test/reference” mean ratio of the secondary variable AUC0-48h falls in the 80% to 125%, bioequivalence range.
Table 18: Results for Telmisartan
Telmisartan (80 mg) From measured data Adjusted Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Fixed dose combination (Test)* | Individual tablets (Reference)† | % Ratio of Adjusted Geometric Means | 90% Confidence Interval |
| AUC0-48h | 875.9 | 820.7 | 106.7 | 101.1 - 112.7 |
| (ng·h/ml) | 1158 (85.51) | 1082 (83.46) | ||
| AUC0-∞ | 1034.5 | 981.9 | 105.4 | 100.0 - 111.0 |
| (ng·h/ml) | 1414 (92.50) | 1364 (91.97) | ||
| CMAX | 196.4 | 167.3 | 117.4 | 106.8 - 129.0 |
| (ng/mL) | 251.5 (87.88) | 207.0 (71.58) | ||
TMAX § (h) | 1.00 (0.50 - 2.00) | 1.00 (0.50 - 2.00) | ||
T½ ‖ (h) | 24.12 (29.65) | 24.73 (35.90) | ||
* batch no. 9960326
† Telmisartan© 80 mg oblong tablet, batch no. 9960326
§ Expressed as the median (range) only.
‖ Expressed as the arithmetic mean (CV%) only.
For Hydrochlorothiazide, the 90% confidence intervals for the “test/reference” mean ratio for the primary pharmacokinetic variables AUC0-∞ and Cmax are 91.8% to 109.5% and 90.8% to 107.4%, respectively. The confidence intervals for the “test/reference” mean ratio of the pharmacokinetic variable Ae0-48h is 91.0% to 103.9%. All confidence intervals fall in the bioequivalence range of 80% to 125%.
Table 19: Results for Hydrochlorothiazide
Hydrochlorothiazide (12.5 mg) From measured data Adjusted Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Fixed dose combination (Test)* | Individual tablets (Reference)† | % Ratio of Adjusted Geometric Means | 90% Confidence Interval |
| AUC0-24h | 478.1 | 467.2 | 102.3 | 97.3 - 107.6 |
| (ng·h/ml) | 493.9 (25.73) | 475.04 (19.09)) | ||
| AUC0-∞ | 575.4 | 574.0 | 100.3 | 91.8 - 109.5 |
| (ng·h/ml) | 580.4 (27.46) | 563.9 (19.85) | ||
| CMAX | 73.1 | 74.1 | 98.7 | 90.8 - 107.4 |
| (ng/mL) | 75.33 (26.14) | 75.72 (26.61) | ||
TMAX § (h) | 2.00 (1.00 -3.00) | 2.00 (1.00 -3.00) | ||
T1/2 ‖ (h) | 11.35 (43.10) | 11.51 (36.33) | ||
* batch no. 9960326
† Hydrochlorothiazide 12.5 mg tablet, batch no. F4260
§ Expressed as the median (range) only.
‖ Expressed as the arithmetic mean (CV%) only.
DETAILED PHARMACOLOGY
Animal
The effect of telmisartan in combination with hydrochlorothiazide was investigated in spontaneously hypertensive rats. Repeated oral administration of telmisartan at a dose of 3 mg/kg/day for 5 days to conscious rats reduced mean arterial blood pressure (MAP) significantly and persistently with maximal decrease in MAP of approximately 36 mmHg. Hydrochlorothiazide alone (10 mg/kg/day) had no effect on blood pressure in this model, however when administered in combination with telmisartan (3 mg/kg/day), induced a significantly greater antihypertensive effect than with telmisartan alone, with a maximal reduction of about 53 mmHg. Furthermore, the telmisartan/hydrochlorothiazide combination ameliorated the alteration in potassium balance when compared to hydrochlorothiazide alone in this model.
A slight, significant increase in heart rate (~ 20 bpm) was observed during treatment with telmisartan and hydrochlorothiazide in combination; this increase reverted to control values during the washout period.
Human
Drug Interaction - Telmisartan and Hydrochlorothiazide
A randomized, 3-way crossover study was conducted in 14 healthy subjects to investigate the potential for a pharmacokinetic interaction between telmisartan and hydrochlorothiazide when administered concomitantly. Oral doses of either hydrochlorothiazide alone (25 mg, qd x 7), telmisartan alone (160 mg, qd x 7) or both drugs at the respective doses in combination, daily for 7 days were administered. Plasma concentrations of both telmisartan and hydrochlorothiazide were assessed at steady state. Based on a comparative analysis, it was concluded that there is no pharmacokinetic interaction between telmisartan and hydrochlorothiazide when administered concomitantly.
Bioavailability
See CLINICAL TRIALS, Comparative Bioavailability Studies.
TOXICOLOGY
Chronic Toxicity
Telmisartan and Hydrochlorothiazide
Repeated-dose toxicity studies of 26 weeks duration were conducted in both rats and dogs. These studies were designed to compare the toxicological profiles of telmisartan and hydrochlorothiazide administered alone, with that of the drugs given in combination.
Table 20: Repeat Dose Toxicity Studies Conducted with Telmisartan/Hydrochlorothiazide
| Species | Dose Telmisartan/HCTZ (mg/kg/day) | Duration | NOTEL (mg/kg/day) |
| Rat (Chbb:THOM) | 0/0 | 26 weeks | 0.1/0.03 |
| (20/sex/dose) | 0.1/0.03 | ||
| 4/1.2 | |||
| 50/7.8 | |||
| 50/15.6 | |||
| 50/0 | |||
| 0/15.6 | |||
| Dogs (Beagle) | 0/0 | 26 weeks | 0.25/0.08 |
| (4/sex/dose) | 0.25/0.08 | ||
| 1/0.31 | |||
| 4/0.63 | |||
| 4/1.25 | |||
| 4/0 | |||
| 0/1.25 |
HCTZ = hydrochlorothiazide
Repeated, oral doses of telmisartan with and without hydrochlorothiazide for 26 weeks in rats induced a pronounced and persistent dose-related decrease of blood pressure without reflex tachycardia. At 50 mg/kg of telmisartan, the addition of hydrochlorothiazide had an additive effect on the blood pressure-lowering effect of telmisartan. Clinical laboratory and histopathological changes were similar to those observed in previous toxicity studies in rats with telmisartan alone. Essentially, there were no new toxicities observed with the addition of hydrochlorothiazide.
In dogs, repeated oral doses of telmisartan with hydrochlorothiazide administered for 26 weeks was associated with nephrotoxicity, which is consistent with the findings from previous studies with telmisartan alone. The addition of 0.63 mg/kg of hydrochlorothiazide to 4 mg/kg telmisartan did not increase renal toxicity whereas the co-administration of 1.25 mg/kg hydrochlorothiazide significantly increased toxicity. The exacerbation of nephrotoxicity in this species can be ameliorated by saline supplementation.
Reproductive Toxicity
Telmisartan and hydrochlorothiazide: A developmental toxicity study was conducted in rats with oral doses of telmisartan and hydrochlorothiazide used in combination (3.2/1.0, 15/4.7,
50/15.6 and 0/15.6 mg/kg/day). Although the two higher dose combinations appeared to be more toxic to the dams than either drug alone, the results indicated the lack of teratogenic, fetotoxic or embryotoxic potential of the telmisartan/hydrochlorothiazide combination at the doses tested in this animal model.
Telmisartan: In studies on fertility and reproductive performance in male and female rats, no effect on mating performance, reproductive organs, or fertility in either sex or on litter parameters was observed with telmisartan oral doses of 5-100 mg/kg. No teratogenic or embryotoxic potential in rats was observed at oral doses of ≤50 mg/kg administered during gestation. However, at toxic dose levels, non-clinical studies indicated some hazardous potential of telmisartan to fetal development (increased number of late resorptions in rabbits) and to the postnatal development of the offspring: lower body weight, delayed eye opening, and higher mortality.
Telmisartan was detectable in the placenta, fetus and amniotic fluid of rats after single oral doses of 1 mg/kg.
Hydrochlorothiazide: Hydrochlorothiazide was orally administered to pregnant mice and rats during gestation, at doses of up to 3000 and 1000 mg/kg/day respectively. There was no evidence of fetotoxicity or teratogenicity.
Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies where these species were exposed via their diet, to doses of ≤100 and ≤4 mg/kg respectively, prior to mating and throughout gestation.
Carcinogenicity and Mutagenicity
No carcinogenicity or mutagenicity studies have been conducted with the combination of telmisartan and hydrochlorothiazide. However, these studies have been conducted for telmisartan and hydrochlorothiazide alone. Based on the preclinical safety profile of the telmisartan and hydrochlorothiazide combination and on human pharmacokinetic studies, there is no indication of any adverse interaction between telmisartan and hydrochlorothiazide.
Telmisartan
The carcinogenic potential of telmisartan was assessed in 2-year feeding studies in mice at doses of 10, 100 and 1000 mg/kg/day in rats at 3, 15, and 100 mg/kg/day. Drug administration did not affect overall survival time in either study nor did it affect the rate of tumour-induced mortality. There were no increases in overall tumour incidence, incidence of benign or malignant tumours or in tumour multiplicity associated with telmisartan administration.
The standard battery of genotoxicity assays did not reveal any telmisartan-related effects at either the gene or chromosome level. These assays included bacterial mutagenicity tests with Salmonella typhimurium and E. coli, a gene mutation test with CHO cells, a cytogenetic test with human lymphocytes and an in vivo mouse micronucleus assay.
Hydrochlorothiazide
The carcinogenic potential of hydrochlorothiazide was assessed in 2-year feeding studies in mice at doses of up to 600 mg/kg/day and rats at doses of up to 100 mg/kg/day. There was no evidence of carcinogenic potential in female mice or male and female rats; equivocal evidence for hepatocarcinogenicity in male mice was reported.
Hydrochlorothiazide was not genotoxic in the Ames mutagenicity assay with Salmonella typhimurium strains TA 98, TA 100, TA 1535, TA 1537 and TA 1538, in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations or in vivo assays using mouse germ cell chromosomes, Chinese hamster bone marrow chromosomes and the Drosophila sex-linked recessive lethal trait gene. Positive test results were obtained only in the in vitro CHO Sister Chromatid Exchange (clastogenicity) and in the Mouse Lymphoma Cell (mutagenicity) assays using concentrations of hydrochlorothiazide from 43 to 1300 mcg/mL and in the Aspergillus nidulans non-disjunction assay at unspecified concentrations.
REFERENCES
McGill JB, Reilly PA. Combination treatment with telmisartan and hydrochlorothiazide in black patients with mild to moderate hypertension. Clin Cardiol 2001; 24(1):66-72.
Neutel JM, Smith DHG. Dose response and antihypertensive efficacy of the AT1 receptor antagonist telmisartan in patients with mild to moderate hypertension. Adv Ther 1998;15(4):206- 217.
Young CL, Dias VC, Stangier J. Multiple-dose pharmacokinetics of telmisartan and of hydrochlorothiazide following concurrent administration in healthy subjects. J Clin Pharmacol 2000; 40(12 Pt 1):1323-30.
Pr MICARDIS® PLUS, Boehringer Ingelheim (Canada) Ltd., Product Monograph dated April 29, 2013, Control No.: 161978.