


Product Monograph - Mylan-Verapamil
ACTIONS AND CLINICAL PHARMACOLOGY
Angina and Arrhythmia
Verapamil hydrochloride is a calcium ion influx inhibitor (calcium entry blocker or calcium ion antagonist). The mechanism of the antianginal and antiarrhythmic effects of verapamil is believed to be related to its specific cellular action of selectively inhibiting transmembrane influx of calcium in cardiac muscle, coronary and systemic arteries and in cells of the intracardiac conduction system. Verapamil blocks the transmembrane influx of calcium through the slow channel (calcium ion antagonism) without affecting, to any significant degree the transmembrane influx of sodium through the fast channel. This results in a reduction of free calcium ions available within cells of the above tissues.
Verapamil's antiarrhythmic effects are believed to be brought about largely by its action on the sinoatrial
(S-A) and atrioventricular (A-V) nodes. Verapamil depresses A-V nodal conduction and prolongs
functional refractory periods. Verapamil does not alter the normal atrial action potential or intraventricular conduction time, but depresses amplitude, velocity of depolarization and conduction in depressed atrial fibers. Through this action, it interrupts re-entrant pathways and slows the ventricular rate.
Verapamil may shorten the antegrade effective refractory period of the accessory bypass tract.
Acceleration of ventricular rate and/or ventricular fibrillation has been reported in patients with atrial flutter or atrial fibrillation and a coexisting accessory A-V pathway following administration of verapamil
(see WARNINGS).
Verapamil is a potent smooth muscle relaxant with vasodilatory properties, as well as a depressant of myocardial contractility, and these effects are largely independent of autonomic influences. Its antianginal action in exertional angina seems to result from a decrease in resistance in the systemic vasculature, as well as from a direct effect on myocardial contraction. The net pharmacologic effect is a decrease in myocardial oxygen consumption. Verapamil's effectiveness in vasospastic angina is due to a decrease in coronary vascular tone.
Essential Hypertension
Verapamil exerts antihypertensive effects by inducing peripheral vasodilation and reducing peripheral vascular resistance usually without reflex tachycardia. These effects are mediated by inhibition of calcium ion influx into smooth muscle cells of the arteriolar wall. Verapamil does not blunt hemodynamic response to isometric or dynamic exercise.
Compared to baseline, verapamil administration did not affect electrolytes, glucose and creatinine. The hypotensive effect of verapamil is not blunted by an increase in sodium intake.
In hypertensive normolipidemic patients, verapamil had no effects on plasma lipoprotein fractions.
Pharmacodynamics
In a study in five healthy males, the S enantiomer was found to be 8 to 20 times more active than the R enantiomer in slowing AV conduction. In another study using septal strips isolated from the left ventricle of 5 patients with mitral disease, the S enantiomer was 8 times more potent than the R enantiiomer in reducing mycocardial contractility.
Pharmacokinetics
Verapamil hydrochloride is a racemic mixture consisting of equal portions of the R enantiomer and the S enantiomer. More than 90% of the orally administered dose of verapamil is absorbed. Upon oral administration, there is rapid stereoselective biotransformation during the first pass of verapamil through the portal circulation. The systemic concentrations of R and S enantiomer are dependent upon the route and the rate of administration and the rate and extent of release from the dosage forms.
Peak plasma concentrations are reached between 1 and 2 hours after oral administration. Chronic oral administration of 120 mg of verapamil every 6 hours resulted in plasma levels of verapamil ranging from
125 to 400 ng/mL, with higher values reported occasionally. A nonlinear correlation between the verapamil dose administered and verapamil plasma levels does exist. In initial dose titration with verapamil a relationship exists between verapamil plasma concentration and prolongation of the PR interval.
The mean elimination half-life in single-dose studies ranged from 2.8 to 7.4 hours. In these same studies, after repetitive dosing the half-life increased to a range from 4.5 to 12.0 hours (after less than 10 consecutive doses given 6 hours apart). Half-life of verapamil increases during titration due to saturation of hepatic enzyme systems as plasma verapamil levels rise. Aging affects the pharmacokinetics of verapamil. Elimination half-life is prolonged in the elderly.
In healthy men, orally administered verapamil undergoes extensive metabolism in the liver. Thirteen metabolites have been identified in plasma, all except norverapamil are present in trace amounts only.
Norverapamil can reach steady-state plasma concentrations approximately equal to those of verapamil itself. The cardiovascular activity of norverapamil appears to be approximately 20% that of verapamil.
Approximately 70% of an administered dose is excreted as metabolites in the urine and 16% or more in the feces within 5 days. About 3 to 4% is excreted in the urine as unchanged drug. Approximately 90% is bound
to plasma proteins. In patients with hepatic insufficiency, metabolism is delayed and elimination half-life prolonged up to 14 to 16 hours (see WARNINGS and DOSAGE AND ADMINISTRATION).
After 4 weeks of oral dosing (120 mg q.i.d.) verapamil and norverapamil levels were noted in the cerebrospinal fluid with estimated partition coefficients of 0.06 for verapamil and 0.04 for norverapamil.
A single dose comparative study was performed on non-fasted subjects using MYLAN-VERAPAMIL
TABLETS 120 mg and a marketed brand of verapamil hydrochloride tablets 120 mg. The pharmacokinetic data (arithmetic means, C.V.) for both formulations is tabulated below:
Geometric mean
Arithmetic Mean (C.V.%)
PARAMETER MYLAN-VERAPAMIL ISOPTINR RATIO OF (120 mg Tablet) (120 mg Tablet) MEANS %
AUC0-t (ng hr/mL) 466.9 473.3 99 508.6 (41.4) 512.3 (42.6)
AUCinf (ng hr/mL) 506.7 512.4 100 552.3 (41.5) 554.4 (42.4)
Cmax (ng/mL) 102.8 106.0 98 115.7 (52.0) 118.4 (48.9)
Tmax* (h) 2.27 (45.2) 2.12 (50.5)
T2* (h) 4.46 (15.3) 4.49 (16.4)
* - For Tmax and T2 arithmetic mean (standard deviation) are presented.
Influence of Food: A single dose comparative study on fasted subjects was performed using MYLAN-
VERAPAMIL TABLETS 120 mg and a marketed brand of verapamil hydrochloride tablets 120 mg. The pharmacokinetic data (arithmetic means, C.V.) for both formulations is tabulated below:
Geometric mean
Arithmetic Mean (C.V.%)
PARAMETER MYLAN-VERAPAMIL ISOPTINR RATIO OF
(120 mg Tablet) (120 mg Tablet) MEANS %
AUC0-t (ng hr/mL) 440.9 420.6 105
493.8 (49.6) 463.5 (43.2)
AUCinf (ng hr/mL) 462.7 452.9 102
515.7 (49.3) 495.9 (42.4)
Cmax (ng/mL) 134.5 125.7 107
151.6 (50.5) 137.0 (40.9)
Tmax* (h) 1.281 (0.588) 1.321 (0.563)
T2* (h) 3.485 (1.587) 3.376 (1.415)
* - For Tmax and T2 arithmetic mean (standard deviation) are presented.
INDICATIONS AND CLINICAL USE
MYLAN-VERAPAMIL (Verapamil hydrochloride) Tablets are indicated in:
- 1. Chronic stable angina of effort
- 2. Angina resulting from coronary artery spasm
- 3. Obstructive hypertrophic cardiomyopathy, where surgery is not otherwise indicated
- 4. Atrial fibrillation or flutter with rapid ventricular response not otherwise controllable with digitalis preparations
- 5. Follow-up treatment to the use of injectable verapamil in paroxysmal supraventricular tachycardia
- 6. Verapamil is indicated in the treatment of mild to moderate essential hypertension. It should normally be used in those patients in whom treatment with diuretics or beta-blockers has been associated with unacceptable adverse effects.
Verapamil can be tried as an initial agent in those patients in whom the use of diuretics and/or beta-blockers is contraindicated or in patients with medical conditions in which these drugs frequently cause serious adverse effects.
Combination of verapamil with a diuretic has been found to be compatible and showed additive antihypertensive effect.
Verapamil should not be used concurrently with beta-blockers in the treatment of hypertension (see
PRECAUTIONS, Drug Interactions).
Safety of concurrent use of verapamil with other antihypertensive agents has not been established and such use cannot be recommended at this time.
CONTRAINDICATIONS
- 1. Complicated myocardial infarction (patients who have ventricular failure manifested by pulmonary congestion)
- 2.
Severe congestive heart failure and/or severe left ventricular dysfunction (i.e ejection fraction
<40%), unless secondary to a supraventricular tachycardia amenable to oral verapamil therapy
- 3. Cardiogenic shock
- 4. Severe hypotension
- 5. Second or third degree A-V block
- 6. Sick sinus syndrome (see WARNINGS)
- 7. Marked bradycardia
- 8. Hypersensitivity to the drug
- 9.
Patients with atrial flutter or atrial fibrillation and an accessory bypass tract (e.g.
Wolff-Parkinson-White, Lown-Ganong-Levine syndromes) (see WARNINGS).
WARNINGS
General: In patients with angina or arrhythmias using antihypertensive drugs, the additional hypotensive effect of verapamil should be taken into consideration.
Heart Failure: Because of verapamil's negative inotropic effect, do not use the drug in patients with poorly compensated congestive heart failure, unless the failure is complicated by or caused by a dysrhythmia. If verapamil is used in such patients, they must be digitalized prior to treatment. It has been reported that digoxin plasma levels may increase with chronic verapamil administration (see PRECAUTIONS, Drug
Interactions).
The use of verapamil in the treatment of hypertension is not recommended in patients with heart failure caused by systolic dysfunction.
Hypotension: Hypotensive symptoms of lethargy and weakness with faintness have been reported following single oral doses and even after some months of treatment. In some patients it may be necessary to reduce the dose.
Conduction Disturbance: Verapamil slows conduction across the A-V node and rarely may produce second or third degree A-V block, bradycardia and in extreme cases, asystole.
Verapamil causes dose-related suppression of the S-A node. In some patients, sinus bradycardia may occur, especially in patients with a sick sinus syndrome (S-A nodal disease), which is more common in older patients (see CONTRAINDICATIONS).
Bradycardia: The total incidence of bradycardia (ventricular rate less than 50 beats/min) was 1.4% in controlled studies. Asystole in patients other than those with sick sinus syndrome is usually of short
duration (few seconds or less), with spontaneous return to A-V nodal or normal sinus rhythm. If this does not occur promptly, appropriate treatment should be initiated immediately (see SYMPTOMS AND
TREATMENT OF OVERDOSAGE).
Accessory Bypass Tract (Wolff-Parkinson-White or Lown-Ganong-Levine):
Verapamil may result in significant acceleration of ventricular response during atrial fibrillation or atrial flutter in the Wolff-Parkinson-White (WPW) or Lown-Ganong-Levine syndromes after receiving intravenous verapamil. Although a risk of this occurring with oral verapamil has not been established, such patients receiving oral verapamil may be at risk and its use in these patients is contraindicated (see
CONTRAINDICATIONS).
Concomitant Use with Beta Blockers: Generally, oral verapamil should not be given to patients receiving beta-blockers since the depressant effects on myocardial contractility, heart rate and A-V conduction may be additive. However, in exceptional cases when in the opinion of the physician, concomitant use in angina and arrhythmias is considered essential, such use should be instituted gradually under careful supervision. If combined therapy is used, close surveillance of vital signs and clinical status should be carried out and the need for continued concomitant treatment periodically assessed.
Verapamil gives no protection against the dangers of abrupt beta-blocker withdrawal and such withdrawal should be done by the gradual reduction of the dose of beta-blocker. Then verapamil may be started with the usual dose.
Patients with Hypertrophic Cardiomyopathy: In 120 patients with hypertrophic cardiomyopathy who received therapy with verapamil at doses up to 720 mg/day, a variety of serious adverse effects was seen.
Three patients died in pulmonary edema; all had severe left ventricular outflow obstruction and a past history of left ventricular dysfunction. Eight other patients had pulmonary edema and/or severe
hypotension, abnormally high (greater than 20 mm Hg) pulmonary wedge pressure and a marked left ventricular outflow obstruction were present in most of these patients. Concomitant administration of quinidine (see PRECAUTIONS, Drug Interactions) preceded the severe hypotension in 3 of the 8 patients (2 of whom developed pulmonary edema). Sinus bradycardia occurred in 11% of the patients, second degree A-V block in 4%, and sinus arrest in 2%. It must be appreciated that this group of patients had a serious disease with a high mortality rate. Most adverse effects responded well to dose reduction, but in some cases, verapamil use had to be discontinued.
Elevated Liver Enzymes: Elevation of transaminase with and without concomitant elevations in alkaline phosphatase and bilirubin have been reported. Several published cases of hepatocellular injury produced by verapamil have been proven by rechallenge. Clinical symptoms of malaise, fever, and/or right upper quadrant pain, in addition to elevation of AST (SGOT), ALT (SGPT) and alkaline phosphatase have been reported. Periodic monitoring of liver function in patients receiving verapamil is therefore prudent.
Hepatic Insufficiency: Because verapamil is extensively metabolized by the liver, it should be administered cautiously to patients with impaired hepatic function, since the elimination half-life of verapamil in these patients is prolonged 4-fold (from 3.7 to 14.2 hours). A decreased dosage should be used in patients with hepatic insufficiency and careful monitoring for abnormal prolongation of the PR interval or other signs of excessive pharmacologic effect should be carried out (see PHARMACOLOGY,
Pharmacokinetics and Dosage).
Renal Insufficiency: About 70% of an administered dose of verapamil is excreted as metabolites in the urine. In one study in healthy volunteers, the total body clearance after intravenous administration of verapamil was 12.08 mL/min/kg, while in patients with advanced renal disease it was reduced to 5.33 mL/min/kg. This pharmacokinetic finding suggests that renal clearance of verapamil in patients with
renal disease is decreased. In 2 studies with oral verapamil no difference in pharmacokinetics could be demonstrated. Therefore, until further data are available, verapamil should be used with caution in patients with impaired renal function. These patients should be carefully monitored for abnormal prolongation of the PR interval or other signs of excessive pharmacologic effect (see DOSAGE AND
ADMINISTRATION).
PRECAUTIONS
Atypical lens changes and cataracts were observed in beagle dog studies at high doses. This has been concluded to be species specific for the beagle dog. (These ophthalmological changes were not seen in a second study.) No similar changes have been observed in long-term prospective human ophthalmological trials.
Verapamil does not alter total serum calcium levels. However, one report suggested that calcium levels above the normal range may decrease the therapeutic effect of verapamil.
Patients With Attenuated (Decreased) Neuromuscular Transmission: It has been reported that verapamil decreases neuromuscular transmission in patients with Duchenne's muscular dystrophy, and that verapamil prolongs recovery from the neuromuscular blocking agent vercuronium. It may be necessary to decrease the dosage of verapamil when it is administered to patients with attenuated neuromuscular transmission.
Use in the Elderly: Caution should be exercised when verapamil is administered to elderly patients ($65 years) especially those prone to developing hypotension or those with a history of cerebrovascular
insufficiency. The incidence of adverse reactions is approximately 4% higher in the elderly. The adverse reactions occurring more frequently include dizziness and constipation.
Use in Pregnancy: Teratology and reproduction studies have been performed in rabbits and rats at oral doses up to 1.5 (15 mg/kg/day) and 6 (60 mg/kg/day) times the human oral daily dose, respectively, and have revealed no evidence of teratogenicity or imparired fertility. In rat however, this multiple of the human dose was embryocidal and retarded fetal growth and development, probably because of adverse maternal effects reflected in reduced weight gains of the dams. This oral dose has also been shown to cause hypotension in rats.
There are no studies in pregnant women. However, verapamil crosses the placental barrier and can be detected in umbilical vein blood at delivery. Verapamil is not recommended for use in pregnant women unless the potential benefits outweight potential risks to mother and fetus.
Labor and Delivery: It is not known whether the use of verapamil during labor or delivery has immediate or delayed adverse effects on the fetus, or whether it prolongs the duration of labor, increases the need for forceps delivery or other obstetric intervention. Preliminary studies have shown that unchanged drug crosses the placental barrier. In all patients of childbearing potential, anticipated benefits must be weighed against possible hazards.
Use in Nursing Mothers: Verapamil is excreted in human milk. Because of the potential for adverse reactions in nursing infants from verapamil, nursing should be discontinued while the drug is administered.
Use in Children: The safety and dosage regimen of verapamil in children has not yet been established.
DRUG INTERACTIONS
Digoxin: Verapamil treatment increases serum digoxin levels by 50 to 75% during the first week of therapy, and this can result in digitalis toxicity. In patients with hepatic cirrhosis the influence of verapamil on digoxin kinetics is magnified. Verapamil may reduce total body clearance and extrarenal clearance of digitoxin by 27 and 29%, respectively. Maintenance and digitalization doses should be reduced when verapamil is administered and the patient should be reassessed to avoid over- or underdigitalization. Whenever overdigitalization is suspected, the daily dose of digitalis should be reduced or temporarily discontinued. On discontinuation of verapamil use, the patient should be reassessed to avoid underdigitalization.
Quinidine: In a small number of patients with hypertrophic cardiomyopathy, concomitant use of verapamil and quinidine resulted in significant hypotension. Until further data are obtained combined therapy of verapamil and quinidine in patients with hypertrophic cardiomyopathy should probably be avoided. The electrophysiologic effects of quinidine and verapamil on A-V conduction were studied in 8 patients. Verapamil significantly counteracted the effects of quinidine on A-V conduction. There has been a report of increased quinidine levels during verapamil therapy.
Beta-Adrenergic Blockers: The concomitant administration of verapamil with beta-blockers can result in severe adverse effects (see WARNINGS).
Antihypertensive Agents: Verapamil administered concomitantly with other antihypertensive agents such as vasodilators, ACE inhibitors and diuretics, may have an additive effect on lowering blood pressure. In patients with angina or arrhythmias using anti-hypertensive drugs, this additional hypotensive effect should be taken into consideration. Verapamil should not be combined with beta
blockers for the treatment of hypertension. Concomitant use of verapamil and alpha-adrenoreceptor blockers may result in excessive fall in blood pressure in some patients as observed in one study following the concomitant administration of verapamil and prazosin.
Nitrates, Diuretics: No cardiovascular adverse effects have been attributed to any interaction between these agents and verapamil.
Neuromuscular Blocking Agents: Clinical data and animal studies suggest that verapamil may potentiate the activity of neuromuscular blocking agents (curare-like and depolarizing). It may be necessary to decrease the dose of verapamil and/or the dose of the neuromuscular blocking agent when the drugs are used concomitantly.
Carbamazepine: The concomitant oral administration of verapamil and carbamazepine may potentiate the effects of carbamazepine neurotoxicity. Symptoms include nausea, diplopia, headache, ataxia or dizziness.
Disopyramide: Until data on possible interactions between verapamil and disopyramide are obtained, disopyramide should not be administered within 48 hours before or 24 hours after verapamil administration.
Flecainide: A study in healthy volunteers showed that the concomitant administration of flecainide and verapamil may have additive effects on myocardial contractility, A-V conduction and repolarization.
Concomitant therapy with flecainide and verapamil may result in additive negative inotropic effect and prolongation of atrioventricular conduction.
Cimetidine: Two clinical trials have shown a lack of significant verapamil interaction with cimetidine.
A third study showed cimetidine reduced verapamil clearance and increased elimination half-life.
Lithium: Increased sensitivity to the effects of lithium (neurotoxicity) has been reported during concomitant verapamil-lithium therapy with either no change or an increase in serum lithium levels.
However, the addition of verapamil has also resulted in the lowering of serum lithium levels in patients receiving chronic stable oral lithium. Patients receiving both drugs must be monitored carefully.
Rifampin: Therapy with rifampin may markedly reduce oral verapamil bioavailability.
Phenobarbital: Phenobarbital therapy may increase verapamil clearance.
Cyclosporin: Verapamil therapy may increase serum levels of cyclosporin.
Theophylline: Verapamil may inhibit the clearance and increase the plasma levels of theophylline.
Sulfinpyrazone: Increased clearance and decreased bioavailability of verapamil may occur.
Inhalation Anesthetics: When used concomitantly, inhalation anesthetics and calcium antagonists, such as verapamil, should be titrated carefully because additive hemodynamic depressive effects have been observed.
ADVERSE EFFECTS
In 4826 patients treated with verapamil HCl tablets for arrhythmias, angina or hypertension, the overall adverse reaction rate in these patients was 37.1% and the dropout rate was 10.2%. The majority of these patients were seriously ill and treated under emergency drug regulations.
In controlled pivotal studies with 128 patients treated with sustained release verapamil HCl tablets for hypertension the overall adverse reaction rate was 21.7% and the dropout rate was 3.9%.
The most common adverse reactions were: constipation (7.3%), dizziness (3.2%) and nausea (2.7%). In hypertension studies, constipation occurred in 18.5% of patients on verapamil and 4.7% of patients on sustained-release verapamil tablets.
The most serious adverse reactions reported with verapamil are heart failure (1.8%), hypotension (2.5%),
A-V block (1.2%) and rapid ventricular response (see WARNINGS).
The following adverse reactions divided by body system have been reported in clinical trials or marketing experience. When incidences are shown, they are calculated based on the 4954 (4826 " 128) patient base.
Cardiovascular
hypotension 2.5%
edema 2.1%
CHF/pulmonary edema 1.9%
bradycardia 1.4%
A-V block
total (first, second and third degree) 1.2%
second and third degree 0.8%
Central Nervous System
dizziness 3.2%
headache 2.2%
fatigue 1.7%
Gastrointestinal
constipation 7.3%
nausea 2.7%
The following reactions were reported in 1% or less of patients:
Cardiovascular: flushing, angina pectoris, atrioventricular dissociation, chest pain, claudication, myocardial infarction, palpitations, purpura, syncope, severe tachycardia, developing or worsening of heart failure, development of rhythm disturbances, ventricular dysrhythmias, painful coldness and numbness of extremities.
Central Nervous System: cerebrovascular accident, confusion, equilibrium disorders, insomnia, muscle cramps, paresthesia, psychotic symptoms, shakiness, somnolence, excitation, depression, rotary nystagmus, vertigo, tremor, extrapyramidal disorders, muscle fatigue, hyperkinesis.
Gastrointestinal: diarrhea, dry mouth, gastrointestinal distress, gingival hyperplasia, vomiting.
Respiratory: dyspnea, bronchospasm.
Urogenital: gynecomastia, increased frequency of urination, spotty menstruation, oligo-menorrhea, impotence.
Hematologic and Lymphatic: ecchymosis or bruising.
Skin: arthralgia and rash, exanthema, hair loss, hyperkeratosis, macules, sweating, urticaria,
Stevens-Johnson Syndrome, erythema multiforme, pruritus.
Special Senses: blurred vision, diplopia.
Hepatotoxicity with elevated enzymes (AST (SGOT), ALT (SGPT), alkaline phosphatase) and bilirubin levels, jaundice and associated symptoms of hepatitis with cholestasis have been reported (see
WARNINGS).
Isolated cases of angioedema have been reported. Angioedema may be accompanied by breathing difficulty.
In clinical trials related to the control of ventricular response in digitalized patients who had atrial fibrillation or flutter, ventricular rates below 50 at rest occurred in 15% of patients and asymptomatic hypotension occurred in 5% of patients.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Based on reports of intentional overdosage of verapamil, the following symptoms have been observed.
Hypotension occurs, varying from transient to severe. Conduction disturbances seen included:
prolongation of A-V conduction time, A-V dissociation, nodal rhythm, ventricular fibrillation and ventricular asystole.
Treatment of overdosage should be supportive. Gastric lavage should be undertaken even later than 12 hours after ingestion, if no gastrointestinal motility is present. Beta-adrenergic stimulation or parenteral administration of calcium solutions may increase calcium ion influx across the slow channel. These pharmacologic interventions have been effectively used in treatment of overdosage with verapamil.
Clinically significant hypotensive reactions should be treated with vasopressor agents. A-V block is treated with atropine and cardiac pacing. Asystole should be handled by the usual advanced cardiac life support measures including the use of vasopressor agents, e.g., isoproterenol HCl. Verapamil is not removed by hemodialysis.
Suggested Treatment of Acute Cardiovascular Adverse Effects
| Adverse Effect | Proven Effective Treatment | Treatment with Good Theoretical Rationale | Supportive Treatment |
Shock, cardiac failure, severe hypotension | Calcium salts, e.g., Calcium gluconate I.V; IV metaraminol bitartrate* | Dopamine HCl I.V.* Dobutamine HCl IV* | I.V. fluids; Trendelenburg position |
Bradycardia, A-V block, asystole | IV isoproterenol HCl*; IV atropine sulphate; Cardiac pacing | -- | IV fluids (slow drip) |
Rapid ventricular rate (due to antegrade conduction flutter/ fibrillation with W-P-W or L-G-L syndrome) | D.C cardioversion (high energy may be required); IV procainamide; IV lidocaine HCl | -- | IV fluids (slow drip) |
Actual treatment and dosage should depend on the severity of the clinical situation and the judgment of the treating physician. Patients with hypertrophic cardiomyopathy treated with verapamil should not be administered positive inotropic agents. (Marked by asterisks)
DOSAGE AND ADMINISTRATION
MYLAN-VERAPAMIL (Verapamil hydrochloride) Tablets should be taken with food (see
PHARMACOLOGY, Pharmacokinetics).
- 1. Angina Pectoris
Usual starting dose in adults is 80 mg 3 to 4 times daily. This may be increased to 120 mg 3 to 4 times daily until optimum response is obtained. The dose should not be increased beyond 480 mg/day. In some cases the dose may be decreased following clinical improvement.
- 2. Obstructive Hypertrophic Cardiomyopathy:
Usual starting dose is 80 to 120 mg 3 to 4 times daily, and occasionally patients may require doses up to
600 to 720 mg/day.
- 3. Paroxysmal Supraventricular Tachycardia:
Oral treatment should replace intravenous therapy as soon as possible. In adults, use the same dosage schedule as for angina pectoris. Duration of treatment will depend on the underlying cause and history of recurrence. At this time there is insufficient data to establish a safe and effective oral dose for children.
- 4. Atrial Fibrillation and Flutter with Rapid Ventricular Response:
Verapamil may be administered to adults not completely controlled with digitalis preparations. The same dosage as for angina pectoris can be used but the physician should be aware that digoxin plasma levels may increase with verapamil administration and downward adjustment of the digoxin dose may be necessary (see PRECAUTIONS, Drug Interactions).
- 5. Mild to Moderate Essential Hypertension: (see INDICATIONS.)
The dosage should be individualized by titration depending on patient tolerance and responsiveness to verapamil.
The usual initial adult dose is 80 mg 3 times a day. If required, the dose may be increased up to 160 mg 3 times a day. A maximum daily dose of 480 mg should not be exceeded.
The antihypertensive effects of verapamil tablets are evident within the first week of therapy. Optimal doses are usually lower in patients also receiving diuretics since additive antihypertensive effects can be expected.
Elderly: Lower dosage may be warranted in elderly patients ($65 years) (see PRECAUTIONS). The dosage should be carefully and gradually adjusted depending on patient tolerability and response.
Patients with Impaired Hepatic and Renal Function: MYLAN-VERAPAMIL should be administered cautiously to patients with liver or renal function impairment. The dosage should be carefully and gradually adjusted depending on patient tolerance and response. These patients should be monitored carefully for abnormal prolongation of the PR interval or other signs of overdosage. At this time, verapamil tablets should not be used in patients with severe hepatic dysfunction (see WARNINGS).
PHARMACEUTICAL INFORMATION
DRUG SUBSTANCE
Proper Name : Verapamil hydrochloride, BP
Chemical Name: Benzeneacetonitrile, α-[3-[[2-(3,4-dimethoxy-
phenyl)ethyl]methylamino]propyl]]-3,4-dimethoxy-
α-(1-methylethyl)-, monohydrochloride,(")-.
Structural formula:
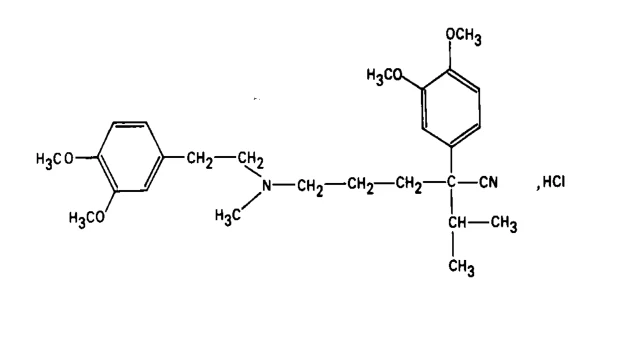
Molecular formula: C27H38N2O4 @ HCl
Molecular Weight: 491.1
Description: A white, crystalline powder. It melts at about 144 ºC. Soluble in water; soluble in chloroform; sparingly soluble in ethanol (96%); practically insoluble in ether.
pKa = 8.6, pH = 4.5 to 6.0.
STABILITY AND STORAGE RECOMMENDATIONS
Store between 15 ºC and 30 ºC in a well-closed container. Protect from light.
AVAILABILITY OF DOSAGE FORMS
MYLAN-VERAPAMIL (Verapamil hydrochloride) Tablets 80 mg: Each yellow, biconvex, film-coated tablet marked "VL" breakline "80" on one side and "G" on the other side contains 80 mg of verapamil hydrochloride. Available in bottles of 100.
MYLAN-VERAPAMIL (Verapamil hydrochloride) Tablets 120 mg: Each white,
biconvex, film-coated tablet marked "VL" breakline "120" on one side and "G" on the other side contains
120 mg of verapamil hydrochloride. Available in bottles of 100.
The non-medicinal ingredients include Lactose, Magnesium Stearate, Microcrystalline Cellulose,
Pregelatinized Maize Starch, Purified Talc and Sodium Starch Glycolate. The coating contains D&C
Yellow # 10 Al Lake, Polydextrose and Triacetin (80 mg tablets only), Lactose (120 mg tablets only),
Hydroxypropyl Methylcellulose, Polyethylene Glycol and Titanium Dioxide.
PHARMACOLOGY
Verapamil hydrochloride was initially investigated in experimental animal as a smooth muscle relaxant, with vasodilator properties. Subsequent studies have demonstrated that verapamil hydrochloride has significant antiarrhythmic effects when tested in a variety of experimental arrhythmias. The mechanism of action of verapamil seems to be the blocking of transmembrane influx of calcium through the slow channels, without affecting, to any significant degree, transmembrane influx of sodium through the fast channels. It does not directly modify calcium uptake, binding or exchange of cardiac microsomes. Its main locus of action seems to be the superficially located membrane storage sites for calcium.
In isolated cardiac tissues, at low concentrations, verapamil hydrochloride exerts little or no effect on action potential amplitude, but suppresses activity in the sinoatrial (S-A) and atrioventricular (A-V)
nodes. Any activity within the S-A and A-V nodes seems to be particularly sensitive to the suppressant effects of verapamil hydrochloride because normal impulse formation in the sinus node and conduction in the A-V node appear to be maintained by operation of slow channel mechanisms. The depressant effects exerted by verapamil hydrochloride on A-V nodal conduction may in part explain its effectiveness in treating supraventricular tachycardia.
Verapamil hydrochloride has a marked negative inotropic effect on isolated cardiac muscle. In intact animals, the depressant effect on cardiac and stroke volume is dose-dependent.
Although verapamil hydrochloride has local anaesthetic properties, in clinically relevant doses it does not affect the rate of either the depolarization or the repolarization phase of the cardiac action potential.
Verapamil hydrochloride does not have beta-blocking properties, although it antagonizes beta-blocking influences on the heart by a functional antagonism, due to its basic pharmacodynamic properties at the level of the conduction system and the myocardium.
TOXICOLOGY
Acute toxicity
LD50 (mg/kg)
I.V. I.P. S.C. Oral
Rat 16 67 107 114
Mouse 8 68 68 163
Guinea Pig - - - 140
Juvenile Rats - - - 93 (M)
- - - 113 (F)
Juvenile Rabbits - - - 114.2 (M)
- - - 129.8 (F)
Symptoms preceding death were similar in both sexes with marked sedation, decreased excitability, forced respirations, clonic spasms and convulsions.
Subacute toxicity
Oral studies: Verapamil was administered orally in doses of 12.5, 25 and 50 mg/kg per day, top rats via food for 14 weeks (29 animals/group) and to dogs for 6 days/week in capsules, for 15-16 weeks (4 animals/group). baboons received 2, 4, 8, 16, 32 and 64 mg/kg by mouth daily for 4 weeks (2 animals/group).
In rats, a dose-related increase in heart and lung weights was found. Dogs given 15-50 mg/kg showed slight weight loss and a significant reduction in heart rate up to week 11, followed by a gradual return to normal. In one dog on 12.5 mg/kg, one on 25 mg/kg and in all animals on 50 mg/kg, there was emesis during the first two weeks of the study. SGPT was elevated for one dog on 25 mg/kg at week 9 and for
two animals on 50 mg/kg at the end of the test. Macroscopic examinations at necropsy were negative and there was no drug-attributal histological changes. The baboons showed no drug-related changes.
Intramuscular Studies: Beagle dogs were given 0, 2 and 10 mg/kg, 5 days/week for 30 days (4 animals/group). Injection sites in all animals became edematous and a dose-related reduction in heart rate was observed. At 10 mg/kg, hemoglobin and hematocrit values decreased and one animal had a raised
SGPT. At necropsy, edema was noted at injection sites and higher spleen weights were recorded on the
10 mg/kg dose. One dog on this dose also showed increased inflammatory cell infiltration in the liver, with some hepatic cell degenerative changes.
Intravenous Studies: Verapamil was given to Sprague-Dawley rats at 0.2, 1 and 5.0 mg/kg once daily for 4 weeks (30 animals/group) and similarly to beagle dogs at 0.1, 0.4 and 1.6 mg/kg levels (6 animals/group).
At the highest level, all dogs showed some restlessness, salivation and laboured breathing, along with delayed A-V conduction in one-half of the animals. In 4 of 6 animals at this highest dose (1.6 mg/kg)
sporadic small focal gatherings of Kupffer cells, with death of individual liver cells (necrobioses and/or necrosis of hepatocytes) were found histopatholo-gically.
Chronic toxicity
Oral: Rats were given verapamil at 10, 15, 25, 30, 60 and 62.5 mg/kg/day (50 animals/group) and beagle dogs at 10, 15, 25, 30, 40, 60, 62.5, 70, 81 and 85 mg/kg (6 animals/group) for 12 and 18 months.
Clinical signs were observed and changes in food consumption, consistency of stools, hemograms, clinical chemistry and urinalyses performed. Blood pressure, ECG and ophthalmic examinations were done on the dogs.
In one 18-month rat study, an increase in weight of the thyroid glands in females on the 62.5 mg dose was noted. In a later 12-month study, a slight reduction in weight gain was recorded.
In dogs, at doses of 60 mg and greater, toxic signs such as vomiting, salivation, reversible hyperplasia of the gums, reduced food consumption, slight weight loss and a transitory, slight to moderate elevation of
SGPT were noted and three of the animals died. The 40 mg dose caused loss of coat colour and hair, and a delay in A-V conduction.
In another study, atypical lens changes (cataracts) were observed in 8 beagles receiving toxic dose levels
(62.5 and 70 mg/kg). In a later study, 4 beagles were given 81 mg/kg for 18 months and none developed cataracts. It was concluded that any changes caused by verapamil in lens transparency are specific to beagles. This is supported by the absence of similar lesions in other species studied, and by the apparent lack of any impairment by verapamil of carbohydrate or energy metabolism in lenticular tissue. The water-soluble proteins of the canine lens are known to have differences from those in other species.
Mutagenicity
In vitro mutagenicity tests showed that verapamil did not have mutagenic properties in five different strains of Salmonella thyphimurium, nor in studies on chromosomal aberrations and sister chromatid exchanges (SCE) in human lymphocytes, nor in the HGPRT-test with V-79 Chinese hamster cells, and also not in the cell transformation assay with Syrian hamster embryo cells. Neither did verapamil show and SCE-inducing activity in vivo (Chinese hamster).
Carcinogenicity
In a 24-month carcinogenicity study, verapamil hydrochloride was administered orally to 50 male and 50 female rats in the diet as actual mean doses of 9.3/9.5, 32.6/33.2, and 112.2/102.5 mg/kg/day, respectively. Two hundred animals served as controls.
Drug-related significant reductions in body weight and mortality were seen in males and females of the high dose group.
Dose-related cardiac lesions (dilatation, atrial thrombi and myocardial metaplasia, combined with hydrothorax) were seen in the high dose group. These cardiac lesions are considered to be related to a chronic, exaggerated pharmacologic effect at this high dose level.
At the end of the study, all rats were examined histopathologically with regards to tumorigenesis. All non-neoplastic and neoplastic lesions were considered to reflect the spectrum of spontaneous lesions commonly encountered in rats of this age and strain. A compared to the controls, the type and incidence of these lesions were not increased in treated rats.
Reproduction
Studies were carried out in rats and rabbits with verapamil given in food and/or gastric tube. The studies included fertility and general reproduction performance in rats, teratogenicity studies in rats and rabbits and peri- and postnatal studies in rats. Rats were given 2.5, 12.5, 25 and 100 mg/kg body weight, by gastric tube and 1.3, 1.6, 5.2, 7.5, 13.3, 16 and 55 mg/kg body weight in food. In another teratogenicity study, rats were given 5, 10 and 20 mg/kg body weight by gavage three times daily at an interval of about
4.5 hours. Rabbits were given 5 and 15 mg/kg body weight by gastric tube.
There was no evidence of teratogenicity in either species and no embryotoxic effects observed in the rats dosed via food, or with doses up to 12.5 mg/kg body weight given by gastric tube, or with doses up to 10 mg/kg t.i.d. The single daily dose of 25 mg/kg body weight or more, and the multiple daily dose of 25 mg/kg t.i.d., caused a higher resorption rate in the rat. There was no difference in resorption rates observed in the rabbit and no effect on peri- and postnatal development or fertility in the rat.
REFERENCES
- 1. Anavekar SR, Christophidis N, Louis WJ, Doyle AE. Verapamil in the treatment of hypertension. J Cardiovasc Pharm 1981; 3:287-92.
- 2.
Bonow RO, Leon MB, Rosing DR, Kent KM, Lipson LC, Bacharach SL, Green MV, Epstein SE.
Effects of verapamil and propranolol on left ventricular systolic function and diastolic filling in patients with coronary artery disease: radionuclide angiographic studies at rest and during exercise. Circulation 1981; 65:1337-50.
- 3.
Calcium Channel Blocking Agents. In: USP DI. Drug Information for the Health Care
Professional. Vol I. Maryland. United States Pharmacopoeial Convention Inc. 1994; 678-695.
- 4. Cubeddu LX, Aranda J, Singh B, Klein M, Brachfield J, Freis E, Roman J, Eades T. A comparison of verapamil and propranolol for the initial treatment of hypertension - racial differences in response. JAMA 1986; 256:2214-21.
- 5.
Ferlinz J, Easthope JL. Effects of verapamil on myocardial performance in coronary disease.
Circulation 1979; 59:313-9.
- 6. Ferlinz J, Turbow ME, Aronow WS. Myocardial metabolism and anginal threshold in coronary disease after verapamil administra-tion. Clin Invest Med 1980; 3:101-9.
- 7. Follath F, Fromer M, Meier P, Vozeh S. Pharmacodynamic comparison of oral and intravenous verapamil in atrial fibrillation. Clin Invest Med 1980; 3:49-52.
- 8.
Frishman WH, Klein NA, Strom JA, Willens H, Le Jemtel TH, Jentzer J, Siegel L, Klein P,
Kirschen N, Silverman R, Pollack S, Doyle R, Kirsten E, Sonnenblick EH. Superiority of verapamil to propranolol in stable angina pectoris: a double-blind randomized crossover trial.
Circulation 1982; 65:(Suppl 1):I51-9.
8a. Mylan Pharmaceuticals ULC. Data on file. 37 Advance Rd, Etobicoke, Ontario.
- 9.
Isoptin. In: Compendium of Pharmaceuticals and Specialties. Ottawa: Canadian Pharmaceutical
Association. 1994. 632-635.
- 10. Johnson SM, Mauritson DR, Corbett JR, Woodward W, Willerson JT, Hillis LD. Double-blind, randomized, placebo-controlled comparison of propranolol and verapamil in the treatment of patients with stable angina pectoris. Am J Med 1981; 71:443-51.
- 11.
Johnson SM, Mauritson DR, Willerson JT, Hillis LD. A controlled trial of verapamil for
Prinzmetal's variant angina. New Engl J Med 1981; 304:862-6.
- 12. Kaltenbach M, Hopf R, Kober G, Bussman WD, Keller M, Petersen Y. Treatment of hypertrophic obstructive cardiomyopathy by verapamil. Br Heart J 1979; 42:35-42.
- 13. Klein HO, Lang R, Weiss E, Di Segni E, Libhaber C, Guerrero J, Kaplinsky E. The influence of verapamil in serum digoxin concentrations. Circulation 1982; 65:998-1003.
- 14.
Miller MR, Withers R, Bhamra R, Holt DW. Verapamil and breast-feeding. Eur J Clin
Pharmacol 1986; 30:125-6.
- 15.
Nayler WG. Cardioprotective effects of calcium ion antagonists in myocardial ischemia. Clin
Invest Med 1980; 3:91-9.
- 16.
Packer M, Meller J, Medina N, Yushak M, Smith H, Holt J, Guerrero J, Todd GD, McAllister R,
Gorlin R. Hemodynamic consequences of combined beta-adrenergic and slow calcium channel blockade in man. Circulation 1982; 65:660-8.
- 17. Rinkenberger RL, Prystowsky EN, Heger JJ, Troup PJ, Jackman WM, Zipes DP. Effects of intravenous and chronic verapamil administration in patients with supraventricular tachyarrhythmias. Circulation 1980; 62:996-1010.
- 18.
Rosing DR, Condit JR, Maron BJ, Kent KM, Leon MB, Bonow RO, Lipson LC, Epstein SE.
Verapamil therapy: a new approach to the pharmacologic treatment of hypertrophic cardiomyopathy: III. Effects of long term administration. Am J Cardiol 1981; 48:545-53.
- 19. Schwartz JB, Keefe DL, Kirsten E, Kates RE, Harrison DC. Prolongation of verapamil elimination kinetics during chronic oral administration. Am Heart J 1982; 104:198-203.
- 20.
Searle Canada Inc. Product Monograph. Isoptin (Verapamil hydrochloride) Tablets, Isoptin-SR
(Verapamil hydrochloride) Sustained Release Tablets. Oakville, Ontario. January 2, 1991.
- 21.
Subramanian VB, Bowles MJ, Khurmi NS, Davies AB, Raferty EB. Randomized double-blind comparison of verapamil and nifedipine in chronic stable angina. Am J Cardiol 1982; 50:696-
703.
- 22.
Verapamil hydrochloride. In: Reynolds J.E.F., Parfitt K., Parsons A.V., Sweetman S.C., eds.
Martindale the Extra Pharmacopoeia. London. The Pharmaceutical Press. 1993; 75-78.
- 23.
Zachariah PK, Sheps SG, Schirger A, Spiekerman RE, O'Brien PC, Simpson KK. Verapamil and
24-hour ambulatory blood pressure monitoring in essential hypertension. Am J Cardiol 1986;
57:74D-79D.