


Product Monograph - NRA-Domperidone
ACTIONS AND CLINICAL PHARMACOLOGY
Domperidone is a peripheral dopamine antagonist structurally related to the butyrophenones with antiemetic and gastroprokinetic properties.
Domperidone effectively increases oesophageal peristalsis and lower oesophageal sphincter pressure (LESP), increases gastric motility and peristalsis, enhances gastroduodenal coordination and consequently facilitates gastric emptying and decreases small bowel transit time.
The mechanism of action of domperidone is related to its peripheral dopamine receptor blocking properties. Emesis induced by apomorphine, hydergine, morphine or levodopa through stimulation of the chemoreceptor trigger zone (situated outside the blood-brain barrier) can be blocked by domperidone. There is indirect evidence that emesis is also inhibited at the gastric level, since domperidone also inhibits emesis induced by oral levodopa, and local gastric wall concentrations following oral domperidone are much greater than those of the plasma and other organs. Domperidone does not readily cross the blood-brain barrier and therefore is not expected to have central effects.
A thorough QT study was performed in healthy subjects. This study included a placebo, active comparator and positive control and was conducted using 10 to 20 mg administered 4 times per day. The study found a maximal difference of QTc between domperidone and placebo in LS- mean in the change from baseline of 3.4 msec for 20 mg domperidone administered 4 times a day on Day 4. The 2-sided 90% CI (1.0 to 5.9 msec) did not exceed 10 msec. Although the results of the thorough QT study with domperidone indicate that it does not significantly prolong the QTc interval when administered to healthy subjects at 10 mg and 20 mg four times daily, there are limitations in the study that restrict the conclusions that can be drawn. The main limitation of the study was the absence of a supra-therapeutic dose (5-fold multiple over the recommended dose), which does not allow to predict the effect of higher drug concentration on the patient.
Domperidone elevates serum prolactin levels but has no effect on circulating aldosterone levels.
In man, peak plasma levels of domperidone occur within 10 to 30 minutes following intramuscular injection and 30 minutes after oral (fasted) administration. Plasma concentrations two hours after oral administration are lower than following intramuscular injection, and this is likely the result of hepatic first-pass and gut wall metabolism. Peak plasma concentrations are 40 ng/mL following an i.m. injection of 10 mg, 20 ng/mL after a single 10 mg tablet, and 70-100 ng/mL after oral doses of 60 mg (tablets or oral drops). The half-life was calculated as approximately 7.0 hours in each case. The degree of human plasma protein binding was calculated from tritiated domperidone concentrations of 10 and 100 ng/mL as 91.7 and 93.0%, respectively.
The major metabolic pathways for domperidone in man are hydroxylation and oxidative N- dealkylation, the products of which are hydroxy-domperidone and 2,3 dihydro-2-oxo-1-H- benzimidazole-1-propionic acid, respectively. After oral administration of 40 mg 14C- domperidone to healthy volunteers, 31% of the radioactivity is excreted in the urine and 66% in the feces over a period of 4 days.
Comparative Bioavailability Study
A randomized, double blind, single dose, two-way crossover study of NRA-DOMPERIDONE (domperidone maleate) Tablets, 10 mg (Nora Pharma Inc.) and PrAPO-DOMPERIDONE (domperidone maleate) Tablets, 10 mg (Apotex Inc.) administered as 1 x 10 mg dose, was conducted in healthy, adult, male subjects under fasting conditions. The results from the 31 subjects who completed the study are summarized in the table below.
Domperidone (1 × 10 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 87.38 92.62 (34.08) | 84.40 90.00 (39.24) | 103.5 | 96.6 - 110.9 |
AUCI (ng·h/mL) | 94.61 100.40 (34.36) | 92.14 98.29 (39.13) | 97.4 | 90.8 - 104.5 |
Cmax (ng/mL) | 17.98 19.20 (35.69) | 15.70 16.99 (41.73) | 114.5 | 102.5 - 128.0 |
Tmax3 (h) | 0.75 (0.50 - 1.67) | 1.00 (0.50 - 1.67) | - | - |
T½4 (h) | 15.93 (23.60) | 17.18 (29.91) | - | - |
1 NRA-DOMPERIDONE (domperidone maleate) tablets, 10 mg (Nora Pharma Inc.)
2 PrAPO-DOMPERIDONE tablets, 10 mg (Apotex Inc.) were purchased in Canada
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
INDICATIONS AND CLINICAL USE
NRA-DOMPERIDONE (domperidone maleate) is indicated in the symptomatic management of upper gastrointestinal motility disorders associated with chronic and subacute gastritis and diabetic gastroparesis.
NRA-DOMPERIDONE may also be used to prevent gastrointestinal symptoms associated with the use of dopamine agonist antiparkinsonian agents.
CONTRAINDICATIONS
NRA-DOMPERIDONE (domperidone maleate) is contraindicated in patients who are hypersensitive to this drug or any ingredient in the formulation. For a complete listing, see PHARMACEUTICAL INFORMATION section.
NRA-DOMPERIDONE (domperidone maleate) is contraindicated in patients with:
- known existing prolongation of cardiac conduction intervals, particularly QT;
- have significant electrolyte disturbances;
- underlying cardiac diseases, such as congestive heart failure;
- moderate or severe liver impairment.
The co-administration of domperidone with QT-prolonging drugs is contraindicated.
The co-administration of domperidone with potent CYP3A4 inhibitors such as azole antifungals (e.g., ketoconazole), macrolide antibiotic such as erythromycin, HIV protease inhibitors and nefazadone are contraindicated (see Warning, Drug Interactions).
NRA-DOMPERIDONE should not be used whenever gastrointestinal stimulation might be dangerous, i.e., gastrointestinal hemorrhage, mechanical obstruction or perforation.
NRA-DOMPERIDONE is contraindicated in patients with a prolactin-releasing pituitory tumour (prolactinoma).
WARNINGS
Serious Warnings and Precautions
Cardiovascular adverse events:
Recent epidemiological studies and review of postmarket safety data demonstrated that domperidone may be associated with an increased risk of serious ventricular arrhythmias or sudden cardiac death (see Adverse Reactions).
The risk may be higher in patients older than 60 years or in patients taking a daily dose of more than 30 mg.
Based on the above-mentioned products of serious ventricular arrhythmias and sudden cardiac death, domperidone should not be used:
- concomitantly with drugs which prolong QT intervals see Contraindications, Drug Interactions);
- in patients who have existing prolongation of cardiac conduction intervals, particularly QT (see Contraindications, Drug Interactions);
- in patients with significant electrolyte disturbances or underlying cardiac diseases such as congestive heart failure (see Contraindications);
- concomitantly with CYP3A4 inhibitors which may increase plasma levels of domperidone (see Contraindications, Drug Interactions).
Domperidone should be used at the lowest possible dose for the shortest duration necessary.
One 10 mg tablet three times per day with a maximum dose of 30 mg per day is recommended for all indications as the risk of serious cardiac events may be increased in association with daily doses> 30 mg. (see Contraindications Dosage and Administration, Drug Interactions, Adverse Reactions). Patients at a higher risk of QT interval prolongation and/or cardiac arrhythmia should be considered for cardiac assessment including ECG before initiation of domperidone therapy and during the treatment.
Cardiovascular:
In an interaction study, when domperidone was adminstrated with ketoconazole, an increase in the QT interval was observed. The increase was greater than that observed when ketoconazole was adminstrated alone (See Drug Interactions section below). Co-adminstration of ketoconazole with domperidone is contraindicated. QT prolongation was not observed at oral doses of domperidone of up to 160 mg/day, i.e., twice the maximum recommended daily therapeutic dose. It is noteworthy that cardiac arrhythmia and death were reported following very high parenteral doses of domperidone.
These results should be considered when domperidone is prescribed with other CYP3A4 inhibitors because they may increase plasma levels of domperidone.
Co-administration of domperidone with potent CYP3A4 inhibitors such as systemic azole antifungals, macrolide antibiotics such as erythromycin, clarithromycin and telitromycin, HIV protease inhibitors, nefazodone and grapefruit juice is contraindicated (see Contraindications, Drug Interactions).
Concomitant use of domperidone with moderate CYP3A4 inhibitors such as diltiazem, verapamil and some macrolides is not recommended. Co-administration with QT prolonging drugs (see list below*) is contraindicated (see Contraindications, Drug Interactions)
List of QT prolonging drugs:
- Antiarrhymics class IA (e.g., disopyramide, hydroquinidine, quinidine),
- Antiarrhymics class III (e.g., amiodarone, dofetilide, dronedarone, ibutilide, sotalol),Certain antipsychotics (e.g., haloperidol, pimozide, sentindole),
- Certain antidepressants (e.g., citalopram, escitalopram),
- Certain antibiotics (e.g., erythromycin, levofloxacin, moxifloxacin, spiramycin),
- Certain antifungal agents (e.g., pentamidine),
- Certain antimalarial agents (in particular halofantrine, lumefantrine),
- Certain gastrointestinal agents (e.g., cisapride, dolasetron, prucalopride),
- Cetain antihistamines (e.g., mequitazine, mizolastine),
- Certain medicines used in cancer (e.g., toremifene, vandetanib, vincamine),
- Certain other medicines (e.g., bepridil, diphemanil, methadone)
*The list of examples of QT-prolonging drugs may not be exhaustive.
Prolactin Levels
Dopamine receptor blocking agents elevate prolactin levels; the elevation persists during chronic administration. Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin dependent in vitro, a factor of potential importance if the prescription of these drugs is contemplated in a patient with a previously detected breast cancer. Although disturbances such as galactorrhea, amenorrhea, gynecomastia, and impotence have been reported, the clinical significance of elevated serum prolactin levels is unknown for most patients. An increase in mammary neoplasms has been found in rodents after chronic administration of dopamine receptor blocking agents. Neither clinical studies nor epidemiologic studies conducted to date, however, have shown an association between chronic administration of these drugs and mammary tumorigenesis. The available evidence is considered too limited to be conclusive at this time.
Use in Pregnancy
While animal studies have not shown drug related teratogenic or primary embryotoxic effects on animal fetuses (see TOXICOLOGY), comparable studies have not been performed in pregnant women. For this reason, NRA-DOMPERIDONE (domperidone maleate) should not be used in pregnant women unless the expected benefit outweighs the potential hazard.
Use During Lactation
Domperidone is excreted in breast milk in very low concentrations. Therefore, nursing is not recommended for mothers taking NRA-DOMPERIDONE unless the expected benefits outweigh any potential risk.
Use in Children
The safety and efficacy of domperidone in children have not been established. Therefore, domperidone should not be used in children.
Renal
In patients with severe renal insufficiency (serum creatinine > 6 mg/100 ml or > 0.6 mmol/l) the elimination half-life of domperidone was increased from 7.4 to 20.8 hours, but plasma drug level were lower than in healthy volunteers. Since very little unchanged drug is excreted via the kidneys, it is unlikely that a single administration needs to be adjusted in patients with renal insufficiency.
However, on repeated administration, the dosing frequency should be reduced to once or twice daily, depending on the severity of the impairment, and the dose may need to be reduced.
Generally, patients on prolonged therapy should be reviewed regularly.
PRECAUTIONS
In the event that the patient develops galactorrhea and/or gynecomastia, withdrawal of the drug will result in alleviation of these symptoms.
Use in Patients with Hepatic Impairment
Since domperidone is highly metabolized in the liver, it should not be used in patients with moderate to severe hepatic impairment (see Contraindications)
Use in Patients with Renal Impairment
In patients with severe renal insufficiency (serum creatinine > 6mg/100mL, i.e.,> 0.6mmol/L) the elimination half-life of domperidone was increased from 7.4 to 20.8 hours, but plasma drug levels were lower than in healthy volunteers. In patients with renal insufficiency, the dosing frequency should be reduced (see DOSAGE AND ADMINISTRATION).
ADVERSE REACTIONS
In clinical studies with oral domperidone the overall incidence of side effects was <7%. Some of these side effects are an extension of the dopamine antagonist properties of domperidone. Most side effects resolve spontaneously during continued therapy or are easily tolerated. The more serious or troublesome side effects (galactorrhea, gynecomastia, menstrual irregularities) are dose-related and gradually resolve after lowering the dose or discontinuing therapy.
Central Nervous System (4.6%): dry mouth (1.9%), headache/migraine (1.2%), insomnia, nervousness, dizziness, thirst, lethargy, irritability (all
<1%).
Gastrointestinal (2.4%): abdominal cramps, diarrhea, regurgitation, changes in appetite, nausea, heartburn,constipation (all <1%).
Endocrinological (1.3%): hot flushes, mastalgia, galactorrhea, gynecomastia, menstrual irregularities.
Mucocutaneous (1.1%): rash, pruritus, urticaria, stomatitis, conjunctivitis. Urinary (0.8%): urinary frequency, dysuria.
Cardiovascular (0.5%): edema, palpitations.
Musculoskeletal (0.1%): leg cramps, asthenia.
Miscellaneous (0.1%): drug intolerance.
Laboratory parameters: elevated serum prolactin, elevation of SGOT, SGPT and cholesterol (all <1.0%).
Extrapyramidal phenomena are rare in adults; they reverse spontaneously as soon as treatment is stopped. When the blood-brain barrier is immature (as in infants) or impaired, the possible occurrence of neurological side effects cannot be excluded.
Post-Market Drug Reactions:
Cardiovascular: torsade de pointes, serious ventricular arrhythmias (frequency unknown), sudden cardiac death (frequency unknown).
DRUG INTERACTIONS
In vivo interactions studies have shown that ketoconazole strongly inhibits the CYP3A4- dependent metabolism of domperidone. Pharmacokinetic studies showed 3-10 fold increase in the area under curve (AUC) and the peak concentration (Cmax) of domperidone when ketoconazole was co-administered.
This co-administration also resulted in a prolongation of the QT interval (maximum of 10-20 msec) which was greater than the prolongation observed with ketoconazole alone. QT prolongation was not observed at oral doses of domperidone of up to 160 mg/day, i.e., twice the maximum recommended daily therapeutic dose. It is important to note that cardiac arrhythmia and death were reported following high parenteral doses of domperidone.
Results of the interaction study should be considered when domperidone is prescribed with CYP3A4 inhibitors (which may increase plasma levels of domperidone) or with drugs that can cause QT prolongation or torsade de pointes, especially in patients at risk for torsade de pointes (see Contraindications, Warnings).
Co-administration of domperidone with potent CYP3A4 inhibitors is contraindicated (see
Contraindications, Warnings).
Co-administration of domperidone with drugs which prolong the QT interval is contraindicated (see Contraindications).
List of QT prolonging drugs:
- Antiahhythmics class IA (e.g., disopyramide, hydroquinidine, quinidine),
- Antianhythmics class III (e:g., amiodarorte, dofetilide, dronedarone, ibutilide, sotalol),
- Certain antipsychoties(e.g. haloperidol, pimozide, sentindole),
- Certain antidepressants (e.g. citalopram, escitalopram),
- Certain antibiotics (e.g. erythromycin, levofloxacin, moxifloxacin, spiramycin),
- Certain antifungal agents (e.g. pentamidine),
- Certain antimalarial agents (in particular halofantrine, lumefantrine),
- Certain gastrointestinal agents (e.g. cisapride, dolasetron, prucalopride),
- Certain antihistamines (e.g, mequipitazine, mizolastine),
- Certain medicines used in cancer (e,g., toremifene, vandetanib, vincamine),
- Certain other medicines (e.g., bepridil, diphemanil, methadone)
- The list of examples of QT-prolonging drugs may not be exhaustive.
The concomitant administration of anticholinergic drugs may compromise the beneficial effects of NRA-DOMPERIDONE (domperidone maleate).
The main metabolic pathway of domperidone is through CYP3A4. In vitro data suggest that the concomitant use of drugs that significantly inhibit this enzyme may result in increased plasma levels of domperidone. Examples of CYP3A4 inhibitors include the following:
- azole antifungals;
- macrolide antibiotics;
- HIV protease inhibitors; and
- nefazodone.
Since domperidone enhances gastric and small intestinal motility, it may accelerate absorption of drugs from the small bowel while slowing absorption of drugs taken up from the stomach, particularly those with sustained release or enteric-coated formulations.
Care should be exercised when domperidone is administered in combination with MAO inhibitors.
The concomitant administration of domperidone with antacids or H2-receptor blockers does not decrease the absorption of domperidone.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Symptoms
For management of a suspected drug overdose, contact your regional Poison Control Centre immediately.
Based on the pharmacological properties of domperidone, symptoms of overdosage may include CNS effects (such as drowsiness, disorientation and extrapyramidal reactions, especially in children) and cardiovascular effects (arrhythmia, hypotension) might possibly occur.
Treatment
Anticholinergic, anti-parkinsonian drugs or antihistamines with anticholinergic properties may be helpful in controlling the extrapyramidal reactions. There is no specific antidote to domperidone but in the event of overdosage, gastric lavage as well as the administration of activated charcoal may be useful. Close observation including ECG monitoring and supportive therapy are recommended.
DOSAGE AND ADMINISTRATION
Important considerations:
The expected benefit of an increased dose should out weight the potential risks.
Recent post-market epidemiological studies and review of post-market safety data have shown that the risk of serious ventricular arrhythmias or sudden cardiac death may be higher in patients older than 60 years of age or in patients taking a daily dose of more than 30 mg. (see Warnings- Serious Warnings and Precautions, Drug Interactions, Adverse Reactions).
Domperidone should be used at the lowest possible dose for the shortest duration necessary.
Dosage Consideration
One 10 mg tablet three times per day with a maximum dose of 30 mg per day is recommended for all indications as the risk of serious cardiac events may be increased in association with daily doses> 30 mg (see Contraindication and Warnings).
Patients with renal impairment:
Since very little unchanged drug is excreted via the kidneys, it is unlikely that a single administration needs to be adjusted in patients with renal insufficiency. However, on repeated administration, the dosing frequency should be reduced to once or twice daily, depending on the severity of the impairment, and the dose may need to be reduced.
Generally, patients on prolonged therapy should be reviewed regularly (see Warnings, Precautions).
PHARMACEUTICAL INFORMATION
Drug Substance
Proper/Common Name: domperidone maleate
Chemical Name: 5-chloro-1-[1-[3-(2-oxo-2,3-dihydro-1H-benzimidazol-1-yl)propyl] piperidin-4-yl]-1,3-dihydro-2H-benzimidazol-2-one hydrogen (Z), butenedioate
Structural Formula:
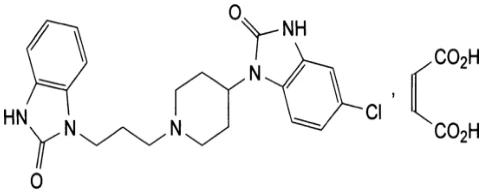
Molecular Formula: C26H28ClN5O6
Molecular Weight: 542.0 g/mol
Description: Domperidone maleate is a white or almost white powder, sparingly soluble in N,N-dimethylformamide; slightly soluble in methanol, and very slightly soluble in water and ethanol 96%.
Composition
Each tablet contains 10 mg of domperidone as domperidone maleate and the following non-medicinal ingredients: colloidal silicon dioxide, croscarmellose sodium, fumaric acid, hypromellose, magnesium stearate, microcrystalline cellulose, polyethylene glycol and titanium dioxide.
Stability and Storage Recommendations
Store at room temperature 15ºC - 30ºC. Protect from light and moisture. Preserve in airtight container.
AVAILABILITY OF DOSAGE FORM
NRA-DOMPERIDONE 10 mg Tablets
Each white to off white round, biconvex, film-coated tablets debossed “DOM” on one side and “10” on the other, contains domperidone maleate equivalent to 10 mg of domperidone.
NRA-DOMPERIDONE tablets are available in bottles of 100’s and 500’s.
PHARMACOLOGY
Domperidone is a dopamine antagonist which does not readily cross the blood-brain barrier and exerts its primary effect on peripheral dopamine receptors.
While 3H-domperidone binds specifically and selectively to mouse and rat striatal dopamine receptors in vitro, domperidone, administered in vivo, showed no displacement of 3H-spiperone in rat brain dopaminergic areas and did not increase rat brain homovanillic acid (HVA) concentrations. Accordingly, domperidone had no effect on behaviour, conditioned reflexes, intracranial self-stimulation or EEG tracings at concentrations up to 100 times in excess of the antiemetic dose. These studies indicate that domperidone does not cross the blood brain barrier.
In baboons and in the dog, domperidone given intravenously produced a dose-dependent increase in lower oesophageal sphincter pressure. Gastric relaxation studies in the dog showed that at i.v. doses of 1 and 3 mg/kg domperidone increased gastric tone. In the dog, dopamine- induced gastric relaxation was prevented by domperidone i.v. at a dose of 0.3 mg/kg.
In the isolated guinea-pig stomach-duodenum preparation, dopamine and noradrenaline produced gastric relaxations which could be antagonized in a dose-dependent manner by domperidone.
Domperidone also increased the amplitude and decreased the frequency of peristaltic waves in the same in vitro preparation. In female dogs, domperidone (1 mg/kg) increased the antral contraction pressure while decreasing the frequency. A dose of 0.3 mg/kg i.v. domperidone also prevented both the gastric relaxation and the reduced amplitude of phasic activity induced by dopamine. Domperidone also improved antroduodenal coordination (defined as the propagation of peristaltic waves from the stomach to the duodenum) in the isolated guinea-pig stomach- duodenum preparation. In the dog, intravenous administration of 0.31 mg/kg domperidone resulted in an increase in antroduodenal coordination from 35% to 80%. In dogs, 0.35 and
0.7 mg/kg i.v. domperidone significantly increased the distention of the pyloric sphincter.
Gastric emptying studies performed in the dog showed that domperidone 0.4 mg/kg i.v. significantly decreased the stationary phase of a solid meal by 50% and also increased the emptying rate. Domperidone also reversed the dopamine-induced prolongation of the stationary phase of both solid and semi-solid meals.
Domperidone was found to be a potent inhibitor of apomorphine-induced emesis in the dog. After a s.c. injection of 0.31 mg/kg apomorphine, the ED50 was 0.007 mg/kg s.c. and 0.031 mg/kg p.o. for domperidone. Domperidone was also highly effective in preventing emesis induced by hydergine, levodopa and morphine but ineffective in preventing copper sulfate induced emesis.
In rats, domperidone induced a significant rise in plasma prolactin levels. This effect could be reversed by apomorphine. In rats treated with 0.25 mg/kg/day domperidone for 14 days, prolactin levels were found to be significantly higher than those of untreated animals.
TOXICOLOGY
Acute Toxicity:
Signs of toxicity:
- 1. Following i.v administration:
in mice: ptosis (≥ 20 mg/kg), sedation (≥ 40 mg/kg), tremors and convulsions (> 80 mg/kg). in rats: ptosis, sedation and catalepsy (≥ 5 mg/kg), convulsions (≥ 80 mg/kg).
in guinea pigs: ptosis and sedation (≥ 20 mg/kg) and dyspnea before death at 40 mg/kg. in dogs: ataxia, sedation and vomiting starting at 10 mg/kg.
- 2. Following oral administration:
in mice: ptosis, sedation, and occasionally ataxia (≥ 320 mg/kg). in rats: ptosis, sedation and catalepsy (≥ 40 mg/kg).
in guinea pigs: ptosis sedation and occasionally diarrhea (≥ 320 mg/kg). in dogs: vomiting at 160 mg/kg.
Species
Route of
Administration
LD50 (mg/Kg)
7 days
Mice
M
i.v.
56.5 (43.2-73.8)
F
i.v.
56.8 (43.5-74.2)
Rats
M
i.v.
56.3 (43.1-73.6)
F
i.v.
68.8 (52.6-89.9)
Guinea-pigs
M
i.v.
42.9 (32.8-56.1)
F
i.v.
44.4 (34.0-58.0)
Dogs
M & F
i.v.
42.7 (32.7-55.9)
Mice
M
p.o.
>1280
F
p.o.
>1280
Rats
M
p.o.
>1280
F
p.o.
>1280
Guinea-pigs
M
p.o.
796 (424-1493)
F
p.o.
>1280
Dogs
M & F
p.o.
>160
Dogs
M & F
s.c.
>160
- 3. Following subcutaneous administration:
in dogs: sedation and cataleptic immobility.
SUBACUTE TOXICITY
Intravenous toxicity study in Wistar rats (3 weeks)
Rats (10 M, 10 F/group) received intravenously 0, 2.5, 10 and 40 mg/kg domperidone once a day, six days a week. There was no effect on mortality, behaviour and appearance. At the high dose, food consumption and body weight gains were significantly lower in male animals only.
There was an increase of segmented heterophils and a decrease of lymphocytes in high dose animals. Serum analyses were normal except for an increase in alkaline phosphatase in all dosed female groups and an increase of haptoglobin in high dosed males and females.
At 40 mg/kg, a moderate to strong irritation of the tail with progressive necrosis was noted in both males and females. Also at this high dose, stimulation of the mammary glands was seen in several females. A decrease in spleen weight was noted in all groups of dosed males and females. At high dose, most of the organ weights decreased, especially in male animals where a lower terminal body weight was noted. Histopathology revealed the following: reduced number of corpora lutea in the ovary at 40 mg/kg, reduced eosinophilic infiltration of the uterine wall and more folded uterine mucosa at 40 mg/kg, mucification of the vagina at 40 mg/kg and rarely at lower dosages, atrophied and female aspect of the mammary gland in dosed males and glandular development with secretion in the dosed females in a dose-related fashion, more extended chromophobe tissue of the hypophysis at all dosages.
Intravenous toxicity study in Beagle dogs (3 weeks)
Dogs (3 M, 3 F/group) received intravenously 0, 1.25, 5 and 20 mg/kg domperidone once a day, six days a week. There was no effect on mortality. Emesis and reduced appetite were seen at the 20 mg/kg dose. Behaviour and appearance were otherwise unaffected. Body weight remained comparable between control and dosed groups. Heart rate, ECG and blood pressure remained normal in all groups.
At the high dose, there was a marginal decrease in hematocrit and hemoglobin. Serum analysis and urinalysis remained normal throughout the study.
Organ weights remained normal in all groups except for a slight increase in relative liver weight at high dose and a slight decrease in absolute and relative adrenal weight at all doses.
Histologically, both liver and adrenals were normal and comparable to controls. The following changes were seen histopathologically: reduced or absent spermatogenesis at high dose, atrophy of the prostate high dose, degranulation of the erythrosinophilic cells of the hypophysis at 5 and 20 mg/kg.
Oral toxicity study in Wistar rats (15 weeks)
Rats (10 M, 10 F/groups) received orally 0, 10, 40 and 160 mg/kg domperidone mixed in the diet.
At the high dose, a decrease in appetite and weight gain was observed as well as two deaths, both unrelated to drug administration. Food consumption was increased in low and medium dose females. Hematology and serum analysis were normal in all groups.
Urinalyses were normal except for a decrease in creatinine in all dosed females. Stimulation of the mammary glands was seen in all dosed females. Organ weights were comparable in all groups with following exceptions: increase in absolute liver weight in low dose females where body weight increased. At the high dose, the absolute weight of several organs was significantly lower than in the control group, due to lower total body weight in this group. Histopathology revealed the following changes: mucification of the vaginal epithelium, reduction in number of corpora lutea in all dosed females, female aspect with sometimes fluid secretion in the mammary gland of dosed male animals, marked development of grandular tissue filled with secretion in all dosed females, increased chromophobe or erythrosinophilic tissues and less active gonadotrophs in the hypophysis.
Oral toxicity study in Beagle dogs (3 months)
Dogs (3 M, 3 F/group) received orally 0, 2.5, 10 and 40 mg/kg domperidone once a day, six days a week. All animals survived the experiment. At the high dose, there was a decrease in appetite, and ocular discharge and ptosis were noted. Food consumption decreased at high dose, and there was a persistent body weight loss. Heart rate, ECG and blood pressure remained normal in all groups.
Hematological parameters were normal except for a decrease in hematocrit, hemoglobin and red blood cells at the high dose. Serum analysis and urinalysis remained normal in all groups. Organ weights were normal except for a dose-related increase of the relative liver weight in all dosage groups.
At the high dose, an increase of most relative organ weights was expected from decreased total body weight. The following histopathological observations were noted: desquamation and some degeneration of germial epithelium with no spermatogenesis in 2/3 males at high dose; prostatic atrophy at 10 and 40 mg/kg; some thymus involution in 2/3 high dosed females; more extended erythrosinophilic tissue in the hypophysis in high dosed males and mid and high dosed females.
CHRONIC TOXICITY
Oral toxicity study in Wistar rats (6-12-18 months)
Four groups of 10 male and 10 female rats received domperidone orally each day, seven days a week, at doses of 0, 10, 40 and 160 mg/kg during 6, 12 and 18 months, so that a total of 240 animals were used throughout the course of the study.
No dose-related effects on the mortality rate were observed in the 6, 12, and 18 month studies. The only effect on behaviour was an increased appetite observed in the 10 mg/kg dosed females, and also in the 40 mg/kg females, but to a lesser extent. This resulted in adipositas in several animals, especially in the 12 and 18 months studies. Stimulation of the mammary glands was noticed at all dose levels in the females and also in most of the high dosed males in the 18 month study. Food consumption was decreased at high dose for both males and females in the 6 month study, and in males of the 12 and 18 month studies. Increased food consumption was observed in the 10 mg/kg females of the 6, 12 and 18 month studies.
Decreased food consumption correlated with decreased body weight at 160 mg/kg in males and females (6 months) and in males (12 months). Hematology and biochemistry were normal except for the following findings: slight increase of non-segmented heterophils in the 40 and 160 mg/kg dosed females (12 months), marginal increase of monocytes in the 40 and 160 mg/kg dosed females (18 months), marginal increases of inorganic phosphorus in dosed females (12 months). Urinalysis was normal. Most of the necropsy findings occurring in dosed as well as undosed animals were related to aging process: pneumonia, lung abscesses, alopecia, thymus involution. Drug administration caused stimulation of the mammary glands in all dosed females of the 6, 12 and 18 month studies, and in several of the 160 mg/kg dosed males of the 18 month study. No adverse effect on organ weight was noted.
Histopathological changes were described as follows:
- enhanced prostatitis in many dosed rats at all dosages, but not at 10 mg/kg in the 6 month experiment;
- progestational aspect of the female genital tract at all dosages (6 and 12 month experiments);
- female aspect or atrophy of the mammary gland in males at all dosages;
- mammary glands stimulation in the females at all dosages after 6 and 12 months and at 160 mg/kg after 18 months;
- inverted or irregular gradient of fat in the adrenals of males at 160 and 40 mg/kg after 6 and 12 months, and at 160 mg/kg after 18 months in the males; absence of fat gradient at 160 mg/kg and 40 mg/kg in the females after 6 months;
- chronic stimulation of the chromophobe or erythrosinophilic tissues of the hypophysis at all dosages.
Oral toxicity study in Beagle dogs (12 months)
Four groups of 3 male and 3 female dogs received domperidone orally each day, seven days a week, at dosages of 0, 2.5, 10 and 40 mg/kg for a period of 12 months.
There was no mortality during the study, except for 1 animal at 40 mg/kg which died during week 8 with gastro-enteritis and peritonitis. This death was not considered to be drug related. Behaviour and appearance were unaffected, except for some temporary ocular lesions believed to be of an infectious origin which regressed during the study, and were observed in a few dogs.
Some decreased food consumption was observed at the high dose, causing a lower terminal body weight. ECG, heart rate and blood pressure remained within normal values. Hematological values remained normal except for a slight decrease of hematocrit, hemoglobin and red blood cells at 10 and 40 mg/kg and slight increase in monocytes and thrombocytes at 40 mg/kg. Serum analysis was normal in all groups except for a marginal to moderate increase of haptoglobin in the 10 and 40 dosage groups.
Urinalysis remained normal throughout the study. Gross pathology changes were limited to a small sized prostate in the 10 and 40 mg/kg dosed males. Organ weights were normal except at high dose, where the increased relative liver weight was considered a possible drug and dose related effect.
Histopathological changes were described as follows:
Testis: A tendency to more marked desquamation or to a looser germinal epithelium at 10 and
40 mg/kg, two dogs at these dosages showing more extended degeneration changes with impairment of spermatogenesis.
Prostate: Atrophy and/or fibrosis of the prostate characterized the 40 mg/kg dosed males and to a lesser extent the 10 mg/kg dosed one.
Eyes: Keratitis was noted in 10 and 40 mg/kg dosed animals; these changes were explained by the lowered resistance of these animals to some kennel infection at the time of the experiment.
CARCINOGENICITY STUDIES
Oral carcinogenicity study in Albino Swiss mice
Four hundred Albino Swiss mice were divided into four groups of 50 males and 50 females. Each group received orally through the drinking water for 18 months, 0, 6.25 ppm (2.5 mg/kg body weight/day), 25 ppm (10 mg/kg/day) or 100 ppm (40 mg/kg/day) domperidone. No dose related effects on overall survival rate or on the time at which mortalities occurred were observed. There were no dose-related effects on health, appearance or behaviour. No dose- related effects on gross pathology were seen.
Histopathological examinations revealed no difference between groups with regard to the number of tumor-bearing mice. The incidences of the various tumor types in both males and females were comparable for each dosage group except for a dose related increase in mammary carcinomas which was significant in the high dose females. The latter finding was expected for a dopamine antagonist given at high dosages.
Oral carcinogenicity study in Wistar rats
Four hundred Wistar rats were divided into four groups of 50 males and 50 females. Each group received orally admixed in the diet for 24 months, 0, 2.5 mg/100 g food/day (2.5 mg/kg body weight/day), 10 mg/100 g food/day (10 mg/kg body weight/day) and 40 mg/100 g food/day (40 mg/kg body weight/day) domperidone.
No dose-related effects on survival rate were noticed and no dose-related effects on health, behaviour and physical appearance were observed. No dose-related effects on gross pathology were seen.
Histopathological examinations revealed that no statistical differences could be noted on the total incidence of tumor bearing rats when the various dosage groups of the males and females were compared. The incidence of various tumor types was not significantly different from the control values except for the males of the high dosage group which showed a marginally increased incidence of pituitary adenomas. In the high-dosed females, there was a slight tendency towards an increase in mammary carcinomas. The number of thyroid adenomas found in the mid-dosed females was quite high, but this was not so in the high-dosed females. These findings on pituitary and mammary glands tumourigenesis were expected for a dopamine-antagonist at high dosages.
Mutagenicity Studies:
Domperidone was shown to have no mutagenic potential in the following models: dominant lethal test in male and female mice, micronucleus test in mice, Salmonella typhimurium (Ames's test), in vitro chromosomal aberrations in human lymphocytes, sex-linked recessive lethal test in Drosophila melanogaster.
REPRODUCTION AND TERATOGENICITY STUDIES
- A) Oral Embryotoxicity and Teratogenicity Studies in the Rat
Oral embryotoxicity and teratogenicity study in Wistar rats (Segment II)
Eighty female Wistar rats were divided in 4 groups of 20 animals each and received orally 0, 10, 40 and 160 mg/kg domperidone each day from day 6 to day 15 of gestation. Pregnancy rate was 65% in the high dose group as compared to 100% in the lower dosage groups and 90% in the control group. Administration of domperidone had no effect on the following parameters: number of implantations, pregnancies and pups, litter size and weight at birth, number of resorptions, live and dead fetuses, number of distribution of live, dead and resorbed embryos. No embryotoxic or teratogenic effects were seen.
Oral embryotoxicity and teratogenicity study in Wistar rats (Segment II)
Eighty female Wistar rats were divided in 4 groups of 20 animals each and received 0, 5, 20 or 80 mg/kg domperidone p.o. each day from day 6 to day 15 of gestation. Pregnancy rate was 80% at low dose, 100% at mid dose and 95% at high dose, compared to 95% in the control group.
There was no embryotoxic or teratogenic effect and no effect on number of implantations, pregnancies and pups, litter size and weight at birth, number of resorptions, live and dead fetuses, number and distribution of live, dead and resorbed embryos.
Oral embryotoxicity and teratogenicity study in Wistar rats (Segment II)
Eighty female Wistar rats were divided in 4 groups of 20 animals each and received by gavage 0, 160, 320 and 640 mg/kg domperidone each day from day 6 to day 15 of gestation. Body weight gain was much lower in all dosage groups and was correlated to lower food consumption in these groups.
One female at 320 and 2 females at 640 mg/kg died during the study. These females were not pregnant and autopsy failed to reveal the cause of death. Rates of pregnancy were 95% in the control group, 85% in the 160 mg/kg group, 20% in the 320 mg/kg group and 25% in the 640 mg/kg groups. The percentage of resorptions increased with dose and was 100% in the high dose group. Litter size and weight of pups at delivery were also decreased in the low and mid dose groups. No drug related teratogenic effect was detected. However, at these high dosages, there was no evidence of maternal toxicty.
Oral three generation reproduction study in Wistar rats Exp. No. 913
Forty young and healthy adult males and one hundred and twenty young and healthy virgin females (Wistar rats) were used as the F0 generation. The animals were divided into 4 groups of equal size and dosed with domperidone at 0, 10, 40 and 160 mg/100 g food. The F0 generation was dosed from the age of 3 months onwards, i.e., from day 0 of mating and further through breeding and weaning. A total of 20 inseminated females per dosage group (i.e., 80/120) were followed during their gestation. Their progeny on days 1, 4, 14 and 21. After weaning at day 21 and a further 21/2 months growing period, a second generation was bred from the F1 litter. The males and the females of the second generation were randomly chosen: at least 10 males and 20 females per dosage group. Upon reaching sexual maturity at 3 months, one was coupled with two females by excluding brother-sister mating. The inseminated females were isolated until 3 weeks after parturition. The pups of the F2 litter were weighed on days 1, 4, 14 and 21. After weaning at day 21 and a further 21/2 months growing period, a third generation was bred from the F2 litter in the same way as described above. The males and females of the third generation were randomly chosen: at least 10 males and 20 females per dosage group. Upon reaching sexual maturity at 3 months, one male was coupled with two females by excluding brother-sister mating. The inseminated females were isolated until sacrifice at day 22 of gestation. All delivered F3 pups were weighed.
The males and females of the second (F1) and third (F2) generations were dosed continuously at the same dose levels as the F0 generation.
Body weight gain was lower in the high dosage group of the three generations, but only in the first generation was this difference significant. This correlated with a decreased food consumption in that same group. No mortality was recorded in each of the groups. No differences in pregnancy rates were observed between groups. The observed differences in gestation periods between groups in the first generation were not dose-related and were all within normal limits. No differences were seen in the second generation. There were some small differences between groups in litter size and number of live fetuses but all were considered to be within normal limits, except for the decrease seen in the high dosage group, which is attributed to maternal toxicity. The same applies to birth-weight, weight at 2 and 3 weeks and survival rate. There was no difference in abnormalities between treated and untreated groups.
- B) Intravenous Embryotoxicity and Teratogenicity Study in the Rat
Intravenous embryotoxicity and teratogenicity study in Wistar rats
Eighty female Wistar rats were divided into 4 groups of 20 animals each and received intravenously 0, 2.5, 10 and 40 mg/kg/day from day 6 to day 15 of gestation. Body weight increase was normal and no mortality occurred in all groups. Pregnancy rates were respectively 95%, 100%, 95% and 85% in the control, low, mid and high dose groups, The percentages of live, dead and resorbed fetuses were respectively 97.2%, 0% and 2.8% in the control group, 94.8% 0% and 5.2% in the low-dose group, 92.1%, 0% and 7.9% in the mid-dose group, 90.5%, 0% and 9.5% in the high dose group, indicating a slight increase in resorptions with increasing dosages. No differences in abnormalities were seen between treated and untreated groups.
- C) Oral Embroyotoxicity and Teratogenicity Studies in the rabbit
Oral embryotoxicity and teratogenicity study in New Zealand white rabbits
Sixty female New Zealand white rabbits were divided into three groups of 20 animals each and received 0, 10 and 40 mg/kg domperidone by gavage from day 6 through day 18 of gestation. There was one death at low dose and 9 deaths at the high dose. The cause of death was lobular pneumonia in 2 cases, enteritis in one case and pneumonia with mucoid enteritis in another case. Weight gain was apparent in all groups but was decreased in dosed animals. Rates of pregnancies were 85% in the control and low dose groups, and 70% in the high dose group. The average litter size was 6.2 in the control group, 5.7 in the low dose group and 5.5 in the high dose group. The percentage of live, dead and resorbed fetuses for all groups were respectively 83.9%, 0.8% and 15.3% (control group); 72.6%, 1.6% and 25.8% (low dose group); 76.6%, 2.6% and 20.8% (high dose group). Therefore the percentage of resorption increased in dosed groups. At resection the average birth weight of live pups at resection was 41.5 g (control), 40.7 g (low dose) and 36.3 g (high dose). The 24 hour survival rate of incubated pups was 75% in controls, 61.1% in low- dosed animals and 40.7% in high-dosed animals. No abnormalities were noted in any group.
In conclusion, it can be said that domperidone did not produce teratogenic effects at doses of 10 and 40 mg/kg.
There was, however, a slight increase in resorptions in dosed animals with evidence of maternal toxicity.
Oral embryotoxicity and teratogenicity study in New Zealand white rabbits
Sixty female New Zealand white rabbits were divided into three groups of 20 animals each and received 0, 5 and 20 mg/kg/day domperidone by gavage from day 6 through day 18 of gestation. There was no death in the control group, but three animals died in the 5 mg/kg groups and twelve died in the high dose group. Pregnancy rates were 60% for the control group, 70% for the low dose group and 40% for the high dose group.
The percentages of live, dead and resorbed foetuses were respectively 70.0%, 0% and 30% in the control group, 64.6%, 0% and 35.4% in the low dose group and 82.4%, 5.9% and 11.7% for the high dose group. At resection, the average birth weight of live pups was: 42.5 g (control), 39.0 g (5 mg/kg group) and 34.7 g (20 mg/kg group). Survival rate of of incubated pups, 24 hours after delivery was: 54.3% (controls), 52.4% (5 mg/kg), and 14.3% (20 mg/kg). Survival rate was significantly decreased at 20 mg/kg. No teratogenic effect was seen. Maternal toxicity is evident at 5 and 20 mg/kg as pregnancy rate decreased (20 mg/kg), mortality rate increased and weight gain decreased (5 and 20 mg/kg).
- D) Intravenous Embryotoxicity and Teratogenicity Studies in the Rabbit
Intravenous embryotoxicity and teratogenicity study in New Zealand white rabbits
Sixty female New Zealand rabbits were divided into three groups of 20 animals each and received intravenously 0, 0.63 and 1.25 mg/kg from day 6 through day 18 of gestation. Survival rate in the dams was 100% in the control group, 85% at low dose and 100% at high dose. Three animals died in the low dose group. Body weight gains were comparable in all groups.
Pregnancy rates were 100% in the control group. Pregnancy rates were 100% in the control group, 85% in the low dose group and 90% in the high dose group. Average litter size was comparable in all groups.
The percentages of live, dead and resorbed fetuses for all group were respectively 90.2%, 0% and 9.8% for the control, 99.2%, 0% and 0.8% in the low dose group and 97.1%, 0% and 2.9% in the high dose group. The average birth weight of live pups was: 34.6 g (controls), 35.3 g (low dose), and 36.9 g (high dose). Survival rate of incubated pups 24 hours after delivery was: 77.7% (controls), 76.7% (low dose) and 76.5% (high dose). Domperidone administered under these conditions did not produce any embryotoxic or teratogenic effects.
Intravenous embryotoxicity and teratogenicity study in New Zealand white rabbits
Sixty female New Zealand white rabbits were divided into four groups of 15 animals each and received by the intravenous route 0, 0.63, 1.25 and 2.5 mg/kg from day 6 through day 18 of gestation. There were 3 of 15 deaths in the control group, 1 of 15 in the low dose group, 2 of 15 in the mid dose group and 8 of 15 in the high dose group. The decreased survival rate in the high dose group was significant. No difference in pregnancy rates was seen among the various groups. The average litter size was 4.9 in control group, 3.9 (0.63 mg/kg group), 3.9 (1.25 mg/kg group) and 1.7 (2.5 mg/kg group). The number of live, dead and resorbed fetuses per female for all groups were respectively: 4.3, 0.6, 1.7 (controls), 3.8, 0.1, 0.3 (0.63 mg/kg), 3.8, 0.1, 1.7 (1.25 mg/kg) and 1.7, 0.0, 2.5 (2.5 mg/kg). At resection. the average birth weight of live pups was: 42.6 g (control), 43.6 g (0.63 mg/kg), 46.7 g (1.25 mg/kg) and 41.6 g (2.5 mg/kg). Survival rate incubated pups, 24 hours after delivery was: 81.4% (control), 80.4% (0.63 mg/kg), 97.4% (1.25 mg/kg), and 60.0% (2.5 mg/kg).
Mean litter size was low in all groups, but no statistically significant differences between groups were noted. Also, no differences between groups were seen with regard to number of live, dead and resorbed fetuses, birth weight and 24 hour survival rate. No teratogenic or embryotoxic effects were observed in rabbit fetuses.
- E) Oral Male and Female Fertility Study in Wistar Rats
Oral male and female fertility study in Wistar rats (Segment I)
Three hundred and twenty Wistar rats (160 males and 160 females) were used in this experiment. Groups of 20 males and 20 females each received 0, 10, 40 and 160 mg/kg domperidone daily.
Males received the drug a minimum of 60 days prior to mating with non-dosed females and females a minimum of 14 days prior to mating with non-dosed males and further throughout gestation. Body weight gain was normal in all dosed and non–dosed females, except for a lower weight gain (due to lower food consumption) in the high-dosed females.
Only two animals died during the study: one low-dosed female and one non–dosed female coupled with a high–dosed male died during the study. There was no difference in gestation between all groups of dosed and non–dosed females. No embryotoxic or teratogenic effect was seen and fertility was not affected in males and females.
- F) Oral Embryotoxicity and Teratogenicity Study in Wistar Rats during the peri-and post-natal Period
Oral embryotoxicity and teratogenicity study in Wistar rats during the peri- and post-natal period (Segment III)
Eighty female Wistar rats were divided into four groups of 20 animals each and received 0, 10, 14 and 160 mg/kg domperidone orally from day 16 of gestation through a 3 week lactation period. There was significantly lower body weight gain in the high-dosed females with decreased food consumption. One low-dosed female died during the course of the experiment. Pregnancy rates were 95%, 90%, 70%, and 90% respectively in the control, low, mid and high dose groups. The percentage of live and dead foetuses at birth were respectively: 97.1%, 2.9% (control), 98,4%, 1.6% (low dose), 92.7%, 7.3% (mid dose) and 86.1%, 13.9% (high dose). No abnormalities were noted in any of groups. Pups of all groups showed normal body weight gain during a 3 week neonatal period. After 3 weeks, at weaning, survival rate of pups born to control dams was 85.5% as compared to 77.2% at 10 mg/kg, 72.1% at 40 mg/kg and 32.3% at 160 mg/kg dosed dams. The effects observed at high dose are probably due to maternal toxicity.
BIBLIOGRAPHY
- 1. Agid Y, Quinn N, Pollak P, Illas A, Destee A, Signoret JL, Lhermitte F. The treatment of Parkinson's disease with dopaminergic agonists in combination with domperidone. Clin Pharmacol 1981; 2:107-115.
- 2. Bekhti A, Rutgeerts L. Domperidone in the treatment of functional dyspepsia in patients with delayed gastric emptying. Postgrad Med J 1979; 55 (Suppl 1):30-32.
- 3. Brouwers JRBJ, Assies J, Wiersinga WM, Huizing G, Tytgat GN. Plasma prolactin levels after acute and subchronic oral administration of domperidone and of metoclopramide: a cross-over study in healthy volunteers. Clin Endocrinol 1980; 12:435-440.
- 4. Corinaldesi R, Stanghellini V, Zarabini GE, et al. The effect of domperidone on the gastric emptying of solid and liquid phases of a mixed meal in patients with dyspepsia. Curr Ther Res 1983; 34:982-986.
- 5. Goethals C. Domperidone in the treatment of post-prandial symptoms suggestive of gastroesophageal reflux. Curr Ther Res 1979; 26:874-880.
- 6. Haarmann K, Lebkuchner F, Widmann A, Kief W, Esslinger M. A double-blind study of domperidone in the symptomatic treatment of chronic post-prandial upper gastrointestinal distress. Postgrad Med J 1979; 55 (Suppl 1):24-27.
- 7. Heykants J, Hendriks R, Meuldermans W, Michiels M, Scheygrond H, Reyntjens H. On the pharmacokinetics of domperidone in animals and man. IV. The pharmacokinetics of intravenous domperidone and its bioavailability in man following intramuscular, oral and rectal administration. Eur J Drug Metab Pharmacokinet 1981; 6:61-70.
- 8. Horowitz M, Harding PE, Chatterton BE, Collins PJ, Shearman DJC. Acute and chronic effects of domperidone on gastric emptying in diabetic autonomic neuropathy. Digest Dis Sci 1985; 30:1-9.
- 9. Johannes CB, Varas-Lorenzo C, McQuay LJ, Midkiff KD, Fife D. Risk of serious ventricular arrhythmia and sudden cardiac death in a cohort of users of domperidone: a nested case-control study. Pharmacoepidemiology and Drug Safety 2010; 19:881-888
- 10. Laduron PM, Leysen JE. Domperidone, a specific in vitro dopamine antagonist, devoid of in vivo central dopaminergic activity. Biochem Pharmacol 1979; 28:2161-2165.
- 11. Lienard J, Janssen J, Verhaegen H, Bourgeois E, Willocx R. Oral domperidone (R 33 812) in the treatment of chronic dyspepsia: a multicentre evaluation. Curr Ther Res 1978; 23:529-537.
- 12. Malagelada J-R. Gastric emptying disorders. Clinical significance and treatment. Drugs 1982;24:353-359.
- 13. Meuldermans W, Hurkmans R, Swysen E, Hendrickx J, Michiels M, Lauwers W, Heykants J. On the pharmacokinetics of domperidone in animals and man. III. Comparative study on the excretion and metabolism of domperidone in rats, dogs and man. Eur J Drug Metab Pharmacokinet 1981; 6:49-60.
- 14. Milo R. Use of the peripheral dopamine antagonist, domperidone, in the management of gastrointestinal symptoms in patients with irritable bowel syndrome. Curr Med Res Opin 1980; 6:577-584.
- 15. Molino D, Mosca S, Angrisani G, Magliacano V. Symptomatic effects of domperidone in postvagotomy gastric stasis. Curr Ther Res 1987; 41:13-16.
- 16. Niemegeers CJE, Schellekens KHL, Janssen PAJ. The antiemetic effects of domperidone, a novel potent gastrokinetic. Arch Int Pharmacodyn 1980; 244:130-140.
- 17. Parkes JD. Domperidone and Parkinson's disease. Clin Neuropharmacol 1986; 9:517-532.
- 18. Quinn N, Illas A, Lhermitte F, Agid Y. Bromocriptine and domperidone in the treatment of Parkinson disease. Neurology 1981; 31:662-667.
- 19. Tatsuta M, Iishi H, Okuda S. Gastric emptying and gastrointestinal symptoms in patients with atrophic gastritis and the effects of domperidone. Scand J Gastroenterol 1989; 24:251-256.
- 20. Van Ganse W, Van Damme L, Van de Mierop L, Deruyttere M, Lauwers W, Coenegrachts J. Chronic dyspepsia: double-blind treatment with domperidone (R 33 812) or a placebo. A multicentre therapeutic evaluation. Curr Ther Res 1978; 23:695-701.
21.Van Noord C., Dieleman JP, van Herpen G, Verhamme K, Sturkenboom MC. Domperidone and ventricular arrhythmia or sudden cardiac death: a population-based case-control study in the Netherlands. Drug Saf 2010 Nov 1: 33(11)1003-14
- 22. Wauquier A, Niemegeers CJE, Janssen PAJ. Neuropharmacological comparison between domperidone and metoclopramide. Japan J Pharmacol 1981; 31:305-314.
- 23. PrMOTILUM (domperidone maleate tablets; 10 mg), Submission Control Number 24885, Product Monograph, Janssen Inc. (May 27, 1994).
- 24. PrApo-Domperidone (domerpidone maleate tablets;10 mg), Control Number180396, Product Monograph, Apotex Inc. (March 6, 2015).