


Product Monograph - Oxaliplatin Injection (Teva Canada)
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Intravenous infusion | Aqueous solution 50 mg/10 mL, 100 mg/20 mL and 200 mg/40 mL | Lactose monohydrate and Water for Injection |
INDICATIONS AND CLINICAL USE
OXALIPLATIN INJECTION (oxaliplatin) in combination with infusional 5-fluorouracil/ leucovorin (5-FU/LV) is indicated for:
- Adjuvant treatment of patients with stage III (Dukes’ C) colon cancer after complete resection of primary tumor. The indication is based on a demonstrated improvement in disease-free survival. Survival data at 6 years show a numerical improvement in overall survival.
- Treatment of patients with metastatic colorectal cancer.
Geriatrics (≥ 65 years of age): In patients previously untreated for metastatic colorectal cancer, patients ≥ 65 years (99 of 279 patients) receiving oxaliplatin in combination with 5-FU/LV experienced more fatigue, dehydration, diarrhea, leukopenia, and syncope than patients < 65 years, although the difference was not statistically significant. Starting doses were the same in both age groups. In the adjuvant trial, patients ≥ 65 years receiving the oxaliplatin combination therapy (393 of 1108 patients) experienced more grade 3-4 granulocytopenia and diarrhea than patients < 65 years, although the difference was not statistically significant. The efficacy of oxaliplatin on disease free survival benefit in patients ≥ 65 years of age was not conclusive in the adjuvant trial (see DOSAGE AND ADMINISTRATION).
Pediatrics (≤ 22 years of age): There is no indication for use of oxaliplatin in children. The effectiveness of oxaliplatin single agent in the pediatric populations with solid tumors has not been established (see WARNINGS and PRECAUTIONS).
CONTRAINDICATIONS
OXALIPLATIN INJECTION should not be administered to patients:
- with a history of known allergy to oxaliplatin or other platinum compounds or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the Product Monograph.
- who are breast-feeding.
- who are pregnant.
- with severe renal impairment (creatinine clearance ClCr < 30 mL/min).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
|
General
Do not use OXALIPLATIN INJECTION intraperitoneally. Peritoneal hemorrhage may occur when OXALIPLATIN INJECTION is administered by intraperitoneal route (not an approved route of administration) (see SUMMARY PRODUCT INFORMATION, Route of Administration).
No studies on the effects on the ability to drive and operate machinery have been performed. However, OXALIPLATIN INJECTION treatment resulting in an increased risk of dizziness, nausea and vomiting, and neurologic gait and balance disorders may have influence on the ability to drive and operate machinery.
Vision abnormalities, in particular transient vision loss (reversible following therapy discontinuation), were reported with oxaliplatin administration (see Other Clinical Trial Adverse Drug Reactions and Post-Market Adverse Drugs Reactions, Eye Disorders). Transient blindness episodes lasting for periods of seconds or minutes may recur repeatedly during the event duration (usually hours to days). Therefore, patients should be warned of the potential effect of these events on the ability to drive or operate machinery.
Carcinogenesis and Mutagenesis
Oxaliplatin was shown to be mutagenic and clastogenic in mammalian test systems in vitro and in vivo. The teratogenic potential of oxaliplatin was manifested by the embryonic mortality, decreased fetal weight and delayed ossifications in rats at doses up to 12 mg/m2/day. This daily dose is approximately one-sixth of the recommended human dose. Related compounds with similar mechanism of action and genotoxicity profiles have been reported to be teratogenic.
Oxaliplatin may increase the risk of genetic defects or fetal malformations. Oxaliplatin is contraindicated in pregnancy, and males are advised not to father a child during treatment and up to 6 months thereafter. Because oxaliplatin may cause irreversible infertility, men are advised to seek counseling on sperm storage before starting treatment (see TOXICOLOGY).
Carcinogenicity studies have not been performed with oxaliplatin. However given that oxaliplatin is genotoxic, it should be considered a human carcinogen, which should be taken into consideration for the overall risk/benefit in the adjuvant setting.
Cardiovascular
Cases of QT prolongation and Torsade de Pointes have been reported. QT prolongation may lead to an increased risk for ventricular arrhythmias including Torsade de Pointes, which can be fatal.
Caution should be exercised in patients with a history or a predisposition for prolongation of QT, those who are taking medicinal products known to prolong QT interval, and those with electrolyte disturbances such as hypokalemia, hypocalcaemia, or hypomagnesaemia. In case of
QT prolongation, oxaliplatin treatment should be discontinued (see ADVERSE REACTIONS,
Post-Market Adverse Drugs Reactions and DRUG INTERACTIONS).
No formal clinical cardiac safety studies have been carried out. Preclinical data are limited. No standard hERG or Purkinje fibre tests have been done. Cardiotoxicity was observed in dogs (see TOXICOLOGY). No formal clinical QT studies with oxaliplatin were done. The effect of oxaliplatin in combination with 5-HT3 blocker antiemetics (given as pre-medication in clinical studies) on QTc has not been formally studied. In case of grade 3 or grade 4 hypersensitivity reaction associated with hemodynamic instability (eg. bradycardia, tachycardia, hypotension, hypertension) ECG monitoring should be done.
Gastrointestinal
Gastrointestinal toxicity, which manifests as nausea and vomiting, warrants prophylactic and/or therapeutic antiemetic therapy (see ADVERSE REACTIONS).
Dehydration, ileus, intestinal obstruction, hypokalemia, metabolic acidosis, and even renal disorders, may be associated with severe diarrhea/emesis, particularly when combining oxaliplatin with 5-FU. In rare cases, colitis, including Clostridium difficile diarrhea, have occurred (see ADVERSE REACTIONS, Other Clinical Trial Adverse Drug Reactions).
Patients must be adequately informed of the risk of diarrhea/emesis after OXALIPLATIN INJECTION /5-FU administration in order to contact urgently their treating physician for appropriate management (see subsection Monitoring and Laboratory Tests below).
Cases of intestinal ischaemia, including fatal outcomes, have been reported with oxaliplatin treatment. In case of intestinal ischaemia, OXALIPLATIN INJECTION treatment should be discontinued and appropriate measures initiated (see ADVERSE REACTIONS, Post-Market Adverse Drugs Reactions).
OXALIPLATIN INJECTION treatment can cause duodenal ulcer (DU) and potential complications, such as duodenal ulcer haemorrhage and perforation, which can be fatal. In case of duodenal ulcer, OXALIPLATIN INJECTION treatment should be discontinued and appropriate measures taken (see ADVERSE REACTIONS, Post-Market Adverse Drugs Reactions).
Hematologic
Patients must be adequately informed of the risk of neutropenia after OXALIPLATIN INJECTION /5-FU administration in order to contact urgently their treating physician for appropriate management (see subsection Monitoring and Laboratory Tests below). Cases of febrile neutropenia (including fatal cases) have been reported (see ADVERSE REACTIONS, Adverse Drug Reactions Overview – Blood and Lymphatic System Disorders). If neutropenia or febrile neutropenia (fever of unknown origin without clinically or microbiologically documented infection with an absolute neutrophil count < 1.0 x 10⁹/L, a single temperature of > 38.3°C or a sustained temperature of > 38°C for more than one hour) occurs, OXALIPLATIN INJECTION must be discontinued until improvement or resolution, and the dose of OXALIPLATIN INJECTION should be reduced at subsequent cycles, in addition to any 5-FU dose reductions required (see DOSAGE AND ADMINISTRATION).
Thrombocytopenia is commonly seen with oxaliplatin combination therapy, although the risk of grade 3 or 4 bleeding is low (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Anemia (rarely presenting as Hemolytic Uremic Syndrome) can also occur.
Hemolytic Uremic Syndrome (HUS) is a life-threatening side effect. OXALIPLATIN INJECTION should be discontinued at the first signs of any evidence of microangiopathic hemolytic anemia, such as rapidly falling hemoglobin with concomitant thrombocytopenia, elevation of serum bilirubin, serum creatinine, blood urea nitrogen, or lactate dehydrogenase (LDH). Renal failure may not be reversible with discontinuation of therapy and dialysis may be required.
Disseminated intravascular coagulation (DIC), including fatal outcomes, has been reported in association with oxaliplatin treatment. If DIC is present, OXALIPLATIN INJECTION treatment should be discontinued and appropriate treatment should be administered (see ADVERSE REACTIONS, Post-Market Adverse Drugs Reactions).
Hepatic/Biliary/Pancreatic
Routine monitoring of liver function should be performed on all patients receiving OXALIPLATIN INJECTION. Hepatotoxicity with the use of oxaliplatin plus 5-FU/LV has been noted in clinical studies (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, “Hepatic Adverse Events” tables 4, 6 and 9). In adjuvant setting, elevation in hepatic enzymes (all grades: 57% vs. 34%) and alkaline phosphatase levels (all grades: 42% vs. 20%) was observed more frequently in FOLFOX4 arm than in the 5-FU/LV arm. Hepatic vascular disorders should be considered, and if appropriate, should be investigated in cases of abnormal liver function test results or portal hypertension, which cannot be explained by liver metastases. There is evidence that oxaliplatin causes liver sinusoidal obstruction syndrome, also known as veno-occlusive disease of the liver, which, on liver biopsy is manifested as peliosis, nodular regenerative hyperplasia, and perisinusoidal fibrosis. In the literature, there is a case report of fatal hepatic failure following liver metastasis resection in a patient treated pre-operatively with oxaliplatin (see References: Rubbia-Brandt 2004, Vauthey 2006, Hewes 2007, Tisman 2004 and Schouten van der Velden 2006). Very rare cases of hepatic failure, hepatitis and rare cases of pancreatitis have been reported (see ADVERSE REACTIONS – Other Clinical Trial Adverse Drug Reactions).
Immune
Hypersensitivity, anaphylactic reactions, and/or allergic reactions are reported with the use of oxaliplatin. The incidence of grade 3 or 4 events was 2-3% across clinical studies. In the post-marketing experience, some cases of anaphylaxis have been fatal. These allergic reactions can occur within minutes of oxaliplatin administration, and can include rash, urticaria, erythema, pruritus, laryngospasm and, rarely, bronchospasm and hypotension. Allergic reactions can occur during any cycle. Patients with a history of allergic reaction to platinum compounds should be monitored for allergic symptoms. In case of an anaphylactic-like reaction to OXALIPLATIN INJECTION, the infusion should be immediately discontinued and appropriate symptomatic treatment initiated. These reactions are usually managed with epinephrine, corticosteroid, and antihistamine therapy. Oxaliplatin rechallenge is contraindicated (see Serious Warnings and Precautions Box).
Infections and infestations
Sepsis, neutropenic sepsis and septic shock have been reported in patients treated with oxaliplatin, including fatal outcomes. If any of these events occurs, OXALIPLATIN INJECTION should be discontinued.
Musculoskeletal
Rhabdomyolysis has been reported in patients treated with oxaliplatin, including fatal outcomes. In case of muscle pain and swelling, in combination with weakness, fever or darkened urine, OXALIPLATIN INJECTION treatment should be discontinued. If rhabdomyolysis is confirmed, appropriate measures should be taken. Caution is recommended if medicinal products associated with rhabdomyolysis are administered concomitantly with OXALIPLATIN INJECTION (see ADVERSE REACTION, Post-Market Adverse Drugs Reactions, DRUG INTERACTIONS).
Neurologic
Oxaliplatin is consistently associated with two types of neuropathy:
(1) An acute, reversible, sensory peripheral neuropathy can develop (reported in 85 to 95% of patients) at the end of the 2-hour oxaliplatin infusion, or within 1 to 2 days of dosing. It usually resolves between cycles, but frequently recurs with further cycles. Symptoms may be precipitated or exacerbated by exposure to cold temperatures or objects. The symptoms usually present as transient paresthesias, dysesthesias and hypoesthesias in the hands, feet, perioral area, or throat. Other symptoms occasionally observed include, abnormal tongue sensation, dysarthria, eye pain, and throat or chest tightness. In addition, acute motor symptoms, including jaw spasms, muscle spasms, involuntary muscle contractions, ptosis, vocal cord paralysis and cranial nerve dysfunction have been reported. Acute neuropathy (all grades) occurred in 58% of patients with metastatic colorectal cancer receiving oxaliplatin plus 5-FU/LV but grade 3/4 events occurred in only 4% of patients. In any individual cycle, acute neurotoxicity was observed in about one third of patients.
An acute syndrome of pharyngolaryngeal dysesthesia (grades 3/4) characterized by subjective sensations of dysphagia or dyspnea, feeling of suffocation, without any evidence of respiratory distress (no cyanosis or hypoxia) or of laryngospasm or bronchospasm (no stridor or wheezing) occurs in 1-2% of the patients. All grades of pharyngo-laryngeal dysesthesia were reported in up to 38% of the patients. Because cold temperatures can precipitate or exacerbate acute neurological symptoms, ice (mucositis prophylaxis) should be avoided during OXALIPLATIN INJECTION infusion (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
(2) A persistent peripheral sensory neuropathy can develop. It is characterized by paresthesias, dysesthesias and/or hypoesthesias, and may include deficits in proprioception, thus resulting in difficulties performing activities of daily living (ADLs). This can result in difficulty with delicate movements such as writing or buttoning, as well as difficulty walking due to impaired proprioception.
In another clinical trial in patients with metastatic colorectal cancer, activities of daily living were evaluated. The most frequent abnormal abilities (up to 23% of the patients) were in relation with difficulties in fine movement/activities such as buttoning or zipping, writing and sewing, recognizing coins or keys, filling up a glass. Other activities were affected, such as going up or down stairs, walking in the dark, using car pedals. Abnormal ability was observed at 3 months after last treatment.
In the adjuvant colon cancer trial, neuropathy was graded using a prelisted module derived from the Neuro-Sensory section of the National Cancer Institute Common Toxicity Criteria (NCI
CTC) as follows:
| Grade | Definition |
| Grade 0 | No change or none |
| Grade 1 | Mild paresthesias, loss of deep tendon reflexes |
| Grade 2 | Mild or moderate objective sensory loss, moderate paresthesias |
| Grade 3 | Severe objective sensory loss or paresthesias that interface with function |
In adjuvant patients, sensory neuropathy was reported in 92% (all grades) and 13% (grade 3) of patients. The median cycle of onset for grade 3 neuropathy was cycle 9. At the 28-day follow-up after the last treatment cycle, 60% of all patients had neuropathy of any grade (grade 1 – 40%; grade 2 – 16%; grade 3 – 5%) decreasing to 21% at 18 months (grade 1 – 17%; grade 2 – 3%; grade 3 – 1%). At the 48-month follow-up, neuropathy status was as follows: grade 0 – 62%; grade 1 – 9%; grade 2 – 2%; grade 3 – 0.5%; not evaluable – 26.5%. This suggests that there can be partial or complete recovery of sensory neuropathy over time after cessation of therapy.
However, in some cases, an increase in severity of the sensory neuropathy was reported years after completion of adjuvant therapy.
The long term impact of the neuropathy is difficult to measure, and needs to be considered carefully in the overall risk/benefit ratio during therapy with OXALIPLATIN INJECTION.
In the metastatic colorectal cancer studies, neuropathy was graded using a study-specific neurotoxicity scale, which was different from the NCI CTC scale as follows:
| Grade | Definition |
| Grade 1 | Resolved and did not interface with functioning |
| Grade 2 | Interfered with function but not daily activities |
| Grade 3 | Pain or functional impairment that interfered with daily activities |
| Grade 4 | Persistent impairment that is disabling or life-threatening |
In patients previously untreated for metastatic colorectal cancer, neuropathy was reported in 82% (all grades) and 19% (grade 3/4), and in the previously treated patients in 79% (all grades) and 11% (grade 3/4). The probability of developing peripheral sensory neuropathy is dependent upon the cumulative dose of oxaliplatin administered. These symptoms may improve in some patients upon discontinuation of oxaliplatin.
Sensory peripheral neurotoxicity of OXALIPLATIN INJECTION should be carefully monitored, especially if coadministered with other medications with specific neurological toxicity (see Serious Warnings and Precautions Box; ADVERSE REACTIONS section; subsection Monitoring and Laboratory Tests below). The risk factors that make a patient more likely to develop neuropathy have not been identified.
Cases of reversible posterior leucoencephalopathy syndrome (RPLS, also known as PRES, posterior reversible encephalopathy syndrome) have been reported with platinum agents and in combination regimens that include oxaliplatin. Signs and symptoms of RPLS could be headache, altered mental functioning, seizures, abnormal vision from blurriness to blindness, associated or not with hypertension (see ADVERSE REACTIONS section). Diagnosis of RPLS is based upon confirmation by brain imaging (see REFERENCES section).
Discontinuation of oxaliplatin and initiation of treatment of hypertension if present is recommended in patients developing RPLS. The safety of reinitiating oxaliplatin therapy in patients that previously experienced RPLS is unknown.
In a clinical trial, nerve conduction studies were performed at baseline and after 12 cycles of oxaliplatin 85 mg/m² every 2 weeks (or at end of treatment for patient that have discontinued earlier). Results showed decrease mostly in the sensory action potential amplitude (SAP) and slightly in the compound muscle action potential amplitude. The magnitude of the change in SAP amplitude increased in relation with the severity of the PSN, as clinically evaluated using the oxaliplatin neurological specific scale for evaluation of PSN.
Respiratory
Oxaliplatin has been uncommonly associated with pulmonary fibrosis/interstitial lung disease (< 1% of study patients). In the adjuvant trial, the combined incidence of cough and dyspnea in patients receiving oxaliplatin plus 5-FU/LV compared to patients receiving infusional 5-FU/LV alone was 7% vs. 5% (all grades) and 0.8% vs. 0.1% (grade 3-4), respectively. In previously untreated patients with metastatic colorectal cancer, the combined incidence of cough, dyspnea and hypoxia in patients receiving oxaliplatin plus 5-FU/LV vs. irinotecan plus 5-FU/LV was 43% vs. 32% (all grades) and 7% vs. 5% (grade 3-4). In previously treated patients, the combined incidence of cough, dyspnea and hypoxia in patients receiving oxaliplatin plus 5-FU/LV vs. 5-FU/LV alone was 30% vs. 21% (all grades) and 5% vs. 2% (grade 3-4). One fatal case of eosinophilic pneumonia was reported in a patient receiving combination oxaliplatin therapy on study.
In case of unexplained respiratory symptoms such as non-productive cough, dyspnea, crackles, or radiological pulmonary infiltrates, OXALIPLATIN INJECTION should be discontinued until further pulmonary investigation excludes interstitial lung disease (see Serious Warnings and Precautions Box and ADVERSE REACTIONS). Fatal cases of interstitial lung disease have been reported in the post-market setting.
Skin
In case of OXALIPLATIN INJECTION extravasation, the infusion must be stopped immediately and usual local symptomatic treatment initiated. Extravasation of OXALIPLATIN INJECTION may result in local pain and inflammation that may be severe and lead to complications, including necrosis and injection site reaction, including redness, swelling, and pain. In the literature, tissue necrosis has been reported with oxaliplatin extravasation (see References: De Lemos 2005).
Special Populations
Geriatrics (≥ 65 years of age): In patients previously untreated for metastatic colorectal cancer, patients ≥ 65 years (99 of 279 patients) receiving oxaliplatin in combination with 5-FU/LV experienced more fatigue, dehydration, diarrhea, leukopenia, and syncope than patients
< 65 years, although the difference was not statistically significant. Starting doses were the same in both age groups. In the adjuvant trial, patients ≥ 65 years receiving the oxaliplatin combination therapy (393 of 1108) experienced more grade 3-4 granulocytopenia and diarrhea than patients < 65 years although the difference was not statistically significant.
Pediatrics (≤ 22 years of age): Oxaliplatin single agent has been evaluated in pediatric population in 2 Phase I (69 patients) and 2 Phase II (166 patients) studies. A total of 235 pediatric patients (7 months-22 years of age) with solid tumors have been treated. The effectiveness of oxaliplatin single agent in the pediatric populations treated has not been established. Accrual in both Phase II studies was stopped for lack of tumor response (see INDICATIONS AND CLINICAL USES).
Pregnant Women: To date, there is no available information on safety of use in pregnant women. Based on preclinical findings, oxaliplatin is likely to be lethal and/or teratogenic to the human foetus at the recommended therapeutic doses. Therefore, oxaliplatin is contraindicated in pregnancy.
As with other cytotoxic agents, effective contraceptive measures should be taken in potentially fertile patients (male and female) prior to initiating chemotherapy with OXALIPLATIN INJECTION (see CONTRAINDICATIONS).
Nursing Women: Excretion in breast milk has not been studied. Breast-feeding is contraindicated during oxaliplatin therapy (see CONTRAINDICATIONS).
Hepatic Insufficiency: No increase in oxaliplatin acute toxicities was observed in the subset of patients with abnormal liver function tests at baseline. No specific dose adjustment for patients with abnormal liver function tests was performed during clinical development.
Renal Insufficiency: The primary route of platinum elimination is renal. Clearance of ultrafilterable platinum is decreased in patients with mild, moderate and severe renal impairment.
A pharmacodynamic relationship between platinum ultrafiltrate levels and clinical safety and effectiveness has not been established (see ACTION AND CLINICAL PHARMACOLOGY).
Oxaliplatin has not been studied in patients with severe renal impairment (see
CONTRAINDICATIONS).
Due to limited information on safety in patients with moderately impaired renal function, administration should be considered after suitable appraisal of the benefit/risk for the patient. In this situation, treatment may be initiated at the normally recommended dose and renal function should be closely monitored and dose adjusted according to toxicity.
Monitoring and Laboratory Tests
Complete blood count with differential, hemoglobin, platelets, and blood chemistries, including
ALT, AST, bilirubin, creatinine, magnesium and electrolytes should be performed prior to the start of therapy and before each subsequent course (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
There have been reports while on study and from post-marketing surveillance of prolonged prothrombin time and INR occasionally associated with hemorrhage in patients who received oxaliplatin plus 5-FU/LV while on anticoagulants. Patients receiving OXALIPLATIN
INJECTION plus 5-FU/LV and requiring oral anticoagulants may require closer monitoring (see DRUG INTERACTIONS).
Patients receiving OXALIPLATIN INJECTION combination therapy should be monitored for diarrhea, vomiting, and mucositis, which can lead to severe/life-threatening dehydration. If this occurs, discontinue OXALIPLATIN INJECTION until improvement or resolution (see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
A neurological examination should be performed before each administration and periodically thereafter. See DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment for guidance if neurological symptoms occur.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Both 5-FU and oxaliplatin are associated with gastrointestinal and hematologic adverse events. When oxaliplatin is administered in combination with 5-FU, the incidence of these events is increased.
The most common adverse reactions in patients treated with oxaliplatin in combination with 5-FU in the adjuvant colon and metastatic colorectal cancer trials were peripheral sensory neuropathies, fatigue, thrombocytopenia, anemia, neutropenia, nausea, vomiting, diarrhea, stomatitis and increase in hepatic enzymes and alkaline phosphatase (see WARNINGS AND PRECAUTIONS).
Blood and Lymphatic System Disorders:
Anemia, neutropenia and thrombocytopenia were reported with the combination of oxaliplatin and infusional 5-FU/LV (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
In adjuvant patients the incidence of febrile neutropenia was 0.1% in the 5-FU/LV infusion arm and 0.7% in the oxaliplatin plus 5-FU/LV arm. The incidence of febrile neutropenia in the patients previously untreated for metastatic colorectal cancer was 15% (3% of cycles) in the irinotecan plus 5-FU/LV arm and 4% (less than 1% of cycles) in the oxaliplatin plus 5-FU/LV arm. The incidence of febrile neutropenia in the previously treated patients was 1% in the 5-FU/LV arm and 5% (less than 1% of cycles) in the oxaliplatin plus 5-FU/LV combination arm.
In adjuvant patients the incidence of thrombocytopenia (all grades) was 77% vs. 19% (oxaliplatin plus 5-FU/LV vs. 5-FU/LV) while grade 3-4 thrombocytopenia incidence was 1.7% vs. 0.4%. There were more bleeding events in the oxaliplatin plus 5-FU/LV arm (gastrointestinal hemorrhage 0.5%; hematemesis 0.3%; rectal hemorrhage 1.3%). The incidence of thrombocytopenia in patients previously untreated for metastatic colorectal cancer was higher in the oxaliplatin plus 5-FU/LV arm vs irinotecan plus 5-FU/LV arm (all grade thrombocytopenia: 70% vs. 26%; grade 3 and 4: 5% vs 2%). However, bleeding events in the oxaliplatin plus 5-
FU/LV arm were infrequent and included: epistaxis, rectal bleeding, melena, vaginal bleeding, hematuria, and hemoptysis. The incidence of thrombocytopenia in patients previously treated for metastatic colorectal cancer was higher in the oxaliplatin plus 5-FU/LV arm vs. the 5-FU/LV arm (all grade thrombocytopenia: 67% vs 21%; grade 3 and 4: 6% vs. 0%).
Hemolytic Uremic Syndrome has been rarely reported with the use of oxaliplatin.
Gastrointestinal Disorders:
Anorexia, nausea, vomiting, diarrhea, stomatitis/mucositis and abdominal pain were commonly reported in the adjuvant treatment of patients with colon cancer and the previously untreated and treated patients for metastatic colorectal cancer (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Dehydration, hypokalemia, metabolic acidosis, ileus, intestinal obstruction and renal disorders may be associated with severe diarrhea or vomiting, particularly when OXALIPLATIN INJECTION is combined with 5-FU (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS, Other Clinical Trial Adverse Drug Reactions).
General Disorders and Administration Site Conditions:
Fever and rigors (tremors) either from infection (with or without febrile neutropenia) or possibly from immunological mechanism were reported in the adjuvant treatment of patients with colon cancer and in the previously untreated and treated patients for metastatic colorectal cancer (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Injection Site
Injection site reactions, including local pain, redness, swelling and thrombosis have been reported (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions). In the literature, tissue necrosis has been reported with oxaliplatin extravasation (see References: De Lemos 2005).
Immune System Disorders
Allergic reactions such as: skin rash (particularly urticaria), conjunctivitis, rhinitis and anaphylactic reactions were reported (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Musculoskeletal and Connective Tissue Disorders:
Back pain was reported in patients receiving oxaliplatin plus 5-FU/LV as adjuvant therapy and in the previously treated patients for metastatic colorectal cancer. In case of such adverse reaction, hemolysis (as part of Hemolytic Uremic Syndrome) which has been rarely reported should be investigated (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Arthralgia was also reported (see ADVERSE REACTIONS, Clinical Trial Adverse Drug
Reactions).
Nervous System Disorders:
Oxaliplatin is frequently associated with acute and chronic sensory peripheral neuropathy. There have been very rare reports of symptoms compatible with a diagnosis of Guillain-Barre Syndrome, for which a causal relationship has not been established (see ADVERSE REACTIONS, Other Clinical Trial Adverse Drug Reactions).
Peripheral sensory neuropathy was reported in adjuvant patients treated with the oxaliplatin combination with a frequency of 92% (all grades) and 13% (grade 3). In patients previously untreated for metastatic colorectal cancer, neuropathy was reported in 82% (all grades) and 19% (grade 3/4), and in the previously treated patients in 79% (all grades) and 11% (grade 3/4) events.
Peripheral Sensory Neuropathy
Acute sensory neuropathy
These symptoms usually develop at the end of the 2-hour oxaliplatin infusion or within a few hours, abate spontaneously within the next hours or days, and frequently recur with further cycles. They may be precipitated or exacerbated by exposure to cold temperatures or objects. They usually present as transient paresthesia, dysesthesia and hypoesthesia. An acute syndrome of pharyngolaryngeal dysesthesia (grades 3/4) characterized by subjective sensations of dysphagia or dyspnea, feeling of suffocation, without any evidence of respiratory distress (no cyanosis or hypoxia) or of laryngospasm or bronchospasm (no stridor or wheezing) occurs in 1- 2% of the patients. All grades of pharyngo-laryngeal dysesthesia were reported in up to 38% of the patients.
Dysesthesia / paresthesia of extremities and peripheral neuropathy
The dose limiting toxicity of oxaliplatin is neurological. It involves a sensory peripheral neuropathy characterized by peripheral dysesthesia and/or paresthesia with or without cramps, often triggered by the cold (85 to 95% of patients).
The duration of these symptoms, which usually recede between the cycles of treatment, increases with the number of treatment cycles. The onset of pain and /or a functional disorder and their duration are indications for dose adjustment, or even treatment discontinuation (see WARNINGS AND PRECAUTIONS; DOSAGE AND ADMINISTRATION). This functional disorder, including difficulties in executing delicate movements, is a possible consequence of sensory impairment. The risk of occurrence of a functional disorder for a cumulative dose of approximately 800 mg/m² (i.e. 10 cycles) is 15% or less. The neurological signs and symptoms improve when treatment is discontinued in the majority of cases.
Other neurologic manifestations
Other symptoms occasionally observed include cranial nerve dysfunction which may be either associated with above mentioned events, occur as a single, isolated event or several events may occur in combination. These include: ptosis, diplopia, aphonia, dysphonia, hoarseness, sometimes described as vocal cord paralysis, abnormal tongue sensation or dysarthria, sometimes described as aphasia, trigeminal neuralgia, facial pain, fasciculations, eye pain, decrease of visual acuity, visual field disorders, transient blindness (reversible following therapy discontinuation), amaurosis and amaurosis fugax. In addition, the following have been observed: jaw spasm, muscle spasms, involuntary muscle contractions, muscle twitching, myoclonus, abnormal coordination, abnormal gait, ataxia, balance disorders and throat or chest tightness/pressure/ discomfort/pain (see WARNINGS AND PRECAUTIONS, General).
Dysgeusia (taste perversion) was also reported (see ADVERSE REACTIONS, Clinical Trial
Adverse Drug Reactions).
Skin and Subcutaneous Tissue Disorders:
Alopecia in patients receiving oxaliplatin has been reported across clinical studies with an incidence of approximately one third (all grades), most cases being mild hair loss only.
Clinical Trial Adverse Drug Reactions
PATIENTS TREATED IN THE ADJUVANT SETTING FOR COLON CANCER
One thousand one hundred and eight (1108) patients with colon cancer were treated adjuvantly in a clinical study with oxaliplatin in combination with infusional 5-FU/LV (see CLINICAL TRIALS).
Treatment was discontinued due to an adverse event in 15% of patients on the oxaliplatin plus infusional 5-FU/LV arm compared to 6% of patients on the 5-FU/LV only arm.
The incidence of death within 28 days of last treatment, regardless of causality, was 0.5% (n=6) in both the oxaliplatin combination (primarily septic deaths) and infusional 5-FU/LV arms, respectively.
Deaths within 60 days from initiation of therapy were 0.3% (n=3) in both the oxaliplatin combination and infusional 5-FU/LV arms, respectively.
Although specific events can vary, the overall frequency of adverse events was similar in men and women and in patients <65 and ≥ 65 years. However, the following grade 3/4 events were more common in females regardless of treatment arm: diarrhea, fatigue, granulocytopenia, nausea and vomiting. In patients ≥ 65 years old, the incidence of grade 3/4 granulocytopenia and diarrhea was higher than in younger patients, although the difference was not statistically significant.
The following table provides adverse events reported in the adjuvant treatment of patients with colon cancer pivotal study (see CLINICAL TRIALS) for events with overall incidences ≥ 5 % in the arm combining oxaliplatin and 5-FU/LV.
Table 1 - Adverse Events Reported in the Adjuvant Treatment of Patients with Colon Cancer Pivotal Clinical Trial (≥ 5 % of all patients in the Oxaliplatin + 5-FU/LV arm) – by Body System
Oxaliplatin + 5-FU/LV N=1108 | 5-FU/LV N=1111 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||||
| Any Event | 100 | 70 | 99 | 31 | |||||||||
| Application Site Disorders | |||||||||||||
| Injection Site Reaction | 11 | 3 | 10 | 3 | |||||||||
| Body as a Whole – General Disorders | |||||||||||||
| Allergic Reaction | 10 | 3 | 2 | <1 | |||||||||
| Fatigue | 44 | 4 | 38 | 1 | |||||||||
| Fever | 27 | 1 | 12 | 1 | |||||||||
| Pain | 5 | <1 | 5 | <1 | |||||||||
| Weight Increase | 10 | <1 | 10 | <1 | |||||||||
| Central and Peripheral Nervous System Disorders | |||||||||||||
| Headache | 7 | <1 | 5 | <1 | |||||||||
| Overall Peripheral Sensory Neuropathy2 | 92 | 12 | 16 | <1 | |||||||||
| Sensory Disturbance | 8 | <1 | 1 | 0 | |||||||||
| Gastrointestinal System Disorders | |||||||||||||
| Abdominal Pain | 18 | 1 | 17 | 2 | |||||||||
| Anorexia | 13 | 1 | 8 | <1 | |||||||||
| Constipation | 22 | 1 | 19 | <1 | |||||||||
| Diarrhea | 56 | 11 | 48 | 7 | |||||||||
| Dyspepsia | 8 | <1 | 5 | 0 | |||||||||
| Nausea | 74 | 5 | 61 | 2 | |||||||||
| Stomatitis | 42 | 3 | 40 | 2 | |||||||||
| Vomiting | 47 | 6 | 24 | 1 | |||||||||
| Liver and Biliary System Disorders | |||||||||||||
| Bilirubinemia | 20 | 4 | 20 | 5 | |||||||||
| Hepatic Enzyme Increased | 57 | 2 | 34 | 1 | |||||||||
| Metabolic and Nutritional Disorders | |||||||||||||
| Phosphatase Alkaline Increased | 42 | <1 | 20 | <1 | |||||||||
| Platelet, Bleeding and Clotting Disorders | |||||||||||||
| Epistaxis | 16 | <1 | 12 | 0 | |||||||||
| Thrombocytopenia | 77 | 2 | 19 | <1 | |||||||||
| Red Blood Cell Disorders | |||||||||||||
| Anemia | 76 | 1 | 67 | <1 | |||||||||
| Resistance Mechanism Disorders | |||||||||||||
| Infection | 25 | 4 | 25 | 3 | |||||||||
| Respiratory System Disorders | |||||||||||||
| Dyspnea | 5 | 1 | 3 | <1 | |||||||||
Oxaliplatin + 5-FU/LV N=1108 | 5-FU/LV N=1111 |
|---|
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Rhinitis | 6 | 0 | 8 | <1 | ||||||
| Skin and Appendage Disorders | ||||||||||
| Alopecia1 | 30 | 0 | 28 | 0 | ||||||
| Skin Disorders | 32 | 2 | 36 | 2 | ||||||
| Special Senses Disorders | ||||||||||
| Taste Perversion | 12 | <1 | 8 | 0 | ||||||
| Vision Disorders | ||||||||||
| Conjunctivitis | 9 | 1 | 15 | 1 | ||||||
| White Cell and Res Disorders | ||||||||||
| Granulocytopenia | 79 | 41 | 40 | 5 | ||||||
1 Alopecia: only grades 1 and 2 according to the NCI grading scale used
2 Overall Peripheral Sensory Neuropathy: only grades 1, 2 and 3 according to the NCI grading scale used
RES: reticulo-endothelial system
The following additional most common and potentially important adverse events regardless of treatment causality were reported in less than 5 % of the patients in the oxaliplatin combined with 5-FU/LV arm in the pivotal study in the adjuvant treatment of patients with colon cancer.
Body as a whole – General Disorders: chest pain
Central & Peripheral Nervous System Disorders: dizziness
Metabolic/laboratory: magnesium levels were not prospectively tested
Psychiatric Disorders: insomnia
Respiratory System Disorders: coughing
Vision Disorders: abnormal lacrimation
White Cell and Reticulo-endothelial System Disorders: leukopenia
PATIENTS PREVIOUSLY UNTREATED FOR METASTATIC COLORECTAL CANCER
Two hundred and fifty-nine (259) patients were treated in the oxaliplatin plus 5-FU/LV combination arm of the randomized trial in patients previously untreated for metastatic colorectal cancer (see CLINICAL TRIALS).
Twenty-six percent (26 %) of patients in the oxaliplatin plus 5-FU/LV combination arm and 8 % in the irinotecan plus 5-FU/LV arm had to discontinue treatment because of adverse effects related most commonly to gastrointestinal, hematologic or neurologic adverse events.
The incidence of death within 30 days of treatment in the previously untreated for metastatic colorectal cancer study, regardless of causality, was 3 % with the oxaliplatin plus 5-FU/LV, 5 % with irinotecan plus 5-FU/LV and 3 % with oxaliplatin plus irinotecan. Deaths within 60 days from initiation of therapy were 2 % with oxaliplatin plus 5-FU/LV, 5 % with irinotecan plus 5-FU/LV and 3 % with oxaliplatin plus irinotecan. Deaths within 60 days from initiation of therapy on the oxaliplatin plus 5-FU/LV arm were attributed to disease progression, sepsis, dehydration/electrolyte imbalance, and liver failure.
The following adverse events were reported more frequently in patients ≥ 65 years old on the oxaliplatin and 5-FU/LV combination arm: constitutional symptoms, fatigue, anorexia, dehydration, leukopenia, musculoskeletal events, syncope and pulmonary events.
For any class of adverse event (all inclusive), the overall reported cases were similar across arms and populations. When grade 3 or 4 events were evaluated, the female patient population reported a higher number of events independent of treatment arm.
The following table provides adverse events reported in the previously untreated for metastatic colorectal cancer pivotal study (see CLINICAL TRIALS) for events with overall incidences ≥ 5 % in the oxaliplatin and 5-FU/LV combination arm.
Table 2 - Adverse Events Reported in Patients Previously Untreated for Metastatic Colorectal Cancer Clinical Trial (≥ 5 % of all patients in the Oxaliplatin + 5-FU/LV arm) – by Body System
oxaliplatin + 5-FU/LV N =259 | irinotecan + 5-FU/LV N=256 | oxaliplatin + irinotecan N=258 | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||||
| Any Event | 99 | 82 | 98 | 70 | 99 | 76 | |||||||||
| Allergy/Immunology | |||||||||||||||
| Allergic rhinitis | 10 | 0 | 6 | 0 | 6 | 0 | |||||||||
| Hypersensitivity | 12 | 2 | 5 | 0 | 6 | 1 | |||||||||
| Cardiovascular | |||||||||||||||
| Oedema | 15 | 0 | 13 | <1 | 10 | 1 | |||||||||
| Thrombosis | 6 | 5 | 6 | 6 | 3 | 3 | |||||||||
| Constitutional Symptoms | |||||||||||||||
| Fatigue | 70 | 7 | 58 | 11 | 66 | 16 | |||||||||
| Fever - no ANC* | 16 | 1 | 9 | <1 | 9 | 0 | |||||||||
| Rigors | 8 | <1 | 2 | 0 | 7 | 0 | |||||||||
| Sweating | 5 | 0 | 6 | 0 | 12 | 0 | |||||||||
| Weight loss | 11 | 0 | 9 | <1 | 11 | <1 | |||||||||
| Dermatology/Skin | |||||||||||||||
| Alopecia | 38 | 0 | 44 | 0 | 67 | 0 | |||||||||
| Dermatology NOS* | 6 | 0 | 1 | 0 | 2 | 0 | |||||||||
| Dry skin | 6 | 0 | 2 | 0 | 5 | 0 | |||||||||
| Flushing | 7 | 0 | 2 | 0 | 5 | 0 | |||||||||
| Injection site reaction | 6 | 0 | 1 | 0 | 4 | 1 | |||||||||
| Pruritus | 6 | 0 | 4 | 0 | 2 | 0 | |||||||||
| Rash | 11 | <1 | 4 | 0 | 7 | 1 | |||||||||
Skin reaction – hand/foot syndrome | 7 | 1 | 2 | <1 | 1 | 0 | |||||||||
| Gastrointestinal | |||||||||||||||
| Anorexia | 35 | 2 | 25 | 4 | 27 | 5 | |||||||||
| Constipation | 32 | 4 | 27 | 2 | 21 | 2 | |||||||||
oxaliplatin + 5-FU/LV N =259 | irinotecan + 5-FU/LV N=256 | oxaliplatin + irinotecan N=258 |
|---|
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Dehydration | 9 | 5 | 16 | 11 | 14 | 7 | |||||||
| Diarrhea - colostomy | 13 | 2 | 16 | 7 | 16 | 3 | |||||||
| Diarrhea - no colostomy | 56 | 12 | 65 | 29 | 76 | 25 | |||||||
| Dyspepsia | 12 | 0 | 7 | 0 | 5 | <1 | |||||||
| Dysphagia | 5 | 0 | 3 | 0 | 3 | <1 | |||||||
| Flatulence | 9 | 0 | 6 | 0 | 5 | <1 | |||||||
| Mouth dryness | 5 | 0 | 2 | 0 | 3 | 0 | |||||||
| Nausea | 71 | 6 | 67 | 15 | 83 | 19 | |||||||
| Stomatitis | 38 | 0 | 25 | 1 | 19 | <1 | |||||||
| Taste | 14 | 0 | 6 | 0 | 8 | <1 | |||||||
| Vomiting | 41 | 4 | 43 | 13 | 64 | 23 | |||||||
| Hemorrhage | |||||||||||||
| Epistaxis | 10 | 0 | 2 | 0 | 2 | <1 | |||||||
| Infection/Febrile Neutropenia | |||||||||||||
| Infection – ANC* | 8 | 8 | 12 | 11 | 9 | 8 | |||||||
| Infection - no ANC* | 10 | 4 | 5 | 1 | 7 | 2 | |||||||
| Neurology | |||||||||||||
| Anxiety | 5 | 0 | 2 | 0 | 6 | <1 | |||||||
| Depression | 9 | 1 | 5 | <1 | 7 | 1 | |||||||
| Dizziness | 8 | <1 | 6 | 0 | 10 | 1 | |||||||
| Insomnia | 13 | 0 | 9 | 0 | 11 | 0 | |||||||
| Neuro-sensory | 12 | 1 | 2 | 0 | 9 | 1 | |||||||
| Paresthesias | 77 | 18 | 16 | 2 | 62 | 7 | |||||||
Pharyngo-laryngeal dysesthesias | 38 | 2 | 1 | 0 | 28 | 1 | |||||||
| Ocular/Visual | |||||||||||||
| Abnormal vision | 5 | 0 | 2 | <1 | 6 | 1 | |||||||
| Tearing | 9 | 0 | 1 | 0 | 2 | <1 | |||||||
| Pain | |||||||||||||
| Abdominal pain | 29 | 8 | 31 | 7 | 39 | 10 | |||||||
| Arthralgia | 5 | <1 | 5 | 0 | 8 | <1 | |||||||
| Headache | 13 | <1 | 6 | <1 | 9 | <1 | |||||||
| Myalgia | 14 | 2 | 6 | 0 | 9 | 2 | |||||||
| Pain | 7 | 1 | 5 | 1 | 6 | 1 | |||||||
| Pulmonary | |||||||||||||
| Cough | 35 | 1 | 25 | 2 | 17 | <1 | |||||||
| Dyspnea | 18 | 7 | 14 | 3 | 11 | 2 | |||||||
| Renal/Genitourinary | |||||||||||||
| Urinary frequency | 5 | 1 | 2 | <1 | 3 | 1 | |||||||
* ANC: absolute neutrophil count; NOS: Not otherwise specified
The following additional most common and potentially important adverse events regardless of treatment causality were reported in less than 5 % of the patients in the oxaliplatin and 5-FU/LV combination arm in the previously untreated for metastatic colorectal cancer pivotal study.
Cardiovascular: hypertension, hypotension, prothrombin time
Dermatology/skin: nail changes, pigmentation changes, urticaria
Gastrointestinal: gastrointestinal not otherwise specified (NOS)
Hemorrhage: rectal bleeding
Infection/febrile neutropenia: catheter infection, febrile neutropenia, unknown infection
Metabolic/laboratory: magnesium levels were not prospectively tested
Neurology: syncope, vertigo
Pain: bone pain, chest pain, neuralgia, rectal pain
Pulmonary: hiccups, hypoxia, pneumonitis, pulmonary NOS
Renal/Genitourinary: creatinine, dysuria
PATIENTS PREVIOUSLY TREATED FOR METASTATIC COLORECTAL CANCER
Seven hundred and ninety one (791) patients were studied in a randomized trial in patients with refractory and relapsed colorectal cancer in which 268 patients received the combination of oxaliplatin and 5-FU/LV (see CLINICAL TRIALS).
Fourteen percent (14 %) of patients in the oxaliplatin and 5-FU/LV combination arm and 7 % in the 5-FU/LV arm of the previously treated study had to discontinue treatment because of adverse effects related to allergy, fatigue, gastrointestinal events, hematological events or neuropathies.
The incidence of death within 30 days of treatment in the previously treated study, regardless of causality, was 6 % with the oxaliplatin and 5-FU/LV combination, 6 % with oxaliplatin alone and 5 % with 5-FU/LV.
The following adverse events were reported more frequently in patients ≥ 65 years old on the oxaliplatin and 5-FU/LV combination arm: cellulitis, general cardiovascular disorders, anorexia, dehydration, platelet, bleeding and clotting disorders and secondary terms.
For any class of adverse event (all inclusive), the proportion of patients reporting adverse events (all grade) was similar across arms and patient populations (male, female). When grade 3 or 4 events were evaluated, the female patient population reported a higher number of events independent of treatment arm.
The following table provides adverse events reported in the previously treated pivotal study (see
CLINICAL TRIALS) for events with overall incidences ≥ 5 % in the oxaliplatin and 5-FU/LV combination arm.
Table 3- Adverse Events Reported in Patients Previously Treated for Metastatic Colorectal Cancer Clinical Trial (≥ 5% of all patients in the oxaliplatin and 5-FU/LV arm) – by Body System
oxaliplatin + 5-FU/LV (N =268) | oxaliplatin (N=266) | 5-FU/LV (N=257) | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||||||
| Any event | 100 | 81 | 100 | 46 | 98 | 44 | ||||||||||||
| Application Site Disorders | ||||||||||||||||||
| Injection site reaction | 13 | 3 | 7 | 0 | 7 | 1 | ||||||||||||
| Autonomic Nervous System Disorders | ||||||||||||||||||
| Flushing | 10 | 0 | 3 | 0 | 2 | 0 | ||||||||||||
| Body as a Whole | ||||||||||||||||||
| Accidental injury | 7 | 0 | 2 | 0 | 4 | 0 | ||||||||||||
| Allergic reaction | 8 | 1 | 3 | 1 | 2 | 1 | ||||||||||||
| Chest pain | 8 | 1 | 4 | <1 | 5 | 1 | ||||||||||||
| Fatigue | 75 | 10 | 59 | 10 | 57 | 6 | ||||||||||||
| Fever | 31 | 0 | 20 | 1 | 19 | 1 | ||||||||||||
| Pain | 16 | 2 | 13 | 3 | 12 | 3 | ||||||||||||
| Rigors | 11 | 0 | 7 | 0 | 5 | 0 | ||||||||||||
| Weight decrease | 9 | <1 | 8 | 0 | 6 | 0 | ||||||||||||
| Cardiovascular Disorders, General | ||||||||||||||||||
| Oedema legs | 8 | <1 | 5 | 1 | 6 | 1 | ||||||||||||
| Peripheral oedema | 6 | 0 | 3 | <1 | 5 | 1 | ||||||||||||
| Central & Peripheral Nervous System Disorders | ||||||||||||||||||
| Dizziness | 15 | 1 | 7 | <1 | 9 | <1 | ||||||||||||
| Headache | 16 | <1 | 14 | 0 | 10 | 1 | ||||||||||||
| Neuropathy | 6 | <1 | 9 | 0 | 2 | <1 | ||||||||||||
| Paresthesia | 54 | 7 | 49 | 2 | 13 | 0 | ||||||||||||
| Sensory disturbance | 58 | 4 | 58 | 4 | 2 | 0 | ||||||||||||
| Gastrointestinal System Disorders | ||||||||||||||||||
| Abdominal pain | 35 | 4 | 32 | 6 | 33 | 5 | ||||||||||||
| Anorexia | 33 | 3 | 25 | 2 | 22 | 2 | ||||||||||||
| Constipation | 33 | 1 | 32 | 2 | 24 | 1 | ||||||||||||
| Diarrhea | 65 | 11 | 40 | 3 | 42 | 2 | ||||||||||||
| Dyspepsia | 13 | 0 | 7 | 0 | 9 | 0 | ||||||||||||
| Flatulence | 9 | 0 | 5 | <1 | 8 | 0 | ||||||||||||
| Hiccup | 5 | <1 | 2 | 0 | 1 | <1 | ||||||||||||
| Intestinal obstruction | 5 | 5 | 4 | 3 | 2 | 2 | ||||||||||||
| Mucositis NOS* | 8 | 1 | 2 | 0 | 9 | 1 | ||||||||||||
| Nausea | 68 | 10 | 58 | 4 | 53 | 2 | ||||||||||||
| Stomatitis | 28 | 2 | 8 | 0 | 22 | 1 | ||||||||||||
| Vomiting | 44 | 9 | 38 | 5 | 27 | 2 | ||||||||||||
| Metabolic and Nutritional Disorders | ||||||||||||||||||
| Dehydration | 9 | 4 | 5 | 3 | 4 | 2 | ||||||||||||
| Musculo-skeletal System Disorders | ||||||||||||||||||
| Arthralgia | 10 | 1 | 8 | <1 | 11 | 3 | ||||||||||||
| Back pain | 16 | 2 | 11 | <1 | 17 | 4 | ||||||||||||
| Myalgia | 6 | <1 | 4 | 0 | 2 | 0 | ||||||||||||
| Neoplasms | ||||||||||||||||||
Aggravated neoplasm malignant | 13 | 12 | 10 | 9 | 13 | 13 | ||||||||||||
| Platelet, Bleeding & Clotting Disorders | ||||||||||||||||||
| Epistaxis | 11 | 0 | 3 | 0 | 3 | 0 | ||||||||||||
oxaliplatin + 5-FU/LV (N =268) | oxaliplatin (N=266) | 5-FU/LV (N=257) |
|---|
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Hematuria | 6 | 2 | 1 | 0 | 3 | 1 | |||||||
| Thrombocytopenia | 15 | 5 | 5 | 1 | 0 | 0 | |||||||
| Psychiatric Disorders | |||||||||||||
| Anxiety | 7 | <1 | 6 | 0 | 5 | 0 | |||||||
| Depression | 7 | <1 | 5 | 0 | 5 | <1 | |||||||
| Insomnia | 16 | 0 | 9 | <1 | 5 | 0 | |||||||
| Red Blood Cell Disorders | |||||||||||||
| Anemia | 20 | 5 | 7 | 1 | 11 | 2 | |||||||
| Respiratory System Disorders | |||||||||||||
| Coughing | 19 | 2 | 10 | <1 | 13 | 0 | |||||||
| Dyspnea | 20 | 3 | 13 | 4 | 13 | 2 | |||||||
| Pharyngitis | 10 | 0 | 2 | 0 | 7 | 0 | |||||||
| Rhinitis | 13 | 0 | 6 | 0 | 7 | 0 | |||||||
| Sinusitis | 6 | 0 | 3 | 0 | 4 | 0 | |||||||
| Upper resp. tract infection | 12 | 1 | 7 | 0 | 9 | 0 | |||||||
| Skin and Appendage Disorders | |||||||||||||
| Alopecia | 8 | 0 | 3 | <1 | 4 | 0 | |||||||
| Rash | 14 | 0 | 4 | 0 | 5 | 0 | |||||||
| Skin exfoliation | 9 | 1 | 2 | 0 | 11 | 1 | |||||||
| Sweating increased | 7 | 0 | 8 | 0 | 4 | 0 | |||||||
| Special Senses Other, Disorders | |||||||||||||
| Taste perversion | 12 | 0 | 3 | 0 | 4 | 0 | |||||||
| Urinary System Disorders | |||||||||||||
| Dysuria | 6 | <1 | 1 | 0 | 2 | <1 | |||||||
| Urinary tract infection | 5 | <1 | 5 | 2 | 4 | 1 | |||||||
| Vision Disorders | |||||||||||||
| Abnormal lacrimation | 8 | 0 | 1 | 0 | 8 | 0 | |||||||
| White cell and RES Disorders* | |||||||||||||
| Decreased neutrophils | 5 | 2 | 0 | 0 | <1 | <1 | |||||||
| Granulocytopenia | 52 | 41 | 1 | 0 | 9 | 3 | |||||||
| Leukopenia | 9 | 4 | 0 | 0 | 1 | <1 | |||||||
* NOS: Not otherwise specified; RES: Reticulo-Endothelial System
The following additional most common and potentially important adverse events regardless of treatment causality were reported in less than 5 % of the patients in the oxaliplatin and 5-FU/LV combination arm in the previously treated for metastatic colorectal cancer pivotal study.
Body as a whole – General Disorders: ascites
Cardiovascular Disorders, General: oedema
Central and Peripheral Nervous System Disorders: ataxia
Gastro-intestinal System Disorders: dry mouth, gastroesophageal reflux, tenesmus
Heart Rate and Rhythm Disorders: tachycardia
Metabolic/laboratory: magnesium levels were not prospectively tested
Musculo-Skeletal System Disorders: bone pain
Platelet, Bleeding and Clotting Disorders: bruise, deep thrombophlebitis, melena, rectal hemorrhage
Respiratory System Disorders: pneumonia
Skin and Appendage Disorders: dry skin, erythematous rash, pruritus, skin disorder
Vision Disorders: abnormal vision, conjunctivitis
White Cell and Reticulo-Endothelial System Disorders: febrile neutropenia
Abnormal Hematologic and Clinical Chemistry Findings
PATIENTS TREATED IN THE ADJUVANT SETTING FOR COLON CANCER
Table 4 – Hepatic Adverse Events in Patients with Colon Cancer Receiving Adjuvant Therapy (≥ 5% of patients)
| Hepatic Parameter | Oxaliplatin + 5-FU/LV (N=1108) | 5-FU/LV (N=1111) | |||||||
All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||
| Hepatic enzymes elevation | 57 | 2 | 34 | 1 | |||||
| Phosphatase alkaline increased | 42 | <1 | 20 | <1 | |||||
| Bilirubinemia | 20 | 4 | 20 | 5 | |||||
Table 5 – Hematologic Adverse Events in Patients with Colon Cancer Receiving Adjuvant Therapy (≥ 5% of patients)
Oxaliplatin + 5-FU/LV (N=1108) | 5-FU/LV (N=1111) | ||||||||
Adverse Event* (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||
| Anemia | 76 | 1 | 67 | 0.3 | |||||
| Neutropenia | 79 | 41 | 40 | 5 | |||||
| Thrombocytopenia | 77 | 2 | 19 | <1 | |||||
*The hematology data were collected by NCI grade; no laboratory values were collected.
The worst grade observed during each cycle period was reported.
PATIENTS PREVIOUSLY UNTREATED FOR METASTATIC COLORECTAL CANCER
Table 6 - Hepatic Adverse Events in Patients Previously Untreated for Metastatic Colorectal Cancer (≥ 5 % of patients).
oxaliplatin + 5-FU/LV N =259 | irinotecan + 5-FU/LV N=256 | oxaliplatin + irinotecan N=258 | |||||||||||
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||
| Alkaline phosphatase | 16 | 0 | 7 | 0 | 16 | 2 | |||||||
| ALT (SGPT)* | 6 | 1 | 2 | 0 | 5 | 2 | |||||||
| AST (SGOT)* | 17 | 1 | 2 | <1 | 11 | 1 | |||||||
| Bilirubin Total | 6 | <1 | 3 | 1 | 3 | 2 | |||||||
| Hypoalbuminemia | 8 | 0 | 5 | 2 | 9 | <1 | |||||||
*AST/SGOT: aspartate aminotransferase; ALT/SGPT: alanine aminotransferase
Table 7 - Hematologic Adverse Events in Patients Previously Untreated for Metastatic Colorectal Cancer (≥ 5 % of patients).
oxaliplatin + 5-FU/LV N =259 | irinotecan + 5-FU/LV N=256 | oxaliplatin + irinotecan N=258 | |||||||||||
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||
| Anemia | 27 | 3 | 28 | 4 | 25 | 3 | |||||||
| Leukopenia | 87 | 20 | 84 | 23 | 78 | 25 | |||||||
| Lymphopenia | 6 | 2 | 4 | 1 | 5 | 2 | |||||||
| Neutropenia | 81 | 54 | 77 | 46 | 73 | 39 | |||||||
| Thrombocytopenia | 71 | 5 | 26 | 3 | 45 | 4 | |||||||
Table 8 – Metabolic Adverse Events in Patients Previously Untreated for Metastatic Colorectal Cancer (≥ 5 % of patients).
oxaliplatin + 5-FU/LV N =259 | irinotecan + 5-FU/LV N=256 | oxaliplatin + irinotecan N=258 | |||||||||||
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||||
| Hyperglycemia | 14 | 2 | 11 | 3 | 12 | 3 | |||||||
| Hypocalcemia | 7 | 0 | 5 | 1 | 4 | 0 | |||||||
| Hypokalemia | 11 | 3 | 7 | 4 | 6 | 2 | |||||||
| Hyponatremia | 8 | 2 | 7 | 4 | 4 | 1 | |||||||
PATIENTS PREVIOUSLY TREATED FOR METASTATIC COLORECTAL CANCER
Table 9 – Hepatic clinical chemistry abnormalities in Patients Previously Treated for Metastatic Colorectal Cancer (≥ 5 % of patients)
oxaliplatin + 5-FU/LV (N =268) | oxaliplatin (N=266) | 5-FU/LV (N=257) | ||||||||||||
| Clinical Chemistry | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||
| Alkaline phosphatase | 60 | 4 | 60 | 7 | 50 | 5 | ||||||||
| ALT (SGPT)* | 36 | 0 | 39 | 1 | 27 | 1 | ||||||||
| AST (SGOT)* | 53 | 0 | 57 | 4 | 42 | 2 | ||||||||
| Bilirubin Total | 13 | 1 | 15 | 4 | 20 | 6 | ||||||||
| Lactate dehydrogenase | 53 | 22 | 53 | 23 | 46 | 24 | ||||||||
*AST/SGOT: aspartate aminotransferase; ALT/SGPT: alanine aminotransferase
Table 10 - Clinically Significant Hematologic abnormalities by Preferred Term and Body System in Patients Previously Treated for Metastatic Colorectal Cancer (≥ 5 % of patients).
oxaliplatin + 5-FU/LV (N =268) | oxaliplatin (N=266) | 5-FU/LV (N=257) | ||||||||||||
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||
| Anemia | 84 | 5 | 61 | 2 | 67 | 2 | ||||||||
| Leukopenia | 81 | 27 | 13 | <1 | 35 | 2 | ||||||||
| Neutropenia | 77 | 52 | 7 | 0 | 25 | 6 | ||||||||
| Thrombocytopenia | 67 | 6 | 28 | 2 | 21 | 0 | ||||||||
Table 11– Metabolic Adverse Event by Preferred Term and Body System in Patients Previously Treated for Metastatic Colorectal Cancer (≥ 5 % of patients).
oxaliplatin + 5-FU/LV (N =268) | oxaliplatin (N=266) | 5-FU/LV (N=257) | ||||||||||||
Adverse Event (WHO/Pref) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||
| Hypokalemia | 9 | 6 | 3 | 2 | 3 | 1 | ||||||||
Other Clinical Trial Adverse Drug Reactions
Frequencies are defined using the following convention: very common (≥10%); common (≥ 1%,
< 10%); uncommon (≥ 0.1%, < 1%); rare (≥ 0.01%, <0.1%): very rare (< 0.01%), not known (cannot be estimated from the available data).
Blood and Lymphatic System Disorders
Rare: hemolysis
Ear and Labyrinth Disorders:
Rare: deafness.
Eye Disorders:
Rare: visual acuity reduced transiently, optic neuritis, transient vision loss reversible following therapy discontinuation, visual field disturbances. Several cases of positive rechallenge associated with subsequent cycles of chemotherapy were reported indicating probable causal relationship to oxaliplatin.
Gastrointestinal Disorders:
Very common: Dehydration, hypokalemia, metabolic acidosis, ileus, intestinal obstruction, renal disorders may be associated with severe diarrhea/vomiting, particularly when oxaliplatin is combined with 5-FU.
Common: gastrointestinal hemorrhage
Rare: colitis, including Clostridium difficile diarrhea
General Disorders and Administration Site Conditions:
Very common: asthenia.
Extravasation may also result in local pain and inflammation, which may be severe and lead to complications including necrosis, especially when oxaliplatin is infused through a peripheral vein.
Hepatobiliary Disorders:
Rare: pancreatitis
Very rare: hepatic failure, hepatitis, liver sinusoidal obstruction syndrome, also known as veno-occlusive disease of liver, or pathological manifestations related to such liver disorder, including nodular regenerative hyperplasia, peliosis hepatis, perisinusoidal fibrosis. Clinical manifestations of this syndrome may be portal hypertension and/or increased transaminases.
Immune System Disorders:
Common: anaphylactic reactions including bronchospasm, angioedema, hypotension, sensation of chest pain and anaphylactic shock.
Rare: immuno-allergic hemolytic anemia, immuno-allergic thrombocytopenia.
Nervous System Disorders:
Very common: acute neuro-sensory manifestations, dysesthesia, paresthesia of extremities and peripheral neuropathy.
Rare: dysarthria, Lhermitte’s sign, loss of deep tendon reflexes, reversible posterior leucoencephalopathy syndrome (RPLS, also known as PRES) (see WARNINGS and
PRECAUTIONS, Neurologic section).
Very rare: Reports of symptoms compatible with a diagnosis of Guillain-Barre Syndrome.
Causal relationship has not been established.
Renal and Urinary Disorders:
Very rare: acute tubular necrosis, acute interstitial nephritis and acute renal failure were reported.
Respiratory, Thoracic and Mediastinal Disorders:
Rare: acute interstitial lung diseases (including fatalities), pulmonary fibrosis (see WARNINGS AND PRECAUTIONS).
Vascular Disorders:
Common: hypertension, thromboembolic events, including deep vein thrombosis.
Post-Market Adverse Drug Reactions
The following events have been reported from worldwide post-marketing experience.
Blood and Lymphatic System Disorders: hemolytic uremic syndrome; febrile neutropenia; disseminated intravascular coagulation (DIC), including fatalities (see WARNINGS AND
PRECAUTIONS, Hematologic), autoimmune pancytopenia, pancytopenia, secondary leukemia
Cardiac Disorders: QT prolongation, which may lead to ventricular arrhythmias including
Torsade de Pointes, which may be fatal (see WARNINGS AND PRECAUTIONS,
Cardiovascular).
Eye Disorders: amaurosis, amaurosis fugax. Cases of positive rechallenge associated with subsequent cycles of chemotherapy were reported indicating probable causal relationship to oxaliplatin.
Few cases of optic ischemic neuropathy were reported without established causal relationship.
Gastrointestinal disorders: intestinal ischaemia (including fatalities); duodenal ulcer, and complications, such as duodenal ulcer haemorrhage or perforation, which can be fatal (see
WARNINGS AND PRECAUTIONS, Gastrointestinal).
Hepatobiliary Disorders: increased bilirubin
Immune System Disorders: delayed hypersensitivity
Infections and Infestations: sepsis, neutropenic sepsis, septic shock, including fatal outcome
(see WARNINGS AND PRECAUTIONS, Infections and Infestations)
Metabolism and Nutrition Disorders: Hypomagnesemia
Musculoskeletal and Connective Tissue Disorders: Rhabdomyolysis (including fatalities) (see
WARNINGS AND PRECAUTIONS, Musculoskeletal)
Nervous System Disorders: convulsion, hyperammonaemic encephalopathy, ischemic and hemorrhagic cerebrovascular disorder
Respiratory, Thoracic and Mediastinal Disorders: laryngospasm, pneumonia and bronchopneumonia, including fatal outcomes
Skin and Subcutaneous Tissue Disorders: hypersensitivity vasculitis
DRUG INTERACTIONS
Overview
No specific cytochrome P-450-based drug interaction studies have been conducted.
In vitro, oxaliplatin is not metabolized by, nor does it inhibit, human cytochrome P450 isoenzymes. No P450-mediated drug-drug interactions are therefore anticipated in patients.
Since platinum-containing species are eliminated primarily through the kidney, clearance of these products may be decreased by coadministration of potentially nephrotoxic compounds; although, this has not been specifically studied (see ACTION AND CLINICAL PHARMACOLOGY).
Drug-Drug Interactions
In patients who have received a single dose of 85 mg/m² of oxaliplatin immediately before administration of 5-FU, no change in the level of exposure to 5-FU has been observed. No pharmacokinetic interaction between 85 mg/m2 oxaliplatin and 5-FU/LV has been observed in patients treated every 2 weeks. Increases of 5-FU plasma concentrations by approximately 20 % have been observed with doses of 130 mg/m2 oxaliplatin administered every 3 weeks. The approved dose of oxaliplatin is 85 mg/m2 every 2 weeks in combination with 5-FU/LV (see DOSAGE AND ADMINISTRATION).
In vitro, platinum was not displaced from plasma proteins by the following medications: erythromycin, salicylate, sodium valproate, granisetron and paclitaxel.
There have been reports while on study and from post-marketing surveillance of prolonged prothrombin time and INR occasionally associated with hemorrhage in patients who received oxaliplatin plus 5-FU/LV while on anticoagulants. Patients receiving oxaliplatin plus 5-FU/LV and requiring oral anticoagulants may require closer monitoring.
Caution is advised when OXALIPLATIN INJECTION treatment is co-administered with other medicinal products known to cause QT interval prolongation. In case of combination with such medicinal products, the QT interval should be closely monitored (see WARNINGS AND PRECAUTIONS, Cardivascular).
Caution is advised when OXALIPLATIN INJECTION treatment is administered concomitantly with other medicinal products known to be associated with rhabdomyolysis (see WARNINGS AND PRECAUTIONS, Musculoskeletal).
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herbs Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Dosage given should be adjusted according to tolerability.
- If severe/life-threatening diarrhea, neurotoxicity or hematological toxicity occurs, a dose adjustment may be required (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
Recommended Dose and Dosage Adjustment
Administer OXALIPLATIN INJECTION in combination with 5-FU/LV every 2 weeks. For metastatic disease, treatment is recommended until disease progression or unacceptable toxicity. For adjuvant use, treatment is recommended for a total of 12 cycles (6 months). The recommended dose schedule given every 2 weeks is as follows:
Day 1:
OXALIPLATIN INJECTION 85 mg/m2 IV infusion in 250 to 500 mL of 5% (50 mg/mL) glucose solution (D5W) is given at the same time as leucovorin 200 mg/m2 IV infusion in 5 % glucose solution (D5W), over 2 to 6 hours in separate bags using a Y-line.
Followed by 5-FU 400 mg/m2 IV bolus given over 2-4 minutes, followed by 5-FU 600 mg/m2 IV infusion in 500 mL of 5 % glucose solution (D5W) (recommended) as a 22-hour continuous infusion.
Day 2:
Leucovorin 200 mg/m2 IV infusion over 2 hours.
Followed by 5-FU 400 mg/m2 IV bolus given over 2-4 minutes, followed by 5-FU 600 mg/m2 IV infusion in 500 mL of 5 % glucose solution (D5W) (recommended) as a 22-hour continuous infusion.
| Day 1 | 5-FU bolus 400 mg/m2 over 2-4 minutes ↓ | Day 2 | 5-FU bolus 400 mg/m2 over 2-4 minutes ↓ |
Leucovorin 200 mg/m2 | 5-FU infusion 600 mg/m2 | Leucovorin 200 mg/m2 | 5-FU infusion 600 mg/m2 |
Oxaliplatin 85 mg/m2 | |||
| 0 h | 2 h 22 hrs | 0 h | 2 h 22 hrs |
| ←2 hrs→ | ←2 hrs→ |
Geriatrics (≥ 65 years of age): Starting dose in this age group is the same. In studies of patients with metastatic colorectal cancer, patients ≥ 65 years receiving oxaliplatin in combination with 5-FU/LV experienced more fatigue, dehydration, diarrhea, leukopenia, and syncope than patients < 65 years, although the difference was not statistically significant. In the adjuvant trial, patients ≥ 65 years receiving the oxaliplatin combination therapy experienced more grade 3/4 granulocytopenia and diarrhea than patients < 65 years, although the difference was not statistically significant.
Gastrointestinal:
Adjuvant Stage III colon cancer: If severe/life-threatening gastrointestinal toxicity (NCI CTC grade 3-4) occurs despite prophylactic treatment, OXALIPLATIN INJECTION must be discontinued until resolution. A dose reduction of OXALIPLATIN INJECTION to 75 mg/m2 and bolus 5-FU to 300 mg/m2 and infusional 5-FU to 500 mg/m2 over 22 hours is recommended at subsequent cycles.
Metastatic colorectal cancer: After recovery from grade 3 or 4 gastrointestinal toxicity (despite prophylactic treatment), a dose reduction of OXALIPLATIN INJECTION to 65 mg/m2 and 5-FU by 20% (300 mg/m2 bolus and 500 mg/m2 22-hour infusion) is recommended.
Hematologic:
Adjuvant Stage III colon cancer: After recovery from grade 3-4 neutropenia (ANC < 1.0 x 10⁹/L) febrile neutropenia (fever of unknown origin without clinically or microbiologically documented infection with an absolute neutrophil count < 1.0 x 10⁹/L, a single temperature of
> 38.3°C or a sustained temperature of > 38°C for more than one hour) or grade 3-4 thrombocytopenia (platelets < 50 x 109/L), a dose reduction of OXALIPLATIN INJECTION to 75 mg/m2 and bolus 5-FU to 300 mg/m2 and infusional 5-FU to 500 mg/m2 over 22 hours is recommended. The next dose should be delayed until neutrophils ≥ 1.5 x 10⁹/L and platelets ≥ 75 x 109/L.
Metastatic colorectal cancer: After recovery from grade 3/4 neutropenia (ANC < 1.0 x 10⁹/L), febrile neutropenia (fever of unknown origin without clinically or microbiologically documented infection with an absolute neutrophil count < 1.0 x 10⁹/L, a single temperature of > 38.3°C or a sustained temperature of > 38°C for more than one hour) or grade 3/4 thrombocytopenia (platelets < 50 x 109/L), a dose reduction of OXALIPLATIN INJECTION to 65 mg/m2 and 5-FU by 20% (300 mg/m2 bolus and 500 mg/m2 22-hour infusion) is recommended. The next dose should be delayed until: neutrophils ≥ 1.5 x 10⁹/L and platelets ≥ 75 x 109/L.
Neurologic:
For patients (any indication) who develop acute laryngo-pharyngeal dysesthesia (see ADVERSE
REACTIONS), during or within the hours following the 2-hour infusion, the next OXALIPLATIN INJECTION infusion should be administered over 6 hours. To prevent such dysesthesia, inform the patient to avoid exposure to cold and to avoid ingesting fresh/cold food or/and beverages during or within the hours following OXALIPLATIN INJECTION administration.
No dose adjustment is required to the 5-FU/LV regimen for neurotoxicity.
Adjuvant Stage III colon cancer:
Neurotoxicity was graded using the NCI CTC grading system (see WARNINGS AND PRECAUTIONS). For patients who experience persistent grade 2 neurotoxicity (mild or moderate objective sensory loss, moderate paresthesias), the OXALIPLATIN INJECTION dose should be reduced to 75 mg/m2. For patients with persistent grade 3 neurotoxicity, therapy should be discontinued.
Metastatic colorectal cancer: In the metastatic colorectal cancer trials, neurotoxicity was graded using a study-specific neurotoxicity scale, and dose adjustments for OXALIPLATIN INJECTION were recommended, as follows:
Table 12. Neurologic toxicity scale for oxaliplatin dose adjustments
| Toxicity (grade) | Duration of Toxicity | Persistenta Between Cycles | |||||
| 1 - 7 Days | > 7 Days | ||||||
Paresthesias/dysesthesiasb that do not interfere with function (grade 1) | No change | No change | No change | ||||
Paresthesias/dysesthesiasb interfering with function, but not activities of daily living (ADL) (grade 2) | No change | No change | 65 mg/m2 | ||||
Paresthesias/dysesthesiasb with pain or with functional impairment that also interfere with ADL (grade 3) | No change | 65 mg/m2 | Stop | ||||
Persistent paresthesias/dysesthesias that are disabling or life-threatening (grade 4) | Stop | Stop | Stop | ||||
Acute (during or after the 2 hour infusion) laryngopharyngeal dysesthesiasb | ↑ duration of next infusion to 6 hoursc | ↑ duration of next infusion to 6 hoursc | ↑ duration of next infusion to 6 hoursc | ||||
a Not resolved by the beginning of the next cycle.
b May have been cold-induced.
c May also have been pre-treated with benzodiazepines.
Renal Insufficiency: Oxaliplatin has not been studied in patients with severe renal impairment. In patients with moderate renal impairment, treatment may be initiated at the normally recommended dose and renal function should be closely monitored. Dose should be adjusted according to toxicity (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Special Populations).
Hepatic Insufficiency: No increase in oxaliplatin acute toxicities was observed in the subset of patients with abnormal liver function tests at baseline. No specific dose adjustment for patients with abnormal liver function tests was performed during clinical development.
Administration
OXALIPLATIN INJECTION is considered moderately emetogenic. Premedication with antiemetics, including 5-HT3 blockers with or without dexamethasone, is recommended.
The administration of OXALIPLATIN INJECTION does not require prehydration.
OXALIPLATIN INJECTION is administered by intravenous infusion.
OXALIPLATIN INJECTION aqueous solution must be diluted before use (see subsection Dilution Before Infusion).
OXALIPLATIN INJECTION diluted in 250 to 500 mL of 5 % glucose solution to give a concentration not less than 0.2 mg/mL must be infused via a central venous line or peripheral vein over 2 to 6 hours.
In the event of extravasation, administration must be discontinued immediately.
Instruction for use with leucovorin (as calcium folinate or disodium folinate):
OXALIPLATIN INJECTION 85 mg/m² IV infusion in 250 to 500 mL of 5% glucose solution is given at the same time as leucovorin IV infusion in 5% glucose solution, over 2 to 6 hours, using a Y-line placed immediately before infusion.
These two drugs should not be combined in the same infusion bag.
Leucovorin must not contain trometamol as an excipient and must only be diluted using isotonic
5% glucose solution, never in alkaline solutions or sodium chloride or chloride containing solutions.
For information on leucovorin, see the Product Monograph and package insert.
Instruction for use with 5-FU:
OXALIPLATIN INJECTION should always be administered before fluoropyrimidines – i.e. 5-FU.
After OXALIPLATIN INJECTION administration, flush the line and then administer 5-FU.
For information on 5-FU, see the Product Monograph and package insert.
OXALIPLATIN INJECTION AQUEOUS SOLUTION
OXALIPLATIN INJECTION aqueous solution must be diluted with 5% glucose solution before use (see the subsection Dilution Before Infusion below).
Dilution Before Infusion
Only 5% glucose infusion solution is to be used to dilute the product.
NEVER use sodium chloride or chloride containing solutions for dilution.
Inspect visually for clarity, particulate matter, precipitate, discoloration and leakage prior to use.
Only clear solutions without particles, precipitate, discoloration or leakage should be used.
The medicinal product is for single-use only. Any unused solution should be discarded.
Needles or intravenous administration sets containing aluminum parts that may come in contact with OXALIPLATIN INJECTION should not be used for the preparation or mixing of the drug. Aluminum has been reported to cause degradation of platinum compounds.
The compatibility of OXALIPLATIN INJECTION solution for infusion has been tested with representative, PVC-based, administration sets.
OXALIPLATIN INJECTION AQUEOUS SOLUTION
Withdraw the required amount of concentrate from the vial(s) and then dilute with 250 mL to 500 mL of a 5% glucose solution to give an OXALIPLATIN INJECTION concentration between not less than 0.2 mg/mL and 0.7 mg/mL (0.70 mg/mL is the highest concentration in clinical practice for an oxaliplatin dose of 85 mg/m²).
The concentration range over which the physico-chemical stability of OXALIPLATIN INJECTION has been demonstrated is 0.2 mg/mL to 2.0 mg/mL. After dilution in 5% glucose solution, chemical and physical in-use stability has been demonstrated for 24 hours at 25°C and 48 hours at 2°C to 8°C.
From a microbiological point of view, this infusion preparation should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user and would normally not be longer than 24 hours at 2°C to 8°C unless dilution has taken place in controlled and validated aseptic conditions.
Incompatibilities
- DO NOT administer undiluted.
- Only 5% glucose infusion solution is to be used to dilute the product.
- DO NOT reconstitute or dilute OXALIPLATIN INJECTION with saline or other solutions containing chloride ions (including calcium, potassium or sodium chloride).
- The diluted medicinal product should not be mixed with other medicinal products in the same infusion bag or infusion line. OXALIPLATIN INJECTION can be co-administered with leucovorin via a Y-line (see DOSAGE AND ADMINISTRATION, Administration, Instruction for use with leucovorin).
- DO NOT mix with alkaline medicinal products or solutions, in particular 5-FU, leucovorin preparations containing trometamol as an excipient and trometamol salts of others active substances. Alkaline medicinal products or solutions will adversely affect the stability of OXALIPLATIN INJECTION.
- DO NOT use injection equipment containing aluminium.
Disposal
Remnants of the medicinal product as well as all materials that have been used for reconstitution, for dilution and administration must be destroyed according to hospital standard procedures applicable to cytotoxic agents in accordance with local requirements related to the disposal of hazardous waste.
OVERDOSAGE
The approved dose of OXALIPLATIN INJECTION is 85 mg/m2 every 2 weeks in combination with 5-FU/LV (see DOSAGE AND ADMINISTRATION).
In cases of overdose, exacerbation of adverse events can be expected.
In addition to thrombocytopenia, the anticipated complications of an oxaliplatin overdose include hypersensitivity reaction, myelosuppression, nausea and vomiting, diarrhea, neurotoxicity and cardiotoxicity.
Several cases of overdoses have been reported with oxaliplatin. Adverse events observed were grade 4 thrombocytopenia (<25,000/mm3) without any bleeding, anemia, blood creatinine increased, sensory neuropathy such as paresthesia, dysesthesia, laryngospasm and facial muscle spasms, asthenia, fatigue, anxiety, dizziness, gastrointestinal disorders such as diarrhea, nausea, vomiting, stomatitis, flatulence, abdomen enlarged and grade 4 intestinal obstruction, grade 4 dehydration, dyspnea, wheezing, hypotension, chest pain, respiratory failure and severe bradycardia.
Among overdose cases, one patient was mistakenly administered oxaliplatin instead of carboplatin. The patient received a total oxaliplatin dose of 500 mg and experienced dyspnea, wheezing, paresthesia, profuse vomiting and chest pain on the day of administration. The patient developed respiratory failure and severe bradycardia, and subsequent resuscitation efforts failed.
Another patient who was mistakenly administered a 700 mg dose experienced rapid onset of dysesthesia. Inpatient supportive care was given, including hydration, electrolyte support and platelet transfusion. Recovery occurred 15 days after the overdose. The maximum dose of oxaliplatin that has been administered in a single infusion is 825 mg. The patient who received this oxaliplatin dose experienced intestinal obstruction, dehydration, nausea, flatulence and an enlarged abdomen. The treatment was discontinued and the patient recovered.
There is no known antidote for OXALIPLATIN INJECTION overdose. Patients suspected of receiving an overdose should be monitored and supportive treatment should be administered.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Oxaliplatin is a platinum-type alkylating agent. It undergoes nonenzymatic conversion in physiologic solutions to active derivatives via displacement of the labile oxalate ligand. Several transient reactive species are formed, including monoaquo and diaquo 1,2-diaminocyclohexane (DACH) platinum, which covalently bind with macromolecules. Both inter- and intrastrand Pt-DNA crosslinks are formed. Crosslinks are formed between the N7 positions of two adjacent guanines (GG), adjacent adenine-guanines (AG), and guanines separated by an intervening nucleotide (GNG). These crosslinks inhibit DNA replication and transcription leading to cytotoxic and antitumor effects.
Pharmacodynamics
The antitumor activity of oxaliplatin relevant to the proposed indication is confirmed both in vitro and in vivo in human colorectal cancer models. Oxaliplatin demonstrates in vitro cytotoxicity against HT-29, CaCo2 and HEC59 colon cancer cells. Oxaliplatin as a single agent displays only modest in vivo antitumor activity in HT-29 and DLD2 human colon cancer xenografts. Oxaliplatin is additively effective with 5-FU against human colonic tumor xenograft in vivo.
Pharmacokinetics
Absorption:
Maximum platinum concentrations in blood, plasma and plasma ultrafiltrate were reached at the end of 2-hour infusion of oxaliplatin at 85 mg/m2. Low interpatient variability in Cmax values was observed in plasma and whole blood (CV 19% and 16%, respectively). Variability in Cmax in ultrafiltrate was higher (CV 45%). Following biotransformation in vivo, the reactive products from oxaliplatin bind plasma proteins, cellular proteins and DNA. The reactive oxaliplatin derivatives are present as a fraction of the unbound platinum in plasma ultrafiltrate.
The Cmax obtained after a single 2-hour IV infusion of oxaliplatin at a dose of 85 mg/m2 expressed as ultrafilterable platinum was 0.814 μg/mL.
Interpatient and intrapatient variability in ultrafilterable platinum exposure (AUC0-48) assessed over 3 cycles was moderate to low (23% and 6%, respectively). A pharmacodynamic relationship between platinum ultrafiltrate levels and clinical safety and effectiveness has not been established.
Table 13 - Summary of Pharmacokinetic Parameters in Patients Following Single Dosing of oxaliplatin at 85 mg/m2 q2w (every two weeks)
Cmax (μg/mL) | t½α (h) | t½β (h) | t½γ (h) | AUC0-inf (μg.h/mL) | Clearance (L/h) | Volume of distribution (L) | |
Mean SD | 0.814 0.193 | 0.43 0.35 | 16.8 5.74 | 391 406 | 4.68 1.4 | 17.4 6.35 | 440 199 |
Distribution: The volume of distribution obtained after a single 2-hour IV infusion of oxaliplatin at a dose of 85 mg/m2 expressed as ultrafilterable platinum was 440 L.
At the end of a 2-hour infusion of oxaliplatin, approximately 15% of the administered platinum is present in the systemic circulation. The remaining 85% is rapidly distributed into tissues or eliminated in the urine. The relative distribution ratio of platinum between blood cells, plasma, and plasma ultrafiltrate is approximately 3.1: 3.7: 1.0.
In patients, plasma protein binding of platinum is irreversible and is greater than 90%. The main binding proteins are albumin and gamma-globulins. Platinum also binds irreversibly and accumulates (approximately 2-fold) in erythrocytes. Based on AUC values, statistically significant accumulation of platinum was observed in blood cells with a mean terminal-phase half-life of 589 ± 89.8 hrs.
No platinum accumulation was observed in plasma ultrafiltrate following 85 mg/m2 every two weeks.
Metabolism: Oxaliplatin undergoes extensive nonenzymatic biotransformation in patients and no intact drug was detectable in plasma ultrafiltrate at the end of a 2-hour infusion. There is no evidence of cytochrome P450-mediated metabolism in vitro.
Up to 17 platinum-containing derivatives have been observed in plasma ultrafiltrate samples from patients, including several cytotoxic species (monochloro DACH platinum, dichloro DACH platinum, and monoaquo and diaquo DACH platinum) and a number of noncytotoxic, conjugated species.
Excretion: The decline of ultrafilterable platinum levels following oxaliplatin administration is triphasic, characterized by two relatively short distribution phases (t1/2α: 0.43 hours and t1/2β:16.8 hours) and a long terminal elimination phase (t1/2γ: 391 hours).
The major route of platinum elimination is renal excretion. At five days after a single 2-hour infusion of oxaliplatin, urinary elimination accounted for about 54% of the platinum eliminated, with fecal excretion accounting for only about 2%. Platinum was cleared from plasma at a rate (9 – 19 L/h) that was similar to or exceeded the average human glomerular filtration rate (GFR: 7.5 L/h). The volume of distribution was high with interpatient variability of 33-45%. A significant decrease in clearance of ultrafilterable platinum from 17.6 ± 2.18 L/h to 9.95 ± 1.91 L/h in renal impairment (creatinine clearance 12 - 57 mL/min) was observed together with a statistically significant decrease in distribution volume from 330 ± 40.9 to 241 ± 36.1 L.
The renal clearance of ultrafilterable platinum is significantly correlated with GFR (see ADVERSE REACTIONS).
Special Populations and Conditions
Pediatrics: See INDICATIONS AND CLINICAL USES and WARNINGS and PRECAUTIONS, Special Populations, Pediatrics.
Geriatrics: There was no significant effect of age (26-72 years) on the clearance of ultrafilterable platinum.
Gender: There was no significant effect of gender on the clearance of ultrafilterable platinum.
Hepatic Insufficiency: Mild to moderate hepatic impairment did not affect the clearance of platinum in a clinically significant manner. No increase in oxaliplatin acute toxicities was observed in the subset of patients with abnormal liver function tests at baseline. No specific dose adjustment for patients with abnormal liver function tests was performed during clinical development (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION).
Renal Insufficiency: The primary route of platinum elimination is renal. The AUC0-48 of platinum in the plasma ultrafiltrate increases as renal function decreases. The AUC0-48 of platinum in patients with mild (creatinine clearance, CLcr 50 to 80 mL/min), moderate (CLcr 30 to < 50 mL/min) and severe (CLcr < 30 mL/min) renal impairment is increased by about 60, 140 and 190%, respectively, compared to patients with normal renal function (CLcr > 80 mL/min) (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION).
STORAGE AND STABILITY
OXALIPLATIN INJECTION AQUEOUS SOLUTION
Stored between 15°C to 25°C. Do not freeze. Protect from light.
SPECIAL HANDLING INSTRUCTIONS
As with other potentially toxic compounds, care should be exercised in the handling and preparation of OXALIPLATIN INJECTION solutions.
The handling of this cytotoxic agent by healthcare personnel requires every precaution to guarantee the protection of the handler and his surroundings. If OXALIPLATIN INJECTION concentrate or solution for infusion contacts the skin or the mucous membranes, wash immediately and thoroughly with water.
Procedures for the handling and disposal of anticancer drugs should be considered. Several guidelines on this subject have been published (see References: AMA Council Report 1985, ASHP 1990, ONS 1988 and 1999, OSHA 1986). There is no general agreement that all of the procedures recommended in the guidelines are necessary or appropriate.
DOSAGE FORMS, COMPOSITION AND PACKAGING
OXALIPLATIN INJECTION AQUEOUS SOLUTION
OXALIPLATIN INJECTION is supplied in a clear, glass, single-use vial, with bromobutyl rubber stoppers and flip-off seals, containing 50 mg, 100 mg or 200 mg of oxaliplatin as a sterile, preservative-free, aqueous solution at a concentration of 5 mg/mL. Water for Injection and lactose monohydrate are present as inactive ingredients.
The stopper used for OXALIPLATIN INJECTION is latex-free.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Oxaliplatin
Chemical name: (SP-4-2)-[(1R,2R)-Cyclohexane-1,2-diamine-kN,κN´][ethanedioato(2-)-κO1, κO2] platinum
Molecular formula: C8H14N2O4Pt
Molecular weight: 397.3 g/mol
Structural formula:
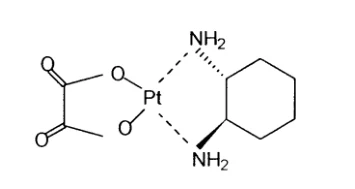
Physicochemical properties: Oxaliplatin is slightly soluble in water, very slightly soluble in methanol, and practically insoluble in ethanol.
CLINICAL TRIALS
COMBINATION ADJUVANT THERAPY WITH OXALIPLATIN AND INFUSIONAL 5-FU/LV IN PATIENTS WITH COLON CANCER.
An international, multicenter, open-label, randomized study compared the efficacy and evaluated the safety of oxaliplatin in combination with an infusional schedule of 5-FU/LV to infusional 5-FU/LV alone, in patients with stage II (Dukes’ B2) or III (Dukes’ C) colon cancer who had undergone complete resection of the primary tumor. The primary objective of the study was to compare the 3-year disease-free survival (DFS) in patients receiving oxaliplatin and infusional 5-FU/LV to those receiving 5-FU/LV alone. The secondary efficacy endpoint was overall survival (OS). Patients were to be treated for a total of 6 months (i.e., 12 cycles) (References: Andre 2004, de Gramont 2005)
A total of 2246 patients were randomized; 1123 patients per study arm. Patients in the study had to be between 18 and 75 years of age, have histologically proven stage II (T3-T4 N0 M0; Dukes’
B2) or III (any T N1-2 M0; Dukes’ C) colon carcinoma (with the inferior pole of the tumor above the peritoneal reflection, i.e., ≥ 15 cm from the anal margin) and undergone (within 7 weeks prior to randomization) complete resection of the primary tumor without gross or microscopic evidence of residual disease. Patients had to have had no prior chemotherapy, immunotherapy or radiotherapy, and have an ECOG performance status of 0, 1 or 2 (KPS ≥ 60%), absolute neutrophil count (ANC) > 1.5 x 10⁹/L, platelets ≥ 100 x 109/L, serum creatinine ≤ 1.25 x upper limit of normal (ULN) total bilirubin < 2 x ULN, AST/ALT < 2 x ULN and carcino-embryogenic antigen (CEA) < 10 ng/mL. Patients with preexisting peripheral neuropathy (NCI grade ≥ 1) were ineligible for this trial.
The following table shows the dosing regimens for the two arms of the study.
Table 14 - Dosing Regimens in Adjuvant Therapy Study
Treatment Arm | Dose | Regimen |
Oxaliplatin + 5-FU/LV FOLFOX4 (N =1123) | Day 1: Oxaliplatin: 85 mg/m2 (2-hour infusion) + LV: 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) Day 2: LV: 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) | q2w 12 cycles |
5-FU/LV (N=1123) | Day 1: LV: 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) Day 2: LV: 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) | q2w 12 cycles |
q2w: every 2 weeks
The following tables show the baseline characteristics and dosing of the patient population entered into this study. The baseline characteristics were well balanced between arms.
Table 15 - Patient Characteristics in Adjuvant Therapy Study
Oxaliplatin + 5-FU/LV N=1123 | 5-FU/LV N=1123 | |||||
| Sex: Male (%) | 56.1 | 52.4 | ||||
| Female (%) | 43.9 | 47.6 | ||||
| Median age (years) | 61.0 | 60.0 | ||||
| < 65 years of age (%) | 64.4 | 66.2 | ||||
| ≥ 65 years of age (%) | 35.6 | 33.8 | ||||
| Karnofsky Performance Status (KPS) (%) | ||||||
| 100 | 29.7 | 30.5 | ||||
| 90 | 52.2 | 53.9 | ||||
| 80 | 4.4 | 3.3 | ||||
| 70 | 13.2 | 11.9 | ||||
| ≤ 60 | 0.6 | 0.4 | ||||
| Primary site (%) | ||||||
| Colon including cecum | 54.6 | 54.4 | ||||
| Sigmoid | 31.9 | 33.8 | ||||
| Recto sigmoid | 12.9 | 10.9 | ||||
| Other including rectum | 0.6 | 0.9 | ||||
| Bowel obstruction (%) | 17.9 | 19.3 | ||||
| Perforation (%) | 6.9 | 6.9 | ||||
| Stage at Randomization | ||||||
| II (T=3,4 N=0, M=0) | 40.2 | 39.9 | ||||
| III (T=any, N=1,2, M=0) | 59.8 | 60.1 | ||||
| IV (T=any, N=any, M=1) | 0 | 0 | ||||
| Staging – T (%) | ||||||
| T1 | 0.5 | 0.7 | ||||
| T2 | 4.5 | 4.8 | ||||
| T3 | 76.0 | 75.9 | ||||
| T4 | 19.0 | 18.5 | ||||
| Staging – N (%) | ||||||
| N0 | 40.2 | 39.9 | ||||
| N1 | 39.4 | 39.4 | ||||
| N2 | 20.4 | 20.7 | ||||
| Staging –M(%) | ||||||
| M1 | 0.4 | 0.8 | ||||
Table 16 - Dosing in Adjuvant Therapy Study
oxaliplatin + 5-FU/LV N=1108 | 5-FU/LV N=1111 | |||
| Median Relative Dose Intensity (%) | ||||
| 5-FU | 84.4 | 97.7 | ||
| oxaliplatin | 80.5 | N/A | ||
| Median Number of Cycles | 12 | 12 | ||
Median Number of cycles with oxaliplatin | 11 | N/A | ||
The following tables and figures summarize the disease-free survival (DFS) and overall survival
(OS) results in the overall randomized population and in patients with stage II and III disease based on an ITT analysis.
Table 17. Summary of DFS and OS analysis
Endpoint (Median follow-up) | Overall (FOLFOX4 vs. LV5FU2) | Stage II (FOLFOX4 vs. LV5FU2) | Stage III (FOLFOX4 vs. LV5FU2) |
3 yr DFS* (35.7 months) | 78.2% vs. 72.9% HR 0.77 [0.65-0.91] p = 0.002 | 87.0% vs. 84.3% HR 0.80 [0.56-1.15] p = 0.23 | 72.2% vs. 65.3% HR 0.76 [0.62-0.92] p = 0.005 |
5 yr DFS (61.3 months) | 73.5% vs. 67.3% HR 0.78 [0.67-0.91] | 84.0% vs. 80.4% HR 0.84 [0.61-1.14] | 66.4% vs. 58.5% HR 0.76 [0.64-0.91] |
5 yr OS** (61.3 months) | 81.8% vs. 79.4% HR 0.91 [0.75-1.10] | 89.8% vs. 90.3% HR 1.10 [0.74-1.65] | 76.3% vs. 72.1% HR 0.86 [0.69-1.06] |
6 yr DFS (73.4 months) | 73.3% vs. 67.4% HR 0.80 [0.68-0.93] | 83.7% vs. 79.9% HR 0.84 [0.62-1.14] | 66.4% vs. 58.9% HR 0.78 [0.65-0.93] |
6 yr OS*** ( 81.9 months) | 78.5% vs. 75.8% HR 0.85 [0.71-1.01] | 86.8% vs. 86.8% HR 1.00 [0.70-1.43] | 72.9% vs. 68.3% HR 0.80 [0.66-0.98] |
HR: Hazard Ratio; p value based on log rank
* Protocol-planned primary efficacy endpoint
** The original protocol specified a 5 year follow-up
*** This analysis was planned after the 5 year OS analysis and shows a numerical improvement in the overall survival for stage III patients only
The 3 year DFS (protocol-planned primary efficacy endpoint) was statistically significantly improved in the oxaliplatin combination arm compared to infusional 5-FU/LV alone arm for the overall study population and stage III patients, but not in stage II patients. The DFS benefit was maintained at 5 years and 6 years (median follow-up 73.4 months). In this trial, 723 patients treated with oxaliplatin and infusional 5-FU/LV were < 65 years and 400 patients were ≥ 65 years. The effect of oxaliplatin on DFS benefit in patients ≥ 65 years of age was not conclusive.
Figure 1 shows the Kaplan-Meier DFS curves for the comparison of oxaliplatin and infusional 5-FU/LV combination and infusional 5-FU/LV alone for the overall population (ITT analysis).
Figure 1 - DFS Kaplan-Meier curves by treatment arm (Cutoff = 1 Jun 2006) – ITT population
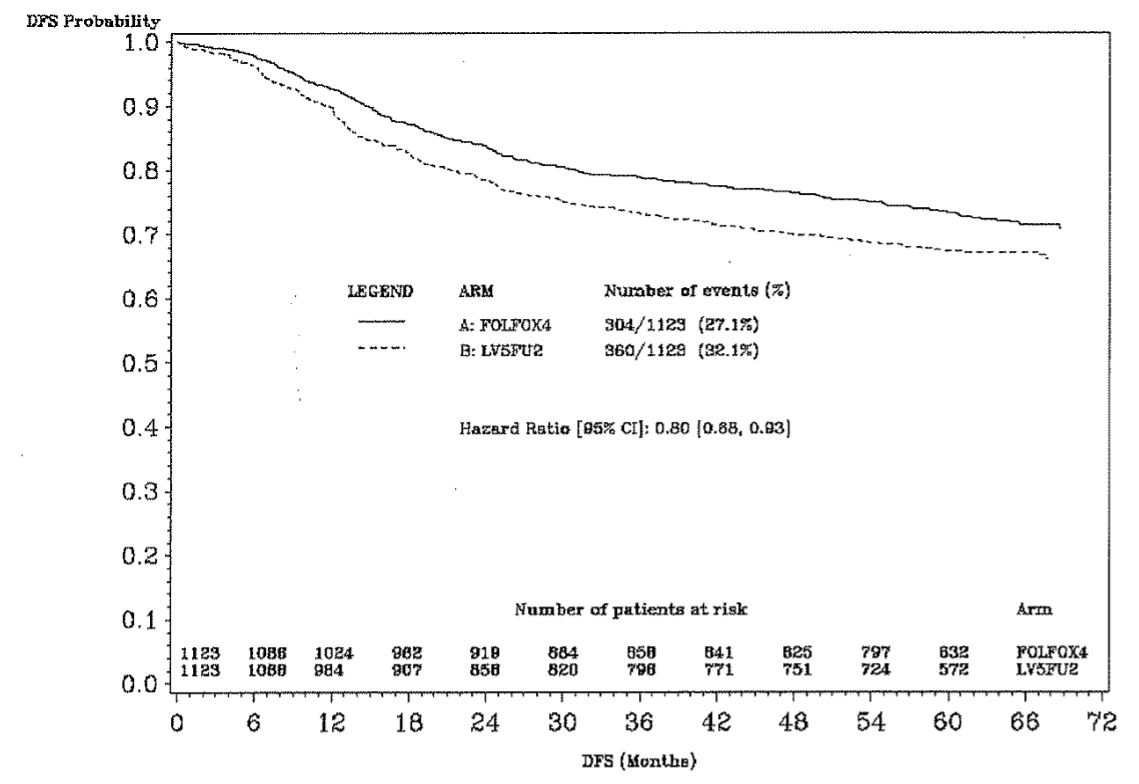
At the median follow-up 81.9 months, a numerically improved OS (secondary efficacy endpoint) was noted in stage III patients, but not in the overall study population nor in stage II patients.
Figure 2 shows the Kaplan-Meier OS curves for the comparison of oxaliplatin and infusional 5-FU/LV combination and infusional 5-FU/LV alone for the overall population (ITT analysis).
Figure 2. Kaplan-Meier OS curves for the comparison of oxaliplatin and infusional 5-FU/LV combination and infusional 5-FU/LV alone for the ITT population.
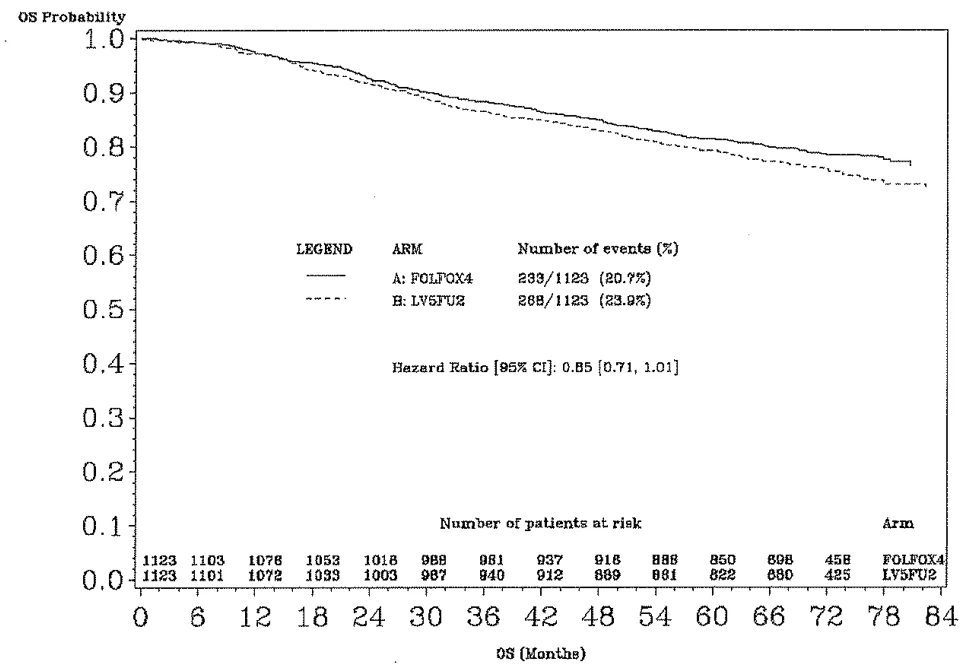
COMBINATION THERAPY WITH OXALIPLATIN AND 5-FU/LV IN PATIENTS PREVIOUSLY UNTREATED FOR METASTATIC COLORECTAL CANCER
A North American, multicenter, open-label, randomized controlled study was sponsored by the National Cancer Institute (NCI) as an intergroup study led by the North Central Cancer
Treatment Group (NCCTG). The study had 7 arms at different times during its conduct, four of which were closed due to either changes in the standard of care, toxicity, or simplification.
During the study, the control arm was changed to irinotecan plus 5-FU/LV (see references:
Goldberg 2004).
The results reported below compared the efficacy and safety of two experimental regimens, oxaliplatin in combination with infusional 5-FU/LV and a combination of oxaliplatin plus irinotecan, to an approved control regimen of irinotecan plus 5-FU/LV in 795 concurrently randomized patients previously untreated for metastatic colorectal cancer.
After completion of enrollment, the dose of irinotecan plus 5-FU/LV was decreased due to toxicity. Patients had to be at least 18 years of age, have known locally advanced, locally recurrent, or metastatic colorectal adenocarcinoma not curable by surgery or amenable to radiation therapy with curative intent, histologically proven colorectal adenocarcinoma, measurable or evaluable disease, with an Eastern Cooperative Oncology Group (ECOG) performance status 0, 1 or 2. Patients had to have granulocyte count ≥ 1.5 x 10⁹/L, platelets ≥
100 x 109/L, hemoglobin ≥ 9.0 g/dL (90 g/L), creatinine ≤ 1.5 x Upper Limit of Normal (ULN), total bilirubin ≤ 1.5 mg/dL (25 μmol/L), AST ≤ 5 x ULN and alkaline phosphatase ≤ 5 x ULN.
Patients may have received adjuvant therapy for resected Stage II or III disease without recurrence within 12 months. The patients were stratified for ECOG performance status (0, 1 vs. 2), prior adjuvant chemotherapy (yes vs. no), prior immunotherapy (yes vs. no) and age (< 65 vs. ≥ 65 years).
Although no post study treatment was specified in the protocol, 65 to 72% of patients received additional post study chemotherapy after study treatment discontinuation on all arms. Fifty-eight percent of patients on the oxaliplatin plus 5-FU/LV arm received an irinotecan-containing regimen and 23% of patients on the irinotecan plus 5-FU/LV arm received oxaliplatin-containing regimens. Oxaliplatin was not commercially available during the trial.
The following table presents the dosing regimens of the three arms of the study.
Table 18– Dosing Regimens in Patients Previously Untreated for Metastatic Colorectal Cancer Clinical Trial
Treatment Arm | Dose | Regimen |
Oxaliplatin + 5-FUL/LV FOLFOX4 (N=267) | Day 1: Oxaliplatin: 85 mg/m2 (2-hour infusion) + LV 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) Day 2: LV 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) | q2w |
Irinotecan + 5-FU/LV IFL (N=264) | Day 1: irinotecan 125 mg/m2 as a 90–min infusion + LV 20 mg/m2 as a 15-min infusion or IV push, followed by 5-FU 500 mg/m2 IV bolus weekly x 4 | q6w |
Oxaliplatin + Irinotecan IROX (N=264) | Day 1: Oxaliplatin: 85 mg/m2 IV (2-hour infusion) + irinotecan 200 mg/m2 IV over 30 minutes | q3w |
LV: leucovorin, q2w: every 2 weeks; q3w: every 3 weeks; q6w: every 6 weeks
The following table presents the demographics and dosing of the patient population entered into this study.
Table 19– Patient Demographics and Dosing in Patients Previously Untreated for Metastatic Colorectal Cancer Clinical Trial
Oxaliplatin + 5-FU/LV N=267 | Irinotecan + 5-FU/LV N=264 | Oxaliplatin + irinotecan N=264 | |
| Sex: Male (%) | 58.8 | 65.2 | 61.0 |
| Female (%) | 41.2 | 34.8 | 39.0 |
| Median age (years) | 61.0 | 61.0 | 61.0 |
| < 65 years of age (%) | 61.0 | 62.1 | 62.5 |
| ≥ 65 years of age (%) | 39.0 | 37.9 | 37.5 |
| ECOG (%) |
| 0.1 | 94.4 | 95.5 | 94.7 |
| 2 | 5.6 | 4.5 | 5.3 |
| Involved organs (%) | |||
| Colon only | 0.7 | 0.8 | 0.4 |
| Liver only | 39.3 | 44.3 | 39.0 |
| Liver + other | 41.2 | 38.6 | 40.9 |
| Lung only | 6.4 | 3.8 | 5.3 |
| Other (including lymph nodes) | 11.6 | 11.0 | 12.9 |
| Not reported | 0.7 | 1.5 | 1.5 |
| Prior radiation (%) | 3.0 | 1.5 | 3.0 |
| Prior surgery (%) | 74.5 | 79.2 | 81.8 |
| Prior adjuvant (%) | 15.7 | 14.8 | 15.2 |
The length of a treatment cycle was 2 weeks for the oxaliplatin and 5-FU/LV regimen; 6 weeks for the irinotecan plus 5-FU/LV regimen; and 3 weeks for the oxaliplatin plus irinotecan regimen. The median number of cycles administered per patient was 10 (23.9 weeks) for the oxaliplatin and 5-FU/LV regimen, 4 (23.6 weeks) for the irinotecan plus 5-FU/LV regimen, and 7 (21.0 weeks) for the oxaliplatin plus irinotecan regimen.
The primary efficacy endpoint was time to tumor progression (TTP); the secondary efficacy endpoints were overall survival (OS) and response rate (RR).
Patients treated with the oxaliplatin and 5-FU/LV combination had a significantly longer time to tumor progression (TTP) based on investigator assessment, longer overall survival (OS), and a significantly higher confirmed response rate (RR) based on investigator assessment compared to patients given irinotecan plus 5-FU/LV. The following table summarizes the efficacy results.
Table 20– Summary of Efficacy
oxaliplatin + 5-FU/LV N=267 | irinotecan + 5-FU/LV N=264 | oxaliplatin + irinotecan N=264 | |
| Overall Survival (ITT) | |||
| Number of deaths N (%) | 155 (58.1) | 192 (72.7) | 175 (66.3) |
| Median survival (months) | 19.4 | 14.6 | 17.6 |
| Hazard Ratio and (95% confidence interval) | 0.65 (0.53-0.80)* | ||
| P-value | <0.0001* | - | - |
| TTP (ITT, investigator assessment) | |||
| Percentage of progressors | 82.8 | 81.8 | 89.4 |
| Median TTP (months) | 8.7 | 6.9 | 6.5 |
| Hazard Ratio and (95% confidence interval) | 0.74 (0.61-0.89)* | ||
| P-value | 0.0014* | - | - |
| Response Rate (investigator assessment)** | |||
| Patients with measurable disease | 210 | 212 | 215 |
| Complete response N (%) | 13 (6.2) | 5 (2.4) | 7 (3.3) |
| Partial response N (%) | 82 (39.0) | 64 (30.2) | 67 (31.2) |
| Complete and partial response N (%) | 95 (45.2) | 69 (32.5) | 74 (34.4) |
| 95% confidence interval | (38.5 – 52.0) | (26.2 – 38.9) | (28.1 – 40.8) |
| P-value | 0.0075* | - | - |
ITT: Intention-To-Treat
* Compared to irinotecan plus 5-FU/LV (IFL) arm
** Based on all patients with measurable disease at baseline
The numbers in the response rate and TTP analysis are based on unblinded investigator assessment.
Figure 3 illustrates the Kaplan-Meier survival curves for the comparison of oxaliplatin and 5-FU/LV combination and oxaliplatin plus irinotecan to irinotecan plus 5-FU/LV.
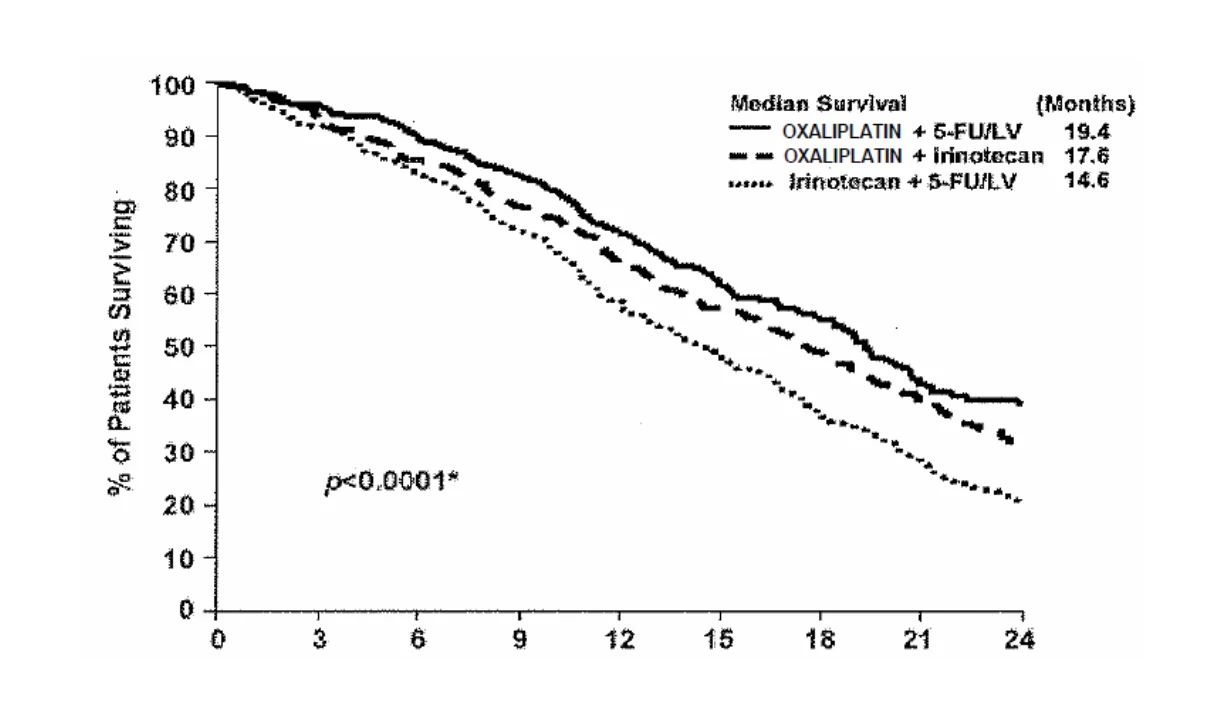
*Log rank test comparing oxaliplatin plus 5-FU/LV to irinotecan plus 5-FU/LV.
Figure 3 – Kaplan-Meier Overall Survival by treatment arm
A pre-planned subgroup analysis demonstrated that the improvement in survival for oxaliplatin plus 5-FU/LV compared to irinotecan plus 5-FU/LV appeared to be maintained across age groups, prior adjuvant therapy, and number of organs involved.
The supportive study (EFC2962) in previously untreated patients (oxaliplatin plus 5-FU/LV vs 5-FU/LV) demonstrated improvement in progression free survival (PFS) and response rate (RR), while overall survival (OS), based on unadjusted analysis, was not significantly improved with the addition of oxaliplatin. Patients treated with oxaliplatin plus 5-FU/LV experienced higher grade 3/4 events of: vomiting (5% vs. 2%); diarrhea (12% vs. 5%); and stomatitis (6% vs. 1%) compared to patients treated with 5-FU/LV (see reference: de Gramont 2000).
COMBINATION THERAPY WITH OXALIPLATIN AND 5-FU/LV IN PREVIOUSLY TREATED PATIENTS WITH METASTATIC COLORECTAL CANCER
A multicenter, open-label, randomized, three-arm controlled superiority study was conducted in the US and Canada comparing the efficacy and safety of oxaliplatin in combination with an infusional schedule of 5-FU/LV to the same dose and schedule of 5-FU/LV alone and to single agent oxaliplatin in patients with metastatic colorectal cancer. Patients had all relapsed/progressed during or within 6 months of first-line therapy with bolus 5-FU/LV and irinotecan.
The primary efficacy endpoint was overall survival. Secondary efficacy endpoints were time to tumor progression (TTP) and response rate (RR) (see References: Rothenberg 2003).
In total, 821 patients were enrolled. Patients in the study had to be at least 18 years of age, have unresectable, measurable, histologically proven colorectal adenocarcinoma, with a Karnofsky performance status ≥ 50 %. Patients had to have SGOT (AST) and SGPT (ALT) as well as alkaline phosphatase ≤ 2 x the institution’s ULN, unless liver metastases were present and documented at baseline by computed tomography (CT) or magnetic resonance imaging (MRI) scan, in which case ≤ 5 x ULN was permitted. Prior radiotherapy was permitted if it had been completed at least 3 weeks before randomization.
The dosing regimens of the three arms of the study are presented in the table below.
Table 21– Dosing Regimens in Refractory and Relapsed Colorectal Cancer Clinical Trial
| Treatment Arm | Dose | Regimen |
oxaliplatin + 5-FUL/LV (N=270) | Day 1: Oxaliplatin: 85 mg/m2 (2-hour infusion) + LV 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) Day 2: LV 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) | q2w |
5-FU/LV (N=272) | Day 1: LV 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) Day 2: LV 200 mg/m2 (2-hour infusion), followed by 5-FU: 400 mg/m2 (bolus), 600 mg/m2 (22-hour infusion) | q2w |
| oxaliplatin (N=274) | Day 1: Oxaliplatin 85 mg/m2 (2-hour infusion) | q2w |
q2w: every 2 weeks;
Patients entered into the study for evaluation of response must have had at least one unidimensional lesion measuring ≥ 20 mm using conventional CT or MRI scans, or ≥ 10 mm using a spiral CT scan. Tumor response and progression were assessed every 3 cycles (6 weeks) using the Response Evaluation Criteria in Solid Tumors (RECIST) until radiological documentation of progression or for 13 months following the first dose of study drug(s), whichever came first. Confirmed responses were based on two tumor assessments separated by at least 4 weeks.
The demographics of the patient population entered into this study are shown in the table below.
Table 22– Patient Demographics in Refractory and Relapsed Colorectal Cancer Clinical Trial
5-FU/LV (N = 272) | oxaliplatin (N = 274) | oxaliplatin + 5-FU/LV (N = 270) | |||||||
| Sex: Male (%) | 55.9 | 59.9 | 56.7 | ||||||
| Female (%) | 44.1 | 40.1 | 43.3 | ||||||
| Median age (years) | 59.0 | 59.0 | 59.0 | ||||||
| Race (%) | |||||||||
| Caucasian | 86.4 | 85.0 | 87.4 | ||||||
| 7.0 | 8.0 | 7.0 | |||||||
| Asian | 1.8 | 1.5 | 2.2 | ||||||
| Other | 4.8 | 5.5 | 3.3 | ||||||
| KPS (%) | |||||||||
| 70 – 100 | 95.6 | 96.5 | 97.4 | ||||||
| 50 – 60 | 3.0 | 3.3 | 2.6 | ||||||
| Not reported | 1.5 | 0.4 | 0.0 | ||||||
| Prior adjuvant chemotherapy (%) | 29.4 | 33.2 | 33.0 | ||||||
| If yes (%) | Adj. Saltz | 0.7 | 3.3 | 1.5 | |||||
| 5-FU only | 4.0 | 4.0 | 7.4 | ||||||
| 5-FU + LV | 21.3 | 21.5 | 20.7 | ||||||
| 5-FU + LV +other | 1.8 | 1.5 | 0.0 | ||||||
| 5-FU + other | 1.1 | 1.8 | 2.2 | ||||||
| Other | 0.4 | 1.1 | 1.1 | ||||||
| Prior radiotherapy (%) | 24.6 | 20.8 | 23.7 | ||||||
| Prior surgery for colon/rectal cancer (%) | 96.0 | 89.8 | 91.9 | ||||||
| Number of metastatic sites (%) | |||||||||
| 1 | 36.0 | 34.7 | 34.8 | ||||||
| ≥2 | 64.0 | 65.3 | 65.2 | ||||||
| Liver involvement (%) | |||||||||
| Liver only | 22.1 | 24.8 | 19.3 | ||||||
| Liver + other | 60.7 | 57.3 | 55.6 | ||||||
The median number of cycles administered per patient was 7 for the oxaliplatin and 5-FU/LV combination, 3 for 5-FU/LV alone and 4 for oxaliplatin alone.
At final analysis, when 90% of events had occurred in the ITT population, there was no statistically significant difference in the primary efficacy endpoint of overall survival between the oxaliplatin plus 5-FU/LV and the 5-FU/LV arms. Median overall survival was 9.9 months in the oxaliplatin plus 5-FU/LV arm (95% CI: 9.1-10.5) and 8.8 months in the 5-FU/LV arm (95% CI: 7.3-9.3, stratified log-rank test p = 0.09, not statistically significant). Thus, the study failed to show a statistically significant improvement in overall survival with the addition of oxaliplatin to 5-FU/LV.
Analysis of secondary efficacy endpoints demonstrated a higher response rate and longer time to tumor progression for patients treated with the combination of oxaliplatin and 5-FU/LV compared to patients treated with 5-FU/LV or oxaliplatin alone. The efficacy results are summarized in the tables below.
Table 23. Summary of Overall Survival – ITT Population (updated analysis)
5-FU/LV (N = 272) | Oxaliplatin (N = 274) | Oxaliplatin + 5-FU/LV (N = 270) | |
| Number of deaths | 252 (92.6) | 251 (91.6) | 246 (91.1) |
| Median survival (months) | 8.8 | 8.1 | 9.9 |
| (95% confidence limits) | (7.3, 9.3) | (7.2, 8.7) | (9.1, 10.5) |
Table 24- Response Rates (ITT Analysis)
5-FU/LV (N = 272) | Oxaliplatin (N = 274) | Oxaliplatin + 5-FU/LV (N = 270) | ||||||
| RR* | 2 (0.7) | 3 (1.1) | 30 (11.1) | |||||
| 95% CI | 0-2.7% | 0.2-3.2% | 7.6-15.5% | |||||
| p-valuea | 0.001 for oxaliplatin + 5-FU/LV vs. 5-FU/LV | |||||||
| CR + PR + SD, n (%) | 132 (48.5) | 127 (46.4) | 198 (73.3) | |||||
| 95% CI | 42.4-54.7 | 40.3-52.5 | 67.6-78.6 | |||||
* All responses were confirmed PRs by an independent radiologic review a P value from Fisher’s exact test.
CR: complete response; PR: partial response; SD: disease stabilization; CI: confidence interval; RR: response rate
Table 25 - Summary of Time to Progression*
| Arm | 5-FU/LV (N = 272) | oxaliplatin (N = 274) | oxaliplatin + 5-FU/LV (N = 270) | |
| No. of Progressors, n (%) | 173 (63.6) | 195 (71.2) | 164 (60.7) | |
| Median TTP (months) | 2.6 | 2.1 | 5.3 | |
| 95% CI | 1.8-2.9 | 1.6-2.7 | 4.7-6.1 | |
| p-valueb | 0.001 for oxaliplatin + 5-FU/LV vs. 5-FU/LV | |||
* Confirmed by an independent radiologic review
b P value from stratified log-rank test.
TTP: time to progression
DETAILED PHARMACOLOGY
Pharmacodynamics
In vitro studies
OXALIPLATIN AS SINGLE AGENT
Oxaliplatin as a single agent has a broad spectrum of in vitro cytotoxic/antiproliferative activity against a variety of murine and human tumor cell lines.
Oxaliplatin is a new antineoplastic drug containing the platinum atom complexed to 1,2-diaminocyclohexane (DACH) in the trans-RR conformation and an oxalate as a leaving group.
Following biotransformation in vivo, the reactive products from oxaliplatin bind plasma proteins, cellular proteins and DNA. Similar to other platinum cytotoxic agents, oxaliplatin forms DNA-Pt adducts disrupting DNA replication and transcription. However, oxaliplatin has different cytotoxic profile. Based on in vitro studies, oxaliplatin is effective against HT-29, CaCo2 and HEC59 colon tumor cell lines. Oxaliplatin also demonstrates in vitro activity against cisplatin resistant cell lines.
OXALIPLATIN IN COMBINATION
Drug combinations in vitro tumor cell cytotoxicity studies have been conducted with oxaliplatin in combination with a number of established chemotherapeutic agents.
The combination of oxaliplatin and 5-FU demonstrated synergistic cytotoxicity against CaCo2 and the 5-FU-resistant HT-29FU the colon cell lines, but not in HT-29 colonic cells. Oxaliplatin in combination with CPT-11 produced synergistic activity against HT-29 cancer cells.
In vivo antitumor activity
OXALIPLATIN AS SINGLE AGENT
Oxaliplatin as a single agent displays modest in vivo antitumor activity in human colon carcinoma models. A single dose of 45 mg/m2 oxaliplatin produces tumor growth inhibition (TGI) of 20.5% and 51.2% in HT-29 and DLD2 xenograft models, respectively.
OXALIPLATIN IN COMBINATION
In vivo studies of oxaliplatin in combination with several other agents have been conducted in a variety of tumor models and demonstrate additive and/or synergistic activity in combination with a number of anticancer drugs. In particular, oxaliplatin was additively effective with 5-FU against human colonic tumor in athymic mice. The increase in systemic toxicity was observed when 5-FU/FA was combined with oxaliplatin. The combination oxaliplatin (45 mg/m2, in saline) and CTP-11 (150 mg/m2, IV) resulted in the TGI=97.7%, compared to TGI=90% with
CTP-11 alone. A number of toxic deaths occurred with the CPT-11 plus oxaliplatin combination regimen.
Mechanism of antitumor action
Oxaliplatin undergoes nonenzymatic conversion in physiologic solutions to active derivatives via displacement of the labile oxalate ligand. Several transient reactive species are formed, including monoaquo and diaquo DACH platinum, which covalently bind with macromolecules. Both inter-and intra-strand Pt-DNA crosslinks are formed between the N7 positions of two adjacent guanines, adjacent adenine-guanines and guanines separated by an intervening nucleotide. These crosslinks inhibit DNA replication and transcription leading to cytotoxic and antitumor effects.
Pharmacokinetics
Following intravenous administration to mice (17 mg/kg or 51 mg/m2), plasma levels of total platinum initially declined within a few minutes with Cmax of 15.57 μg/mL then more slowly
(t1/2β, 0.82 h). Unbound platinum concentrations reached C max = 12.16 μg/mL, AUC0-∞ =3.27
μg.h/mL, declined rapidly with t1/2 of 6.7 min and were non-detectable after 1 hour. In red blood cells platinum levels changed little with time, most likely reflecting the extensive cellular uptake.
In male rabbits following IV injection of oxaliplatin (3.97 mg/kg or 44 mg/m2): plasma ultrafiltrate platinum declined biexponentially and was detectable for up to 60 min post-dose.
In dogs receiving 7.5 or 10 mg/kg (150 or 200 mg/m2) of oxaliplatin as a 2-hour IV infusion in 5% dextrose solution platinum exposure in PUF (AUC =11.7 μg.h/mL for 7.5 mg/kg and 14.3
μg.h/mL for 10 mg/kg) was similar to a human exposure at a dose of 130 mg/m2 (AUC = 11.9 μg.h/mL). The PUF peak platinum levels (C max =1.95 and 3.11 μg/mL) were reached at the end infusion (t max = 2 h), and then declined in a bi-phasic manner with an elimination half-life, t1/2 ~
24 hours. Higher platinum levels were detected in blood and plasma than in the PUF, and declined much more slowly. The blood plasma profiles were similar to that of plasma (t 1/2 =
115-125 h). The approved dose of oxaliplatin in humans is 85 mg/m2 every 2 weeks in combination with 5-FU/LV (see DOSAGE AND ADMINISTRATION).
Distribution
Tissue distribution studies with oxaliplatin were conducted in mice, tumor bearing rats and in rabbits. In all species tested, the highest levels of platinum were detected in the spleen, followed by the kidney and liver. In a tissue distribution study in tumor bearing rats, the actual doses of oxaliplatin following intraperitoneal (IP) administration were probably lower than indicated because of the instability of the compound in the saline vehicle. However, evidence of platinum
(Pt) uptake into colonic tumors (CC 531) could be observed.
In mice, extensive tissue distribution of Pt was observed in all tissues following a single intravenous dose of oxaliplatin (17 mg/kg), with the exception of brain, where levels were negligible. The highest levels were observed at 24 hour post-dose in the spleen (reflecting red blood cell uptake) and kidney. By 96 hour post-dose, Pt levels had declined although high levels were still present in the spleen.
Platinum from oxaliplatin was also widely distributed into tissues when administered IV to rabbits at 10 μmol/kg (3,97 mg/kg, or 44 mg/m2). The highest Pt levels from oxaliplatin were detected in the kidney and spleen. Similar to the mouse, Pt levels were not detected in the brain of rabbits administered oxaliplatin, indicating that oxaliplatin and its products either do not penetrate or are not retained in the CNS.
Metabolism
Oxaliplatin biotransformed products were studied in both in vitro and in vivo test systems. The in vitro biotransformation products of oxaliplatin were examined in rat blood. In addition, [3H]-oxaliplatin was used to determine biotransformation products in human blood and hepatic microsomes and in dog blood and urine samples. In all species oxaliplatin formed several biotransformation products when incubated in whole blood. One in vivo biotransformation study on oxaliplatin was conducted in dog following i.v. administration of a single dose of 3.6 mg/kg (72 mg/m2) of [3H]-oxaliplatin. Plasma ultrafiltrates and urine were examined for radiolabeled oxaliplatin products.
Results showed that oxaliplatin undergoes rapid nonenzymatic biotransformation, initially by displacement of the oxalate group by a variety of nucleophiles, to give a mixture of DACH, chloro, or aquo derivatives, as well as amino acid derivatives, e.g. methionine DACH platin.
Most of these biotransformed products of oxaliplatin appear to be common across all species tested. The reaction pathway via the diaquo and related derivatives is thought to produce the activated derivatives which interact with cellular DNA. In the dog, only 10% of the unchanged oxaliplatin was found in the plasma ultrafiltrate after 1.5-hour infusion. Four major biotransformation products were observed in PUF, two of which identified as monochloro DACH platin and dichloro DACH platin. At two hours post infusion most of the radioactivity in
PUF was distributed between 2 unknown components. Four major biotransformation products and at least seven minor ones were observed in the dog urine, where the free DACH was characterized as the major component.
Excretion
Renal elimination was the major route of excretion of oxaliplatin and total platinum in dogs and rabbits. Following oxaliplatin administration approximately 70% of a total dose was eliminated within 24 hours. Terminal phase of excretion was slow reflecting some irreversible binding of labeled products to cellular components. In dogs, after the IV administration of [3H]-oxaliplatin at 3.6 mg/kg (72 mg/m2), overall excretion over 7 days accounted for 76.5% with 5-6% contribution of fecal excretion. There is no data on the excretion of oxaliplatin into the milk of animals or humans.
TOXICOLOGY
Single dose studies
Rodents
The lethal dose 10% (LD10) values for oxaliplatin given as a single IV administration were in the range of 14.4 to 20 mg/kg (43.2 to 60 mg/m2) for mice and 14 mg/kg (84 mg/m2) for rats. The LD10 of the solution for which approval is being sought was estimated at 17 mg/kg (51 mg/m2).
A summary of the LD10 values determined for different formulations of oxaliplatin is presented in Table 26.
Table 26. LD10 Values across studies using different formulations
| Study | Oxaliplatin Formulation | Vehicle | Route | LD10 mg/kg | LD10 mg/m2 |
| Mouse | |||||
| TXA0551 | Lactose-containing lyophilisate | 5% glucose | IV | 16.5 | 49.5 |
| Aqueousa | 5% glucose | IV | 17.0 | 51.0 | |
| TXA0427 | Lactose-containing lyophilisate | 5% glucose | IV | 14.4 | 43.2 |
| Mannitol-containing lyophilisate | 5% glucose | IV | 14.8 | 44.4 | |
| Aqueous (bulk drug substance) | 5% glucose | IV | 16.7 | 50.1 | |
| TXA0428 | Aqueous | Sterile water | IV | 20.0 | 60.0 |
| Aqueous | Sterile water | IP | 17.5 | 52.5 | |
| Rat | |||||
| TXA0428 | Aqueous | Sterile water | IP | 14.0 | 84.0 |
| TXA0429 | Aqueous | Sterile water | IV | 18.9b | 113.4b |
a The solution formulation for which approval is being sought.
b LD05 rather than LD10 estimated
The nephrotoxicity of oxaliplatin was studied in rats given single IP doses of 0, 5.73 or 11.2 mg/kg (0, 34.4 or 67.2 mg/m2). Oxaliplatin did not increase in blood urea or relative kidney weight.
Dogs
Toxicity was evaluated in dogs administered single (IV) doses 2.5, 7.5 or 15 mg/kg (50, 150 or 300 mg/m2) oxaliplatin. Oxaliplatin caused emesis, diarrhea, and decreased food consumption, body weight gain, WBCs and RBCs. Cardiac effects were evaluated at dosages of 4, 10 or 15 mg/kg (80, 200 or 300 mg/m2). Oxaliplatin caused decreased heart rate, arrhythmias, and ECG changes, such as tachycardia, bradycardia, extrasystoles, ectopic beats, abnormal T waves and decreased ST segment. One oxaliplatin treated dog died due to ventricular fibrillation (300 mg/m2).
Cardiac and respiratory effects were investigated in anesthetized dogs administered a single dose of oxaliplatin 2.6, 13.6, or 15 mg/kg (52, 272 or 300 mg/m2). Low- and mid-dose dogs received a second dose of 6.4 mg/kg (128 mg/m2) oxaliplatin. The high dose of oxaliplatin lowered blood pH levels (acidosis). One dog experienced pulmonary and systematic arterial hypertension and respiratory arrest.
Summary single dose toxicity
- LD10 = 51 mg/m2 in mice
- LD10 = 84 mg/m2 (IP); LD05=113 mg/m2 (IV) in rats
- The doses of 70 mg/m2 and 150 mg/m2 were lethal to the monkey
- The doses ≥ 150 mg/m2 were lethal to the dog
- Cardiotoxicity: ECG changes, QT prolongation, arrhythmias (dogs, monkeys), ventricular extrasystoles, ventricular fibrillation, dose-related increase in blood pressure (dogs), ventricular fibrillation and death (dogs)
- Pulmonary and systemic arterial hypertension and respiratory arrest (dogs)
- Dyspnea
- Acidosis (dogs)
- Cachexia (monkeys)
- Hepatotoxicity: decreased relative liver weight (rats), increased AST, ALT (rats, dogs, monkeys)
- Neurotoxicity: coordination, motor activity
- Gastrointestinal system: emesis (dog) and diarrhea
- Lymphohematopoietic system: decreased WBC and RBC
Repeated dose studies
Repeated dose toxicology studies were conducted in rats and dogs using a number of different of dose schedules, cycles and doses. A summary of the studies and the main findings are presented in the table below.
Table 27. Repeat dose studies
Species of Animal/ Strain | Number Animals/ Dose Group | Route and Period of Administration | Admin. Dose or Treatment (mg/kg/day) | Results |
| Rat/SD | 25 M 25 F | i.v. Rate: 2 mL/min; Cycle: 5-day treatment followed by 16 days with no treatment; 3 cycles; Total: 63 days | 0, 0.5, 1.0 and 2.0 | Target organs included the bone marrow (decreased cellularity and decreases in WBC and RBCs) and kidney (increased blood urea nitrogen, creatinine, necrosis and degeneration of tubules). Most effects occurred at 2.0 mg/kg (12 mg/m2). |
| Dog/Beagle | 1 M 1 F | i.v. slow infusion Rate: 2 mL/min 5 daily doses | 0.75, 1.5, 2.25 and 3.0 | Significant findings included emesis and decreases in body weight and WBCs. Mortality occurred in the high dose groups. ECGs from oxaliplatin-treated dogs revealed only minor modifications (ectopic beats and decreased heart rates) except in the high dose. The high dose caused mortality after the fourth dose; ECGs showed decreased heart rate and increased ectopic beats. There was no indication of renal impairment. |
| Dog/Beagle | 1-2 M 1-2 F | i.v. Rate: 2 mL/min Cycle: single dose or 5 daily sequential doses per week followed by 3 weeks with no treatment; 1 to 6 cycles | Single dose: 0, 5, 7.5, 8.75, 10.0 and 15.0 5 daily doses: 0, 1.5 and 2.0 | Significant findings included emesis and diarrhea and decreases in WBCs and RBCs, (with recovery between cycles) and testicular weights. ECGs revealed ventricular extrasystoles and ventricular fibrillation in at least one of the dogs that died after a single dose (300 mg/m2). There was no indication of renal impairment. |
| Dog/Beagle | 3 M 3 F | i.v. Rate: 2 mL/min Cycle: 5-day treatment every 28 days; 3 cycles; Total: 84 days | 0, 0.75, 1.25 and 1.75 | Significant findings included decreases in body weights and WBCs (partial or complete recovery), testicular hypoplasia and atrophy, slight to moderate degeneration in the kidney proximal tubules, and pancreatitis. |
| Dog/Beagle | 3 M 3 F | i.v. 2-hr infusion Rate: 1 mL/min Cycle: 1-day treatment every 21 days; 3 cycles; Total: 63 days | 0, 2.5, 5.0 and 7.5 | Significant findings included emesis, myelosuppression (with recovery), testicular hypoplasia, kidney effects, and death at the dose of 150 mg/m2. ECGs appeared normal. Dogs that died had firm, rigid hearts. |
Summary of repeat dose toxicity
- Anorexia
- Gastrointestinal system: pancreatitis, emesis, and diarrhea
- Hematological toxicity: myelosuppression
- Heart: increase in heart weight, tachycardia, bradycardia, extrasystoles, ventricular fibrillation and death
- Kidney: necrosis and regeneration of proximal tubules, interstitial inflammatory reaction, increased blood urea, creatinine, proteins and blood in the urine
- Liver: elevated AST, ALT, inflammatory lesions, periportal sclerosis, stasis, periportal infiltration, bilirubin in the urine
- Local tolerance: R41 (risk of serious damage) eye irritation, focal edema and lesion
- Mammary gland hypertrophy
- Respiratory system: respiratory arrhythmia, dyspnea, moderate emphysema
- Reproductive system: decreased weight of testes and prostate, testicular hypoplasia, granulomatous interstitial prostatitis
Genetic toxicology studies
Oxaliplatin was mutagenic and clastogenic in mammalian test systems (in vitro and in vivo) and negative in the bacterial test system (Ames assay).
Reproductive toxicology and teratology studies
Oxaliplatin did not affect fertility in rats. Study findings in oxaliplatin-treated rats included a dose-related increase in embryonic deaths, decrease of foetal weight and delayed ossifications.
Fetotoxicity in rats was dose-dependent and reached up to 100% at a dose of 12 mg/m2. Thus, possible risks of miscarriage and congenital malformations exist. It is very likely that oxaliplatin is toxic to the human fetus and should be contraindicated during pregnancy.
In the male dogs administered oxaliplatin at 15 mg/m2/day x 5 days every 28 days for 3 cycles, testicular degeneration, hypoplasia and atrophy were observed. A no-effect level was not identified. This daily dose is approximately one-sixth of the recommended human dose. These findings indicate the possible reproductive and developmental toxicities of oxaliplatin in humans.
Carcinogenicity
Carcinogenicity studies have not been performed with oxaliplatin. However given that oxaliplatin is genotoxic, it should be considered a human carcinogen.
Local Tolerance
R41 (risk of serious damage) eye irritation, focal edema and irritation.
Other Toxicity Studies
Cardiac Toxicity
In cultured neonatal rat cardiac myocytes, oxaliplatin produced double beats (1 μg/mL) and reduced beats (10 μg/mL).
In dogs administered ≥ 150 mg/m2 via 2-hour IV infusion, oxaliplatin caused emesis, ventricular fibrillation, ventricular ectopic beats, increases in blood pressure and heart rate, and death. Studies with ondansetron, an antiemetic, showed that reducing emesis did not prevent ventricular fibrillation and death (150 mg/m2). The cardiotoxicity of oxaliplatin resulted in the death of 2 out of the 3 dogs after 4.5 and 9 hours post 2-hour infusion. The dose of 150 mg/m2 produced delayed ventricular repolarization (QT interval prolongation) and changes in cardiovascular safety parameters such as RR interval, PR interval, QRS duration, and heart rhythm disorders: ventricular extrasystoles and ventricular fibrillation. Thus, oxaliplatin’s cardiac toxicity threshold appeared to be lower than 150 mg/m2 in dogs.
The ECG changes of animals that died at a dose of 10 mg/kg (200 mg/m2) are described as ventricular premature depolarizations with fixed coupling preceding and evolving into ventricular fibrillation. The onset of arrhythmic activity was closely associated with death. Repolarization and conductance abnormalities were not evaluated in the in vitro cardiotoxicity (i.e., hERG and Purkinje fiber) tests. To-date, the mechanism of dose-dependent cardiotoxicity of oxaliplatin remains unknown.
In cynomologous monkeys given oxaliplatin at 6.4, 13.6, or 18.2 mg/kg (70, 150, or 200 mg/m2) via 2-hour IV infusion, the ECG abnormalities included: decrease in heart rate and increase in QT prolongation (not corrected for heart rate) 7 hours post-dose in one male and on Day 8 in one female in the 200 mg/m2 dose group; decrease in heart rate, increase in QT interval (not corrected for heart rate) on Day 7 (male) and on Day 8 (female) in the 150 mg/m2 dose group.
The post-dose ECG examinations were not performed in the 70 mg/m2 dose group. This dose is very close to the approved human dose of 85 mg/m2. Two out of six animals (dosed 70 and 150 mg/m2) died, and 3/6 sacrificed in morbid condition. Mortality was attributed to severe diarrhea and cachexia.
Summary of Cardiac Toxicity
Based on preclinical studies, oxaliplatin is cardiotoxic. In the dog, a single dose of ≥ 150 mg/m2 oxaliplatin caused serious cardiovascular reactions such as increased blood pressure, arrhythmia, ventricular ectopic events, followed by fatal ventricular fibrillation. Oxaliplatin cardiac toxicity was the most frequent cause of lethal events observed in dogs. Based on the similarities in the drug biotransformation and exposure in dogs and humans, there is a safety concern for patients treated with oxaliplatin at a dose ≥ 130 mg/m2 (see DETAILED PHARMACOLOGY). It should be anticipated that, if overdosed, oxaliplatin may possibly cause cardiac dysfunction that may lead to the death of the patient. The approved dose of oxaliplatin in humans is 85 mg/m2 every 2 weeks in combination with 5-FU/LV (see DOSAGE AND ADMINISTRATION).
Nephrotoxicity
In rats administered single IP doses of oxaliplatin (6.6 mg/kg; 39.6 mg/m2), only a slight increase in urinary enzyme excretion was observed. In rats administered IV oxaliplatin 0, 1.5, 3, and 6 mg/kg/day (0, 9, 18, and 36 mg/m2) for five consecutive days, there were decreased kidney weights and proximal tubule cell necrosis.
Myelotoxicity
The myelotoxicity of oxaliplatin was compared to cisplatin and carboplatin, in an in vitro human bone marrow stem cell assay. Myelotoxicity was ranked as follows: cisplatin > oxaliplatin > carboplatin.
Oxaliplation combination studies
Acute mouse toxicity (lethality) studies were conducted with oxaliplatin in combination with other antineoplastic agents or antiemetics. Mice were administered oxaliplatin IV at the approximate LD10 dose of 20 mg/kg (60 mg/m2), followed by an antiemetic (metoclopramide, ondansetron, or granisetron) or an antineoplastic agent (cyclophosphamide, 5-FU, methotrexate, adriamycin, or cisplatin). In general, the combinations produced a slight increase in mortality compared to oxaliplatin alone. Exceptions to this were oxaliplatin in combination with cyclophosphamide or 5-FU, which appeared to be similar or less toxic than oxaliplatin alone. In addition, the combination of oxaliplatin plus cisplatin produced a significant increase in mortality.
REFERENCES
- 1. AMA Council Report. Guidelines for Handling Parenteral Antineoplastics. JAMA 1985;253(11):1590-2.
- 2. American Society of Hospital Pharmacists Technical Assistance Bulletin on Handling. Cytotoxic and Hazardous Drugs. Am J Hosp Pharm 1990; 47(95):1033-49.
- 3. Andre T, Boni C, Mounedji-Boudiaf L, Navarro M, Tabernero J, Hickish T, et al. A Multicenter International Study of Oxaliplatin/5-Fluorouracil/Leucovorin in the Adjuvant Treatment of Colon Cancer (MOSAIC) Investigators. Oxaliplatin, fluorouracil, and leucovorin as adjuvant treatment for colon cancer. New Engl J Med. 2004;350(23):2343-51.
- 4. de Gramont A, Boni C, Navarro M, et al. Oxaliplatin/5FU/LV in the adjuvant treatment of stage II and stage III colon cancer: efficacy results with a median follow-up of 4 years. Paper presented at the 41st Annual Meeting of the American Society of Clinical Oncology; May 13–17, 2005; Orlando, Fla. Abstract 3501.
- 5. de Gramont A, Figer A, Seymour M, et al. Leucovorin and fluorouracil with or without oxaliplatin as first-line treatment in advanced colorectal cancer. J Clin Oncol 2000;18:2938-2947.
- 6. De Lemos ML, Walisser S. Management of extravasation of oxaliplatin. J Oncol Pharm Practice 2005;11:159-62.
- 7. Goldberg RM, Sargent DJ, Morton RF, Fuchs CS, Ramanathan RK, Williamson SK, et al. A randomized controlled trial of fluorouracil plus leucovorin, irinotecan, and oxaliplatin combinations in patients with previously untreated metastatic colorectal cancer. J Clin Oncol 2004;22:23-30.
- 8. Hewes JC, Dighe S, Morris RW, Hutchins RR, Bhattacharya S, Davidson BR. Preoperative chemotherapy and the outcome of liver resection for colorectal metastases. World J Surg 2007;31(2):353-64.
- 9. Oncology Nursing Society Clinical Practice Committee. Cancer Chemotherapy Guidelines. Module II - Recommendations of Nursing Practice in the Acute Care Setting. ONS 1988; 2-14.
- 10. Oncology Nursing Society Clinical Practice Committee. Cancer Chemotherapy Guidelines and Recommendations for Practice. Pittsburgh, Pa: ONS 1999:32-41.
- 11. OSHA Work-Practice Guidelines for Personnel Dealing with Cytotoxic (Antineoplastic) Drugs. Am J Hosp Pharm 1986; 43(5):1193-204.
- 12.
Pinedo D, Farheen S, Shah P. Reversible Posterior Leukoencephalopathy Syndrome
Associated with Oxaliplatin. J Clin Oncol 2007;25(33):5320-21.
- 13. Rothenberg ML, Oza AM, Begelow RH, Berlin JD, Marshall JL, Ramanathan RK, et al. Superiority of oxaliplatin and fluorouracil-leucovorin compared with either therapy alone in patients with progressive colorectal cancer after irinotecan and fluorouracil-leucovorin: interim results of a phase III trial. J Clin Oncol 2003;21:2059-69.
- 14. Rubbia-Brandt L, Audard V, Sartoretti P, Roth AD, Brezault C, Le Charpentier M, et al. Severe hepatic sinusoidal obstruction associated with oxaliplatin-based chemotherapy in patients with metastatic colorectal cancer. Annals of Oncology 2004;15(3):460-6.
- 15. Shouten van der Velden AP, Punt CJA, Van Krieken JHJ, Derleyn VA, Ruers TJM. Hepatic veno-occlusive disease after neoadjuvant treatment of colorectal liver metastases with oxaliplatin. European Journal of Surgical Oncology 2006;10:1-3.
- 16. Skelton MR, Goldberg RM, O'Neil BHA. Case of oxaliplatin-related posterior reversible encephalopathy syndrome. Clin Colorectal Cancer 2007;6(5):386-8.
- 17. Tisman G, MacDonald D, Shindell N, Reece E, Patel P, Honda N, et al. Oxaliplatin toxicity masquerading as recurrent colon cancer. Journal of Clinical Oncology 2004: 22 (15); 3202-4.
- 18. Vauthey JN, Pawlik TM, Ribero D, Wu TT, Zorzi D, Hoff PM, et al. Chemotherapy regimen predicts steatohepatitis and an increase in 90-day mortality after surgery for hepatic colorectal metastases. Journal of Clinical Oncology 2006; 24(13):2065-72.
- 19. PrELOXATIN® Product Monograph by sanofi-aventis Canada Inc. Date of Revision August 28, 2018. Control Number 216163.
I
MPOR