


Product Monograph - Panhematin
1 INDICATIONS
PANHEMATIN (hemin for injection) is indicated for the amelioration of recurrent attacks of acute intermittent porphyria temporally related to the menstrual cycle in susceptible women, after initial carbohydrate therapy is known or suspected to be inadequate.
Limitations of Use
- Before administering PANHEMATIN, consider an appropriate period of carbohydrate loading (i.e., 400 g glucose/day for 1 to 2 days) (see Dosage and Administration).
- Attacks of porphyria may progress to a point where irreversible neuronal damage has occurred. PANHEMATIN therapy is intended to prevent an attack from reaching the critical stage of neuronal degeneration. PANHEMATIN is not effective in repairing neuronal damage.
1.1 Pediatrics
Pediatrics (< 16 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of PANHEMATIN in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical data in the geriatric population is not sufficient to determine whether they respond differently from younger subjects.
2 CONTRAINDICATIONS
PANHEMATIN is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
3 DOSAGE AND ADMINISTRATION
3.1 Dosing Considerations
- PANHEMATIN should only be used by or in consultation with physicians experienced in the management of porphyrias.
Before PANHEMATIN therapy is begun, the presence of acute porphyria must be diagnosed using the following criteria:
- 1. Presence of clinical symptoms suggestive of acute porphyric attack.
- 2. Quantitative measurement of porphobilinogen (PBG) in urine. The single-void urine sample should be refrigerated or frozen without additives and shielded from light for subsequent quantitative δ-aminolevulinic acid (ALA), PBG, and total porphyrin determinations. (Note: the classical Watson-Schwartz or Hoesch tests are considered to be less reliable).
- Clinical benefit from PANHEMATIN depends on prompt administration. For mild porphyric attacks (mild pain, no vomiting, no paralysis, no hyponatremia, no seizures), a trial of glucose therapy is recommended while awaiting hemin treatment or if hemin is unavailable. For moderate to severe attacks, immediate hemin treatment is recommended. Symptoms of severe attacks are severe or prolonged pain, persistent vomiting, hyponatremia, convulsion, psychosis, and neuropathy. In addition to treatment with PANHEMATIN, consider other necessary measures such as the elimination of triggering factors.
Monitor urinary concentrations of the following compounds during PANHEMATIN therapy.
Effectiveness is demonstrated by a decrease in one or more of the following compounds.
ALA - δ-aminolevulinic acid
PBG - porphobilinogen
Uroporphyrin
Coproporphyrin
3.2 Recommended Dose and Dosage Adjustment
The dose of PANHEMATIN is 0.8 to 3.1 mg/kg/day of hematin for 3 to 14 days based on the clinical signs. The standard dose in clinical practice is 2.3 to 3.1 mg/kg/day. In more severe cases this dose may be repeated no earlier than every 12 hours. Do not exceed 4.6 mg/kg of hematin in any 24 hour period. After reconstitution each mL of PANHEMATIN contains the equivalent of approximately 5.4 mg of hematin (see dosage calculation table below).
Dosage Calculation Table
1 mg hematin equivalent = 0.18 mL PANHEMATIN 2 mg hematin equivalent = 0.37 mL PANHEMATIN 3 mg hematin equivalent = 0.55 mL PANHEMATIN 4 mg hematin equivalent = 0.74 mL PANHEMATIN
Health Canada has not authorized an indication for pediatric use.
3.3 Administration
- For intravenous infusion only.
- PANHEMATIN may be administered directly from the vial. After the first withdrawal from the vial, discard any solution remaining.
- Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Since reconstituted PANHEMATIN is not transparent, any undissolved particulate matter is difficult to see when inspected visually. Therefore, terminal filtration through a sterile 0.45 micron or smaller filter is recommended.
- Infuse the dose over a period of at least 30 minutes via a separate line.
- After the infusion, flush the vein with 100 mL of 0.9% NaCl.
3.4 Reconstitution
Parenteral Products: Reconstitute PANHEMATIN by aseptically adding 48 mL of
Sterile Water for Injection, USP, to the dispensing vial. Shake the vial well for a period of 2 to 3 minutes to aid dissolution.
Table 1 – Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration Hematin per mL |
| 268 mg | 48 mL | 48 mL | 5.4 mg/mL |
- Because PANHEMATIN contains no preservative and undergoes rapid chemical decomposition in solution, it must be reconstituted immediately before use.
- Do not add other drug or chemical agent to a PANHEMATIN fluid admixture.
4 OVERDOSAGE
Reversible renal shutdown has been observed in a case where an excessive hematin dose (12.2 mg/kg) was administered in a single infusion (see Warnings and Precautions). Treatment of this case consisted of ethacrynic acid and mannitol.
For management of a suspected drug overdose, contact your regional poison control centre.
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
PANHEMATIN is formatted as a sterile, lyophilized powder for intravenous administration after reconstitution. Each dispensing vial of PANHEMATIN contains the equivalent of 268 mg hemin, 240 mg sodium carbonate and 335 mg of sorbitol. The pH may have been adjusted with hydrochloric acid. When mixed as directed with Sterile Water for Injection, USP, each 48 mL provides the equivalent of approximately 261 mg hematin (5.4 mg/mL). The product contains no preservatives.
PANHEMATIN is supplied as a sterile, lyophilized black powder in single dose dispensing vials in a carton.
The vial stopper contains natural rubber latex.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous (IV) Infusion | Sterile Powder for Reconstitution for Injection, 268 mg/vial | Sodium carbonate and sorbitol. |
6 DESCRIPTION
PANHEMATIN (hemin for injection) is an enzyme inhibitor derived from processed red blood cells. This product is prepared from large pools of human red blood cells which may contain the causative agents of hepatitis and other viral diseases (See Warnings and Precautions).
7 WARNINGS AND PRECAUTIONS
General
There are insufficient data available for a long term use of PANHEMATIN for prevention.
Risk of Phlebitis
A large arm vein or a central venous catheter should be utilized for the administration of PANHEMATIN to minimize the risk of phlebitis.
Since reconstituted PANHEMATIN is not transparent, any undissolved particulate matter is difficult to see when inspected visually. Therefore, terminal filtration through a sterile 0.45 micron or smaller filter is recommended (see Dosage and Administration).
Transmissible Infectious Agents
Because PANHEMATIN is made from human blood, it may carry a risk of transmitting infectious agents, e.g., viruses, the variant Creutzfeldt-Jacob disease (vCJD) agent, and theoretically the Creutzfeldt-Jacob disease (CJD) agent. The risk that this product may transmit an infectious agent has been reduced by screening blood donors for prior exposure to certain viruses, by testing for the presence of certain current virus infections, and by inactivating certain viruses. Despite these measures, this product can still potentially transmit disease. There is also the possibility that unknown infectious agents may be present in the product.
All infections thought by a physician possibly to have been transmitted by this product should be reported by the physician or other healthcare provider to Recordati Rare Diseases Canada Inc. at 905-827-1300.
Carcinogenesis and Mutagenesis
See Part II: Scientific Information – Non-Clinical Toxicology.
Hematologic
Because PANHEMATIN has exhibited transient, mild anticoagulant effects during clinical studies, avoid concurrent anticoagulant therapy. The extent and duration of the hypocoagulable state induced by PANHEMATIN has not been established.
Monitoring and Laboratory Tests
Because increased levels of iron and serum ferritin have been reported in post-marketing experience, physicians must monitor iron and serum ferritin in patients receiving multiple administrations of PANHEMATIN (see Adverse Reactions). In case of elevated iron or serum ferritin levels, consider iron chelation therapy.
Renal
Recommended dosage guidelines should be strictly followed. Reversible renal shutdown has been observed in a case where an excessive hematin dose (12.2 mg/kg) was administered in a single infusion. Oliguria and increased nitrogen retention occurred although the patient
remained asymptomatic. No worsening of renal function has been seen with administration of recommended dosages of hematin.
7.1 Special Populations
7.1.1 Pregnant Women
The available human data is not sufficient to assess the risks of PANHEMATIN during pregnancy. It is also not known whether hematin can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. PANHEMATIN should be given to a pregnant woman only if clearly needed.
Avoid administering hematin in severe pre-eclampsia because of a theoretical risk of potentiation of the coagulation disorder (see Warnings and Precautions).
7.1.2 Breast-feeding
It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for PANHEMATIN and any potential adverse effects on the breastfed child from PANHEMATIN or from the underlying maternal condition.
7.1.3 Pediatrics
Pediatrics (< 16 years of age): Safety and effectiveness in pediatric patients under 16 years of age have not been established.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Clinical data for subjects aged 65 and over was not sufficient to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common adverse reactions (occurring in >1% of patients) are: headache, pyrexia, infusion site reactions, and phlebitis.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The safety of PANHEMATIN use was evaluated in a compassionate use study. A total of 130 patients were treated with hemin for acute attacks, prophylaxis or both. Of those,
111 patients were administered hemin for treatment of 305 acute porphyria attacks and to 40 patients for prophylaxis. The majority (92%) of patients were Caucasian. Most (72%) were female; all adult patients had a mean age ± SD of 40.3 ± 12.3 years. Proportionally more females (15 out of 19) received prophylaxis or a combination of acute treatment and prophylaxis (19 out of 21). For the treatment of acute attacks, patients received 2 to 4 mg/kg/day PANHEMATIN intravenously for 1 to 9 doses. For prophylaxis patients, the most common doses were weekly or biweekly infusions. Table 3 summarizes adverse reactions occurring in >1% of patients treated with PANHEMATIN, categorized by body system and order of decreasing frequency.
Table 3 – Adverse Reactions in >1% of Patients Treated with PANHEMATIN
| System Organ Class Preferred Term | ||
Adverse Events
| N (% of Total Adverse Events) | ||
| Description | Total | Possibly or Probably Related to Treatment |
| Infections and infestations | ||
| Cellulitis | 3 (1.5%) | 2 (1.0%) |
| Nervous System Disorders | ||
| Headache | 18 (9.2%) | 5 (2.6%) |
| Vascular Disorders | ||
| Phlebitis / Injection site phlebitis | 7 (3.6%) | 6 (3.1%) |
| Skin and subcutaneous tissue disorders | ||
| Rash | 3 (1.5%) | 3 (1.5%) |
| General Disorders and Administration Site Conditions | ||
| Pyrexia | 9 (4.6%) | 6 (3.1%) |
| Catheter-related Complication | 7 (3.6%) | 3 (1.5%) |
Note: In this study, the actual content of drug in the supplied vials ranged from 64.4% to 88.2% of the labelled content. Therefore, the actual amount of drug given to the patients was less than the calculated dose.
8.3 Post-Market Adverse Reactions
The following adverse reactions associated with the use of PANHEMATIN were identified in open-label clinical trials or postmarketing reports. Because these reactions were reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency reliably or to establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: thrombocytopenia, coagulopathy (including prolonged prothrombin time and prolonged partial thromboplastin time), and hemolysis
Immune System Disorders: hypersensitivity reactions including a report of infusion-related anaphylactoid reaction presenting as circulatory collapse
Vascular Disorders: injection site venous thrombosis including some that occurred in large veins such as venae cavae
General Disorders and Administration Site Conditions: infusion site reactions (such as erythema, pain, bleeding and extravasation)
Metabolism and Nutrition Disorders: iron overload and serum ferritin increased (see Warnings and Precautions)
9 DRUG INTERACTIONS
9.1 Overview
PANHEMATIN therapy is intended to limit the rate of porphyria/heme biosynthesis possibly by inhibiting the enzyme δ-aminolevulinic acid synthase 1 (ALAS1) (see Action and Clinical Pharmacology). Most of the heme synthesized in liver is used for the production of cytochrome P450 (CYP) enzymes. Therefore, avoid CYP inducing drugs (such as estrogens, barbituric acid derivatives and steroid metabolites) while on PANHEMATIN therapy, because these drugs increase the activity of ALAS leading to induction of ALAS1 through a feedback mechanism.
9.2 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.3 Drug-Food Interactions
Interactions with food have not been established.
9.4 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.5 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 ACTION AND CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Heme acts to limit the hepatic and/or marrow synthesis of porphyrin. This action is likely due to the inhibition of δ-aminolevulinic acid synthase, the enzyme which limits the rate of the porphyrin/heme biosynthetic pathway. The exact mechanism by which hematin produces symptomatic improvement in patients with acute episodes of the hepatic porphyrias has not been elucidated.
PANHEMATIN therapy for the acute porphyrias is not curative. After discontinuation of PANHEMATIN treatment, symptoms generally return although in some cases remission is prolonged. Some neurological symptoms have improved weeks to months after therapy although little or no response was noted at the time of treatment.
10.2 Pharmacokinetics
Following intravenous administration of hematin in non-jaundiced human patients, an increase
in fecal urobilinogen can be observed which is roughly proportional to the amount of hematin administered. This suggests an enterohepatic pathway as at least one route of elimination. Bilirubin metabolites are also excreted in the urine following hematin injections.
Other aspects of human pharmacokinetics have not been defined.
11 STORAGE, STABILITY AND DISPOSAL
Store lyophilized powder at 20-25°C (68-77°F).
PART II: SCIENTIFIC INFORMATION
12 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Hemin
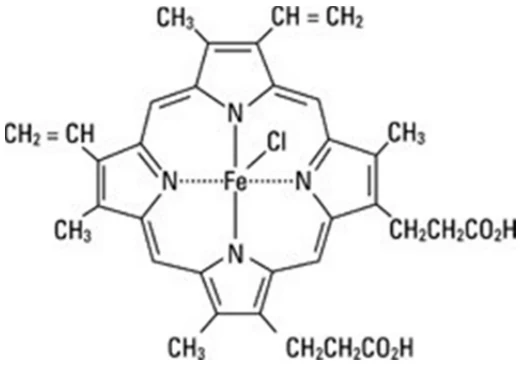
Chemical name: chloro [7,12-diethenyl-3,8,13,17-tetramethyl-21H,23H-porphine-2,18-dipropanoato(2-)-N21,N22,N23,N24] iron
Molecular formula and molecular mass: C34H32ClFeN4O4; 651.96
Structural formula:
Physicochemical properties:
Appearance: Crystalline
Color: Dark gray to black when viewed in reflected light and pale orange to brown with transmitted light
Solubilities: The drug substance is freely soluble in nitrogenous bases such as pyridine as well as in dimethylformamide, dimethylacetamide and aqueous alkaline solutions. It is slightly soluble in acidic alcohol and acetone solutions and insoluble in water and most organic solvents.
Other: The compound is not hygroscopic.
The compound exhibits strong ultraviolet and visible absorbance and can be reduced polarographically.
The compound does not melt below 300°C.
Product Characteristics
PANHEMATIN (hemin for injection) is an enzyme inhibitor derived from processed red blood cells. Hemin for injection was known previously as hematin. The term hematin has been used to describe the chemical reaction product of hemin and sodium carbonate solution. Hemin and hematin are iron containing metalloporphyrin complexes with either bound chloride or hydroxide ions, respectively.
Viral Inactivation
Table 4 is a summary of viral inactivation at three processing steps:
Table 4 – Summary of Inactivation Mechanisms
| Viral Inactivation Step # | 1 | 2 | 3 |
| Inactivation Mechanism | Acetone | Heat | Acetic Acid |
| Description | Acetone + Blood | Buffer + Heat | Acetic Acid + Hemin |
| Method of Inactivation | Organic Solvent | Heat | Acid |
13 CLINICAL TRIALS
The effectiveness of PANHEMATIN for the amelioration of recurrent attacks of acute intermittent porphyria (AIP) was evaluated in five open-label studies, one compassionate-use study, case reports, and an observational study investigating patient reported outcomes in patients with acute porphyrias.
Open-Label Studies
In the initial 5 open-label studies, 99 patients with acute porphyrias (72 with AIP) were treated with 3-4 mg/kg/day of hemin once or twice daily. Of the 99 patients in these studies, 30 received prior or concomitant glucose administration. Patients experienced a clinical response in 85.5% (141/165) of treatment courses (Figure 1). Clinical response was defined by improvement of symptoms and reduction in pain. All patients experienced a chemical response which was defined as normalization of urinary aminolevulinic acid (ALA) and porphobilinogen (PBG).
Watson et al.1 studied the use of hemin treatment in 15 patients with acute porphyrias, of whom 11 were with AIP. Seven patients were female and four were male with an age range of 19-45 years with biochemical evidence of AIP. Preparations of 4 mg/kg IV of hemin were infused at 12- or 24-hour intervals for 1 to 4 days after trials of glucose of various durations and dosages in all patients. All patients, with exception of one, experienced a clear clinical response most of which was rapid after hemin infusion. All patients also demonstrated a chemical response based on 58%-100% reduction in serum ALA and PBG levels.
Pierach et al.2 examined the use of 2 to 4 mg/kg of hemin IV in 57 patients with acute porphyrias, of whom 43 were with AIP. Out of 82 individual acute intermittent porphyria attacks with 476 hemin infusions (82 treatment courses) administered, a clinical response was seen in 74 (90%) acute attacks. A chemical response was seen for those patients who had elevated urinary ALA and PBG levels prior to hemin treatment.
McColl et al.3 reported the use of 4 mg/kg of hemin IV given either every 12 or 24 hours for three to five days in the treatment of 13 attacks of acute porphyria in eight patients. Seven of these 8 patients had AIP. Five patients with AIP were female and two were male with a mean age of 25 years (range 19-31 years). All patients had biochemical and clinical evidence of an attack of acute porphyria at the time of hemin administration. All patients had a chemical response of approximately 50% reduction in urinary ALA and PBG from pre-treatment values. In addition, clinical response was seen after hemin treatment in a total of 7 attacks in 5 AIP patients.
Lamon et al.4 reported on 12 patients with acute porphyrias, of whom 11 were with AIP. These AIP patients received 190 infusions of approximately 2 to 4 mg/kg of hemin IV given every 12 or 24 hours for 3 to 13 days as 20 separate courses of treatment, when high carbohydrate intake (300 g for a minimum of 72 hours) and supportive measures were unsuccessful. Urinary ALA and PBG levels were collected as well as clinical signs and symptoms of AIP recorded. Out of 20 treatment courses for acute attacks, there was a clinical response in 14. All patients had significant reductions in ALA and/or PBG levels after hemin treatment (p-value in the range from less than 0.001 to 0.05).
In another study by Lamon et al.5 seven patients with acute attacks of porphyria were administered 11 hemin courses (each course: 1 mg/kg every 24 hours for 3 to 13 days). Before and during hemin administration, patients were maintained on a 250-300 g/24 h carbohydrate diet. Patients had elevated urinary ALA and PBG and clinical evidence of an acute attack. Chemical response of a decrease in ALA and PBG occurred in every patient (except one PBG value in one patient) when treatment lasted 5 days or longer (p<0.001).
Figure 1 – Efficacy Data on Hemin in Acute Intermittent Porphyria from 5 Open-Label Studies
Compassionate Use Study
In the compassionate use, multi-center open-label non-comparative study6, 130 patients with a diagnosis of acute porphyria were enrolled, including 90 patients (69%) treated for acute attacks, 19 patients (15%) for prophylaxis, and 21 patients (16%) for both acute attacks and prophylaxis. Diagnostic laboratory findings reported for 69 patients were confirmatory in 26 patients. Reported abnormalities did not support the diagnosis in 20 patients (29%). ALA or PBG was reported as normal in 18 patients (26%). Seventy-two percent of the patients were female and 28% were male.
Hemin was administered to 111 patients (enrolled in the "acute attack" and the "both" treatment groups) for the treatment of 305 acute attacks and to 40 patients (enrolled in the "prophylaxis"
| Clincal Response | Chemical Response | |||||
| Yes | 85.5% | 100.0% | ||||
| No | 14.5% | 0.0% | ||||
0% 20% 40% 60% 80% 100% 120%
Clinical Response after Hemin Therapy
and the "both" treatment groups) for prophylactic treatment. Out of the 40 patients who received prophylaxis, 19 received prophylaxis only and 21 patients were treated for up to 3 acute attacks prior to receiving prophylactic treatment. Prophylaxis treatment varied greatly in frequency with the most common hemin regimen given once a week. Clinical response was achieved if the physician determined that the admitting symptoms were resolved, there was a clinically acceptable response, or the patient went into remission.
A physician-assessed clinical response was achieved for all acute attacks in 81 (73%) of 111 patients. Ninety-four patients (85%) of 111 had ≥ 1 clinical response and 17 patients (15%) of 111 had no response. Among 31 of 40 patients who received hemin prophylaxis for >1 month, 21 (68%) did not require subsequent hemin treatment for acute attacks.
Observational Patient Reported Outcomes Study
An observational study investigated patient reported outcomes in 108 patients with acute porphyrias7. Out of 108 patients, 90 patients were with AIP and reported the following:
- 55% reported having received hemin during acute attacks, and 74% of these patients assessed PANHEMATIN therapy as very successful in the treatment of abdominal pain and other symptoms.
- 50% reported having received treatment with opiates during an acute attack, and 44% of these patients reported that opiates were effective.
Hemin therapy effectiveness was assessed along with glucose infusions, high carbohydrate diets, and pain medications on a scale from zero being least effective to 10 highly effective. Hemin infusions received a 7.9, glucose infusions a 4.4 (p=0.0781), high carbohydrate diets a 4.7 (p=0.0021), and pain medications a 4.2 (p=0.0049).
14 NON-CLINICAL TOXICOLOGY
PANHEMATIN was not mutagenic in bacteria systems in vitro and was not clastogenic in mammalian systems in vitro and in vivo. No data are available on potential for carcinogenicity or impairment of fertility in animals.
15 REFERENCES
- 1. Watson CJ, Pierach CA, Bossenmaier I, Cardinal R. Use of hematin in the acute attack of the “inducible” hepatic porphyrias. Adv Intern Med. 1978;23:265-286.
- 2. Pierach CA, Bossenmaier I, Cardinal R, Weimer M, Watson CJ. Hematin therapy in porphyric attacks. Klin Wochenschr. 1980;58:829-832.
- 3. McColl KE, Moore MR, Thompson GG, Goldberg A. Treatment with haematin in acute hepatic porphyria. Q J Med. 1981;50(198):161-174.
- 4. Lamon JM, Frykholm BC, Hess RA, Tschudy DP. Hematin therapy for acute porphyria. Medicine. 1979b;58(3):252-269.
- 5. Lamon JM, Frykholm BC, Hess RA, Tschudy DP. Hematin therapy in acute porphyria. ASCI Genetics. 1977;471A.
- 6. Anderson KE, Collins S. Open-label study of hemin for acute porphyria: clinical practice
implications. Am J Med. 2006;119(9):801.e19-801.e24.
- 7. Bonkovsky HL, Maddukuri VC, Yazici C, Anderson KE, Bissell M, Bloomer JR, et al. Acute porphyrias in the USA: features of 108 subjects from porphyrias consortium. Am J Med. 2014;127:1233-1241.