


Product Monograph - Pendo-Irbesartan-HCTZ
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form/Strength | All Non-Medicinal Ingredients |
| Oral | Tablet / 300 mg/12.5 mg | Colloidal Silicon Dioxide, Copovidone, Croscarmellose Sodium, Lactose, Magnesium Stearate. The coating of the tablets contains: Hypromellose, Iron Oxide Black, Iron Oxide Red, Iron Oxide Yellow, Polyethylene Glycol, Titanium Dioxide. |
INDICATIONS AND CLINICAL USE
pendo-IRBESARTAN-HCTZ (irbesartan/hydrochlorothiazide) is indicated:
- For the treatment of essential hypertension in patients for whom combination therapy is appropriate (see DOSAGE AND ADMINISTRATION).
- As initial therapy in patients with severe essential hypertension (Sitting DBP ≥ 110 mmHg) for whom the benefit of a prompt blood pressure reduction exceeds the risk of initiating combination therapy in these patients (see CLINICAL TRIALS and DOSAGE AND ADMINISTRATION).
pendo-IRBESARTAN-HCTZ is not indicated as initial therapy in patients with mild to moderate essential hypertension.
Geriatrics (> 65 years of age): In clinical studies, no overall differences in safety or efficacy were observed between patients > 65 years of age and younger patients (See WARNINGS AND PRECAUTIONS- Special populations).
Pediatrics (< 18 years of age): The safety and efficacy of irbesartan/hydrochlorothiazide in patients < 18 years of age have not been established (See WARNINGS AND PRECAUTIONS- Special populations).
CONTRAINDICATIONS
pendo-IRBESARTAN-HCTZ is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
- Patients who are hypersensitive to other sulphonamide-derived drugs, because of the hydrochlorothiazide component.
- Patients with anuria.
- Pregnant women (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women)
- Nursing women (see WARNINGS AND PRECAUTIONS, Special Populations, Nursing Women)
- Combination with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or type 2) or moderate to severe renal impairment (GFR <60 ml/min/1.73m2) (see WARNINGS AND PRECAUTIONS, Renal - Renal Impairment, and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACE inhibitors or aliskiren containing drugs).
- Combination with angiotensin converting enzyme (ACE) inhibitors in patients with diabetic nephropathy (see WARNINGS AND PRECAUTIONS, Renal - Renal Impairment, and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACE inhibitors or aliskiren-containing drugs).
- Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption (due to lactose component of the pendo-IRBESARTAN-HCTZ tablets).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions When used in pregnancy, angiotensin receptor (AT1) blockers (ARB) can cause injury and even death of the developing fetus. When pregnancy is detected, pendo-IRBESARTAN-HCTZ should be discontinued as soon as possible (see WARNINGS AND PRECAUTIONS – Special Populations). |
General
The effect of irbesartan on the ability to drive and use machinery has not been studied, but based on its pharmacodynamic properties, irbesartan is unlikely to affect this ability. When driving vehicles or operating machinery, it should be taken into account that occasionally dizziness or weariness may occur during treatment of hypertension.
Cardiovascular
Hypotension
Occasionally, symptomatic hypotension has occurred after administration of irbesartan, in some cases after the first dose. It is more likely to occur in patients who are volume depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, or vomiting. In these patients, because of the potential fall in blood pressure, therapy should be started under close medical supervision (see DOSAGE AND ADMINISTRATION). Similar considerations apply to patients with ischemic heart or cerebrovascular disease, in whom an excessive fall in blood pressure could result in myocardial infarction or cerebrovascular accident.
Valvular Stenosis
There is concern on theoretical grounds that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Dual Blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin receptor antagonists (ARBs), such as the irbesartan component of pendo-IRBESARTAN-HCTZ, or of angiotensin converting enzyme (ACE) inhibitors with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR < 60 ml/min/1.73m2). Therefore, the use of pendo-IRBESARTAN-HCTZ in combination with aliskiren-containing drugs is contraindicated in these patients (see CONTRAINDICATIONS).
The use of pendo-IRBESARTAN-HCTZ in combination with an ACE inhibitor is contraindicated in patients with diabetic nephropathy (see CONTRAINDICATIONS).
Further, co-administration of ARBs, including the irbesartan component of pendo-IRBESARTAN-HCTZ, with other agents blocking the RAS, such as ACE inhibitors or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia.
Endocrine and Metabolism
Thiazides, including hydrochlorothiazide, can cause fluid or electrolyte imbalance (hypokalemia, hyponatremia and hypochloremic alkalosis). Periodic determination of serum electrolytes to detect possible electrolyte imbalance should be performed at appropriate intervals.
Calcium excretion is decreased by thiazides which may cause intermittent and slight elevation of serum calcium. If calcium or a calcium sparing drug (e.g., vitamin D therapy) is prescribed, serum calcium levels should be monitored and calcium dosage adjusted accordingly. Marked hypercalcemia suggests the possibility of hyperparathyroidism. Thiazides should be discontinued before carrying out tests for parathyroid function.
Thiazides have been shown to increase the urinary excretion of magnesium, which may result in hypomagnesemia.
Hyperuricemia may occur, and an acute attack of gout may be precipitated in certain patients receiving thiazide therapy.
Insulin requirements in diabetic patients may be altered and latent diabetes mellitus may become manifest during thiazide diuretic therapy.
Increases in cholesterol and triglyceride levels may be associated with thiazide diuretic therapy.
Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Hepatic/Biliary/Pancreatic
Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations in fluid and electrolyte balance may precipitate hepatic coma.
Immune
Hypersensitivity Reaction
Sensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma.
Systemic Lupus Erythematosus
Thiazide diuretics have been reported to cause exacerbation or activation of systemic lupus erythematosus.
Ophthalmic
Acute Myopia and Secondary Acute Angle-Closure Glaucoma
Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in acute transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss. The primary treatment is to discontinue drug intake as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
Renal
Azotemia
Azotemia may be precipitated or increased by hydrochlorothiazide. Cumulative effects of the drug may develop in patients with impaired renal function.
If increasing azotemia and oliguria occur during treatment of severe progressive renal impairment, the diuretic should be discontinued.
Renal Impairment
As a consequence of inhibiting the renin-angiotensin-aldosterone system (RAAS), changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the RAAS, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk.
The use of ARBs including the irbesartan component of pendo-IRBESARTAN-HCTZ or of the ACE inhibitors with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR < 60 ml/min/1.73m2). (see CONTRAINDICATIONS and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACE inhibitors, or aliskiren-containing drugs).
The use of ARBs including the irbesartan component of pendo-IRBESARTAN-HCTZ in combination with an ACE inhibitor is contraindicated in patients with diabetic nephropathy due to risk of hyperkalemia, hypotension and renal impairment (see CONTRAINDICATIONS and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS)).
Use of irbesartan should include appropriate assessment of renal function.
Thiazides should be used with caution.
Because of the hydrochlorothiazide component, pendo-IRBESARTAN-HCTZ (irbesartan/hydrochlorothiazide) is not recommended in patients with severe renal impairment (creatinine clearance ≤ 30 mL/min).
Special Populations
Pregnant Women
Drugs that act directly on the renin-angiotensin system (RAS) can cause fetal and neonatal morbidity and death when administered to pregnant women. When pregnancy is detected, pendo-IRBESARTAN-HCTZ should be discontinued as soon as possible.
The use of ARB is contraindicated during pregnancy. Epidemiological evidence regarding the risk of teratogenicity following exposure to ACE inhibitors (another class of therapeutic products interfering with the RAAS) during the first trimester of pregnancy has not been conclusive; however a small increase in risk cannot be excluded. Given the current evidence available on the risk with ARB, similar risks may exist for this class of drugs. Patients planning pregnancy should be changed to alternative anti-hypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with ARBs should be stopped immediately, and, if appropriate, alternative therapy should be started.
The use of ARBs during the second and third trimesters is known to induce human fetotoxicity (decreased renal function, oligohydramnios, skull ossification, retardation) and neonatal toxicity (renal failure, hypotension, hyperkalaemia).
Infants with histories of in utero exposure to an ARB should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion may be required as means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit. Irbesartan is not removed by hemodialysis.
Thiazides cross the placental barrier and appear in cord blood. The routine use of diuretics in otherwise healthy pregnant women is not recommended and exposes mother and fetus to unnecessary hazard, including fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults. Diuretics do not prevent development of toxemia of pregnancy and there is no satisfactory evidence that they are useful in the treatment of toxemia.
Nursing Women
It is not known whether irbesartan is excreted in human milk, but significant levels of radioactivity have been found in the milk of lactating rats. Thiazides appear in human milk. Thiazides in high doses causing intense diuresis can inhibit the milk production.
Because many drugs are excreted in human milk and because of their potential for affecting the nursing infant adversely, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
Pediatrics (< 18 years of age)
Safety and effectiveness have not been established.
Geriatrics (> 65 years of age)
Of the 2650 hypertensive patients receiving irbesartan/hydrochlorothiazide in clinical studies, 618 patients were ≥ 65 years of age. No overall age-related differences were seen in the adverse effect profile but greater sensitivity in some older individuals cannot be ruled out.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Irbesartan/hydrochlorothiazide was evaluated for safety in 2746 patients with essential hypertension including 968 patients for ≥ 1 year.
The most commonly reported adverse events (AEs) (occurring in ≥ 10% of patients treated with irbesartan/hydrochlorothiazide) was headache (11.0%), which occurred at a significantly higher incidence in the placebo group (16.1%).
The AEs most frequently resulting in clinical intervention (discontinuation of irbesartan/hydrochlorothiazide) were due to dizziness (0.7%) and headache (0.7%). The AE of hypotension is more likely to occur in volume depleted patients (see Warnings and Precautions related to Cardiovascular under Hypotension).
The following potentially serious adverse reactions have been reported rarely with irbesartan in controlled clinical trials: syncope, hypotension.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Hypertension
In placebo-controlled clinical trials, therapy was discontinued due to a clinical or laboratory AE in 3.6% of patients treated with irbesartan/hydrochlorothiazide, versus 6.8% of patients given placebo.
AEs regardless of drug relationship, occurring in ≥ 1% of the irbesartan/hydrochlorothiazide patients in placebo-controlled clinical trials include the following:
Table 1 Adverse events regardless of drug relationship, occurring in ≥1 % of the irbesartan/hydrochlorothiazide patients in placebo-controlled clinical trials
Irbesartan/ HCTZ n = 898 | Irbesartan n = 400 | HCTZ n = 380 | Placebo n = 236 | |
|---|---|---|---|---|
| (%) | (%) | (%) | (%) | |
| Cardiovascular | ||||
| Edema | 3.1 | 1.5 | 1.6 | 2.5 |
| Tachycardia | 1.2 | 0.5 | 0.5 | 0.4 |
| Dermatologic | ||||
| Rash | 1.2 | 1.8 | 3.2 | 1.7 |
| Gastrointestinal | ||||
Nausea/vomiting Dyspepsia Diarrhea Abdominal Pain | 3.2 2.1 2.1 1.7 | 1.5 0.3 2.8 1.5 | 2.4 1.6 1.1 1.6 | 0.4 0.8 3.4 0.8 |
| General | ||||
Fatigue Influenza Chest Pain | 6.5 2.8 1.8 | 4.0 2.0 1.5 | 3.2 1.8 1.6 | 3.0 1.3 1.3 |
Immunology Allergy | 1.1 | 0.5 | 0.5 | 0 |
Musculoskeletal Musculoskeletal Pain Muscle Cramp | 6.5 1.0 | 6.0 0.8 | 9.7 2.1 | 4.7 1.3 |
Nervous System Headache Dizziness Orthostatic Dizziness Anxiety / Nervousness | 11.0 7.6 1.1 1.0 | 9.3 5.5 1.0 1.0 | 11.6 4.7 0.8 0.5 | 16.1 4.2 0.4 1.7 |
Renal/Genitourinary Urination abnormal Urinary Tract Infection | 1.9 1.6 | 0.5 1.5 | 2.1 2.4 | 0.8 2.5 |
Irbesartan/ HCTZ n = 898 | Irbesartan n = 400 | HCTZ n = 380 | Placebo n = 236 |
|---|
| (%) | (%) | (%) | (%) | |
|---|---|---|---|---|
| Respiratory | ||||
| URTI | 5.6 | 8.3 | 7.1 | 5.5 |
| Sinus disorder | 2.9 | 4.5 | 3.2 | 4.7 |
| Cough | 2.2 | 2.3 | 2.6 | 3.0 |
| Pharyngitis | 2.1 | 2.3 | 2.9 | 1.7 |
| Rhinitis | 1.9 | 2.0 | 1.6 | 2.5 |
Severe Hypertension
In a clinical study in patients with severe hypertension (SeDBP ≥110 mmHg), the overall pattern of AEs reported through seven weeks of follow-up was similar in patients treated with irbesartan/hydrochlorothiazide as initial therapy and in patients treated with irbesartan as initial therapy.
Table 2 Most common adverse events regardless of drug relationship, occurring in ≥ 1% of the irbesartan/ hydrochlorothiazide patients with Severe Hypertension in controlled clinical trial
Number (%) of Subjects Irbesartan/HCTZ | Number (%) of Subjects Irbesartan | |
|---|---|---|
| N = 468 | N= 227 | |
| Headache | 19 (4.1) | 15 (6.6) |
| Dizziness | 16 (3.4) | 9 (4.0) |
| Nasopharyngitis | 8 (1.7) | 10 (4.4) |
| Bronchitis | 6 (1.3) | 6 (2.6) |
| Fatigue | 6 (1.3) | 1 (0.4) |
| Upper Respiratory Tract Infection | 6 (1.3) | 4 (1.8) |
| Erectile Dysfunction | 5 (1.1) | 0 |
| Nausea | 5 (1.1) | 5 (2.2) |
| Diarrhea | 4 (0.9) | 3 (1.3) |
| Sinusitis | 4 (0.9) | 3 (1.3) |
| Cough | 3 (0.6) | 4 (1.8) |
| Muscle Spasms | 2 (0.4) | 3 (1.3) |
The incidence of the pre-specified AEs was: 0% reported cases of syncope in either treatment group; 0.6% and 0% cases of hypotension, 3.6% and 4.0% cases of dizziness, 4.3% and 6.6% cases of headache, 0.2% and 0% cases of hyperkalemia, and 0.6% and 0.4% cases of hypokalemia reported in the group treated with irbesartan/hydrochlorothiazide and the group treated with irbesartan, respectively.
The rate of discontinuation due to AEs was 1.9% and 2.2% in the group treated with irbesartan/hydrochlorothiazide and the group treated with irbesartan, respectively.
Irbesartan Alone
In addition, the following potentially important events occurred in < 1% of patients receiving irbesartan, regardless of drug relationship:
Body as a Whole: chills, facial edema, fever, upper extremity edema;
Cardiovascular: angina pectoris, arrhythmic/conduction disorder, cardiac murmur, cardio-respiratory arrest, flushing, heart failure, hypertension, hypertensive crisis, myocardial infarction, syncope;
Dermatologic: dermatitis, ecchymosis, erythema, erythema face, photosensitivity, pruritus, urticaria;
Endocrine: gout, libido disorder, sexual dysfunction;
Gastrointestinal: abdominal distention, constipation, flatulence, gastroenteritis, hepatitis;
Musculoskeletal: arthritis, bursitis, extremity swelling, joint stiffness, muscle cramp, muscular weakness, musculoskeletal chest pain, musculoskeletal trauma, myalgia;
Nervous System: cerebrovascular accident, depression, emotional disturbances, numbness, paraesthesia, sleep disturbance, somnolence, transient ischemic attack, tremor, vertigo;
Renal/Genitourinary: abnormal urination, prostate disorder;
Respiratory: congestion, dyspnea, epistaxis, pulmonary congestion, tracheobronchitis, wheezing;
Special Senses: conjunctivitis, ear infection, ear pain, hearing impaired, taste disturbance, visual disturbance.
Hydrochlorothiazide alone
Other adverse events that have been reported with hydrochlorothiazide, without regard to causality, are listed below:
Body as a Whole: weakness;
Digestive: cramping, gastric irritation, jaundice (intrahepatic cholestatic jaundice), pancreatitis, sialadenitis;
Hematologic: agranulocytosis, aplastic anemia, hemolytic anemia, leukopenia, thrombocytopenia
Hypersensitivity: anaphylactic reactions, fever, necrotizing angiitis (vasculitis and cutaneous vasculitis), photosensitivity, purpura, respiratory distress including pneumonitis and pulmonary edema, urticaria;
Metabolic: glycosuria, hyperglycemia, hyperuricemia;
Musculoskeletal: muscle spasm;
Nervous System/Psychiatric: restlessness;
Renal: interstitial nephritis, renal dysfunction, renal failure;
Skin: erythema multiforme including Stevens-Johnson syndrome, exfoliative dermatitis including toxic epidermal necrolysis;
Special Senses: transient blurred vision, xanthopsia.
Abnormal Hematologic and Clinical Chemistry Findings
Irbesartan/hydrochlorothiazide
Liver Function Tests: Occasional elevations of liver enzymes and/or serum bilirubin have occurred. In patients with essential hypertension treated with irbesartan/hydrochlorothiazide alone, one patient was discontinued due to elevated liver enzymes.
Creatinine, Blood Urea Nitrogen: Minor increases in blood urea nitrogen (BUN) or serum creatinine were observed in 2.3% of patient. No patient was discontinued due to increased BUN. One patient was discontinued due to a minor increase in serum creatinine.
IRBESARTAN
Liver Function Tests: In placebo-controlled trials, elevations of aspartate aminotransferase (AST) and alanine transaminase (ALT) ≥ 3X upper limit of normal (ULN) occurred in 0.1% and 0.2%, respectively, of irbesartan treated patients compared to 0.3% and 0.3%, respectively, of patients receiving placebo. In patients treated with irbesartan for a mean duration of > 1 year, the cumulative incidence of AST and/or ALT elevations ≥ 3X ULN was 0.4%.
Hyperkalemia: In placebo-controlled trials, greater than a 10% increase in serum potassium was observed in 0.4% of irbesartan treated patients compared to 0.5% of patients receiving placebo.
Creatinine, Blood Urea Nitrogen: Minor increases in BUN or serum creatinine were observed in less than 0.7% of patients with essential hypertension treated with irbesartan alone versus 0.9% on placebo.
Hemoglobin: Mean decreases in hemoglobin of 0.16 g/dL were observed in patients receiving irbesartan. No patients were discontinued due to anemia.
Neutropenia: Neutropenia (<1000 cells/mm3) was observed in 0.3% of irbesartan treated patients compared to 0.5% of patients receiving placebo.
In clinical trials, the following were noted to occur with an incidence of < 1%, regardless of drug relationship: anemia, increased creatinine phosphokinase (CPK), lymphocytopenia, thrombocytopenia.
Post-Market Adverse Drug Reactions
The following adverse reactions were reported in post-marketing use:
Angioedema (involving swelling of the face, lips, and/or tongue) has been reported rarely.
Anaphylactic reactions; asthenia; elevated liver function tests; hepatobiliary disorders (acute hepatitis, cholestatic or cytolytic hepatitis); impaired renal function including cases of renal failure in patients at risk (see WARNINGS AND PRECAUTIONS – Renal - Renal Impairment); jaundice; myalgia; syncope.
Cases of muscle pain, muscle weakness, myositis and rhabdomyolysis have been reported in patients receiving angiotensin II receptor blockers.
Other adverse reactions reported with the use of hydrochlorothiazide alone include: agranulocytosis, anorexia, bone marrow depression, gastric irritation, interstitial nephritis, leucopenia, necrotizing angiitis (vasculitis, cutaneous vasculitis), pancreatitis, respiratory distress (including pneumonitis and pulmonary oedema), sialadenitis, tinnitus, toxic epidermal necrolysis, xanthopsia.
DRUG INTERACTIONS
Overview
Irbesartan does not substantially induce or inhibit the following isoenzymes: CYP 1A1, 1A2, 2A6, 2B6, 2D6, 2E1. There was no induction or inhibition of CYP 3A4.
Drug-Drug Interactions
Table 3 Established or Potential Drug-Drug Interactions
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
| Alcohol, barbiturates, or narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Agents increasing Serum Potassium | RCS | Based on experience with the use of other drugs that affect the renin-angiotensin system, concomitant use of irbesartan with potassium-sparing diuretics, potassium supplements, salt substitutes containing potassium or other potassium-raising medicinal products may lead to increases in serum potassium, sometimes severe. Such co-administration |
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
requires close monitoring of serum potassium. Concomitant thiazide diuretic use may attenuate any effect that irbesartan may have on serum potassium. | |||
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics | Monitor serum potassium level. |
| Antidiabetic agents (e.g. insulin and oral hypoglycemic agents) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
Antihypertensive drugs See also: Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACE inhibitors or aliskiren-containing drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, beta blockers, vasodilators, calcium channel blockers, diuretics, ACE inhibitors, ARB, and direct renin inhibitors). | Thiazides, including hydrochlorothiazide, can cause fluid or electrolyte imbalance (hypokalemia, hyponatremia and hypochloremic alkalosis). Periodic determination of serum electrolytes to detect possible electrolyte imbalance should be performed at appropriate intervals. |
| Antineoplastic drugs, including cyclophosphamide and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Beta-blockers | C | The hyperglycaemic effect of beta-blockers may be enhanced by thiazides. | |
| Bile acid sequestrants, e.g., cholestyramine | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothaizide by 30-35%. | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of thiazide, if necessary. |
| Calcium and vitamin D supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. If possible, another class of diuretics should be used. |
| Corticosteroids, and adrenocorticotropic hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia, may occur. | Monitor serum potassium, and adjust medications, as required. |
| Diazoxide | C | The hyperglycaemic effect of diazoxide may be enhanced by | |
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
| thiazides. | |||
| Dual Blockade of the Renin-Angiotensin- System (RAS) with ARBs, ACE inhibitors or aliskiren-containing drugs | CT | Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACE inhibitors or aliskiren-containing drugs is contraindicated in patients with diabetes and/or moderate to severe renal impairment, and is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia. Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs and ACE inhibitors is contraindicated in patients with diabetic nephropathy and is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure and hyperkalemia. | See CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin-System (RAS). |
| Digoxin | CT | When irbesartan was administered as 150 mg once daily under steady-state conditions, no effect was seen on the pharmacokinetics of digoxin at steady-state. Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin levels closely. Supplement potassium or adjust doses of digoxin or thiazide, as required. |
| Drugs that alter GI motility, i.e., anti-cholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of thiazide may be required. |
| Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RCS | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co-administration of hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Dosage adjustment of gout medications may be required. |
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high risk of lithium toxicity. As with other drugs which eliminate sodium, lithium clearance may be reduced in the presence of irbesartan. Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of irbesartan and lithium. | Concomitant use of thiazide diuretics with lithium is generally not recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor lithium levels closely. Serum lithium levels should be monitored carefully if lithium salts are to be administered with irbesartan. |
| Nonsteroidal anti-inflammatory drugs (NSAID) (including selective COX-2 inhibitors) | CT | In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with ARBs, including irbesartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. The antihypertensive effect of ARBs, including irbesartan, may be attenuated by NSAIDs including selective COX-2 inhibitors. In some patients, the administration of a non-steroidal anti-inflammatory agent can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics. | Monitor renal function periodically in patients receiving irbesartan and NSAID therapy. When pendo-IRBESARTAN-HCTZ and NSAID are used concomitantly, the patient should be observed closely to determine if the desired effect is obtained. |
| Pressor Amines (e.g., Norepinephrine) | CT | In the presence of diuretics, possible decreased response to pressor amines may be seen but not sufficient to preclude their use. | |
| Selective serotonin reuptake inhibitors (SSRIs, e.g., citalopram, escitalopram, sertraline) | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Skeletal muscle relaxants of the curare family, e.g., tubocurare | C | Thiazide drugs may increase the responsiveness of some skeletal muscle relaxants, such as curare derivatives |
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. |
| Warfarin | CT | When irbesartan was administered as 300 mg once daily under steady-state conditions, no pharmacodynamic effect on PT was demonstrated in subjects stabilized on warfarin. |
Legend: C = Case Study; RCS = Retrospective Cohort Study; CT = Clinical Trial; T =Theoretical
Drug-Food Interactions
No statistically significant effects of food were observed on the Cmax, AUC(inf) or T1/2 of irbesartan or on the AUC(inf) or T1/2 of hydrochlorothiazide. In the fasted and fed states, Tmax increased from 1 to 2 hours for irbesartan and from 1.5 to 3.5 hours for hydrochlorothiazide. The Cmax for hydrochlorothiazide decreased 21% in the fed state relative to the fasted state. None of these changes were considered to be clinically significant.
Drug-Herb Interactions
There have been no clinical studies to assess the possible interaction of any herbal products and irbesartan/hydrochlorothiazide.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Dosage must be individualized.
- The fixed combination is not for initial therapy except for severe hypertension.
- The dose of pendo-IRBESARTAN-HCTZ should be determined by the titration of the individual components.
- Use pendo-IRBESARTAN-HCTZ in patients with liver impairment is not advisable.
- Dosage adjustment may be required in hemodialysis patients (see Recommended Dose and Dosage Adjustment - Adjustment in Renal Insufficiency).
Recommended Dose and Dosage Adjustment
Once the patient has been stabilized on the individual components as described below, one tablet of irbesartan/hydrochlorothiazide 300/12.5 mg once daily may be substituted if the doses on which the patient was stabilized are the same as those in the fixed combination.
pendo-IRBESARTAN-HCTZ may be administered with or without food, however it should be taken consistently with respect to food intake.
Irbesartan Monotherapy
The recommended dose of irbesartan is 150 mg once daily. In patients whose blood pressure is not adequately controlled, the daily dose may be increased to 300 mg.
SEVERE HYPERTENSION (Sitting DBP ≥ 110 mmHg)
The starting dose of pendo-IRBESARTAN-HCTZ for initial treatment of severe hypertension is one tablet of pendo-IRBESARTAN-HCTZ 150/12.5 mg once daily (see INDICATIONS AND CLINICAL USE and CLINICAL TRIALS: Severe Hypertension). The dosage may be increased after 2 - 4 weeks of therapy to a maximum of one 300/25 mg tablet once daily. pendo-IRBESARTAN-HCTZ is not recommended as initial therapy in patients with intravascular volume depletion (see WARNINGS AND PRECAUTIONS: Hypotension).
DOSE ADJUSTMENT IN SPECIAL POPULATION
Diuretic Treated Patients
In patients receiving diuretics, irbesartan therapy should be initiated with caution, since these patients may be volume-depleted and thus more likely to experience hypotension following initiation of additional antihypertensive therapy. Whenever possible, all diuretics should be discontinued 2 - 3 days prior to the administration of irbesartan to reduce the likelihood of hypotension (see WARNINGS AND PRECAUTIONS – Cardiovascular: Hypotension, and DRUG INTERACTIONS). If this is not possible because of the patient’s condition, irbesartan should be administered with caution and the blood pressure monitored closely. The recommended starting dose of irbesartan is 75 mg once daily in hypovolemic patients (see WARNINGS AND PRECAUTIONS – Cardiovascular: Hypotension). Thereafter, the dosage should be adjusted according to the individual response of the patient.
Geriatric
No initial dosage adjustment in irbesartan is necessary for most elderly patients. Appropriate caution should nevertheless be used when prescribing to the elderly, as increased vulnerability to drug effect is possible in this patient population (see WARNINGS AND PRECAUTIONS –Special Populations Geriatrics).
Hepatic Insufficiency
No initial dosage adjustment in irbesartan is generally necessary in patients with mild to moderate hepatic impairment. Since thiazide diuretics may precipitate hepatic coma, the use of a fixed combination product such as irbesartan/hydrochlorothiazide is not advisable.
Renal Insufficiency
No initial dosage adjustment in irbesartan is generally necessary in patients with renal impairment, although due to the apparent greater sensitivity of hemodialysis patients, an initial dose of 75 mg is recommended in this group of patients.
The usual regimens of therapy with pendo-IRBESARTAN-HCTZ may be followed as long as the patient’s creatinine clearance is > 30mL/min. In patients with more severe renal impairment, loop diuretics are preferred to thiazides so pendo-IRBESARTAN-HCTZ is not recommended.
Missed Dose
Patients should be instructed to take pendo-IRBESARTAN-HCTZ at the next scheduled dose and not take two doses at the same time if they miss a dose.
OVERDOSAGE
No specific information is available on the treatment of overdosage with irbesartan/hydrochlorothiazide. The patient should be closely monitored, and the treatment should be symptomatic and supportive, including fluid and electrolyte replacement.
Irbesartan
No data or very little data available in regard to overdosage in humans.
The most likely manifestations of overdosage would be hypotension and/or tachycardia; bradycardia might also occur in this setting. Irbesartan is not removed by hemodialysis.
Hydrochlorothiazide
The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias.
The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
pendo-IRBESARTAN-HCTZ (irbesartan/hydrochlorothiazide) combines the actions of irbesartan, an angiotensin II AT1 receptor blocker (ARB), and that of a thiazide diuretic, hydrochlorothiazide.
Irbesartan
Irbesartan antagonizes angiotensin II by blocking AT1 receptors.
Angiotensin II is the primary vasoactive hormone in the renin-angiotensin system (RAS). Its effects include vasoconstriction and the stimulation of aldosterone secretion by the adrenal cortex.
Irbesartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking in a non-competitive manner the binding of angiotensin II to the AT1 receptor found in many tissues. Irbesartan has no agonist activity at the AT1 receptor. AT2 receptors have been found in many tissues, but to date they have not been associated with cardiovascular homeostasis. Irbesartan has essentially no affinity for the AT2 receptors.
Irbesartan does not inhibit ACE, also known as kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin, nor does it affect renin or other hormone receptors or ion channels involved in cardiovascular regulation of blood pressure and sodium homeostasis.
Hydrochlorothiazide
Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an ARB tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is not fully understood.
Pharmacodynamics
Irbesartan
In healthy subjects, single oral doses of irbesartan ≤ 300 mg produced dose-dependent inhibition of the pressor effect of angiotensin II infusions. The inhibition was complete (100%) 4 hours following oral doses of 150 mg or 300 mg. Partial inhibition of 40% and 60% was still present 24 hours post-dose with 150 mg and 300 mg irbesartan respectively.
In hypertensive patients, angiotensin II receptor inhibition following chronic administration of irbesartan caused a 1.5-2 fold rise in angiotensin II plasma concentration and a 2-3 fold increase in plasma renin levels. Aldosterone plasma concentrations generally declined following irbesartan administration, however serum potassium levels were not significantly affected at recommended doses.
During clinical trials, minimal incremental blood pressure response was observed at doses > 300 mg.
The blood pressure lowering effect of irbesartan was apparent after the first dose and substantially present within 1-2 weeks, with the maximal effect occurring by 4-6 weeks. In long-term studies, the effect of irbesartan appeared to be maintained for more than one year. There was essentially no change in average heart rate in patients treated with irbesartan in controlled trials.
There was no rebound effect after withdrawal of irbesartan.
Black hypertensive patients had a smaller blood pressure response to irbesartan monotherapy than caucasians.
There was no significant difference in blood pressure response based on age and gender.
Hydrochlorothiazide
Onset of the diuretic action following oral administration occurred in 2 hours and the peak action in about 4 hours. Diuretic activity lasts about 6 - 12 hours.
Irbesartan/Hydrochlorothiazide
The components of irbesartan/hydrochlorothiazide were shown to have an additive effect on blood pressure reduction, reducing blood pressure to a greater degree than either component alone.
The blood pressure lowering effect of irbesartan in combination with hydrochlorothiazide was apparent after the first dose and substantially present within 1-2 weeks, with the maximal effect occurring by 6-8 weeks. In long-term follow-up studies, the effect of irbesartan/hydrochlorothiazide was maintained for >1 year.
Pharmacokinetics
Table 4 Pharmacokinetic Parameters for Irbersartan
| Irbesartan | Tmax (h) | t½ (h) | Clearance (mL/minute) | Volume of distribution (L) |
| Single dose mean | 1.5-2 | 11-15 | Plasma 157 -176 Renal 3.0 – 3.5 | 53 -93 |
Table 5 Pharmacokinetic Parameters for hydrochlorothiazide
| Hydrochlorothiazide | Tmax (h) | t½ (h) | Clearance (mL/minute) | Volume of distribution (L/kg) |
| Single dose mean | 1.5-2 | 5-15 | Plasma 192-343 Predominantly Renal (unchanged) | 1.5-4.2 |
Irbesartan
Absorption
Irbesartan is an orally active agent. The oral absorption of irbesartan is rapid and complete with an average absolute bioavailability of 60% - 80%. Following oral administration, peak plasma concentrations are attained at 1.5-2 hours after dosing. Steady-state concentrations are achieved within 3 days.
Distribution
The average volume of distribution of irbesartan is 53-93 litres.
Irbesartan is approximately 96% protein-bound in the plasma, primarily to albumin and α1-acid glycoprotein.
Metabolism
Irbesartan is metabolized via glucuronide conjugation and oxidation by the cytochrome P-450 system.
Excretion
Irbesartan and its metabolites are excreted by both biliary and renal routes. Following either oral or intravenous administration of 14C-labeled irbesartan, about 20% of radioactivity is recovered in the urine and the remainder in the feces. Less than 2% of the dose is excreted in urine as unchanged irbesartan. Irbesartan exhibits linear pharmacokinetics over the therapeutic dose range with an average terminal elimination half-life of 11-15 hours.
Total plasma and renal clearances are in the range of 157 - 176 and 3.0 - 3.5 mL/minute, respectively.
Hydrochlorothiazide
Absorption
Hydrochlorothiazide is rapidly absorbed from the gastrointestinal tract. The bioavailability is approximately 65% - 70%.
Distribution
Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk.
Metabolism
Hydrochlorothiazide is not metabolized.
Excretion
Hydrochlorothiazide is eliminated rapidly by the kidney. At least 61% of the oral dose is eliminated unchanged within 24 hours. The plasma half life has been observed to vary from 5.6 and 14.8 hours.
Special Populations and Conditions
Geriatrics
In subjects > 65 years old, irbesartan elimination half-life was not significantly altered, but AUC and Cmax values were about 20% - 50% greater than those of young subjects.
Renal Insufficiency
The mean AUC and Cmax of irbesartan were not altered in patients with any degree of renal impairment, including patients on hemodialysis. However, a wide variance was seen in patients with severe renal impairment.
Hepatic Insufficiency
The pharmacokinetics of irbesartan following repeated oral administration were not significantly affected in patients with mild to moderate cirrhosis of the liver. No data is available in patients with severe liver disease.
STORAGE AND STABILITY
Store between 15°C and 30°C.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Tablets
300 mg/12.5 mg: Each peach, biconvex, coated tablet debossed with “P” on one side and “300-12.5” on the other side, contains 300 mg of irbesartan, 12.5 mg of hydrochlorothiazide, and the following non-medicinal ingredients: Colloidal Silicon Dioxide, Copovidone,Croscarmellose Sodium, Lactose, Magnesium Stearate. The coating contains: Hypromellose, Iron Oxide Black, Iron Oxide Yellow, Iron Oxide Red, Polyethylene Glycol, Titanium Dioxide. Available in HDPE bottles of 100 tablets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: irbesartan/hydrochlorothiazide
| Irbesartan | Hydrochlorothiazide | |
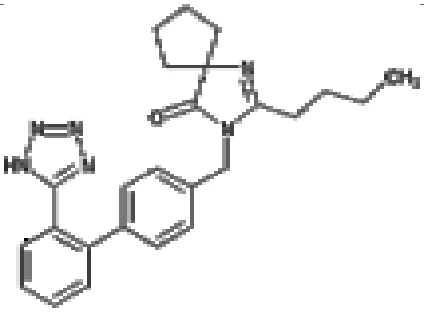
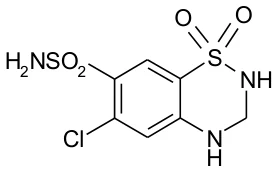
| Chemical Name | 2-butyl-3-[(21-(1H-tetrazol-5- yl) biphenyl-4-yl)methyl]-1,3- diazaspiro [4,4] non-1-en-4-one. | 6-chloro-3,4-dihydro-2H-1,2,4-benzo- thiadiazine-7-sulfonamide 1,1-dioxide |
| Molecular Formula | C25H28N6O | C7H8ClN3O4S2 |
| Structural Formula | ||
| Molecular Weight | 428.53 g/mol | 297.72 g/mol |
Physicochemical Properties | Irbesartan is a white to off-white crystalline powder. It is a nonpolar compound with a partition coefficient (octanol/water) of 10.1 at a pH of 7.4. Irbesartan is slightly soluble in alcohol and methylene chloride and practically insoluble in water. | Hydrochlorothiazide is a white, or practically white, crystalline powder. Hydrochlorothiazide is slightly soluble in water and freely soluble in sodium hydroxide solution. |
CLINICAL TRIALS
Comparative Bioavailability Study
A single-dose, crossover comparative bioavailability study was conducted in healthy male volunteers (n=26) under fasting conditions comparing irbesartan/hydrochlorothiazide 300 mg/25 mg tablets (PENDOPHARM, Division of Pharmascience Inc.) to AVALIDE® (irbesartan/hydrochlorothiazide) 300 mg/25 mg tablets (Sanofi-Aventis Canada Inc.). A summary of the pharmacokinetic data is presented in the following tables.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA IRBESARTAN
Irbesartan (1 x 300mg/25mg Irbesartan/Hydrochlorothiazide Tablet) From measured data Geometric Mean+ Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means+ | Confidence Interval (90%)+ |
AUCT (ng·h/mL) | 20144.5 20953.4 (29.5) | 19543.1 20593.4 (32.9) | 103.08 | 98.67-107.68 |
AUCI (ng·h/mL) | 21817.2 22573.6 (29.7) | 21792.4 22726.2 (32.3) | 100.11 | 95.13-105.36 |
Cmax (ng/mL) | 3845.6 3989.4 (30.4) | 3425.4 3528.2 (29.2) | 112.27 | 106.98-117.81 |
Tmax§ (h) | 1.25 (0.500 – 5.00) | 1.25 (0.500 – 5.00) | ||
T½€ (h) | 10.34 (27.4) | 13.39 (39.2) | ||
*irbesartan/hydrochlorothiazide, PENDOPHARM, Division of Pharmascience Inc., Montréal, Canada
†Avalide® Tablets (Sanofi-Aventis Canada Inc.) were purchased in Canada
§ Expressed as the median (range)
€ Expressed as the arithmetic mean (CV%)
+ Based on least squares estimates
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA HYDROCHOROTHIAZIDE
Hydrochlorothiazide (1 x 300mg/25mg Irbesartan/Hydrochlorothiazide Tablet) From measured data Geometric Mean+ Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means+ | Confidence Interval (90%)+ |
AUCT (ng·h/mL) | 889.01 917.76 (24.5) | 873.99 903.72 (25.3) | 101.72 | 97.24-106.40 |
AUCI (ng·h/mL) | 1000.38 1029.70 (24.1) | 978.90 (1006.75 (23.5) | 102.19 | 98.07-106.49 |
Cmax (ng/mL) | 146.83 157.00 (38.7) | 145.52 153.24 (35.5) | 100.90 | 92.17-110.45 |
Tmax§ (h) | 1.75 (1.00 – 3.00) | 1.75 (1.00 – 3.00) | ||
T½€ (h) | 10.28 (15.7) | 10.20 (17.3) | ||
*irbesartan/hydrochlorothiazide, PENDOPHARM, Division of Pharmascience Inc., Montréal, Canada
†Avalide® Tablets (Sanofi-Aventis Canada Inc.) were purchased in Canada
§ Expressed as the median (range)
€ Expressed as the arithmetic mean (CV%)
+ Based on least squares estimates
Irbesartan-Hydrochlorothiazide
The antihypertensive effects of irbesartan/hydrochlorothiazide tablets were examined in 4 placebo-controlled studies of 8–12 weeks in patients with mild-moderate hypertension. These trials included 1914 patients randomized to fixed doses of irbesartan (37.5 to 300 mg) and concomitant hydrochlorothiazide (6.25 to 25 mg). One factorial study compared all combinations of irbesartan (37.5, 100 and 300 mg or placebo) and hydrochlorothiazide (6.25, 12.5, and 25 mg or placebo). The irbesartan/hydrochlorothiazide combinations of 75/12.5 mg and 150/12.5 mg were compared to their individual components and placebo in a separate study. A third study investigated the ambulatory blood pressure responses to irbesartan-hydrochlorothiazide (75/12.5 mg and 150/12.5 mg) and placebo after 8 weeks of dosing. Another trial investigated the effects of the addition of irbesartan (75 mg) in patients not controlled on hydrochlorothiazide (25 mg) alone.
In controlled trials, the addition of irbesartan 150–300 mg to hydrochlorothiazide doses of 6.25, 12.5 or 25 mg produced further dose-related reductions in blood pressure of 8–10/3–6 mmHg, comparable to those achieved with the same monotherapy dose of irbesartan. The addition of hydrochlorothiazide to irbesartan produced further dose related reductions in blood pressure at trough (24 hours post-dose) of 5–6/2–3 mmHg (12.5 mg) and 7–11/4–5 mmHg (25 mg), also comparable to effects achieved with hydrochlorothiazide alone. Once-daily dosing with 150 mg irbesartan and 12.5 mg hydrochlorothiazide, 300 mg irbesartan and 12.5 mg hydrochlorothiazide, or 300 mg irbesartan and 25 mg hydrochlorothiazide produced mean placebo-adjusted blood pressure reductions at trough (24 hours post-dosing) of about 13–15/7–9, 14/9–12, and 19–21/11–12 mmHg, respectively. Peak effects occurred at 3–6 hours, with the trough-to peak ratios >65%.
In another study, irbesartan (75–150 mg) or placebo was added on a background of 25 mg hydrochlorothiazide in patients not adequately controlled (SeDBP 93–120 mmHg) on hydrochlorothiazide (25 mg) alone. The addition of irbesartan (75–150 mg) gave an additive effect (systolic/diastolic) at trough (24 hours post-dosing) of 11/7 mmHg.
There was no difference in response for men and women or in patients over or under 65 years of age. Black patients had a larger response to hydrochlorothiazide than non-black patients and a smaller response to irbesartan. The overall response to the combination was similar for black and non-black patients.
Severe Hypertension
The efficacy of irbesartan/hydrochlorothiazide as initial therapy for severe hypertension (defined as a mean seated diastolic blood pressure (SeDBP) ≥110 mmHg confirmed on 2 separate occasions off all antihypertensive therapy) was studied in a 7-week, double-blind, randomized, multicenter study. Patients were randomized to either irbesartan and hydrochlorothiazide (150/12.5 mg) or to irbesartan (150 mg) once daily and followed for blood pressure response. These initial study regimens were increased at 1 week to irbesartan 300 mg/HCTZ 25 mg or to irbesartan 300 mg, respectively. The primary endpoint was a comparison at 5 weeks of the proportion of patients who achieved through SeDBP <90 mmHg. An additional supportive endpoint compared the proportion of subjects in each treatment group whose blood pressure was controlled, defined as simultaneous SeDBP <90 mmHg and SeSBP <140 mmHg.
Study demographics and trial design
The study randomized 697 patients, in a 2:1 ratio to receive either combination therapy (irbesartan plus HCTZ, N=468) or irbesartan monotherapy (N=229), and included 296 (42%) females, 101 (14%) blacks, and 92 (13%) ≥65 years of age. The mean age was 52 years. The mean blood pressure at baseline for the total population was 172/113 mmHg.
Table 6 Summary of patient demographics for clinical trial with irbesartan/hydrochlorothiazide in subjects with severe hypertension
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age in years (Range) | Gender |
| CV131176 | Multicenter, randomized, double-blind, active controlled , 7-week, parallel group study | Oral administration of irbesartan /HCTZ 150/12.5 mg or irbesartan 150 mg increased at 1 week to irbesartan /HCTZ 300/25 mg or to irbesartan 300 mg. | 697 Irbesartan: 229 Irbesartan/HCTZ: 468 | 52.5 (23.0 - 83.0) | Male 57.5% Female 42.5% |
Study results
The study results are summarized in table 7.
After 5 weeks of therapy, the mean SeDBP was 4.7 mmHg lower (p≤0.0001) and the mean SeSBP was 9.7 mmHg lower (p<0.0001) in the group treated with irbesartan/hydrochlorothiazide than in the group treated with irbesartan. Mean reductions from baseline for SeDBP and SeSBP at trough were 24.0 mmHg and 30.8 mmHg for irbesartan/hydrochlorothiazide-treated patients and 19.3 mmHg and 21.1 mmHg for irbesartan-treated patients, respectively. A greater proportion of patients on irbesartan/hydrochlorothiazide achieved a diastolic blood pressure <90 mmHg (47.2% for irbesartan/hydrochlorothiazide, 33.2% for irbesartan; p=0.0005) and a greater proportion of the patients on irbesartan/hydrochlorothiazide achieved simultaneous control of SeSBP <140 mmHg and SeDBP <90 mmHg (34.6% versus 19.2%; p<0.0001). Similar results were seen when the patients were grouped according to gender, race or age (<65 years, ≥65 years). The proportions of subjects with controlled SeDBP, as well as with simultaneous SeDBP/SeSBP control, at each week of the double-blind period were consistently larger and statistically significantly greater for irbesartan/hydrochlorothiazide-treated patients than for irbesartan-treated patients.
Table 7 Results at Week 5 of Study with Irbesartan/Hydrochlorothiazide in Subjects with Severe Hypertension
| Endpoints | Irbesartan/HCTZ 150/12.5 mg force titrated to 300/25 mg | Irbesartan 150 mg force titrated to 300 mg | p-value |
|---|---|---|---|
| Primary Endpoint: Proportion of subjects in each treatment group whose SeDBP was controlled (SeDBP <90 mmHg). | 47.2% | 33.2% | 0.0005 |
Other Endpoints:
| 34.6% | 19.2% | <0.0001 |
| Endpoints | Irbesartan/HCTZ 150/12.5 mg force titrated to 300/25 mg | Irbesartan 150 mg force titrated to 300 mg | p-value |
|---|---|---|---|
| -24.0 -30.8 | -19.3 -21.1 | <0.0001 <0.0001 |
DETAILED PHARMACOLOGY
Pharmacokinetics
Irbesartan
Following either oral or intravenous administration of 14C-labeled irbesartan, > 80% of the circulating plasma radioactivity was attributable to unchanged irbesartan. The primary circulating metabolite was the inactive irbesartan glucuronide (approximately 6%). The remaining oxidative metabolites did not add appreciably to the pharmacologic activity.
In vitro studies of irbesartan indicated that the oxidation of irbesartan was primarily by cytochrome P-450 isoenzyme CYP 2C9. Metabolism of irbesartan by CYP 3A4 was negligible. Irbesartan was neither metabolized, nor does it substantially induce or inhibit the following isoenzymes: CYP 1A1, 1A2, 2A6, 2B6, 2D6, 2E1. There was no induction or inhibition of CYP 3A4.
Hydrochlorothiazide
Hydrochlorothiazide was not metabolized but is eliminated rapidly by the kidney. The plasma half-life was observed to vary between 5.6 and 14.8 hours when the plasma levels could be followed for at least 24 hours. At least 61 percent of the oral dose was eliminated unchanged within 24 hours.
TOXICOLOGY
Acute Toxicity
Irbesartan
Table 8 Acute Toxicity for Irbesartan
| Species | Sex (N) | Route | LD50 (mg/kg) |
|---|---|---|---|
| Mouse | M (5) F (5) | PO | > 2000 |
| Rat | M (5) F (5) | PO | > 2000 |
| Mouse | M (5) F (5) | IV | > 50 |
| Rat | M (5) F (5) | IV | > 50 |
| Mouse | M (5) F (5) | IP | 200 - 2000 |
| Rat | M (5) F (5) | IP | 200 - 2000 |
After single administration, toxicity was slight and no target organ was identified. Very few toxic effects, characterized by pilo-erection and/or somnolence were noted at 2000 mg/kg by the oral route, 200 mg/kg by the intraperitoneal route and 50 mg/kg by the intravenous route. Acute oral toxicity studies with irbesartan in mice and rats indicated acute lethal doses were in excess of 2000 mg/kg, about 25 - 50 fold the maximum human dose (300 mg) on a mg/m2 basis, respectively.
Irbesartan – hydrochlorothiazide
Table 9 Acute Toxicity for Irbesartan – hydrochlorothiazide
| Species | Sex (N) | Route | LD50 (mg/kg) | |||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Irbesartan | HCTZ | Irbesartan/ HCTZ | ||||||||
| Mouse | M (5) F (5) | PO | > 2000 | > 4000 | > 2000/4000 | |||||
| Rat | M (5) | PO | > 3000 | > 500 | > 3000/500 | |||||
No mortality occurred following administration of the irbesartan/hydrochlorothiazide combination up to and including the highest dose of irbesartan:hydrochlorothiazide (2000/4000 mg/kg in mice or 3000/500 mg/kg in rats). No treatment-related clinical signs and body weight changes were observed. At necropsy, performed at the end of the 14-day observation period, pathologic examinations did not reveal any treatment-induced changes.
Subacute and Chronic Toxicity
Irbesartan
Table 10 Subacute and Chronic Toxicity Irbesartan
Species/ Strain | Sex (N/Dose) | Dose (mg/kg/day) | Route | Time | Effects | ||
|---|---|---|---|---|---|---|---|
| SUBACUTE TOXICITY | |||||||
| Rat | M (10) F (10) | 0, 30, 70, 150 | PO | 4 weeks |
| ||
| Rat | M (10) F (10) | 0, 0.8, 2, 5 | IV | 16 days |
| ||
| Monkey | M (3) F (3) | 0, 10, 30, 90 | PO | 4 weeks |
| ||
| Monkey | M (3) F (3) | 0, 250, 500, 1000 | PO | 4 weeks |
| ||
| Monkey | M (3) F (3) | 0, 0.8, 2, 5 | IV | 2 weeks |
| ||
| Rat | M (20) – F (20) [main study] M (10) – F (10) [reversibility study for control and | 0, 10, 30, 90 | PO | 26 weeks |
| ||
Species/ Strain | Sex (N/Dose) | Dose (mg/kg/day) | Route | Time | Effects | ||||
|---|---|---|---|---|---|---|---|---|---|
high dose groups] M (5) – F (5) [toxicokineti cs study] | |||||||||
| CHRONIC TOXICITY | |||||||||
| Rat | M (20) – F (20) [main study] M (10) – F (10) [reversibility study for control and high dose groups] M (5) – F (5) [toxicokinetics study] | 0, 250, 500, 1000 | PO | 26 weeks |
| ||||
| Monkey | M (5) – F (5) [main study] M (3) – F (3) [reversibility study for control and high dose groups] | 0, 10, 30, 90 | PO | 6 months |
| ||||
| Monkey | M (5) F (5) | 0, 20, 100, 500 | PO | 52 weeks |
| ||||
After repeated oral administrations at dose levels up to 1000 mg/kg per day, most of the treatment-related effects noted in all species are linked to the pharmacological activity of irbesartan. The kidney can be considered as the primary target organ: hyperplasia/hypertrophy of the juxtaglomerular apparatus which was observed in all species, is a direct consequence of the interaction with the renin-angiotensin system. Irbesartan also induced some hematology (slight decrease in erythrocyte parameters) and blood biochemistry variations (slight increase in urea, creatinine, phosphorus, potassium and calcium levels) likely due to a disturbance in the renal blood flow, and a slight decrease in heart weight which could result from a decrease in cardiac work load due to decreased peripheral vascular resistance. At high doses (> 500 mg/kg per day), degenerative changes of the kidney were noted which could be secondary to prolonged hypotensive effects.
Subacute and Chronic Toxicity (Cont’d)
Irbesartan/hydrochlorothiazide
Table 11 Subacute and Chronic Toxicity Irbesartan/hydrochlorothiazide
Species/ Strain | Sex (N/Dose) | Dose (mg/kg/day) | Rout e | Time | Effects |
|---|---|---|---|---|---|
| Rat | M (20) F (20) | 0*/0**, 10/10, 90/90, 90/0, 0/90 | PO | 6 months |
|
| Monkey | M (20) F (20) | 0*/0**, 10/10, 90/90 0/90, 90/0 | PO | 6 months |
|
Species/ Strain | Sex (N/Dose) | Dose (mg/kg/day) | Rout e | Time | Effects | |
|---|---|---|---|---|---|---|
| ||||||
* Irbesartan
** Hydrochlorothiazide
Reproduction and Teratology
Irbesartan
Fertility and reproductive performance were not affected in studies of male and female rats even at oral doses of irbesartan causing pronounced toxicity (up to 650 mg/kg/day). No significant effects on the number of corpora lutea, implants, or live fetuses were observed. Irbesartan did not affect survival, development, or reproduction of offspring except for a slight decrease of body weight gain during lactation which was reversible after weaning.
In a study of rats receiving maternally toxic doses of irbesartan (650 mg/kg/day), transient effects were observed in fetuses. These effects included increased incidences of renal pelvic cavitation at doses ≥50 mg/kg/day and subcutaneous edema at doses ≥180 mg/kg/day. Slight decreases in body weight gain were noted (prior to weaning) in offspring of females receiving irbesartan at doses ≥ 50 mg/kg/day. In rabbits, maternally toxic doses of irbesartan (30 mg/kg/day) were associated with maternal mortality and abortion. Surviving females receiving this dose had a slight increase in early resorption. However, no teratogenic effect was observed. Radioactivity was present in the rat and rabbit fetus during late gestation and in rat milk following oral doses of radiolabeled irbesartan. These findings are attributed to drug exposure in late gestation and during lactation.
Irbesartan/hydrochlorothiazide
In a Segment II teratology study carried out in rats, a dose of the combination irbesartan/hydrochlorothiazide up to 150/150 mg/day/kg did not show any teratogenic potential. There was decreased foetal body weight in the litters of dams given 150/150 mg/kg/day.
Carcinogenicity and Mutagenicity
Irbesartan
No evidence of carcinogenicity was observed when irbesartan was administered at doses of up to 500/1000 mg/kg/day (males/females, respectively) in rats and 1000 mg/kg/day in mice for 2 years. These doses provided systemic exposures of 3.6 - 24.9 times (rats) and 3.8 - 6.2 times (mice) the exposures in humans receiving 300 mg daily.
Irbesartan was not mutagenic in a battery of in vitro tests (Ames microbial test, rat hepatocyte DNA repair test, V79 mammalian cell forward gene mutation assay). Irbesartan was negative in several tests for induction of chromosomal aberrations (in vitro - human lymphocyte assay; in vivo - mouse micronucleus study).
Irbesartan/hydrochlorothiazide
No carcinogenicity studies have been conducted with the irbesartan/hydrochlorothiazide combination.
Irbesartan/hydrochlorothiazide was not mutagenic in standard in vitro tests (Ames microbial test and Chinese hamster mammalian-cell forward gene-mutation assay).
Irbesartan/hydrochlorothiazide was negative in tests for induction of chromosomal aberrations (in vitro - human lymphocyte assay; in vivo - mouse micronucleus study).
REFERENCES
- 1. Cazaubon C, Gougat J, Bousquet F, Guiraudou P, Gayraud R, Lacour C, et al. Pharmacological characterization of SR 47436, a new nonpeptide AT1 subtype angiotensin II receptor antagonist. J Pharmacol Exp Ther 1993; 265:826-834
- 2. Hagmann M, Burnier M, Nussberger J, Leenhardt AF, Brouard R, Waeber B, et al. Natriuretic and hormonal effects of SR 47436 (BMS 186295), a new angiotensin II receptor antagonist in normotensive volunteers. Am J Hyperten 1994; 7 (4,Pt.2): 13A
- 3. Marino MR, Langenbacher KM, Raymond RH, Whigan D, and Ford NF. Pharmacokinetics (pK) and antihypertensive effects of irbesartan (an AII receptor antagonist) in subjects with hypertension. J Hyperten 1996; 14(1): S348
- 4. Martinez F, Schmitt F, Savoiu C, Leenhardt AF, Brouard R, Peronnet P, et al. Effect of SR 47436 (BMS 186295) on renal hemodynamics and on glomerular permselectivity in healthy humans. J Am Soc Nephrol 1994; 5: 607
- 5. McIntyre M, McFadyen RJ, Meredith PA, Bruard R, and Reid JL. Dose-ranging study of the angiotensin II receptor antagonist irbesartan (SR 47436 / BMS 186295) on blood pressure and neurohormonal effects in salt-deplete men. J Cardiovas Pharmacol 1996; 28: 101-106
- 6. Ribstein J, Sissmann J, Picard A, Bouroudian M, and Mimran A. Effects of the angiotensin II antagonist SR 47436 (BMS 186295) on the pressor response to exogenous angiotensin II and the renin-angiotensin system in sodium replete normal subjects. J Hypertens 1994; 12:131
- 7. Sissmann J, Bouroudian M, Armagnac C, Donazollo Y, Latreille M, and Panis R. Angiotensin II blockade in healthy volunteers: Tolerability and impact on renin angiotensin system components of single and repeated doses of a new angiotensin II receptor antagonist SR 47436 (BMS 186295). J Hypertens 1994; 12: S92
- 8. Pool JL et al. Dose-Related Antihypertensive Effects of Irbesartan in Patients with Mild-to-Moderate Hypertension. American Journal of Hypertension, 1998, 11: 462-470.
- 9. Ribstein J, Picard A, Armagnac C, Sissman J and Mimran A. Inhibition of the Acute Effects of Angiotensin II by the Receptor Antagonist Irbesartan in Normotensive Men. Journal of Cardiovascular Pharmacology, 2001, 37:449-46
- 10. Pr AVALIDE® Product Monograph, sanofi-aventis Canada Inc, dated September 9, 2015, Control No.: 185045.