


Product Monograph - Pimozide
Recent Major Label Changes
None at time of the most recent authorization.
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ......................................................................................................... 2
Table of Contents .......................................................................................................................... 2
Part 1: Healthcare Professional Information ................................................................................. 4
- 1.
Indications ............................................................................................................................. 4
1.1. Pediatrics ....................................................................................................................... 4
1.2. Geriatrics ....................................................................................................................... 4
- 2. Contraindications ................................................................................................................... 4
- 3. Serious Warnings and Precautions Box .................................................................................. 5
- 4.
Dosage and Administration ................................................................................................... 5
4.1. Dosing Considerations ................................................................................................... 5
4.2. Recommended Dose and Dosage Adjustment............................................................... 5
4.2.1. Discontinuing Treatment ....................................................................................... 6
4.4. Administration ............................................................................................................... 6
4.5. Missed Dose .................................................................................................................. 6
- 5. Overdose................................................................................................................................ 6
- 6. Dosage Forms, Strengths, Composition, and Packaging .......................................................... 7
- 7.
Warnings and Precautions ..................................................................................................... 7
General................................................................................................................................... 7
Carcinogenesis and Genotoxicity ........................................................................................... 7
Cardiovascular ........................................................................................................................ 7
Dependence, Tolerance and/or Abuse Liability ...................................................................... 8
Driving and Operating Machinery .......................................................................................... 9
Endocrine and Metabolism .................................................................................................... 9
Gastrointestinal ...................................................................................................................... 9
Genitourinary ......................................................................................................................... 9
Hematologic ........................................................................................................................... 9
Hepatic/Biliary/Pancreatic ................................................................................................... 10
Neurologic ............................................................................................................................ 10
Reproductive Health ............................................................................................................ 10
7.1. Special Populations ..................................................................................................... 10
7.1.1. Pregnancy ................................................................................................................ 10
7.1.2. Breastfeeding .......................................................................................................... 11
7.1.3. Pediatrics ................................................................................................................. 11
7.1.4. Geriatrics ................................................................................................................. 11
- 8.
Adverse Reactions ............................................................................................................... 11
8.1. Adverse Reaction Overview ......................................................................................... 11
8.2. Clinical Trial Adverse Reactions ................................................................................... 11
8.5. Post-Market Adverse Reactions ................................................................................... 12
- 9.
Drug Interactions ................................................................................................................. 13
9.1. Serious Drug Interactions ............................................................................................ 13
9.2. Drug Interactions Overview ......................................................................................... 13
9.3. Drug-Behaviour Interactions ....................................................................................... 14
9.4. Drug-Drug Interactions ................................................................................................ 15
9.5. Drug-Food Interactions ................................................................................................ 16
9.6. Drug-Herb Interactions ................................................................................................ 16
9.7. Drug-Laboratory Test Interactions ............................................................................... 16
- 10.
Clinical Pharmacology .......................................................................................................... 16
10.1. Mechanism of Action .................................................................................................. 16
10.2. Pharmacodynamics ..................................................................................................... 17
10.3. Pharmacokinetics ........................................................................................................ 18
- 11. Storage, Stability, and Disposal ............................................................................................ 19
Part 2: Scientific Information ...................................................................................................... 20
- 13. Pharmaceutical Information ................................................................................................ 20
- 14.
Clinical Trials ........................................................................................................................ 20
14.2. Comparative Bioavailability Studies ............................................................................. 20
- 16. Non-Clinical Toxicology ........................................................................................................ 21
- 17. Supporting Product Monographs ......................................................................................... 24
Patient Medication Information .................................................................................................. 25
Part 1: Healthcare Professional Information
1. Indications
PIMOZIDE (pimozide tablets) is indicated for:
- Management of the manifestations of chronic schizophrenia in which the main manifestations do not include excitement, agitation or hyperactivity.
PIMOZIDE has relatively little sedative action and can be used as a once-daily medication.
PIMOZIDE is not indicated in the management of patients with mania or acute schizophrenia.
1.1. Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of pimozide tablets in children under the age of 18 have not been studied.
1.2. Geriatrics
Geriatrics (≥65 years of age): PIMOZIDE is not indicated in elderly patients with dementia. The safety and efficacy of pimozide tablets in patients 65 years of age or older have not been studied. See 3 Serious Warnings and Precautions Box and 7.1.4 Geriatrics.
2. Contraindications
PIMOZIDE is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container, see 6 Dosage Forms, Strengths, Composition, and Packaging.
- Central nervous system depression, brain damage, comatose states, liver disorders, renal insufficiency, pheochromocytoma and blood dyscrasias. It should not be used in depressive disorders or Parkinson's syndrome.
- Patients with congenital long QT syndrome or with a family history of this syndrome and in patients with a history of cardiac arrhythmias or Torsade de Pointes. A pre-treatment ECG is thus recommended to exclude these conditions. PIMOZIDE should not be used in the case of acquired long QT interval, such as associated with concomitant use of drugs known to prolong the QT interval (see 9.2 Drug Interactions Overview), known hypokalemia or hypomagnesemia, or clinically significant bradycardia.
- Combination with CYP 3A4-inhibiting drugs (such as azole antimycotics, antiviral protease inhibitors, macrolide antibiotics or nefazodone) or CYP 2D6-inhibiting drugs (such as quinidine). The inhibition of either or both enzymes (CYP 3A4 and CYP 2D6) of the cytochrome P450 system may result in the elevation of pimozide blood concentration and increase the possibility of QT-prolongation. See 9.2 Drug Interactions Overview.
- The treatment of simple tics or tics other than those associated with Tourette’s Disorder.
Combination with serotonin reuptake inhibitors, such as, sertraline, paroxetine, citalopram and
- escitalopram. See 9.4 Drug-Drug Interactions.
- A scheduled regional or spinal anesthesia.
3. Serious Warnings and Precautions Box
|
|---|
4. Dosage and Administration
4.1. Dosing Considerations
- Geriatrics: PIMOZIDE is not indicated in elderly patients with dementia. The safety and efficacy of pimozide tablets in patients 65 years of age or older have not been studied. See 7.1.4 Geriatrics.
- Given the higher incidence of concomitant illness (renal, hepatic and cardiovascular) and concomi-tant medication in the elderly, PIMOZIDE should be used with caution in this population. It is recom-mended that treatment be started with half of the adult starting dose.
- Patients should have baseline and periodic monitoring of blood glucose and body weight (See 7 Warnings and Precautions, Endocrine and Metabolism, Hyperglycemia).
- Patients should have their complete blood count (CBC) tested prior to starting PIMOZIDE and then periodically throughout treatment (See 8.5 Post-Market Adverse Reactions, Blood and Lymphatic System Disorders).
- Patients should be advised of the risk of severe constipation during PIMOZIDE treatment, and that they should tell their healthcare professional if constipation occurs or worsens, as they may need laxatives.
- All potential risk factors for venous thromboembolism (VTE) should be identified and preventative measures undertaken when prescribing PIMOZIDE (See 7 Warnings and Precautions, Hematologic, Venous Thromboembolism).
4.2. Recommended Dose and Dosage Adjustment
- A single morning dose is recommended for all patients.
Adults
Usual Starting Dose: The initial recommended dose in patients with chronic schizophrenia for whom PIMOZIDE might be indicated is 2 mg to 4 mg once daily, with weekly increments of 2 mg to 4 mg until a satisfactory level of therapeutic effect is attained or excessive adverse effects occur.
Maintenance Therapy: The average maintenance dose is 6 mg daily with the usual range of 2 mg to 12 mg per day. Daily doses above 20 mg are not recommended.
The patients should be reviewed regularly to ensure the minimum effective dose is being used.
4.2.1. Discontinuing Treatment
Acute withdrawal symptoms, including nausea, vomiting, transient dyskinetic signs, and insomnia, have very rarely been described after abrupt cessation of high doses of antipsychotic drugs. Gradual withdrawal is advisable. (See 7 Warning and Precautions, Dependence, Tolerance and/or Abuse Liability, Withdrawal).
4.4. Administration
Tablets are for oral administration.
4.5. Missed Dose
If a patient misses a dose, advise the patient to take the dose as soon as possible and continue with their regular schedule. If it is almost time for the next dose, advise the patient to skip the missed dose and continue with the next scheduled dose. Advise patients not to take 2 doses of PIMOZIDE at the same time to make up for a missed dose.
5. Overdose
Symptoms
In general, the signs and symptoms of overdosage with PIMOZIDE would be an exaggeration of known pharmacologic effects and adverse reactions, the most prominent of which would be extrapyramidal symptoms. The risk of cardiac arrhythmias, possibly associated with QT prolongation and ventricular arrhythmias including Torsade de Pointes should be considered. If these arrhythmias are severe, they can be associated with hypotension and circulatory collapse.
Treatment
There is no specific antidote to pimozide. In the event of overdosage, establishment of a patent airway and, if necessary, mechanically-assisted respiration are advised. Continuous electrocardiographic monitoring should be performed due to risk of QT interval prolongation and ventricular arrhythmias including Torsade de Pointes and continued until the ECG parameters are within the normal range. Severe arrhythmias should be treated with appropriate antiarrhythmic treatment. Associated hypotension and circulatory collapse may be counteracted by use of intravenous fluids, plasma, or concentrated albumin, and vasopressor agents such as dopamine or dobutamine. Epinephrine should not be used. In case of severe extrapyramidal reactions, antiparkinson medication should be administered. Because of the long half-life of pimozide, patients who take an overdose should be observed for at least 4 days. As with all drugs, the physician should consider contacting a poison control centre for additional information on the treatment of overdose.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
| Oral | Tablets, 2 mg, 4 mg of pimozide | Anhydrous lactose, croscarmellose sodium, magnesium stearate. 4 mg Tablets: contains additional D & C yellow #10 Aluminium Lake 14-18%, indigotine AL Lake 12-14% (Blue #2). |
PIMOZIDE 2 mg Tablets: White, round tablet. Plain on one side, scored and engraved “PIM” over “2” on the other side. Available in HDPE bottles of 100 tablets.
PIMOZIDE 4 mg Tablets: Light green, round, flat-faced, bevelled-edge tablet. Plain on one side, scored and engraved “PIM” over “4” on the other side. Available in HDPE bottles of 100 tablets.
7. Warnings and Precautions
See 3 Serious Warning and Precautions Box.
General
Body Temperature Regulation: Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Hyperpyrexia has been reported with other antipsychotic drugs. Appropriate care is advised when prescribing PIMOZIDE to patients who will be experiencing conditions which may contribute to an elevation in core body temperature, e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity or being subject to dehydration.
Carcinogenesis and Genotoxicity
See 16 Non-Clinical Toxicology, Carcinogenicity.
Cardiovascular
There have been very rare reports of QT prolongation, ventricular arrhythmias, and Torsade de Pointes in patients without risk factors for QT prolongation administered therapeutic doses of pimozide tablets, and in the setting of overdose. Ventricular tachycardia and ventricular fibrillation (in some cases with fatal outcomes) have also been reported, in addition to very rare reports of sudden death and cardiac arrest.
As with other neuroleptics, cases of sudden, unexpected deaths have been reported with pimozide tablets, at recommended doses and in the setting of overdoses.
Many drugs that cause QT/QTc prolongation are suspected to increase the risk of Torsade de Pointes. Generally, the risk of Torsade de Pointes increases with the magnitude of QT/QTc prolongation produced by the drug. Torsade de Pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
An ECG should be performed prior to initiation of treatment with PIMOZIDE, as well as periodically during treatment (although there is no proof that periodic ECG monitoring will reduce the risk of Torsade de Pointes). If repolarization changes (prolongation of QT interval, T-wave changes or U-wave development) appear or arrhythmias develop, the need for treatment with PIMOZIDE in these patients should be reviewed. They should be closely monitored and their dose of PIMOZIDE should be reduced or the drug discontinued. If QT or QTc exceeds 500 msec, PIMOZIDE should be discontinued.
Particular care should be exercised when administering PIMOZIDE or its use avoided in patients who are suspected to be at an increased risk of experiencing Torsade de Pointes during treatment with a QT/QTc-prolonging drug. Risk factors for Torsade de Pointes in the general population include, but are not limited to, the following:
- female
- age 65 years or older
- baseline prolongation of the QT/QTc interval
- presence of genetic variants affecting cardiac ion channels or
- regulatory proteins, especially congenital long QT syndromes
- family history of QT prolongation, or sudden cardiac death at <50 years
- cardiac disease (e.g., myocardial ischemia or infarction, congestive heart failure, left ventricular hypertrophy, cardiomyopathy, conduction system disease)
- history of arrhythmias (especially ventricular arrhythmias, atrial fibrillation, or recent conversion from atrial fibrillation)
- electrolyte disturbances (e.g., hypokalemia, hypomagnesemia, hypocalcemia)
- bradycardia (<50 beats per minute)
- acute neurological events (e.g., intracranial or subarachnoid haemorrhage, stroke, intracranial trauma)
- nutritional deficits (e.g., eating disorders, extreme diets)
- diabetes mellitus
- autonomic neuropathy
- hepatic dysfunction, renal dysfunction, and/or phenotypic/genotypic poor metabolizers of drug metabolizing enzyme isoforms, if relevant to the elimination of the drug.
Physicians who prescribe drugs that prolong the QT/QTc interval should counsel their patients concerning the nature and implications of the ECG changes, underlying diseases and disorders that are considered to represent risk factors, demonstrated and predicted drug-drug interactions, symptoms suggestive of arrhythmia, risk management strategies, and other information relevant to the use of the drug.
Potential for Hypotension: Hypotension may very rarely occur. Patients receiving PIMOZIDE should be observed for evidence of hypotension. Some individuals, especially the elderly or debilitated, have demonstrated transient hypotension for several hours following drug administration.
Dependence, Tolerance and/or Abuse Liability
Withdrawal Emergent Neurological Signs: Generally, patients receiving short-term therapy experience no problem with abrupt discontinuation of antipsychotic drugs. However, some patients on maintenance treatment experience transient dyskinetic signs after abrupt withdrawal. In certain of these cases the dyskinetic movements are indistinguishable from the syndrome described above under ‘Tardive Dyskinesia’ except for duration. It is not known whether gradual withdrawal of antipsychotic drugs will reduce the rate of occurrence of withdrawal emergent neurological signs but, until further evidence becomes available, it seems reasonable to gradually withdraw use of antipsychotic drugs.
In schizophrenia, the response to antipsychotic drug treatments may be delayed. If drugs are withdrawn, recurrence of symptoms may not become apparent for several weeks or months. Acute withdrawal symptoms, including nausea, vomiting, transient dyskinetic signs, and insomnia, have very rarely been described after abrupt cessation of high doses of antipsychotic drugs. Gradual withdrawal is advisable.
Driving and Operating Machinery
PIMOZIDE may impair alertness, especially at the start of treatment. These effects may be potentiated by alcohol. Patients should be warned of the risks of sedation and advised not to drive or operate machinery during treatment until their susceptibility is known.
Endocrine and Metabolism
Hyperprolactinemia: Hormonal effects of antipsychotic/neuroleptic drugs include hyperprolactinaemia, which may cause galactorrhoea, gynaecomastia, oligomenorrhoea or amenorrhoea, and erectile dysfunction.
Tissue culture experiments indicate that approximately one-third of human breast cancers are prolactin-dependent in vitro, a factor of potential importance if the prescription of these drugs is contemplated in a patient with a previously detected breast cancer. An increase in mammary neoplasms has been found in rodents after chronic administration of neuroleptic drugs. The clinical significance of elevated serum prolactin levels is unknown for most patients. Neither clinical studies, nor epidemiological studies conducted to date, have shown an association between chronic administration of these drugs and mammary tumorogenesis; the available evidence is considered too limited to be conclusive at this time.
Long-standing hyperprolactinemia when associated with hypogonadism may lead to decreased bone mineral density in both female and male subjects.
Hyperglycemia: Diabetic ketoacidosis (DKA) has occurred in patients with no reported history of hyperglycemia. Patients should have baseline and periodic monitoring of blood glucose and body weight.
Gastrointestinal
Antiemetic Effects: As with other antipsychotics, PIMOZIDE has a substantial antiemetic effect. Thus, caution should be exercised in cases where the suppression of nausea and vomiting might hinder the diagnosis of an underlying physical disorder.
Genitourinary
Rare cases of priapism have been reported with antipsychotic use, such as pimozide tablets. This adverse reaction, as with other psychotropic drugs, did not appear to be dose-dependent and did not correlate with the duration of treatment.
Hematologic
Leukopenia, Neutropenia, and Agranulocytosis Class Effect: Neutropenia, leukopenia, granulocytopenia, agranulocytosis and anemia have been reported during antipsychotic use. Therefore, it is recommended that patients have their complete blood count (CBC) tested prior to starting PIMOZIDE, and then periodically throughout treatment. (See 4.1 Dosing Considerations and 8.5 Post-Market Adverse Reactions).
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC) and history of drug-induced leukopenia/neutropenia. Patients with a history of a clinically significant low WBC or a drug-induced leukopenia/neutropenia should be monitored during the first few months of therapy and discontinuation of PIMOZIDE should be considered at the first sign of a clinically significant decline in WBC in the absence of other causative factors.
Venous thromboembolism (VTE): VTE, including fatal pulmonary embolism, has been reported with antipsychotic drugs, including pimozide tablets, in case reports and/or observational studies. When prescribing PIMOZIDE, all potential risk factors for VTE should be identified and preventative measures undertaken.
Hepatic/Biliary/Pancreatic
Caution is advised in patients with liver disease because PIMOZIDE is metabolized in the liver.
Neurologic
Increased Psychomotor Activity: Clinical trials with pimozide indicate that it is not effective in, and therefore should not be used in the management of manifestations of chronic schizophrenia in which the main symptoms include agitation, excitement and anxiety.
Neuroleptic Malignant Syndrome: In common with other antipsychotic drugs, pimozide tablets has been associated with neuroleptic malignant syndrome: an idiosyncratic response characterized by hyperthermia, generalised muscle rigidity, autonomic instability, and altered consciousness.
Hyperthermia is often an early sign of this syndrome. Antipsychotic treatment should be withdrawn immediately and appropriate supportive therapy and careful monitoring instituted.
Tardive Dyskinesia: As with all antipsychotic agents, tardive dyskinesia may appear in some patients on long-term therapy or after drug discontinuation. The syndrome is mainly characterized by rhythmical involuntary movements of the tongue, face, mouth or jaw. The manifestations may be permanent in some patients. The syndrome may be masked when treatment is reinstituted, when the dosage is increased or when a switch is made to a different antipsychotic drug. Treatment should be discontinued as soon as possible.
Seizures: As with other antipsychotic drugs, PIMOZIDE should be used cautiously in patients with a history of seizures or other conditions that potentially lower the seizure threshold. In addition, grand mal convulsions have been reported in association with pimozide tablets.
Extrapyramidal Symptoms: In common with all neuroleptics, extrapyramidal symptoms may occur. See 8.5 Post-Market Adverse Reactions.
Anticonvulsants: Since PIMOZIDE may lower the convulsive threshold, it should be used with caution in epileptic patients and adequate anticonvulsive medication should be maintained.
Reproductive Health
- Fertility
When pimozide was administered to male rats for 60 days pre-mating and to female rats for 14 days pre-mating, no effect was noted on male or female fertility, but the estrus cycle of dosed females was increased (See 16 Non-Clinical Toxicology, Reproductive and developmental toxicology).
- Function
Erectile dysfunction and rare cases of priapism have been reported with antipsychotic use, such as pimozide tablets (See 7 Warnings and Precautions, Genitourinary and 8.5 Post-Market Adverse Reactions).
7.1. Special Populations
7.1.1. Pregnancy
The safety of pimozide tablets in pregnancy has not been studied. Spontaneous abortions have been reported (See 8.5 Post-Market Adverse Reactions). Therefore, it should not be administered to women of child-bearing potential, particularly during the first trimester of pregnancy, unless, in the opinion of the physician, the expected benefits of the drug to the patient outweigh the potential risk to the fetus or child.
Teratogenic Risk
Teratogenic Effects: Teratogenic effects have not been observed.
Non-Teratogenic Effects: Neonates exposed to antipsychotic drugs (including PIMOZIDE) during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases, neonates have required intensive care unit support and prolonged hospitalization.
Animal data have shown some embryo-toxicity at dose levels similar to the maximum human use level (MHUL). In addition, fetal growth retardation and fetal-toxicity was observed at dose levels of approximately 6 times the MHUL on an mg/kg basis.
7.1.2. Breastfeeding
Pimozide may be excreted in breast milk. If the use of PIMOZIDE tablets is considered essential, breast feeding should be discontinued.
7.1.3. Pediatrics
Pediatrics (<18 years of age): The safety and efficacy in children have not been studied; therefore, this drug is not recommended for use in the pediatric age group.
7.1.4. Geriatrics
Geriatrics (≥65 years of age): The safety and efficacy of pimozide tablets in patients 65 years of age or older have not been studied. Caution should be exercised with the use of PIMOZIDE in the elderly patient, recognizing the more frequent hepatic, renal, central nervous system, and cardiovascular dysfunctions, and more frequent use of concomitant medication in this population. See 4 Dosage and Administration.
Use in Geriatric Patients with Dementia: PIMOZIDE is not indicated in elderly patients with dementia. Elderly patients with dementia treated with atypical antipsychotic drugs showed increased mortality compared to placebo in a meta-analysis of 13 controlled trials of various atypical antipsychotic drugs.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Information is not available.
8.2. Clinical Trial Adverse Reactions
Information is not available.
8.5. Post-Market Adverse Reactions
The following serious and unexpected adverse events have been reported. Because these events are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: blood dyscrasias* (agranulocytosis, anemia, aplastic anemia, eosinophilia, granulocytopenia, leukopenia, neutropenia, pancytopenia, thrombocytopenic purpura), bone marrow failure, disseminated intravascular coagulation, leukocytosis, lymphadenopathy, polycythaemia, thrombocytopenia.
* It is recommended that patients have their complete blood count (CBC) tested prior to starting PIMOZIDE and then periodically throughout treatment.
Cardiac Disorders: angina pectoris, arrhythmia, coronary atherosclerosis, atrioventricular block, cardiac arrest, cardiac failure, cardiac valve disease, cardio-respiratory arrest, cardiomegaly, coronary artery disease, myocardial infarction, myocardial ischemia, myocarditis, stress cardiomyopathy, torsade de pointes, ventricular tachycardia, ventricular fibrillation.
Congenital, Familial and Genetic Disorders: congenital anomaly, congenital hydronephrosis, double ureter, dysmorphism, macrocephaly, microphthalmos, skull malformation, Tourette’s disorder, urinary tract malformation, ventricular septal defect.
Endocrine Disorder: increased blood prolactin, hyperglycemia (in patients with pre-existing diabetes), hyperprolactinemia, hyperthyroidism, inappropriate antidiuretic hormone secretion.
Eye Disorder: accommodation disorder, glaucoma, oculogyration, blurred vision, visual impairment.
Gastrointestinal Disorders: constipation**, diarrhea, dry mouth, haemorrhagic enterocolitis, fecal incontinence, intestinal ischemia, pancreatitis, salivary hypersecretion, subileus, vomiting.
**Patients should be advised of the risk of severe constipation during PIMOZIDE treatment, and that they should tell their healthcare professional if constipation occurs or worsens, as they may need laxatives.
General Disorder and Administration Site Conditions: asthenia, death, drug interaction, face oedema, fatigue, hyperthermia, hypothermia, macrosomia, malaise, pyrexia.
Hepatobiliary Disorders: abnormal hepatic function, hepatitis, hepatomegaly, liver injury.
Immune System Disorders: antiphospholipid syndrome.
Infections and Infestations: bacterial infection, bacterial toxaemia, bronchitis, bronchopneumonia, pneumonia, pustular rash.
Injury, Poisoning and Procedural Complications: accidental exposure, contusion, drug dispensing error, drug toxicity, fall, femoral neck fracture, overdose, wound.
Investigations: increased blood creatinine phosphokinase, increased blood phosphorus, decreased blood pressure, increased blood pressure, breath sounds, circulating coagulant, increased drug level, abnormal electrocardiogram (repolarisation, ST segment depression, T wave inversion, T wave peaked), prolonged electrocardiogram QT interval, abnormal electroencephalogram, decreased hematocrit, decreased haemoglobin, increased hepatic enzyme, decreased red blood cell count, increased red cell distribution width, increased respiratory rate, increased transaminases, increased weight, decreased white blood cell count, increased white blood cell count.
Metabolism and Nutrition Disorders: decreased appetite, diabetes mellitus (type I and type II), dyslipidaemia, reduced fluid intake, hyperphagia, hypoglycaemia, hypokalaemia, hyponatraemia, ketoacidosis.
Musculoskeletal and Connective Tissue Disorders: arthralgia, muscle rigidity, myalgia, nuchal rigidity, rhabdomyolysis, soft tissue haemorrhage, systemic lupus erythematosus.
Benign, Malignant and Unspecified Neoplasms (Including Cysts and Polyps): endometrial cancer, myelodysplastic syndrome.
Nervous System Disorders: akathisia, altered state of consciousness, bradykinesia, cognitive disorder, cogwheel rigidity, coma, convulsion, dementia, disturbance in attention, dizziness, drooling, dyskinesia, dystonia, epilepsy, extrapyramidal disorder, grand mal convulsion, haemorrhagic cerebral infarction, headache, hypoaesthesia, hypokinesia, hypoxic-ischemic encephalopathy, loss of consciousness (syncope), lethargy, masked facies, mental retardation, neuroleptic malignant syndrome, parkinsonism, somnolence, stupor, tardive dyskinesia, tremor, unresponsive to stimuli.
Pregnancy, Puerperium and Prenatal Conditions: missed abortion, spontaneous abortion.
Psychiatric Disorder: abnormal behaviour, aggression, agitation, apathy, confusional state, decreased activity, delusion, depression, disorientation, drug dependence, euphoric mood, hallucination, insomnia, decreased libido, mutism, psychomotor retardation, restlessness, schizophrenia, self injurious behaviour, sleep disorder, suicide, suicide attempt, withdrawal syndrome.
Renal and Urinary Disorders: anuria, glycosuria, haematuria, nephrotic syndrome, renal failure, urinary incontinence, urinary retention.
Reproductive System and Breast Disorder: amenorrhoea, breast cysts, erectile dysfunction, galactorrhoea, gynaecomastia.
Respiratory, Thoracic and Mediastinal Disorders: asphyxia, bradypnoea, dyspnoea, hypoxia, lung disorder, oropharyngeal spasm, pulmonary congestion, pulmonary embolism, pulmonary oedema, pulmonary thrombosis, respiratory arrest.
Skin and Subcutaneous Tissue Disorders: angioedema, hyperhidrosis, photosensitivity reaction, pruritus, rash (exfoliative, erythematous, popular), skin exfoliation, skin toxicity, toxic skin eruption, urticaria.
Vascular Disorders: arteriosclerosis, circulatory collapse, deep vein thrombosis, venous embolism, hematoma, hypertension (orthostatic), phlebitis, shock, thrombosis.
9. Drug Interactions
9.1. Serious Drug Interactions
|
|---|
9.2. Drug Interactions Overview
Drugs that Inhibit Cytochrome P450
Pimozide is metabolized mainly via the cytochrome P450 subtype 3A4 (CYP 3A4) enzyme system and more discreetly via the CYP 2D6 subtype. In vitro data indicate that especially potent inhibitors of CYP 3A4 enzyme system, such as aprepitant, azole antimycotics, antiviral protease inhibitors, macrolide antibiotics and nefazodone will inhibit the metabolism of pimozide, resulting in markedly elevated plasma levels of pimozide. In vitro data also indicate that quinidine diminishes the CYP 2D6 dependent metabolism of pimozide. Elevated pimozide levels may enhance the risk of QT prolongation.
As CYP 1A2 may also contribute to the metabolism of pimozide tablets, prescribers should be aware of the theoretical potential for drug interactions with inhibitors of this enzymatic system.
Drugs that Prolong QT Interval
Concomitant use of pimozide with drugs known to prolong the QT interval are contraindicated. See 2 Contraindications.
Drugs that have been associated with QT/QTc interval prolongation and/or torsade de pointes include, but are not limited to, the examples in the following list. Chemical/pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QT/QTc prolongation and/or torsade de pointes:
- Class IA antiarrhythmics (e.g., quinidine, procainamide, disopyramide)
- Class III antiarrhythmics (e.g., amiodarone, sotalol, ibutilide)
- Class 1C antiarrhythmics (e.g., flecainide, propafenone)
- antipsychotics (e.g., chlorpromazine, pimozide, haloperidol, droperidol)
- antidepressants (e.g., fluoxetine, venlafaxine, tricyclic/tetracyclic antidepressants)
- opioids (e.g., methadone)
- macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, telithromycin)
- quinolone antibiotics (e.g., moxifloxacin, gatifloxacin)
- pentamidine
- antimalarials (e.g., quinine)
- azole antifungals (e.g., fluconazole, itraconazole, ketoconazole, voriconazole)
- domperidone
- 5-HT3 antagonists (e.g., dolasetron, ondansetron)
- tacrolimus
- beta-2 adrenoceptor agonists (e.g., salmeterol, formoterol)
Particular care should be taken to avoid toxic plasma levels of lithium when this agent is administered together with pimozide, since such toxic levels have also been associated with QT prolongation.
Do not administer in combination with drugs causing electrolyte alteration. Concomitant use with diuretics should be avoided, in particular those causing hypokalemia. Other drugs that can disrupt electrolyte levels, include, but are not limited to, the followings:
- laxatives and enemas
- amphotericin B
- high dose corticosteroids
9.3. Drug-Behaviour Interactions
Alcohol potentiates the adverse effects of pimozide tablets. Patients should be advised to avoid alcohol while taking PIMOZIDE.
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| Antihypertensives | T | ↓Antihyperten sive effect | Concomitant administration of antihypertensive agents should be undertaken with caution in view of the fact that other antipsychotics, notably the phenothiazines, have blocked the action of these agents. |
| Drugs acting on CNS | T | ↑Pimozide | Potentiation of the effects of drugs acting on the central nervous system (anesthetics, opiates, alcohol, etc.) as well as atropine and organophosphorous insecticides may occur with the use of pimozide. Both animal and human data indicate that pimozide may block the action of amphetamines. Therefore, concomitant use of the two medications is not recommended. |
| Levodopa | T | ↓Levodopa | Pimozide may, in a dose-related way, impair the antiparkinson effect of levodopa. |
| SSRI (Selective Serotonin Reuptake Inhibitor) Antidepressants | C | ↑Pimozide AUC and Cmax | An in vivo study of pimozide added to steady state sertraline revealed a 40% increase in the pimozide AUC and Cmax. See 2 Contraindications. |
| Citalopram | C | ↑ QTc values ↔ AUC and Cmax of Pimozide | An in vivo study of co-administered pimozide and citalopram resulted in a mean increase of QTc values of approximately 10 milliseconds. Citalopram did not alter the AUC and Cmax of pimozide. See 2 Contraindications. |
| Paroxetine | C | ↑Pimozide AUC and Cmax | An in vivo study of co-administered pimozide (a single 2 mg dose) and paroxetine (60 mg daily) was associated with mean increases of 151% in pimozide AUC and 62% in pimozide Cmax. See 2 Contraindications. |
C = Case Study, T = Theoretical
9.5. Drug-Food Interactions
Grapefruit Juice
As grapefruit juice is known to inhibit the metabolism of CYP 3A4 metabolized drugs, concomitant use of grapefruit juice with PIMOZIDE tablets should be avoided.
9.6. Drug-Herb Interactions
Betel Nut
Concurrent use of Betel nut may result in an increased risk of extrapyramidal side effects of pimozide.
Case reports have described increased extrapyramidal side effects when betel nut was chewed by patients taking fluphenazine and fluphenthixol for schizophrenia. The extrapyramidal effects were not improved with anticholinergic therapy with procyclidine, and resolved with betel nut discontinuation.
A similar effect may occur if betel nut is chewed with concomitant pimozide therapy. The cholinergic activity of betel nut has been attributed to the arecoline content. When given with peripheral anticholinergics, arecoline increased the heart rate due to central muscarinic agonist activity. Case reports suggest the onset of betel nut activity to be within 2 weeks with resolution within 4 to 7 days after discontinuation.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been studied.
10. Clinical Pharmacology
10.1. Mechanism of Action
Pimozide is a diphenylbutylpiperidine derivative with neuroleptic properties that has been found to be useful in the management of chronic schizophrenic patients. It is relatively non-sedating and can be administered in a single daily dosage.
It is assumed that the basic mechanism of action of pimozide is related to its action on central aminergic receptors. It appears to have a selective ability to block central dopaminergic receptors, although it affects noradrenaline turnover at higher doses. The extrapyramidal effects typical of other neuroleptic agents are seen also with pimozide, but it appears to have fewer autonomic effects. As with other neuroleptics, endocrine effects and ECG changes have also been reported with pimozide.
10.2. Pharmacodynamics
Animals
The pharmacological profile of pimozide in laboratory animals resembles that of other antipsychotics.
As with other neuroleptics, pimozide reduces locomotor and exploratory behaviour at low doses, and induces catatonic immobility and palpebral ptosis in rats at higher doses.
Pimozide inhibits conditioned avoidance responding in rats and dogs and self-stimulation in rats.
Pimozide is a potent antagonist to amphetamine- and apomorphine-induced stereotypy in most animal species tested. It also blocks apomorphine-induced emesis.
Pimozide has little activity in the norepinephrine test in rats.
Typical neuroleptic catalepsy was observed in 8 out of 8 monkeys treated with 0.8 mg/kg pimozide. Obvious to severe extrapyramidal (dystonic) effects were observed at the same doses in 4 out of 8 pimozide-treated monkeys.
Pimozide causes no significant alterations in the hemodynamic parameters in cardiovascular experiments in rats, dogs, and dwarf pigs. It is a weak hypotensive agent and norepinephrine antagonist in rats and dogs, and exhibits very weak alpha-adrenergic blocking activity in dogs. In other tests, it has been found to antagonize the action of angiotensin on rat colon and rabbit aorta.
Bio- and histochemical studies in rats have indicated that, at the lower-dose levels, pimozide is a highly selective blocker of central dopamine receptors and increases turnover of dopamine in the central nervous system. At higher doses, increased turnover of noradrenaline has also been observed.
The following Table shows dosage details for some of the above-mentioned tests.
Table 3 – Activity Profile of Pimozide
| Pharmacological Test | PIM mg/kg | |||||
|---|---|---|---|---|---|---|
| S.C. | P.O. | |||||
| Lowest dose producing at least 40% ptosis | 2.5 | 2.5 | ||||
| Catalepsy: ED50 | 0.2 | 0.22 | ||||
| Ptosis/Catalepsy ratio | 12.5 | 11.0 | ||||
| Jumping box: ED50 | 0.11 | 0.09 | ||||
Sidman shock avoidance:
| 0.16 | |||||
| Noise escape: ED50 | 0.17 | |||||
| Intracranial self-stimulation: - 50% decrease - 90% increase | 0.2 0.6 | |||||
Anti-apomorphine test:
| 0.17 | |||||
Anti-amphetamine test
| 0.11 | |||||
Anti-norepinephrine test:
| -40 | |||||
Anti-apomorphine test (dogs):
| 0.012 | 0.018 | ||||
| Jumping box (dogs): ED50 | 0.1 | 0.2 | ||||
* Results from earlier pharmacological studies.
** The ED50's varied with time after administration; on the anti-apomorphine test, the lower ED50 with PIM occurred at 4 hours, the peak value on the anti-amphetamine test occurred at 4 hours and at 2 hours on the anti-norepinephrine test.
10.3. Pharmacokinetics
Absorption
Pimozide is well absorbed after oral administration, as demonstrated by the similarity of effective oral and parenteral doses. In rats, approximately 10% of the radioactivity of tritium-labelled doses is stored in the liver, 0.7% in blood, and 0.1% in the brain throughout the first 8 hours; thereafter the concentration in the brain decreases more slowly than that in blood and the liver. Detectable levels of radioactivity have been found in all three tissues 64 hours after the injection. In the brain, the concentration of radioactivity is highest in the caudate nucleus. Peak levels of unchanged pimozide occur one hour after injection, whereafter they gradually decrease at a similar rate in all three tissues.
More than 50% of a dose of pimozide is absorbed after oral administration. Peak serum levels occur generally six to eight hours (range: 4 to 12 hours) after dosing.
Distribution
The biological half-life of pimozide in rats has been estimated to be 5.6 hours. At one hour, the percentage unchanged pimozide of total tritiated material was 84% in the brain, 47% in blood and 33% in the liver. The liver contained approximately 36 times more unchanged pimozide than the brain and about 11 times more than blood. When tritium-labelled pimozide was given subcutaneously to dogs, 0.13% of the dose was recovered in the brain 6 hours following the injection. Virtually all of the radioactivity present was due to unchanged pimozide. The highest concentrations were found in the pituitary gland and the caudate nucleus.
Metabolism
The major metabolic pathway in rats is oxidative N-dealkylation, the main metabolites being 4-bis (p-fluorophenyl) butyric acid and N-4-piperidyl-2-benzimidazolinone. It is thought that the metabolites are pharmacologically inactive, since peak pharmacological activity has been found to correlate with maximum brain levels of unchanged pimozide, but not of the total radioactivity.
Pimozide appears to undergo significant first-pass metabolism. Pimozide is extensively metabolized, primarily by N-dealkylation in the liver. Two major metabolites have been identified: 1-(4-piperidyl)-2-benzimidazolinone and 4,4-bis(4-fluorphenyl) butyric acid. These metabolites have no antipsychotic activity.
The mean elimination half-life of pimozide in schizophrenic patients was approximately 55 hours. There was a more than ten-fold interindividual difference in the area under the serum pimozide level time curve and an equivalent degree of variation in peak serum levels among patients studied. The significance of this is unclear, since there are few correlations between plasma levels and clinical findings.
Elimination
Most of the injected pimozide is excreted within 48 hours in rats. When 14C-labelled drug was used, 32% of the radioactivity was excreted in urine, mainly as N-4-piperidyl-2-benzimidazolinone, and 42% in the feces, half as unchanged pimozide, half as N-4-piperidyl-2-benzimidazolinone. With 3H-labelled pimozide, excretion was mainly in the feces as unchanged pimozide and as 4-bis (p-fluorophenyl) butyric acid and bis (p-fluorophenyl) acetic acid.
Only a very small fraction of pimozide is excreted unchanged in the urine. The major route of elimination of the metabolites is through the kidney.
Special populations and conditions
- Pediatrics: The safety and efficacy of pimozide in children under the age of 18 have not been studied. See 7.1.3 Pediatrics.
- Geriatrics: Pimozide is not indicated in elderly patients with dementia. See 7.1.4 Geriatrics.
- Sex: The clinical trial data on which the indication was originally authorized is not available.
Pregnancy and breastfeeding: The safety of pimozide in pregnancy has not been studied. There-fore, it should not be administered to women of child-bearing potential, particularly during the first trimester of pregnancy. See 7.1.1 Pregnancy.
Pimozide may be excreted in breast milk. If the use of pimozide tablets is considered essential, breast feeding should be discontinued. See 7.1.2 Breastfeeding.
- Genetic polymorphism: The clinical trial data on which the indication was originally authorized is not available.
- Ethnic origin: The clinical trial data on which the indication was originally authorized is not avail-able.
- Hepatic Insufficiency: Caution is advised in patients with liver disease because pimozide is me-tabolized in the liver. See 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic.
- Renal Insufficiency: See 4.1 Dosing Considerations.
- Obesity: The clinical trial data on which the indication was originally authorized is not available.
- Storage, Stability, and Disposal
Store at controlled room temperature (15°C to 30°C) in well-closed containers.
PIMOZIDE should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Pimozide
Chemical names: 1) 1-[1-[4,4-bis(4-fluorophenyl)butyl]-4-piperidinyl]-1,3-dihydro-
2H-benzimidizole-2-one
- 2)
1-[1-[4,4-bis(p-fluorophenyl)butyl]-4-piperidinyl]-2-
benzimidizolinone
Molecular formula and molecular mass: C28H29F2N3O and 461.6 g/mol
Structural formula:
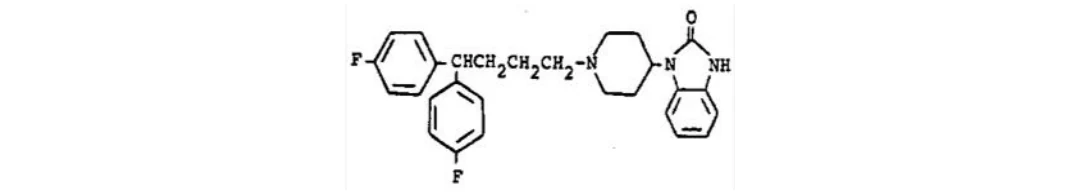
Physicochemical properties:
Description: A white, or almost white, powder.
14. Clinical Trials
The clinical trial data on which the original indication was authorized is not available.
14.2. Comparative Bioavailability Studies
A randomized, two-way, single-dose crossover comparative bioavailability study of PIMOZIDE tablets, 4 mg (AA Pharma Inc.) and ORAP® tablets, 4 mg (Janssen-Ortho Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 23 subjects that were included in the statistical analysis are summarized in the following table:
Table 4 - Summary Table of the Comparative Bioavailability Data
Pimozide (1 x 4 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72h (ng·h/mL) | 62.14 70.61 (63.77) | 58.70 66.69 (61.06) | 105.9 | 98.7 – 113.7 |
CMAX (ng/mL) | 2.29 2.50 (48.57) | 2.11 2.31 (48.59) | 108.1 | 100.5 – 116.3 |
TMAX3 (h) | 6.50 (4.00 – 10.00) | 6.50 (4.00 – 16.00) | ||
1 PIMOZIDE (pimozide) tablets, 4 mg (AA Pharma Inc.).
2 ORAP® (pimozide) tablets, 4 mg (Janssen-Ortho Inc., Canada).
3 Expressed as the median (range) only.
Due to the long elimination half-life of pimozide, AUCI and T1/2 could not be accurately calculated from the data ob-tained in this study.
16. Non-Clinical Toxicology
General toxicology
Acute Toxicity
Table 4 - The following table presents the results of the acute pimozide toxicity studies in rats, mice, hamsters and dogs.
| Species | Sex | Route & Vehicle* | LD50 mg/kg (95% confidence limits)** |
| Rat | M F M M | Oral(1) Oral(2) S.C.(4) I.V.(4) | > 5120 1430 (996-2116) > 40 > 5 |
| Mouse | M M&F M M | Oral(1) Oral(2) S.C.(4) I.V.(4) | 228 (141-369) > 640 > 40 11.1 (7.4-16.7) |
| Hamster | M F | Oral(2) Oral(2) | 1100 (524-2310) 550 (249-1216) |
| Dog | M&F M&F M&F | Oral(3) Oral(2) S.C.(4) | ~ 40 > 80 > 5 |
* (1) UItrasonicalIy micronized aqueous suspension.
(2) Suspension in Tween 80 + Syrup.
(3) Capsules.
(4) Aqueous solution with 0.1 M tartaric acid.
** Due to the poor solubility of pimozide in an aqueous medium, few actual LD50's could be determined; the results also varied widely with the vehicle in which the drug was administered.
When death occurred, it was frequently delayed for several days.
The main toxic symptoms noted in all species were sedation, catalepsy, and prelethal clonic seizures. In dogs, doses as low as 0.16 mg/kg p.o. or i.v. induced catalepsy and sedation, while ataxia and clonic seizures were observed at 20 mg/kg or more orally.
Subacute Toxicity
In a 14-week study, pimozide was administered in the diet in doses of 0, 0.04, 0.31 and 2.5 mg/kg/day. Sedation, decreased food consumption and reduced body weight gain were noted in the 2.5 mg/kg group only. At this dosage level, there was also a significant decrease in the absolute organ weights for almost all organs and an increase in the relative weight of the brain. No significant gross or histopathological changes were observed.
Eight dogs were given pimozide orally in gradually increasing doses from 4 to 24 mg/kg/day. Six of the animals completed 4 to 5 weeks on the drug; one male dog died on day 15 after a week on 16 mg/kg/day (ataxia and daily convulsions), and another male was removed from the study on day 16 after a week on 24 mg/kg/day, following convulsions, emesis, anorexia and a very depressed state. All animals exhibited hyperactivity, convulsions, decreased food intake, emesis and weight loss. Some hemorrhages were observed on gross pathological examination, but there were no drug-related histopathological abnormalities.
Chronic Toxicity
In an 18-month study, rats received 0, 0.025, 0.21, 1.7 and 13.3 mg/kg/day pimozide in the diet. Health, behaviour and appearance were normal in the low- and medium-dose rats throughout the study. In the two high-dose groups, sedation was noted in the first week and persisted throughout the study in the highest dose group. Decreased food consumption and body weight gain occurred also from the first week of dosing in the two high-dose groups and persisted throughout the experiment.
The only pathological change clearly related to pimozide administration was mammary activation in most medium- and high-dose females and 2 high-dose males. This response is a common feature of all potent neuroleptics, and it was observed as early as 6 months after initiation of drug administration. Gonadal atrophy was noted terminally in a number of the males and some females. Necropsy at 18 months showed a decreased absolute weight of most organs of the animals in the two high-dose groups, while the relative weight of the brain in these groups was increased compared with controls. Significant histopathological changes were noted only in the two higher dosage groups. In the spleen there was a tendency to more hemosiderin and an increased number of lipofuscin-loaded macrophages and plasmocytes. The mesenteric lymph nodes also showed a tendency to an increased number of histiocytes in the sinuses and lipofuscin-loaded macrophages. The adrenals had minimal changes in the cortex, such as a slightly more fatty fasciculata and a few more lipofuscin-loaded cells in the reticularis in the 13.3 mg/kg dose animals. Females in both higher dosage groups had atrophic uteri and more mucified vaginas, while males had some mammary ductular development, as well as depressed secretory activity, inflammation and fibrosis of the prostate gland. Hypophyseal alterations consisted of increased numbers and signs of chronic stimulation of the erythrosinophils in both male and female rats and decreased numbers and signs of depression of the basophils in male animals. There was a greater tendency to fatty bone marrow in the highest dose animals.
In a one-year study, 40 Beagle dogs received pimozide orally 7 days a week at dose levels of 0, 0.5, 1.5 and 3 mg/kg/day. No deaths occurred at these dosages. In the treated groups, effects attributed to drug administration were mild sedation, muscular tremors, and mammary and gingival hyperplasia. Body weight loss was observed in the 3 mg/kg group only. Sedation and tremors occurred at first in most dogs, gradually decreasing in frequency and becoming rare or absent during the last nine months. Mammary hyperplasia occurred in females only and had completely regressed in all animals by the third month of the study. Lactation was observed in one high- and one medium-dose female. During the seventh month, gingival hyperplasia appeared in all high- and medium-dose dogs. The severity of the gingival hyperplasia was dose-related and the lesions persisted in all but one dog to the end of the study. There were no significant drug effects on hematology, coagulation, clinical chemistry, urinalysis, and ophthalmology. S-T and T-wave changes occurred more frequently in treated than control animals. Two animals from each group were kept for observation for 20 weeks following the termination of the one-year study.
Drug withdrawal had no apparent effect on the usual clinical parameters in these dogs. However, histopathological evaluation revealed gingival hyperplasia in all mid- and high-dose animals, although only one high-dose dog showed signs of regressed gingival hyperplasia macroscopically. Evidence of mammary hyperplasia was also observed in the mid- and high-dose females.
Genotoxicity
The results of mutagenic studies indicate no genotoxicity.
Pimozide did not have mutagenic activity in the Ames test with four bacterial test strains, in the mouse-dominant lethal test or in the micronucleus test in rats.
Carcinogenicity
Mice were given pimozide as a drug/diet mixture at dosage levels of 0, 0.62, 5.0 and 40.0 mg/kg/day for 18 months. A dose-related sedative effect was noted at the 5 and 40 mg/kg dose levels.
Carcinogenicity studies revealed no treatment related tumors in rats or male mice, but increased incidences of pituitary adenomas and mammary gland adenocarcinomas in female mice.
These histopathology changes in the mammary gland and pituitary are thought to be prolactin-mediated and have been shown in rodents following hyperprolactinemia by a variety of neuroleptic drugs with the relevance to humans being questionable.
In a 24-month carcinogenicity study in rats, pimozide was mixed with the animals' normal daily diet at dosage levels of 0, 0.31, 2.5 and 20 mg/kg/day.
Clinical observations included paraphimosis in high-dose males and emaciation in mid- dose females and high-dose animals of both sexes. In addition, the testes of male rats in all drug groups were undersized and/or soft.
Reproductive and developmental toxicology
In two studies, pimozide was administered to female Wistar rats for the first 21 days of pregnancy: 0.16, 0.63, 2.5 and 10 mg/kg/day subcutaneously in one study and 0.04, 0.31 and 2.5 mg/kg/day by gavage in the other study. At 2.5 and 10 mg/kg s.c. and 2.5 mg/kg p.o. the food intake and weight gain of dams were decreased and their mortality rates increased. The number of pregnancies in these high-dose groups was also decreased. In the 10 mg/kg s.c. group there were no live births, all fetuses being resorbed, while in the 2.5 mg/kg s.c. group the average litter size and % live fetuses were decreased and % resorptions increased. The average birth weight of pups in both 2.5 mg/kg groups was significantly lower than in the control group, and in the orally treated group, most pups showed retarded, although normal, embryological development. With the exception of the 0.63 mg/kg dams, which showed increased resorptions and lower birth weight of pups, no adverse effects were noted in the other treated groups. Pimozide, at doses of 0.04, 0.31 and 2.5 mg/kg/day, was also administered in the diet to male rats for 60 days pre-mating and to female rats for 14 days pre-mating and throughout pregnancy. No effect was noted on male or female fertility, but the estrus cycle of dosed females was increased. No abnormalities were observed among the offspring, although the percentage of stillborn was slightly increased in the high-dose group. In a fourth rat study, 0, 0.4, 0.31 and 2.5 mg/kg/day was administered in the diet to pregnant females through days 6 to 15 of pregnancy. No significant effects were noted in any of the treated groups, although in the high-dose group the average food intake of dams was lower, the % resorptions slightly increased, and the average litter size and birth weight of pups was slightly smaller. Finally, pimozide 0, 0.04, 0.31 and 2.5 mg/kg/day was given to female rats in the diet during the last third of pregnancy and lactation. There was a decrease in the weight gain of the 2.5 mg/kg dams during the last week of pregnancy. Compared with controls, the average litter size in this group was slightly smaller, the average birth weights slightly lower, and the % of stillborn pups considerably higher. The survival rate of pups at weaning was reduced in all the treated groups in a dose-related manner.
Two studies were conducted in rabbits, pimozide being administered during days 6 to 18 of pregnancy in both. In the first study, 0, 0.16, 0.31, 0.63, 1.25 and 2.5 mg/kg/day was given by gavage to Belgian hares. There was a dose-related decrease in the percent of females found pregnant at the end of the study. No other effects were observed apart from a decrease in litter size in the 1.25 mg/kg group and a slight decrease in the birth weights in the 0.63, 1.25 and 2.5 mg/kg groups. In the second study, New Zealand white rabbits received 0, 0.16, 0.63 and 2.5 mg/kg/day pimozide, also by gavage. In the high-dose group, mortality was increased and the number of pregnancies slightly reduced. A dose-related decrease in the body weight gain was noted in all treated groups. A dose-related decrease in the average litter size was also seen in all treated groups. In the 2.5 mg/kg group, the % resorptions was increased and the % live fetuses decreased, but no other abnormalities were observed.
17. Supporting Product Monographs
- 1) ORAP® (tablets, 2 mg and 4 mg), control 304190, product monograph, AA Pharma Inc. (2026-05-13)