


Product Monograph - PMS-Cilazapril
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| oral | tablet 1.0 mg, 2.5 mg, 5.0 mg | Colloidal Silicon Dioxide, Crospovidone, FD&C BlueNo. 1 Aluminum Lake (5 mg), FD&C Red No. 40 Aluminum Lake (5 mg), FD&C Yellow No. 6 Aluminum Lake (5 mg), Iron Oxide Yellow (1 mg), Iron Oxide Red (2.5 mg), Lactose Monohydrate Spray Dried, Polyethylene glycol, Magnesium Stearate, Microcrystalline Cellulose, Polyvinyl Alcohol-part Hydrolyzed, Titanium Dioxide, and Talc. |
INDICATIONS AND CLINICAL USE
pms-CILAZAPRIL (cilazapril) is indicated in the treatment of mild to moderate essential hypertension. pms-CILAZAPRIL may be used alone or in combination with thiazide-type diuretics. pms-CILAZAPRIL is also indicated in the treatment of congestive heart failure as an adjunctive therapy with digitalis and/or diuretics.
In using pms-CILAZAPRIL consideration should be given to the risk of angioedema (see WARNINGS AND PRECAUTIONS).
Hypertension
pms-CILAZAPRIL should normally be used in those patients in whom treatment with a diuretic or a beta-blocker was found ineffective or has been associated with unacceptable adverse effects.
pms-CILAZAPRIL can also be tried as an initial agent in those patients in whom use of diuretics and/or beta-blockers is contraindicated or in patients with medical conditions in which these drugs frequently cause serious adverse effects.
The safety and efficacy of cilazapril in renovascular hypertension has not been established and therefore, its use in this condition is not recommended.
The safety and efficacy of concomitant use of cilazapril with antihypertensive agents other than thiazide diuretics has not been established.
Congestive Heart Failure
pms-CILAZAPRIL is indicated in the treatment of congestive heart failure as adjunctive therapy in patients who have not responded adequately to digitalis and/or diuretics. There is limited data on New York Heart Association Class IV patients (see ACTIONS AND CLINICAL PHARMACOLOGY). Treatment with pms-CILAZAPRIL should be initiated in patients with congestive heart failure under close medical supervision.
Geriatrics:
Although clinical experience has not identified differences in response between the elderly and younger patients, greater sensitivity of some older individuals cannot be ruled out. In elderly patients with congestive heart failure on high diuretic dosage, the recommended starting dose of pms-CILAZAPRIL 0.5 mg must be strictly followed (see WARNINGS AND PRECAUTIONS, Geriatrics).
Pediatrics:
The safety and effectiveness of the use of cilazapril in children have not been established. Therefore, use in this age group is not recommended.
CONTRAINDICATIONS
pms-CILAZAPRIL is contraindicated in:
- Patients who are hypersensitive to cilazapril, any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- Patients with hereditary/idiopathic angioedema or a history of angioedema related to previous treatment with an angiotensin converting enzyme inhibitor (see WARNINGS AND PRECAUTIONS, General).
- Patients with anuria
- Patients with ascites
Women who are pregnant, intend to become pregnant, or of childbearing potential who
- are not using adequate contraception (see WARNINGS AND PRECAUTIONS: Serious Warnings and Precautions and Special Populations, Pregnant Women and ADVERSE REACTIONS).
- Nursing Women (see WARNINGS AND PRECAUTIONS: Special Populations, Nursing Women).
Combination with aliskiren-containing drugs in patients with:
- diabetes mellitus (type 1 or type 2)
- moderate to severe renal impairment (GFR ˂60 ml/min/1.73m2) (see WARNINGS and PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) and Renal, and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs).
- Patients with hereditary problems of galactose intolerance, glucose-galactose malabsorption, or the Lapp lactase deficiency as pms-CILAZAPRIL contains lactose (see WARNINGS AND PRECAUTIONS, Sensitivity/Resistance)
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions The use of pms-CILAZAPRIL (cilazapril) is contraindicated during pregnancy (see CONTRAINDICATIONS). When used in pregnancy, angiotensin converting enzyme (ACE) inhibitors can cause injury or even death of the developing fetus. Pregnant women should be informed of the potential hazards to the fetus and must not take pms-CILAZAPRIL during pregnancy. Patients planning pregnancy should be changed to alternative antihypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is detected, pms-CILAZAPRIL should be discontinued as soon as possible and, if appropriate, alternative therapy should be started (see WARNINGS AND PRECAUTIONS). |
Cardiovascular
Angioedema
Angioedema has been reported in patients treated with angiotensin-converting enzyme inhibitors including cilazapril. Angioedema has been associated with ACE inhibitors, with a reported incidence of 0.1-0.5%. Angioedema due to ACE inhibitors can present as recurrent episodes of facial swelling, which resolve on withdrawal, or as acute oropharyngeal edema and potentially life-threatening airway obstruction, which requires emergency treatment. Angioedema associated with laryngeal edema and/or shock may be fatal. If angioedema occurs, pms-CILAZAPRIL should be promptly discontinued and appropriate therapy instituted without delay. A variant form is angioedema of the intestine, which tends to occur within the first 24-48 hours of treatment.
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at an increased risk of angioedema while receiving an ACE inhibitor (see CONTRAINDICATIONS).
Concomitant use of ACE inhibitors with mammalian target of rapamycin (mTOR) inhibitors or dipeptidyl peptidase IV (DPP-IV) inhibitors may lead to an increased risk for angioedema. Caution should be used when using mTOR inhibitors or DPP-IV inhibitors concomitantly with ACE inhibitors (see DRUG INTERACTIONS, Drug-Drug Interactions).
Aortic Stenosis/Hypertrophic Cardiomyopathy
As with other ACE inhibitors, pms-CILAZAPRIL should be used with caution in patients with obstructive cardiac disorders (e.g. mitral stenosis, aortic stenosis, hypertrophic cardiomyopathy), since cardiac output cannot increase to compensate for systemic vasodilation, and there is a risk of severe hypotension.
There is concern on theoretical grounds that patients with aortic stenosis might be at particular risk of decreased coronary perfusion when treated with vasodilators because they do not develop as much afterload reduction.
Hypotension
pms-CILAZAPRIL , like other ACE inhibitors, may cause severe hypotension, especially when starting treatment, usually after the first dose or when the dose had been increased. First-dose hypotension is most likely to occur in patients whose renin-angiotensin-aldosterone system is activated, such as in renovascular hypertension or other causes of renal hypoperfusion, sodium or volume depletion, previous treatment with other vasodilators and in patients with dietary salt restriction, dialysis, diarrhea, or vomiting. These conditions can co-exist, particularly in severe heart failure.
Patients with congestive heart failure, especially those vigorously treated with loop diuretics, may experience excessive hypotension in response to ACE inhibitors. Because of the potential fall in blood pressure in these patients, therapy should be started under very close medical supervision. Such patients should be followed closely for the first two weeks of treatment and whenever the dose of cilazapril and/or diuretic is increased. Similar considerations may apply to patients with ischemic heart or cerebrovascular disease in whom an excessive fall in blood pressure could result in a myocardial infarction or cerebrovascular accident (see ADVERSE REACTIONS).
Patients at risk for hypotension should start treatment with cilazapril under medical supervision, with a low initial dose and careful titration. If possible, diuretic therapy should be discontinued temporarily.
Similar caution should be taken for patients with angina pectoris or cerebrovascular disease, in whom hypotension can cause myocardial or cerebral ischemia.
In patients with severe heart failure, whose renal function may depend on the activity of the renin-angiotensin-aldosterone system, treatment with ACE inhibitors, including pms-CILAZAPRIL , may be associated with oliguria and/or progressive azotemia and rarely acute renal failure and/or death.
Hypotension should be treated by placing the patient supine and with volume expansion. Cilazapril may be continued once the patient is volume replete, but should be given at a lower dose or discontinued if hypotension persists.
Dual Blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin converting enzyme (ACE) inhibitors, such as cilazapril, or of angiotensin receptor antagonists (ARBs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR ˂ 60 ml/min/1.73m2). Therefore, the use of pms-CILAZAPRIL in combination with aliskiren-containing drugs is contraindicated in these patients (see CONTRAINDICATIONS). Further, co-administration of ACE inhibitors, including pms-CILAZAPRIL , with other agents blocking the RAS, such as ARBs or aliskiren-containing drugs, is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia.
Ear/Nose/Throat
Cough
A dry, persistent cough, which usually disappears only after withdrawal or lowering of the dose of cilazapril, has been reported.
Such possibility should be considered as part of the differential diagnosis of the cough.
Endocrine and Metabolism
Diabetes
Administration of ACE inhibitors to patients with diabetes may potentiate the blood glucose lowering effect of oral hypoglycemic agents or insulin, especially in patients with renal impairment. In such patients, glucose levels should be carefully monitored during initiation of treatment with an ACE inhibitor.
Ethnicity
ACE inhibitors are less effective as antihypertensives in black-skinned patients of African descent. Black-skinned patients also have a higher risk of angioedema.
Hematologic
Neutropenia/Agranulocytosis
Agranulocytosis and bone marrow depression have been caused by ACE inhibitors. Cases of leucopenia and neutropenia have rarely been reported in patients treated with ACE Inhibitors.
Periodic monitoring of white blood cell counts should be considered in patients with collagen vascular disease and renal disease such as systemic lupus erythematosus and scleroderma, or in patients receiving immunosuppressive therapy, especially when they also have impaired renal function.
Hepatic
Patients With Impaired Liver Function
Hepatitis (hepatocellular and/or cholestatic), jaundice, elevations of liver enzymes and/or serum bilirubin have occurred during therapy with cilazapril in patients with or without pre-existing liver abnormalities. In most cases the changes were reversed on discontinuation of the drug.
Cases of liver function disorders, such as increased values of liver function tests (transaminases, bilirubin, alkaline phosphatase, gamma GT) and cholestatic hepatitis have been reported. Patients receiving cilazapril who develop jaundice or marked elevations of hepatic enzymes should discontinue cilazapril and receive appropriate medical follow-up.
There are no adequate studies in patients with cirrhosis and/or liver dysfunction. pms-CILAZAPRIL should be used with particular caution in patients with pre-existing liver abnormalities. In such patients baseline liver function tests should be obtained before administration of the drug and close monitoring of response and metabolic effects should apply.
In patients with liver cirrhosis (but without ascites) who require therapy for hypertension, cilazapril should be initiated at a lower dose and with great caution because significant hypotension may occur. In patients with ascites, cilazapril administration is not recommended.
Rarely, ACE inhibitors have been associated with a syndrome that starts with cholestatic jaundice and progresses to fulminant hepatic necrosis, and (sometimes) death. The mechanism of this syndrome is not understood.
Hyperkalemia
ACE inhibitors can cause hyperkalemia because they inhibit the release of aldosterone. The effect is usually not significant in patients with normal renal function. However, in patients with impaired renal function and/or in patients taking potassium supplements (including salt substitutes) or potassium-sparing diuretics, and especially aldosterone antagonists, hyperkalemia can occur. Potassium-sparing diuretics should be used with caution in patients receiving ACE inhibitors, and serum potassium and renal function should be monitored.
In clinical trials, elevated serum potassium (greater than 5.5 mEq/L) was observed in approximately 0.7% of hypertensive patients and 0.8% of congestive heart failure patients receiving cilazapril. In most cases these were isolated values which resolved despite continued therapy, however in one case the patient discontinued treatment. Risk factors for the development of hyperkalemia may include renal insufficiency, diabetes mellitus, and the concomitant use of agents to treat hypokalemia (see DRUG INTERACTIONS and ADVERSE REACTIONS).
Immune
Anaphylactoid Reactions during Membrane Exposure
Hemodialysis: Anaphylactoid reactions have been reported in patients dialysed with high-flux membranes (e.g., polyacrylonitrile [PAN], AN 69) and treated concomitantly with an ACE inhibitor. Dialysis should be stopped immediately if symptoms such as nausea, abdominal cramps, burning, angioedema, shortness of breath and severe hypotension occur. Symptoms are not relieved by antihistamines. In these patients, consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent.
Anaphylactoid Reactions during Low Density Lipoproteins (LDL) Apheresis
Patients receiving ACE inhibitors during LDL apheresis with dextran sulfate have experienced life-threatening anaphylactoid reactions. These reactions can be avoided by temporarily withholding ACE inhibitor therapy prior to each apheresis.
Anaphylactoid Reactions during Desensitization
There have been reports of patients experiencing sustained life threatening anaphylactoid reactions while receiving ACE inhibitors during desensitizing treatment with hymenoptera (bees, wasps) venom. In the same patients, these reactions have been avoided when ACE inhibitors were temporarily withheld for at least 24 hours, but they have reappeared upon inadvertent rechallenge.
Cilazapril use must be stopped before the start of desensitization therapy and must not be replaced by a beta-blocker.
Nitritoid Reactions-Gold
Nitritoid reactions (symptoms include facial flushing, nausea, vomiting, and symptomatic hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including cilazapril in combination with hydrochlorothiazide (see DRUG INTERATIONS).
Peri-Operative Considerations
Surgery/Anesthesia
In patients undergoing major surgery or during anesthesia with agents that produce hypotension, cilazapril blocks angiotensin II formation, secondary to compensatory renin release. This may result in arterial hypotension which can be corrected by volume expansion.
Renal
Renal Impairment
As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin aldosterone system, rarely, acute renal failure have been reported such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk and produce increases in blood urea nitrogen and/or serum creatinine. Although these alterations are usually reversible upon discontinuation of pms-CILAZAPRIL and/or diuretic therapy, cases of severe renal dysfunction and, rarely, acute renal failure have been reported. In susceptible patients, concomitant diuretic use may further increase risk.
When treated with cilazapril, patients with renal artery stenosis have an increased risk of renal insufficiency, including acute renal failure. Therefore, caution should be exercised in these patients.
Use of pms-CILAZAPRIL should include appropriate assessment of renal function.
Reduced dosages may be required for patients with renal impairment depending on their creatinine clearance (see DOSAGE AND ADMINISTRATION, Dosage Adjustment in Patients with Renal Impairment).
The use of ACE inhibitors – including pms-CILAZAPRIL – or ARBs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR ˂ 60 ml/min/1.73 m2). (See CONTRAINDICATIONS and DRUG INTERACTIONS, Dual Blockade of the Renin-Angiotension System (RAS) with ARBs, ACE inhibitors, or aliskiren-containing drugs).
Sensitivity/Resistance
Lactose Intolerance
pms-CILAZAPRIL tablets contain lactose monohydrate. Therefore, patients with hereditary galactose intolerance, Lapp lactase deficiency or glucose-galactose malabsorption should not take this medicine (see CONTRAINDICATIONS).
Special Populations
Pregnant Women:
ACE inhibitors can cause fetal and neonatal morbidity and mortality when administered to pregnant women. The use of cilazapril is contraindicated during pregnancy. Pregnant women should be informed of the potential hazards to the fetus and must not take pms-CILAZAPRIL during pregnancy (see CONTRAINDICATIONS). Patients planning pregnancy should be changed to alternative antihypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with ACE inhibitors should be stopped immediately, and, if appropriate, alternative therapy should be started.
Fetal exposure to ACE inhibitors during the first trimester of pregnancy has been reported to be associated with prematurity, an increased risk of malformations of the cardiovascular (atrial and/or ventricular septal defect, pulmonic stenosis, patent ductus arteriosus) and central nervous system (microcephaly, spina bifida) and of kidney malformations.
Exposure to ACE inhibitor therapy during the second and third trimesters is known to induce human fetotoxicity (decreased renal function, oligohydramnios, skull ossification retardation) and neonatal toxicity (hypotension, hyperkalemia, neonatal skull hypoplasia, intrauterine growth restriction, anuria, renal tubular dysplasia, reversible or irreversible renal failure and death). Oligohydramnios reported with the use of ACE inhibitors presumably resulted from decreased fetal renal function, associated with fetal limb contractures, craniofacial deformation, and hypoplastic lung development. Should exposure to ACE inhibitors have occurred from the second trimester of pregnancy, ultrasound examination of renal function and skull is recommended. Infants whose mothers have taken ACE inhibitors should be closely observed for hypotension.
Infants with a history of in utero exposure to ACE inhibitors should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit.
Dialysis clearance was estimated to be 2.4 L/h for cilazapril and 2.2-2.8 L/h for cilazaprilat.
Animal Data:
In fertility and general reproduction performance testing in rats, dosing with
50 mg/kg/day of cilazapril resulted in greater implantation losses, less viable fetuses, smaller pups, and dilatation of the renal pelvis in the pups. No teratogenic effects and no adverse effects on postnatal pup development were observed in rats and cynomolgus monkeys during embryotoxicity testing. In the rats, however, at a dose of 400 mg/kg/day, renal cavitation was observed in the pups. In peri- and post-natal toxicity testing in rats, dosing with 50 mg/kg/day resulted in greater pup mortality, smaller pups, and delayed unfolding of the pinna. On administration of 14C-cilazapril to pregnant mice, rats and monkeys, radioactivity was measured in the fetuses.
Nursing Women:
Animal data show the presence of cilazaprilat in rat milk. However, no information is available regarding the safety of cilazapril during breast-feeding in humans. pms-CILAZAPRIL must not be administered to nursing mothers (see CONTRAINDICATIONS) and alternative treatments with better established safety profiles during breast-feeding are preferable.
Ability to Drive and Use Machines:
Occasionally dizziness and fatigue may occur, especially when starting therapy (see ADVERSE REACTIONS).
Pediatrics:
The safety and effectiveness of the use of cilazapril in children have not been established. Therefore, use in this age group is not recommended.
Geriatrics:
Although clinical experience has not identified differences in response between the elderly and younger patients, greater sensitivity of some older individuals cannot be ruled out. In elderly patients with congestive heart failure on high diuretic dosage, the recommended starting dose of pms-CILAZAPRIL 0.5 mg must be strictly followed (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypotension, and DOSAGE AND ADMINISTRATION).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Headache and dizziness were the most frequently reported events in patients taking cilazapril for hypertension. In chronic heart failure clinical trials, dizziness and coughing were the most frequently reported events in patients taking cilazapril.
The most frequent drug-attributable adverse events observed in patients taking ACE inhibitors are cough, skin rash and renal dysfunction. Cough is more common in women and non-smokers. Where the patient can tolerate the cough, it may be reasonable to continue treatment. In some cases, reducing the dose may help.
Treatment-related adverse events severe enough to stop treatment occur in less than 5% of patients receiving ACE inhibitors.
Hypotension and postural hypotension may occur when starting treatment or increasing dose, especially in at-risk patients (see WARNINGS AND PRECAUTIONS).
Renal impairment and acute renal failure are more likely in patients with severe heart failure, renal artery stenosis, pre-existing renal disorders or volume depletion (see WARNINGS AND PRECAUTIONS).
Hyperkalaemia is most likely to occur in patients with renal impairment and those taking potassium sparing diuretics or potassium supplements.
The events of cerebral ischaemia, transient ischaemic attack and ischaemic stroke reported rarely in association with ACE inhibitors may be related to hypotension in patients with underlying cerebrovascular disease. Similarly, myocardial ischaemia may be related to hypotension in patients with underlying ischaemic heart disease.
Headache is a commonly reported adverse event, although the incidence of headache is greater in patients receiving placebo than in those receiving ACE inhibitors.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Cilazapril has been evaluated for safety in 5,450 patients treated for essential hypertension and 1,106 patients treated for congestive heart failure.
Of these, 2,586 hypertensive and 900 congestive heart failure patients were treated with Cilazapril in controlled clinical trials. Cilazapril was evaluated for long-term safety in 798 hypertensive and 264 congestive heart failure patients treated for one year or longer.
The most serious adverse reactions reported in the 5,450 patients treated with Cilazapril for hypertension included: angioedema/face edema (0.1%) (see WARNINGS AND PRECAUTIONS, Cardiovascular, Angioedema), postural hypotension (0.3%), orthostatic hypotension (2.1%), myocardial infarction (0.1%), cerebrovascular disorder (0.04%), renal failure (0.09%), and thrombocytopenic purpura (0.02%).
In the 1,106 patients treated with cilazapril for congestive heart failure, the most serious adverse reactions were: postural hypotension (1.6%), symptomatic hypotension (1.2%), myocardial infarction (0.3%), renal failure (0.1%) (see WARNINGS AND PRECAUTIONS, Renal), and cardiogenic shock (1 patient) (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypotension).
Two elderly male patients, with a history of previous myocardial infarctions, on high diuretic dosage (240 mg and 120 mg of furosemide daily, respectively) for congestive heart failure NYHA Class III died within 8 hours after the addition of a single dose of 2.5 mg of Cilazapril (see WARNINGS AND PRECAUTIONS, Cardiovascular, Hypotension).
Hypotension and syncope, each reported in 0.1% of the hypertensive patients treated with cilazapril, were reported in 2.1% and 0.8% of the congestive heart failure patients treated with cilazapril.
Discontinuation of therapy was required in 63 (2.4%) of the hypertensive patients and 143 (12.9%) of the congestive heart failure patients.
See Table 1 for the most frequent adverse reactions reported in controlled clinical trials (> 1% and more frequent than in placebo treated patients).
Table 1 The Most Frequent Adverse Reactions in Controlled Clinical Trials (> 1% and More Frequent than in Placebo Treated Patients) | ||||
| Hypertension n=2586 | Congestive Heart Failure n=900 | |||
| headache | 5.1% | 3.2% | ||
| dizziness | 3.0% | 8.2% | ||
| fatigue | 2.1% | 2.6% | ||
| cough | 1.8% | 7.5% | ||
| nausea | 1.3% | 2.9% | ||
| asthenia | 0.3% | 1.6% | ||
| palpitation | 0.2% | 1.2% | ||
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Other adverse reactions occurring in less than 1% of the 5,450 hypertension patients and the
1,106 congestive heart failure patients treated with cilazapril were:
Cardiovascular: Chest pain, angina pectoris, tachycardia, atrial fibrillation, arrhythmia, flushing.
In the patient population treated with cilazapril for congestive heart failure, there were reports of bradycardia, AV block, extra systoles, cardiac failure and cardiac decompensation.
Renal: Micturition frequency, polyuria, dysuria, uremia, renal pain.
Hematologic: Epistaxis, anemia, purpura.
Gastrointestinal: Dyspepsia, abdominal pain, diarrhea, constipation, vomiting, flatulence, GI bleeding, rectum bleeding, anorexia.
Dermatologic/Allergic: Rash (includes maculo-papular rash and erythematous rash), dermatitis, pruritus, urticaria, angioedema (including face edema).
Nervous System: Increased sweating, paresthesia, hypoesthesia, impotence, decreased libido, depression, anxiety, dry mouth, vertigo, migraine, tremor, dysphonia, ataxia, confusion, somnolence, insomnia, nervousness.
Musculoskeletal: Myalgia, leg cramps, arthralgia.
Special Senses: Tinnitus, abnormal vision, photophobia, conjunctivitis, taste perversion.
Respiratory: Rhinitis, sinusitis, pharyngitis, bronchitis, respiratory tract infection, dyspnea, bronchospasm.
In the congestive heart failure patient database the overall incidence of dyspnea was 3.1%. Dyspnea however was less frequent after cilazapril than after placebo.
Metabolic: Gout.
Body as a Whole: Malaise, hot flushes, pain, edema, rigors.
Abnormal Hematologic and Clinical Chemistry Findings
Hematology:
Patients had clinically relevant changes in platelet (0.4% and 0.7%), neutrophil (1.9% and 1.4%) or white blood cell counts (1.3% and 0.7%) while treated for hypertension and congestive heart failure respectively.
Leucopenia and neutropenia:
Leucopenia was observed in 0.2% (10/3,580) and 0% (0/1,163) and neutropenia in 0.4% (22/5,720) and 0.6% (7/1,163) of the hypertensive and congestive heart failure patients respectively. Most of these were single transient occurrences; one case with two successive abnormalities showed no associated clinical symptoms.
Liver Function Tests:
Clinically relevant changes in the values associated with liver function (SGOT, SGPT, GGTP, LDH, total bilirubin and alkaline phosphatase) occurred in 0.1% (bilirubin) to 1.1% (SGPT, GGTP) of the hypertensive patients and in 0.8% (LDH) to 2.9% (SGPT) of the congestive heart failure patients. Most of these abnormalities were transient. See WARNINGS AND PRECAUTIONS, Hepatic, Patients with Impaired Liver Function.
Renal:
Clinically relevant changes in renal function test results (BUN or serum creatinine concentrations) occurred in 0.6% or less of the hypertensive patients and in 2.6% and 0.9% respectively of the congestive heart failure patients.
Hyperkalemia: (see WARNINGS AND PRECAUTIONS)
Creatinine: Serum creatinine values > 2 mg/dL were reported in 1.3% (44/3,468) of the hypertensive patients. Two thirds of these patients had renal impairment at baseline. Serum creatinine values >2.8 mg/dL were reported in 0.4% (5/1,163) of the congestive heart failure patients. Of these, four of the five had abnormal serum creatinine values at baseline.
Proteinuria (>2+ dipstick reaction or excretion of > 1 g/24h): Proteinuria considered remotely, possibly or probably related to therapy was reported in 0.5% (17/3,421) of the hypertensive patients. Five patients had prior renal impairment. In congestive heart failure patients, 1.4% (16/1,106) experienced potentially clinically relevant proteinuria.
Other: In congestive heart failure patients, hyperglycemia considered remotely, possibly or probably related to therapy was reported in 0.2% (2/1,106) patients.
Post-Market Adverse Drug Reactions
Cilazapril is usually well tolerated. In most cases, side effects are transient, mild or moderate in degree, and do not require discontinuation of therapy. The most common adverse effects include dry cough, rash, hypotension, dizziness, fatigue, headache, and nausea, dyspepsia and other gastrointestinal disturbances.
The following adverse reactions have been seen in association with cilazapril and/or other ACE inhibitors.
Frequency categories are as follows: Very common ≥ 1/10
Common ≥ 1/100 and < 1/10
Uncommon ≥ 1/1,000 and < 1/100
Rare < 1/1,000
Blood and lymphatic systems disorders
Blood disorders have been reported with ACE Inhibitors and include neutropenia and agranulocytosis (especially in patients with renal failure and those with collagen vascular disorders such as systemic lupus erythematosus and scleroderma), thrombocytopenia, and hemolytic anemia.
Rare: Neutropenia, agranulocytosis, thrombocytopenia, anemia
Cardiac disorders
Pronounced hypotension may occur at the start of therapy with ACE inhibitors, particularly in patients with heart failure and in sodium- or volume depleted patients. Myocardial infarction and stroke have been reported and may relate to severe falls in blood pressure in patients with ischaemic heart disease or cerebrovascular disease. Other cardiovascular effects that have occurred include tachycardia, palpitations, and chest pain.
Uncommon: Angina pectoris, tachycardia, palpitations
Rare: Myocardial infarction
Vascular disorders
Common: Dizziness
Uncommon: Hypotension (sometimes severe, see WARNINGS AND PRECAUTIONS) Symptoms of hypotension may include syncope, weakness, dizziness and visual impairment.
Respiratory, thoracic and mediastinal disorders
Common: Cough (sometimes severe)
Gastrointestinal disorders
As for other ACE inhibitors, isolated cases of pancreatitis, in some cases fatal, have been reported in patients treated with cilazapril.
Common: Nausea
Rare: Pancreatitis
Hepatobiliary disorders
Rare: Abnormal liver function test including transaminases, bilirubin, alkaline phosphatase, gamma GT) and cholestatic hepatitis with or without necrosis.
Immune system disorders
As with other ACE inhibitors, angioneurotic edema has been reported, although rarely, in patients receiving cilazapril. Since this syndrome can be associated with laryngeal edema, pms-CILAZAPRIL should be discontinued and appropriate therapy instituted without delay when involvement of the face, lips, tongue, glottis and/or larynx occurs.
Uncommon: Angioedema (may involve the face, lips, tongue, larynx or gastrointestinal tract) (see WARNINGS AND PRECAUTIONS).
Rare: Anaphylaxis (see WARNINGS AND PRECAUTIONS), Lupus-like syndrome (symptoms may include vasculitis, myalgia, arthralgia/arthritis, positive antinuclear antibodies, increased erythrocyte sedimentation rate, eosinophilia and leukocytosis).
Nervous system disorders Common: Headache Uncommon: Dysgeusia
Rare: Transient ischaemic attack, ischaemic stroke (may be related in some cases to hypotension in patients with underlying cerebrovascular disease.)
Skin and subcutaneous tissue disorders
Skin rashes (including pemphigus, Stevens-Johnson syndrome, erythema multiforme, and toxic epidermal necrolysis) may occur; photosensitivity, alopecia, and other hypersensitivity reactions have also been reported.
Uncommon: Rash
Rare: Toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome, erythema multiforme, pemphigus, bullous pemphigoid, exfoliative dermatitis, psoriaform dermatitis, psoriasis (exacerbation), lichen planus, urticaria, vasculitis/purpura, photosensitivity reactions, alopecia, onycholysis.
Renal and urinary disorders
Cases of acute renal failure have been reported in patients with severe heart failure, renal artery stenosis or renal disorders (see WARNINGS AND PRECAUTIONS: Renal Impairment).
Rare: Renal impairment, acute renal failure, blood creatinine increased, blood urea increased, hyperkalemia, hyponatremia (see WARNINGS AND PRECAUTIONS, Renal).
General disorders and administration site conditions
Common: Fatigue
Hypotension may occur when starting treatment or increasing dose, especially in at-risk patients (see WARNINGS AND PRECAUTIONS). Symptoms of hypotension may include syncope, weakness, dizziness and visual impairment.
Renal impairment and acute renal failure are more likely in patients with severe heart failure, renal artery stenosis, pre-existing renal disorders or volume depletion (see WARNINGS AND PRECAUTIONS).
Hyperkalemia is most likely to occur in patients with renal impairment and those taking potassium sparing diuretics or potassium supplements.
The events of transient ischemic attack and ischemic stroke reported rarely in association with ACE inhibitors may be related to hypotension in patients with underlying cerebrovascular disease. Similarly, myocardial ischemia may be related to hypotension in patients with underlying ischemic heart disease.
DRUG INTERACTIONS
Drug-Drug Interactions
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
Agents increasing serum potassium (potassium sparing diuretics, potassium supplements or potassium-containing salt substitutes) | CT, C | Hyperkalemia may occur in some patients treated with cilazapril. Potassium sparing diuretics (e.g. spironolactone, triamterene, or amiloride), potassium supplements, or potassium- containing salt substitutes may lead to significant increases in serum potassium impairment (see ACTION AND CLINICAL PHARMACOLOGY and WARNINGS AND PRECAUTIONS). | Therefore, the combination of cilazapril with agents increasing serum potassium (potassium sparing diuretics, potassium supplements or potassium-containing salt substitutes) is not recommended (see WARNINGS AND PRECAUTIONS). If concomitant use is indicated severe hyperkalemia may occur they should be used with caution and with frequent monitoring of serum potassium. |
| Antidiabetics | CT* CT, CT* | Concomitant administration of ACE inhibitors and antidiabetic medicines (insulins, oral hypoglycaemic agents) may cause an increased blood-glucose lowering effect with risk of hypoglycemia. This phenomenon appeared to be more likely to occur during the first weeks of combined treatment and in patients with renal impairment. Concomitant use of ACE inhibitors with DPP-IV inhibitors may lead to an increased risk for angioedema. | Close monitoring of blood glucose levels is advised. See WARNINGS AND PRECAUTIONS, Cardiovascular, Angioedema |
| Allopurinol, immunosupressants, and steroid medicines | T | Concomitant administration with ACE inhibitors may lead to an increased risk of hematological reactions. | Increased likelihood of hematological reactions. |
| Digoxin | CT | No pharmacodynamic or pharmacokinetic interactions (and no increase in plasma digoxin concentrations) were observed when cilazapril therapy (5 mg once daily) was administered to healthy volunteers receiving digoxin (0.25 mg twice daily). |
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
Diuretic therapy (thiazide or loop diuretics) | CT | Patients concomitantly taking ACE inhibitors and diuretics, and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy. | The possibility of hypotensive effects after the first dose of cilazapril can be minimized by either discontinuing the diuretic, or increasing the salt intake prior to initiation of treatment with cilazapril. If it is not possible to discontinue the diuretic, the starting dose of cilazapril should be reduced and the patient should be closely observed for several hours following the initial dose and until blood pressure has stabilized (see WARNINGS AND PRECAUTIONS and DOSAGE AND ADMINISTRATION). |
| Gold | C | Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy. | Use with caution when cilazapril and hydrochlorothiazide is coadministered with gold salts. |
| Lithium Salts | CT | Reversible increases in serum lithium concentrations have been reported during concomitant administration of lithium with ACE inhibitors. Concomitant use of thiazide diuretics may increase the risk of lithium toxicity and enhance the already increased risk of lithium toxicity with ACE inhibitors. Lithium toxicity, including CNS symptoms, ECG changes and renal failure, has occurred in patients taking ACE inhibitors. Proposed mechanisms include decreased renal elimination of lithium due to decreased aldosterone secretion or decreased renal function. | Lithium should generally not be given with ACE inhibitors. Use of cilazapril with lithium is not recommended, but if the combination proves necessary, careful and frequent monitoring of serum lithium levels should be performed. |
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
Non-steroidal anti- inflammatory medicinal products (NSAIDs) | CT | When ACE inhibitors, including cilazapril, are administered simultaneously with non-steroidal anti-inflammatory drugs (i.e. acetylsalicylic acid at anti- inflammatory dosage regimens, COX-2 inhibitors and non- selective NSAIDs), attenuation of the antihypertensive effect may occur. Concomitant use of ACE inhibitors, including cilazapril, and NSAIDs may lead to an increased risk of worsening of renal function, including possible acute renal failure, and an increase in serum potassium, especially in patients with poor pre-existing renal function. The introduction of therapy with cilazapril (2.5 mg once daily) in hypertensive patients receiving indomethacin (50 mg twice daily) did not result in a reduction in blood pressure. However, the introduction of therapy with indomethacin (50 mg twice daily) in hypertensive patients receiving cilazapril (2.5 mg once daily) did not attenuate the blood pressure lowering effects of cilazapril. The interaction does not appear to occur in patients treated with cilazapril prior to the administration of a NSAID. There was no evidence of a pharmacokinetic interaction between cilazapril and indomethacin. | The combination should be administered with caution, especially in the elderly. Patients should be adequately hydrated and consideration should be given to monitoring for signs of worsening heart failure or renal function or loss of blood pressure control after initiation of concomitant therapy, and periodically thereafter. |
Other antihypertensive agents | CT | An additive effect may be observed when cilazapril is administered in combination with other blood pressure-lowering agents (e.g., diuretics, beta-adrenergic blocking drugs). Agents affecting sympathetic activity (e.g., ganglionic blocking agents or adrenergic neuron blocking agents) should be used with caution. Sympathomimetics may reduce the antihypertensive effects of ACE inhibitors. | These drugs should be introduced at a low initial dosage, and used with caution. Close monitoring of blood pressure is advised and dose/regimen adjustment should be considered if necessary. |
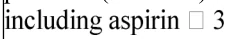 g/day
| Proper Name | Ref. | Effect | Clinical comment |
|---|---|---|---|
Tricyclic antidepressants/antipsych otics/anesthetics/narcotic s | C | Concomitant use of anesthetics during the course of general anesthesia, as well as tricyclic antidepressants and antipsychotics with ACE inhibitors may result in further reduction of blood pressure (see WARNINGS AND PRECAUTIONS). | Close monitoring of blood pressure is advised and dose/regimen adjustment should be considered if necessary. |
| Dual blockade of the Renin-Angiotensin-System (RAS) with ACE inhibitors, ARBs or aliskiren-containing drugs | CT | Dual Blockade of the Renin-Angiotensin-System (RAS) with ACE inhibitors, ARBs or aliskiren containing drugs is contraindicated in patients with diabetes and/or renal impairment, and is generally not recommended in other patients, since such treatment has been associated with an increased incidence of severe hypotension, renal failure, and hyperkalemia. | See CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Dual Blockade of the Renin-Angiotensin System (RAS) |
| mTOR inhibitors | C, RCS | Concomitant use of ACE inhibitors with mTOR inhibitors may lead to an increased risk for Angioedema. | See WARNINGS AND PRECAUTIONS, Cardiovascular, Angioedema |
Legend: C = Case Study; RCS = Retrospective Cohort Study; CT = Clinical Trial; T = Theoretical, CT*: Epidemiological studies.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Dosage of pms-CILAZAPRIL (cilazapril) must be individualized.
Initiation of therapy requires consideration of recent antihypertensive drug treatment, the extent of blood pressure elevation, salt restriction, and other pertinent clinical factors. The dosage of other antihypertensive agents being used with pms-CILAZAPRIL may need to be adjusted.
The dose should always be taken at about the same time each day.
Recommended Dose and Dosage Adjustment
Hypertension:
Monotherapy:
The recommended initial dose of pms-CILAZAPRIL is 2.5 mg once daily. Dosage should be adjusted according to blood pressure response, generally, at intervals of at least two weeks. The usual dose range for pms-CILAZAPRIL is 2.5 to 5 mg once daily. Minimal additional blood pressure lowering effects were achieved with a dose of 10 mg once daily. A dose of 10 mg should not be exceeded.
In most patients, the antihypertensive effect of cilazapril is maintained with a once a day dosing regimen. In some patients treated once daily, the antihypertensive effect may diminish toward the end of the dosing interval. This can be evaluated by measuring blood pressure just prior to dosing to determine whether satisfactory control is being maintained for 24 hours. If it is not, either twice daily administration with the same total daily dose, or an increase in dose should be considered. If blood pressure is not adequately controlled with pms-CILAZAPRIL alone a non-potassium-sparing diuretic may be administered concomitantly. After the addition of a diuretic, it may be possible to reduce the dose of pms-CILAZAPRIL.
Patients with a strongly activated renin-angiotensin-aldosterone system (in particular, salt and/or volume depletion, cardiac decompensation or severe hypertension) may experience an excessive drop in blood pressure following the initial dose. A lower starting dose of 0.5 mg once daily is recommended in such patients and the initiation of treatment should take place under medical supervision.
Concomitant Diuretic Therapy:
In patients receiving diuretics, pms-CILAZAPRIL therapy should be initiated with caution, since they are usually volume depleted and more likely to experience hypotension following ACE inhibition. Whenever possible, all diuretics should be discontinued two to three days prior to the administration of pms-CILAZAPRIL to reduce the likelihood of hypotension (see WARNINGS AND PRECAUTIONS). If this is not possible because of the patient’s condition, pms-CILAZAPRIL should be started at 0.5 mg once daily and the blood pressure closely monitored after the first dose until stabilized. Thereafter, the dose should be adjusted according to individual response.
Dosage in Elderly Patients (Over 65 Years)
pms-CILAZAPRIL treatment should be initiated with 1.25 mg (half of a 2.5 mg tablet) once daily or less, depending on the patient’s volume status and general condition. Thereafter, the dose of pms-CILAZAPRIL must be adjusted according to individual tolerability, response, and clinical status.
Dosage Adjustment in Renal Impairment
(see WARNINGS AND PRECAUTIONS, Immune, Anaphylactoid Reactions during Membrane Exposure)
See Table 2 for the dose schedules recommended in patients with hypertension.
Table 2 Recommended Dosage Schedule for Patients with Hypertension and Renal Impairment | ||
| Creatinine Clearance | Initial Dose of pms-CILAZAPRIL | Maximal Dose of pms-CILAZAPRIL |
| > 40 mL/min | 1 mg once daily | 5 mg once daily |
| 10-40 mL/min | 0.5 mg once daily | 2.5 mg once daily |
| < 10 mL/min | Not recommended. | |
Dosage Adjustment in Hepatic Impairment
In patients with liver cirrhosis (but without ascites) who require therapy for hypertension, cilazapril should be dosed with great caution not exceeding 0.5 mg/day accompanied by a careful monitoring of the blood pressure, because severe hypotension may occur. In patients with ascites, cilazapril administration is not recommended (see WARNINGS AND PRECAUTIONS).
Congestive Heart Failure
pms-CILAZAPRIL can be used as adjunctive therapy with digitalis and/or diuretics in patients with congestive heart failure. Therapy should be initiated under close medical supervision. Blood pressure and renal function should be monitored both before and during treatment with cilazapril because severe hypotension and more rarely, renal failure have been reported (see WARNINGS and PRECAUTIONS).
Initiation of therapy requires consideration of recent diuretic therapy and the possibility of severe salt/volume depletion. If possible, the dose of diuretic should be reduced before beginning treatment, to reduce the likelihood of hypotension. Serum potassium should also be monitored (see WARNINGS AND PRECAUTIONS, DRUG INTERACTIONS).
Therapy with pms-CILAZAPRIL should be initiated with a recommended starting dose of 0.5 mg once daily under close medical supervision. In elderly patients with congestive heart failure on high diuretic dosage the recommended starting dose of pms-CILAZAPRIL 0.5 mg must be strictly followed (see WARNINGS AND PRECAUTIONS).
The dose should be increased to the lowest maintenance dose of 1 mg daily, usually within a 5 day period, according to tolerability and clinical status. Further titration within the usual maintenance dose of 1 mg to 2.5 mg daily should be carried out based on patients response, clinical status and tolerability.
The usual maximum dose is 2.5 mg once daily. A few patients have been titrated to 5 mg once daily with some additional benefits being achieved. However only limited data is available in congestive heart failure patients treated with 5 mg once daily.
Dosage Adjustment in Patients with Congestive Heart Failure and Renal Impairment or
Hyponatremia:
Reduced dosage may be required for patients with congestive heart failure and renal impairment or hyponatremia depending on the creatinine clearance. See Table 3 below.
Table 3 Recommended Dosage Schedule for Patients with Congestive Heart Failure and Renal Impairment or Hyponatremia | ||
| Creatinine Clearance | Initial Dose of pms-CILAZAPRIL | Maximal Dose of pms-CILAZAPRIL |
| > 40 mL/min | 0.5 mg once daily | 2.5 mg once daily |
| 10-40 mL/min | 0.25 - 0.5 mg once daily | 2.5 mg once daily |
| < 10 mL/min | Not recommended. | |
OVERDOSAGE
Limited data are available with regard to overdosage in humans. Symptoms associated with overdosage of ACE inhibitors may include hypotension, which may be severe, circulatory shock, electrolyte disturbances including hyperkalaemia and hyponatraemia, renal impairment with metabolic acidosis, renal failure, hyperventilation, tachycardia, palpitations, bradycardia, dizziness, anxiety and cough.
The recommended treatment of overdosage is intravenous infusion of sodium chloride 9 mg/ml (0.9%) solution. If hypotension occurs, the patient should be placed in the shock position. If available, treatment with angiotensin II infusion and/or intravenous catecholamines may also be considered. Specific therapy with angiotensinamide may be considered if conventional therapy is ineffective.
Pacemaker therapy is indicated for therapy-resistant bradycardia. Vital signs, serum electrolytes and creatinine concentrations should be monitored continuously.
Hemodialysis removes cilazapril and cilazaprilat from the general circulation to a limited extent.
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action / Pharmacodynamics
Cilazapril is an angiotensin converting enzyme (ACE) inhibitor, which is used in the treatment of hypertension and congestive heart failure.
Cilazapril suppresses the renin-angiotensin-aldosterone system and thereby reduces both supine and standing systolic and diastolic blood pressures. Renin is an enzyme that is released by the kidneys into the circulation to stimulate the production of angiotensin I, an inactive decapeptide. Angiotensin I is converted by angiotensin converting enzyme (ACE) to angiotensin II, a potent vasoconstrictor. Angiotensin II also stimulates aldosterone secretion, leading to sodium and fluid retention. After absorption, cilazapril, a pro-drug, is hydrolysed to cilazaprilat, the active metabolite, which prevents the conversion of angiotensin I to angiotensin II by inhibition of ACE. Following the administration of cilazapril, plasma ACE activity is inhibited more than 90% within two hours at therapeutic doses. Plasma renin activity (PRA) and angiotensin I concentrations are increased and angiotensin II concentrations and aldosterone secretion are decreased. The increase in PRA comes as a result of the loss of negative feedback on renin release caused by the reduction in angiotensin II. The decreased aldosterone secretion may lead to small increases in serum potassium along with sodium and fluid loss. In patients with normal renal function, serum potassium usually remains within the normal range during cilazapril treatment. Mean serum potassium values increased by 0.02 mEq/L in patients with a normal baseline serum creatinine and by 0.11 mEq/L in patients with a raised serum creatinine. In patients concomitantly taking potassium-sparing diuretics, potassium levels may rise.
ACE is identical to kininase II. Therefore, cilazapril may interfere with the degradation of the vasodepressor peptide bradykinin. The role that this plays in the therapeutic effects of cilazapril is unknown.
Hypertension
The antihypertensive effect of cilazapril is usually apparent within the first hour after administration, with maximum effect observed between three and seven hours after dosing. Supine and standing heart rates remain unchanged. Reflex tachycardia has not been observed. Small, clinically insignificant alterations of heart rate may occur.
At recommended doses, the effect of cilazapril in hypertensive patients and in patients with congestive heart failure is maintained for up to 24 hours. In some patients, blood pressure reduction may diminish toward the end of the dosage interval. Blood pressure should be assessed after two to four weeks of therapy, and dosage adjusted if required. The antihypertensive effect of cilazapril is maintained during long-term therapy. No rapid increase in blood pressure has been observed after abrupt withdrawal of cilazapril.
The antihypertensive effect of angiotensin converting enzyme inhibitors, including cilazapril is generally lower in black patients than in non-blacks. Racial differences in response are no longer evident when cilazapril is administered in combination with hydrochlorothiazide.
In hypertensive patients with moderate to severe renal impairment, the glomerular filtration rate and renal blood flow remained in general unchanged with cilazapril.
Congestive Heart Failure
In patients with congestive heart failure the renin-angiotensin-aldosterone and the sympathetic nervous systems are generally activated leading to enhanced systemic vasoconstriction and to the promotion of sodium and water retention. By suppressing the renin-angiotensin-aldosterone system, cilazapril improves loading conditions in the failing heart by reducing systemic vascular resistance (afterload) and pulmonary capillary wedge pressure (preload) in patients on diuretics and/or digitalis. The onset of action of cilazapril occurs within 1-2 hours, reaching its maximum effect within 2-4 hours after the first dose. The exercise tolerance of these patients was increased and was associated with an improvement of clinical symptomatology. Patients studied belonged primarily to New York Heart Association Class II and III. The effect of cilazapril on survival in patients with heart failure has not been evaluated.
Pharmacokinetics
Cilazapril is well absorbed and rapidly converted to the active form, cilazaprilat. Peak plasma concentrations, and times to peak plasma concentrations for cilazapril and cilazaprilat following the oral administration of 0.5 to 5 mg cilazapril are given below.
Table 4 Peak Plasma Concentrations and Times to Peak Plasma Concentrations for Cilazapril and Cilazaprilat | ||||||||||
Oral Dose (mg) | Cilazapril | Cilazaprilat | ||||||||
Cmax (ng/mL) | tmax (h) | Cmax (ng/mL) | tmax (h) | |||||||
0.5 1.0 2.5 5.0 | 17.0 33.9 82.7 182.0 | 1.1 1.1 1.1 1.0 | 5.4 12.4 37.7 94.2 | 1.8 1.8 1.9 1.6 | ||||||
Maximum plasma concentrations of cilazaprilat are reached within two hours after administration of cilazapril.
Maximum ACE inhibition is greater than 90% after 1 to 5 mg cilazapril. Maximum ACE inhibition is 70 to 80% after 0.5 mg cilazapril. Dose proportionality is observed following the administration of 1 to 5 mg cilazapril. Apparent non-proportionality is observed at 0.5 mg reflective of the binding to ACE. The higher doses of cilazapril are associated with longer duration of maximum ACE inhibition.
The absolute bioavailability of cilazaprilat after oral administration of cilazapril is 57% based on urinary recovery data. (The absolute bioavailability of cilazaprilat after oral administration of cilazaprilat is 19%). Ingestion of food immediately before the administration of cilazapril reduces the average peak plasma concentration of cilazaprilat by 29%, delays the peak by one hour and reduces the bioavailability of cilazaprilat by 14%. These pharmacokinetic changes have little influence on plasma ACE inhibition.
Cilazaprilat is eliminated unchanged by the kidneys. The total urinary recovery of cilazaprilat after intravenous administration of 2.5 mg is 91%. Total clearance is 12.3 L/h and renal clearance is 10.8 L/h. The total urinary recovery of cilazaprilat following the oral administration of 2.5 mg cilazapril is 52.6%.
Half-lives for the periods 1 to 4 hours and 1 to 7 days after the intravenous administration of 2.5 mg cilazaprilat are 0.90 and 46.2 hours respectively. These data suggest the saturable binding of cilazaprilat to ACE. The early elimination phase corresponds to the clearance of free drug. During the terminal elimination phase, almost all of the drug is bound to enzyme. Following the oral administration of 0.5, 1, 2.5 and 5 mg cilazapril, terminal elimination phase half-lives for cilazaprilat are 48.9, 39.8, 38.5 and 35.8 h respectively.
After multiple dose, daily administration of 2.5 mg cilazapril for 8 days, pharmacokinetic parameter values for intact cilazapril after the last dose are similar to the first dose. For cilazaprilat, peak plasma concentrations are achieved at the same time but are 30% higher after the last dose. Trough plasma concentrations and areas under the curve are 20% higher. The terminal elimination phase half-life after the last dose is 53.8 h. The effective half-life of accumulation for cilazaprilat is 8.9 h.
Special Populations and Conditions
Congestive Heart Failure: In patients with congestive heart failure the clearance of cilazaprilat is correlated with the creatinine clearance. Thus, dosage adjustments beyond those recommended for patients with impaired renal functions (see DOSAGE AND ADMINISTRATION, Congestive Heart Failure) should not be necessary.
Geriatrics: Following the administration of 1 mg cilazapril to healthy elderly and young volunteers, the elderly group experienced greater peak plasma concentrations of cilazaprilat and areas under the curve (39% and 25%, respectively) and lower total clearance and renal clearance (20% and 28%, respectively) than the younger volunteers.
Hepatic Insufficiency: Following the administration of 1 mg cilazapril in patients with moderate to severe compensated liver cirrhosis, peak plasma concentrations of cilazapril and cilazaprilat are increased (57% and 28% respectively), attained 30 minutes and 45 minutes earlier, and total clearances are decreased (51% and 31% respectively), in comparison to healthy subjects.
The renal clearance and early and terminal elimination phase half-lives of cilazaprilat are decreased 52%, 42% and 62% respectively.
Renal Insufficiency: In patients with renal impairment, peak plasma concentrations of cilazaprilat, times to peak plasma concentrations, early elimination phase half-lives, areas under the curve and 24 hour plasma concentrations all increase as creatinine clearance decreases. The changes in these parameters are small for patients with creatinine clearances of 40 mL/min or more. Cilazaprilat clearance (total and renal) decreases in parallel with creatinine clearance. Cilazaprilat is not eliminated in patients with complete renal failure. Hemodialysis reduces concentrations of both cilazapril and cilazaprilat to a limited extent.
STORAGE AND STABILITY
pms-CILAZAPRIL tablets should be stored between 15oC and 30oC in a tightly closed container.
SPECIAL HANDLING INSTRUCTIONS
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater, and disposal through household waste should be avoided. Use established ‘collection systems' if available in your location.
DOSAGE FORMS, COMPOSITION AND PACKAGING
pms-CILAZAPRIL (cilazapril) is available as oval-shaped, coated, biconvex tablets in the following strengths as described below:
1 mg: Yellow, scored on one side and debossed with “P” logo and “1" on the other side.
2.5 mg: Pinkish-brown, scored on one side and debossed with “P” logo and “2.5" on the other side.
5 mg: Reddish-brown, scored on one side and debossed with “P” logo and “5" on the other side.
Supplied: in HDPE bottles of 100 tablets for the 1 mg and 2.5 mg strengths, and in 100 tablets and 500 tablets for the 5 mg strength.
Composition
pms-CILAZAPRIL (cilazapril) Tablets contain 1 mg, 2.5 mg or 5 mg of anhydrous cilazapril, as cilazapril monohydrate, respectively. The tablets also contain the following non-medical ingredients (alphabetically): Colloidal Silicon Dioxide, Crospovidone, FD&C Blue No. 1 Aluminum Lake (5 mg), FD&C Red No. 40 Aluminum Lake (5 mg), FD&C Yellow No. 6 Aluminum Lake (5 mg), Iron Oxide Yellow (1 mg), Iron Oxide Red (2.5 mg), Lactose Monohydrate Spray Dried, Polyethylene glycol, Magnesium Stearate, Microcrystalline Cellulose, Polyvinyl Alcohol-part Hydrolyzed, Titanium Dioxide, and Talc.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: cilazapril monohydrate
Chemical Name: 9(s)-[1(s)-(ethoxycarbonyl)-3-phenylpropylaminol]-octahydro-10-oxo- 6H-pyridazo [1,2-a][1,2] diazepine-carboxylic acid monohydrate
Molecular formula: C22H31N3O5•H2O
Molecular mass: 435.5 g/mol
Structural formula:
O O CH3 NH O N N COOH H H H . H2O
Physicochemical properties: Cilazapril is a white to off-white crystalline powder. Cilazapril is slightly soluble in water (25°C), the solubility is 0.5 g/100 mL. The partition coefficient is 0.8 (octanol-pH 7.4 buffer 22°C), the melting point is 98°C with decomposition.
CLINICAL TRIALS
Comparative Bioavailability Studies
Bioavailability:
A comparative, single-dose, blinded, two-way crossover bioavailability study was performed under fasting conditions on Cilazapril tablets using Pharmascience Inc. pms-CILAZAPRIL 5 mg tablets versus the reference product, INHIBACE® 5 mg Tablets, by Hoffmann-LaRoche Limited Canada,. The pharmacokinetic data calculated for the pms-CILAZAPRIL 5 mg tablets and INHIBACE® 5 mg tablets formulation are tabulated below:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA Cilazapril (1 x 5 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng.hr/mL) | 172.21 185.53 (42.41) | 174.20 185.68 (40.38) | 98.86 | 92.86-105.24 |
AUCI (ng.hr/mL) | 174.88 188.22 (42.14) | 178.84 190.39 (39.73) | 100.02 | 94.04-106.37 |
Cmax (ng/mL) | 114.59 120.70 (33.48) | 123.69 129.65 (31.07) | 92.65 | 84.35-101.75 |
Tmax§ (h) | 0.75 (0.50-1.00) | 0.75 (0.50-1.00) | ||
T½€ (h) | 1.09 (18.86) | 1.09 (18.42) | ||
* pms-CILAZAPRIL
† INHIBACE® (Hoffmann-LaRoche Limited, Canada) was purchased in Canada.
§ Expressed as the median (range) only
€ Expressed as the arithmetic mean (CV%) only
DETAILED PHARMACOLOGY
In in vitro studies, using hippurylhistidylleucine as substrate, cilazaprilat, the active metabolite of cilazapril, inhibited the activity of ACE from rabbit lung (IC50 0.97-1.93 nM), hog lung (IC50 2.83 nM), human lung (IC50 1.39 nM), and human plasma (IC50 0.61 nM). Cilazaprilat (20 µM) did not have any effect on a number of other porcine, bovine, or human enzymes except E. coli dipeptidyl carboxypeptidase.
In ex vivo studies, oral administration of 0.1 and 0.25 mg/kg cilazapril to rats inhibited plasma ACE activity by 76% and 96% respectively and 0.3-3 mg/kg significantly inhibited tissue ACE activity in a number of arteries and veins.
In vivo, the dose of cilazapril and/or cilazaprilat required to reduce the angiotensin pressor response by 50% are summarized in Table 5 below.
Table 5 ED50 Values for Cilazapril and/or Cilazaprilat | ||
| Animal Model | Cilazapril Activity | Cilazaprilat Activity |
| Conscious normotensive rats | ED50 0.02 mg/kg p.o. (at 60 min) | — |
| Anesthetised SHAD (unilaterally adrenalectomised and contralaterally adrenal demedulated SHR) rats | ED50 0.44 µmol/kg i.v. | ED50 0.06 µmol/kg i.v. |
| 2-kidney-1-clip Goldblatt renal hypertensive rats | ED50 0.043 mg/kg i.v. | ED50 0.006 mg/kg i.v. |
| Anesthetised normotensive dogs | ED50 0.035 mg/kg i.v. (0.084 µmol/kg) | — |
In the anesthetised SHAD rats 0.06 µmol/kg i.v. cilazaprilat potentiated the bradykinin induced vasodepressor response.
The antihypertensive activity of cilazapril was assessed in a number of experimental animal models. In spontaneously hypertensive rats (SHR), single oral doses of 10 and 30 mg/kg cilazapril reduced systolic blood pressure for longer than six hours. Repeated daily dosing with oral doses of 10 and 30 mg/kg cilazapril demonstrated 24-hour activity and at the higher dose, antihypertensive effect became maximum after one week. When administered twice daily, the lowest oral dose of cilazapril that reduced systolic blood pressure was 1 mg/kg. Dose dependent decreases in systolic blood pressure were observed between oral doses of 1 and 10 mg/kg twice daily. No further increase in effect was observed with an oral dose of 30 mg/kg twice daily.
Intravenous administration of up to 10 mg/kg of either cilazapril or cilazaprilat to conscious SHR evoked only small reductions in blood pressure. The reason for this disparity with the oral dosing data in the same animal model is unclear.
Following the oral administration of 10 mg/kg cilazapril, the maximum decrease in systolic arterial pressure observed in conscious renal hypertensive hypovolemic dogs was approximately double that observed in normovolemic dogs. In the hypovolemic dogs, the systolic blood pressure fell significantly within 30 minutes of the first dose. The effect persisted for 6 hours. Maximum decrease in systolic arterial pressure in conscious normotensive hypovolemic dogs was similar to that observed in renal hypotensive normovolemic dogs.
Heart rate changes accompanying the antihypertensive action of cilazapril in the rat and the dog were minimal.
Total peripheral resistance and regional vascular resistance were reduced in all vascular beds except in the heart in SHR administered multiple, oral, daily doses of 10 mg/kg cilazapril. Regional blood flow to the kidneys, intestine and skin increased. Regional blood flow to the heart decreased. No changes were observed in cardiac output, cardiac index, stroke volume or heart rate. Hemodynamic and blood flow changes were similar after acute or repeated (twice daily for two weeks) administration of 1 mg/kg cilazapril. Additional increases in blood flow to the lungs, stomach, small intestine, pancreas and thymus were observed however.
In conscious dogs, cilazapril had no effect on left ventricular pressure and on force of cardiac contraction at 3 mg/kg p.o. and marginal effects at 10 mg/kg p.o. At these doses, slight decreases were noted in abdominal aortic blood flow and heart rate. In anesthetized dogs, intravenous cilazapril doses of 0.03-1 mg/kg evoked dose dependent decreases in blood pressure and left ventricular pressure. At 1 mg/kg, left ventricular end diastolic pressure was decreased 15%, myocardial contractile force was reduced and heart rate was unchanged. At 0.3 mg/kg, cardiac output, coronary blood flow, left ventricular minute work, left ventricular stroke work, and cardiac index were decreased 15%, 12%, 31%, 40%, and 12% respectively. In the anesthetized dog with ischemic heart failure, intravenous doses of cilazaprilat (0.1-1 mg/kg) reduced total peripheral resistance, left ventricular end diastolic pressure, dp/dt, and mean aortic blood pressure. Cardiac output, heart rate, pulmonary arterial pressure and right arterial pressure remained unchanged.
Oral administration of 3 mg/kg cilazapril did not have an effect on the increase in blood pressure and heart rate accompanying exercise in conscious cats. In anesthetized cats, cilazapril (10 mg/kg i.v.) increased right ventricular force of contraction (28%) and cardiac output (19%). Heart rate changes were minor.
The pharmacokinetics of cilazapril and cilazaprilat have been examined in mice, rats, dogs, monkeys, marmosets and baboons. The oral absorption of cilazapril is rapid and peak plasma concentrations of cilazapril occur in less than 1 hour. Absorption is 70-89%. Cilazapril plasma concentrations decline rapidly with a half-life of 0.7-2.7 hours. Plasma concentrations are less than dose proportional in baboons, and in rats and marmoset levels are too low for reliable quantitation.
Cilazaprilat is produced rapidly in all species and peak concentrations occur in less than 1.5 hours. Bioavailability from oral cilazapril is 70-89%. Cilazaprilat plasma concentrations decline in a biphasic manner with half-lives of 0.5-3.5 hours and 12-68 hours. Plasma concentrations are less than dose proportional, and show a low order of dose dependence during the terminal phase. This is consistent with saturable binding to ACE.
The distribution of drug related material is largely confined to excretory organs, but all major tissues are exposed, including the fetus of pregnant animals. There is no evidence of tissue retention, and more than 95% of the dose is recovered within three days. Repeat administration leads to some accumulation, but only in a limited number of tissues, notably the liver and kidney.
Excretion is rapid in all species. More than 90% of the total recovery in urine is achieved within 24 hours. Excretion is predominantly hepatic in rats and baboons, and renal in marmosets.
TOXICOLOGY
Table 6
Acute Toxicity
| Species | Sex | Route | Approximate LD50 (mg/kg) |
| Mouse | M F M + F M F M + F | p.o. p.o. i.v. i.p. i.p. s.c. | 4,600 2,500 - <5,000 >250 1,600 1,300 >1,000 |
| Rat | M + F M + F | p.o. i.p. | >4,000 - <5,000 830 |
| Monkey | M + F | p.o. | >4,000 - <5,000 |
The signs of toxicity include: ataxia, reduced motor activity, diarrhea, respiratory depression, tremors, piloerection, prostration, hunched appearance, salivation, emesis and facial fur-staining.
Long-Term Toxicity
Table 7
Long-Term Toxicity
Species (# group) | Study Duration | Dose Administration (mg/kg/day) | Route | Findings |
|---|---|---|---|---|
Rat (8M + 8F) | 2 Weeks | 0, 2, 6, 20 | i.v. | All dose groups: Swollen tails in individual rats after 8-10 days; slight increase in urine volume (males). |
Monkey Marmoset (3M + 3F) | 2 Weeks | 0, 2, 6, 20 | i.v. | All dose groups: Slightly depressed heart rates. |
Rat (5M + 5F) | 4 Weeks | 0, 5, 15, 50 | p.o. | All dose groups: Increased water consumption. 15 and 50 mg/kg/day: Minimal decreases in RBC, Hb and PCV values (females); increase in plasma urea (2-3x). 50 mg/kg/day: Salivation (6/10) from week 2; decrease body weight gain (20%); slight reduction in food consumption; increased incidence of kidney tubule cells in urine (females). |
Rat (16M + 16F) | 4 weeks | 25, 125, 625 | p.o. | All dose groups: Salivation; slight reduction in motor activity; increased urine volumes and minimal decreases in specific gravity (males). 125 and 625 mg/kg/day: Decreased body weight gain and food consumption (males only at 125 mg/kg/day); slight decreases in RBC, Hb and PCV (males); very slight thickening of glomerular afferent arteriolar wall in the kidney (males) (1/10 - 125 mg/kg/day, 6/10 - 625 mg/kg/day). 625 mg/kg/day: Increased BUN values (1.5x) (males); decreased BMC1 (males); slight decrease in heart and liver (males) weight. |
Species (# group) | Study Duration | Dose Administration (mg/kg/day) | Route | Findings |
|---|---|---|---|---|
| Monkey Marmoset (3/6M + 3F) | 4 Weeks | 0, 5, 15, 50 | p.o. | 15 and 50 mg/kg/day: Marginal decreases in RBC, Hb and PCV values. 50 mg/kg/day: Increase in plasma urea (2x), K + and cholesterol values; increased incidence of kidney tubule cells in urine. |
Rat (16M + 16F) | 13 Weeks | 0, 10, 50, 250 | p.o. | All dose groups: Very slight increases in urine volume and decreased SG values (males). 50 and 250 mg/kg/day: Dose-related decrease in body weight gain (males only at 50 mg/kg/day); increased BUN levels (2x) (males); slight thickening of glomerular afferent arterioles in the kidneys (10/30). 250 mg/kg/day: Slight decrease in spontaneous activity and salivation; inhibition of food consumption; small decreases in RBC and BMC (males), and in RBC, PCV and Hb (females). |
| Monkey Cynomolgus (4M + 4F) | 13 Weeks | 0, 2.5, 25, 50 | p.o. | 25 and 50 mg/kg/day: Slight decreases in RBC, Hb and PCV. Slight to moderate hyperplasia of the juxtaglomerular apparatus; dose- related decreased body weight gains. 50 mg/kg/day: Two deaths; salivation; emesis; decreased spontaneous activity. Slight decrease in BMC, total protein and inorganic phosphate; increase in BUN (4x), blood creatinine; enlargement of kidney (1 female); reduction in heart weight; kidney tubular dilatation. |
Species (# group) | Study Duration | Dose Administration (mg/kg/day) | Route | Findings |
|---|---|---|---|---|
Monkey Baboon (2M + 2F) | 13 Weeks | 0, 2, 10, 20, 40 | p.o. | All dose groups: Emesis; slight reductions in heart rate, body weight gain and heart weight; hypertrophy and hyperplasia of the juxtaglomerular cells (1/4 - 10 mg/kg, 3/4 - 20 mg/kg, 4/4 - 40 mg/kg). 20 and 40 mg/kg/day: Slight decrease in RBC, PCV and Hb; kidney tubular basophilia/dilatation (1/4 - 20 mg/kg; 3/4 - 40 mg/kg). Increased urea (2x) in 40 mg/kg only. |
Rat (30M + 30F) | 26 Weeks | 0, 5, 30, 200; 0, 2, 12, 75 - from Week 6; 0, 2, 12, 50 from Week 14 | p.o. | All dose groups: Slight decrease in heart rate; weight loss; lethargy; hunched posture. Pilo-rection; facial fur-staining; dose-related increases in kidney weights (male). 12 and 50 mg/kg/day: Hypertrophy of afferent glomerular arterioles in the kidneys (13 weeks). 50 mg/kg/day: Body weight gain decrease (14%) (males); increased water intake. Increased BUN levels (3x) (males), ALP activity, and liver weights (males); prominent kidney tubular regeneration; kidney tubular dilatation; minimal kidney tubular necrosis (2 animals at 13 weeks). Sclerosis (2 animals at 26 weeks). |
Species (# group) | Study Duration | Dose Administration (mg/kg/day) | Route | Findings |
|---|---|---|---|---|
Monkey Marmoset (9, 7, 7, 11 M + 9, 7, 7, 11F) | 26 Weeks | 0, 5, 30, 200; 0, 2, 15, 100 from Week 9; 0, 2, 15, 50 from Week 14 | p.o. | 200 mg/kg/day: Depression in heart rate; body weight loss (females). 15 mg/kg/day: Two deaths (unrelated to treatment) of minor glomerular arteriolar hypertrophy (13 and 26 weeks). 50 mg/kg/day: Six deaths (two unrelated to treatment); unsteadiness; inactivity; salivation; emesis; diarrhea; slight decrease in RBC, PCV, Hb and bone marrow, myeloid/erythroid ratio (26 weeks). Increase in plasma urea (2x); small reductions in urine osmolality; slight kidney tubular dilatation and tubular epithelium regeneration (4/5 at 13 weeks - 100 mg/kg) (4/10 after 26 weeks). |
Monkey Baboon (7M + 7F) | 52 Weeks | 0, 0.5, 4, 40 | p.o. | 4 and 40 mg/kg/day: Hyperplasia and hypertrophy of juxtaglomerular apparatus with hypertrophy of muscle cells of glomerular arterioles (1/10 - 4 mg/kg; 8/10 - 40 mg/kg/day). 40 mg/kg/day: Emesis; body weight gain reduction; slight reduction in RBC, PCV and Hb; increase in urea values (2x) and creatinine; osmolality reductions; increased incidence in proteinous casts (Week 52); small increase in adrenal and thyroid weights. |
Species (# group) | Study Duration | Dose Administration (mg/kg/day) | Route | Findings |
|---|---|---|---|---|
Rat (35M + 35F) | 78 Weeks | 0, 0.5, 4, 40 | p.o. | All dose levels: Small reductions in body weight gain. 4 and 40 mg/kg/day: Slight decrease in RBC, PCV and Hb; minimal reduction in food intake; increase in BUN (2x) (males). 40 mg/kg/day: Increased water consumption; slight increase in total WBC count (males); increased urine volumes (males); irregular surface ocysts in the kidneys (7/40 at 76 weeks); increased kidney weights (males); slight decrease in heart and liver weight (females); vascular hypertrophy (20/20 males, 17/20 females) consisting of glomerular afferent arteriolar wall thickening; similar but less frequent and less severe changes were observed in the mid dose group. |
Table 8
Reproduction and Teratology
Species (# group) | Dose (mg/kg/day) | Route | Duration of Dosing | Findings |
| Fertility and General Reproduction Performance | ||||
Rat Charles River (Crl:CD (SD) BR) (30M + 30F) | 0, 1, 7, 50 | p.o. | Males - 70 days prior to mating and up to 14 days during mating. Females - 14 days before mating, during gestation and until Day 21 post- partum. | All dose groups: No effect on mating or fertility at any dose. Retching reflex after dosing (dose- related) (males). Decreased body weight gain. Males at 50 mg/kg/day: Six deaths (due to dosing error). Females at 50 mg/kg/day: Two deaths (50 mg/kg) (due to dosing error). Increased preimplantation loss (forced delivery group at 50 mg/kg). F1 generation at 7 and 50 mg/kg/day: Reduced body weight at the end of lactation; increased incidence of dilatation of the renal pelvis. Reduction in viable fetuses due to a lower number of implantations (50 mg/kg). |
| Embryotoxicity | ||||
Rat Charles River (CD) (35F) | 0, 2, 30, 400 | p.o. | Days 6-17 of gestation. | All dose groups: No effect on embryonic, fetal or postnatal development. Females at 400 mg/kg/day: Body weight gain and food consumption were reduced during latter half of gestation. F1 generation at 400 mg/kg/day: Slight increase in renal cavitation incidence. |
| Fertility and General Reproduction Performance | ||||
Monkey cynomolgus (10 or 11F) | 0, 20 | p.o. | Days 21 to 31 or Days 32 to 45 of gestation. | Control group: Reduced food consumption and diarrhea (5/10 females); 2/10 abortions between Days 51-53 of pregnancy; low incidence of skeletal variations in tail (2/8 fetuses) and ribs (2/8). 20 mg/kg/day - Days 21-31: Reduced food consumption (10/10 females); diarrhea (2/10); vomiting (2/10). Skeletal findings - ribs (2/8 fetuses), humeri (2/8), distal caudal variations (4/8), and prepuce not patent (2/8) - not treatment related. 20 mg/kg/day - Days 32-45: Decreased food consumption and/or diarrhea (11/11 females); 5/11 abortions; 2/11 maternal deaths (not treatment related). Caudal and humerus variations (1/5 fetuses) - not treatment related. |
| Peri- and Post-natal Toxicity | ||||
Rat Charles River (CDCrl: CD(SD) BR) (25 or 30F) | 0, 1, 7, 50 | p.o. | Day 15 of gestation to Day 21 post- partum. | Females at 50 mg/kg/day: 5 deaths on Day 18 postcoitus or Days 4-16 of lactation (due to dosing error). F1 generation at 50 mg/kg/day: Increased pup mortality (4.9%); reduction in body weight gain during lactation; an associated slight delay in pinna unfolding. |
CARCINOGENICITY
An eighty-eight week carcinogenicity study with cilazapril was conducted in mice initially dosed at 5, 25 or 100 mg/kg/day, subsequently reduced to 1, 7 or 50 mg/kg/day from week 11 onwards. Another carcinogenicity study was conducted in rats in which dose levels of 0.5, 4 or 40 mg/kg/day were administered for 104 weeks. Hypertrophy of renal afferent glomerular arterioles and interlobular arteries, and increased cortical nephropathy were the only recorded findings and occurred in the mid- and high-dose groups in both studies. Tri-PAs staining of kidney sections from the 104 week rat carcinogenicity study indicated no hyperplastic or 7 neoplastic oxyphilic cell response and no enhancement of the development of oncocytomas.
MUTAGENICITY
No evidence of mutagenicity with cilazapril was found in the Ames test with or without metabolic activation (up to 2.0 mg/plate), “Treatment and Plate” test (up to 7,000 µcg/mL), unscheduled DNA synthesis assay (up to 200 µcg/mL), mutagenic assay with Chinese hamster V79 cells with or without metabolic activation (up to 4,800 µcg/mL), chromosomal abbreration test with or without metabolic activation (up to 3,500 µcg/mL), or in vivo micronucleus test in mice (2.0 g/kg).
REFERENCES
- 1.
Ajayi AA, Elliott HL, Reid JL. The pharmacodynamics and dose-response relationships of the angiotensin converting enzyme inhibitor, cilazapril, in essential hypertension.
Br J Clin Pharmacol 1986;22:167-75.
- 2. Francis RJ, et al. Pharmacokinetics of the converting enzyme inhibitor cilazapril in normal volunteers and the relationship of enzyme inhibition: development of a mathematical model. J Cardiovasc Pharmacol 1987;9:32-8.
- 3. Belz GG, et al. Interactions between cilazapril and propranolol in man; plasma drug concentrations, hormone and enzyme responses, haemodynamics, agonist, dose-effect curves and baroreceptor reflex. Br J Clin Pharmacol 1988;26:547-56.
- 4. Nussberger J, et al. Repeated administration of the converting enzyme inhibitor cilazapril to normal volunteers. J Cardiovasc Pharmacol 1987;9:39-44.
- 5. Sanchez RA, et al. Antihypertensive, enzymatic, and hormonal activity of cilazapril, a new angiotensin-converting enzyme inhibitor in patients with mild to moderate essential hypertension. J Cardiovasc Pharmacol 1988;11:230-4.
- 6.
Shionoiri H, et al. Antihypertensive effects and pharmacokinetics of single and consecutive doses of cilazapril in hypertensive patients with normal and impaired renal function.
J Cardiovasc Pharmacol 1988;11:242-9.
- 7. Shionoiri H, et al. Pharmacokinetics of single and consecutive doses of cilazapril and its depressor effects and patients with essential hypertension. Am J Hypertens 1988;1:269-73.
- 8.
Shionoiri H, et al. Pharmacokinetics of single and consecutive doses of cilazapril and its depressor effects in hypertensive patients with renal dysfunction. Am J Hypertens
1988;1:230-2.
- 9.
White WB, et al. The effects of the long-acting angiotensin-converting enzyme inhibitor cilazapril on casual, exercise, and ambulatory blood pressure. Clin Pharmacol Ther
1988;44:173-8.
- 10. Lacourciere Yves, et al. Antihypertensive effects of cilazapril, 2.5 and 5.0 mg, once daily versus placebo on ambulatory blood pressure following single- and repeat-dose administration. J CARDIOVASCPHARMACOL 1991;18(2):219-223.
- 11. Kobrin, I., et al. Antihypertensive duration of action of cilazapril in patients with mild to moderate essential hypertension. Drugs 1991;27(Suppl 2):225S-234S.
- 12. Guntzel, P, et al. The effect of cilazapril, a new angiotensin converting enzyme inhibitor, on peak and trough blood pressure measurements in hypertensive patients. J Cardiovasc Pharmacol 1991;17:8-12.
- 13.
Sanchez, RA, et al. Effects of ACE inhibition on renal haemodynamics in essential hypertension and hypertension associated with chronic renal failure. Drugs
1991;41(Suppl 1):25-30.
- 14. Tunon-de-Lara JM, et al. ACE inhibitors and anaphylactoid reactions during venom immunotherapy. Lancet 1992;340:908.
- 15.
Corder CN, et al. Effect of cilazapril on exercise tolerance in congestive heart failure.
Pharmacology 1993;46(3):148-54.
- 16. Doessegger L, et al. Comparison of the effects of cilazapril and captopril versus placebo on exercise testing in chronic heart failure patients: a double-blind, randomized, multicenter trial. Cardiology 1995;86(S1):34-40.
- 17. Drexler H, et al. Contrasting peripheral short-term and long-term effects of converting enzyme inhibition in patients with congestive heart failure. A double-blind, placebo- controlled trial. Circulation 1989;79(3):491-502.
- 18. Garg R, et al. Overview of randomized trials of angiotensin-converting enzyme inhibitors on mortality and morbidity in patients with heart failure. JAMA 1995;273(18):1450-56.
- 19.
Kiowski W, et al. Cilazapril in congestive heart failure. A pilot study. Drugs 1991;S41(1):54-
61.
- 20. Kiowski W, et al. Coronary vasodilation and improved myocardial lactate metabolism after angiotensin converting enzyme inhibition with cilazapril in patients with congestive heart failure. American Heart Journal 1991;122(5):1382-88.
- 21. Rosenethal E, et al. A pharmacokinetic study of cilazapril in patients with congestive heart failure. British Journal of Clinical Pharmacology 1989;27(S2):267S-273S.
- 22. Wiseman MN, et al. Initial and steady state pharmacokinetics of cilazapril in congestive cardiac failure. Journal of Pharmacy and Pharmacology 1991;43(6):406-10.
- 23. INHIBACE® Product Monograph (Hoffmann-La Roche Limited, Mississauga Ontario) Revision date: March 12, 2015, control number: 180630