


Product Monograph - PRISM0CAL B22K0/0
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Non-medicinal Ingredients |
For intravenous use. For hemodialysis. | Sterile solution for hemodialysis, hemofiltration and hemodiafiltration / Sodium chloride 7.14 g/L, Magnesium chloride hexahydrate 3.05 g/L, Sodium hydrogen carbonate 2.12 g/L | Not relevant. All non-medicinal ingredients are pharmacologically inactive. For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Prism0CAL B22K0/0 is indicated for:
- treatment of acute renal failure as replacement solution in hemofiltration or hemodiafiltration and as dialysis solution in hemodialysis or hemodiafiltration in continuous renal replacement therapy (CRRT).
- patients who have tendency to hyperkalaemia and/or hypercalcemia,
- treatment in case of drug poisoning with dialyzable or filterable substances.
The solution should be used only by, or under the direction of, a health professional competent in treatment of acute renal failure using hemofiltration, hemodiafiltration and hemodialysis in CRRT in a hospital setting.
Geriatrics (> 65 years of age):
There are no adequate data for use in geriatric patients.
Pediatrics (< 16 years of age):
There are no adequate data for use in pediatric patients.
CONTRAINDICATIONS
Solution-dependent, relative contraindications
- Hypocalcaemia
- Hypokalaemia
WARNINGS AND PRECAUTIONS
General
Use only if the solution is clear and free from visible particles. All seals must be intact. Use only if the overwrap and solution bag are undamaged. Use of a contaminated solution may cause sepsis and shock.
The instructions for use must be strictly followed.
The solutions in the two compartments must be mixed before use.
Use only for CRRT. The product is not intended to be used with other renal replacement therapies, including conventional hemodialysis, sustained low-efficiency dialysis (SLED), extended daily dialysis (EDD), or prolonged intermittent renal replacement therapy (PIRRT).
Prism0CAL B22K0/0 contains no calcium or potassium and its use could result in hypocalcaemia and/or hypokalaemia. Close monitoring might be necessary.
Because Prism0CAL B22K0/0 contains no dextrose, administration of Prism0CAL B22K0/0 may lead to hypoglycemia. Blood glucose levels should be monitored regularly. If hypoglycemia develops, use of a dextrose-containing solution should be considered. Other corrective measures may be necessary to maintain desired glycemic control.
In case of hypervolaemia, one possible cause is a discrepancy between the prescribed and actual rates of dialysate, replacement fluid and effluent. If such a discrepancy exists, the user should determine its cause. The net ultrafiltration rate (i.e., patient weight loss rate) may need to be increased or the rate of administration of solutions other than dialysate and/or replacement fluid may need to be reduced to correct the hypervolaemia.
In case of hypovolaemia, one possible cause is a discrepancy between the prescribed and actual rates of dialysate, replacement fluid and effluent. If such a discrepancy exists, the user should determine its cause. The net ultrafiltration rate (i.e., patient weight loss rate) may need to be reduced or the rate of administration of solutions other than dialysate and/or replacement fluid may need to be increased to correct the hypovolaemia.
Special Populations
Pregnant Women: There are no adequate data from the use of the Prism0CAL B22K0/0 solution in pregnant women. The prescribing health professional should consider the benefit/risk relationship before administering this solution to pregnant women. The Prism0CAL B22K0/0 solution may be considered during pregnancy if clearly needed.
Nursing Women: There are no adequate data from the use of the Prism0CAL B22K0/0 solution in lactating women. The prescribing health professional should consider the benefit/risk relationship before administering this solution to breast-feeding women.
Pediatrics (< 16 years of age): There are no adequate data for use in pediatric patients.
Geriatrics (> 65 years of age): There are no adequate data for use in geriatric patients.
Monitoring and Laboratory Tests
Hemodynamic status, fluid balance, electrolyte and acid-base balance and glucose level should be closely monitored throughout the procedure.
As the solution contains no calcium and potassium, blood calcium and potassium concentrations should be measured regularly.
The blood inorganic phosphate concentration should be monitored regularly.
Assessment of buffer needs through repeated blood pH and blood bicarbonate measurements and review of the overall therapy is mandatory. A solution with higher hydrogen carbonate content may be required, based on the patient’s clinical condition, the CRRT prescription (including the flow rates of dialysate and/or replacement fluid), and the type of anticoagulation prescribed. Frequent monitoring of blood electrolytes, acid-base parameters, and ionized calcium is especially important when RCA is prescribed.
In case of metabolic alkalosis, the alkali content of other fluids being administered to the patient (including those prescribed as part of the CRRT procedure) should be evaluated. Buffer load provided as part of RCA is especially important to assess.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Adverse drug reactions can result from the solution used or the treatment.
Hydrogen carbonate-buffered hemofiltration, hemodiafiltration and hemodialysis solutions are generally well tolerated. However, the following adverse drug reactions are conceivable:
Hyper- or hypovolemia, electrolyte disturbances, hypophosphataemia, metabolic alkalosis.
Some adverse reactions related to the dialysis treatments (hemodialysis, hemofiltration and hemodiafiltration) can occur, such as nausea, vomiting, muscle cramps and hypotension.
Clinical Trial Adverse Drug Reactions
Not applicable.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Not applicable.
Abnormal Hematologic and Clinical Chemistry Findings
Not applicable.
Post-Market Adverse Drug Reactions
Not applicable.
DRUG INTERACTIONS
Overview
The blood concentration of filterable/dialysable drugs may be reduced during treatment. In addition, the blood concentration of potassium, calcium, or other electrolytes may be modified by the treatment, influencing the action of certain drugs. Corresponding monitoring, preventive or corrective therapy should be instituted if necessary.
It is the responsibility of the physician to consider the compatibility of any medication that is to be mixed with the Prism0CAL B22K0/0 solution, by checking for colour change and precipitation of insoluble complexes or crystals. The Instructions for Use of the medication to be added must be consulted.
Before adding a drug, verify it is soluble and stable in water at the pH of this solution (pH of reconstituted solution is 7.0 to 8.0).
The compatible medication must be added to the reconstituted solution and the solution must be administered immediately.
Medication should only be added under the direction of a physician in the following way: Remove any fluid from injection port, hold the bag upside down, insert the drug through the injection port and mix thoroughly. When introducing additives, use aseptic techniques. The solution must be administered immediately.
Drug-Drug Interactions
Interactions with other drugs have not been established.
However, the following interactions are conceivable:
- The risk of digitalis-induced cardiac arrhythmia is increased during hypokalaemia;
- Additional buffer substitution (e.g. sodium hydrogen carbonate) may increase the risk of metabolic alkalosis.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
Not relevant.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The volume of the Prism0CAL B22K0/0 solution used will depend on the clinical condition of the patient, the CRRT prescription (including the type of anticoagulation prescribed), and the desired fluid, electrolyte and acid-base balance. The dose is therefore at the discretion of the responsible health professional.
Recommended Dose and Dosage Adjustment
The range of flow rates for the replacement solution in hemofiltration and hemodiafiltration in CRRT are:
Adult and adolescents: 500-3000 mL/h
Children: 15-35 mL/kg/h
The range of flow rates for the dialysis solution (dialysate) in continuous hemodialysis and continuous hemodiafiltration in CRRT are:
Adult and adolescents: 500-3000 mL/h
Children: 15-30 mL/kg/h
Commonly used flow rates in adults may be approximately 2000-2500 mL/h which correspond to a daily replacement fluid volume of approximately 20-30 mL/kg/h.
Missed Dose
Not relevant, since the Prism0CAL B22K0/0 solution is administered continuously.
Administration
Intravenous use for hemofiltration (and part of hemodiafiltration) and dialysis transmembrane use for hemodialysis.
Prism0CAL B22K0/0, when used as a replacement solution, is administered into the extracorporeal circuit before (pre-dilution) or after (post-dilution) the hemofilter or hemodiafilter.
Prism0CAL B22K0/0, when used as a dialysis fluid (dialysate), is administered in the dialysate compartment of the filter separated from the blood flow by a semipermeable membrane.
Reconstitution:
The solution in the small compartment A is added to the solution in the large compartment B after breaking the peel seal immediately before use to obtain the clear and colorless reconstituted solution.
Instruction for Use:
Remove the overwrap from the bag immediately before use. Aseptic technique should be used throughout administration to the patient. The solution should be used immediately after opening to avoid microbiological contamination.
Use only if the overwrap is not damaged, all seals are intact, peel seal is not broken, and the solution is clear. Press bag firmly to test for any leakage. If leakage is discovered, discard the solution immediately since sterility can no longer be assured.
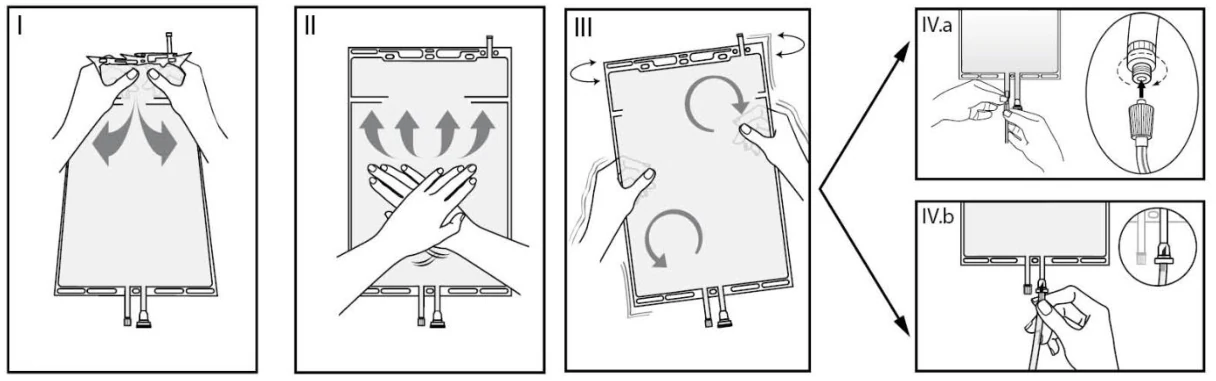
I Open the seal by holding the small compartment with both hands and squeezing it until an opening is created in the peel seal between the two compartments. (See figure I below)
II Push with both hands on the large compartment until the peel seal between the two compartments is entirely open. (See figure II below)
III Secure complete mixing of the solution by shaking the bag gently. The solution is now ready for use, and can be hung on the equipment. (See figure III below)
IV The dialysis or replacement line may be connected to either of the two access ports.
IV.a If the luer connector is used, remove the cap with a twist and pull motion, and connect the male luer connector on the dialysis or replacement line to the female luer connector on the bag using a push and twist motion. Ensure that the connection is fully seated and tighten. The connector is now open. Verify that the fluid is flowing freely. (See figure IV.a below)
When the dialysis or replacement line is disconnected from the luer connector, the connector will close and the flow of solution will stop. The luer connector is a needle-less and swabbable port.
IV.b If the injection port (spike connector) is used, first remove the snap-off cap. The injection port is a swabbable port. Introduce the spike through the rubber septum. Verify that the fluid is flowing freely. (See figure IV.b below)
Adding drugs to the solution:
The large compartment is fitted with an injection port (spike connector) for the possible addition of other necessary drugs after reconstitution of the solution. Additives may be incompatible. The instructions for use of the medication to be added and other relevant literature must be consulted. After addition, if there is a color change and/or the appearance of precipitates, insoluble complexes, or crystals, do not use.
The instructions for use of the medication to be added must be consulted.
Mix the solution thoroughly when additives have been introduced. The introduction and mixing of additives must always be performed prior to connecting the solution bag to the extracorporeal circuit.
Before adding a drug, verify it is soluble and stable in the Prism0CAL B22K0/0 solution at the pH of the reconstituted solution (7.0-8.0).
Drugs should only be added to the solution under the responsibility of a health professional in the following way: Remove any fluid from the injection port, hold the bag upside down, insert the drug through the injection port and mix thoroughly. The solution must be administered immediately.
OVERDOSAGE
Symptoms of overdose
Overdose of Prism0CAL B22K0/0 can lead to severe clinical conditions, such as fluid overload (including congestive heart failure), electrolyte disturbances (including hypokalaemia and hypocalcaemia), or acid-base disturbances.
Treatment of overdose
- Hypervolaemia In case of hypervolaemia, a potential discrepancy between the prescribed and actual rates of dialysate, replacement fluid and effluent should be considered. If such a discrepancy exists, the user should determine its cause. The net ultrafiltration rate (i.e., patient weight loss rate) may need to be increased or the rate of administration of solutions other than dialysate and/or replacement fluid may need to be reduced to correct the hypervolaemia.
- Hypovolaemia
In case of hypovolaemia a possible discrepancy between the prescribed and actual rates of dialysate, replacement fluid and effluent should be considered. If such a discrepancy exists, the user should determine its cause. The net ultrafiltration rate (i.e., patient weight loss rate) may need to be reduced or the rate of administration of solutions other than dialysate and/or replacement fluid may need to be increased to correct the hypovolaemia.
- Electrolyte disturbances
In case of either hypokalaemia or hypocalcaemia, the flow rate of Prism0CAL B22K0/0 may need to be reduced or electrolyte administration rate may need to be increased from other sources, such as another CRRT therapeutic fluid (dialysate or replacement fluid) or a solution not part of the CRRT prescription.
- Acid-base disturbances
In case of metabolic acidosis, the overall rate of net alkali administration needs to be increased. The alkali content of all fluids being administered to the patient (including those prescribed as part of the CRRT procedure) should be evaluated. If RCA is part of the CRRT prescription, it is important to assess the clinical factors potentially influencing citrate metabolism (especially liver function).
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
|---|
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The Prism0CAL B22K0/0 solution is pharmacologically inactive. The sodium, magnesium and chloride ions are present at concentrations similar to physiological levels in plasma.
The solution is used to replace water and electrolytes removed during hemofiltration and hemodiafiltration or to serve as a suitable exchange medium for use during hemodiafiltration or hemodialysis in CRRT.
Hydrogen carbonate is used as an alkalising buffer.
Pharmacodynamics
No factor affects the pharmacodynamic response.
Pharmacokinetics
Not relevant, since the drug substances sodium, magnesium and chloride ions are pharmacologically inactive and are present at concentrations similar to physiological levels in plasma.
Special Populations and Conditions
Not relevant, since the pharmacokinetics are not modified with specific population and conditions.
STORAGE AND STABILITY
Store between 4°C and 30°C. Do not refrigerate. Protect from freezing.
Prism0CAL B22K0/0 is for single use only. Any unused solution must be discarded.
Chemical and physical in-use stability of the reconstituted solution has been demonstrated for 24 hours at 22°C. If not used immediately in-use storage times and conditions prior to use are the responsibility of the user and should not be longer than 24 hours including the duration of the treatment.
Others
Keep in a safe place out of the reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
The container is a two-compartment bag made of a multilayer film containing polyolefins and elastomers. The 5000 mL bag is comprised of a small compartment (250 mL) and a large compartment (4750 mL). The two compartments are separated by a peel seal. The bag is fitted with an injection port (spike connector) and a luer connector for the connection with a suitable solution line. The bag is overwrapped with a transparent overwrap made of polymer film.
The solutions are sterile.
Pack size: 2 x 5000 mL in a box
Composition of the Prism0CAL B22K0/0 solution before reconstitution
Compartment A contains concentrated solution for hemofiltration and hemodialysis without buffer and compartment B contains concentrated solution for hemofiltration and hemodialysis with bicarbonate as buffer.
| Before reconstitution | Prism0CAL B22K0/0 |
| Small compartment A (250 mL) | |
Magnesium chloride, hexahydrate Water for injection Hydrochloric acid, dilute | 3.05 g/L to 1000 mL pH adjuster |
| Large compartment B (4750 mL) | |
Sodium chloride Sodium hydrogen carbonate Water for injection Carbon dioxide | 7.14 g/L 2.12 g/L to 1000 mL pH adjuster |
Composition of the Prism0CAL B22K0/0 solution after reconstitution
| After reconstitution | Prism0CAL B22K0/0 | ||
| mmol/L | mEq/L | ||
Sodium Na+ Magnesium Mg2+ Chloride Cl- Hydrogen carbonate | Na+ Mg2+ Cl- HCO3- | 140 0.75 119.5a 22 | 140 1.50 119.5a 22 |
- a) The chloride concentration from the hydrochloric acid excipient is included in this figure.
Theoretical osmolarity: 282 mOsm/L
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance 1
Proper name: Sodium Chloride
Chemical name: Sodium Chloride
Molecular formula and molecular mass:
NaCl
Mr: 58.44 g/mol
Structural formula:

Physicochemical properties:
Appearance: White or almost white, crystalline powder or colourless crystals or white or almost white pearls.
Solubility: Freely soluble in water, practically insoluble in anhydrous ethanol.
Drug Substance 2
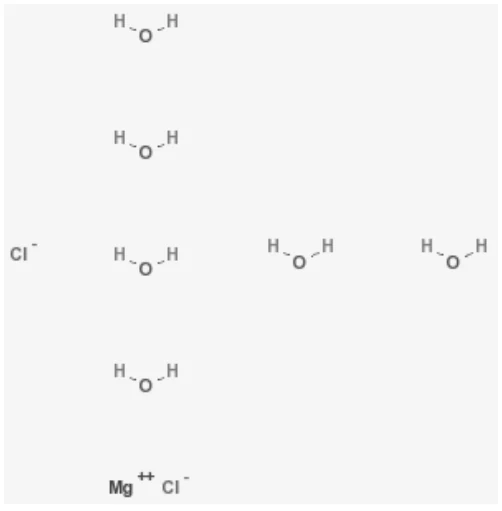
Proper name: Magnesium Chloride Hexahydrate
Chemical name: Magnesium Chloride Hexahydrate
Molecular formula and molecular mass:
MgCl2, 6H2O
Mr: 203.3 g/mol
Structural formula:
Physicochemical properties:
Appearance: Colourless crystals, hygroscopic.
Solubility: Very soluble in water, freely soluble in ethanol (96 per cent).
Drug Substance 3
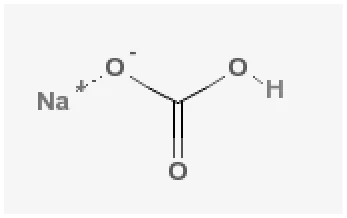
Proper name: Sodium Hydrogen Carbonate
Chemical name: Sodium Hydrogen Carbonate
Molecular formula and molecular mass:
NaHCO3
Mr: 84.0 g/mol
Structural formula:
Physicochemical properties:
Appearance: White or almost white crystalline powder.
Solubility: Soluble in water, practically insoluble in ethanol (96 per cent).
Other Properties: When heated in the dry state or in solution, it gradually changes into sodium carbonate.
CLINICAL TRIALS
The Prism0CAL B22K0/0 solution is based on concentrations of electrolytes already in use in the treatment of severe Acute Kidney Injury (AKI) in CRRT. There was no specific clinical trial initiated by the applicant for the development of the formulation of this solution.
DETAILED PHARMACOLOGY
Pharmacological studies with the Prism0CAL B22K0/0 solution have not been performed. The omission of preclinical studies is justified by the clinical experience with solutions with similar composition as the Prism0CAL B22K0/0 solution, used for hemodialysis, hemofiltration and hemodiafiltration.
MICROBIOLOGY
Not applicable.
TOXICOLOGY
Toxicological studies with the Prism0CAL B22K0/0 solution have not been performed. The omission of preclinical studies is justified by the clinical experience with solutions with similar composition as the Prism0CAL B22K0/0 solution, used for hemodialysis, hemofiltration and hemodiafiltration.
REFERENCES
Not applicable.