


Product Monograph - Pro-Atorvastatin
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions, Musculoskeletal | 06/2026 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ......................................................................................... 1
TABLE OF CONTENTS ........................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ..................................................................................................................... 4
1.2 Geriatrics ...................................................................................................................... 5
2 CONTRAINDICATIONS ................................................................................................... 5
4 DOSAGE AND ADMINISTRATION................................................................................... 5
4.1 Dosing Considerations ................................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ............................................................ 6
4.4 Administration ............................................................................................................. 8
4.5 Missed dose ................................................................................................................. 8
5 OVERDOSAGE ............................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................... 9
7 WARNINGS AND PRECAUTIONS .................................................................................... 9
7.1 Special Populations .................................................................................................... 14
7.1.1 Pregnant Women ....................................................................................................... 14
7.1.2 Breastfeeding ............................................................................................................. 14
7.1.3 Pediatrics ................................................................................................................... 15
7.1.4 Geriatrics .................................................................................................................... 15
8 ADVERSE REACTIONS ................................................................................................. 16
8.1 Adverse Reaction Overview ....................................................................................... 16
8.2 Clinical Trial Adverse Reactions ................................................................................. 16
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ............................................................. 17
8.3 Less Common Clinical Trial Adverse Reactions .......................................................... 18
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data ...................................................................................................... 18
8.5 Post-Market Adverse Reactions ................................................................................ 19
9 DRUG INTERACTIONS ................................................................................................. 20
9.1 Serious Drug Interactions .......................................................................................... 20
9.2 Drug Interactions Overview ....................................................................................... 20
9.3 Drug-Behavioural Interactions .................................................................................. 21
9.4 Drug-Drug Interactions .............................................................................................. 21
9.5 Drug-Food Interactions .............................................................................................. 30
9.6 Drug-Herb Interactions .............................................................................................. 30
9.7 Drug-Laboratory Test Interactions ............................................................................ 31
10 CLINICAL PHARMACOLOGY ......................................................................................... 31
10.1 Mechanism of Action ................................................................................................. 31
10.2 Pharmacodynamics .................................................................................................... 31
10.3 Pharmacokinetics ....................................................................................................... 32
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 34
12 SPECIAL HANDLING INSTRUCTIONS............................................................................. 35
PART II: SCIENTIFIC INFORMATION .................................................................................... 36
13 PHARMACEUTICAL INFORMATION ............................................................................. 36
14 CLINICAL TRIALS ......................................................................................................... 36
14.1 Clinical Trials by Indication ........................................................................................ 36
14.3 Comparative Bioavailability Studies .......................................................................... 50
15 MICROBIOLOGY ......................................................................................................... 51
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 51
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 54
PATIENT MEDICATION INFORMATION ............................................................................... 55
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
PRO-ATORVASTATIN (atorvastatin calcium tablets) is indicated in adults as an adjunct to lifestyle changes, including diet for:
the reduction of elevated total cholesterol (total-C), LDL-C, triglycerides (TG), apolipoprotein B (apo B), the Total-C/HDL-C ratio and for increasing HDL-C in hyperlipidemic and dyslipidemic conditions, including:
- Primary hypercholesterolemia (Type IIa);
- Combined (mixed) hyperlipidemia (Type IIb), including familial combined hyperlipidemia, regardless of whether cholesterol or triglycerides are the lipid abnormality of concern;
- Dysbetalipoproteinemia (Type III);
- Hypertriglyceridemia (Type IV);
- Familial hypercholesterolemia (homozygous and heterozygous). For homozygous familial hypercholesterolemia, PRO-ATORVASTATIN should be used as an adjunct to treatments such as LDL apheresis, or as monotherapy if such treatments are not available.
the prevention of Cardiovascular Disease, to reduce the risk of myocardial infarction in the following conditions:
- hypertensive patients without clinically evident coronary heart disease, but with at least three additional risk factors for coronary heart disease such as age ≥55 years, male sex, smoking, type 2 diabetes, left ventricular hypertrophy, other specified abnormalities on ECG, microalbuminuria or proteinuria, ratio of plasma total cholesterol to HDL-cholesterol ≥6, or premature family history of coronary heart disease.
- patients with type 2 diabetes mellitus and hypertension without clinically evident coronary heart disease, but with other risk factors such as age ≥55 years, retinopathy, albuminuria or smoking. It also reduced the risk of stroke in this population.
- patients with clinically evident coronary heart disease.
1.1 Pediatrics
Pediatrics (10 to <18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of atorvastatin calcium in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use as an adjunct to diet to reduce total-C, LDL-C, and apo B levels in boys and postmenarchal girls with heterozygous familial hypercholesterolemia, if after an adequate trial of diet therapy the following findings are still present:
- a. LDL-C remains ≥4.9 mmol/L (190 mg/dL) or
- b. LDL-C remains ≥4.1 mmol/L (160 mg/dL) and there is a positive family history of premature cardiovascular disease or two or more other CVD risk factors are present in the pediatric patient.
(see 4.1 Dosing Considerations, 7.1.3 Pediatrics)
Pediatrics (< 10 years of age). The safety and efficacy in pediatric patients under the age of 10 has not been established, therefore, Health Canada has not authorized an indication for this age range.
1.2 Geriatrics
Geriatrics: Based on the data submitted and reviewed by Health Canada, PRO-ATORVASTATIN use in geriatric patients has been authorized for all indications (see 1 INDICATIONS). Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Atorvastatin calcium is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Active liver disease or unexplained persistent elevations of serum transaminases exceeding 3 times the upper limit of normal (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
- Pregnancy and breastfeeding women (see 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential, 7.1.1 Pregnant Women, 7.1.2 Breastfeeding).
- Concomitant treatment with hepatitis C antivirals (see 9.4 Drug-Drug Interactions).
- Concomitant treatment with the immunosuppressant cyclosporine (see 9.4 Drug-Drug Interactions).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Patients should be placed on a standard cholesterol-lowering diet before receiving
PRO-ATORVASTATIN, and should continue on this diet during treatment with
PRO-ATORVASTATIN. If appropriate, a program of weight control and physical exercise should be implemented.
- Prior to initiating therapy with PRO-ATORVASTATIN, secondary causes for elevations in plasma lipid levels should be excluded. A lipid profile should also be performed.
- Elevated serum triglycerides are most often observed in patients with the metabolic syndrome (abdominal obesity, atherogenic dyslipidemia {elevated triglycerides, small dense LDL particles and low HDL-cholesterol}, insulin resistance with or without glucose intolerance, raised blood pressure and prothrombic and proinflammatory states).
- When drugs are prescribed attention to therapeutic lifestyle changes (reduced intake of saturated fats and cholesterol, weight reduction, increased physical activity, ingestion of soluble fibers) should always be maintained and reinforced.
- The dosage of PRO-ATORVASTATIN should be individualized according the baseline LDL-C, total-C/HDL-C ratio and/or TG levels to achieve the recommended desired lipid values at the lowest dose needed to achieve LDL-C desired level. Lipid levels should be monitored periodically and, if necessary, the dose of PRO-ATORVASTATIN adjusted based on desired lipid levels recommended by guidelines.
4.2 Recommended Dose and Dosage Adjustment
Primary Hypercholesterolemia and Combined (Mixed) Dyslipidemia, Including Familial Combined Hyperlipidemia
The recommended starting dose of PRO-ATORVASTATIN is 10 or 20 mg once daily, depending on patient’s LDL-C reduction required. Patients who require a large reduction in LDL-C (more than 45%) may be started at 40 mg once daily. The dosage range of
PRO-ATORVASTATIN is 10 to 80 mg once daily. A significant therapeutic response is evident within 2 weeks, and the maximum response is usually achieved within 2 to 4 weeks. The response is maintained during chronic therapy. Adjustments of dosage, if necessary, should be made at intervals of 2 to 4 weeks. The maximum dose is 80 mg/day.
Severe Dyslipidemias
In patients with severe dyslipidemias, including homozygous and heterozygous familial hypercholesterolemia and dysbetalipoproteinemia (Type III), higher dosages (up to 80 mg/day) may be required (see 7 WARNINGS AND PRECAUTIONS, Pharmacokinetic Interactions, 7 WARNINGS AND PRECAUTIONS, Muscle Effects; 9 DRUG INTERACTIONS).
Patients with high or very high triglyceride levels, i.e. > 2.2 mmol/L (200 mg/dL) or > 5.6 mmol/L (500 mg/dL), respectively, may require triglyceride-lowering therapy (fenofibrate, bezafibrate or nicotinic acid) alone or in combination with
PRO-ATORVASTATIN.
In general, combination therapy with fibrates must be undertaken cautiously and only after risk-benefit analysis (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects, 7 WARNINGS AND PRECAUTIONS, Pharmacokinetic Interactions and 9.4 Drug-Drug Interactions).
Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to <18 years of age)
The recommended starting dose of PRO-ATORVASTATIN is 10 mg/day; the maximum recommended dose is 20 mg/day (doses greater than 20 mg/day have not been studied in this patient population). Doses should be individualized according to the recommended goal of therapy (see 1.1 Pediatrics and 14 CLINICAL TRIALS). Adjustments should be made at intervals of 4 weeks or more.
Health Canada has not authorized an indication for pediatric use in a population under 10 years of age.
Prevention of Cardiovascular Disease
The recommended starting dose of PRO-ATORVASTATIN for the primary prevention of myocardial infarction is 10 mg/day.
For secondary prevention of myocardial infarction, optimal dosing may range from 10 mg to 80 mg atorvastatin once daily, to be given at the discretion of the prescriber, taking into account the expected benefit and safety considerations relevant to the patient to be treated.
Dosage in Patients with Renal Insufficiency
Patients with a history of renal insufficiency of unknown severity and severe renal insufficiency [creatinine clearance <30 mL/min (<0.5 mL/sec)] should be given lowest dose (10 mg/day) of PRO-ATORVASTATIN. (see 7 WARNINGS AND PRECAUTIONS, Renal).
Drug discontinuation
If the patient becomes pregnant while taking PRO-ATORVASTATIN, the drug should be discontinued immediately (see 7.1.1 Pregnant Women).
If increases in alanine aminotransferase (ALT) or aspartate aminotransferase (AST) show evidence of progression, particularly if they rise to greater than 3 times the upper limit of normal and are persistent, the dosage should be reduced or the drug discontinued (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
PRO-ATORVASTATIN therapy should be temporarily withheld or discontinued in any patient with an acute serious condition suggestive of myopathy or having a risk factor predisposing to the development of renal failure secondary to rhabdomyolysis (such as sepsis, severe acute infection, hypotension, major surgery, trauma, severe metabolic, endocrine and electrolyte disorders, and uncontrolled seizures). PRO-ATORVASTATIN therapy should be discontinued if markedly elevated CK levels occur or myopathy is diagnosed or suspected (see 7 WARNINGS AND PRECAUTIONS, Musculoskeletal).
PRO-ATORVASTATIN should be discontinued if hypersensitivity is suspected (see 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance).
If it is suspected a patient has developed interstitial lung disease, statin therapy should be discontinued (see 8.5 Post-Market Adverse Reactions).
If serious liver injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs during treatment with PRO-ATORVASTATIN, promptly interrupt therapy (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
4.4 Administration
Doses can be given at any time of the day, preferably in the evening, with or without food.
4.5 Missed dose
If patient misses a dose, it should be taken immediately unless the time is close to the next dose. In such an event, patient should wait for next scheduled dose and continue on the regular schedule. A double dose should not be taken to make up for a missed dose.
5 OVERDOSAGE
There is no specific treatment for atorvastatin overdosage. Should an overdose occur, the patient should be treated symptomatically and supportive measures instituted as required. Due to extensive drug binding to plasma proteins, hemodialysis is not expected to significantly enhance atorvastatin clearance (see 8 ADVERSE REACTIONS).
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets: 10 mg, 20 mg, 40 mg and 80 mg atorvastatin | Calcium acetate, colloidal silicon dioxide, croscarmellose sodium, hydroxypropyl cellulose, hydroxypropyl methylcellulose, magnesium stearate, microcrystalline cellulose, polyethylene glycol, sodium carbonate, titanium dioxide. |
PRO-ATORVASTATIN (atorvastatin calcium) tablets are formulated for oral administration and are available as tablet in dosage strength of 10 mg, 20 mg, 40 mg and 80 mg.
10 mg: Each tablet contains 11 mg atorvastatin calcium propylene glycol solvate, equivalent to 10 mg free acid. White to off-white, oval, biconvex film-coated tablets. Engraved “APO” on one side, “A10” on the other side. Available in bottles of 90, 100 and 500 tablets, blisters of 30.
20 mg: Each tablet contains 22 mg atorvastatin calcium propylene glycol solvate, equivalent to 20 mg free acid. White to off-white, oval, biconvex film-coated tablets. Engraved “APO” on one side, “ATV20” on the other side. Available in bottles of 90, 100 and 500 tablets, blisters of 30.
40 mg: Each tablet contains 44 mg atorvastatin calcium propylene glycol solvate, equivalent to 40 mg free acid. White to off-white, oval, biconvex film-coated tablets. Engraved “APO” on one side, “ATV40” on the other side. Available in bottles of 90, 100 and 500 tablets, blisters of 30.
80 mg: Each tablet contains 88 mg atorvastatin calcium propylene glycol solvate, equivalent to 80 mg free acid. White to off-white, oval, biconvex film-coated tablets. Engraved “APO” on one side, “ATV80” on the other side. Available in bottles of 90, 100 and 500 tablets, blisters of 30.
7 WARNINGS AND PRECAUTIONS
General
Patients should be advised to inform health professionals of the prior use of
PRO-ATORVASTATIN or any other lipid-lowering agents.
Cardiovascular
Hemorrhagic Stroke in Patients with Recent Stroke or Transient Ischemic Attack (TIA)
The highest dose of PRO-ATORVASTATIN (80 mg) was associated with an increased risk of hemorrhagic stroke in a post-hoc analysis of a clinical study in 4,731 patients without coronary heart disease (CHD) who had a stroke or TIA within the preceding six months compared to placebo.
Patients with hemorrhagic stroke on entry appeared to be at increased risk for recurrent hemorrhagic stroke. The potential risk of hemorrhagic stroke should be carefully considered before initiating treatment with atorvastatin in patients with recent (1 to 6 months) stroke or TIA.
Effect on Ubiquinone (CoQ10) Levels
Significant decreases in circulating ubiquinone levels in patients treated with atorvastatin and other statins have been observed. The clinical significance of a potential long-term statin- induced deficiency of ubiquinone has not been established. It has been reported that a decrease in myocardial ubiquinone levels could lead to impaired cardiac function in patients with borderline congestive heart failure. CoQ10 Levels should be measured when clinically indicated.
Endocrine and Metabolism
Endocrine Function
HMG-CoA reductase inhibitors interfere with cholesterol synthesis and as such might theoretically blunt adrenal and/or gonadal steroid production. Clinical studies with atorvastatin and other HMG-CoA reductase inhibitors have suggested that these agents do not reduce plasma cortisol concentration or impair adrenal reserve and do not reduce basal plasma testosterone concentration. However, the effects of HMG-CoA reductase inhibitors on male fertility have not been studied in adequate numbers of patients. The effects, if any, on the pituitary-gonadal axis in premenopausal women are unknown.
Patients treated with atorvastatin who develop clinical evidence of endocrine dysfunction should be evaluated appropriately. Caution should be exercised if an HMG-CoA reductase inhibitor or other agent used to lower cholesterol levels is administered to patients receiving other drugs (e.g. ketoconazole, spironolactone or cimetidine) that may decrease the levels of endogenous steroid hormones.
Increases in fasting glucose and HbA1c levels have been reported with inhibitors of HMG-CoA reductase as a class. For some patients, at high risk of diabetes mellitus, hyperglycemia was sufficient to shift them to the diabetes status. The benefit of treatment continues to outweigh the small increased risk. Periodic monitoring of these patients is recommended.
Effect on Lipoprotein (a)
In some patients, the beneficial effect of lowered total cholesterol and LDL-C levels may be partly blunted by a concomitant increase in Lp(a) lipoprotein concentrations. Present knowledge suggests the importance of high Lp(a) levels as an emerging risk factor for coronary heart disease. It is thus desirable to maintain and reinforce lifestyle changes in high risk patients placed on atorvastatin therapy.
Patients with Severe Hypercholesterolemia
Higher drug dosages (80 mg/day) required for some patients with severe hypercholesterolemia (including familial hypercholesterolemia) are associated with increased plasma levels of atorvastatin. Caution should be exercised in such patients who are also severely renally impaired, elderly, or are concomitantly being administered digoxin or CYP 3A4 inhibitors (see 7 WARNINGS AND PRECAUTIONS, Pharmacokinetic Interactions, 7 WARNINGS AND PRECAUTIONS, Muscle Effects; 9.4 Drug-Drug Interactions; 4 DOSAGE AND ADMINISTRATION).
Hepatic/Biliary/Pancreatic
Hepatic Effects
In clinical trials, persistent increases in serum transaminases greater than three times the upper limit of normal occurred in <1% of patients who received atorvastatin calcium. When the dosage of atorvastatin calcium was reduced, or when drug treatment was interrupted or discontinued, serum transaminase levels returned to pretreatment levels. The increases were generally not associated with jaundice or other clinical signs or symptoms. Most patients continued treatment with a reduced dose of atorvastatin calcium without clinical sequelae.
Liver function tests should be performed before the initiation of treatment, and repeated as clinically indicated. There have been rare post marketing reports of fatal and non-fatal hepatic failure in patients taking statins, including atorvastatin. If an alternate etiology is not found, do not restart PRO-ATORVASTATIN.
PRO-ATORVASTATIN, as well as other HMG-CoA reductase inhibitors, should be used with caution in patients who consume substantial quantities of alcohol and/or have a past history of liver disease. Active liver disease or unexplained transaminase elevations are contraindications to the use of PRO-ATORVASTATIN; if such a condition should develop during therapy, the drug should be discontinued.
Musculoskeletal
Pharmacokinetic Interactions
The use of HMG-CoA reductase inhibitors has been associated with severe myopathy, including rhabdomyolysis, which may be more frequent when they are co-administered with drugs that inhibit the cytochrome P-450 enzyme system. Atorvastatin is metabolized by cytochrome P-450 isoform 3A4 and as such may interact with agents that inhibit this enzyme (see 7 WARNINGS AND PRECAUTIONS, Muscle effects, and
9.2 Drug Interactions Overview).
Muscle Effects
Effects on skeletal muscle such as myalgia, myositis, myopathy and rarely, rhabdomyolysis have been reported in patients treated with atorvastatin calcium.
Rare cases of rhabdomyolysis, with acute renal failure secondary to myoglobinuria, have been reported with atorvastatin calcium and with other HMG-CoA reductase inhibitors.
Myopathy, defined as muscle pain or muscle weakness in conjunction with increases in creatine kinase (CK) values to greater than ten times the upper limit of normal, should be considered in any patient with diffuse myalgia, muscle tenderness or weakness, and/or marked elevation of CK. Patients should be advised to report promptly any unexplained muscle pain, tenderness or weakness, particularly if accompanied by malaise or fever. Patients who develop any signs or symptoms suggestive of myopathy should have their CK levels measured.
Pre-disposing Factors for Myopathy/Rhabdomyolysis: PRO-ATORVASTATIN, as with other HMG-CoA reductase inhibitors, should be prescribed with caution in patients with pre-disposing factors for myopathy/rhabdomyolysis. Such factors include:
- Personal or family history of hereditary muscular disorders
- Previous history of muscle toxicity with another HMG-CoA reductase inhibitor
- Concomitant use of a fibrate, or niacin
- Hypothyroidism
- Alcohol abuse
- Excessive physical exercise
- Age > 65 years
- Renal impairment
- Hepatic impairment
- Diabetes with hepatic fatty change
- Surgery and trauma
- Frailty
- Situations where an increase in plasma levels of active ingredient may occur
The risk of myopathy and rhabdomyolysis is increased with concurrent administration of drugs that increase the systemic concentration of atorvastatin via the inhibition of CYP 3A4 or transporter proteins (see 7 WARNING AND PRECAUTIONS, Pharmacokinetic Interactions; 9.4 Drug-Drug Interactions).
Although patients with renal impairment are known to be predisposed to the development of rhabdomyolysis with administration of HMG-CoA reductase inhibitors (also known as statins), those with a history of renal impairment may also be predisposed to the development of rhabdomyolysis. Such patients merit close monitoring for skeletal muscle effects.
There have been rare reports of an immune-mediated necrotizing myopathy (IMNM) during or after treatment with statins (see 8.5 Post-Market Adverse Reactions). IMNM is clinically characterized by:
- persistent proximal muscle weakness and elevated serum creatine kinase, which persist despite discontinuation of statin treatment
- positive anti-HMG CoA reductase antibody
- muscle biopsy showing necrotizing myopathy without significant inflammation
- improvement with immunosuppressive agents.
Myasthenia Gravis/Ocular Myasthenia
Statins may in rare instances induce or aggravate the conditions in patients with myasthenia gravis or ocular myasthenia (see 8.5 Post-Market Adverse Reactions) including causing recurrence when the same or a different statin was administered. PRO-ATORVASTATIN should be used with caution in patients with these conditions and should be discontinued if the symptoms are induced or aggravated.
Ophthalmologic
Effect on the Lens
Current long-term data from clinical trials do not indicate an adverse effect of atorvastatin on the human lens.
Renal
Plasma concentrations and LDL-C lowering efficacy of atorvastatin calcium was shown to be similar in patients with moderate renal insufficiency compared with patients with normal renal function. However, since several cases of rhabdomyolysis have been reported in patients with a history of renal insufficiency of unknown severity, as a precautionary measure and pending further experience in renal disease, the lowest dose (10 mg/day) of PRO-ATORVASTATIN should be used in these patients. Similar precautions apply in patients with severe renal insufficiency [creatinine clearance <30 mL/min (<0.5 mL/sec)]; the lowest dosage should be used and implemented cautiously (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects; 9 DRUG INTERACTIONS, 4.2 Recommended Dose and Dosage Adjustment).
Sensitivity/Resistance
An apparent hypersensitivity syndrome has been reported with other HMG-CoA reductase inhibitors which has included 1 or more of the following features: anaphylaxis, angioedema, lupus erythematous-like syndrome, polymyalgia rheumatica, vasculitis, purpura, thrombocytopenia, leukopenia, hemolytic anemia, positive ANA, ESR increase, eosinophilia, arthritis, arthralgia, urticaria, asthenia, photosensitivity, fever, chills, flushing, malaise, dyspnea, toxic epidermal necrolysis, erythema multiforme, including Stevens-Johnson syndrome.
Although to date hypersensitivity syndrome has not been described as such.
Reproductive Health: Female and Male Potential
Cholesterol and other products of cholesterol biosynthesis are essential components for fetal development (including synthesis of steroids and cell membranes). PRO-ATORVASTATIN should be administered to women of childbearing age only when such patients are highly unlikely to conceive and have been informed of the possible harm. Atherosclerosis being a chronic process, discontinuation of lipid metabolism regulating drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hypercholesterolemia. (see 2 CONTRAINDICATIONS, 7.1.1 Pregnant Women)
Fertility -There is no available data on effect of atorvastatin on human fertility. Non-clinical studies did not show an effect on animal fertility (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1 Special Populations
7.1.1 Pregnant Women
PRO-ATORVASTATIN is contraindicated during pregnancy (see 2 CONTRAINDICATIONS).
The extent of exposure in pregnancy during clinical trials: No experience.
PRO-ATORVASTATIN should be administered to women of childbearing age only when such patients are highly unlikely to conceive and have been informed of the potential hazards. If the patient becomes pregnant while taking PRO-ATORVASTATIN, the drug should be discontinued and the patient apprised of the potential risk to the fetus.
There is evidence from animal experimental studies that HMG-CoA reductase inhibitors may affect the development of embryos or fetuses. In rats, rabbits and dogs atorvastatin had no effect on fertility and was not teratogenic, however, at maternally toxic doses fetal toxicity was observed in rats and rabbits. The development of the rat offspring was delayed and post-natal survival reduced during exposure of the dams to high doses of atorvastatin. In rats, there is evidence of placental transfer (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1.2 Breastfeeding
It is unknown if atorvastatin calcium is excreted in human milk. Precaution should be exercised because many drugs can be excreted in human milk. Because of the potential for adverse reactions in nursing infants, women taking PRO-ATORVASTATIN should not breast-feed (see 2 CONTRAINDICATIONS). In rats, milk concentrations of atorvastatin are similar to those in plasma.
7.1.3 Pediatrics
Since the safety and tolerability profile of atorvastatin in pediatric patients (10 to <18 years) is generally similar to the known safety profile of atorvastatin in adult patients, similar warning apply to this patient population. Patients should be particularly monitored for liver enzymes (AST/ALT) and creatine kinase, and adverse events of interest (e.g.: headache, gastrointestinal, musculoskeletal and connective tissue disorders). Doses greater than 20 mg have not been studied in this patient population.
Safety and effectiveness of atorvastatin calcium in pediatric patients has not been determined in the prevention of myocardial infarction.
Atorvastatin calcium had no effect on growth or sexual maturation in boys and in girls. The effects on menstrual cycle were not assessed [see 14 CLINICAL TRIALS; 8.2.1 Clinical Trial Adverse Reactions - Pediatrics; and 4.2 Recommended Dose and Dose Adjustment, Heterozygous Familial Hypercholesterolemia in Pediatric Patients (10 to <18 years of age)].
Adolescent females should be counselled on appropriate contraceptive methods while on PRO-ATORVASTATIN therapy (see 2 CONTRAINDICATIONS and 7.1.1 Pregnant Women).
Atorvastatin calcium has not been studied in controlled clinical trials involving pre-pubertal patients or patients younger than 10 years of age. For this patient population, there are limited data available from uncontrolled, open label studies (see 1.1 Pediatrics, 8.2.1 Clinical Trial Adverse Reactions – Pediatrics, Heterozygous Familial Hypercholesterolemia in Pediatric Patients and 10.3 Pharmacokinetics, Special Populations and Conditions: Pediatrics).
Doses of atorvastatin calcium up to 80 mg/day for 1 year have been evaluated in 8 pediatric patients with homozygous familial hypercholesterolemia (see 14 CLINICAL TRIALS - Heterozygous Familial Hypercholesterolemia in pediatric patients).
7.1.4 Geriatrics
Treatment experience in adults 70 years or older (N=221) with doses of atorvastatin calcium up to 80 mg/day has demonstrated that the safety and effectiveness of atorvastatin in this population was similar to that of patients <70 years of age. Pharmacokinetic evaluation of atorvastatin in subjects over the age of 65 years indicates an increased AUC. As a precautionary measure, the lowest dose should be administered initially (see 10.3 Pharmacokinetics, Special Populations and Conditions: Geriatrics).
Elderly patients may be more susceptible to myopathy (see 7 WARNINGS AND PRECAUTIONS, Pre-disposing Factors for Myopathy/Rhabdomyolysis).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most serious adverse reactions associated with atorvastatin calcium were rhabdomyolysis, with acute renal failure secondary to myoglobinuria, myalgia, myositis, myopathy (see 7 WARNINGS AND PRECAUTIONS, Musculoskeletal, 8.5 Post-Market Adverse Reactions). The most commonly reported adverse reactions in placebo controlled trials, that may be associated with atorvastatin therapy were nasopharyngitis (8.3%), arthralgia (6.9%), diarrhea (6.8%), pain in extremity (6.0%), and hyperglycemia (5.9%) (see 8.2 Clinical Trial Adverse Reactions).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse reactions with atorvastatin calcium have usually been mild and transient. In the atorvastatin placebo-controlled clinical trial database of 16,066 (8755 atorvastatin calcium versus 7311 placebo) patients treated for a median period of 53 weeks, 5.2% of patients on atorvastatin discontinued due to adverse reactions compared to 4.0% of the patients on placebo.
Adverse experiences occurring at an incidence ≥1% in patients participating in placebo- controlled clinical studies of atorvastatin calcium and reported to be possibly, probably or definitely drug related are shown in Table 1 below:
Table 1: Associated Adverse Events Reported in ≥ 1 % of Patients in Placebo Controlled Clinical Trials
| Atorvastatin % (n=8755) | Placebo % (n=7311) | |
|---|---|---|
| 8.3 | 8.2 | Nasopharyngitis |
Metabolism and nutrition disorders: Hyperglycemia | 5.9 | 5.5 |
| Liver function test abnormal* | 4.1 | 2.0 |
| Blood creatine phosphokinase increased | 1.9 | 1.8 |
| Musculoskeletal and connective tissue disorders: | ||
| Arthralgia | 6.9 | 6.5 |
| Pain in extremity | 6.0 | 5.9 |
| Musculoskeletal pain | 3.8 | 3.6 |
| Muscle spasms | 3.6 | 3.0 |
| Myalgia | 3.5 | 3.1 |
| Joint swelling | 1.3 | 1.2 |
| Nervous system disorders: | 6.5 | 6.7 |
| Headache | ||
| Respiratory, thoracic and mediastinal disorders: | ||
| Pharyngolaryngeal pain | 2.3 | 2.1 |
| Epistaxis | 1.2 | 1.1 |
| Nausea | 4.0 | 3.5 |
| Constipation | 3.9 | 4.3 |
| Flatulence | 1.2 | 1.0 |
| General disorders and administration site conditions: | 1.1 | 1.1 |
| Asthenia | ||
| Infections and Infestations: | ||
| Atorvastatin % (n=8755) | Placebo % (n=7311) | |
| Gastrointestinal disorders: | ||
| Diarrhea | 6.8 | 6.3 |
| Dyspepsia | 4.6 | 4.3 |
*alanine aminotransferase increased, aspartate aminotransferase increased, blood bilirubin increased, hepatic enzyme increased, liver function test abnormal and transaminases increased.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Heterozygous Familial Hypercholesterolemia in Pediatric Patients (ages 10 to 17 years)
In a 26-week controlled study in boys and postmenarchal girls (n=187, where 140 patients received atorvastatin calcium), the safety and tolerability profile of atorvastatin calcium 10 to 20 mg daily was similar to that of placebo. The adverse events reported in ≥1% of patients were as follows: abdominal pain, depression and headache (see 14 CLINICAL TRIALS and 7.1.3 Pediatrics).
In an uncontrolled, open-label, 3-year study in children with heterozygous familial hypercholesterolemia ages 6 and above, physical growth (height, weight and BMI) and sexual maturation (Tanner Stage) appear to be consistent with the trend in the general pediatric population when atorvastatin was used as indicated. Patients should be evaluated for growth abnormalities if shifts in growth percentiles become evident. The safety and tolerability profile in pediatric patients had similar patterns to the known safety profile of atorvastatin in adult patients. Patients should be particularly monitored for liver enzymes (AST/ALT) and creatine kinase, and adverse events of interest (e.g.: headache, gastrointestinal, musculoskeletal and connective tissue disorders).
8.3 Less Common Clinical Trial Adverse Reactions
The following additional adverse events were reported in placebo-controlled clinical trials during atorvastatin calcium therapy: Muscle cramps, myositis, muscle fatigue, myopathy, paresthesia, peripheral neuropathy, pancreatitis, hepatitis, cholestatic jaundice, cholestasis, anorexia, vomiting, abdominal discomfort, alopecia, pruritus, rash, urticaria, erectile dysfunction, nightmare, vision blurred, tinnitus, eructation, neck pain, malaise, pyrexia and white blood cells urine positive.
In summary, the adverse events occurring at a frequency <1% are listed below:
Ear and labyrinth disorders: tinnitus
Eye disorders: vision blurred
Gastrointestinal disorders: abdominal discomfort, anorexia, eructation, pancreatitis, vomiting
General disorders and administration site conditions: malaise; pyrexia
Hepatobiliary disorders: hepatitis, cholestasis, cholestatic jaundice
Investigations: white blood cells urine positive
Musculoskeletal and connective tissue disorders: muscle fatigue, neck pain, myopathy, myositis, muscle cramps
Neurological: peripheral neuropathy, paresthesia
Psychiatric disorders: nightmare
Skin and subcutaneous tissue disorders: alopecia, rash, pruritus, urticarial
Urogenital: erectile dysfunction
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial findings: The criteria for clinically significant laboratory changes were >3 X the upper limit of normal (ULN) for liver enzymes, and >5 X ULN for creatine kinase. A total of 8 unique subjects met one or more of these criteria during the double-blind phase. Hence, the incidence of patients who experienced abnormally high enzymatic levels (AST/ALT and creatine kinase) was > 4% (8/187).
Five atorvastatin and one placebo subjects had increases in CK >5 X ULN during the double- blind phase; two of the five atorvastatin treated subjects had increases in CK > 10 X ULN.
There were 2 subjects who had clinically significant increases in ALT.
Laboratory Tests: Increases in serum transaminase levels and serum glucose have been noted in clinical trials (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; 8.2 Clinical Trial Adverse Reactions).
8.5 Post-Market Adverse Reactions
The following adverse events have also been reported during post-marketing experience with atorvastatin calcium, regardless of causality assessment:
Rare reports: severe myopathy with or without rhabdomyolysis (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects, 7 WARNINGS AND PRECAUTIONS, Renal and 9 DRUG INTERACTIONS).
There have been rare reports of immune-mediated necrotizing myopathy with statins (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects).
Isolated reports: Gynecomastia, thrombocytopenia, arthralgia and allergic reactions including urticaria, angioedema (angioneurotic edema), anaphylaxis and bullous rashes (including erytheme multiforme, Stevens-Johnson syndrome and toxic epidermal necrolysis), fatigue, myositis, back pain, chest pain, malaise, dizziness, amnesia, peripheral edema, weight gain, abdominal pain, insomnia, hypoesthesia, tinnitus, tendon rupture, pancreatitis, dysgeusia and Ewing’s sarcoma (pediatric).
Eye disorders: ocular myasthenia, see 7 WARNINGS AND PRECAUTIONS, Ophthalmologic.
Musculoskeletal: Myasthenia gravis.
Cases of erectile dysfunction have been reported in association with the use of statins.
The following adverse events have been reported with some statins:
- Sleep disturbances, including insomnia and nightmares;
- Mood related disorders, including depression;
- Very rare cases of interstitial lung disease, especially with long term therapy.
Endocrine disorders: Increases in fasting glucose and HbA1c levels have been reported with atorvastatin calcium.
There have been rare post-marketing reports of cognitive impairment (e.g. memory loss, forgetfulness, amnesia, memory impairment, confusion) associated with statin use. These cognitive issues have been reported for all statins. The reports are generally non-serious and reversible upon statin discontinuation, with variable times to symptom onset (1 day to years)
and symptom resolution (median of 3 weeks).
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Pharmacokinetic interaction studies conducted with drugs in healthy subjects may not detect the possibility of a potential drug interaction in some patients due to differences in underlying diseases and use of concomitant medications (see also 7 WARNINGS AND PRECAUTIONS, Renal; 7 WARNINGS AND PRECAUTIONS, Patients with Severe Hypercholesterolemia; 7.1 Special Populations).
Concomitant Therapy with Other Lipid Metabolism Regulators: Based on post-marketing surveillance, increase in the risk of myopathy may be seen when given concomitantly with HMG-CoA reductase inhibitors (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects; 9.4 Drug-Drug Interactions, Table 2 - Established or Potential Drug-Drug Interactions).
Cytochrome P-450-mediated Interactions: Atorvastatin is metabolized by the cytochrome P-450 isoenzyme, CYP 3A4. Interaction may occur when PRO-ATORVASTATIN is administered with inhibitors of cytochrome P450 3A4. Concomitant administration can lead to increased plasma concentrations of atorvastatin (see 7 WARNINGS AND PRECAUTIONS, Pharmacokinetic Interactions; 7 WARNINGS AND PRECAUTIONS, Muscle Effects; 7 WARNINGS AND PRECAUTIONS, Renal and 7 WARNINGS AND PRECAUTIONS, Endocrine Function; 9.4 Drug-Drug Interactions, Table 2 – Established or Potential Drug-Drug Interactions).
Transporter Inhibitors: Atorvastatin is a substrate of the hepatic transporters (see section 9.4 Drug-Drug Interactions). Active liver disease or unexplained transaminase elevations are contraindications to the use of PRO-ATORVASTATIN; if treatment for active liver disease is necessary during therapy with PRO-ATORVASTATIN, the drug should be discontinued (see 2 CONTRAINDICATIONS).
Inducers of cytochrome P450 3A: Concomitant administration of atorvastatin with inducers of cytochrome P450 3A4 can lead to variable reductions in plasma concentrations of atorvastatin (see 9.4 Drug-Drug Interactions).
9.3 Drug-Behavioural Interactions
PRO-ATORVASTATIN, as well as other HMG-CoA reductase inhibitors, should be used with caution in patients who consume substantial quantities of alcohol and/or have a past history of liver disease. Plasma concentrations of atorvastatin are markedly increased in patients with chronic alcoholic liver disease (See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic)
9.4 Drug-Drug Interactions
Pharmacokinetic interaction studies have been conducted in healthy subjects with 3 macrolide antibiotics: erythromycin and clarithromycin (both of which inhibit CYP 3A4), and with azithromycin. Coadministration of atorvastatin with erythromycin or clarithromycin, resulted in moderately increased atorvastatin plasma levels but atorvastatin plasma levels were not altered by azithromycin. Twelve healthy subjects were administered atorvastatin 10 mg on days 1 and 15; erythromycin 500 mg QID was administered from days 8 to 19. Erythromycin increased atorvastatin Cmax (ratio of Cmax: 1.38) and AUC (ratio of AUC: 1.33). In a second study, atorvastatin 10 mg was administered daily for 8 days; clarithromycin (500 mg BID) or azithromycin (500 mg QD) was coadministered from days 6 to 8 (N=12/treatment). Coadministration with clarithromycin increased atorvastatin AUC (ratio of AUC: 1.82) and Cmax (ratio of Cmax: 1.56), but atorvastatin plasma levels were not significantly altered by coadministration with azithromycin.
Steady-state, open-label, pharmacokinetic studies with digoxin have been performed in healthy subjects with both low and high doses of atorvastatin. Atorvastatin (10 mg or 80 mg QD; N=11 and N=12, respectively), was administered from days 1 to 20 and digoxin (0.25 mg QD) from days 11 to 20. At steady-state, atorvastatin 10 mg daily had no significant effect on steady-state digoxin pharmacokinetics. However, following co-administration with atorvastatin 80 mg QD, the mean steady-state digoxin AUC and Cmax increased (ratio of atorvastatin AUC: 1.15; ratio of atorvastatin Cmax: 1.20). Patients taking digoxin should be
monitored appropriately.
The effect of amlodipine on the pharmacokinetics of atorvastatin was assessed at steady-state in a randomized, open-label, placebo-controlled, crossover study in healthy male subjects (N=16). Atorvastatin (80 mg QD) was administered with amlodipine (10 mg QD) or placebo from days 1 to 8. Following a 14 day washout, the alternate combination was administered from days 22 to 29. At steady-state, the coadministration of maximum doses of atorvastatin and amlodipine did not significantly alter the pharmacokinetics of atorvastatin and there were no apparent changes in blood pressure or heart rate.
The effect of quinapril on the pharmacokinetics of atorvastatin was assessed in a randomized, open-label study in healthy volunteers (N=22). Single doses of atorvastatin (10 mg) were administered on days 1 to 14, and single doses of quinapril (80 mg) were administered on days 1 to 7 or days 8 to 14. The mean Tmax value for atorvastatin during steady state quinapril administration was shortened by 1.25 hours compared to that of atorvastatin administered alone but with no change in absorption/AUC or Cmax. No significant changes in blood pressure or heart rates were observed.
Concomitant administration of atorvastatin 20 to 40 mg and itraconazole 200 mg daily resulted in an increase in atorvastatin AUC (ratio of atorvastatin AUC:3.3 and ratio of atorvastatin Cmax: 1.20 for atorvastatin 40 mg only).
Concomitant administration of atorvastatin 10 mg and cyclosporine 5.2 mg/kg/day resulted in an increase in exposure to atorvastatin (ratio of atorvastatin AUC: 8.7 and ratio of atorvastatin Cmax: 10.7).
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Proper name | Effect | Clinical comment | |
|---|---|---|---|
| Antacids | |||
↓ in plasma concentrations of atorvastatin calcium (ratio of atorvastatin AUC: 0.66 and ratio of atorvastatin Cmax: 0.67) following administration of aluminum and magnesium based antacids, such as Maalox® TC Suspension. LDL-C reduction was not altered; TG-lowering effect of atorvastatin calcium may be affected. | This decrease in exposure should be considered when prescribing atorvastatin with antacids. | ||
Antihypertensive Agents:
Amlodipine
In healthy subjects, atorvastatin PK were not altered by the
coadministration of atorvastatin calcium 80 mg and amlodipine 10 mg at steady state. No apparent changes in BP or HR.
In healthy volunteers, co-
administration of multiple 10 mg doses of amlodipine with 80 mg of atorvastatin resulted in no clinical significant change in the AUC or Cmax
| Close monitoring is required. | ||
|---|---|---|
| Quinapril | or Tmax of atorvastatin (ratio of atorvastatin AUC: 1.18 and ratio of atorvastatin Cmax: 0.91). Steady-state quinapril dosing of 80 mg QD did not significantly affect the PK profile of atorvastatin tablets 10 mg QD. | |
| Proper name | Effect | Clinical comment |
| Antipyrine | Atorvastatin calcium had no effect on the PK of antipyrine Ratio of antipyrine AUC: 1.03 and ratio of antipyrine Cmax: 0.89 with atorvastatin 80 mg QD and antipyrine 600 mg SD. | Antipyrine was used as a non- specific model for drugs metabolized by the microsomal hepatic enzyme system (cytochrome P-450 system). Interactions with other drugs metabolized via the same cytochrome isozymes are not expected. |
Bile Acid Sequestrants Proper name | Patients with mild to moderate HC: ↑ LDL-C reduction (-45%) when atorvastatin calcium 10 mg and colestipol 20 g were coadministered than when either drug was administered alone (-35% for atorvastatin calcium and -22% for colestipol). Patients with severe HC: LDL-C reduction was similar (-53%) when atorvastatin calcium 40 mg and colestipol 20 g were coadministered when compared to that with atorvastatin calcium 80 mg alone. ↓ plasma atorvastatin concentration (ratio of 0.74) when atorvastatin calcium 40 mg plus colestipol 20 g were coadministered compared with atorvastatin calcium 40 mg alone. | When PRO-ATORVASTATIN is used concurrently with colestipol or any other resin, an interval of at least 2 hours should be maintained between the two drugs, since the absorption of PRO-ATORVASTATIN may be impaired by the resin. |
| Effect | Clinical comment | |
| Digoxin | Patients taking digoxin should be monitored appropriately. | |
| However, the combination drug therapy was less effective in lowering TG than atorvastatin calcium monotherapy in both types of hypercholesterolemic patients. | ||
| Cimetidine | No effect on plasma concentrations (ratio of atorvastatin AUC: 1.00 and ratio of atorvastatin Cmax: 0.89) or LDL-C lowering efficacy of atorvastatin calcium ↓ in TG-lowering effect of atorvastatin calcium from 34% to 26% | This decrease in TG-lowering should be considered when prescribing atorvastatin with cimetidine. |
| Colchicine | Although interaction studies with atorvastatin and colchicine have not been conducted, cases of myopathy have been reported with atorvastatin co-administrated with colchicine. | Caution should be exercised when prescribing atorvastatin with colchicine (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects). |
| Coumarin Anticoagulants | No clinically significant effect on prothrombin time | Atorvastatin calcium had no clinically significant effect on prothrombin time when administered to patients receiving chronic warfarin therapy. |
| Cyclosporine | Concomitant administration of atorvastatin 10 mg and cyclosporine 5.2 mg/kg/day resulted in an increase in exposure to atorvastatin (ratio of atorvastatin AUC: 8.7; ratio of atorvastatin Cmax: 10.7). In healthy subjects, digoxin PK at steady-state were not significantly altered by coadministration of digoxin 0.25 mg and atorvastatin calcium 10 mg daily. ↑ in digoxin steady-state concentrations (ratio of atorvastatin AUC:1.15 and ratio of atorvastatin Cmax: 1.20) following coadministration of digoxin 0.25 mg and atorvastatin | Concomitant use is contraindicated. (See 2 CONTRAINDICATIONS; 7 WARNINGS AND PRECAUTIONS, Muscle Effects). |
Although interaction studies with atorvastatin and fusidic acid have not been conducted, rhabdomyolysis resulting in fatal outcome has been reported in patients receiving a combination of statins, including atorvastatin, and fusidic acid. The mechanism of this interaction is not known. | The concurrent use of atorvastatin and fusidic acid should be avoided. In patients where the use of systemic fusidic acid is considered essential, statin treatment should be discontinued throughout the duration of fusidic acid treatment. Statin therapy may be re-introduced at least seven days after the last dose of | |
| Proper name | Effect | Clinical comment |
| calcium 80 mg daily. | ||
| Diltiazem Hydrochloride | Steady-state diltiazem increases the atorvastatin exposure, based on AUCLASTs, of a single dose of atorvastatin by approximately 50% (ratio of atorvastatin AUC: 1.51 and ratio of atorvastatin Cmax: 1.00). | |
| Efavirenz | Ratio of AUC: 0.59 and ratio of Cmax: 1.01 with atorvastatin 10 mg and Efavirenz 600 mg daily. | This decrease in exposure should be considered when prescribing atorvastatin with efavirenz. |
Fibric Acid Derivatives (Gemfibrozil, Fenofibrate, Bezafibrate) and Niacin (nicotinic acid) Fusidic Acid | ↑ in the risk of myopathy during treatment with other drugs in this class, including atorvastatin. Ratio of atorvastatin AUC: 1.35 and ratio of atorvastatin Cmax: 1.00 with atorvastatin 40 mg SD and Gemfibrozil 600 mg BID. Ratio of atorvastatin AUC: 1.03 and ratio of atorvastatin Cmax: 1.02 with atorvastatin 40 mg SD and Fenobibrate 160 mg BID. | The concomitant therapy with PRO-ATORVASTATIN and gemfibrozil should be avoided. The benefits and risks of combined therapy with PRO-ATORVASTATIN and fenofibrate, bezafibrate and niacin should be carefully considered; lower starting and maintenance doses of atorvastatin should be considered (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects). |
| Proper name | Effect | Clinical comment |
fusidic acid. Patients should be advised to seek medical advice immediately if they experience any symptoms of muscle weakness, pain or tenderness (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects). | ||
Hepatitis C virus inhibitors: Telaprevir Boceprevir | Ratio of atorvastatin AUC: 7.9 and ratio of atorvastatin Cmax: 10.6 with atorvastatin 20 mg SD and Telaprevir 750 mg q8h, 10 days* Ratio of atorvastatin AUC: 2.3 and ratio of atorvastatin Cmax: 2.7 with atorvastatin 40 mg SD and Boceprevir 800 mg TID, 7 days | Concomitant use of atorvastatin and drugs used for the treatment of active liver disease, such as HCV inhibitors, is contraindicated. (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS) Discontinue PRO-ATORVASTATIN if treatment for active liver disease is necessary. |
| Glecaprevir / Pibrentasvir | Ratio of atorvastatin AUC: 8.3 and ratio of atorvastatin Cmax: 22.0 with atorvastatin 10 mg QD for 7 days and Glecaprevir 400 mg QD/Pibrentasvir 120 mg QD for 7 days* | |
| Elbasvir / Grazoprevir | Ratio of atorvastatin AUC: 1.95 and ratio of atorvastatin Cmax: 4.3 with atorvastatin 10 mg SD and Elbasvir 50 mg QD/Grazoprevir 200 mg QD for 13 days* | |
| Simeprevir | Ratio of atorvastatin AUC: 2.12 and ratio of atorvastatin Cmax: 1.70 with atorvastatin 40 mg SD and Simeprevir 150 mg QD for 10 days* | |
| Ledipasvir / Sofosbuvir | Although interaction studies with atorvastatin and ledipasvir/sofosbuvir have not been conducted, cases of myopathy and rhabdomyolysis have been reported with atorvastatin co- administrated with ledipasvir/sofosbuvir. | The dose of PRO-ATORVASTATIN used in combination with letermovir should not exceed 20 mg daily. Patients should be closely monitored for statin-associated adverse events such as myopathy or rhabdomyolysis (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects). |
In healthy adults, coadministration of atorvastatin calcium (10 mg QD) and azithromycin (500 mg QD) did not significantly alter the plasma concentrations of atorvastatin. Ratio of atorvastatin AUC: 1.33 and ratio of atorvastatin Cmax: 1.38 with erythromycin (500 mg QID) when | See 7 WARNINGS AND PRECAUTIONS, Muscle Effects. | |
| Proper name | Effect | Clinical comment |
| Velpatasvir / Sofosbuvir | Co-administration of atorvastatin (40 mg) with velpatasvir (100 mg)/sofosbuvir (400 mg) resulted in increased exposure to atorvastatin by 1.68-fold for Cmax and 1.54-fold for AUC. | |
Itraconazole Letermovir Macrolide Antibiotics (azithromycin, clarithromycin, erythromycin). Clarithromycin and erythromycin are both CYP3A4 inhibitors | Concomitant administration of atorvastatin 20 to 40 mg and itraconazole 200 mg daily resulted in an increase in atorvastatin (ratio of atorvastatin AUC: 3.3 and ratio of atorvastatin Cmax: 1.20 for atorvastatin 40 mg only). Concomitant administration of atorvastatin 20 mg SD and letermovir 480 mg daily resulted in an increase in exposure to atorvastatin (ratio of AUC 3.29 and ratio of atorvastatin Cmax: 2.17). | The dose of PRO-ATORVASTATIN used in combination with itraconazole should not exceed 20 mg daily |
| Proper name | Effect | Clinical comment |
| coadministered with atorvastatin (10 mg QD) Ratio of atorvastatin AUC: 1.82 and ratio of atorvastatin Cmax: 1.56 with clarithromycin (500 mg BID) when coadministered with atorvastatin (10 mg QD) | ||
| Oral Contraceptives and Hormone Replacement Therapy | ↑ plasma concentrations (AUC levels) of norethindone (ratio of atorvastatin AUC: 1.28 and ratio of atorvastatin Cmax: 1.23) and ethinyl estradiol (ratio of atorvastatin AUC: 1.19 and ratio of atorvastatin Cmax: 1.30) following coadministration of atorvastatin calcium with an oral contraceptive containing 1 mg norethindone and 35 mcg ethinyl estradiol. In clinical studies, atorvastatin calcium was used concomitantly with estrogen replacement therapy without evidence to date of clinically significant adverse interactions. | These increases should be considered when selecting an oral contraceptive. |
| Protease Inhibitors (nelfinavir mesylate, lopinavir/ritonavir, tipranavir/ritonavir, saquinavir/ritonavir, darunavir/ritonavir, fosamprenavir/ritona vir, fosamprenavir) | ↑ plasma concentrations of atorvastatin when atorvastatin 10 mg QD is coadministered with nelfinavir mesylate 1250 mg BID. Ratio of atorvastatin AUC: 1.74 and ratio of atorvastatin Cmax: 2.2. Ratio of atorvastatin AUC: 5.9 and ratio of atorvastatin Cmax: 4.7 with atorvastatin 20 mg QD and Lopinavir 400 mg / Ritonavir 100 mg BID Ratio of atorvastatin AUC: 9.4 and ratio of atorvastatin Cmax: 8.6 with | The dose of PRO-ATORVASTATIN used in combination with nelfinavir should not exceed 40 mg daily. The concomitant therapy with PRO-ATORVASTATIN and the combination of lopinavir/ritonavir should be used with caution and lowest PRO-ATORVASTATIN dose necessary. (See 7 WARNINGS AND PRECAUTIONS, Muscle Effect) The concomitant therapy |
| Proper name | Effect | Clinical comment |
atorvastatin 10 mg SD and Tipranavir 500 mg BID / Ritonavir 200 mg BID, 7 days. Atorvastatin 10 mg SD had no effect on the PK of Tripanavir 500 mg BID / Ritonavir 200 mg BID, 7 days Ratio of atorvastatin AUC: 3.9 and ratio of atorvastatin Cmax: 4.3 with atorvastatin 40 mg QD for 4 days and Ritonavir 400 mg BID, 15 days / Saquinavir 400 mg BID† Ratio of atorvastatin AUC: 3.4 and ratio of atorvastatin Cmax: 2.2 with atorvastatin 10 mg QD for 4 days and Darunavir 300 mg BID/ Ritonavir 100 mg BID, 9 days Ratio of atorvastatin AUC: 2.5 and ratio of atorvastatin Cmax: 2.8 with atorvastatin 10 mg QD for 4 days and Fosamprenavir 700 mg BID/ritonavir 100 mg BID,14 days Ratio of atorvastatin AUC: 2.3 and ratio of atorvastatin Cmax: 4.0 with atorvastatin 10 mg QD for 4 days and Fosamprenavir 1400 mg BID, 14 days. Atorvastatin 10 mg QD for 4 days had the following effect on the PK of Fosamprenavir 1400 mg BID, 14 days: Ratio of atorvastatin AUC: 0.73 and ratio of atorvastatin Cmax: 0.82 Atorvastatin 10 mg QD, 4 days had no effect on the PK of Fosamprenavir 700 mg BID/ Ritonavir 100 mg BID, | with PRO-ATORVASTATIN and the combination of tipranavir/ritonavir or PRO-ATORVASTATIN and telaprevir should be avoided. The dose of PRO-ATORVASTATIN should be restricted to 20 mg daily when used in combination with saquinavir/ritonavir, darunavir/ritonavir, fosamprenavir alone or fosamprenavir/ritonavir. † The dose of saquinavir/ritonavir in this study is not the clinically used dose. The increase in atorvastatin exposure when used clinically is likely to be higher than what was observed in this study. Therefore caution should be applied and the lowest dose necessary should be used | |
| Proper name | Effect | Clinical comment |
| 14 days (ratio of atorvastatin AUC: 0.99 and ratio of atorvastatin Cmax: 0.94) | ||
| Rifampin | Co-administration: Ratios of AUC and Cmax are 1.12 and 2.9, respectively, for co-administered atorvastatin 40 mg single dose and 7 day Rifampin 600 mg daily vs. atorvastatin 40 mg single dose alone. Separate administration Ratio of atorvastatin AUC: 0.20 and ratio of atorvastatin Cmax: 0.60 with atorvastatin 40 mg single dose and Rifampin 600 mg daily (doses separated) | Due to the dual interaction mechanism of rifampin (cytochrome P450 3A4 induction and inhibition of hepatocyte uptake transporter OATP1B1), simultaneous co- administration of atorvastatin with rifampin is recommended, as delayed administration of atorvastatin after administration of rifampin has been associated with a significant reduction in atorvastatin plasma concentrations. |
Legend: HC = hypercholesterolemia; TG = Triglycerides; PK = pharmacokinetics; BP = Blood Pressure; HR = Heart Rate; AUC = Area under the curve
Ratio of AUC and Cmax represent ratio treatments (co-administered drug plus atorvastatin versus atorvastatin alone).
9.5 Drug-Food Interactions
PRO-ATORVASTATIN may be taken with or without food. Do not take with grapefruit juice. Coadministration of grapefruit juice has the potential to increase plasma concentrations of HMG CoA reductase inhibitors including PRO-ATORVASTATIN. The equivalent of 1.2 litres per day resulted in an increase in AUC (ratio of AUC up to 2.5) and Cmax (ratio of Cmax up to 1.71) of atorvastatin.
For 240 mL of grapefruit juice, the ratio of AUC was 1.37 and the ratio of Cmax was 1.16 for atorvastatin 40 mg.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
PRO-ATORVASTATIN may elevate serum transaminase and creatine kinase levels (from skeletal muscle). In the differential diagnosis of chest pain in a patient on therapy with
PRO-ATORVASTATIN, cardiac and noncardiac fractions of these enzymes should be determined.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Atorvastatin calcium is a synthetic lipid-lowering agent. It is a selective, competitive inhibitor of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase. This enzyme catalyzes the conversion of HMG-CoA to mevalonate, which is an early and rate-limiting step in the biosynthesis of cholesterol.
Atorvastatin calcium lowers plasma cholesterol and lipoprotein levels by inhibiting HMG-CoA reductase and cholesterol synthesis in the liver and by increasing the number of hepatic Low Density Lipoprotein (LDL) receptors on the cell-surface for enhanced uptake and catabolism of Low Density Lipoprotein (LDL).
Atorvastatin calcium reduces LDL-Cholesterol (LDL-C) and the number of LDL particles. Atorvastatin calcium also reduces Very Low Density Lipoprotein-Cholesterol (VLDL-C), serum triglycerides (TG) and Intermediate Density Lipoproteins (IDL), as well as the number of apolipoprotein B (apo B) containing particles, but increases High Density Lipoprotein-Cholesterol (HDL-C). Elevated serum cholesterol due to elevated LDL-C is a major risk factor for the development of cardiovascular disease. Low serum concentration of HDL-C is also an independent risk factor. Elevated plasma TG is also a risk factor for cardiovascular disease, particularly if due to increased IDL, or associated with decreased HDL-C or increased LDL-C.
Epidemiologic, clinical and experimental studies have established that high LDL-C, low HDL-C and high plasma TG promote human atherosclerosis and are risk factors for developing cardiovascular disease. Some studies have also shown that the total (TC):HDL-C ratio (TC:HDL-C) is the best predictor of coronary artery disease. In contrast, increased levels of HDL-C are associated with decreased cardiovascular risk. Drug therapies that reduce levels of LDL-C or decrease TG while simultaneously increasing HDL-C have demonstrated reductions in rates of cardiovascular mortality and morbidity.
10.2 Pharmacodynamics
The lowering of total cholesterol, LDL-C and ApoB have been shown to reduce the risk of cardiovascular events and mortality.
Atorvastatin calcium is a selective, competitive inhibitor of HMG-CoA reductase. In both subjects and in patients with homozygous and heterozygous familial hypercholesterolemia, nonfamilial forms of hypercholesterolemia, mixed dyslipidemia, hypertriglyceridemia, and dysbetalipoproteinemia, atorvastatin calcium has been shown to reduce levels of total cholesterol (total-C), LDL-C, apo B and total TG, and raises HDL-C levels.
Epidemiologic and clinical studies have associated the risk of coronary artery disease (CAD) with elevated levels of total-C, LDL-C and decreased levels of HDL-C. These abnormalities of lipoprotein metabolism are considered as major contributors to the development of the disease. Like LDL, cholesterol-enriched lipoproteins, including VLDL, IDL and remnants can also promote atherosclerosis. Elevated plasma triglycerides are frequently found in a triad with low HDL-C levels and small LDL particles, as well as in association with non-lipid metabolic risk factors for coronary heart disease (metabolic syndrome). Clinical studies have also shown that serum triglycerides can be an independent risk factor for CAD. CAD risk is especially increased if the hypertriglyceridemia is due to increased intermediate density lipoproteins (IDL) or associated with decreased HDL or increased LDL-C. In addition, high TG levels are associated with an increased risk of pancreatitis. Although epidemiological and preliminary clinical evidence link low HDL-C levels and high triglyceride levels with coronary artery disease and atherosclerosis, the independent effect of raising HDL or lowering TG on the risk of coronary and cerebrovascular morbidity and mortality has not been demonstrated in prospective, well- controlled outcome studies. Other factors, e.g. interactions between lipids/lipoproteins and endothelium, platelets and macrophages, have also been incriminated in the development of human atherosclerosis and of its complications. Regardless of the intervention used (low- fat/low-cholesterol diet, partial ileal bypass surgery or pharmacologic therapy), effective treatment of hypercholesterolemia/ dyslipidemia has consistently been shown to reduce the risk of CAD.
Atorvastatin calcium reduces LDL-C and the number of LDL particles, lowers Very Low Density Lipoprotein-Cholesterol (VLDL-C) and serum triglyceride, reduces the number of apo B containing particles, and also increases HDL-C. Atorvastatin calcium is effective in reducing LDL-C in patients with homozygous familial hypercholesterolemia, a condition that rarely responds to any other lipid-lowering medication. In addition to the above effects, atorvastatin calcium reduces IDL-C and apolipoprotein E (apo E) in patients with dysbetalipoproteinemia (Type III).
In patients with type II hyperlipidemia, atorvastatin improved endothelial dysfunction. Atorvastatin significantly improved flow-mediated endothelium-dependent dilatation induced by reactive hyperemia, as assessed by brachial ultrasound (p<0.01).
10.3 Pharmacokinetics
Absorption
Atorvastatin is rapidly absorbed after oral administration; maximal plasma concentrations occur within 1 to 2 hours. Extent of absorption and plasma atorvastatin concentrations increases in proportion to atorvastatin dose. Atorvastatin tablets are 95 to 99% bioavailable compared to solutions. The absolute bioavailability (parent drug) of atorvastatin is approximately 12% and the systemic availability of HMG-CoA reductase inhibitory activity is approximately 30%. The low systemic availability is attributed to presystemic clearance in gastrointestinal mucosa and/or first-pass metabolism in the liver. Although food decreases the rate and extent of drug absorption by approximately 25% and 9%, as assessed by Cmax and AUC respectively, LDL-C reduction and HDL-C elevation are similar when atorvastatin is given with and without food.
Plasma atorvastatin concentrations are lower (approximately 30% for Cmax and AUC) following drug administration in the evening compared with morning dosing. However, LDL-C reduction and HDL-C elevation are the same regardless of the time of drug administration.
Distribution
Mean volume of distribution of atorvastatin is approximately 381 liters. Atorvastatin is ≥98% bound to plasma proteins. A blood/plasma ratio of approximately 0.25 indicates poor drug penetration into red blood cells. Based on observations in rats, atorvastatin is likely to be secreted in human milk.
Metabolism
Atorvastatin is extensively metabolized to ortho- and para-hydroxylated derivatives by cytochrome P-450 3A4 (CYP 3A4) and to various beta-oxidation products. In vitro, inhibition of HMG-CoA reductase by ortho- and para-hydroxylated metabolites is equivalent to that of atorvastatin. Approximately 70% of circulating inhibitory activity for HMG-CoA reductase is attributed to active metabolites. In animals, the ortho-hydroxy metabolite undergoes further glucuronidation. Atorvastatin and its metabolites are eliminated by biliary excretion.
Atorvastatin is a substrate of the hepatic transporters, organic anion-transporting polypeptide 1B1 (OATP1B1) and 1B3 (OATP1B3) transporter. Metabolites of atorvastatin are substrates of OATP1B1. Atorvastatin is also identified as a substrate of the efflux transporters MDR1 and BCRP, which may limit the intestinal absorption and biliary clearance of atorvastatin.
Elimination
Atorvastatin is eliminated primarily in bile following hepatic and/or extrahepatic metabolism; however, the drug does not appear to undergo significant enterohepatic recirculation. Mean plasma elimination half-life of atorvastatin in humans is approximately 14 hours, but the half-life for inhibitory activity for HMG-CoA reductase is 20 to 30 hours due to the contribution of longer- lived active metabolites. Less than 2% of a dose of atorvastatin is recovered in urine following oral administration.
Special Populations and Conditions
Pediatrics: Assessment of pharmacokinetic parameters such as Cmax, AUC and bioavailability of atorvastatin calcium in pediatric patients (>10 to <17 years old, postmenarche) was not performed during the 6-month, placebo-controlled trial referred to earlier (see 14 CLINICAL TRIALS - Heterozygous Familial Hypercholesterolemia in Pediatric Patients and 7.1.3 Pediatrics).
In an open-label, 8-week study, Tanner Stage 1 (N=15) and Tanner Stage ≥2 (N=24) pediatric patients (ages 6 to 17 years) with heterozygous familial hypercholesterolemia and baseline LDL-C ≥4 mmol/L were treated with 5 or 10 mg of chewable or 10 or 20 mg of film-coated atorvastatin tablets once daily, respectively. Population PK analyses indicated that variability in atorvastatin PK was primarily affected by body weight. Allometric scaling by body weight was used to describe the changes in the apparent oral clearance of atorvastatin in the pediatric subjects. Apparent oral clearance (CL/F) of atorvastatin in pediatric subjects with the reference covariates Tanner Stage ≥ 2 and body weight of 70 Kg appeared similar to adults however the value of CL/F is expected to be relatively lower for a lower weight individual. Consistent decreases in LDL-C and TC (at week 8, 40% and 30% from baseline, respectively) were observed over the range of atorvastatin and o-hydroxyatorvastatin simulated exposures.
Geriatrics: Plasma concentrations of atorvastatin are higher (approximately 40% for Cmax and 30% for AUC) in healthy elderly subjects (age 65 years or older) compared with younger individuals. LDL-C reduction, however, is comparable to that seen in younger patient populations.
Sex: Plasma concentrations of atorvastatin in women differ (approximately 20% higher for Cmax and 10% lower for AUC) from those in men; however, there is no clinically significant difference in LDL-C reduction between men and women.
Ethnic Origin: Plasma concentrations of atorvastatin are similar in black and white subjects.
Hepatic Insufficiency: Plasma concentrations of atorvastatin are markedly increased (approximately 16-fold in Cmax and 11-fold in AUC) in patients with chronic alcoholic liver disease (Childs-Pugh B).
Renal Insufficiency: Plasma concentrations and LDL-C lowering efficacy of atorvastatin calcium are similar in patients with moderate renal insufficiency compared with patients with normal renal function. However, since several cases of rhabdomyolysis have been reported in patients with a history of renal insufficiency of unknown severity, as a precautionary measure and pending further experience in renal disease, the lowest dose (10 mg/day) of atorvastatin calcium should be used in these patients. Similar precautions apply in patients with severe renal insufficiency [creatinine clearance <30 mL/min (<0.5 mL/sec)]; the lowest dosage should be used and implemented cautiously (see 7 WARNINGS AND PRECAUTIONS, Muscle Effects; 9 DRUG INTERACTIONS; 4.2 Recommended Dose and Dosage Adjustment).
11 STORAGE, STABILITY AND DISPOSAL
Store at controlled room temperature 15°C to 30°C. Dispense in a tight container. Protect from moisture. Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Atorvastatin Calcium Propylene Glycol Solvate
Chemical name: (3R,5R)-7-{2-(4-Flurophenyl)-5-(1-methylethyl)-3-phenyl-4-[(phenylamino)carbonyl]-1H-pyrrole-1-yl}-3,5-dihydroxy-1-heptanoic acid, calcium salt (2:1), propylene glycol solvate
Molecular formula and molecular weight: C69H76CaF2N4O12 and 1231.45 g/mol
Structural Formula:
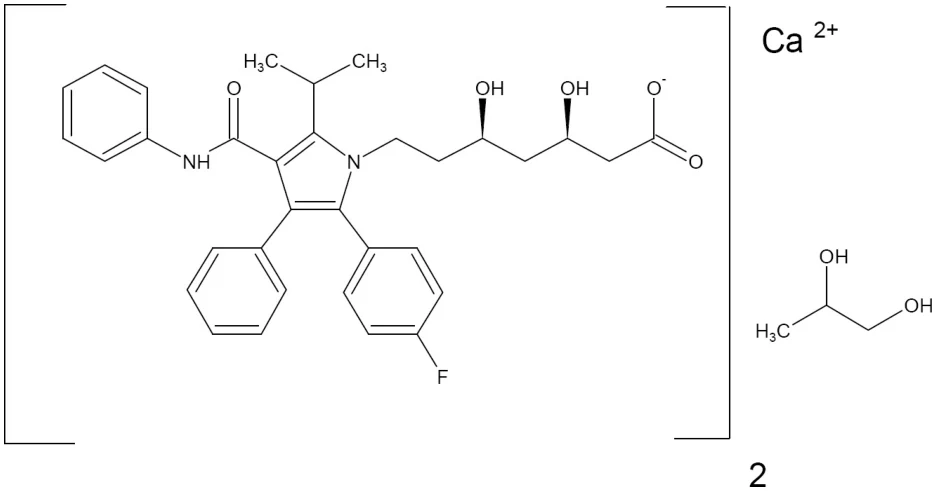
Physicochemical properties: Atorvastatin calcium propylene glycol solvate is a white to off-white crystalline powder that is practically insoluble in aqueous solutions of pH 4 and below. Atorvastatin calcium propylene glycol solvate is very slightly soluble in distilled water, pH 7.4 phosphate buffer and acetonitrile, slightly soluble in ethanol, and freely soluble in methanol.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Primary Hypercholesterolemia
Atorvastatin calcium has been shown to significantly improve lipid profiles in a variety of dyslipidemic conditions. Atorvastatin calcium has been shown to be highly effective in reducing total and LDL-cholesterol, and triglycerides and apolipoprotein B in patients with primary hypercholesterolemia.
Combined Hyperlipidemia
Atorvastatin calcium has been shown to significantly improve lipid profiles in a variety of dyslipidemic conditions. Atorvastatin calcium has been shown to be highly effective in reducing total and LDL-cholesterol, and triglycerides and apolipoprotein B in patients with mixed hyperlipidemia.
Dysbetalipoproteinemia
Atorvastatin calcium has been shown to significantly improve lipid profiles in a variety of dyslipidemic conditions. Atorvastatin calcium has been shown to be highly effective in reducing total and LDL-cholesterol, and triglycerides and apolipoprotein B in patients with familial combined hyperlipidemia.
Hypertriglyceridemia
Atorvastatin calcium has been shown to significantly improve lipid profiles in a variety of dyslipidemic conditions. Atorvastatin calcium has been shown to be highly effective in reducing total and LDL-cholesterol, and triglycerides and apolipoprotein B in patients with hypertriglyceridemia (Type IV). Atorvastatin calcium (10 to 80 mg daily) reduced TG (25 to 56%) and LDL-C levels (23 to 40%). Atorvastatin calcium has not been studied in conditions where the major abnormality is elevation of chylomicrons (TG levels > 11 mmol/L), i.e. types I and V.
Familial Hypercholesterolemia
Atorvastatin calcium has been shown to significantly improve lipid profiles in a variety of dyslipidemic conditions. Atorvastatin calcium has been shown to be highly effective in reducing total and LDL-cholesterol, and triglycerides and apolipoprotein B in patients with familial hypercholesterolemia.
Prevention of Cardiovascular Disease
Atorvastain calcium significantly reduced the rate of coronary events [either fatal coronary heart disease or nonfatal MI. The risk reduction was consistent regardless of age, smoking status, obesity or presence of diabetes or renal dysfunction. The effect of atorvastatin calcium was seen regardless of baseline LDL levels. Due to the small number of events, results for women were inconclusive.
In 2 multicenter, placebo-controlled, double-blind dose-response studies in patients with mild to moderate hypercholesterolemia (Fredrickson types IIa and IIb), atorvastatin calcium given as a single daily dose over 6 weeks reduced total-C, LDL-C, apo B, and TG; HDL-C was increased (Table 3). A therapeutic response was evident within 2 weeks, and the maximum response was usually achieved within 2 to 4 weeks.
Table 3. Dose-Response in Patients with Mild to Moderate Hypercholesterolemia (Fredrickson Types IIa and IIb)
(Mean Percent Change from Baseline)a
| Atorvastatin calcium Dose (mg/day) | N | Total-C | LDL-C | Apo B | TG | HDL-C |
|---|---|---|---|---|---|---|
| Placebo | 21 | +4 | +4 | +3 | +10 | -3 |
| 10 | 22 | -29 | -39 | -32 | -19 | +6 |
| 20 | 20 | -33 | -43 | -35 | -26 | +9 |
| 40 | 21 | -37 | -50 | -42 | -29 | +6 |
| 80 | 23 | -45 | -60 | -50 | -37 | +5 |
a Results are pooled from 2 dose-response studies
In a pooled data set from 24 controlled clinical trials in patients with primary hypercholesterolemia (type IIa) and mixed (combined) dyslipidemia (type IIb), atorvastatin calcium increased HDL C by 5% to 8% from baseline at each dose tested (10, 20, 40, and 80 mg QD) (Table 4). In patients with HDL C < 0.9 mmol/L (a condition often observed in persons with the metabolic syndrome) [see 1 INDICATIONS], atorvastatin calcium raised HDL- C 7% to 14%. These changes were independent of the dose administered. Atorvastatin calcium also decreased total-C/HDL-C, LDL-C/HDL-C, and non-HDL-C/HDL-C ratios from baseline in a dose dependent manner (Table 4). Atorvastatin calcium (10, 20, 40 and 80 mg QD) increased HDL-C levels from baseline for both men and women.
Table 4. Adjusteda Mean Percent Changes from Baseline in HDL-C, Total-C/HDL-C, LDL-C/HDL-C, Non-HDL-C/HDL-C, and HDL-C ≤ 0.9 mmol/L for Patientsb With Mild to Moderate Hypercholesterolemia (Fredrickson Types IIa and IIb)
| Atorvastatin calcium Dose (mg/day) | N (all patients) | HDL-C | Total-C/ HDL-C | LDL-C/ HDL-C | Non-HDL-C/ HDL-C | HDL-C (baseline ≤ 0.9 mmol/L) (N) |
|---|---|---|---|---|---|---|
| Placebo | 250 | +0.2** | +2.8** | +3.8** | +3.5** | +6.2* (17) |
| 10 | 1871 | +6.4 | -29.3† | -37.0† | -35.5† | +13.8 (248) |
| 20 | 147 | +7.8 | -36.0† | -44.1† | -43.0† | +8.3 (20) |
| 40 | 115 | +7.1 | -38.9† | -49.6† | -47.1† | +8.6 (8) |
| Atorvastatin calcium Dose (mg/day) | N (all patients) | HDL-C | Total-C/ HDL-C | LDL-C/ HDL-C | Non-HDL-C/ HDL-C | HDL-C (baseline ≤ 0.9 mmol/L) (N) |
| 80 | 318 | +5.0 | -43.5† | -55.3† | -52.4† | +7.1 (58) |
a Least squares means from ANCOVA model with study, treatment and baseline
b Data pooled from 24 controlled studies
† significant linear dose trend
** significantly different from atorvastatin calcium 10 mg (p<0.01)
* significantly different from atorvastatin calcium 10 mg (p<0.05)
In another multicenter, placebo controlled, double blind trial in patients with hypertriglyceridemia, atorvastatin lowered triglycerides in a dose related manner, without causing a redistribution of triglycerides into various lipoprotein fractions (Table 5).
Table 5. Efficacy in Patients with Hypertriglyceridemia (Mean Percent Change from Baseline)
| Atorvastatin calcium Dose (mg/day) | N | VLDL-C | Total-C | VLDL-TG | LDL-C | TG | HDL-C | Apo B |
|---|---|---|---|---|---|---|---|---|
| Placebo | 12 | -2.0 | +0.3 | -6.6 | +1.4 | -5.3 | +2.4 | +2.7 |
| 5 | 11 | -34.0* | -19.9* | -28.7 | -12.7* | -27.3 | +7.1 | -15.4* |
| 20 | 12 | -46.0* | -33.1* | -35.7* | -31.1* | -33.7* | +10.6 | -32.7* |
| 80 | 11 | -54.2* | -41.3* | -43.6* | -36.1* | -42.4* | +11.8* | -38.7* |
* Significantly different from placebo, p<0.05
Comparison of pooled data by Fredrickson types shows similar reductions for Type IIa and IIb patients in total-C, LDL-C and apo B; however, Type IIb patients, and Types IV patients experience a greater percent decrease in VLDL-C and TG levels (Table 6).
Table 6. Efficacy in Patients by Fredrickson Typea (Mean Percent Change from Baseline)
| Lipid Parameter | Atorvastatin calcium 10 mg/day | ||
|---|---|---|---|
Type IIa (N=935) | Type IIb (N=550) | Type IV (N=29) | |
| HDL-C | +6 | +10 | +13 |
| Apo B/HDL-C | -31 | -34 | -33 |
| Non-HDL-C/HDL-C | -37 | -38 | -38 |
| Lipid Parameter | Atorvastatin calcium 10 mg/day | ||
Type IIa (N=935) | Type IIb (N=550) | Type IV (N=29) | |
| LDL-C | -36 | -35 | -26 |
| Apo B | -28 | -28 | -25 |
| Total-Cl | -27 | -27 | -25 |
| TG | -14 | -24 | -29 |
| VLDL-C | -15 | -28 | -41 |
a Pooled dataset
In a pilot study of 8 patients with homozygous familial hypercholesterolemia, the mean decrease in LDL-C with 80 mg/day atorvastatin calcium was 30% for patients not on plasmapheresis, and 31% for patients who continued plasmapheresis. A LDL-C lowering of 35% was observed in receptor defective patients (n=6) and of 19% in receptor negative patients (n=2). All patients also experienced decreases in total-C, apo B, LDL-C/HDL-C and non-HDL-C/HDL-C ratios (Table 7).
Table 7. Patients with Homozygous FH (Mean Percent Change from Baseline After 8 Weeks)
| Lipid Parameter | Atorvastatin calcium 80 mg/day | ||
|---|---|---|---|
All Patients (N=8) | Patients Not on Plasmapheresis (N=3) | Patients on Plasmapheresis (N=5) | |
| Total-C | -29 | -29 | -29 |
| LDL-C | -31 | -30 | -31 |
| Apo B | -28 | -17 | -34 |
| TG | -20 | -41 | -8 |
| LDL-C/HDL-C Ratio | -23 | -19 | -25 |
Non-HDL-C/HDL-C Ratio | -22 | -19 | -24 |
In an open label study, 69 patients (2 to 61 years of age) with homozygous familial hypercholesterolemia, and 92 patients with severe hypercholesterolemia who had ≤15% response to maximum combination therapy, received atorvastatin calcium 10 to 80 mg/day. Most patients began atorvastatin calcium treatment with 40 mg/day, but severely debilitated and very young patients began treatment with 10 mg/day. Atorvastatin calcium was titrated at 4- week intervals to ≤80 mg/day. The mean reduction in LDL-C for 69 patients diagnosed with homozygous familial hypercholesterolemia was 22%. Table 8 shows the mean percent change in lipid parameters. In 2 receptor-negative patients mean LDL-C reduction was 19%. Six patients had less than a 10% response to treatment.
Table 8. Patients with Homozygous FH or Severe Nonresponsive Hypercholesterolemia (Mean Percent Change from Baseline after 8 Weeks)
| Lipid Parameter | Atorvastatin calcium 80 mg/day | |
|---|---|---|
| Homozygous FH (N=69a) | Severe Unresponsive Hypercholesterolemia (N=92) | |
| Total-C | -21% | -34% |
| LDL-C | -22% | -39% |
| TG | -9% | -29% |
| HDL-C | +3% | +6% |
a Data available from 68 patients
In a 1-year study in patients with heterozygous familial hypercholesterolemia , atorvastatin calcium monotherapy (80 mg/day) was compared with combination therapy of colestipol (10 g BID) plus atorvastatin calcium (40 mg/day). The 2 treatments produced similar effects on total- C, LDL-C, TG, VLDL-C, apo B and HDL-C; however, atorvastatin calcium monotherapy was more effective than atorvastatin calcium plus colestipol in decreasing TG levels (Table 9).
Table 9. Efficacy in Patients with Heterozygous Familial Hypercholesterolemia (Mean Percent Change from Baseline after 52 Weeks)
| Lipid Parameter | Atorvastatin calcium 80 mg/day (N=189) | Atorvastatin calcium 40 mg/day Plus Colestipol 10 g BID (N=124) |
|---|---|---|
| Total-C | -44 | -42 |
| LDL-C | -53 | -53 |
| VLDL-C | -33 | -17 |
| HDL-C | +7 | +9 |
| TG | -33a | -17 |
| non-HDL/HDL-C Ratio | -53 | -52 |
| Apo B | -46 | -45 |
a Significantly different from atorvastatin calcium plus colestipol (p<0.05), ANCOVA.
A comparison of results in patients with heterozygous familial and non-familial hypercholesterolemia shows similar magnitudes of reductions in LDL-C, apo B and non-HDL- C/HDL-C ratio, in both patient populations (Table 10).
Table 10. Efficacy in Heterozygous FH and Non FH Patients† (Mean Percent Change from baseline)
| Lipid Parameter | Phenotype | Atorvastatin calcium | |
|---|---|---|---|
| 10 mg/day | 80 mg/day | ||
| LDL-C | Heterozygous FH | -36 (N=140) | -53 (N=154) |
| Non FH | -36 (N=1215) | -52 (N=166) | |
| Apo B | Heterozygous FH | -27 (N=134) | -46 (N=153) |
| Non FH | -28 (N=1149) | -46 (N=144) | |
| Non-HDL-C/HDL-C Ratio | Heterozygous FH | -37 (N=140) | -53 (N=132) |
| Non FH | -37 (N=1215) | -54 (N=166) | |
† Data from several studies
Comparison of results in patients with and without familial combined hyperlipidemia (FCH) demonstrated that atorvastatin calcium lowered LDL-C, apo B, total-C, VLDL-C, TG, and the non-HDL-C/HDL-C ratio to a similar extent in both patient populations (Table 11).
Table 11. Efficacy in Patients With and Without FCH†,a (Mean Percent Change from Baseline)
| Lipid Parameter | Atorvastatin calcium 10 mg/day | |
|---|---|---|
FCH (N=78-84) | Non-FCH (N=1084-1224) | |
| Total-C | -26% | -27% |
| LDL-C | -34% | -36% |
| TG | -21% | -17% |
| HDL-C | +8% | +7% |
| Apo B | -26% | -28% |
| VLDL-C | -25% | -18% |
| Non-HDL-C/HDL-C Ratio | -36% | -37% |
| LDL-C/Apo B Ratio | -9% | -11% |
† Data from several studies
a The following criteria were used to define patients with FCH: first degree relative with lipid disorder, TG >250 mg/dL (>2.8 mmol/L), VLDL >45 mg/dL (>1.16 mmol/L), HDL <35 mg/dL
(<0.9 mmol/L) (men) or <45 mg/dL (<1.16 mmol/L) (women).
In an open-label, randomised, cross-over study in patients with dysbetalipoproteinemia (Type III), atorvastatin calcium 80 mg/day resulted in a significantly greater reduction in serum lipids than either atorvastatin calcium 10 mg/day or gemfibrozil 1200 mg/day (Table 12).
Table 12. Efficacy in Patients with Type III Hyperlipoproteinemia (Familial Dysbetalipoproteinemia) Mean Percent Change from Baseline
| Lipid parameter | Atorvastatin calcium 10 mg/day (N=15) | Atorvastatin calcium 80 mg/day (N=16) | Gemfibrozil 1200 mg/day (N=16) |
|---|---|---|---|
| Total-C | -40 | -57a | -34 |
| LDL-C | +20a | -6a | +86 |
| TG | -40a | -56 | -52 |
| VLDL-C | -32 | -59a | -35 |
| IDL-C | -28a | -50a | -13 |
| IDL-C + VLDL-C | -34 | -58a | -33 |
| HDL-C | +3 | +13 | +11 |
| Apo B (total) | -47 | -66a | -53 |
| Apo-C III | -16 | -31 | -12 |
| Apo-E | -27 | -41a | -24 |
asignificantly different from gemfibrozil, p<0.05 (ANOVA)
In a 6-month, double-blind, study in patients with hyperlipidemia and non-insulin dependent diabetes mellitus (NIDDM), atorvastatin calcium (10 or 20 mg/day) lowered total cholesterol by 27%, LDL-C by 34%, apo B by 30%, TG by 24%, and increased HDL-C by 12% (Table 13)
Table 13. Efficacy in Patients with NIDDM (Mean Percent Change From Baseline)
| Lipid Parameter | Atorvastatin calcium 10 or 20 mg/day (N=84) |
|---|---|
| Total-C | -27 |
| LDL-C | -34 |
| VLDL-C | -35 |
| TG | -24 |
| VLDL-TG | -26 |
| HDL-C | +12 |
| Apo B | -30 |
In three, double-blind, multicenter studies in patients with mild to moderate hypercholesterolemia, the number of patients meeting NCEP target LDL-C levels on atorvastatin calcium was assessed over a 1-year period. After 16 weeks, between 46 to 74% of patients receiving 10 mg/day atorvastatin calcium reached target LDL-C levels. The efficacy of atorvastatin calcium (10 or 20 mg/day) was maintained over 52 weeks, with between 50 to 78% of patients achieving their LDL-C target levels.
The effect of atorvastatin calcium was evaluated in comparative clinical trials with lovastatin, simvastatin and pravastatin.
In a 1-year study in postmenopausal women with primary hyperlipidemia, atorvastatin calcium monotherapy (10 mg/day) was compared with estradiol monotherapy (1 mg/day) and with combination therapy of atorvastatin calcium 10 mg/day plus estradiol 1 mg/day (Table 14).
Atorvastatin calcium monotherapy (10 mg/day) was significantly more effective in lowering total-C, LDL-C, VLDL-C, TG, apo B and non-HDL-C/HDL-C ratio than estradiol monotherapy (1 mg/day). For combination therapy (atorvastatin calcium plus estradiol), reductions in total-C, LDL-C, VLDL-C, Lp(a), apo B and non-HDL-C/HDL-C ratio were similar compared with atorvastatin calcium monotherapy. However, HDL-C levels were significantly higher for combination therapy compared with atorvastatin calcium monotherapy. TG levels were lower with atorvastatin calcium monotherapy compared with combination therapy. Adverse reactions were similar in type and incidence following combination therapy (atorvastatin calcium plus estradiol) compared with estradiol monotherapy.
Table 14. Efficacy in Post-menopausal Women (Mean Percent Change from Baseline After 52 Weeks)
| Lipid Parameter | Atorvastatin calcium 10 mg/day (N=38) | Estradiol 1 mg/day (N=16) | Atorvastatin calcium 10 mg/day Plus Estradiol (1 mg/day) (N=21) |
|---|---|---|---|
| TOTAL-C | -29 | -1 a | -27 |
| LDL-C | -40 | -5 a | -42 |
| VLDL-C | -32 | +13 a | -20 |
| HDL-C | +8 | +11 | +20 a |
| TG | -27 | +5 a | -13 a |
| non-HDL/HDL-C Ratio | -43 | -12 a | -48 |
| Apo B | -34 | -3 a | -34 |
aSignificantly different from atorvastatin monotherapy (p<0.05), ANCOVA.
In a comparative study with niacin in patients with hypercholesterolemia and mixed hyperlipidemia (Fredrickson types IIa and IIb) and hypertriglyceridemia (Frederickson Type IV), atorvastatin calcium (10 mg/day) had greater cholesterol-lowering efficacy (greater decreases in LDL-C, apo B, LDL-apo B), while niacin (3 g/day) had greater triglyceride-lowering efficacy (greater decreases in TG, VLDL-TG, HDL-TG, VLDL-apo B). Atorvastatin calcium was better tolerated by patients compared with niacin (Table 15).
Table 15. Atorvastatin calcium versus Niacin (Mean Percent Change from Baseline)
| Parameter | Fredrickson Types IIa and IIb | Fredrickson Type IV | ||
|---|---|---|---|---|
Atorvastatin 10 mg (N=43) | Niacin 3 g/day (N=39) | Atorvastatin 10 mg (N=11) | Niacin 3 g/day (N=12) | |
| LDL-C | -33* | -8 | -15* | +14 |
| Apo B | -30* | -16 | -23* | -3 |
| Total-C | -28* | -11 | -26* | 0 |
| TG | -16 | -29* | -36 | -29 |
| HDL-C | +4 | +27* | +4 | +25 |
| VLDL-C | -28 | -39 | -43 | -36 |
| Non-HDL-C/HDL-C | -34 | -32 | -34 | -19 |
| Apo B/HDL | -32 | -31 | -28 | -18 |
* Significant difference between treatments, ANCOVA p<0.05.
In a comparative study with fenofibrate in patients with combined hyperlipidemia or hypertriglyceridemia, atorvastatin calcium (20 mg/day) was more effective in lowering LDL-C, apo B and total cholesterol levels compared to fenofibrate (100 mg TID). Treatment with atorvastatin calcium also resulted in clinically significant reductions in TG and VLDL-C, and increases in HDL-C levels, although not to the same extent as was seen with fenofibrate. Atorvastatin calcium therapy resulted in a better reduction of the non-HDL-C/HDL-C ratio, which may be a good indicator of overall lipid-regulating benefit. Atorvastatin calcium was also better tolerated compared with fenofibrate (Table 16).
Table 16. Atorvastatin calcium versus Fenofibrate Mean Percent Change From Baseline After 24 Weeks
| Parameter | Fredrickson Types IIa and IIb | Fredrickson Type IV | ||
|---|---|---|---|---|
Atorvastatin 20 mg (N=36) | Fenofibrate 300 mg (N=33) | Atorvastatin 20 mg (N=9) | Fenofibrate 300 mg (N=8) | |
| LDL-C | -39* | -7 | -28* | +27 |
| Apo B | -36* | -17 | -27 | -9 |
| Total-C | -34* | -14 | -26 | -13 |
| TG | -27 | -39 | -34 | -57* |
| HDL-C | +9 | +22* | +8 | +30* |
| VLDL-C | -39 | -50 | -36 | -73* |
| Parameter | Fredrickson Types IIa and IIb | Fredrickson Type IV | ||
Atorvastatin 20 mg (N=36) | Fenofibrate 300 mg (N=33) | Atorvastatin 20 mg (N=9) | Fenofibrate 300 mg (N=8) | |
| Non-HDL-C/HDL-C | -44* | -32 | -36 | -35 |
* Significant difference between treatments, ANCOVA p<0.05.
Heterozygous Familial Hypercholesterolemia in Pediatric Patients:
In a double-blind, placebo-controlled study followed by an open-label phase, 187 boys and postmenarchal girls 10 to 17 years of age (mean 14.1 years) with heterozygous familial hypercholesterolemia (FH) or severe hypercholesterolemia were randomized to atorvastatin calcium (n=140) or placebo (n=47) for 26 weeks after that, all received atorvastatin calcium for 26 weeks. Inclusion in the study required 1) a baseline LDL-C level ≥ 4.9 mmol/L (190 mg/dL) or 2) a baseline ≥ 4.1 mmol/L (160 mg/dL) and positive family history of FH or documented premature cardiovascular disease in a first- or second-degree relative.
Table 17. Effect of atorvastatin calcium on LDL-C, TC and TG in a controlled trial of 6 months duration in adolescent boys and postmenarchal girls 10 to 17 years of age (N=187) with heterozygous familial hypercholesterolemia at a dose of 10 and 20 mg.
| N | Age | Dose | % Change | |||||
|---|---|---|---|---|---|---|---|---|
| LDL-C | TC | TG | ||||||
| 22 | 10-13 | 10 mg | -37.85 | -29.3 | -9.2 | |||
| 40 | 14-17 | 10 mg | -38.2 | -29.4 | -6.9 | |||
| 33 | 10-13 | 20 mg | -42.1 | -34.0 | -13.3 | |||
| 43 | 14-17 | 20 mg | -40.3 | -33.0 | -18.3 | |||
The mean baseline LDL-C value was 5.7 mmol/L (218.6 mg/dL) (range: 3.6 to 10.0 mmol/L [138.5 to 385.0 mg/dL]) in the atorvastatin calcium group compared to 5.9 mmol/L
(230.0 mg/dL) (range: 4.1 to 8.4 mmol/L [160.0 to 324.5 mg/dL]) in placebo group. The dosage of atorvastatin calcium (once daily) was 10 mg for the first 4 weeks and up-titrated to 20 mg if the LDL-C level was >3.4 mmol/L (130 mg/dL). The number of atorvastatin calcium-treated patients who required up-titration to 20 mg after Week 4 during the double-blind phase was
78 (55.7%).
Atorvastatin calcium significantly decreased plasma levels of total-C, LDL-C, triglycerides, and apolipoprotein B during the 26 week double-blind phase (see Table 17, and Table 18).
Table 18. Lipid-lowering Effects of Atorvastatin in Adolescent Boys and Girls with Heterozygous Familial Hypercholesterolemia or Severe Hypercholesterolemia (Mean Percent Change from Baseline at Endpoint in Intention-to-Treat Population)
| Dosage | N | Total-C | LDL-C | HDL-C | TG | Apolipoprotein B |
|---|---|---|---|---|---|---|
| Placebo | 47 | -1.5 | -0.4 | -1.9 | 1 | 0.7 |
| Atorvastatin | 140 | -31.4 | -39.6 | 2.8 | -12 | -34 |
The mean achieved LDL-C value was 3.8 mmol/L (130.7 mg/dL) (range: 1.8 to 6.3 mmol/L [70.0 to 242.0 mg/dL]) in the atorvastatin calcium group compared to 5.9 mmol/L (228.5 mg/dL) (range: 3.9 to 10.0 mmol/L [152.0 to 385.0 mg/dL]) in the placebo group during the 26 week double-blind phase. The safety and tolerability profile of atorvastatin calcium 10 to 20 mg daily was similar to that of placebo.
In this controlled study, there was no effect on growth or sexual maturation in boys and in girls, as measured by Tanner staging during 26 weeks. The proportion of subjects who had an increase in Tanner stage between baseline and week 26 of the double-blind phase was similar for the atorvastatin and placebo groups (28% and 31%, respectively; P = 0.7). No specific documentation of menstrual cycle was recorded. Atorvastatin calcium had no effect on plasma levels of LH, FSH, cortisol, testosterone and dehydroepiandrosterone. Effect of treatment on cognitive function was not captured during the course of this study.
Atorvastatin calcium has not been studied in controlled clinical trials involving pre pubertal patients or patients younger than 10 years of age. The safety and efficacy of doses above 20 mg have not been studied in controlled trials in children.
Prevention of Cardiovascular Disease
In the Anglo-Scandinavian Cardiac Outcomes Trial (ASCOT), the effect of atorvastatin calcium on fatal and non-fatal coronary heart disease was assessed in 10,305 hypertensive patients 40 to 80 years of age (mean of 63 years), without a previous myocardial infarction and with TC levels ≤6.5 mmol/L. Additionally all patients had at least 3 of the following cardiovascular risk factors: male gender (81.1%), age ≥55 years (84.5%), smoking (33.2%), diabetes (24.3%), history of CHD in a first-degree relative (26%), TC:HDL ≥ 6 (14.3%), peripheral vascular disease (5.1%), left ventricular hypertrophy (14.4%), prior cerebrovascular event (9.8%), specific ECG abnormality (14.3%), proteinuria/albuminuria (62.4%). In this double-blind, placebo-controlled study, patients were treated with anti-hypertensive therapy (Goal BP <140/90 mm Hg for non- diabetic patients, <130/80 mm Hg for diabetic patients) and allocated to either atorvastatin calcium 10 mg daily (n=5168) or placebo (n=5137), using a covariate adaptive method which took into account the distribution of nine baseline characteristics of patients already enrolled and minimized the imbalance of those characteristics across the groups. Patients were followed for a median duration of 3.3 years.
The effect of 10 mg/day of atorvastatin calcium on lipid levels was similar to that seen in previous clinical trials.
Atorvastatin calcium significantly reduced the rate of coronary events [either fatal coronary heart disease (46 events in the placebo group vs 40 events in the atorvastatin calcium group) or nonfatal MI (108 events in the placebo group vs 60 events in the atorvastatin calcium group)] with an absolute risk reduction of 1.1% and a relative risk reduction of 36% (based on incidences of 1.9% for atorvastatin calcium vs 3.0% for placebo), p=0.0005 (see Figure 1)]. This risk reduction yields a Number Needed to Treat of 311 patients per year. The risk reduction was consistent regardless of age, smoking status, obesity or presence of renal dysfunction. The effect of atorvastatin calcium was seen regardless of baseline LDL levels. Due to the small number of events, results for women were inconclusive.
Figure 1. Effect of atorvastatin calcium 10 mg/day on Cumulative Incidence of Nonfatal Myocardial Infarction or Coronary Heart Disease Death (in ASCOT-LLA)
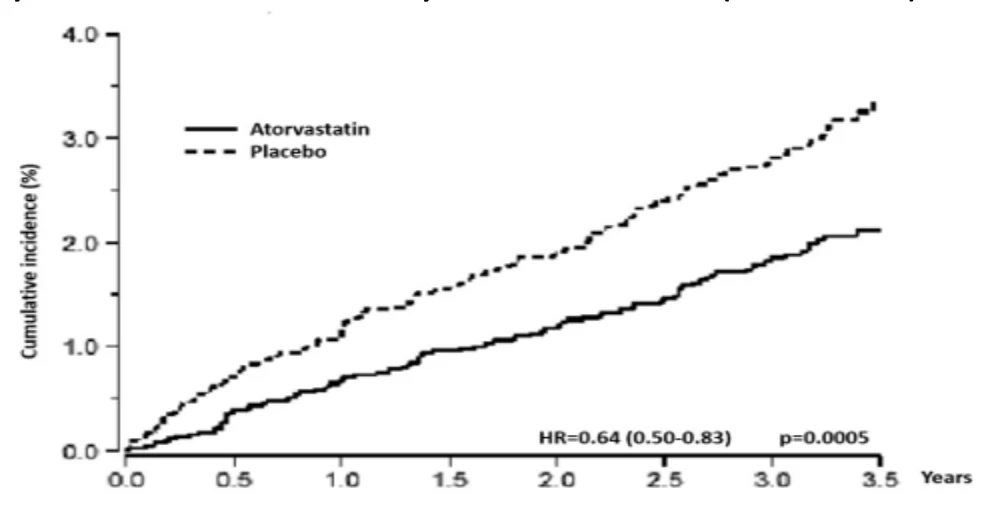
In the Collaborative AtoRvastatin Diabetes Study (CARDS), the effect of atorvastatin calcium on coronary heart disease (CHD) and non-CHD endpoints was assessed in 2838 men (68%) and women (32%), ages 40 to 75 with type 2 diabetes based on WHO criteria, without prior history of cardiovascular disease and with LDL ≤ 4.14 mmol/L and TG ≤ 6.78 mmol/L. In addition to type 2 diabetes, subjects had one or more of the following CHD risk factors: current smoking (23%), hypertension (80%), retinopathy (30%), microalbuminuria (9%) or macroalbuminuria (3%). In this multicenter, placebo-controlled, double blind clinical trial of primary prevention of fatal and nonfatal cardiovascular and cerebrovascular disease in subjects with type 2 diabetes and 1 other CHD risk factor, patients were randomly allocated to either atorvastatin calcium
10 mg daily (1429) or placebo (1411) in a 1:1 ratio.
Patients were followed for a median duration of 3.9 years. Due to significant treatment benefits (p<0.0005, one-sided, in favor of atorvastatin calcium) seen early in the study, the study was stopped by the CARDS Steering Committee two years earlier than anticipated.
Baseline characteristics of subjects were: mean age of 62 years, mean HbA1c 7.7%; median LDL-C 3.10 mmol/L; median TC 5.35 mmol/L; median TG 1.70 mmol/L; median HDL-C 1.34 mmol/L.
The effect of atorvastatin calcium 10 mg/day on lipid levels was similar to that seen in previous clinical trials.
Treatment with atorvastatin calcium was associated with a statistically significant 37% relative risk reduction (RRR), or 3.2% absolute risk reduction (ARR) in the rate of major cardiovascular events. Efficacy analysis showed that 83 (5.8%) of atorvastatin calcium treated patients and 127 (9.0%) of placebo treated patients experienced their first primary clinical endpoint.
Comparison of the time to the first primary endpoint in the two groups yielded the hazard ratio (HR) of 0.63 with 95% CI 0.48, 0.83 and p=0.001 in favour of atorvastatin calcium. The number needed to treat (NNT) for one year to prevent one case experiencing the primary clinical endpoint, based on the ARR 3.2% yields 125 patients. The effect of atorvastatin calcium was seen regardless of age, sex, or baseline lipid levels.
Figure 2. Time to Occurrence of First Primary Endpoint
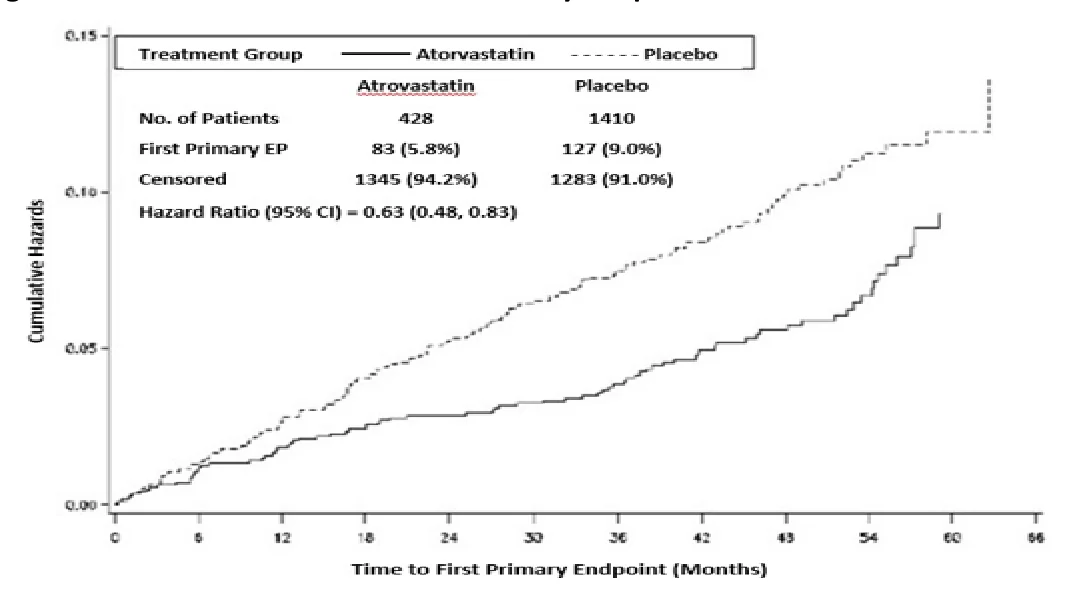
When cardiovascular events were evaluated separately, atorvastatin calcium significantly reduced the relative risk of stroke by 48% (ARR of 1.3%). There were 21 cases of stroke (1.5%) in the atorvastatin calcium group vs 39 cases (2.8%) in the placebo group, HR 0.52, 95% CI 0.31, 0.89, p=0.016. To prevent one case of stroke 307 patients are needed to be treated for one year.
Figure 3. Time to Occurrence of First Stroke
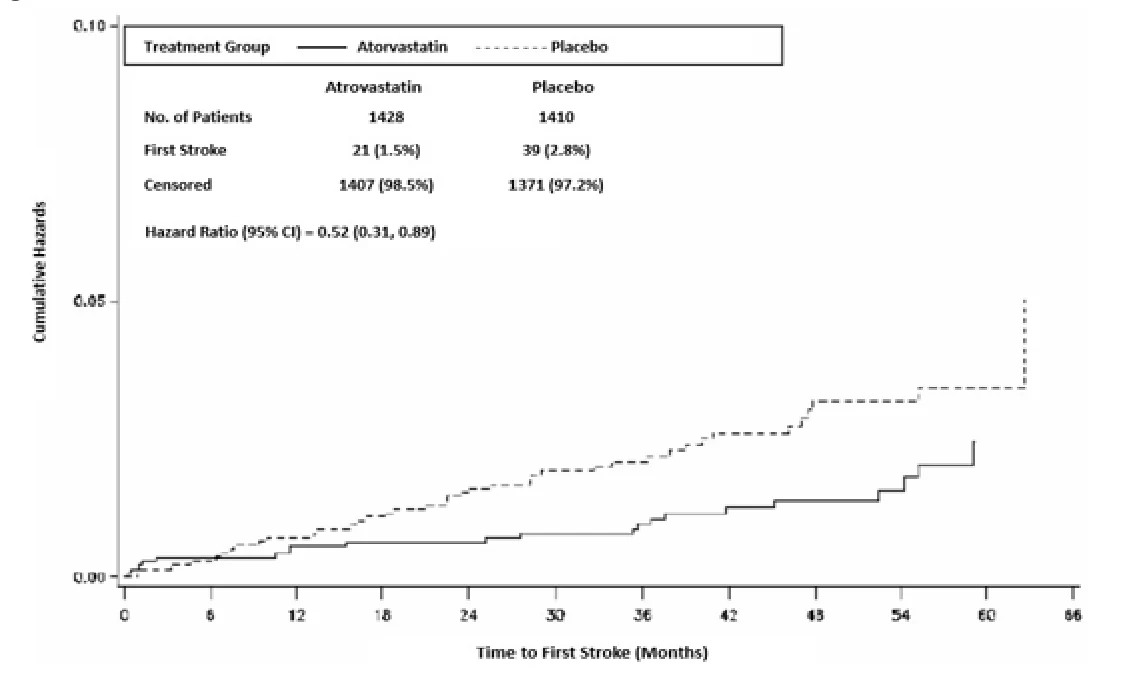
Relative risk of myocardial infarction was reduced by 42%, or ARR by 1.8%, with 38 cases (2.7%) in the atorvastatin calcium group vs 64 cases (4.5%) in the placebo group, HR 0.58, 95% CI 0.39, 0.86, p = 0.007. To prevent one case of myocardial infarction 222 patients have to be treated for one year.
No significant risk reduction was observed in the time to first CABG, PTCA or other coronary revascularization procedure, time to first unstable angina or time to acute CHD death. No significant reduction was observed in time to death due to all causes (61 deaths in the atorvastatin calcium group vs 82 deaths in the placebo group, HR 0.73, 95% CI 0.52, 1.01, p=0.059), cardiovascular causes, or non-cardiovascular causes.
14.3 Comparative Bioavailability Studies
A randomized, single-dose, two-way, crossover comparative bioavailability study of
PRO-ATORVASTATIN tablets, 80 mg (Pro Doc Ltée.) and LIPITOR® tablets, 80 mg (Pfizer Canada Inc.) was conducted in 17 healthy, adult, male subjects under fasting conditions. A summary of the comparative bioavailability data is presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Atorvastatin (1 x 80 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUC0-t | 156.68 | 142.53 | 109.9 | 99.7 – 121.2 |
| (ng·h/mL) | 164.03 (33.69) | 152.43 (40.01) | ||
| AUCI | 160.67 | 146.91 | 109.4 | 99.4 – 120.4 |
| (ng·h/mL) | 168.40 (34.59) | 157.05 (40.71) | ||
| Cmax | 38.40 | 34.43 | 111.5 | 94.9 – 131.0 |
| (ng/mL) | 41.00 (37.94) | 38.58 (51.36) | ||
| Tmax3 | 1.33 (0.75- | 0.75 (0.33- | Not applicable | Not applicable |
| (h) | 5.00) | 1.67) | ||
T½4 (h) | 9.66 (13.54) | 9.92 (14.69) | Not applicable | Not applicable |
1 PRO-ATORVASTATIN (atorvastatin calcium) tablets, 80 mg (Pro Doc Ltée.)
2 LIPITOR® (atorvastatin calcium) tablets, 80 mg (Pfizer Canada Inc.)
3 Expressed as median (range) only
4 Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
The acute toxicity of atorvastatin following single doses was evaluated in mice, rats and dogs by oral and intravenous routes, and the results are summarized below:
Table 19. Acute Oral and Intravenous Toxicity Studies with Atorvastatin
| Species | Sex | Route | Dose Range (mg/kg) | Results |
|---|---|---|---|---|
| Dog | Male/Female | Oral | 10 - 400 | No Deaths |
| Dog | Male/Female | IV | 0.4 - 4 | No Deaths |
| Species | Sex | Route | Dose Range (mg/kg) | Results |
| Mouse | Male/Female | Oral | 200 - 5000 | No Deaths |
| Mouse | Male/Female | IV | 0.4 - 4 | No Deaths |
| Rat | Male/Female | Oral | 200 - 5000 | No Deaths |
| Rat | Male/Female | IV | 0.4 - 4 | No Deaths |
The acute toxicity of atorvastatin in rodents and dogs is low. Oral median lethal doses in mice and rats are greater than 5000 mg/kg.
The target organs affected by atorvastatin in multiple dose toxicity studies in rats (2 weeks to 52 weeks), and dogs (2 weeks to 104 weeks) are summarized in the table below. The spectrum of effects observed is not unexpected in view of the magnitude of the dose levels used, potency of atorvastatin in inhibiting mevalonate synthesis and the essential role of HMG-CoA reductase in maintaining cellular homeostasis.
Table 20. Atorvastatin: Target Organs Affected in Animal Studies
| Rat | Dog |
|---|---|
Liver Stomach (non-glandular) Skeletal Muscle | Liver Gallbladder Skeletal Muscle Intestine Brain/Optic Nerve* |
* Occurred after administration of high, intolerable doses (280 mg/kg)
The following table summarizes the significant adverse changes observed during long-term toxicology studies in rats (52 weeks) and dogs (104 weeks):
Table 21. Atorvastatin: Significant Adverse Changes in Chronic Studies
| Species/Results | Minimal Toxic Dose (mg/kg/day) | No-Effect Dose (mg/kg/day) |
|---|---|---|
| RAT | ||
| Hepatocellular atypia | 70 | 5 |
| Bile Duct hyperplasia1 | 125 | 70 |
| Nonglandular stomach acanthosis | 125 | 70 |
| DOG | ||
| Death2 | 120 | 40 |
| Hepatocellular granulomata3 | 10 | ND |
| Hepatocellular necrosis3 | 120 | 40 |
| Gallbladder edema/hemorrhage3 | 120 | 40 |
| Bile duct hyperplasia3 | 120 | 10 |
| Intestinal ulcers and single cell | 120 | 40 |
| necrosis3 | ||
| Skeletal muscle (tongue) necrosis2 | 120 | 40 |
1 Present only at Week 26; not observed at Week 52.
2 Findings occurred in Week 7 or 9.
3 Findings occurred at Week 52 or in moribund dogs, were less pronounced after a 12-week withdrawal period (Week 64), and were not observed after 104 weeks of dosing.
ND = Not determined
The results of the long-term toxicology studies with atorvastatin indicated that similar to other HMG-CoA reductase inhibitors, the liver is the primary target organ. This is expected since the liver is the primary site of the pharmacologic action of atorvastatin and it is subject to the greatest drug exposure following oral administration. In both the rat and dog studies, the hepatic changes diminished with time (i.e. effects were less pronounced at the end of the 52-week and 104-week studies) suggesting an adaptive response.
Brain hemorrhage, optic nerve degeneration, lenticular opacities and testicular degeneration were not seen in dogs treated for 104-weeks with atorvastatin up to 120 mg/kg/day.
Carcinogenicity:
Atorvastatin was not carcinogenic in rats given 10, 30 or 100 mg/kg/day for 2 years. The 100 mg/kg dose is 63-fold higher than the maximum recommended human dose of 80 mg (1.6 mg/kg, based on a 50 kg human) and AUC (0 to 24 hr) values were 8 to 16-fold higher.
In a 2-year study in mice given 100, 200 or 400 mg/kg/day, incidences of hepatocellular adenoma in males and hepatocellular carcinoma in females were increased at 400 mg/kg. This dose is 250 times the maximum recommended human dose on a mg/kg basis and systemic exposure based on AUC (0 to 24 hr) was 6 to 11 times higher. There was no evidence of treatment-related increases in tumor incidences at the lower doses of 100 and 200 mg/kg/day (i.e. up to 125 times the maximum recommended human dose on a mg/kg basis and systemic exposures of 3 times higher based on AUC (0 to 24 hr).
Genotoxicity:
Atorvastatin did not demonstrate mutagenic or clastogenic potential in four in vitro tests with and without metabolic activation or in one in vivo assay. It was negative in the Ames test with Salmonella typhimurium and Escherichia coli, and in the in vitro HGPRT forward mutation assay in Chinese hamster lung cells. Atorvastatin did not produce significant increases in chromosomal aberrations in the in vitro Chinese hamster lung cell assay and was negative in the in vivo mouse micronucleus test.
Reproductive and Developmental Toxicology:
No adverse effects on fertility or reproduction were observed in male rats given doses of atorvastatin up to 175/mg/kg/day or in female rats given doses up to 225 mg/kg/day. These doses are 100 to 140 times the maximum recommended human dose on a mg/kg basis.
Atorvastatin did not cause any adverse effects on sperm or semen parameters, or in reproductive organ histopathology in dogs given doses of 10, 40 or 120 mg/kg for 2 years.
Atorvastatin was not teratogenic in either rats or rabbits.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. LIPITOR® (Atorvastatin Calcium Tablets USP, 10 mg, 20 mg, 40 mg, and 80 mg), submission control 294009, Product Monograph, BGP Pharma ULC. (JUL 22, 2025)