


Product Monograph - Q-Metformin
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Tablet / 500 & 850 mg | For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Q-METFORMIN (metformin HCl) is indicated to control hyperglycemia in responsive, stable, mild, non-ketosis prone, maturity onset type of diabetes (Type II) which cannot be controlled by proper dietary management, exercise and weight reduction or when insulin therapy is not appropriate.
Q-METFORMIN can be of value for the treatment of obese diabetic patients.
CONTRAINDICATIONS
- Unstable and/or insulin-dependent (Type I) diabetes mellitus.
- Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma, history of ketoacidosis with or without coma. Diabetic ketoacidosis should be treated with insulin.
- In patients with a history of lactic acidosis, irrespective of precipitating factors.
- In the presence of renal impairment or when renal function is not known, and also in patients with serum creatinine levels above the upper limit of normal range. Renal disease or renal dysfunction (e.g., as suggested by serum creatinine levels ≥ 136 μmol/L (males), ≥ 124 μmol/L (females) or abnormal creatinine clearance < 60 mL/min)) which may result from conditions such as cardiovascular collapse (shock), acute myocardial infarction, and septicemia (see also WARNINGS and PRECAUTIONS).
- In excessive alcohol intake, acute or chronic.
In patients suffering from severe hepatic dysfunction, since severe hepatic dysfunction has been associated with some cases of lactic acidosis, metformin should generally be avoided in patients with clinical or laboratory evidence of hepatic disease.
Metformin should be temporarily discontinued in patients undergoing radiologic studies involving intravascular administration of iodinated contrast materials, because use of such products may result in acute alteration of renal function (see WARNINGS AND PRECAUTIONS).
- In cases of cardiovascular collapse and in disease states associated with hypoxemia such as cardiorespiratory insufficiency, which are often associated with hyperlactacidemia.
- During stress conditions, such as severe infections, trauma or surgery and the recovery phase thereafter.
- In patients suffering from severe dehydration.
- Known hypersensitivity or allergy to metformin HCl or any of the excipients. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- During pregnancy and breastfeeding.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
- Lactic acidosis is a rare, but serious, metabolic complication that occurs due to metformin accumulation during treatment with Q-METFORMIN (see Endocrine and Metabolism, Lactic Acidosis section below).
- Patients should be cautioned against excessive alcohol intake, either acute or chronic, when taking Q-METFORMIN, since alcohol intake potentiates the effect of metformin on lactate metabolism (see Endocrine and Metabolism, Lactic Acidosis section below).
General
Patient Selection and Follow-up:
Careful selection of patients is important. It is imperative that there be rigid attention to diet and careful adjustment of dosage. Regular thorough follow-up examinations are necessary.
If vomiting occurs, withdraw drug temporarily, exclude lactic acidosis, then resume dosage cautiously (see ADVERSE REACTIONS).
Particular attention should be paid to short range and long range complications which are peculiar to diabetes. Periodic cardiovascular, ophthalmic, hematological, hepatic and renal assessments are advisable.
Use of Q-METFORMIN must be considered as treatment in addition to proper dietary regimen and not as a substitute for diet.
Care should be taken to ensure that Q-METFORMIN is not given when a contraindication exists.
If during Q-METFORMIN therapy the patient develops acute intercurrent disease such as: clinically significant hepatic dysfunction, cardiovascular collapse, congestive heart failure, acute myocardial infarction, or other conditions complicated by hypoxemia, the drug should be discontinued.
Change in clinical status of previously controlled diabetes patients:
A diabetic patient previously well controlled on Q-METFORMIN who develops laboratory abnormalities or clinical illness (especially vague and poorly defined illness) should be evaluated promptly for evidence of ketoacidosis or lactic acidosis. Evaluation should include serum electrolytes and ketones, blood glucose and, if indicated, blood pH, lactate, pyruvate and metformin levels. If acidosis of either form occurs, Q-METFORMIN must be stopped immediately and appropriate corrective measures initiated.
Hypoxic states: Cardiovascular collapse (shock) from whatever cause, acute congestive heart failure, acute myocardial infarction and other conditions characterized by hypoxemia have been associated with lactic acidosis and may also cause prerenal azotemia. When such event occur in patients on Q-METFORMIN therapy, the drug should be promptly discontinued.
Endocrine and Metabolism
Lactic acidosis:
Lactic acidosis is a rare, but serious, metabolic complication that occurs due to metformin accumulation during treatment with Q-METFORMIN. When it occurs, it is fatal in approximately 50% of cases. Lactic acidosis may also occur in association with a number of pathophysiologic conditions, including diabetes mellitus, and whenever there is significant tissue hypoperfusion and hypoxemia. Lactic acidosis is characterized by elevated blood lactate levels (> 5 mmol/L), decreased blood pH, electrolyte disturbances with an increased anion gap, and an increased lactate/pyruvate ratio. When metformin is implicated as the cause of lactic acidosis, metformin plasma levels >5 µg/mL are generally found.
The reported incidence of lactic acidosis in patients receiving metformin HCl is very low (approximately 0.03 cases / 1000 patient-years, with approximately 0.015 fatal cases / 1000 patient-years) and occurs primarily in diabetic patients with significant renal insufficiency,
including both intrinsic renal disease and renal hypoperfusion, often in the setting of multiple concomitant medical/surgical problems and multiple concomitant medications. Patients with congestive heart failure requiring pharmacologic management, in particular those with unstable or acute congestive heart failure who are at risk of hypoperfusion and hypoxemia, are at increased risk of lactic acidosis. In particular, treatment of the elderly should be accompanied by careful monitoring of renal function. Q-METFORMIN treatment should not be initiated in patients ≥ 80 years of age, unless measurement of creatinine clearance demonstrates that renal function is not reduced, as the patients are more susceptible to developing lactic acidosis. The risk of lactic acidosis increases with the degree of renal dysfunction and the patient’s age. The risk of lactic acidosis may, therefore, be significantly decreased by regular monitoring of renal function in patients taking Q-METFORMIN and by use of the minimum effective dose of Q-METFORMIN. In addition, Q-METFORMIN should be promptly withheld in the presence of any condition associated with hypoxemia, dehydration or sepsis. Because impaired hepatic function may significantly limit the ability to clear lactate, Q-METFORMIN should generally be avoided in patients with clinical or laboratory evidence of hepatic disease. Patients should be cautioned against excessive alcohol intake, either acute or chronic, when taking Q-METFORMIN (metformin HCl), since alcohol intake potentiates the effect of metformin HCl on lactate metabolism. In addition, Q-METFORMIN should be temporarily discontinued prior to any intravascular radiocontrast study and for any surgical procedure. The onset of lactic acidosis often is subtle, and accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, increasing somnolence and non-specific abdominal distress. There may be associated hypothermia, hypotension and resistance bradyarrhythmias with more marked acidosis. The patient and the patient’s physician must be aware of the possible importance of such symptoms and the patient should be instructed to notify the physician immediately if they occur. Q-METFORMIN should be withdrawn until the situation is clarified. Serum electrolytes, ketones, blood glucose and, if indicated, blood pH, lactate levels and even blood metformin levels may be useful. Once a patient is stabilized on any dose level of Q-METFORMIN, gastrointestinal symptoms, which are common during initiation of therapy, are unlikely to be drug related. Later occurrence of gastrointestinal symptoms could be due to lactic acidosis or other serious disease. Levels of fasting venous plasma lactate above the upper limit of normal but less than 5 mmol/L in patients taking Q-METFORMIN do not necessarily indicate impending lactic acidosis and may be explainable by other mechanisms, such as poorly controlled diabetes or obesity, vigorous physical activity or technical problems in sample handling. Lactic acidosis should be suspected in any diabetic patient with metabolic acidosis lacking evidence of ketoacidosis (ketonuria and ketonemia).
Lactic acidosis is a medical emergency that must be treated in a hospital setting. In a patient with lactic acidosis who is taking Q-METFORMIN, the drug should be discontinued immediately and general supportive measures promptly instituted. Because metformin HCl is dialysable (with clearance of up to 170 mL/min under good hemodynamic conditions), prompt hemodialysis is recommended to correct the acidosis and remove the accumulated metformin. Such management often results in prompt reversal of symptoms and recovery (see CONTRAINDICATIONS).
NOTE: When used as indicated, there has not been a single case of lactic acidosis in Canada. Q-METFORMIN should be immediately discontinued in the presence of acidosis.
Physicians should instruct their patients to recognize the symptoms which could be signal onset of lactic acidosis. If acidosis of any kind develops, Q-METFORMIN should be discontinued immediately.
Loss of control of blood glucose:
When a patient stabilized on any diabetic regimen is exposed to stress such as fever, trauma, infection, or surgery, a temporary loss of glycemic control may occur. At such times, it may be necessary to withhold Q-METFORMIN and temporarily administer insulin. Q-METFORMIN may be reinstituted after the acute episode is resolved.
The effectiveness of oral antidiabetic drugs in lowering blood glucose to a targeted level decreases in many patients over a period of time. This phenomenon, which may be due to progression of the underlying disease or to diminished responsiveness to the drug, is known as secondary failure, to distinguish it from primary failure in which the drug is ineffective during initial therapy.
Should secondary failure occur with Q-METFORMIN, therapeutic alternatives should be considered.
Vitamin B12 levels:
Impairment of vitamin B12 absorption has been reported in some patients. Therefore, measurements of serum vitamin B12 are advisable at least every one to two years in patients on long-term treatment with Q-METFORMIN.
A decrease to subnormal levels of previously normal serum Vitamin B12 levels, without clinical manifestations, is observed in approximately 7% of patients receiving metformin in controlled clinical trials of 28 weeks duration. Such decrease, possibly due to interference with B12 absorption from B12-intrinsic factor complex is, however, very rarely associated with anemia and appears to be rapidly reversible with discontinuation of metformin or vitamin B12 supplementation. Measurement of hematologic parameters on an annual basis is advised in patients on Q-METFORMIN and any apparent abnormalities should be appropriately investigated and managed (see LABORATORY TESTS). Certain individuals (those with inadequate vitamin B12 or calcium intake or absorption) appear to be predisposed to developing subnormal vitamin B12 levels.
Hepatic/Biliary/Pancreatic
Since impaired hepatic function has been associated with some cases of lactic acidosis, Q-METFORMIN should generally be avoided in patients with clinical or laboratory evidence of hepatic disease.
Hypoglycemia
Hypoglycemia does not occur in patients receiving Q-METFORMIN alone under usual circumstances of use, but could occur when caloric intake is deficient, when strenuous exercise is not compensated by caloric supplementation, or during concomitant use with other glucose lowering agents or ethanol.
Elderly, debilitated or malnourished patients, and those with adrenal or pituitary insufficiency or alcohol intoxication are particularly susceptible to hypoglycemic effects. Hypoglycemia may be difficult to recognize in the elderly, and in people who are taking beta-adrenergic blocking drugs.
The patient should be warned about driving a vehicle or operating machinery under these conditions where risk of hypoglycaemia is present.
Peri-Operative Considerations
Q-METFORMIN therapy should be temporarily suspended for any surgical procedure (except minor procedures not associated with restricted intake of food and fluids). Q-METFORMIN should be discontinued 2 days before surgical intervention and should not be restarted until the patient’s oral intake has resumed and renal function has been evaluated as normal.
Renal
Q-METFORMIN is known to be substantially excreted by the kidney, and the risk of metformin accumulation and lactic acidosis increases with the degree of impairment of renal function. Thus, patients with serum creatinine levels above the upper limit of the normal range for their age should not receive Q-METFORMIN. In patients with advanced age, Q-METFORMIN should be carefully titrated to establish the minimum dose for adequate glycemic effect, because aging is associated with reduced renal function. In elderly patients, renal function should be monitored regularly and generally, Q-METFORMIN should not be titrated to the maximum dose (see DOSAGE AND ADMINISTRATION).
Before initiation of Q-METFORMIN therapy and every 6 months while on Q-METFORMIN therapy, renal function should be assessed and verified as being within normal range.
In patients in whom development of renal dysfunction is anticipated, renal function should be assessed more frequently and Q-METFORMIN discontinued if evidence of renal impairment is present.
Special caution should be exercised in situations where renal function may become impaired, for example when initiating antihypertensive therapy or diuretic therapy and when starting therapy with an NSAID.
Use of concomitant medications that may affect renal function or metformin disposition: Concomitant medication(s) that may affect renal function or result in significant hemodynamic change or may interfere with disposition of Q-METFORMIN, such as cationic drugs that are eliminated by renal tubular secretion (see DRUG INTERACTIONS), should be used with caution.
Radiological studies involving the use of intravascular iodinated contrast materials (for example, intravenous urogram, intravenous cholangiography, angiography, and computed tomography (CT) scans with intravascular contrast material.
Intravascular contrast studies with iodinated materials can lead to acute alteration of renal function and have been associated with lactic acidosis in patients receiving metformin (see CONTRAINDICATIONS). Therefore, in patients in whom any such study is planned, Q-METFORMIN should be temporarily discontinued at the time of or prior to the procedure, and withheld for 48 hours subsequent to the procedure and reinstituted only after renal function has been re-evaluated and found to be normal.
Special Populations
Pregnant Women:
Safety in pregnant women has not been established. Metformin was not teratogenic in rats and rabbits at doses up to 600 mg/kg/day, or about two times the maximum recommended human daily dose on a body surface area basis. Determination of fetal concentrations demonstrated a partial placental barrier to metformin. Because animal reproduction studies are not always predictive of human response, the use of Q-METFORMIN is not recommended during pregnancy.
Because recent information suggests that abnormal blood glucose levels during pregnancy are associated with a higher incidence of congenital abnormalities, there is a consensus among experts that insulin be used during pregnancy to maintain blood glucose levels as close to normal as possible.
Nursing Women:
Studies in lactating rats show that metformin is excreted into milk and reaches levels comparable to those in plasma. Similar studies have not been conducted in nursing mothers, but caution should be exercised in such patients, and a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
Pediatrics:
Safety and effectiveness in pediatric patients have not been established.
Geriatrics:
Controlled clinical studies of metformin (metformin HCl) did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients, although other reported clinical experience has not identified differences in responses between the elderly and younger patients. Metformin is known to be substantially excreted by the kidney and because the risk of serious adverse reactions to the drug is greater in patients with impaired renal function, it should only be used in patients with normal renal function (see CONTRAINDICATIONS and WARNINGS and PRECAUTIONS). Because aging is associated with reduced renal function, Q-METFORMIN should be used with caution as age increases. Care should be taken in dose selection and should be based on careful and regular monitoring or renal function.
Generally, elderly patients should not be titrated to the maximum dose of Q-METFORMIN.
Monitoring and Laboratory Tests
Response to all diabetic therapies should be monitored by periodic measurements of fasting blood glucose and glycosylated hemoglobin levels, with a goal of decreasing these levels toward the normal range. During initial dose titration, fasting glucose can be used to determine the therapeutic response. Thereafter, both glucose and glycosylated hemoglobin should be monitored. Measurements of glycosylated hemoglobin may be especially useful for evaluating long-term control (see DOSAGE AND ADMINISTRATION).
Initial and periodic monitoring of hematologic parameters (e.g., hemoglobin/hematocrit and red blood cell indices) and renal function (serum creatinine) should be performed, at least on an annual basis. While megaloblastic anemia has rarely been seen with metformin (metformin HCl) therapy, if this is suspected, vitamin B12 deficiency should be excluded.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The adverse events most commonly associated with metformin (metformin HCl) are diarrhea, nausea, and upset stomach. Lactic acidosis is a rare, but serious side effect. Lactic acidosis is fatal in approximately 50% of cases.
Lactic Acidosis: very rare (<1/10, 000 and isolated reports). See WARNINGS AND PRECAUTIONS, and OVERDOSAGE Sections.
Gastrointestinal Reactions: very common: (>1/10) Gastrointestinal symptoms (diarrhea, nausea, vomiting, abdominal bloating, flatulence, and anorexia) are the most common reactions to metformin and are approximately 30% more frequent in patients on metformin monotherapy than in placebo-treated patients, particularly during initiation of metformin therapy. These
symptoms are generally transient and resolve spontaneously during continued treatment. Occasionally, temporary dose reduction may be useful.
Because gastrointestinal symptoms during therapy initiation appear to be dose-related, they may be decreased by gradual dose escalation and by having patients take metformin (metformin HCl) with meals (see DOSAGE and ADMINISTRATION).
Because significant diarrhea and/or vomiting can cause dehydration and prerenal azotemia, metformin should be temporarily discontinued, under such circumstances.
For patients who have been stabilized on metformin, nonspecific gastrointestinal symptoms should not be attributed to therapy unless intercurrent illness or lactic acidosis have been excluded.
Special Senses: common (≥1/100): During initiation of metformin therapy complaints of taste disturbance are common, i.e. metallic taste.
Dermatologic Reactions: very rare (<1/10,000 and isolated reports): The incidence of rash/dermatitis in controlled clinical trials was comparable to placebo for metformin monotherapy and to sulfonylurea for metformin/sulfonylurea therapy. Reports of skin reactions such as erythema, pruritus, and urticaria are very rare.
Hematologic: During controlled clinical trials of 29 weeks duration, approximately 9% of patients on metformin monotherapy and 6% of patients on metformin/sulfonylurea therapy developed asymptomatic subnormal serum vitamin B12 levels; serum folic acid levels did not decrease significantly. However, only five cases of megaloblastic anemia have been reported with metformin administration (none during U.S. clinical studies) and no increased incidence of neuropathy has been observed. (see also WARNINGS AND PRECAUTIONS).
Decrease of vitamin B12 absorption with decrease of serum levels during long-term use of metformin is rare (≥1/10,000 and <1/1,000). Consideration of such aetiology is recommended if a patient presents with megaloblastic anemia.
Hepatic: very rare (<1/10,000 and isolated reports): Liver function tests abnormalities or hepatitis resolving upon metformin discontinuation has been documented in isolated reports.
DRUG INTERACTIONS
Overview
Certain drugs may potentiate the effect of metformin, particularly sulfonylurea type of drugs in the treatment of diabetes. The simultaneous administration of these two types of drugs could produce a hypoglycemic reaction, especially if they are given in patients already receiving other drugs which, themselves, can potentiate the effect of sulfonylureas. These drugs
can be: long-acting sulfonamides, tubercolostatics, phenylbutazone, clofibrate, monoamine oxidase inhibitors, salicylates, probenecid and propanolol.
In healthy volunteers, the pharmacokinetics of propranolol and ibuprofen were not affected by metformin when co-administered in single-dose interaction studies.
Metformin is negligibly bound to plasma proteins and is, therefore, less likely to interact with highly protein-bound drugs such as salicylates, sulfonamides, chloramphenicol, and probenecid, as compared to sulfonylureas, which are extensively bound to serum proteins.
Drug-Drug Interactions
Glyburide:
In a single-dose interaction study in NIDDM subjects, co-administration of metformin and glyburide did not result in any changes in either metformin pharmacokinetics or pharmacodynamics. Decreases in glyburide AUC and Cmax were observed, but were highly variable. The single-dose nature of this study and the lack of correlation between glyburide blood levels and pharmacodynamics effects, makes the clinical significance of this interaction uncertain.
Furosemide:
A single-dose study, metformin-furosemide drug interaction study in healthy subjects demonstrated that pharmacokinetic parameters of both compounds were affected by co- administration. Furosemide increased the metformin plasma and blood Cmax by 22% and blood AUC by 15%, without any significant change in metformin renal clearance. When administered with metformin, the Cmax and AUC of furosemide were 31% and 12% smaller, respectively, than when administered alone, and the terminal half-life was decreased by 32%, without any significant change in furosemide renal clearance. No information is available about the interaction of metformin and furosemide when co-administered chronically.
Nifedipine: A single-dose, metformin-nifedipine drug interaction study in healthy volunteers demonstrated that co-administration of nifedipine increased plasma metformin Cmax and AUC by 20% and 9%, respectively, and increased the amount excreted in the urine. Tmax and half-life were unaffected. Nifedipine appears to enhance the absorption of metformin. Metformin had minimal effects on nifedipine.
Cationic Drugs:
Cationic drugs (e.g., amiloride, digoxin, morphine, procainamide, quinidine, quinine, ranitidine, triamterene, trimethoprim, and vancomycin) that are eliminated by renal tubular secretion, theoretically have the potential for interaction with metformin by competing for common renal tubular transport systems. Such an interaction has been observed between metformin and oral cimetidine in normal healthy volunteers in both single and multiple- dose, metformin-cimetidine drug interaction studies, with a 60% increase in peak metformin
plasma and whole blood concentrations and a 40% increase in plasma and whole blood metformin AUC was observed. There was no change in elimination half-life in the single-dose study. Metformin had no effect on cimetidine pharmacokinetics. Therefore, careful patient monitoring and dose adjustment of metformin or the interfering drug is recommended in patients who are taking cationic medications that are excreted via renal tubular secretion.
Other:
Other drugs tend to produce hyperglycemia and may lead to a loss of blood sugar control. These include thiazide and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, estrogen plus progestogen, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, isoniazid, and beta-2-agonists. ACE-inhibitors may decrease the blood glucose levels. When such drugs are administered to patients receiving metformin, the patient should be closely observed to maintain adequate glycemic control.
Elimination rate of the anticoagulant phenprocoumon has been reported to be increased by 20% when used concurrently with metformin. Therefore, patients receiving phenprocoumon or other antivitamin K anticoagulants should be monitored carefully when both types of drugs used simultaneously. In such cases, an important increase of prothrombin time may occur upon cessation of metformin therapy, with an increased risk of hemorrhage.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Test Interactions
Intravascular contrast studies with iodinated materials can lead to acute alteration of renal function and have been associated with lactic acidosis in patients receiving metformin (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Drug-Lifestyle Interactions
Patients should be cautioned against excessive alcohol intake, either acute or chronic, when taking metformin, since alcohol intake potentiates the effect of metformin on lactate metabolism (see CONTRAINDICATIONS).
DOSAGE AND ADMINISTRATION
Dosing Considerations
In diabetic patients, individual determination of the minimum dose that will lower blood glucose adequately should be made, aiming for glycemic targets as close to normal as possible. A lower recommended starting dose and gradually increased dosage is advised to minimize gastrointestinal symptoms.
Over a period of time, patients may become progressively less responsive to therapy with oral hypoglycemic agents because of deterioration of their diabetic state. Patients should therefore be monitored with regular clinical and laboratory evaluations, including blood glucose and glycosylated hemoglobin (AIC) determinations, to determine the minimum effective dosage and to detect primary failure or secondary failure (see WARNINGS AND PRECAUTIONS).
In patients in whom the maximum dose fails to lower the blood glucose adequately, therapeutic alternatives should be considered.
The usual dose is 500 mg three or four times a day, or 850 mg two or three times a day. Maximal dose should not exceed 2.55 g a day. To minimize gastric intolerance such as nausea and vomiting Q-METFORMIN (metformin HCl) should be taken with food whenever possible.
Transfer from Other Antidiabetic Therapy
When transferring patients from standard oral hypoglycaemic agents, other than chlorpropamide, to Q-METFORMIN, no transition period generally is necessary. When transferring patients from chlorpropamide, care should be exercised during the first two weeks because of the prolonged retention of chlorpropamide in the body, leading to overlapping drug effects and possible hypoglycaemia.
Missed Dose
In case the patient forgets to take Q-METFORMIN tablets, he/she should wait for the next dose at the usual time. He/she should not double the dose to make up the forgotten dose.
OVERDOSAGE
Available information concerning treatment of a massive overdosage of Q-METFORMIN (metformin HCl) is very limited. It would be expected that adverse reactions of a more intense character including epigastric discomfort, nausea and vomiting followed by diarrhea, drowsiness, weakness, dizziness, malaise and headache might be seen. Should those
symptoms persist, lactic acidosis should be excluded. The drug should be discontinued and proper supportive therapy instituted.
Overdose of Metformin hydrochloride has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin hydrochloride has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases (see WARNINGS AND PRECAUTIONS). Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Q-METFORMIN (metformin HCl) is a biguanide derivative producing an antihyperglycemic effect which can only be observed in man or in the diabetic animal and only when there is insulin secretion. Metformin, at therapeutic doses, does not cause hypoglycemia when used alone in man or in the non-diabetic animal, except when using a near lethal dose. Metformin has no effects on the pancreatic beta cells. The mode of action of metformin is not fully understood. It has been postulated that metformin might potentiate the effect of insulin or that it might enhance the effect of insulin on the peripheral receptor site. This increased sensitivity seems to follow an increase in the number of insulin receptors on cell surface membranes.
Metformin absorption is relatively slow and may extend over about 6 hours. The drug is excreted in urine at high renal clearance rate of about 450 mL/min. The initial elimination of metformin is rapid with a half-life varying between 1.7 and 3 hours. The terminal elimination phase accounting for about 4 to 5 % of the absorbed dose is slow with a half- life between 9 and 17 hours. Metformin is not metabolized. Its main sites of concentration are the intestinal mucosa and the salivary glands. The plasma concentration at steady-state ranges about 1 to 2 mcg/mL. Certain drugs may potentiate the effects of metformin (see WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS).
STORAGE AND STABILITY
Store at room temperature (15° to 30°C) in well closed containers.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Q-METFORMIN (Metformin Tablets, BP) 500 mg Tablets are white, round, biconvex, film-coated, with blackberry scent, marked "MF" scoreline "1" on one side and "G" on the other.
Q-METFORMIN (Metformin Tablets, BP) 850 mg Tablets are white, capsule shaped, biconvex, film-coated, with blackberry scent, marked "MF2" on one side and "G" on the other.
Q-Metformin 500 mg & 850 mg tablets are available in bottles of 100 and 500 tablets.
COMPOSITION: Each Q-METFORMIN 500 mg film-coated tablet contains 500 mg of Metformin hydrochloride, magnesium stearate, povidone, artificial blackberry flavour, titanium dioxide, macrogol and talc.
Each Q-METFORMIN 850 mg film-coated tablet contains 850 mg of Metformin hydrochloride, magnesium stearate, povidone, artificial blackberry flavour, titanium dioxide, macrogol and talc.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
DRUG SUBSTANCE
Proper name: Metformin Hydrochloride, BP
Chemical name: 1,1-dimethyl-biguanide hydrochloride
Empirical formula: C4H11N5, HCl
Structural formula:
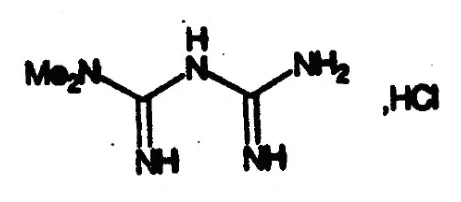
Molecular weight: 165.6
Description: Metformin is a white crystalline powder; odourless or almost odourless.
Hygroscopic. Soluble in 2 parts of water; slightly soluble in ethanol \ (96%), practically insoluble in chloroform and in ether. The partition coefficient (octanol/water) is 1.43 determined using pH 7.3 phosphate buffer. The pH of an aqueous solution ranges between 6 and 7, and pka 2.8, 11.5 (32oC). Melting point is about 225EC.
CLINICAL TRIALS
A single dose, 2-way crossover comparative bioavailability study, conducted under fasting conditions, was performed on 18 healthy male volunteers. The rate and extent of absorption of metformin was measured and compared following a single oral dose (2 x 500 mg tablet) of GLUCOPHAGETM (metformin hydrochloride) and Q-METFORMIN (metformin hydrochloride). The results from measured data are summarized in the following table.
TABLE 1: MEAN PHARMACOKINETIC DATA
Metformin Tablets
(2 x 500 mg)
From measured data
Geometric Mean
Arithmetic Mean (CV %)
| Q-METFORMIN QD Pharmaceuticals ULC (2 x 500 mg Tablet) | GLUCOPHAGE Marion Merrell Dow, Canada (2 x 500 mg Tablet) | Ratio Generic/brand (%) | 90% Confidence Interval | |
| AUC(0-T) (ng.hr.mL-1) | 10938.0 11287.4 (25.8) | 10301.0 10645.5 (27.0) | 106 | 95.3 – 116.7 |
| AUC (0-inf) (ng.hr.mL-1) | 11158.98 11526.7 (25.6) | 10509.1 10886.3 (26.5) | 106 | 95.5 – 116.3 |
Cmax (ng.mL-1) | 1826.2 1890.0 (24.6) | 1719.9 1807.4 (34.7) | 106 | 90.4 – 118.8 |
| Tmax(hrs)* T1/2 (hrs)* | 2.01 (0.87) 5.44 (0.82) | 2.36 (0.84) 5.71 (1.05) |
* For Tmax and T1/2 arithmetic means (standard deviation) are presented.
The data which formed the basis of approval for the original metformin submission are not available. Rather, this section presents data from a published study which investigated the safety and efficacy of metformin.
The prospective randomised (UKPDS) study has established the long-term benefit of intensive blood glucose control in adult patients with type 2 diabetes. Analysis of the results for overweight patients treated with metformin after failure of diet alone showed:
- a significant reduction of the absolute risk of any diabetes-related complication in the metformin group (29.8 events/1000 patient-years) versus diet alone (43.3 events/1000 patient-years), p=0.0023, and versus the combined sulfonylurea and insulin monotherapy groups (40.1 events/1000 patient-years), p=0.0034;
- a significant reduction of the absolute risk of diabetes-related mortality: metformin 7.5 events/1000 patient years, diet alone 12.7 events/1000 patient-years, p=0.017. There was no significant difference between the metformin group and those assigned intensive therapy with sulfonylurea or insulin.
- a significant reduction of the absolute risk of overall mortality; metformin 13.5 events/1000 patient-years versus diet alone 20.6 events/1000 patient-years (p=0.011), and versus the combined sulfonylurea and insulin monotherapy groups 18.9 events/1000 patient-years (p=0.021);
- a significant reduction in the absolute risk of myocardial infarction: metformin 11 events/1000 patient-years, diet alone 18 events/1000 patient-years (p=0.01). There was no significant difference between the metformin group and those assigned intensive therapy with sulfonylurea or insulin.
- There were no significant differences between the metformin group and the diet alone in the other aggregate endpoints (stroke, peripheral vascular disease and microvascular complications.
DETAILED PHARMACOLOGY
Metformin absorption is relatively slow and may extend over about 6 hours.
Animal studies with metformin, labelled with 14C have shown that the drug is neither concentrated by liver cells nor is it excreted in the bile; it is concentrated in the intestinal mucosa and salivary glands.
It has been shown that, following a 2 g dose of metformin, the blood level remains under 10 mcg/mL even at the peak, occurring 2 hours after absorption. During the experiments, metformin was shown to be devoid of any notable action in the body, apart from its specific metabolic activity.
In the healthy animal, metformin lowers blood sugar only at a nearly lethal dose. Different animal species are of unequal sensitivity. On the other hand, the animal with experimental diabetes, is sensitive to a much lower dosage, providing some insulin is still secreted.
The antihyperglycemic action of metformin is probably mediated through insulin:
Metformin improves the K co-efficient of glucose assimulation.
Metformin improves the co-efficient of insulin efficiency.
In the obese diabetic with hyperinsulinemia, metformin is reported to normalize insulin output. This normalizing effect is concurrent to that of glycemia.
Metformin has little effect on liver glycogen of the healthy animal. In low and average doses, no change occurs. In high doses nearing lethal levels, liver glycogen decreases. This lowering precedes the fall in blood sugar. This reaction represents a defense mechanism tending to mobilize body reserves in order to combat hypoglycemia.
In the diabetic animal with a low liver glycogen reserve, the opposite occurs and metformin builds up glycogen stores of the liver. In vitro, on muscular tissue isolated in Warburg’s apparatus, metformin increases glucose uptake by the muscle. This action follows an aerobic pathway. Even in high concentration, contrary to phenethyl-biguanide, metformin apparently does not block respiration or change carbohydrate metabolism via the anaerobic pathway.
Metformin is eliminated in faeces and urine. It is rapidly excreted by the kidneys in an unchanged form.
Renal clearance is 450 mL/minute; this appears to explain the absence of accumulation.
Metabolites of metformin have not been identified, neither by radio-active nor by chemical methods.
A single Rf spot is always present following radiochromatographic study of urine and always corresponds to that of pure metformin. Administration during 10 consecutive days has not shown any sign of accumulation.
Inhibition of glyconeogenesis has been observed in animals following its stimulation by fasting, cortisol, alcohol or other substrates such as alanine lactate or pyruvate. However, such an effect varies according to the type and dosage of the biguanide used, nutritional state of the animal species and design of experimental model.
This inhibition of glyconeogenesis is observed only in the presence of insulin and it does not appear to play an important role in man.
Inhibition of intestinal absorption of sugars, which is not related to a malasorption phenomenon has been observed with biguanides under certain experimental conditions in animal and in man. In one study, a 20% retardation of galactose absorption was observed in man receiving metformin. However, such an effect of metformin could not be confirmed in another study in man.
Recent findings appear to indicate that most of the metabolic effects of the biguanides are exerted through a single mechanism, namely inhibition of fatty acid oxidation and of acetyl-CoA generation.
However, inhibition of insulin-stimulated lipogenesis which has also been observed appears to be due to the inhibition of acetyl-CoA carboxylase by the biguanides. Such an effect may
explain, at least partly, the weight-reducing effect exerted by these drugs in obese diabetic patients.
TOXICOLOGY
- 1.
Animal Toxicity
Acute Toxicity (LD50)
Animal Subcutaneously Orally
Mouse 225 mg/kg 3500 mg/kg
Chicken 150 mg/kg
Rat 300 mg/kg 1000 mg/kg
Rabbit 150 mg/kg 350 mg/kg
Guinea Pig 150 mg/kg 500 mg/kg
Chronic Toxicity
A) The following doses of metformin produced no organ toxicity:
Rats 125 mg/kg per os for one year
Rabbits 100 mg/kg per os for one year
Dogs 50 mg/kg subcutaneously for 2 years
Acute or chronic organ toxicity was not produced in the animal species involved.
B) A study was carried out during 9 months with 80 rats, male and female, divided in 4 groups, with the following dosage regimen:
1st GROUP control
2nd GROUP 150 mg/kg per os
3rd GROUP 300 mg/kg per os
4th GROUP 300 mg/kg per os, dose increased by 100 mg/kg/day every 15 days.
In summary, the authors report the excellent tolerance of metformin by rats, even when administered in very high doses. No drug related lesion has been observed.
C) Chronic toxicity studies of 9 months duration were carried through with 16 beagle dogs, although the complete intolerance of this animal species to oral hypoglycemic agents is a well established fact. Trophic and neurologic disorders with cachexia rapidly lead to the dog’s death. During the periods of metformin administration, laboratory findings were within normal limits. The levels of enzymes were somewhat elevated, but it is difficult
to ascribe a pathological significance to their values, since subjects in the control group were at the same level as treated animals.
Pathological studies show an extreme degree of undernutrition in all metformin treated animals. Profound wasting especially marked in fat tissues was evident in all organs. Cachexia appears as the common cause of death of these animals.
- 2.
Human Toxicity
In man, no adverse effect has been reported on liver or kidney function, the hematopoietic system or on the blood vessels.
The reported incidence of lactic acidosis in patients receiving metformin hydrochloride is very low (approximately 0.03 cases/1000 patient/years with approximately 0.015 fatal cases/1000 patients/years).
The consecutive administration of both phenformin and metformin to the same patient has allowed for the demonstration of a fundamental difference between these two biguanides in relation to lactacidemia. In some instances, patients developed hyperlactacidemia with phenformin when the same patients were presenting normal lactic acid levels while being treated with metformin. In other instances, hyperlactacidemia observed during a treatment with phenformin did regress when metformin was substituted for phenformin. Metformin may increase lactacidemia but to a degree that is clinically less significant than the elevation seen after phenformin.
- 3.
Teratology
Teratological studies were carried out in albino rats divided in three groups: No abnormalities were found, even when high doses were administered. The number of animals was the same in each group.
Death rate in the three groups of treated animals and controls was approximately the same. However, the number of living animals in each group treated was slightly lower than in the control group. Also, the frequency of litters exceeding 10 live animals was slightly higher in the control group. A loss of weight at the time of weaning has been observed when compared to the control group.
Nevertheless, on a statistical basis, differences were shown to be non-significant. There is no difference between the groups of treated animals and the control group regarding the number of stillborn. The number of deaths after birth was slightly higher in metformin treated groups than in the control group, but the comparison of average death rates is not significant (p < 0.05).
_____________________________________________________________________________________________
BIBLIOGRAPHY
- 1. Alberti KGM, et al. Lactic Acidosis. The Lancet. 1977 July2:25-29.
- 2.
Beckmann R. Résorbtion, distribution dans l`organisme et élimination de la
Metformine. Diabétologia. 1969;5:318-324.
- 3.
Benoit R, et al. Acidose lactique et phenformine. L’Union Médicale du Canada.
1976; 105: 1810-1814.
- 4. Berger W, et al. Problèmes d’actualité concernant le mécanisme d’action des biguanides. Jour. Diab. Hôtel-Dieu Paris. 1975; 239-258.
- 5. Bermond P, The coefficient of insulin efficacy. Effect of Metformin on this parameter. Xième Congrès Fédération Int. Diabétologie, Stockholm; 1967. Ed. Excerpa Medica F.Amsterdam; 1968.
- 6. Biron P. Metformin monitoring. C.M.A.J. 1980;123:11-12.
- 7. Bouaziz Pl. Apport à l’étude de l’épreuve d’hyperglycémie provoquée par voie veineuse sous thérapie diabétique. Thèse de doctorat en Médecine, Paris. 1966.
- 8.
Canadian Diabetes Association. Nephropathy. Canadian Journal of Diabetes. 2003
Clinical Practice Guidelines;2003:S66-71
- 9.
Canadian Diabetes Association. Pharmacologic management of type 2 diabetes.
Canadian Journal of Diabetes. 2003 Clinical Practice Guidelines;2003:S37-S42
- 10.
Canadian Diabetes Association. Physical activity and diabetes. Canadian Journal of
Diabetes. 2003 Clinical Practice Guidelines;2003:S24-S26.
- 11.
Canadian Diabetes Association. Targets for glycemic control. Canadian Journal of
Diabetes. 2003 Clinical Practice Guidelines;2003:S18-S20.
- 12.
Canadian Diabetes Association. Pre-existing diabetes and pregnancy. Canadian
Journal of Diabetes. Clinical Practice Guidelines Expert Committee;2003;S94-S98.
- 13. Chan JCN, et al. Drug-induced disorders of glucose metabolism. Mechanisms and management. Drug Safety, 1996 Aug; 15(2):135-157.
- 14. Cohen RD. The relative risks of different biguanides in the causation of lactic acidosis. Research and Clinical Forums. 1979;1(4):125-134.
- 15.
Cohen Y, et al. Etude autoradiographique chez la souris d’un antidiabétique oral, le
N.N. Diméthylbiguanide, marqué au C14 Thérapie. 1961;109-120.
- 16. Cohen Y, et al. Etude autoradiographique chez la souris d’un antidiabétique oral marqué au C14, le N.N. Diméthylbiguanide, après administrations répétées. Thérapie. 1968;23:1185-1191.
- 17. Cox D, et al. The effects of glucose fluctuation on cognitive function and QOL: the functional costs of hypoglycaemia and hyperglycaemia among adults with Type 1 or Type 2 diabetes. IJCP 2002 July; (Suppl.129):20-26.
- 18.
Daubresse JC, et al. Acidose lactique et thérapeutique par biguanides. Méd. et Hyg.
1975;1168.
- 19. Debry G, et al. Etude du mode d’excrétion du N.N. Diméthylbiguanide chez le diabétique adulte. Thérapie. 1965;20:351-358.
- 20. Derot M, et al. Retrospective study of the cardiovascular fate of 190 patients treated for 5 year or more with biguanides alone. Abstracts, 11th Annual Meeting, Munich.Sept.; 1975.
- 21. Duval D. Contribution à l’étude de l’action hypoglycémiante des biguanides. Thèse de Doctorat en Médecine, Paris. 1960.
- 22. Duwoos H, et al: Hyperlactacidémie réversible induite par la phenformine avec asthénie musculaire et signes cardio-respiratoires. Presse Méd. 1970;78:23-26.
- 23. Glueck CJ, Wang P, Kobayashi S, Phillips H, Sieve-Smith L. Metformin therapy throughout pregnancy reduces the development of gestational diabetes in women with polycystic ovary syndrome. Fertility and Sterility. 2002;77(3):520-525.
- 24. Hermann LS. Metformin: A review of its pharmacological properties and therapeutic use. Diabète et Métabolisme. 1979;3:233-245.
- 25. Hermann LS. Metabolic effects of Metformin in relation to clinical effects and side effects in Biguanide Therapy Today. International Congress and Symposium, series published by the Royal Society of Medicine. 1981;48:17-43.
- 26. Holle A, et al. Biguanide treatment increases the number of insulin receptor sites on human erythrocytes. The New Engl. J. Med. 1981;305(10):563-566.
- 27.
Hunt JA, et al. The use of phenformin and metformin. Letter to the Editor, C.M.A.J.
1977;117(5):429-430.
- 28.
Irsigler K. Glucoseutilisation and Plasmaliporide bei adiposen Patienten unter dem
Einfluss von Dimethylbiguanide (GLUCOPHAGE®). wiener med. Wsch. 1969;119:191-194.
- 43.
Stowers JM. Long-term therapy with biguanides in Biguanide Therapy Today.
International Congress and Symposium, series published by the Royal Society of Medicine. 1981;48:49-57.
- 44. Stowers JM,et al. Oral hypoglycemic agents: Clinical pharmacology and therapeutic use. Drugs. 1977;14:41-56.
- 45. Vague P. Effet d’une dose unique de metformine sur la tolérance au glucose des sujets normaux ou obèses. Le Diabète. 1970;18:35-39.
- 46. Vermulen A, et al. Influence of dimethylbiguanide (metformin) on carbohydrate metabolism in obese, non diabetic women. Diabetologia. 1972;8:8-11.
- 47. UK Prospective Diabetes Study (UKPDS) Group. Effect of intensive blood-glucose control with metformin on complications in overweight patients with type 2 diabetes (UKPDS 34). The Lancet. 1998;352:854-865.
- 48. UK Prospective Diabetes Study (UKPDS) Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). The Lancet. 1998;352:837- 853.
- 49.
GLUCOPHAGE® Product Monograph. Sanofi-Aventis Canada Inc. Control No.
128147. October 28, 2009.