


Product Monograph - Remifentanil for Injection (Teva Canada)
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| intravenous | 1 mg, 2 mg vials of remifentanil base as the hydrochloride salt | Glycine For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING section. |
INDICATIONS AND CLINICAL USE
Adults
REMIFENTANIL FOR INJECTION (remifentanil hydrochloride) is indicated for i.v. administration as an analgesic agent for use during the induction and maintenance of general anesthesia for inpatient and outpatient procedures.
Due to insufficient safety and efficacy data, remifentanil is not recommended for use in spontaneous ventilation anesthesia, in monitored anesthesia care, for continuation as an analgesic in the immediate postoperative period, in neurosurgery, in cardiac surgery, or in pediatric anesthesia.
Geriatrics (> 65 years of age)
For details, see DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment.
Pediatrics
REMIFENTANIL FOR INJECTION is not indicated in children.
CONTRAINDICATIONS
Due to the presence of glycine in the formulation, REMIFENTANIL FOR INJECTION (remifentanil hydrochloride) is contraindicated for epidural or intrathecal administration.
- Patients who are hypersensitive to the active substance Remifentanil hydrochloride or other opioid analgesics or to any ingredient in the formulation. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
- In patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction or strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- Patients with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis).
- Patients with mild pain that can be managed with other pain medications.
- Patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus.
- Patients with acute respiratory depression, elevated carbon dioxide levels in the blood and cor pulmonale.
- Patients with acute alcoholism, delirium tremens, and convulsive disorders.
- Patients with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury.
- Patients taking monoamine oxidase (MAO) inhibitors (or within 14 days of such therapy).
WARNINGS AND PRECAUTIONS
SERIOUS WARNINGS AND PRECAUTIONS
Limitations of Use
Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, and because of the risks of overdose and death with immediate release opioid formulations, REMIFENTANIL FOR INJECTION should only be used in patients for whom alternative treatment options (e.g., non-opioid analgesics) are ineffective, not tolerated, or would be otherwise inadequate to provide appropriate management of pain (see DOSAGE AND ADMINISTRATION).
Addiction, Abuse, and Misuse
REMIFENTANIL FOR INJECTION poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing REMIFENTANIL FOR INJECTION, and all patients should be monitored regularly for the development of these behaviours or conditions (see WARNINGS AND PRECAUTIONS). REMIFENTANIL FOR INJECTION should be stored securely to avoid theft or misuse.
Life-threatening Respiratory Depression: OVERDOSE
SERIOUS WARNINGS AND PRECAUTIONS
Serious, life-threatening, or fatal respiratory depression may occur with use of REMIFENTANIL FOR INJECTION. Infants exposed in-utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of REMIFENTANIL FOR INJECTION or following a dose increase. Further, instruct patients of the hazards related to taking opioids including fatal overdose.
Accidental Exposure
Accidental ingestion of even one dose of REMIFENTANIL FOR INJECTION, especially by children, can result in a fatal overdose of remifentanil hydrochloride.
Neonatal Opioid Withdrawal Syndrome
Prolonged maternal use of REMIFENTANIL FOR INJECTION during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see WARNINGS AND PRECAUTIONS).
Interaction with Alcohol
The co-ingestion of alcohol with REMIFENTANIL FOR INJECTION should be avoided as it may result in dangerous additive effects, causing serious injury or death (see WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS).
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see WARNINGS AND PRECAUTIONS, Neurologic and DRUG INTERACTIONS).
- Reserve concomitant prescribing of REMIFENTANIL FOR INJECTION and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
General
REMIFENTANIL FOR INJECTION should only be prescribed by persons knowledgeable in the continuous administration of potent opioids, in the management of patients receiving potent opioids for the treatment of pain, and in the detection and management of respiratory depression, including the use of opioid antagonists.
Patients should be cautioned not to consume alcohol while taking REMIFENTANIL FOR INJECTION as it may increase the chance of experiencing serious adverse events, including death.
Hyperalgesia that will not respond to a further dose increase of remifentanil hydrochloride can occur at particularly high doses. A remifentanil hydrochloride dose reduction or change in opioid may be required.
Remifentanil is not recommended for use as the sole agent in general anesthesia because loss of consciousness cannot be assured and because of a high incidence of apnea, muscle rigidity and tachycardia.
Continuous infusions of remifentanil should be administered only by an infusion device. I.V. bolus administration should only be used in intubated patients during the maintenance of general anesthesia. For induction of anesthesia in nonintubated patients, a single dose of remifentanil, not exceeding 1 µg/kg, may be administered over 30 to 60 seconds.
Interruption of an infusion of remifentanil will result in rapid offset of effect. Rapid clearance and lack of drug accumulation result in rapid dissipation of respiratory depressant and analgesic effects upon discontinuation of remifentanil at recommended doses. However, delayed respiratory depression may occur in some patients up to 30 minutes after termination of remifentanil infusions due to residual effects of concomitant anesthetics. Discontinuation of an infusion of remifentanil should be preceded by the establishment of adequate postoperative analgesia (see WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION).
Injections of remifentanil should be made into i.v. tubing at or close to the venous cannula. Upon discontinuation of remifentanil, the i.v. tubing should be removed or cleared to prevent the inadvertent administration of remifentanil at a later point in time. Failure to adequately clear the i.v. tubing to remove residual remifentanil has been associated with the appearance of respiratory depression, apnea and muscle rigidity upon the administration of additional fluids or medications through the same i.v. tubing.
Use of remifentanil is associated with apnea and respiratory depression. Remifentanil should be administered only in a setting fully equipped for the monitoring and support of respiratory and cardiovascular function. Resuscitative and intubation equipment, oxygen and an opioid antagonist must be readily available.
Remifentanil should be administered only by persons specifically trained in the use of anesthetic drugs and the recognition and management of the expected adverse effects of potent opioids, including respiratory and cardiac resuscitation of patients in the age-group being treated. Such training must include the establishment and maintenance of a patent airway and assisted ventilation.
Skeletal muscle rigidity can be caused by remifentanil and is related to the dose and speed of administration. Remifentanil may cause chest wall rigidity (inability to ventilate) after single doses > 1 µg/kg administered over 30 to 60 seconds, or after infusion rates > 0.1 µg/kg/min.
Single doses < 1 µg/kg may cause chest wall rigidity when given concurrently with a continuous infusion of remifentanil.
Muscle rigidity induced by remifentanil should be managed in the context of the patient’s clinical condition. Muscle rigidity occurring during the induction of anesthesia should be treated by the administration of a neuromuscular blocking agent and the concurrent induction medications.
Remifentanil should not be administered into the same i.v. tubing with blood/serum/plasma due to potential inactivation by nonspecific esterases in blood products.
Vital signs and oxygenation must be continually monitored during the administration of remifentanil.
Intraoperative awareness has been reported in patients under 55 years of age when remifentanil has been administered with propofol infusion rates of ≤ 75 µg/kg/min. Therefore, propofol rates < 100 µg/kg/min are not recommended for use with remifentanil for total intravenous anesthesia in patients < 55 years of age.
Abuse and Misuse
Like all opioids, remifentanil is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, REMIFENTANIL FOR INJECTION should be prescribed and handled with caution.
Patients should be assessed for their clinical risks for opioid abuse or addiction prior to being prescribed opioids. All patients receiving opioids should be routinely monitored for signs of misuse and abuse.
Opioids, such as REMIFENTANIL FOR INJECTION, should be used with particular care in patients with a history of alcohol and illicit/prescription drug abuse. However, concerns about abuse, addiction, and diversion should not prevent the proper management of pain.
Carcinogenesis and Mutagenesis
See TOXICOLOGY section.
Cardiovascular
Remifentanil hydrochloride administration may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by reduced blood volume, or concurrent administration of drugs such as phenothiazines and other tranquilizers, sedative/hypnotics, tricyclic antidepressants or general anesthetics. These patients should be monitored for signs of hypotension after initiating or titrating the dose of REMIFENTANIL FOR INJECTION.
The use of REMIFENTANIL FOR INJECTION in patients with circulatory shock should be avoided as it may cause vasodilation that can further reduce cardiac output and blood pressure.
Rapid intravenous injection of opioid analgesics increases the possibility of hypotension and respiratory depression and should be avoided (see DOSAGE AND ADMINISTRATION).
Dependence/Tolerance
As with other opioids, tolerance and physical dependence may develop upon repeated administration of REMIFENTANIL FOR INJECTION and there is a potential for development of psychological dependence.
Physical dependence and tolerance reflect the neuroadaptation of the opioid receptors to chronic exposure to an opioid, and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
Patients on prolonged therapy should be tapered gradually from the drug if it is no longer required for pain control. Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning (see ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION).
Use in Drug and Alcohol Addiction
REMIFENTANIL FOR INJECTION is an opioid with no approved use in the management of addictive disorders. Its proper usage in individuals with drug or alcohol dependence, either active or in remission is for the management of pain requiring opioid analgesia. Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to REMIFENTANIL FOR INJECTION; extreme caution and awareness is warranted to mitigate the risk.
Gastrointestinal Effects
Remifentanil hydrochloride and other morphine-like opioids have been shown to decrease bowel motility. Remifentanil hydrochloride may obscure the diagnosis or clinical course of patients with acute abdominal conditions (see CONTRAINDICATIONS).
Hepatic/Biliary/Pancreatic
Remifentanil pharmacokinetic/pharmacodynamic profile is not changed in patients with severe hepatic impairment. However, these patients may be slightly more sensitive to respiratory
depressant effects of remifentanil. Therefore these patients should be closely monitored and the dose of remifentanil titrated to individual patient need.
Neonatal Opioid Withdrawal Syndrome (NOWS)
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn.
REMIFENTANIL FOR INJECTION is not recommended to be used in pregnant women unless, in the judgement of the physician, the potential benefits outweigh the risks. If REMIFENTANIL FOR INJECTION was used during pregnancy, special attention to NOWS is warranted.
Neurologic
Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol): Remifentanil hydrochloride should be used with caution and in a reduced dosage during concomitant administration of other opioid analgesics, general anesthetics, phenothiazines and other tranquilizers, sedative-hypnotics, tricyclic antidepressants, antipsychotics, antihistamines, benzodiazepines, centrally-active anti-emetics and other CNS depressants. Respiratory depression, hypotension and profound sedation, coma or death may result.
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risk with the concomitant use of other CNS depressant drugs with opioid analgesics (see DRUG INTERACTIONS). If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation.
Advise both patients and caregivers about the risks of respiratory depression and sedation when REMIFENTANIL FOR INJECTION is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the benzodiazepine or other CNS depressant have been
determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk for overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs (see DRUG INTERACTIONS). REMIFENTANIL FOR INJECTION should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects, including death (see CONTRAINDICATIONS and ADVERSE REACTIONS, Sedation, and DRUG INTERACTIONS).
Severe pain antagonizes the subjective and respiratory depressant actions of opioid analgesics. Should pain suddenly subside, these effects may rapidly become manifest.
Head Injury: The respiratory depressant effects of remifentanil hydrochloride, and the capacity to elevate cerebrospinal fluid pressure, may be greatly increased in the presence of an already elevated intracranial pressure produced by trauma. Also, remifentanil hydrochloride may produce confusion, miosis, vomiting and other side effects which obscure the clinical course of patients with head injury. In such patients, remifentanil hydrochloride must be used with extreme caution and only if it is judged essential (see CONTRAINDICATIONS).
Peri-Operative Considerations
REMIFENTANIL FOR INJECTION is not indicated for pre-emptive analgesia (administration pre-operatively for the management of post-operative pain).
In the case of planned chordotomy or other pain-relieving operations, patients should not be treated with REMIFENTANIL FOR INJECTION for at least 24 hours before the operation and REMIFENTANIL FOR INJECTION should not be used in the immediate post-operative period.
Physicians should individualize treatment, moving from parenteral to oral analgesics as appropriate. Thereafter, if REMIFENTANIL FOR INJECTION is to be continued after the patient recovers from the post-operative period, a new dosage should be administered in accordance with the changed need for pain relief. The risk of withdrawal in opioid-tolerant patients should be addressed as clinically indicated.
The administration of analgesics in the peri-operative period should be managed by healthcare providers with adequate training and experience (e.g., by an anesthesiologist).
Remifentanil hydrochloride and other morphine-like opioids have been shown to decrease bowel motility. Ileus is a common post-operative complication, especially after intra-abdominal surgery with opioid analgesia. Caution should be taken to monitor for decreased bowel motility in postoperative patients receiving opioids. Standard supportive therapy should be implemented.
Use in Cardiovascular Surgery
Clinical experience with remifentanil in patients undergoing cardiac surgery is limited to coronary artery bypass graft procedures (CABG). There are insufficient data to make a dosage recommendation.
Use in Neurosurgery
Due to the limited number of patients studied, there are insufficient data to make dosage recommendations.
Psychomotor Impairment
REMIFENTANIL FOR INJECTION may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery. Patients should be cautioned accordingly. Patients should also be cautioned about the combined effects of remifentanil hydrochloride with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol.
Renal
The pharmacodynamic/pharmacokinetic profile of remifentanil is not changed in patients with end stage renal disease (creatinine clearance < 10 mL/min). No dosage adjustment is necessary in this patient population.
In anephric patients, the half-life of the carboxylic acid metabolite increases from 90 minutes to approximately 30 hours. The metabolite is removed by hemodialysis with a dialysis extraction ratio of approximately 30%.
Respiratory
Respiratory Depression: Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient’s clinical status. Remifentanil hydrochloride should be used with extreme caution in patients with substantially decreased respiratory reserve, pre-existing respiratory depression, hypoxia or hypercapnia (see CONTRAINDICATIONS).
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of REMIFENTANIL FOR INJECTION, the risk is greatest during the initiation of therapy or following a dose increase. Patients should be closely monitored for respiratory depression when initiating therapy with REMIFENTANIL FOR INJECTION and following dose increases.
Life-threatening respiratory depression is more likely to occur in the elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients.
To reduce the risk of respiratory depression, proper dosing and titration of REMIFENTANIL FOR INJECTION are essential. Overestimating the REMIFENTANIL FOR INJECTION dose when converting patients from another opioid product can result in a fatal overdose with the first
dose. In these patients, the use of non-opioid analgesics should be considered, if feasible (see WARNINGS AND PRECAUTIONS, Special Populations, Special Risk Groups, and DOSAGE AND ADMINISTRATION).
Use in Patients with Chronic Pulmonary Disease: Monitor patients with significant chronic obstructive pulmonary disease or cor pulmonale, and patients having a substantially decreased respiratory reserve, hypoxia, hypercapnia, or preexisting respiratory depression for respiratory depression, particularly when initiating therapy and titrating with REMIFENTANIL FOR INJECTION, as in these patients, even usual therapeutic doses of REMIFENTANIL FOR INJECTION may decrease respiratory drive to the point of apnea. In these patients, use of alternative non-opioid analgesics should be considered, if possible. The use of REMIFENTANIL FOR INJECTION is contraindicated in Patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus (see CONTRAINDICATIONS).
Within 5 to 10 minutes after the discontinuation of REMIFENTANIL FOR INJECTION (remifentanil hydrochloride), no residual analgesic activity will be present. However, respiratory depression may occur in some patients up to 30 minutes after termination of infusion due to residual effects of concomitant anesthetics. Standard monitoring should be maintained in the postoperative period to ensure adequate recovery without stimulation. For patients undergoing surgical procedures where postoperative pain is generally anticipated, other analgesics should be administered prior to the discontinuation of remifentanil.
Bradycardia has been reported with remifentanil and is responsive to ephedrine or anticholinergic drugs, such as atropine and glycopyrrolate.
Special Populations
Special Risk Groups: REMIFENTANIL FOR INJECTION should be administered with caution to patients with a history of alcohol and drug abuse and in a reduced dosage to debilitated patients, and in patients with severely impaired pulmonary function, Addison’s disease, hypothyroidism, myxedema, toxic psychosis, prostatic hypertrophy or urethral stricture.
Pregnant Women: Studies in humans have not been conducted. REMIFENTANIL FOR INJECTION crosses the placental barrier and is not recommended to be administered to pregnant women unless, in the judgement of the physician, potential benefits outweigh the risks.
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening (see WARNINGS AND PRECAUTIONS, Neonatal Opioid Withdrawal Syndrome, ADVERSE REACTIONS, Post-marketing Experience). Pregnant women using opioids should not discontinue their medication abruptly as this can cause pregnancy complication such as miscarriage or still-birth. Tapering should be slow and under medical supervision to avoid serious adverse events to the fetus.
Labour, Delivery and Nursing Women:
Since opioids can cross the placental barrier and are excreted in breast milk, REMIFENTANIL FOR INJECTION is not recommended to be used in nursing women and during labour and delivery unless, in the judgement of the physician, the potential benefits outweigh the risks. Life-threatening respiratory depression can occur in the infant if opioids are administered to the mother. Naloxone, a drug that counters the effects of opioids, should be readily available if REMIFENTANIL FOR INJECTION is used in this population.
Pediatrics (< 18 years of age):
The safety and efficacy of Remifentanil Hydrochloride for Injection have not been studied in the pediatric population. Therefore, use of Remifentanil Hydrochloride for Injection is not recommended in patients under 18 years of age.
Geriatrics (> 65 years of age): In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range and titrate slowly, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Geriatrics).
The clearance of remifentanil is reduced (approximately 25%) in the elderly (> 65 years of age) compared to young adults (average 25 years of age). However, remifentanil blood concentrations fall as rapidly after termination of administration in the elderly as in young adults. The pharmacodynamic activity of remifentanil (as measured by the EC50 for development of delta waves on the electroencephalogram [EEG]) increases with increasing age. The EC50 of remifentanil for this measure was 50% less in patients over 65 years of age when compared to healthy volunteers (25 years of age); therefore, the recommended starting dose of remifentanil should be decreased by 50% in elderly patients and then titrated to individual patient need (see DOSAGE AND ADMINISTRATION).
Morbidly Obese Patients
As for all potent opioids, caution is required when used in morbidly obese patients because of alterations in cardiovascular and respiratory physiology (see DOSAGE AND ADMINISTRATION).
ASA III/IV Patients
Limited data is available from 65 ASA III and 1 ASA IV patients. As the hemodynamic effects of potent opioids can be expected to be more pronounced in ASA III/IV patients, caution should be exercised in the administration of remifentanil in this population. Initial dosage reduction and subsequent titration to effect is therefore recommended.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
REMIFENTANIL FOR INJECTION (remifentanil hydrochloride) produces adverse events that are characteristic of µ-opioids, such as respiratory depression, bradycardia, hypotension, and skeletal muscle rigidity. These adverse events dissipate within minutes of discontinuing or decreasing the infusion rate of remifentanil (see ACTION AND CLINICAL PHARMACOLOGY, WARNINGS AND PRECAUTIONS on the management of these events).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse event information is derived from controlled clinical trials that were conducted in a variety of surgical procedures of varying duration, using a variety of premedications and other anesthetics, and in patient populations with diverse characteristics including underlying disease.
Approximately 2,492 patients were exposed to remifentanil in controlled clinical trials. The frequencies of adverse events during general anesthesia with the recommended doses of REMIFENTANIL FOR INJECTION are given in Table 1.
In the elderly population (> 65 years), the incidence of hypotension is higher, whereas the incidence of nausea and vomiting is lower (see WARNINGS AND PRECAUTIONS).
Data from cardiac risk analysis in non-cardiac general anesthesia studies indicate the incidence of hypotension in patients with cardiac risk factors (i.e., > 65 years of age, concomitant use of cardiac medication) is higher with remifentanil then comparator drugs (27% vs. 12%, respectively).
Table 1: Adverse Events ≥ 1% of Patients in General Anesthesia Studies at the
Recommended Doses of Remifentanil*
| Adverse Event | Induction/Maintenance | After Discontinuation | ||
| Remifentanil (n = 921) | Alfentanil/Fentanyl (n = 466) | Remifentanil (n = 929) | Alfentanil/Fentanyl (n = 466) | |
Nausea Hypotension Vomiting Muscle rigidity Bradycardia Shivering | 8 (<1%) 178 (19%) 4 (<1%) 98 (11%)** 62 (7%) 3 (<1%) | 0 30 (6%) 1 (<1%) 37 (8%) 24 (5%) 0 | 339 (36%) 16 (2%) 150 (16%) 2 (<1%) 11 (1%) 49 (5%) | 202 (43%) 9 (2%) 91 (20%) 1 (<1%) 6 (1%) 10 (2%) |
Fever Dizziness Visual disturbance Headache Respiratory depression Apnea Pruritis Tachycardia Postoperative pain Hypertension Agitation Hypoxia | 1 (<1%) 0 0 0 1 (<1%) 0 2 (<1%) 6 (<1%) 0 10 (1%) 2 (<1%) 0 | 0 0 0 0 0 1 (<1%) 0 7 (2%) 0 7 (2%) 0 0 | 44 (5%) 27 (3%) 24 (3%) 21 (2%) 17 (2%) 2 (<1%) 22 (2%) 10 (1%) 4 (<1%) 12 (1%) 6 (<1%) 10 (1%) | 9 (2%) 9 (2%) 14 (3%) 8 (2%) 20 (4%) 1 (<1%) 7 (2%) 8 (2%) 5 (1%) 8 (2%) 1 (<1%) 7 (2%) |
* Not all doses of remifentanil were equipotent to the comparator opioid. Administration of remifentanil in excess of the recommended dose (i.e., doses >1 and up to 20 µg/kg) resulted in a higher incidence of some adverse events: muscle rigidity (37%), bradycardia (12%), hypertension (4%), and tachycardia (4%).
** Included in the muscle rigidity incidence is chest wall rigidity (5%). The overall muscle rigidity incidence is reduced to <1% when remifentanil is administered concurrently with or after a hypnotic induction agent.
Sedation: Sedation is a common side effect of opioid analgesics, especially in opioid naïve individuals. Sedation may also occur partly because patients often recuperate from prolonged fatigue after the relief of persistent pain. Most patients develop tolerance to the sedative effects of opioids within three to five days and, if the sedation is not severe, will not require any treatment except reassurance. If excessive sedation persists beyond a few days, the dose of the opioid should be reduced and alternate causes investigated. Some of these are: concurrent CNS depressant medication, hepatic or renal dysfunction, brain metastases, hypercalcemia and respiratory failure. If it is necessary to reduce the dose, it can be carefully increased again after three or four days if it is obvious that the pain is not being well controlled. Dizziness and unsteadiness may be caused by postural hypotension, particularly in elderly or debilitated patients, and may be alleviated if the patient lies down.
Nausea and Vomiting: Nausea is a common side effect on initiation of therapy with opioid analgesics and is thought to occur by activation of the chemoreceptor trigger zone, stimulation of the vestibular apparatus and through delayed gastric emptying. The prevalence of nausea declines following continued treatment with opioid analgesics. When instituting therapy with an opioid for chronic pain, the routine prescription of an antiemetic should be considered. In the cancer patient, investigation of nausea should include such causes as constipation, bowel obstruction, uremia, hypercalcemia, hepatomegaly, tumor invasion of celiac plexus and concurrent use of drugs with emetogenic properties. Persistent nausea which does not respond to dosage reduction may be caused by opioid-induced gastric stasis and may be accompanied by other symptoms including anorexia, early satiety, vomiting and abdominal fullness. These symptoms respond to chronic treatment with gastrointestinal prokinetic agents.
Constipation: Practically all patients become constipated while taking opioids on a persistent basis. In some patients, particularly the elderly or bedridden, fecal impaction may result. It is essential to caution the patients in this regard and to institute an appropriate regimen of bowel management at the start of prolonged opioid therapy. Stimulant laxatives, stool softeners, and other appropriate measures should be used as required. As fecal impaction may present as
overflow diarrhea, the presence of constipation should be excluded in patients on opioid therapy prior to initiating treatment for diarrhea.
The following adverse effects occur less frequently with opioid analgesics and include those reported in Remifentanil Hydrochloride clinical trials, whether related or not to remifentanil hydrochloride.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Other adverse events reported less frequently (<1%) include constipation and sedation.
Post-Market Adverse Drug Reactions
Very rarely, allergic reactions including anaphylaxis have been reported in patients receiving remifentanil hydrochloride in conjunction with one or more anesthetic agents.
Cough as an adverse event induced by fentanyl, sufentanil, remifentanil and alfentanil is documented in the literature.
Post-marketing reports describe patients with symptoms suggestive of, or diagnostic of, serotonin syndrome following the concomitant use of remifentanil with a serotonergic drug, such as a Selective Serotonin Reuptake Inhibitor or a Serotonin Norepinephrine Reuptake Inhibitor (see also DRUG INTERACTIONS).
DRUG INTERACTIONS
Overview
Drug-Drug Interactions
Remifentanil clearance is not altered by concomitant administration of thiopental, isoflurane, propofol or temazepam during anesthesia. In vitro studies with atracurium, mivacurium, esmolol, echothiophate, neostigmine, physostigmine and midazolam revealed no inhibition of remifentanil hydrolysis in whole human blood by these drugs. In animals the duration of muscle paralysis from succinylcholine is not prolonged by remifentanil.
Remifentanil is synergistic with other anesthetics and doses of thiopental, propofol, isoflurane and midazolam have been reduced by up to 75% with the co-administration of remifentanil. If doses of concomitantly administered CNS depressant drugs are not reduced, patients may experience an increased incidence of adverse effects associated with these agents.
Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants (e.g. other opioids, sedatives/hypnotics, antidepressants, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, phenothiazines, neuroleptics, antihistamines, antiemetics, and alcohol) and beta-blockers, increases the risk of respiratory depression, profound sedation, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Follow patients closely for signs of respiratory depression and sedation (see WARNINGS AND PRECAUTIONS, Neurologic, Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol) and Psychomotor Impairment). REMIFENTANIL FOR INJECTION should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects.
Serotonergic Drugs
Coadministration of remifentanil with a serotonergic agent, such as a Selective Serotonin Reuptake Inhibitor or a Serotonin Norepinephrine Reuptake Inhibitor, may increase the risk of serotonin syndrome, a potentially life threatening condition. (See also ADVERSE REACTIONS)
Drug-Lifestyle Interactions
The concomitant use of alcohol should be avoided (see WARNINGS AND PRECAUTIONS, General).
DOSAGE AND ADMINISTRATION
Dosing Considerations
Due to insufficient safety and efficacy data, REMIFENTANIL FOR INJECTION (remifentanil hydrochloride) is not recommended for use in spontaneous ventilation anesthesia, in monitored anesthesia care, for continuation as an analgesic in the immediate postoperative period, in neurosurgery, in cardiac surgery, or in pediatric anesthesia.
Remifentanil is not recommended as the sole agent in general anesthesia because loss of consciousness cannot be assured and because of a high incidence of apnea, muscle rigidity, and tachycardia.
Rapid intravenous injection of opioid analgesics increases the possibility of hypotension and respiratory depression.
Recommended Dose and Dosage Adjustment
Remifentanil is synergistic with other anesthetics and doses of thiopental, propofol, isoflurane and midazolam have been reduced by up to 75% with the co-administration of remifentanil. At the recommended doses shown in Table 2, remifentanil significantly reduces the amount of
hypnotic agent required to maintain anesthesia. Therefore isoflurane and propofol should be administered as recommended below to avoid excessive depth of anesthesia.
Intraoperative awareness has been reported in patients under 55 years of age when remifentanil has been administered with propofol infusion rates of ≤ 75 µg/kg/min. Therefore, propofol rates <100 µg/kg/min are not recommended for use with remifentanil for total intravenous anesthesia in patients < 55 years of age.
I.V. bolus administration should only be used in intubated patients during the maintenance of general anesthesia. For induction of anesthesia in nonintubated patients, a single dose of remifentanil, not exceeding 1 µg/kg, may be administered over 30 to 60 seconds.
Reconstituted solutions of remifentanil should be diluted prior to administration (see DOSAGE AND ADMINISTRATION, Reconstitution, Parenteral Products).
The administration of remifentanil must be individualized based on the patient's response. Table 2 summarizes the recommended doses in adult patients, predominately ASA physical status I, II, or III.
Table 2: Dosing Guidelines
| Phase | Continuous i.v. Infusion of Remifentanil Hydrochloride (µg/kg/min) | Infusion Dose Range of Remifentanil Hydrochloride (µg/kg/min) | Supplemental i.v. Bolus Dose of Remifentanil Hydrochloride (µg/kg) |
Induction of Anesthesia (through intubation) | 0.5 - 1† | ||
Maintenance of anesthesia with: Nitrous oxide (66%) Isoflurane (starting dose 0.5 MAC) Propofol (starting dose 100 µg/kg/min) | 0.4 0.25 0.25 | 0.1-2 0.05-2 0.05-2 | 0.5-1 0.5-1 0.5-1 |
† An initial dose of 1 µg/kg may be administered over 30 to 60 seconds.
During Induction of Anesthesia
Remifentanil should be administered at an infusion rate of 0.5 to 1 µg/kg/min with a hypnotic or volatile agent for the induction of anesthesia. If endotracheal intubation is to occur less than 8 minutes after the start of the infusion of remifentanil, then an initial dose of 1 µg/kg may be administered over 30 to 60 seconds.
During Maintenance of Anesthesia
After endotracheal intubation, the infusion rate of remifentanil should be decreased in accordance with the dosing guidelines in Table 2. Due to the fast onset and short duration of action of remifentanil, the rate of administration during anesthesia can be titrated upward in 25% to 100% increments or downward in 25% to 50% decrements every 2 to 5 minutes to attain the
desired level of µ-opioid effect. In response to light anesthesia or transient episodes of intense surgical stress, supplemental bolus doses of 0.5 to 1 µg/kg may be administered every 2 to 5 minutes. At infusion rates >1 µg/kg/min, increases in the concomitant anesthetic agents should be considered to increase the depth of anesthesia.
Guidelines for Discontinuation
Upon discontinuation of remifentanil, the i.v. tubing should be cleared to prevent the inadvertent administration of remifentanil at a later time. Due to the rapid offset of action of remifentanil, no residual analgesic activity will be present within 5 to 10 minutes after discontinuation. However respiratory depression may occur in some patients up to 30 minutes after termination of infusion due to residual effects of concomitant anesthetics. Standard monitoring should be maintained in the postoperative period to ensure adequate recovery without stimulation. For those patients undergoing surgical procedures where postoperative pain is generally anticipated, alternative analgesics should be administered prior to discontinuation of remifentanil. Sufficient time must be allowed to reach the maximum effect of the longer acting analgesic. The choice of analgesic should be appropriate for the patient's surgical procedure and the level of follow-up care.
Use in Elderly Patients
Respiratory depression has occurred in the elderly following administration of large initial doses of opioids to patients who were not opioid-tolerant or when opioids were co-administered with other agents that can depress respiration. Due to the increased sensitivity to the pharmacological effects of remifentanil in this population (> 65 years), the starting doses of remifentanil should be decreased by 50% and then be titrated to individual patient need (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY).
Use in Obese Patients
The starting doses of remifentanil should be based on ideal body weight in obese patients as the clearance and volume of distribution of remifentanil are better correlated with ideal body weight than actual body weight in this population.
Preanesthetic Medication
The need for premedication and the choice of anesthetic agents must be individualized. In clinical studies, patients who received remifentanil frequently received a benzodiazepine premedication.
Individualization of Infusion Rates
Infusion rates of REMIFENTANIL FOR INJECTION can be individualized for each patient using Table 3.
Table 3: Infusion Rates of REMIFENTANIL FOR INJECTION (mL/kg/h)
Drug Delivery Rate (µg/kg/min) | Infusion Delivery Rate (mL/kg/h) | |
| 25 µg/mL | 50 µg/mL | |
| 0.05 0.075 0.1 0.15 0.2 0.25 0.5 0.75 1.0 1.25 1.5 1.75 2.0 | 0.12 0.18 0.24 0.36 0.48 0.6 1.2 1.8 2.4 3.0 3.6 4.2 4.8 | 0.06 0.09 0.12 0.18 0.24 0.3 0.6 0.9 1.2 1.5 1.8 2.1 2.4 |
Table 4 is a guideline for milliliter-per-hour delivery for a solution of 25 µg/mL with an infusion device.
Table 4: Infusion Rates of REMIFENTANIL FOR INJECTION (mL/h) for a 25-
µg/mL Solution
| Infusion Rate (µg/kg/min) | Patient Weight (kg) | |||||||
| 30 | 40 | 50 | 60 | 70 | 80 | 90 | 100 | |
| 0.05 0.075 0.1 0.15 0.2 | 3.6 5.4 7.2 10.8 14.4 | 4.8 7.2 9.6 14.4 19.2 | 6.0 9.0 12.0 18.0 24.0 | 7.2 10.8 14.4 21.6 28.8 | 8.4 12.6 16.8 25.2 33.6 | 9.6 14.4 19.2 28.8 38.4 | 10.8 16.2 21.6 32.4 43.2 | 12.0 18.0 24.0 36.0 48.0 |
Table 5 is a guideline for milliliter-per-hour delivery for a solution of 50 µg/mL with an infusion device.
Table 5: Infusion Rates of REMIFENTANIL FOR INJECTION (mL/h) for a 50-
µg/mL Solution
| Infusion Rate (µg/kg/min) | Patient Weight (kg) | |||||||
| 30 | 40 | 50 | 60 | 70 | 80 | 90 | 100 | |
| 0.05 0.075 0.1 0.15 0.2 0.25 0.5 0.75 1.0 1.25 1.5 1.75 2.0 | 1.8 2.7 3.6 5.4 7.2 9.0 18.0 27.0 36.0 45.0 54.0 63.0 72.0 | 2.4 3.6 4.8 7.2 9.6 12.0 24.0 36.0 48.0 60.0 72.0 84.0 96.0 | 3.0 4.5 6.0 9.0 12.0 15.0 30.0 45.0 60.0 75.0 90.0 105.0 120.0 | 3.6 5.4 7.2 10.8 14.4 18.0 36.0 54.0 72.0 90.0 108.0 126.0 144.0 | 4.2 6.3 8.4 12.6 16.8 21.0 42.0 63.0 84.0 105.0 126.0 147.0 168.0 | 4.8 7.2 9.6 14.4 19.2 24.0 48.0 72.0 96.0 120.0 144.0 168.0 192.0 | 5.4 8.1 10.8 16.2 21.6 27.0 54.0 81.0 108.0 135.0 162.0 189.0 216.0 | 6.0 9.0 12.0 18.0 24.0 30.0 60.0 90.0 120.0 150.0 180.0 210.0 240.0 |
Physical Dependence
Physical dependence with or without psychological dependence tends to occur with chronic administration of opioids, including REMIFENTANIL FOR INJECTION. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. These symptoms may include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning.
Following successful relief of moderate to severe pain, periodic attempts to reduce the opioid dose should be made. Smaller doses or complete discontinuation may become feasible due to a change in the patient’s condition or mental state. Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer required for pain control. In patients who are appropriately treated with opioid analgesics and who undergo gradual withdrawal for the drug, these symptoms are usually mild (see WARNINGS AND PRECAUTIONS). Tapering should be individualised and carried out under medical supervision.
Patient should be informed that reducing and/or discontinuing opioids decreases their tolerance to these drugs. If treatment needs to be re-initiated, the patient must start at the lowest dose and titrate up to avoid overdose.
Opioid analgesics may only be partially effective in relieving dysesthetic pain, postherpetic neuralgia, stabbing pains, activity-related pain and some forms of headache. That is not to say that patients with advanced cancer suffering from some of these forms of pain should not be given an adequate trial of opioid analgesics, but it may be necessary to refer such patients at an early time to other forms of pain therapy.
Administration
Remifentanil should be administered only in a setting fully equipped for the monitoring and support of respiratory and cardiovascular function. Resuscitative and intubation equipment, oxygen and an opioid antagonist must be readily available.
Remifentanil should only be administered by persons specifically trained in the use of anesthetic drugs and the recognition and management of the expected adverse effects of potent opioids, including respiratory and cardiac resuscitation of patients in the age-group being treated. Such training must include the establishment and maintenance of a patent airway and assisted ventilation.
Remifentanil is for i.v. use only and must not be administered by epidural or intrathecal injection. Continuous infusions of remifentanil should be administered only by an infusion device. The injection site should be close to the venous cannula and all i.v. tubing should be cleared at the time of discontinuation of infusion.
Reconstitution:
Parenteral Products:
Preparation for Administration
To reconstitute solution, add 1 mL of diluent per mg of remifentanil. Shake well to dissolve. When reconstituted as directed, the solution contains approximately 1 mg of remifentanil activity per 1 mL. REMIFENTANIL FOR INJECTION should be reconstituted and diluted to a recommended final concentration of 25 or 50 µg/mL prior to administration as indicated in Table 6 and Table 7 below.
REMIFENTANIL FOR INJECTION should not be administered without dilution. REMIFENTANIL FOR INJECTION does not contain any antimicrobial preservatives and thus care must be taken to assure the sterility of prepared solutions.
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration whenever solution and container permit. Product should be a clear, colourless liquid after reconstitution and free of visible particulate matter.
REMIFENTANIL FOR INJECTION can be reconstituted and diluted to concentrations of 20 to 50 µg/mL in any of the following i.v. fluids:
- Sterile Water for Injection, USP
- 5% Dextrose Injection, USP
- 5% Dextrose and 0.9% Sodium Chloride Injection, USP
- 0.9% Sodium Chloride Injection, USP
- 0.45% Sodium Chloride Injection, USP
- Lactated Ringer’s and 5% Dextrose Injection, USP
- Lactated Ringer’s Injection, USP
REMIFENTANIL FOR INJECTION has been shown to be compatible with these i.v. fluids when co-administered into a running i.v. administration set.
Table 6: Reconstitution of REMIFENTANIL FOR INJECTION
Vial Size (mg of remifentanil base) | Volume of Diluent to be Added to Vial | Approximate*Available Volume | Nominal Concentration |
| 1 mg | 1 mL | 1 mL | 1 mg/mL |
| 2 mg | 2 mL | 2 mL | 1 mg/mL |
* Densities for water and reconstituted REMIFENTANIL FOR INJECTION are not significantly different
Table 7: Dilution of REMIFENTANIL FOR INJECTION
Final Concentration | Amount of remifentanil in Each Vial | Volume to be Added to Dilute* | Final Volume after Dilution |
| 25 µg/mL | 1 mg | 39 mL | 40 mL |
| 2 mg | 78 mL | 80 mL | |
| 50 µg/mL | 1 mg 2 mg | 19 mL 38 mL | 20 mL 40 mL |
* note amounts indicated are those to be added after REMIFENTANIL FOR INJECTION has been reconstituted to a 1 mg/mL solution as indicated in Table 6 above.
Compatibility With Other Therapeutic Agents
REMIFENTANIL FOR INJECTION has been shown to be compatible with Propofol Injection when coadministered into a running i.v. administration set. The compatibility of REMIFENTANIL FOR INJECTION with other therapeutic agents has not been evaluated.
Incompatibilities
Nonspecific esterases in blood products may lead to the hydrolysis of remifentanil to its carboxylic acid metabolite. Therefore, administration of REMIFENTANIL FOR INJECTION into the same i.v. tubing with blood/serum/plasma is not recommended.
Note: Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration whenever solution and container permit. Product should be a clear, colourless liquid after reconstitution and free of visible particulate matter.
OVERDOSAGE
As with all potent opioid analgesics, overdosage would be manifested by an extension of the pharmacological actions of REMIFENTANIL FOR INJECTION (remifentanil hydrochloride). Expected signs and symptoms of overdosage include: apnea, chest-wall rigidity, seizures, hypoxemia, hypotension, and bradycardia.
In case of overdosage or suspected overdosage, discontinue administration of remifentanil, maintain a patent airway, initiate assisted or controlled ventilation with oxygen, and maintain adequate cardiovascular function. If depressed respiration is associated with muscle rigidity, a neuromuscular blocking agent or a µ-opioid antagonist may be required to facilitate assisted or controlled respiration. Intravenous fluids and vasopressors for the treatment of hypotension and other supportive measures may be employed. Glycopyrrolate or atropine may be useful for the treatment of bradycardia and/or hypotension.
Intravenous administration of an opioid antagonist such as naloxone may be employed as a specific antidote to manage severe respiratory depression or muscle rigidity. Respiratory depression following overdosage with remifentanil is not expected to last longer than the opioid antagonist, naloxone. Reversal of the opioid effects may lead to acute pain and sympathetic hyperactivity.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
REMIFENTANIL FOR INJECTION (remifentanil hydrochloride) is a µ-opioid agonist with rapid onset and peak effect, and ultra-short duration of action. The µ-opioid activity of remifentanil is antagonized by opioid antagonists such as naloxone.
The analgesic effects of remifentanil are rapid in onset and offset. Its effects and side effects are dose dependent and similar to other µ-opioids. Remifentanil in humans has a rapid blood-brain equilibration half-time of 1 ± 1 minutes (mean ± SD) and a rapid onset of action. The pharmacodynamic effects of remifentanil closely follow the measured blood concentrations, allowing direct correlation between dose, blood levels, and response. Blood concentration decreases 50% in 3 to 6 minutes after a 1-minute infusion or after prolonged continuous infusion due to rapid distribution and elimination processes and is independent of duration of drug administration. Recovery from the effects of remifentanil occurs rapidly (within 5 to 10 minutes). New steady-state concentrations occur within 5 to 10 minutes after changes in infusion rate. When used as a component of an anesthetic technique, remifentanil can be rapidly titrated to the desired depth of anesthesia/analgesia (e.g., as required by varying levels of intraoperative stress) by changing the continuous infusion rate or by administering an i.v. bolus injection.
Pharmacodynamics
Central Nervous System
Remifentanil hydrochloride produces respiratory depression by direct action on brain stem respiratory centres. The respiratory depression involves both a reduction in the responsiveness of the brain stem centres to increases in CO2 tension and to electrical stimulation.
Remifentanil hydrochloride depresses the cough reflex by direct effect on the cough centre in the medulla. Antitussive effects may occur with doses lower than those usually required for analgesia.
Remifentanil hydrochloride causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings). Marked mydriasis rather than miosis may be seen with hypoxia in the setting of oxycodone overdose.
Gastrointestinal Tract and Other Smooth Muscle
Remifentanil hydrochloride causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in gastric, biliary and pancreatic secretions, spasm of the sphincter of Oddi, and transient elevations in serum amylase.
Cardiovascular System
Remifentanil hydrochloride may produce release of histamine with or without associated peripheral vasodilation. Manifestations of histamine release and/or peripheral vasodilatation may include pruritus, flushing, red eyes, hyperhidrosis and/or orthostatic hypotension.
Assays of histamine in patients and normal volunteers have shown no elevation in plasma histamine levels after administration of remifentanil in doses up to 30 μg/kg over 60 seconds.
Endocrine System
Opioids may influence the hypothalamic-pituitary-adrenal or -gonadal axes. Some changes that can be seen include an increase in serum prolactin, and decreases in plasma cortisol and testosterone. Clinical signs and symptoms may be manifest from these hormonal changes.
Immune System
In vitro and animal studies indicate that opioids have a variety of effects on immune functions, depending on the context in which they are used. The clinical significance of these findings is unknown.
Haemodynamics
In premedicated patients undergoing anesthesia, 1-minute infusions of < 2 µg/kg of remifentanil caused dose-dependent hypotension and bradycardia. While additional doses > 2 µg/kg (up to 30 µg/kg) do not produce any further decreases in heart rate or blood pressure, the duration of the hemodynamic change is increased in proportion to the blood concentrations achieved. Peak hemodynamic effects occur within 3 to 5 minutes of a single dose of remifentanil or an infusion rate increase. Glycopyrrolate, atropine, and vagolytic neuromuscular blocking agents attenuate the hemodynamic effects associated with remifentanil. When appropriate, bradycardia and hypotension can be reversed by reduction of the rate of infusion of remifentanil, or the dose of concurrent anesthetics, or by the administration of fluids or vasopressors.
Respiration
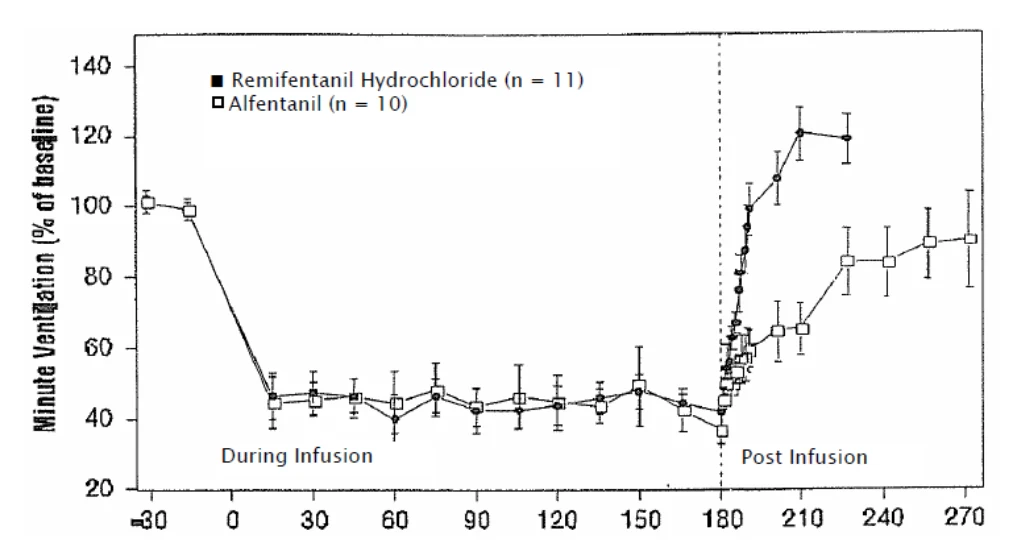
Remifentanil depresses respiration in a dose-related fashion. Unlike other fentanyl analogs, the duration of action of remifentanil at a given dose does not increase with increasing duration of administration, due to lack of drug accumulation. When remifentanil and alfentanil were dosed to equal levels of respiratory depression, recovery of respiratory drive after 3-hour infusions was more rapid and less variable with remifentanil (see Figure 1).
Time (minutes)
Figure 1: Recovery of Respiratory Drive after Equipotent* Doses of Remifentanil and Alfentanil Using CO2-Stimulated Minute Ventilation in Volunteers (±1.5 SEM)
*Equipotent refers to level of respiratory depression.
Spontaneous respiration occurs at blood concentrations of 4 to 5 ng/mL in the absence of other anesthetic agents; for example, after discontinuation of a 0.25-µg/kg/min infusion of remifentanil, these blood concentrations would be reached in 2 to 4 minutes. In patients undergoing general anesthesia, the rate of respiratory recovery depends upon the concurrent anesthetic; N2O < propofol < isoflurane.
Muscle Rigidity
Skeletal muscle rigidity can be caused by remifentanil and is related to the dose and speed of administration. Remifentanil may cause chest wall rigidity (inability to ventilate) after single doses of > 1 µg/kg administered over 30 to 60 seconds or infusion rates > 0.1 µg/kg/min; peripheral muscle rigidity may occur at lower doses. Administration of doses < 1 µg/kg may cause chest wall rigidity when given concurrently with a continuous infusion of remifentanil. Prior or concurrent administration of a hypnotic (propofol or thiopental) or a neuromuscular blocking agent may attenuate the development of muscle rigidity. Excessive muscle rigidity can be treated by decreasing the rate or discontinuing the infusion of remifentanil or by administering a neuromuscular blocking agent.
Anesthesia
Remifentanil is synergistic with the activity of hypnotics (propofol and thiopental), inhaled anesthetics, and benzodiazepines (see WARNINGS AND PRECAUTIONS, and DOSAGE AND ADMINISTRATION).
Gender
No differences have been shown in the pharmacodynamic activity (as measured by the EEG) of remifentanil between men and women.
Pharmacokinetics
Absorption
After i.v. doses administered over 60 seconds, the pharmacokinetics of remifentanil fit a three-compartment model with a rapid distribution half-life of 1 minute, a slower distribution half-life of 6 minutes, and a terminal elimination half-life of 10 to 20 minutes. Since the terminal elimination component contributes less than 10% of the overall area under the concentration versus time curve (AUC), the effective biological half-life of remifentanil is 3 to 10 minutes. This is similar to the 3- to 10-minute half-life measured after termination of prolonged infusions (up to 4 hours; see Figure 2) and correlates with recovery times observed in the clinical setting after infusions up to 12 hours. Concentrations of remifentanil are proportional to the dose administered throughout the recommended dose range. The pharmacokinetics of remifentanil are unaffected by the presence of renal or hepatic impairment.
Distribution
The initial volume of distribution (Vd) of remifentanil is approximately 100 mL/kg and represents distribution throughout the blood and rapidly perfused tissues. Remifentanil subsequently distributes into peripheral tissues with a steady-state volume of distribution of approximately 350 mL/kg. These two distribution volumes generally correlate with total body weight (except in severely obese patients when they correlate better with ideal body weight [IBW]). Remifentanil is approximately 70% bound to plasma proteins of which two-thirds is binding to alpha-1-acid-glycoprotein.
Metabolism
Remifentanil is an esterase-metabolized opioid. A labile ester linkage renders this compound susceptible to hydrolysis by nonspecific esterases in blood and tissues. This hydrolysis results in production of the carboxylic acid metabolite (3-[4-methoxycarbonyl-4-[(1-oxopropyl) phenylamino]-1-piperidine]propanoic acid), and represents the principal metabolic pathway for remifentanil (> 95%). The carboxylic acid metabolite is essentially inactive (1/4 600 as potent as remifentanil in dogs) and is excreted by the kidneys with an elimination half-life of approximately 90 minutes. Remifentanil is not metabolized by plasma cholinesterase (pseudocholinesterase) and is not appreciably metabolized by the liver or lung.
Excretion
The clearance of remifentanil in young, healthy adults is approximately 40 mL/min/kg. Clearance generally correlates with total body weight (except in severely obese patients when it correlates better with ideal body weight). The high clearance of remifentanil combined with a relatively small volume of distribution produces a short elimination half-life of approximately 3 to 10 minutes (see Figure 2). This value is consistent with the time taken for blood or effect site concentrations to fall by 50% (context-sensitive half-times), which is approximately 3 to 6 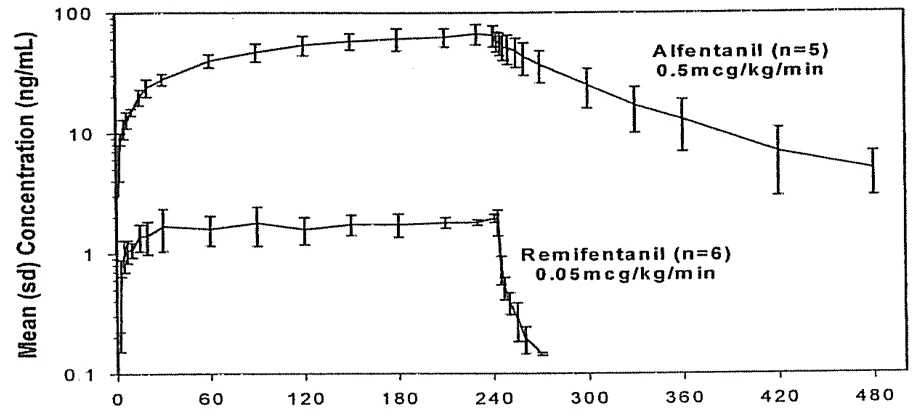
minutes. Unlike other fentanyl analogs, the duration of action does not increase with prolonged administration.
Time (minutes) Figure 2: Mean Concentration (sd) versus Time
Titration to Effect
The rapid elimination of remifentanil permits the titration of infusion rate without concern for prolonged duration. In general, every 0.1-µg/kg/min change in the i.v. infusion rate will lead to a corresponding 2.5-ng/mL change in blood remifentanil concentration within 5 to 10 minutes. In intubated patients only, a more rapid increase (within 3 to 5 minutes) to a new steady state can be achieved with a 1.0-µg/kg bolus dose in conjunction with an infusion rate increase.
STORAGE AND STABILITY
REMIFENTANIL FOR INJECTION should be stored between 15 - 25°C. Reconstituted and diluted solutions of REMIFENTANIL FOR INJECTION (20 to 50 µg/mL) are stable for 24 hours at room temperature for all recommended IV fluids except those containing Lactated Ringer's Solution (stable for 4 hours).
DOSAGE FORMS, COMPOSITION AND PACKAGING
REMIFENTANIL FOR INJECTION (remifentanil hydrochloride) is available as:
1 mg remifentanil base lyophilized powder in cartons of 10.
2 mg remifentanil base lyophilized powder in cartons of 10.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: remifentanil hydrochloride
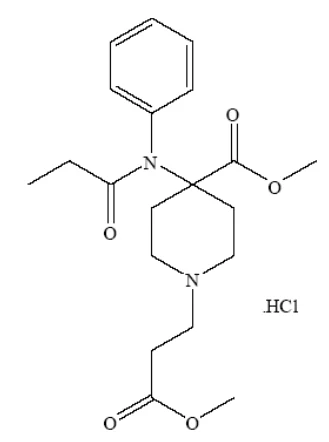
Chemical name: 3-(4-Methoxycarbonyl-4-((1-oxopropyl)phenylamino)-1-piperidine)propanoic acid, methyl ester hydrochloride
Molecular formula: C20H28N2O5.HCl
Molecular mass: 412.9
Structural formula:
Physicochemical properties:
Physical Characteristics: White to off-white crystalline solid
pH and pKa: The pH of a 1 % aqueous solution of remifentanil hydrochloride lies in the range of 4.0 – 6.0.
Remifentanil hydrochloride has a pKa of 7.07. n-octanol:water partition coefficient: 17.9 at pH = 7.3
Melting Point: 205°C (decomposes)
Solubility: Freely soluble in water, sparingly soluble in ethanol, slightly soluble in isopropyl alcohol, very slightly soluble in methyl isobutyl ketone.
Composition: REMIFENTANIL FOR INJECTION (remifentanil hydrochloride)
for injection contains 1 mg or 2 mg of remifentanil base (as the hydrochloride salt) per vial. Non-medicinal ingredients include Glycine 15 mg, Hydrochloric Acid (adjust pH) and/or Sodium Hydroxide (adjust pH).
DETAILED PHARMACOLOGY
Animal Pharmacology
Pharmacodynamics
The antinociceptive properties of remifentanil were determined by rodent tail withdrawal in response to noxious radiant heat and by canine paw withdrawal in response to a noxious pinch. The potency of remifentanil seen was similar to that of alfentanil, fentanyl and sufentanil. Reversal of antinociception by naloxone confirmed that this response was opioid receptor-mediated.
Duration of antinociceptive response following intravenously administered remifentanil was dose-related and was much shorter that of alfentanil, fentanyl, or sufentanil. Remifentanil did not accumulate with repeated or prolonged administration.
Receptor binding studies confirmed remifentanil was selective for the µ-opioid receptor. EC50 values for remifentanil at µ-, δ-, к-opioid receptors were 2.6 nM, 66 nM, and 6.1 µM, respectively. In isolated tissues, remifentanil was a potent µ-opioid agonist, with its actions reversed by the µ-opioid antagonist, naltrexone, but not by the δ- and к-opioid antagonists, ICI-174864 and nor-binaltorphimine, respectively. Therefore, although remifentanil has some affinity for δ- and к-opioid receptors in binding assays, it lacks the intrinsic efficacy to produce significant activation at these receptors.
Secondary effects produced by remifentanil are characteristic for µ-opioid agonists (consisting of dose-related bradycardia and hypotension) but are consistently shorter in duration than for other opioids. These hemodynamic effects may lessen the cardiovascular risk, and may ameliorate increased heart rate and blood pressure seen during the intraoperative stress response to surgery and anesthesia.
Pharmacokinetics
The propanoic acid methyl ester moiety of remifentanil is rapidly hydrolyzed by esterases in the blood and tissues to yield the carboxylic acid of remifentanil (and also the major metabolite). After infusion of remifentanil, the pharmacokinetics in dogs are linear between 0.4 µg/kg/min and the highest rate tested 40 µg/kg/min. The pharmacokinetics of remifentanil in beagle dogs
and the metabolism and excretion of remifentanil in mice, rats, rabbits and dogs are similar to those in humans. Remifentanil does not accumulate upon repeated administration in any of the animal species studied.
Elimination is primarily through urine in all toxicological species as well as humans. The only other identified metabolite (other than the carboxylic acid of remifentanil) found in urine or feces of mice, rats or dogs was the product of N-dealkylation on the piperidine ring. It accounted for less than 2% of the dose in all animal species.
Approximately 16-18% of the total systemic clearance of remifentanil could be accounted for in liver, kidney, blood, muscle, brain and lung. Of these, muscle contributed most to the clearance (5-9%). Liver or kidney contributed only 0-3%. This suggests that hepatic or renal insufficiency in humans should not impact greatly on remifentanil clearance.
Remifentanil was approximately 70% bound to human plasma proteins, mostly to α-1-acid glycoprotein.
TOXICOLOGY
Acute Toxicology
Maximum Non Lethal Doses observed in animals (and corresponding multiples of the clinical dose) seen in acute toxicology studies were:
| Species/Sex | MNLD mg/kg | Clinical Multiplea |
Male mice Female mice Male rat Female rat Male and female dogs | 84 70 5 7.5 80 | 42,000 25,000 2,500 3,750 40,000 |
a Based on the maximum recommended human bolus dose of 2 µg /kg
In all studies, remifentanil produced expected signs of µ-opioid intoxication when administered as large single bolus intravenous doses to non-ventilated mice, rats and dogs. In the rat and mouse studies, no macroscopic or microscopic changes could be attributed to administration of remifentanil. Hypoxia-induced brain microhemorrhages were observed in dogs, but these were not present in dogs killed 14 days after dosing, suggesting reversibility of this effect.
Long-Term Toxicology
Subacute Toxicity Studies
| Species | Route | Dose | Duration of Study | Results |
| Rat | Continuous i.v. Infusion | up to 5 µg/kg/min | 2 weeks | ↓ food consumption and bodyweight gain, ↓ pancreatic acinar cell zymogen granules, ↑ serum glucose. |
| Bolus i.v. | up to 2.5 mg/kg/day | 4 weeks | ↓ absolute and relative epididymus weight | |
| Dog | Continuous i.v. Infusion | up to 0.25 µg/kg/min | 2 weeks | ↓ food consumption and bodyweight gain |
| Bolus i.v. | up to 40 mg/kg/day* | 4 weeks | brain microhemorrhages | |
| Bolus Intrathecal | 100-1600 µg** | 19 days | agitation, pain, ↑ in heart rate and blood pressure, hindlimb dysfunction |
* Dosing was reduced to 1.0 mg/kg/day on day 5 due to severity of clinical signs
** Initial dose which was doubled daily up to 1600 µg after which the maximum tolerated dose (800 µg) was administered daily for 14 days.
The toxicological profile of remifentanil is consistent with that expected from a potent µ-opioid agonist. Clinical signs of opioid intoxication were observed in both rats and dogs. Respiratory depression led to death in some animals. The incidence of clonic convulsions increased with increasing days of dosing in both species in the 4 week bolus studies.
In the 4 week rat bolus study, slightly reduced absolute and relative epididymal weights were observed at 2.5 mg/kg/day and sloughed epithelial cells were noted in epididymal tubules at 0.25, 1.0 and 2.5 mg/kg/day. These observations are not predictive of effects in man, where clinical exposure is brief and at relatively low doses.
Continuous infusion of remifentanil to rats was associated with a reversible increase (up to 54%) in serum glucose. Microscopic findings were limited to a reversible decrease in pancreatic acinar cell zymogen granules in mid and high dose animals.
Microscopic brain hemorrhages were noted in the midbrain areas of dogs receiving 0.03 and 0.05 mg/kg (at least 15 times the maximum recommended human bolus dose of 2 µg/kg). These hemorrhages were reversible, and are thought to be due to hypoxia. Additional studies in ventilated dogs showed that adequate ventilation eliminated the occurrence of microhemorrhages, or reduced their incidence to below that seen in dogs treated with saline alone.
Single and repeat dose comparator studies in non-ventilated dogs with bolus intravenous injections of up to 1 mg/kg alfentanil, resulted in morphologically identical microscopic brain hemorrhages, confirming that this finding was not specific to remifentanil. Intrathecal administration of remifentanil to dogs produced hindlimb dysfunction and increased agitation and pain. Bolus intrathecal doses of the glycine formulation (without remifentanil) resulted in clinical observations of agitation and pain, but no microscopic evidence of tissue damage. These effects are believed to be secondary to the glycine excipient. Because of the better buffering properties of blood, the more rapid dilution, and the low glycine concentration of the Remifentanil hydrochloride formulation, this finding has no clinical relevance for intravenous administration of Remifentanil hydrochloride.
Reproduction and Teratology
There were no adverse effects on the mating performance of male and female rats, as well as on fertility of female rats. The male fertility index (number of pregnancies/number of rats that mated) was reduced, probably due to decreases in testes and epididymal weights and increased
incidences of macroscopic lesions and microscopic changes in these organs. However, these changes were observed only after prolonged exposure to relatively high doses of remifentanil, and are not relevant to its clinical use.
In organogenesis studies in rats and rabbits, remifentanil was not considered to present a developmental hazard to fetuses. Maternal toxicity was considered responsible for the reduced fetal bodyweights in rats, as well as two abortions, increased incidences of resorption, and the increased fetal incidence of the skeletal variation of “greater than 12 full pair of ribs” in rabbits.
Placental and milk transfer studies showed that pups are exposed to remifentanil and/or its metabolites during growth and development.
Carcinogenesis and Mutagenesis
Remifentanil, with or without a rat liver enzyme fraction (S9), was not mutagenic in the 5 strains of Salmonella typhimurium tested by gene mutation assay (Ames test) and did not produce chromosome aberrations in the Chinese hamster ovary cells. Remifentanil was also negative in the in vivo micronucleus test and the liver unscheduled DNA synthesis assay.
Remifentanil was found to be genotoxic in mammalian cells in vitro in the mouse lymphoma assay. Remifentanil concentrations over 4000 times greater than those seen with clinical use (50 ng/mL) were mutagenic only in the presence of metabolic activation.
REFERENCES
These references are intended to support only approved indications in the product monograph and not the non-approved indications even though they may be mentioned in some of the publications listed.
- 1.
Amin HM, Sopchak AM, Esposito BF, Graham CL, Batenhorst RL, Camporesi EM.
Naloxone reversal of depressed ventilatory response to hypoxia during continuous infusion of remifentanil. Anesthesiology 1993; 79(3A):A1203.
- 2.
Dershwitz M, Rosow CE, Michalowski P, Connors PM, Hoke JF, Muir KT, Dienstag JL.
Pharmacokinetics and pharmacodynamics of remifentanil in volunteer subjects with severe liver disease compared with normal subjects. Anesthesiology 1994; 81:A377.
- 3. Egan TD, Lemmens HJM, Fiset P, Hermann DJ, Muir KT, Stanski DR, Shafer SL. The pharmacokinetics of the new short-acting opioid remifentanil (GI87084B) in healthy adult male volunteers. Anesthesiology 1993; 79(5):881-892.
- 4.
Fragan RJ. Implications of the use of remifentanil on patient outcomes. Eur J Anaesth
1995; 12(10): 75-76.
- 5. Glass PSA. Pharmacology of remifentanil. Eur J Anaesth 1995; 12(10):73-74.
- 6.
Hoke JF, Muir KT, Glass PSA, Shlugman D, Rosow CE, Derschwitz M, Michalowski P.
Pharmacokinetics (PK) of remifentanil (R) and its metabolite (GR90291) in subjects with renal disease. Clin Pharmacol Ther 1995; 57(2): PI-55.
- 7.
James MK. Remifentanil and anaesthesia for the future. Exp Opin Invest Drugs 1994;
3(4):331-340.
- 8.
Kapila A, Lang E, Glass P, Sebel P, Shlugman D, Hill A, Wood M, Batenhorst R,
Goodman D. MAC reduction of isoflurane by remifentanil. Anesthesiology 1994; 81(3A):A378.
- 9. Marton JP, Hardman HD, Kamiyama Y, Donn KH., Glass PSA. Analgesic efficacy of single escalating doses of GI87084B administered intravenously to healthy male volunteers. Anesthesiology 1991; 75: A378.
- 10. Minto CF, Schnider THW, Cohane CA, Gambus PH, Lemmens H, Shafer SL. The hemodynamic effects of remifentanil in volunteers over 70 years. Anesthesiology 1994: 81(3A):A11.
- 11.
Monk TG, Batenhorst RL, Folger WH, Kirkham AJT, Lemon DJ, Martin KJ., Venker
DC. A comparison of remifentanil and alfentanil during nitrous-narcotic anaesthesia. Anesth Analg 1994; 78:S293.
- 12.
Robinson C, Castaher J. Remifentanil hydrochloride. Drugs of the future 1994;
19(12):1088-1092.
- 13. Sebel PS, Hoke JF, Westmoreland C, Hug CC, Muir KT, Szlam F. Histamine concentrations and hemodynamic responses after remifentanil. Anesth Analg 1995; 80:990-993.
- 14.
Shlugman D, Dufore S, Dershwitz M, Michalowski P, Hoke J, Muir KT, Dosow C, Glass
PSA. Respiratory effects of remifentanil in subjects with severe renal impairment compared to matched controls. Anesthesiology 1994; 81(3A): A1417.
- 15. Westmoreland CL, Hoke JF, Sebel PS, Hug CC, Muir KT. Pharmacokinetics of remifentanil (GI87084B) and its major metabolite (GI90291) in patients undergoing elective inpatient surgery. Anesthesiology 1993; 79:893-903.
- 16. Patel SS, Spencer CM. Remifentanil. Drugs 1996, 52(3):417-427.
- 17.
Remifentanil Hydrochloride for Injection Product Monograph, SteriMax Inc., Control
No. 215290, Date of Revision: August 17, 2018.