


Product Monograph - Repaglinide
INDICATIONS AND CLINICAL USE
Repaglinide (repaglinide) is indicated:
As an adjunct to diet and exercise to lower the blood glucose in patients with type
2 diabetes mellitus whose hyperglycemia cannot be controlled satisfactorily by diet and exercise alone.
- In combination therapy with metformin to lower blood glucose in patients whose hyperglycemia cannot be controlled by diet and exercise plus metformin monotherapy.
- In combination with rosiglitazone in patients who show intolerance to metformin or for whom metformin is contraindicated, when diet and exercise plus rosiglitazone or Repaglinide monotherapy do not result in adequate glycemic control.
Geriatrics (> 65 years of age): Special care and monitoring is recommended in elderly patients between 65 and 75 years of age with renal, hepatic or other medical problems (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Repaglinide is not recommended for use in elderly patients above 75 years of age due to lack of data on safety and/or efficacy (see WARNINGS AND PRECAUTIONS, Special Populations).
Pediatrics (< 18 years of age): Safety and effectiveness of repaglinide has not been established in patients under 18 years of age. Use of Repaglinide is not recommended in pediatric patients (see WARNINGS AND PRECAUTIONS, Special Populations).
CONTRAINDICATIONS
Repaglinide is contraindicated in patients:
- with known hypersensitivity to the drug or any of its components. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
- with diabetic ketoacidosis, with or without coma.
- with Type 1 diabetes.
- with severe liver disease.
- who are using gemfibrozil (see ADVERSE REACTIONS and DRUG INTERACTIONS).
- who are using clopidogrel (see DRUG INTERACTIONS).
WARNINGS AND PRECAUTIONS
General
Repaglinide is effective as a prandial glucose regulator and should be taken before meals (2, 3 or 4 times a day preprandially). Therefore, if a meal is missed or delayed, the dose of repaglinide should be skipped or delayed as appropriate.
Carcinogenesis and Mutagenesis
See TOXICOLOGY.
Cardiovascular
The administration of insulin secretagogues in general has been reported to be associated with increased cardiovascular (CV) mortality as compared to treatment with diet alone or diet plus insulin. In controlled clinical trials comparing repaglinide with glyburide and other sulfonylureas, there was no excess mortality with repaglinide use. The overall incidence of serious CV events including death was 4.2 per 100 patient years. In clinical trials, the incidence of serious cardiovascular treatment emergent adverse events was higher for repaglinide than for glyburide but lower than that for glipizide (see ADVERSE REACTIONS and CLINICAL TRIALS).
Endocrine and Metabolism
Hypoglycemia: Repaglinide is capable of inducing hypoglycemia. Proper patient selection, dosage, and instructions to the patient are important to avoid hypoglycemic episodes.
Hepatic insufficiency may cause elevated repaglinide levels in the blood and may also diminish gluconeogenic capacity, both of which increase the risk of serious hypoglycemic reactions (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic). Repaglinide is contraindicated in patients with severe liver disease (see CONTRAINDICATIONS).
Elderly, debilitated or malnourished patients and those with adrenal, pituitary or hepatic insufficiency are particularly susceptible to the hypoglycemic action of glucose-lowering drugs.
Hypoglycemia may be difficult to recognize in the elderly, and in people who are taking beta-adrenergic blocking drugs.
Hypoglycemia is more likely to occur when caloric intake is deficient or when meals are skipped. Given the preprandial dosing regimen, patients taking repaglinide can adjust dosing according to their changing meal patterns, thereby reducing the risk of hypoglycemia when meals are missed (see DOSAGE AND ADMINISTRATION).
Hypoglycemia is also more likely to occur after strenuous or prolonged exercise, when alcohol is ingested, or when more than one glucose-lowering drug is used.
Loss of control of blood glucose: When a patient, stabilized on repaglinide is exposed to stress such as fever, trauma, infection, or surgery, a loss of control of blood glucose may occur. At such times, it may be necessary to temporarily discontinue repaglinide and administer insulin.
Hepatic/Biliary/Pancreatic
Patients with impaired liver function may be exposed to higher concentrations of repaglinide than would patients with normal liver functions receiving usual doses. Repaglinide should be used cautiously in patients with impaired liver function. Longer intervals between dose adjustments should be utilized to allow full assessment of response (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism and Monitoring and Laboratory Tests, ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions). Repaglinide is contraindicated in patients with severe liver disease (see CONTRAINDICATIONS).
Neurologic
Severe hypoglycemic reactions with coma, seizure, or other neurological impairment occur infrequently, but constitute medical emergencies requiring immediate hospitalization. If hypoglycemic coma is diagnosed or suspected, the patient should be given a rapid intravenous injection of glucose solution, followed by a continuous infusion, according to standard medical practice.
Renal
Renal Insufficiency
Typically, repaglinide does not require initial dose adjustment in patients with reduced kidney function. However, subsequent increases in repaglinide should be made carefully in patients with type 2 diabetes who have renal function impairment or renal failure requiring hemodialysis (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Pre-operative considerations
See WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Loss of control of blood glucose.
Special Populations
Pregnant Women: Repaglinide is not recommended for use during pregnancy. The safety of repaglinide in pregnant women has not been established (see TOXICOLOGY).
Nursing Women: The safety of repaglinide in nursing women has not been established. In rat reproduction studies, measurable levels of repaglinide were detected in the breast milk of the dams and lowered blood glucose levels were observed in the pups. It is not known whether repaglinide is excreted in human milk. Repaglinide is not recommended in nursing women because the potential for hypoglycemia in nursing infants may exist (see TOXICOLOGY).
Pediatrics (< 18 years of age): The use of repaglinide is not recommended in pediatric patients. The safety and effectiveness in pediatrics has not been established. No studies of repaglinide have been performed in pediatric patients.
Geriatrics (>65 years of age): No special dose titration is necessary in elderly patients. In repaglinide clinical studies of 24 weeks or greater duration, 415 patients were over 65 years of age. In one-year, active-controlled trials, no differences were seen in effectiveness or adverse events between these subjects and those less than 65 other than the expected age-related increase in cardiovascular events observed for repaglinide and comparator drugs. There was no increase in frequency or severity of hypoglycemia in older subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals to repaglinide therapy cannot be ruled out, in particular in those with renal, hepatic and other problems (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY).
No specific clinical studies have been conducted in type 2 patients >75 years of age.
Hepatic Impairment: Repaglinide should be used cautiously in patients with impaired liver function. Repaglinide is contraindicated in patients with severe liver disease (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Renal Impairment: Dosage adjustment should be made cautiously in patients with type
2 diabetes mellitus who have renal function impairment or renal failure requiring hemodialysis (see WARNINGS AND PRECAUTIONS, Renal and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Monitoring and Laboratory Tests
In addition to self –monitoring of blood and/or urinary glucose, the patient’s blood glucose should be monitored by the physician to determine the minimum effective dose for the patient. Periodic monitoring is necessary to detect primary failure (inadequate lowering of blood glucose at the maximum recommended dose of medication), and to detect secondary failure (loss of adequate blood glucose-lowering after an initial period of effectiveness).
For patients with an increased risk of hypoglycemia, or at risk of losing blood glucose control, a closer glucose monitoring should be considered (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism). Glycosylated hemoglobin levels (HbA1C) are of value in monitoring the patient’s longer term response to therapy.
Hepatic function should be assessed before initiating the therapy and periodically in patients with impaired hepatic function (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most frequently reported Adverse Drug Reaction (ADR) is hypoglycemia. The occurrence of such reactions depends, as for every diabetes therapy, on individual factors, such as dietary habits, dosage, exercise and stress.
In one-year comparator trials, the incidence of individual events was not greater than 1% except for chest pain (1.8%) and angina (1.8%). The overall incidence of other cardiovascular events (hypertension, abnormal EKG, myocardial infarction, arrhythmias, and palpitations) was ≤ 1% and not different for repaglinide and the comparator drugs.
The incidence of serious cardiovascular adverse events added together, including ischemia, was slightly higher for repaglinide (4%) than for sulfonylurea drugs (3%) in controlled comparator clinical trials. In 1-year controlled trials, repaglinide treatment was not associated with excess mortality rates compared to rates observed with other oral hypoglycemic agent therapies.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Repaglinide has been administered to 2931 individuals worldwide during clinical trials. Approximately 1500 of these individuals with type 2 diabetes have been treated for at least 3 months, 1000 for at least 6 months, and 800 for at least 1 year. The majority of these individuals (1228) received repaglinide in one of five 1-year, active-controlled trials, where repaglinide was administered three times a day with meals in doses of 0.5-4 mg per meal. The comparator drugs in these 1-year trials were oral sulfonylurea drugs (SU).
Repaglinide was well-tolerated in these clinical trials and analysis of adverse events shows no dose relationship to rate of occurrence. The adverse event profile for the repaglinide and SU groups in these trials was generally comparable over one year. The rate of withdrawals due to adverse events was 13% among repaglinide treated patients and 14% among SU- treated patients. The most common adverse events leading to withdrawal were hyperglycemia, hypoglycemia, and related symptoms. Mild or moderate hypoglycemia occurred in 16% of repaglinide patients and 20% of sulfonylurea patients.
The table below lists common clinical trial adverse drug reactions for repaglinide patients compared to both placebo (in trials less than 6 months duration) and to glyburide, gliclazide and glipizide in one year trials. The clinical trial adverse drug reactions profile of repaglinide was generally comparable to that for SU.
Table 2 – Treatment-Emergent Adverse Events with Possible or Probable Relationship - Reported at a
Frequency of ≥ 1% with Repaglinide
| EVENT | REPAGLINIDE n = 1228 | SU n = 597 | REPAGLINIDE n = 352 | PLACEBO n = 108 |
|---|---|---|---|---|
| Active controlled studies | Placebo controlled studies | |||
| n (%) | n (%) | n (%) | n (%) | |
| Eye disorders | ||||
| Vision abnormal | 5 (<1.0) | 2 (<1.0) | 7 (2.0) | 1 (<1.0) |
| General disorders | ||||
| Fatigue | 21 (1.7) | 4 (<1.0) | 9 (2.6) | 3 (2.8) |
| Gastrointestinal disorders | ||||
| Diarrhea | 11 (<1.0) | 7 (1.2) | 6 (1.7) | -* |
| Constipation | 7 (<1.0) | 6 (1.0) | 4 (1.1) | -* |
| Abdominal pain | 12 (1.0) | 6 (1.0) | 4 (1.1) | 1 (<1.0) |
| Flatulence | 7 (<1.0) | 2 (<1.0) | 4 (1.1) | -* |
| Nausea | 12 (1.0) | 7 (1.2) | 4 (1.1) | 2 (1.9) |
| Dyspepsia | 13 (1.1) | 5 (<1.0) | -* | -* |
| Nervous system disorders | ||||
| Headache | 28 (2.3) | 12 (2.0) | 9 (2.6) | 1 (<1.0) |
| Dizziness | 16 (1.3) | 9 (1.5) | 8 (2.3) | 3 (2.8) |
| Tremor | 14 (1.1) | 6 (1.0) | 1 (<1.0) | -* |
| Metabolism and nutrition disorders | ||||
| Hypoglycemia | 179 (14.6) | 102 (17.1) | 24 (6.8) | 2 (1.9) |
| Hyperglycaemia | 35 (2.9) | 18 (3.0) | 4 (1.1) | 5 (4.6) |
| Skin and subcutaneous tissue disorders | ||||
| Sweating increased | 13 (1.1) | 4 (<1.0) | -* | -* |
* No events observed
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Cardiovascular disorders: In one-year comparator trials, the incidence of individual cardiovascular events considered possibly or probably related to trial drug was less than 1%.
The incidence of all observed serious cardiovascular adverse events (i.e. including events not considered possibly or probably related to trial drug) added together, including ischemia, was slightly higher for repaglinide (4%) than for sulfonylurea drugs (3%) in controlled comparator clinical trials. In 1-year controlled trials, repaglinide treatment was not associated with excess mortality rates compared to rates observed with other oral hypoglycemic agent therapies.
Table 3 – Summary of Serious Cardiovascular Events (% of total patients with events)
| Repaglinide | SU* | |
| Total Exposed | 1228 | 498 |
| Serious CV Events | 4% | 3% |
| Cardiac Ischemic Events | 2% | 2% |
| Deaths due to CV Events | 0.5% | 0.4% |
*glyburide and glipizide
Eye disorders: Very rare visual disturbance
Such disturbances have only been reported in very few cases, after initiation of repaglinide treatment. No such cases have led to discontinuation of repaglinide treatment in clinical trials.
Gastrointestinal disorders: Vomiting
Hepatobiliary disorders: Severe hepatic dysfunction
In very rare cases, severe hepatic dysfunction has been reported. However, other causes were implicated in these cases and causal relationship with repaglinide has not been established.
Immune system disorders: Allergy
Generalized hypersensitivity reactions or immunological reactions such as vasculitis may occur very rarely.
Skin and subcutaneous tissue disorders: Hypersensitivity reactions of skin may occur as erythema, itching, rashes and urticaria.
Abnormal Hematologic and Clinical Chemistry Findings: Less common adverse clinical and laboratory events observed in clinical trials, including events not considered possibly or probably related to trial drug included elevated liver enzymes, bilirubinaemia, thrombocytopenia and leukopenia.
Isolated cases of increased liver enzymes have been reported during treatment with repaglinide. Most cases were mild and transient, and very few patients discontinued treatment due to an increase in liver enzymes.
Post-Market Adverse Drug Reactions
Eye disorders: visual disturbance
Gastrointestinal disorders: abdominal pain, diarrhea, vomiting, constipation, nausea
Hepatobiliary disorders: hepatic function abnormal, hepatic enzymes increased
Immune system disorders: allergy, anaphylactic reactions have been observed in very few cases
Metabolism and nutrition disorders: hypoglycemia, hypoglycemic coma, hypoglycemic unconsciousness
Serious hypoglycemic events have been reported in patients co-administered repaglinide and gemfibrozil. Concomitant use of repaglinide and gemfibrozil is contraindicated (see CONTRAINDICATIONS and DRUG INTERACTIONS).
Skin and subcutaneous disorders: hypersensitivity (erythema, itching, rash, urticaria)
DRUG INTERACTIONS
Serious Drug Interactions
Overview
Drug interaction studies performed in healthy volunteers show that repaglinide had no clinically relevant effect on the pharmacokinetic properties of digoxin, theophylline, or warfarin at steady state. Dosage adjustment of these compounds when co-administered with repaglinide is therefore not necessary. Co-administration of cimetidine, nifedipine, estrogen, or simvastatin with repaglinide did not significantly alter the absorption and disposition of repaglinide.
Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
The concomitant use of gemfibrozil and repaglinide is contraindicated (see CONTRAINDICATIONS and DRUG INTERACTIONS, Drug-Drug Interactions).
The concomitant use of clopidogrel and repaglinide is contraindicated (see CONTRAINDICATIONS and DRUG INTERACTIONS, Drug-Drug Interactions).
The drugs were studied in healthy volunteers with co-administration of repaglinide.
Table 4: Established or Potential Drug-Drug Interactions
| Drug Class | Ref | Effect | Clinical Comment |
|---|---|---|---|
| Clopidogrel | CT | 300 mg clopidogrel ↑ AUC by 5.1-fold ↑ Cmax by 2.5-fold 75 mg clopidogrel ↑ AUC by 3.9-fold ↑ Cmax by 2.0-fold |
| Co-administration of clopidogrel (a CYP2C8 inhibitor; 300 mg on day 1 followed by 75 mg daily for two consecutive days) and repaglinide (single dose of 0.25 mg on day 1 and day 3), in healthy volunteers, increased repaglinide systemic exposure (AUC0-∞) by 5.1-fold and 3.9-fold, and Cmax by 2.5-fold and 2.0-fold, respectively. The elimination half-life of repaglinide also increased from 1.6 hours to 2.3 hours (300 mg clopidogrel) and to 2.0 hours (75 mg clopidogrel), along with a significant decrease in blood glucose levels. In CYP2C8*1/*4 polymorphic individuals, repaglinide AUC0-∞ increased up to 8.8-fold and 7.4-fold, on co-administration, respectively. The concomitant use of repaglinide and clopidogrel is contraindicated (see CONTRAINDICATIONS). |
| Gemfibrozil | CT | ↑ AUC by 8.1 fold ↑ Cmax by 2.4 fold | Co-administration of gemfibrozil (600 mg), an inhibitor of CYP2C8 and OATP1B1, and a single dose of 0.25 mg repaglinide (after 3 days of twice-daily 600 mg gemfibrozil) resulted in an 8.1 fold higher repaglinide AUC and prolonged repaglinide half-life from 1.3 to 3.7 hr. The concomitant use of gemfibrozil and repaglinide is contraindicated (see CONTRAINDICATIONS). |
| Gemfibrozil and itraconazole | CT | ↑ AUC by 19 fold | Co-administration of both gemfibrozil and itraconazole with repaglinide, resulted in a 19-fold higher repaglinide AUC and prolonged repaglinide half-life from 1.3 to 6.1 hr. Plasma repaglinide concentration at 7 h increased 28.6-fold with gemfibrozil co-administration and 70.4 fold with the gemfibrozil-itraconazole combination. Concomitant use of gemfibrozil and repaglinide is contraindicated (see CONTRAINDICATIONS). |
| ACE inhibitors | T | May potentiate the hypoglycemic effect of repaglinide. | The patient should be observed for hypoglycemia. |
| Anabolic steroids |
| T | May potentiate the hypoglycemic effect of repaglinide. | The patient should be observed for hypoglycemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. | |
| Drug Class | Ref | Effect | Clinical Comment |
|---|---|---|---|
| Beta-blockers | T | May potentiate the hypoglycemic effect of repaglinide. Beta-blockers may also mask the symptoms of hypoglycemia. | The patient should be observed for hypoglycemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Clarithro- mycin | CT | ↑ AUC by 1.4 fold ↑ Cmax by 1.7 fold | Co-administration of 250 mg clarithromycin, a potent CYP3A4 inhibitor, and a single dose of 0.25 mg repaglinide (after 4 days of twice daily clarithromycin 250 mg resulted in a 40% and 67% increase in repaglinide AUC and Cmax, respectively. The increase in repaglinide AUC was from 5.3 ng/mL*hr to 7.5 ng/mL*hr and the increase in Cmax was from 4.4 ng/mL to 7.3 ng/mL. |
| Cortico-steroids | T | May reduce the hypoglycemic effect of repaglinide and potentiate hyperglycemia. | The patient should be observed for hyperglycemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Cyclosporine | CT | ↑ AUC by 2.5 fold ↑ Cmax by 1.8 fold | Co-administration of cyclosporine, an inhibitor of CYP3A4 and strong OATP1B1 inhibitor, caused an increase in repaglinide (0.25 mg) mean peak plasma concentrations of 175% and the total area under the plasma concentration-time curve was 244% of that in the placebo phase. |
| Danazol | T | May reduce the hypoglycemic effect of repaglinide and potentiate hyperglycemia. | The patient should be observed for hyperglycaemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Deferasirox | CT | ↑ AUC by 2.3 fold ↑ Cmax by 0.62 fold | Co-administration in healthy volunteers of deferasirox (30 mg/kg/day for 4 days) and repaglinide (single dose of 0.5 mg) resulted in an increase in repaglinide systemic exposure (AUC) to 2.3-fold of control and an increase in Cmax of 62%, and a small, significant decrease in blood glucose values. If repaglinide and deferasirox are used concomitantly, decreasing the dose of repaglinide should be considered and patient blood glucose levels carefully monitored. |
| Itraconazole | CT | ↑ AUC by 1.4 fold |
| Co-administration of itraconazole, a CYP3A4 inhibitor, and a single dose of 0.25 mg repaglinide (on the third day of a regimen of 200 mg initial dose, twice-daily 100 mg itraconazole) resulted in a 1.4-fold higher repaglinide AUC. |
| Drug Class | Ref | Effect | Clinical Comment |
|---|---|---|---|
| Ketoconazole | CT | ↑ AUC by 1.2 fold ↑ Cmax by 1.2 fold | Co-administration of 200 mg ketoconazole, a potent and competitive inhibitor of CYP3A4, and a single dose of 2 mg repaglinide in healthy subjects (after 4 days of once daily ketoconazole 200 mg) resulted in a 15% and 16% increase in repaglinide. The increases were from 20.2 ng/mL to 23.5 ng/mL for Cmax and from 38.9 ng/mL*hr to 44.9 ng/mL*hr for AUC. |
| Monoamine Oxidase inhibitors (MAOI) | T | May potentiate the hypoglycemic effect of repaglinide | The patient should be observed for hypoglycemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Octreotide | T | May potentiate the hypoglycemic effect of repaglinide | The patient should be observed for hypoglycemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Oral contraceptives (ethinyl estradiol/levo-norgestrel) | CT | A pharmacokinetic clinical trial in healthy volunteers demonstrated that concomitant oral contraceptive administration (ethinyl estradiol/levonorgestrel) did not alter repaglinide’s total bioavailability to a clinically relevant degree, although peak levels of repaglinide occurred earlier. Repaglinide had no clinically meaningful effect upon bioavailability of levonorgestrel but effects on ethinyl estradiol bioavailability cannot be excluded. | |
| Other antidiabetic agents | T | May potentiate the hypoglycemic effect of repaglinide | The patient should be observed for hypoglycemia. |
| Phenytoin, carbamaze-pine and phenobarbital | T | May reduce the hypoglycemic effect of repaglinide and potentiate hyperglycemia. | The patient should be observed for hyperglycaemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Drug Class | Ref | Effect | Clinical Comment |
| Rifampicin | CT | Co-administration: ↓ AUC by 32% - 48% ↓ Cmax by 26% - 17% Monoadministration of repaglinide after 7 days of rifampicin: ↓ AUC by 80% ↓ Cmax by 79% | Co-administration of 600 mg rifampicin and a single dose of 4 mg repaglinide (after 6 days of once daily rifampicin 600 mg) resulted in a 32% and 26% decrease in repaglinide AUC and Cmax respectively. The decreases were from 40.4 ng/mL to 29.7 ng/mL for Cmax and from 56.8 ng/mL*hr to 38.7 ng/mL*hr for AUC. In another study co-administration of 600 mg rifampicin and a single dose of 4 mg repaglinide (after 6 days of once daily rifampicin 600 mg) resulted in a 48% and 17% decrease in repaglinide AUC and Cmax respectively. The decreases were from 54 ng/mL*hr to 28 ng/mL*hr for AUC and from 35 ng/mL to 29 ng/mL for Cmax . Repaglinide administered by itself (after 7 days of once daily rifampicin 600 mg) resulted in an 80% and 79% decrease in repaglinide AUC and Cmax respectively. The decreases were from 54 ng/mL*hr to 11 ng/mL*hr for AUC and from 35 ng/mL to 7.5 ng/mL for Cmax. |
| Salicylates e.g. aspirin and non-steroidal anti-inflammatory agents (NSAIDs) | T | May potentiate the hypoglycemic effect of repaglinide. | The patient should be observed for hypoglycemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Sympatho-mimetics | T | May reduce the hypoglycemic effect of repaglinide and potentiate hyperglycemia. | The patient should be observed for hyperglycaemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Thiazides | T | May reduce the hypoglycemic effect of repaglinide and potentiate hyperglycemia. | The patient should be observed for hyperglycaemia. When these drugs are either administered or withdrawn from a patient receiving repaglinide, the patient should be observed for loss of glycemic control. |
| Thyroid hormones | T | May reduce the hypoglycemic effect of repaglinide and potentiate hyperglycemia. | The patient should be observed for hyperglycaemia. |
| Trimetho- prim | CT | ↑ AUC by 1.6 fold ↑ Cmax by 1.4 fold | Co-administration of trimethoprim, 160 mg and a single dose of 0.25 mg repaglinide (after 2 days of twice daily and one dose on the third day of trimethoprim 160 mg) resulted in a 61% and 41% increase in repaglinide AUC and Cmax , respectively. The increase in AUC was from 5.9 ng/mL*hr to 9.6 ng/mL*hr and the increase in Cmax was from 4.7 ng/mL to 6.6 ng/mL. The concomitant use of trimethoprim with repaglinide should be avoided. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Drug-Food Interactions
Grapefruit may increase the plasma concentration of repaglinide. In a study with healthy volunteers where grapefruit juice was consumed 2 hours prior to repaglinide intake, a 13% increase in AUC was observed. No other interactions with food have been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
Alcohol may enhance and/or prolong the hypoglycemic effect of repaglinide.
The patient’s ability to concentrate and react may be impaired as a result of hypoglycemia. This may constitute a risk in situations where these abilities are of special importance (e.g. driving a car or operating machinery).
Patients should be advised to take precautions to avoid hypoglycemia while driving. This is particularly important in those who have reduced or absent awareness of the warning signs of hypoglycemia or have frequent episodes of hypoglycemia. The advisability of driving should be considered in these circumstances.
DOSAGE AND ADMINISTRATION
Dosing Considerations
There is no fixed dosage regimen for the management of type 2 diabetes with Repaglinide.
Repaglinide doses are usually taken 15 minutes before the meal but time may vary from immediately before the meal to as long as 30 minutes before the meal. Patients who skip a meal (or add an extra meal) should be instructed to skip (or add) a dose for that meal.
Short-term administration of Repaglinide may be sufficient during periods of transient loss of control in patients usually controlled by their diet.
Recommended Dose and Dosage Adjustment
Initiation Dose
For patients not previously treated with antidiabetic agents or whose HbA1c < 8%, the starting dose should be 0.5 mg with each meal preprandially.
For patients previously treated with blood glucose-lowering drugs or whose HbA1c is ≥ 8%, the initial dose is 1 or 2 mg with each meal preprandially.
Transfer from other therapies
When Repaglinide is used to replace therapy with other oral hypoglycemic agents, Repaglinide may be started on the day after the final dose is given. Patients should then be observed carefully for hypoglycemia due to potential overlapping of drug effects. When transferred from longer half-life sulfonylurea agents (e.g., chlorpropamide) to Repaglinide close monitoring may be indicated for up to one week or longer.
Titration
Dosing adjustments should be determined by blood glucose response, usually fasting blood glucose. The preprandial dose should be doubled up to 4 mg until satisfactory blood glucose response is achieved. A minimum of one week should elapse between titration steps to assess response after each dose adjustment.
Maintenance
The recommended dose range is 0.5 mg to 4.0 mg taken with meals. Repaglinide offers flexible dietary options and may be dosed preprandially 2, 3 or 4 times a day in response to changes in the patient’s meal pattern. The recommended maximum daily dose is 16 mg.
Long-term efficacy should be monitored by measurement of HbA1C levels every 3 months.
Failure to follow an appropriate dosage regimen may precipitate hypoglycemia or hyperglycemia. Patients who do not adhere to their prescribed dietary and drug regimen are more prone to exhibit unsatisfactory response to therapy, including hypoglycemia.
For patients maintained in tight glucose control, Repaglinide treatment has less associated risk of hypoglycemia when meals are missed than does treatment with agents with a longer half-life.
Combination Therapy
If Repaglinide monotherapy does not result in adequate glycemic control, metformin may be added. Or, if metformin or rosiglitazone monotherapy does not provide adequate control, Repaglinide may be added. The starting dose and dose adjustments for Repaglinide combination therapy is the same as for Repaglinide monotherapy. The dose of each drug should be carefully adjusted to determine the minimal dose required to achieve the desired pharmacologic effect. Failure to do so could result in an increase in the incidence of hypoglycemic episodes. Appropriate monitoring of FPG and HbA1C measurements should be used to ensure that the patient is not subjected to excessive drug exposure or increased probability of secondary drug failure.
Missed Dose
If a dose is missed the next dose should be taken as usual. The dose should not be doubled.
OVERDOSAGE
In a clinical trial, patients received increasing doses of repaglinide up to 80 mg a day for 14 days. There were few adverse effects other than those associated with the intended pharmacodynamic effect of lowering blood glucose. Hypoglycemia did not occur when meals were given with these high doses.
Hypoglycemic symptoms without loss of consciousness or neurologic findings should be treated aggressively with oral glucose and adjustments in drug dosage and/or meal patterns. Close monitoring should continue until the physician is assured that the patient is out of danger. Patients should be closely monitored for a minimum of 24 to 48 hours, since hypoglycemia may recur after apparent clinical recovery. There is no evidence that repaglinide is dialyzable using hemodialysis.
For management of a suspected drug overdose, contact your regional Poison Control Centre immediately.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Repaglinide is an oral blood glucose-lowering drug used in the management of type 2 diabetes mellitus. Repaglinide is a short-acting insulin secretagogue which lowers blood glucose levels (as measured by HbA1C and fasting plasma glucose) and is effective in regulating meal-related (prandial) glucose loads. Repaglinide lowers blood glucose levels by stimulating the release of insulin from the pancreas. This action is dependent upon functioning beta cells in the pancreatic islets. Insulin release is glucose-dependent and diminishes at low glucose concentrations.
Repaglinide is chemically unrelated to oral sulfonylurea insulin secretagogues used in the treatment of type 2 diabetes.
Repaglinide closes ATP-dependent potassium channels in the β-cell membrane by binding at characterizable sites. This potassium channel blockade depolarizes the β-cell which leads to an opening of calcium channels. The resulting increased calcium influx induces insulin secretion. The ion channel mechanism is highly tissue selective with low affinity for heart and skeletal muscle.
Pharmacokinetics
Absorption: After oral administration, repaglinide is rapidly and completely absorbed from the gastrointestinal tract. After single and multiple oral doses in healthy subjects or in patients, peak drug levels (Cmax) occur within 1 hour (Tmax). Repaglinide is rapidly eliminated from the blood stream with a half-life of approximately 1 hour. The mean absolute bioavailability is 56%. When repaglinide was given with food, the mean Tmax was not changed, but the mean Cmax and AUC (area under the plasma concentration-time curve) were decreased 20% and 12.4%, respectively.
Distribution: After intravenous (IV) dosing in healthy subjects, the volume of distribution at steady state (VSS) was approximately 31 L, and the total body clearance (CL) was 38 L/h. Protein binding and binding to human serum albumin was greater than 98%.
Metabolism: Repaglinide is completely metabolized by oxidative biotransformation and direct conjugation with glucuronic acid after either an IV or oral dose. The major metabolites are an oxidized dicarboxylic acid (M2), the aromatic amine (M1) and the acyl glucuronide (M7). The cytochrome P-450 enzyme system, specifically 2C8 and 3A4 has been shown to be involved in the N-dealkylation of repaglinide to M2 and the further oxidation to M1. Metabolites do not contribute to the glucose-lowering effect of repaglinide.
Excretion: Within 96 hours after dosing with 14C-repaglinide as a single oral dose, approximately 90% of the radiolabel was recovered in the feces and 8% in the urine. Only 0.1% of the dose is cleared in the urine as parent compound. The major metabolite (M2) accounted for 60% of the administered dose. Less than 2% of parent drug was recovered in feces.
Pharmacokinetic parameters: Data indicate that repaglinide did not accumulate in serum. Repaglinide demonstrated pharmacokinetic linearity over the 0.5 - 4 mg dose range.
The pharmacokinetic parameters of repaglinide obtained from a single-dose, crossover study in healthy subjects and from a multiple- dose, parallel, dose-proportionality (0.5, 1, 2 and 4 mg) study in patients with Type 2 diabetes are summarized below:
Table 5 – Pharmacokinetic parameters of repaglinide
| PARAMETER | PATIENTS WITH Type 2 diabetesa |
|---|---|
AUC0-24 hr (ng/mLxh): 0.5 mg 1.0 mg 2.0 mg 4.0 mg | Mean (SD): 68.9 (154.4) 125.8 (129.8) 152.4 (89.6) 447.4 (211.3) |
Cmax0-5 hr (ng/mL): 0.5 mg 1.0 mg 2.0 mg 4.0 mg | Mean (SD): 9.8 (10.2) 18.3 (9.1) 26.0 (13.0) 65.8 (30.1) |
Tmax0-5 hr (h): 0.5 to 4 mg | Means (SD range): 1.0 to 1.4 (0.3 to 0.5) |
T½ (h): 0.5 to 4 mg | Means (Indiv. Range): 1.0 to 1.4 (0.4 to 8.0) |
| PARAMETER | PATIENTS WITH Type 2 diabetesa |
| CL based on IV (L/h) | 38 (16) |
| VSS based on IV (L) | 31 (12) |
| AbsBio (%) | 56 (9) |
a: dose preprandially three times daily
CL = Total body clearance
Vss = Volume of distribution at steady state
AbsBio = Absolute bioavailability
Variability: The intra-individual and inter-individual variabilities (coefficient of variation) in AUC were 36% and 69%, respectively after multiple dosing of repaglinide tablets (0.25 to 4 mg with each meal) in patients.
Special Populations and Conditions
Geriatrics: Healthy volunteers were treated with a regimen of 2 mg taken before each of 3 meals. There were no significant differences in repaglinide pharmacokinetics between the group of patients < 65 years of age and a comparably sized group of patients ≥ 65 years of age.
Gender: A comparison of pharmacokinetics in males and females showed the AUC over the 0.5 mg to 4 mg dose range to be 15% to 70% higher in females with type 2 diabetes. This difference was not reflected in the frequency of hypoglycemic episodes (male: 16%; female: 17%) or other adverse events. With respect to gender, no change in general dosage recommendation is indicated since dosage for each patient should be individualized to achieve optimal clinical response.
Race: No pharmacokinetic studies to assess the effects of race have been performed, but in a U.S. 1-year study in patients with type 2 diabetes, the blood glucose-lowering effect was comparable between Caucasians (n=297) and African-Americans (n=33). In a U.S. dose-response study, there was no apparent difference in exposure (AUC) between Caucasians (n=74) and Hispanics (n=33).
Hepatic Insufficiency: A single-dose, open-label study was conducted in 12 healthy subjects and 12 patients with chronic liver disease (CLD) classified by caffeine clearance. Patients with moderate to severe impairment of liver function had higher and more prolonged serum concentrations of both total and unbound repaglinide than healthy subjects
(AUChealthy: 91.6 ng/mL*h; AUCCLD patients: 368.9 ng/mL*h; Cmax, healthy: 46.7 ng/mL;
Cmax, CLD patients: 105.4 ng/mL.). AUC was statistically correlated with caffeine clearance. No difference in glucose profiles was observed across patient groups. Patients with impaired liver function may be exposed to higher concentrations of repaglinide and its associated metabolites than would patients with normal liver function receiving the same doses.
Renal Insufficiency: Single-dose and steady state pharmacokinetics of repaglinide have been evaluated in patients with various degrees of renal impairment. Repaglinide was found to be well tolerated in all groups. Measures of AUC and Cmax after multiple dosing of 2 mg repaglinide were found to be higher in three groups of patients with reduced renal function (AUCmild/moderate impairment: 90.8 ng/mL*hr to AUCsevere impairment:137.7 ng/mL*hr versus AUChealthy: 29.1 ng/mL*hr; Cmax, mild/moderate impairment: 46.7 ng/mL to Cmax, severe impairment: 44.0 ng/mL versus Cmax, healthy: 20.6 ng/mL). Repaglinide AUC is only weakly correlated to creatinine clearance.
Genetic Polymorphism: In healthy subjects, polymorphism in the SLCO1B1 gene (c.521T>C) encoding for the OATP1B1 transporter has been observed to lead to approximately 72% higher exposure (AUC). Polymorphism in CYP2C8 (CYP2C8*3) has been studied in different studies in healthy subjects. The CYP2C8*3 allele has been found to have either no effect or been associated with an approximately 50% lower exposure (AUC). The observed effects are explaining factors for the observed inter individual variability together with the variability in the expression of metabolizing enzymes.
STORAGE AND STABILITY
Repaglinide should be stored at 15°C - 25°C.
Keep out of reach of children.
Unused medication should not be disposed of down the drain or in household garbage.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Repaglinide tablets are available in 0.5 mg, 1 mg and 2 mg strengths.
Repaglinide 0.5 mg tablets are white, round, without score notch, with embossment “SZ” on one side and “05” on the other side.
Repaglinide 1 mg tablets are yellow, slightly dotted, round, without score notch, with embossment “SZ” on one side and “1” on the other side.
Repaglinide 2 mg tablets are pale red, slightly dotted, round, without score notch, with embossment “SZ” on one side and “2” on the other side.
All strengths are available in HDPE bottles of 100 tablets.
Non-medicinal ingredients: calcium hydrogen phosphate, anhydrous; cellulose, microcrystalline; ferric oxide red (2 mg only); ferric oxide yellow (1 mg only); glycerol; hydroxypropylcellulose; magnesium stearate; maize starch; meglumine; polacrilin potassium; poloxamer type 188; silica, colloidal anhydrous.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Repaglinide
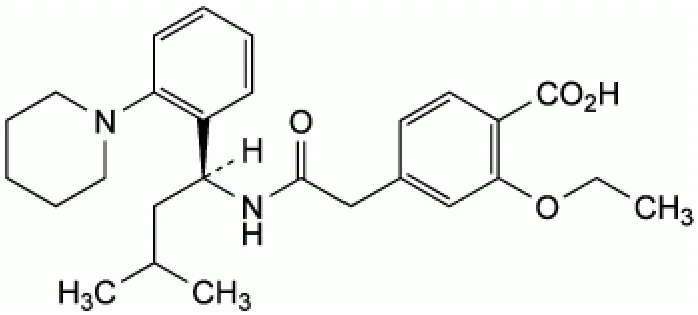
Chemical name: (+)-2-Ethoxy-α[[(S)-α-isobutyl-o-piperdinobenzyl] carbamoyl]-p-toluic acid
Molecular formula: C27H36N2O4,
Molecular mass: 452.6 g/mol
Structural formula:
Physicochemical properties: White or almost white powder.
Practically insoluble in water, freely soluble in methanol and in methylene chloride.
Repaglinide has a melting point of 133°C and its pKa is: pKa1= 4.2 and pKa2=5.8 (calculated).
CLINICAL TRIALS
A comparative, single dose, blinded, randomized, 2-way crossover bioequivalence study of Repaglinide vs GlucoNorm® (NovoNordisc Canada Inc.), each administered as 1 x 2 mg tablet dose, was conducted on a total of 16 healthy male volunteers, aged 18-55 years, under fasting conditions.
Repaglinide (1 x 2 mg) From measured data uncorrected for potency Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means1 | 90% Confidence Interval1 |
AUC0-t (pg.h/mL) | 39611.18 42830.58 (46.63) | 36788.27 39410.05 (40.01) | 107.67 % | 99.95 % to 116.00 % |
AUC0-inf (pg.h/mL) | 41181.60 44478.78 (46.31) | 38534.64 41118.66 (39.30) | 106.87 % | 99.31 % to 115.00 % |
Cmax (pg/mL) | 11608.32 12398.92 (38.78) | 11464.50 11959.94 (33.74) | 101.25 % | 85.93 % to 119.31 % |
Tmax (h) | 1.06 (55.93) | 0.959 (65.28) | ||
T½ el (h) | 2.69 (24.60) | 2.79 (38.60) | ||
* Repaglinide, manufactured for Pro Doc Ltée.
† GlucoNorm® manufactured by Novo Nordisk, Canada, and purchased in Canada.
1 Based on least-squares mean estimates
Study demographics and trial design
A four-week, double-blind, placebo-controlled dose-response trial was conducted in patients with type 2 diabetes using doses ranging from 0.25 to 4 mg taken with each of three meals. Repaglinide therapy resulted in dose- proportional glucose-lowering over the full dose range. Plasma insulin levels increased after meals and reverted toward baseline before the next meal. Most of the fasting blood glucose-lowering effect was demonstrated within 1-2 weeks.
In a double-blind, placebo-controlled, 3-month dose titration study, repaglinide or placebo doses for each patient were increased weekly from 0.25 mg through 0.5, 1, and 2 mg, to a maximum of 4 mg, until a fasting plasma glucose (FPG) level <8.9 mmol/L was achieved or the maximum dose reached. The dose that achieved the targeted control or the maximum dose was continued to end of study. FPG and 2-hour post-prandial glucose (PPG) increased in patients receiving placebo and decreased in patients treated with repaglinide. Differences between the repaglinide- and placebo-treated groups were -3.41 mmol/L (FPG) and -5.78 mmol/L (PPG). The between-group change in HbA1C, which reflects long-term glycemic control, was 1.7% units.
Table 6 – Repaglinide vs. Placebo Treatment: Mean FPG, PPG and HbA1C
| FPG, PPG, and HbA1C | ||||||
| FPG (mmol/L) | PPG (mmol/L) | HbA1C (%) | ||||
| PL | R | PL | R | PL | R | |
| Baseline | 11.96 | 12.23 | 13.62 | 14.54 | 8.1 | 8.5 |
| Change from Baseline (at last visit) | 1.68 | -1.72* | 3.14 | -2.64* | 1.1 | -0.6* |
PL = placebo, R = repaglinide
* p ≤ 0.05 for between group difference
Another double-blind, placebo-controlled trial was carried out in 362 patients treated for 24 weeks. The efficacy of 1 and 4 mg preprandial doses was demonstrated by lowering of fasting blood glucose and by HbA1C at the end of the study. HbA1C for the repaglinide treated groups
(1 and 4 mg groups combined) at the end of the study was decreased compared to the placebo-treated group in previously naïve patients and in patients previously treated with oral hypoglycemic agents by 2.1% units and 1.7% units, respectively. In this fixed-dose trial, patients who were naïve to oral hypoglycemic agent therapy and patients in relatively good glycemic control at baseline (HbA1C below 8%) showed greater blood glucose-lowering including a higher frequency of hypoglycemia. Patients who were previously treated and who had baseline
HbA1C ≥ 8% reported hypoglycemia at the same rate as patients randomized to placebo. There was no average gain in body weight when patients previously treated with oral hypoglycemic agents were switched to repaglinide. The average weight gain in patients treated with repaglinide and not previously treated with sulfonylurea drugs was 3.3%.
The dosing of repaglinide relative to meal-related insulin release was studied in three trials including 58 patients. Glycemic control was maintained during a period in which the meal and dosing pattern was varied (2, 3, or 4 meals per day; before meals x 2, 3, or 4) compared with a period of 3 regular meals and 3 doses per day (before meals x 3). It was also shown that repaglinide can be administered at the start of a meal, 15 minutes before, or 30 minutes before the meal with the same blood glucose lowering effect.
Repaglinide was compared to other insulin secretagogues in 1-year controlled trials to demonstrate comparability of efficacy and safety. Hypoglycemia was reported in 16% of
1228 repaglinide patients, 20% of 417 glyburide patients, and 19% of 81 glipizide patients. Of repaglinide treated patients with symptomatic hypoglycemia, none developed coma or required hospitalization.
Repaglinide was studied in combination with metformin in 83 patients not satisfactorily controlled on exercise, diet, and metformin alone. Combination therapy with repaglinide and metformin resulted in synergistic improvement in glycemic control compared to repaglinide or metformin monotherapy. HbA1C was improved by 1% unit and FPG decreased by an additional 1.94 mmol/L.
Table 7 - Repaglinide and Metformin Therapy: Mean HbA1C and FPG - Changes from Baseline after 3 Months Treatment
| Repaglinide | Combination | Metformin | |
| n | 28 | 27 | 27 |
| HbA1C (% units) | -0.38 | -1.41* | -0.33 |
| FPG (mmol/L) | 0.49 | -2.18* | -0.25 |
* p ≤ 0.05 for comparison between combination and both monotherapies
A combination therapy regimen of repaglinide and rosiglitazone was compared to monotherapy with either agent alone in a 24-week trial that enrolled 252 patients previously treated with sulfonylurea or metformin (HbA1c > 7.0%). Combination therapy resulted in significantly greater improvement in glycemic control as compared to monotherapy. The glycemic effects of the combination therapy were dose-sparing with respect to both total daily repaglinide dosage and total daily rosiglitazone dosage. A greater efficacy response of the combination therapy group was achieved with half the median daily dose of repaglinide and rosiglitazone, as compared to the respective monotherapy groups. Mean weight increases associated with combination, repaglinide and rosiglitazone therapy were 4.4 kg, 1.6 kg, and 2.3 kg, respectively.
Table 8 - Repaglinide and rosiglitazone Therapy: Mean HbA1c and FPG - Changes from Baseline After 24 Weeks of Therapy
| Repaglinide | Combination | Rosiglitazone | |
| n | 59 | 126 | 55 |
| HbA1c (% units) | -0.17 | -1.43* | -0.56 |
| n | 57 | 122 | 56 |
| FPG (mmol/L) | -3.01 | -5.24* | -3.70 |
* p< 0.001 for comparison between combination and both monotherapies
Combination therapy with Rosiglitazone
During a 24-week treatment clinical trial of repaglinide -rosiglitazone combination therapy (a total of 127 patients in combination therapy), hypoglycemia (blood glucose < 2.78mmol/L) occurred in 9% of combination therapy patients in comparison to 6% for repaglinide monotherapy, and 2% for rosiglitazone monotherapy.
Peripheral edema was reported in 5 out of 127 repaglinide -rosiglitazone combination therapy patients and 2 out of 62 rosiglitazone monotherapy patients, with no cases reported in this trial for repaglinide monotherapy. There were no patients treated with repaglinide -rosiglitazone therapy that reported episodes of edema with congestive heart failure.
Mean change in weight from baseline was +4.4 kg for repaglinide -rosiglitazone therapy. There were no patients on repaglinide -rosiglitazone combination therapy who had elevations of liver transaminases (defined as 3 times the upper limit of normal levels).
Table 9 - Repaglinide and rosiglitazone Therapy: Events of hypoglycemia, peripheral edema and weight change
| Repaglinide | Combination | Rosiglitazone | |
Minor hypoglycemic episode (blood glucose < 2.78mmol/L) | 6% | 9% | 2% |
| Peripheral edema | 0% | 3.9% | 3.2% |
| Weight change at end of study (24 weeks) | +1.6 kg | +4.4 kg | +2.3 kg |
Cardiovascular
The observed difference in the incidence of serious cardiovascular treatment emergent adverse events was higher for repaglinide than for glyburide but lower for glipizide and was not statistically significant when adjustments for baseline differences in prior medical history and predisposing conditions were made. In part, differences in baseline ECG, cardiovascular medical history and baseline cholesterol may have contributed to the difference in rates. When comparing repaglinde to the sulfonylurea drugs as a whole, no statistically significant differences were found either for serious cardiovascular (CV) events or for all CV events. Dose analyses revealed no increase in CV risk with increasing doses of repaglinde.
See also ADVERSE REACTIONS.
DETAILED PHARMACOLOGY
ANIMAL STUDIES:
Pharmacodynamics:
Table 10 – Animal Pharmacology Models and Study Results
| Test | Species/ Cellular Material | Route | Results and Conclusions |
|---|---|---|---|
| Hypoglycemic effect, comparison with AG-EE 388 ZW | Rat/Chbb:Thom (female) | PO IV | Intravenous administration of repaglinide or racemic mixture demonstrated a significant hypoglycemic effect in rats beginning at a dose of 0.01% mg/kg (racemic mixture) and 0.003 mg/kg (repaglinide). The ED10 was 2-5 mcg/kg. There was no hypoglycemic activity following oral administration up to 1.0 mg/kg. |
| Test | Species/ Cellular Material | Route | Results and Conclusions |
| Hypoglycemic effect, comparison with AG-EE 388 ZW |
| Dog/Chbb: Beagle (female) | PO | In dogs, oral administration of repaglinide resulted in significant hypoglycemic activity and increased plasma insulin levels. The ED10 was 5.6 mcg/kg. | |
| Antihyperglycemic effects, comparison with glyburide | Normal and diabetic rats (male, 6-8/group) | PO IV | Repaglinide 10 times more potent than glyburide following both oral and intravenous administration. The duration of action and maximal efficacy, however, were similar (maximum effect at 120 mins for oral and 60 mins for IV administration). |
| Profile in vivo- Rat | |||
| Insulin-stimulated glucose uptake, comparison with glyburide and placebo | Perifused rat hind limb (Wistar rats, male, 4/group) | -- | Sensitivity to insulin in skeletal muscles not altered by either repaglinide or glyburide. |
| Evaluation of the effect of repaglinide and glyburide in rats with chronic renal dysfunction | Nephrectomized rat (male) | PO | No significant differences in dynamic profile compared to normal rats with either drug. |
| Hypoglycemic activity of AG-EE 388 ZW and its metabolites | Rat (female, Wistar) | IV | Metabolism of the racemic compound did result in active hypoglycemic metabolites. None of the metabolites exhibited an activity that was equal to or greater than the parent compound and they do not contribute to the hypoglycemic effect of the racemic compound. |
| In - vitro mechanism of action studies: | |||
| Effects of repaglinide and glyburide on ATP-sensitive K+ channels and intracellular [Ca2+] using patch clamp techniques and digital Ca2+ imaging | Newborn rat islets and mouse βTC3 cells | -- | Equipotent with glyburide with respect to inhibition of beta-cell ATP-sensitive K+-channel and stimulation of an increase in [Ca2+] (Both compounds causing dose-dependent inhibition and subsequent calcium influx). |
| Characterization of binding sites in β cells | Rat βTC3 cells and membranes | -- | A unique binding profile different from SUs glyburide, glipizide, tolbutamide, glimepiride. Higher affinity to a binding site in βTC3 cells than SUs. |
| Regulation of ATP sensitive K+-channel by repaglinide and glyburide through different binding sites | Intact βTC3 | -- | Repaglinide and glyburide regulate the ATP-sensitive K+-channel through different binding sites in the β-cells. These sites are not equally dependent upon ADP and ATP. |
| Test | Species/ Cellular Material | Route | Results and Conclusions |
|---|---|---|---|
| Insulinotropic action: modulation by activator of ATP-sensitive K+-channel and high extracellular [K+]. | Rat pancreatic islets (female rats) | -- | The insulinotropic action of repaglinide is mainly attributable to a primary block of ATP-sensitive K+-channels |
| Effect on glucose-stimulated insulin release in metabolic stressed mouse islets. | Mouse islets treated with Dinitrophenol (DNP) by perifusion | -- | DNP-treated cells did not influence the activity of repaglinide but did affect glyburide and glibornuride. Repaglinide normalizes a situation of metabolic stress in isolated mouse islets, in contrast to glyburide and glibornuride. |
| Effect on glucose-stimulated insulin release in normal mouse islet. | Mouse islets | -- | Repaglinide is 3-5 times more potent than glyburide. Activity of repaglinide is more dependent on presence of D-glucose than glyburide. |
| Profile in vitro. Effect on direct exocytosis. Binding characteristics to whole murine β-cells (βTC3 cells) | β-cells | -- | Repaglinide had contrary to glyburide no direct effect on exocytosis Three binding sites were identified. Findings suggest that repaglinide possesses both structural and mechanistic properties which are distinct from glyburide. |
| Effect on Ba2+-induced insulin release, comparison with meglitinide analogues | Rat islets isolated from pancreas | -- | Insulinotropic action of meglitinide and repaglinide is due to primary and direct action on ATP-sensitive K+-channels as opposed to being primarily attributable to an intracellular redistribution of Ca2+ ions. |
| Ionophoretic activity, comparison with meglitinide analogues | Artificial membrane model | -- | Each hypoglycemic agent was able to cause translocation of 45Ca and 22Na from an aqueous solution into an immiscible organic phase. Iontophoretic activity did not closely parallel the insulinotropic potential of these compounds. Therefore, the ionophoretic capacity may not represent an essential determinant of the insulin-releasing action. |
| Insulinotropic activity, comparison with meglitinide and its analogues | Rat islets of Langerhans | -- | Repaglinide the second most potent drug in its ability to evoke a secretory response in the islet cells. It is a potent insulin secretagogue. Augmented insulin release evoked by exogenous glucose. |
| Effect on biosynthetic activity | Rat islets | -- | Repaglinide did not affect adversely glucose-stimulated protein and proinsulin biosynthesis. Repaglinide may offer the advantage over hypoglycemic SUs to preserve nutrient - stimulated biosynthetic activity in β-cells. |
| Test | Species/ Cellular Material | Route | Results and Conclusions |
| Relationship between reversibility and insulin releasing potency | Perifused rat islets | -- | No parallelism between insulinotropic potency and reversibility of cationic and secretory effects |
| Effect on malate dehydrogenase, comparison with AG-EE 624 ZW | Mouse islets | -- | No effect on activity or sub-cellular localization of enzymes with either compound |
Pharmascreen Testing Biochemical Testing | In vivo: mouse In vitro: isolated guinea pig trachea | PO -- | Anti-hyperglycemic action. No extra-pancreatic effect. Closure of ATP-sensitive K+-channel. Clean profile i.e. only high affinity in one receptor assay. |
TOXICOLOGY
Acute Toxicity:
Repaglinide did not have significant acute oral toxicity in the rat; the LD50 was > 3000 mg/kg for males and between 2500-3000 mg/kg for females. Intravenous administration of repaglinide to rats resulted in LD50 values of > 50 mg/kg for males and 20-50 mg/kg for females. Clinical signs were similar to those seen following oral administration.
Dogs were more sensitive than rats. Deaths occurred in dogs at both 300 & 1000 mg/kg.
Both species had signs suggesting CNS effects, and included decreased activity; ptosis and hypothermia in the rat; and tremor, emesis, and staggering in the dog. No drug-induced lesions were observed for either species at necropsy.
Table 11 - Long-Term Toxicity Studies
| Species/Strain Initial Group | Dosing Method | Duration of Treatment (w) | Dose (mg/kg/day) | Results |
|---|---|---|---|---|
| Subchronic Toxicity | ||||
Mouse: CD-1 5M, 5F/ group, 4 w old | Diet | 8 | 0, 380, 480, 600, 750, 1000 (380 dose increased to 1500 at week 6) | Deaths: No treatment related effects Clinical Signs: No treatment related effects Conclusions: No treatment related effects. |
| Species/Strain Initial Group | Dosing Method | Duration of Treatment (w) | Dose (mg/kg/day) | Results |
Mouse Chbb:NMRI 10M,10F/ dose, 42 days old, 20.6-29.2 g | Diet | 13 | 0, 30, 120, 480 | No treatment related effects on mortality, clinical signs, organ weight or gross and microscopic pathology. Food consumption decreased in weeks 1-2 for males and weeks 1-7 for females, but not in dose-dependent manner. Reductions in body weight gain in all groups (12-14% for high dose group). Increased water consumption in 30 mg/kg group. Laboratory: treatment-related increases in alkaline phosphatase levels in high dose males, liver glycogen values decreased in all treated males and mid and high dose females. |
Rat Chbb:Thom 20M, 20F/ group, 150-180 g females; 180-250 g males | Diet | 13 , 6 week recovery groups after 13 weeks treatment (10 animals/ group) | 0, 30, 60, 120, 240 | No treatment related effects on mortality, water consumption, ophthalmology, heart rates, hematology, fecal occult blood, gross pathology, organ weights, histopathology or bone marrow cytology. Clinical Signs: Unkempt appearance during first 2 weeks of treatment for 120 and 240 mg/kg groups. Food consumption slightly decreased in males (all groups) and high dose females; decreases in body weight gains greatest in high dose group; increase in liver weights for females and heart weights (high dose females). Laboratory: Treatment-related increases in alkaline phosphatase in two high dose groups (reversible); decreased GPT, decreased leucine arylamidase (females only), liver glycogen (high dose grps only), increased total cholesterol (females) and increased amylase (females, two high doses). All lab changes were reversible and generally not statistically significant. Conclusions: 120 mg probably the MTD. |
| Chronic Toxicity | ||||
Rat Sprague-Dawley 25M, 25F/ group; 4 weeks old at receipt | Diet | 52 | 0, 2, 16, 120 in lactose | No treatment -related effects on mortality, clinical signs, food consumption, water consumption, ophthalmoscopy, hematology, urinalysis, organ weights or gross or microscopic pathology. Body weight gains decreased by 15% for the high dose animals. Laboratory: Alkaline phosphatase values increased at weeks 26 and 52 in high dose animals. Conclusions: MTD is 120 mg/kg/day. |
| Species/Strain Initial Group | Dosing Method | Duration of Treatment (w) | Dose (mg/kg/day) | Results |
Dog Chbb:Beagle 4M, 4F/ group; age 11-18 months, weight 9.1-13.6 kg | Capsule | 52 | 0, 0.05, 2, 50 | No treatment-related effects on body weights, food consumption, heart rate, ECGs, blood pressure, ophthalmoscopy, hematology, bone marrow cytology, urinalysis and gross pathology. Clinical Signs: Clonic tonic spasms in mid and high dose groups eliminated with glucose injection. Two deaths possibly due to seizures in high dose groups. Decreased prostate weight in 50 mg males, enlarged periportal areas in liver in some high dose animals. Laboratory: Reduced glucose concentrations up to 60%, increased liver enzymes and amylase in some high dose animals. Conclusions: NOEL: 0.05 mg/kg. |
Table 12 – Carcinogenicity
| Species/Strain Initial Group | Dosing Method | Duration of Treatment (w) | Dose (mg/kg/day) | Results |
|---|---|---|---|---|
Mouse CD-1 50M, 50F | Diet | 104 | 0, 50, 170, 500 | Deaths: 271 premature deaths. High dose males showed a slight increase in mortality compared with controls. Clinical Signs: Body weight reductions up to 11% observed at 170 and 500 mg doses. Tumours/Lesions: No evidence of tumourigenic potential, no indication of non-neoplastic toxic effects. Conclusions: No carcinogenic potential. |
| Species/Strain Initial Group | Dosing Method | Duration of Treatment (w) | Dose (mg/kg/day) | Results |
Rat Chbb:Thom 50M, 50F | Diet | 104 | 0, 15, 30, 60, 120 | Deaths: 184 died or were sacrificed prematurely (83 M, 101 F). A dose-related decrease in mortality compared to controls was apparent in males given 60 or 120 mg/kg. Clinical Signs: No signs of tumorigenic effect up to 30 mg/kg, and no evidence of non-neoplastic toxic effects. Tumors/Lesions: Slight increase in incidence of benign thyroid and liver tumors observed at 60 and/or 120 mg/kg. Thyroid, follicular cell adenomas increased in males but not females; Hepatocellular adenomas increased in males at 120 mg/kg but no progression to malignant carcinomas; Females had increased incidence of non-neoplastic hepatocellular metaplasia of the pancreas at all dose levels and males at 60 and 120 mg/kg. Conclusions: NOEL:30 mg/kg for males and females. |
Table 13 – Reproduction and Teratology
| Species/Strain Initial Group | Dosing Method | Duration of Treatment | Dose (mg/kg/day) | Results |
|---|---|---|---|---|
| Fertility Studies - Segment I Studies | ||||
Rat, Chbb:Thom FO:24M, 24F F1: 1M, 1F per litter | Gavage | FO:PND22 F1:GD14 to 16 | M-O: 1, 30, 300 F-O: 1, 30, 80 -Dosing prior to breeding and continued for females throughout lactation. F0 Dosing: M= + 10 w to mating F= +2 w to GD22 | Parental Effects: Decreased body weight gain (males and females high dose groups). No effect on reproduction or fertility. High dose females had decreased corpora lutea and implantation sites, increased resorptions, decrease in live births and decreased fetal survival. Offspring Effects: Abnormal limb development resulting in abnormal gait. Conclusions (NOEL): F0: M: 1 mg/kg; F: 30 mg/kg; F1: M:<1 mg/kg; F: 1mg/kg |
| Species/Strain Initial Group | Dosing Method | Duration of Treatment | Dose (mg/kg/day) | Results |
| Embryo Toxicity Studies - Segment II | ||||
Rat, Chbb:Thom 36F (pregnant) | Gavage | Day 7-16; Some rats sacrificed on G22. The remainder allowed to naturally deliver their pups. | 0, 0.5, 5, 80 | Maternal Effects: Significant decrease in body weight gain and food consumption (high dose) and slightly decreased at 5 mg/kg dose; For GD22 sacrificed rats there was an increase in the no. of total and early resorptions and post-implantation loss in the high dose group. Offspring Effects: No malformations; however, dose dependent ossification delays and decrease in post-weaning body weight gain in male offspring at two highest doses. Conclusions (NOEL): F: 0.5 mg/kg; Embryo/fetal: 0.5 mg/kg |
Rabbit Chbb:HM 21F (pregnant) | Gavage | Day 6-18; Dams sacrificed on GD 29 | 0, 0.1, 0.25, 0.9 | Maternal Effects: Increase in food consumption and body weight gain in mid and high dose groups; increased incidence in abortion and resorptions in high dose group. Offspring Effects: Higher incidence of skeletal malformations and variations in the high dose group. Conclusions (NOEL): F: 0.1 mg/kg; Embryo/fetal: 0.1 mg/kg |
| Species/Strain Initial Group | Dosing Method | Duration of Treatment | Dose (mg/kg/day) | Results |
| Peri-postnatal Toxicity Studies - Segment III | ||||
Rat, Chbb:Thom 23F (pregnant) 4F (pregnant- for milk analysis) control and high dose | Gavage | Day 16 PC up to day 22 PP; cross-fostering group also included | 0, 0.5, 5, 30, 80 | Maternal Effects: Decrease in body weight gain for two high dose groups. Offspring Effects: Dose-dependent increase in postnatal mortality, reduced body weight gain, abnormal limb development in two high dose groups and delay in vaginal opening for three high dose groups. Cross-fostered offspring also demonstrated abnormal limb development. Reduction in the reproductive capacity of offspring in low dose groups; mid dose groups unaffected, however corpora lutea, implantation sites and viable fetuses were affected at 5 mg/kg or higher. Conclusions (NOEL): F: 5 mg/kg; Embryo/fetus: <0.5 mg/kg |
Rat Chbb:Thom 13F (pregnant) | Gavage | Dosing Windows: GD 1 to 5 GD 6 to 16 GD 17 to 22 PND 1 to 14 PND 15 to 21 | 80 (5 treatment window groups) | Offspring Effects: No developmental impairment during embryogenesis and early fetogenesis. Long bone deformities not evident if treatment limited to first 2 trimesters (GD 1-16). Conclusions: Critical time point appears to be late gestation and/or were more pronounced in early lactation. |
| Species/Strain Initial Group | Dosing Method | Duration of Treatment | Dose (mg/kg/day) | Results |
Rat, Chbb:Thom 25F (pregnant) | Gavage | Dosing Windows: GD 7 to 22 PN 1 to 21 Bone x-ray analyses performed postpartum weeks 4, 6 and 10. | 0, 80 | Offspring Effects: Moderate to severe bone deformities at postnatal week 4, gradually dissipating by week 10. Lactational exposure produced a persistent moderate to severe deformation in the bones. X-ray confirmed chondromalacia and inhibited ingrowth of osteogenic buds. Conclusions: Impairment of chondrogenesis due to pharmacodynamic effect. |
Rat, Chbb:Thom 6F (pregnant) | Gavage | GD7 to PND7 | 0, 80 80+ 10% glucose water 80+streptozoto cin | Expected limb deformity observed; evaluation of glucose levels showed statistically lower values in the treated females, but animals with the glucose supplement showed no decreases. |
Rat, Chbb:Thom 32F (pregnant) | Gavage | Dosing Windows: GD 17-22 (G2) PP 1-14 (G3) GD 17-PP 14 (G4) | 0 or 80 | Maternal Effects: High mortality in G3 dams during the first 4 days post-delivery. Clinical signs in G2 and G4 dams were related to severe hypoglycemia, decreases in blood glucose levels in treated dams during gestation only. Offspring Effects: Decreases in blood glucose levels in G3 and G4 offspring. X-ray analyses confirmed skeletal deformities in 40% of G2 and 100% of the G3 and G4 offspring. Conclusions: Repaglinide transmitted to milk. |
Repaglinide was not teratogenic in rats and rabbits at doses 40 times (rats) and approximately 0.8 times (rabbit) the maximum recommended human dose (on a mg/m2 basis) throughout pregnancy. However, in some studies in rats, offspring of dams exposed to high levels of repaglinide during the last trimester of pregnancy and during lactation developed skeletal deformities consisting of shortening, thickening and bending of the humerus during the postnatal period. This effect was not seen at doses up to 2.5 times the maximum recommended human dose (on a mg/m2 basis) throughout pregnancy or at higher doses given during the first two trimesters of pregnancy.
Since animal reproduction studies are not always predictive of human response, repaglinide is not recommended for use during pregnancy.
REFERENCES
- 1. Ampudia-Blasco FJ, Heinemann L, Bender R et al. Comparative dose-related time-action profiles of glibenclamide and a new non-sulphonylurea drug, AG-EE 623 ZW, during euglycaemic clamp in healthy subjects. Diabetologia 1994; 37: 703-707.
- 2. Kajosaari L.I., Niemi M, Neuvonen M, Laitila J, Neuvonen P.J., Backman J.T. Clinical Pharmacology and Therapeutics 2006; 78 (4): 388-399.
- 3. Wolffenbuttel BHR, Nijst L, Sels JPJE, Menheere PPCA, Muller PG. Effects of a new oral hypoglycemic agent, repaglinide, on metabolic control in sulphonylurea-treated patients with NIDDM. Eur J Clin Pharmacol 1993; 45: 113-116.
- 4. Expert Committee of the Canadian Diabetes Advisory Board. Clinical practice guidelines for treatment of diabetes mellitus. Can Med Assoc J 1992;147:697-712.
- 5. Raskin P, McGill J, Hale P, Khutoryansky N, Santiago, O. Repaglinide/Rosiglitazone Combination Therapy of Type 2 Diabetes. DIABETES, Abstracts from ADA 61st Scientific Sessions, June 2001, Vol 50, Supp 2.
- 6. Marbury T, Ruckle JL, Hatorp P et al. Pharmacokinetics of repaglinide in subjects with renal impairment. Clinical Pharmacology and Therapeutics 2000; 67(1): 7-15.
- 7. Bidstrup TB, Damkier P, Olsen AK, Ekblom M, Karlsson A, Brøsen K. The impact of CYP2C8 polymorphism and grapefruit juice on the pharmacokinetics of repaglinide. Br J Clin Pharmacol 2006; 61(1):49-57.
- 8. Kalliokoski A, Neuvonen M, Neuvonen PJ, Niemi M. Different effects of SLCO1B1 polymorphism on the pharmacokinetics and pharmacodynamics of repaglinide and nateglinide. J Clin Pharmacol 2008; 48(3):311-321.
- 9. Kalliokoski A, Backman JT, Kurkinen KJ, Neuvonen PJ, Niemi M. Effects of Gemfibrozil and Atorvastatin on the Pharmacokinetics of Repaglinide in Relation to SLCO1B1 Polymorphism. Clin Pharmacol Ther 2008;doi: 10.1038/clpt.2008.74.
- 10. Niemi M, Backman JT, Kajosaari LI et al. Polymorphic organic anion transporting polypeptide 1B1 is a major determinant of repaglinide pharmacokinetics. Clin Pharmacol Ther 2005; 77(6):468-478.
- 11. Niemi M, Leathart JB, Neuvonen M, Backman JT, Daly AK, Neuvonen PJ. Polymorphism in CYP2C8 is associated with reduced plasma concentrations of repaglinide. Clin Pharmacol Ther 2003; 74(4):380-387.
- 12. Tirona RG, Leake BF, Merino G, Kim RB. Polymorphisms in OATP-C. Identification of multiple allelic variants associated with altered transport activity among European- and African-Americans. Journal of Biological Chemistry 2001; 276(38):35669-35675.
- 13. Dai D, Zeldin DC, Blaisdell JA et al. Polymorphisms in human CYP2C8 decrease metabolism of the anticancer drug paclitaxel and arachidonic acid. Pharmacogenetics 2001; 11(7):597-607.
- 14. Bahadur N, Leathart JBS, Mutch E et al. CYP2C8 polymorphisms in Caucasians and their relationship with paclitaxel 6alpha-hydroxylase activity in human liver microsomes. Biochemical Pharmacology 2002; 64(11):1579-1589.
- 15. Lecointre, K, Furlan V, Taburet A.M. In vitro effects of tacrlimus on human cytochrome P450. Fundamental & Clinical Pharmacology 2002; 455-460
- 16. Niwa T, Yamamoto S, Saito M, Shiraga T, Takagi A. Effect of Cyclosporine and Tacrolimus on Cytochrome P450 Activities in Human Liver Microsomes. The Pharmaceutical Society of Japan 2007; 127(1): 209-216
- 17. Turk T., Pietruck F., Dolff S., Kriben A., Janseen O.E., Mann K., Philipp T., Heemann U. and Witzke O. Repaglinide in the Management of New-Onset Diabetes Mellitus After Renal Transplntation. American journal of Transplantation 2006; 6: 842-846
- 18. Hatorp V. and Thomsen MS. Drug interaction studies with repaglinide on digoxin or theophylline pharmacokinetics and cimetidine on repaglinide pharmacokinetics. J. Clin. Pharmacol. 2002; 40; 184
- 19. Hatorp V., Hansen Kristian T. and Thomsen M.S. Influence of Drugs Interacting with CYP3A4 on the Pharmacokinetics, Pharmacodynamics, and Safety of the Prandial Glucose Regulator Repaglinide. J. Clin. Pharmacol. 2003; 43;649
- 20. Rosenberg M.A., Strange P., Chohen A. Assessment of pharmacokinetic and pharmacodynamic interactions between warfarin and repaglinide [abstract]. Diabetes 48 suppl. 1:A356, 1999
- 21. Novo Nordisk Canada Inc., GlucoNorm Product Monograph (repaglinide tablets 0.5 mg, 1 mg, 2 mg), Control No.: 186101; Date of Revision: September 9, 2015.