


Product Monograph - Revatio (BGP Pharma, 0.8 mg)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Oral | Film-coated tablet/ 20 mg sildenafil as sildenafil citrate | Tablet core: Anhydrous dibasic calcium phosphate, croscarmellose sodium, magnesium stearate, microcrystalline cellulose. Film coat: hypromellose, lactose, titanium dioxide (E-171), triacetin. |
| Intravenous | Solution/ 0.8 mg/mL sildenafil as sildenafil citrate | glucose, water for injection (see Dosage Forms, Composition and Packaging) |
INDICATIONS AND CLINICAL USE
REVATIO (sildenafil citrate) is indicated for:
- treatment of primary pulmonary arterial hypertension (PPH) or pulmonary hypertension secondary to connective tissue disease (CTD) in adult patients with WHO functional class II or III who have not responded to conventional therapy. In addition, improvement in exercise ability and delay in clinical worsening was demonstrated in adult patients who were already stabilised on background epoprostenol therapy.
REVATIO solution is indicated for:
- the continued treatment of patients with pulmonary arterial hypertension (PAH) who are currently prescribed oral REVATIO and who are temporarily unable to take oral medication.
Pediatrics (< 18 years of age)
REVATIO is not indicated for use in children less than18 years of age (see WARNINGS AND PRECAUTIONS, Pediatrics and ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, Pediatric Clinical Trial Safety Data)
CONTRAINDICATIONS
- Sildenafil citrate has been shown to potentiate the hypotensive effects of nitrates in healthy volunteers and in patients, and is therefore contraindicated in patients who are taking any type of nitrate drug therapy, or who utilize short-acting nitrate-containing medications, due to the risk of developing potentially life-threatening hypotension. The use of organic nitrates, either regularly and/or intermittently, in any form (e.g. oral, sublingual, transdermal, by inhalation) is absolutely contraindicated (see ACTION AND CLINICAL PHARMACOLOGY, DOSAGE AND ADMINISTRATION).
- REVATIO is contraindicated in patients who are hypersensitive to this drug or any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- REVATIO is contraindicated in patients with previous episode of non-arteritic anterior ischaemic optic neuropathy (NAION) (see WARNINGS AND PRECAUTIONS).
- REVATIO is contraindicated in combination with the most potent of the CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, ritonavir).
Vaso-occlusive crises in patients with sickle cell anaemia
Sildenafil should not be used in patients with pulmonary hypertension secondary to sickle cell anaemia. In a clinical study events of vaso-occlusive crises requiring hospitalisation were reported more commonly by patients receiving REVATIO than those receiving placebo leading to the premature termination of this study.
The safety of sildenafil has not been studied in the following sub-groups of patients and its use is therefore contraindicated:
- Severe hepatic impairment,
- Recent history of stroke or myocardial infarction, or life-threatening arrhythmia
- Patients with coronary artery disease causing unstable angina;
- Severe hypotension (blood pressure < 90/50 mmHg) at initiation.
- The co-administration of PDE5 inhibitors, including REVATIO, with guanylate cyclase stimulators, such as riociguat, is contraindicated as it may lead to potentially life-threatening episodes of symptomatic hypotension or syncope.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
General
REVATIO (sildenafil citrate) is not recommended in the following cases:
- Pulmonary vasodilators may significantly worsen the cardiovascular status of patients with pulmonary veno-occlusive disease. Since there are no clinical data on administration of REVATIO to patients with venous occlusive disease, administration of REVATIO to such patients is not recommended.
- The efficacy of sildenafil in patients already on bosentan therapy has not been conclusively demonstrated (6-minute walk distance (6MWD)). No benefit of sildenafil coadministered with bosentan was demonstrated over bosentan alone. The results of the 6MWD were different between primary PAH (PPH) and PAH associated with CTD. In PAH associated with CTD patients, on average, there was a reduction of 6MWD in sildenafil-bosentan group as compared to bosentan alone (-18.32m vs. 17.50m). The concomitant administration of sildenafil and bosentan is not an optimal choice in PPH patients stable on bosentan therapy and the use of sildenafil with bosentan is not recommended in patients with PAH associated with CTD (see DRUG INTERACTIONS, Drug-Drug Interactions and DETAILED PHARMACOCOLGY, Human, Pharmacodynamic Studies).
Before prescribing REVATIO, it is important to note the following:
- In clinical trials, sildenafil has been shown to have systemic vasodilatory properties that result in transient decreases in blood pressure (see ACTION AND CLINICAL PHARMACOLOGY). Prior to prescribing REVATIO, physicians should carefully consider whether their patients with certain underlying conditions could be adversely affected by such vasodilatory effects, for example patients with resting hypotension (BP <90/50), or with fluid depletion, severe left ventricular outflow obstruction, or autonomic dysfunction.
Sildenafil citrate is also marketed as VIAGRA for male erectile dysfunction.
When used to treat male erectile dysfunction, non-arteritic anterior ischaemic optic neuropathy (NAION) has been reported rarely post-marketing in temporal association with the use of all phosphodiesterase type-5 inhibitors. NAION, a rare condition, can result in varying degrees of permanent loss of vision, for which there is no treatment. Most, but not all of these patients had underlying risk factors for the development of NAION, including but not necessarily limited to: low cup to optic disc ratio (the “crowded disc at risk”), age over 50, diabetes, hypertension, coronary artery disease, hyperlipidaemia and smoking. An observational study evaluated whether recent, episodic use of PDE5 inhibitors (as a class), typical of erectile dysfunction treatment, was associated with acute onset of NAION. The results suggest an approximately 2-fold increase in the risk of NAION within 5 half-lives of PDE5 inhibitor use. Based on published literature, the annual incidence of NAION is 2.5-11.8 cases per 100,000 males aged ≥ 50 per year in the general population. In case of sudden visual loss, patients should be advised to stop taking sildenafil and consult a physician immediately.
Individuals who have already experienced NAION are at increased risk of NAION recurrence. Therefore physicians should discuss this risk with these patients and whether they could be adversely affected by use of PDE5 inhibitors. PDE5 inhibitors, including sildenafil should be used with caution in these patients and only when the anticipated benefits outweigh the risks.
There is evidence that patients at risk for NAION may have abnormal optic discs (e.g. crowded disc) prior to development of the condition. If physicians are concerned about the overall risk of NAION, they should consider discussing these concerns with an ophthalmologist.
Physicians should advise patients to stop use of REVATIO and seek medical attention in the event of a sudden loss of vision in one or both eyes.
Administration of REVATIO (a PDE5 inhibitor) to patients with previously diagnosed NAION is contraindicated (see CONTRAINDICATIONS).
- There are no controlled clinical data on the safety or efficacy of REVATIO in patients with retinitis pigmentosa (a minority of these patients have genetic disorders of retinal phosphodiesterases) (see ACTION AND CLINICAL PHARMACOLOGY). If prescribed, this should be done with caution.
- Rare cases of central serous chorioretinopathy have been reported post-marketing in temporal association with the use of sildenafil citrate. It is not known if medical and other facts were reported that may have also played a role in the development of the condition. It is not possible to determine whether the development of the condition was related directly to the use of sildenafil, to the patient’s possibly underlying risk factors, a combination of these factors, or to other factors. (See POST-MARKET ADVERSE DRUG REACTIONS).
- Alpha-blockers: Caution is advised when Phosphodiesterase Type 5 (PDE5) inhibitors are co-administered with alpha-blockers. PDE5 inhibitors, including sildenafil, and alpha-adrenergic blocking agents are both vasodilators with blood pressure lowering effects. When vasodilators are used in combination, an additive effect on blood pressure may be anticipated. In some patients, concomitant use of these two drug classes can lower blood pressure significantly, leading to symptomatic hypotension. In the sildenafil interaction studies with alpha-blockers (see DRUG INTERACTIONS), cases of symptomatic hypotension consisting of dizziness and lightheadedness were reported. In order to minimize the potential for developing postural hypotension, patients should be hemodynamically stable on alpha-blocker therapy prior to initiating sildenafil treatment. Physicians should advise patients what to do in the event of postural hypotensive symptoms. No cases of syncope or fainting were reported during these interaction studies. Consideration should be given to the fact that safety of combined use of PDE5 inhibitors and alpha-blockers may be affected by other variables, including intravascular volume depletion and concomitant use of anti-hypertensive drugs.
REVATIO should be used with caution in patients with anatomical deformation of the penis (such as angulation, cavernosal fibrosis or Peyronie’s disease) or in patients who have conditions, which may predispose them to priapism (such as sickle cell anemia, multiple myeloma or leukemia).
Prolonged erections and priapism have been reported with sildenafil in post-marketing experience. In the event of an erection that persists longer than 4 hours, the patient should seek immediate medical assistance. If priapism is not treated immediately, penile tissue damage and permanent loss of potency could result (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
- In humans, sildenafil has no effect on bleeding time when taken alone or with acetylsalicyclic acid. In vitro studies with human platelets indicate that sildenafil potentiates the anti-aggregatory effect of sodium nitroprusside (a nitric oxide donor). The combination of heparin and sildenafil had an additive effect on bleeding time in the anesthetized rabbit, but this interaction has not been studied in humans (see DRUG INTERACTIONS, ACTION AND CLINICAL PHARMACOLOGY, DETAILED PHARMACOLOGY).
- The incidence of epistaxis was higher in patients with PAH secondary to CTD (sildenafil 12.9%, placebo 0%) than in PPH patients (sildenafil 2.3%, placebo 2.4%). Incidence was also higher in sildenafil-treated patients with concomitant oral Vitamin K antagonist (8.8% versus 1.7% not treated with concomitant Vitamin K antagonist).
- There is no safety information on the administration of REVATIO to patients with bleeding disorders or active peptic ulceration. Therefore, REVATIO should be administered with caution to these patients.
- The safety and efficacy of sildenafil when co-administered with other PDE5 inhibitor products, including VIAGRA, has not been studied in PAH patients and such concomitant use is not recommended (see DRUG INTERACTIONS, Serious Drug Interactions).
Cardiovascular
There is no controlled clinical data on the safety or efficacy of REVATIO in the following groups, if prescribed, this should be done with caution:
- Patients with hypertension (BP >170/110);
Cardiovascular risk factors
In post-marketing experience with sildenafil for male erectile dysfunction, serious cardiovascular events, including myocardial infarction, unstable angina, sudden cardiac death, ventricular arrhythmia, cerebrovascular haemorrhage, transient ischaemic attack, hypertension and hypotension have been reported in temporal association with the use of sildenafil. Most, but not all, of these patients had pre-existing cardiovascular risk factors. Many events were reported to occur during or shortly after sexual intercourse and a few were reported to occur shortly after the use of sildenafil without sexual activity. It is not possible to determine whether these events are related directly to these factors or to other factors (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Otologic
Sudden decrease or loss of hearing has been reported in a few numbers of postmarketing cases with the use of PDE5 inhibitors, including REVATIO. These events, which may be accompanied by tinnitus and dizziness, have been reported in temporal association to the intake of PDE5 inhibitors, including REVATIO. In some of the cases, medical conditions and other factors were reported that may have also played a role in the otologic adverse events. In many cases, medical follow-up information was limited. It is not possible to determine whether these events are related directly to the use of PDE5 inhibitors or to other factors (see POST-MARKET ADVERSE DRUG REACTIONS). Physicians should advise patients to seek prompt medical attention in case of sudden decrease or loss of hearing.
Skin / Appendages
Rare cases of Stevens-Johnson’s Syndrome (SJS), Toxic Epidermal Necrolysis (TEN) and Erythema Multiforme (EM) have been reported during the post-marketing period.
Special Populations
Pregnant Women: No evidence of teratogenicity, embryotoxicity or fetotoxicity was observed in rats and rabbits, which received up to 200 mg/kg/day during organogenesis. There are no data from the use of sildenafil in pregnant women. Studies in animals have shown toxicity with respect to postnatal development. (see TOXICOLOGY).
Due to lack of data, REVATIO should not be used in pregnant women unless strictly necessary.
Nursing Women: There are no adequate and well-controlled studies in lactating women. Limited data indicate that sildenafil and its active metabolite are excreted into breast milk at very low levels. Prescribers should carefully assess the mother’s clinical need for REVATIO and any potential adverse effects on the breastfed child.
Fertility:
Non-clinical data revealed no special hazard for humans based on conventional studies of fertility.
Pediatrics (< 18 years old): REVATIO is not indicated for use in children less than 18 years of age.
In a long-term trial in pediatric patients with PAH, an increase in mortality with increasing REVATIO dose was observed. Deaths were first observed after about 1 year of treatment, and causes of death were typical of patients with PAH (See INDICATIONS AND CLINICAL USE and ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, Pediatric Clinical Trial Safety Data).
Geriatrics (≥ 65 years): Healthy elderly volunteers had a reduced clearance of sildenafil, but studies did not include sufficient numbers of subjects to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in response between the elderly and younger pulmonary arterial hypertension patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION).
Combination Sildenafil Citrate + Epoprostenol: (see ADVERSE REACTIONS and Drug-Drug Interactions)
No clinical data are available for sildenafil intravenous administration in patients who are clinically or haemodynamically unstable. Its use is accordingly not recommended in these patients.
Information for Patients
Physicians should discuss with patients the contraindication of REVATIO with regular and/or intermittent use of organic nitrates.
Physicians should advise patients to stop use of REVATIO and seek immediate medical attention in the event of a sudden loss of vision in one or both eyes. Such an event may be a sign of non-arteritic anterior ischemic optic neuropathy (NAION), a cause of decreased vision including permanent loss of vision, that has been reported rarely post-marketing in temporal association with the use of all PDE5 inhibitors when used in the treatment of male erectile dysfunction. Should the vision loss be diagnosed as NAION, continued use of REVATIO is not recommended (see WARNINGS AND PRECAUTIONS, General).
Effects on ability to drive and use machines:
As dizziness and altered vision were reported in clinical trials with sildenafil, patients should be aware of how they might be affected by REVATIO, before driving or operating machinery. The effect of sildenafil on the ability to drive and use machinery has not been studied.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Sildenafil Oral Administration:
Safety data on REVATIO (sildenafil citrate) were obtained from a single pivotal study, consisting of 68 (25%) men and 209 (75%) women, and an open-label extension study in 277 treated patients with pulmonary arterial hypertension. The 259 subjects who completed the pivotal study entered a long-term extension study. Doses up to 80 mg three times a day were studied and after 3 years 87% of 183 patients on treatment were receiving REVATIO 80 mg t.i.d..
The overall frequency of discontinuation in REVATIO-treated patients at the recommended daily dose of 20 mg t.i.d. was low (2.9%) and the same as placebo (2.9%).
Sildenafil Intravenous Administration:
Undesirable effects that resulted from intravenous REVATIO use are similar to those associated with oral REVATIO use. Since there are limited data for intravenous REVATIO use and since pharmacokinetic models predict that 20 mg oral and 10 mg intravenous formulations will yield similar plasma exposures, the safety information for intravenous REVATIO is supported by that of oral REVATIO (see ACTION AND CLINICAL PHARMACOLOGY- Pharmacokinetics).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Sildenafil Oral Administration:
In the pivotal placebo-controlled trial in pulmonary arterial hypertension, the adverse drug reactions that occurred in at least 3% of REVATIO-treated patients at any of the 20, 40, or 80 mg t.i.d. doses, and more commonly on REVATIO than on placebo, are shown in Table 1.
Table 1. Sildenafil Adverse Events More Frequent than Placebo in ≥ 3% of Patients (N ≥ 2
Patients) Reported in Percentage
ADVERSE EVENT (%) | Placebo (N=70) | SILDENAFIL TREATMENT GROUPS | |||
| 20 mg (N=69) | 40 mg (N=67) | 80 mg (N=71) | Total (N=207) | ||
| Headache | 39 | 46 | 42 | 49 | 46 |
| Flushing | 4 | 10 | 9 | 16 | 12 |
| Dyspepsia | 7 | 13 | 8 | 13 | 11 |
| Back pain | 11 | 13 | 13 | 9 | 12 |
| Diarrhea | 6 | 9 | 12 | 10 | 10 |
| Pain in extremity | 6 | 7 | 15 | 9 | 10 |
| Myalgia | 4 | 7 | 6 | 14 | 9 |
| Cough | 6 | 7 | 5 | 9 | 7 |
| Epistaxis | 1 | 9 | 8 | 4 | 7 |
| Pyrexia | 3 | 6 | 3 | 10 | 6 |
| Influenza | 3 | 6 | 6 | 4 | 5 |
| Vertigo | 1 | 1 | 5 | 3 | 3 |
| Gastritis | 0 | 3 | 3 | 4 | 3 |
| Erythema | 0 | 6 | 2 | 1 | 3 |
| Insomnia | 1 | 7 | 6 | 4 | 6 |
| Visual disturbance | 0 | 0 | 5 | 7 | 4 |
| Dyspnea (exacerbated) | 3 | 7 | 2 | 1 | 3 |
| Sinusitis | 0 | 3 | 5 | 1 | 3 |
| Paresthesia | 0 | 3 | 5 | 1 | 3 |
| Rhinitis | 0 | 4 | 2 | 3 | 3 |
In a placebo-controlled fixed dose titration study of REVATIO (starting with recommended dose of 20 mg t.i.d. and increased to 40 mg t.i.d. and then 80 mg t.i.d.) as an adjunct to intravenous epoprostenol in pulmonary arterial hypertension, the clinically meaningful adverse drug reactions that were reported by at least 2% of patients in the REVATIO arm are shown in Table 2. The duration of treatment was 16 weeks. The overall frequency of discontinuations in sildenafil/epoprostenol treated patients due to adverse events was 5.2% compared to 10.7% in the placebo/epoprostenol treated patients. There were 242 subjects who completed the initial study and entered a long-term extension study. Doses up to 80 mg three times a day were studied and after 3 years 68% of 133 patients on treatment were receiving REVATIO 80 mg t.i.d..
Table 2. Sildenafil-Epoprostenol all causality adverse events reported by ≥ 2% of sildenafil treated patients and more frequent than placebo.
| Adverse Event | Percentage of Subjects Reporting Event | ||||
|---|---|---|---|---|---|
Placebo + epoprostenol (N=131) | Sildenafil + epoprostenol (N=134) | ||||
Blood and lymphatic system disorders Anaemia | 3.1 | 4.5 | |||
Cardiac disorders Palpitations | 6.1 | 7.5 | |||
Endocrine disorders Hyperthyroidism | 0.8 | 2.2 | |||
Eye disorders Chromatopsia Ocular hyperaemia Vision blurred | 0 0 1.5 | 5.2 2.2 4.5 | |||
Gastrointestinal disorders Abdominal distension Diarrhoea Dry mouth Gastrooesophageal reflux disease Nausea Rectal haemorrhage Vomiting | 0.8 18.3 0 0.8 18.3 0 9.9 | 3 25.4 3.7 6 34.3 2.2 14.9 | |||
General disorders and administration site conditions Asthenia Chest pain Chills Malaise Oedema Pain | 20.6 9.9 0 0.8 13 2.3 | 23.9 14.2 5.2 2.2 24.6 4.5 | |||
Infections and infestations Bronchitis Cellulitis Gastroenteritis Upper respiratory tract infection | 0.8 1.5 0.8 9.2 | 3.7 3.7 2.2 15.7 | |||
Investigations International normalised ratio increased | 3.1 | 5.2 | |||
| Metabolism and nutrition disorders | |||||
| Adverse Event | Percentage of Subjects Reporting Event |
|---|
Placebo + epoprostenol (N=131) | Sildenafil + epoprostenol (N=134) | |
|---|---|---|
Anorexia Hypervolaemia | 1.5 1.5 | 4.5 3.7 |
Musculoskeletal and connective tissue disorders Arthralgia Back pain Myalgia Pain in extremity Pain in jaw Shoulder pain | 2.3 3.1 5.3 6.1 8.4 1.5 | 6.7 4.5 9.7 17.2 10.4 2.2 |
Nervous system disorders Dizziness Headache Hypoaesthesia | 19.1 33.6 1.5 | 20.9 56.7 3 |
Psychiatric disorders Anxiety | 1.5 | 3 |
Renal and urinary disorders Renal failure | 1.5 | 2.2 |
Respiratory, thoracic and mediastinal disorders Epistaxis Haemoptysis Hypoxia Nasal congestion | 5.3 1.5 1.5 2.3 | 9 2.2 3 9 |
Skin and subcutaneous tissue disorders Rash | 10.7 | 17.2 |
Vascular disorders Flushing Hypotension | 13 6.1 | 19.4 9 |
Sildenafil Intravenous Administration
In a placebo-controlled study of intravenous REVATIO in pulmonary hypertension, a total of 66 patients were treated with REVATIO resulting in plasma concentrations up to a minimum of 8 times the predicted Cmax in healthy volunteers for the recommended intravenous dose of 10 mg. Nineteen (19) patients received placebo. The study population consisted of patients with PAH, pulmonary venous hypertension (PVH) and pulmonary hypertension secondary to COPD. The subjects received increases in dose to achieve plasma concentrations from 10 ng/mL to 500 ng/mL. The commonly reported treatment-related adverse reactions (>1/100, <1/10 and in more than 1 subject) were vasodilatation (flushing) (6%), headache (3%), hypotension (3%) and nausea (3%). In the PAH group, the commonly reported treatment-related adverse events (>1/100, <1/10 and in more than 1 subject) were vasodilatation (6%) and nausea (6%). The adverse events were generally mild to moderate in severity. The adverse event profile for intravenous REVATIO in adults with PAH was consistent with the adverse event profile for oral REVATIO in the same patient population.
Solution
Study A1481262 was a single center, open label study to assess the safety, tolerability and pharmacokinetics of a single intravenous dose of sildenafil (10 mg) administered as a bolus injection to patients with PAH who were stable on oral REVATIO 20 mg t.i.d..
A total of 10 PAH subjects enrolled and completed the study. The mean postural changes in systolic and diastolic blood pressure over time were small (< 10 mmHg) and returned towards baseline beyond 2 hours. No symptoms of hypotension were associated with these changes. The mean changes in heart rate were clinically insignificant. Two subjects experienced a total of 3 adverse reactions (flushing, flatulence and hot flush). There was one serious adverse event in a subject with severe ischaemic cardiomyopathy who experienced ventricular fibrillation and death 6 days post study drug; the event was judged to be unrelated to study drug.
Post-Market Adverse Drug Reactions
Cardio-vascular system
In post-marketing experience with sildenafil citrate at doses indicated for male erectile dysfunction (MED), serious cardiovascular, cerebrovascular, and vascular events, including myocardial infarction, sudden cardiac death, ventricular arrhythmia, cerebrovascular hemorrhage, transient ischemic attack, hypertension, pulmonary hemorrhage, and subarachnoid and intracerebral hemorrhages have been reported in temporal association with the use of the drug. Most, but not all, of these patients had preexisting cardiovascular risk factors. Many of these events were reported to occur during or shortly after sexual activity, and a few were reported to occur shortly after the use of sildenafil without sexual activity. Others were reported to have occurred hours to days after use concurrent with sexual activity. It is not possible to determine whether these events are related directly to sildenafil citrate, to sexual activity, to the patient’s underlying cardiovascular disease, or to a combination of these or other factors.
Nervous System: seizure, seizure recurrence, transient global amnesia
Otologic system: Cases of sudden decrease or loss of hearing have been reported post-marketing in temporal association with the use of PDE5 inhibitors, including REVATIO. In some of the cases, medical conditions and other factors were reported that may have also played a role in the otologic adverse events. In many cases, medical follow-up information was limited. It is not possible to determine whether these events are related directly to the use of REVATIO, to the patient’s underlying risk factors for hearing loss, a combination of these factors, or to other factors (see WARNINGS AND PRECAUTIONS).
Rare cases of central serous chorioretinopathy have been reported post-marketing in temporal association with the use of sildenafil citrate. It is not known if medical and other factors were reported that may have also played a role in the development of the condition. It is not possible to determine whether the development of the condition was related directly to the use of sildenafil, to the patient’s possibly underlying risk factors, a combination of these factors, or to other factors. (See WARNINGS AND PRECAUTIONS).
Skin / Appendages: Stevens-Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN) and Erythema Multiforme (EM).
Reproductive system and breast disorders: priapism, erection increased and prolonged.
Pediatric Clinical Trial Safety Data
Pulmonary arterial hypertension
Adverse reactions reported in ≥ 3% of 229 subjects treated with sildenafil (combined dose group) were:
From a data-cut > 7 years after the start of a placebo-controlled safety study in patients 1 to 17 years of age with PAH, there were a total of 42 deaths reported which were dose-dependent. The following AEs occurred in the trial:
Eye Disorders: visual impairment (3%)
Gastrointestinal disorders: vomiting (22%), diarrhea (15%), nausea (9%), dyspepsia (6%) General disorders and administration site conditions: pyrexia (17%)
Investigations: blood pressure diastolic decreased
Musculoskeletal and connective tissue disorders: pain in extremity (4%);
Nervous system disorders: headache (26%)
Respiratory, thoracic, and mediastinal disorders: epistaxis (12%), rhinorrhea (3%)
Respiratory Infection and infestations: upper respiratory tract infection (31%), bronchitis (20%), pharyngitis (18%), influenza (12%), pneumonia (10%)
Most of these adverse reactions were considered mild to moderate in severity.
Persistent pulmonary hypertension of the newborn
A randomized, double-blind, two-arm, parallel-group, placebo-controlled study was conducted in 59 neonates with persistent pulmonary hypertension of the newborn (PPHN), or hypoxic respiratory failure (HRF) and at risk for PPHN with oxygenation index (OI) >15 and <60. The primary objective was to evaluate the efficacy and safety of IV sildenafil when added to inhaled nitric oxide (iNO) compared with iNO alone. Administration of IV sildenafil when added to iNO did not result in a statistically significant difference in treatment failure rates. IV sildenafil should not be used in neonates with PPHN as benefits do not outweigh the risks.
Treatment-emergent adverse events of all causalities and serious adverse events were reported in 22 (75.9%) and 7 (24.1%) subjects in the iNO + IV sildenafil treatment group, respectively, and in 19 (63.3%) and 2 (6.7%) subjects in the iNO + placebo group, respectively. The most commonly reported treatment-emergent adverse events of all causalities were hypotension (8 [27.6%] subjects), hypokalemia (7 [24.1%] subjects), anemia and drug withdrawal syndrome (4 [13.8%] subjects each) and bradycardia (3 [10.3%] subjects) in the iNO + IV sildenafil treatment group and pneumothorax (4 [13.3%] subjects), anemia, edema, hyperbilirubinemia, C-reactive protein increased, and hypotension (3 [10.0%] subjects each) in the iNO + placebo treatment group. Most events in both treatment groups were mild in intensity.
DRUG INTERACTIONS
Serious Drug Interactions
|
Overview
In vitro studies:
Sildenafil metabolism is principally mediated by the cytochrome P-450 (CYP) isoforms 3A4 (major route) and 2C9 (minor route) (see ACTION AND CLINICAL PHARMACOLOGY). Therefore inhibitors of these isoenzymes may reduce sildenafil clearance and inducers of these isoenzymes may increase sildenafil clearance.
Sildenafil is a weak inhibitor of the cytochrome P450 isoforms 1A2, 2C9, 2C19, 2D6, 2E1 and 3A4 (IC50 >150 mM). Sildenafil is not expected to affect the pharmacokinetics of compounds which are substrates of these CYP enzymes at clinically relevant concentrations.
In vivo studies:
Sildenafil (50 mg) did not potentiate the hypotensive effect of alcohol in healthy volunteers with mean maximum blood alcohol levels of 0.08%.
The drugs listed are based on either drug interaction case reports or studies, or predicted interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Drug-Drug Interactions
Unless otherwise specified, drug interaction studies have been performed in healthy adult male subjects using oral sildenafil. These results are relevant to other populations and routes of administration.
Table 3 – Established or Potential Drug-Drug Interactions
| Proper Name | Ref | Effect | Clinical comment |
| Cimetidine (800 mg) | CT | Cimetidine, a nonspecific CYP inhibitor, caused a 56% increase in plasma sildenafil concentrations when co-administered with sildenafil (50 mg) to healthy volunteers. | Close monitoring is advised. |
Macrolide antibiotics Erythromycin Clarithromycin and telithromycin | CT T | When a single 100 mg dose of sildenafil was co-administered with erythromycin, a moderate CYP3A4 inhibitor, at steady state (500 mg twice daily [b.i.d.] for 5 days), there was a 182% increase in sildenafil systemic exposure (AUC). Potent CYP3A4 inhibitors like clarithromycin and telithromycin are expected to have an effect in between that of ritonavir and moderate CYP3A4 inhibitors like saquinavir or erythromycin, a seven-fold increase in exposure is assumed. | A downward dose adjustment to 20 mg twice a day should be considered when sildenafil is co-administered to patients already receiving moderate CYP3A4 inhibitors like erythromycin or saquinavir. Concomitant administration of sildenafil with these CYP3A4 inhibitors is not recommended. |
| Nefazodone | T | Potent CYP3A4 inhibitors like nefazodone are expected to have an effect in between that of ritonavir and moderate CYP3A4 inhibitors like saquinavir or erythromycin, a seven-fold increase in exposure is assumed. | Concomitant administration of sildenafil with these CYP3A4 inhibitors is not recommended. |
Azole antifungals Ketoconazole and itraconazole | T | The most potent CYP3A4 inhibitors such as ketoconazole or itraconazole will have effects similar to those of ritonavir, i.e. increase of exposure (AUC) to sildenafil by 11-fold. (see CONTRAINDICATIONS and DOSAGE AND ADMINISTRATION) | Concomitant administration of sildenafil with these most potent CYP3A4 inhibitors is contraindicated. |
HIV Protease Inhibitors Saquinavir | CT | In a study performed in healthy volunteers, co-administration of the HIV protease inhibitor saquinavir, a moderate CYP3A4 inhibitor, at steady state (1200 mg t.i.d.) with sildenafil (100 mg single dose) resulted in a 140% increase in sildenafil Cmax and a 210% increase in sildenafil AUC. (see DOSAGE AND ADMINISTRATION). In the study of healthy volunteers, sildenafil (100 mg) did not affect the steady-state pharmacokinetics of the HIV protease inhibitors saquinavir (1200 mg t.i.d). | Safety monitoring is advised and a downward dose adjustment to 20 mg twice a day should be considered when sildenafil is co-administered to patients already receiving moderate CYP3A4 inhibitors like saquinavir. |
| Ritonavir | CT | In healthy volunteers, co-administration with the HIV protease inhibitor ritonavir (a highly potent P450 inhibitor) at steady state (500 mg b.i.d.) with sildenafil (100 mg single dose) resulted in a 300% (4-fold) increase in sildenafil Cmax and a 1000% (11-fold) increase in sildenafil plasma AUC. At 24 hours, the plasma levels of sildenafil were still approximately 40-fold compared to approximately when sildenafil was dosed alone. This is consistent with ritonavir's marked effects on a broad range of P450 substrates (see CONTRAINDICATIONS and DOSAGE AND ADMINISTRATION). In a study of healthy volunteers, sildenafil (100 mg did not affect the steady-state pharmacokinetics of the HIV protease inhibitors ritonavir (500 mg b.i.d). Although the interaction between other protease inhibitors and REVATIO has not been studied, their concomitant use is expected to increase sildenafil levels. | Concomitant administration of sildenafil with the most potent CYP3A4 inhibitors such as ritonavir is contraindicated. |
| Mild to moderate CYP3A4 Inhibitors | CT | A population pharmacokinetic analysis of data from patients in clinical trials indicated an approximately 30% reduction in sildenafil clearance when sildenafil was co-administered with mild/moderate CYP3A4 inhibitors. | Sildenafil exposure without concomitant medication is shown to be 5-fold higher at a dose of 80 mg t.i.d. compared to its exposure at a dose of 20 mg t.i.d.. Safety monitoring is advised and a downward dose adjustment to 20 mg twice a day should be considered when sildenafil is co-administered to patients already receiving moderate CYP3A4 inhibitors. |
| Beta Blockers | CT | A population pharmacokinetic analysis of data from patients in clinical trials indicated an approximately 34% reductions in sildenafil clearance when co-administered with beta-blockers, thus leading to 1.5 fold increase of sildenafil concentration. | Safety monitoring is advised and a downward dose adjustment may be necessary. |
| CYP3A4 Inducers | CT | A population pharmacokinetic analysis of data from patients in clinical trials indicated an approximately 3-fold increase in sildenafil clearance when sildenafil was co-administered with mild CYP3A4 inducers, which is consistent with the effect of bosentan on sildenafil clearance in healthy volunteers. | Concomitant administration of potent CYP3A4 inducers is expected to cause substantial decreases in plasma levels of sildenafil. Safety monitoring is required and dose adjustment (increase) may be necessary. |
| Bosentan | CT | In a study of healthy male volunteers, co-administration of sildenafil at steady state (80 mg t.i.d.) with the endothelin antagonist bosentan (a moderate inducer of CYP3A4, CYP 2C9 and possibly of cytochrome P450 2C19) at steady state (125 mg b.i.d.) resulted in a 62.6% decrease of sildenafil AUC and a 55.4% decrease in sildenafil Cmax. The combination of both drugs did not lead to clinically significant changes of blood pressure (supine and standing) and was well tolerated in healthy volunteers. Sildenafil at steady state (80 mg t.i.d.) resulted in a 49.8% increase in AUC and a 42% increase in Cmax of bosentan (125 mg b.i.d.). The efficacy of sildenafil in patients already on bosentan therapy has not been conclusively demonstrated (6-minute walk distance (6MWD)). No benefit of sildenafil co-administered with bosentan was demonstrated over bosentan alone. The results of the 6MWD were different between primary PAH (PPH) and PAH associated with CTD. In PAH associated with CTD patients, there was a reduction of 6MWD in sildenafil-bosentan group as compared to bosentan alone (-18.32 m vs. 17.50 m). | There are no data to support increasing the dose of sildenafil in combination with bosentan. Concomitant administration of sildenafil with bosentan in PAH with CTD subgroup of patients is not recommended. |
Alpha-blocker Doxazosin | CT | In drug-drug interaction studies, sildenafil (25 mg, 50 mg, or 100 mg) and the alpha-blocker doxazosin (4 mg or 8 mg) were administered simultaneously to patients with benign prostatic hyperplasia (BPH) stabilized on doxazosin therapy. In these study populations, mean additional reductions of supine systolic and diastolic blood pressure of 7/7 mmHg, 9/5 mmHg, and 8/4 mmHg, respectively, were observed. Mean additional reductions of standing blood pressure of 6/6 mmHg, 11/4 mmHg, and 4/5 mmHg, respectively, were also observed. There were infrequent reports of patients who experienced symptomatic postural hypotension. These reports included dizziness and light-headedness, but not syncope (see PRECAUTIONS). Concomitant administration of single doses of doxazosin (4 or 8 mg) and sildenafil (25 or 50 mg) did not produce any clinically relevant effect on each other’s pharmacokinetic parameters (AUC, Cmax, Tmax). | Caution is advised when sildenafil is co-administered with alpha-blockers. Safety monitoring is required and dose adjustment (decrease) may be necessary. |
| Oral Contraceptive | CT | Concomitant administration of oral contraceptives (ethinyl estradiol 30 μg and levonorgestrel 150 μg) did not affect the pharmacokinetics of sildenafil. Sildenafil had no impact on the plasma levels of oral contraceptives (ethinyl estradiol 30 μg and levonorgestrel 150 μg). |
|
| Antacid | CT | Single doses of antacid (magnesium hydroxide/aluminum hydroxide) did not affect the bioavailability of sildenafil. |
|
| Amlodipine | CT | When sildenafil 100 mg oral was co-administered with amlodipine, 5 mg or 10 mg oral, to hypertensive patients, the mean additional reduction on supine blood pressure was 8 mmHg systolic and 7 mmHg diastolic. | Safety monitoring is required and dose adjustment (decrease) may be necessary. |
CYP2C9 Substrates Tolbutamide or warfarin | CT | No significant interactions were shown with tolbutamide (single 250 mg dose) or warfarin (single 40 mg dose), both of which are metabolized by CYP2C9, when co-administered with 50 mg sildenafil. |
|
| Acenocoumarol | CT | No interactions were observed between sildenafil (100 mg single dose) and acenocoumarol. |
|
C = Case Study; CT = Clinical Trial; T = Theoretical
Effects of Other Drugs on REVATIO Intravenous Administration
Predictions based on a pharmacokinetic model suggest that drug-drug interactions with CYP3A4 inhibitors should be less than observed after oral sildenafil administration. The magnitude of the interaction is expected to be reduced for intravenous sildenafil, as interactions for oral sildenafil are due, at least in part, to effects on oral first pass metabolism.
Drug-Food Interactions
Grapefruit juice is a weak inhibitor of CYP3A4 gut wall metabolism and co-administration results in 1.23-fold higher sildenafil exposure (AUC) with no change in peak plasma concentrations.
Alcohol has the potential for interaction with REVATIO. Sildenafil (50 mg) did not potentiate the hypotensive effects of alcohol in healthy volunteers with mean maximum blood alcohol levels of 0.08% (80 mg/dL). However, patients taking PDE5 inhibitors, including sildenafil, should avoid consuming alcohol, which may increase the potential for orthostatic signs and symptoms including increase in heart rate, decrease in standing blood pressure, dizziness, and headache.
Drug-Herb Interactions
Efficacy of sildenafil should be closely monitored in patients using concomitant St-Johns’s wort, a CYP3A4 inducer.
| Acetylsalicyclic acid | CT | Sildenafil (50 mg) did not potentiate the increase in bleeding time, measured using a standard simplate method, caused by acetylsalicyclic acid (150 mg). |
|
| Epoprostenol | CT | Based on the population pharmacokinetic analysis of Study A1481141 (sildenafil + epoprostenol), a 27% of decrease in sildenafil bioavailability was estimated. In the analysis of this study data, the inter-subject variability in the relative bioavailability of sildenafil was estimated at 48.2 %. | The effect of epoprostenol on sildenafil exposure was not considered as clinically relevant. |
Drug-Laboratory Interactions
Interaction with laboratory tests has not been established. (See DOSAGE AND ADMINISTRATION)
DOSAGE AND ADMINISTRATION
Dosing Considerations
Dosing of REVATIO (sildenafil citrate) may be affected by the following:
- concomitant administration of alpha-blockers
- concomitant administration of potent CYP3A4 inhibitors (e.g. ketoconazole, itraconazole, ritonavir) and weak CYP3A4 inhibitors (e.g. grapefruit juice)
- co-administration with CYP3A4 inducers (e.g. rifampin) (see PRECAUTIONS, DRUG INTERACTIONS)
Recommended Dose and Dosage Adjustment
Adult Oral Dose:
The recommended dose of REVATIO oral administration is 20 mg three times a day (t.i.d.).
Adult Intravenous Dose:
The recommended dose of REVATIO intravenous administration is 10 mg (corresponding to 12.5 mL) three times a day administered as an intravenous bolus injection.
A 10 mg dose of REVATIO solution is predicted to provide exposure of sildenafil and its N-desmethyl metabolite and pharmacological effects comparable to those of a 20 mg oral dose.
Use in patients with renal and hepatic impairment:
No dose adjustments are required for renal impaired patients (including severe renal impairment, creatinine clearance <30 mL/min), and hepatic impaired patients (Child Pugh class A and B).
Patients using other medicinal products:
Co-administration of REVATIO with CYP3A4 inducers (e.g. potent inducers such as barbiturates, carbamazepine, phenytoin, efavirenz, nevirapine, rifampin, rifabutin) may alter plasma levels of either or both medications. Dosage adjustments may be necessary (see PRECAUTIONS).
Co-administration of most potent CYP3A4 inhibitors (e.g. ketoconazole, itraconazole, ritonavir) with REVATIO substantially increases serum concentrations of sildenafil and is therefore not recommended (see WARNINGS, DRUG INTERACTIONS).
A downward dose adjustment to 20 mg (10 mg if by intravenous injection) twice daily should be considered when sildenafil is co-administered to patients already receiving CYP3A4 inhibitors like erythromycin or saquinavir. A downward dose adjustment to 20 mg (10 mg if by intravenous injection) once daily is recommended in case of co-administration with more potent CYP3A4 inhibitors like clarithromycin, telithromycin and nefazodone.
Sildenafil was shown to potentiate the hypotensive effects of nitrates and its administration in patients who use nitric oxide donors, or nitrates in any form, is therefore contraindicated.
REVATIO may be used concomitantly in patients stabilized on epoprostenol (see ADVERSE REACTIONS and Drug-Drug Interactions).
Geriatric Use (≥ 65 years):
No dose adjustment is required. However, in general, dose selection for elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see ACTION AND CLINICAL PHARMACOLOGY).
Use in children:
REVATIO is not indicated for use in children less than 18 years of age.
Administration
Oral Dose Administration
REVATIO should be taken approximately 6-8 hours apart, with or without food.
Intravenous Dose Administration
REVATIO solution is for intravenous use as a bolus injection.
This medicinal product does not require dilution or reconstitution before use.
Do not administer more than 12.5 mL and dispose of all the remainder of the solution after use. Each dose requires a new vial.
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products or intravenous diluents.
OVERDOSAGE
In studies with healthy volunteers of single oral doses up to 800 mg, adverse events were similar to those seen at lower doses but incidence rates and severities were increased.
In cases of overdose, standard supportive measures should be adopted as required. Renal dialysis is not expected to accelerate clearance as sildenafil is highly bound to plasma proteins and it is not eliminated in the urine (see DETAILED PHARMACOLOGY).
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Sildenafil is a potent and selective inhibitor of cGMP specific phosphodiesterase type-5 (PDE5) in the smooth muscle of the pulmonary vasculature, where PDE5 is responsible for degradation of cGMP. Sildenafil, therefore, increases cGMP within pulmonary vascular smooth muscle cells resulting in relaxation. In patients with pulmonary hypertension, this can lead to selective vasodilation of the pulmonary vascular bed and, to a lesser degree, vasodilatation in the systemic circulation.
Studies in vitro have shown that sildenafil has between 10 and 10,000-fold greater selectivity for PDE5 than for other phosphodiesterase isoforms namely PDEs 1, 2, 3, 4, and 6 and greater than 700-fold effect on PDE7-PDE11. In particular, sildenafil has greater than 4,000-fold selectivity for PDE5 over PDE3, the cAMP-specific phosphodiesterase isoform involved in the control of cardiac contractility. Sildenafil is about 10-fold as potent for PDE5 compared to PDE6, an isoenzyme found in the retina; this lower selectivity is thought to be the basis for colour vision abnormalities observed with higher doses or plasma levels of sildenafil (see PRECAUTIONS, DETAILED PHARMACOLOGY).
In addition to pulmonary vascular smooth muscle and the corpus cavernosum, PDE5 is also found in other tissues including vascular and visceral smooth muscle and in platelets. The inhibition of PDE5 in these tissues by sildenafil may be the basis for the enhanced platelet anti-aggregatory activity observed in vitro, and the mild peripheral arterial-venous dilatation in vivo.
Pharmacodynamics
Effects of REVATIO (sildenafil citrate) on Blood Pressure-Oral Administration
Single oral doses of sildenafil (100 mg) administered to healthy volunteers produced decreases in supine blood pressure (mean maximum decrease in systolic/diastolic blood pressure of 8.3/5.3 mmHg). The decrease in blood pressure was most notable approximately 1-2 hours after dosing, and was not different than placebo at 8 hours. Similar effects on blood pressure were noted with 25 mg, 50 mg and 100 mg doses of sildenafil, therefore the effects are not related to dose or plasma levels within this dosage range. Larger effects were recorded among patients receiving concomitant nitrates (see CONTRAINDICATIONS, DETAILED PHARMACOLOGY).
Single oral doses of sildenafil up to 100 mg in healthy volunteers produced no clinically relevant effects on ECG. After chronic dosing of 80 mg t.i.d. to patients with pulmonary arterial hypertension, no clinically relevant effects on ECG were reported.
After chronic dosing of 80 mg t.i.d. sildenafil to healthy patients, the largest mean change from baseline in supine systolic and supine diastolic blood pressure was a decrease of 9.0 mmHg and 8.4 mmHg respectively.
After chronic oral dosing of 80 mg t.i.d. sildenafil to patients with systemic hypertension, the mean change from baseline in systolic and diastolic blood pressure was a decrease of 9.4 mmHg and 9.1 mmHg respectively.
After chronic oral dosing of 80 mg t.i.d. sildenafil to patients with pulmonary arterial hypertension, lesser effects in blood pressure reduction were observed (a reduction in both systolic and diastolic pressure of 2 mmHg). This may be due to improvements in cardiac output secondary to the beneficial effects of sildenafil on pulmonary vascular resistance.
In a study of the hemodynamic effects of a single oral 100 mg dose of sildenafil in 14 patients with severe coronary artery disease (CAD) (>70% stenosis of at least one coronary artery), the mean resting systolic and diastolic blood pressures decreased by 7% and 6% respectively compared to baseline. Mean pulmonary systolic blood pressure decreased by 9%. Sildenafil showed no effect on cardiac output, and did not impair blood flow through the stenosed coronary arteries.
Effects of REVATIO (sildenafil citrate) on Pulmonary Vascular Resistance and Other Heamodynamic Parameters-Intravenous Administration
The efficacy of intravenous sildenafil with or without inhaled nitric oxide (iNO) on pulmonary vascular resistance (PVR) in subjects with pulmonary hypertension was assessed in a randomised, placebo-controlled study. The primary diagnosis of all 85 subjects in Study A1481024 was pulmonary hypertension, 45 with PAH (35 treated with sildenafil, 10 placebo), 34 with PVH (25 treated with sildenafil, 9 placebo), and 6 with pulmonary hypertension secondary to COPD (6 treated with sildenafil). Sildenafil was effective at reducing the PVR and mPAP across all groups of patients. Specifically in the PAH group, the reduction in PVR showed a dose response across plasma concentrations of 10 to 100 ng/mL, but at concentrations of 100 to 500 ng/mL the reduction appeared to plateau. Mean absolute values of cardiac output increased after each dose in the sildenafil groups. There were reductions in systolic and diastolic blood pressure across the sildenafil groups; however, this was not clinically significant in subjects not receiving iNO. There were no clinically significant changes observed in heart rate across the different sildenafil plasma concentrations. There were no clinically significant changes in blood gases (PaO2, PaCO2, SvO2 and SpO2).
Effects of REVATIO (sildenafil citrate) on Persistent Pulmonary Hypertension or Hypoxic Respiratory Failure of the Newborn
A randomized, double-blind, two-arm, parallel-group, placebo-controlled study was conducted in 59 neonates with persistent pulmonary hypertension of the newborn (PPHN), or hypoxic respiratory failure (HRF) and at risk for PPHN with oxygenation index (OI) >15 and <60. The primary objective was to evaluate the efficacy and safety of IV sildenafil when added to inhaled nitric oxide (iNO) compared with iNO alone.
The co-primary endpoints were treatment failure rate, defined as need for additional treatment targeting PPHN, need for extracorporeal membrane oxygenation (ECMO), or death during the study; and time on iNO treatment after initiation of IV study drug for patients without treatment failure. The difference in treatment failure rates was not statistically significant between the two treatment groups (27.6% and 20.0% in the iNO + IV sildenafil group and iNO + placebo group, respectively). For patients without treatment failure, the mean time on iNO treatment after initiation of IV study drug was the same, approximately 4.1 days, for the two treatment groups.
Pharmacokinetics
REVATIO is rapidly absorbed after oral administration, with mean absolute bioavailability of about 41%. After oral three-times-daily (t.i.d.) dosing of REVATIO, AUC and Cmax increase in proportion with dose over the dose range of 20-40 mg t.i.d. After 80 mg t.i.d., a slightly more than dose-proportional increase of sildenafil plasma levels has been observed. It is eliminated predominantly by hepatic metabolism (mainly cytochrome P450 3A4) and is converted to an active metabolite with properties similar to the parent, sildenafil. The concomitant use of potent cytochrome P450 3A4 (CYP3A4) inhibitors (e.g. ritonavir ketoconazole, itraconazole) as well as the nonspecific CYP inhibitor, cimetidine, is associated with increased plasma levels of sildenafil (see DRUG INTERACTIONS, DOSAGE AND ADMINISTRATION, DETAILED PHARMACOLOGY). Both sildenafil and the metabolite have terminal half-lives of about 4 hours.
The pharmacokinetic profile of REVATIO solution has been characterized following intravenous administration. A 10 mg dose of REVATIO solution is predicted to provide exposure of sildenafil and its N-desmethyl metabolite and pharmacological effects comparable to those of a 20 mg oral dose.
Absorption: REVATIO is rapidly absorbed. Maximum observed plasma concentrations are reached within 30 to 120 minutes (median 60 minutes) of oral dosing in the fasted state. When REVATIO was administered with a high-fat meal, the rate of absorption was significantly decreased, with a 29% mean reduction in Cmax and a 60-minute mean delay in Tmax, however, the extent of absorption was not significantly affected (AUC decreased by 11%). This is not clinically relevant for chronic dosing in this patient population.
An intravenous dose of 10 mg is required in order to achieve plasma concentrations similar to those observed following oral administration of 20 mg.
Distribution: The mean steady state volume of distribution (Vss) for sildenafil is 105 L, indicating distribution into the tissues. Sildenafil and its major circulating N-desmethyl metabolite are both approximately 96% bound to plasma proteins. Protein binding is independent of total drug concentrations.
Based upon measurements of sildenafil in semen of healthy volunteers 90 minutes after dosing, less than 0.0002% (average 188 ng) of the administered dose may appear in the semen of patients.
Metabolism: Sildenafil is cleared predominantly by the CYP3A4 (major route) and CYP2C9 (minor route) hepatic microsomal isoenzymes. The major circulating metabolite (UK-103,320) results from N-desmethylation of sildenafil at the N-methyl piperazine moiety. This metabolite has a phosphodiesterase selectivity profile similar to sildenafil and an in vitro potency for PDE5 approximately 50% of the parent drug. In healthy volunteers, plasma concentrations of this metabolite are approximately 40% of those seen for sildenafil, so that the metabolite accounts for about 20% of sildenafil’s pharmacologic effects. In patients with pulmonary arterial hypertension, however, the ratio of UK-103,320 to sildenafil is higher. Plasma concentrations of UK-103,320 are approximately 72% those of sildenafil after 20 mg t.i.d. oral dosing (translating into a 36% contribution to sildenafil’s pharmacological effects). The subsequent effect on efficacy is unknown.
In healthy volunteers, the plasma levels of the N-desmethyl metabolite following intravenous dosing are significantly lower than those observed following oral dosing.
Excretion: The total body clearance of sildenafil is 41 L/h with a resultant terminal phase half-life of 3-5 hours. After either oral or intravenous administration, sildenafil is excreted as metabolites predominantly in the feces (approximately 80% of administered dose) and to a lesser extent in the urine (approximately 13% of the administered dose).
Special Populations and Conditions
Pediatrics: REVATIO is not indicated for use in children less than 18 years of age.
Geriatrics: Healthy elderly volunteers (65 years or over) had a reduced clearance of sildenafil, resulting in approximately 90% higher plasma concentrations of sildenafil and the active N-desmethyl metabolite compared to those seen in healthy younger volunteers (18-45 years). Due to age differences in plasma protein binding, the corresponding increase in free sildenafil plasma concentration was approximately 40%.
Gender: Comparison of the female PK data with historic control of male data resulted in ratios (90% CI) for Cmax and AUCt of 80% (65%; 99%) and 103% (85%; 124%) respectively with a difference (90% CI) in Tmax of 0.5h (0.2h; 0.8h). The average estimates for apparent oral clearance (CL/F) and volume of distribution (V/F) were similar for males (n=1335) and females (n=433). Therefore, there are no clinically significant gender differences in sildenafil pharmacokinetics.
Hepatic Impairment: In volunteers with hepatic cirrhosis (Child-Pugh A and B), sildenafil clearance was reduced, resulting in increases in AUC (85%) and C max (47%) compared to age-matched volunteers with no hepatic impairment. Patients with severe hepatic impairment (Child-Pugh class C) have not been studied.
Renal Impairment: In volunteers with mild (CLcr = 50-80 mL/min) and moderate (CLcr = 30-49 mL/min) renal impairment, the pharmacokinetics of a single oral dose of sildenafil (50 mg) were not altered. In volunteers with severe (CLcr < 30 mL/min) renal impairment, sildenafil clearance was reduced, resulting in AUC (100%) and Cmax (88%) compared to age-matched volunteers with no renal impairment. In addition, N-desmethyl metabolite AUC and Cmax values were significantly increased 200% and 79% respectively in subjects with severe renal impairment compared to subjects with normal renal function.
Population Pharmacokinetics: Age, gender, race, and renal and hepatic function were included as covariates in the population pharmacokinetic model to evaluate sildenafil pharmacokinetics in pulmonary arterial hypertension patients. The data set available for the population pharmacokinetic evaluation contained a wide range of demographic data and laboratory parameters associated with hepatic and renal function. None of these factors had a statistically significant impact on sildenafil pharmacokinetics in patients with pulmonary hypertension. However, CYP3A4 substrates reduced the apparent clearance of sildenafil, alone and in combination, with beta-blockers (by 22.3% and 37.4%, respectively). No other factor had a statistically significant influence on sildenafil pharmacokinetics.
In patients with pulmonary hypertension, the average steady state concentrations were 20-50% higher over the investigated dose range of 20-80 mg t.i.d., when compared to those of healthy volunteers. There was a doubling of Cmin levels compared to healthy volunteers. Both findings suggest a lower clearance and/or a higher oral bioavailability of sildenafil in patients with pulmonary hypertension compared to healthy volunteers.
STORAGE AND STABILITY
Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature].
SPECIAL HANDLING INSTRUCTIONS
Not Applicable.
DOSAGE FORMS, COMPOSITION AND PACKAGING
REVATIO (sildenafil citrate) is supplied as white, film-coated, round tablets and as a clear, colourless, sterile solution containing sildenafil citrate equivalent to the nominally indicated amount of sildenafil as follows:
| REVATIO Tablets | |||
| Package Configuration | Tablet Strength | Engraving on Tablet | |
| One Side | Other Side | ||
Blisters of 90 tablets (15 tablets per blister strip) | 20 mg (as sildenafil citrate) | RVT20 | PFIZER |
| REVATIO Solution | |||
| A 20 mL vial contains 12.5 mL of solution (10 mg of sildenafil, as citrate) | 0.8 mg/mL (as sildenafil citrate) | Type I glass vial with a chlorobutyl rubber stopper and an aluminium overseal | |
The tablet core contains microcrystalline cellulose, anhydrous dibasic calcium phosphate, croscarmellose sodium, magnesium stearate. The film coat contains hypromellose, titanium dioxide (E-171), lactose, triacetin.
The solution contains glucose and water for injection.
PART II : SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: sildenafil citrate
Chemical name:
Piperazine,1-[[3-(6,7-dihydro-1-methyl-7-oxo-3-propyl-1H-pyrazolo[4,3-d]pyrimidin-5-yl)-4-ethoxyphenyl]sulphonyl]-4-methyl-,2-hydroxy-1,2,3-propanetricarboxylate
Molecular formula and molecular mass:
C22H30N6O4S·C6H8O7; 666.7
Structural formula:
C N NH O2S N N CH3 H3CH2O O N N CH3 CH2CH2CH3 HOOC OH CO2H CO2H
Physicochemical properties: Sildenafil citrate is a white to off-white crystalline powder.
pka: protonation of tertiary amine 6.53 deprotonation of pyrimidirone moiety 9.17
Partition coefficient: octanol/water 2.7
Solubility (23 C): water 3.5 mg/mL
1M HCl 5.8 mg/mL
1M NaOH 42.3 mg/mL
CLINICAL TRIALS
Study Demographics and Trial Design
Table 4. Summary of patient demographics for Study A1481140
| Study # | ||||
| Trial design | ||||
Dosage, route of administration and duration (tablets/t.i.d./12 weeks) | ||||
| Study subjects (n=number) | Mean age (Range) | Gender (n=number) | ||
| Men | Women | |||
| A1481140 | ||||
| 12-week, multinational, multicenter randomized, double-blind, placebo-controlled study designed to assess the efficacy and safety of 3 doses of oral sildenafil (20, 40, and 80 mg t.i.d.) for the treatment of PAH | ||||
| Placebo | 70 | 49.1 | 13 | 57 |
| 20 mg | 69 | 47.2 | 20 | 49 |
| 40 mg | 67 | 51.4 | 20 | 47 |
| 80 mg | 71 | 48.1 | 15 | 56 |
Study Results
Study A1481140
A randomized, double-blind, placebo-controlled study was conducted in 278 patients with PAH. Of the 278 patients randomized, 277 patients received at least one dose of study drug. Patients were randomized to receive placebo (n=70) or REVATIO (sildenafil citrate) 20 mg (n=69), 40 mg (n=67) or 80 mg (n=71) t.i.d. for a period of 12 weeks. A total of 175 (63%) patients had PPH, 84 (30%) had PAH associated with CTD, and 18 (7%) had PAH following surgical repair of left-to-right congenital heart lesions. The study population consisted of 68 (25%) men and 209 (75%) women with a mean age of 49 years (range: 18-81 years) and baseline 6-minute walk test distance between 100 and 450 meters (inclusive). Patients across WHO functional classes I-IV participated in the study.
In this study, REVATIO (or placebo) was added to patients’ background therapy, which could have included a combination of anticoagulant, digoxin, calcium channel blockers, diuretics and / or oxygen. The use of prostacyclin analogues, endothelin receptor antagonists, and arginine supplementation was not permitted. Patients with left ventricular ejection fraction <45% or left ventricular shortening fraction <0.2 were not studied.
The primary efficacy endpoint was the change from baseline at Week 12 in 6-minute walk distance. Supportive endpoints included changes in hemodynamic parameters, functional class, background therapy, dyspnea score, Quality of Life (SF36 & EQ5D) and clinical worsening. At the recommended dose of 20 mg t.i.d., a placebo-corrected increase in walk distance of 45 meters was observed (p<0.0001). Placebo-corrected increases of 46 meters (p<0.0001) and 50 meters (P<0.0001) were observed on sildenafil 40 mg and 80 mg t.i.d., respectively, indicating no significant difference in effect between REVATIO doses.
The improvement in walk distance was apparent after 4 weeks of treatment and was maintained at Week 8 and Week 12. Mean treatment effects consistently showed improvement in 6-minute walk distance in all sildenafil groups compared to placebo in all pre-defined subpopulations based on demographics, geographical regions, disease characteristics and baseline parameters (walk test and hemodynamics).
Patients on all REVATIO doses achieved a statistically significant reduction in mean right arterial pressure (mPAP) compared to those on placebo. At the recommended dose of 20 mg t.i.d., a placebo-corrected decrease in mPAP of -2.7 mmHg was observed (p=0.04) (Table 5). Additionally, placebo-corrected reductions of -3.0 mmHg (p=0.01) and -5.1 mmHg (p<0.0001) were observed for sildenafil 40 mg and 80 mg t.i.d., respectively. There was no significant difference in effect between sildenafil doses. Improvements were also seen across all doses of REVATIO in pulmonary vascular resistance (PVR), right arterial pressure (RAP) and cardiac output (CO). Changes in heart rate (HR) and systemic blood pressure were negligible. The reduction in PVR was proportionally greater than the reduction in systemic vascular resistance (SVR).
Table 5. Changes from Baseline to Week 12 in Key Hemodynamic Parameters at the Recommended Daily Dose of 20 mg t.i.d.
PARMETER [mean (95% CI)] | Placebo (N=65)* | Sildenafil 20 mg t.i.d. (N=65)* |
| mPAP (mmHg) | 0.6 (-.08, 2.0) | -2.1 (-4.3, 0.0)a |
| PVR (dyn·s/cm5) | 49 (-54, 153) | -122 (-217, -27) |
| SVR (dyn·s/cm5) | -78 (-197, 41) | -167 (-307, -26) |
| RAP (mmHg) | 0.3 (-0.9, 1.5) | -0.8 (-1.9, 0.3) |
| CO (L/min) | -0.1 (-0.4, 0.2) | 0.4 (0.1, 0.7) |
| HR (beats/min) | -1.3 (-4.1, 1.4) | -3.7 (-5.9, -1.4) |
* The number of patients per treatment group varied slightly for each parameter due to missing assessments.
a (p=0.04)
In the pivotal trial, the incidence of clinical worsening (in particular hospitalizations due to pulmonary arterial hypertension) showed a favorable trend in the REVATIO treatment groups. A greater percentage of patients on sildenafil 20 mg t.i.d. (28%) showed an improvement of at least one WHO functional class over the 12-week period compared with placebo (7%). Similarly, fewer patients on sildenafil 20 mg t.i.d. (3 %) deteriorated by one or more WHO functional class over the 12-week period compared with placebo (10 %). Improvements were also seen in Quality of Life parameters and a favorable trend was seen in Borg dyspnea score in REVATIO-treated patients compared with placebo. Additionally, the proportion of patients requiring an added class of background medication during the trial was greater in the placebo group (20%) compared to the patients receiving sildenafil 20 mg (13%).
Long-Term Treatment Effect
Following the pivotal study, two hundred fifty nine of the 277 REVATIO-treated patients entered a separate long-term extension study. At the end of 1 year, 94% of these patients were still alive. Long-term effects on the subjects treated with REVATIO for at least 1 year (N=149) showed that change from baseline in 6-Minute Walk distance was 50 m (95% CI: 40, 60) at Week 12 and 54 m (95% CI: 42, 67) at 1 year. In addition, 54 (36%) and 61 (41%) of the patients improved by at least one WHO functional class at Week 12 and at 1 year, respectively. These estimates do not account patients who discontinued prior to reaching 1 year of treatment, or those ongoing in the study that had not reached 1 year of treatment. Results may be influenced by the presence of additional therapy for pulmonary arterial hypertension (prostacyclins or endothelin receptor antagonists) in 6 (4%) of the 149 patients. Without a control group, these data must be interpreted cautiously and cannot be interpreted as an improvement in survival, or as maintenance of effect.
Study A1481141
A randomized, double-blind, placebo controlled, study was conducted in 267 patients with PAH who were stabilized on intravenous epoprostenol. Patients had to have a mean pulmonary artery pressure (mPAP) ≥ 25 mmHg and a pulmonary capillary wedge pressure (PCWP) ≤ 15mmHg at rest via right heart catheterization within 21 days before randomization, and a baseline 6-Minute Walk test distance ≥ 100 m and ≤ 450 m. Patients were randomized to placebo or sildenafil (in a fixed titration starting from 20 mg, to 40 mg and then 80 mg, three times a day) when used in combination with intravenous epoprostenol.
The majority of patients in both treatment groups had PPH (78.9% on placebo and 79.9% on sildenafil). The remaining patients had PAH secondary to CTD (21.1% on placebo and 20.1% on sildenafil). The study population consisted of 20% men and 80% women with a mean age of 48 years (range: 18-75).
Analysis of the primary endpoint showed that there was a statistically significant greater increase in 6-Minute Walk distance for the sildenafil group compared with the placebo group at Week 16. The mean change from baseline at Week 16 (LOCF) was 30.1 m for the sildenafil group compared with 4.1 m for the placebo group giving an adjusted treatment difference of 26.0 m (95% CI: 10.8, 41.2) (p = 0.0009).
Patients on sildenafil achieved a statistically significant reduction in mean Pulmonary Arterial Pressure (mPAP) compared to those on placebo. A mean placebo-corrected treatment effect of -3.9 mmHg was observed in favor of sildenafil (95% CI: -5.7, -2.1) (p = 0.00003).
Clinical Worsening
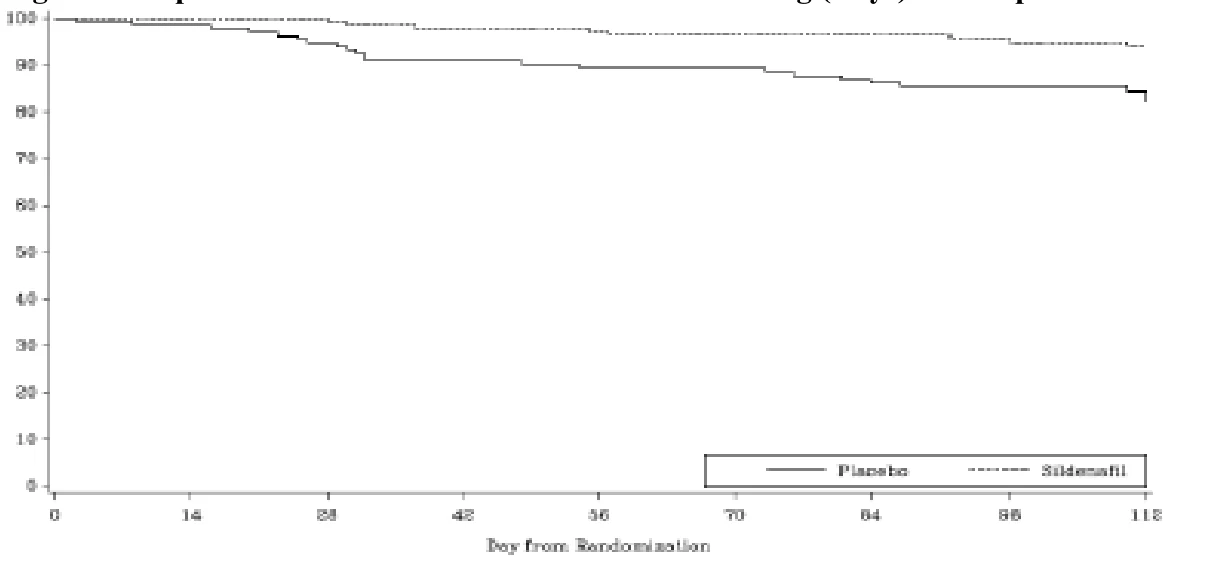
Time to clinical worsening of PAH was defined as the time from randomization to the first occurrence of a clinical worsening event (death or lung transplantation or initiation of bosentan therapy or clinical deterioration requiring a change in epoprostenol therapy). Patients with clinical worsening events are summarized in Table 6. Kaplan-Meier estimates and a stratified log-rank test demonstrated that placebo patients were 3 times more likely to experience an event and that patients receiving sildenafil experienced a significant delay in time to clinical worsening versus placebo (p = 0.0074). In a post-hoc analysis this improvement is seen as early as Week 4 in which there is a statistically significant (p = 0.0256) difference between patients on sildenafil 20 mg t.i.d. compared to placebo (Figure 1).
Table 6. Clinical Worsening Events
Placebo (n = 131) | Sildenafil (n = 134) | |
Number of subjects with clinical worsening event n (%) | 23 (17.6) | 8 (6.0) |
Proportion Worsened 95% Confidence Intervals | 0.187 (0.12 - 0.26) | 0.062 (0.02 - 0.10) |
Figure 1. Kaplan-Meier Plot of Time to Clinical Worsening (Days) ITT Population
Improvements in functional class were also demonstrated in subjects on sildenafil compared to placebo. More than twice as many sildenafil treated patients (35.6%) as the placebo group (14.4%) showed an improvement of at least one functional class.
Intravenous Administration
There is no evidence supporting the use of intravenous sildenafil in the treatment of primary (“idiopathic”) pulmonary arterial hypertension (PPH) or pulmonary hypertension secondary to CTD, in patients with WHO functional class II or III.
However, a general trend to reduce pulmonary vascular resistance in patients with PAH was demonstrated in small numbers of patients (some of whom were also receiving concomitant nitric oxide therapy) in a Phase IIa Pharmacodynamic study (see ACTION AND CLINICAL PHARMACOLOGY).
DETAILED PHARMACOLOGY
Human Pharmacodynamic Studies
Effects of REVATIO (sildenafil citrate) on Blood Pressure (BP):
Oral doses of sildenafil of 50 mg, 100 mg and 200 mg produced statistically significant decreases in supine systolic and diastolic blood pressure (a mean maximum decrease of approximately 8.3 mmHg and 5.3 mmHg, respectively) compared with placebo, with no effect on pulse rate. The mean maximum fall in systolic and diastolic blood pressure occurred at peak plasma levels (approximately 1 hour post-dose), and there was a tendency for blood pressure to return to baseline values by 4 hours post-dose.
In healthy volunteers, there were no clinically significant changes in cardiac index (derived from bio-impedence measures of cardiac output) up to 12 hours post-dose for sildenafil administered orally (100 mg, 150 mg and 200 mg), nor intravenously (20-80 mg), compared with placebo. Sildenafil has both arteriodilator and venodilator effects on the peripheral vasculature.
Single oral doses of sildenafil above 15 mg were generally associated with a potentiation of the antiaggregatory effects of sodium nitroprusside (SNP) on ADP aggregation of ex vivo platelets. Sildenafil had no effect on other ex vivo tests (ADP-induced platelet aggregation of whole blood and ADP-induced aggregation of platelet-rich plasma in the absence of SNP). Sildenafil therefore has no direct effect on platelet function ex vivo, but potentiates the action of a nitric oxide (NO) donor, SNP. This confirms the need for an NO drive before sildenafil will produce its pharmacological effects. These modest effects on platelet activity, ex vivo, did not result in a clinically significant effect on bleeding time in healthy volunteers.
Effects of REVATIO on Vision:
At single oral doses of 100 mg and 200 mg, transient dose-related impairment of color discrimination (blue/green) was detected using the Farnsworth-Munsell 100-hue test, with peak effects near the time of peak plasma levels. This finding is consistent with the inhibition of PDE6, which is involved in phototransduction in the retina. An evaluation of visual function at doses up to 200 mg revealed no effects of REVATIO on visual acuity, contrast sensitivity, ERGs, intraocular pressure, or pupillometry. In a small size placebo-controlled study of patients with documented early age-related macular degeneration (n=9), sildenafil (single dose, 100 mg) demonstrated no significant changes in visual tests conducted (visual acuity, Amsler grid, color discrimination simulated traffic light, Humphrey perimeter and photostress).
REVATIO added to bosentan therapy:
In a study of pulmonary arterial hypertension (PAH) patients (PPH and secondary PAH associated with CTD) on background bosentan therapy, no benefit (6-minute walk distance (6MWD)) of sildenafil (20 mg three times a day) co-administered with bosentan (62.5-125 mg twice a day) was demonstrated over bosentan alone. The PAH patients included those with primary PAH (PPH), and PAH associated with CTD. In this trial, the concomitant use of sildenafil and bosentan was associated with a neutral effect on 6MWD in PAH patients, with mean changes of 13.62 m (n=49, 95% CI: -3.89 to 31.12) and 14.08 m (n=53, 95% CI: -1.78 to 29.95) in sildenafil add-on and placebo add-on groups, respectively. The concomitant administration of sildenafil and bosentan is not an optimal choice in PPH patients stable on bosentan therapy. In a subgroup analysis for PPH (67 subjects), mean changes in 6MWD were 26.39 m (n=35, 95% CI: 10.70 to 42.08) in the sildenafil add-on group compared with 11.84 m (n=32, 95% CI: -8.83 to 32.52) in the bosentan alone group. In a subgroup analysis for pulmonary hypertension associated with CTD (36 subjects), there was a reduced 6MWD, 18.32 m (n=14, 95% CI: -65.66 to 29.02) in sildenafil add-on group compared with 17.50 m (n=21, 95% CI: -9.41 to 44.41) in the bosentan alone group. Therefore the use of sildenafil with bosentan is not recommended in patients with PAH associated with CTD.
Metabolism and Elimination
The major circulating metabolite of sildenafil, results from N-demethylation of sildenafil at the N-methyl piperazine moiety. It has a similar selectivity for PDE isozymes as sildenafil, but exhibits around 50% of the potency of sildenafil. The metabolism of sildenafil occurs in human hepatic microsomes and is mediated by two cytochrome P-450 isoforms [CYP2C9 (minor route) and CYP3A4 (major route)].
The concomitant use of potent cytochrome P-450 3A4 inhibitors (e.g. erythromycin, saquinavir, ritonavir, ketoconazole, itraconazole) as well as the non-specific CYP inhibitor, cimetidine, is associated with increased plasma levels of sildenafil (see PRECAUTIONS, DRUG INTERACTIONS, DOSAGE AND ADMINISTRATION).
TOXICOLOGY
Acute Toxicity Mice and Rats:
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | |||||
| Single dose oral toxicity in mice and rats (90155/56) | ||||||||||
Sprague- Dawley rat CD1 mice | Oral (gavage) | rat: 300 500 1000 mice: 500 1000 | 5/sex | 1 day | At 1000 mg/kg one male mouse died within 24 hours after drug administration. In rats, mortality occurred in three females at 1000 mg/kg and in one female at 500 mg/kg. The dose of 1000 mg/kg induced clinical signs in both species, generally within 24 hours following the administration, which persisted less than 24-48 hours. Some of these signs were similar in mice and rats and consisted of partially-closed eyes, hunched posture, tremours, depression, coldness to the touch (with pallor of ears and paws in rats) and prostration. Female rats were more affected than male rats. Dyspnea was limited to one mouse, and chromodacryorrhea to four female rats. Clinical signs at 500 mg/kg included partially-closed eyes in one mouse and subdued behaviour in the female rat which died. No clinical signs were observed in rats at 300 mg/kg. In both species, the doses administered induced no changes in body weight gain and there were no treatment-related macroscopical changes at gross necropsy. These results indicate that the no observed adverse effect level (NOAEL) was 500 mg/kg in mice and 300 mg/kg in rats. | |||||
| Single dose intravenous toxicity in mice and rats (91045/046) | ||||||||||
Sprague- Dawley rat CD1 mice | I.V. | rat: 10 mice:20 | 5/sex | 1 day | All animals survived the treatment and gained weight over the 14-day study period. There were no clinical signs during the study and no abnormalities at necropsy. Under the conditions of this study, the no observed effect level (NOEL) after intravenous administration was 20 mg/kg in mice and 10 mg/kg in rats. | |||||
| Long-Term Toxicity - Mice: | ||||||||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | |||||
| 3-Month oral (gavage) prechronic toxicity study in mice (94049) | ||||||||||
| CD1 | Oral (gavage) | 10 50 100 200 | 10/sex | 3 months | The exposure to sildenafil and its metabolite UK-103,320 was similar in males and females and approximately dose-related. Treatment-related mortality occurred in 3/20 animals in each group given 50, 100 or 200 mg/kg. A marked gastrointestinal dilation was the cause of the death and was associated with a number of clinical signs, in particular dyspnea and/or swollen abdomen. This dilation resulted in gastrointestinal inflammation, fatty changes and focal/multifocal necrosis in the liver, atrophy of adipose tissues and hemoconcentration. There was also a mild gastrointestinal dilation in a few survivors of these groups. In males treated with 50, 100 or 200 mg/kg, there was an apparent decrease in body weight gain. However, in the absence of dose relationship and consistent statistical significance, the association with treatment is questionable. Plasma cholesterol was slightly increased in females treated with 50, 100 or 200 mg/kg and plasma triglycerides were slightly decreased in males treated with 100 or 200 mg/kg. However we consider these changes to be of minor toxicological importance. The NOAEL in this study was 10 mg/kg, given the mortality and gastrointestinal dilation at higher doses. | |||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | ||||
| 3-Month oral (gavage) exploratory toxicity study in mice (94101) | |||||||||
| CD1 | Oral (gavage) | 20 40 100 | 10/sex | 3 months | The exposure to sildenafil and its metabolite UK-103,320 was similar in males and females and increased superproportionally with dose level. Treatment-related mortality occurred in 1/20 animals in each group given 40 or 100 mg/kg. A marked gastrointestinal dilation was the cause of the death and was associated with a number of clinical signs, in particular dyspnea and/or swollen abdomen. There was also a transient abdominal swelling in a few survivors of these groups. The NOAEL in this study was 20 mg/kg, given the mortality and gastrointestinal dilation at higher doses. | ||||
| Long-Term Toxicity - Rats: | |||||||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | ||||
| 10-Day oral range-finding toxicity in rats (90080) | |||||||||
| Sprague Dawley | Oral (gavage) | 50 150 500 | 5/sex | 10 days | Measurement of plasma concentrations of sildenafil and UK-103,320 showed that females were exposed predominantly to the drug while males were exposed mainly to the metabolite, UK-103,320, and a lower level of unchanged compound. Concentrations of UK-95,340 were generally below the limit of determination (30 ng/mL). Exposure increased with dose but not in linear manner. At 500 mg/kg, 1/5 females died after the second dose with no apparent cause of death. Of the animals used for plasma drug determination, 1/10 rats at 150 mg/kg and 2/10 rats at 500 mg/kg died after the first or second dose. As these animals died after taking blood samples, they were not considered in the analysis of mortality. Food consumption was decreased between day 1 and 4 in mid- and high-dose males and in all treated female groups. A dose-related decrease of plasma triglycerides occurred in males, and an increase of plasma cholesterol was seen in high-dose females. Blood urea increased in mid- and high-dose males and in the 3 treated female groups. Relative heart weight was slightly increased in high-dose males. Kidney and liver weights were increased in mid- and high-dose females, and in high-dose males. The increase of liver weight was associated with centrilobular hypertrophy. Changes in red blood cell parameters were seen in females. They indicate a decrease of circulating red blood cells at the 3 dose levels, with some evidence of regenerative response at the high dose. An increase of white blood cell counts was recorded at the mid dose in females and at the high dose in both sexes. Changes at the dose of 50 mg/kg were considered minor. The NOAEL in this study was 150 mg/kg, based on the mortality at 500 mg/kg. | ||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | |||
| 1-Month oral toxicity in rats (90143) | ||||||||
| Sprague Dawley | Oral (gavage) | 10 45 200 | 10/sex | 1 month | Plasma concentrations of sildenafil were higher in females than in males, while concentrations of the metabolite, UK-103,320, were higher in males than in females. As a result, females were exposed predominantly to the unchanged drug and males to an almost equal balance of drug and metabolite. These data indicate that N-demethylation of sildenafil to UK-103,320 is an important route of sildenafil biotransformation in male rats. Concentrations of UK-95,340 were generally below the limit of determination (30 ng/mL). One of the high-dose females used for plasma drug level determination died after the first dose, before blood samples had been taken. Clinical signs were limited to a few high-dose animals and consisted of chromodacryorrhea and palpebral closure. Slight increases in water and food intake were seen generally in mid- and high-dose animals. A mild dose-related decrease in circulating red blood cells with evidence of a regenerative response was found in mid- and high-dose females and, to a smaller extent, in high-dose males. A moderate neutrophilia was seen in high-dose males, while a moderate lymphocytosis occurred in mid- and high-dose females. Plasma chemistry changes at the high dose consisted of increases in urea, decreases in triglycerides (males) and increases in cholesterol (females), but remained within our normal range of values. Doses of 45 and/or 200 mg/kg were associated with an increase in liver weight and centrilobular hypertrophy in both sexes. Hypertrophy of the zona glomerulosa of the adrenal glands was seen in the high-dose males and in the mid- and high-dose females. Thyroid follicular hypertrophy occurred at the high dose in both sexes. In addition, mesenteric arteritis was found in two mid-dose and one high-dose males, but was not considered to be related to the treatment. The NOAEL was 45 mg/kg in this study. | |||
| 28-Day oral exploratory toxicity study in rats (94085) | ||||||||
| Sprague-Dawley | Oral (gavage) | 0 60 120 | 10 males/ group | 28 days | A 2-year rat carcinogenicity study with sildenafil citrate at a contract laboratory (Study No. 911/002), at doses of 1.5, 5 and 60 mg/kg, was terminated after unexpectedly high mortality and severe toxic effects in high-dose males during weeks 3 and 4. An exploratory study was performed to confirm that the batch of sildenafil used at the contract laboratory did not induce severe toxicity. The only treatment-related effects were a mild dose-related increase in liver and kidney weights and possibly a slight decrease in body weight gain. Importantly, the absence of death in this study confirms the results of previous studies up to 200 mg/kg, and contrasts with the results of the study at the contract laboratory. Subsequently, it was shown that the mortality in the carcinogenicity study (Study No. 911/002) was due to dosing with a cytotoxic compound from another company and not sildenafil. Consequently, the contracted carcinogenicity study was invalid. | |||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | ||||
| Investigation of the relationship between liver enzyme induction and thyroxine clearance in rats (96010) | |||||||||
| Sprague-Dawley | Oral (gavage) | 200 | 10 females | 1 month | Following the appearance of thyroid follicular hypertrophy in rats, an investigative study was conducted to examine the relationship between liver enzyme induction and thyroid hypertrophy in rats. Two groups of 10 female rats were treated orally with sildenafil citrate at 200 mg/kg for 29 days, and two control groups received the vehicle alone. One treated group and one control group were used for assessment of exogenous thyroxine clearance. The other treated group and the other control group were used for measurement of plasma TSH and thyroid hormones, for histopathological examination of the liver and thyroid, and for determination of UDP-glucuronyl transferase (UDPGT) activity in the liver. The treatment caused the deaths of 2/20 rats on days 2 or 3. In the treated group, there was an increase in the weight of liver and thyroid, associated with minimal centrilobular hypertrophy of the liver and thyroid follicular cell hypertrophy. There was also an increase in hepatic UDPGT activity, an increase in TSH, and a decrease in T3 and T4 hormones. In addition, the clearance of exogenous thyroxine was increased in treated animals. These results are consistent with the view that the thyroid hypertrophy associated with treatment of rats with sildenafil was due to induction of hepatic UDPGT which increased the clearance of thyroid hormone and consequently caused a compensatory increase in plasma TSH which stimulated the thyroid gland. | ||||
| 6-Month oral toxicity study in rats (91098) | |||||||||
| Sprague-Dawley | Oral (gavage) | 3 12 60 | 20/sex | 6 months | Drug and metabolite plasma level determinations showed that females were exposed predominantly to sildenafil while males were exposed almost exclusively to the metabolite. No treatment-related deaths were recorded. Chromodacryorrhea was seen in the 3 treated groups. Body weight gain and food consumption were increased at the low dose and, to a lesser extent, at the mid dose. A trend towards a reduced body weight gain was seen at the high dose; however, the relationship to compound administration cannot be ascertained. Decreases of plasma bilirubin and triglycerides, and increases in plasma urea, total proteins and cholesterol were seen at the high dose. These changes suggest compound-induced metabolic changes in the liver. Increase in liver weight associated with mild centrilobular hypertrophy indicate an adaptive response. Thyroid hypertrophy occurred at the high dose in both sexes and at a lower incidence in mid-dose males. This change was considered to be a secondary phenomenon related to increased hepatic clearance of thyroid hormone. Although thyroid hormones and hepatic clearance were not measured in this study, changes in these parameters were demonstrated in an exploratory study (Study No. 96010). Hypertrophy of the zona glomerulosa of the adrenal gland occurred with a dose-related incidence at the mid and high doses and was associated with an increase in the weight of the organ at 60 mg/kg. The NOAEL in this study was 60 mg/kg. | ||||
| 13-Day intravenous range-finding in rats (90139) | |||||||||
| Sprague-Dawley | I.V. | 2.5 5 10 | 5/sex | 13 days | No deaths occurred during the treatment period. The only clinical sign noted was a transient redness of the ears in a few treated animals, notably in the high-dose male group. The NOAEL in this study was 10 mg/kg. | ||||
| 1-Month intravenous toxicity study in rats (91044) | |||||||||
| Sprague-Dawley | I.V. | 0.5 2 4 | 10/sex | 1 month | No compound-related changes were seen at the doses of 0.5 and 2 mg/kg. At the dose of 4 mg/kg, the incidence and severity of mild myocardial inflammation was slightly increased compared to the control group; the relationship to treatment cannot be ascertained. The NOAEL in this study was 2 mg/kg. | ||||
| Long-Term Toxicity - Dogs: | |||||||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | ||||
| 10-Day oral range-finding toxicity in dogs (90081) | |||||||||
| Beagle | Oral (gavage) | 10 30 100 | 1 male 2 females | 10 days | Plasma concentrations of sildenafil and UK-103,320 were similar in males and females and increased with dose, although subproportionally at the high dose. The proportion of UK-103,320 relative to sildenafil varied minimally (18-24%) over the dose range examined and indicates no detectable saturation of this metabolic pathway. Concentrations of UK-95,340 were generally below the limit of determination (30 ng/mL). Emesis and salivation occurred at the dose of 100 mg/kg, and lacrimation, conjunctival redness and a transient decrease in amplitude of the pupillary reflex were seen at all dose levels. There was no evidence of a convincing change in blood pressure, given the spontaneous variation in this parameter. Heart rate was increased at 30 and 100 mg/kg, and probably represents a reflex response to the vasodilating properties of the compound. Decreases in PQ and QT intervals of the ECG at these doses were secondary to the heart rate changes. Two high-dose animals showed a moderate increase of plasma cholesterol which was not considered to be toxicologically important. An arteritis of an extramural branch of a coronary artery was found in one high-dose female. This is considered to be a spontaneous finding considering the morphological features and the background incidence in Beagle dogs in our laboratories. The NOAEL in this study was therefore 100 mg/kg. | ||||
| 1-Month oral toxicity study in dogs (90125) | |||||||||
| Beagle | Oral (gavage) | 5 20 80 | 3/sex | 1 month | The dogs were exposed to concentrations of sildenafil and UK-103,320, which increased with dose, although subproportionally at the high dose. The proportion of UK-103,320 relative to sildenafil varied minimally (15-19%) over the dose range examined and indicates no detectable saturation of this metabolic pathway. Concentrations of UK-95,340 were generally below the limit of determination (30 ng/mL). At the mid and high doses, the compound induced a low incidence of emesis and transient salivation. A moderate incidence of soft and liquid feces was noted at all doses. There was no evidence of consistent changes in blood pressure, although there were increases in heart rate at 20 and 80 mg/kg. Changes in the ECG (increased P-wave amplitude and decreases in PQ and QT intervals) were expected from the increases in heart rate. There was a moderate increase in plasma cholesterol at the high dose. A mild coronary arteritis was seen in one high-dose animal, but considering the morphological features of this finding, and the high background incidence in Beagle dogs in our laboratories, this was not thought to be treatment-related. The NOAEL was 80 mg/kg in this study. | ||||
| 6-Month oral toxicity in dogs (91099) | |||||||||
| Beagle | Oral (gavage) | 3 15 50 | 4/sex | 6 months | Analyses of plasma sildenafil and UK-103,320 showed dose-related concentrations in the dog. The proportion of UK-103,320 relative to sildenafil varied minimally (15-23%) as the dose increased, indicating no saturation of this process. Salivation, emesis and resistance to compound administration were seen when the animals were treated with an initial high dose of 80 mg/kg, and reflected gastric intolerance to the compound at this dose level. These signs were rare after reducing the high dose to 50 mg/kg. A moderate increase in heart rate, associated with decreases in PQ and QT intervals, occurred at the high dose and is considered to be a reflex response to the vasodilatory properties of the drug. Increases in plasma cholesterol and in liver weight were seen in animals treated with 15 and 50 mg/kg. A high-dose male showed a number of clinical signs and changes in hematological parameters and plasma chemistry associated with a disseminated arteritis. These changes correspond to Idiopathic Juvenile Arteritis Syndrome (Beagle Pain Syndrome) which occurs sporadically in Beagle dogs. Another high-dose male showed arteritis in the thymus which indicated a less severe expression of the same disease. It is probable that the high dose precipitated the expression of this latent spontaneous disorder. The NOAEL in this study was 15 mg/kg, given the appearance of Idiopathic Juvenile Arteritis Syndrome at higher doses. | ||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | |||||
| 12-Month oral toxicity study in dogs (95039) | ||||||||||
| Beagle | Oral (gavage) | 3 10 50 | 4/sex | 12 months | The dogs were exposed to approximately dose-related concentrations of sildenafil and its N-demethylated metabolite, UK-103,320. The proportion of UK-103,320 relative to sildenafil varied minimally as the dose increased. Features typical of a syndrome of Idiopathic Juvenile Arteritis occurred in all high-dose males. In 3/4 high-dose males, there was arteritis which affected several organs. In one of these dogs, arteritis was associated with a number of clinical signs, body weight loss and hematological changes. In the other two animals, there were no clinical or hematological correlates to arteritis. In addition, the fourth high-dose male presented clinical signs and clinical pathology changes typical of the syndrome though no vascular lesion was found at histopathology. Focal coronary arteritis occurred in one low-dose and one high-dose female; neither finding was considered treatment-related. The treatment produced an increase in the amount of lipogenic pigments in renal tubular epithelium in 1/8 animals at the mid dose and 7/8 animals at the high dose, a dose-related decrease in plasma creatine kinase, mainly in males, and a decrease in plasma myosin in high-dose animals. However, these changes were considered of no toxicological importance. A dose-related increase in heart rate occurred at the high and mid doses, and was considered to be due to compensatory mechanisms occurring in response to the vasodilatory properties of the compound. The NOAEL in this study was 10 mg/kg, given the appearance of Idiopathic Juvenile Arteritis Syndrome at higher doses. | |||||
| 14-Day intravenous range-finding toxicity in dogs (90142) | ||||||||||
| Beagle | I.V. | 2.5 5 10 | 2 males 1 female | 14 days | The doses of 5 and 10 mg/kg were associated with liquid feces and an inhibition of the pupillary reflex. An increase in heart rate was observed at the high dose and, to a lesser extent, at the mid dose. This change was probably related to the vasodilator effect of the compound. Evidence of vasodilatation was provided by the peripheral redness seen in two high-dose animals. An increase in plasma cholesterol occurred in 2/3 high-dose animals but was not considered to be toxicologically important. At the dose of 2.5 mg/kg, there were no treatment-related changes. The NOAEL was 10 mg/kg in this study. | |||||
| 1-Month intravenous toxicity in dogs (91041) | ||||||||||
| Beagle | I.V. | 0 0.5 2 4 | 3/sex | 1 month | The treatment induced no adverse effects. The NOAEL is therefore 4 mg/kg in this study. | |||||
| Bioequivalence - Dogs: | |||||||||
| Species | Route | Dose mg/kg/ day | #Animals / dose level | Duration | Findings | ||||
| Bioequivalence between base and citrate in dogs (91058) | |||||||||
| Beagle | Oral | 300 | 1 male 1 female | N/A | The aim of the current study was to assess, in the dog, the oral bioequivalence of a suspension of the base, and of capsules of the citrate. The base was suspended in a 5% aqueous solution of methylcellulose 4000 cps containing 0.1% Tween 80 and acidified with hydrochloric acid 0.1M (final concentration). The citrate salt was administered in gelatin capsules. On day 1, a first group of one male and one female beagle dogs was treated with the base and the second group of one male and one female was treated with the citrate. On day 8, the first group received the citrate, and the second group the base. The animals were regularly examined for clinical signs and weighed before each administration. Blood was sampled 0.25, 0.5, 1, 1.5, 2, 3, 4, 6, 8, 11 and 24 hours after each administration. Plasma levels of UK-92,480 and two metabolites, UK-95-340 and UK-103,320, were measured. One male dog vomited after each administration and its drug and metabolite plasma concentrations were therefore considered not to be relevant. In other dogs, maximal plasma concentrations and AUCs of UK-92,480 and of UK-103,320, observed after administration of the citrate in capsules were similar to or higher than those seen after administration of the base in a suspension. All the plasma concentration of UK-95,340 were below the limit of detection of the assay. These data indicate that bioavailability of the citrate in the dog is identical to or better than that of the base. | ||||
Carcinogenesis and Mutagenesis
Sildenafil was not carcinogenic when administered to rats for 24 months at a dose resulting in systemic drug exposure (AUC) of 110- and 146-times, respectively, for male (unbound sildenafil and its major metabolite) and female (unbound sildenafil) rats. The exposures observed in humans given the Recommended Human Dose (RHD) of 20 mg t.i.d. sildenafil was not carcinogenic when administered to mice for 18-21 months at dosages up to the Maximum Tolerated Dose (MTD) of 10 mg/kg/day, approximately 1.1 times the RHD on a mg/m2 basis.
Sildenafil has been studied in a comprehensive battery of tests designed to detect genotoxic activity. Sildenafil did not display mutagenic activity in bacterial or mammalian cells in vitro, or clastogenic activity in vitro or in vivo.
As the clinical dose is administered three times daily, the clinical free AUC used to calculate exposure multiples was 19 ng-h/mx3, and compared with the AUC 0-24 hours in the preclinical species
| Species | Route | Dose mg/kg/ day | #Animals/ dose level | Duration | Findings | |||||
| Pharmacokinetic study in rats (94067) | ||||||||||
Sprague Dawley | Oral (gavage) | 60 | 5/sex | 14 days | This study was conducted to provide an estimate of the pharmacokinetic exposure of rats over 24 hours. Plasma concentrations of sildenafil were higher in females than in males, while concentrations of the metabolite, UK-103,320, were higher in males than in females. | |||||
| Oral toxicity and carcinogenicity study in mice (95007 & 95120) | ||||||||||
| CD1 | Oral (gavage) | 3 10 30 1 3 5 | 55/sex | 3 & 10 mg: males 649 days females 558 days 30 mg: males 453 days females 404 days 1, 3, 5 mg males and females 719-730 days | The exposure to the parent compound and the demethylated metabolite, UK-103,320 was dose-related. The compound produced an increase in mortality rate with consequent decreases in survival times and percent of survival. The effect was marked at the mid dose in females and at the high dose in both sexes. In addition, the percent of survival was also slightly decreased in mid-dose males, at the end of the study. Because of the lower survival in mid- and high-dose animals interim sacrifices were decided. When the survival in the high-dose group reached about 20%, the survivors were sacrificed, on day 405 (females) or 454 (males). Control, low- and mid-dose groups were sacrificed on day 559 (females) or 650 (males), when the survival at the mid dose was about 20%. In a number of animals, especially high-dose males (40%), unscheduled death was preceded by abdominal swelling and/or dyspnea. Gastrointestinal dilation and gavage accident were identified as causes of unscheduled death related to treatment. Additionally, the number of deaths without explanatory macroscopic or histopathological changes was higher in mid- and high-dose groups than in the control groups. In high-dose males and females, there was also a trend to body weight decrease compared to controls (10 and 18%, respectively). In addition, there was an abrupt body weight loss in most animals dying prematurely which was more marked in mid- and high-dose females. The treatment produced no increase in the incidence of neoplastic lesions. Furthermore, in the animals sacrificed at the various interim and final sacrifices, there were no differences in the incidence of non-neoplastic lesions between control and treated groups. In conclusion, the doses of 10 and 30 mg/kg produced signs of toxicity consisting mainly of a dose-related increase in mortality. At the dose of 3 mg/kg, although there was no compound effect on group mortality, 2 animals died from gastrointestinal dilation. There were no carcinogenic effects at any dose. | |||||
| Species | Route | Dose mg/kg/ day | #Animals/ dose level | Duration | Findings | |||
| 24-Month oral toxicity and carcinogenicity study in rats study (94092) | ||||||||
| Sprague-Dawley | Oral (gavage) | 1.5 5 60 | 60/sex | 24 month | The rats were exposed to plasma concentrations of sildenafil and UK-103,320 that increased with dose levels. Male rats were exposed predominantly to UK-103,320, whereas unchanged drug was the major circulating form in females. Overall, the total exposure to drug and metabolite was higher in females than in males. The treatment produced no mortality. Survival at the end of the study ranged between 18 and 42% in males and between 15 and 25% in females. The body weight was decreased in high-dose animals, compared to controls. A transient decrease in body weight occurred also in mid-dose females. There was a dose-related decrease in plasma bilirubin which, in our view, is related to the enzyme-inducing properties of the compound. In high-dose males there was an increased incidence of proliferative changes in the thyroid which was mainly related to an increase in follicular cell hyperplasia. We consider that these changes are the consequence of an increased turnover of thyroid hormones due to hepatic enzyme induction and bear no relevance to man. To conclude, the dose of 60 mg/kg was associated with a toxicologically significant decrease in body weight and with an increase in follicular proliferative changes in the thyroid in males. At 5 mg/kg there was only an inconsistent decrease in the body weight of females. There were no compound effects at 1.5 mg/kg. There were no indications of a carcinogenic potential of sildenafil. | |||
| Mutagenicity studies (90817-01/02) | ||||||||||||
| Study Type | Strain | Dose | Results | |||||||||
| in vitro bacterial mutagenicity | S. typhimurium TA 1535, 1537, 98, 100 | 0.002 - 1 mg/plate | negative | |||||||||
| in vitro mammalian cell mutagenicity | Chinese Hamster Ovary / HGPRT | 65-240 μg/mL | negative | |||||||||
| in vitro clastogenicity | Human lymphocytes | 10, 20, 25 μg/mL -S9 100, 125, 250 μg/mL + S9 | negative | |||||||||
| in vivo clastogenicity | Mouse bone marrow | 0, 500, 1000, 2000 mg/kg | negative | |||||||||
Reproduction and Teratology
No evidence of teratogenicity, embryotoxicity or fetotoxicity was observed in rats and rabbits which received up to 200 mg/kg/day during organogenesis. These doses represent, respectively, about 32 and 68 times the RHD on a mg/m2 basis in a 50 kg subject. In the rat pre- and postnatal development study, the no observed adverse effect dose was 30 mg/kg/day given for 36 days. In the non-pregnant rat the AUC at this dose was about 24 times unbound human AUC.
In pups of rats which were pre- and postnatally treated with 60 mg/kg sildenafil, a decreased litter size, a lower pup weight on day 1 and a decreased 4-day survival were seen at exposures which were approximately fifty times the expected human exposure at 20 mg three times a day. Effects in non-clinical studies were observed at exposures considered sufficiently in excess of the maximum human exposure indicating little relevance to clinical use.
| Species | Route | Dose mg/kg/ day | #Animals/ dose level | Duration | Findings | |||
| Maternal toxicity study in rats by the oral route (92020) | ||||||||
| Sprague-Dawley | Oral (gavage) | 10 50 200 | 7 females | Gestation days 6-17 | Hematological, biochemical (plasma) and pathological changes were recorded only at 200 mg/kg. Hematological changes consisted of a moderate decrease in hemoglobin, red blood cell count and packed cell volume accompanied by an increase in the mean red blood cell distribution width. The only variation observed in plasma chemistry was a decrease in mean plasma triglycerides. Finally, a mild hepatic weight increase with hepatic centrilobular hypertrophy was noted after pathological examination. With regard to the fetuses, there was a decrease in the mean male body weight at 200 mg/kg. In male fetuses at 10 and 50 mg/kg and in female fetuses at all dose levels, the mean body weights were similar to those of the control group. The NOAEL was 50 mg/kg in dams and fetuses given the changes in plasma chemistry and fetal weight of males at 200 mg/kg. | |||
| Study of fertility and early embryonic development to implantation in rats by the oral route (94081) | ||||||||
| Sprague-Dawley | Oral (gavage) | 3 12 60 | 20/sex | Males: from 9 weeks before mating to gestion day 20 Females: from 2 weeks before mating to gestation day 6 | The treatment produced no adverse effects on the fertility of either sex. In addition, there was no evidence of maternal, embryo- or fetotoxicity. The only finding was a moderate reduction in plasma triglycerides in females treated with 60 mg/kg. Therefore the NOAEL in this study was 60 mg/kg. | |||
| Study for effects on pre- and post-natal development, including maternal function, in rats by the oral route (95068/95095) | ||||||||
| Sprague-Dawley | Oral (gavage) | 10 30 60 | 20 females | from gestation day 6 until 20 days after birth | The only noteworthy finding was a toxicologically significant decrease in the ratio of viable pups at birth, with consequently a decreased litter size of viable pups, at 60 mg/kg. At this high-dose level, there was a toxicologically significant decrease in the 4-day survival index, in the F1 pups body weight on day 1 p.p. and some delay in a developmental landmark, the appearance of upper incisors. There were no findings in the reproductive function of the F1 generation, and in the F2 generation. The NOAEL was 30 mg/kg for F0 females and F1 pups, given the minimal maternal toxicity and the effect on pup development during the first 2 weeks of life. The NOAEL for the F2 generation is 60 mg/kg. | |||
| Species | Route | Dose mg/kg/ day | #Animals/ dose level | Duration | Findings | ||
| Study for effects on embryo-foetal development in rats by the oral route (95058/95059) | |||||||
| Sprague-Dawley | Oral (gavage) | 10 50 200 | 20 females | Gestation days 6-17 | There were detectable levels of sildenafil and UK-103,320 in maternal plasma, amniotic fluid and fetal homogenates at all dose levels. Treatment at 200 mg/kg produced salivation and a reduction in mean body weight gain between days 6 and 9 p.c., accompanied by a decrease in food intake on day 9 p.c. On day 18 p.c., the mean food consumption increased. Hematological changes consisted of a slight decrease in hemoglobin, red blood cell count and hematocrit accompanied by an increase in the mean red blood cell distribution width at 200 mg/kg. A dose-related increase in the reticulocyte count was present, reaching statistical significance at the high-dose only. The only variation in plasma chemistry was a dose-related decrease in mean plasma triglycerides, at most moderate and statistically significant at the high-dose only. The body weight of male fetuses was reduced at 200 mg/kg. There were no treatment-related external, skeletal or visceral anomalies. Treatment with 200 mg/kg produced a slight maternal toxicity without embryotoxicity but a slight toxicity in male fetuses only. There was no maternal, fetal or embryotoxicity after treatment with 10 or 50 mg/kg. There were no teratological effects at any dose. The NOAEL in this study was 50 mg/kg in dams and fetuses, given the slight toxicity at 200 mg/kg. | ||
Rabbits:
| Species | Route | Dose mg/kg/day | #Animals/ dose level | Duration | Findings | ||
| Maternal toxicity study in rabbits by the oral route (95003/95004) | |||||||
| New Zealand White | Oral (gavage) | 50 100 200 | 7 females | Gestation days 6-18 | Pregnant females and fetuses were exposed to the drug. The only noteworthy findings in dams were an increase in plasma glucose and a decrease in plasma cholesterol at the high dose. This is indicative of a minimal toxicity in dams. There were no adverse effects on embryo or fetal development. The NOAEL was 100 mg/kg in dams given the changes in plasma chemistry values at 200 mg/kg. The NOEL was 200 mg/kg in the developing embryos and fetuses. | ||
| Study for effects on embryo-foetal development in rabbits by the oral route (95043/44) | |||||||
| New Zealand White | Oral (gavage) | 10 50 200 | 20 females | Gestation days 6-18 | Sildenafil and UK-103,320 were found in the plasma of pregnant females. The presence of sildenafil was also detected in amniotic fluid. At the high-dose, there were reductions in body weight and body weight gain late in gestation, compared to the control group, which are indicative of minimal maternal toxicity. A reduction in food intake in high-dose females during the same period may have contributed to the body weight changes. The plasma chemistry changes, encountered in the preliminary study, were not found in this study. The treatment had no adverse effects on the developing conceptus. The NOAEL in this study was 50 mg/kg for dams, given the effect on body weight at 100 mg/kg. The NOEL was 100 mg/kg in the developing embryos and fetuses. | ||
Special Studies:
| Species | Route | Dose mg/kg/day | #Animals/ dose level | Duration | Findings | ||||
| Antigenicity study in guinea pigs (95-29-81) | |||||||||
| Hartley Guinea Pigs | Oral _________ _ sub-cutaneous (with Freund’s complete adjuvant) | 4 mg/mL 20 mg/mL ___________ 2 mg/mL 10 mg/mL | 5/group | N/A | In the active systemic anaphylaxis test, male guinea pigs that received daily doses of 4 or 20 mg/kg sildenafil orally 5 days a week for 3 weeks showed no signs of systemic anaphylaxis reactions after intravenous injection of sildenafil 19 days later as challenge antigen. Similarly, when male guinea pigs sensitized subcutaneously with 2 or 10 mg sildenafil/guinea pig (given on 4 occasions at 1 week intervals) were challenged 16 days later with intravenous injection of sildenafil, they showed no signs of systemic anaphylaxis. In the passive cutaneous anaphylaxis test, guinea pigs were challenged with sildenafil (30 mg/guinea pig). No positive PCA reactions were observed against anti-sera obtained from guinea pigs immunized orally or subcutaneously with sildenafil. | ||||
| Intra-arterial irritation in rabbits (91073) | |||||||||
| New Zealand White | Intra- arterial | 1 mg/animal | 4 females | 1 day | Sildenafil (1 mg/animal) was administered into the central ear artery of rabbits in a volume of 0.5 mL to examine the potential irritant reactions. The single injection produced no arterial irritation over a 21-day observation period. | ||||
REFERENCES
- 1. Amsha K, Siddons TE, Armstrong I, et al. Effects of sildenafil on incremental shuttle walking test and haemodynamics in patients with pulmonary hypertension. Euro.Resp.Soc.Annu.Congress 2002:2311.
- 2. Bharani A, Mathew V, Sahu A, et al. The efficacy and tolerability of sildenafil in patients with moderate-to-severe pulmonary hypertension. Indian Heart Journal 2003;55(1):55-9.
- 3. Bhatia S, Frantz RP, Severson CJ, et al. Immediate and long-term hemodynamic and clinical effects of sildenafil in patients with pulmonary arterial hypertension receiving vasodilator therapy. Mayo Clinic Proceedings 2003;78(10):1207-13.
- 4. Galiè N, Ghofrani AH, Torbicki A, et al. Sildenafil Citrate Therapy for Pulmonary Arterial Hypertension. N Engl J Med 2005; 353(20): 2148-57.
- 5. Ghofrani AH, Wiedemann R, Rose F, et al. Sildenafil for treatment of lung fibrosis and pulmonary hypertension: a randomised controlled trial. The Lancet Sep 21, 2002; 360: 895-900.
- 6. Ghofrani H.A., Voswinckel R., Reichenberger F., et al. Differences in hemodynamic and oxygenation responses in three different phosphodiesterase-5 inhibitors in patients with pulmonary arterial hypertension. A randomized prospective study. J Am Coll Cardiol 2004; 44(7): 1488 – 1496.
- 7. Hattenhauer MG, Leavitt JA, Hodge DO, et al. Incidence of nonarteritic anterior ischemic optic neuropathy. Am J Ophthalmol 1997;123:103-107.
- 8. Johnson LN, Arnold AC. Incidence of nonarteritic and arteritic anterior ischemic optic neuropathy. J Neuroophthalmol 1994;14:38-44.
- 9. Keles T, Aydogdu S, Polat K, et al. Effect of short-term oral sildenafil treatment in primary pulmonary hypertension. Turk Kardiyoloji Dernegi Arsivi 2003;31(2):82-87.
- 10. Kerr NM, Chew SSSL, Danesh-Meyer, HV Non-arteritic anterior ischaemic optic neuropathy: A review and update. Journal of Clinical Neuroscience 16 (2009) 994–1000.
- 11. Kirchner PE, Becker R. Ocular effects of sildenafil on patients with pulmonary hypertension. Annual Meeting of the Association for Research in Vision and Ophthalmology, Fort Lauderdale, FL, USA, May 04-08, 2003 Sponsored by: Association for Research in Vision and Ophthalmology. AVRO-Annual-Meeting-Abstract-Search-and-Program-Planner 2003; 2003: Abstract No. 1292.
- 12. Kothari SS, Duggal B. Chronic oral sildenafil therapy in severe pulmonary artery hypertension. Indian Heart Journal 2002;54(4):404-9.
- 13. Kuhn KP, Wickersham NE, Robbins IM et al. Acute effects of sildenafil in patients with primary pulmonary hypertension receiving epoprostenol. Experimental Lung Research 2004;30(2):135-145.
- 14. Lepore JJ, Maroo A, Pereira NL, et al. Effect of sildenafil on the acute pulmonary vasodilator response to inhaled nitric oxide in adults with primary pulmonary hypertension. American Journal of Cardiology 2002;90(6):677.
- 15. McGoon M.D., Frantz R.P., Severson C.J., et al. Acute and short-term hemodynamic and clinical effects of sildenafil in pulmonary arterial hypertension. J Heart Lung Transplant 2003; 22(1s): S153 (abstr 245).
- 16. Michelakis E, Tymchak W, Lien D, et al. Oral sildenafil is an effective and specific pulmonary vasodilator in patients with pulmonary arterial hypertension: comparison with inhaled nitric oxide. Circulation 2002;105(20):2398-403.
- 17. Michelakis ED, Tymchak W, Noga M, et al. Long-term treatment with oral sildenafil is safe and improves functional capacity and hemodynamics in patients with pulmonary arterial hypertension. Circulation 2003;108(17):2066-2069.
- 18. Mikhail GW, Prasad S, Rogers P, et al. Clinical and hemodynamic effects of sildenafil in pulmonary arterial hypertension. Circulation 2002;106(No. 19):Suppl.
- 19. Mikhail GW, Prasad SK, Li W, et al. Clinical and haemodynamic effects of sildenafil in pulmonary hypertension: Acute and mid-term effects. European Heart Journal 2004;25(5):431-436.
- 20. Prasad SK, Mikhail G, Rogers P, et al. Effect of oral sildenafil on cardiac function and remodelling in patients with pulmonary arterial hypertension. Heart 2003;89(Suppl. 1):A24.
- 21. Pritzker MR, Dorman W, Caperton E. The use of sildenafil (Viagra) for the treatment of pulmonary hypertension associated with scleroderma. Arthritis Rheum 2001;44(No. 9):S131.
- 22. Pritzker MR, Groebner R. Acute haemodynamic response to sildenafil in chronic pulmonary hypertension. Journal of Cardiac Failure 2003; 9(5): S69.
- 23. Sastry B, Narasimhan C, Reddy N, et al. Clinical efficacy of sildenafil in primary pulmonary hypertension: a randomised, placebo-controlled, double-blind, crossover study. J Am Coll Cardiol. 2004;43(7):1149-1153.
- 24. Sastry BK, Narasimhan C, Reddy NK, et al. A study of clinical efficacy of sildenafil in patients with primary pulmonary hypertension. Indian Heart Journal 2002;54(4):410-4.
- 25. Watanabe H, Ohashi K, Takeuchi K, et al. Short- and long-term hemodynamic effects and safety of sildenafil in pulmonary hypertension. Circulation 2002;106(No. 19):Suppl.