


Product Monograph - Riva-Cyproterone
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 04/2022 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 04/2022 |
| 7 WARNINGS AND PRECAUTIONS - Carcinogenesis and Mutagenesis | 04/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................................2
TABLE OF CONTENTS ..........................................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................................4
1 INDICATIONS .........................................................................................................................4
2 CONTRAINDICATIONS.............................................................................................................4
3 SERIOUS WARNINGS AND PRECAUTIONS ................................................................................4
4 DOSAGE AND ADMINISTRATION ............................................................................................4
4.1 Dosing Considerations ........................................................................................................... 4
4.2 Recommended Dose and Dosage Adjustment ...................................................................... 5
5 OVERDOSAGE ........................................................................................................................5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ..............................................5
7 WARNINGS AND PRECAUTIONS ..............................................................................................6
7.1 Special Populations ................................................................................................................ 9
7.1.1 Pregnant Women ................................................................................................................ 9
7.1.2 Breast-feeding ..................................................................................................................... 9
7.1.3 Pediatrics............................................................................................................................. 9
8 ADVERSE REACTIONS .............................................................................................................9
8.1 Adverse Reaction Overview ................................................................................................... 9
8.2 Clinical Trial Adverse Reactions ............................................................................................ 11
8.3 Less Common Clinical Trial Adverse Reactions .................................................................... 11
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
.......................................................................................................................................... 11
8.5 Post-Market Adverse Reactions .......................................................................................... 11
9 DRUG INTERACTIONS ........................................................................................................... 11
9.2 Drug Interactions Overview ................................................................................................. 11
9.3 Drug-Behavioural Interactions ............................................................................................ 11
9.4 Drug-Drug Interactions ........................................................................................................ 11
9.5 Drug-Food Interactions ........................................................................................................ 12
9.6 Drug-Herb Interactions ........................................................................................................ 12
9.7 Drug-Laboratory Test Interactions ....................................................................................... 12
10 CLINICAL PHARMACOLOGY ................................................................................................... 12
10.1 Mechanism of Action ........................................................................................................... 12
10.3 Pharmacokinetics ................................................................................................................. 12
11 STORAGE, STABILITY AND DISPOSAL ..................................................................................... 14
12 SPECIAL HANDLING INSTRUCTIONS ....................................................................................... 14
PART II: SCIENTIFIC INFORMATION ................................................................................................... 15
13 PHARMACEUTICAL INFORMATION ........................................................................................ 15
14 CLINICAL TRIALS ................................................................................................................... 16
14.1 Trial Design and Study Demographics ................................................................................. 16
14.2 Study Results ........................................................................................................................ 17
14.3 Comparative Bioavailability Studies .................................................................................... 20
15 MICROBIOLOGY ................................................................................................................... 20
16 NON-CLINICAL TOXICOLOGY ................................................................................................. 20
17 SUPPORTING PRODUCT MONOGRAPHS ................................................................................ 24
PATIENT MEDICATION INFORMATION .............................................................................................. 25
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
RIVA-CYPROTERONE (cyproterone acetate) is indicated for:
- the palliative treatment of patients with advanced prostatic carcinoma
2 CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section.
- Liver disease and hepatic dysfunction.
- Dubin Johnson syndrome, Rotor syndrome
- Previous or existing liver tumors (only if these are not due to metastases from carcinoma of the prostate)
- Presence or history of meningioma
- Wasting diseases (with the exception of inoperable carcinoma of the prostate)
- Severe chronic depression
- Existing thromboembolic processes
3 SERIOUS WARNINGS AND PRECAUTIONS
Serious Warning Precautions RIVA-CYPROTERONE should be prescribed and managed by a qualified physician experienced in the use of hormonal therapy in prostate cancer. The following are clinically significant adverse events:
- Hepatotoxicity with acute hepatic failure (see Hepatic/Biliary/Pancreatic, Hepatotoxicity).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Patients with Hepatic Impairment
The use of RIVA-CYPROTERONE (cyproterone acetate) is contraindicated in patients with liver diseases and/or with hepatic dysfunction.
Patients with Renal Impairment
A pharmacokinetic study in patients with renal impairment has not been conducted. As 33% of cyproterone acetate is excreted via the kidney, caution should be taken when RIVA-CYPROTERONE is administered in this patient population.
4.2 Recommended Dose and Dosage Adjustment
Oral Tablets: The usual daily initial and maintenance dose of RIVA-CYPROTERONE (cyproterone acetate) is 4 to 6 tablets (200-300 mg) divided into 2 to 3 doses and taken with some liquid after meals.
The maximum daily dose is 300 mg.
After orchiectomy, a lower daily dose of 2 to 4 tablets (100-200 mg) is recommended.
RIVA-CYPROTERONE therapy should not be interrupted nor the dosage reduced after remission or improvement occurs.
Because of their pharmacokinetic properties, RIVA-CYPROTERONE and cyproterone acetate injection can be interchanged in the course of long-term treatment. The dosage may be reduced if side effects are intolerable, but should be kept within the oral range of 2 to 6 tablets daily (100-300 mg) or intramuscular injections of 300 mg at weekly intervals, or every two weeks.
Note: RIVA-CYPROTERONE is only available as a 50 mg oral tablet.
Health Canada has not authorized an indication for pediatric use.
5 OVERDOSAGE
There have been no reports of fatal overdosage in man with cyproterone acetate. There are no specific antidotes and treatment should be symptomatic. If oral overdosage is discovered within two to three hours, gastric lavage can safely be used if indicated.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 - Dosage forms, Strengths, Compositions and Packaging.
| Route of Administration | Dosage Form/Strength/Composition | Non-medicinal ingredients |
| Oral | Tablet /50 mg | Lactose, cellulose microcrystalline, croscarmellose sodium, povidone, and magnesium stearate. |
RIVA-CYPROTERONE (cyproterone acetate) 50 mg tablet is presented as white to faintly yellowish, round, flat-sided tablet with beveled edges, imprinted one side "50" in a regular hexagon, other side scored. The tablet can be divided into equal halves.
RIVA-CYPROTERONE (cyproterone acetate) 50 mg tablet is available in bottles of 100 and blisters of 60.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS Box at the beginning of PART I: HEALTH PROFESSIONAL INFORMATION.
General
Concomitant Alcohol: Alcohol may reduce the antiandrogenic effect of RIVA-CYPROTERONE (cyproterone acetate) in hypersexuality. The relevance of this in prostatic carcinoma is not known; however, it would be prudent to inform the patients that the use of alcohol during RIVA-CYPROTERONE therapy is not advisable.
Physical Performance: Patients should be informed that fatigue and lassitude are common in the first few weeks of therapy, but usually become much less pronounced from the third month on. Marked lassitude and asthenia necessitate special care when driving or operating machinery.
Concomitant Use With a GnRH Agonist or Orchiectomy: Based on a retrospective meta-analysis, long-term combination therapy of cyproterone acetate with either orchiectomy or a GnRH agonist as treatment of patients with advanced prostate cancer may result in a 5-year survival disadvantage compared to castration alone.
Carcinogenesis and Mutagenesis
Cyproterone acetate showed a potential to initiate and/or promote liver tumor formation in rodents. Very rare cases of benign and malignant liver tumors have been observed in patients receiving cyproterone acetate.
Meningioma: The occurrence of meningiomas (single and multiple) has been reported in association with long-term use (years) of cyproterone acetate at doses of 25 mg/day and above. The risk of meningioma increases with increasing cumulative doses of cyproterone acetate. In a retrospective cohort study using data from a primary care database, meningiomas were reported very rarely in patients treated with cyproterone acetate for prostate cancer after several months of treatment; in these cases, causality was not established. If a patient treated with RIVA-CYPROTERONE is diagnosed with a meningioma, treatment with cyproterone containing products, including RIVA-CYPROTERONE must be permanently stopped. Patients with prehistory or presence of meningioma should not be treated with RIVA-CYPROTERONE (see 2 CONTRAINDICATIONS).
Antiandrogen Withdrawal Syndrome: In some patients with metastatic prostate cancer, antiandrogens (steroidal or nonsteroidal) may promote, rather than inhibit, the growth of prostate cancer. A decrease in PSA and/or clinical improvement following the discontinuation of antiandrogens has been reported. It is recommended that patients prescribed an antiandrogen, who have PSA progression, should have the antiandrogen discontinued immediately and be monitored for 6 to 8 weeks for a withdrawal response prior to any decision to proceed with other prostate cancer therapy.
Gynecomastia: Benign nodules (hyperplasia) of the breast have been reported; these generally subside 1 to 3 months after discontinuation of therapy and/or after a reduction of dosage. The reduction of dosage should be weighed against the risk of inadequate tumor control.
Endocrine and Metabolism
Adrenocortical Function: Suppression of adrenocortical function tests have occurred in patients receiving cyproterone acetate and preclinical data also revealed a suppression of adrenal gland due to the administration of cyproterone acetate (see 16 NON-CLINICAL TOXICOLOGY).
Reduced response to endogenous ACTH was noted by metyrapone test; furthermore, reduced ACTH and cortisol blood levels determined by the Mattingly method were also found.
It is therefore recommended that adrenocortical function tests should be monitored periodically by serum cortisol assay.
Diabetes: RIVA-CYPROTERONE may impair carbohydrate metabolism. Parameters of carbohydrate metabolism, fasting blood glucose and glucose tolerance tests, should be examined carefully in all patients and particularly in all diabetics before and regularly during therapy with RIVA-CYPROTERONE.
Strict medical supervision is necessary if the patient suffers from diabetes, because the requirement for oral antidiabetics or insulin can change during RIVA-CYPROTERONE treatment.
Metabolic Effects: Fluid retention, hypercalcemia and changes in plasma lipid profile may occur. Accordingly, RIVA-CYPROTERONE should be used with caution in patients with cardiac disease.
Nitrogen Balance: A negative nitrogen balance is usual at the start of therapy, but does generally correct itself within 3 months of continued therapy.
Hematologic
Hematology: Hypochromic anemia has been observed rarely during therapy with cyproterone acetate. Regular hematological assessment is recommended.
Thromboembolism: Clinical investigations have shown that when cyproterone acetate is used alone it has a minor effect on blood clotting factors. However, when cyproterone acetate was combined with ethinyl estradiol, changes were found in increased coagulation capability.
The occurrence of thromboembolic events has been reported in patients using cyproterone acetate, although a causal relationship has not been established. Patients with previous arterial or venous thrombotic / thromboembolic events (eg, deep venous thrombosis, pulmonary embolism, myocardial infarction) or with a history of cerebrovascular accidents or with advanced malignancies are at increased risk of further thromboembolic events.
RIVA-CYPROTERONE should be discontinued at the first sign of thrombophlebitis or thromboembolism, and the patient should be carefully re-evaluated if manifestations of thrombotic disorder occur: thrombophlebitis, cerebrovascular complications, retinal thrombosis, or pulmonary embolism.
In patients with inoperable carcinoma of the prostate, presenting with a history of thromboembolic processes or suffering from sickle cell anemia or from severe diabetes with vascular changes, a careful risk: benefit evaluation must be carried out in each individual case before RIVA-CYPROTERONE is prescribed.
Hepatic/Biliary/Pancreatic
Hepatotoxicity: Direct hepatic toxicity, including jaundice, hepatitis, and acute hepatic failure has been observed in patients treated with cyproterone acetate. At daily doses of 100 mg and above, cases with fatal outcome have also been reported. Most reported fatal cases were in men treated with cyproterone acetate for prostatic cancer. Hepatotoxicity is dose-related and develops, usually, a few weeks to several months after cyproterone treatment has begun. Liver function tests should be performed pretreatment, at regular intervals during treatment, and whenever any symptoms or signs suggestive of hepatotoxicity occur. If hepatotoxicity is confirmed, RIVA-CYPROTERONE should be withdrawn. Benefit and risk should be evaluated carefully if any drug(s) with known hepatotoxicity is to be used concurrently with RIVA-CYPROTERONE. RIVA-CYPROTERONE should not be used in patients with prior history or existing hepatic disease (see 2 CONTRAINDICATIONS).
In very rare cases, benign and malignant liver tumors which may lead to life-threatening intra- abdominal haemorrhage have been observed after the use of cyproterone acetate. If severe upper abdominal complaints, liver enlargement, or signs of intra-abdominal haemorrhage occur, a liver tumor should be included in the differential-diagnostic considerations.
Monitoring and Laboratory Tests
It is recommended that patients prescribed an antiandrogen, who have PSA progression, should have the antiandrogen discontinued immediately and be monitored for 6 to 8 weeks for a withdrawal response prior to any decision to proceed with other prostate cancer therapy.
With the potential for adrenal gland suppression, it is recommended that adrenocortical function tests should be monitored periodically by serum cortisol assay. Parameters of carbohydrate metabolism, fasting blood glucose, and glucose tolerance tests, should be examined carefully in all patients and particularly in all diabetics before and regularly during therapy with RIVA-CYPROTERONE.
During treatment with RIVA-CYPROTERONE, serum electrolytes and complete blood counts should be performed regularly. Liver function tests should be performed pretreatment, at regular intervals during treatment, and whenever any symptoms or signs suggestive of hepatotoxicity occur.
Psychiatric
Depression: Cyproterone acetate therapy has occasionally been associated with an increased incidence of depressive mood changes, especially during the first 6 to 8 weeks of therapy. Similar mood changes have also been seen following surgical castration and are considered to be due to androgen deprivation. Patients with tendencies to depressive reaction should be carefully observed.
Respiratory
Shortness of Breath: A sensation of shortness of breath was commonly reported in patients treated with 300 mg/day cyproterone acetate. Patients with pre-existing pulmonary dysfunction are most likely to be affected.
Reproductive Health
Inhibition of Spermatogenesis: The sperm count and the volume of ejaculate are reduced at oral doses of 50 to 300 mg per day. Infertility is usual, and there may be azoospermia after 8 weeks of therapy, which is associated with atrophy of seminiferous tubules.
Follow-up examinations on discontinuation of therapy have shown these changes to be reversible.
Spermatogenesis usually reverts to its previous level about 3 to 5 months after stopping cyproterone acetate, or in some patients, after up to 20 months. Production of abnormal spermatozoa during cyproterone acetate therapy has been observed; their relationship to abnormal fertilization or malformed embryos is not known.
Skin
RIVA-CYPROTERONE therapy may cause a reduction of sebum production leading to dryness of the skin and transient patchy loss of body hair.
7.1 Special Populations
7.1.1 Pregnant Women
Treatment with RIVA-CYPROTERONE is not indicated for use in women.
7.1.2 Breast-feeding
Treatment with RIVA-CYPROTERONE is not indicated for use in women.
7.1.3 Pediatrics
RIVA-CYPROTERONE is not recommended for use in children and adolescents below 18 years of age.
RIVA-CYPROTERONE must not be given before the conclusion of puberty since an unfavorable influence on longitudinal growth and the still unstabilized axes of endocrine function cannot be ruled out.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The adverse events associated most frequently with the use of cyproterone acetate are those related to the hormonal effects of the drug. These reactions usually disappear upon discontinuation of therapy or reduction of dose: decreased libido, breast enlargement, breast tenderness, benign nodular hyperplasia of the breast, galactorrhea, gynecomastia, abnormal spermatozoa, impotence, and inhibition of spermatogenesis.
The most serious adverse drug reactions (ADRs) in patients receiving cyproterone acetate are hepatic toxicity, benign and malignant liver tumors which may lead to intra-abdominal hemorrhage, and thromboembolic events.
As with other antiandrogenic treatments, long-term androgen deprivation with RIVA-CYPROTERONE may lead to osteoporosis.
Other adverse events which have been reported are listed below:
Cardiovascular System: hypotension, tachycardia, heart failure, syncope, myocardial infarct, hemorrhage, cerebrovascular accident, cardiovascular disorder, retinal vascular disorder, embolus, pulmonary embolism, superficial and deep thrombophlebitis, thrombosis, retinal vein thrombosis, phlebitis, vascular headache, shock, pulmonary oil microembolism, vasovagal reactions.
Gastrointestinal System: constipation, diarrhea, indigestion, anorexia, nausea, vomiting, cholestatic jaundice, cirrhosis of liver, hepatic coma, hepatitis, hepatoma, hepatomegaly, jaundice, liver carcinoma liver failure (for further information see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic), abnormal liver function test, liver necrosis, pancreatitis, glossitis.
Hematology: increased fibrinogen, decreased prothrombin, thrombocytopenia, anemia (for further information see 7 WARNINGS AND PRECAUTIONS, Hematologic), hemolytic anemia, hypochromic anemia, normocytic anemia, leukopenia, leukocytosis.
Metabolism: negative nitrogen balance, decreased response to ACTH, hyperglycemia, lowered cortisol, hypercalcemia, increased SGOT, increased SGPT, increased creatinine, hypernatremia, edema, weight gain, weight loss, diabetes mellitus.
Musculoskeletal System: myasthenia, osteoporosis.
Central Nervous System: fatigue, lassitude, weakness, hot flashes, increased sweating, aphasia, coma, depression, dizziness, encephalopathy, hemiplegia, personality disorder, psychotic depression, abnormal gait, headache, temporary restlessness.
Meningiomas (single and multiple) have been reported in association with long-term use (several years) of cyproterone acetate. In a retrospective cohort study using data from a primary care database, meningiomas were reported very rarely in patients treated with cyproterone acetate for prostate cancer after several months of treatment; in these cases, causality was not established (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis).
Respiratory System: asthma, increased cough, dyspnea, hyperventilation, respiratory disorder, shortness of breath on effort (see 7 WARNINGS AND PRECAUTIONS, Respiratory), lung fibrosis.
Skin: eczema, urticaria, erythema nodosum, exfoliative dermatitis, rash, maculopapular rash, dryness of the skin, pruritus, alopecia, hirsutism, skin discoloration, photosensitivity reactions, scleroderma.
Sensory System: ear disorder, optic atrophy, optic neuritis, abnormality of accommodation, abnormal vision, blindness, retinal disorder.
Urogenital System: enlarged uterine fibroids, uterine hemorrhage, increased urinary frequency, bladder carcinoma, kidney failure, hematuria, urate crystalluria, urine abnormality.
Other: ascites, allergic reaction, asthenia, chills, fetal chromosome abnormality, death, fever, hernia, malaise, injection site reaction.
Adverse reactions are rarely of sufficient severity to require dosage reduction or discontinuation of treatment.
If reactions are severe, it may be beneficial to reduce the dosage.
8.2 Clinical Trial Adverse Reactions
The clinical trial data on which the original indication was authorized is not available.
8.3 Less Common Clinical Trial Adverse Reactions
The clinical trial data on which the original indication was authorized is not available.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
The clinical trial data on which the original indication was authorized is not available.
8.5 Post-Market Adverse Reactions
Meningioma.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Although clinical interaction studies have not been performed, since this drug is metabolized by CYP3A4, it is expected that ketoconazole, itraconazole, clotrimazole, ritonavir, and other strong inhibitors of CYP3A4 inhibit the metabolism of cyproterone acetate. On the other hand, inducers of CYP3A4 such as rifampicin, phenytoin, and products containing St. John’s wort may reduce the levels of cyproterone acetate.
Based on in vitro inhibition studies, an inhibition of the cytochrome P450 enzymes CYP2C8, 2C9, 2C19, 3A4, and 2D6 is possible at high therapeutic cyproterone acetate doses of 300 mg daily. In addition, cyproterone acetate was also shown to increase the enzymatic activity of CYP1A2 and CYP2E1 in vitro. Caution should be exercised when RIVA-CYPROTERONE (cyproterone acetate) is to be co-administered with a substrate of the P450 enzymes.
The risk of statin-associated myopathy or rhabdomyolysis may be increased when those HMGCoA inhibitors (statins) which are primarily metabolized by CYP 3A4 are coadministered with high therapeutic cyproterone acetate doses, since they share the same metabolic pathway.
9.3 Drug-Behavioural Interactions
This information is not available for this drug product.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory test have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
RIVA-CYPROTERONE (cyproterone acetate) is a steroid which clinically demonstrates two distinct properties:
- a) Antiandrogenic: Cyproterone acetate blocks the binding of dihydrotestosterone - the active metabolite of testosterone - to the specific receptors in the prostatic carcinoma cell.
- b) Progestogenic/antigonadotrophic: Cyproterone acetate exerts a negative feed-back on the hypothalamo-pituitary axis, by inhibiting the secretion of LH leading to diminished production of testicular testosterone.
10.3 Pharmacokinetics
Absorption:
Cyproterone acetate
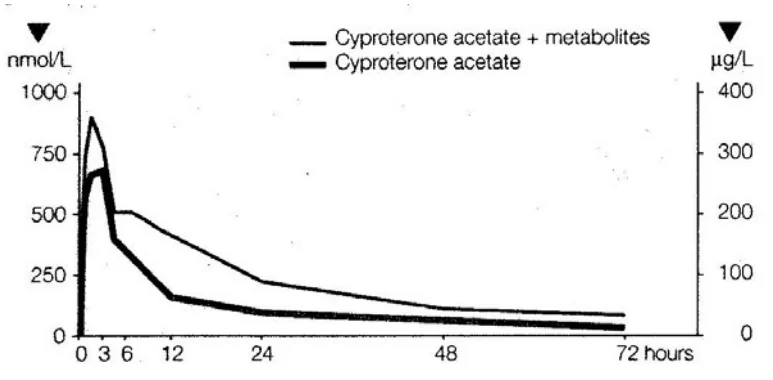
The absorption of cyproterone acetate following oral administration is complete. Peak plasma levels are reached 3 to 4 hours after administration. Plasma levels fall rapidly during the first 24 hours as a result of tissue distribution and excretion, and plasma half-life was 38 ± 5 hours.
Metabolism:
The principal metabolite identified was 15β-hydroxy-cyproterone acetate.
Excretion:
Most of the cyproterone acetate is excreted unchanged in the feces (60%) or urine (33%) within 72 hours.
Cyproterone acetate is eliminated with the urine mainly in the form of unconjugated metabolites and with the bile (feces) in the form of glucuronidized metabolites.
Detailed Human Pharmacology
Antiandrogenic Effect
The following actions which are associated with the antiandrogenic effects have been described in man: reduction of sexual drive; inhibition of spermatogenesis; palliative effect in prostatic carcinoma; inhibition of sebaceous gland activity; suppression of signs of androgenization in women; inhibition of premature genital development in children; and other associated symptoms.
Progestogenic and Antigonadotrophic Effect
Cyproterone acetate in man is also a potent progestogen and has an antigonadotrophic effect. It intervenes with the hypothalamo-pituitary pathway, causing an inhibition of increased secretion of LH, and a decrease in gonadal testicular androgens.
Thus, unlike pure antiandrogens, cyproterone acetate does not cause a compensatory increase in androgen secretion.
Other Endocrine Effects
No distinct influence on the 17-ketosteroids, 17-ketogenic steroids or on total estrogens in the 24-hour urine has been observed in male patients. On fluorometric determination of urinary cortisol, the value apparently increases because the cyproterone acetate eliminated with the urine is also measured. Simultaneously, cyproterone acetate also reduces the reaction of the adrenal cortex to exogenous ACTH in patients; the baseline cortisol and ACTH values may also be reduced.
Pharmacokinetics
A bioavailability study was performed in 5 male volunteer subjects receiving a single oral dose of 50 mg 14C-cyproterone acetate tablets.
Results of the study showed that cyproterone acetate is absorbed slowly, but completely (100%), from the gastrointestinal tract. The maximum plasma level was reached 3 to 4 hours after ingestion. The mean plasma levels were 700 nmol/L (=290mcg/L) cyproterone acetate or, including the radioactivity of metabolites, 960 nmol/L (=400mcg/L) cyproterone acetate equivalent.
The plasma levels fell quickly up to 24 hours after administration because of extensive tissue distribution. The half-life of cyproterone acetate in plasma was calculated as 38 ± 5 hours (see Figure 1).
Figure 1: Relationship of Unchanged Cyproterone Acetate to the Total 14C-labelled Substance (Cyproterone Acetate + Metabolites) in the Plasma of a Male Subject Following Oral Administration of 50 mg 14C cyproterone Acetate
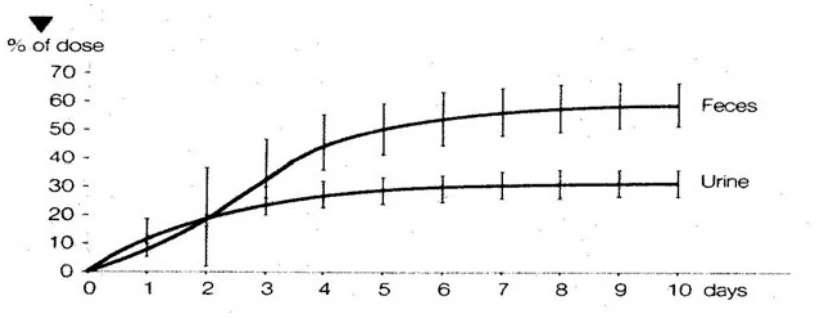
On oral administration cyproterone acetate was eliminated with a half-life of 38 ± 2 hours. After 10 days, 33 ± 6% of the dose could be recovered in the urine and 60 ± 8% in the feces (see Figure 2).
Figure 2: Elimination (% of Dose) Following Oral Administration of 50 mg 14C-cyproterone Acetate in Male Subjects. Mean Values ± Standard Deviation (n=5)
11 STORAGE, STABILITY AND DISPOSAL
Store at controlled room temperature (15°C to 30°C). Protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling requirements for this product. 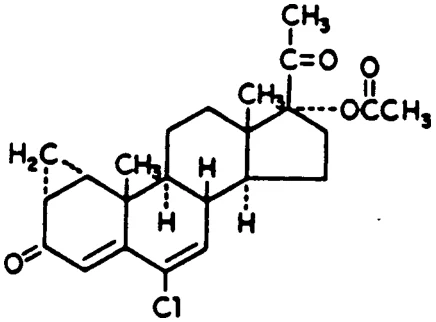
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Cyproterone acetate
Chemical name: 6-chloro-17α-hydroxy-1α, 2α-methylene- pregna-4, 6- diene-3, 20-dione-acetate
Molecular formula and molecular mass: C24H29ClO4 416.95 g/mol
Structural formula:
Physicochemical properties: White to faintly yellow micronized powder.
Insoluble in water, very freely soluble in chloroform and dioxane. Melting range is 206- 213°C.
14 CLINICAL TRIALS
A total of 24 studies have been conducted with cyproterone acetate in patients requiring palliative treatment for advanced prostatic carcinoma. Worldwide, more than 1,000 patients have participated in these studies, which included several large multicentre trials in addition to the important comparative multicentre trial conducted by the European Cancer Oncology Group. North American experience has been accumulated in the U.S. by Drs. Scott (Johns Hopkins Hospital, Baltimore), Geller (Mercy Hospital & Medical Center, San Diego), and by Drs. Wein and Murphy (Hospital of the University of Pennsylvania, Philadelphia).
14.1 Trial Design and Study Demographics
Patients and Stage of Disease
As shown in Table 2, more than 90% of the patients treated with cyproterone acetate had stage C advanced prostatic carcinoma, or stage D1 or D2 prostatic carcinoma with metastasis.
Table 2: Patients
| Stage | No. of Patients |
| A or B | 18 |
| C | 174 |
| C or D | 502 |
| D | 349 |
| Not specified | 39 |
| Total | 1082 |
The majority of patients (75%) had had no therapy prior to treatment with cyproterone acetate. A large group of patients had received various types of estrogen therapy, but had proven to be refractory or unable to tolerate the drug. A few patients had undergone an orchiectomy or had received radiation therapy (Table 3).
Table 3: Previous Therapy
| Previous Therapy | No. of Patients |
| None | 809 |
| Orchiectomy | 76 |
| Estrogen | 253 |
| Radiation | 16 |
Dosage and Administration
The oral route of administration of cyproterone acetate was employed in 910 patients (84%), while 172 patients received cyproterone acetate injection, an oily solution containing 100 mg/mL cyproterone acetate. The standard dose of the latter was one weekly IM injection of 300 mg. As shown in the table below (Table 4), the daily oral dose varied considerably from study to study and from patient to patient. However, most patients were treated with doses ranging from 200 to 300 mg/day. In orchiectomized patients, the daily dose was generally reduced by about 50% to a range of 100 to 200 mg/day orally or the frequency of cyproterone acetate injections was reduced to one every 2 weeks.
Table 4: Dose of cyproterone acetate
| Entity | Route | Dose | No. of Patients |
| Cyproterone acetate | Oral | 100 mg/day | 15 |
| 200 mg/day | 197 | ||
| 250 mg/day | 135 | ||
| 300 mg/day | 114 | ||
| 100-300 mg/day | 449 | ||
| Cyproterone acetate | IM | 300 mg/week | 172 |
Only 32 patients (3%) received concomitant drug therapy with cyproterone acetate. No other patients received concomitant drugs, but 521 patients (48%) underwent an orchiectomy (Table 5).
Table 5: Concomitant Therapy
| Concomitant Therapy | No. of Patients |
| None | 529 |
| Estrogen (DES 0.1 mg) | 32 |
| Orchiectomy | 521 |
14.2 Study Results
Effect on Serum Testosterone and Prostatic Acid Phosphatase (PAP)
Table 6: Effect on Serum Testosterone and Prostatic Acid Phosphatase (PAP)
| Parameter | No. of Studies | Result |
| Serum testosterone | 7 | 70-90% reduction |
| Prostatic acid phosphatase | 11 | Normalization in 90% of responding |
patients
The effect of cyproterone acetate on serum testosterone was monitored in 7 studies (Table 6). Serum testosterone was rapidly reduced following daily oral doses of 200 to 300 mg, with castrate levels being achieved within 1 to 4 weeks. The reduction was usually in the order of 70% to 90%; the greatest percent reduction occurred when cyproterone acetate was combined with estrogen.
Results of PAP evaluations consistently showed a normalization of values within a very short time in responding patients. Similarly, when there were signs of progressing metastasis, PAP values again deviated from normal levels.
Effect on Primary Tumor
The effect of cyproterone acetate on the primary tumor was assessed in a total of 678 patients. Of these, 489 were previously untreated; the primary tumor was reduced in 318 of these (65%) and was stabilized in another 69 (14%). Thus, the overall positive response rate in this group was 79% (Table 7).
A significant, though smaller, percentage (59%) of estrogen-refractory patients also exhibited a positive result.
Table 7: Effect on Primary Tumor
| Patient Group | Number | Response of Primary Tumor | Total With Positive Effect | |
| Reduced | Stabilized | |||
| Previously | 489 | 318 (65%) | 69 (14%) | 387 (79%) |
untreated Estrogen refractory | 189 | 112 (59%) | - | 112 (59%) |
Effect on Metastasis
As shown in Table 8, metastasis was reduced in 31% of 216 evaluable patients who had not previously been treated, but in only 13% of the evaluable estrogen-refractory patients. The progression of metastases appeared to be time-dependent. Despite reduced serum testosterone levels, metastases progressed over a period of several months to years, even in patients who were initially stabilized. The major cause of death during therapy with cyproterone acetate was the progression of metastases and not the primary tumors.
Table 8: Effect on Metastases
| Patient Group | Number | Response of Metastases | Total with Positive Effect | |
| Reduced | Stabilized | |||
| Previously untreated | 216 | 67 (31%) | 82 (39%) | 149 (70%) |
| Estrogen refractory | 71 | 10 (13%) | 7 (10%) | 17 (23%) |
Effect on Pain
Table 9 illustrates the incidence of pain relief reported in each of 13 studies. Pain relief was noted in approximately 50% to 80% of patients receiving treatment with cyproterone acetate. The effect of cyproterone acetate on pain generally paralleled its effect on metastases. As long as metastases remained improved or stabilized, the analgesic requirement was also reduced. Renewed analgesic requirements were frequently indicative of metastatic progression.
Table 9: Pain Relief
| Investigator | Incidence of Pain Relief |
| Dr. Bracci | 172/216 |
| Dr. Giuliani | 12/16 |
| Dr. Smith | 12/25 |
| Dr. Scott | 8/10 |
| Dr. Geller | 8/10 |
| Dr. Mauermayer | 38/58 |
| Dr. Wein | 13/24 |
| Dr. Tveter | 2/6 |
| Dr. Di Silverio | 13/20 |
| Dr. Ah-Lan | 9/16 |
| Dr. Pescatore | 12/16 |
| Dr. Hermabessiere | 2/4 |
| Dr. Bruchovsky | 15/24 |
| Total | 316/425 = 74% |
Subjective and Objective Responses
A general improvement in the subjective assessment of the quality of life was achieved in 70% of the 367 evaluable patients (Table 10).
The objective evaluations of remissions shown in Table 10 were based on ECOG criteria. The best results were obtained when cyproterone acetate was used in combination with orchiectomy. One study revealed that more than 1/3 of the patients treated with cyproterone acetate achieved a complete or partial remission for 3 to 5 years. The Canadian study found that a complete or partial remission was still evident in 75% of the patients after one year of treatment.
Table 10: Subjective and Objective Responses
| Subjective Responses | |||
| No. Evaluable Patients | No. Improveda | ||
| 367 | 255 (70%) | ||
| Objective Responses (ECOG Criteria) | |||
| Treatment | Patient Group | No. of Patients | No. With Complete or Partial Remissions |
| Cyproterone acetate | Previously untreated | 270 | 134 (50%) |
| Cyproterone acetate | Estrogen-refractory | 77 | 31 (44%) |
Cyproterone acetate/Orchiectomy | Previously untreated and/or estrogen-refractory | 274 | 154 (60%) |
a Based on criteria of general improvement in quality of life (ie, weight gain, pain relief, etc.)
Survival Rate
Table 11: Survival Rate
| Investigator | No. of Patients | Stage | Duration of Treatment | Survival | |
| Cyproterone acetate | Estrogen | ||||
| Dr. Mauermayer | 58 | C or D | 2 - 5 years | 38/58 (70%) | - |
| Dr. Wein | 55 | A (7) | 4 years | 39/55 (70%) | - |
| C (25) | |||||
| D (23) | |||||
| Dr. Bracci | 216 | C or D | 5 years | 138/216 (64%) | - |
| Dr. Di Silverio | 20 | D | up to 38 months | 3/20 (15%) | - |
| Dr. Giuliani | 68 | C | 5 years | 30/68 (44%) | 31% |
| Dr. Giuliani | 38 | D | 3 years | 10/38 (27%) | 10% |
| Dr. Jacobi | 51 | C or D | 2 years | 18/40 (45%) | - |
| Dr. Pavone | 103 | C or D | 3.5 - 5 years | 42/103 (41%) | 41% |
| Dr. Bruchovsky | 29 | D | 9 - 15 months | 23/29 (80%) | - |
As shown in Table 11 above, 5-year survival rates ranged from 41% to 64%. The 3-year rate for stage D patients was 27% and 1- to 2-year rates varied from a low of 15% up to a high of 80%. These survival rates generally represented an improvement over results previously obtained with estrogen therapy.
14.3 Comparative Bioavailability Studies
A two-way, single-dose (1 x 50 mg), crossover comparative bioavailability study of RIVA-CYPROTERONE (Laboratoire Riva Inc.) and ANDROCUR® (Bayer Inc., Canada), was conducted in healthy male and female subjects under fasting conditions. A summary of the bioavailability data from the 19 subjects who completed the study are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Cyproterone Acetate (1 x 50 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUC0-72h (ng·h/mL) | 1843.70 1858.70 (24.31) | 1934.41 1949.19 (23.75) | 95.31 | 91.72 - 99.04 |
Cmax (ng/mL) | 135.47 139.41 (34.91) | 145.15 149.23 (28.52) | 93.33 | 86.69 - 100.48 |
| Tmax3 (h) | 2.33 (1.00-6.00) | 2.33 (1.50-3.33) | ||
1 RIVA-CYPROTERONE (cyproterone acetate) tablet, 50 mg (Laboratoire Riva Inc.)
2 ANDROCUR® (cyproterone acetate) tablet, 50 mg (Bayer Inc., Canada)
3 Expressed as the median (range) only
Due to the long elimination half-life of cyproterone, AUCI and T1/2 could not be accurately calculated from the data obtained in this study.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Cyproterone acetate has been found at low doses of 2 to 10 mg/kg to cause liver abnormalities in dogs and rats in the form of proliferative liver changes including increased liver weight, liver cell hypertrophy with an increase in the smooth endoplasmic reticulum, and a rise in the serum glutamic pyruvic transaminase (SGPT). At high doses of 50 to 100 mg/kg, nodular hepatic hyperplasia and hepatomas have also been observed.
In repeat-dose studies conducted in rats (12 weeks) and dogs (54 weeks) with oral administration of cyproterone acetate, decreased adrenal weights in rats at 4.0 mg/kg/day and dogs at 10 mg/kg were noted. Marked atrophy of zona fasciculate and of zona reticularis with preservation of zona glomerulosa was also observed in the adrenal glands of all treated dogs.
Acute Toxicity
The LD50 after single application of cyproterone acetate was as follows:
Table 12: LD50 After Single Application of Cyroterone Acetate
| Animal Species | Oral (mg/kg) | Subcutaneous (mg/kg) | Intraperitoneal (mg/kg) | Intramuscular (mg/kg) |
| Mouse | >6000 | >5000 | >4000 | - |
| Rat | >4000 | 1500 | 1000 | - |
| Dog | >3000 | - | - | >100 (approx.) |
On the basis of the above LD50 values, cyproterone acetate can be considered practically nontoxic following single dose administration. The maximum intramuscular doses were also tolerated without symptoms in the dog, with exception of local tolerance manifestation.
Repeated Dose Toxicity
Repeat-dose toxicity studies revealed pathological changes in the liver, reproductive organs, adrenal glands, abnormal laboratory tests, and neoplasms of various tissues and organs in the animal species tested.
Chronic Toxicity Studies
Table 13: Chronic Toxicity Studies
Animal Species | Dosage and Duration | Mortality and Clinical and Laboratory Observations | Necropsy and Histopathology |
Rats 35/sex/ dose | 0; 10; 50 and 250 mg/kg 78 weeks oral | 250 mg/kg: marked increase in mortality rate. 50 and 250 mg/kg: 40-50% decrease in body weight gain. SGPT increase: males 10 and 250 mg/kg; females 50 mg/kg. BUN increase: males 50 and 250 mg/kg. Cholesterol increase: all treated groups. | Dose-related increase in liver weights. Increase thyroid weight except for low dose males. Dose-related decrease in gonads, adrenal, prostate, seminal vesicle, and uterus weights. Histopathology: toxic manifestation in liver and kidneys - less at 10 mg/kg, more extensive at 50 and 250 mg/kg. Changes included: yellow nodules and mottling of liver (including liver cell hyperplasia and liver cell adenomas and endoplasmic inclusion bodies), discolored kidneys with rough surfaces. |
Animal Species | Dosage and Duration | Mortality and Clinical and Laboratory Observations | Necropsy and Histopathology |
Rats 60/sex/ dose | 0; 0.04; 0.4 and 2 mg/kg 104 weeks oral | No drug-related mortality. Dose-related decrease in body weight gains in males and increase in females. Food consumption reduced and thinning and loss of hair was also noted for high-dose males. Decrease in hemoglobin and erythrocytes at 0.4 and 2 mg/kg. SGOT, SGPT and alkaline phosphatase increased at 2 mg/kg. | 2 mg/kg increased incidence of subcutaneous masses and/or nodules; liver discoloration and nodules; atrophy of testes, seminal vesicles, and prostate. Increased incidence of mammary neoplasms (adenomas and adenocarcinomas). |
Mice 50/sex/ dose | 0; 0.04; 0.4 and 2 mg/kg 105 weeks oral | No dose-related mortality. Thinning and loss of hair at 2 mg/kg. Slightly reduced body weight gain at 2 mg/kg. | Slightly increased incidence of skin masses and/or nodules and alopecia. No drug-related inflammatory, degenerative, proliferative and/or neoplastic lesions. |
| Dogs Beagle 4/sex/ dose | 0; 10; 32 and 100 mg/kg 55 weeks oral | No mortality. Excessive lacrimation, retarded pupillary reflex, mild conjunctivitis, hyperemia of gums, abdominal distention, sparsity of hair, and quieted behaviour. Laboratory tests: slightly elevated alkaline phosphatase and SGPT at 100 mg/kg in 2 dogs. Elevated sedimention rate, slightly reduced lymphocytes with increase in segmented neutrophils and decrease in eosinophils. | Reduced adrenal, testes, and prostate weight for all cyproterone acetate-treated animals. Ovary and uterus weights reduced at 100 mg/kg. Liver weight slightly increased for some dogs. Histopathology: marked adrenal atrophy of zona fasciculata and reticularis, testicular atrophy and absence of spermatogenesis, some Leydig cell hyperplasia, prostatic atrophy, ovarian and uterine atrophy, hyperplasia of mammary gland in males and females. |
Rhesus monkey 4 females/ dose | 0; 0.04; 0.4 and 40 mg/kg 12 weeks oral | No mortality or behaviour changes. Dose-related alopecia. Raised insulin level above 0.04 mg/kg. Negative influence on coagulation at 0.4 mg/kg and 40 mg/kg. Stimulation of ACTH cells at 0.4 mg and above. Increase in prolactin cells and slight reduction in gonadotrophin cells. Galactorrhea in all treated. | At doses of 0.4 mg/kg and above – diffuse liver cell hypertrophy and an increase in smooth endoplasmic reticulum. At the two highest doses, 2 and 3 animals also had occasional eosinophil cytoplasmic inclusion bodies in the liver cells. In most treated animals small mammary nodules were palpable in the glandular tissue; at 40 mg/kg slight ductus proliferation was also noted. |
Mutagenesis and Carcinogenesis
Recognized first-line tests of genotoxicity gave negative results when conducted with CPA. No mutagenic effect of cyproterone acetate was demonstrated in either in vitro (Salmonella typhimurium) or in vivo (micronucleus test in the monkey). However, further tests showed that CPA was capable of producing DNA adducts and an increase in DNA repair activity in liver cells from rats and monkeys and also in freshly isolated human hepatocytes.
This DNA-adduct formation occurred at systemic exposures that might be expected to occur in the recommended dose regimens for CPA. One in vivo consequence of CPA treatment was the increased incidence of focal, possible preneoplastic liver lesions in which cellular enzymes were altered in female rats. An initiating potential besides promoting effect of cyproterone acetate on the formation of ATPase deficient and γGT positive foci in female rat livers was noted. CPA also enhanced the frequencies of mutations in the livers of female transgenic rats in a dose-dependent manner, indicating that CPA is mutagenic.
Investigations into the tumorigenicity of cyproterone acetate did not reveal a specific tumorigenic potential in the liver of rodents although other neoplasms, including mammary adenocarcinoma in rats, were observed (see Table 14).
Reproductive Toxicology
Testicular atrophy and absence of spermatogenesis, some Leydig cell hyperplasia, prostatic atrophy, ovarian and uterine atrophy were observed in beagle dogs. A reduced number of pregnancies in untreated female rats was observed when male rats were administered with 40 mg/kg/day cyproterone acetate. The temporary inhibition of fertility in male rats brought about by daily oral treatment of cyproterone acetate did not result in malformations or impairment of fertility in the offspring produced by untreated female animals.
The treatment of pregnant animals with cyproterone acetate leads to developmental disturbances in male fetuses. Testosterone-dependent differentiation processes are affected: signs of feminization of varying degrees of severity develop.
Table 14: Fertility and Reproduction Study
| Animal Species | Route and Dosage of Administration | Findings |
Rats 24/sex/dose (2 generations) | 0; 0.4; 4.0 and 40 mg/kg oral | 0.4 mg/kg: No influence by drug on fertility of the P1 and F1 generations. 4 mg/kg: Significant decrease in body weights but no impairment of pre-and postnatal development. 40 mg/kg: Food intake and body weight gain reduced. Although attempted matings were increased, less than 50% of the females had litters. No specific pathological changes were found in the dams, fetuses, or young. Similarly, no malformations were observed. |
Detailed Animal Pharmacology
Antiandrogenic Effects
Cyproterone acetate at doses of 10 or 50 mg/kg inhibits the effects of endogenously produced and exogenously administered androgens at the prostate by means of competitive inhibition.
In mice and dogs, cyproterone acetate induces a dose-dependent atrophy of the accessory sex glands, the prostate, seminal vesicles, and preputial glands.
Spermatogenesis is inhibited in a dose-related manner; however, the atrophy in the Leydig cells are slight.
In the rat the start of puberty is prevented or delayed. Cyproterone acetate inhibits the physiological closure of the epiphyseal cartilages and bone maturation.
It impairs the function of the sebaceous glands, and the thickness of the epidermis decreases.
The treatment of pregnant animals with cyproterone acetate leads to developmental disturbances in male fetuses. Testosterone-dependent differentiation processes are affected: signs of feminization of varying degrees of severity develop.
Progestogenic and Antigonadotrophic Effect
On subcutaneous injections a total dose of 0.003 mg cyproterone acetate is about 100 times stronger than progesterone in the maintenance of pregnancy (Clauberg test). Like all potent progestogens, cyproterone acetate has antigonadotrophic properties which can be demonstrated in the parabiosis test, the testicular inhibition test in infantile rats, and by the inhibition of ovulation.
Pharmacokinetic Studies in Animals
Pharmacokinetic studies have been carried out in a number of animal species (rats, rabbits, dogs, and monkeys) using either methylene-14C- or carboxy-14C-labelled cyproterone acetate.
Cyproterone acetate is absorbed at most dose levels tested except in high doses. Peak plasma levels are usually obtained within 1 to 4 hours of oral dosing. Because of its lipophilic character, cyproterone acetate is taken up and concentrated in the liver and fatty tissues in all animal species. Cyproterone acetate is not hydrolysed, and mainly cyproterone acetate and the metabolite 15β-hydroxycyproterone acetate are found in the tissues and in plasma. The elimination half-life of cyproterone acetate is slow in most species (1-2 days), in a ratio of 4:6 with urine and feces; an exception is the dog, which excretes cyproterone acetate in 1 to 3 days. On repeated daily dosing, cyproterone acetate shows limited rise, and plasma levels can be taken as a reliable index of the concentrations of cyproterone acetate in the body. Cyproterone acetate passes the placental barrier, but only reaches the fetus in low concentrations. The pharmacokinetics, biotransformation, and metabolic spectra of cyproterone acetate are similar in man and the rhesus monkey.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1.
ANDROCUR® (cyproterone acetate tablets, 50 mg), submission control no. 245903, Product
Monograph. Bayer Inc. May 13, 2021.