


Product Monograph - Robitussin Ac
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Syrup, each mL of which contains: guaifenesin 20 mg, codeine phosphate 2 mg and pheniramine maleate 1.5 mg | Alcohol, caramel colour, citric acid, FD&C Red No. 40, FD&C Yellow No. 6, glycerin, invert sugar, menthol flavour, purified water, raspberry flavours and sodium benzoate |
INDICATIONS AND CLINICAL USE
Adults
Robitussin® AC is indicated for temporary expectoration and control cough associated with inflamed mucosa.
Geriatrics (> 65 years of age)
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy.
Pediatrics (< 18 years of age)
Robitussin® AC is not indicated for use in patients younger than 18 years of age because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine and because the benefits of symptomatic treatment of cough do not outweigh the risks for use of codeine in these patients (see also CONTRAINDICATIONS and DOSAGE AND ADMINISTRATION).
CONTRAINDICATIONS
- Patients who are hypersensitive to the active substance codeine, guaifenesin, pheniramine or other opioid analgesics or to any ingredient in the formulation. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
- In patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction or strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- Patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus.
- Patients with acute respiratory depression, elevated carbon dioxide levels in the blood and cor pulmonale.
- Patients with acute alcoholism, delirium tremens, and convulsive disorders, diabetes, heart or thyroid disease or glaucoma.
- Patients with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury.
- CYP2D6 ultra-rapid metabolizers who convert codeine into its active metabolite more rapidly and completely than other people (see WARNINGS AND PRECAUTIONS, Risk of Death in Ultra-Rapid Metabolizers of Codeine; SYMPTOMS AND TREATMENT OF OVERDOSAGE, Codeine)
- Pediatric patients <12 years of age.
Pediatric patients (<18 years of age) who have undergone tonsillectomy and/or
adenoidectomy for obstructive sleep apnoea syndrome
- Patients taking monoamine oxidase (MAO) inhibitors (or within 14 days of such therapy).
Women who are breast-feeding, and during pregnancy, or during labour and delivery (see
Serious Warnings and Precautions, and Warnings and Precautions).
WARNINGS AND PRECAUTIONS
SERIOUS WARNINGS AND PRECAUTIONS
Limitations of Use
Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, and because of the greater risks of overdose and death with controlled release opioid formulations, Robitussin® AC should only be used in patients for whom alternative non-opioid treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide appropriate cough management (see DOSAGE AND ADMINISTRATION).
Addiction, Abuse, and Misuse
Robitussin® AC poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing Robitussin® AC, and all patients should be monitored regularly for the development of these behaviours or conditions (see WARNINGS AND PRECAUTIONS). Robitussin® AC should be stored securely to avoid theft or misuse.
General
Before prescribing medication to suppress or modify cough, it is important to ascertain that the underlying cause of the cough is identified, that modification of the cough does not increase the risk of clinical or physiological complications, and that appropriate therapy for the primary disease is provided.
Accidental ingestion, especially by children can result in a fatal overdose of codeine (see DOSAGE AND ADMINISTRATION, disposal, for instructions on proper disposal).
Patients should be instructed not to give Robitussin® AC to anyone other than the patient for whom it was prescribed, as such inappropriate use may have severe medical consequences, including death. Robitussin® AC should be stored securely to avoid theft or misuse.
SERIOUS WARNINGS AND PRECAUTIONS
Life-threatening Respiratory Depression: OVERDOSE
Serious, life-threatening, or fatal respiratory depression including central sleep apnoea (CSA) and sleep-related hypoxemia may occur with use of Robitussin® AC. Infants exposed in-utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of Robitussin® AC or following a dose increase.
Accidental Exposure
Accidental exposure to Robitussin® AC, especially by children, can result in a fatal overdose of Robitussin® AC (see DOSAGE AND ADMINISTRATION, Disposal, for instructions on proper disposal).
Neonatal Opioid Withdrawal Syndrome
Prolonged maternal use of Robitussin® AC during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see WARNINGS AND PRECAUTIONS).
Interaction with Alcohol
The co-ingestion of alcohol with Robitussin® AC should be avoided as it may result in dangerous additive effects, causing serious injury or death (see WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS).
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see WARNINGS AND PRECAUTIONS).
- Reserve concomitant prescribing of Robitussin® AC and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
Patients should be cautioned not to consume alcohol while taking Robitussin® AC as it may increase the chance of experiencing serious adverse events, including death. Patients should be advised to stop use and consult a doctor if symptoms or cough worsen or persist for more than 7 days or if high fever, rash or persistent headache is present, as these may be signs of a serious condition.
Patients should be counselled to discontinue codeine products and to seek urgent medical help at the earliest sign of codeine toxicity including symptoms such as confusion, shallow breathing, or extreme sleepiness which may be life threatening.
Abuse and Misuse
Like all opioids, Robitussin® AC is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, Robitussin® AC should be prescribed and handled with caution.
Opioids, such as Robitussin® AC, should be used with particular care in patients with a history of alcohol and illicit/prescription drug abuse.
Endocrine
Adrenal Insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency.
Cardiovascular
Codeine administration may result in hypotension and dizziness. Use with caution in patients with cardiac arrhythmias due to the cholinergic effects of the drug.
Dependence/Tolerance
As with other opioids, tolerance and physical dependence may develop upon repeated administration of Robitussin® AC and there is a potential for development of psychological dependence.
Physical dependence and tolerance reflect the neuroadaptation of the opioid receptors to chronic exposure to an opioid, and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
Use in Drug and Alcohol Addiction
Robitussin® AC is an opioid with no approved use in the management of addictive disorders. Its proper usage in individuals with drug or alcohol dependence, either active or in remission, is for
the management of cough requiring an opioid. Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to Robitussin® AC; extreme caution and awareness is warranted to mitigate the risk.
Gastrointestinal Effects
Codeine and other morphine-like opioids have been shown to decrease bowel motility. Codeine may obscure the diagnosis or clinical course of patients with acute abdominal conditions. Codeine should not be used in patients with diarrhea associated with pseudomembranous colitis. Use with caution in patients with acute ulcerative colitis or other severe inflammatory bowel disease due to the risk of toxic megacolon.
Neonatal Opioid Withdrawal Syndrome (NOWS)
Use of Robitussin® AC is contraindicated in pregnant women (see CONTRAINDICATIONS).
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn.
Neurologic
Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol): Concomitant use of opioids, including Robitussin® AC, with benzodiazepines, or other CNS depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Because of these risks, avoid use of opioid cough medications in patients taking benzodiazepines, other CNS depressants, or alcohol (see DRUG INTERACTIONS).
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone. Because of similar pharmacologic properties, it is reasonable to expect similar risk with concomitant use of opioid cough medications and benzodiazepines, other CNS depressants, or alcohol.
Advise both patients and caregivers about the risks of respiratory depression and sedation if Robitussin® AC is used with benzodiazepines, alcohol, or other CNS depressants.
Head Injury: The respiratory depressant effects of codeine, and the capacity to elevate cerebrospinal fluid pressure, may be greatly increased in the presence of an already elevated intracranial pressure produced by trauma. Also, codeine may produce confusion, miosis, vomiting and other side effects which obscure the clinical course of patients with head injury. In
such patients, codeine must be used with extreme caution and only if it is judged essential (see CONTRAINDICATIONS).
Risk of Death in Ultra-Rapid Metabolizers of Codeine
Some individuals may be ultra-rapid metabolizers due to a specific CYP2D6*2x2 genotype. These individuals convert codeine into its active metabolite, morphine, more rapidly and completely than other people. This rapid conversion results in higher than expected serum morphine levels. Even at labelled dosage regimens, individuals who are ultra-rapid metabolizers may have life-threatening or fatal respiratory depression or experience overdose symptoms such as extreme sleepiness, confusion, or shallow breathing. (See also Labour, Delivery and Nursing Women in Special Populations).
The prevalence of this CYP2D6 phenotype varies widely and has been estimated at 0.5 to 1% in Chinese and Japanese, 0.5 to 1% in Hispanics, 1 to 10% in Caucasians, 3% in African Americans, and 16 to 28% in North Africans, Ethiopians, and Arabs. Data are not available for other ethnic groups. When physicians prescribe codeine-containing drugs, they should choose the lowest effective dose for the shortest period of time and inform their patients about these risks and the signs of morphine overdose (see DOSAGE AND ADMINISTRATION, Dosing Considerations).
Peri-Operative Considerations
Use with caution in sedated or debilitated patients, in patients who have undergone thoracotomies or laparotomies, since suppression of the cough reflex may lead to retention of secretions postoperatively in these patients.
Serotonin toxicity / Serotonin syndrome
Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported during use of opioids such as Robitussin® AC, particularly during combined use with other serotonergic drugs (see DRUG INTERACTIONS).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus
If concomitant treatment with Robitussin® AC and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see DRUG INTERACTIONS). If serotonin toxicity is suspected, a temporary discontinuation of one or more of the likely causative agents for the serotonin toxicity should be considered.
Psychomotor Impairment
Robitussin® AC may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery. Patients should be cautioned accordingly. Patients should also be cautioned about the combined effects of Codeine with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol.
Respiratory
Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient’s clinical status. Robitussin® AC should be used with extreme caution in patients with substantially decreased respiratory reserve, pre-existing respiratory depression, hypoxia or hypercapnia (see CONTRAINDICATIONS).
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of Robitussin® AC, the risk is greatest during the initiation of therapy or following a dose increase. Patients should be closely monitored for respiratory depression when initiating therapy with Robitussin® AC and following dose increases.
Life-threatening respiratory depression is more likely to occur in the elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients.
Risk Factors for Life-threatening Respiratory Depression in Children: Respiratory depression and death have occurred in children who received codeine in the postoperative period following tonsillectomy and/or adenoidectomy and had evidence of being ultra-rapid metabolizers of codeine (i.e., multiple copies of the gene for cytochrome P450 isoenzyme 2D6 or high morphine concentrations).
- Codeine-containing products are contraindicated for all children younger than 12 years of age.
- Codeine-containing products are contraindicated for post-operative pain management in all pediatric patients undergoing tonsillectomy and/or adenoidectomy for obstructive sleep apnoea syndrome (see CONTRAINDICATIONS).
- Avoid the use of codeine-containing products in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of codeine unless the benefits outweigh the risks. Risk factors include conditions associated with hypoventilation, such as postoperative status, obstructive sleep apnea, obesity, severe pulmonary disease, neuromuscular disease, and concomitant use of other medications that cause respiratory depression.
Use in Patients with Chronic Pulmonary Disease: Monitor patients with significant chronic obstructive pulmonary disease or cor pulmonale, and patients having a substantially decreased
respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression for respiratory depression, particularly when initiating therapy and titrating with Robitussin® AC, as in these patients, even usual therapeutic doses of Robitussin® AC may decrease respiratory drive to the point of apnea. The use of Robitussin® AC is contraindicated in patients with acute or severe bronchial asthma, chronic obstructive airway, or status asthmaticus (see
CONTRAINDICATIONS).
Sleep Apnea
Opioids can cause sleep-related breathing disorders such as sleep apnea syndromes (including central sleep apnea [CSA]) and hypoxia (including sleep-related hypoxia). Opioid use increases the risk of CSA in a dose-dependent fashion. Evaluate patients on an ongoing basis for the onset of a new sleep apnea, or a worsening of an existing sleep apnea. In these patients, consider reducing or stopping the Robitussin® AC treatment if appropriate, using best practices for tapering of opioids (see WARNINGS AND PRECAUTIONS, Dependence/Tolerance; DOSAGE AND ADMINISTRATION, Adjustment or Reduction of Dosage).
Risks of Interactions with Drugs Affecting Cytochrome P450 Isoenzymes
The effects of concomitant use or discontinuation of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with codeine are complex. Use of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with Robitussin® AC requires careful consideration of the effects on the parent drug, codeine, and the active metabolite, morphine. (See DRUG INTERACTIONS)
Sexual Function/Reproduction: Long term use of opioids may lead to a decrease in sex hormone levels. It may also lead to low libido (desire to have sex), erectile dysfunction or being infertile (see ADVERSE REACTIONS, Post-Marketing Experience).
Special Populations
Special Risk Groups: Codeine should be administered with caution to patients with a history of alcohol and drug abuse and in a reduced dosage to debilitated patients, and in patients with severely impaired pulmonary function, Addison’s disease, hypothyroidism, glaucoma, myxedema, toxic psychosis, prostatic hypertrophy or urethral stricture.
Pregnant Women: Studies in humans have not been conducted. Robitussin® AC crosses the placental barrier and is contraindicated in pregnant women.
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal Opioid Withdrawal Syndrome (NOWS), unlike opioid withdrawal syndrome in adults, can be life-threatening (see WARNINGS AND PRECAUTIONS, Neonatal Opioid Withdrawal Syndrome).
Pregnant women using opioids should not discontinue their medication abruptly as this can cause pregnancy complication such as miscarriage or still-birth. Tapering should be slow and under medical supervision to avoid serious adverse events to the fetus.
Labour, Delivery and Nursing Women: Since opioids can cross the placental barrier and are excreted in breast milk, Robitussin® AC is contraindicated in nursing women and during labour and delivery. Life-threatening respiratory depression can occur in the infant if opioids are administered to the mother. Naloxone, a drug that counters the effects of opioids, should be readily available if Robitussin® AC is used in this population.
Codeine is secreted into human milk. In women with normal codeine metabolism (normal CYP2D6 activity), the amount of codeine secreted into human milk is low and dose-dependent. However, some women are ultra-rapid metabolisers of codeine (see
CONTRAINDICATIONS, Ultra-Rapid Metabolisers of Codeine; and WARNINGS AND PRECAUTIONS, Risk of Death in Ultra-rapid Metabolizers of Codeine). These women achieve higher-than-expected serum levels of codeine’s active metabolite, morphine, leading to higher-than-expected levels of morphine in breast milk and potentially dangerously high serum morphine levels in their breast-fed infants. Therefore, maternal use of codeine can potentially lead to serious adverse reactions, including death in nursing infants.
Since there is a risk of infant exposure to codeine and morphine through breast milk, Robitussin® AC is contraindicated in breast-feeding. Prescribers should closely monitor mother-infant pairs and notify treating pediatricians about any use of codeine during breast-feeding.
Pediatrics (< 18 years of age): Robitussin® AC is not indicated for use in patients younger than 18 years of age because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine and because the benefits of symptomatic treatment of cough do not outweigh the risks for use of codeine in these patients (see INDICATIONS, CONTRAINDICATIONS, and DOSAGE AND ADMINISTRATION).
Geriatrics (> 65 years of age): In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range and titrate slowly, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Adverse reactions due to codeine phosphate may include drowsiness, nausea, vomiting and constipation. Infrequent adverse effects include palpitation, dry mouth, skin rash, pruritus and, rarely, hyperhidrosis and agitation have been reported. Respiratory depression is seen in higher dosage, and there is a potential for tolerance, psychological dependence or physical dependence to occur.
Post-marketing Experience
Spontaneously Reported Adverse Events for NROBITUSSIN® AC (guaifenesin, codeine phosphate and pheniramine maleate)
Since the inception of marketing NROBITUSSIN® AC, (combination product Guaifenesin, Codeine Phosphate and Pheniramine Maleate) Pfizer has received 5 cases describing 8 adverse events. The following events were reported singly; Condition aggravated, Cough, Drug hypersensitivity, Drug ineffective, Insomnia and Overdose, while Somnolence was reported twice.
Androgen deficiency: Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
DRUG INTERACTIONS
Overview
Interaction with Benzodiazepines and Other Central Nervous System (CNS) Depressants (including alcohol): Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants (e.g. other opioids, sedatives/hypnotics, antidepressants, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, phenothiazines, neuroleptics, antihistamines, antiemetics, and alcohol) and beta-blockers, increases the risk of respiratory depression, profound sedation, coma, and death and should be avoided (see WARNINGS AND PRECAUTIONS, Neurologic, Interactions with Central Nervous System Depressants (including benzodiazepines and alcohol) and Psychomotor Impairment). Robitussin® AC should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects.
Interaction with Serotonin:
Coadministration of Codeine Phosphate with a serotonergic agent, such as a Selective Serotonin Re-uptake Inhibitor or a Serotonin Norepinephrine Re-uptake Inhibitor, may increase the risk of serotonin syndrome, a potentially life-threatening condition (see WARNINGS AND PRECAUTIONS).
MAO Inhibitors
Serious adverse reactions have been reported in patients who receive MAO inhibitors with pethidine. Other opioid analgesics should be used with extreme caution, if at all, in patients taking MAO inhibitors (including selegiline) or within 14 days of such therapy.
Interactions with Drugs Affecting Cytochrome P450 Isoenzymes
The effects of concomitant use or discontinuation of CYP3A4 inducers, CYP3A4 inhibitors, or CYP2D6 inhibitors with codeine are complex, and requires careful consideration of the effects on the parent drug, codeine, and the active metabolite, morphine.
Avoid the use of Robitussin® AC while taking CYP3A4 inducers, CYP3A4 inhibitors, or
CYP2D6 inhibitors. If concomitant use is necessary, monitor patients for respiratory depression and sedation at frequent intervals or for signs of opioid withdrawal.
CYP3A4 inhibitors: The concomitant use of Robitussin® AC and CYP3A4 inhibitors, such as macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g. ketoconazole), or protease inhibitors (e.g., ritonavir) can increase the plasma concentration of codeine and its subsequent metabolism by CYP2D6, resulting in greater morphine levels, which could increase or prolong opioid effects. The discontinuation of a concomitantly used CYP3A4 inhibitor might results in a reduced efficacy of Robitussin® AC.
CYP2D6 inhibitors: The concomitant use of Robitussin® AC and CYP2D6 inhibitors (e.g., amiodarone, quinidine) may result in a decrease in active metabolite morphine plasma concentration, leading to decreased efficacy or symptoms of opioid withdrawal. The discontinuation of a concomitantly used CYP2D6 inhibitor may lead to an increased metabolism to morphine, which could increase or prolong adverse reactions and may cause potentially fatal respiratory depression.
CYP3A4 inducers: The concomitant use of Robitussin® AC and CYP3A4 inducers, such as rifampin, carbamazepine, and phenytoin, may result in a decreased plasma concentration of codeine and its active metabolite morphine, leading to decreased efficacy or symptoms of opioid withdrawal. The discontinuation of a concomitantly used CYP3A4 inducer can increase the plasma concentration of codeine and its active metabolite morphine which could increase or prolong adverse reactions and may cause potentially fatal respiratory depression.
Drug-Lifestyle Interactions
The concomitant use of alcohol should be avoided (see WARNINGS AND PRECAUTIONS, General).
DOSAGE AND ADMINISTRATION
Pediatrics (under 18 years)
Robitussin® AC is not indicated for use in patients younger than 18 years of age because of the risk of opioid toxicity due to the variable and unpredictable metabolism of codeine to morphine and because the benefits of symptomatic treatment of cough do not outweigh the risks for use of codeine in these patients.
Increasing Risk with Higher Doses
All doses of opioids carry an inherent risk of fatal or non-fatal adverse events. This risk is increased with higher doses. The maximum recommended daily dose of Robitussin AC is 60 mL, which is 120 mg codeine (18 morphine milligram equivalent). Each patient should be assessed for their risk prior to prescribing Robitussin AC, as the likelihood of experiencing serious adverse events can depend upon the type of opioid and duration of treatment, as well as the patient’s own level of tolerance. In addition, the coughing should be assessed routinely to confirm the most appropriate dose and the need for further use of Robitussin AC.
Considerations
Robitussin® AC may be taken with or without food, with a glass of water.
Recommended Dose and Dosage Adjustment
Codeine, including Robitussin AC, should be prescribed at the lowest effective dose for the shortest period of time. Dosing should be as needed every 4 to 6 hours and not on scheduled intervals.
Adults:
Take 10 mL (2 teaspoons) every 4 to 6 hours as follows or as directed by a doctor. Do not exceed 6 doses (12 teaspoons) in a 24-hour period.
Geriatrics:
Respiratory depression has occurred in the elderly following administration of large initial doses of opioids to patients who were not opioid-tolerant or when opioids were co-administered with other agents that can depress respiration. Robitussin® AC should be initiated at a low dose and slowly titrated to effect (see WARNINGS AND PRECAUTIONS).
Adjustment or Reduction of Dosage: Physical dependence with or without psychological dependence tends to occur with chronic administration of opioids, including Robitussin® AC. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. These symptoms may include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning.
Missed Dose
Take the missed dose as soon as you remember. If it is almost time for your next dose, wait until then to take your medicine and skip the missed dose. Do not take two doses at the same time.
Disposal
Robitussin® AC should be kept in a safe place, out of the sight and reach of children before, during and after use. Robitussin® AC should not be used in front of children, since they may copy these actions.
Robitussin® AC should never be disposed of in household trash. Disposal via a pharmacy take back program is recommended. Unused or expired Robitussin® AC should be properly disposed of as soon as it is no longer needed to prevent accidental exposure to others, including children or pets. If temporary storage is required before disposal, a sealed child-proof container, such as a biohazard waste container or a lockable medication box could be obtained from a pharmacy.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Symptoms: May result in euphoria, dysphoria, visual disturbances, hypotension and coma or death from respiratory depression.
Treatment: Symptomatic and supportive therapy. Maintain ventilation and administer oxygen as needed. The narcotic antagonist naloxone should be administered. If the patient is conscious and has not lost the gag reflex, empty the stomach by inducing emesis with ipecac syrup. If the patient is extremely drowsy, unconscious, convulsing or has no gag reflex, perform gastric lavage. Follow with activated charcoal (50 to 100 g in adults) and a cathartic.
ACTION AND CLINICAL PHARMACOLOGY
Pharmacodynamics
Endocrine System:
Opioids may influence the hypothalamic-pituitary-adrenal or -gonadal axes. Some changes that can be seen include an increase in serum prolactin, and decreases in plasma cortisol and testosterone. Clinical signs and symptoms may be manifest from these hormonal changes.
Mechanism of Action
Codeine Phosphate: Codeine is a narcotic analgesic which binds to the mu receptor as an opiate receptor agonist. Although the exact mechanism of analgesic action is unknown, it may come from its conversion to morphine. Codeine is also associated with antitussive effects via direct depression of the medullary cough reflex.
Pheniramine Maleate: Pheniramine is an alkylamine derivative which is a potent H1 antagonist. Its actions are mediated by reversible and competitive inhibition of the interaction of histamine with H1 receptors on cells, preventing histamine effects on target organs.
Guaifenesin: Guaifenesin is thought to act as an expectorant by increasing the volume and reducing the viscosity of secretions in the trachea and bronchi. Thus, it may increase the efficiency of the cough reflex and facilitate removal of the secretions. However, objective evidence for this is limited and conflicting
STORAGE AND STABILITY
Robitussin® AC should be stored at room temperature (15-30°C).
Others:
Keep in a safe place out of the reach of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Composition:
Each mL of orange, cherry-flavored syrup contains: guaifenesin 20 mg, codeine phosphate 2 mg and pheniramine maleate 1.5 mg.
Nonmedicinal ingredients: alcohol, caramel colour, citric acid, FD&C Red No. 40, FD&C Yellow No. 6, glycerin, invert sugar, menthol flavour, purified water, raspberry flavours and sodium benzoate.
Energy: 2.78 kcal / mL. Sodium: 0.16 mg / mL. Gluten-, parabens- and tartrazine (FD&C Yellow No. 5)-free.
Packaging:
Bottles of 1 L.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name:
Guaifenesin
Codeine Phosphate
Pheniramine Maleate
Chemical name:
Guaifenesin:
IUPAC Name: (RS)-3-(2-methoxyphenoxy)propane-1,2-diol
CAS Name: 3-(2-Methoxyphenoxy)-1,2-propanediol
Additional Names: glycerol mono(2-methoxyphenyl) ether; glycerol α-(2-methoxyphenyl) ether; guaiacyl glyceryl ether; glyceryl guaiacyl ether; glycerol guaiacolate; α-glyceryl guaiacol ether; o-methoxyphenyl glyceryl ether; 1,2-dihydroxy-3-(2-methoxyphenoxy)propane; guaiacol glyceryl ether; guaiphenesin; guaiacuran
Codeine:
IUPAC Name: (4R,4aR,7S,7aR,12bS)-9-methoxy-3-methyl-2,4,4a,7,7a,13-hexahydro-1H-4,12-methanobenzofuro[3,2-e]isoquinoline-7-ol
CAS Name: (5α,6α)-7,8-Didehydro-4,5-epoxy-3-methoxy-17-methylmorphinan-6-ol Additional Names: methylmorphine; morphine monomethyl ether; morphine 3-methyl ether
Pheniramine Maleate:
IUPAC Name: (Z)-but-2-enedioic acid;N,N-dimethyl-3-phenyl-3-pyridin-2-ylpropan-1-amine
Molecular formula and molecular mass:
Guaifenesin:
Molecular Formula: C10H14O4
Molecular Weight: 198.22
Codeine:
Molecular Formula: C18H21NO3
Molecular Weight: 299.36
Codeine Phosphate:
Molecular Formula: C18H21NO3·H3PO4
Molecular Weight: 397.36
Pheniramine Maleate:
Molecular Formula: C16H20N2·C4H4O4
Molecular Weight: 356.42
Structural formula:
Guaifenesin:
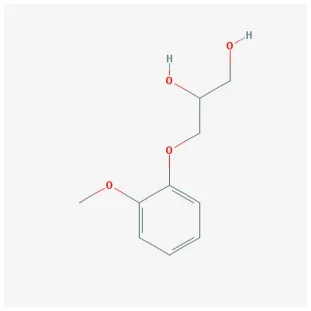
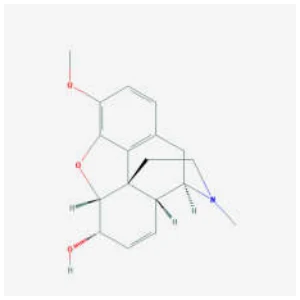
Codeine:
Codeine Phosphate:
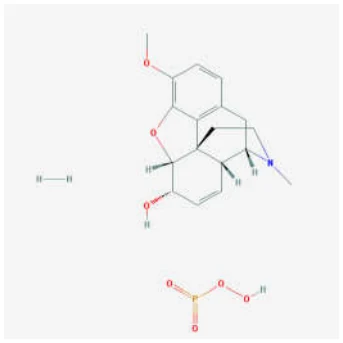
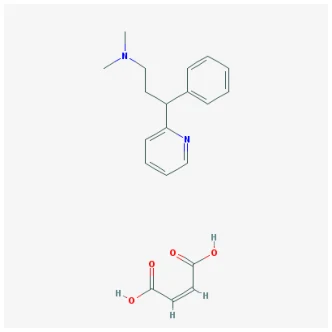
Pheniramine Maleate:
Physicochemical Properties:
Guaifenesin: Crystals, melting point 132-134 °C. Freely soluble in water; soluble in alcohol, chloroform. pH of a 2% aqueous solution about 5. Slightly soluble in ether, benzene.
Codeine Phosphate: Fine, white, needle-shaped crystals or crystalline powder. Odorless; affected by light. Solutions acidic to litmus. Freely soluble in water; very soluble in hot water; slightly soluble in alcohol; more soluble in boiling alcohol.
Pheniramine Maleate: Crystals from amyl alcohol, faint amine-like odor, melting point 107 °C. Soluble in water, alcohol; slightly soluble in ether, benzene. pH of 1% aqueous solution between 4.3 and 4.9.