


Product Monograph - Sandoz Naratriptan
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Tablet 2.5 mg | Aluminum Lake FD&C Blue #2, Cellulose Microcrystalline, Croscarmellose Sodium, Hypromellose, Iron Oxide Yellow, Lactose Anhydrous, Lactose Monohydrate, Magnesium Stearate, Titanium Dioxide, Triacetin |
INDICATIONS AND CLINICAL USE
Sandoz Naratriptan (naratriptan hydrochloride) is indicated for the acute treatment of migraine attacks with or without aura in adults.
Sandoz Naratriptan is not intended for the prophylactic therapy of migraine or for use in the management of hemiplegic, basilar, or ophthalmoplegic migraine (see CONTRAINDICATIONS). Safety and efficacy have not been established for cluster headache which is present in an older, predominantly male population.
Geriatrics (> 65 years of age):
The safety and efficacy of naratriptan tablets have not been adequately studied in individuals over 65 years of age. Naratriptan is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in elderly patients who have reduced renal function. In addition, elderly patients are more likely to have decreased hepatic function; they are at higher risk for Coronary Artery Disease (CAD), and blood pressure increases may be more pronounced in the elderly. Clinical studies of naratriptan tablets did not include patients over 65 years of age. Its use in this age group is, therefore, not recommended (see
WARNINGS AND PRECAUTIONS).
Pediatrics (< 18 years of age)
Adolescents (12-17 years of age):
The efficacy of naratriptan tablets at single doses of 0.25, 1.0 and 2.5 mg was not demonstrated to be greater than placebo in adolescents (12-17 years). Furthermore, the safety of naratriptan tablets in adolescents has not been established. Therefore, the use of the drug in adolescents is not recommended (see WARNINGS AND PRECAUTIONS).
Children (< 12 years of age):
The safety and efficacy of naratriptan tablets have not been studied in children under 12 years of age. Use of the drug in this age group is, therefore, not recommended (see WARNINGS AND PRECAUTIONS).
CONTRAINDICATIONS
Sandoz Naratriptan is contraindicated in patients with history, symptoms, or signs of ischemic cardiac, cerebrovascular or peripheral vascular syndromes, valvular heart disease or cardiac arrhythmias (especially tachycardias). In addition, patients with other significant underlying cardiovascular diseases (e.g. atherosclerotic disease, congenital heart disease) should not receive Sandoz Naratriptan. Ischemic cardiac syndromes include, but are not limited to, angina pectoris of any type (e.g. stable angina of effort and vasospastic forms of angina such as the Prinzmetal’s variant), all forms of myocardial infarction, and silent myocardial ischemia. Cerebrovascular syndromes include, but are not limited to, strokes of any type as well as transient ischemic attacks (TIAs). Peripheral vascular disease includes, but is not limited to, ischemic bowel disease, or Raynaud’s syndrome (see WARNINGS AND PRECAUTIONS).
Because Sandoz Naratriptan can give rise to increases in blood pressure, it is contraindicated in patients with uncontrolled or severe hypertension (see WARNINGS AND PRECAUTIONS).
Ergot-containing drugs have been reported to cause prolonged vasospastic reactions. Because Sandoz Naratriptan may also cause coronary vasospasm and these effects may be additive, the use of Sandoz Naratriptan within 24 hours before or after treatment with other 5-HT1 receptor agonists, or ergotamine-containing drugs or their derivatives (e.g. dihydroergotamine, methysergide) is contraindicated.
Sandoz Naratriptan is contraindicated in patients with hemiplegic, basilar, or ophthalmoplegic migraine.
Sandoz Naratriptan is contraindicated in patients with severe renal impairment (creatinine clearance <15 mL/min) (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY).
Sandoz Naratriptan is contraindicated in patients with severe hepatic impairment (Child-Pugh grade C) (see DOSAGE AND ADMINISTRATION and ACTION AND
CLINICAL PHARMACOLOGY ).
Sandoz Naratriptan is contraindicated in patients with hypersensitivity to naratriptan or to any component of the formulation, or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
WARNINGS AND PRECAUTIONS
General
Sandoz Naratriptan should only be used where a clear diagnosis of migraine has been established.
Cardiovascular
Risk of Myocardial Ischemia and/or Infarction and Other Adverse Cardiac Events:
Naratriptan tablets have been associated with transient chest and/or neck pain and tightness which may resemble angina pectoris. In rare cases, the symptoms have been identified as being the likely result of coronary vasospasm or myocardial ischemia. Rare cases of serious coronary events or arrhythmia have occurred following use of another 5-HT1 agonist. Sandoz Naratriptan should not be given to patients who have documented ischemic or vasospastic coronary artery disease (see CONTRAINDICATIONS). It is strongly recommended that Sandoz Naratriptan not be given to patients in whom unrecognized coronary artery disease (CAD) is predicted by the presence of risk factors (e.g. hypertension, hypercholesterolemia, smoking, obesity, diabetes, strong family history of CAD, female who is surgically or physiologically postmenopausal, or male who is over 40 years of age) unless a cardiovascular evaluation provides satisfactory clinical evidence that the patient is reasonably free of coronary artery and ischemic myocardial disease or other significant underlying cardiovascular disease. The sensitivity of cardiac diagnostic procedures to detect cardiovascular disease or predisposition to coronary artery vasospasm is unknown. If, during the cardiovascular evaluation, the patient’s medical history or electrocardiographic investigations reveal findings indicative of or consistent with coronary artery vasospasm or myocardial ischemia, Sandoz Naratriptan should not be administered (see CONTRAINDICATIONS).
For patients with risk factors predicative of CAD who are considered to have a satisfactory cardiovascular evaluation, the first dose of Sandoz Naratriptan should be administered in the setting of a physician’s office or similarly medically staffed and equipped facility. Because cardiac ischemia can occur in the absence of clinical symptoms, consideration should be given to obtaining electrocardiograms (ECG) in patients with risk factors during the interval immediately following Sandoz Naratriptan administration on the first occasion of use. However, an absence of drug-induced cardiovascular effects on the initial dose does not preclude the possibility of such effects occurring with subsequent administrations.
Intermittent long-term users of Sandoz Naratriptan who have or acquire risk factors predictive of CAD, as described above, should receive periodic interval cardiovascular evaluations over the course of treatment. If symptoms consistent with angina occur after the use of Sandoz Naratriptan ECG evaluation should be carried out to look for ischemic changes.
The systemic approach described above is intended to reduce the likelihood that patients with unrecognized cardiovascular disease will be inadvertently exposed to Sandoz Naratriptan.
Discomfort in the chest, neck, throat, and jaw (including pain, pressure, heaviness, tightness, dyspnea) has been reported after administration of naratriptan tablet (naratriptan hydrochloride). Because 5-HT1 agonists may cause coronary artery vasospasm, patients who experience signs or symptoms suggestive of angina following Sandoz Naratriptan should be evaluated for the presence of CAD or a predisposition to variant angina before receiving additional doses, and should be monitored electrocardiographically if dosing is resumed and similar symptoms recur. Similarly, patients who experience other symptoms or signs suggestive of decreased arterial flow, such as ischemic bowel syndrome or Raynaud’s syndrome following naratriptan administration should be evaluated for artherosclerosis or predisposition to vasospasm (see CONTRAINDICATIONS and ADVERSE DRUG REACTIONS, Clinical Trial Adverse Drug Reactions).
Cardiac Events and Fatalities Associated With 5-HT1 Agonists: Sandoz Naratriptan can cause coronary artery vasospasm. Serious adverse cardiac events, including acute myocardial infarction, life-threatening disturbances of cardiac rhythm, and death have been reported within a few hours following the administration of 5-HT1 agonists. Considering the extent of use of 5-HT1 agonists in patients with migraine, the incidence of these events is extremely low.
Premarketing Experience With Naratriptan Tablets: Among approximately 3500 patients with migraine who participated in premarketing clinical trials of naratriptan tablets, four patients treated with single oral doses of naratriptan tablets ranging from 1 to 10 mg experienced asymptomatic ischemic ECG changes with at least one, who took 7.5 mg, likely due to coronary vasospasm.
Cerebrovascular Events and Fatalities with 5-HT1 Agonists: Cerebral hemorrhage, subarachnoid hemorrhage, stroke, and other cerebrovascular events have been reported in patients treated with 5-HT1 agonists, and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the agonist having been administered in the incorrect belief that the symptoms experienced were a consequence of migraine, when they were not. Before treating migraine headaches with Sandoz Naratriptan in patients not previously diagnosed as migraineurs, and in migraineurs who present with atypical symptoms, care should be taken to exclude other potentially serious neurological conditions. If a patient does not respond to the first dose, the opportunity should be taken to review the diagnosis before a second dose is given. It should be noted that patients with migraine may be at increased risk of certain cerebrovascular events (e.g. stroke, hemorrhage, TIA).
Special Cardiovascular Pharmacology Studies: In subjects (N=10) with suspected coronary artery disease undergoing angiography, naratriptan at a subcutaneous dose of 1.5 mg produced an 8% increase in aortic blood pressure, an 18% increase in pulmonary artery blood pressure, and an 8% increase in systemic vascular resistance. In addition, mild chest pain or tightness was reported by four subjects. Clinically significant increases in blood pressure were experienced by three of the subjects (two of whom also had chest pain/discomfort). Diagnostic angiogram results revealed that 9 subjects had normal coronary arteries and 1 had insignificant coronary artery disease.
Migraine patients (N=35) free of cardiovascular disease were subjected to assessments of myocardial perfusion by positron emission tomography while receiving subcutaneous naratriptan 1.5 mg in the absence of a migraine attack. Naratriptan was associated with a reduced coronary vasodilatory reserve (~10%), increased coronary resistance (~20%), and decreased hyperemic myocardial blood flow (~10%). The relevance of these findings to the use of recommended oral doses of naratriptan is not known.
Other Vasospasm-Related Events: 5-HT1 agonists may cause vasospastic reactions other than coronary artery vasospasm. Extensive postmarket experience has shown the use of naratriptan to be associated with very rare occurrences of peripheral vascular ischemia and colonic ischemia with abdominal pain and bloody diarrhea.
Increases in Blood Pressure: Elevations in blood pressure have been reported following use of naratriptan tablet. At the recommended oral doses, the elevations are generally small (population average maximum increases of <5 mmHg systolic and <3 mmHg diastolic at the 2.5 mg dose). The effects may be more pronounced in the elderly and hypertensive patients. In a pharmacodynamic study conducted in normotensive patients (N=12) and in hypertensive patients controlled by antihypertensive treatment (N=12), the pressor effects of naratriptan tablets were greater in hypertensive patients (weighted mean increases in systolic and diastolic blood pressure of 6 and 4 mmHg in hypertensive subjects versus 3 and 2 mmHg in normotensive patients receiving two 2.5 mg doses separated by a 2 hour time interval). Two hypertensive patients experienced three events of chest discomfort while receiving naratriptan. Significant elevation in blood pressure, including hypertensive crisis, has been reported on rare occasions in patients receiving 5-HT1 agonists with and without a history of hypertension. Sandoz Naratriptan is contraindicated in patients with uncontrolled or severe hypertension (see CONTRAINDICATIONS).
In patients with controlled hypertension, Sandoz Naratriptan should be administered with caution, as transient increases in blood pressure and peripheral vascular resistance have been observed in a small portion of patients.
Immune
Hypersensitivity: Rare hypersensitivity (anaphylaxis/anaphylactoid) reactions may occur in patients receiving 5-HT1 agonists such as Sandoz Naratriptan. Such reactions can be life-threatening or fatal. In general, hypersensitivity reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens (see CONTRAINDICATIONS). Owing to the possibility of cross-reactive hypersensitivity reactions, Sandoz Naratriptan should not be used in patients having a history of hypersensitivity to sumatriptan or chemically-related 5-HT1 receptor agonists.
As Sandoz Naratriptan contains a sulphonamide component, there is a theoretical risk of hypersensitivity reactions in patients with known hypersensitivity to sulphonamides.
Neurologic
Care should be taken to exclude other potentially serious neurologic conditions before treating headache in patients not previously diagnosed with migraine or who experience a headache that is atypical for them. There have been rare reports where patients received 5-HT1 agonists for severe headaches that were subsequently shown to have been secondary to an evolving neurologic lesion. For newly diagnosed patients or patients presenting with atypical symptoms, the diagnosis of migraine should be reconsidered if no response is seen after the first dose of Sandoz Naratriptan.
Seizures: Caution should be observed if Sandoz Naratriptan is to be used in patients with a history of epilepsy or structural brain lesions which lower the convulsion threshold.
Selective Serotonin Reuptake Inhibitors/Serotonin Norepinephrine Reuptake Inhibitors and Serotonin Syndrome: Cases of life-threatening serotonin syndrome have been reported during combined use of selective serotonin reuptake inhibitors (SSRIs)/serotonin norepinephrine reuptake inhibitors (SNRIs) and triptans. If concomitant treatment with Sandoz Naratriptan and SSRIs (e.g. fluoxetine, paroxetine, sertraline) or SNRIs (e.g. venlafaxine) is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. Serotonin syndrome symptoms may include mental status changes (e.g. agitation, hallucinations, coma), autonomic instability (e.g. tachycardia, labile blood pressure, hyperthermia), neuromuscular aberrations (e.g. hyperreflexia, incoordination) and/or gastrointestinal symptoms (e.g. nausea, vomiting, diarrhea) (see DRUG INTERACTIONS, SSRIs/SNRIs).
Psychomotor Impairment: In a study of psychomotor function in healthy volunteers, single oral 5 and 10 mg doses of naratriptan tablets were associated with sedation and decreased alertness. Although these doses are higher than those recommended for the treatment of migraine, patients should be cautioned that drowsiness may occur following treatment with Sandoz Naratriptan. They should be advised not to perform skilled tasks (e.g. driving or operating machinery) if drowsiness occurs.
Ophthalmologic
Melanin Binding: In pigmented rats treated with a single oral dose (10 mg/kg) of radiolabelled naratriptan, radioactivity was detected in the eyes at 3 months post-administration, a finding which suggests that the drug or its metabolites may bind to the melanin of the eye. The possible clinical significance of this finding is unknown. No systematic monitoring of ophthalmologic function was undertaken in clinical trials. Prescribers should consider the possibility of long-term ophthalmologic effects due to accumulation of naratriptan in melanin-rich tissues.
Medication Overuse Headache: Overuse of acute migraine treatments has been associated with the exacerbation of headache (medication overuse headache, MOH) in susceptible patients. Withdrawal of the treatment may be necessary.
Special Populations
Pregnant Women: Naratriptan can cross the placenta in pregnant rats and rabbits, but it is not known if naratriptan can cross the human placental barrier. In animals at high doses, maternal toxicity and associated developmental toxicity (skeletal variation and post implantation loss) occurred (see TOXICOLOGY – Reproduction and Teratology). Post-marketing data from prospective pregnancy registries have documented the pregnancy outcomes in women exposed to naratriptan. Due to a small sample size no definitive conclusion can be drawn regarding the risk of birth defects following exposure to naratriptan during pregnancy. Because its safety to the fetus has not been demonstrated, Sandoz Naratriptan should not be used during pregnancy unless the potential benefit to the mother justifies the potential risk to the fetus.
Nursing Women: Naratriptan and/or its metabolites are distributed into the milk of lactating rats (at 2 hours post oral gavage dosing, levels in milk were 3.5 times higher than maternal plasma levels). It is not known if naratriptan is secreted into the human breast milk. Therefore, caution should be exercised when considering the administration of Sandoz Naratriptan to nursing women.
Children (< 12 years of age): Safety and efficacy of naratriptan tablets have not been studied in children under 12 years of age. Use of the drug in this age group is, therefore, not recommended.
Adolescents (12-17 years of age): The efficacy of naratriptan tablets at single doses of 0.25, 1.0 and 2.5 mg was not demonstrated to be greater than placebo in adolescents (12-17 years). Furthermore, the safety of naratriptan tablets in adolescents has not been established. Therefore, the use of the drug in adolescents is not recommended.
Geriatrics (> 65 years of age): The safety and effectiveness of naratriptan tablets has not been adequately studied in individuals over 65 years of age. Naratriptan tablets are known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in elderly patients who have reduced renal function. In addition, elderly patients are more likely to have decreased hepatic function; they are at higher risk for CAD; and blood pressure increases may be more pronounced in the elderly. Clinical studies of naratriptan tablets did not include patients over 65 years of age. Its use in this age group is, therefore, not recommended.
Hepatic Impairment: Naratriptan tablets should be administered with caution to patients with impaired hepatic function (see CONTRAINDICATIONS, DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY).
Renal Impariment: Naratriptan tablet should be administered with caution to patients with impaired renal function (see CONTRAINDICATIONS, DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY).
Monitoring and Laboratory Tests
No specific laboratory tests are recommended for monitoring patients prior to and/or after treatment with Sandoz Naratriptan.
Dependence/Tolerance
Dependence Liability: In one clinical study enrolling 12 subjects, all of whom had experience using oral opiates and other psychoactive drugs, subjective responses typically associated with many drugs of abuse were produced with less intensity during treatment with naratriptan tablets (1-5 mg) than with codeine (30 to 90 mg). Long-term studies (12 months) in migraine patients using naratriptan tablets revealed no evidence of increased drug utilization.
ADVERSE REACTIONS
Serious cardiac events, including some that have been fatal, have occurred following the use of 5-HT1 agonists. These events are extremely rare and most have been reported in patients with risk factors predictive of CAD. Events reported have included coronary artery vasospasm, transient myocardial ischemia; myocardial infarction, ventricular tachycardia, and ventricular fibrillation (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Experience in Clinical Trials with Naratriptan Tablets
Typical 5-HT1 Agonist Adverse Reactions: As with other 5-HT1 agonists, naratriptan tablets (naratriptan hydrochloride) have been associated with sensations of heaviness, pressure, tightness or pain which may be intense. These may occur in any part of the body including the chest, throat, neck, jaw and upper limb.
Acute Safety: The safety and efficacy of the 1 and 2.5 mg doses of naratriptan tablets were investigated in four placebo-controlled clinical trials in adult migraine patients. Two of these trials were of parallel group design and involved the treatment of a single migraine attack. A third study was of crossover design and involved the treatment of one migraine attack per dose group. The fourth study was a parallel group trial in which patients treated up to 3 migraine attacks. In all studies, patients who achieved headache relief at 240 minutes postdose, but experienced a worsening of severity between 4 and 24 hours postdosing, were permitted to take a second dose of double-blind medication identical to the first.
The overall incidence of adverse events following doses of 1 mg or 2.5 mg naratriptan tablets (one or more doses) were similar to placebo (28.5% and 30.2% versus 28.9% with placebo). Naratriptan tablets were generally tolerated and most adverse reactions were mild, transient and self-limiting. The most common adverse events to occur at a higher rate than in the corresponding placebo group were malaise/fatigue (2.4% versus 0.8% with placebo) and neck/throat/jaw sensations (2.1% versus 0.3% with placebo). Table 1 lists the most common adverse events that occurred in the four large placebo-controlled clinical trials. Only events that occurred at a frequency of 1% or more in the naratriptan tablets
2.5 mg or 1 mg group and were more frequent in that group than in the placebo group are included in Table 1. From this table, it appears that many of these adverse events are related.
Table 1: Treatment-Emergent Adverse Events in Placebo-Controlled Clinical Trials Reported by at Least 1% of Patients with Migraine
| Placebo | Naratriptan Tablets 1 mg | Naratriptan Tablets 2.5 mg | ||||
| Number of Patients | 922 | 1024 | 1016 | |||
| Number of Migraine Attacks Treated | 1059 | 1387 | 1368 | |||
| Symptoms of Potentially Cardiac Origin | ||||||
| Neck/throat/jaw sensations* | 0.3% | 1.7% | 2.1% | |||
| Chest sensations* | 1.1% | 0.8% | 1.2% | |||
| Upper limb sensations* | 0.3% | 0.5% | 1.4% | |||
| Neurological | ||||||
| Dizziness | 1.5% | 1.0 % | 2.2% | |||
| Drowsiness/sleepiness | 0.8% | 0.9% | 1.7% | |||
| Paresthesia | 0.8% | 1.6% | 1.5% | |||
| Head/face sensations* | 0.5% | 0.5% | 1.3% | |||
| Headache | 0.2% | 0.4% | 1.0 % | |||
| Gastrointestinal | ||||||
| Nausea | 6.2% | 5.9% | 6.3% | |||
| Hyposalivation | 0.3% | 0.5% | 1.0% | |||
| Non-site Specific | ||||||
| Malaise & fatigue | 0.8% | 1.6% | 2.4% | |||
*The term “sensations” encompasses adverse events described as pain and discomfort, pressure, heaviness, constriction, tightness, heat/burning sensation, paresthesia, numbness, tingling, and strange sensations.
Long-Term Safety: In a long-term open study, 417 patients treated 15,301 migraine attacks with naratriptan tablets over a period of up to 1 year. The most common adverse events in descending order of frequency were as follows: nausea (16%); malaise/fatigue (11%); drowsiness (10%); chest sensations* (8%); neck/throat/jaw sensations* (8%); paresthesia
(7%); head/face sensations* (6%); vomiting (6%); and dizziness (5%). Due to the lack of a placebo arm in this study, the role of naratriptan tablets in causation cannot be reliably determined. (* See footnote for Table 1)
Other Adverse Events Observed in Association with Naratriptan Tablets: In the paragraphs that follow, the frequencies of less commonly reported adverse clinical events are presented. Because some events were observed in open and uncontrolled studies, the role of naratriptan tablets in their causation cannot be reliably determined. All reported events are included except those already listed in Table 1, those too general to be informative, and those not reasonably associated with the use of the drug. Event frequencies are calculated as the number of patients reporting an event divided by the total number of patients (N=2790) exposed to naratriptan tablets. Events are further classified within body system categories and enumerated in order of decreasing frequency using the following definitions: common adverse events are defined as those occurring in at least 1/100 patients; uncommon adverse events are those occurring in 1/100 to 1/1000 patients; rare adverse events are those occurring in fewer than 1/1000 patients.
General: Common: paresthesia and heat sensations; Uncommon: chills and/or fever, description of odor or taste and feelings of pressure/tightness/heaviness; Rare: allergies, allergic reactions, mobility disorders and faintness.
Cardiovascular: Uncommon: palpitations, increased blood pressure, tachyarrhythmias, abnormal ECGs, and syncope. Rare: bradycardia, hypotension, varicosities and heart murmur.
Ear, Nose and Throat: Common: ear, nose and throat infections. Uncommon: phonophobia, sinusitis, and upper respiratory inflammation. Rare: allergic rhinitis, labyrinthitis, tinnitus, ear, nose and throat hemorrhage and difficulty hearing.
Endocrine and Metabolism: Uncommon: thirst, polydipsia, dehydration and fluid retention. Rare: hyperlipidemia, hypercholesterolemia, hypothyroidism, hyperglycemia, glycosuria, ketonuria and parathyroid neoplasm.
Gastrointestinal: Common: vomiting. Uncommon: dyspeptic syndromes, diarrhea, hyposalivation, gastrointestinal discomfort and pain, gastroenteritis and constipation. Rare: abnormal liver function tests, abnormal bilirubin levels, salivary gland swelling, hemorrhoids, gastritis, esophagitis, oral itching and irritation, regurgitation, reflux and gastric ulcers.
Musculoskeletal: Uncommon: musculoskeletal/muscle pain, muscle cramps, muscle spasms, arthralgia and articular rheumatism. Rare: joint and muscle stiffness, tightness and rigidity.
Neurologic: Common: migraine. Uncommon: vertigo, tremors, sleep disorders, cognitive function disorders and hyperesthesia-. Rare: disorders of equilibrium, decreased consciousness, confusion, sedation, coordination disorders, neuritis, dreams, altered sense of taste, motor retardation, muscle twitching, fasciculation, and convulsions.
Opththalmologic: Uncommon: photophobia. Rare: eye hemorrhage, dry eyes and difficulty focusing
Psychiatric: Uncommon: anxiety and depressive disorders. Rare: aggression, agitation and detachment.
Sexual Function/Reproduction: Rare: lumps of female reproductive tract and inflammation of the fallopian tube.
Skin: Uncommon: skin photosensitivity, rashes, pruritus, sweating and urticaria. Rare: erythema, dermatitis, dermatosis, pruritic skin rash, hair loss and alopecia.
Urologic: Uncommon: urinary infections. Rare: urinary tract hemorrhage, urinary urgency and pyelitis.
Post-Market Adverse Drug Reactions
The following section enumerates potentially important adverse events that have occurred in clinical practice and that have been reported spontaneously to various surveillance systems. The events enumerated represent reports arising from both domestic and nondomestic use of naratriptan. These events do not include those already listed in the ADVERSE REACTIONS section above. Because the reports cite events reported spontaneously from worldwide postmarketing experience, frequency of events and the role of naratriptan in their causation cannot be reliably determined.
General: Hypersensitivity, including anaphylaxis/anaphylactoid reactions, in some cases severe (e.g. circulatory collapse) (see WARNINGS AND PRECAUTIONS).
Cardiovascular: Angina, myocardial infarction, peripheral vascular ischemia, cerebral vascular accident, including transient ischemic attack, subarachnoid hemorrhage and, cerebral infarction (see WARNINGS AND PRECAUTIONS).
Gastrointestinal: Colonic ischemia (see WARNINGS AND PRECAUTIONS).
Neurologic: Somnolence (see WARNINGS AND PRECAUTIONS).
Respiratory: Dyspnea (see WARNINGS AND PRECAUTIONS).
DRUG INTERACTIONS
Overview
The limited metabolism of naratriptan tablets and the wide range of cytochrome P450 isoenzymes involved, as determined by in vitro studies, suggest that significant drug interactions with naratriptan tablets are unlikely. Naratriptan did not inhibit monoaminase oxidase (MAO-A or MAO-B) in vitro. The possibility of pharmacodynamic in vivo interactions between naratriptan tablets and monoaminase oxidase inhibitors has not been investigated.
Drug-Drug Interactions
Ergot-Containing Drugs: Ergot-containing drugs have been reported to cause prolonged vasospastic reactions. Because there is a theoretical basis for these effects being additive, ergot-containing or ergot-type medications (e.g. dihydroergotamine or methysergide) are contraindicated within 24 hours of Sandoz Naratriptan administration (see CONTRAINDICATIONS).
Other 5-HT1 Agonists: The administration of naratriptan tablets with other 5-HT1 agonists has not been evaluated in migraine patients. As an increased risk of coronary vasospasm is a theoretical possibility with coadministration of 5-HT1 agonists, use of these drugs within 24 hours of each other is contraindicated (see CONTRAINDICATIONS).
Selective Serotonin Reuptake Inhibitors (SSRIs)/Serotonin Norepinephrine Reuptake Inhibitors (SNRIs): Cases of life-threatening serotonin syndrome have been reported during combined use of selective serotonin reuptake inhibitors (SSRIs) or serotonin norepinephrine reuptake inhibitors (SNRIs) and triptans (see WARNINGS AND PRECAUTIONS).
Hormonal Contraceptives: In a population pharmacokinetic study in migraine patients, hormonal contraceptive use was associated with a 32% decrease in naratriptan clearance.
Drug-Food Interactions
Alcohol and Food: Clinical studies did not reveal any pharmacokinetic interaction when naratriptan was administered together with alcohol or food.
Drug-Lifestyle Interactions
Tobacco: In a population pharmacokinetic study in migraine patients, tobacco use was associated with a 29% increase in naratriptan clearance.
Drug-Laboratory Interactions
Naratriptan tablets are not known to interfere with commonly employed clinical laboratory tests.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Sandoz Naratriptan is recommended only for the acute treatment of migraine attacks. Sandoz Naratriptan should not be used prophylactically.
- The safety of treating, on average, more than four headaches in a 30 day period has not been established.
- If a patient does not respond to the first dose of Sandoz Naratriptan, a second dose should not be taken for the same attack, as it is unlikely to be of benefit.
- Sandoz Naratriptan can be taken with or without food.
Recommended Dose and Dosage Adjustment
Adults: The minimal effective single adult dose of naratriptan tablet is 1 mg*. The maximum recommended single dose is 2.5 mg which should not be exceeded (see CLINICAL TRIALS).
* Sandoz Naratriptan is not available as 1 mg strength
Table 2: Percentage of Patients with Headache Relief at 4 Hours Post-Dosing▼
| Placebo | Naratriptan Tablets 1 mg* | Naratriptan Tablets 2.5 mg | |||||||
| % | (N) | % | (N) | % | (N) | ||||
| Study 1 | 39 | (91) | 64 | (85) | 63^ | (87) | |||
| Study 2 | 34 | (122) | 50* | (117) | 60*^ | (127) | |||
| Study 3 | 27 | (107) | 52* | (219) | 66*φ | (209) | |||
| Study 4 | 33 | (602) | 57* | (595) | 68*φ | (586) | |||
▼ : Pain relief is defined as a reduction in headache severity from grade 3 or 2 (severe or moderate) to grade 1 or 0 (mild or no pain)
^ : Comparison between 1 mg and 2.5 mg naratriptan tablet doses was not performed
* p<0.05 versus placebo
φ : p<0.01 versus naratriptan tablet 1 mg
In 3 of the 4 studies, optimal rates of headache relief were achieved with a 2.5 mg dose. As patients may vary in their dose-responsiveness, the choice of dose should be made on an individual basis, weighing the possible benefit of the 2.5 mg dose with the potential for a greater risk of adverse events.
Administration
Sandoz Naratriptan should be swallowed whole with water. Sandoz Naratriptan tablets should be taken as early as possible after the onset of a migraine headache, but are effective if taken at a later stage.
Redosing
If the migraine headache returns, or if a patient has a partial response, the initial dose may be repeated once after 4 hours, for a maximum dose of 5 mg in a 24-hour period.
Special Populations
Renal Impairment: Renal disease/functional impairment causes prolongation of the half-life of orally administered naratriptan tablets. Consequently, if treatment is deemed advisable in the presence of renal impairment, a maximum single dose of 1 mg* should be administered. No more than a total of 2 mg should be taken in any 24-hour period. Repeated dosing in renally impaired patients has not been evaluated (see ACTION AND CLINICAL PHARMACOLOGY). Administration of Sandoz Naratriptan in patients with severe renal impairment (creatinine clearance <15 mL/min) is contraindicated (see
CONTRAINDICATIONS).
Hepatic Impairment: Hepatic disease/functional impairment causes prolongation of the half-life of orally administered naratriptan tablets. Consequently, if treatment is deemed advisable in the presence of hepatic impairment, a maximum single dose of 1 mg* should be administered. No more than a total of 2 mg should be taken in any 24 hour period (see ACTION AND CLINICAL PHARMACOLOGY). Administration of Sandoz Naratriptan tablets in patients with severe hepatic impairment (Child-Pugh grade C) is contraindicated (see CONTRAINDICATIONS).
* Sandoz Naratriptan is not available as 1 mg strength.
Hypertension: Sandoz Naratriptan should not be used in patients with uncontrolled or severe hypertension. Patients with mild to moderate controlled hypertension should be treated cautiously at the lowest effective dose.
OVERDOSAGE
For management of suspected drug overdose, contact your regional Poison Control Centre immediately.
In clinical studies, numerous patients (N=222) and healthy subjects (N=196) have received naratriptan tablets (naratriptan hydrochloride) at doses of 5-25 mg. In the majority of cases, no serious adverse events were reported. One patient treated with a 7.5 mg dose experienced ischemic ECG changes which were likely due to coronary vasospasm. This event was not associated with a serious clinical outcome. A patient who was mildly hypertensive experienced a significant increase in blood pressure (baseline value of 150/98 to 204/144 mmHg at 225 minutes) beginning 30 minutes after the administration of a 10 mg dose (4 times the maximum recommended single dose). The event resolved with antihypertensive treatment. Administration of 25 mg (10 times the maximum recommended single dose) in one healthy male subject increased blood pressure from 120/67 mmHg pretreatment up to 191/113 mmHg at approximately 6 hours postdose and resulted in adverse events including lightheadedness, tension in the neck, tiredness, and loss of coordination. Blood pressure returned to near baseline by 8 hours after dosing without any pharmacological intervention.
The elimination half-life of naratriptan is about 5 to 8 hours (see ACTION AND CLINICAL PHARMACOLOGY), and therefore monitoring of patients after overdose with Sandoz Naratriptan should continue for at least 24 hours or longer if symptoms or signs persist. Standard supportive treatment should be applied as required. If the patient presents with chest pain or other symptoms consistent with angina pectoris, electrocardiogram monitoring should be performed for evidence of ischemia. Appropriate treatment (e.g. nitroglycerin or other coronary artery vasodilators) should be administered as required.
It is unknown what effect hemodialysis or peritoneal dialysis has on the serum concentrations of naratriptan.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Naratriptan has been demonstrated to be a selective agonist for a vascular 5-hydroxytryptamine1 receptor subtype (probably a member of the 5-HT1B/1D family) with little or no binding affinity for 5-HT2/3 receptor subtypes, alpha1-, alpha2-, or beta-adrenergic; dopamine1; dopamine2; muscarinic; or benzodiazepine receptors. Naratriptan did not exhibit agonist or antagonist activity in ex vivo assays of 5-HT4 and 5-HT7 receptor-mediated activities.
The therapeutic activity of naratriptan tablet in migraine is generally attributed to its agonist activity at 5-HT1B/5-HT1D receptors. Two current theories have been proposed to explain the efficacy of 5-HT1 receptor agonists in migraine. One theory suggests that activation of 5-HT1 receptors located on intracranial blood vessels, including those on the arteriovenous anastomoses, leads to vasoconstriction, which is believed to be correlated with the relief of migraine headache. The other hypothesis suggests that activation of 5-HT1 receptors on perivascular fibres of the trigeminal system results in the inhibition of pro-inflammatory neuropeptide release. These theories are not mutually exclusive.
Pharmacokinetics
Absorption: Naratriptan is well absorbed, with 74% oral bioavailability in females and 63% in males. After oral administration, the absorption is rapid and peak concentrations are obtained in 2 to 5 hours. A two-period crossover study was performed in 15 female migraine patients who received naratriptan as a single 2.5 mg tablet during a migraine attack, followed 3-7 days later by another 2.5 mg treatment during a non-migraine period. During a migraine attack, absorption is slower, although exposure (AUC) and elimination half-life are not significantly affected.
Table 3: Pharmacokinetic Parameters in Female Migraine Patients After Receiving 2.5 mg Naratriptan Tablets*
| Parameter | Migraine Attack N=15 | Non-Migraine Period N=15 |
| Cmax (ng/mL) | 7.66 (3.07) | 9.50 (3.63) |
| tmax (h) | 3.8 (2.1) | 2.0 (1.0) |
| AUC (ng/mL•h) | 86.7 (32.5) | 92.0 (33.7) |
| CI/F (mL/min) | 467.5 (126.4) | 520.7 (222.6) |
| t1/2 (h) | 6.75 (1.44) | 7.02 (2.39) |
* Values quoted are arithmetic mean (standard deviation)
Cmax : Maximum concentrations tmax : Time to maximum concentrations
CI/F : Apparent clearance t1/2 : Elimination half-life
AUC: Area under the curve of concentration vs time extrapolated to infinity
Plasma levels of naratriptan increase in a dose-proportional manner consistent with linear pharmacokinetics over a 1 to 10 mg dose range. The absorption and elimination are independent of the dose. Administration with food does not appreciably influence the pharmacokinetics of naratriptan. Repeat administration of naratriptan tablets (up to 10 mg once daily for 5 days) does not result in drug accumulation.
Distribution: According to a population pharmacokinetics estimate, naratriptan is distributed into a volume of approximately 261 L. Plasma protein binding is low (29%).
Metabolism: In vitro, naratriptan is metabolized by a wide range of cytochrome P450 isoenzymes into a number of inactive metabolites. Naratriptan is a poor inhibitor of cytochrome P450 isoenzymes, and does not inhibit monoamine oxidase (MAO) enzymes; metabolic interactions between naratriptan and drugs metabolized by P450 or MAO are, therefore, unlikely.
Excretion: The elimination half-life generally ranges from 5-8 hours. Oral clearance is 509 mL/min in females and 770 mL/min in males. The renal clearance (220 mL/min) exceeds the glomerular filtration rate, suggesting that the drug undergoes active tubular secretion. Naratriptan is predominantly eliminated in urine, with 50% of the dose recovered unchanged and 30% as metabolites.
Special Populations and Conditions
Geriatrics: A study was performed to compare the pharmacokinetics of naratriptan in young (6 female/6 male, 24-44 years of age) and elderly (6 female/6 male, 65-77 years of age) subjects. The subjects received two doses each of placebo, 1 mg naratriptan, and 2.5 mg naratriptan separated by 4 hour intervals. A minimum 96 hour period intervened between consecutive treatment days.
Elderly patients experienced a higher degree of exposure to naratriptan than did younger subjects. Mean Cmax and area under the plasma concentration time curve values were 28% and 38% higher, respectively, for the 1 mg treatment group and 15% and 32% higher, respectively, for the 2.5 mg group. Total and renal clearance were decreased by about 30%, while the elimination half-life was increased by about 1 hour.
Elevations in systolic blood pressure at the 2.5 mg dose were more pronounced in the elderly subjects than in the young subjects (mean peak increases 12 mmHg in elderly versus 2 mmHg in young subjects).
Hepatic Impairment: Liver metabolism plays a limited role in the clearance of naratriptan. The pharmacokinetics of a single 2.5 mg dose of naratriptan were determined in subjects with moderate hepatic impairment (Child-Pugh grade A or B, N = 8) and gender- and age-matched healthy subjects (N=8). Subjects with hepatic impairment showed a moderate decrease in clearance (approximately 30%) resulting in increases of approximately 40% in the half-life (range, 8 to 16 hours) and the area under the plasma concentration time curve (see DOSAGE AND ADMINISTRATION).
Renal Impairment: Renal excretion is the major route for elimination of naratriptan. A study to compare male and female subjects with mild to moderate renal impairment (n = 15; 31-58 years of age, screening creatinine clearance: median 41.2 mL/min, range 18 to 115 mL/min,) to gender-matched healthy subjects (N=8, 21-47 years of age) showed a decrease in oral clearance (mean decreased by 50%) resulting in a longer mean half-life (approximately 11 hours, range, 7 to 20 hours) and an increase in the mean Cmax (approximately 40%). In this study, blood pressure measurements suggested that increased exposure in renally-impaired subjects may be associated with increases in blood pressure which are larger than those seen in healthy subjects receiving the same dose (5 mg). (see DOSAGE AND ADMINISTRATION.)
STORAGE AND STABILITY
Sandoz Naratriptan should be stored between 15-30°C.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Availability of Dosage Form
Sandoz Naratriptan 2.5 mg tablets are Green coloured ‘D’ shaped film-coated tablets with ‘SZ’ debossed on one side and ‘248’ on other side, available in blister packs of 9 tablets.
Composition
Sandoz Naratriptan 2.5 mg tablets contain 2.5 mg of naratriptan (base) as the hydrochloride salt and the following nonmedicinal ingredients: Aluminum Lake FD&C Blue #2, Cellulose Microcrystalline, Croscarmellose Sodium, Hypromellose, Iron Oxide Yellow, Lactose Anhydrous, Lactose Monohydrate, Magnesium Stearate, Titanium Dioxide, Triacetin.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Naratriptan hydrochloride
Chemical Name: 2-[3-(1-Methyl-piperidin-4-yl)-1H-indol-5-yl]-ethane sulphonic acid methylamide hydrochloride
Structural Formula:
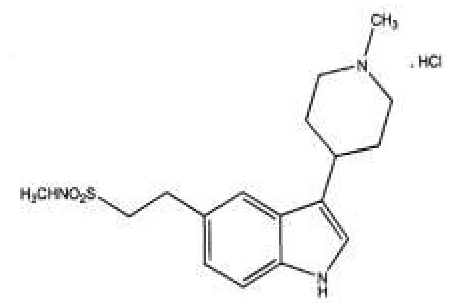
Molecular Formula: C17H25N3O2S•HCl
Molecular Weight: 371.9 g/mol
Physical Characteristics: Off-white to pale yellow crystalline powder with a melting range of 247.7° C to 248.9° C
Solubility: In water (25° C) = 35 mg/mL
pH and pKa: pKa = 12.65 (dimethyl sulphoxide)
pH (1% aqueous solution) = 6.40
CLINICAL TRIALS
Comparative Bioavailability Study
A Blind, Randomized, 2-Way Crossover, comparative bioavailability study of Sandoz Naratriptan (naratriptan hydrochloride, Sandoz Canada Inc.) 2.5 mg tablet versus PrAmerge® (naratriptan hydrochloride, GlaxoSmithKline Inc.) 2.5 mg tablet was conducted in 36 healthy subjects (18 male and 18 female between the ages of 22-39 years old) under fasting conditions. A summary of the pharmacokinetic parameters from the 33 subjects included in the bioavailability comparison is tabulated below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Naratriptan (1 x 2.5 mg) From measured data uncorrected for potency Geometric least-squares Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Sandoz Naratriptan* | PrAmerge® † | % Ratio of Geometric Means1 | 90% Confidence Interval |
AUC0-t (pg.h/mL) | 100763.20 103016.33 (19.36) | 98962.80 101808.96 (22.60) | 101.82% | 98.94% to 104.78% |
AUC0-inf (pg.h/mL) | 104058.64 106381.60 (19.49) | 102128.68 105091.91 (22.74) | 101.89% | 99.16% to 104.69% |
AUCRefTmax (pg.h/mL) | 14853.30 18338.46 (64.68) | 15285.69 17525.11 (52.51) | 97.17% | 89.78% to 105.17% |
Cmax (pg/mL) | 9958.91 10254.18 (22.57) | 10012.44 10383.21 (27.00) | 99.47% | 93.38% to 105.95% |
Tmax€ (h) | 2.61 (50.93) | 2.67 (46.66) | ||
T½ el€ (h) | 7.30 (16.55) | 7.26 (17.16) | ||
* Sandoz Naratriptan (Naratriptan Hydrochloride) 2.5 mg tablets (Sandoz Canada Inc.)
† GlaxoSmithKline Inc., Canada (country of purchase Canada)
€ Expressed as the arithmetic mean (CV%) only
1 Based on least-squares mean estimates
Clinical Trials
Four double-blind, placebo-controlled, dose-ranging clinical trials evaluated the safety and efficacy of naratriptan tablet at oral doses ranging from 0.1 to 10 mg in a total of 3,160 adult patients with migraine attacks characterized by moderate or severe pain. The minimal effective dose was 1.0 mg. In three of the four clinical trials, a higher overall rate of headache relief was achieved with a 2.5 mg dose. Single doses of 5 mg and higher are not recommended due to an increased incidence of adverse events. Onset of significant headache relief (defined as no or mild pain) became apparent at 60-120 minutes after these doses. Naratriptan tablet also relieved the nausea, phonophobia and photophobia associated with migraine attacks.
The following table shows the 4 hour efficacy results obtained for the recommended doses of naratriptan tablet in 2 of the 4 dose-ranging efficacy studies. In Study 1, patients were randomized to receive placebo or a particular dose of naratriptan tablet for the treatment of a single migraine attack according to a parallel group design, whereas, in Study 2, patients were randomized to receive each of the treatments for separate migraine attacks according to a crossover design. In both studies, patients who achieved headache relief at 240 minutes postdose, but experienced a worsening of severity between 4 and 24 hours postdosing were permitted to take a second dose of double-blind medication identical to the first.
Table 4: Results at 240 Minutes Post First Dose
| Parameter | Study 1 | Study 2 | ||||
Placebo (N=107) | Naratriptan tablet 1 mg (N=219) | Naratriptan tablet 2.5 mg (N=209) | Placebo (N=602) | Naratriptan tablet 1 mg (N=595) | Naratriptan tablet 2.5 mg (N=586) | |
| Pain relief (0/1)1 | 27% | 52%* | 66%*φ | 33% | 57%* | 68%*φ |
| Pain free (0)2 | 10% | 26%* | 43%*φ | 15% | 33%* | 45%* |
| Nausea free | 56% | 71%● | 77%● | 54% | 69%* | 75%* |
| Photophobia free | 34% | 57%● | 67%● | 33% | 53%* | 61%* |
| Phonophobia free | ^ | ^ | ^ | 36% | 55%* | 65%* |
Clinical disability (0/1)3 | 49% | 62%● | 72%● | 50% | 70%* | 76%* |
1 Pain relief is defined as a reduction in headache severity from grade 3 or 2 (severe or moderate) to grade 1 or 0 (mild or no pain)
2 : Pain free is defined as a headache severity score of 0 (no pain)
3 : Clinical disability is measured on a 4-point scale (0=able to function normally, 1=ability mildly impaired, 2=ability severely impaired, 3=bed rest required)
^ : Photophobia and phonophobia collected as one measure
* p<0.01 versus placebo
φ : p<0.01 versus Naratriptan tablet 1 mg. Note comparisons were not performed for any parameter other than pain relief and pain free in study 1 and for pain relief in study 2.
- : Statistical comparisons not performed
Significant headache relief was sustained for over 24 hours. Data from four placebo-controlled studies (N=3160) showed that of the patients who achieved headache relief with naratriptan tablets 2.5 mg, 72% to 83% did not experience recurrence of headache between 4 and 24 hours postdosing.
Subgroup analyses of the overall population of patients participating in the placebo-controlled trials, indicate that the efficacy of naratriptan tablets was unaffected by migraine type (with/without aura), gender, oral contraceptive use, or concomitant use of common migraine prophylactic drugs (e.g. beta-blockers, calcium channel blockers, tricyclic antidepressants). In a long-term, repeated dose, open study of 417 patients (all were initiated on a 2.5 mg dose of naratriptan tablet but were given the option to titrate down to a 1 mg dose if 2.5 mg was not well tolerated) a total of 15,301 attacks were treated (mean number of treated attacks/patient of 36 for the 2.5 mg dose and 8 for the 1 mg dose) over a period of up to 12 months. Headache response was sustained (as judged by the proportion of attacks treated with naratriptan tablet resulting in headache relief). The median percentage of attacks per patient requiring a second dose for headache recurrence was 8%. Of the 417 patients treating attacks, 10 patients opted for a dosage reduction.
DETAILED PHARMACOLOGY
Animal
Naratriptan has been shown to have a high affinity for human recombinant 5-HT1B (pKi=8.7) and 5-HT1D (pKi=8.3) receptors. Naratriptan appears to act as an agonist at these receptors, causing selective vasoconstriction of isolated intracranial blood vessels from dogs in in vitro models (ED50=0.07-0.11 mcM). In anesthetized dogs, naratriptan treatment was associated with a dose-dependent decrease in carotid arterial blood flow in association with an increase in carotid arterial vascular resistance. The cumulative dose required to produce 50% of its own maximum vasoconstriction was 19 mcg/kg IV. Naratriptan was also associated with increases in vascular resistance in the femoral, renal, vertebral, and coronary artery beds, although these effects were less than at the cranial artery.
Naratriptan caused vasoconstriction of isolated coronary arteries obtained from anesthetized monkeys (ED50 30-47 nM) and from humans (ED50 170 nM) undergoing heart transplantation.
In addition, naratriptan inhibits plasma protein extravasation from blood vessels in the dura following trigeminal nerve stimulation in anesthetized rats resulting in a decrease of the neurogenic inflammation response (ID50=4.1 mcg/kg IV). In anesthetized cats, naratriptan (30-100 mcg/kg IV) gains access to the central nervous system (CNS) and inhibits trigeminal nerve firing. Naratriptan does not exert a generalized analgesic effect.
In rats receiving oral (50 mg/kg) or intravenous (24 mg/kg) naratriptan, the main acute effects consisted of behavioural depression. In dogs receiving the drug by means of oral (1 mg/kg) or intravenous (0.3 mg/kg) routes, the predominant acute effects consisted of mydriasis, hind limb stiffness, increased barking, and tachycardia. Effects seen in the rat occurred at exposures around 40 (oral, based on AUC) and 400 (intravenous, based on Cmax) times that seen in humans following a single 5 mg (tablet) dose; whilst the main effects in the dog occurred at exposures around 5 (oral, based on AUC) and 11 (intravenous, based on Cmax) times that seen in humans.
No evidence was found to suggest that naratriptan would interfere with pentobarbitone metabolism; nor was it seen to produce symptoms characteristic of 5-HT behavioural syndrome when administered together with a monoamine oxidase inhibitor (pargyline), a 5-HT reuptake inhibitor (fluoxetine) or lithium.
The absorption, distribution and excretion of naratriptan are similar in rats, mice, rabbits, dogs and humans. Oral bioavailability has been determined to be 39% in the rat and 68% in the dog. The time to peak plasma concentrations following oral administration varies from less than 1 hour in the dog to 3 to 4 hours in the rat. The elimination half-life ranges from 0.7 hours in the rabbit to 4.6 hours in the mouse.
The drug undergoes limited metabolism with unchanged naratriptan being the predominant plasma component in all species studied, as well as the major urinary component in humans, dogs, rats, and mice. The majority of metabolites have been characterized and are shown to be excreted rapidly in the urine. The metabolism of naratriptan in humans is most similar to that in the dog, with the N-oxide of naratriptan as the major metabolite. None of the metabolites tested, including the N-oxide, demonstrated any significant pharmacological activity at vascular 5-HT1 receptors.
Plasma protein binding was low in all species studied (21-35%). Drug-related material was widely distributed throughout most tissues following oral or intravenous administration to the rat with highest concentrations being observed in the gastrointestinal tract, liver, kidneys, and bladder. Only trace concentrations were detected in the brain and central nervous system following intravenous dosing. Following oral dosing, radioactive drug-related material in central nervous tissues was undetectable. Low levels of radioactivity persisted in the eyes (of pigmented animals, probably associated with melanin), testes, liver and kidney (and in some cases bladder and thyroid) at later timepoints (up to 168 hours after dosing). Radioactive drug-related material was still detected in the eyes 3 months post-administration (last time point studied).
Drug-related material has been shown to cross the placenta in pregnant rats and rabbits. Following oral administration, the ratio of drug-related radioactivity in fetal tissue to maternal plasma ranged from 0.2 to 1.9 in rats and 0.3 to 0.7 in rabbits. Naratriptan is likewise distributed into the milk of lactating rats. At 2 hours post oral gavage dosing levels in milk were 3.5 times higher than maternal plasma levels.
Following oral administration to the dog approximately 65-75% of the dose was excreted in the urine and 22-32% in the feces. For mice and rats, urinary excretion accounted for 30-40% of the dose, while 50-60% was excreted in the feces.
TOXICOLOGY
Acute Toxicology
Naratriptan was shown to have low acute toxicity. Mice and rats of both sexes appeared equally sensitive to the effects of naratriptan. Maximum oral non-lethal dosages of >1000 mg/kg and approximately 750 mg/kg were established for the mouse and rat, respectively. Maximum non-lethal dosages for both species were in the range ≥ 180 to 225 mg/kg and ≥ 30 to 40 mg/kg for the subcutaneous and intravenous routes, respectively.
Clinical signs were indicative of behavioural depression and effects on the central nervous system, consistent with findings seen with sumatriptan. Target organ toxicity was seen in the testes/epididymides at an oral dose of 340 mg/kg, in the rat only. All treatment-related effects occurred at dosages significantly greater than the maximum oral dose proposed for clinical use (2 x 2.5 mg/day).
Long-Term Toxicology and Carcinogenicity
Naratriptan has low acute toxicity and is well tolerated in repeat dose studies in the rat and dog, at dosages, and resulting systemic exposures (based on AUC), considerably higher than those achieved in humans.
In rats, increased mortality was observed following repeat oral administration for up to 29 weeks at a systemic exposure ranging from approximately 400 to 1000 times that seen in humans following an oral (tablet) dose of 5 mg. At the same exposure level, effects on the testes and epididymides, a slight reduction in prostate weight, changes in the female reproductive tract (atrophic or cystic ovaries and vaginal anoestrus), and atrophy of the granular ducts of the submandibular salivary glands (predominantly in females) were observed. The effects in females, together with the changes in oestrus cycles seen in the oral fertility study, are considered indicative of a disturbance in hormonal balance. The effects were mild and with the exception of the testicular/epididymal atrophy, showed recovery after a treatment-free period. At the no-effect level for these findings systemic exposure was approximately 70 to 100 times that seen in humans following an oral (tablet) dose of 5 mg.
In the dog, two high dosage (5 mg/kg/day) males were killed towards the end of the oral 12-month study following repeated convulsive episodes, but neurological and histological examination revealed no significant findings. The Beagle is recognized as having a high incidence of primary epilepsy and no similar findings were seen in the other animals at this dosage. Transient changes in the pre-corneal tear film were observed following repeated oral or intravenous administration. These effects were considered to be pharmacologically mediated and have been seen previously with sumatriptan. They were not associated with any histological damage to the cornea or surrounding tissue.
In a carcinogenicity study, naratriptan (90 mg/kg/day) caused an increased incidence of proliferative lesions of the thyroid gland, in the rat only. At the maximum oral dosage with no oncogenic effect (20 mg/kg/day), systemic exposure was up to approximately 100 times that seen in humans following an oral (tablet) dose of 5 mg. In mice, an increased incidence of hypophyseal adenoma was reported in females and Harderian gland adenoma in males at the intermediate dosage only (65 mg/kg/day). Naratriptan was therefore considered not to be oncogenic in the mouse up to a dosage of 200 mg/kg/day.
Mutagenicity
Naratriptan, or naratriptan spiked with certain synthetic or degradation impurities, was not mutagenic in any of the in vitro or in vivo systems used, presenting no detectable genetic hazard or clastogenic effect. Naratriptan can be nitrosated in vitro in the World Health Organization Nitrosation Assay Procedure test to form an N-nitroso derivative which is a bacterial mutagen. Exposure to the N-nitroso derivative of naratriptan was demonstrated in the stomach of nitrite-supplemented rats in a specially designed carcinogenicity study.
However, the generation in situ of this nitrosated product was not associated with any carcinogenic potential in the liver or gastro-intestinal tract.
Reproduction and Teratology
In the oral fertility study in rats, naratriptan resulted in maternal toxicity which was associated with increased pre-implantation loss, fetal growth retardation, delayed fetal ossification, and reduced survival of F1 pups at the high dosage (340 mg/kg/day). However, overall reproductive performance of the F0 and F1 generations, and development of the F1 and F2 generations, were unaffected by treatment with naratriptan.
Naratriptan was not teratogenic in the rat or rabbit. In the rat, maternal toxicity was seen, which was accompanied by slight increases in early post-implantation loss and minor skeletal effects. In the Dutch rabbit, maternal toxicity was accompanied by increases in pre- and post-implantation loss and, at all dosages (1, 5 and 30 mg/kg PO), minor skeletal effects and variations in the position of the cervico-thoracic vasculature. In the New Zealand White rabbit, however, the embryonic loss and effects on the fetal vasculature were not reproducible despite exposure to identical doses, and maternal toxicity was accompanied only by an increased incidence of minor skeletal variants.
In the peri-/post-natal study, maternal toxicity which was accompanied by reduced survival of F1 pups was seen at the high dosage (340 mg/kg/day), together with some transient effects on early post-natal development which reversed after weaning. However, parturition, outcome of pregnancy, reproductive performance of the F1 generation, and F2 embryonic development were unaffected by treatment with naratriptan.
Local Tolerance
In local tolerance studies, naratriptan hydrochloride was slightly irritant to the rabbit eye and produced no significant irritant reactions, when applied topically to intact skin in the guinea pig, but was slightly irritant on abraded skin. The sensitizing potential of the compound in the guinea pig, if any, was considered to be very low. In addition, neither naratriptan hydrochloride nor a naratriptan-protein mixture showed any activity in either an active systemic anaphylaxis test or passive cutaneous anaphylaxis test in guinea pigs.
REFERENCES
- 1. Connor HE, Feniuk North PC, Oxford AW & Humphrey PPA. Naratriptan: biological profile in animal models relevant to migraine. Cephalalgia 1997;17:145-152.
- 2. Fuseau E, Kempsford RD, Moss J. The pharmacokinetics of oral naratriptan in subjects with impaired hepatic function [abstract].Cephalalgia 1997;17(3):409.
- 3. Gobel H, Winter P, Boswell D, Crisp A, Becher W, Hange T et al. Comparison of Naratriptan and Sumatriptan in Recurrence-Prone Migraine Patients. Clinical Therapeutics 2000; 22 (8): 981-989
- 4. Gunasekara NS and Wiseman LR. Naratriptan. CNS Drugs 1997;8(5):402-408.
- 5. Heywood J, Enahoro H, Winter P and Hassani H. Tolerability and efficacy of oral naratriptan 2.5 mg in the acute treatment of migraine over a 12-month period [abstract]. J Neurol Sci 1997;150(Suppl):S34.
- 6. Kempsford RD, Baille P, Fuseau E. Oral naratriptan tablets (2.5 mg to 10 mg) exhibit dose-proportional pharmacokinetics [abstract]. Cephalalgia 1997;17(3):408.
- 7. Kempsford RD, Fuseau E, Snell P, Crisp A, Noble JM, Ford GA. Oral naratriptan pharmacokinetics are predictable in subjects with impaired renal function [abstract]. Cephalalgia 1997;17(3):408.
- 8. Kempsford RD, Hoke JF, Huffman CS. The safety, tolerability and pharmacokinetics of oral naratriptan in healthy subjects [abstract]. Cephalalgia 1997;17(3):416-417.
- 9. Klassen A, Elkind A, Asgharnejad M, Webster C, Laurenza A. Naratriptan is effective and well tolerated in the acute treatment of migraine. Results of a double-blind, placebo-controlled, parallel-group study. Headache 1997;37:640-645.
- 10. Mathew NT, Asgharnejad M, Peykamian M, Laurenza A. Naratriptan is effective and well tolerated in the acute treatment of migraine. Neurology 1997;49:1485-1490.
- 11. Yogendran L, Boswell D, Winter PBO’B, Nacci P. Subcutaneous naratriptan (1 mg, 5 mg, 10 mg) has no effect on peripheral blood flow as measured by forearm blood flow [abstract]. Cephalalgia 1997;17(3):425.
- 12. GlaxoSmithKline Inc.; Product Monograph: AMERGE (Naratriptan hydrochloride tablets); Date of Revision: November 2, 2016; Control number: 195190.