


Product Monograph - Sandoz Valsartan HCT
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery | 11/2023 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Ophthalmologic | 11/2023 |
| 7 WARNINGS AND PRECAUTIONS, Respiratory | 11/2023 |
| 9.1 Serious Drug Interactions | 11/2023 |
TABLE OF CONTENTS
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics (< 18 years of age) .................................................................................... 4
1.2 Geriatrics (> 65 years of age) .................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 5
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations .............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ......................................................... 6
4.5 Missed Dose .............................................................................................................. 6
5 OVERDOSAGE ............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 7
7 WARNINGS AND PRECAUTIONS .................................................................................. 8
7.1 Special Populations ................................................................................................. 13
7.1.1 Pregnant Women ................................................................................................ 13
7.1.2 Breast-feeding ..................................................................................................... 14
7.1.3 Pediatrics ............................................................................................................. 15
7.1.4 Geriatrics ............................................................................................................. 15
8 ADVERSE REACTIONS................................................................................................ 15
8.2 Clinical Trial Adverse Reactions .............................................................................. 15
8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 18
8.4 Abnormal Laboratory Findings: Hematologic, Clinical chemistry and Other Quantitative Data .............................................................................................................. 18
8.5 Post-Market Adverse Reactions .............................................................................. 19
9 DRUG INTERACTIONS ............................................................................................... 20
9.1 Serious Drug Interactions ....................................................................................... 20
9.2 Drug-Drug Interactions ........................................................................................... 20
9.5 Drug-Food Interactions ........................................................................................... 26
9.6 Drug-Herb interactions ........................................................................................... 26
9.7 Drug-Laboratory Test Interactions.......................................................................... 26
10 CLINICAL PHARMACOLOGY ....................................................................................... 26
10.1 Mechanism of Action .......................................................................................... 26
10.2 Pharmacodynamics ............................................................................................. 27
10.3 Pharmacokinetics ................................................................................................ 28
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 30
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 30
PART II : SCIENTIFIC INFORMATION ..................................................................................... 31
13 PHARMACEUTICAL INFORMATION ........................................................................... 31
14 CLINICAL TRIALS ....................................................................................................... 32
14.1 Clinical Trials by Indication .................................................................................. 32
15 MICROBIOLOGY ....................................................................................................... 32
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 32
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 40
PATIENT MEDICATION INFORMATION ................................................................................. 41
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Sandoz Valsartan HCT (valsartan and hydrochlorothiazide tablets) is indicated for the treatment of mild to moderate essential hypertension in patients for whom combination therapy is appropriate.
Sandoz Valsartan HCT is not indicated for initial therapy (see 4 DOSAGE AND ADMINISTRATION).
Patients should be titrated on individual drugs. If the fixed combination represents the dose and dosing frequency determined by this titration, the use of Sandoz Valsartan HCT may be more convenient in the management of patients. If during maintenance therapy dosage adjustment is necessary it is advisable to use the individual drugs.
1.1 Pediatrics (< 18 years of age)
The safety and efficacy of valsartan and hydrochlorothiazide tablets in children and adolescents (below the age of 18 years) have not been established and use in this age group is not recommended.
1.2 Geriatrics (> 65 years of age)
No overall age-related differences were seen in the adverse effect profile but greater sensitivity in some older individuals cannot be ruled out and appropriate caution is recommended.
2 CONTRAINDICATIONS
- Sandoz Valsartan HCT is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
- Because of the hydrochlorothiazide component, it is also contraindicated in patients with anuria, severe progressive renal disease and if increasing azotemia and oliguria occur during treatment.
- Patients who are hypersensitive to other sulfonamide-derived drugs.
- Sandoz Valsartan HCT is also contraindicated in pregnant and nursing women (see 7.1.2 Breast-feeding).
- Thiazide diuretics are contraindicated in patients with hyponatremia, hypercalcemia, symptomatic hyperuricemia, and conditions involving enhanced potassium loss.
Concomitant use of angiotensin receptor antagonists (ARBs) - including valsartan - or of angiotensin-converting-enzyme inhibitors (ACEIs) with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or type 2) or moderate to severe renal impairment (GFR <60ml/min/1.73m2) is contraindicated (see 7 WARNINGS AND PRECAUTION, Cardiovascular, Dual Blockade of the Renin-Angiotensin System (RAS) and Renal and 9.4 Drug-Drug Interactions, Dual Blockade of the Renin-Angiotensin-System
- (RAS) with ARBs, ACEIs, or aliskiren).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Dosage must be individualized. The fixed combination is not for initial therapy. The dose of Sandoz Valsartan HCT (valsartan and hydrochlorothiazide) should be determined by the titration of the individual components.
- Hepatic Impairment
No initial dosage adjustment in valsartan is required in patients with mild to moderate hepatic impairment. Due to the hydrochlorothiazide component, Sandoz Valsartan HCT is not recommended in patients with severe hepatic impairment (see 7 Warnings and Precautions). Because thiazide diuretics may precipitate hepatic coma, care should be exercised when administering a fixed combination product containing hydrochlorothiazide (see 7 WARNINGS AND PRECAUTIONS). Due to the valsartan component, Sandoz Valsartan HCT should be used with particular caution in patients with biliary obstructive disorders (see 2 Contraindications and 7 Warnings and Precautions).
- Renal Impairment
No dosage adjustment is required for patients with mild to moderate renal impairment (Glomerular Filtration Rate (GFR) ≥30 mL/min/1.73m2). Due to the hydrochlorothiazide component, Sandoz Valsartan HCT is contraindicated in patients with severe renal impairment (creatinine clearance < 30 mL/min/1.73m2) and with anuria (see 2 Contraindications) and should be used with caution in patients with severe renal impairment (GFR <30 mL/min/1.73m2) (see 7 Warnings and precautions and 10.3 Pharmacokinetics).
- Elderly
No dosage adjustment is usually necessary however see 7 WARNINGS AND PRECAUTIONS.
Serious Warnings and Precautions
Pregnancy: angiotensin receptor (AT1) blockers (ARB) can cause injury to or even death of the developing fetus. When pregnancy is detected, Sandoz Valsartan HCT should be discontinued as soon as possible (see 2 CONTRAINDICATIONS and 7.1 Special Populations).
4.2 Recommended Dose and Dosage Adjustment
Once the patient has been stabilized on the individual components as described below, Sandoz Valsartan HCT tablet, 80mg/12.5mg, 160mg/12.5mg, 160 mg/25, 320mg/12.5mg, or 320mg/25mg once daily may be substituted if the doses on which the patient was stabilized are the same as those in the fixed combination (see 1 INDICATIONS and 7 WARNINGS AND PRECAUTIONS).
The maximum recommended dose is 320 mg valsartan and 25 mg hydrochlorothiazide and the titration will be based on physician’s judgment according to severity of hypertension and other associated risk factors.
Sandoz Valsartan HCT may be administered with or without food, however it should be taken consistently with respect to food intake.
- Valsartan monotherapy
The recommended starting dose of valsartan tablets is 80 mg once daily. The antihypertensive effect is present within 2 weeks and maximal reduction is usually attained within 4 weeks following initiation of therapy. In patients whose blood pressure is not adequately controlled, the daily dose may be increased to a maximum of 320 mg or a thiazide diuretic added.
- Diuretic-Treated Patients
In patients receiving diuretics, valsartan therapy should be initiated with caution, since these patients may be volume-depleted and thus more likely to experience hypotension following initiation of additional anti-hypertensive therapy. Whenever possible, all diuretics should be discontinued two to three days prior to the administration of Sandoz Valsartan HCT to reduce the likelihood of hypotension (see 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS). If this is not possible because of the patient’s condition, Sandoz Valsartan HCT should be administered with caution and the blood pressure monitored closely. Thereafter, the dosage should be adjusted according to the individual response of the patient.
4.5 Missed Dose
Patients should try to take their dose at the same time each day, preferably in the morning. However, if they have forgotten to take the dose during the day, they should carry on with the next dose at the usual time. They should not double doses.
5 OVERDOSAGE
No specific information is available on the treatment of overdosage with valsartan and hydrochlorothiazide tablets. Treatment is symptomatic and supportive.
For management of a suspected drug overdose, contact your regional poison control centre.
Valsartan
Limited data are available in regard to overdosage with valsartan in humans. The most likely manifestations of overdosage would be hypotension, which could lead to depressed level of consciousness, circulatory collapse and/or shock, and/or tachycardia. If symptomatic hypotension should occur, supportive treatment should be instituted.
Valsartan is not removed from the plasma by dialysis.
Hydrochlorothiazide
The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias.
The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral | Tablets: 80mg/12.5mg 160mg/12.5mg 160mg/25mg 320mg/12.5mg 320mg/25mg (valsartan/hydrochlorothiazide) | Colloidal silicon dioxide, crospovidone, hydroxypropyl methylcellulose, magnesium stearate, microcrystalline cellulose, polyethylene glycol, talc, and titanium dioxide. Additional nonmedicinal ingredients for: Sandoz Valsartan HCT 80/12.5 mg tablets: red iron oxide and yellow iron oxide. Sandoz Valsartan HCT 160/12.5 mg tablets: red iron oxide. Sandoz Valsartan HCT 160/25 mg tablets: black iron oxide, red iron oxide and yellow iron oxide. Sandoz Valsartan HCT 320/12.5 mg tablets: black iron oxide and red iron oxide. Sandoz Valsartan HCT 320/25 mg tablets: yellow iron oxide. |
Description
Sandoz Valsartan HCT tablets, 80mg/12.5mg: Each light orange, ovaloid, film-coated tablet with slightly convex faces and bevelled edges, debossed with “HGH” on one side and “CG” on the other contains 80 mg of valsartan and 12.5 mg of hydrochlorothiazide as the active ingredients. These are supplied in bottles of 100 and 500 tablets and in cartons containing 2 blister strips of 15 tablets.
Sandoz Valsartan HCT tablets, 160mg/12.5mg: Each dark red, ovaloid, film-coated tablet with slightly convex faces and bevelled edges, debossed with “HHH” on one side and “CG” on the other contains 160 mg of valsartan and 12.5 mg of hydrochlorothiazide as the active ingredients. These are supplied in bottles of 100 and 500 tablets and in cartons containing 2 blister strips of 15 tablets.
Sandoz Valsartan HCT tablets, 160mg/25mg: Each brown orange, ovaloid, film-coated tablet with slightly convex faces, debossed with “HXH” on one side and “NVR” on the other contains 160 mg of valsartan and 25 mg of hydrochlorothiazide as the active ingredients. These are supplied in bottles of 100 and 500 tablets and in cartons containing 2 blister strips of 15 tablets.
Sandoz Valsartan HCT tablets, 320mg/12.5mg: Each pink, ovaloid, film-coated tablet with bevelled edges, debossed with “NVR” on one side and “HIL” on the other contains 320 mg of valsartan and 12.5 mg of hydrochlorothiazide as the active ingredients. These are supplied in cartons containing 2 blister strips of 15 tablets.
Sandoz Valsartan HCT tablets, 320mg/25mg: Each yellow, ovaloid, film-coated tablet with bevelled edges debossed with “NVR” on one side and “CTI” on the other contains 320 mg of valsartan and 25 mg of hydrochlorothiazide as the active ingredients. These are supplied in bottles of 100 and in cartons containing 2 blister strips of 15 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Angioedema
Angioedema, including swelling of the larynx and glottis, causing airway obstruction and/or swelling of the face, lips, pharynx, and/or tongue has been reported in patients treated with valsartan: some of these patients previously experienced angioedema with other drugs including ACE inhibitors. Sandoz Valsartan HCT should be immediately discontinued in patients who develop angioedema, and Sandoz Valsartan HCT should not be re-administered.
If laryngeal stridor or angioedema of the face, extremities, lips, tongue, or glottis occurs, Sandoz Valsartan HCT should be discontinued immediately, the patient treated appropriately in accordance with accepted medical care, and carefully observed until the swelling disappears. In instances where swelling is confined to the face and lips, the condition generally resolves without treatment, although antihistamines may be useful in relieving symptoms. Where there is involvement of tongue, glottis, or larynx, likely to cause airway obstruction, appropriate therapy (including, but not limited to 0.3 to 0.5 ml of subcutaneous epinephrine solution 1:1000) should be administered promptly (see 8.5 Post Marketing Adverse Reactions).
Patients with a known hypersensitivity (anaphylaxis) or angioedema to ARBs should not be treated with Sandoz Valsartan HCT (see 8.5 Post Market Adverse Reactions).
Carcinogenesis and Mutagenesis
Non-melanoma skin cancer
An increased risk of non-melanoma skin cancer (NMSC) [basal cell carcinoma (BCC) and squamous cell carcinoma (SCC) of the skin] after hydrochlorothiazide therapy was reported in some epidemiological studies. The risk may be higher with increasing cumulative use. The certainty of the evidence was assessed by Health Canada (see 8.5 Post Market Adverse Reactions). The photosensitizing action of hydrochlorothiazide may be a possible mechanism for NMSC (see 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity – Hydrochlorothiazide).
Patients taking hydrochlorothiazide should be informed of the potential risk of NMSC, They should be advised to regularly check their skin for new lesions as well as changes to existing ones, and to promptly report any suspicious skin lesions. Patients should also be advised to limit exposure to sunlight, to avoid the use of indoor tanning equipment, and to use adequate protection (e.g. a broad spectrum sunscreen with a SPF of 30 or higher, clothing, and a hat) when exposed to sunlight or UV light to minimize the risk of skin cancer.
Alternatives to hydrochlorothiazide may be considered for patients who are at a particularly high risk for NMSC (e.g., light coloured skin, known personal or family history of skin cancer, ongoing immunosuppressive therapy, etc.) (see 8.5 Post Market Adverse Reactions).
Photosensitivity
Photosensitivity reactions have been reported with the use of thiazide diuretics.
If photosensitivity reactions occur during treatment with hydrochlorothiazide-containing drugs, treatment should be stopped.
Cardiovascular
Hypotension
Occasionally, symptomatic hypotension has occurred after administration of valsartan, in some cases after the first dose. It is more likely to occur in patients who are volume-depleted by diuretic therapy, dietary salt restriction, dialysis, diarrhea, or vomiting. In these patients, because of the potential fall in blood pressure, therapy should be started under close medical supervision. Similar considerations apply to patients with ischemic heart or cerebrovascular disease, in whom an excessive fall in blood pressure could result in myocardial infarction or cerebrovascular accident.
Valvular Stenosis
There is concern on theoretical grounds that patients with aortic stenosis might be at a particular risk of decreased coronary perfusion when treated with vasodilators, because they do not develop as much after load reduction.
Dual Blockade of the Renin-Angiotensin System (RAS)
There is evidence that co-administration of angiotensin receptor antagonists (ARBs), including valsartan, or of angiotensin-converting-enzyme inhibitors (ACEIs) with aliskiren increases the risk of hypotension, syncope, stroke, hyperkalemia and deterioration of renal function, including renal failure, in patients with diabetes mellitus (type 1 or type 2) and/or moderate to severe renal impairment (GFR<60ml/min/1.73m2). Therefore, the use of Sandoz Valsartan HCT in combination with aliskiren-containing drugs is contraindicated in these patients. Co-administration of ARBs, including Sandoz Valsartan HCT, with other agents blocking the RAS such as ACEIs or aliskiren-containing drugs is not recommended in any patient, as adverse outcomes cannot be excluded.
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism
Serum electrolyte changes
Concomitant use with potassium supplements, potassium-sparing diuretics, salt substitutes containing potassium, or other drugs that may increase potassium levels (heparin, etc.) should be used with caution. Thiazide diuretics can precipitate new onset hypokalemia or exacerbate pre-existing hypokalemia. Thiazide diuretics are contraindicated in patients with conditions involving enhanced potassium loss (refractory hypokalemia), for example salt-losing nephropathies and prerenal (cardiogenic) impairment of kidney function. All patients receiving thiazide diuretics should be monitored for imbalances in electrolytes, particularly potassium.
Thiazide diuretics can precipitate new onset hyponatremia and hypochloremic alkalosis or exacerbate pre-existing hyponatremia. Hyponatremia, accompanied by neurological symptoms (nausea, progressive disorientation, apathy) has been observed in isolated cases. Regular monitoring of serum sodium concentrations is recommended. Patients receiving thiazides should be carefully observed for clinical signs of fluid and electrolyte imbalance (hyponatremia, hypochloremic alkalosis and hypokalemia). Periodic determinations of serum electrolytes to detect possible electrolyte disturbance should be performed at appropriate intervals. Warning signs or symptoms of fluid and electrolyte imbalance include dryness of the mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, and gastrointestinal disturbances such as nausea and vomiting.
Other metabolic disturbances
Like other diuretics, hydrochlorothiazide may raise the serum uric acid level due to reduced clearance of uric acid and may cause or exacerbate hyperuricemia and precipitate gout in susceptible patients. Thiazides are contraindicated in patients with symptomatic hyperuricemia.
Thiazides decrease urinary calcium excretion and may cause mild elevation of serum calcium in the absence of known disorders of calcium metabolism. Since hydrochlorothiazide can increase serum calcium concentrations, it should not be used (see 2 Contraindications) in patients with hypercalcemia.
Pathological changes in the parathyroid gland of patients with hypercalcemia and hypophosphatemia have been observed in a few patients on prolonged thiazide therapy. If hypercalcemia occurs, further diagnostic clarification is necessary and thiazides should be discontinued.
Hypokalemia may develop, especially with brisk diuresis, when severe cirrhosis is present, or after prolonged therapy.
Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g. increased ventricular irritability).
Any chloride deficit during thiazide therapy is generally mild and usually does not require specific treatment except under extraordinary circumstances (as in liver disease or renal disease). Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction rather than administration of salt, except in rare instances, when the hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Increases in cholesterol, triglyceride and glucose levels may be associated with thiazide diuretic therapy, including hydrochlorothiazide.
Hepatic/Biliary/Pancreatic
Hydrochlorothiazide should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance or of serum ammonia may precipitate hepatic coma.
In general, no dosage adjustment is needed in patients with mild to moderate liver disease. Due to the hydrochlorothiazide component, Sandoz Valsartan HCT should not be used (not recommended) in patients with severe hepatic impairment (see 4 DOSAGE AND ADMINISTRATION, Hepatic impairment). However, care should be exercised in patients with liver disease, especially in those patients with biliary obstructive disorders, as the major portion of valsartan is eliminated in the bile. No information is available in patients with severe liver disease (see 10.3 Pharmacokinetics).
Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma.
Ophthalmologic
Choroidal Effusion, Acute Myopia and Secondary Angle-Closure Glaucoma
Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in choroidal effusion, acute transient myopia and/or acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity, blurred vision or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute-angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
Renal
As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function have been seen in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system, such as patients with bilateral renal artery stenosis, unilateral renal artery stenosis to a solitary kidney, or severe congestive heart failure, treatment with agents that inhibit this system has been associated with oliguria, progressive azotemia, and rarely, acute renal failure and/or death. In susceptible patients, concomitant diuretic use may further increase risk.
The incidence of clinically relevant hyperkalemia has also been observed to be increased with valsartan (see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data). Patients exposed to potassium-sparing diuretics and/or potassium supplements were more likely to develop hyperkalemia. Accordingly, their use should be carefully monitored or avoided (see 9 DRUG INTERACTIONS - Agents Increasing Serum Potassium).
Some patients with heart failure have developed increases in blood urea nitrogen, serum creatinine, and potassium. These effects are more likely to occur in patients with pre-existing renal impairment. Dosage reduction and/or discontinuation of Sandoz Valsartan HCT may be required. In the Valsartan Heart Failure Trial, in which 93% of patients were on concomitant ACE inhibitors, treatment was discontinued for elevations in creatinine or potassium in a total of 1.0% on valsartan vs. 0.2% on placebo.
Use of valsartan should include appropriate assessment of renal function.
No dosage adjustment is required for patients with mild to moderate renal impairment (GFR ≥30 mL/min/1.73m2). Because of the hydrochlorothiazide component, Sandoz Valsartan HCT should not be used in patients with severe renal impairment (GFR<30 mL/min/1.73m2). Thiazide diuretics may precipitate azotemia in patients with chronic kidney disease (see 2 CONTRAINDICATIONS). They are ineffective as monotherapy in severe renal impairment (GFR<30 mL/min) (see 4 DOSAGE AND ADMINISTRATION, renal impairment, and 10.3 Pharmacokinetics).
Azotemia
Azotemia may be precipitated or increased by hydrochlorothiazide. Cumulative effects of the drug may develop in patients with impaired renal function. If increasing azotemia and oliguria occur during treatment of severe progressive renal disease the diuretic should be discontinued (see 2 CONTRAINDICATIONS).
Patients with renal impairment
The use of ARBs – including valsartan – or of ACEIs with aliskiren-containing drugs is contraindicated in patients with moderate to severe renal impairment (GFR <60ml/min/1.73m2) (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions, Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACEIs, or aliskiren-containing drugs).
Respiratory
Acute Respiratory Distress
Severe cases of acute respiratory toxicity, including acute respiratory distress syndrome (ARDS), have been reported after taking hydrochlorothiazide. Pulmonary edema typically develops within minutes to hours after hydrochlorothiazide intake. At the onset, symptoms can include dyspnea, fever, pulmonary deterioration and hypotension. If diagnosis of ARDS is suspected, Sandoz Valsartan HCT should be withdrawn, and appropriate treatment should be given. Sandoz Valsartan HCT must not be administered to patients who previously experienced ARDS following intake of hydrochlorothiazide or another thiazide diuretic.
Sensitivity/Resistance
Sensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma.
The possibility of exacerbation or activation of systemic lupus erythematosus has been reported in patients treated with hydrochlorothiazide.
7.1 Special Populations
7.1.1 Pregnant Women
Drugs that act directly on the renin-angiotensin-aldosterone-system (RAAS) can cause fetal and neonatal morbidity and death when administered to pregnant women. When pregnancy is detected, Sandoz Valsartan HCT should be discontinued as soon as possible.
The use of ARB is not recommended during pregnancy. Epidemiological evidence regarding the risk of teratogenicity following exposure to angiotensin converting enzyme inhibitors (another class of therapeutic products interfering with the RAAS) during the first trimester of pregnancy has not been conclusive; however a small increase in risk cannot be excluded. Given the current evidence available on the risk with ARB, similar risks may exist for this class of drugs. Patients planning pregnancy should be changed to alternative anti-hypertensive treatments which have an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with angiotensin II antagonists should be stopped immediately, and, if appropriate, alternative therapy should be started.
The use of ARBs during the second and third trimesters is known to induce human fetotoxicity (decreased renal function, oligohydramnios, skull ossification retardation) and neonatal toxicity (renal failure, hypotension, hyperkalaemia).
There have been reports of spontaneous abortion, oligohydramnios and newborn renal dysfunction, when pregnant women have inadvertently taken valsartan.
Infants with histories of in utero exposure to ARBs should be closely observed for hypotension, oliguria, and hyperkalemia. If oliguria occurs, attention should be directed toward support of blood pressure and renal perfusion. Exchange transfusion may be required as a means of reversing hypotension and/or substituting for impaired renal function; however, limited experience with those procedures has not been associated with significant clinical benefit. Valsartan is not removed from plasma by dialysis.
Thiazides cross the placental barrier and appear in cord blood. The routine use of diuretics, including hydrochlorothiazide in otherwise healthy pregnant women is not recommended and exposes mother and fetus to unnecessary hazard including fetal or neonatal jaundice, thrombocytopenia and possibly other adverse experiences which have occurred in the adult. Diuretics do not prevent development of toxemia of pregnancy and there is no satisfactory evidence that they are useful in the treatment of toxemia.
Animal Data: No teratogenic effects were observed when valsartan was administered orally to pregnant mice and rats at doses up to 600 mg/kg/day and to pregnant rabbits at oral doses up to 10 mg/kg/day. However, significant decreases in fetal weight, pup birth weight, pup survival rate and slight delays in developmental milestones were observed in studies in which parental rats were treated orally with valsartan at maternally toxic (reduction in body weight gain and food consumption) doses of 600 mg/kg/day during organogenesis or late gestation and lactation. In rabbits, fetotoxicity associated with maternal toxicity (mortality) was observed at doses of 5 and 10 mg/kg/day.
7.1.2 Breast-feeding
It is not known whether valsartan is excreted in human milk but significant levels have been found in the milk of lactating rats. Thiazides appear in human milk. Because many drugs are excreted in human milk and because of their potential for affecting the nursing infant adversely, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of valsartan and hydrochlorothiazide tablets in children and adolescents (below the age of 18 years) have not been established and use in this age group is not recommended.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No overall age-related differences were seen in the adverse effect profile but greater sensitivity in some older individuals cannot be ruled out and appropriate caution is recommended.
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Valsartan and hydrochlorothiazide tablets have been evaluated for safety in more than 7616 patients treated for essential hypertension. Of these, 4372 were treated with valsartan and hydrochlorothiazide tablets in controlled clinical trials with a mean exposure of 8 weeks.
In controlled clinical trials, discontinuation due to Adverse Experiences (AEs) occurred in 2.3 % and 3.1 % of patients treated with valsartan and hydrochlorothiazide tablets and placebo, respectively. The most common AEs resulting in discontinuation of therapy with valsartan and hydrochlorothiazide tablets were dizziness and headache.
The most common serious AEs with valsartan and hydrochlorothiazide tablets were myocardial infarction and chest pain.
The following table is based on double-blind, active or placebo-controlled trials in patients treated with valsartan and hydrochlorothiazide tablets at doses of 80mg/12.5mg, 80mg/25mg, 160mg/12.5mg, 160mg/25mg, 320mg/12.5mg and 320mg/25mg, valsartan tablets at doses of 80mg, 160mg, and 320 mg, and HCT at doses of 12.5mg and 25mg (see 14 CLINICAL TRIALS). The table includes all AEs with an incidence of 1% or greater in either the valsartan and hydrochlorothiazide, valsartan monotherapy, HCT monotherapy, or placebo group, irrespective of causal relationship to study drug.
Table 2 - Occurrence of adverse events during double-blind controlled trials in patients treated with valsartan and hydrochlorothiazide tablets at doses of 80mg/12.5mg, 80mg/25mg, 160mg/12.5mg, 160mg/25mg, 320mg/12.5mg and 320mg/25mg.
Valsartan / HCT N= 4372 | Valsartan N= 2447 | Hydrochlorothiazid e N= 535 | Placebo N= 262 | |
|---|---|---|---|---|
| n (%) | n (%) | n (%) | n (%) | |
| Ear and Labyrinth disorders | ||||
| Vertigo | 35 (0.8) | 10 (0.4) | 6 (1.1) | 1 (0.4) |
| Gastrointestinal disorders | ||||
| Diarrhoea | 48 (1.1) | 41 (1.7) | 10 (1.9) | 3 (1.1) |
| Nausea | 37 (0.8) | 21 (0.9) | 10 (1.9) | 4 (1.5) |
| Dyspepsia | 25 (0.6) | 18 (0.7) | 6 (1.1) | 1 (0.4) |
| Vomiting | 13 (0.3) | 11 (0.4) | 1 (0.2) | 4 (1.5) |
| Toothache | 9 (0.2) | 4 (0.2) | 1 (0.2) | 3 (1.1) |
| Constipation | 6 (0.1) | 3 (0.1) | 12 (2.2) | 2 (0.8) |
| General Disorders | ||||
| Fatigue | 72 (1.6) | 26 (1.1) | 22 (4.1) | 4 (1.5) |
| Oedema Peripheral | 25 (0.6) | 27 (1.1) | 10 (1.9) | 3 (1.1) |
| Infections | ||||
| Nasopharyngitis | 103 (2.4) | 67 (2.7) | 15 (2.8) | 5 (1.9) |
| Upper respiratory tract infection | 53 (1.2) | 49 (2.0) | 23 (4.3) | 9 (3.4) |
| Influenza | 37 (0.8) | 22 (0.9) | 8 (1.5) | 3 (1.1) |
| Bronchitis | 33 (0.8) | 15 (0.6) | 6 (1.1) | 3 (1.1) |
| Sinusitis | 29 (0.7) | 23 (0.9) | 7 (1.3) | 6 (2.3) |
| Urinary tract infection | 26 (0.6) | 12 (0.5) | 7 (1.3) | 1 (0.4) |
| Metabolic and nutrition disorders | ||||
| Hypokalaemia | 7 (0.2) | 2 (0.1) | 13 (2.4) | 2 (0.8) |
| Musculoskeletal and connective tissue disorders | ||||
| Back pain | 52 (1.2) | 37 (1.5) | 11 (2.1) | 7 (2.7) |
| Arthralgia | 44 (1.0) | 25 (1.0) | 8 (1.5) | 3 (1.1) |
| Myalgia | 25 (0.6) | 15 (0.6) | 6 (1.1) | 1 (0.4) |
| Pain in extremity | 21 (0.5) | 10 (0.4) | 11 (2.1) | 0 (0.0) |
| Muscle cramp | 18 (0.4) | 3 (0.1) | 10 (1.9) | 3 (1.1) |
| Nervous system disorders | ||||
| Headache | 161 (3.7) | 126 (5.1) | 54 (10.1) | 38 (14.5) |
Valsartan / HCT N= 4372 | Valsartan N= 2447 | Hydrochlorothiazid e N= 535 | Placebo N= 262 | |
|---|---|---|---|---|
| n (%) | n (%) | n (%) | n (%) | |
| Dizziness | 153 (3.5) | 49 (2.0) | 27 (5.0) | 10 (3.8) |
| Somnolence | 11 (0.3) | 8 (0.3) | 1 (0.2) | 3 (1.1) |
| Hypoaesthesia | 10 (0.2) | 5 (0.2) | 2 (0.4) | 4 (1.5) |
| Sinus headache | 4 (0.1) | 7 (0.3) | 3 (0.6) | 3 (1.1) |
| Migraine | 2 (0.0) | 7 (0.3) | 0 (0.0) | 4 (1.5) |
| Psychiatric disorders | ||||
| Insomnia | 16 (0.4) | 12 (0.5) | 3 (0.6) | 3 (1.1) |
| Renal and urinary disorders | ||||
| Pollakiuria | 30 (0.7) | 11 (0.4) | 8 (1.5) | 2 (0.8) |
| Respiratory, thoracic and mediastinal disorders | ||||
| Cough | 52 (1.2) | 37 (1.5) | 11 (2.1) | 2 (0.8) |
| Pharyngolaryngeal pain | 30 (0.7) | 12 (0.5) | 6 (1.1) | 1 (0.4) |
| Sinus congestion | 19 (0.4) | 7 (0.3) | 12 (2.2) | 3 (1.1) |
| Nasal congestion | 16 (0.4) | 14 (0.6) | 7 (1.3) | 0 (0.0) |
| Skin and subcutaneous tissue disorders | ||||
| Rash | 11 (0.3) | 10 (0.4) | 6 (1.1) | 1 (0.4) |
Evaluation of the AEs in the total active-, or placebo-controlled safety population, showed that the most common events, regardless of relationship to treatment in patients treated with valsartan 320 mg/HCT were, dizziness, nasopharyngitis, headache and fatigue. The incidence of hypotension was 0.7% in patients treated with valsartan 320mg/HCT.
The following adverse reactions have been reported in patients treated with thiazide diuretics alone, including hydrochlorothiazide:
Very common: mainly at higher doses, hypokalemia, blood lipids increased (total cholesterol and triglycerides).
Common: Hyponatremia, hypomagnesemia, hyperuricemia, urticaria and other forms of rash, decreased appetite, mild nausea and vomiting, orthostatic hypotension, which may be aggravated by alcohol, anaesthetics or sedatives, and impotence.
Rare: Hypercalcemia, hyperglycemia, glycosuria and worsening of diabetic metabolic state, photosensitivity reaction, abdominal discomfort, constipation, diarrhoea, cholestasis or jaundice, arrhythmias, headache, dizziness, sleep disorders, depression, paresthesia, visual impairment, thrombocytopenia, sometimes with purpura.
Very rare: Hypochloremic alkalosis, vasculitis necrotising, toxic epidermal necrolysis, cutaneous lupus erythematosus-like reactions, reactivation of cutaneous lupus erythematosus, pancreatitis, leukopenia, agranulocytosis, bone marrow failure, haemolytic anaemia, hypersensitivity reactions, respiratory distress including pneumonitis and pulmonary oedema.
8.3 Less Common Clinical Trial Adverse Reactions
Body as a whole: arthritis, asthenia, hypersensitivity, influenza, contusion, insomnia, peripheral oedema, pyrexia, sprains and strains
Cardiovascular: angina pectoris, hypotension, myocardial infarction, palpitations, tachycardia, ventricular systoles
Digestive: motion sickness, stomach discomfort
Ear and Labyrinth: ear pain
Gastrointestinal: abdominal pain, dry mouth, dyspepsia, flatulence, gastritis, toothache, vomiting
Muscoskeletal and connective tissue: arthralgia, myalgia, muscle strain
Metabolic and Nutritional: diabetes mellitus, gout, hypokalaemia, hyperuricaemia
Nervous system/Psychiatric: anxiety, somnolence
Renal and urinary system: micturition frequency, urinary tract infection, pollakiuria
Respiratory, thoracic, mediastinal: bronchitis, chest discomfort/pain, dyspnea pharyngolaryngeal pain, sinus congestion, sinusitis
Reproductive: erectile dysfunction
Skin and subcutaneous tissue: rash
Special senses: blurred vision, conjunctivitis, vertigo, tinnitus, visual disturbance
Other: viral infection
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Potassium: In the double-blind, active or placebo-controlled trials potassium decrease of >20% was observed most frequently with HCT 25mg (9.7%), followed by HCT 12.5mg (6.3%), valsartan/HCT 320/25 mg (4.5%), valsartan 320/12.5 mg (3.8%), and valsartan 320mg (2.0%) compared to placebo (3.1%). Also some patients showed serum potassium increase >20 % but no dose relationship could be demonstrated.
Creatinine/Blood urea nitrogen (BUN)/Uric acid: Minor elevations in creatinine and BUN occurred in 1.9% and 14.7%, respectively, of patients treated with valsartan and hydrochlorothiazide tablets and 0.4% and 6.3%, respectively, of patients given placebo in controlled clinical trials. Uric acid increase of > 50% was observed most frequently with valsartan/HCT 320/25mg (5.5%), followed by valsartan/HCT 320/12.5mg (2.8%), HCT 25mg (2.0%), valsartan 320mg (1.7%), and HCT 12.5mg (0.8%) compared to placebo (1.6%).
Hemoglobin and Hematocrit: Greater than 20% decreases in hemoglobin and hematocrit were observed in less than 0.1% of patients treated with valsartan and hydrochlorothiazide tablets compared with 0.0% of patients given placebo.
Neutropenia: Neutropenia was observed in 0.1% of patients treated with valsartan and hydrochlorothiazide and 0.4% of patients treated with placebo.
8.5 Post-Market Adverse Reactions
Other adverse reactions reported in post-marketing use of valsartan alone include: anaphylaxis (very rarely), angioedema (involving swelling of the face, lips and/or tongue), dermatitis bullous (frequency unknown), photosensitivity, increase in blood pressure and taste disorders. Very rare cases of impaired renal function have also been reported.
The following adverse drug reactions have also been identified based on post-marketing experiences. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequencies. Therefore, the frequency assigned is “not known”: Acute renal failure, renal disorder, aplastic anemia, erythema multiforme, pyrexia, muscle spasm, asthenia, acute angle-closure glaucoma.
Non-melanoma skin cancer: Some pharmacoepidemiological studies have suggested a higher risk of squamous cell carcinoma (SCC) and basal cell carcinoma (BCC) of the skin with increasing use of hydrochlorothiazide. A systematic review and meta-analysis undertaken by Health Canada suggested, with important uncertainty, that the use of hydrochlorothiazide for several years (>3 years) could lead to:
- 122 additional cases (95% CI, from 112 to 133 additional cases) of SCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 3 observational studies);
- 31 additional cases (95% CI, from 24 to 37 additional cases) of BCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 2 observational studies).
Cases of muscle pain, muscle weakness, myositis and rhabdomyolysis have been reported in patients receiving angiotensin II receptor blockers.
Cases of syncope were reported with valsartan and hydrochlorothiazide tablets. It is unknown whether these effects were causally related to the therapy.
Cases of dehydration, dizziness postural, hypoesthesia, prutitus and rhinitis, leucopenia, abdominal pain upper, bronchitis acute, epistaxis, gastroenteritis, hyperhidrosis, neck pain, otitis media, paraesthesia, ligament sprain, hypersensitivity/allergic reactions including serum sickness, non-cardiogenic pulmonary oedema and libido decreased have also been reported.
Hepato-biliary disorders: Hepatic enzyme increased including blood bilirubin increased.
The following serious adverse events, irrespective of causality and with unknown frequency, have been reported from clinical studies or post-marketing experiences: Toxic epidermal necrolysis (TEN), Stevens-Johnsons syndrome (SJS), erythema multiforme (EM), toxic skin eruption, skin necrosis, exfoliative rash, pemphigus and pemphigoid.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
| Concomitant use of angiotensin receptor antagonists (ARBs) – including valsartan – or of angiotensin-converting-enzyme inhibitors (ACEIs) with aliskiren-containing drugs in patients with diabetes mellitus (type 1 or type 2) or moderate to severe renal impairment (GFR<60 ml/min/1.73m2) is contraindicated (See 9.4 Drug-Drug Interactions Dual Blockade of the Renin-Angiotensin-System (RAS) with ARBs, ACEIs, or aliskiren). |
|---|
9.2 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 – Established or Potential Drug-Drug Interactions for valsartan
| Proper Name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Agents Increasing Serum Potassium | T | Concomitant use of potassium-sparing diuretics (e.g., spironolactone, triamterene, amiloride), or other drugs that can increase potassium levels (e.g., heparin, non-steroidal anti-inflammatory [NSAID] drugs, trimethoprim-sulfamethoxazole), potassium supplements, or salt substitutes containing potassium, may lead to increases in serum potassium. Concomitant thiazide diuretic use may attenuate any effect that valsartan may have on serum potassium. Since valsartan decreases the production of | Monitor serum potassium level. |
| Proper Name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| aldosterone, potassium-sparing diuretics or potassium supplements should be given only for documented hypokalemia and with frequent monitoring of serum potassium. Potassium-containing salt substitutes should also be used with caution. | |||
| Lithium | CT, C | Reversible increases in serum lithium concentrations and toxicity have been reported during concomitant administration of lithium with ACE inhibitors, angiotensin II receptor antagonists or thiazides. Since renal clearance of lithium is reduced by thiazides, the risk of lithium toxicity may presumably be increased further with valsartan and hydrochlorothiazide tablets. | Careful monitoring of serum lithium concentrations is recommended during concomitant use. |
| Non-Steroidal Anti-Inflammatory (NSAID) Drugs, including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) | CT | When angiotensin II antagonists are administered simultaneously with NSAIDs, attenuation of the antihypertensive effect may occur. Furthermore, in patients who are elderly, volume-depleted (including those on diuretic therapy), or have compromised renal function, concomitant use of angiotensin II antagonists and NSAIDs may lead to an increased risk of worsening of renal function. | Monitoring of renal function is recommended when initiating or modifying the treatment in patients on valsartan who are taking NSAIDs concomitantly. |
| OATP1B1 and MRP2 | T | The results from an in vitro | Monitor blood pressure as |
| Proper Name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Transporters | study with human liver tissue indicate that valsartan is a substrate of the hepatic uptake transporter, OATP1B1, and the hepatic efflux transporter MRP2. Co-administration of inhibitors of the uptake transporter (rifampin, cyclosporine) or efflux transporter (ritonavir) may increase the systemic exposure to valsartan. | per routine. | |
| Warfarin | CT | Co-administration of valsartan and warfarin over 3 days did not affect the bioavailability of valsartan. Co-administration of valsartan and warfarin resulted in a 12% increase in prothrombin time (PT) but had no effect on activated partial thromboplastin time (APTT). | Interaction is not clinically relevant. Monitor PT as per routine. |
| Dual blockade of the Renin-Angiotensin- System (RAS) with ARBs, ACEIs, or aliskiren-containing drugs | CT | See WARNINGS AND PRECAUTIONS, Cardiovascular, Dual Blockade of the Renin-Angiotensin System (RAS). | |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Table 4 – Established or Potential Drug-Drug Interactions for hydrochlorothiazide
| Proper Name | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| Alcohol, barbiturates, or narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Amantadine | C | Co-administration of thiazide diuretics (including hydrochlorothiazide) may | Monitor for adverse effects of amantadine. |
| Proper Name | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| increase the risk of adverse effects caused by amantadine. | |||
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics | Monitor serum potassium level. |
| Antidiabetic agents (e.g. insulin and oral hypoglycemic agents) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
| Antihypertensive drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, beta-blockers, vasodilators, calcium channel blockers, ACEI, ARB, and direct renin inhibitors). | |
| Antineoplastic drugs, including cyclophosphamide and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Bile acid sequestrants, eg. cholestyramine | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothiazide by 30-35%. | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of thiazide, if necessary. |
| Calcium and vitamin D supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose |
| Proper Name | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. | |||
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Corticosteroids, and adrenocorticotropic hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia, may occur. | Monitor serum potassium, and adjust medications, as required. |
| Cyclosporine | C | Concomitant treatment with cyclosporine may increase the risk of hyperuricemia and gout-type complications. | Monitor serum uric acid. |
| Diazoxide | C | Thiazide diuretics may enhance the hyperglycemic effect of diazoxide. | Monitor serum glucose. |
| Digoxin | CT | Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, which may lead to fatal arrhythmic events. | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin levels closely. Supplement potassium or adjust doses of digoxin or thiazide, as required. |
| Drugs that alter GI motility, i.e., anti-cholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of thiazide may be required. |
| Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RCS | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co-administration of | Dosage adjustment of gout medications may be required. |
| Proper Name | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | |||
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high risk of lithium toxicity. | Concomitant use of thiazide diuretics with lithium is generally not recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor lithium levels closely. |
| Medicinal products affecting serum potassium level | CT, C | The hypokalemic effect of diuretics may be synergetically aggravated by concomitant administration of kaliuretic diuretics, corticosteroids, ACTH, amphotericin, carbenoxolone, penicillin G, salicylic acid derivatives or antiarrhythmics, β2-agonists, pseudoephedrine, ephedrine, chloroquine, and antibiotics. | Monitoring of serum electrolyte balance is recommended. Simultaneous administration of potassium supplements may be necessary. |
| Nonsteroidal anti-inflammatory drugs (NSAID) | CT | NSAID-related retention of sodium and water antagonises the diuretic and antihypertensive effects of thiazides. NSAID-induced inhibition of renal prostaglandins leading to decreases of renal blood flow, along with thiazide-induced decreases in GFR may lead to acute renal failure. Patients with heart failure may be at particular risk. | If combination use is necessary, monitor renal function, serum potassium, and blood pressure closely. Dose adjustments may be required. |
| Pressor amines (e.g. norepinephrine) | T | Hydrochlorothiazide may reduce the response to pressor amines such as norepinephrine. | The clinical significance of this effect is not sufficient to preclude their use. |
| Selective serotonin reuptake inhibitors (SSRIs, e.g. citalopram, | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Proper Name | Source of evidence | Effect | Clinical comment |
|---|---|---|---|
| escitalopram, sertraline) | |||
| Skeletal muscle relaxants of the curare family, eg., tubocurare | C | Thiazide drugs may increase the responsiveness of some skeletal muscle relaxants, such as curare derivatives | |
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. |
Legend: C = Case Study; RCS = Retrospective Cohort Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Sandoz Valsartan HCT may be administered with or without food, however it should be taken consistently with respect to food intake (see 4 DOSAGE AND ADMINISTRATION).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
Sandoz Valsartan HCT combines the actions of valsartan, an orally active angiotensin II AT1 receptor blocker, and that of a diuretic, hydrochlorothiazide.
10.1 Mechanism of Action
Valsartan
Valsartan acts selectively on AT1, the receptor subtype that mediates the known cardiovascular actions of angiotensin II, the primary vaso-active hormone of the renin-angiotensin-system. The AT2 receptor subtype, found in tissues such as brain, endometrium, myometrium and fetal kidney and adrenals, plays no known role in cardiovascular homeostasis to date. Valsartan does not exhibit any partial AT1 receptor agonist activity and has essentially no activity at the AT2 receptor. Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. The primary metabolite, valeryl 4-hydroxy valsartan, is essentially inactive.
Angiotensin II has a wide variety of physiological effects; many are either directly or indirectly involved in blood pressure regulation. A potent vasoconstrictor, angiotensin II exerts a direct pressor response. In addition it promotes sodium retention and aldosterone secretion.
Blockade of angiotensin II AT1 receptors results in two- to three-fold increase in plasma renin and angiotensin II plasma concentrations in hypertensive patients. Long-term effects of increased AT2 receptor stimulation by angiotensin II are unknown.
Valsartan does not inhibit angiotensin converting enzyme (ACE), also known as kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin.
Hydrochlorothiazide
Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanism of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, therefore co-administration of an angiotensin II AT1 Receptor Blocker tends to reverse the potassium loss associated with thiazide diuretics.
Hydrochlorothiazide is useful in the treatment of hypertension. It may be used alone or as an adjunct to other antihypertensive drugs. Hydrochlorothiazide does not affect normal blood pressure.
10.2 Pharmacodynamics
Valsartan
Valsartan inhibits the pressor effect of an angiotensin II infusion. An oral dose of 80 mg inhibits the pressor effect by about 80% at peak with approximately 30% inhibition persisting for 24 hours.
After a single oral dose, the antihypertensive activity of valsartan has an onset within approximately 2 hours and peaks within 4-6 hours in most patients.
The anti-hypertensive effect of valsartan persists for 24 hours after dosing. Trough/peak ratio ranges from 0.54 to 0.76. Valsartan reduces blood pressure in hypertensive patients without affecting heart rate.
During repeated dosing, the maximum blood pressure reduction with any dose is generally attained within 4 weeks, and is sustained during long-term therapy. Combinations with hydrochlorothiazide produce additional reduction in blood pressure.
There is no apparent rebound effect after abrupt withdrawal of valsartan therapy.
Although data available to date indicate a similar pharmacodynamic effect of valsartan in black and white hypertensive patients, this should be viewed with caution since antihypertensive drugs that affect the renin-angiotensin system, such as ACE inhibitors and angiotensin II AT1 receptor blockers, have generally been found to be less effective in low-renin hypertensives (frequently blacks).
Hydrochlorothiazide
Onset of the diuretic action following oral administration occurs in 2 hours and the peak action in about 4 hours. Diuretic activity lasts about 6-12 hours.
Valsartan-Hydrochlorothiazide
The components of valsartan and hydrochlorothiazide tablets have been shown to have additive effect on blood pressure reduction, reducing blood pressure to a greater degree than either component used alone.
The antihypertensive effect of valsartan and hydrochlorothiazide tablets is sustained for a 24-hour period. In clinical studies of at least one year duration, the antihypertensive effect was maintained with continued therapy. Despite the significant decrease in blood pressure, administration of valsartan and hydrochlorothiazide tablets had no clinically significant effect on heart rate.
10.3 Pharmacokinetics
Valsartan
Since its pharmacokinetics are linear in the 80 to 320 mg dose range, valsartan does not accumulate appreciably in plasma following repeated administration. Plasma concentrations are similar in males and females.
Absorption: Following oral administration of valsartan alone, peak plasma concentrations of valsartan are reached in 2 -4 hours. The mean absolute bioavailability of valsartan is about 23%, but with high variability.
Distribution: Valsartan is 94-97% bound to serum protein, mainly serum albumin. The steady-state volume of distribution of valsartan after intravenous administration is about 17 L, indicating that valsartan is not distributed into tissues extensively.
Metabolism: Valsartan is not biotransformed to a high extent as only about 20% of dose is recovered as metabolites. A hydroxyl metabolite has been identified in plasma at low concentrations (less than 10% of the valsartan AUC). This metabolite is pharmacologically inactive.
Valsartan biotransformation does not seem to involve the cytochrome P-450 system. The enzyme(s) responsible for valsartan metabolism have not been identified.
Elimination: Following intravenous administration, valsartan shows bi-exponential decay kinetics (t1/2α <1 hour and t1/2β between 5-9 hours). Following administration of an oral solution of 14C labeled valsartan, 83% of absorbed valsartan is primarily excreted in the feces and 13% in the urine, mainly as unchanged compound. Following intravenous administration, plasma clearance of valsartan is about 2 L/h. The half-life of valsartan is 6 hours.
Hydrochlorothiazide
Absorption: The absorption of hydrochlorothiazide, after an oral dose, is rapid (Tmax about 2 h).The increase in mean AUC is linear and dose proportional in the therapeutic range. Concomitant administration with food has been reported to both increase and decrease the systemic availability of hydrochlorothiazide compared with the fasted state. The magnitude of these effects is small and has little clinical importance. Absolute bioavailability of hydrochlorothiazide is 70 % after oral administration.
Distribution: The distribution and elimination kinetics have generally been described as a bi-exponential decay function. The apparent volume of distribution is 4-8 L/kg. Circulating hydrochlorothiazide is bound to serum proteins (40-70%), mainly serum albumin. Hydrochlorothiazide also accumulates in erythrocytes at approximately 3 times the level in plasma.
Metabolism: Hydrochlorothiazide is eliminated predominantly as unchanged drug.
Elimination: Hydrochlorothiazide is eliminated from plasma with a half-life averaging 6 to 15 hours in the terminal elimination phase. There is no change in the kinetics of hydrochlorothiazide on repeated dosing, and accumulation is minimal when dosed once daily. There is more than 95 % of the absorbed dose being excreted as unchanged compound in the urine.
Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk.
Valsartan- Hydrochlorothiazide
The systemic availability of hydrochlorothiazide is reduced by about 30% when co-administered with valsartan. The kinetics of valsartan are not markedly affected by the co-administration of hydrochlorothiazide. This observed interaction has no impact on the combined used of valsartan and hydrochlorothiazide.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of valsartan have not been investigated in patients <18 years of age.
Geriatrics: Exposure to valsartan is about 50% higher as measured by AUC and Cmax and the half life is longer in elderly subjects than in young subjects. However, this difference has not been shown to have any clinical significance.
Sex: Plasma concentrations are similar in males and females.
Hepatic Insufficiency: On average, patients with mild to moderate chronic liver disease have twice the exposure to valsartan of healthy volunteers as measured by AUC and Cmax (see 7 WARNINGS AND PRECAUTIONS, and 4 DOSAGE AND ADMINISTRATION).
Sandoz Valsartan HCT should be used with particular caution in patients with biliary obstructive disorders. Because of hydrochlorothiazide, Sandoz Valsartan HCT is not recommended in patients with severe hepatic impairment (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
Renal Insufficiency: Renal clearance accounts for only 30% of total plasma clearance. There is no apparent correlation between renal function and exposure to valsartan, as measured by AUC and Cmax, in patients with different degrees of renal impairment. In patients with renal failure undergoing hemodialysis, limited information showed that exposure to valsartan is comparable to that in patients with creatinine clearance > 10 mL/min.
In the patients with moderate to severe renal impairment, mean peak plasma levels and AUC values of hydrochlorothiazide are increased by 2.27 fold and 8.46 fold respectively and the mean cumulative urinary excretion rate is reduced by 35% as compared to baseline 51% of the oral dose.
As expected for a compound which is cleared almost exclusively via the kidneys, renal function has a marked effect on the kinetics of hydrochlorothiazide. Therefore, Sandoz Valsartan HCT is not recommended for use in patients with severe renal impairment (creatinine clearance < 30 mL/min).
Valsartan is not removed from plasma by dialysis.
11 STORAGE, STABILITY AND DISPOSAL
Protect from moisture. Store at 15 - 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II : SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper Names: | |||||||
| valsartan | hydrochlorothiazide | ||||||
| Chemical Names: | |||||||
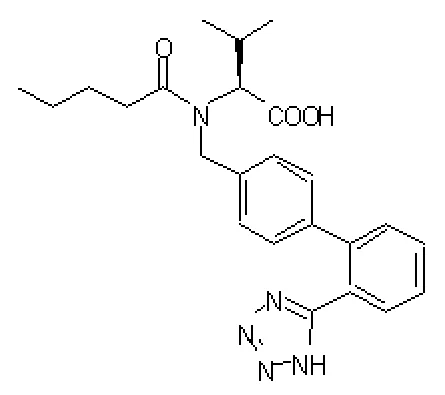
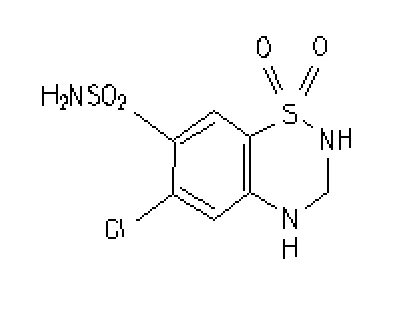
| (S)-N-valeryl-N-{[2'-(1H-tetrazol-5-yl) biphenyl-4-yl] methyl}-valine | 6-chloro-3,4-dihydro-2H-1,2,4-benzothiazidine-7-sulfonamide 1,1-dioxide | ||||||
| Molecular formulae: | |||||||
| C24H29N5O3 | C7H8ClN3O4S2 | ||||||
| Molecular mass: | |||||||
| 435.5 | 297.74 | ||||||
| Structural formula: | |||||||
 |  | ||||||
| Physicochemical properties: | |||||||
| Fine white to practically white, practically odourless powder. It is soluble in ethanol, methanol and slightly soluble in water. | White, or practically white, crystalline powder. It is slightly soluble in water; freely soluble in sodium hydroxide solution and dimethyl sulfoxide, sparingly soluble in methanol and ethanol; practically insoluble in diethyl ether. | ||||||
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Hypertension
In controlled clinical trials including over 7600 patients with essential hypertension, 4372 patients were exposed to valsartan (80, 160 and 320 mg) and concomitant hydrochlorothiazide (12.5 and 25 mg). Two randomized, double-blind factorial trials compared various combinations of 80/12.5 mg, 80/25 mg, 160/12.5 mg, 160/25 mg, 320/12.5 mg and 320/25 mg with their respective components and placebo. The combination of valsartan and hydrochlorothiazide resulted in additive placebo-adjusted decreases in systolic and diastolic blood pressure at trough of 14-21/8-11 mmHg at 80/12.5 mg to 320/25 mg, compared to 7- 10/4-5 mmHg for valsartan 80 mg to 320 mg and 5-11/2-5 mmHg for hydrochlorothiazide 12.5 mg to 25 mg, alone.
Three other controlled trials investigated the addition of hydrochlorothiazide to patients who did not respond to adequately to valsartan 80 mg to valsartan 320 mg, resulted in the additional lowering of systolic and diastolic blood pressure by approximately 4-12/2-5 mmHg.
The maximal antihypertensive effect was attained 4 weeks after the initiation of therapy, the first time point at which blood pressure was measured in these trials.
In one year open label follow up study (without placebo control) the effect of the combination of valsartan and hydrochlorothiazide was maintained. The antihypertensive effect was independent of age or gender. The overall response to the combination was similar for black and non-black patients.
There was essentially no change in heart rate in patients treated with the combination of valsartan and hydrochlorothiazide in controlled trials.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Pharmacodynamics
The in vitro data support that valsartan is a specific antagonist of the AT1 sub-type receptor, that valsartan does not react at other receptor sites and has an affinity for the receptor that is similar in the rat, marmoset and human; whereas the affinity of valsartan for the AT1 sub-type receptor in the dog is significantly smaller. This is further reinforced by data from in vivo studies and the literature. From animal and human studies, there is also no evidence that AT1 receptor blockade by valsartan together with the resulting Ang II increase causes any arrhythmogenic effects.
Vascular reactivity in the rat to exogenous Ang II is attenuated by sodium restriction and increased during sodium loading. These effects are opposite to those exhibited by the adrenal glomerulosa where sensitivity to Ang II increases during sodium restriction. This phenomenon is the consequence of changes in circulating Ang II levels linked to the altered sodium balance. As expected, in rats, after treatment with valsartan, there is a high level of circulating Ang II, so a down regulation of the receptor could therefore be expected which would reduce the efficacy of valsartan, but vascular receptor density and therefore vascular reactivity in the liver does not decrease after chronic treatment. So valsartan, should not produce internalisation of the Ang II receptor and hence, tolerance. With the increase in circulating Ang II, there is the possibility of some effects through stimulation of the AT2 receptor. The role of the AT2 receptor is currently unknown. No untoward effects were noted in preclinical or clinical studies that might suggest an AT2 receptor mediated action.
The correlation between plasma levels and pharmacological response is not very clear. A similar effect is also seen in the clinic where there is also not a very clear relationship between plasma levels and blood pressure reduction. The variability of the plasma levels is most likely due to the variability in absorption which is pH dependent and thus there will be a limited window of absorption in the alimentary tract. However the critical factor in the relationship between plasma drug levels and effect is that once the AT1 receptors are blocked, increasing plasma concentrations produce very little further action. Therefore this individual variability is not of major importance.
Pharmacokinetics
Results from the absorption, distribution, metabolism and excretion studies show a fairly similar pattern for the rat, marmoset and human though the volume of distribution is greater in the two former species. In the rat the distribution is rapid and valsartan is found mainly in the blood, plasma, liver, lung and renal cortex. In all 3 species the extent of protein binding is comprised between 94% and 97% and the metabolism is fairly low (> 10%) with excretion mainly via the bile. The vast majority of the dose is cleared within 24 hours and there does not appear to be any accumulation on repeated dosing. It does not cross the blood/brain barrier or transfer into the foetus.
General Toxicology
Acute Toxicity
Valsartan
| Species | Route | Dose mg/kg | Major findings |
| Rat | Gavag e | 100 | No adverse findings. |
| Rat | Gavag e | 1000, 2000 | 2000 mg/kg: Diarrhea, white substance (similar to test substance) in feces. Approximate LD50 >2000 mg/kg. |
| Marmos et | Gavag e | 600, 1000 | No effect 600 mg/kg. 1000 mg/kg: Vomiting, white substance (similar to test substance) in vomitus. Approximate LD50 >1000 mg/kg. |
Valsartan and hydrochlorothiazide
| Species | Route | Dose (mg/kg) | Major Findings | ||||
| valsartan | HCT | ||||||
| Rat | Gavag e | 1524 | 476 | No adverse findings. Approximate LD50 > 1524.0:476.0 mg/kg | |||
| Marmos et | Gavag e | 320.0 761.9 | 100.0 238.1 | No adverse findings Approximate LD50 > 761.9:238.1 mg/kg | |||
Long-Term Toxicity
Valsartan
In toxicity studies conducted in several animal species, the main preclinical safety findings involving the kidney and related effects, are attributed to the pharmacological action of the compound.
In preclinical safety studies, high doses of valsartan (200 to 600 mg/kg body weight) caused in rats a reduction of red blood cell parameters (erythrocytes, hemoglobin, hematocrit) and evidence of changes in renal hemodynamics (slightly raised plasma urea, and renal tubular hyperplasia and basophilia in males). These doses in rats (200 and 600 mg/kg/day) are approximately 6 and 18 times the maximum recommended human dose on a mg/m2 basis (calculations assume an oral dose of 320 mg/day and a 60-kg patient). In marmosets at similar doses, the changes were similar though more severe, particularly in the kidney where the changes developed to a nephropathy which included raised urea and creatinine. Hypertrophy of the renal juxtaglomerular cells was also seen in both species. All changes were considered to be caused by the pharmacological action of valsartan which produces prolonged hypotension, particularly in marmosets.
| Species | Route | Duration | Dose mg/kg | Major findings |
| Species | Route | Duration | Dose mg/kg | Major findings |
| Rat | Gavage | 14 day | 60, 200, 600 | Mid & High dose groups: ↑ urea NOEL = 60 mg/kg. |
| Marmos et | Gavage | 14 day | 60, 200, 600 | High dose group: Vomiting and mild to moderate ↑ in urea NOEL = 200 mg/kg. |
| Rat | Intra-venous | 14 day | 10, 30, 100 | No adverse findings. NOAEL = 100 mg/kg. |
| Marmos et | Intra-venous | 14 day | 6, 20, 60 | No adverse findings. NOAEL = 60 mg/kg. |
| Rat | Gavage | 91 day | 60, 200, 600 | Mid & High dose groups: ↑ urea High dose group: Renal tubular hyperplasia, glomerular arteriolar hypertrophy. Anemia with regenerative response. NOEL = 60 mg/kg. |
| Marmos et | Gavage | 91 day | 30, 60, 200, 600 → 400 | Plasma urea & creatinine ↑from 200 mg/kg. Nephropathy at 200 & 600 mg/kg. Alk. Phos. ↑ at 400 mg/kg. Anemia from 200 mg/kg. Hypertrophy of glomerular arteriole at 400 mg/kg. Adrenal cortex hypertrophy from 200 mg/kg in F. Cachexia including 3 deaths at 600 mg/kg. One death at 200 mg/kg. One death at 400 mg/kg during the recovery period. NOEL = 60 mg/kg. |
| Rat | Gavage | 12 months | 20, 60, 200 | Mid dose group: ↑ urea at 60 mg/kg High dose group: anemia & renal arteriolar hypertrophy. NOAEL = 20 mg/kg. |
| Marmos et | Gavage | 12 months | 12, 40, 120 | Mid & High dose groups: ↑ in urea and creatinine NOAEL = 12 mg/kg. |
NOEL No observable effect level.
NOAEL No observable adverse effect level.
Valsartan and hydrochlorothiazide
The combination of valsartan/hydrochlorothiazide was evaluated for toxicity in the rat and marmoset for up to 6 months. Treatment-related findings were mainly related to the exaggerated pharmacological effects of valsartan and/or hydrochlorothiazide and consisted of reduction in red cells parameters, alterations in electrolyte and water concentrations in the body, hypertrophy of the juxtaglomerular apparatus and renal tubular changes. The marmoset was a much more sensitive species in which there was an approximate 10-fold potentiation of blood pressure reduction with the combination of valsartan and hydrochlorothiazide as compared to valsartan alone. Hydrochlorothiazide alone had no effect on the blood pressure of marmosets. This potentiation has not been seen in the human subject; the effect of valsartan and hydrochlorothiazide is additive.
| Species | Route | Duratio n | Dose (mg/kg) | Major findings | ||||||
| valsartan | HCT | |||||||||
| Marmos et | Gavage | 14 days | -- -- -- | 100 300 1000 | No adverse findings. All groups: ↓ Plasma Na+ and K+ | |||||
| Rat | Gavage | 1 month | 50.0 200.0 600.0 -- | 15.625 62.5 187.5 187.5 | All groups: Pharmacological dose-related findings; ↑ in urea. NOAEL > 600.0:187.5 mg/kg | |||||
| Marmos et | Gavage | 1 month | 30.0 120.0 400.0 -- | 9.375 37.5 125 125 | High dose group: Early death of all 3 F. High dose and HCT groups: Renal changes including tubular basophilia Low and mid dose groups: Minor pharmacological dose-related changes. NOAEL = 30.0:9.375 mg/kg | |||||
| Rat | Gavage | 6 months | 30.0 100.0 300.0 -- | 9.375 31.25 93.75 93.75 | All groups: Pharmacological dose-related findings; ↑ urea. High dose group: Changes in plasma lipid parameters. NOAEL = 100.0:31.25 mg/kg | |||||
| Marmos et | Gavage | 6 months | 30.0 60.0 120.0 240.0→120 .0 | 9.375 18.75 37.5 75.0→37 .5 75.0 | All dose levels (not HCT): Deaths associated with renal changes related to severe pharmacological effects. HCT: Minor effects. NOAEL not identified. | |||||
| Marmos et | Gavage | 6 months | 3.0 10.0 30.0 | 0.93 3.125 9.325 | No adverse findings NOAEL=10.0:3.125 | |||||
NOAEL: No Observed Adverse Effect Level
NOEL: No Observed Effect Level
Carcinogenicity
Valsartan
| Species | Route | Duratio n | Dose (mg/kg) | Major Findings |
| Mouse | Diet | 2 years | 10, 40, 160 | Hyperplasia of gastric mucosa in males. ↓ body weight gain at ≥10 mg/kg. No carcinogenic effect |
| Rat | Diet | 2 years | 10, 50, 200 | ↓ body weight gain, anemia, nephropathy at ≥ 50 mg/kg. ↑ urea and creatinine, ↓ total proteins and albumin at 200 mg/kg. No carcinogenic effect. |
Hydrochlorothiazide
According to the experimental data available, hydrochlorothiazide revealed inconsistent evidence of carcinogenic activity in rats and mice with conflicting evidence of hepatic adenoma in male mice at the highest dose and adrenal pheocytochroma in one rat study but not in another. Current evidence is inadequate to draw a clear conclusion for a carcinogenic effect of hydrochlorothiazide in animals.
The mutagenic potential was assessed in a series of in vitro and in vivo test systems. While some positive results were obtained in vitro, all in vivo studies provided negative results. Hydrochlorothiazide enhanced the UVA-induced formation of pyrimidine dimers in vitro and in the skin of mice following oral treatment. It is therefore concluded that there is no relevant mutagenic potential in vivo, although hydrochlorothiazide could enhance the genotoxic effects of UVA light. This mechanism of photosensitization could be associated with a higher risk for non-melanoma skin cancer.
Genotoxicity:
Mutagenicity
Valsartan
Valsartan has been tested for mutagenicity, clastogenicity, reproductive performance and carcinogenicity with negative results.
In vitro
| Test | System | mcg/mL or *plate | Comments |
| Mutagenicity | Bacteria** | *5.0 - 5000.0 | Negative |
| Mutagenicity | Bacteria*** | *5000.0 | Negative |
| Gene mutation | Chinese hamster cells (V79) | 81.88 - 5550.00 | Negative |
| Chromosome aberration | Chinese hamster cells (ovary) | 81.88 - 1310.00 | Negative |
In-vivo
| Test | System | mg/kg | Comments |
| Micro-nucleus | Rat | 781.3 - 3 125.0 | Negative |
** S typhimurium - TA98, TA100, TA 1537 E coli - WP2uvrA
*** S typhimurium - TA98, TA100, TA1535, TA 1537 E coli - WP2uvrA
Reproductive and Developmental Toxicology
Valsartan
In reproductive studies in rats, mice and rabbits, only minor effects were noted. In rabbits there was evidence of low fetal weights, litter loss and abortion, but no teratogenicity at 5 and 10 mg/kg. Rabbits are extremely susceptible to compounds acting on the RAAS so this finding is not unexpected. There was also a slightly reduced postnatal F1 survival and development together with reduced maternal bodyweight gain in rats at 600 mg/kg. Otherwise, there was no effect at the highest doses tested on fertility, reproductive performance in rats (200 mg/kg), embryotoxcity, fetotoxicity, teratogenicity in rats and mice (600 mg/kg).
In embryofetal development studies (Segment II) in mice rats and rabbits, fetotoxicity was observed in association with maternal toxicity in rats and valsartan doses of > 200 mg/kg/days and in rabbits at doses of > 10 mg/kg/day. In a peri- and postnatal development toxicity (segment III) study, the offsprings from rats treated at 600 mg/kg during the last trimester and during lactation showed a slightly reduced survival rate and a slight developmental delay (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women).
Segment I
| Species | Route | Duration of dosing | Dose mg/kg | Major findings |
| Rat | Gavage | M: 90 days F: day 14 to 19 or 14 to +20 | 10, 50, 200 | High dose: ↓ in field motor activity in F; no effect on fertility, reproductive performance in F0 & F1 and on F1 development. No effect on kidney development. |
Segment II
| Species | Route | Duration of dosing | Dose mg/kg | Major Findings |
| Mouse | Gavage | Day 6 to 15 | 60, 200, 600 | All dose groups: No embryotoxicity, fetotoxicity or teratogenicity. |
| Rat | Gavage | Day 6 to 15 | 60, 200, 600 | Mid & High dose groups:↓ maternal body weight gain High dose group: ↓ fetal weights All dose groups: No embryotoxicity, fetotoxicity or teratogenicity |
| Rabbit1 | Drench | Day 6 to 18 | 2.5, 15, 30, 45, 50, 150 | Litter losses and deaths at 15 mg/kg and above. One litter loss (1/5) at 2.5 mg/kg. |
| Rabbit | Gavage | Day 6 to 18 Day 7 to 19 | 2, 5, 10 | Mid dose group: ↑ incidence of low fetal weights Mid & High dose groups: Litter loss and abortion All dose groups: No teratogenicity. |
1 Range Finding
Segment III
| Rat | Gavage | Day 15 to 20 or + 20 | 60, 200, 600 | High dose group: Slightly reduced post-natal F1 survival and development in the presence of reduced maternal body weight gain. No effect on kidney development. |
+ - Number of days post-parturition
Valsartan and hydrochorothiazide
Reproductive studies with the combination of valsartan/hydrochlorothiazide were conducted in rats, mice and rabbits. In all 3 species, there was no evidence of teratogenicity. In rats, there were maternal changes, mainly decreased food consumption, bodyweight or bodyweight gain at 50:115.6 mg/kg and above and deaths at 200:62.5 mg/kg and above. Fetotoxicity was seen at 262.5 mg/kg and above. This was considered to be related to the maternal toxicity. No effects were noted in mice at 600:187.5 mg/kg. Rabbits showed similar effects to those of valsartan alone at equivalent doses.
Segment II
| Species | Route | Duration | Dose (mg/kg) | Major Findings | |
| Valsarta n | HCT | ||||
| Rat | Gavag e | Day 6 to 15 | 50.0 200.0 600.0 | 15.6 62.5 187.5 187.5 | All dose groups: Maternal & fetal toxicty, ↓ food consumption, body weight & weight gain Mid dose & High dose groups: Maternal deaths (3/26 & 11/26), salivation and stool changes and ↓ fetal weight No embryotoxicity or teratogenicity. |
| Rat | Gavag e | Day 6 to 15 | 10.0 25.0 100.0 | 3.1 7.8 31.3 31.3 | High dose group:↓ food consumption and weight gain No evidence of embryo- & feto-toxicity or embryotoxicity NOEL (maternal): 25.0:7.8 mg/kg NOEL (fetal): 100:31.3 mg/kg |
| Rabbit | Gavag e | Day 7 to 19 | 1.0 3.0 10.0 | 0.3 0.9 3.1 3.1 | All dose groups: Slightly ↓ food consumption Mid dose group: Maternal death (1/18) High dose group: ↑ no. of late resorptions, total resorptions, mean & % post implantation loss; slight ↓ in no. of live fetuses. No evidence of teratogenecity NOAEL (fetal): 3.0:0.9 mg/kg |
| Mouse | Gavag e | Day 6 to 15 | 50 200 600 | 15.6 62.5 187.5 187.5 | No maternal effects, embryo-, fetotoxicity or teratogenicity. NOAEL (fetal & Maternal): 600.0:187.5 mg/kg |
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Novartis Pharmaceuticals Canada Inc., DIOVAN-HCT Product Monograph (Valsartan and hydrochorothiazide tablets) Control No.:266715; Date of Revision: February 28, 2023.